Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: growth hormone research

Cardiovascular Stress Markers in Growth Hormone Research: Monitoring Lisinopril and ACE Pathways Alongside Secretagogues

Cardiovascular Stress Markers in Growth Hormone Research: Monitoring Lisinopril and ACE Pathways Alongside Secretagogues

September 16, 2026/0 Comments/in Uncategorized/by

Fewer than 30% of researchers tracking growth hormone secretagogue protocols routinely measure ACE-related cardiovascular endpoints, a gap that carries real physiological consequences. As interest in GHRH analogs and synthetic secretagogues accelerates in 2026, the intersection of cardiovascular stress markers in growth hormone research and blood pressure regulation via the renin-angiotensin-aldosterone system (RAAS) has become one of the most clinically relevant monitoring challenges in the field.

When secretagogues elevate IGF-1 and promote fluid retention, the cardiovascular system absorbs much of that load. Lisinopril, an ACE inhibitor, is frequently co-administered to manage that burden, but the interaction between these two pathways demands a structured, marker-driven approach.

Key Takeaways

  • Growth hormone secretagogues raise IGF-1 and can promote sodium and fluid retention, increasing cardiac preload and blood pressure.
  • Lisinopril and other ACE inhibitors blunt RAAS activation but introduce their own monitoring needs, including potassium elevation and renal function shifts.
  • Tracking cardiovascular stress markers, hemodynamic, structural, biomarker, and vascular, is essential when combining these agents in research protocols.
  • NT-proBNP, hs-troponin, seated and ambulatory blood pressure, and echocardiographic data form the core monitoring panel.
  • Integrated monitoring of the ACE pathway alongside secretagogue use reduces the risk of undetected cardiac stress.

How Secretagogues Interact With the Cardiovascular System
How Secretagogues Interact With the Cardiovascular System

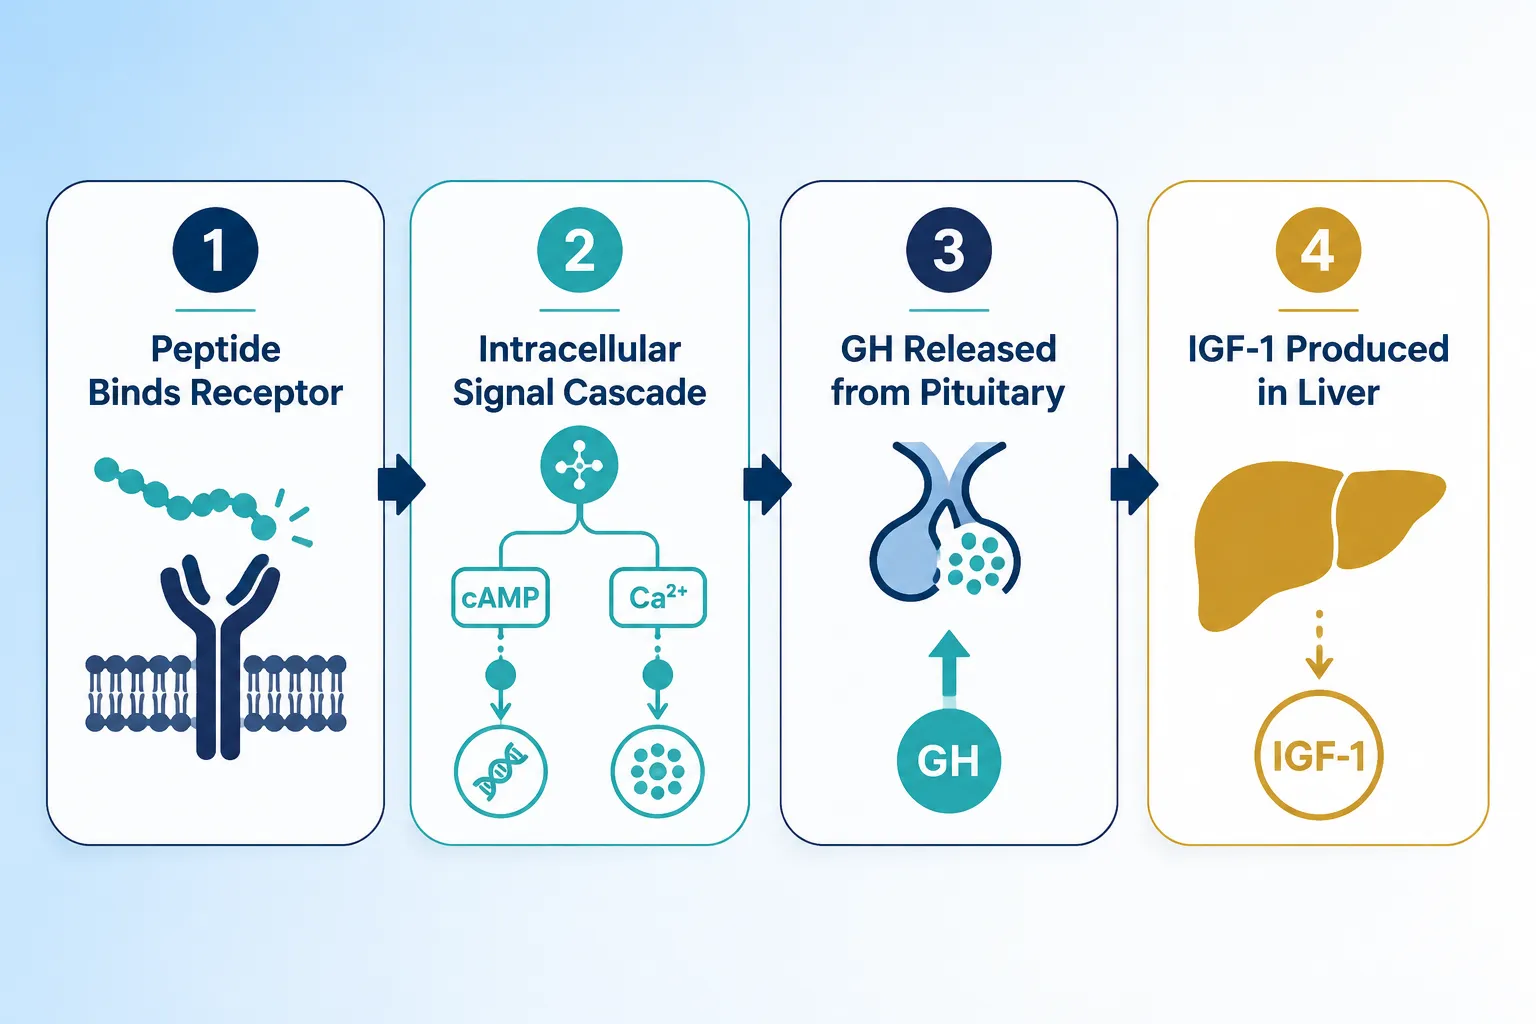
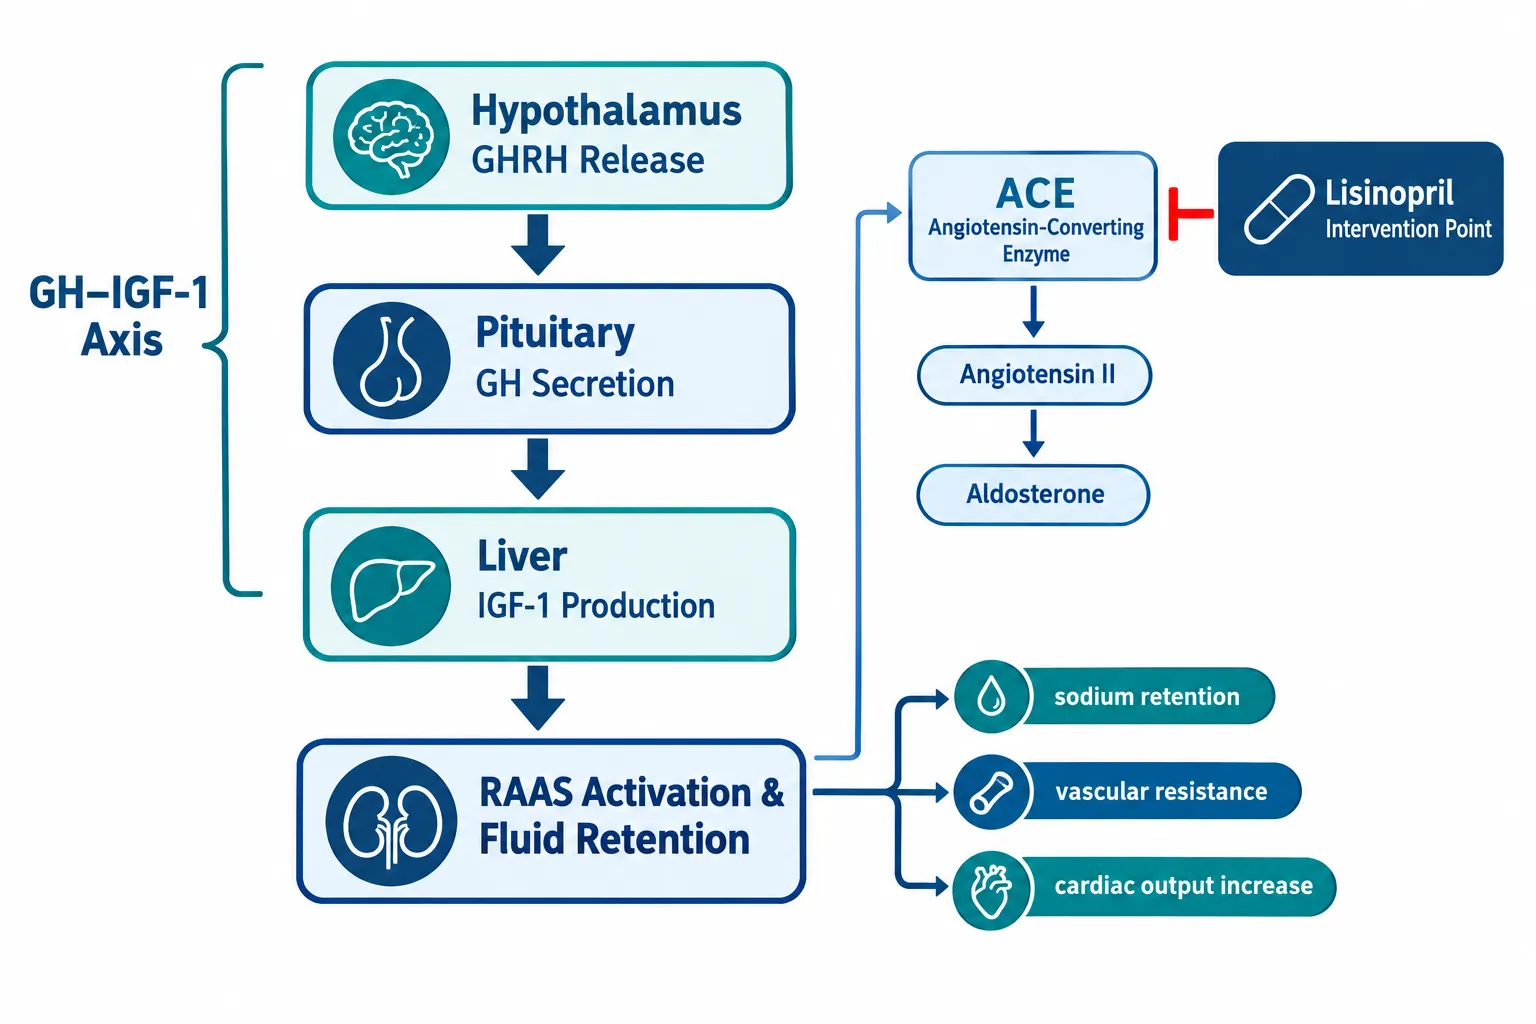
Growth hormone secretagogues, including GHRH analogs, ghrelin mimetics, and synthetic GH-releasing peptides, stimulate pituitary GH release, which in turn drives hepatic IGF-1 production. This cascade carries meaningful cardiovascular effects that researchers must account for.

IGF-1 elevation promotes myocardial growth, increases cardiac output, and enhances vascular smooth muscle responsiveness. In the short term, these effects can look beneficial. Over longer exposures, however, elevated IGF-1 contributes to left ventricular hypertrophy and arterial stiffness, both established markers of cardiovascular stress.

Ghrelin and its synthetic analogs add another layer. Research consistently shows that ghrelin-type secretagogues exert vasodilatory, anti-ischemic, and anti-apoptotic effects on cardiac tissue. They reduce peripheral vascular resistance and may lower blood pressure acutely. However, this vasodilation can interact unpredictably with ACE inhibitors, raising the risk of orthostatic hypotension.

Fluid retention is a particularly important concern. GH directly stimulates renal sodium reabsorption via the IGF-1 receptor, expanding plasma volume. This increases cardiac preload and, over time, elevates systolic blood pressure. Researchers working with IPA Sermorelin stack protocols should factor this mechanism into their baseline cardiovascular assessments.

The RAAS responds to this expanded volume by modulating aldosterone and angiotensin II levels. This is precisely where lisinopril enters the picture.

Lisinopril and ACE Pathway Dynamics in Secretagogue Protocols

Lisinopril and ACE Pathway Dynamics in Secretagogue Protocols

Lisinopril blocks ACE, the enzyme that converts angiotensin I to the potent vasoconstrictor angiotensin II. By reducing angiotensin II, lisinopril lowers peripheral resistance, reduces aldosterone-driven sodium retention, and decreases cardiac afterload. These are exactly the mechanisms that counteract GH-induced fluid retention.

"The ACE pathway and the GH/IGF-1 axis do not operate in isolation, co-administration of lisinopril alongside secretagogues creates a dynamic cardiovascular environment that requires active, structured monitoring."

However, ACE inhibition introduces its own variables. Potassium levels rise because aldosterone suppression reduces urinary potassium excretion. Renal perfusion pressure can drop, particularly in subjects with any pre-existing renal sensitivity. Bradykinin accumulates, which may amplify the vasodilatory effects already present from ghrelin-type secretagogues.

Key interaction points to monitor:

  • Blood pressure response may be exaggerated when ghrelin-type secretagogues and lisinopril are combined
  • Potassium can climb into hyperkalemic ranges without regular electrolyte testing
  • Renal function (creatinine, eGFR) may shift as RAAS suppression alters glomerular filtration dynamics
  • Fluid balance changes can mask or amplify biomarker readings

Researchers exploring peptide combinations that modulate metabolic and cardiovascular pathways, such as those reviewed in tesofensine noradrenergic and incretin-based pathway research, will recognize that multi-pathway interactions demand multi-marker monitoring frameworks.

Core Cardiovascular Stress Markers for Combined RAAS-GH Axis Monitoring
Core Cardiovascular Stress Markers for Combined RAAS-GH Axis Monitoring

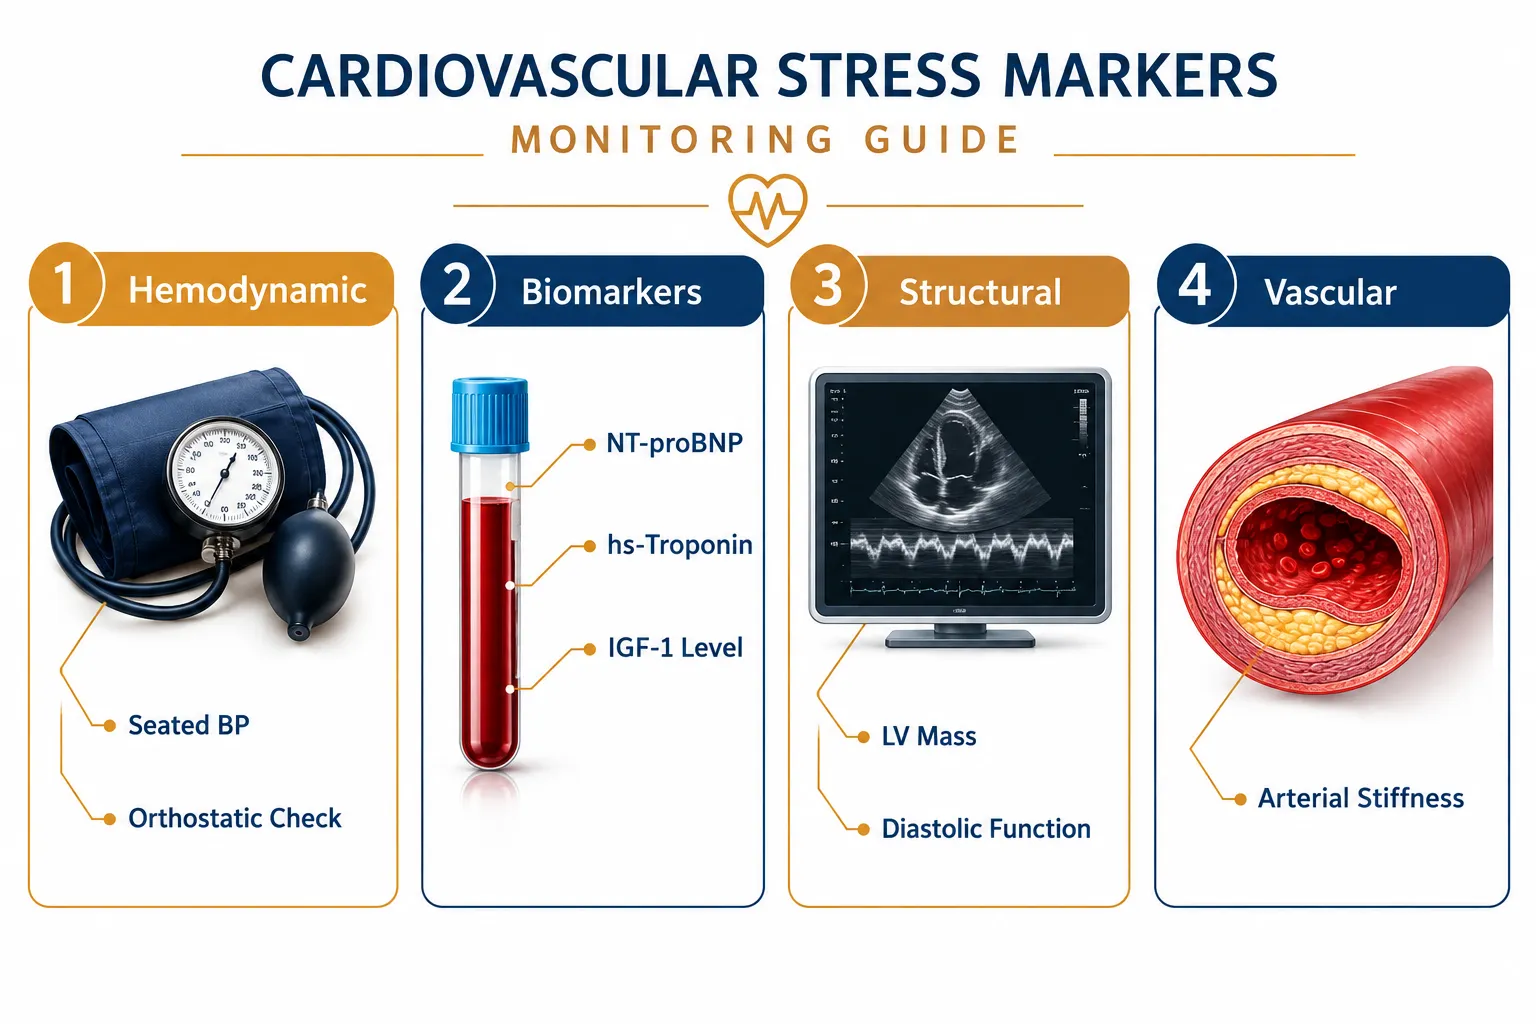
Monitoring cardiovascular stress markers in growth hormone research alongside lisinopril and ACE pathway modulation requires a structured, four-domain approach.

Hemodynamic Markers

Marker Measurement Method Key Concern
Seated blood pressure Manual or automated sphygmomanometry Hypertension from GH fluid load
Ambulatory blood pressure 24-hour ABPM device Masked hypertension patterns
Orthostatic blood pressure Supine to standing protocol Hypotension risk with ACE + ghrelin
Resting heart rate ECG or pulse oximetry Tachycardia from volume shifts

Structural Markers

Echocardiography provides the most direct window into cardiac remodeling. Left ventricular mass index, wall thickness, and both systolic and diastolic function should be assessed at baseline and at defined intervals. Diastolic dysfunction often precedes systolic changes and can appear early in GH-excess states.

Biomarker Panel

NT-proBNP is the most sensitive biomarker for detecting early cardiac wall stress and volume overload. Elevated levels signal that the heart is under pressure before symptoms appear. High-sensitivity troponin (hs-troponin) identifies subclinical myocardial injury.

Additional biomarkers include:

  • IGF-1 (to calibrate secretagogue dosing and exposure)
  • Serum creatinine and eGFR (renal safety on ACE inhibitor)
  • Potassium and sodium (electrolyte balance under RAAS suppression)
  • Fasting glucose and lipid panel (metabolic context)

Research on mitochondrial cardioprotection compounds such as those examined in SS-31 mitochondrial research highlights how cellular stress markers can complement systemic biomarker panels in cardiovascular monitoring.

Vascular Markers

Arterial stiffness indices, measured via pulse wave velocity or augmentation index, capture changes in large-vessel compliance that echocardiography and biomarkers may miss. Endothelial function assessment adds further resolution in longer-duration protocols.

Practical Monitoring Frequency and Protocol Design

Effective cardiovascular stress monitoring in growth hormone research is not a one-time assessment. A tiered frequency model works best:

Baseline (before protocol initiation): Full panel, hemodynamic, echocardiographic, biomarker, and vascular measures.

Early phase (weeks 2-4): Blood pressure, heart rate, potassium, creatinine, and eGFR. This window captures the most acute RAAS-GH interaction effects.

Mid-protocol (weeks 6-12): Repeat biomarker panel including NT-proBNP and hs-troponin. Reassess IGF-1 to confirm secretagogue response is within target range.

End of protocol: Full repeat of baseline panel plus echocardiographic comparison for structural changes.

Researchers working with GLP-based peptide compounds, including those available as GLP-3 Reta 10mg or GLP-3 Reta 20mg, should apply similarly structured cardiovascular monitoring, as GLP receptor pathways also influence cardiac output and vascular tone.

Conclusion

Cardiovascular stress markers in growth hormone research represent a non-negotiable component of responsible secretagogue protocol design, particularly when lisinopril and ACE pathway modulation are part of the picture. The interaction between GH-driven fluid retention, IGF-1-mediated cardiac remodeling, and ACE inhibitor-induced RAAS suppression creates a layered hemodynamic environment that no single marker can fully capture.

Actionable next steps for researchers:

  1. Establish a full cardiovascular baseline before initiating any secretagogue-lisinopril combination protocol.
  2. Prioritize NT-proBNP, hs-troponin, potassium, and eGFR as the minimum biomarker panel throughout the study period.
  3. Use ambulatory blood pressure monitoring to detect masked hypertension or exaggerated hypotensive responses.
  4. Schedule echocardiographic assessment at baseline and protocol end to quantify structural changes.
  5. Adjust secretagogue dosing based on IGF-1 levels and correlate with hemodynamic trends rather than treating them as independent variables.

Structured monitoring transforms cardiovascular risk from an unknown variable into a manageable, measurable research parameter.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/cardiovascular-stress-markers-in-growth-hormone-research-monitoring-lisinopril-a.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-16 13:07:362026-09-16 13:07:36Cardiovascular Stress Markers in Growth Hormone Research: Monitoring Lisinopril and ACE Pathways Alongside Secretagogues
Best Research‑Use GH Secretagogue Peptides: Comparing CJC‑1295 (With and Without DAC), Ipamorelin, and Tesamorelin

Best Research‑Use GH Secretagogue Peptides: Comparing CJC‑1295 (With and Without DAC), Ipamorelin, and Tesamorelin

September 2, 2026/0 Comments/in Uncategorized/by

Growth hormone secretagogue research has expanded sharply since 2020, yet fewer than one in four investigators working with these compounds can clearly articulate why half-life differences between CJC-1295 variants change their assay endpoints. Choosing the wrong peptide for a given experimental design wastes reagents, distorts GH pulse data, and undermines reproducibility. This buyer's guide for research labs breaks down the Best Research-Use GH Secretagogue Peptides: Comparing CJC-1295 (With and Without DAC), Ipamorelin, and Tesamorelin across the variables that matter most: mechanism, pharmacokinetics, regulatory standing, and fit for specific study designs.

Key Takeaways

  • CJC-1295 with DAC provides a prolonged, near-continuous GH elevation useful for chronic exposure models; without DAC it mimics natural pulsatile release.
  • Ipamorelin is the most selective ghrelin-receptor agonist in this class, making it valuable for mechanistic studies that need to isolate GHS-R1a signaling.
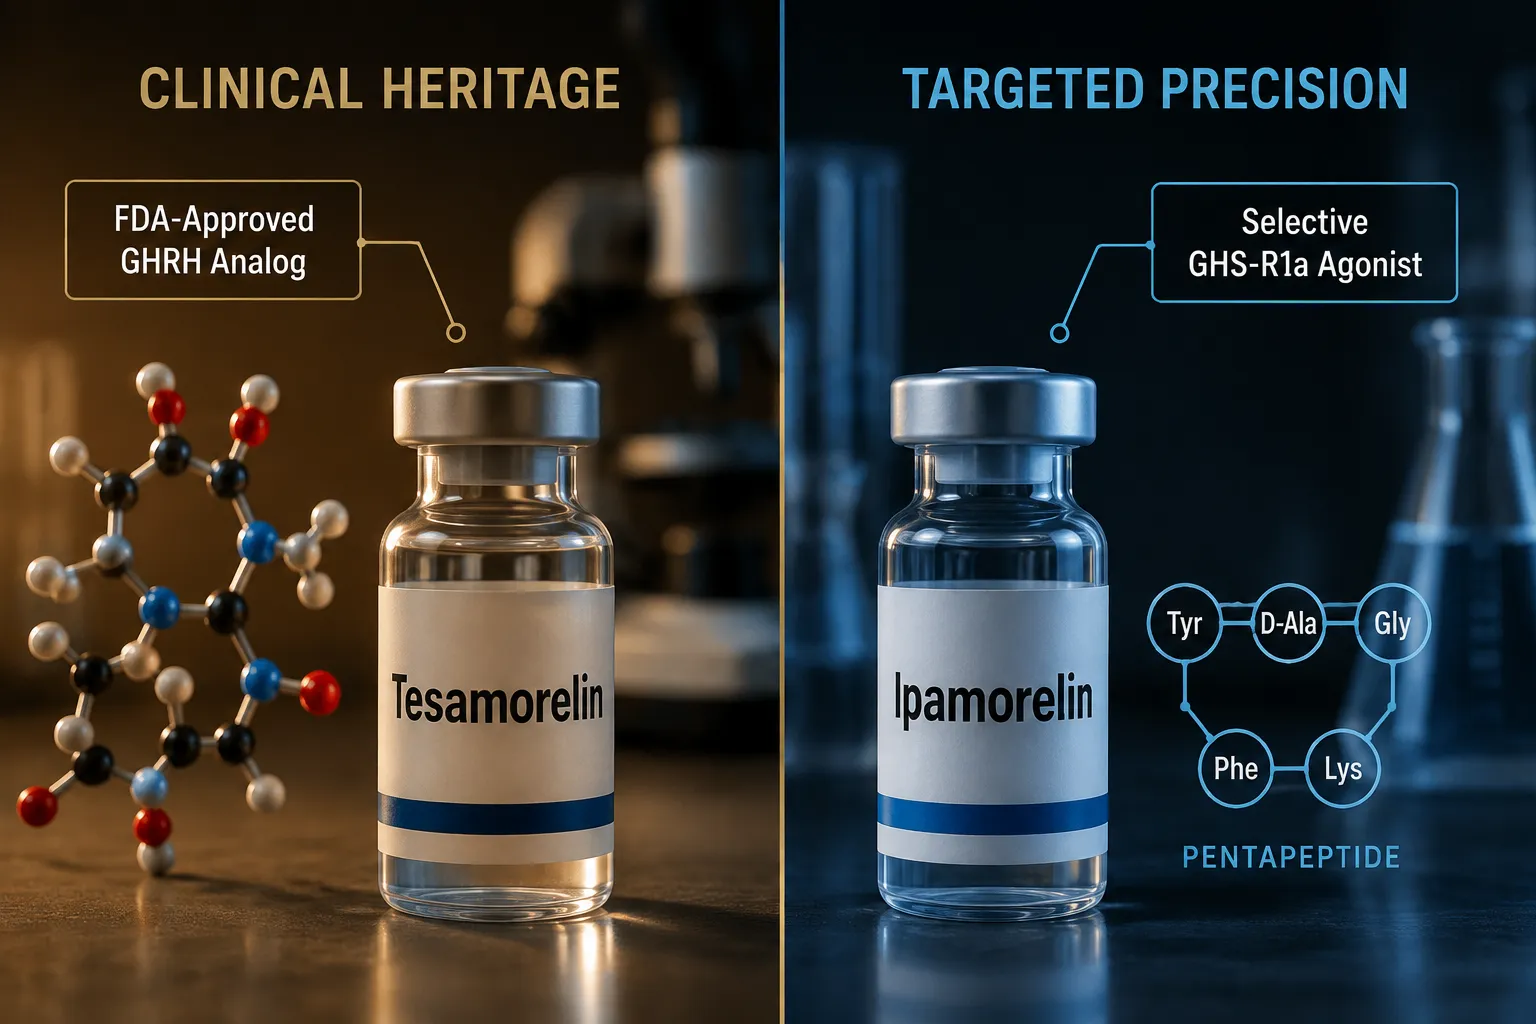
  • Tesamorelin is the only FDA-approved compound in this group, with the strongest clinical evidence base and a recently updated formulation (EGRIFTA WR).
  • For multi-peptide stack research, synergistic GHRH-plus-GHSR designs can amplify GH output beyond what either compound achieves alone.
  • Regulatory and anti-doping status differs sharply across these peptides and must be factored into any research protocol or sourcing decision.

Understanding the Pharmacological Landscape of GH Secretagogue Peptides

Understanding the Pharmacological Landscape of GH Secretagogue Peptides

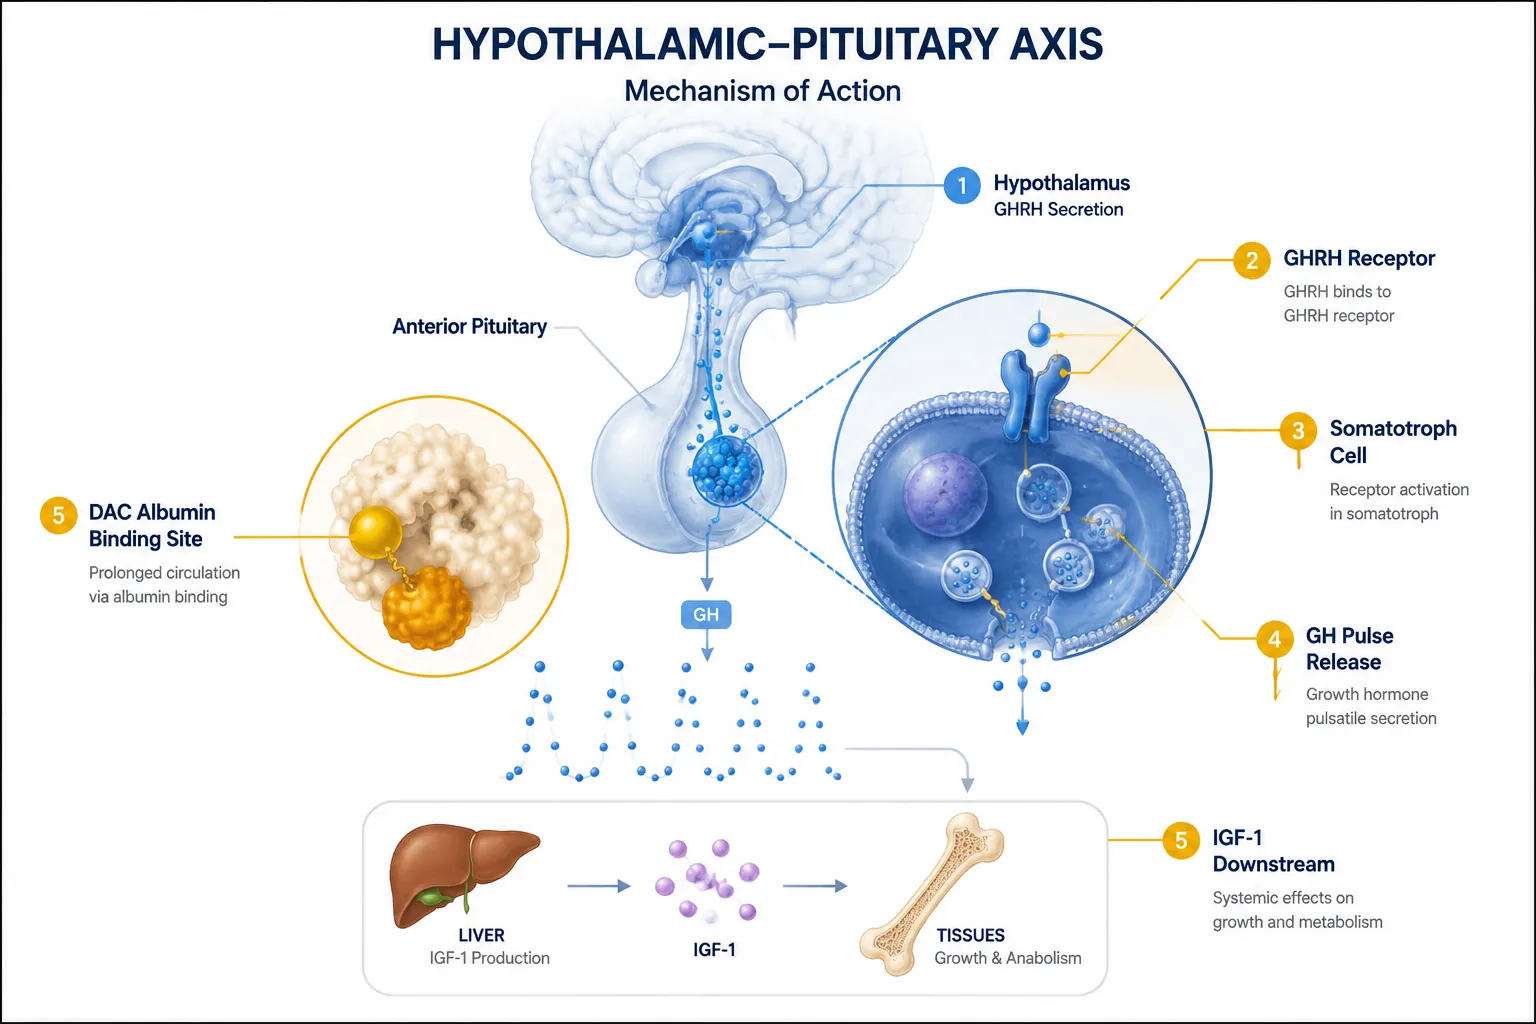
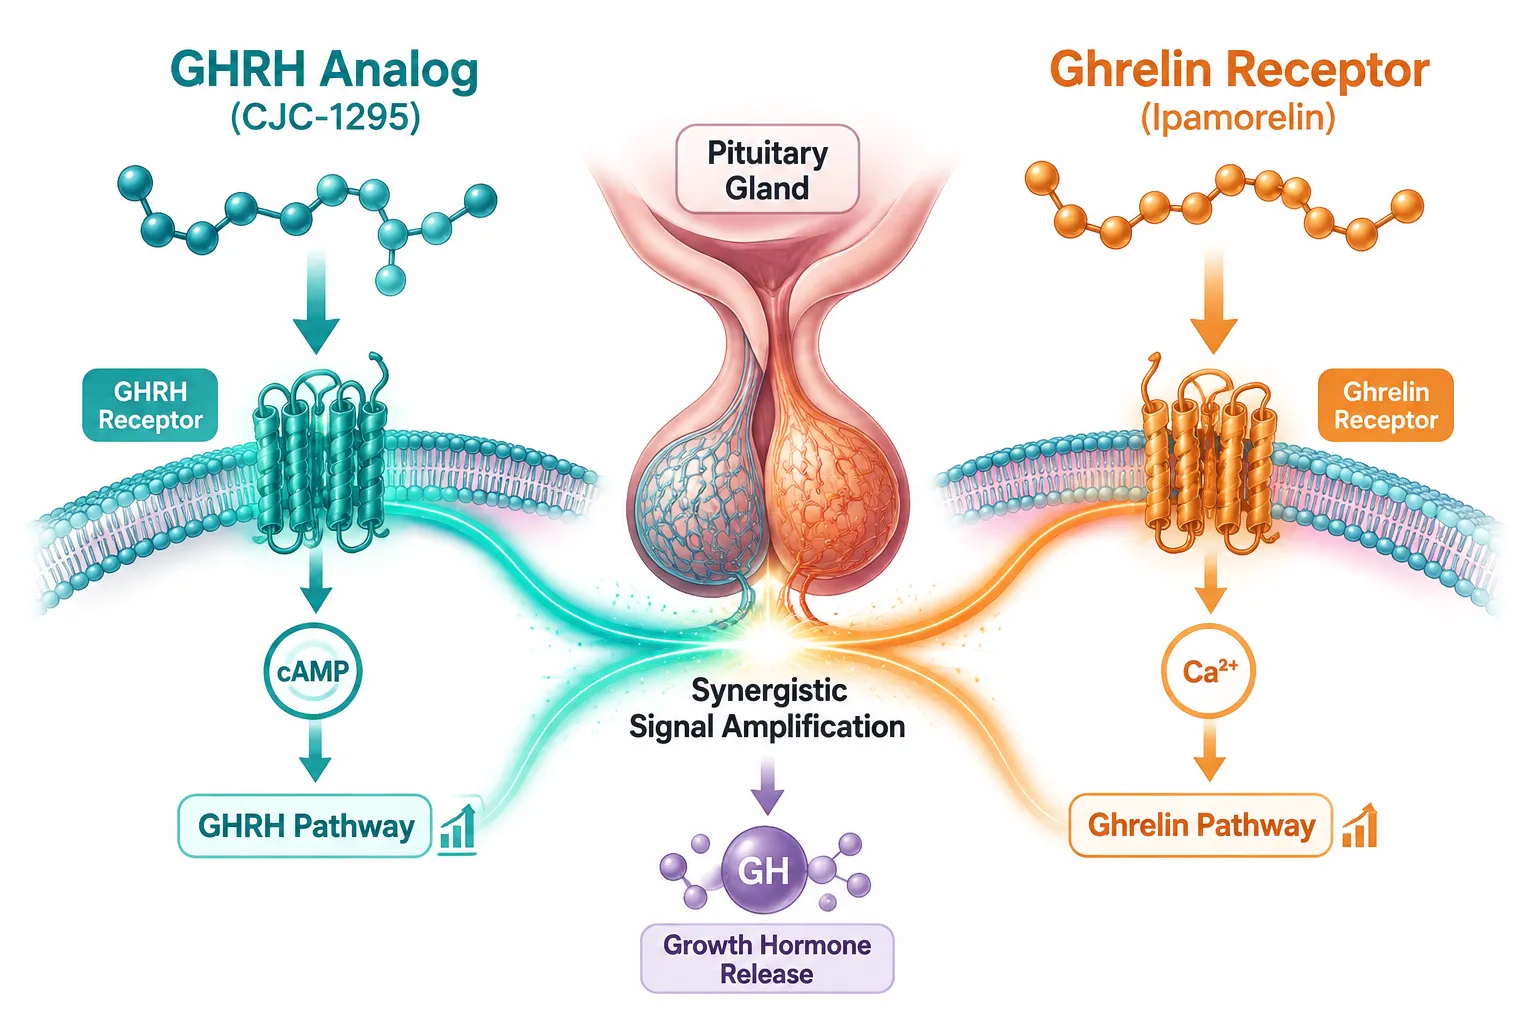
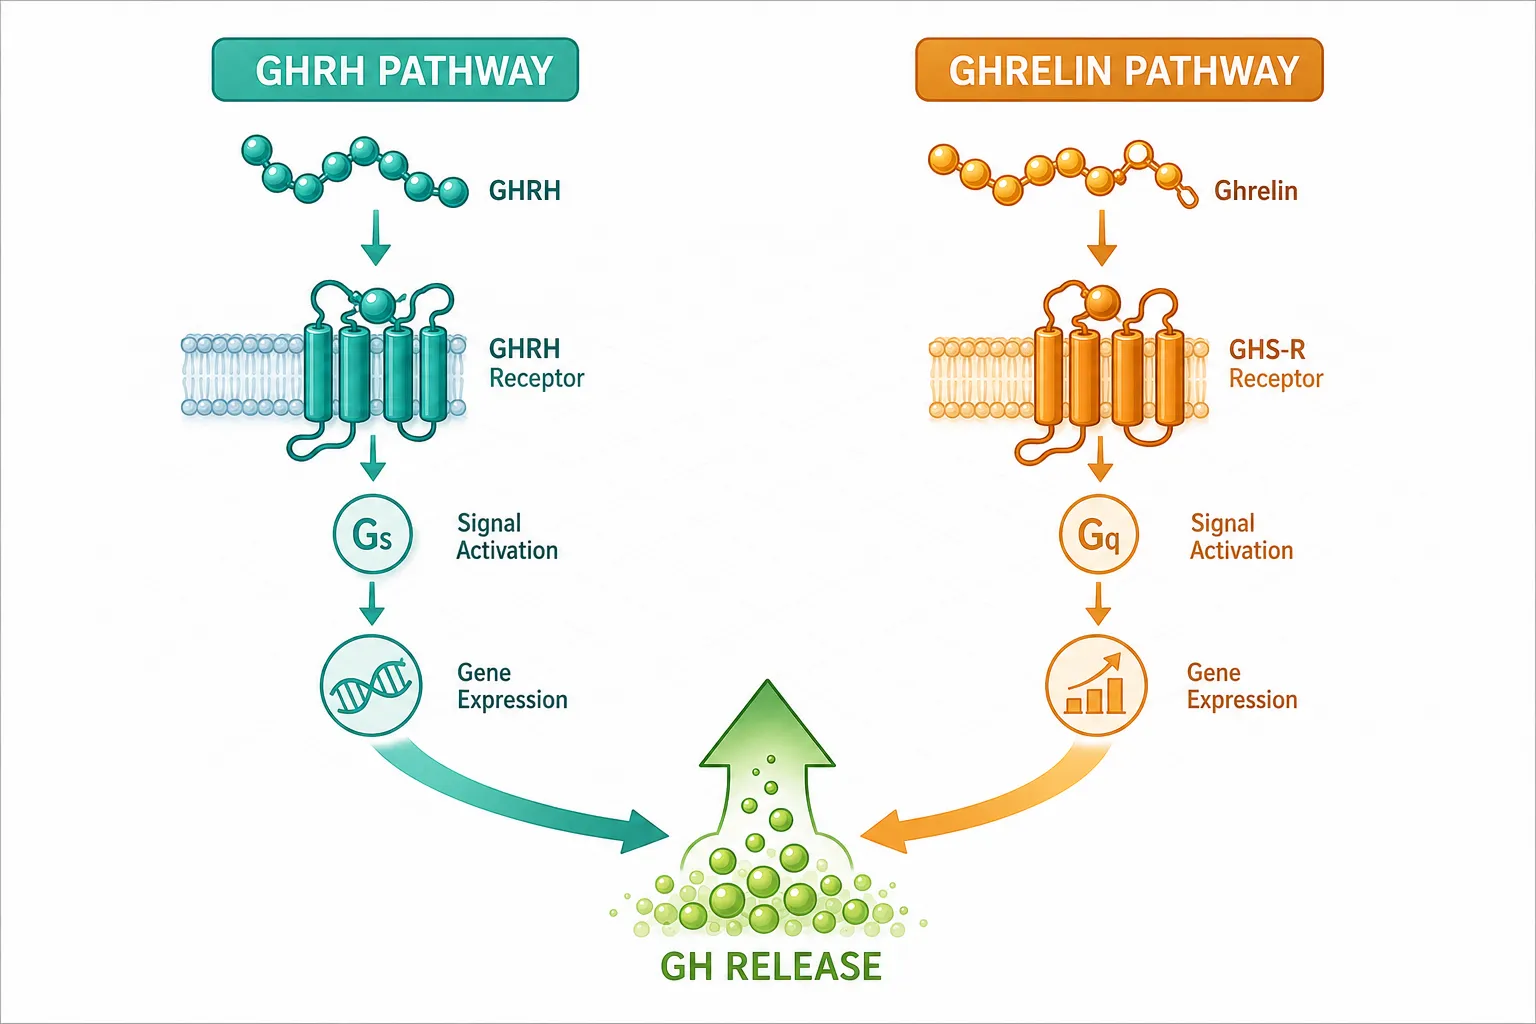
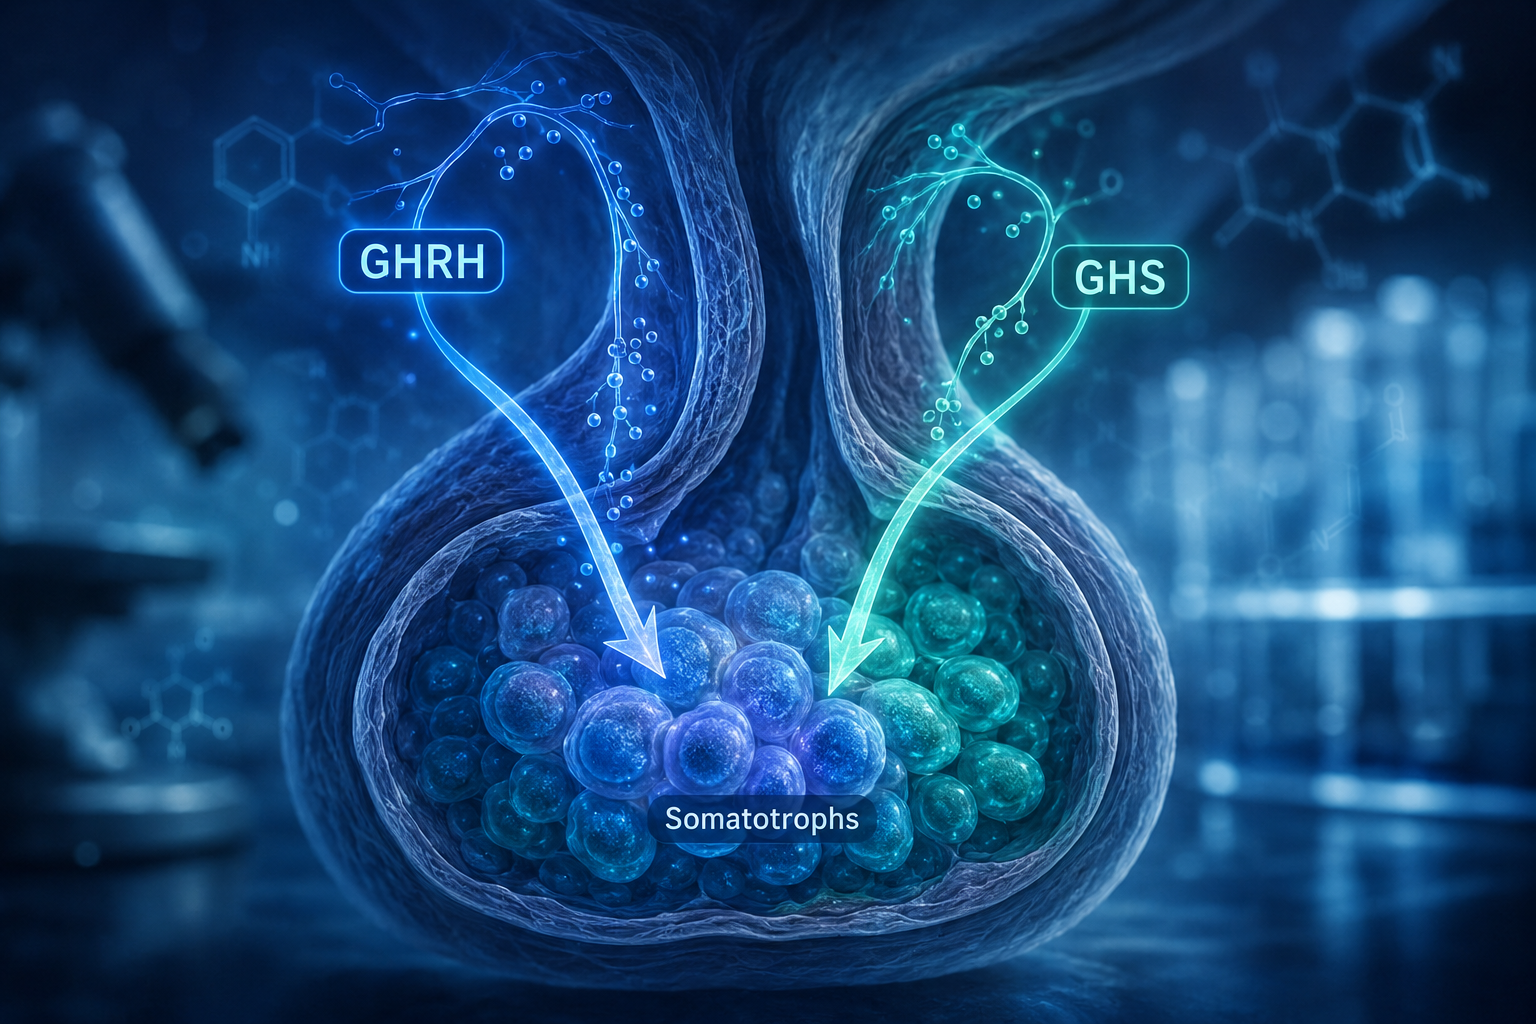
The Best Research-Use GH Secretagogue Peptides: Comparing CJC-1295 (With and Without DAC), Ipamorelin, and Tesamorelin all stimulate GH release, but they do so through distinct receptor pathways. CJC-1295 and tesa act at the GHRH receptor on pituitary somatotrophs. Ipamorelin acts at the GHS-R1a (ghrelin) receptor. This distinction is not trivial for experimental design.

GHRH-receptor agonists (CJC-1295 variants, tesa) amplify the amplitude of GH pulses. GHS-R1a agonists (ipamorelin) primarily increase pulse frequency and can act synergistically when combined with GHRH-pathway compounds. Researchers designing assays around IGF-1 AUC, pulse frequency, or receptor-specific downstream signaling need to select accordingly.

CJC-1295 With DAC vs. Without DAC: A Critical Distinction

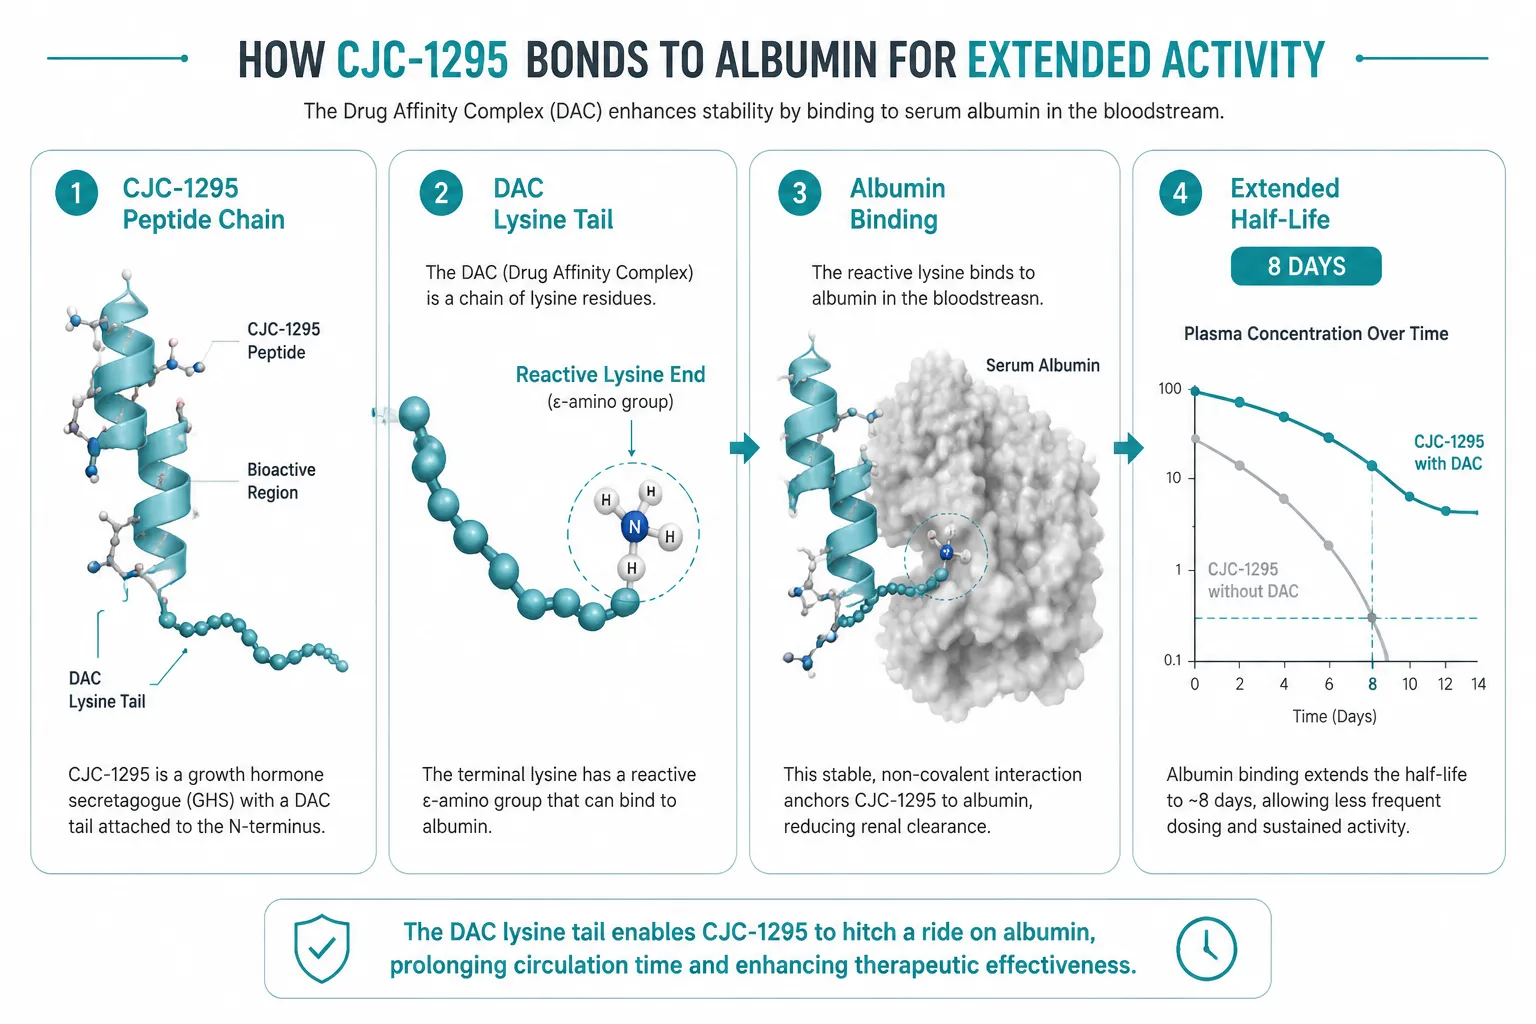
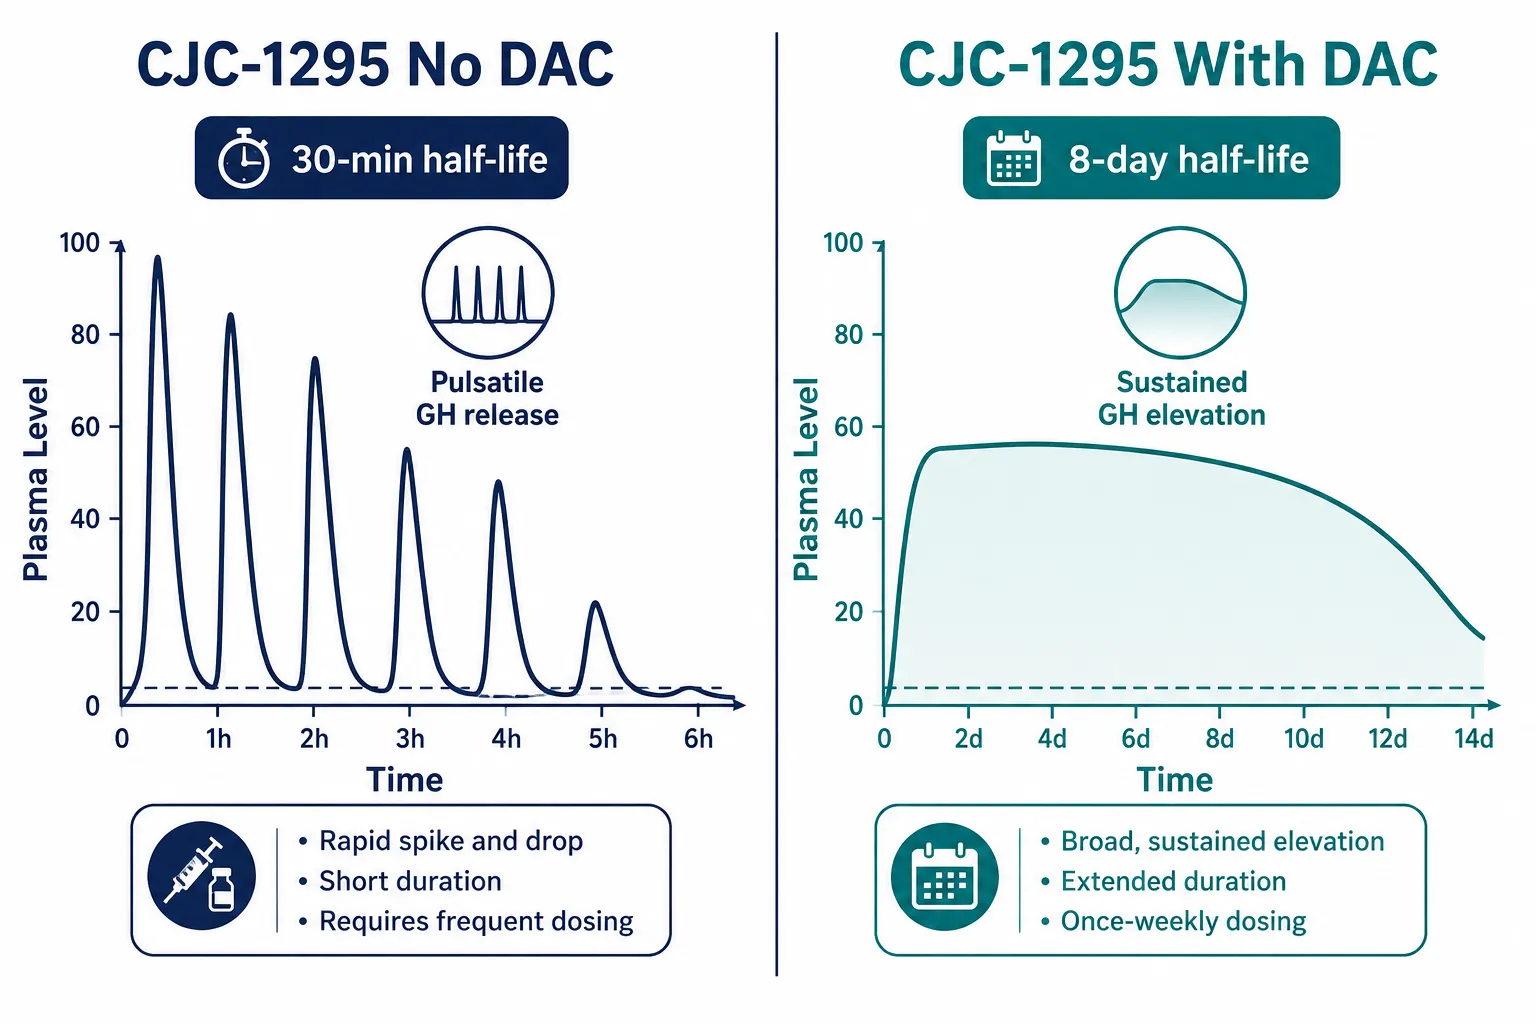
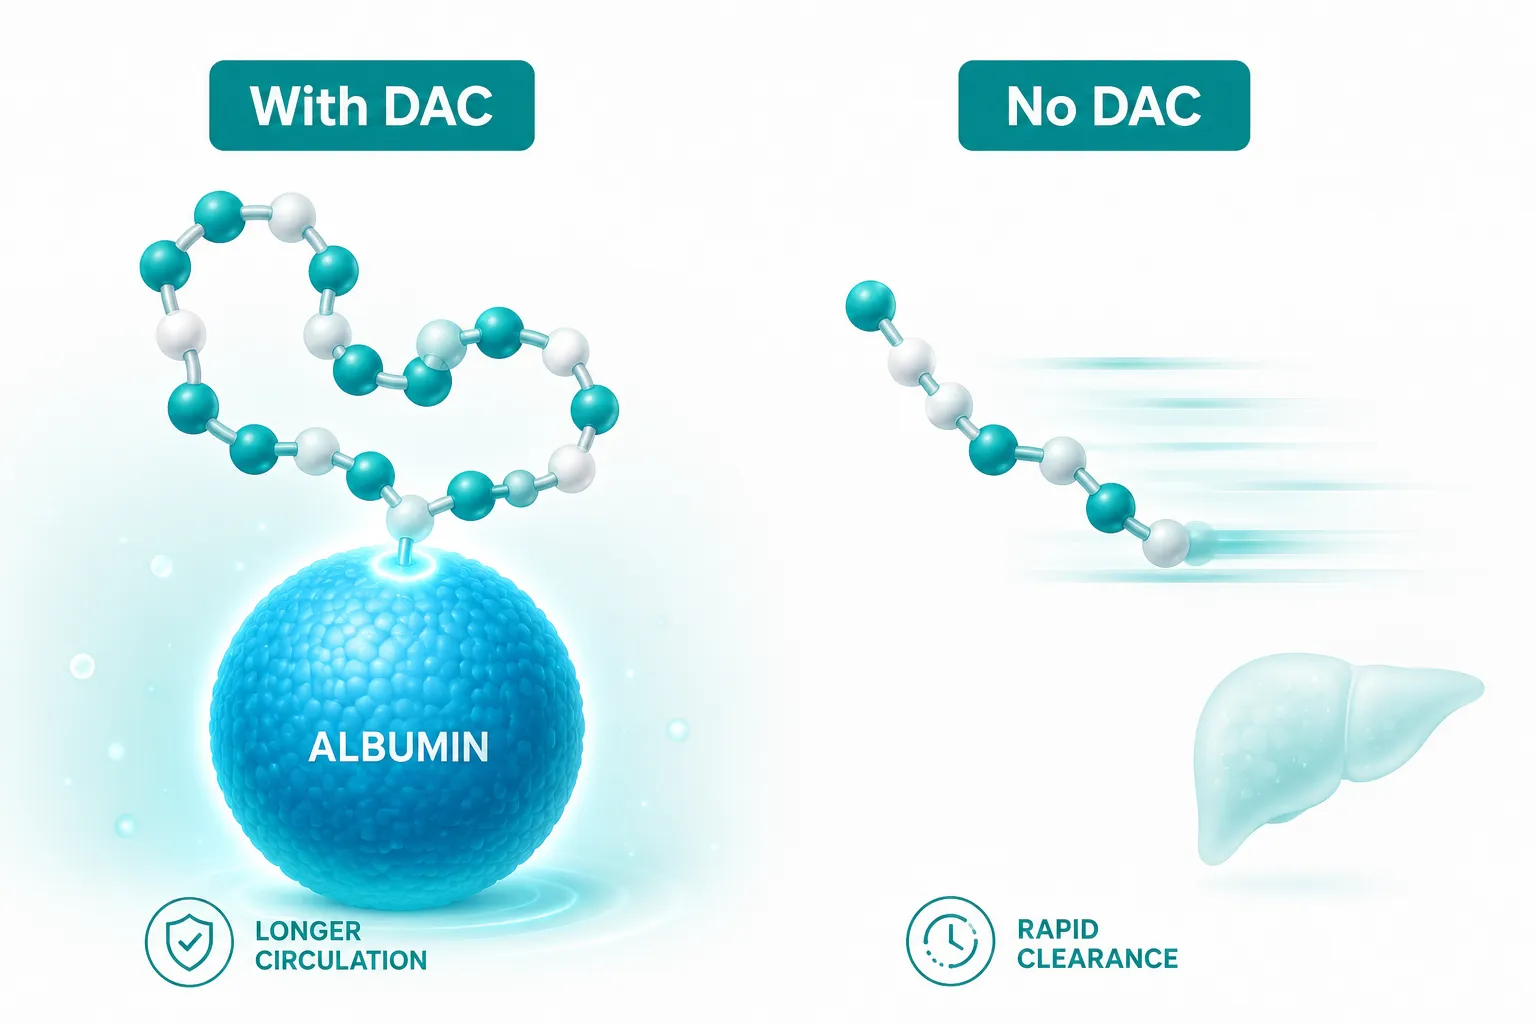
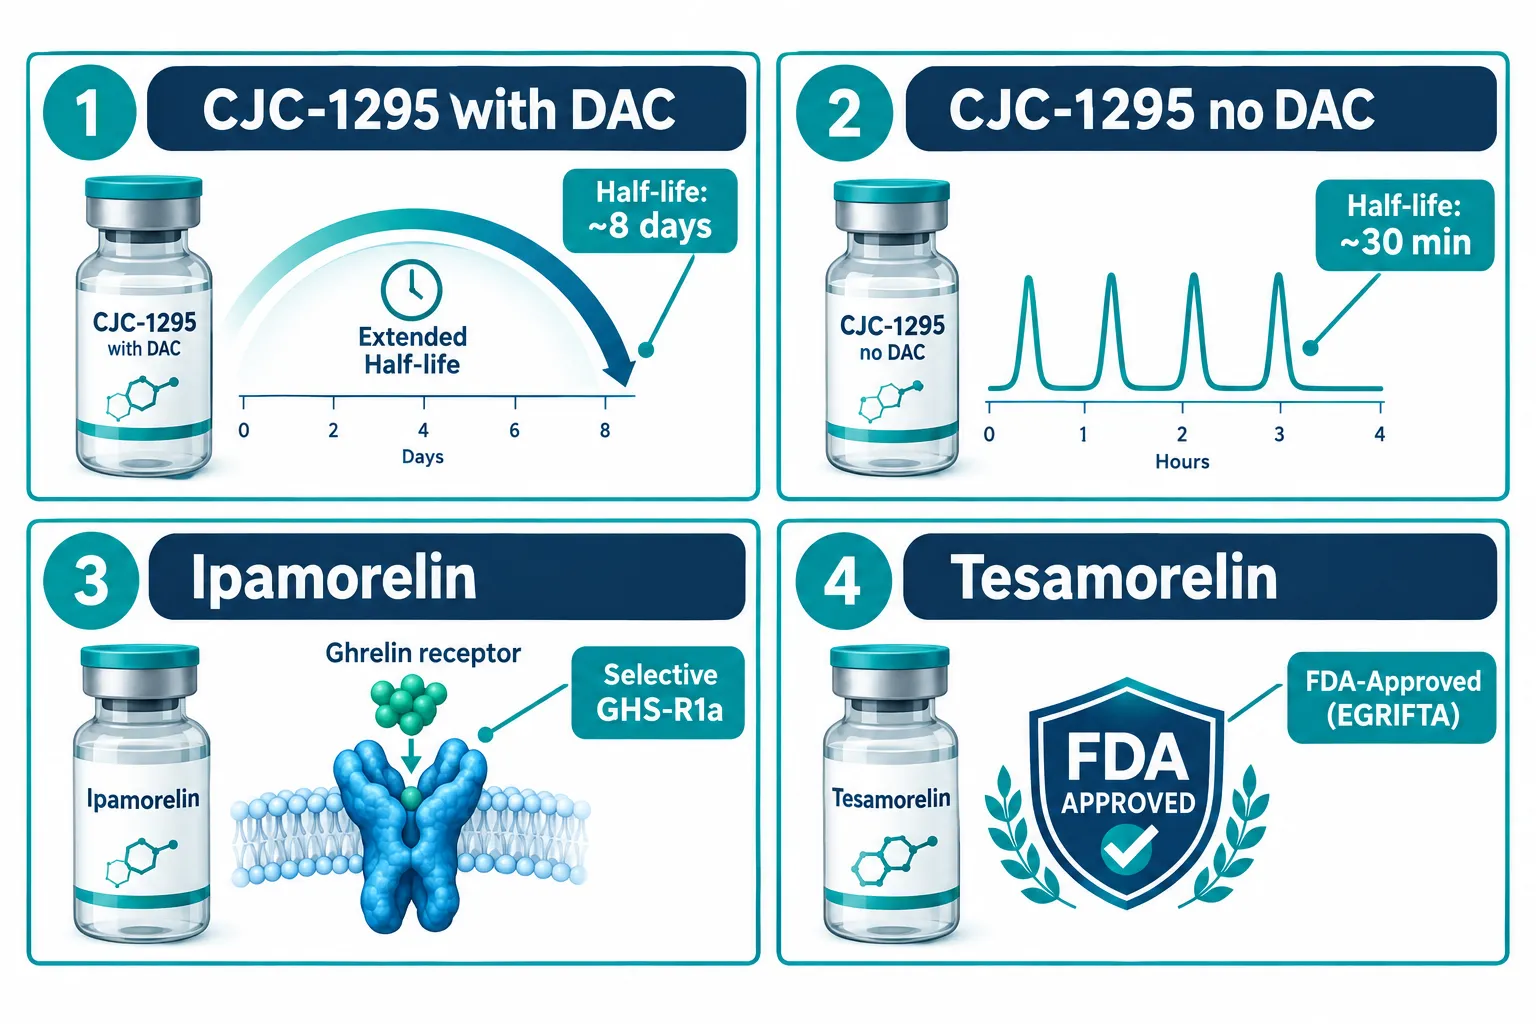
The Drug Affinity Complex (DAC) modification covalently binds CJC-1295 to circulating albumin, extending its half-life from roughly 30 minutes to approximately 8 days. The practical consequences for research are significant:

Parameter CJC-1295 Without DAC CJC-1295 With DAC
Half-life ~30 minutes ~6-8 days
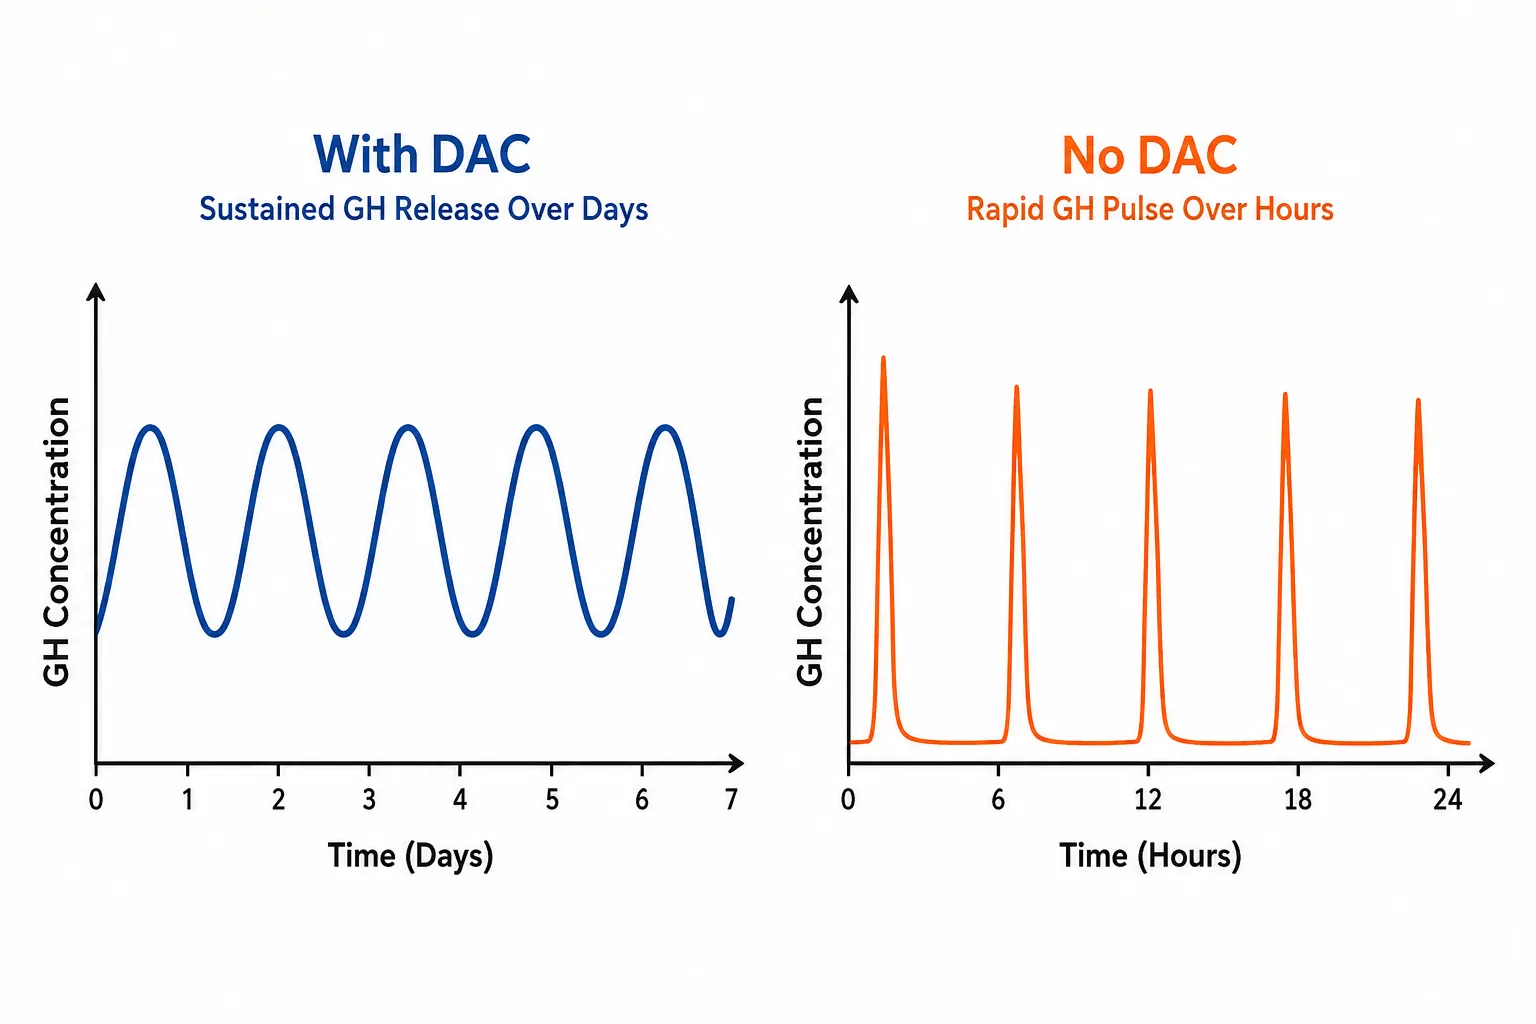
GH release pattern Pulsatile (physiological) Sustained, blunted pulsatility
Best assay fit Pulse-frequency studies Chronic GH-exposure models
Dosing frequency Multiple daily Once or twice weekly

CJC-1295 without DAC is the better tool when pulsatility itself is the endpoint. It produces a sharp, short GH spike that mirrors endogenous GHRH-driven release. CJC-1295 with DAC suits chronic body-composition or metabolic models where sustained GH elevation, rather than pulse architecture, is the variable of interest. Neither compound has cleared phase III clinical trials, and both remain unapproved. They are also banned under the World Anti-Doping Agency code, a factor relevant to any research that interfaces with sport science. For labs exploring combination approaches, the Sermorelin Ipamorelin CJC-1295 dosage resource offers useful context on multi-peptide protocol considerations.

Ipamorelin: Selectivity as a Research Advantage

Ipamorelin: Selectivity as a Research Advantage

Among all GHS-R1a agonists studied in humans, ipamorelin stands out for its receptor selectivity. Unlike earlier ghrelin mimetics such as GHRP-6, ipamorelin does not meaningfully elevate cortisol, prolactin, or ACTH at research-relevant doses. This makes it a cleaner tool for isolating GH-axis effects without confounding hormonal noise.

Human safety data, while limited in volume, show a generally benign profile. The compound has not produced serious adverse signals in short-term studies. However, ipamorelin's clinical development effectively stalled after a pivotal efficacy trial failed to meet its primary endpoint, and no regulatory approval has followed. Compounding scrutiny of ipamorelin has also increased between 2024 and 2026, narrowing its availability through pharmacy channels.

For research purposes, ipamorelin's value is clearest in two scenarios:

  • Mechanistic GHS-R1a studies where receptor-specific signaling must be isolated
  • Stack designs pairing ipamorelin with a GHRH-pathway compound to achieve synergistic GH output

The CJC-1295 IPA 10mg combination format reflects this stack logic. Labs interested in broader systemic peptide research contexts can also review the systemic peptide research resource library for supporting literature.

Tesamorelin: The Gold Standard for Evidence-Based GH Secretagogue Research

Tesamorelin: The Gold Standard for Evidence-Based GH Secretagogue Research

Tesamorelin occupies a different tier entirely. It is a stabilized synthetic analog of endogenous GHRH and the only compound in this comparison with FDA approval. Originally cleared for HIV-associated lipodystrophy, its label was revised in 2025-2026 to reflect the new EGRIFTA WR (F8) formulation, which offers improved stability and reconstitution characteristics relevant to both clinical and research settings.

The evidence base for tesa is substantially deeper than for either CJC-1295 variant or ipamorelin. Randomized controlled trial data confirm meaningful reductions in visceral adipose tissue in people with HIV-associated lipodystrophy. More recently, tesa has shown the strongest disease-modifying signals of any compound in this class for non-alcoholic fatty liver disease (NAFLD) in HIV-positive populations, a finding that has driven an active 2026 research pipeline focused on NAFLD extension and body-composition outcomes.

Researchers benefit from tesa's approval status in several ways:

  • Published pharmacokinetic and safety data are extensive and peer-reviewed
  • Regulatory-grade sourcing is available through licensed channels
  • The compound can serve as a positive control in GH-secretagogue assay panels

For labs designing fat-metabolism or metabolic-syndrome models, reviewing the tesa benefits and tesa dosage for fat loss literature provides a strong foundation. Labs examining safety profiles should also consult the tesa side effects data before designing protocols. For those evaluating tesa against other GHRH-class compounds, the tesa vs. sermorelin comparison is a useful reference point.

Choosing the Right Peptide or Stack for Your Experimental Design

The decision framework below summarizes how to match compound to research objective:

Use CJC-1295 without DAC when: the study endpoint is GH pulse frequency, amplitude, or pulsatility architecture under acute stimulation conditions.

Use CJC-1295 with DAC when: the model requires sustained GH elevation over days or weeks without repeated dosing, such as chronic metabolic or tissue-remodeling studies.

Use ipamorelin when: the research question isolates GHS-R1a signaling, or when a clean GH stimulus is needed without cortisol or prolactin interference. Combining ipamorelin with a GHRH-pathway peptide amplifies GH output through complementary receptor mechanisms.

Use tesa when: the study requires an FDA-approved reference compound, when visceral adiposity or NAFLD endpoints are primary, or when the research must align with published clinical benchmarks. Multi-peptide blend formats such as the Tesamorelin CJC-1295 Ipamorelin 12mg blend are available for labs exploring combined-pathway designs.

Conclusion

Selecting among the Best Research-Use GH Secretagogue Peptides: Comparing CJC-1295 (With and Without DAC), Ipamorelin, and Tesamorelin is fundamentally an experimental-design decision, not a preference. CJC-1295 without DAC is the tool for pulsatility research; CJC-1295 with DAC suits chronic-exposure models; ipamorelin delivers receptor selectivity for mechanistic work; and tesa provides the only clinically validated, regulatory-grade option in the group.

Actionable next steps for research teams:

  1. Define the primary assay endpoint first (pulse architecture, IGF-1 AUC, body composition, receptor signaling) before selecting a compound.
  2. Review the current regulatory and anti-doping status of any unapproved compound before sourcing or publishing.
  3. Consider tesa as a positive control in any GH-secretagogue panel to anchor results to published clinical benchmarks.
  4. For stack designs, pair a GHRH-pathway compound with ipamorelin to exploit complementary receptor mechanisms and maximize GH output in the model.
  5. Source from suppliers that provide third-party purity testing documentation to ensure assay reproducibility.
https://www.puretestedpeptides.com/wp-content/uploads/2026/09/best-research-use-gh-secretagogue-peptides-comparing-cjc-1295-with-and-without-d.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-02 13:04:272026-09-02 13:04:27Best Research‑Use GH Secretagogue Peptides: Comparing CJC‑1295 (With and Without DAC), Ipamorelin, and Tesamorelin
Tesamorelin and Ipamorelin: A Comparative Analysis of Their Mechanisms in Growth Hormone Secretion Research

Tesamorelin and Ipamorelin: A Comparative Analysis of Their Mechanisms in Growth Hormone Secretion Research

August 23, 2026/0 Comments/in Uncategorized/by

Growth hormone deficiency affects an estimated 1 in 4,000 to 10,000 adults worldwide, yet the molecular tools researchers use to study GH axis modulation have grown far more precise than most realize. Two peptides sit at the center of this research landscape: Tesamorelin and Ipamorelin. A comparative analysis of their mechanisms in growth hormone secretion research reveals that these compounds work through fundamentally different receptor systems, signaling cascades, and downstream effects, making their distinction scientifically significant rather than merely academic.

Key Takeaways

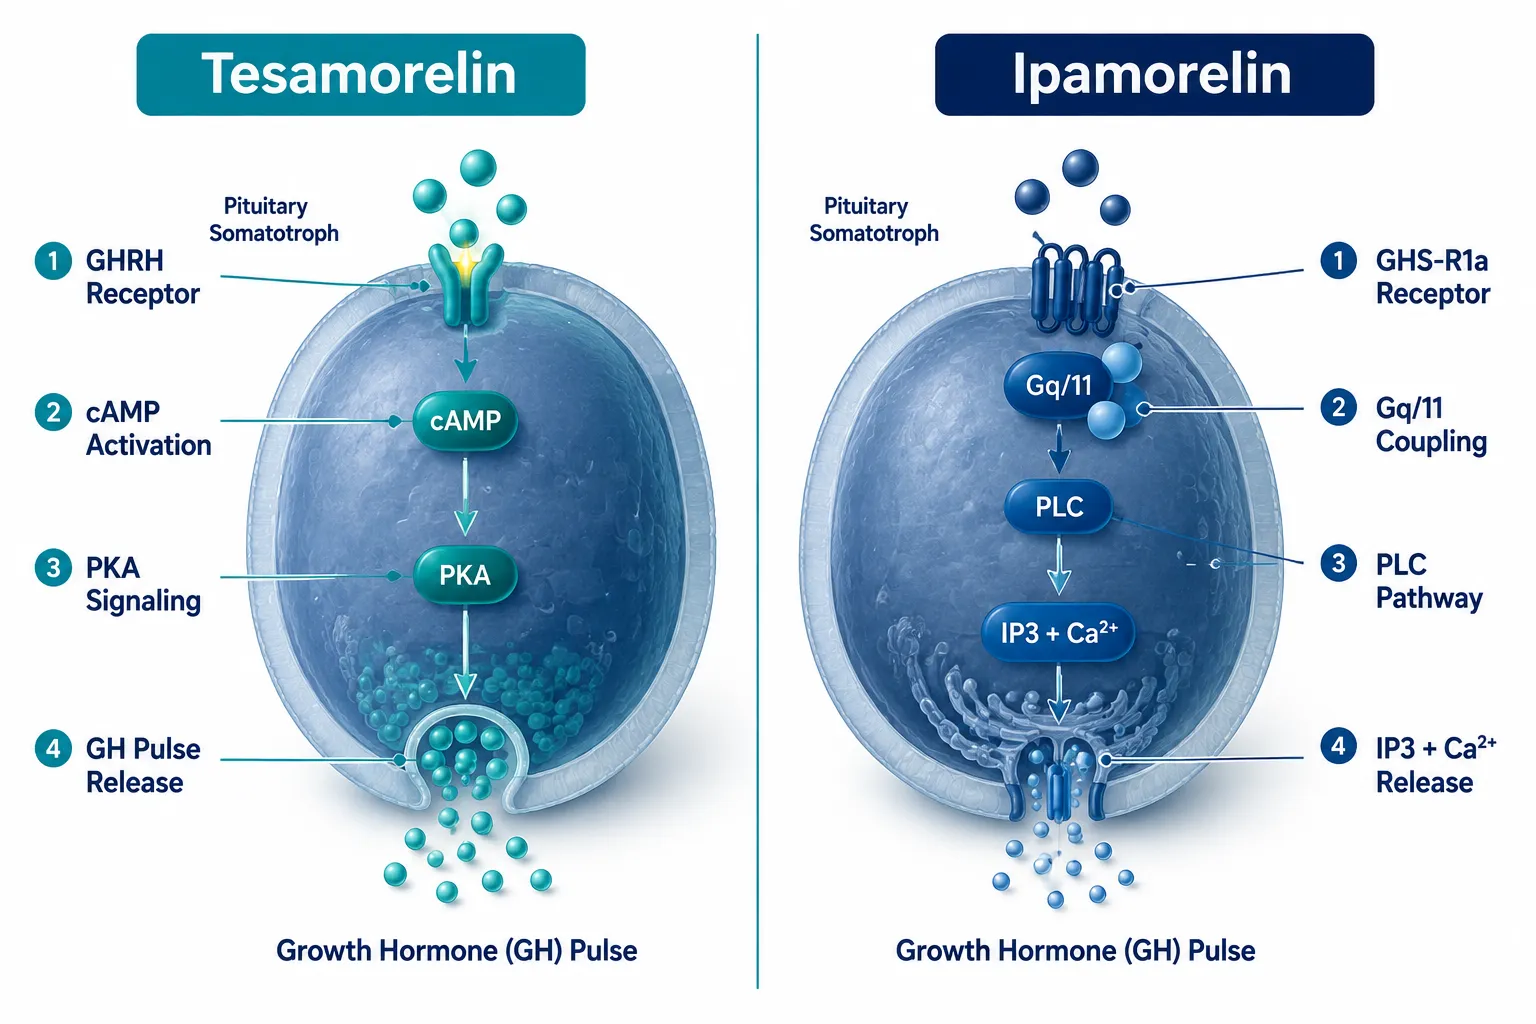
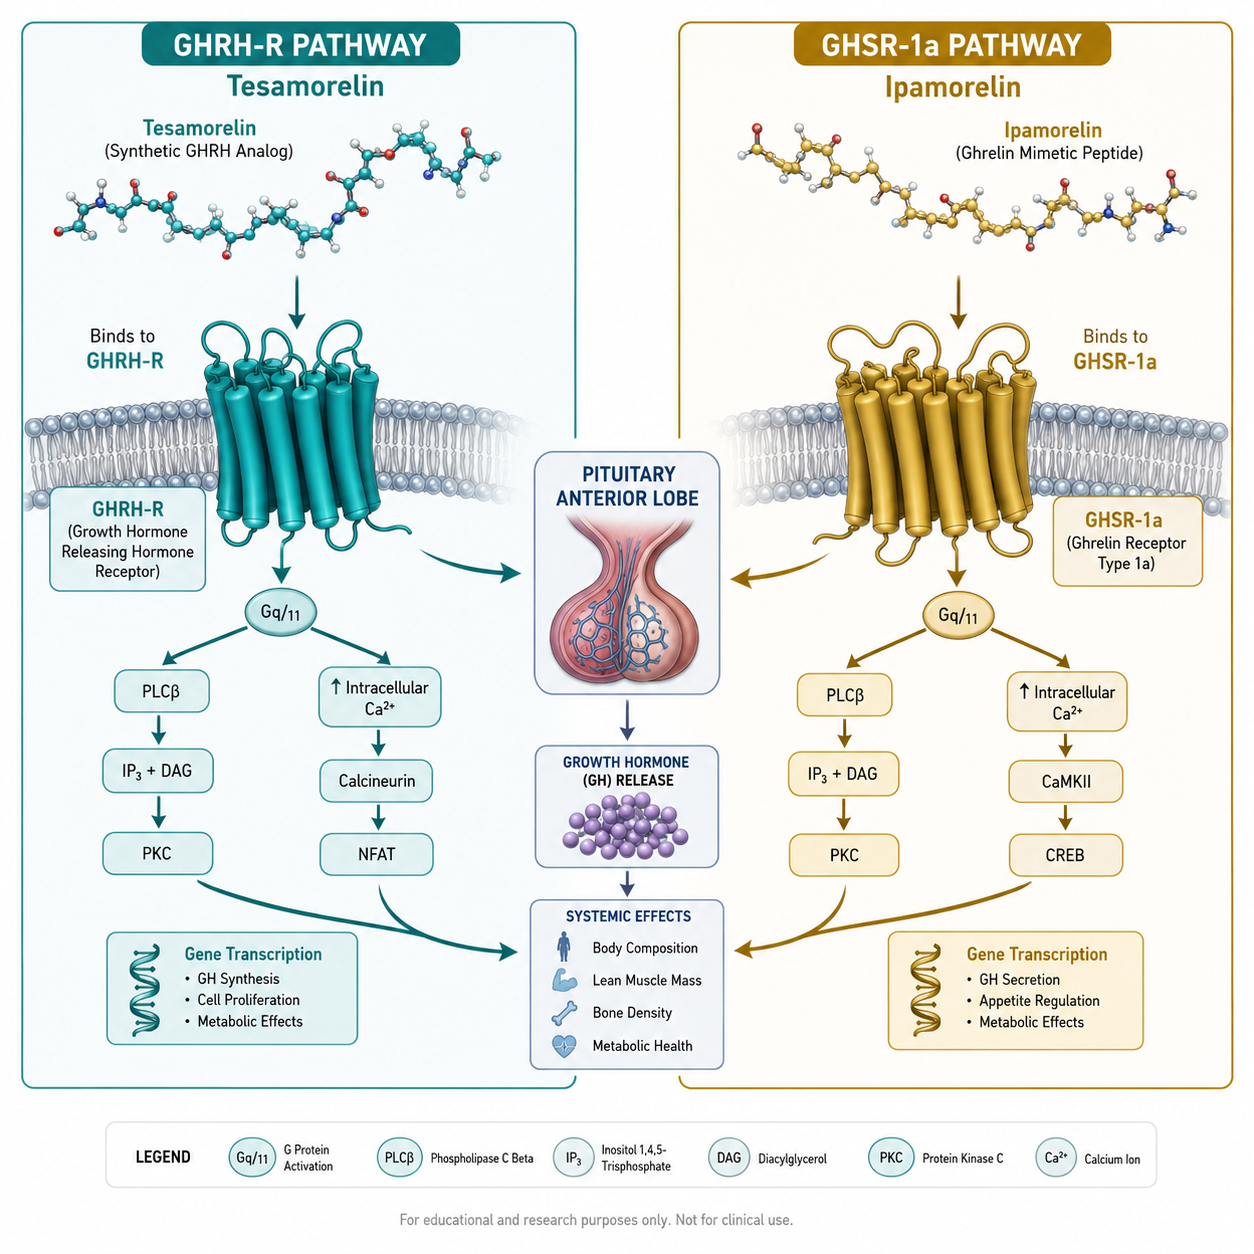
  • Tesamorelin is a synthetic GHRH analog that binds GHRH receptors and triggers cAMP/PKA signaling to stimulate pulsatile GH release.
  • Ipamorelin is a selective GHS-R1a agonist that activates the Gq/11-PLC-calcium pathway to induce GH exocytosis.
  • The two peptides operate through distinct receptor systems and intracellular cascades, making them complementary rather than interchangeable in research models.
  • Tesamorelin holds FDA-approved status for HIV-associated lipodystrophy; Ipamorelin remains a research compound as of 2026.
  • Combining both peptides in research protocols may amplify GH output by engaging two separate stimulatory pathways simultaneously.

Distinct Receptor Targets: The Foundation of Mechanistic Differences

Distinct Receptor Targets: The Foundation of Mechanistic Differences

Understanding Tesamorelin and Ipamorelin through a comparative analysis of their mechanisms in growth hormone secretion research begins at the receptor level. These two peptides do not compete for the same binding site, they target entirely separate receptor classes on pituitary somatotroph cells.

Tesamorelin is a 44-amino acid synthetic analog of endogenous human growth hormone-releasing hormone (GHRH). It binds with high affinity to GHRH receptors (GHRH-R), which are G-protein-coupled receptors linked to the Gs alpha subunit. Once bound, the receptor activates adenylyl cyclase, elevating intracellular cyclic AMP (cAMP) levels. This rise in cAMP activates protein kinase A (PKA), which phosphorylates downstream targets that ultimately trigger GH gene transcription and secretion in a pulsatile pattern that mirrors the body's natural rhythm.

Ipamorelin, by contrast, is a synthetic pentapeptide and a selective agonist of the growth hormone secretagogue receptor subtype 1a (GHS-R1a), the same receptor that endogenous ghrelin activates. GHS-R1a couples to the Gq/11 protein, which activates phospholipase C (PLC). PLC cleaves phosphatidylinositol 4,5-bisphosphate into inositol trisphosphate (IP3) and diacylglycerol (DAG). IP3 then triggers calcium release from intracellular stores, and the resulting surge in intracellular calcium drives GH-containing vesicle exocytosis.

Feature Tesamorelin Ipamorelin
Receptor target GHRH-R GHS-R1a
G-protein coupling Gs Gq/11
Second messenger cAMP IP3 / Ca2+
Signaling kinase PKA PLC / DAG
Structural class 44-AA GHRH analog Synthetic pentapeptide

For researchers exploring Ipamorelin vs Tesamorelin in experimental models, this receptor divergence is the starting point for every downstream comparison.

Intracellular Signaling Cascades and GH Pulsatility

Intracellular Signaling Cascades and GH Pulsatility

The intracellular pathways activated by each peptide produce meaningfully different GH secretion profiles, and this distinction matters for research design.

The cAMP/PKA pathway activated by Tesamorelin is closely aligned with the body's endogenous GHRH signaling. It supports the natural pulsatile architecture of GH release, bursts of secretion followed by troughs, which is important for maintaining physiological feedback sensitivity. Research on the science behind Tesamorelin consistently highlights this pulsatility as a defining feature.

The Gq/PLC/Ca2+ pathway activated by Ipamorelin operates on a slightly different temporal scale. Calcium-mediated exocytosis can be rapid and robust, but Ipamorelin's selectivity for GHS-R1a is a key research advantage. Unlike earlier-generation GH secretagogues such as GHRP-6, Ipamorelin produces minimal elevation in cortisol or prolactin at research-relevant doses. This selectivity makes it a cleaner tool for isolating GH axis effects.

"The mechanistic separation between GHRH-analog and ghrelin-receptor pathways is precisely what makes dual-peptide research protocols scientifically compelling."

When both pathways are engaged simultaneously, as studied in Tesamorelin CJC1295 Ipamorelin blend research, the synergistic effect on GH output is substantially greater than either compound alone. The cAMP arm primes somatotrophs while the calcium arm triggers rapid vesicle release, creating an amplified but still physiologically patterned secretion event.

Researchers examining CJC-1295 without DAC and half-life considerations in GH research will find similar half-life dynamics at play with Tesamorelin, which has a relatively short active window compared to DAC-modified analogs.

Downstream Effects, Regulatory Status, and Research Applications

Downstream Effects, Regulatory Status, and Research Applications

A thorough Tesamorelin and Ipamorelin comparative analysis of their mechanisms in growth hormone secretion research must extend beyond receptor binding to examine what happens after GH is released.

IGF-1 elevation is a shared downstream outcome. Both peptides stimulate pituitary GH secretion, which in turn drives hepatic production of insulin-like growth factor 1 (IGF-1). IGF-1 mediates many of GH's anabolic and metabolic effects, including lean mass support and lipid metabolism regulation. Researchers tracking Tesamorelin benefits note its well-documented effect on visceral adipose tissue reduction, an outcome directly tied to elevated GH and IGF-1 signaling.

Regulatory status as of 2026 differs sharply between the two:

  • Tesamorelin (brand name Egrifta) holds FDA approval specifically for reducing excess abdominal fat in HIV-positive adults with lipodystrophy. This clinical validation provides a strong evidence base for its GHRH-mimetic mechanism.
  • Ipamorelin remains a research compound with no current FDA-approved indication, used exclusively in preclinical and investigational contexts.

Researchers should also note that Tesamorelin side effects in clinical data include injection-site reactions and potential glucose metabolism changes, findings relevant to any research protocol design.

For those designing multi-peptide studies, the is it safe to combine Tesamorelin with Ipamorelin resource offers protocol-level considerations worth reviewing before initiating research.

Key research applications in 2026:

  • Metabolic and adipose tissue studies (Tesamorelin-dominant protocols)
  • Selective GH axis stimulation with minimal hormonal off-target effects (Ipamorelin-dominant protocols)
  • Synergistic dual-pathway activation studies using blended formulations
  • Age-related GH decline models examining somatotroph responsiveness

Conclusion

The mechanistic divergence between Tesamorelin and Ipamorelin is not a minor technical footnote, it defines how each compound fits into a research protocol and what questions each can answer. Tesamorelin replicates endogenous GHRH signaling through the cAMP/PKA axis, producing pulsatile GH release with strong clinical validation. Ipamorelin engages the ghrelin receptor pathway via Gq/PLC/calcium signaling, offering high selectivity and a clean hormonal profile.

Actionable next steps for researchers:

  1. Define the specific GH axis question before selecting a compound, receptor target determines the answer you can extract.
  2. Review half-life and dosing timing data for each peptide to align secretion peaks with measurement windows.
  3. Consider dual-pathway protocols when maximum GH output with physiological patterning is the research goal.
  4. Consult current regulatory guidance, as the status of research peptides continues to evolve in 2026.
  5. Source compounds from verified, tested suppliers to ensure purity and consistency across experimental runs.

Researchers who understand the mechanistic distinction between these two peptides are better positioned to design rigorous, reproducible studies that advance the broader science of hormone research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/tesa-and-ipamorelin-a-comparative-analysis-of-their-mechanisms-in-growth.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-23 13:03:142026-08-23 13:03:14Tesamorelin and Ipamorelin: A Comparative Analysis of Their Mechanisms in Growth Hormone Secretion Research
Understanding Polypeptide Peptides: Mechanism of Action in Research Applications

Understanding Polypeptide Peptides: Mechanism of Action in Research Applications

August 20, 2026/0 Comments/in Uncategorized/by

The global peptide therapeutics market was valued at approximately USD 68 billion in 2024 and is projected to reach roughly USD 175 billion by 2031, a compound annual growth rate near 15%. Behind that growth sits a single driving force: a deeper understanding of how polypeptide peptides work at the molecular level and what that means for research design.

For researchers moving from general biology into peptide-specific work, the terminology can feel overwhelming. "Polypeptide" and "peptide" are often used interchangeably, yet the distinction in chain length, secondary structure, and receptor interaction changes every research question that follows. This guide on understanding polypeptide peptides: mechanism of action in research applications translates that complexity into practical lab language.

Key Takeaways

  • Polypeptides are amino acid chains whose length, charge, and secondary structure directly determine how they interact with cells and tissues.
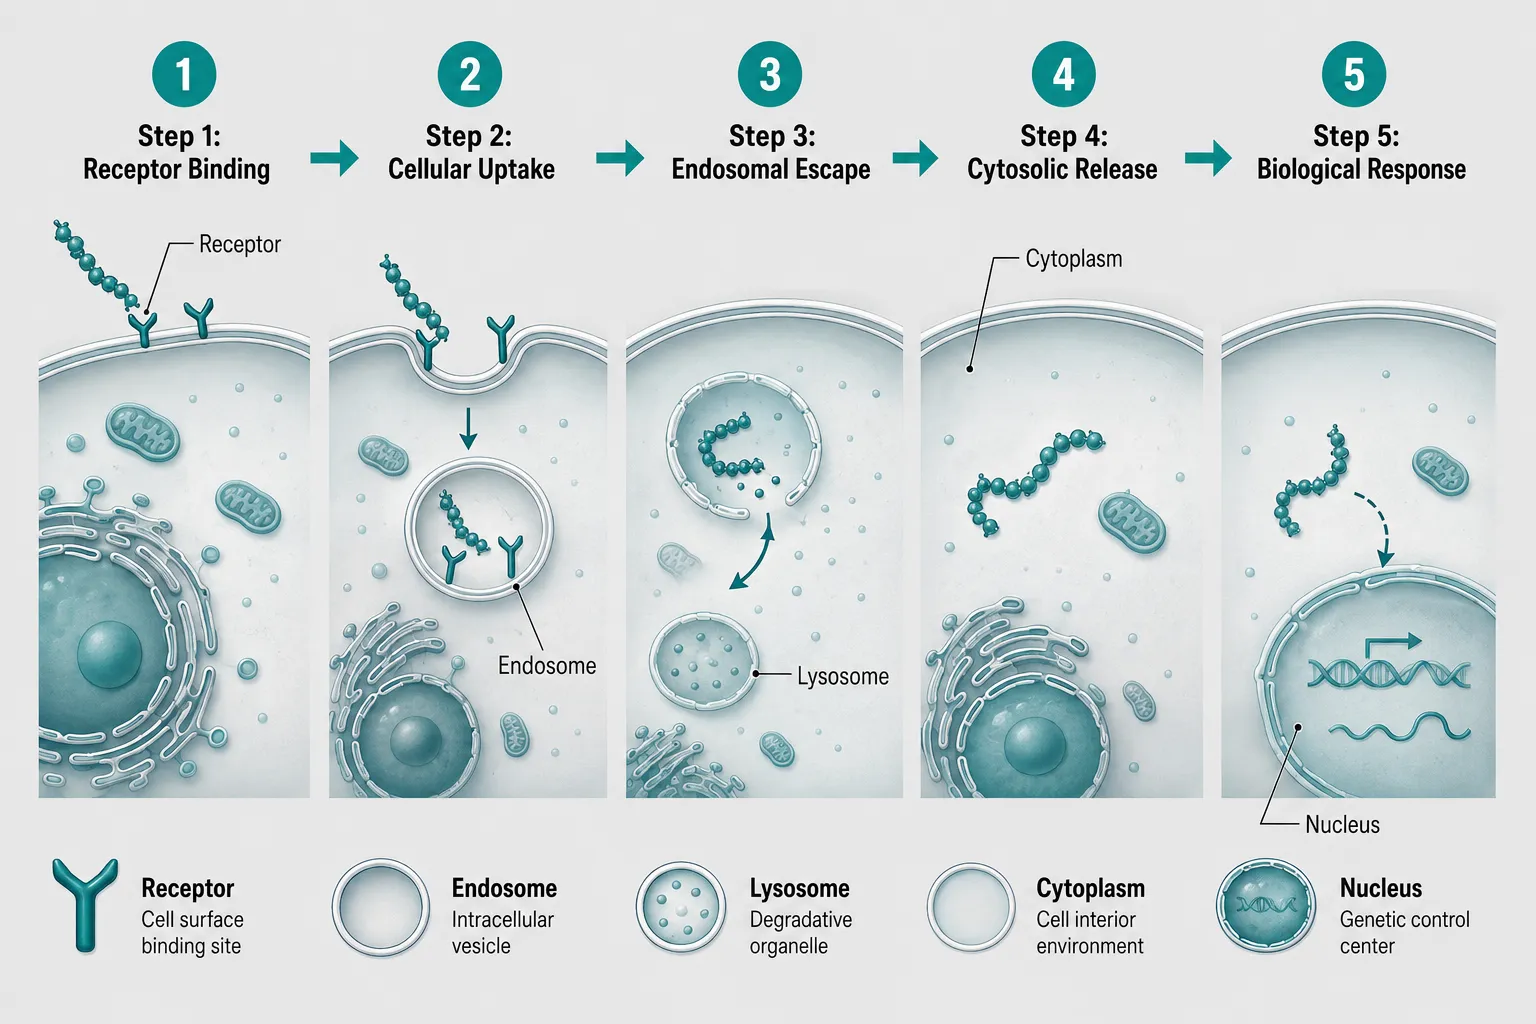
  • Core mechanisms include receptor binding, cellular uptake, endosomal escape, and cytosolic release, each step is a variable a researcher can tune.
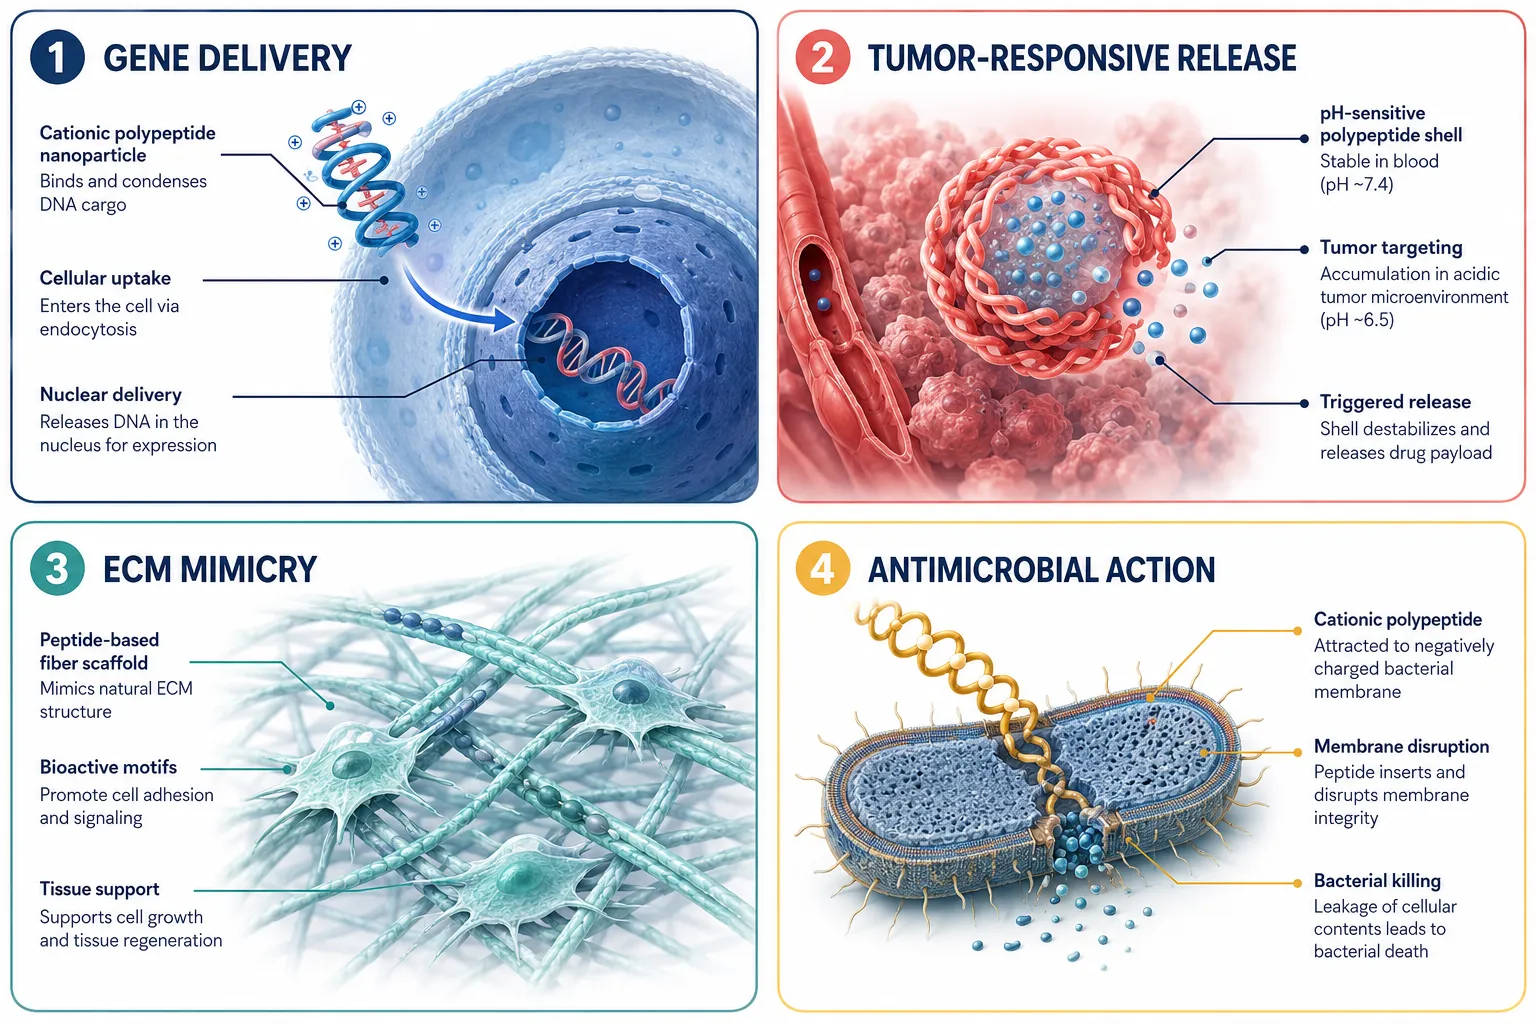
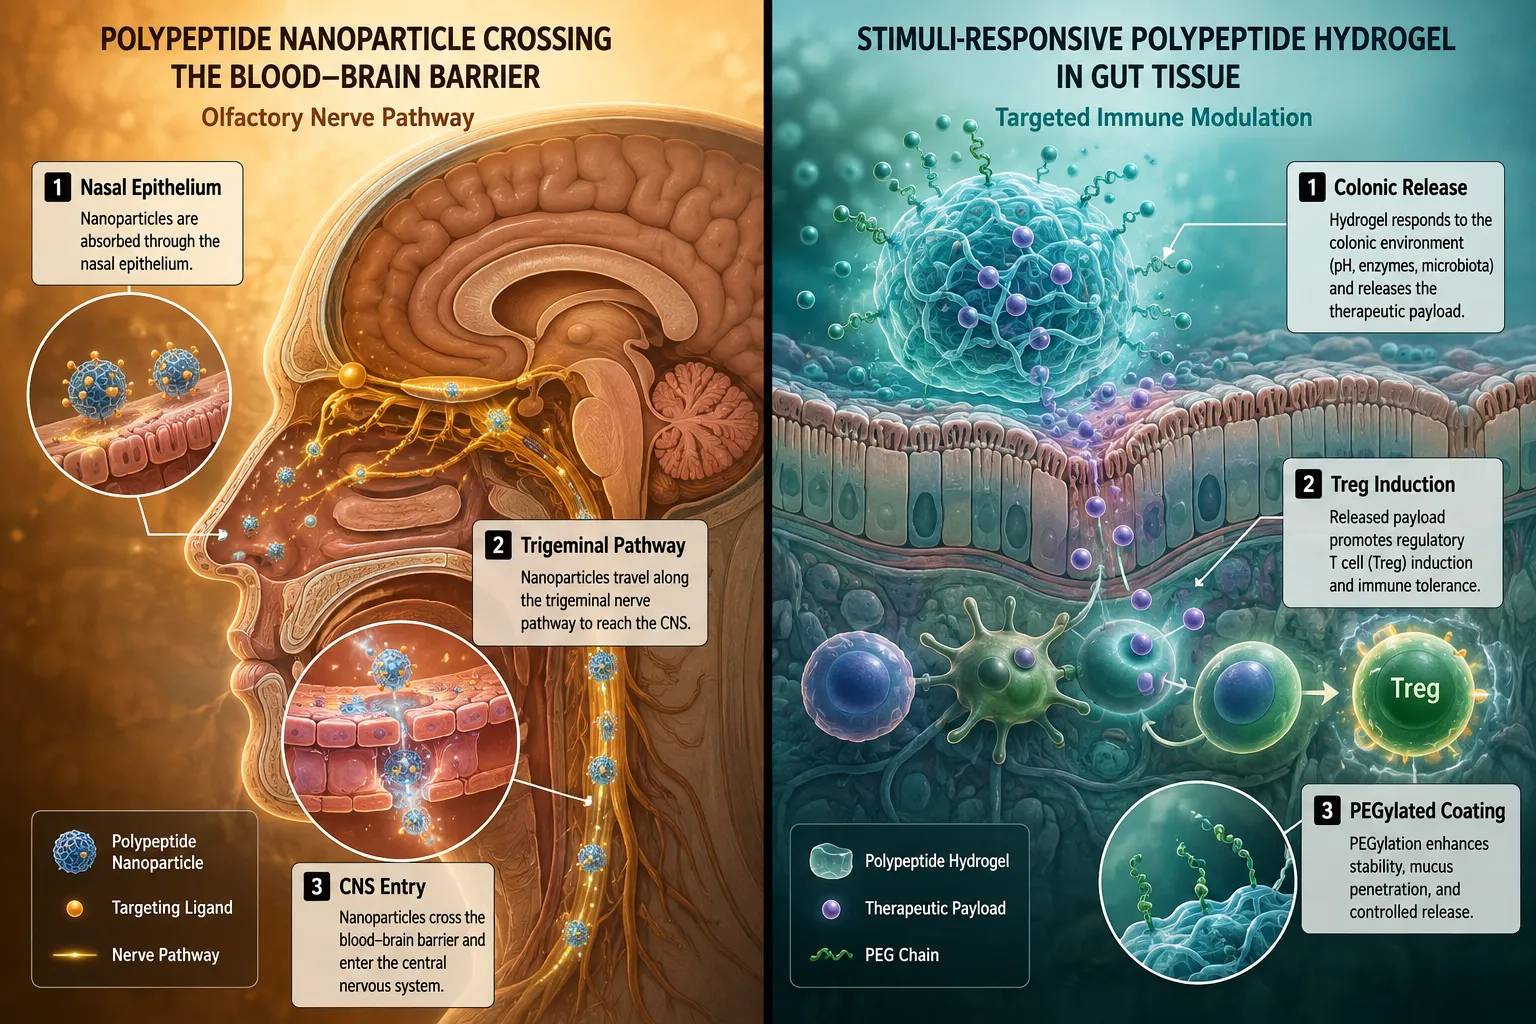
  • Stimuli-responsive polypeptide carriers can activate selectively at tumor sites, in the gut, or across the blood-brain barrier.
  • Formulation choices, nanoparticles, hydrogels, PEGylation, cyclization, protect peptides from degradation and shape their pharmacokinetics.
  • With over 800 peptide drug projects currently in development, polypeptide mechanisms are central to oncology, metabolic disease, CNS research, and antimicrobial pipelines.

What Are Polypeptide Peptides and Why Do Definitions Matter in Research

A peptide is a short chain of amino acids linked by peptide bonds. A polypeptide is a longer chain, typically more than 50 residues, that can fold into defined secondary structures such as alpha-helices or beta-sheets. That structural difference is not academic. A helical polypeptide carries a different surface charge distribution than a random coil, and that difference controls how it binds receptors, crosses membranes, and survives enzymatic degradation in biological fluids.

What Are Polypeptide Peptides and Why Do Definitions Matter in Research

For researchers sourcing compounds, it also affects formulation. Shorter peptides may be candidates for oral peptides for sale formats, while longer, more structured polypeptides often require injectable or nanoparticle-based delivery to preserve their active conformation. Understanding this distinction prevents mismatched experimental designs before a single assay is run.

Three structural features that shape mechanism of action:

Feature Research Impact
Chain length Determines folding, receptor fit, and metabolic stability
Net charge (cationic/anionic) Controls membrane interaction and endosomal escape efficiency
Secondary structure (helix, sheet) Dictates self-assembly behavior and biological target specificity

Core Mechanisms: How Polypeptide Peptides Act Inside Cells

Understanding polypeptide peptides: mechanism of action in research applications begins with a five-step cellular journey that every research protocol must account for.

Step 1, Receptor binding. Polypeptides recognize specific cell-surface receptors through shape and charge complementarity. GLP-1 peptides, for example, bind the glucagon-like peptide-1 receptor with high specificity, triggering downstream signaling cascades relevant to metabolic research. Researchers exploring this pathway can review the GLP-3, GLP-1, and GLP-2 explained: a researcher's guide to the peptide family for mechanistic context.

Step 2, Cellular uptake. Peptides enter cells primarily through endocytosis or direct membrane penetration. Which pathway dominates depends on the peptide's charge, size, and the cell type being studied. Most mRNA-carrying polypeptide systems rely predominantly on endocytosis for internalization.

Step 3, Endosomal escape. This is the critical bottleneck. After endocytosis, peptides are trapped in acidifying endosomes that route toward lysosomal degradation. Cationic helical polypeptides can disrupt endosomal membranes through membrane stress, releasing their cargo into the cytosol. Recent KAIST research demonstrated that a helical quaternary amine polypeptide nanoparticle achieves this while simultaneously triggering immunogenic cell death signals, combining gene delivery and cancer immunotherapy in a single platform.

Step 4, Cytosolic release and translation. Once in the cytoplasm, nucleic acid cargo is released and translated. The efficiency of this step depends on how well the polypeptide carrier dissociates from its payload under intracellular conditions.

Step 5, Biological response. The downstream effect, gene expression, receptor activation, immune modulation, is what the researcher measures. Every upstream variable influences this output.

Core Mechanisms: How Polypeptide Peptides Act Inside Cells

Formulation Strategies That Change Research Outcomes

Mechanism of action does not exist in isolation from formulation. A polypeptide with ideal receptor affinity will fail in vivo if it degrades in serum before reaching its target. This is where understanding polypeptide peptides: mechanism of action in research applications becomes inseparable from delivery science.

Stimuli-responsive systems engineer polypeptide carriers to activate only under specific conditions, low pH, elevated glutathione, or tumor-associated enzymes. This selectivity improves target specificity and reduces off-target effects, a key consideration in oncology research pipelines. For mitochondria-targeted research, the SS-31 10mg research peptide considerations page provides a concrete example of how a short, charge-rich peptide is formulated for organelle-level action.

ECM-mimicking scaffolds use polypeptide fiber membranes to replicate extracellular matrix architecture, supporting cell adhesion and proliferation in tissue engineering and wound-healing studies. These systems work because the polypeptide's secondary structure physically resembles native collagen or fibronectin networks.

CNS delivery represents a newer frontier. Intranasal polypeptide delivery can bypass the blood-brain barrier via olfactory and trigeminal nerve pathways, enabling direct CNS access. The underlying transport mechanisms remain an active research area. Neurologically active peptides such as those discussed in Semax and Selank peptides: comparative research on neurogenesis and synaptic plasticity illustrate how CNS-targeted polypeptides are being studied in practice.

Key formulation tools researchers use:

  • PEGylation, attaches polyethylene glycol chains to extend circulation half-life
  • Cyclization and stereochemical modification, resists proteolytic degradation
  • Lipid and polymer nanoparticles, protect peptide cargo and enable targeted colonic or tumor-site release
  • Hydrogels, provide sustained local release for tissue engineering or IBD applications

Half-life is a particularly important variable in growth hormone research. The CJC-1295 without DAC: why half-life matters in growth hormone research article explores how small structural changes dramatically alter a polypeptide's pharmacokinetic profile, a principle that applies broadly across peptide research categories. Additional context on this topic is available through the growth hormone research resource library.

Formulation Strategies That Change Research Outcomes

"Polypeptide carriers are not passive vehicles, their sequence, charge, and structure actively program the biological outcome at every step from membrane contact to cytosolic release."

Conclusion

Polypeptide research in 2026 is defined by precision: precise sequence design, precise delivery engineering, and precise measurement of mechanism-specific outcomes. Researchers who understand the five-step cellular mechanism, binding, uptake, endosomal escape, cytosolic release, and biological response, are positioned to design experiments that generate meaningful, reproducible data rather than ambiguous results caused by formulation failures.

Actionable next steps for researchers:

  1. Map the specific mechanism step your compound is intended to target before selecting a formulation strategy.
  2. Match chain length and secondary structure requirements to delivery format, not every peptide suits every route of administration.
  3. Evaluate stimuli-responsive carrier designs when working in tumor, gut, or CNS microenvironments where selectivity is critical.
  4. Consult half-life data early; small structural modifications can shift pharmacokinetics significantly and alter experimental windows.
  5. Source compounds from verified suppliers with documented purity data to ensure that observed biological effects reflect the peptide's mechanism, not contaminant activity.

With approximately 300 peptide drug projects in clinical stages and more than 80 in Phase III or pre-registration, the mechanistic foundations covered here are no longer theoretical, they are the operating language of modern peptide science.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/understanding-polypeptide-peptides-mechanism-of-action-in-research-applications.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-20 13:04:542026-08-20 13:04:54Understanding Polypeptide Peptides: Mechanism of Action in Research Applications
CJC-1295 With DAC Half-Life and Dosing Frequency: Why Formulation Matters in GH Research

CJC-1295 With DAC Half-Life and Dosing Frequency: Why Formulation Matters in GH Research

August 19, 2026/0 Comments/in Uncategorized/by

A single chemical modification, the addition of a Drug Affinity Complex tail, extends a peptide's active window from roughly 30 minutes to approximately eight days. That gap is not a minor pharmacokinetic footnote; it fundamentally changes how growth hormone research is designed, how dosing schedules are structured, and what biological outcomes investigators can realistically expect. Understanding CJC-1295 With DAC Half-Life and Dosing Frequency: Why Formulation Matters in GH Research is therefore not optional background reading, it is the starting point for any rigorous GH study protocol in 2026.

Key Takeaways

  • CJC-1295 with DAC achieves an estimated half-life of 6-8 days through albumin binding, enabling once- or twice-weekly dosing in research settings.
  • The DAC modification is the sole structural reason for the extended half-life; removing it collapses the active window to roughly 30 minutes.
  • Sustained GH elevation ("GH bleed") differs meaningfully from physiologic pulsatile release, a distinction that shapes research endpoint selection.
  • Formulation choice, with or without DAC, is a primary design variable, not a secondary procurement decision.
  • Nomenclature errors and mislabeling remain a documented problem in the 2026 peptide supply chain, making third-party verification essential.

The DAC Mechanism: How One Modification Changes Everything

The DAC Mechanism: How One Modification Changes Everything

CJC-1295 is a synthetic analogue of growth hormone-releasing hormone (GHRH). In its base form, commonly called CJC-1295 without DAC or Modified GRF 1-29, the peptide stimulates the pituitary to release GH in a sharp, short burst before enzymatic degradation clears it from circulation. For a deeper look at how that shorter-acting version behaves, the article on CJC-1295 without DAC and why half-life matters in growth hormone research provides a useful parallel reference.

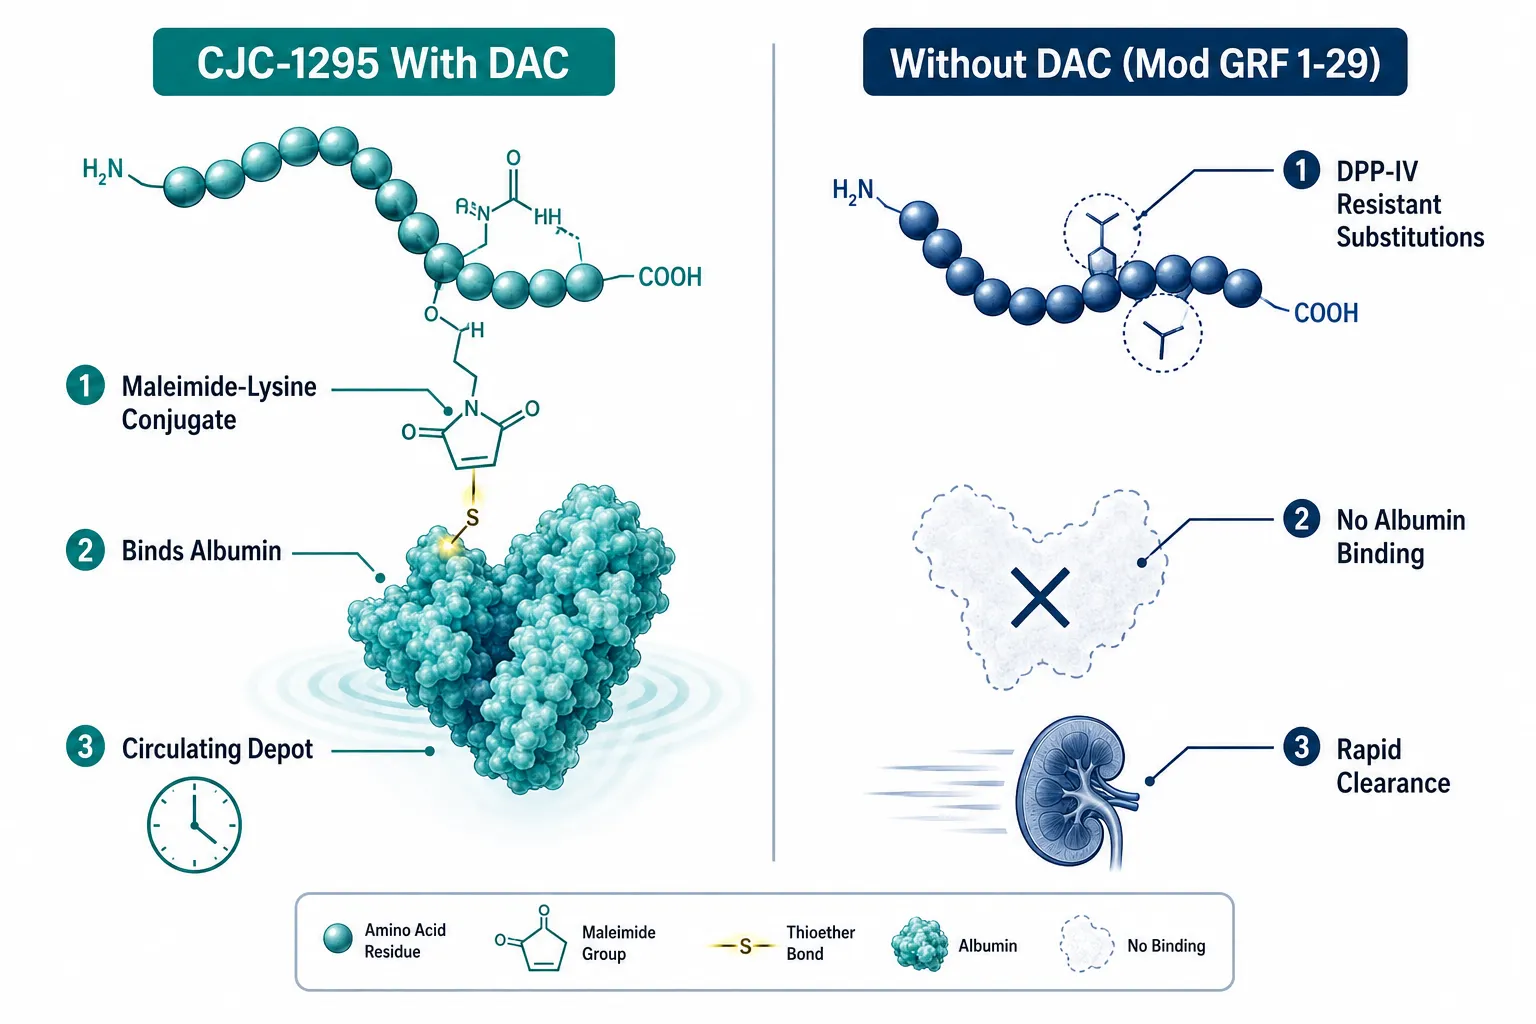
The DAC version adds a maleimidoproprionic acid-lysine linker, the Drug Affinity Complex, to the C-terminus of the peptide. This reactive group forms a covalent bond with cysteine-34 on circulating serum albumin. Because albumin has a natural half-life of roughly 19 days and is protected from renal filtration by its molecular weight, any peptide hitching a ride on albumin inherits a dramatically extended residence time.

The result: CJC-1295 with DAC achieves a documented half-life of approximately 6-8 days in preclinical and early human pharmacokinetic studies, compared to the 30-minute window of the no-DAC formulation. This is not a marginal improvement, it represents a roughly 300-fold increase in active exposure per dose.

"The DAC tail converts a transient GHRH mimetic into a sustained-release depot, fundamentally altering the pharmacodynamic profile and the entire research design logic that follows."

Dosing Frequency Implications: Once-Weekly vs. Twice-Weekly Patterns

Dosing Frequency Implications: Once-Weekly vs. Twice-Weekly Patterns

The extended half-life of CJC-1295 with DAC directly determines practical dosing intervals in research settings. Because plasma concentrations remain therapeutically relevant for approximately 7 days after a single administration, once-weekly dosing is the most commonly reported schedule in published research protocols. Some investigators use a twice-weekly schedule during initial loading phases to accelerate steady-state accumulation, then reduce to weekly maintenance.

Typical research dosing patterns observed in the literature:

Schedule Rationale Common Research Context
Once weekly Matches approximate half-life Steady-state GH/IGF-1 elevation studies
Twice weekly Faster steady-state accumulation Short-duration loading protocols
Every 10-14 days Conservative washout buffer Safety or tolerability assessments

This contrasts sharply with the no-DAC formulation, which requires daily or even multiple-daily administrations to maintain meaningful GH stimulation. Researchers exploring hormone research protocols should treat this dosing gap as a core variable when comparing outcomes across studies that used different formulations.

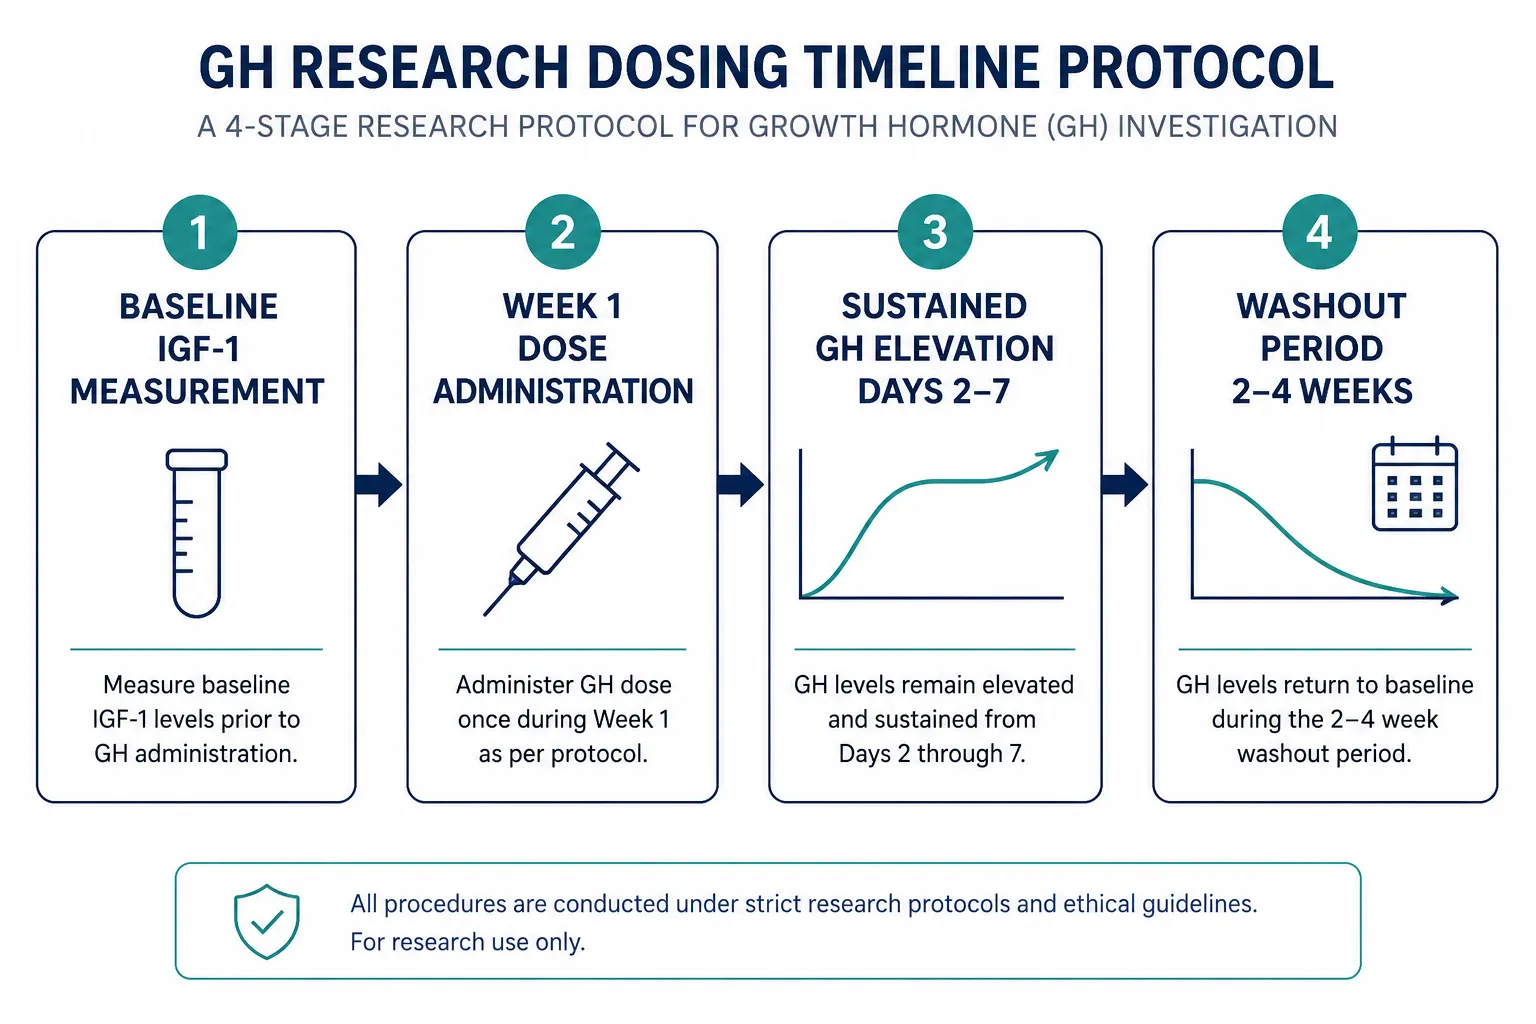
Washout and clearance also follow the extended half-life logic. Near-complete clearance of CJC-1295 with DAC requires approximately 2-4 weeks after the last dose, a window that must be factored into crossover study designs and endpoint timing.

GH Bleed vs. Physiologic Pulses: A Critical Research Design Distinction

GH Bleed vs. Physiologic Pulses: A Critical Research Design Distinction

One of the most actively debated topics in 2026 GH research circles is the difference between the "GH bleed" pattern produced by CJC-1295 with DAC and the pulsatile GH release that characterizes normal physiology.

Natural GH secretion occurs in discrete pulses, primarily during slow-wave sleep, with trough levels near zero between peaks. CJC-1295 with DAC, by contrast, produces a sustained, relatively flat elevation of GH and downstream IGF-1 over days. This pattern has both advantages and limitations depending on research objectives:

Advantages of sustained GH elevation in research:

  • Consistent IGF-1 elevation allows cleaner dose-response measurements
  • Reduced intra-subject variability in GH readings
  • Simpler blood sampling schedules

Limitations and considerations:

  • Does not replicate the physiologic pulsatile pattern
  • Prolonged GH exposure may confound endpoints sensitive to GH pulse amplitude
  • Longer washout periods complicate crossover designs

Researchers studying metabolic outcomes or body composition changes may find the sustained profile advantageous. Those focused on neuroendocrine signaling or sleep architecture may prefer the pulsatile dynamics of the no-DAC version or combination approaches. Blend formulations that combine multiple peptides, such as those explored in Tesamorelin/CJC-1295/Ipamorelin 12mg blend research, add further complexity by layering GHRP activity onto the GHRH backbone.

For broader context on growth hormone research design principles, the sustained vs. pulsatile distinction is increasingly recognized as a primary variable rather than a secondary consideration.

Formulation Integrity and Nomenclature Challenges in 2026

The phrase "CJC-1295 With DAC Half-Life and Dosing Frequency: Why Formulation Matters in GH Research" carries a practical warning embedded in its title: formulation identity must be verified, not assumed. A 2026 market analysis of peptide supply chains identified persistent mislabeling between CJC-1295 with DAC and Modified GRF 1-29 (no DAC). Because the two compounds look identical in lyophilized powder form and share similar molecular weights, visual inspection cannot distinguish them.

Verification best practices for research procurement:

  • Require certificate of analysis (CoA) from an independent third-party laboratory
  • Confirm mass spectrometry data matches the expected molecular weight for the DAC-conjugated form
  • Cross-reference HPLC purity data against published reference standards
  • Source from suppliers with documented quality control processes

This is not a theoretical concern. A researcher who believes they are administering a once-weekly sustained-release compound but is actually using the no-DAC version will see dramatically different GH kinetics, potentially invalidating the study's conclusions. Similar quality-verification principles apply across the broader peptide research space, as discussed in resources like the BPC-157 core peptides documentation first research guide and MOTS-C peptide and mitochondrial biogenesis research.

Researchers working with multi-peptide stacks that include Sermorelin or Ipamorelin alongside CJC-1295 should also consult formulation-specific documentation, such as the Sermorelin/Ipamorelin/CJC-1295 combination reference.

Conclusion

The pharmacokinetic profile of CJC-1295 with DAC is not a background detail, it is the central design parameter around which every other element of a GH research protocol should be built. The 6-8 day half-life, driven by albumin binding through the DAC modification, enables once-weekly dosing, produces sustained IGF-1 elevation, and requires a 2-4 week washout window. Each of these characteristics creates both opportunities and constraints that differ fundamentally from the no-DAC formulation.

Actionable next steps for researchers in 2026:

  1. Clarify the research objective first. If pulsatile GH dynamics are relevant to the endpoint, the no-DAC formulation may be more appropriate. If sustained IGF-1 elevation is the goal, the DAC version offers a cleaner signal.
  2. Verify formulation identity independently. Do not rely on labeling alone; require third-party mass spectrometry and HPLC data before initiating a protocol.
  3. Design washout periods around the actual half-life. A minimum of 2-4 weeks is necessary for near-complete clearance, and crossover designs must account for this window explicitly.
  4. Document the formulation used in all published outputs. Ambiguous nomenclature in the literature contributes to reproducibility failures; specifying "with DAC" or "without DAC" in every reference prevents downstream confusion.

Formulation choice is a research lever. Using it deliberately, with a clear understanding of the pharmacokinetics involved, is what separates rigorous GH research from inconclusive data.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/cjc-1295-with-dac-half-life-and-dosing-frequency-why-formulation-matters-in-gh-r.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-19 13:03:462026-08-19 13:03:46CJC-1295 With DAC Half-Life and Dosing Frequency: Why Formulation Matters in GH Research
CJC-1295 With DAC vs Without DAC: Mechanism, Duration, and Research Design Differences

CJC-1295 With DAC vs Without DAC: Mechanism, Duration, and Research Design Differences

August 14, 2026/0 Comments/in Uncategorized/by

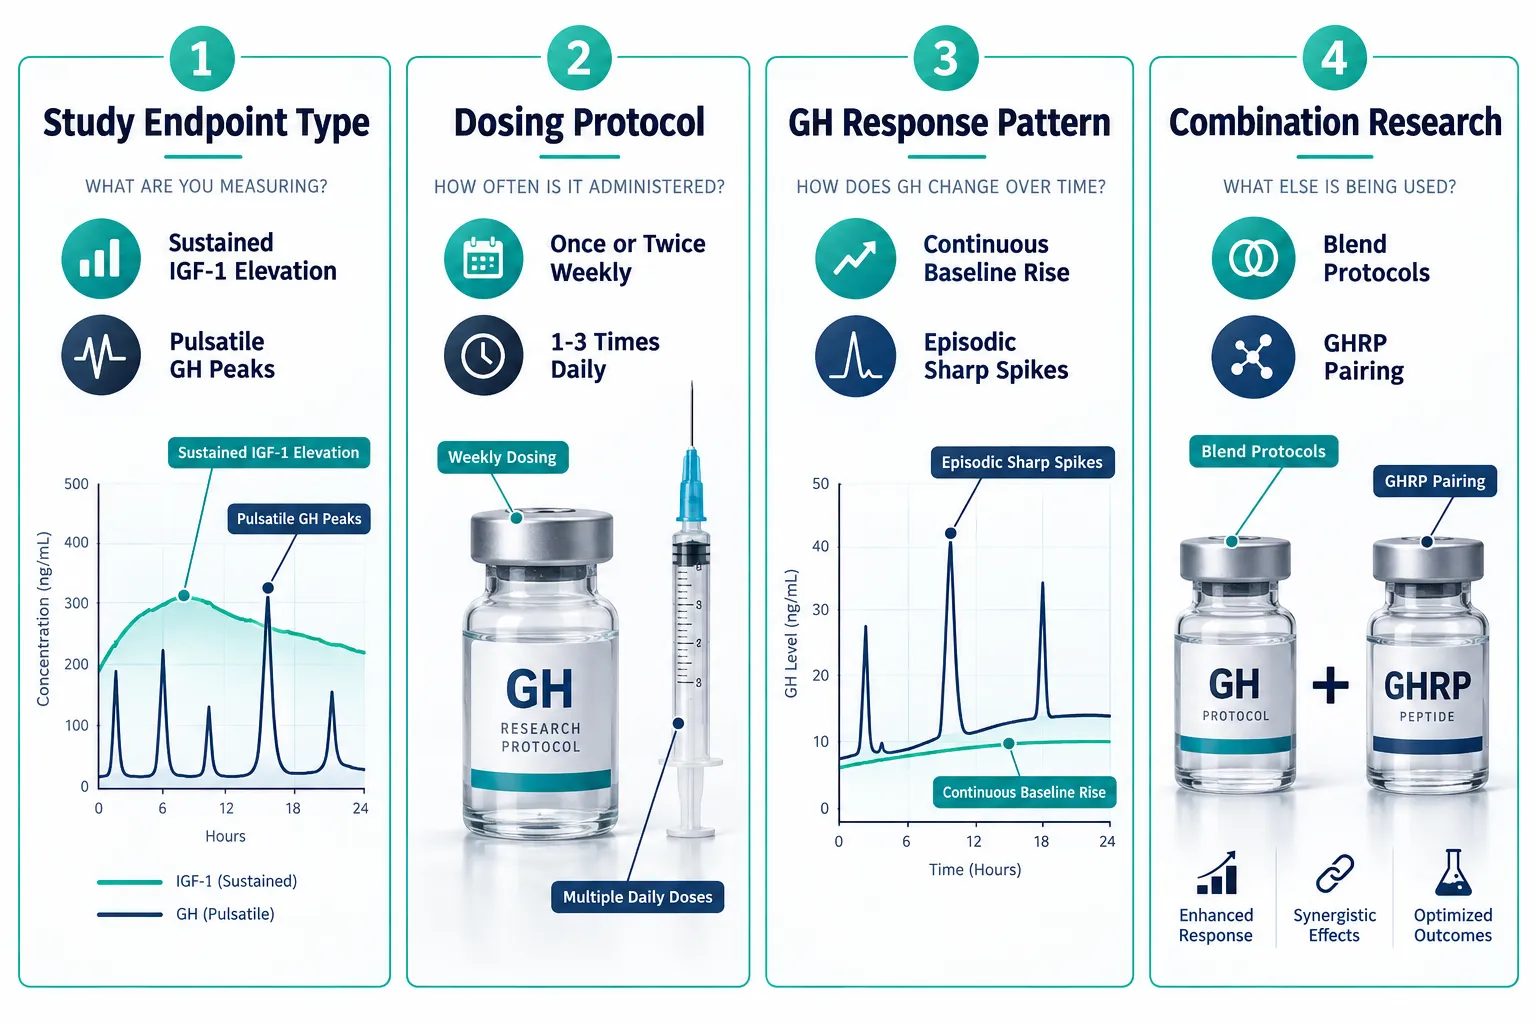
A single molecular attachment, a drug affinity complex, or DAC, separates two peptides that share a name but behave in fundamentally different ways inside a biological system. Understanding the CJC-1295 with DAC vs without DAC mechanism, duration, and research design differences is not a matter of splitting hairs; it determines whether a study captures sustained growth hormone (GH) elevation or episodic GH pulses, and whether dosing happens once a week or three times a day.

Key Takeaways

  • CJC-1295 with DAC covalently binds serum albumin via a maleimide-lysine conjugate, creating a circulating depot with a half-life of 5.8 to 8.1 days.
  • CJC-1295 without DAC, more accurately called Modified GRF 1-29, resists DPP-IV degradation but clears within 30 to 120 minutes, producing short GH pulses.
  • With DAC produces sustained GH and IGF-1 elevation; without DAC mimics physiologic pulsatile secretion.
  • Dosing frequency differs dramatically: once or twice weekly for the DAC form versus one to three times daily for the no-DAC form.
  • Research design must align with the pharmacokinetic profile of whichever form is selected; the two are not interchangeable in study protocols.

The Core Structural Difference: Albumin Binding vs DPP-IV Resistance

The Core Structural Difference: Albumin Binding vs DPP-IV Resistance

The CJC-1295 with DAC vs without DAC distinction begins at the molecular level. CJC-1295 with DAC incorporates a lysine-linked maleimidopropionic acid group at position 30. This chemical handle covalently attaches to serum albumin once the peptide enters circulation. Albumin is the most abundant plasma protein in the body, and by hitching to it, the peptide essentially becomes part of a large, slowly cleared macromolecule. The result is a circulating depot that releases active peptide gradually over days rather than hours.

CJC-1295 without DAC, the compound more precisely termed Modified GRF 1-29, takes a different approach to stability. It uses four strategic amino acid substitutions to resist cleavage by dipeptidyl peptidase-IV (DPP-IV), the enzyme that rapidly degrades native growth hormone-releasing hormone (GHRH). There is no albumin-binding group. The peptide remains free in plasma, acts quickly at the pituitary, and clears within 30 to 120 minutes.

In plain terms:

  • With DAC = albumin-bound, extended-release GHRH analog
  • Without DAC = short-acting, DPP-IV-resistant GHRH analog

This structural difference is the single most important concept when evaluating research that involves either compound. For a broader look at how peptide structure governs function, the overview of polypeptide peptides explained: structure, function, and research applications provides useful context.

Half-Life and Duration: Minutes vs Days

Half-Life and Duration: Minutes vs Days

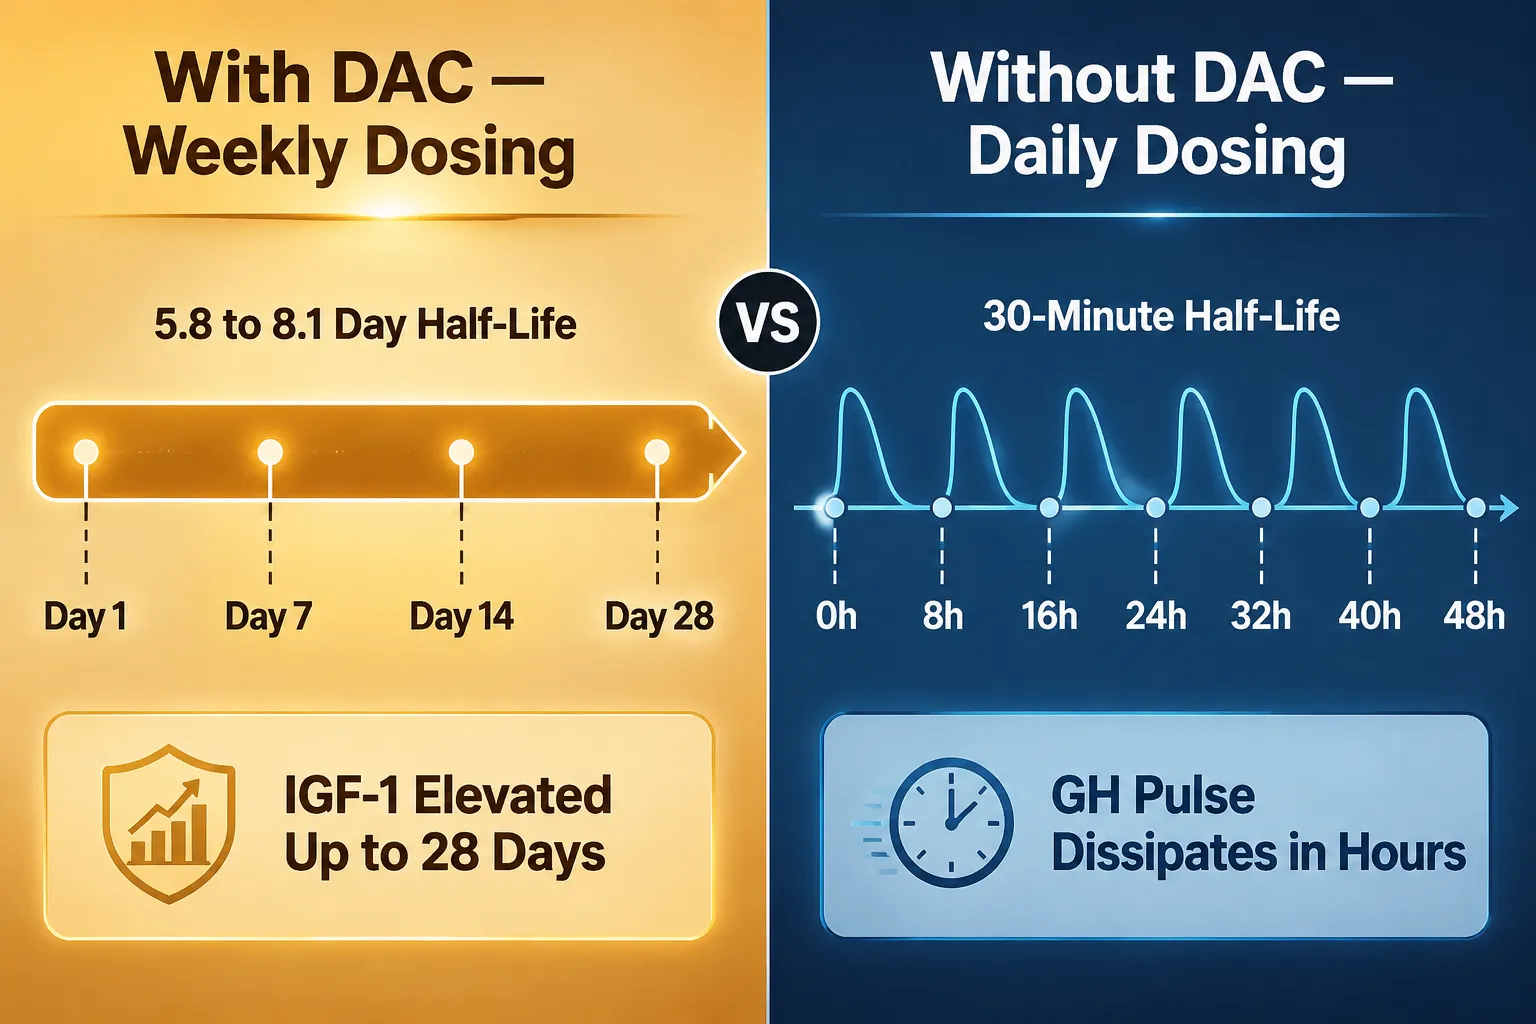
The pharmacokinetic gap between these two forms is striking. Phase 2 data on CJC-1295 with DAC in approximately 65 adults established a half-life of 5.8 to 8.1 days. After multiple doses, IGF-1 levels remained elevated above baseline for up to 28 days. Mean plasma GH showed two- to tenfold increases persisting for six days or more after a single injection. This is not a transient spike, it is a prolonged hormonal shift.

CJC-1295 without DAC tells a very different story. Its half-life sits around 30 minutes, occasionally extended to 30 to 120 minutes depending on the measurement methodology. GH pulses rise sharply after injection and return toward baseline within hours, leaving no lasting depot activity.

Key insight: The DAC form produces a “continuous GH/IGF-1 elevation” pattern. The no-DAC form produces “episodic GH pulses.” Neither pattern is inherently superior, the right choice depends entirely on the research question.

Dosing frequency follows directly from half-life:

Form Half-Life Typical Research Dosing
CJC-1295 with DAC 5.8 to 8.1 days Once or twice weekly
CJC-1295 without DAC (Mod GRF 1-29) 30 to 120 minutes 1 to 3 times daily

Researchers studying combination protocols, for example, pairing a GHRH analog with a ghrelin mimetic, should review how these compounds are combined in products like the CJC-1295 IPA 10mg formulation, or in multi-compound blends such as the Tesamorelin AOD9604 CJC1295 Ipamorelin 12mg protocol. For a broader comparison of GHRH-axis peptides, the article on Tesamorelin and Ipamorelin peptides: mechanism, synergy, and growth hormone research design is also worth consulting.

Research Design Implications of CJC-1295 With DAC vs Without DAC

Research Design Implications of CJC-1295 With DAC vs Without DAC

Selecting between these two forms is a research design decision, not simply a dosing preference. The CJC-1295 with DAC vs without DAC mechanism, duration, and research design differences translate directly into how endpoints are measured, how frequently samples are collected, and what kind of GH-axis activity the study is actually designed to observe.

When studying sustained IGF-1 elevation:
The with-DAC form is appropriate. Its long half-life means fewer injections, simpler dosing schedules, and a more stable hormonal environment during the observation window. Researchers can track IGF-1 over days or weeks without daily interventions.

When studying pulsatile GH dynamics:
The no-DAC form is the better fit. Its short action window allows researchers to time injections precisely and observe discrete GH pulses. This is useful when the research question involves mimicking natural secretion patterns or assessing acute pituitary responsiveness.

Additional design considerations:

  • Washout periods differ substantially. The DAC form may require weeks of washout; the no-DAC form clears within hours.
  • Combination protocols involving a GHRP (such as Ipamorelin) are common with the no-DAC form, since both compounds share a short-acting, pulse-oriented profile. Researchers can explore Sermorelin Ipamorelin CJC1295 combination designs for reference.
  • Endpoint timing must account for the GH response curve. Sampling 24 hours post-injection is meaningful for the DAC form but largely irrelevant for the no-DAC form.
  • Blinding and control arms are easier to manage with the weekly-dosed DAC form in longer studies, since compliance and administration frequency are reduced.

For researchers interested in how metabolic peptides fit into broader study frameworks, the top 5 research peptides for metabolic health: an updated buyer's guide offers comparative context across multiple compound classes.

Conclusion

The CJC-1295 with DAC vs without DAC mechanism, duration, and research design differences are not trivial. They represent two distinct pharmacological tools built on the same GHRH backbone but optimized for entirely different applications. The DAC form, with its albumin-binding mechanism and multi-day half-life, is suited to studies targeting sustained GH and IGF-1 elevation. The no-DAC form, with its rapid clearance and pulsatile GH output, fits studies that require episodic, physiologically patterned hormone responses.

Actionable next steps for researchers:

  1. Define the primary endpoint first, sustained IGF-1 elevation or pulsatile GH dynamics, before selecting a form.
  2. Build washout periods and sampling schedules around the specific half-life of the chosen compound.
  3. Review existing combination protocols (GHRH plus GHRP) to determine whether the dosing frequencies of all compounds in the design are compatible.
  4. Source compounds with verified purity and documentation, since structural integrity is essential when the entire mechanistic distinction rests on a single molecular group.

Matching the compound to the research question is the foundation of valid, reproducible GH-axis research in 2026.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/cjc-1295-with-dac-vs-without-dac-mechanism-duration-and-research-design-differen.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-14 13:06:412026-08-14 13:06:41CJC-1295 With DAC vs Without DAC: Mechanism, Duration, and Research Design Differences
CJC-1295 with Ipamorelin: What the Combination Means for Growth Hormone Research Models

CJC-1295 with Ipamorelin: What the Combination Means for Growth Hormone Research Models

August 9, 2026/0 Comments/in Uncategorized/by

Growth hormone secretion is not a steady stream, it is a series of discrete pulses, and the architecture of those pulses determines downstream IGF-1 output, receptor sensitivity, and metabolic signaling. Understanding that architecture is exactly why researchers studying CJC-1295 with Ipamorelin: What the Combination Means for Growth Hormone Research Models have moved away from single-agent designs toward dual-pathway protocols. The two peptides act on different receptors, and that difference is the entire point.

Isometric scientific illustration in bright, teal and orange color accents, flat-vector infographic style, educational

Key Takeaways

  • CJC-1295 is a GHRH analog that extends GH-releasing hormone signaling; Ipamorelin is a selective ghrelin receptor agonist, they stimulate GH through distinct mechanisms.
  • Combining both compounds targets two independent receptor pathways simultaneously, producing additive or potentially synergistic GH pulse amplification in preclinical models.
  • The combination preserves pulsatile GH secretion rather than creating a flat, supraphysiological hormone profile, which matters for study design validity.
  • IGF-1 elevation in research models follows GH pulse amplitude and duration, making the dual-protocol a useful tool for studying downstream anabolic and metabolic signaling.
  • Researchers must account for somatostatin tone, dosing interval, and model-specific variables when designing protocols around this combination.

Why Two Receptors Are Better Than One in GH Research

The hypothalamic-pituitary axis regulates GH through two primary stimulatory inputs: growth hormone-releasing hormone (GHRH) and ghrelin. These inputs converge on the pituitary somatotroph but bind to entirely separate receptors, the GHRH receptor and the growth hormone secretagogue receptor (GHS-R1a), respectively.

CJC-1295 is a synthetic GHRH analog. Its key structural feature is a drug affinity complex (DAC) modification that allows it to bind albumin in circulation, dramatically extending its half-life compared to native GHRH. In early human studies, single injections produced dose-dependent increases in mean GH concentrations and IGF-1 levels that persisted for several days. That sustained elevation distinguishes it from shorter-acting GHRH peptides like Sermorelin, a distinction worth noting when reviewing IPA Sermorelin stack research alongside CJC-1295 data.

Ipamorelin, by contrast, is a pentapeptide GH secretagogue. It activates GHS-R1a, the same receptor targeted by ghrelin, but with a notably selective profile. Unlike older secretagogues such as GHRP-6, Ipamorelin produces minimal cortisol or prolactin release at research-relevant doses, making it a cleaner signal in experimental models. Its GH pulses are sharp and short-lived, which is mechanistically opposite to CJC-1295's prolonged baseline elevation.

"The combination does not simply add two GH signals together, it modulates the pituitary from two independent angles, which changes the shape, amplitude, and downstream consequences of each pulse."

This receptor-level distinction is the conceptual foundation for understanding CJC-1295 with Ipamorelin: what the combination means for growth hormone research models at a mechanistic level.

GH Pulsatility, IGF-1 Signaling, and What the Combination Changes

GH Pulsatility, IGF-1 Signaling, and What the Combination Changes

Physiological GH secretion is pulsatile. The liver and peripheral tissues respond differently to pulsatile versus continuous GH exposure, a fact with direct implications for IGF-1 production, receptor downregulation, and metabolic outcomes in research models.

When CJC-1295 alone is administered, it raises the trough GH level and sustains a higher baseline. Ipamorelin alone produces discrete, clean GH spikes. Together, the two compounds are thought to:

  • Raise the baseline GH environment (CJC-1295 effect)
  • Amplify individual pulses on top of that elevated baseline (Ipamorelin effect)
  • Preserve pulsatility rather than creating a flat supraphysiological curve

This matters for IGF-1 research. IGF-1 synthesis in the liver is sensitive to both GH pulse amplitude and cumulative exposure. A protocol that maintains pulsatility while elevating pulse height may produce more physiologically representative IGF-1 responses than continuous GH infusion models. Researchers exploring metabolic signaling themes will find this relevant alongside IPA muscle and fat research themes that examine body composition endpoints downstream of GH axis activation.

For researchers also working with Tesamorelin, another GHRH analog with an established clinical evidence base, multi-peptide blend formats have become a practical consideration. Resources covering Tesamorelin, CJC-1295, and Ipamorelin 12mg blend dosing and Tesamorelin, CJC-1295, and Ipamorelin 12mg blend reconstitution offer protocol-relevant context for multi-agent GH secretagogue studies.

Somatostatin tone is a critical confounding variable. Somatostatin inhibits GH release, and its rhythmic activity shapes natural pulse timing. Neither CJC-1295 nor Ipamorelin directly suppresses somatostatin, which means the combination works within, rather than overriding, the existing inhibitory architecture. Researchers should time dosing to coincide with periods of lower somatostatin tone (typically overnight in rodent models) to maximize signal clarity.

Study Design Considerations for the Dual-Protocol Model

Study Design Considerations for the Dual-Protocol Model

Translating the mechanistic rationale into a well-controlled study requires deliberate design choices. Several variables consistently affect outcomes in CJC-1295 with Ipamorelin research models:

Variable Research Consideration
Dosing interval CJC-1295 DAC variant allows less frequent dosing; Ipamorelin requires more frequent administration for pulse induction
Species differences Rodent GH pulse frequency differs significantly from human patterns
IGF-1 sampling timing Peak IGF-1 elevation lags GH pulse by hours; sampling windows must account for this
Endpoint selection Distinguish between GH pulse metrics, IGF-1 AUC, and downstream anabolic markers

Researchers working on broader peptide axis questions, including those examining Tesamorelin science and sourcing or Tesamorelin, AOD9604, CJC-1295, and Ipamorelin blend dosage protocols, will recognize that multi-peptide designs require particularly careful endpoint hierarchies to isolate which compound is driving which effect.

It is also worth noting the evidence gap: robust, controlled human trial data specifically on the CJC-1295 and Ipamorelin combination remains limited. Most of the mechanistic rationale is extrapolated from individual compound studies and preclinical data. This is not a reason to dismiss the combination as a research model, it is a reason to design studies that generate the controlled data currently missing from the literature.

Conclusion

The rationale for pairing CJC-1295 with Ipamorelin in growth hormone research models is mechanistically coherent: two distinct receptor pathways, complementary pharmacokinetics, and a combined effect that preserves pulsatility while amplifying GH output. For researchers, the actionable next steps are clear. First, define whether the primary endpoint is GH pulse architecture, IGF-1 elevation, or downstream metabolic or anabolic signaling, each requires a different sampling and analysis strategy. Second, account for somatostatin rhythm in dosing timing. Third, treat the combination as a dual-variable design and include single-agent control arms where possible to isolate each compound's contribution. The combination is a powerful research tool precisely because it mirrors the complexity of endogenous GH regulation, and that complexity demands equally rigorous protocol thinking.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/cjc-1295-with-ipamorelin-what-the-combination-means-for-growth-hormone-research.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-09 13:05:112026-08-09 13:05:11CJC-1295 with Ipamorelin: What the Combination Means for Growth Hormone Research Models
CJC-1295 With and Without DAC: A Detailed Mechanism and Pharmacokinetic Comparison for Growth Hormone Research

CJC-1295 With and Without DAC: A Detailed Mechanism and Pharmacokinetic Comparison for Growth Hormone Research

August 3, 2026/0 Comments/in Uncategorized/by

The difference between a peptide that clears the bloodstream in under two hours and one that persists for more than a week comes down to a single molecular modification, the Drug Affinity Complex, or DAC. That distinction sits at the heart of CJC-1295 with and without DAC: a detailed mechanism and pharmacokinetic comparison for growth hormone research, and it has significant implications for how researchers design experiments, interpret data, and select appropriate compounds.

Key Takeaways

  • CJC-1295 with DAC binds to serum albumin, extending its half-life to approximately 6-8 days, while the no-DAC variant (Modified GRF 1-29) has a half-life of roughly 30 minutes.
  • The DAC modification creates a continuous, blunted GH release pattern; the no-DAC form produces sharp, pulsatile GH spikes that more closely mimic natural secretion.
  • Pulsatile dosing with Modified GRF 1-29 is commonly paired with a GHRP such as Ipamorelin to amplify GH pulse magnitude.
  • Receptor desensitization is a key concern with the long-acting DAC form; pulse-based protocols may reduce this risk.
  • Experimental design must account for these pharmacokinetic differences when measuring GH or IGF-1 endpoints.

Key Takeaways

Understanding the DAC Modification at the Receptor Level

CJC-1295 is a synthetic analogue of growth hormone-releasing hormone (GHRH), engineered to stimulate the GHRH receptor (GHRHR) on somatotroph cells in the anterior pituitary. Both the DAC and no-DAC variants bind the same receptor, but their pharmacokinetic profiles diverge sharply because of one structural addition.

The DAC moiety is a maleimidopropionic acid group attached to the peptide's lysine residue. Once injected, this reactive group forms a covalent bond with the cysteine-34 residue on circulating serum albumin. Because albumin has a natural half-life of roughly 19 days and is protected from renal filtration by its size, the CJC-1295/albumin complex becomes a slow-release depot.

The result:

  • CJC-1295 with DAC, half-life of approximately 6-8 days; single injection sustains elevated GH secretion for up to two weeks in preclinical models.
  • CJC-1295 without DAC (Modified GRF 1-29), half-life of approximately 30 minutes; rapid enzymatic degradation by dipeptidyl peptidase IV (DPP-IV) limits its activity window.

The no-DAC form retains four amino acid substitutions that improve DPP-IV resistance compared to native GHRH(1-29), but it still clears quickly. This makes it functionally a short-acting, pulsatile secretagogue, whereas the DAC version operates more like a sustained-release depot.

"The albumin-anchoring mechanism of DAC does not change receptor affinity, it changes residence time. The receptor sees the same signal; the body sees it for far longer."

Pharmacokinetic Comparison: Half-Life, GH Pulse Architecture, and Desensitization Risk

Pharmacokinetic Comparison: Half-Life, GH Pulse Architecture, and Desensitization Risk

The pharmacokinetic divergence between the two forms directly shapes the GH secretion pattern observed in research subjects.

GH Release Profiles

Parameter CJC-1295 with DAC CJC-1295 without DAC (Mod GRF 1-29)
Half-life ~6-8 days ~30 minutes
GH release pattern Sustained, blunted elevation Sharp, pulsatile spikes
Dosing frequency Once or twice weekly Per-pulse (multiple times daily)
IGF-1 elevation Gradual, prolonged Transient, context-dependent

Receptor Desensitization

Continuous GHRHR stimulation from the DAC form raises a legitimate concern: receptor downregulation. Prolonged agonist exposure can reduce receptor density on somatotrophs, potentially blunting GH output over extended research periods. The pulsatile pattern of Modified GRF 1-29 more closely mirrors endogenous GHRH secretion, which occurs in discrete bursts, and may carry a lower desensitization risk when protocols include adequate inter-dose intervals.

Enzymatic Stability

Both variants include substitutions at positions 2 and 8 to resist DPP-IV cleavage. However, the DAC form's albumin binding provides an additional layer of protection simply by shielding the peptide from enzymatic access, a pharmacokinetic advantage that extends far beyond the amino acid modifications alone.

Experimental Design Considerations: CJC-1295 With and Without DAC in Growth Hormone Research

Experimental Design Considerations: CJC-1295 With and Without DAC in Growth Hormone Research

Selecting between these two forms is not merely a pharmacokinetic preference, it fundamentally shapes what a research protocol can and cannot measure. A thorough understanding of CJC-1295 with and without DAC: a detailed mechanism and pharmacokinetic comparison for growth hormone research is essential before any experimental design is finalized.

When the DAC Form May Be Appropriate

  • Studies requiring stable, elevated IGF-1 levels over days without frequent dosing
  • Long-duration models where consistent GH axis stimulation is the independent variable
  • Protocols where injection frequency must be minimized

When Modified GRF 1-29 (No-DAC) Is Preferred

  • Research modeling physiological GH pulsatility
  • Studies examining acute GH secretion dynamics or GH pulse amplitude
  • Combination protocols with a GHRP such as Ipamorelin, where synergistic pulse amplification is the target

Stacking with Ipamorelin

The most widely studied combination in growth hormone research pairs Modified GRF 1-29 with a ghrelin mimetic. Researchers interested in this approach can review CJC-1295 and Ipamorelin dosage protocols for detailed experimental parameters, or explore the Sermorelin, Ipamorelin, and CJC-1295 combination framework for broader GHRH-stack context.

When Ipamorelin acts on the ghrelin receptor (GHS-R1a) simultaneously with Mod GRF 1-29 acting on GHRHR, the two signals converge on somatotrophs through separate intracellular pathways (cAMP and IP3/PKC, respectively), producing a synergistic GH pulse larger than either compound alone. For researchers comparing related secretagogues, the Ipamorelin vs. Tesamorelin analysis provides useful receptor-level context.

Researchers working with blended formulations can also reference the Tesamorelin, CJC-1295, and Ipamorelin 12mg blend as a reference point for multi-peptide GH axis research designs, or consult the Sermorelin, Ipamorelin, and CJC-1295 dosage guide for structured dosing frameworks.

For researchers also exploring peptides outside the GH axis, the GHK-Cu peptide sourcing and research guide offers a parallel reference for compound quality standards.

Measuring Outcomes

  • With DAC protocols: Measure IGF-1 at baseline and at steady-state (typically day 7-14). Single-point GH measurements are less informative given the blunted pulse architecture.
  • No-DAC protocols: Time GH sampling to the expected pulse window (typically 15-45 minutes post-administration). IGF-1 measurements should be taken at 24-hour intervals to capture cumulative secretion effects.

Conclusion

The choice between CJC-1295 with DAC and its no-DAC counterpart is a mechanistic decision, not simply a convenience preference. The DAC modification transforms a short-acting GHRH analogue into an albumin-anchored depot with a multi-day half-life, producing sustained but blunted GH elevation and a meaningful desensitization risk over time. Modified GRF 1-29 preserves pulsatile GH dynamics, integrates cleanly with GHRP co-administration, and offers more granular experimental control over GH secretion timing.

Actionable next steps for researchers:

  1. Define the GH secretion pattern required by the study endpoint before selecting a form.
  2. For pulse-based designs, establish co-administration timing with a GHRP and confirm sampling windows align with expected GH peaks.
  3. For DAC-based designs, include receptor desensitization controls and monitor IGF-1 at multiple time points.
  4. Verify peptide purity and sequence confirmation from the source before initiating any protocol.
  5. Cross-reference related GHRH analogue data, including Tesamorelin and Sermorelin comparisons, to contextualize findings within the broader GH secretagogue literature.
https://www.puretestedpeptides.com/wp-content/uploads/2026/08/cjc-1295-with-and-without-dac-a-detailed-mechanism-and-pharmacokinetic-compariso.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-03 13:03:562026-08-03 13:03:56CJC-1295 With and Without DAC: A Detailed Mechanism and Pharmacokinetic Comparison for Growth Hormone Research

Tag Archive for: growth hormone research

Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols

Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols

July 24, 2026/0 Comments/by Pure Tested

Growth hormone secretion declines by roughly 14% per decade after age 30, a physiological reality that has driven sustained scientific interest in peptide-based GH secretagogues. Among the most studied pairing in preclinical and translational research is the Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols framework, which exploits two distinct receptor pathways to amplify pulsatile GH output in ways that neither compound achieves alone.

Isometric scientific illustration in bright daylight palette showing two distinct molecular pathway diagrams side by side —

Key Takeaways

  • Tesamorelin acts as a GHRH analog; ipamorelin acts as a ghrelin receptor agonist, together they engage complementary pathways.
  • Dual-pathway stimulation produces additive or potentially synergistic GH pulses compared to single-agent protocols.
  • Tesamorelin holds FDA-approved status for HIV-associated lipodystrophy; ipamorelin and the combination remain unapproved for any indication.
  • Dosing protocols in research settings are weight-independent, time-sensitive, and typically administered subcutaneously at night.
  • Researchers designing peptide stacks should treat this combination as an investigational model requiring rigorous experimental controls.

Individual Mechanisms: Two Pathways, One Goal

Understanding why the Ipamorelin and Tesamorelin Combination generates research interest begins with their separate mechanisms.

Tesamorelin is a stabilized analog of endogenous growth hormone-releasing hormone (GHRH). It binds GHRH receptors on somatotroph cells in the anterior pituitary, directly stimulating GH synthesis and secretion. Because it mirrors the body's own GHRH signal, the resulting GH pulse follows a physiologically normal pattern. Researchers studying tesa benefits note its well-characterized pharmacokinetic profile and the clinical data supporting its lipid-mobilization effects.

Ipamorelin belongs to a different class entirely. It is a selective ghrelin receptor (GHS-R1a) agonist, a pentapeptide that triggers GH release through the ghrelin pathway without meaningfully elevating cortisol or prolactin. This selectivity is a key research advantage. For a deeper look at how ipamorelin fits within broader GH secretagogue stacks, the CJC-1295 plus Ipamorelin research overview provides useful context.

"Two keys, two locks, one door", the GHRH pathway and the ghrelin pathway converge on the same somatotroph cell, and activating both simultaneously produces a GH pulse that exceeds what either key unlocks alone.

Why Dual-Pathway Activation Matters

The pituitary integrates signals from both GHRH and ghrelin receptors. When both are occupied concurrently:

  • Intracellular cAMP (via GHRH-R) and intracellular calcium (via GHS-R1a) rise together.
  • The two second-messenger cascades have a documented additive interaction at the somatotroph level.
  • The resulting GH pulse is larger and may be more sustained than single-receptor stimulation.

This is the mechanistic foundation for the synergistic GH secretagogue concept that makes the combination worth investigating.

Research Findings on the Ipamorelin and Tesamorelin Combination

Research Findings on the Ipamorelin and Tesamorelin Combination

Preclinical data consistently show that GHRH analogs and ghrelin-pathway agonists produce greater GH output when co-administered than when used separately. Tesamorelin's clinical track record, it is FDA-approved for reducing visceral adiposity in HIV-associated lipodystrophy, provides a validated pharmacological anchor. Ipamorelin's selectivity profile makes it a preferred ghrelin agonist in research designs that require minimal off-target hormonal noise.

Researchers comparing secretagogue classes should also review Tesamorelin vs. Sermorelin to understand how tesa's modified structure confers greater plasma stability than first-generation GHRH analogs.

Key observations from the literature on combined GH secretagogue protocols include:

Parameter Single GHRH Analog Single Ghrelin Agonist Combined Protocol
GH Pulse Amplitude Moderate Moderate Higher (additive/synergistic)
Cortisol Elevation Minimal Minimal Minimal
Prolactin Elevation Minimal Minimal Minimal
IGF-1 Upregulation Moderate Moderate Greater

Important regulatory note: Tesamorelin is FDA-approved only as monotherapy for a specific indication. Ipamorelin carries no regulatory approval. The combination is not approved by any regulatory authority and is appropriate only for controlled research settings.

For researchers exploring multi-peptide formulations, the Tesamorelin, CJC-1295, and Ipamorelin 12mg blend represents a pre-formulated research option that adds a DAC-modified GHRH analog to the stack.

Dosing Protocols for Synergistic GH Secretagogue Research

Dosing Protocols for Synergistic GH Secretagogue Research

Designing a rigorous protocol around the Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols model requires attention to timing, dose selection, and experimental controls.

Timing Principles

GH is secreted in pulses, with the largest pulse occurring shortly after sleep onset. Research protocols typically align administration with this natural rhythm:

  • Preferred window: 30-60 minutes before sleep
  • Administration route: Subcutaneous injection (standard for both peptides)
  • Fasting state: A 2-hour fast before dosing reduces somatostatin tone and improves GH pulse amplitude

Commonly Referenced Research Doses

These figures appear in the preclinical and translational research literature and are provided for scientific reference only:

  • Tesamorelin: 1-2 mg per administration
  • Ipamorelin: 200-300 mcg per administration
  • Frequency: Once daily (evening) or twice daily (morning and evening) depending on study design

Researchers seeking dose-calculation guidance can consult the Tesamorelin dosage calculator for reference modeling.

Protocol Design Considerations

  • Cycling: Most research designs run 8-12 week active phases followed by 4-week washout periods to prevent receptor desensitization.
  • Controls: Include single-agent arms (tesa alone, ipamorelin alone) to quantify the additive contribution.
  • Biomarkers: Track serum IGF-1, fasting GH pulse amplitude, and body composition metrics as primary endpoints.
  • Safety monitoring: Assess fasting glucose and insulin sensitivity at baseline and at 4-week intervals given GH's known effects on glucose metabolism.

For researchers interested in how this combination compares within broader secretagogue stacks, the Sermorelin, Ipamorelin, and CJC-1295 combination overview offers comparative mechanistic context. Additionally, the safety considerations for combining Tesamorelin with CJC and Ipamorelin addresses common protocol safety questions.

Conclusion

The Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols framework offers a mechanistically coherent strategy for amplifying pulsatile GH secretion in research models. By simultaneously engaging the GHRH receptor pathway through tesa and the ghrelin receptor pathway through ipamorelin, researchers can generate GH pulses that exceed single-agent outputs while maintaining a favorable hormonal selectivity profile.

Actionable next steps for researchers:

  1. Review the regulatory landscape, tesa's FDA-approved monotherapy status sets a pharmacological benchmark; the combination remains strictly investigational.
  2. Design protocols with single-agent control arms to isolate the synergistic contribution.
  3. Align dosing with natural GH pulse timing (evening administration, fasted state).
  4. Monitor IGF-1, glucose metabolism, and body composition as primary experimental endpoints.
  5. Plan 8-12 week active cycles with structured washout periods to preserve receptor sensitivity.

Rigorous experimental design, not anecdotal stacking, is what transforms a mechanistically promising combination into reproducible, publishable science.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/ipamorelin-and-tesa-combination-synergistic-gh-secretagogue-research-and.webp 672 1008 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-24 13:09:592026-07-27 13:32:06Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
CJC-1295 with Ipamorelin vs. Tesamorelin: Which GHRH Mimetic Stack is Best for Your Research?

CJC-1295 with Ipamorelin vs. Tesamorelin: Which GHRH Mimetic Stack is Best for Your Research?

July 12, 2026/0 Comments/by Pure Tested

Only one growth hormone peptide has ever cleared FDA approval, and it is not the stack that dominates anti-aging clinics worldwide. That contrast sits at the heart of the CJC-1295 with Ipamorelin vs. Tesamorelin debate, and understanding it can sharpen the focus of any serious growth hormone research program in 2026.

Editorial () split-screen conceptual illustration: left half shows a stylized dual-vial peptide stack labeled 'CJC-1295' and

Key Takeaways

  • CJC-1295 paired with Ipamorelin exploits two distinct pituitary signaling pathways simultaneously, producing a synergistic, pulsatile GH release pattern.
  • Tesamorelin is the only FDA-approved GHRH analog, backed by multiple randomized controlled trials confirming visceral fat reduction.
  • The dual-peptide stack offers more flexible dosing protocols; Tesamorelin follows a fixed, well-validated clinical regimen.
  • Side-effect profiles differ meaningfully: Ipamorelin's selectivity avoids cortisol and prolactin spikes, while Tesamorelin's risks are thoroughly documented from clinical trial data.
  • Choosing between these options depends on the specific research question, dual-pathway GH modulation versus targeted visceral adiposity outcomes.

Mechanisms of Action: How Each Approach Stimulates GH

CJC-1295 is a synthetic GHRH analog that binds GHRH receptors on pituitary somatotroph cells, prompting them to synthesize and release growth hormone. Its standard (non-DAC) form carries a half-life of roughly 30 minutes, closely mimicking the natural GHRH pulse. Researchers interested in CJC-1295 research findings will note that the DAC-modified version extends the half-life dramatically but at the cost of disrupting the pulsatile GH pattern.

Ipamorelin operates through a completely different receptor. Originally developed by Novo Nordisk, it is a selective ghrelin receptor agonist, a Growth Hormone Secretagogue (GHS), with a half-life of approximately two hours. Critically, it does not elevate cortisol or prolactin at research-relevant doses, a selectivity advantage that older GHRPs lack. Explore the Ipamorelin research profile for a deeper look at its receptor pharmacology.

Tesamorelin is a synthetic GHRH analog comprising all 44 amino acids of human GHRH plus a trans-3-hexenoic acid group attached at the N-terminus. This structural modification boosts receptor binding affinity and provides modest resistance to dipeptidyl peptidase-IV (DPP-IV) cleavage. Its half-life ranges from 26 to 38 minutes, similar to native GHRH, yet its clinical performance is meaningfully stronger than unmodified GHRH.

"The synergistic interaction between GHRH-pathway and ghrelin-pathway signaling creates a permissive window that amplifies GH output beyond what either peptide achieves alone."


Synergistic Effects and Research Applications of the CJC-1295 with Ipamorelin vs. Tesamorelin Comparison

Synergistic Effects and Research Applications of the CJC-1295 with Ipamorelin vs. Tesamorelin Comparison

The Dual-Pathway Advantage of the Stack

When CJC-1295 and Ipamorelin are co-administered, they act on two distinct receptor populations on the same somatotroph cell. CJC-1295 activates the GHRH receptor; Ipamorelin activates the ghrelin receptor (GHS-R1a). The result is a synergistic amplification of GH pulse amplitude while preserving the natural pulsatile secretion pattern, a research-relevant feature because pulsatility governs downstream IGF-1 signaling and metabolic effects.

This combination is the most widely used GH peptide stack in anti-aging research settings. Typical research protocols administer 100-300 mcg of each peptide in a single subcutaneous injection, one to three times daily, often timed before sleep to align with endogenous GH peaks. Cycles commonly run 8-12 weeks on a 5-days-on, 2-days-off schedule.

For researchers exploring broader peptide combination strategies, the Sermorelin, Ipamorelin, and CJC-1295 stack overview provides useful context on stacking GHRH analogs with secretagogues.

Tesamorelin's Targeted Research Niche

Tesamorelin's research value is concentrated and well-defined. It received FDA approval in 2010 under the brand name Egrifta for HIV-associated lipodystrophy, making it the only GH-axis peptide with a validated clinical indication. Multiple randomized controlled trials using CT-measured visceral fat as an endpoint confirm its efficacy in reducing abdominal adiposity.

For researchers focused on visceral fat outcomes, the tesa dosage for fat loss resource outlines the validated 2 mg subcutaneous daily protocol with abdominal injection site rotation.

The trade-off is scope: Tesamorelin's evidence base is deep but narrow. The CJC-1295/Ipamorelin stack has broader exploratory application but far less published clinical-trial data supporting body composition outcomes specifically.

Feature CJC-1295 + Ipamorelin Tesamorelin
FDA Approval No Yes (2010, Egrifta)
Half-Life ~30 min / ~2 hr 26-38 min
Mechanism GHRH + GHS dual-pathway GHRH analog only
Primary Research Use Broad GH modulation Visceral fat reduction
Clinical RCT Data Limited Multiple trials

Choosing the Right Option: Practical Guidance for Researchers Comparing CJC-1295 with Ipamorelin vs. Tesamorelin

Choosing the Right Option: Practical Guidance for Researchers Comparing CJC-1295 with Ipamorelin vs. Tesamorelin

Matching Peptide Choice to Research Objectives

Choose the CJC-1295/Ipamorelin stack when:

  • The research question involves broad GH pulse modulation
  • Dual-pathway receptor pharmacology is the focus
  • Flexible dosing frequency is operationally important
  • Cortisol and prolactin neutrality is a study requirement

Choose Tesamorelin when:

  • Visceral adiposity is the primary endpoint
  • Regulatory-grade clinical precedent is required
  • A single-compound, once-daily protocol simplifies the study design
  • Comparison to FDA-approved benchmarks is methodologically necessary

Researchers comparing these agents against other GHRH-related compounds may also find value in the tesa vs. sermorelin comparison and the broader tesa research sourcing guide.

Blend Formulations as a Third Path

A growing area of interest involves pre-formulated blends that combine all three peptides. The Tesamorelin, CJC-1295, and Ipamorelin 12 mg blend consolidates the GHRH analog and GHS mechanisms into a single research compound, reducing preparation complexity. Detailed dosage guidance for the 12 mg blend is available for researchers designing protocols around this formulation.


Conclusion

The CJC-1295 with Ipamorelin vs. Tesamorelin question does not have a single universal answer, it has a research-design answer. The dual-peptide stack delivers synergistic, pulsatile GH stimulation through complementary receptor pathways, making it the more versatile tool for exploratory GH-axis research. Tesamorelin offers something the stack cannot: a validated, FDA-backed clinical record with reproducible visceral fat endpoints.

Actionable next steps for researchers in 2026:

  1. Define the primary endpoint before selecting a compound, body composition, GH pulse amplitude, or receptor pharmacology each favor a different agent.
  2. Review the IPA and Sermorelin stack research overview to benchmark against adjacent peptide combinations.
  3. Consult the tesa daily dosage protocols to ensure any Tesamorelin study arm aligns with established clinical parameters.
  4. Consider pre-blended formulations when protocol simplicity and multi-pathway coverage are both priorities.

Rigorous peptide research begins with matching the compound's mechanism to the study's question, and on that basis, both options have a legitimate, distinct place in the modern growth hormone research toolkit.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/cjc-1295-with-ipamorelin-vs-tesa-which-ghrh-mimetic-stack-is-best-for-you.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-12 13:03:352026-07-20 15:00:14CJC-1295 with Ipamorelin vs. Tesamorelin: Which GHRH Mimetic Stack is Best for Your Research?
Tesamorelin and Ipamorelin: Differentiating Their Growth Hormone Releasing Mechanisms for Research

Tesamorelin and Ipamorelin: Differentiating Their Growth Hormone Releasing Mechanisms for Research

July 8, 2026/0 Comments/by Pure Tested

Two peptides can both raise growth hormone levels yet work through completely different biological locks and keys, that distinction is exactly what makes studying Tesamorelin and Ipamorelin: Differentiating Their Growth Hormone Releasing Mechanisms for Research so valuable for investigators designing targeted protocols in 2026.

Key Takeaways

  • Tesamorelin acts on the GHRH receptor (GHRH-R), mimicking the body's natural growth hormone-releasing hormone.
  • Ipamorelin acts on the ghrelin receptor (GHSR-1a), classifying it as a growth hormone secretagogue.
  • These distinct receptor targets produce different pulse patterns, selectivity profiles, and downstream effects.
  • Combining both peptides may amplify GH release through complementary, non-competing pathways.
  • Researchers must account for these mechanistic differences when designing assays, dosing schedules, and outcome measures.

Key Takeaways

Understanding the Two Core Mechanisms

At the heart of Tesamorelin and Ipamorelin: Differentiating Their Growth Hormone Releasing Mechanisms for Research is a straightforward but critical distinction: receptor class.

Tesamorelin is a synthetic analogue of endogenous growth hormone-releasing hormone (GHRH). It binds selectively to the GHRH receptor (GHRH-R) on somatotroph cells in the anterior pituitary. This binding triggers a cyclic AMP (cAMP)-dependent signaling cascade that stimulates GH synthesis and secretion. Because it mirrors the body's own GHRH, the resulting GH pulses tend to follow a physiologically familiar pattern. Researchers interested in Tesamorelin's benefits and mechanisms often note its strong clinical validation, including FDA approval for HIV-associated lipodystrophy.

Ipamorelin, by contrast, belongs to the growth hormone secretagogue (GHS) class. It binds to the ghrelin receptor, formally called GHSR-1a. Rather than mimicking GHRH, Ipamorelin mimics ghrelin, a gut-derived hormone that signals energy status to the pituitary. This receptor engagement activates a phospholipase C / inositol trisphosphate (IP3) pathway, which is mechanistically separate from the cAMP route used by Tesamorelin. Ipamorelin is also noted for its high selectivity; unlike older GHS peptides, it produces minimal stimulation of cortisol or prolactin.

Research Insight: Because Tesamorelin and Ipamorelin engage separate receptor classes, they can stimulate GH release through additive or synergistic pathways without directly competing for the same binding site.

Side-by-Side Comparison for Research Planning

Feature Tesamorelin Ipamorelin
Peptide Class GHRH Analogue GH Secretagogue (GHS)
Primary Receptor GHRH-R GHSR-1a (Ghrelin Receptor)
Signaling Pathway cAMP / PKA PLC / IP3
Selectivity High (GH axis) Very High (minimal cortisol/prolactin)
Combination Potential Complementary with GHS Complementary with GHRH analogues

Side-by-Side Comparison for Research Planning

For researchers evaluating Ipamorelin versus Tesamorelin as standalone or combined agents, this receptor-level separation is the most important design variable to control.


Research Applications and Combination Protocols

Understanding Tesamorelin and Ipamorelin: Differentiating Their Growth Hormone Releasing Mechanisms for Research becomes especially actionable when planning multi-peptide protocols.

Because the two peptides work on different receptors, stacking them does not create direct receptor competition. Studies examining the safety of combining Tesamorelin with CJC/Ipamorelin suggest that dual-pathway stimulation can produce a more robust GH pulse than either agent alone. This is also why blended formulations, such as the Tesamorelin, CJC-1295, and Ipamorelin 12mg blend, have attracted research interest.

Key research considerations when using both peptides:

  • Pulse timing: Tesamorelin pulses follow endogenous GHRH rhythms; Ipamorelin pulses can be timed more flexibly due to ghrelin receptor kinetics.
  • Feedback sensitivity: Both peptides remain subject to somatostatin-mediated negative feedback, so researchers should account for somatostatin tone in study design.
  • Dosing protocols: Reviewing established Tesamorelin dosage frameworks alongside Ipamorelin titration data helps set appropriate research benchmarks.
  • Outcome markers: IGF-1 levels, GH pulse amplitude, and body composition metrics each respond differently depending on which receptor pathway is engaged.

Researchers comparing GHRH-class peptides more broadly may also find value in reviewing Sermorelin, Ipamorelin, and CJC-1295 combination research to contextualize Tesamorelin's relative potency and duration of action.

Research Applications and Combination Protocols


Conclusion

Differentiating Tesamorelin and Ipamorelin at the receptor level, GHRH-R versus GHSR-1a, is not a minor technical detail. It shapes every aspect of a well-designed GH research protocol, from signal pathway selection and pulse timing to combination strategy and outcome measurement.

Actionable next steps for researchers:

  1. Define whether the study goal requires GHRH-pathway activation, ghrelin-pathway activation, or both.
  2. Review published Tesamorelin benefit profiles and Ipamorelin selectivity data before finalizing dosing schedules.
  3. Source peptides from verified, lab-tested suppliers to ensure purity and accurate concentration for reliable data.
  4. Consider CJC-1295 and Ipamorelin assay planning resources when building a multi-peptide experimental framework.

Mechanistic clarity is the foundation of reproducible peptide research. Knowing precisely how each compound triggers GH release allows investigators to isolate variables, interpret results accurately, and build on findings with confidence.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/Tesamorelin-and-Ipamorelin-Differentiating-Their-Growth-Hormone-Releasing-Mechanisms-for-Research.png 1024 1024 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-08 13:05:332026-07-20 15:00:48Tesamorelin and Ipamorelin: Differentiating Their Growth Hormone Releasing Mechanisms for Research
CJC-1295 with Ipamorelin: Synergistic Effects and Optimized Protocols in Growth Hormone Research

CJC-1295 with Ipamorelin: Synergistic Effects and Optimized Protocols in Growth Hormone Research

July 6, 2026/0 Comments/by Pure Tested

Growth hormone pulse amplitudes reaching 340% above baseline from a single timed dosing sequence, that figure alone explains why researchers studying CJC-1295 with Ipamorelin: Synergistic Effects and Optimized Protocols in Growth Hormone Research have made this peptide pairing one of the most actively investigated combinations in endocrinology today.

Neither compound achieves that magnitude alone. CJC-1295 (no-DAC) activates GHRH receptors, while Ipamorelin targets ghrelin/GHSR-1a receptors, two separate pathways that, when triggered in sequence, produce a larger yet still pulsatile growth hormone release. That pulsatility matters because it more closely mirrors natural GH physiology than flat, supraphysiologic exposure.

Wide-angle laboratory research scene showing two distinct molecular structures labeled CJC-1295 and Ipamorelin converging

Key Takeaways

  • Combining CJC-1295 no-DAC with Ipamorelin within a 30-minute dosing window produces GH pulses approximately 340% above baseline, significantly higher than either peptide alone.
  • The synergy stems from dual receptor activation: GHRH receptors (CJC-1295) and ghrelin/GHSR-1a receptors (Ipamorelin), preserving natural pulsatility.
  • Co-administration in research settings has produced IGF-1 elevations of roughly 1.8-2.3 times baseline compared with single-agent protocols.
  • Phase II and Phase III trials in 2026 are actively investigating this pairing for age-related GH deficiency, metabolic dysfunction, and body-composition outcomes.
  • As of 2026, neither peptide holds FDA approval; both remain strictly research-use compounds.

Mechanism Behind the Synergistic Effects

The core reason researchers prioritize CJC-1295 with Ipamorelin: Synergistic Effects and Optimized Protocols in Growth Hormone Research lies in complementary receptor biology.

CJC-1295 no-DAC is a modified GHRH analogue. It binds GHRH receptors on somatotroph cells in the anterior pituitary, stimulating GH synthesis and release. Its relatively short active window, compared with the DAC version, makes it well-suited for protocols that aim to replicate natural pulsatile GH secretion. For a deeper look at the structural differences, the CJC-1295 with DAC deeper dive resource provides useful mechanistic context.

Ipamorelin is a selective growth hormone secretagogue and ghrelin receptor agonist. It stimulates GH release through GHSR-1a receptors while showing minimal effect on cortisol or prolactin, a selectivity profile that makes it a preferred research tool. Researchers exploring the broader secretagogue landscape will find the Ipamorelin as the most important GHRH secretagogue overview informative.

When both peptides are administered within a 30-minute window, the two receptor systems amplify each other's downstream signaling. The result is a GH pulse that is substantially larger than additive effects would predict, a true pharmacological synergy.

"Sequential activation of GHRH and ghrelin receptors generates a larger yet still pulsatile GH release, preserving physiological rhythm while amplifying amplitude."


Optimized Protocols in Growth Hormone Research Settings

Optimized Protocols in Growth Hormone Research Settings

Translating receptor biology into practical research protocols requires attention to timing, frequency, and cycle structure. Current data from ongoing Phase II and Phase III trials in 2026 point toward several consistent design principles.

Timing and Sequencing

Administering CJC-1295 no-DAC first, followed by Ipamorelin within a 30-minute window, consistently outperforms simultaneous injection in terms of peak GH amplitude. The sequential approach allows GHRH receptor priming before ghrelin receptor activation compounds the signal.

Dosing Frequency

Most active research protocols use twice-daily administration, once in the morning and once before sleep, to align with natural GH secretory patterns. Sleep-time dosing is particularly relevant because endogenous GH pulses are largest during slow-wave sleep.

Cycle Length and IGF-1 Outcomes

Protocol Variable Research Finding
Dosing window Sequential, within 30 minutes
GH pulse amplitude ~340% above baseline
IGF-1 elevation 1.8-2.3x baseline (co-administration)
Frequency Twice daily in most active trials

Researchers combining these peptides with broader metabolic interventions have also explored Tesamorelin, CJC-1295, and Ipamorelin blend protocols to address body-composition endpoints more comprehensively.

For those examining metabolic outcomes specifically, the Tesamorelin body composition research themes page offers relevant parallel data.


2026 Clinical Trial Landscape and Regulatory Considerations

2026 Clinical Trial Landscape and Regulatory Considerations

Active Phase II and Phase III trials in 2026 are examining CJC-1295 with Ipamorelin: Synergistic Effects and Optimized Protocols in Growth Hormone Research across three primary indications: age-related GH deficiency, metabolic dysfunction, and body-composition optimization.

Investigators are specifically studying:

  • Sequential vs. simultaneous dosing to determine which produces superior IGF-1 outcomes with fewer desensitization effects
  • Injection frequency optimization, balancing pulse amplitude against receptor downregulation over extended cycles
  • Cycle length variables to identify the minimum effective duration for meaningful IGF-1 and lean-mass endpoints

Much of this trial data remains unpublished, though secondary summaries from 2026 trial overviews confirm the dual-peptide design as the central mechanistic feature.

Regulatory status as of 2026: Neither CJC-1295 nor Ipamorelin holds FDA approval for any clinical indication. Both remain research-use compounds subject to increasingly strict compounding guidance. Researchers and institutions should review current regulatory frameworks before initiating any protocol. For context on related peptide regulatory considerations, the Ipamorelin and Sermorelin stack research page addresses comparable compliance questions.

Researchers interested in expanding their GH axis investigation may also find value in reviewing what is somatotropin for foundational context, or exploring NAD+ energetics and longevity research themes for adjacent metabolic pathways.


Conclusion

The evidence base for CJC-1295 with Ipamorelin: Synergistic Effects and Optimized Protocols in Growth Hormone Research continues to strengthen in 2026, with mechanistic data confirming 340% GH pulse amplification and IGF-1 elevations nearly 2.3 times baseline under optimized sequential protocols. The dual receptor mechanism, GHRH and GHSR-1a activation in sequence, represents a reproducible and physiologically coherent research strategy.

Actionable next steps for researchers:

  • Prioritize sequential dosing with a 30-minute window between CJC-1295 no-DAC and Ipamorelin administration
  • Design protocols around twice-daily injection schedules aligned with natural GH secretory rhythms
  • Monitor IGF-1 at regular intervals to detect desensitization before it affects endpoint data
  • Stay current with FDA and compounding regulatory updates, as guidance continues to evolve in 2026
  • Review active trial registries for emerging dose and cycle-length data as Phase III results are published
https://www.puretestedpeptides.com/wp-content/uploads/2026/07/CJC-1295-with-Ipamorelin-Synergistic-Effects-and-Optimized-Protocols-in-Growth-Hormone-Research.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-06 13:03:562026-07-20 15:00:55CJC-1295 with Ipamorelin: Synergistic Effects and Optimized Protocols in Growth Hormone Research
CJC-1295 Without DAC: Why Half-Life Matters in Growth Hormone Research

CJC-1295 Without DAC: Why Half-Life Matters in Growth Hormone Research

June 28, 2026/0 Comments/by Pure Tested

A peptide with a 30-minute half-life may sound like a limitation. In growth hormone research, it is often the point. CJC-1295 Without DAC: Why Half-Life Matters in Growth Hormone Research is a question that cuts to the core of how researchers design protocols that respect the body's natural hormonal rhythms rather than override them.

Also known as Modified GRF 1-29, CJC-1295 without DAC is a synthetic analog of growth hormone-releasing hormone (GHRH). Its short active window is not a flaw in the design — it is the design.

Key Takeaways

  • CJC-1295 without DAC has a half-life of approximately 30 minutes, supporting pulsatile GH release
  • The absence of the Drug Affinity Complex (DAC) distinguishes it from the longer-acting DAC variant
  • Pulsatile GH secretion more closely mirrors natural physiology and may reduce receptor desensitization
  • It is frequently paired with ipamorelin to target complementary GH-release pathways
  • CJC-1295 without DAC is not FDA-approved and is intended strictly for research purposes

Key Takeaways

Understanding the Half-Life Difference in CJC-1295 Without DAC Research

Half-life determines how long a compound remains active in a biological system. For CJC-1295 without DAC, that window is roughly 30 minutes. For the DAC version, the half-life stretches to approximately 5.8 to 8.1 days.

That difference is not trivial. It changes everything about how GH is released.

Variant Half-Life GH Release Pattern
CJC-1295 without DAC ~30 minutes Pulsatile, physiological
CJC-1295 with DAC ~5.8–8.1 days Sustained, continuous

The body does not release GH in a steady stream. It releases it in pulses — sharp peaks followed by quiet troughs. This rhythm is tied to sleep cycles, metabolic signaling, and feedback loops involving IGF-1. A compound that mimics this pattern is considered more physiologically aligned than one that maintains constant elevation.

"The short half-life of the no-DAC variant allows researchers to time GH pulses with precision, which is central to protocols designed around natural secretion windows."

For a deeper look at how the DAC modification changes the pharmacological profile, the CJC-1295 with DAC deeper dive offers a useful comparison.


Mechanism of Action: How the No-DAC Version Triggers GH Pulses

CJC-1295 without DAC binds to GHRH receptors on pituitary somatotroph cells. This binding stimulates the release of GH, which in turn drives IGF-1 production in the liver. The cascade is well-characterized in the scientific literature.

What makes the no-DAC version distinct is its rapid clearance. Because it leaves the system quickly, GH levels rise sharply and then return to baseline — closely matching the body's endogenous pattern.

Why this matters in research:

  • Avoids prolonged receptor activation that can lead to desensitization
  • Allows multiple dosing windows within a single day
  • Enables researchers to observe GH pulse responses in controlled intervals

Typical research protocols use doses of 100–300 mcg administered two to three times daily, often timed around sleep onset and morning windows when natural GH secretion is highest. Cycles in research settings commonly run 12 to 16 weeks.

The CJC-1295 product page provides additional catalog context for researchers sourcing this compound.


Mechanism of Action: How the No-DAC Version Triggers GH Pulses

CJC-1295 Without DAC and Ipamorelin: A Common Research Pairing

One of the most studied combinations in GH research pairs CJC-1295 without DAC with ipamorelin. These two compounds work through different but complementary pathways.

  • CJC-1295 without DAC activates the GHRH receptor, amplifying the GH pulse
  • Ipamorelin activates the growth hormone secretagogue receptor (GHSR), independently triggering GH release

Together, they produce a stronger, more synchronized GH response than either compound alone. Researchers value this pairing because it targets two separate mechanisms while still producing a pulsatile, time-limited GH spike.

Pre-formulated blends are available for research use, including the CJC-1295 and ipamorelin combination and the CJC-1295 plus IPA research blend.

For researchers exploring broader GH-axis protocols, the tesa vs ipamorelin comparison provides useful context on how different GHRH analogs differ in their pharmacological profiles.


CJC-1295 Without DAC and Ipamorelin: A Common Research Pairing

Storage, Safety, and Research Considerations

Lyophilized CJC-1295 without DAC should be stored at 2–8°C. Once reconstituted, it remains stable under refrigeration for up to 30 days.

The available safety data — drawn from studies on the parent CJC-1295 compound — suggest reasonable tolerability at research doses, with no serious adverse reactions reported at doses of 30 or 60 mcg/kg. However, long-term safety data remain limited, and the compound is not FDA-approved for human or veterinary use.

The evidence base includes 18 human studies, 126 animal studies, and over 56 published reviews — a substantial foundation, though researchers should note that studies specific to the no-DAC variant are less numerous than those on the DAC form.

Researchers interested in broader peptide research contexts may also find value in reviewing BPC-157 research documentation and TB-500 and BPC-157 regeneration research as complementary areas of study.


Conclusion

CJC-1295 Without DAC: Why Half-Life Matters in Growth Hormone Research comes down to one core principle: shorter is sometimes smarter. A 30-minute half-life is not a compromise — it is a tool that allows researchers to replicate pulsatile GH dynamics with precision.
Actionable next steps for researchers in 2026:

  1. Review the pharmacokinetic literature on Modified GRF 1-29 before designing protocols
  2. Consider the ipamorelin pairing to target complementary GH-release pathways
  3. Source compounds from verified suppliers with documented purity testing
  4. Align dosing windows with natural GH secretion peaks (sleep onset, morning)
  5. Monitor IGF-1 markers as a downstream indicator of GH pulse activity

Understanding half-life is not a detail — it is the foundation of responsible, reproducible growth hormone research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/CJC-1295-Without-DAC-Why-Half-Life-Matters-in-Growth-Hormone-Research.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-28 13:04:042026-07-20 15:02:00CJC-1295 Without DAC: Why Half-Life Matters in Growth Hormone Research
CJC-1295 Without DAC for Pulsatile GH Research: Why Shorter Half-Life Can Be an Advantage

CJC-1295 Without DAC for Pulsatile GH Research: Why Shorter Half-Life Can Be an Advantage

June 14, 2026/0 Comments/by Pure Tested

A 30-minute plasma half-life sounds like a weakness. In the world of growth hormone research, it is one of the most useful properties a peptide can have.

CJC-1295 without DAC, also known as Modified GRF (1-29), clears the bloodstream rapidly after administration. That rapid clearance is not a flaw in the molecule's design — it is the feature that makes CJC-1295 Without DAC for Pulsatile GH Research: Why Shorter Half-Life Can Be an Advantage such a compelling area of study. When the goal is to replicate the body's natural growth hormone (GH) secretion patterns rather than override them, timing matters more than duration.

Detailed () scientific infographic illustration showing two side-by-side pharmacokinetic curves: one steep short-duration

Key Takeaways

  • CJC-1295 without DAC has a plasma half-life of approximately 30 minutes, enabling discrete, pulsatile GH release.
  • Pulsatile GH secretion more closely mirrors natural physiology than continuous elevation.
  • The absence of the Drug Affinity Complex (DAC) prevents albumin binding, causing rapid clearance.
  • Pairing the peptide with ghrelin receptor agonists like Ipamorelin is a common research protocol.
  • The short duration of action helps preserve natural feedback mechanisms and may reduce desensitization risk.

The Structural Difference That Changes Everything

The DAC (Drug Affinity Complex) modification in the longer-acting CJC-1295 variant allows the peptide to bind to albumin in the bloodstream, extending its half-life to 5.8–8.1 days. Remove that complex, and the peptide loses its anchor. Without albumin binding, Modified GRF (1-29) is cleared within roughly 30 minutes.

This structural distinction creates two fundamentally different research tools. For a deeper look at how the DAC variant behaves, the CJC-1295 with DAC deeper dive provides useful context. The key point for researchers is that neither form is universally superior — the right choice depends entirely on what the study is designed to measure.

The no-DAC form is the tool of choice when the research question centers on GH pulse dynamics.


Why Pulsatile GH Release Matters in Research

The pituitary gland does not release GH in a steady stream. It fires in discrete pulses, typically peaking during deep sleep and in response to exercise or fasting. These pulses are not random — they are tightly regulated by a feedback loop involving growth hormone-releasing hormone (GHRH), somatostatin, and IGF-1.

Continuous GH elevation disrupts this loop. It can blunt receptor sensitivity, promote insulin resistance, and trigger fluid retention. Pulsatile release, by contrast, preserves the natural rhythm that keeps these feedback mechanisms functional.

This is precisely why CJC-1295 Without DAC for Pulsatile GH Research: Why Shorter Half-Life Can Be an Advantage as a research model. Each administration produces a discrete GH pulse and then clears, allowing the system to reset before the next dose. The body's regulatory architecture remains largely intact.

"The transient activity of short-acting GHRH analogs allows for the preservation of natural feedback systems — a critical variable in physiologically valid GH research."


Experimental Use Cases and Protocol Design

Experimental Use Cases and Protocol Design

Because the peptide requires multiple daily administrations to sustain GH pulsatility, research protocols using the no-DAC form tend to be more granular and time-sensitive than those using the DAC variant. This is not a disadvantage — it is what makes the molecule suitable for specific experimental designs.

Common Research Applications

Research Area Why No-DAC Is Preferred
GH pulse frequency studies Short half-life allows discrete, measurable pulses
Metabolic function research Avoids chronic GH elevation that skews metabolic markers
Receptor sensitivity studies Reduces desensitization risk between doses
Aging and GH axis research Mimics natural age-related GH secretion patterns

Pairing with Ghrelin Receptor Agonists

Research protocols frequently combine CJC-1295 without DAC with Ipamorelin, a selective ghrelin receptor agonist. The two peptides act on complementary pathways — one stimulates GHRH receptors, the other activates ghrelin receptors — producing a synergistic GH release without significantly elevating cortisol or prolactin. The CJC-1295 plus Ipamorelin research model outlines how this combination is structured in preclinical settings.

For researchers exploring broader GH-axis stacks, the Sermorelin, Ipamorelin, and CJC-1295 combination offers another framework that incorporates multiple secretagogues.

Researchers interested in metabolic endpoints may also find the Ipamorelin and GHRH/GRF research overview useful for understanding how these pathways interact in experimental models.


Feedback Preservation and Safety Profile Considerations

Feedback Preservation and Safety Profile Considerations

One of the most important — and often underappreciated — advantages of CJC-1295 Without DAC for Pulsatile GH Research: Why Shorter Half-Life Can Be an Advantage is what it does not do. It does not sustain GH elevation long enough to significantly suppress somatostatin feedback. It does not bind albumin and accumulate over days. It does not force the pituitary into a state of chronic stimulation.

This makes it a more conservative tool for studies where receptor desensitization would confound results. Research comparing Tesamorelin versus Ipamorelin highlights how half-life and receptor selectivity interact in GH secretagogue research — a useful parallel for understanding the no-DAC model.

For broader context on how GH-adjacent peptides are being studied in metabolic and longevity research, the AOD-9604 metabolic research overview provides relevant background on downstream GH pathway targets.

It is important to note that CJC-1295 without DAC remains classified as a research chemical as of 2026. It is not approved for therapeutic use in humans, and all studies must be conducted within appropriate regulatory and institutional frameworks.


Conclusion

The short half-life of CJC-1295 without DAC is not a limitation to work around — it is a precision instrument for researchers who need controlled, physiologically relevant GH pulses. When the experimental goal is to study GH dynamics without overriding the body's own regulatory systems, the no-DAC form offers a level of control that longer-acting variants simply cannot provide.

Actionable next steps for researchers:

  • Define whether the study requires sustained GH elevation or discrete pulsatile events before selecting a variant.
  • Consider pairing with Ipamorelin to target complementary GH-release pathways.
  • Design dosing schedules that account for the 30-minute half-life to achieve consistent pulse modeling.
  • Review institutional guidelines to ensure all protocols meet current regulatory standards.

For researchers building multi-peptide GH-axis protocols, exploring Ipamorelin and Sermorelin stack research can provide additional design considerations relevant to pulsatile GH study models.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/CJC-1295-Without-DAC-for-Pulsatile-GH-Research-Why-Shorter-Half-Life-Can-Be-an-Advantage.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-14 13:04:302026-07-20 15:03:16CJC-1295 Without DAC for Pulsatile GH Research: Why Shorter Half-Life Can Be an Advantage
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.
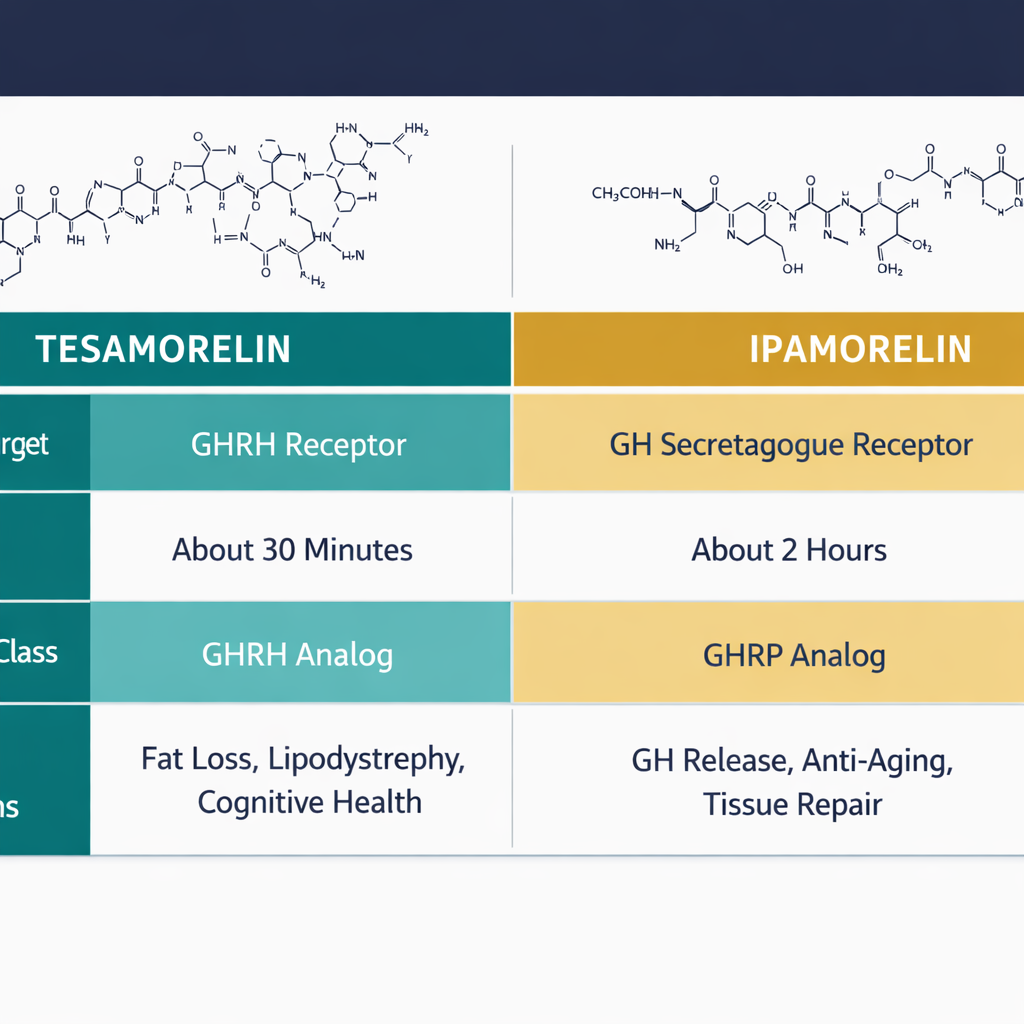
The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top