Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: glp-1 triple agonist

Retatrutide 2026 Trial Data vs Earlier Obesity Models: What Researchers Should Compare Before Drawing Conclusions

Retatrutide 2026 Trial Data vs Earlier Obesity Models: What Researchers Should Compare Before Drawing Conclusions

September 26, 2026/0 Comments/in Uncategorized/by

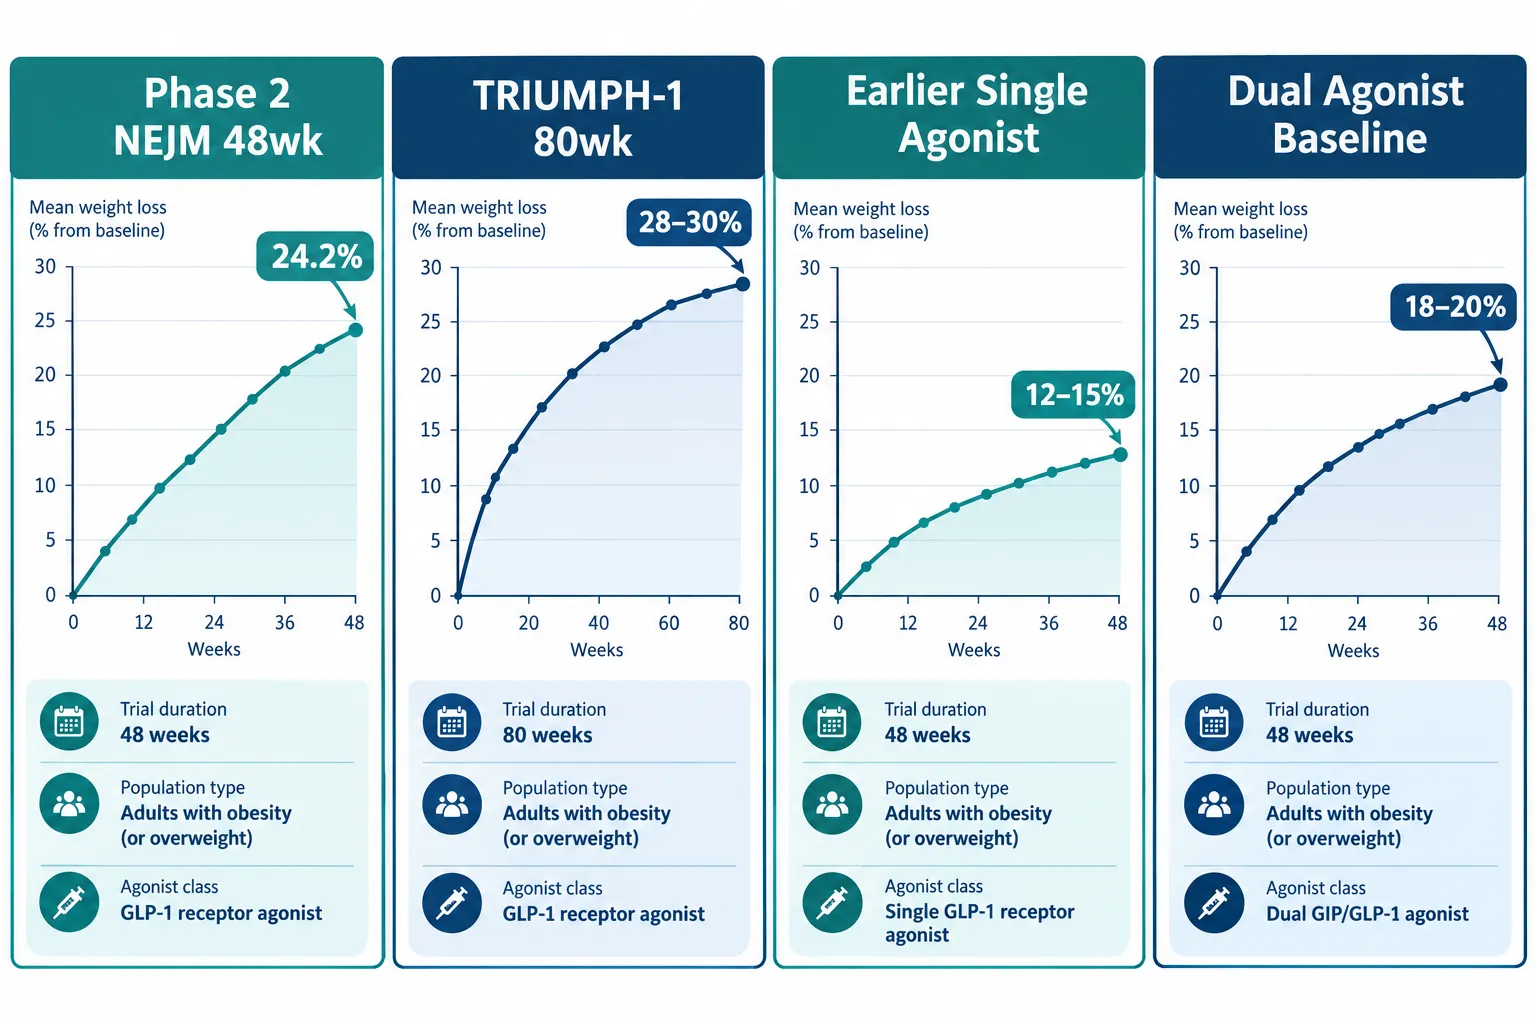
A single Phase 2 result, 24.2% mean body weight loss at 48 weeks, repositioned retatrutide as a potential turning point in obesity pharmacotherapy. Now, with the TRIUMPH program delivering Phase 3 data in 2026 and an FDA submission planned for early 2027, the research community faces a more demanding challenge: comparing these new numbers against earlier obesity models without letting headline figures obscure methodological differences that matter enormously.

Retatrutide 2026 trial data vs earlier obesity models: what researchers should compare before drawing conclusions is not simply a question of which drug produces a bigger number. It is a question of whether the numbers are even measuring the same thing across studies.

Key Takeaways

  • Retatrutide is a triple agonist (GLP-1, GIP, glucagon receptors), making direct comparisons to earlier single- or dual-agonist trials structurally complex.
  • TRIUMPH-1 reports up to 28-30% weight loss over 80 weeks, but population composition, baseline BMI, and trial duration differ from earlier benchmarks.
  • Estimand frameworks, dose escalation schedules, and completeness of adverse-event reporting vary significantly across generations of obesity trials.
  • Glycemic endpoints (A1C reduction) in TRIUMPH-2 require careful alignment with earlier diabetic-population studies before conclusions are drawn.
  • A transparent comparison framework covering at least seven variables is essential before any cross-trial efficacy claim holds scientific weight.

Why the Comparison Problem Is Harder Than It Looks
Why the Comparison Problem Is Harder Than It Looks

The excitement around retatrutide is understandable. The TRIUMPH-1 trial, targeting non-diabetic adults with obesity or overweight, reported weight reductions approaching 28-30% over 80 weeks, figures that have drawn frequent comparisons to bariatric surgery outcomes. TRIUMPH-2 extended the analysis to people with type 2 diabetes, and TRIUMPH-3 enrolled participants with severe obesity and established cardiovascular disease. A global registration trial completed enrollment in late 2025, broadening the population further.

Earlier obesity pharmacotherapy trials, including those for semaglutide and tirzepatide, ran for 68 weeks in many pivotal designs, enrolled populations with somewhat different baseline BMI distributions, and used dose escalation schedules that do not map cleanly onto retatrutide's protocol. Researchers exploring retatrutide clinical trial data will quickly notice that the surface-level weight-loss percentages are not the only variable worth examining.

Seven variables that demand alignment before cross-trial comparison:

Variable Why It Matters
Population baseline BMI Higher baseline BMI inflates absolute kg lost
Trial duration (weeks) Longer trials favor plateau-resistant compounds
Estimand framework Defines how dropouts and discontinuations are handled
Dose escalation schedule Steeper escalation can accelerate early weight loss
Completeness of AE reporting Affects tolerability profile comparisons
Glycemic endpoints (A1C) Critical for diabetic-population sub-analyses
Completers vs ITT analysis Changes the denominator and the headline figure

"A 30% weight loss figure means very little in isolation. The population, the protocol, and the statistical framework are the context that gives the number meaning."


Mechanism Differences That Complicate Direct Comparisons
Mechanism Differences That Complicate Direct Comparisons

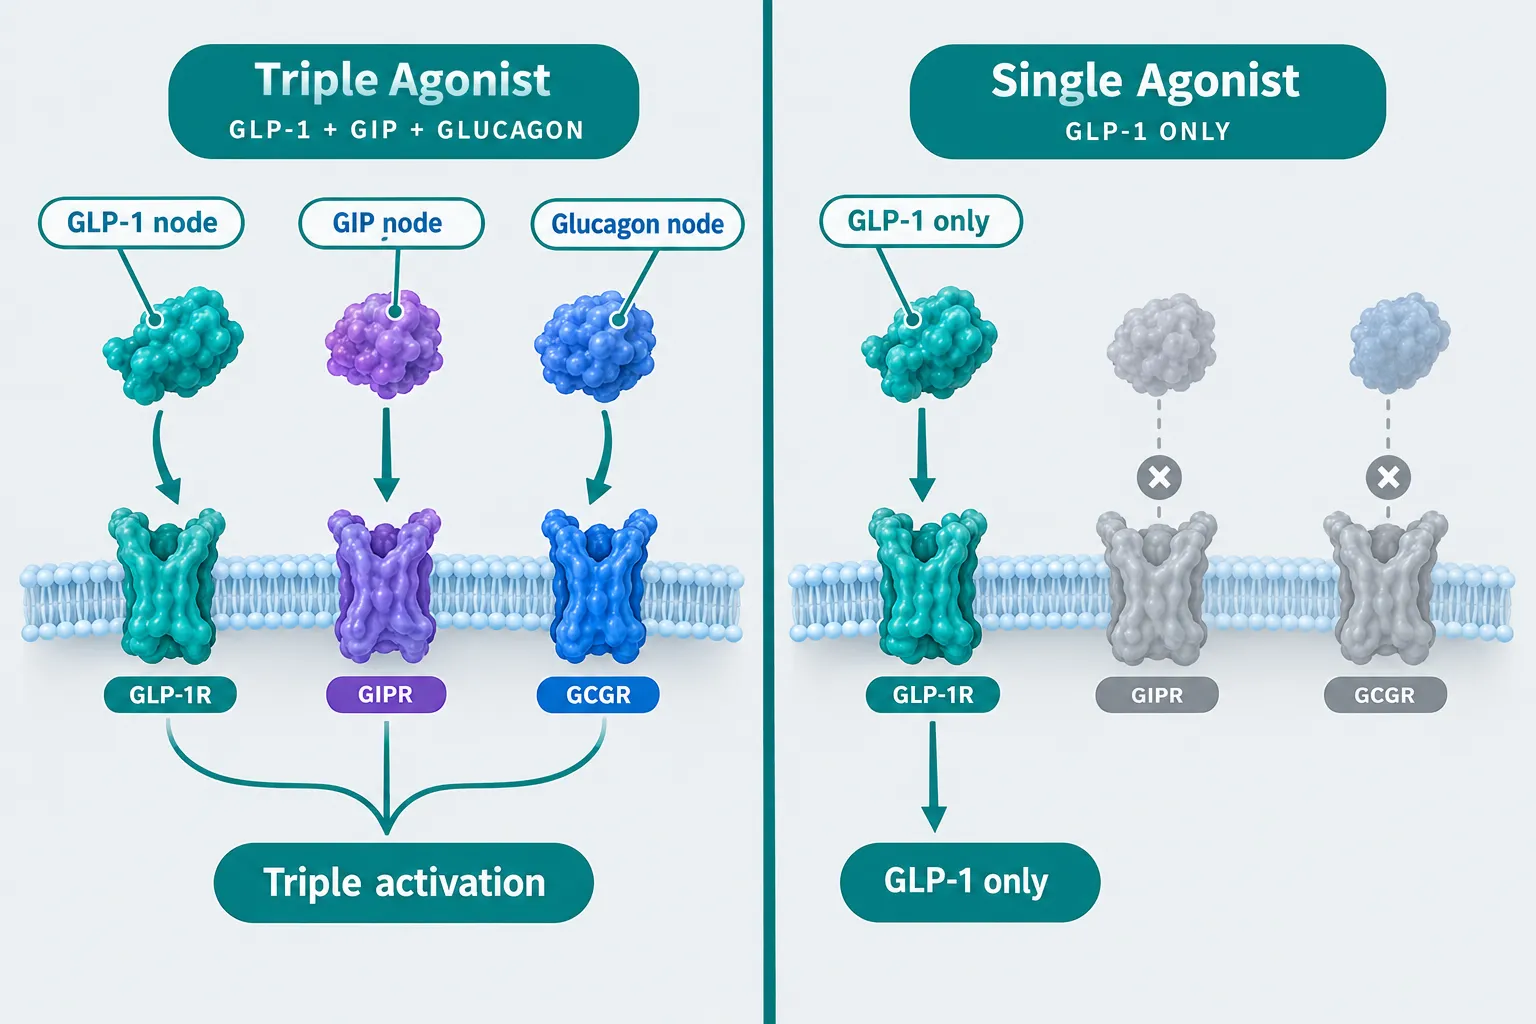
Retatrutide is a triple agonist, activating GLP-1, GIP, and glucagon receptors simultaneously. Earlier approved agents in this space are single agonists (GLP-1 only) or dual agonists (GLP-1 and GIP). This mechanistic distinction is not merely academic, it directly affects which endpoints are most informative and which adverse-event profiles are expected.

Glucagon receptor activation drives additional energy expenditure and lipolysis pathways that are absent in earlier models. This means that comparing retatrutide's weight-loss magnitude against a GLP-1 monotherapy trial without accounting for the additional metabolic burden on participants is methodologically incomplete. Researchers interested in the GLP-3 Reta product tag context will recognize that the triple-agonist classification is central to understanding why the efficacy signal appears larger.

Key mechanistic comparison points:

  • GLP-1 component: Shared with earlier agents; allows partial endpoint alignment on nausea, satiety, and gastric motility outcomes.
  • GIP component: Shared with tirzepatide; permits limited dual-agonist comparison, but retatrutide's GIP binding affinity differs.
  • Glucagon component: Unique to retatrutide in this class; drives hepatic fat reduction and thermogenesis outcomes not tracked in earlier trial designs.

For researchers also examining peptides with distinct metabolic profiles, the Tesamorelin science and sourcing overview offers a useful reference point for understanding how growth-hormone-releasing peptides address visceral fat through a separate mechanism, underscoring why mechanism-first framing matters in any comparative analysis.


Building a Transparent Framework for Cross-Trial Analysis
Building a Transparent Framework for Cross-Trial Analysis

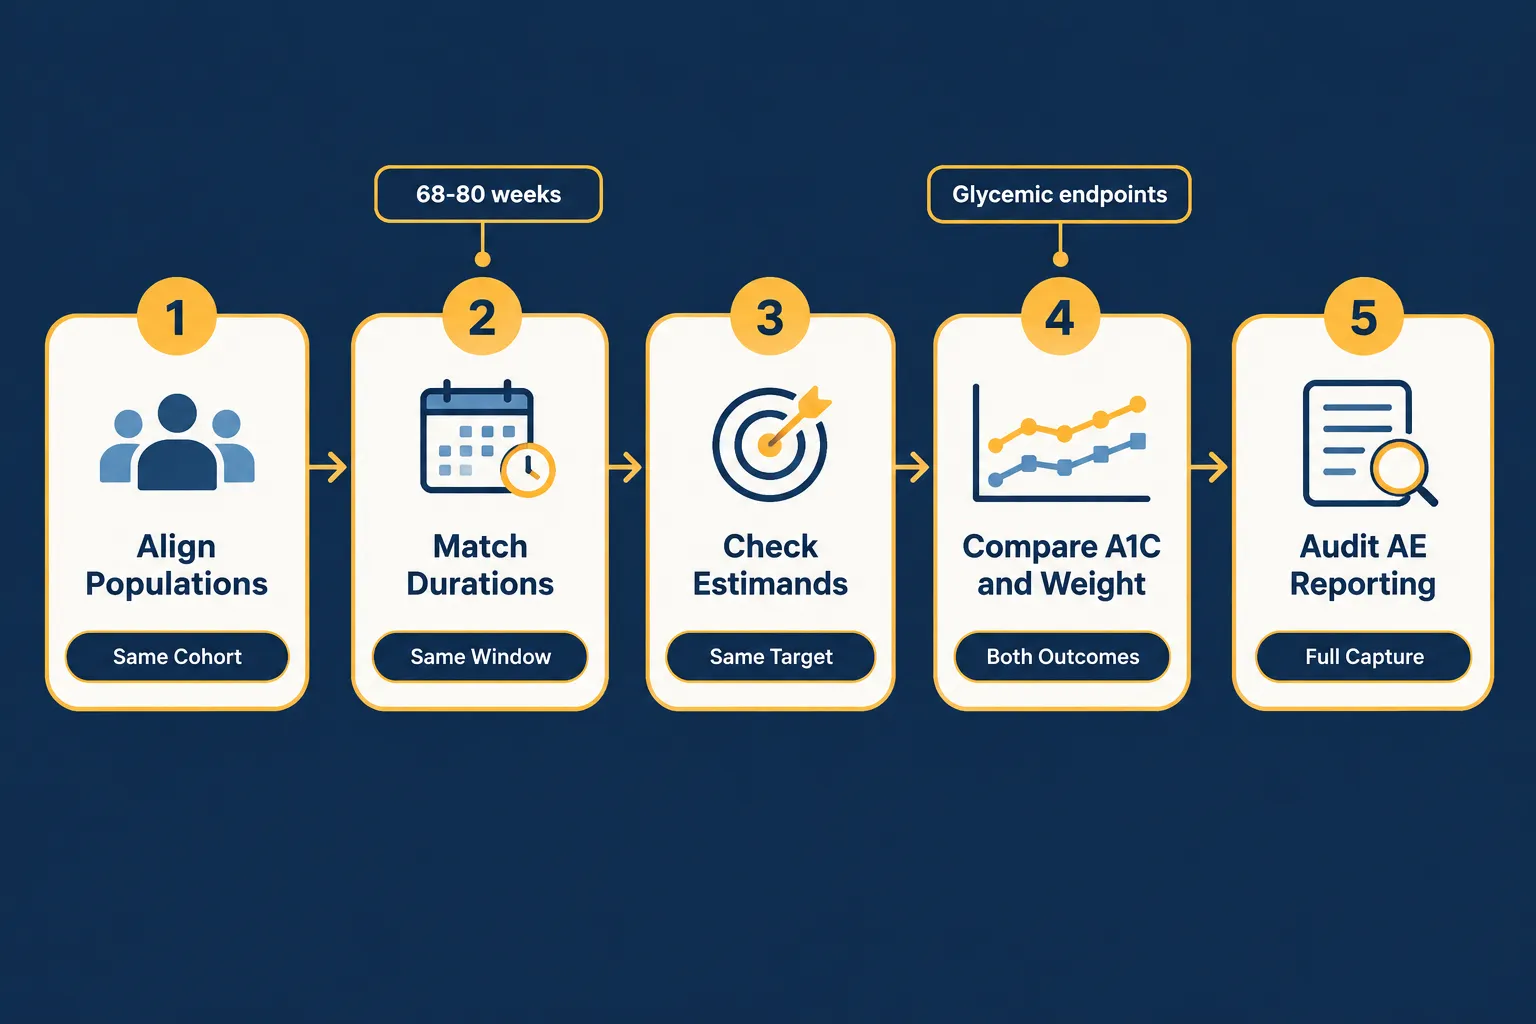
Retatrutide 2026 trial data vs earlier obesity models: what researchers should compare before drawing conclusions comes down to a structured, reproducible framework rather than selective headline matching. The following steps reflect best practice for cross-generational obesity trial comparison.

Step 1, Align populations. Confirm that baseline BMI, diabetes status, cardiovascular comorbidity burden, and geographic distribution are comparable. TRIUMPH-3's cardiovascular-disease population is not equivalent to a general overweight cohort.

Step 2, Match or adjust for duration. TRIUMPH-1's 80-week window exceeds the 68-week standard used in several earlier pivotal trials. Annualized weight-loss rates provide a more honest cross-trial metric than raw endpoint figures.

Step 3, Examine estimands explicitly. The treatment policy estimand (which includes all participants regardless of discontinuation) and the hypothetical estimand (which models outcomes assuming full adherence) produce materially different results. Earlier trials varied in which they pre-specified as primary.

Step 4, Compare A1C and glycemic outcomes in matched populations. TRIUMPH-2 data on weight and glycemic outcomes in type 2 diabetes must be benchmarked only against earlier trials that enrolled comparable diabetic populations with similar baseline A1C ranges.

Step 5, Audit adverse-event completeness. Gastrointestinal adverse events are consistently reported across generations, but cardiovascular safety signals, injection-site reactions, and lean mass loss data have not been uniformly collected. Retatrutide's glucagon component introduces a hepatic safety dimension that earlier single-agonist trial protocols did not systematically monitor.

Researchers building stacks or combination protocols may also find value in reviewing the IPA Sermorelin stack research resource for context on how multi-peptide frameworks are evaluated in research settings, and the SS-31 mitochondrial research tag for parallel work on metabolic and mitochondrial endpoints that may become relevant as retatrutide's full metabolic profile is characterized.

For researchers seeking the compound itself for preclinical work, the Reta 20mg product page provides sourcing details relevant to laboratory use.


Conclusion

The TRIUMPH program represents a genuine advance in obesity pharmacotherapy research, and the 2026 data deserve serious scientific attention. But the value of that data depends entirely on how carefully it is contextualized against earlier obesity models.

Actionable next steps for researchers:

  1. Build a comparison table that explicitly lists population baseline characteristics, trial duration, estimand type, and primary endpoint definition for each study being compared.
  2. Separate efficacy comparisons by population subgroup, non-diabetic, type 2 diabetes, and high-cardiovascular-risk cohorts require distinct reference studies.
  3. Request or locate full adverse-event appendices, not just summary tables, before drawing tolerability conclusions.
  4. Apply annualized weight-loss rates as a normalized cross-trial metric rather than relying on raw endpoint percentages.
  5. Track the FDA submission timeline (currently planned for Q1 2027) and review any agency briefing documents for additional population and estimand disclosures.

Retatrutide 2026 trial data vs earlier obesity models: what researchers should compare before drawing conclusions is ultimately a call for methodological discipline. The numbers are impressive, but the framework used to evaluate them will determine whether the conclusions hold.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-2026-trial-data-vs-earlier-obesity-models-what-researchers-should-co.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-26 13:05:022026-09-26 13:05:02Retatrutide 2026 Trial Data vs Earlier Obesity Models: What Researchers Should Compare Before Drawing Conclusions
Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols

Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols

September 24, 2026/0 Comments/in Uncategorized/by

By August 2026, a key obesity Phase 3 study within the TRIUMPH program was officially marked as completed in clinical trial registries, a milestone that is already forcing researchers to rethink how they design, benchmark, and report nonclinical studies involving metabolic peptides. The Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols conversation is no longer speculative. The data are in, and they are reshaping the field.

Key Takeaways

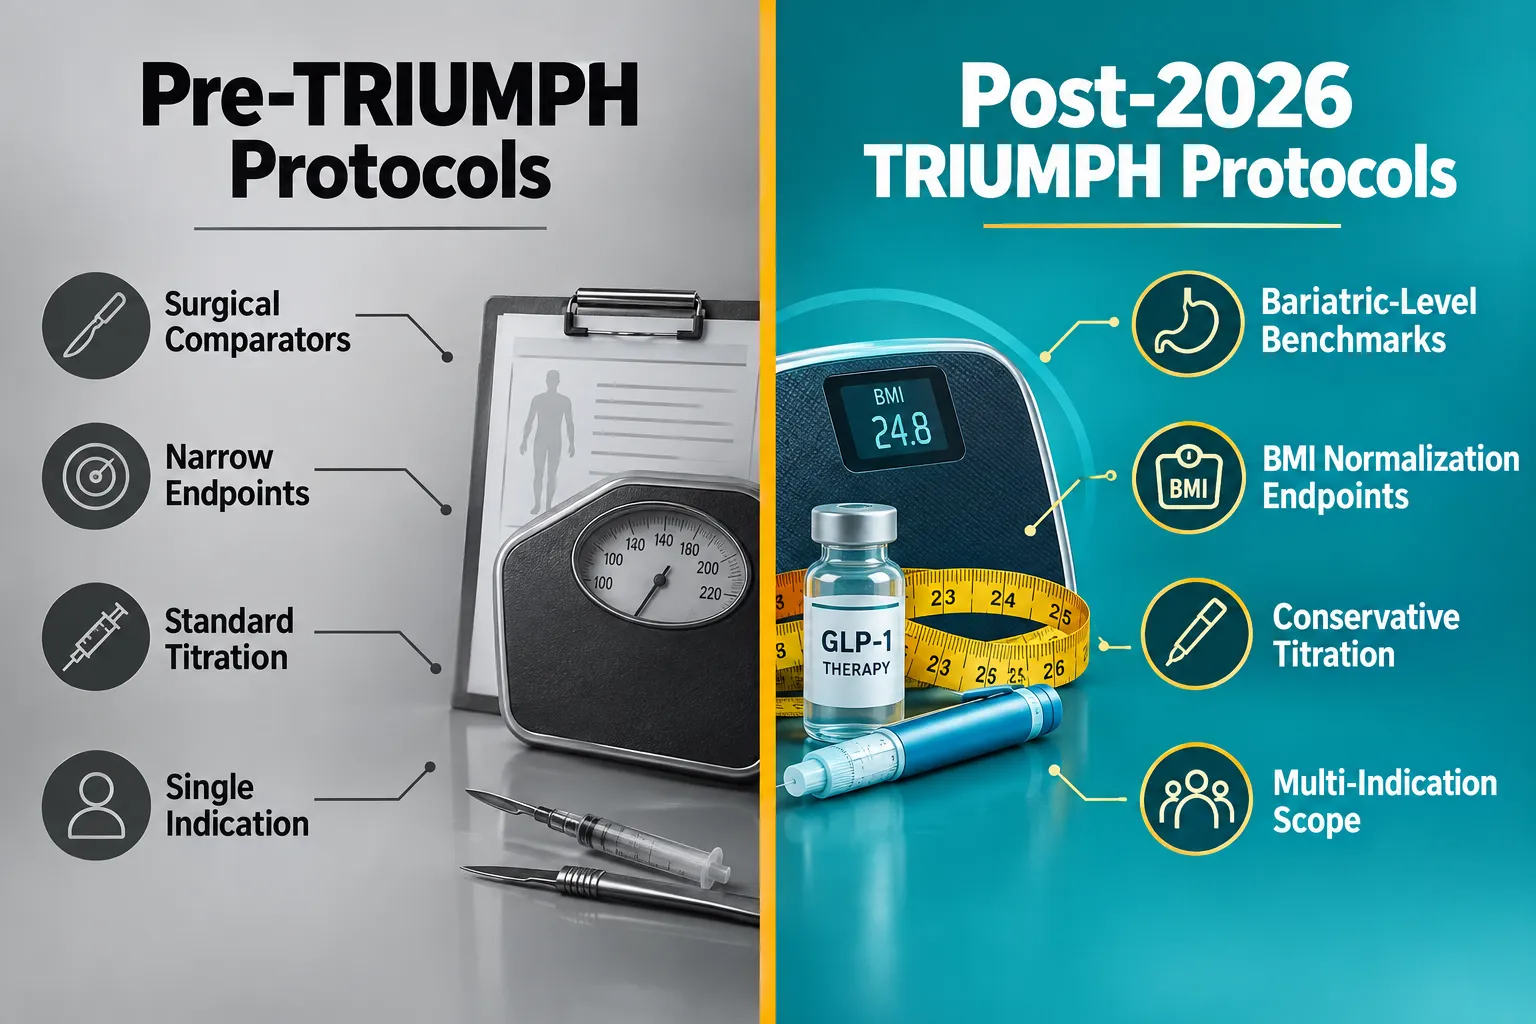
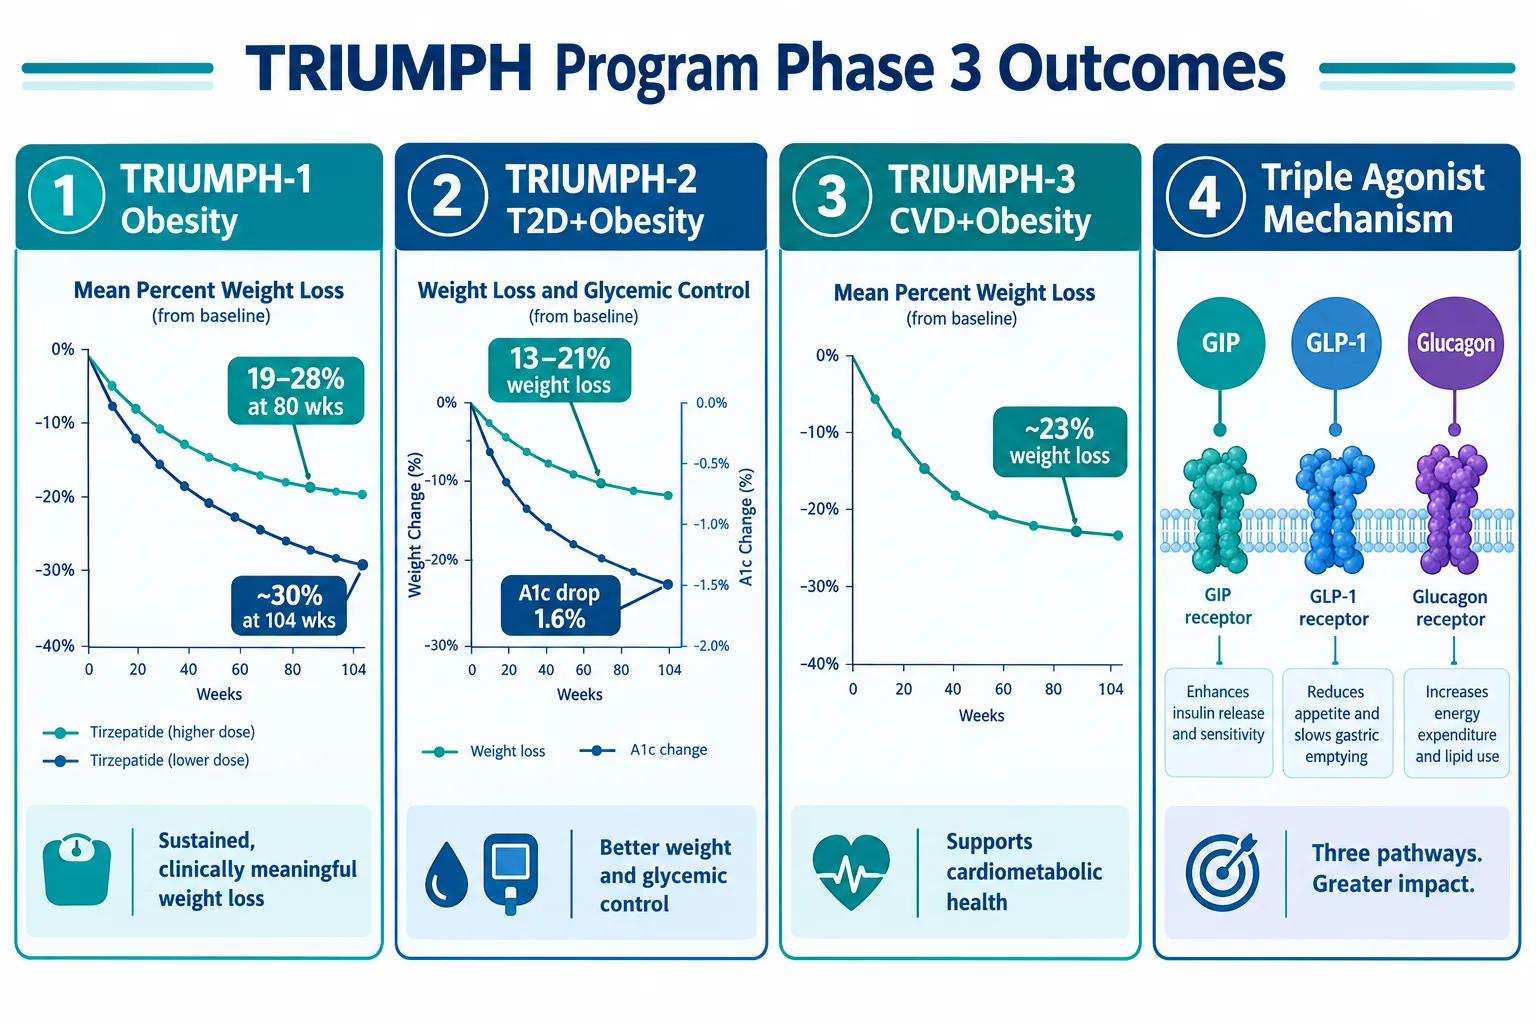
  • Retatrutide's TRIUMPH Phase 3 program has produced weight-loss outcomes of up to 30% at 104 weeks, approaching bariatric surgery benchmarks.
  • Dual efficacy on body weight and glycemic control (up to 1.9-point A1c reduction) makes single-endpoint trial designs increasingly inadequate.
  • Conservative titration schedules and improved retention strategies are now a protocol necessity, not an option.
  • Multi-indication Phase 3 data covering knee OA, OSA, MASLD, and cardiovascular outcomes are expanding the scope of required comparator arms.
  • Retatrutide remains investigational as of late 2026, meaning all research use is subject to regulatory-oriented trial design standards.

The TRIUMPH Program: A Phase 3 Snapshot That Changes Benchmarks

Retatrutide is a first-in-class triple agonist targeting GIP, GLP-1, and glucagon receptors simultaneously. That triple mechanism is what separates it from existing approved therapies and from earlier dual-agonist candidates. For researchers working with retatrutide clinical trial data, the TRIUMPH program now provides the most complete Phase 3 picture available for any triple agonist.

The TRIUMPH Program: A Phase 3 Snapshot That Changes Benchmarks

The headline numbers are striking:

  • TRIUMPH-1 (obesity without diabetes): approximately 19-28% weight loss at 80 weeks, rising to roughly 30% at 104 weeks.
  • TRIUMPH-2 (obesity with type 2 diabetes): 13-21% weight loss plus up to a 1.6% A1c reduction over 80 weeks.
  • TRIUMPH-3 (severe obesity with established cardiovascular disease): approximately 23% weight loss with manageable discontinuation rates.

"Bariatric-like efficacy from a weekly injectable peptide is no longer a theoretical ceiling, TRIUMPH-3 data make it a documented outcome."

These figures introduce what some analysts are calling "de-obesification" endpoints, a term reflecting the normalization of BMI as a primary outcome rather than a secondary marker. For anyone reviewing GLP-1 Reta or GLP-3 Reta research-use compounds, understanding this endpoint shift is essential context.


How the 2026 Obesity and Diabetes Data Rewrites Protocol Design

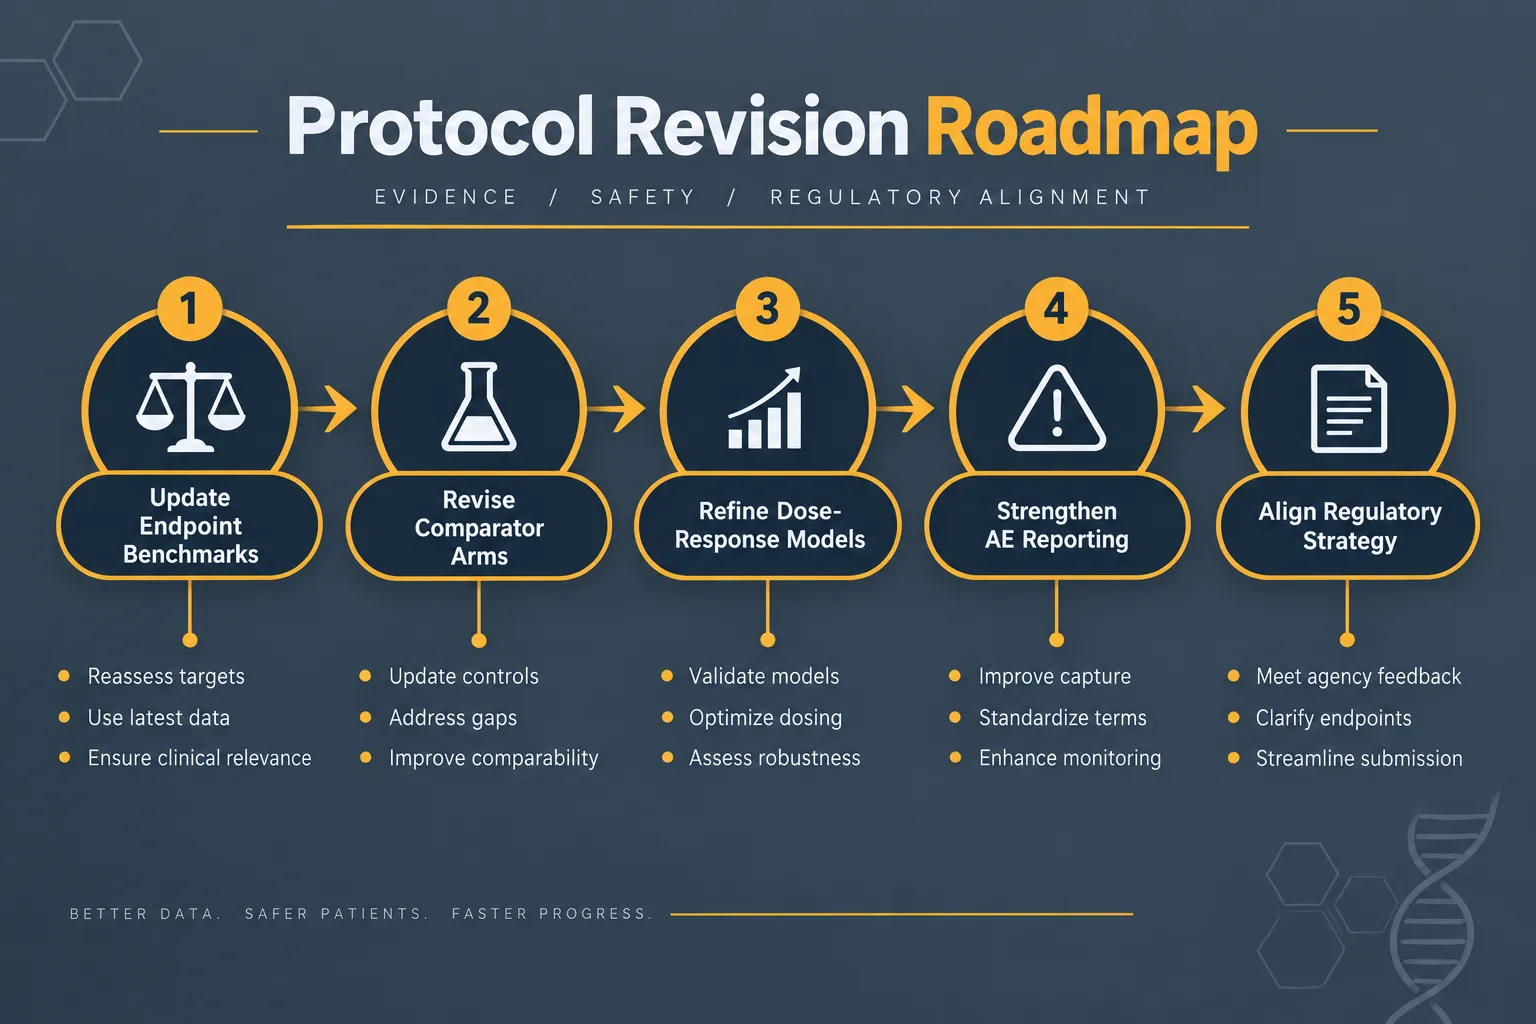
The Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols discussion centers on four concrete areas where existing study designs are now outdated.

1. Endpoint Selection

Single-endpoint designs that measure only weight or only glycemic control are no longer sufficient when the reference compound achieves both simultaneously. Researchers should now plan co-primary endpoints that capture:

  • Percent total body weight loss
  • A1c reduction
  • Cardiometabolic markers (blood pressure, lipids, inflammatory markers)
  • BMI normalization rates

2. Comparator Arm Selection

TRIUMPH data push the efficacy bar to near-surgical levels. Using older GLP-1 monotherapies as the sole active comparator now risks underestimating effect size. Protocol designers should consider:

Comparator Type Relevance Post-TRIUMPH
Older GLP-1 monotherapy Insufficient ceiling for effect-size modeling
Dual agonist (e.g., tirzepatide) Appropriate active comparator
Bariatric surgery outcomes Now a legitimate benchmark arm
Placebo only Acceptable but limits translational value

For broader context on how peptide mechanisms interact with metabolic pathways, the Peptides 101 for Research-Use Only Buyers resource provides a useful structural overview.

3. Dose-Response Modeling

3. Dose-Response Modeling

TRIUMPH safety data revealed that aggressive titration schedules drove higher discontinuation rates. This finding is directly actionable for nonclinical protocol design. Dose-response models should now incorporate:

  • Extended low-dose phases before escalation
  • Plateau detection windows to identify responders before maximum dosing
  • Dropout probability curves built from TRIUMPH discontinuation patterns

Researchers using Reta 10mg formulations in nonclinical settings should map titration schedules against TRIUMPH's published escalation timelines to ensure their models remain translatable.

4. Adverse-Event Reporting Standards

The TRIUMPH program's safety profile, primarily gastrointestinal events, has established a new floor for what must be captured and reported. Nonclinical adverse-event frameworks should now include structured tracking for:

  • Nausea and vomiting incidence by dose level
  • Time-to-onset relative to titration step
  • Severity grading aligned with TRIUMPH's published criteria

Expanding Scope: Multi-Indication Data and What Comes Next

The Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols story does not end with weight and glycemia. The TRIUMPH program includes at least seven additional Phase 3 datasets expected through 2026-2027, covering knee osteoarthritis, obstructive sleep apnea, metabolic-associated steatotic liver disease (MASLD), chronic pain, and cardiovascular-renal outcomes.

Expanding Scope: Multi-Indication Data and What Comes Next

This multi-indication expansion has two immediate implications for protocol designers:

  1. Organ-specific endpoints (liver stiffness scores, AHI reductions, joint function scales) will need to be incorporated into metabolic research designs that previously focused only on weight.
  2. Comparator arms will need to account for condition-specific active controls, not just metabolic benchmarks.

Researchers working in adjacent areas, such as mitochondrial function studies or growth hormone secretagogue research, should note that Tesamorelin data on visceral fat reduction may serve as a useful secondary comparator in MASLD-adjacent protocols.


Conclusion

The TRIUMPH Phase 3 program has fundamentally changed the reference frame for metabolic research protocols. Researchers who continue using pre-2026 endpoint structures, outdated comparator arms, or aggressive titration schedules will produce data that are difficult to interpret against the current evidence base.

Actionable next steps for protocol teams:

  1. Audit existing endpoint frameworks against TRIUMPH co-primary outcomes and add cardiometabolic markers where absent.
  2. Replace or supplement older GLP-1 monotherapy comparators with dual-agonist or bariatric-surgery benchmarks.
  3. Build conservative titration schedules into dose-response models and document dropout probability curves.
  4. Expand adverse-event capture to include time-to-onset data aligned with TRIUMPH's published safety criteria.
  5. Monitor the seven additional TRIUMPH Phase 3 readouts expected through 2027 and update protocols as each dataset publishes.

Retatrutide remains investigational as of late 2026. All research use must align with regulatory-oriented trial design standards. The data, however, are no longer a moving target, and protocol teams that adapt now will be best positioned when regulatory submissions begin.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-phase-3-results-in-2026-what-the-new-obesity-and-diabetes-data-chang.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-24 13:05:072026-09-24 13:05:07Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols
Peptides vs Classic Small‑Molecule Drugs: How GLP-3 Retatrutide, MOTS-c, and 5-Amino-1MQ Change Lab Design Compared With Prednisone and Atorvastatin

Peptides vs Classic Small‑Molecule Drugs: How GLP-3 Retatrutide, MOTS-c, and 5-Amino-1MQ Change Lab Design Compared With Prednisone and Atorvastatin

September 1, 2026/0 Comments/in Uncategorized/by

More than 100 peptide-based drugs are now in clinical development worldwide, yet most research labs were built around the chemistry of small molecules like prednisone and atorvastatin. That gap is widening fast. Understanding Peptides vs Classic Small-Molecule Drugs: How GLP-3 Retatrutide, MOTS-c, and 5-Amino-1MQ Change Lab Design Compared With Prednisone and Atorvastatin is no longer an academic exercise, it is a practical infrastructure question for every team working in metabolic disease, obesity, or longevity research in 2026.

Key Takeaways

  • Peptides like retatrutide and MOTS-c occupy a structural middle ground between small molecules and biologics, demanding specialized synthesis, stability, and PK/PD infrastructure.
  • Classic small molecules such as prednisone and atorvastatin retain strong advantages in oral delivery, cost, and membrane penetration.
  • Retatrutide is a 39-amino-acid triple agonist still in the investigational phase, with commercial launch expected in the mid-2026 to 2027 window.
  • MOTS-c is a mitochondria-derived peptide requiring metabolic stress assays not typically used in standard small-molecule labs.
  • 5-Amino-1MQ remains a preclinical NNMT-inhibiting small molecule with robust mouse data but no human trials yet.

What Separates Peptides From Small Molecules at the Bench

What Separates Peptides From Small Molecules at the Bench

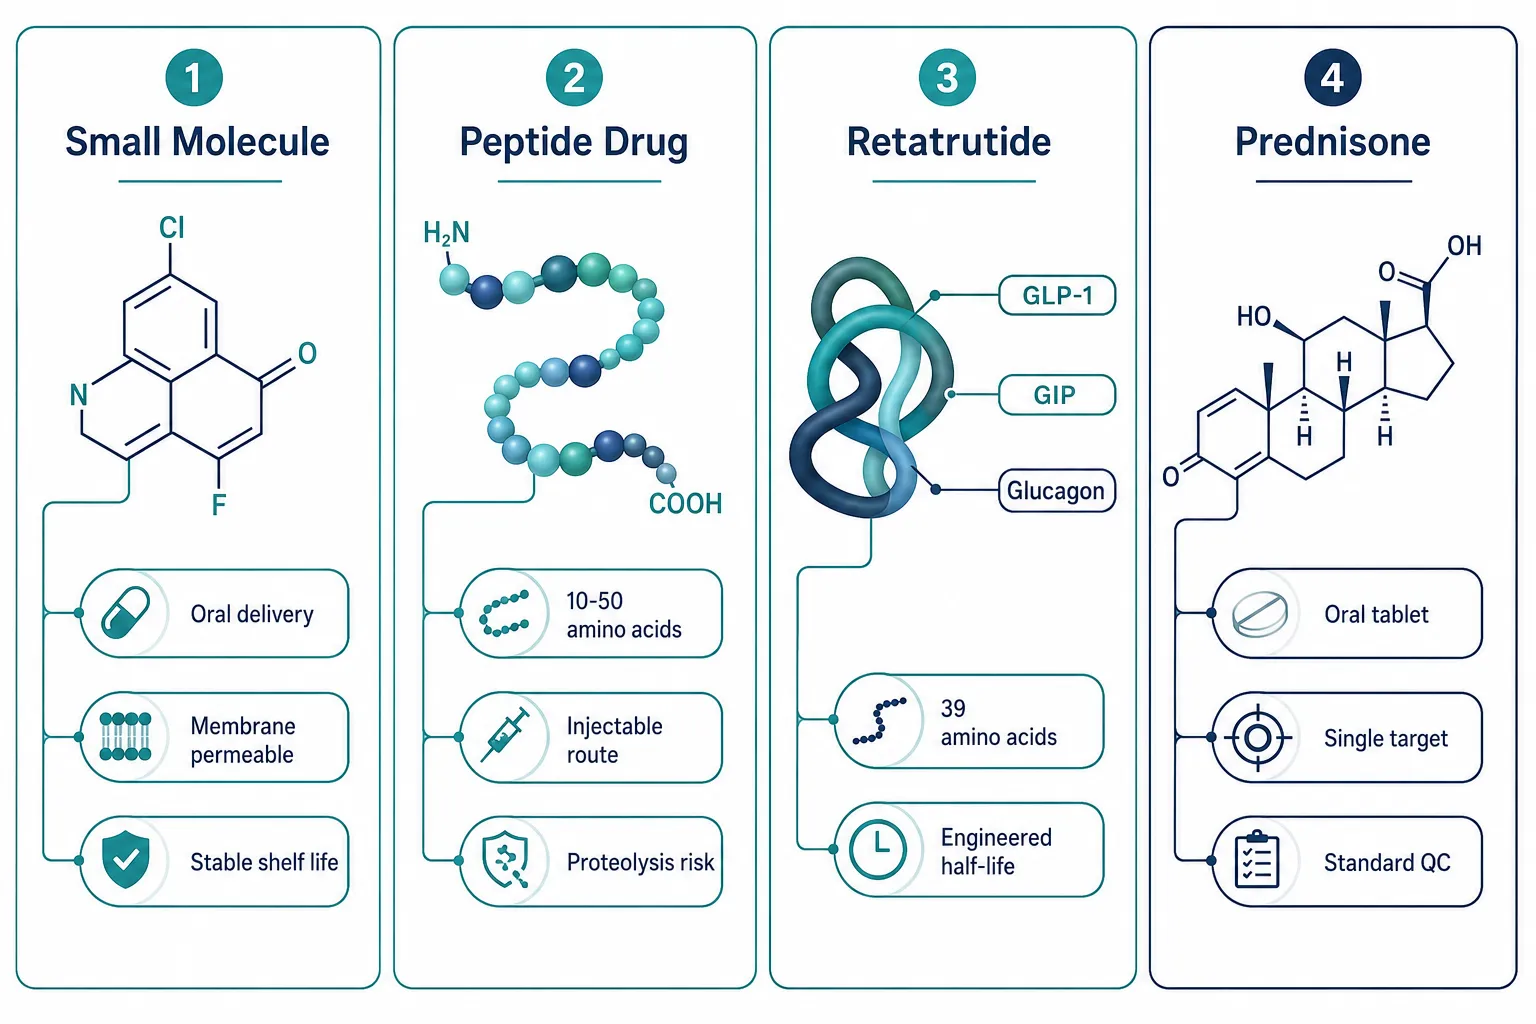
The distinction starts with molecular size and structure. Small molecules, including corticosteroids like prednisone and statins like atorvastatin, typically contain fewer than 500 daltons, cross cell membranes passively, and can be formulated as oral tablets. Their synthesis is well-understood, their shelf stability is high, and standard analytical chemistry labs handle them with ease. These properties explain why small molecules remain the backbone of most early-stage drug discovery pipelines.

Peptides are fundamentally different. Ranging from roughly 10 to 50 amino acids, they are large enough to engage complex receptor surfaces with high selectivity but small enough to be synthesized in the lab rather than expressed in cell culture like antibodies. That middle-ground position comes with trade-offs: peptides are vulnerable to proteolytic degradation, prone to aggregation and fibrillation, and generally require injectable delivery. Researchers working with lab tested peptides must invest in solid-phase synthesis equipment, HPLC-based purity analytics, and cold-chain storage that a standard small-molecule lab simply does not need.

Key structural differences at a glance:

Feature Small Molecule (e.g., Atorvastatin) Peptide (e.g., Retatrutide)
Molecular weight Under 500 Da 1,000 to 5,000+ Da
Delivery route Oral Injectable (typically)
Synthesis method Organic chemistry Solid-phase peptide synthesis
Primary stability risk Oxidation, hydrolysis Proteolysis, aggregation
Receptor engagement Single target, often Multi-target possible

AI-driven drug discovery platforms now explicitly separate peptide and small-molecule design pipelines, reinforcing that the computational infrastructure required is also distinct.

Retatrutide, MOTS-c, and 5-Amino-1MQ as Case Studies in Lab Design

Retatrutide, MOTS-c, and 5-Amino-1MQ as Case Studies in Lab Design

These three compounds illustrate the full spectrum of modern metabolic drug research and the lab demands each creates.

Retatrutide: Engineering Complexity at 39 Amino Acids

Retatrutide is a 39-amino-acid triple agonist that simultaneously activates GLP-1, GIP, and glucagon receptors. Its Phase 3 obesity data set a new efficacy benchmark, and commercial launch is widely anticipated in the mid-2026 to 2027 window, though it remains investigational. Designing research programs around retatrutide requires receptor biology expertise across three distinct pathways, engineered pharmacokinetic modeling, and multi-target assay platforms. Labs accustomed to single-target small-molecule screening must expand significantly. Teams exploring study design for peptides will find that multi-agonist compounds like retatrutide demand endpoint panels that go far beyond standard lipid or glucose readouts.

MOTS-c: Mitochondrial Biology Enters the Clinic

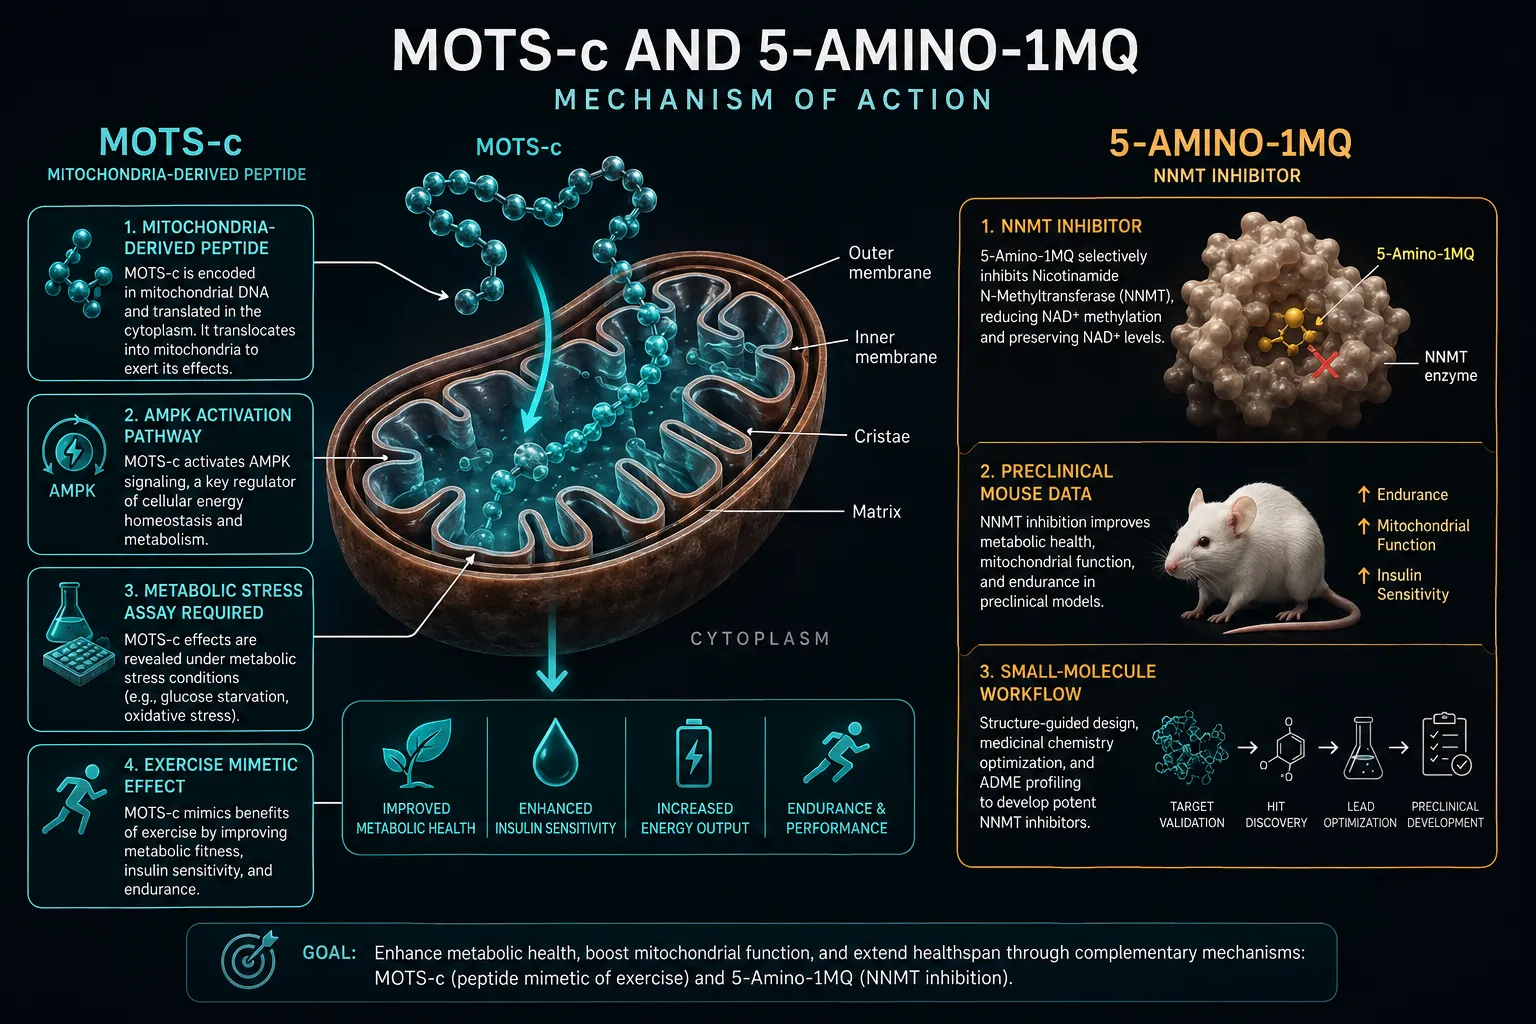
MOTS-c is a mitochondria-derived peptide that functions as an exercise mimetic by activating AMPK and related metabolic stress pathways. It has recently entered a first registered Phase 2a human trial in prediabetes, though it remains far from approval. The critical lab implication is that MOTS-c research requires mitochondrial function assays, metabolic stress platforms, and bioenergetics readouts, none of which are standard in a classic small-molecule lab. This is a meaningful infrastructure investment, not a minor adjustment.

"Mitochondria-derived peptides like MOTS-c are forcing metabolic research labs to build assay capabilities that did not exist in most facilities five years ago."

5-Amino-1MQ: Where Small-Molecule Workflows Still Lead

5-Amino-1MQ is an NNMT (nicotinamide N-methyltransferase) inhibitor with compelling preclinical data in mouse models of obesity and metabolic dysfunction. It has no human trial data yet, and its development follows a conventional small-molecule pathway. This compound is a reminder that classic workflows, organic synthesis, cell-based NNMT activity assays, standard PK profiling, still dominate early metabolic research. For labs evaluating translational research design, 5-Amino-1MQ represents the lower-infrastructure entry point compared with peptide programs.

How Peptide Programs Reshape Lab Infrastructure Compared With Prednisone and Atorvastatin

How Peptide Programs Reshape Lab Infrastructure Compared With Prednisone and Atorvastatin

The contrast becomes sharpest when comparing active peptide programs against established small-molecule drugs. Prednisone and atorvastatin are manufactured at scale with well-documented chemistry, standard QC protocols, and oral formulations that require no cold chain. Their analytical validation is straightforward.

Peptide programs demand a different stack entirely. Solid-phase peptide synthesis units, lyophilization equipment, aggregation assays, and complex PK/PD modeling software are now baseline requirements. Stability analytics must account for fibrillation and proteolysis under physiological conditions, failure modes that simply do not apply to a statin or corticosteroid.

Core lab capability gaps when transitioning from small molecules to peptides:

  • Solid-phase synthesis and purification hardware
  • Aggregation and fibrillation detection assays
  • Proteolytic stability profiling
  • Multi-receptor binding and functional assay panels
  • Cold-chain formulation and storage infrastructure
  • Advanced PK/PD modeling for multi-agonist compounds

For teams considering study design for peptide-versus-small-molecule comparative studies, these capability gaps must be mapped before protocol development begins. Researchers sourcing compounds for preclinical work should also evaluate wholesale peptides options to manage cost at scale.

The near-term outlook is clear: peptide-centric pipelines anchored by compounds like retatrutide and MOTS-c are expanding into obesity and metabolic disease, while 5-Amino-1MQ and similar NNMT inhibitors keep the small-molecule workflow relevant for early discovery. Labs that understand Peptides vs Classic Small-Molecule Drugs: How GLP-3 Retatrutide, MOTS-c, and 5-Amino-1MQ Change Lab Design Compared With Prednisone and Atorvastatin will be better positioned to allocate resources across both paradigms.

Conclusion

The divide between peptide therapeutics and classic small-molecule drugs is not merely chemical, it is operational. Retatrutide's multi-receptor complexity, MOTS-c's mitochondrial biology, and 5-Amino-1MQ's conventional NNMT-inhibitor pathway each demand a different lab configuration, and none of them map cleanly onto the infrastructure built for prednisone or atorvastatin.

Actionable next steps for research teams in 2026:

  1. Audit current lab capabilities against the peptide-specific requirements outlined above before committing to a peptide program.
  2. Prioritize solid-phase synthesis, aggregation analytics, and multi-target assay development if retatrutide or MOTS-c analogs are in the pipeline.
  3. Retain small-molecule workflows for early NNMT-inhibitor screening and compounds like 5-Amino-1MQ where oral delivery and cost efficiency matter.
  4. Build PK/PD modeling capacity that can handle multi-agonist peptide pharmacology, single-target models are insufficient.
  5. Source compounds from verified suppliers and review translational research design frameworks before finalizing study endpoints.

Labs that plan now for peptide-centric infrastructure while maintaining small-molecule competency will be best equipped for the metabolic drug landscape taking shape through 2027 and beyond.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/peptides-vs-classic-small-molecule-drugs-how-glp-3-retatrutide-mots-c-and-5-amin.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-01 13:05:112026-09-01 13:05:11Peptides vs Classic Small‑Molecule Drugs: How GLP-3 Retatrutide, MOTS-c, and 5-Amino-1MQ Change Lab Design Compared With Prednisone and Atorvastatin
Page 2 of 212

Tag Archive for: glp-1 triple agonist

Nothing Found

Sorry, no posts matched your criteria

×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top