

Retatrutide 2026 Trial Data vs Earlier Obesity Models: What Researchers Should Compare Before Drawing Conclusions
A single Phase 2 result, 24.2% mean body weight loss at 48 weeks, repositioned retatrutide as a potential turning point in obesity pharmacotherapy. Now, with the TRIUMPH program delivering Phase 3 data in 2026 and an FDA submission planned for early 2027, the research community faces a more demanding challenge: comparing these new numbers against earlier obesity models without letting headline figures obscure methodological differences that matter enormously.
Retatrutide 2026 trial data vs earlier obesity models: what researchers should compare before drawing conclusions is not simply a question of which drug produces a bigger number. It is a question of whether the numbers are even measuring the same thing across studies.
Key Takeaways
- Retatrutide is a triple agonist (GLP-1, GIP, glucagon receptors), making direct comparisons to earlier single- or dual-agonist trials structurally complex.
- TRIUMPH-1 reports up to 28-30% weight loss over 80 weeks, but population composition, baseline BMI, and trial duration differ from earlier benchmarks.
- Estimand frameworks, dose escalation schedules, and completeness of adverse-event reporting vary significantly across generations of obesity trials.
- Glycemic endpoints (A1C reduction) in TRIUMPH-2 require careful alignment with earlier diabetic-population studies before conclusions are drawn.
- A transparent comparison framework covering at least seven variables is essential before any cross-trial efficacy claim holds scientific weight.
Why the Comparison Problem Is Harder Than It Looks
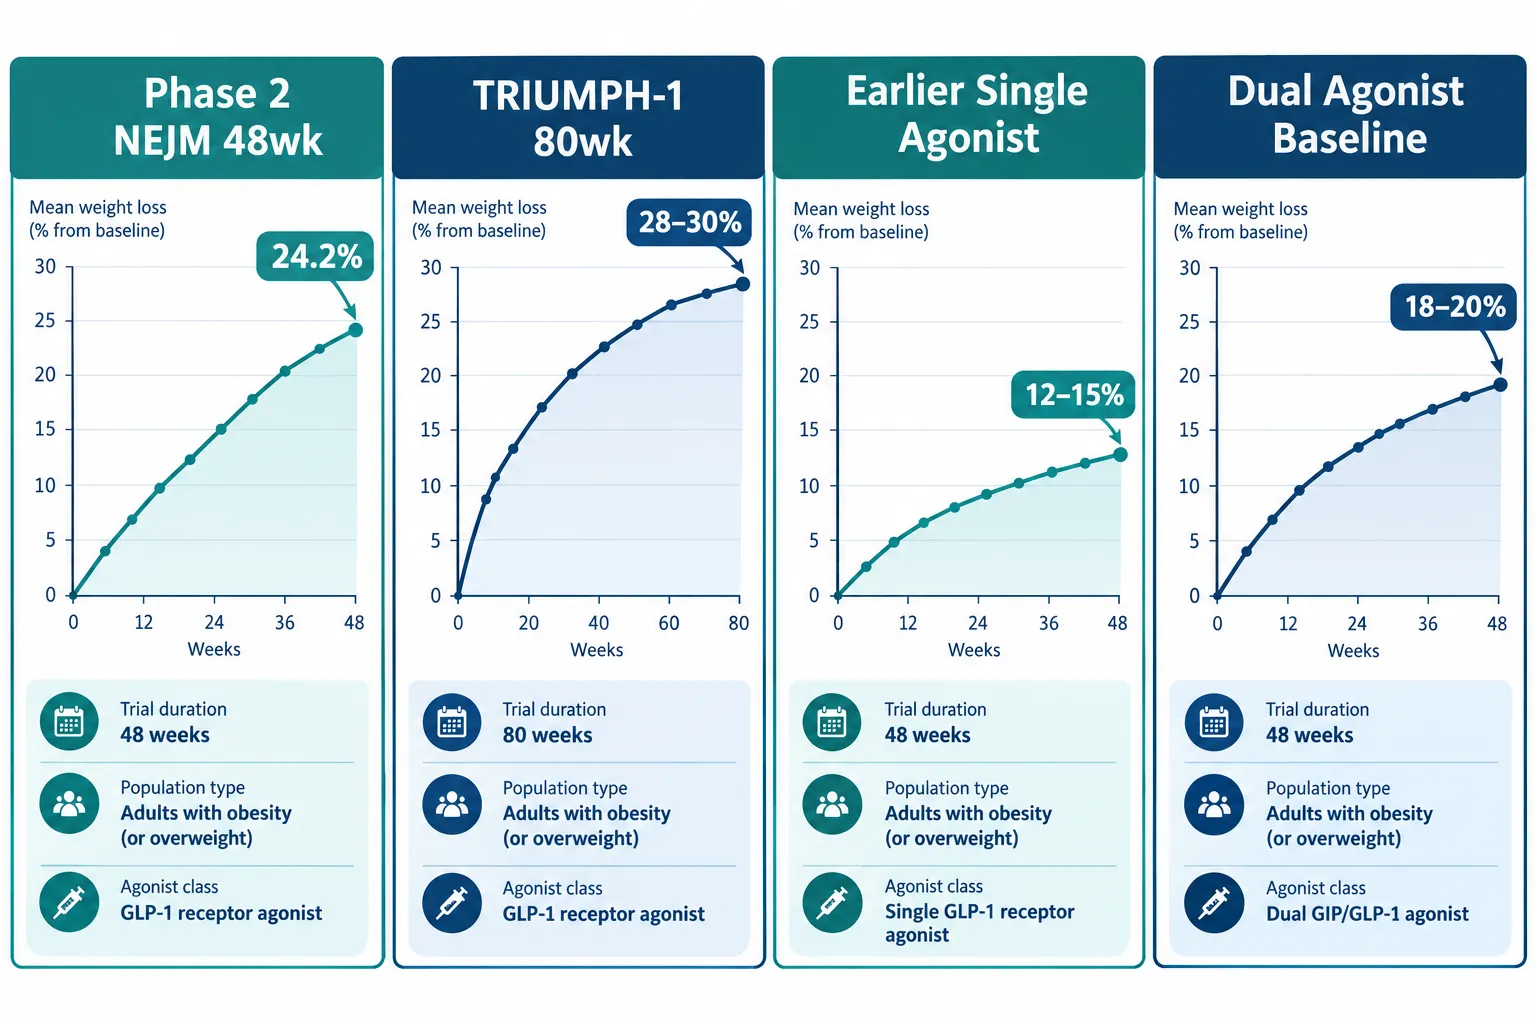
The excitement around retatrutide is understandable. The TRIUMPH-1 trial, targeting non-diabetic adults with obesity or overweight, reported weight reductions approaching 28-30% over 80 weeks, figures that have drawn frequent comparisons to bariatric surgery outcomes. TRIUMPH-2 extended the analysis to people with type 2 diabetes, and TRIUMPH-3 enrolled participants with severe obesity and established cardiovascular disease. A global registration trial completed enrollment in late 2025, broadening the population further.
Earlier obesity pharmacotherapy trials, including those for semaglutide and tirzepatide, ran for 68 weeks in many pivotal designs, enrolled populations with somewhat different baseline BMI distributions, and used dose escalation schedules that do not map cleanly onto retatrutide's protocol. Researchers exploring retatrutide clinical trial data will quickly notice that the surface-level weight-loss percentages are not the only variable worth examining.
Seven variables that demand alignment before cross-trial comparison:
| Variable | Why It Matters |
|---|---|
| Population baseline BMI | Higher baseline BMI inflates absolute kg lost |
| Trial duration (weeks) | Longer trials favor plateau-resistant compounds |
| Estimand framework | Defines how dropouts and discontinuations are handled |
| Dose escalation schedule | Steeper escalation can accelerate early weight loss |
| Completeness of AE reporting | Affects tolerability profile comparisons |
| Glycemic endpoints (A1C) | Critical for diabetic-population sub-analyses |
| Completers vs ITT analysis | Changes the denominator and the headline figure |
"A 30% weight loss figure means very little in isolation. The population, the protocol, and the statistical framework are the context that gives the number meaning."
Mechanism Differences That Complicate Direct Comparisons
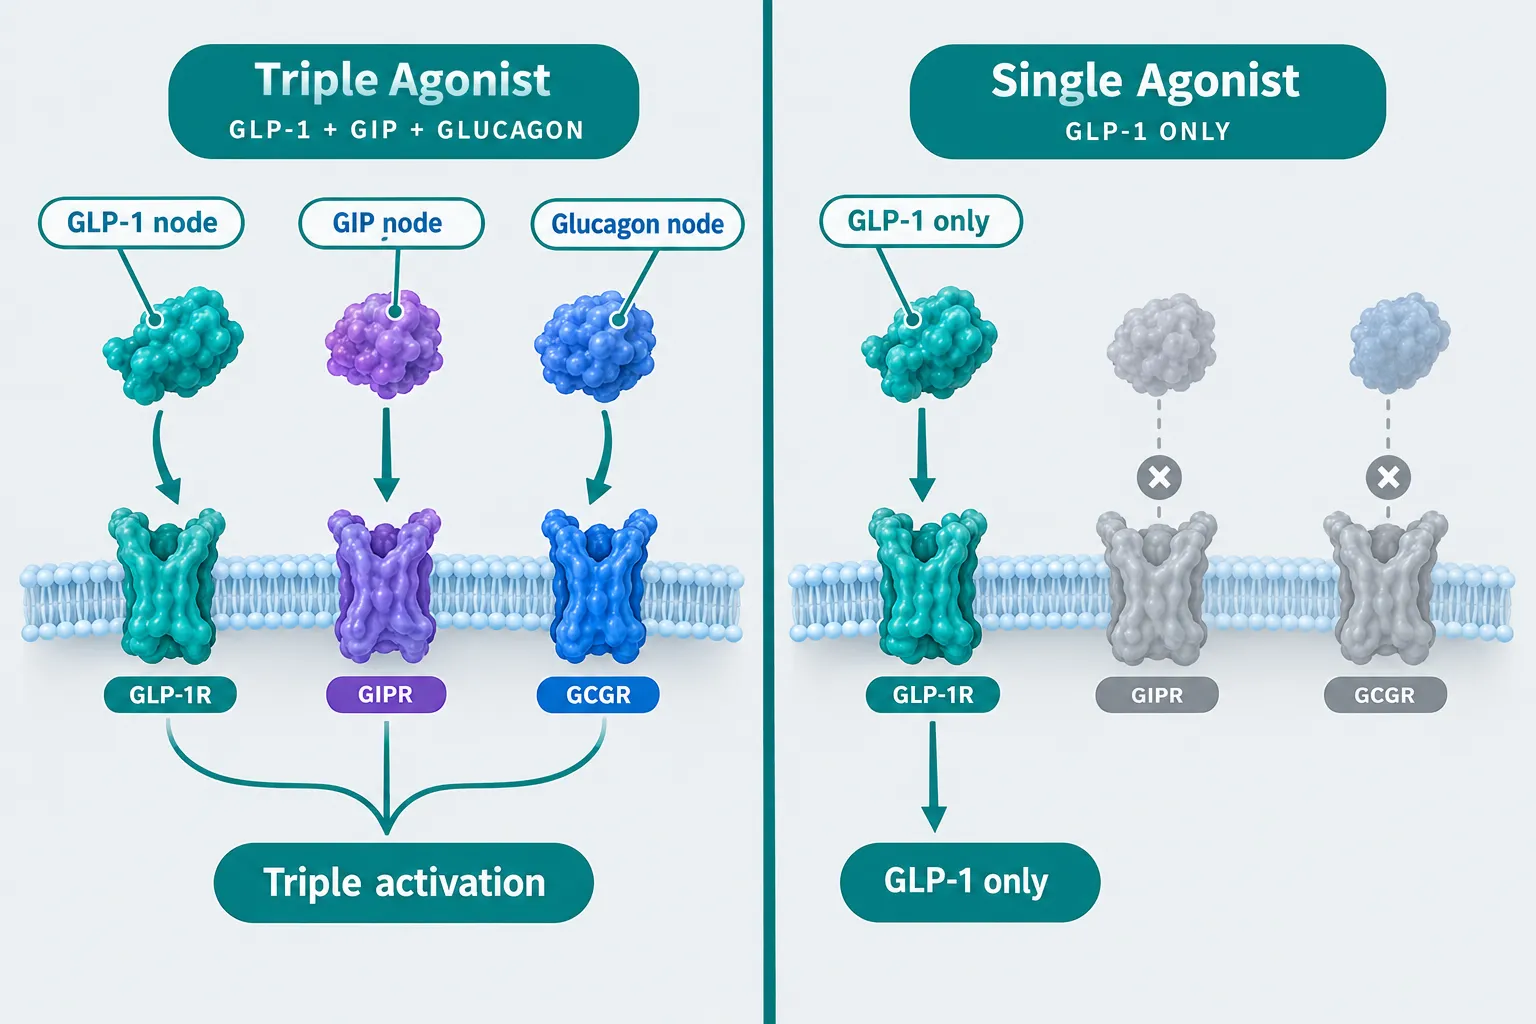
Retatrutide is a triple agonist, activating GLP-1, GIP, and glucagon receptors simultaneously. Earlier approved agents in this space are single agonists (GLP-1 only) or dual agonists (GLP-1 and GIP). This mechanistic distinction is not merely academic, it directly affects which endpoints are most informative and which adverse-event profiles are expected.
Glucagon receptor activation drives additional energy expenditure and lipolysis pathways that are absent in earlier models. This means that comparing retatrutide's weight-loss magnitude against a GLP-1 monotherapy trial without accounting for the additional metabolic burden on participants is methodologically incomplete. Researchers interested in the GLP-3 Reta product tag context will recognize that the triple-agonist classification is central to understanding why the efficacy signal appears larger.
Key mechanistic comparison points:
- GLP-1 component: Shared with earlier agents; allows partial endpoint alignment on nausea, satiety, and gastric motility outcomes.
- GIP component: Shared with tirzepatide; permits limited dual-agonist comparison, but retatrutide's GIP binding affinity differs.
- Glucagon component: Unique to retatrutide in this class; drives hepatic fat reduction and thermogenesis outcomes not tracked in earlier trial designs.
For researchers also examining peptides with distinct metabolic profiles, the Tesamorelin science and sourcing overview offers a useful reference point for understanding how growth-hormone-releasing peptides address visceral fat through a separate mechanism, underscoring why mechanism-first framing matters in any comparative analysis.
Building a Transparent Framework for Cross-Trial Analysis
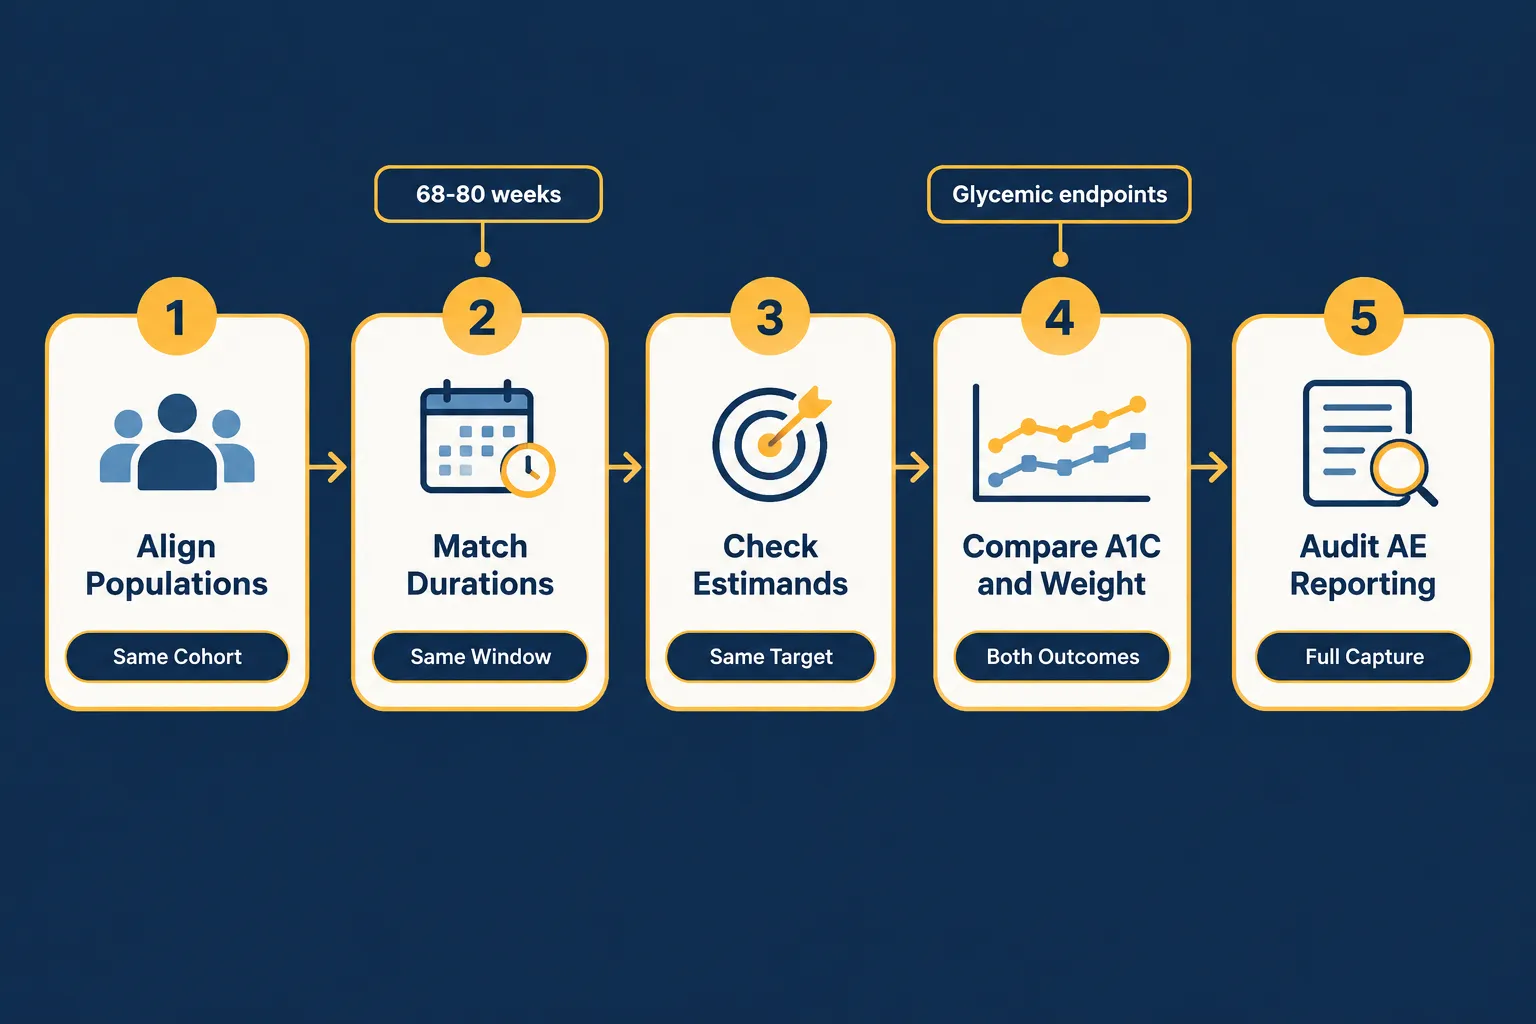
Retatrutide 2026 trial data vs earlier obesity models: what researchers should compare before drawing conclusions comes down to a structured, reproducible framework rather than selective headline matching. The following steps reflect best practice for cross-generational obesity trial comparison.
Step 1, Align populations. Confirm that baseline BMI, diabetes status, cardiovascular comorbidity burden, and geographic distribution are comparable. TRIUMPH-3's cardiovascular-disease population is not equivalent to a general overweight cohort.
Step 2, Match or adjust for duration. TRIUMPH-1's 80-week window exceeds the 68-week standard used in several earlier pivotal trials. Annualized weight-loss rates provide a more honest cross-trial metric than raw endpoint figures.
Step 3, Examine estimands explicitly. The treatment policy estimand (which includes all participants regardless of discontinuation) and the hypothetical estimand (which models outcomes assuming full adherence) produce materially different results. Earlier trials varied in which they pre-specified as primary.
Step 4, Compare A1C and glycemic outcomes in matched populations. TRIUMPH-2 data on weight and glycemic outcomes in type 2 diabetes must be benchmarked only against earlier trials that enrolled comparable diabetic populations with similar baseline A1C ranges.
Step 5, Audit adverse-event completeness. Gastrointestinal adverse events are consistently reported across generations, but cardiovascular safety signals, injection-site reactions, and lean mass loss data have not been uniformly collected. Retatrutide's glucagon component introduces a hepatic safety dimension that earlier single-agonist trial protocols did not systematically monitor.
Researchers building stacks or combination protocols may also find value in reviewing the IPA Sermorelin stack research resource for context on how multi-peptide frameworks are evaluated in research settings, and the SS-31 mitochondrial research tag for parallel work on metabolic and mitochondrial endpoints that may become relevant as retatrutide's full metabolic profile is characterized.
For researchers seeking the compound itself for preclinical work, the Reta 20mg product page provides sourcing details relevant to laboratory use.
Conclusion
The TRIUMPH program represents a genuine advance in obesity pharmacotherapy research, and the 2026 data deserve serious scientific attention. But the value of that data depends entirely on how carefully it is contextualized against earlier obesity models.
Actionable next steps for researchers:
- Build a comparison table that explicitly lists population baseline characteristics, trial duration, estimand type, and primary endpoint definition for each study being compared.
- Separate efficacy comparisons by population subgroup, non-diabetic, type 2 diabetes, and high-cardiovascular-risk cohorts require distinct reference studies.
- Request or locate full adverse-event appendices, not just summary tables, before drawing tolerability conclusions.
- Apply annualized weight-loss rates as a normalized cross-trial metric rather than relying on raw endpoint percentages.
- Track the FDA submission timeline (currently planned for Q1 2027) and review any agency briefing documents for additional population and estimand disclosures.
Retatrutide 2026 trial data vs earlier obesity models: what researchers should compare before drawing conclusions is ultimately a call for methodological discipline. The numbers are impressive, but the framework used to evaluate them will determine whether the conclusions hold.


Leave a Reply
Want to join the discussion?Feel free to contribute!