Retatrutide Phase 3 Obesity Trial Data Updates: Triple Incretin Mechanism Analysis for 2026 Protocols
Nearly one billion adults worldwide live with obesity, and for decades, no pharmacological agent came close to matching the weight reduction achieved by bariatric surgery. That benchmark is now being challenged. The Retatrutide Phase 3 Obesity Trial Data Updates: Triple Incretin Mechanism Analysis for 2026 Protocols represents a pivotal moment in metabolic medicine, with topline results from the TRIUMPH program reshaping how researchers and clinicians think about next-generation weight management strategies.
Key Takeaways
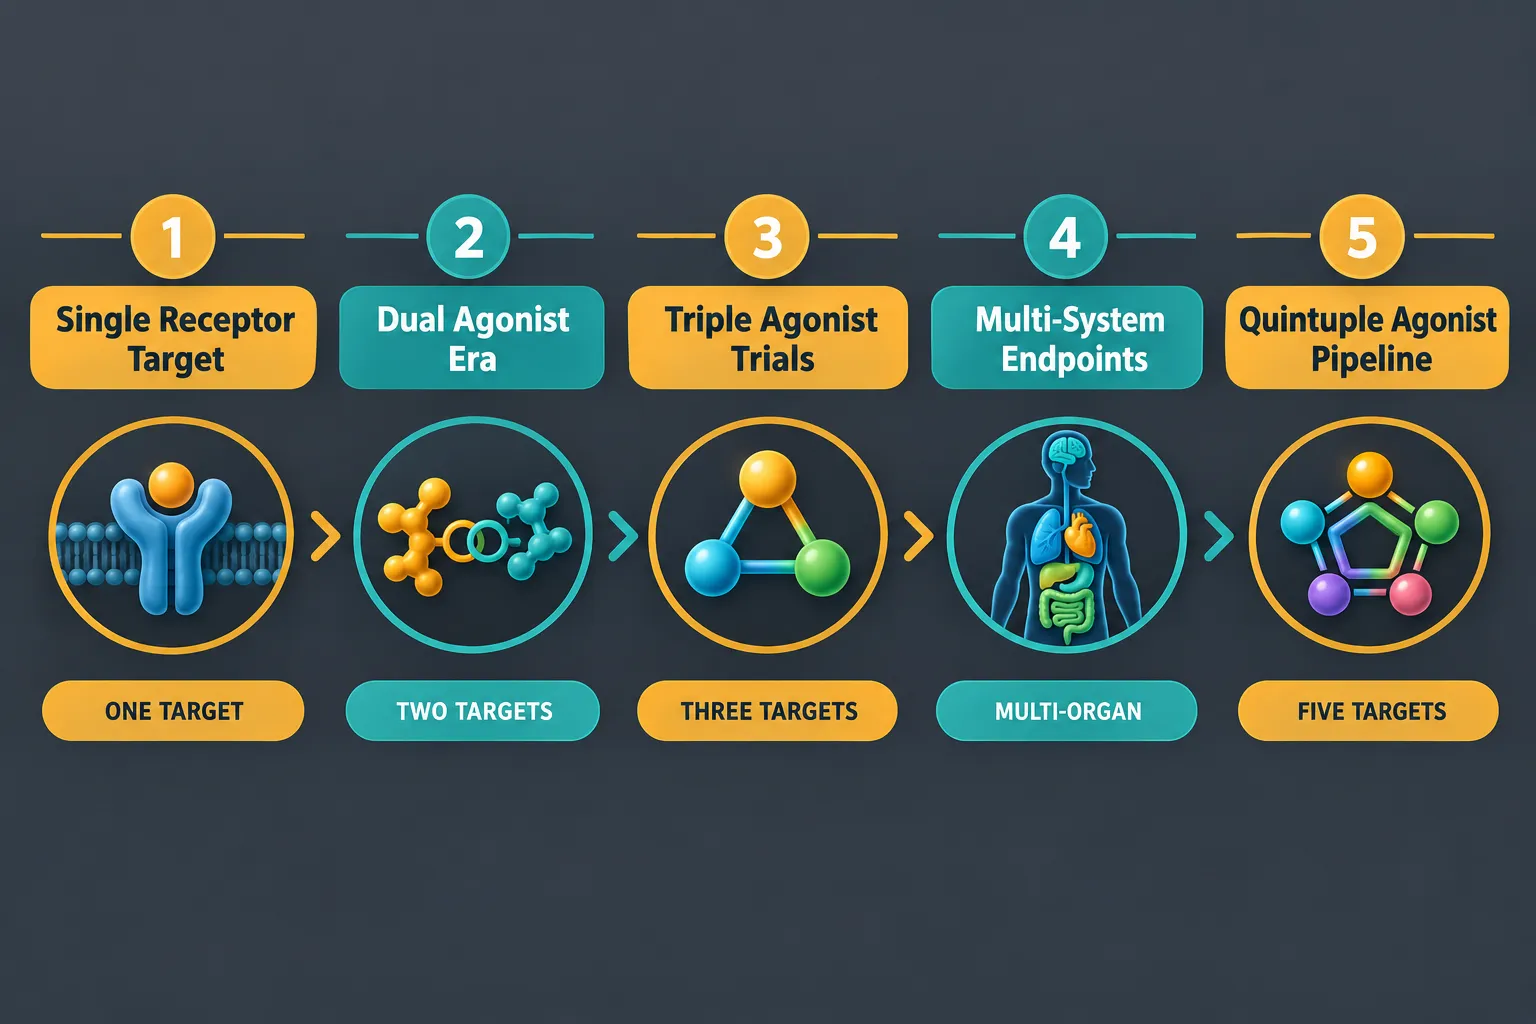
- Retatrutide is the first triple incretin agonist, targeting GLP-1, GIP, and glucagon receptors simultaneously, to reach large-scale Phase 3 evaluation.
- TRIUMPH-1 topline data released May 2026 showed up to approximately 30% body weight reduction over two years at the highest dose.
- The TRIUMPH program spans obesity, type 2 diabetes, sleep apnea, osteoarthritis, cardiovascular, and liver outcomes.
- Titration protocols emerging from TRIUMPH-1 are informing 2026 laboratory research models and preclinical study designs.
- Retatrutide sets a new comparative efficacy benchmark against existing dual incretin therapies such as tirzepatide.
Understanding the Triple Incretin Mechanism Behind 2026 Protocol Design
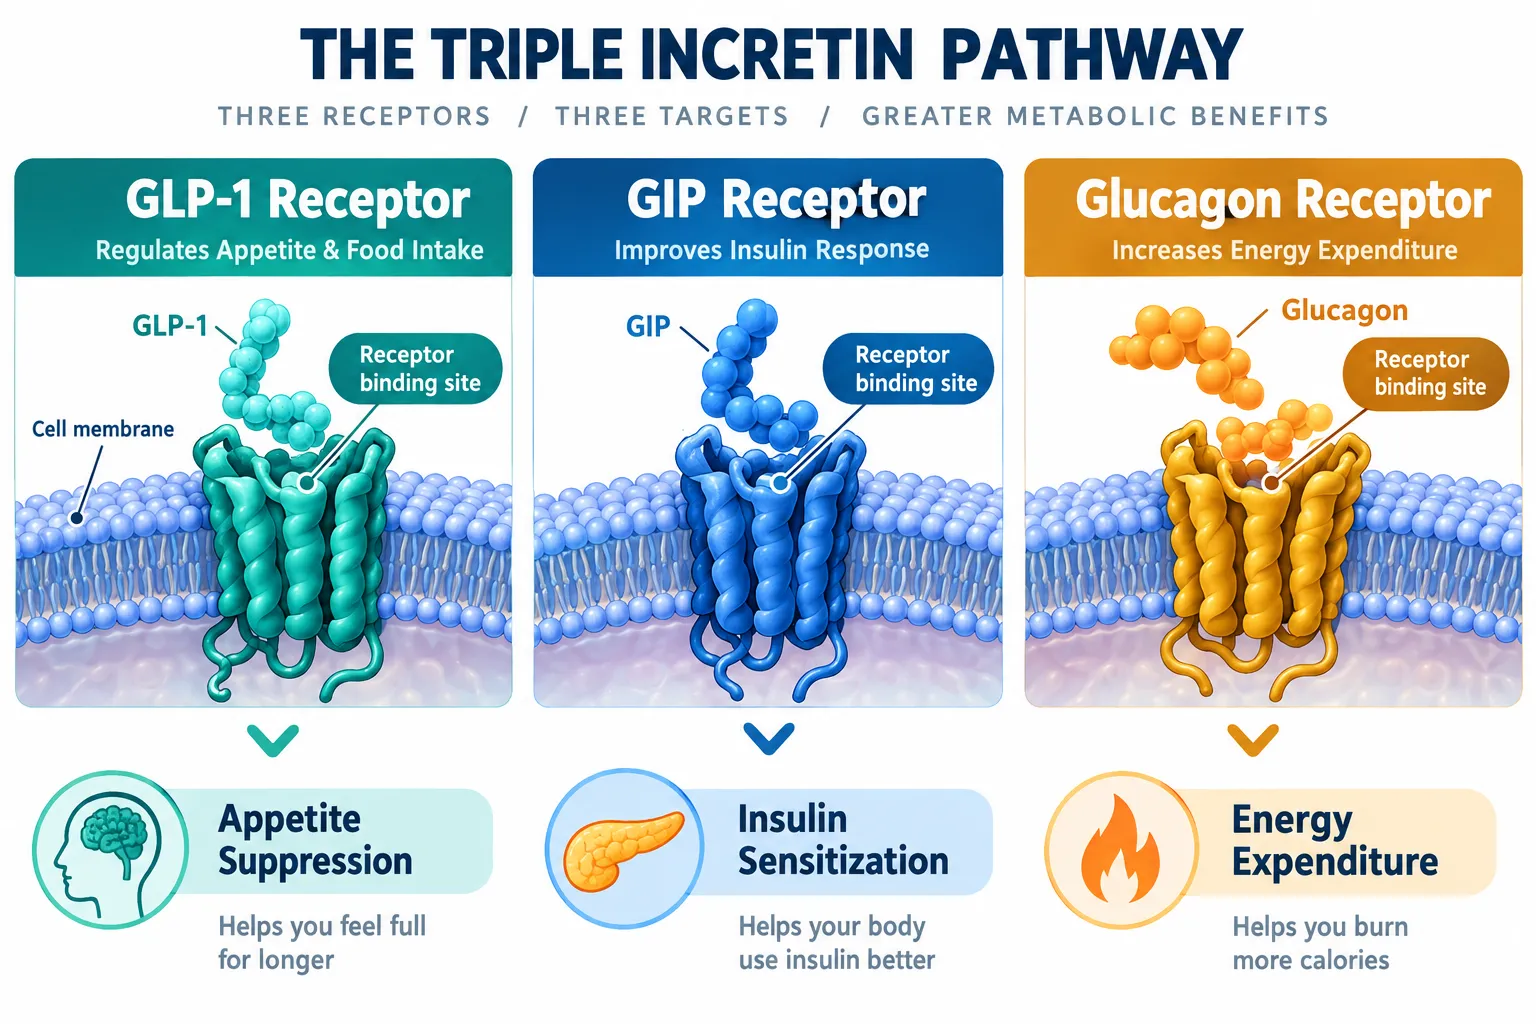
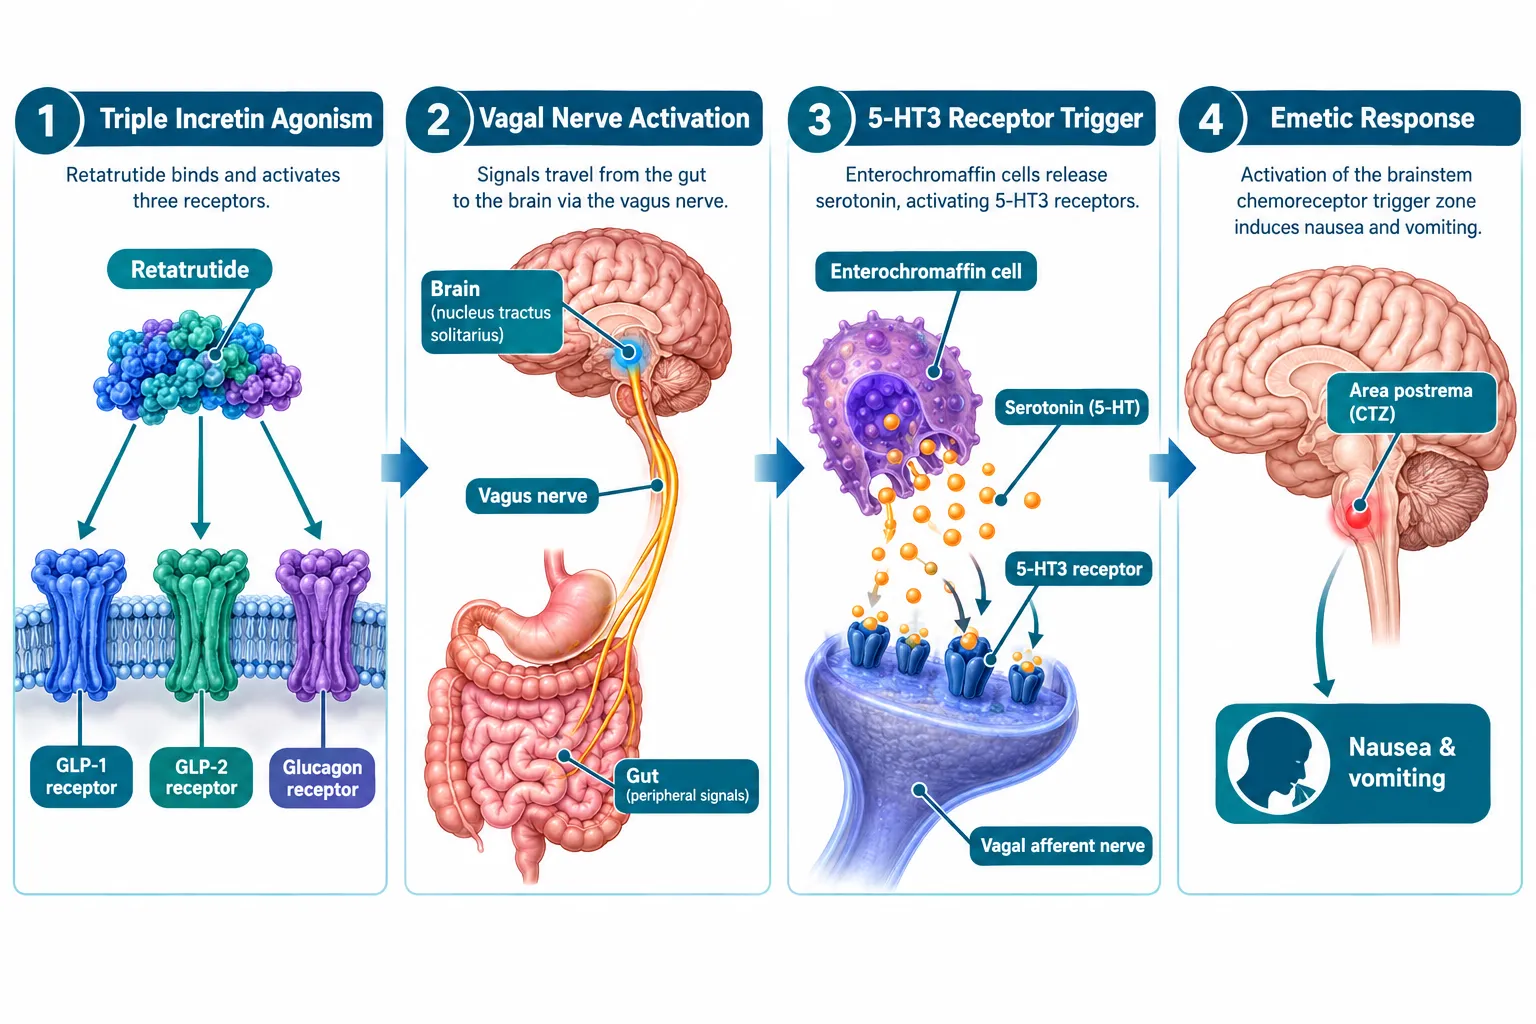
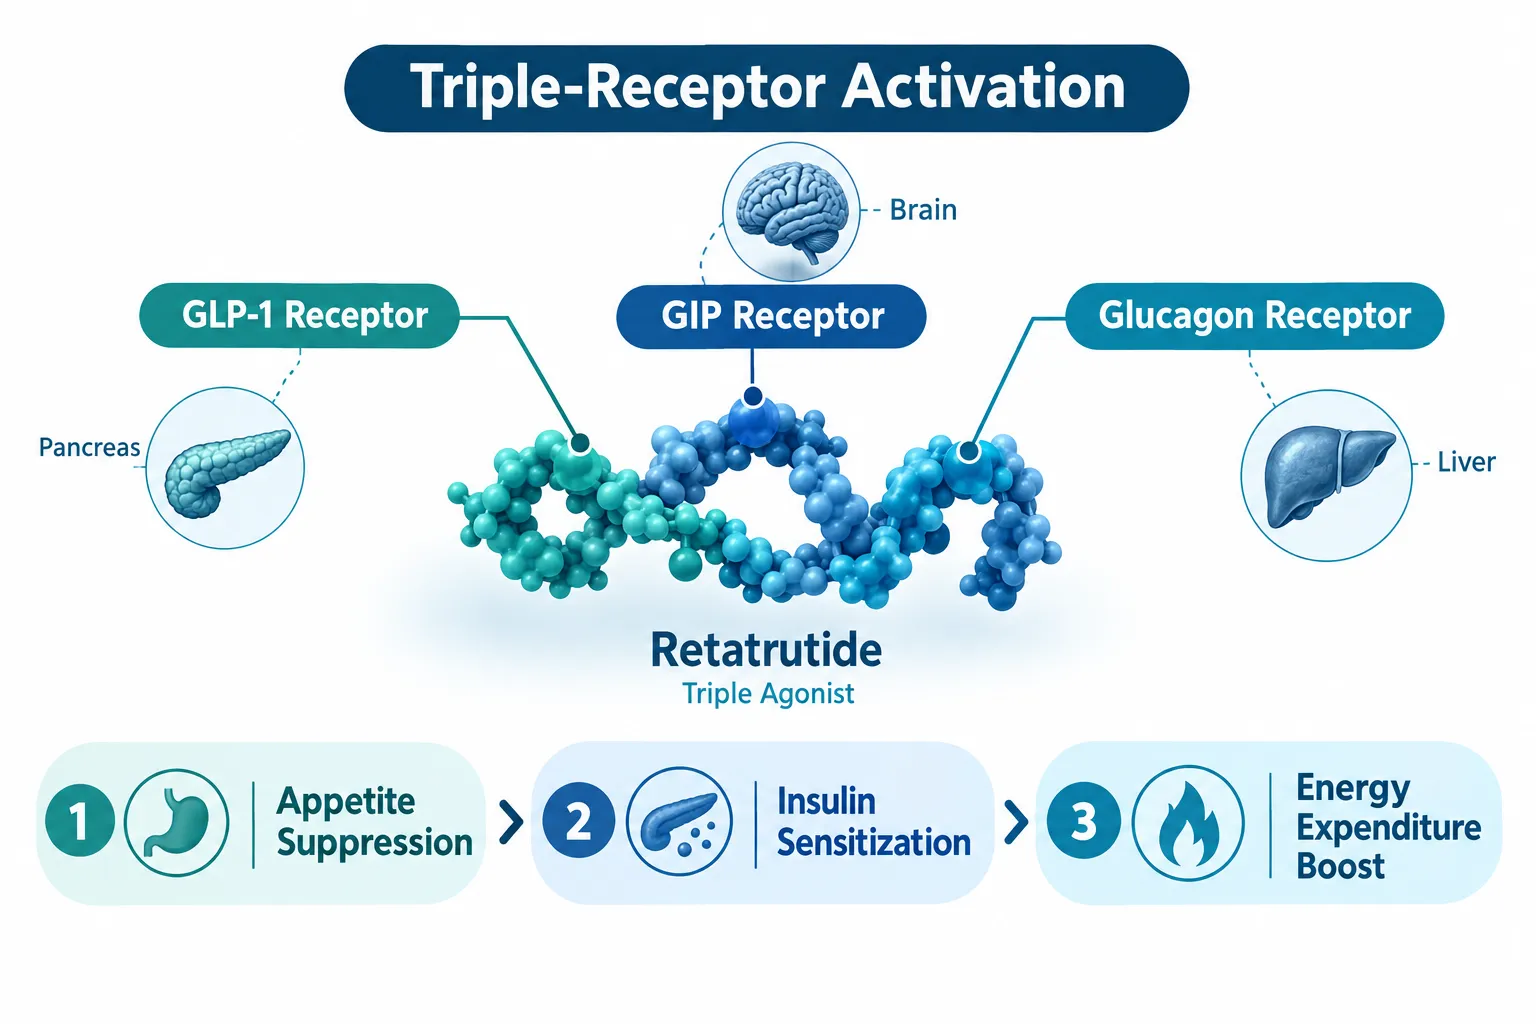
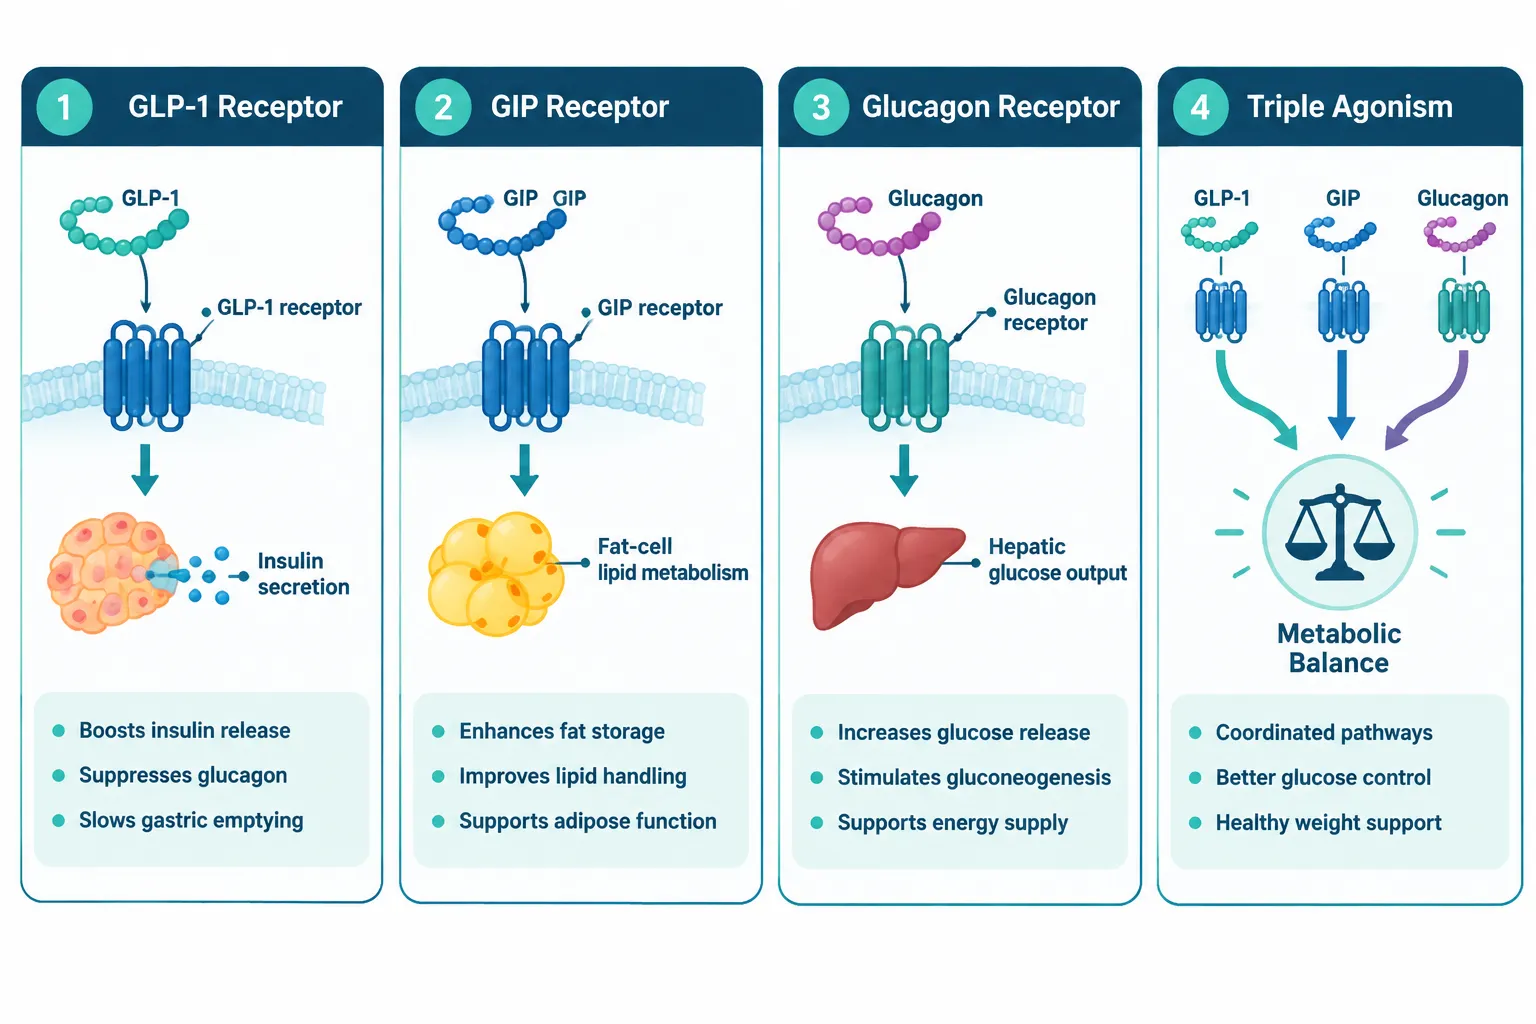
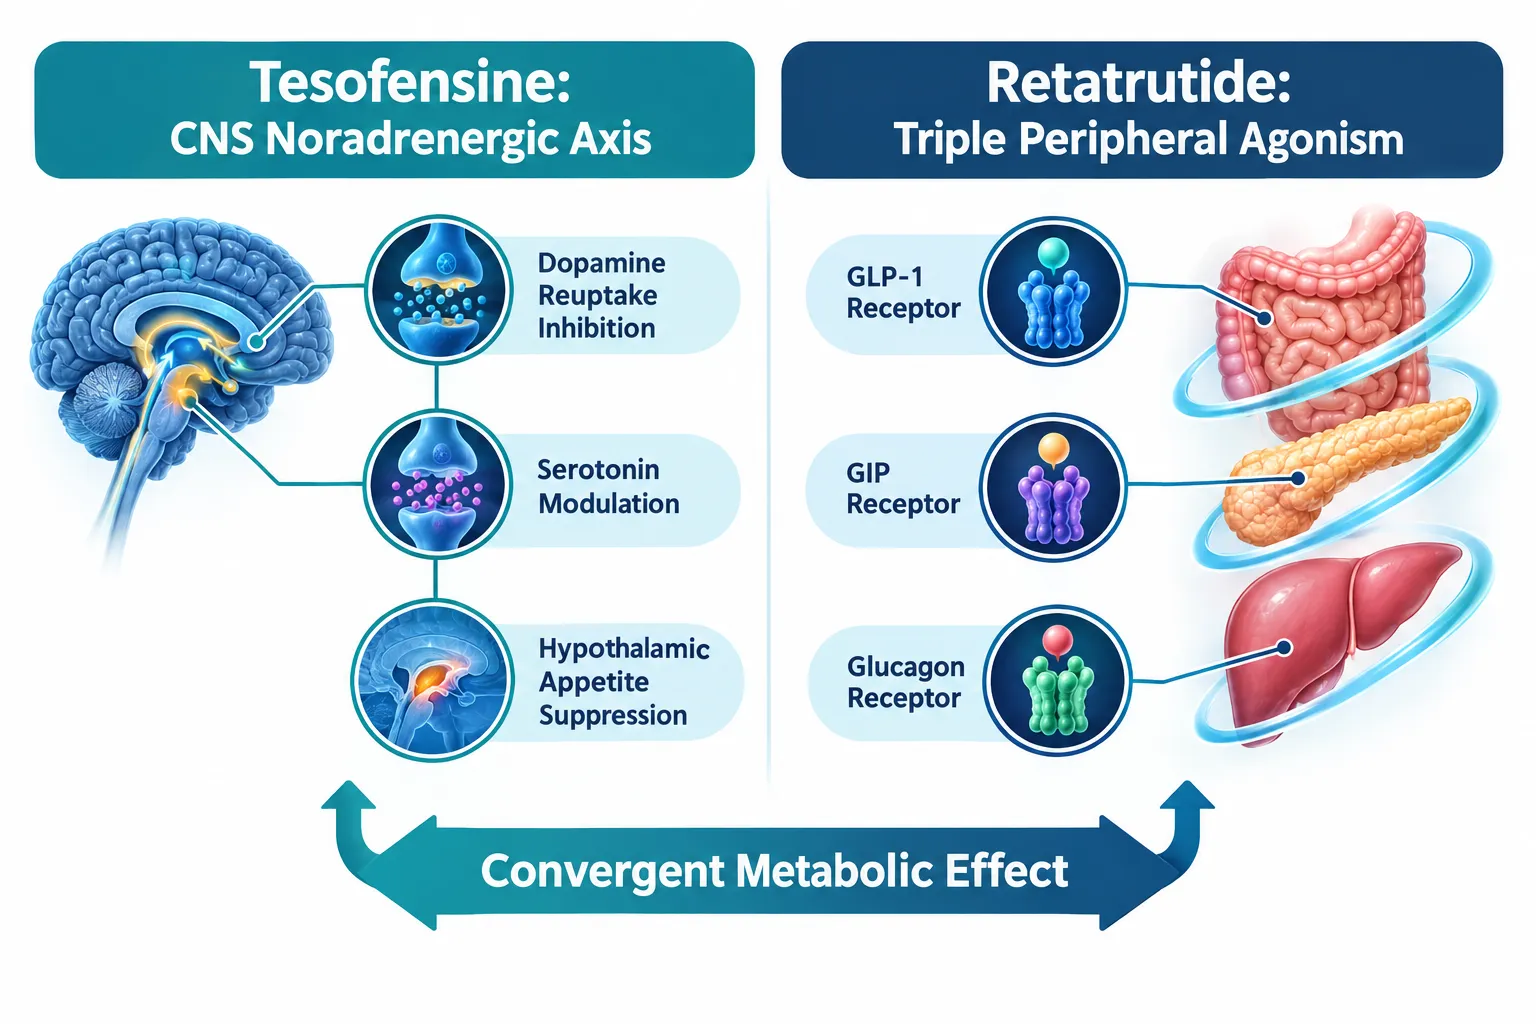
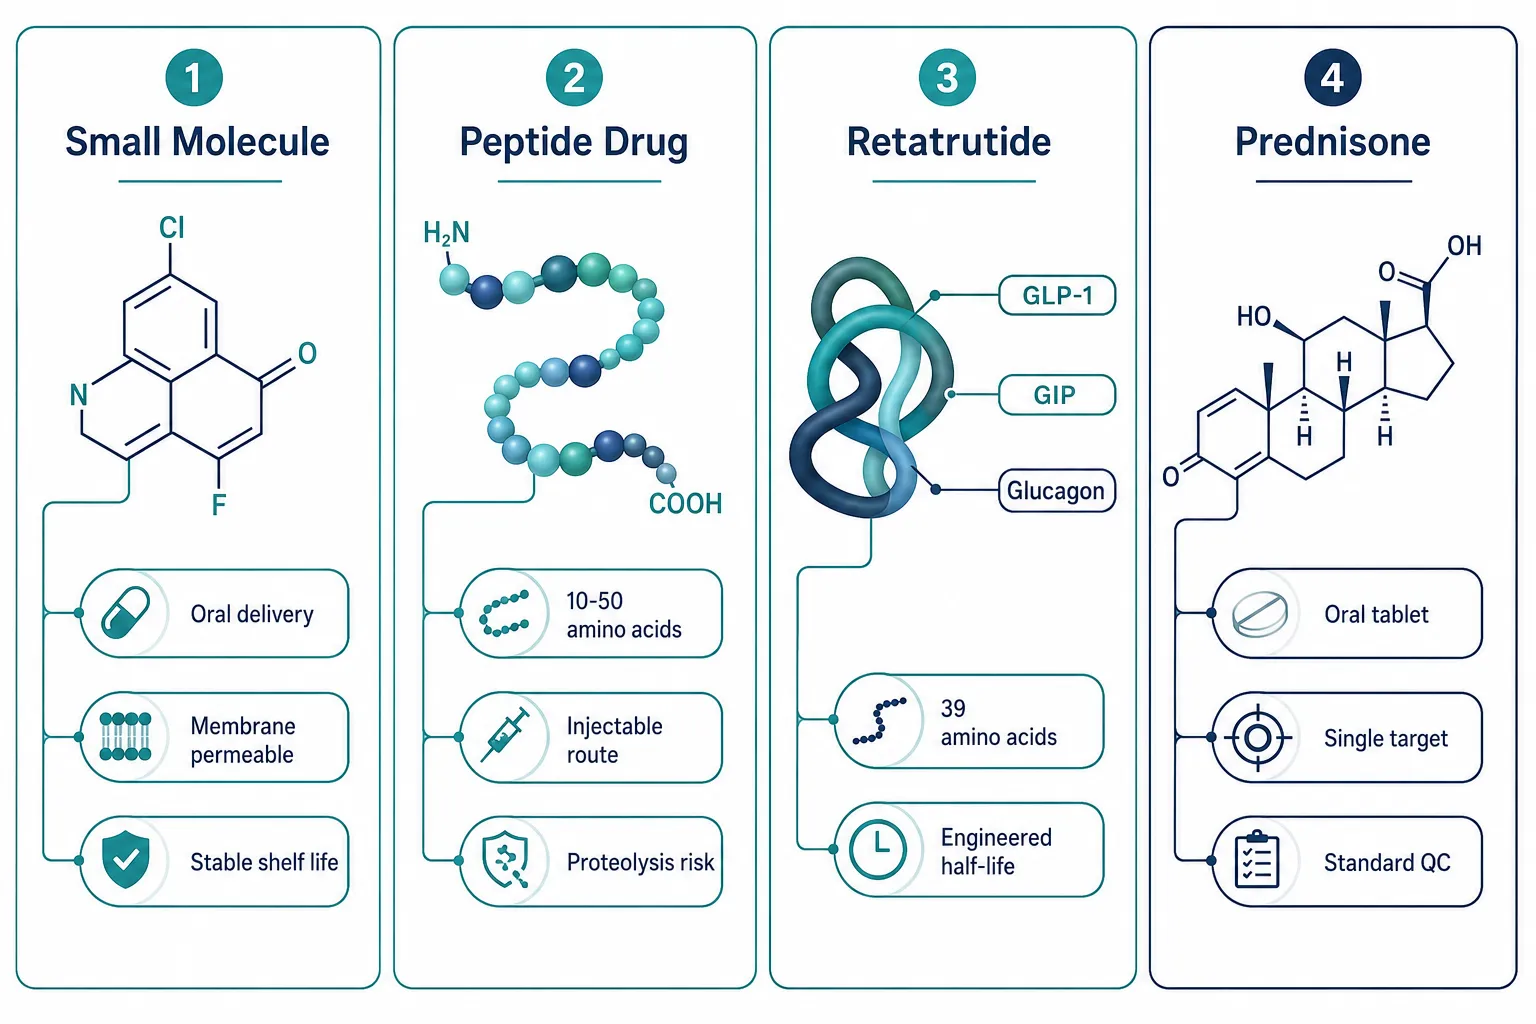
Retatrutide's pharmacological profile is built on simultaneous agonism at three distinct receptors. Understanding this tri-receptor architecture is essential for interpreting the Retatrutide Phase 3 Obesity Trial Data Updates: Triple Incretin Mechanism Analysis for 2026 Protocols in a meaningful way.
The three receptor targets work in coordinated synergy:
| Receptor | Primary Metabolic Role | Contribution to Weight Loss |
|---|---|---|
| GLP-1 | Appetite suppression, gastric emptying | Reduces caloric intake |
| GIP | Insulin sensitization, fat metabolism | Enhances glucose disposal |
| Glucagon | Energy expenditure, hepatic glucose output | Increases caloric burn |
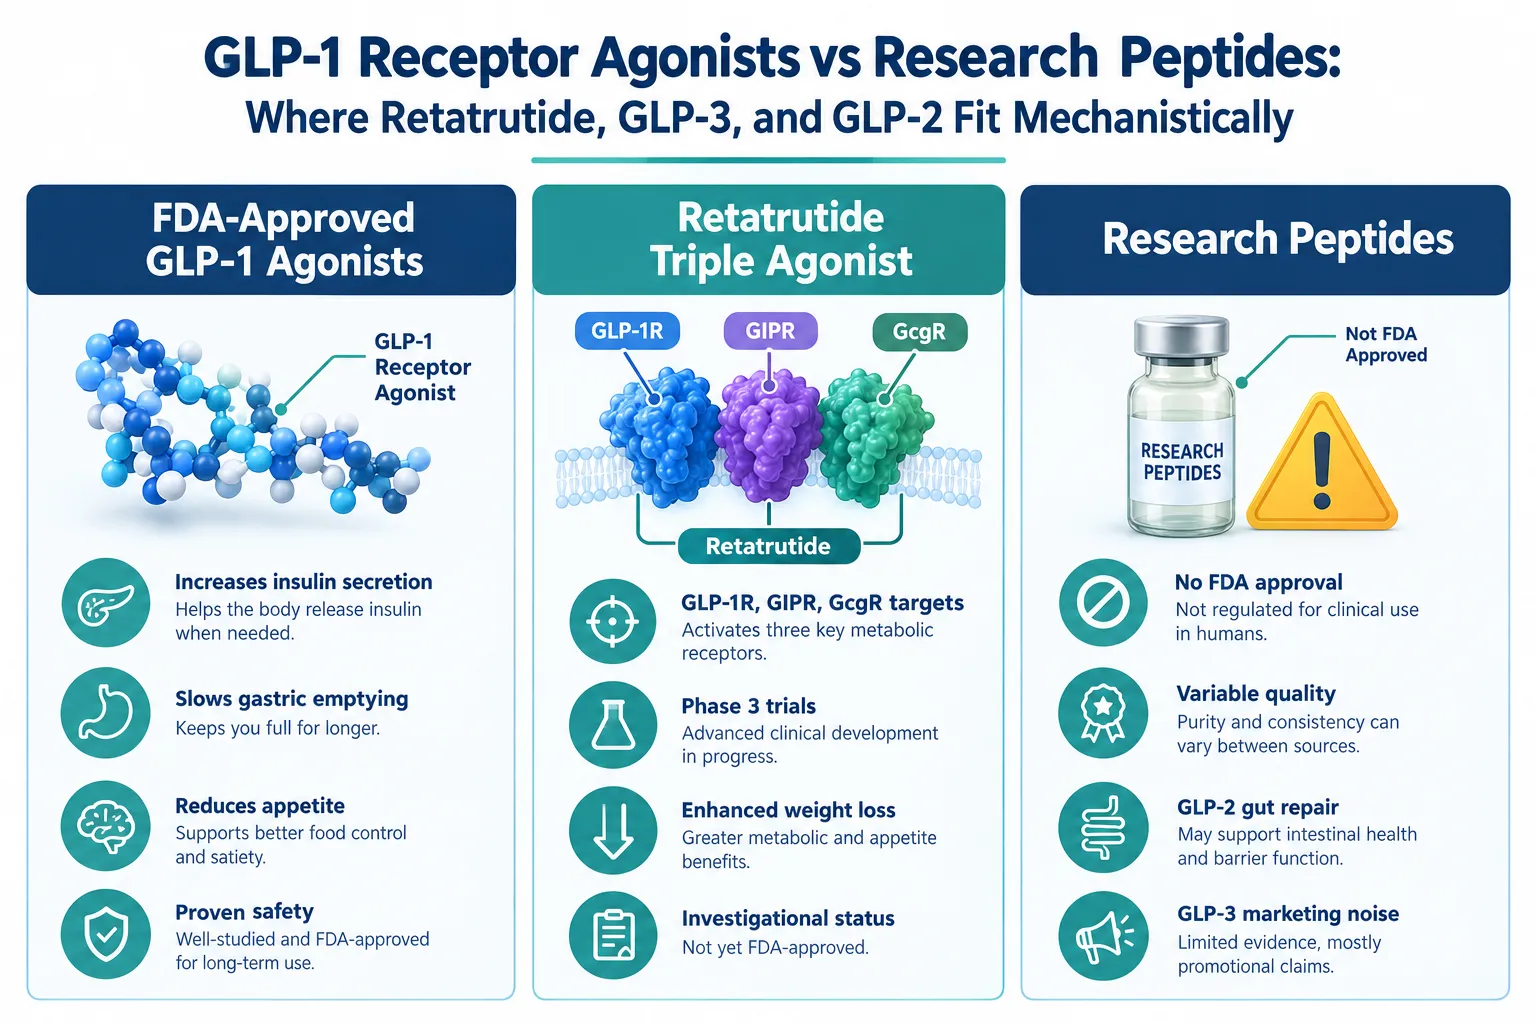
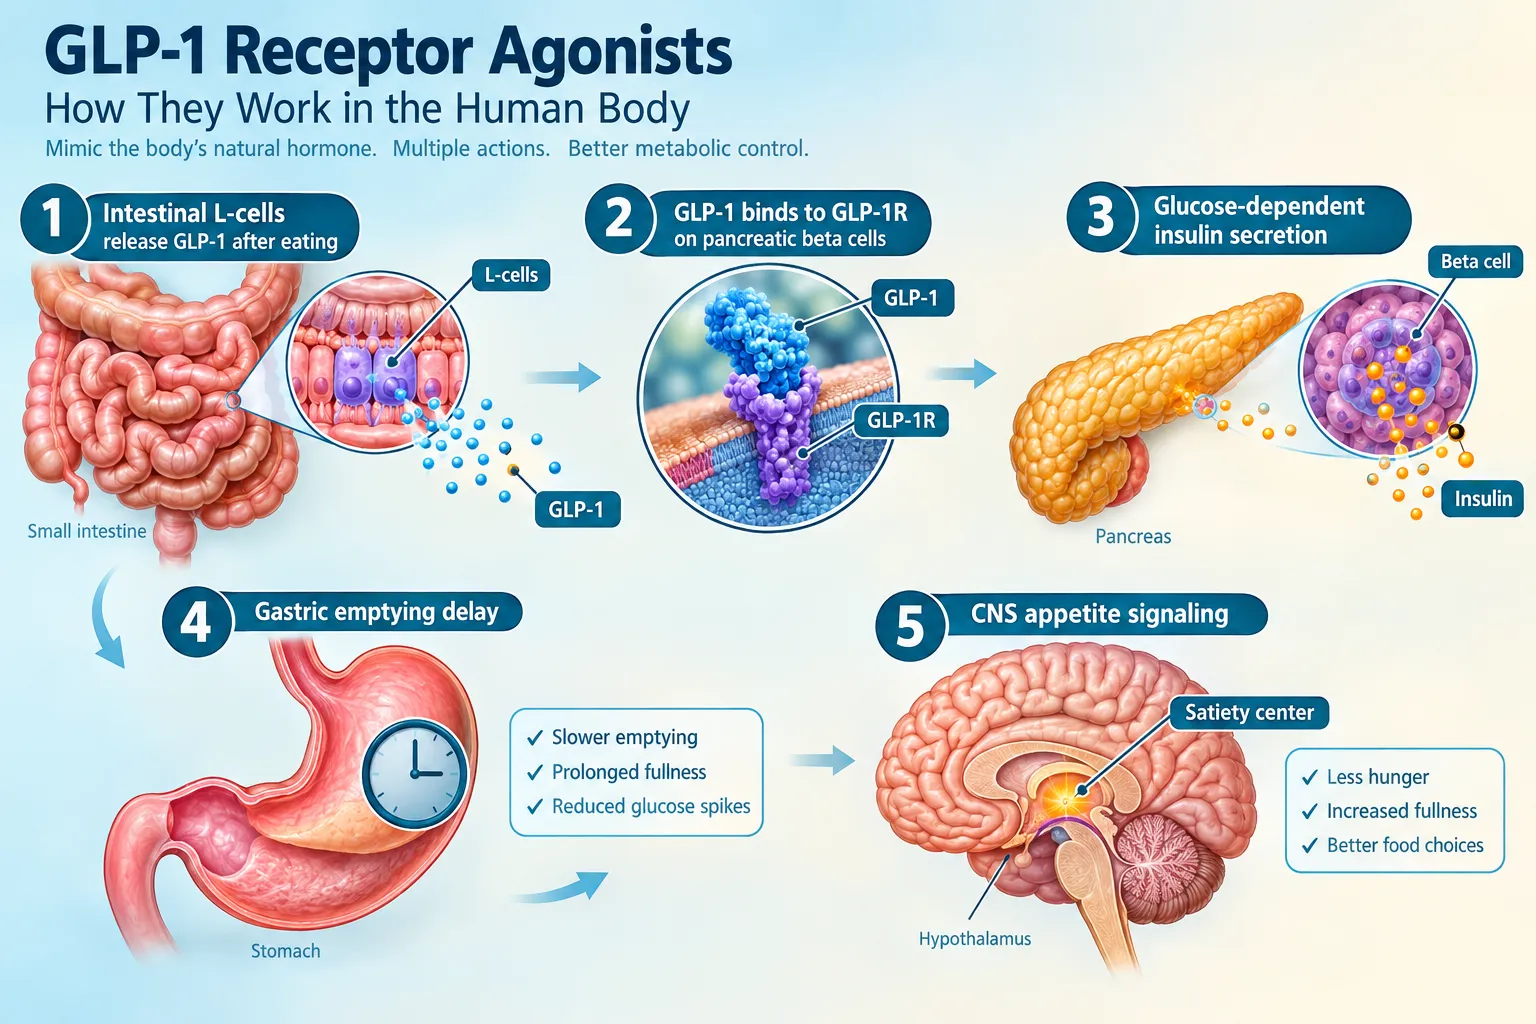
Where GLP-1 receptor agonists like semaglutide act on a single pathway, and tirzepatide engages two, retatrutide's glucagon component adds a thermogenic dimension. This third axis drives energy expenditure independent of caloric restriction, a mechanistic advantage that researchers are now incorporating into cardiometabolic peptide research models.
The glucagon receptor component also accelerates hepatic fat clearance, making retatrutide particularly relevant for metabolic dysfunction-associated steatotic liver disease (MASLD) endpoints now embedded in the TRIUMPH program.
For researchers sourcing compounds for preclinical models, GLP-3 Reta CAG 10mg represents one formulation used in controlled laboratory settings to study this tri-agonist activity.
TRIUMPH Program: Phase 3 Trial Data Updates Across Six Indication Areas
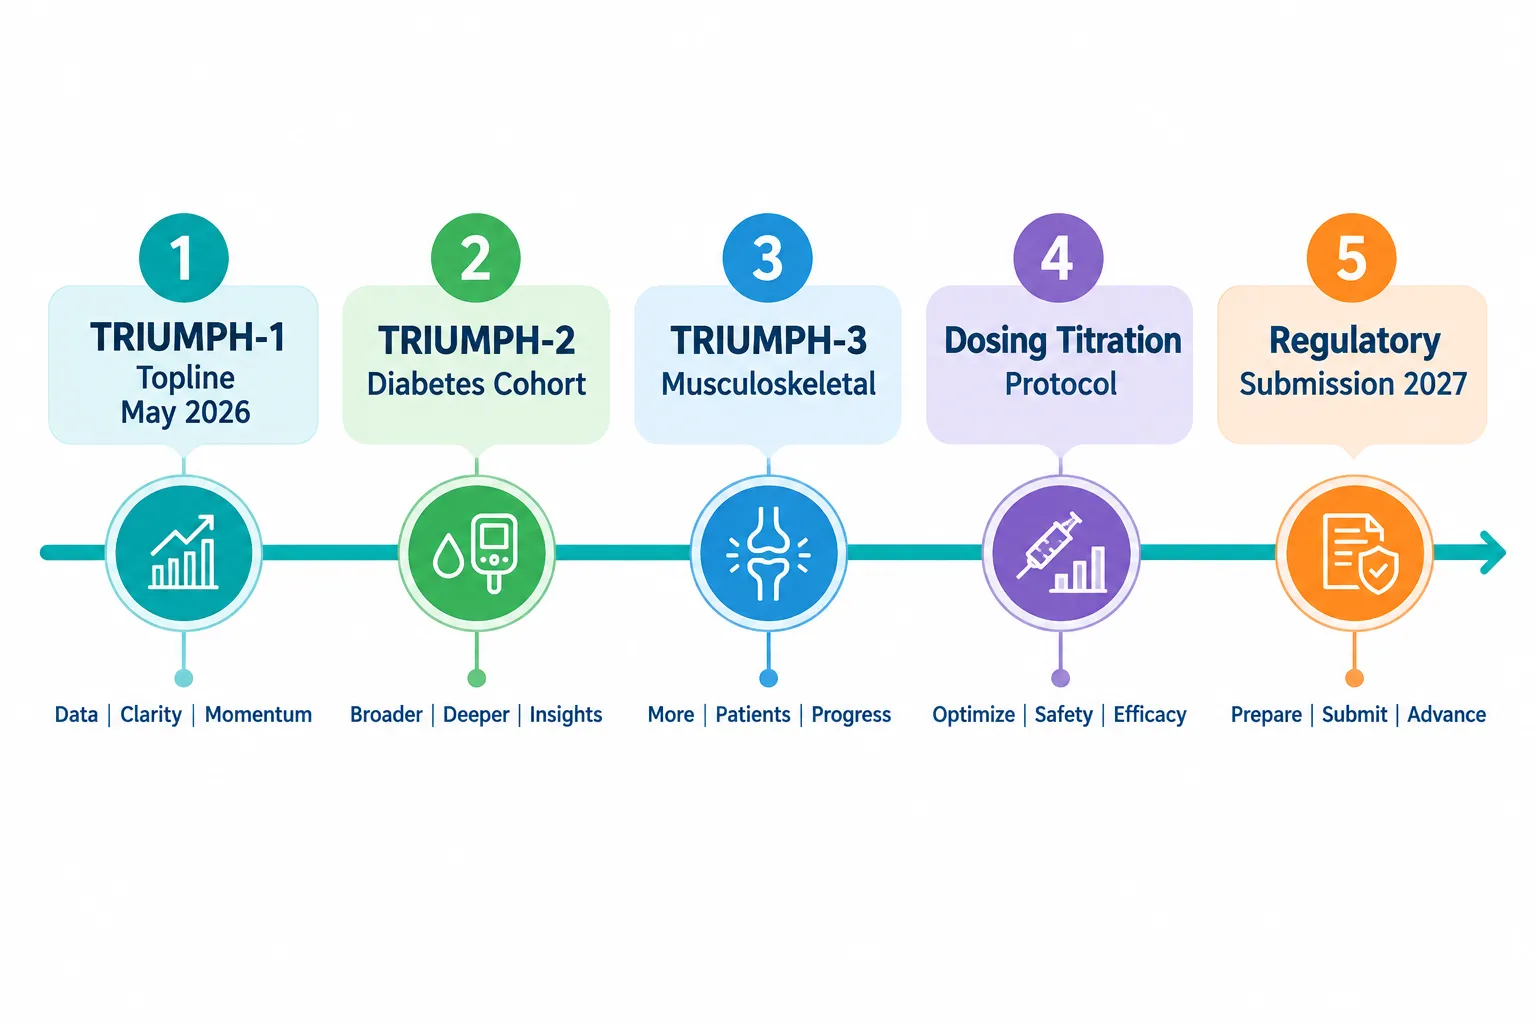
The TRIUMPH program is the most expansive Phase 3 obesity trial program launched for any incretin-based therapy. As of September 2026, six distinct trial arms are active or reporting:
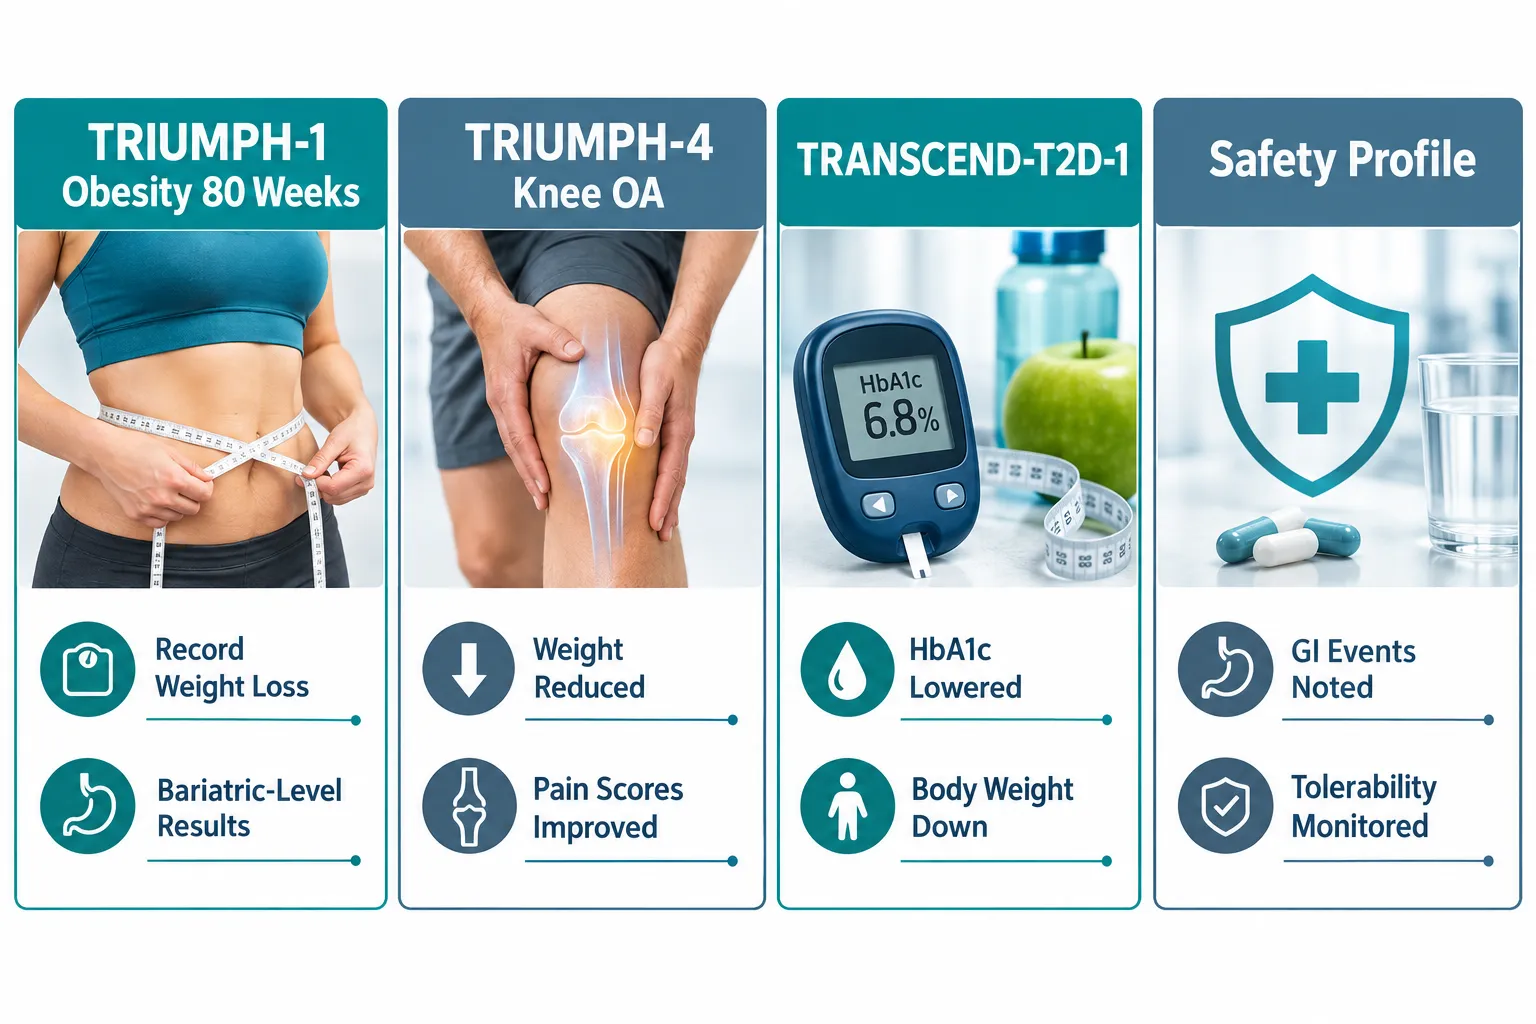
TRIUMPH-1 delivered topline results in May 2026. Participants receiving the highest dose achieved approximately 30% mean body weight reduction over 96 weeks, a figure that exceeds any approved pharmacotherapy currently on the market. Dose-response data confirmed a clear gradient: lower doses produced 20-24% reductions, while the highest titrated dose consistently approached the 30% threshold.
TRIUMPH-2 is the diabetes-specific arm, spotlighted at the EASD 2026 conference. This cohort examines retatrutide in adults with obesity and comorbid type 2 diabetes, where the GIP and glucagon components are expected to deliver additive glycemic benefit beyond what GLP-1 agonism alone provides.
TRIUMPH-3 addresses a frequently overlooked comorbidity: musculoskeletal disease. Early data suggest that weight loss of 20-30% produces clinically meaningful reductions in osteoarthritis pain scores, a finding with direct implications for retatrutide endpoints research design.
Additional arms cover obstructive sleep apnea, cardiovascular outcomes, and liver disease, broadening the clinical utility profile well beyond weight reduction alone.
"A 30% reduction in body weight from a subcutaneous weekly injection would have been considered implausible a decade ago. TRIUMPH-1 has changed that calculus entirely."
Comparative Efficacy and 2026 Protocol Implications for Research Models
The Retatrutide Phase 3 Obesity Trial Data Updates: Triple Incretin Mechanism Analysis for 2026 Protocols has direct consequences for how preclinical and translational researchers structure their metabolic models going forward.
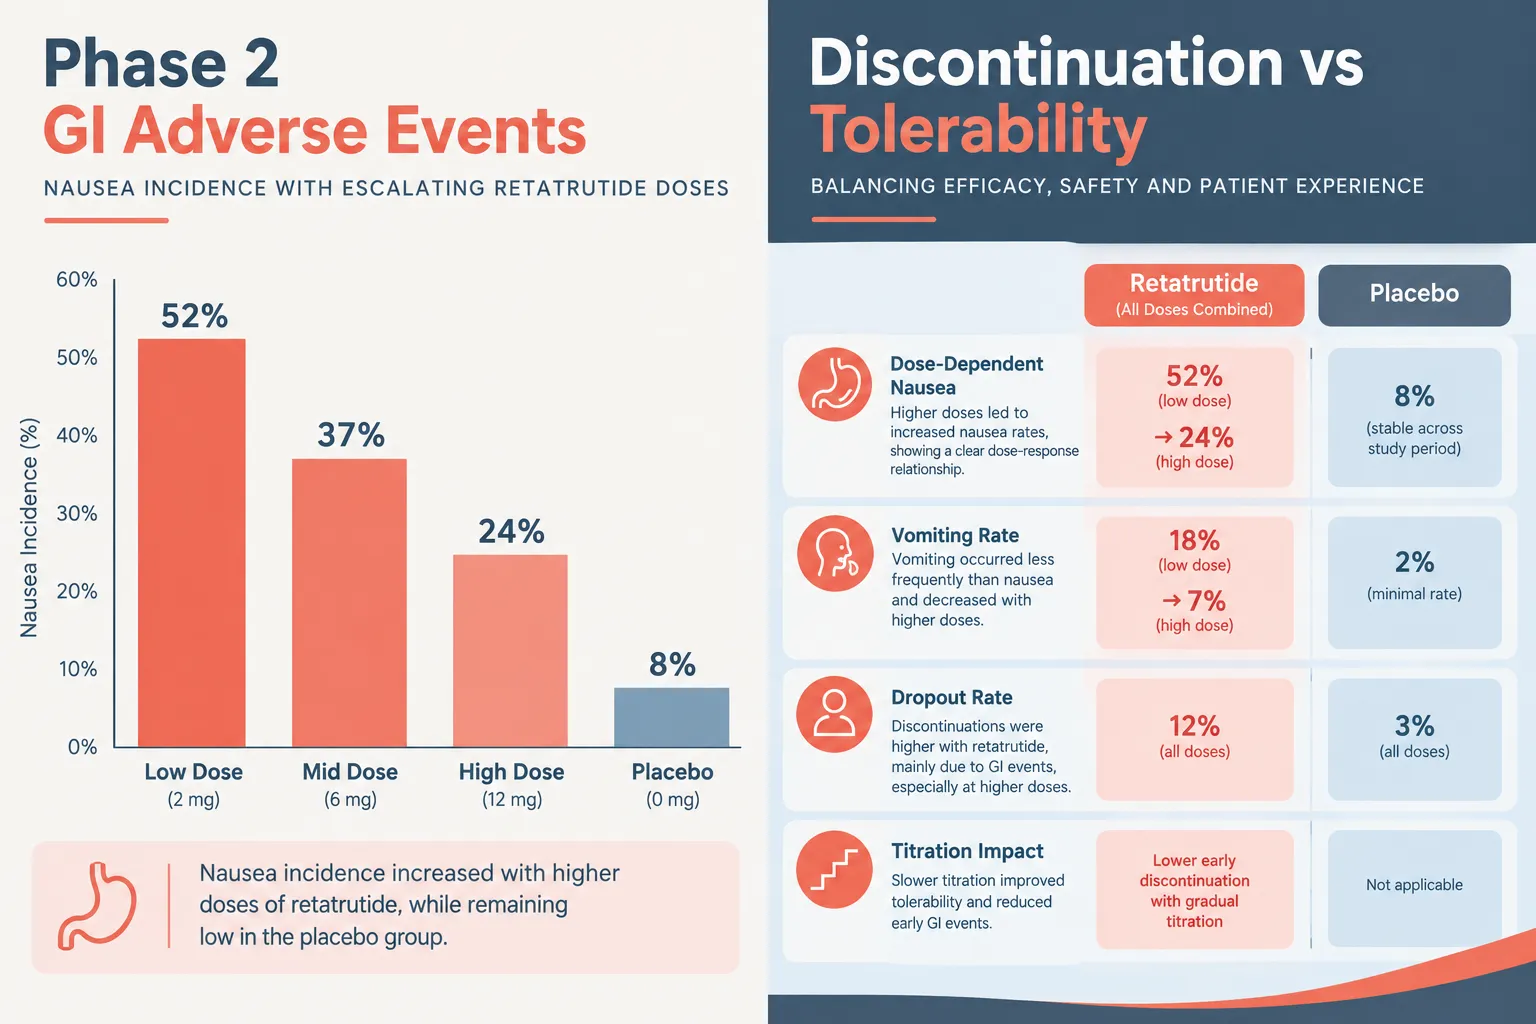
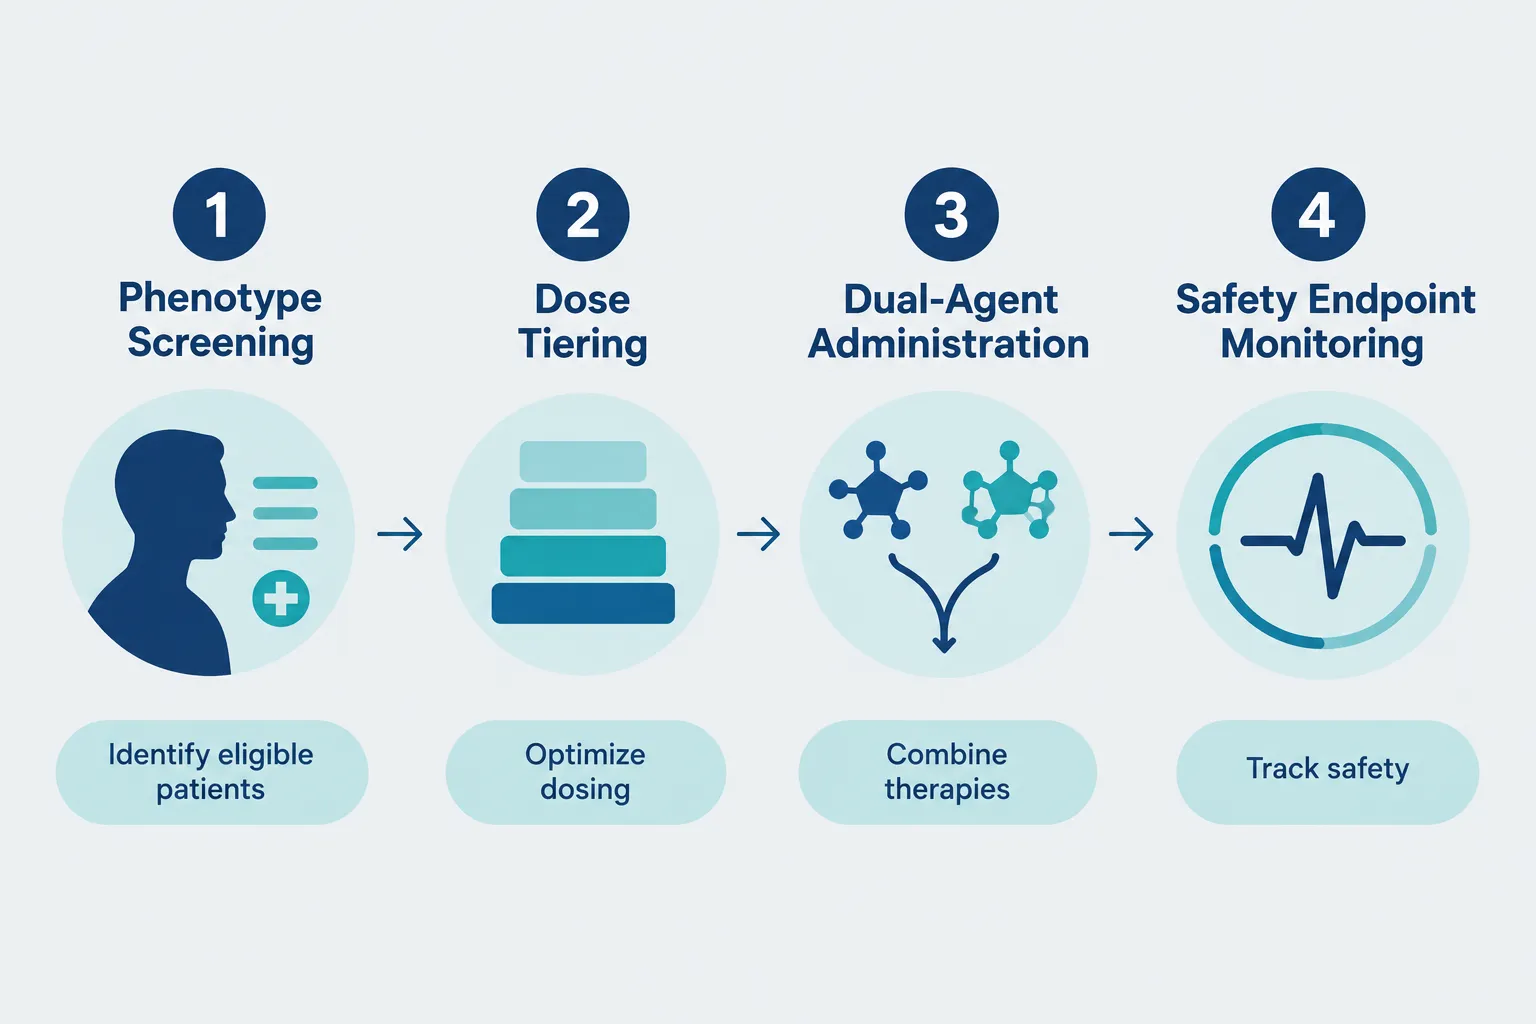
Dosing and titration insights from TRIUMPH-1 show a gradual 24-week escalation protocol reaching a maximum dose of 12 mg weekly. This slow titration minimizes gastrointestinal adverse events, the primary tolerability concern with incretin therapies, while allowing receptor adaptation. Researchers designing laboratory protocols in 2026 are mapping these titration curves to animal model equivalents.
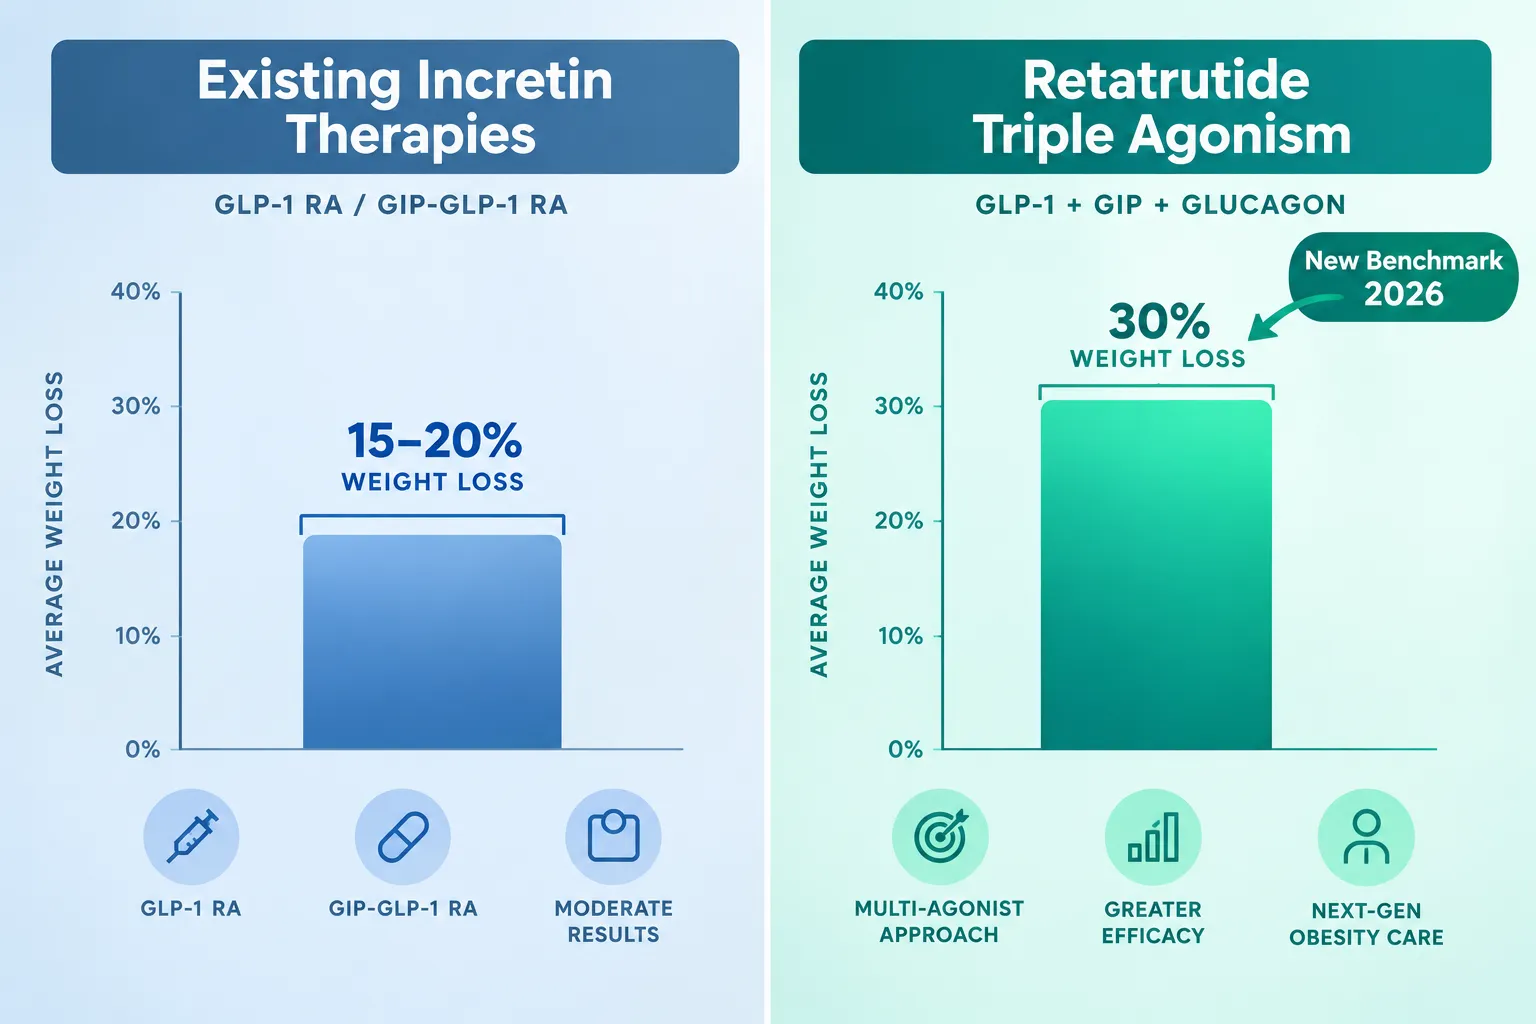
Comparative context matters. Semaglutide at 2.4 mg produces roughly 15-17% weight loss. Tirzepatide achieves approximately 20-22%. Retatrutide's ~30% positions it in a category of its own, approaching surgical outcomes without procedural risk. For those studying GLP-1 Reta formulations in metabolic research, this efficacy differential demands updated experimental benchmarks.
Researchers working with higher-dose models can explore GLP-3 Reta 20mg GSF and GLP-3 Reta 20mg GA1 formulations designed for controlled preclinical studies. Those requiring larger quantities for extended protocols may reference GLP-3 Reta 30mg options.
Key protocol design considerations for 2026 research:
- Incorporate glucagon receptor activity into metabolic outcome measurements
- Align titration schedules with TRIUMPH-1 escalation data
- Include liver fat, inflammatory markers, and joint-loading endpoints alongside body composition
- Account for the extended durability window, two-year data shows sustained, not plateauing, weight loss
Predicted 2027 outlook (speculative): If regulatory submissions proceed following anticipated 2026 data lock milestones, retatrutide could enter FDA review in 2027. Approval would likely trigger a rapid repositioning of existing obesity treatment algorithms across clinical and research settings alike.
Conclusion
The TRIUMPH program's 2026 data outputs have fundamentally repositioned retatrutide as the leading candidate in next-generation obesity pharmacotherapy. The triple incretin mechanism, GLP-1, GIP, and glucagon working in concert, delivers weight loss outcomes that no single or dual agonist has matched in controlled Phase 3 conditions.
Actionable next steps for researchers and protocol designers:
- Review TRIUMPH-1 titration schedules and adapt dose-escalation models to preclinical study designs.
- Expand endpoint panels to include hepatic, musculoskeletal, and cardiovascular markers consistent with the TRIUMPH program's breadth.
- Update comparative benchmarks in metabolic research models to reflect the new ~30% weight loss standard.
- Monitor TRIUMPH-2 diabetes cohort data from EASD 2026 for glycemic endpoint integration.
- Source validated research-grade compounds through verified suppliers to ensure experimental reproducibility.
The science of incretin tri-agonism is no longer theoretical, it is producing real, reproducible, and historically significant clinical outcomes in 2026.