Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: retatrutide

GLP-1 Peptide Alternatives: How Retatrutide, Tesofensine, and Traditional Weight-Loss Drugs Differ in Research Models

GLP-1 Peptide Alternatives: How Retatrutide, Tesofensine, and Traditional Weight-Loss Drugs Differ in Research Models

September 30, 2026/0 Comments/in Uncategorized/by

Obesity-related metabolic disease now affects more than one billion people worldwide, yet the pharmacological tools available to researchers have expanded dramatically in just the past few years. At the center of that expansion sits a deceptively simple question: what separates the new wave of receptor-targeted compounds from the older drugs that came before them? Exploring GLP-1 peptide alternatives, how retatrutide, tesofensine, and traditional weight-loss drugs differ in research models, reveals not just a difference in potency, but a fundamental shift in how scientists approach metabolic endpoints, receptor pharmacology, and trial design.

Key Takeaways

  • Retatrutide activates three receptors simultaneously (GLP-1R, GIPR, GcgR), producing greater weight-loss magnitude in preclinical and clinical models than any single-receptor agent.
  • Tesofensine works through monoamine reuptake inhibition in the central nervous system, a mechanism distinct from peptide-based receptor agonism.
  • Traditional agents such as orlistat and phentermine act peripherally or centrally through narrow pathways, limiting both efficacy and comorbidity coverage.
  • Modern research models prioritize multi-domain endpoints, cardiometabolic, hepatic, and renal outcomes, rather than weight reduction alone.
  • Purity and reference-standard quality are critical variables when comparing compound performance across preclinical studies.

Receptor Pharmacology: The Foundation of Difference
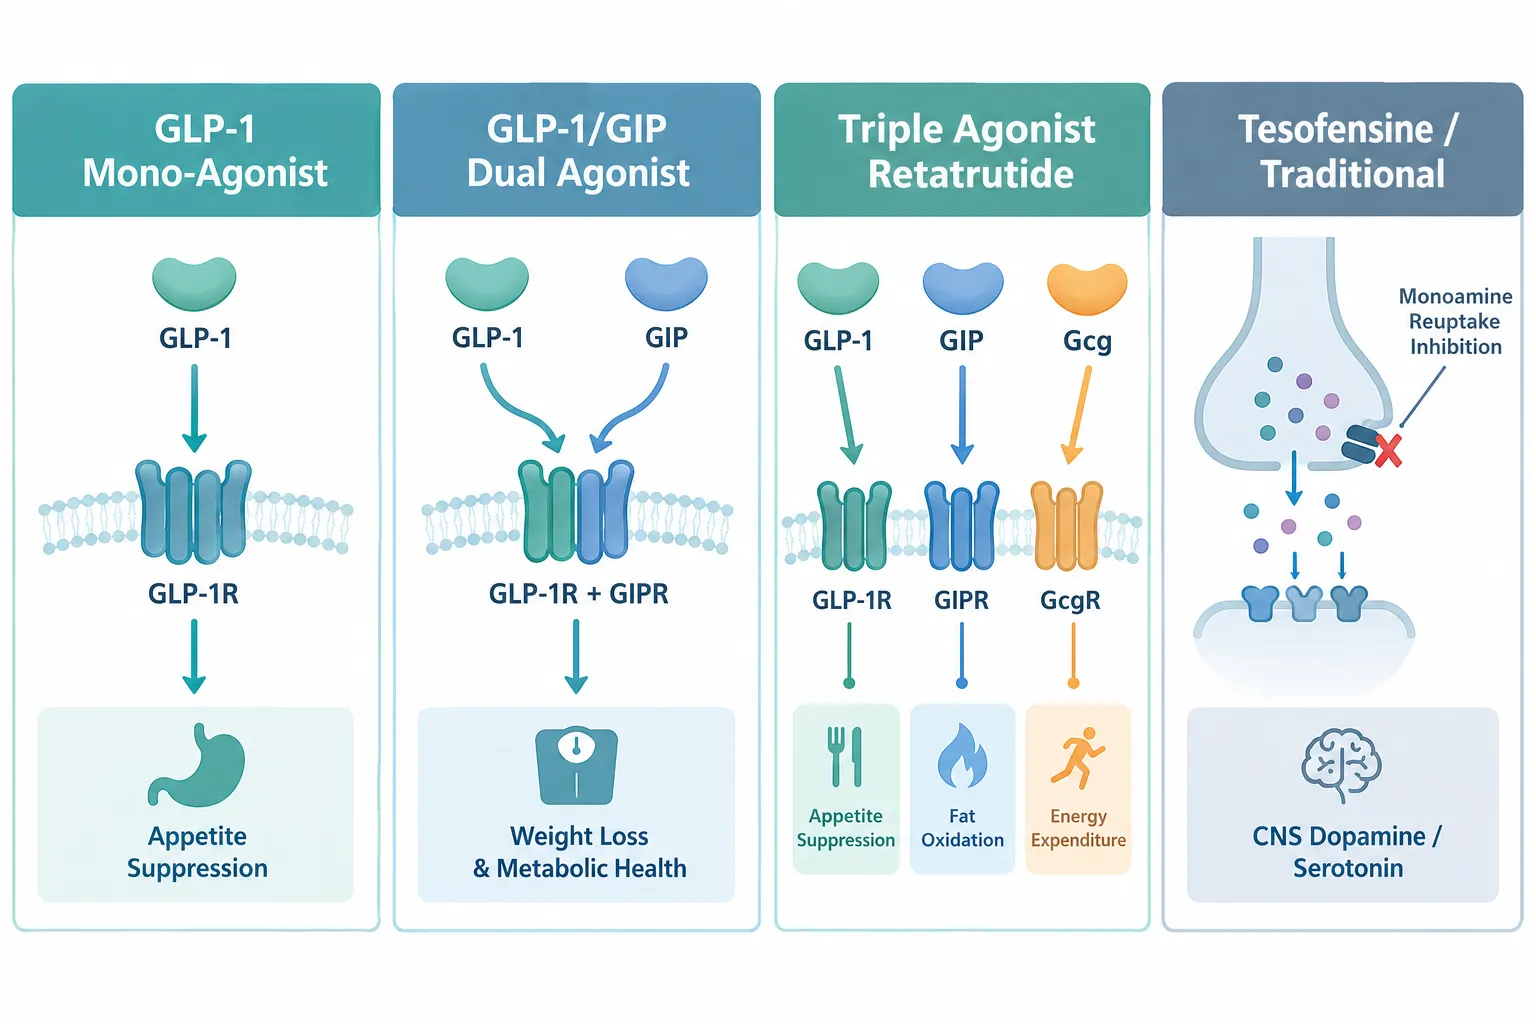
Receptor Pharmacology: The Foundation of Difference

Understanding GLP-1 peptide alternatives begins at the receptor level. GLP-1 receptor agonists mimic glucagon-like peptide-1, a gut-derived incretin hormone that signals satiety to the hypothalamus and regulates insulin secretion. First-generation compounds such as exenatide targeted only GLP-1R. Dual agonists like tirzepatide added glucose-dependent insulinotropic polypeptide receptor (GIPR) activation, amplifying both metabolic and appetite effects.

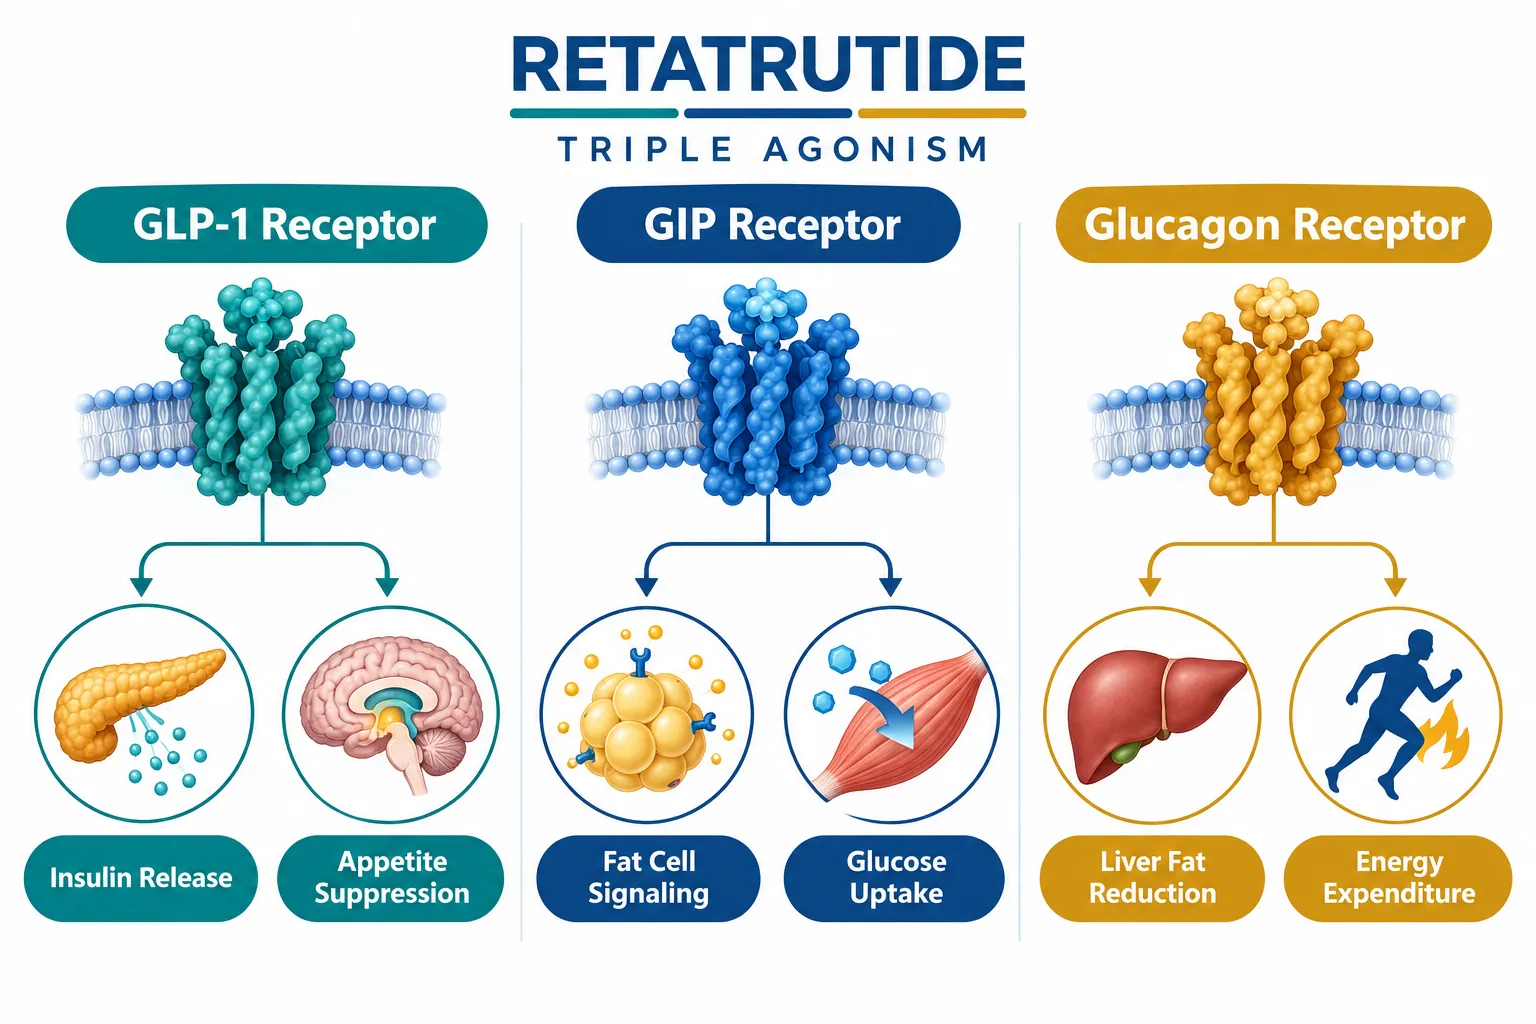
Retatrutide takes this further by adding glucagon receptor (GcgR) agonism to the GLP-1R and GIPR combination. This triple-receptor engagement increases energy expenditure through thermogenic mechanisms while simultaneously reducing caloric intake and improving hepatic fat metabolism. Researchers studying retatrutide clinical trials have noted that this layered mechanism produces additive, and in some models, synergistic, effects across metabolic pathways.

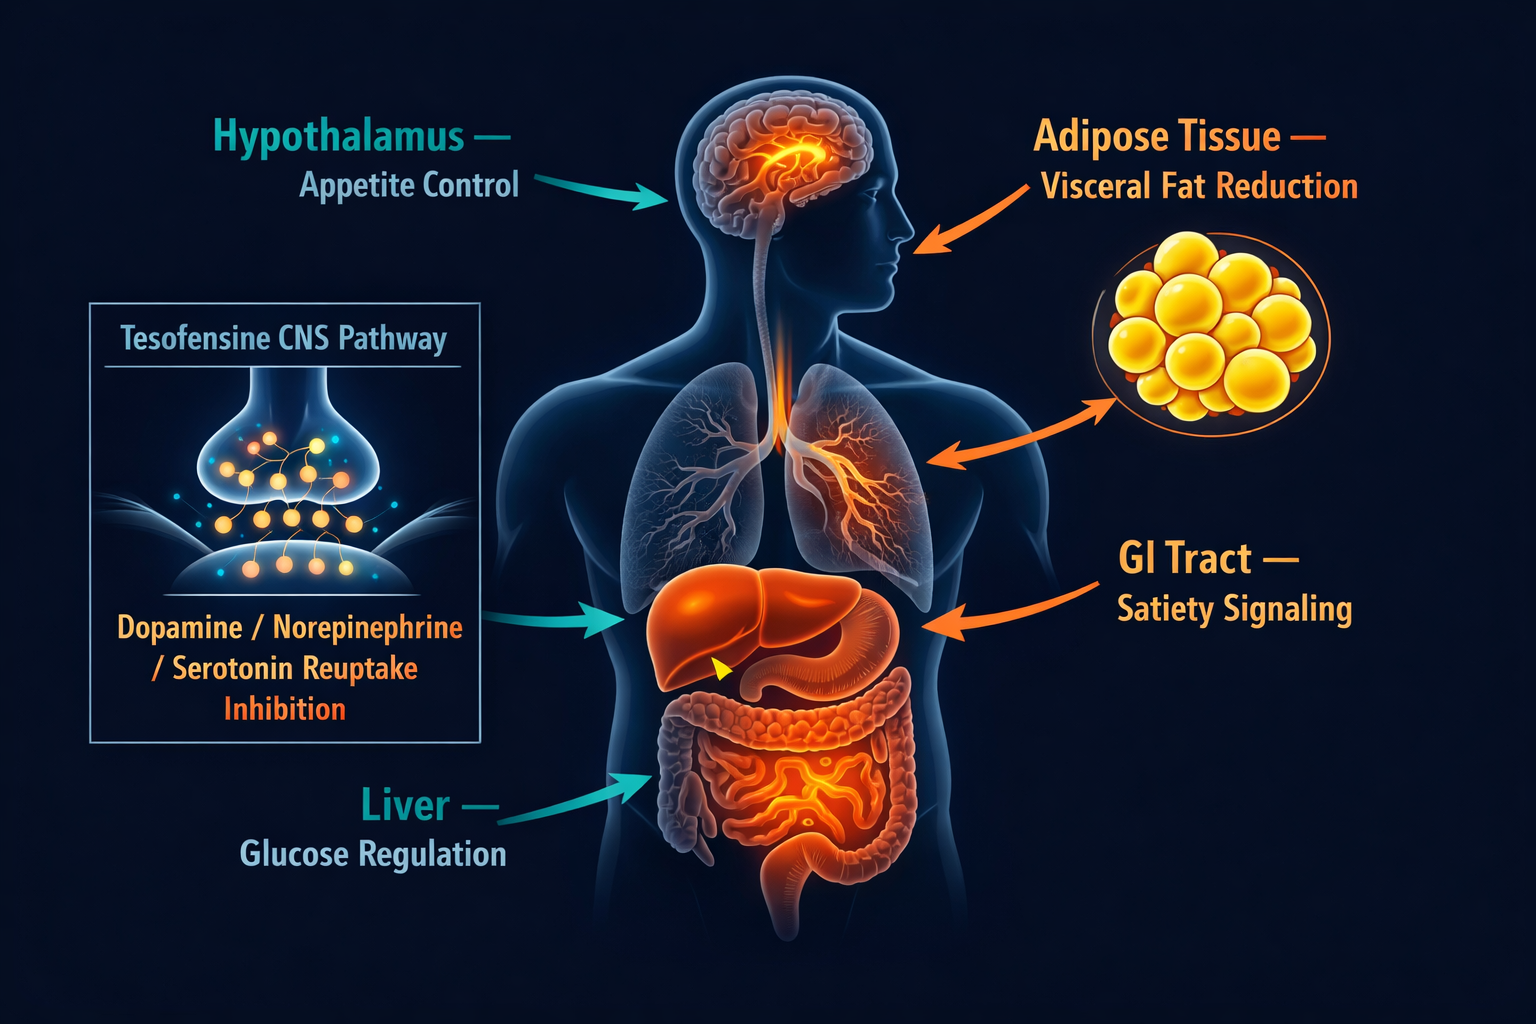
Tesofensine operates through an entirely different mechanism. It inhibits the presynaptic reuptake of dopamine, norepinephrine, and serotonin in the central nervous system. This monoamine reuptake inhibition reduces appetite via hypothalamic pathways but does not engage incretin receptors, insulin signaling, or glucagon pathways. The result is a narrower metabolic footprint compared to triple agonists.

Traditional agents occupy an even narrower pharmacological space:

  • Orlistat blocks pancreatic lipase in the gut, reducing dietary fat absorption by roughly 30%
  • Phentermine stimulates norepinephrine release, suppressing appetite centrally
  • Topiramate modulates GABA receptors and voltage-gated channels with appetite suppression as a secondary effect

"The shift from peripheral lipase inhibition to multi-receptor hormonal agonism represents one of the most significant mechanistic leaps in metabolic pharmacology in decades."


Weight-Loss Magnitude and Metabolic Endpoints in Research Models
Weight-Loss Magnitude and Metabolic Endpoints in Research Models

When comparing compounds in controlled research models, weight-loss magnitude is the most cited metric, but it is far from the only one. Phase 2 data for retatrutide demonstrated mean body weight reductions exceeding 17% at 24 weeks in human subjects, a figure that surpassed both semaglutide and tirzepatide benchmarks at comparable timepoints. Researchers tracking retatrutide endpoints have documented simultaneous improvements in triglycerides, fasting glucose, liver fat fraction, and blood pressure.

Tesofensine phase 2 trials showed weight reductions of approximately 10-12% over 24 weeks, meaningful but below the triple-agonist range. Traditional agents typically produce 5-8% weight loss over 12 months, with limited effects on cardiometabolic markers beyond what weight loss itself produces.

Visceral fat is a particularly important endpoint in modern models. Retatrutide's GcgR component appears to preferentially mobilize visceral adipose tissue, which carries the highest cardiometabolic risk. Research into visceral fat research confirms that visceral depot reduction correlates more strongly with metabolic improvement than total body weight alone.

Comparative Weight-Loss Summary Across Model Types

Compound Class Primary Mechanism Approx. Weight Loss (Research Models)
Retatrutide (triple agonist) GLP-1R + GIPR + GcgR 17-24%
Semaglutide (GLP-1 mono) GLP-1R only 12-15%
Tesofensine Monoamine reuptake inhibition 10-12%
Orlistat / Phentermine Lipase inhibition / NE release 5-8%

Trial Design, Safety Profiles, and the Future of GLP-1 Peptide Alternatives in Research Models
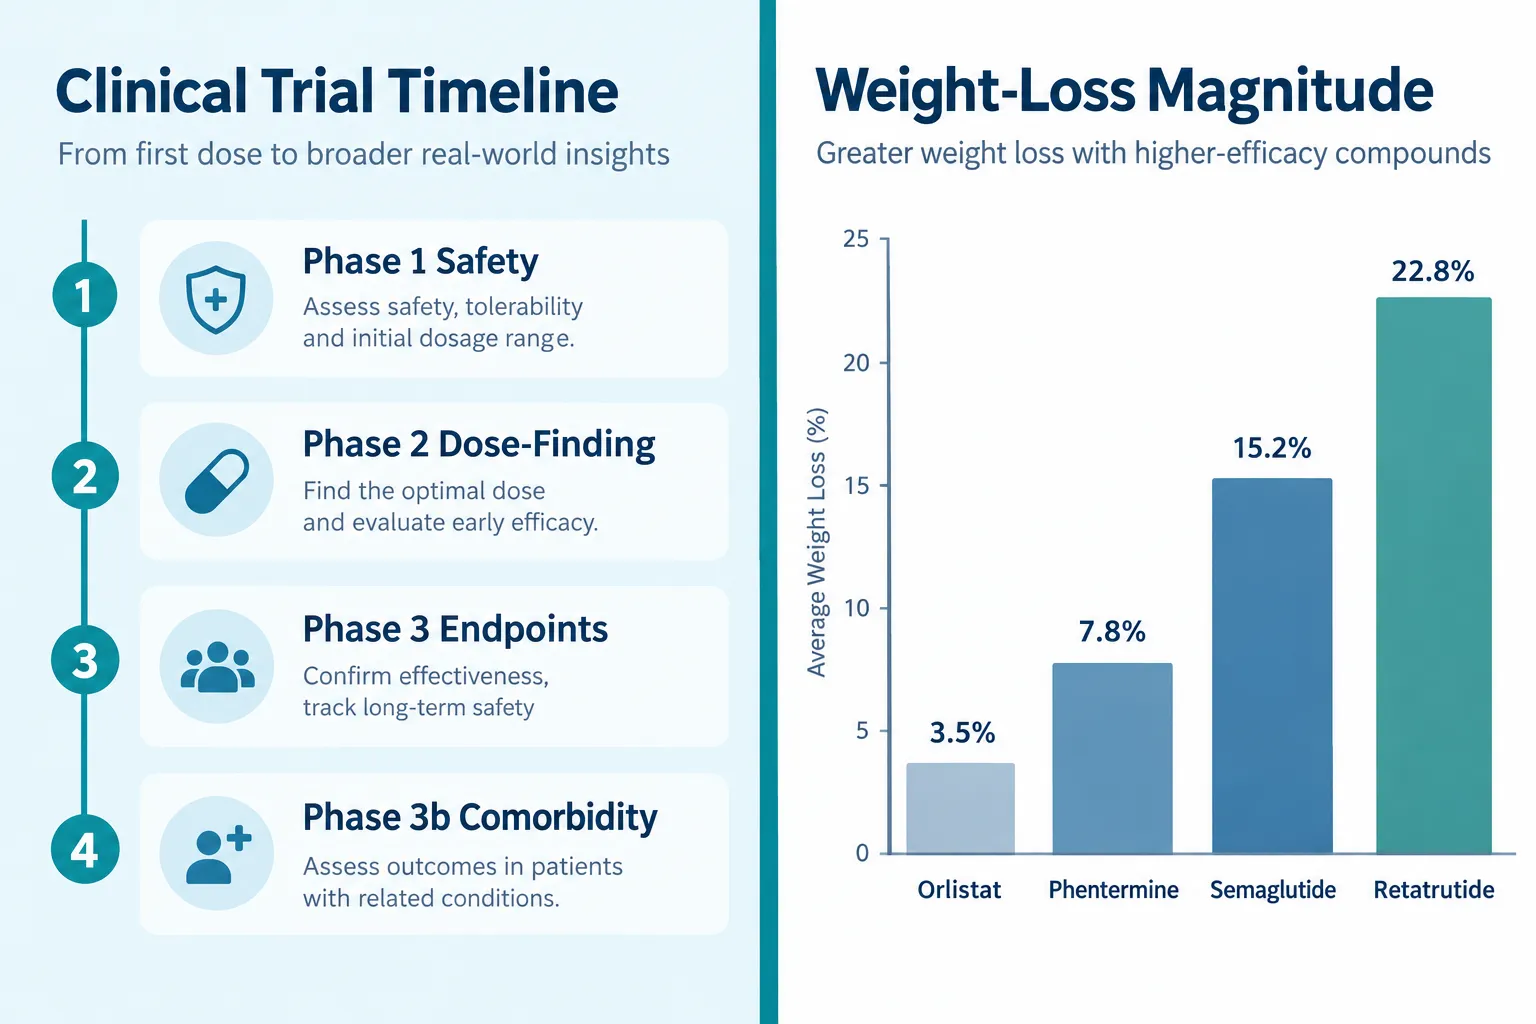
Trial Design, Safety Profiles, and the Future of GLP-1 Peptide Alternatives in Research Models

The design of research models has evolved alongside the compounds themselves. Early trials for orlistat and phentermine measured weight as the sole primary endpoint over 12-52 weeks. Modern phase 3 programs for retatrutide span multiple years and incorporate cardiovascular outcomes, liver histology, kidney function, and quality-of-life measures as co-primary or key secondary endpoints. This comorbidity-focused architecture reflects the understanding that metabolic disease is systemic, not merely a matter of body mass index.

For researchers sourcing compounds for preclinical work, the quality of the peptide used directly affects the reproducibility of results. Resources like Bachem and reference standards for peptide benchmarks highlight how reference-grade materials reduce inter-study variability. Researchers exploring GLP-3 peptide options or looking to buy Reta GLP-3 peptide should prioritize suppliers with verified purity documentation.

Safety profiles also diverge significantly across compound classes:

  • Retatrutide and GLP-1 agonists share a gastrointestinal tolerability profile (nausea, vomiting at initiation) that is dose-dependent and typically transient
  • Tesofensine carries cardiovascular monitoring requirements due to its sympathomimetic properties, including modest increases in heart rate and blood pressure
  • Traditional agents like orlistat produce gastrointestinal side effects tied to fat malabsorption; phentermine carries addiction and cardiovascular risk considerations

As of late 2026, retatrutide is advancing through a global phase 3 program with cardiovascular outcomes data expected to shape its regulatory pathway. Tesofensine remains in development for specific obesity subpopulations. Neither is approved for clinical use, and both are studied exclusively in research contexts.


Conclusion

The landscape of GLP-1 peptide alternatives, how retatrutide, tesofensine, and traditional weight-loss drugs differ in research models, reflects a broader transformation in metabolic science. Receptor pharmacology, not just caloric restriction, now drives compound selection. Retatrutide's triple-agonist mechanism sets a new benchmark for weight-loss magnitude and multi-domain endpoint coverage. Tesofensine offers a distinct CNS-based pathway with meaningful but more limited metabolic reach. Traditional agents remain reference points for historical comparison rather than leading candidates in modern research design.

Actionable next steps for researchers:

  1. Align compound selection with the specific receptor pathways relevant to the research question
  2. Prioritize reference-standard purity to ensure reproducible preclinical outcomes
  3. Design studies around multi-domain endpoints, including visceral fat, hepatic markers, and cardiometabolic indicators
  4. Monitor regulatory developments for retatrutide's phase 3 cardiovascular outcomes data, expected to redefine treatment algorithm modeling
  5. Consult verified suppliers for research-grade GLP-1 pathway compounds, including options available through GLP peptide for sale and GLP-1 Reta peptide product lines
https://www.puretestedpeptides.com/wp-content/uploads/2026/09/glp-1-peptide-alternatives-how-retatrutide-tesofensine-and-traditional-weight-lo.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-30 13:33:042026-09-30 13:33:04GLP-1 Peptide Alternatives: How Retatrutide, Tesofensine, and Traditional Weight-Loss Drugs Differ in Research Models
Tesofensine vs GLP-3 Retatrutide: Comparing Appetite, Dopamine, Noradrenergic, and Incretin Signaling

Tesofensine vs GLP-3 Retatrutide: Comparing Appetite, Dopamine, Noradrenergic, and Incretin Signaling

September 30, 2026/0 Comments/in Uncategorized/by

Obesity pharmacology has split into two sharply different philosophies: rewire the brain's reward circuitry with monoamine reuptake inhibition, or flood peripheral and central receptors with gut-derived hormone signals. Tesofensine vs GLP-3 Retatrutide: Comparing Appetite, Dopamine, Noradrenergic, and Incretin Signaling sits at the center of that debate, and the contrast reveals just how many routes the body uses to regulate food intake, energy expenditure, and metabolic homeostasis.

Key Takeaways

  • Tesofensine suppresses appetite by blocking dopamine, norepinephrine, and serotonin reuptake in the central nervous system, while retatrutide activates three distinct gut-hormone receptors simultaneously.
  • Retatrutide's triple agonism at GLP-1, GIP, and glucagon receptors produces weight loss of up to 24% in phase 2 data, with phase 3 TRIUMPH-2 trials ongoing as of 2026.
  • Tesofensine's monoamine mechanism raises distinct cardiovascular and neuropsychiatric monitoring concerns not shared by incretin-based agents.
  • Both compounds converge on reduced caloric intake, but through entirely different upstream signaling cascades.
  • Retatrutide shows broader metabolic potential, including hepatic glucose regulation and improvements in insulin sensitivity, beyond appetite suppression alone.

How Tesofensine Works: Dopamine, Noradrenergic, and Serotonin Reuptake Inhibition

Tesofensine is a triple monoamine reuptake inhibitor. It blocks the reuptake transporters for dopamine, norepinephrine, and serotonin in presynaptic neurons, extending the time these neurotransmitters remain active in the synaptic cleft.

Tesofensine vs retatrutide mechanism-of-action diagram with receptor callouts

Dopamine signaling is central to reward-driven eating. By prolonging dopamine availability in the mesolimbic and hypothalamic pathways, tesofensine reduces the motivational drive to seek food, particularly calorie-dense, highly palatable foods. This is sometimes described as blunting hedonic hunger.

Noradrenergic signaling adds a second layer. Elevated norepinephrine in the hypothalamus activates alpha-2 adrenergic receptors and suppresses orexigenic neuropeptide Y (NPY) signaling, a well-established appetite-stimulating pathway. The result is a reduction in homeostatic hunger alongside the hedonic suppression from dopamine.

Serotonergic contributions are comparatively modest in tesofensine's profile but reinforce satiety signaling through 5-HT2C receptor activation, a mechanism shared with older weight-loss agents like lorcaserin.

"Tesofensine's strength is its central reach, it simultaneously targets reward, homeostatic, and satiety circuits in the brain."

Phase 2 clinical data showed meaningful short-term weight reduction, with some studies reporting 6-10% body weight loss over 24 weeks. However, cardiovascular monitoring remains a critical safety endpoint because elevated norepinephrine tone can increase heart rate and blood pressure. Neuropsychiatric effects, including insomnia and mood changes, are also tracked closely given the dopaminergic mechanism.

For researchers exploring peptide-based mechanisms, the Peptides 101 guide covering GLP-3, MOTS-C, and 5-Amino-1MQ provides useful structural context on how different compound classes interact with metabolic pathways.


How Retatrutide Works: Triple Incretin and Glucagon Receptor Agonism

Retatrutide operates on an entirely different axis. Rather than modulating neurotransmitter availability, it acts as a simultaneous agonist at three receptors: glucagon-like peptide-1 (GLP-1), glucose-dependent insulinotropic polypeptide (GIP), and glucagon receptors. This is why it is often labeled a GLP-3 receptor agonist in research contexts, the triple-receptor profile distinguishes it from dual agonists like tirzepatide.

Retatrutide vs tesofensine clinical trial weight loss comparison 2026

GLP-1 receptor agonism slows gastric emptying, enhances glucose-dependent insulin secretion, and activates hypothalamic satiety neurons directly. This is the mechanism shared with semaglutide.

GIP receptor agonism amplifies the insulinotropic response and may improve adipocyte insulin sensitivity, reducing lipid overflow into non-adipose tissues.

Glucagon receptor agonism is the differentiating element. Glucagon increases hepatic glucose output and, critically, raises basal energy expenditure by stimulating fatty acid oxidation. This thermogenic effect means retatrutide does not simply reduce caloric intake, it also increases the rate at which stored energy is burned.

Phase 2 data from the retatrutide clinical trial program demonstrated up to 24.2% body weight reduction at 48 weeks, a figure that exceeds any approved anti-obesity pharmacotherapy to date. The TRIUMPH-2 phase 3 program, actively enrolling and reporting interim data through 2026, is evaluating these outcomes at scale across diverse populations.

Researchers can review available GLP-3 retatrutide peptide formats as part of ongoing preclinical investigation.


Side-by-Side Comparison: Signaling Pathways, Efficacy, and Safety

Feature Tesofensine Retatrutide
Primary mechanism Monoamine reuptake inhibition Triple receptor agonism (GLP-1, GIP, glucagon)
Appetite pathway Dopamine, norepinephrine, serotonin Incretin hormones, hypothalamic GLP-1R
Energy expenditure Modest increase via noradrenergic tone Significant increase via glucagon receptor
Glucose regulation Indirect, secondary to weight loss Direct via GLP-1 and GIP insulinotropic action
Phase 2 weight loss 6-10% over 24 weeks Up to 24% over 48 weeks
Key safety watch Heart rate, blood pressure, mood GI tolerability, gallbladder, heart rate
Regulatory status (2026) Phase 2 completed; not approved Phase 3 TRIUMPH-2 ongoing

Metabolic Scope Beyond Weight Loss

The comparison in Tesofensine vs GLP-3 Retatrutide: Comparing Appetite, Dopamine, Noradrenergic, and Incretin Signaling extends well beyond the scale.

Retatrutide metabolic signaling organs liver pancreas hypothalamus diagram

Retatrutide's glucagon component raises its potential in non-alcoholic fatty liver disease (NAFLD) and metabolic-associated steatohepatitis (MASH), conditions driven by hepatic lipid accumulation. By stimulating hepatic fatty acid oxidation, retatrutide addresses the liver pathology that often accompanies severe obesity, a target tesofensine does not reach directly.

Tesofensine, by contrast, may have a role in populations where central reward dysregulation is the dominant driver of excess intake, such as binge-eating phenotypes, given its direct action on dopaminergic circuits. Its noradrenergic component also raises the possibility of mild thermogenic benefit, though this is modest compared to retatrutide's glucagon-driven energy expenditure increase.

For research teams studying broader peptide pharmacology, resources on peptides and polypeptides in endocrine pharmacology offer relevant mechanistic context. Those sourcing GLP-3 peptides for research use should verify purity documentation and third-party testing before use.


Conclusion

The Tesofensine vs GLP-3 Retatrutide: Comparing Appetite, Dopamine, Noradrenergic, and Incretin Signaling framework makes clear that these are not competing versions of the same drug, they are fundamentally different tools built on different biological theories of obesity.

Actionable next steps for researchers and clinicians in 2026:

  • Monitor TRIUMPH-2 phase 3 interim data releases for retatrutide's cardiovascular and hepatic endpoints, which will define its approval trajectory.
  • Evaluate tesofensine's monoamine profile in study designs focused on reward-driven eating behavior, where dopaminergic modulation may offer unique mechanistic insight.
  • When designing metabolic research protocols, consider whether the target endpoint is central appetite regulation (favoring monoamine approaches) or peripheral metabolic correction (favoring incretin-glucagon agonism).
  • Ensure all research-grade peptide sourcing uses lab-tested peptides with verified purity certificates to maintain experimental integrity.

Both compounds represent serious scientific advances. Retatrutide's efficacy data currently leads by a wide margin, but tesofensine's neurochemical mechanism keeps it relevant for specific research questions that incretin agonists cannot address.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/tesofensine-vs-glp-3-retatrutide-comparing-appetite-dopamine-noradrenergic-and-i.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-30 13:20:102026-09-30 13:20:10Tesofensine vs GLP-3 Retatrutide: Comparing Appetite, Dopamine, Noradrenergic, and Incretin Signaling
Retatrutide and Cardiovascular Disease Research: Interpreting Weight, Glycemic, and Safety Endpoints Together

Retatrutide and Cardiovascular Disease Research: Interpreting Weight, Glycemic, and Safety Endpoints Together

September 26, 2026/0 Comments/in Uncategorized/by

Fewer than 40% of adults with severe obesity and established cardiovascular disease achieve meaningful, sustained weight loss through lifestyle intervention alone, yet researchers increasingly face a more complex challenge: determining whether the dramatic weight reductions produced by newer agents like retatrutide actually translate into reduced cardiovascular events, or whether they simply improve the numbers on a lab report.

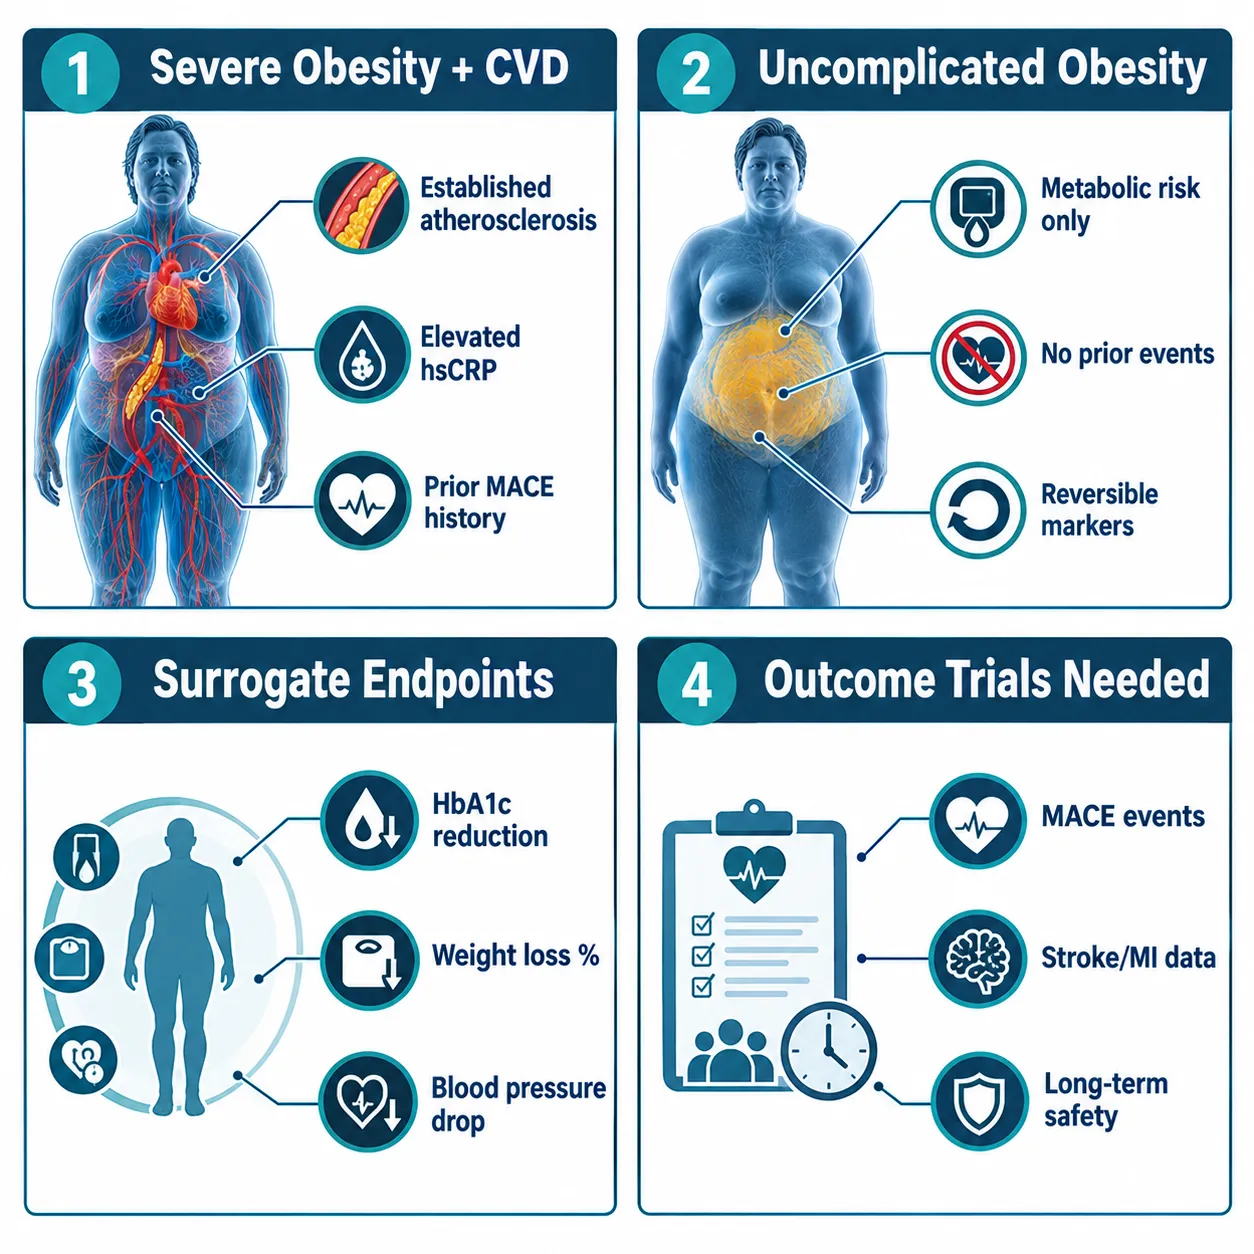
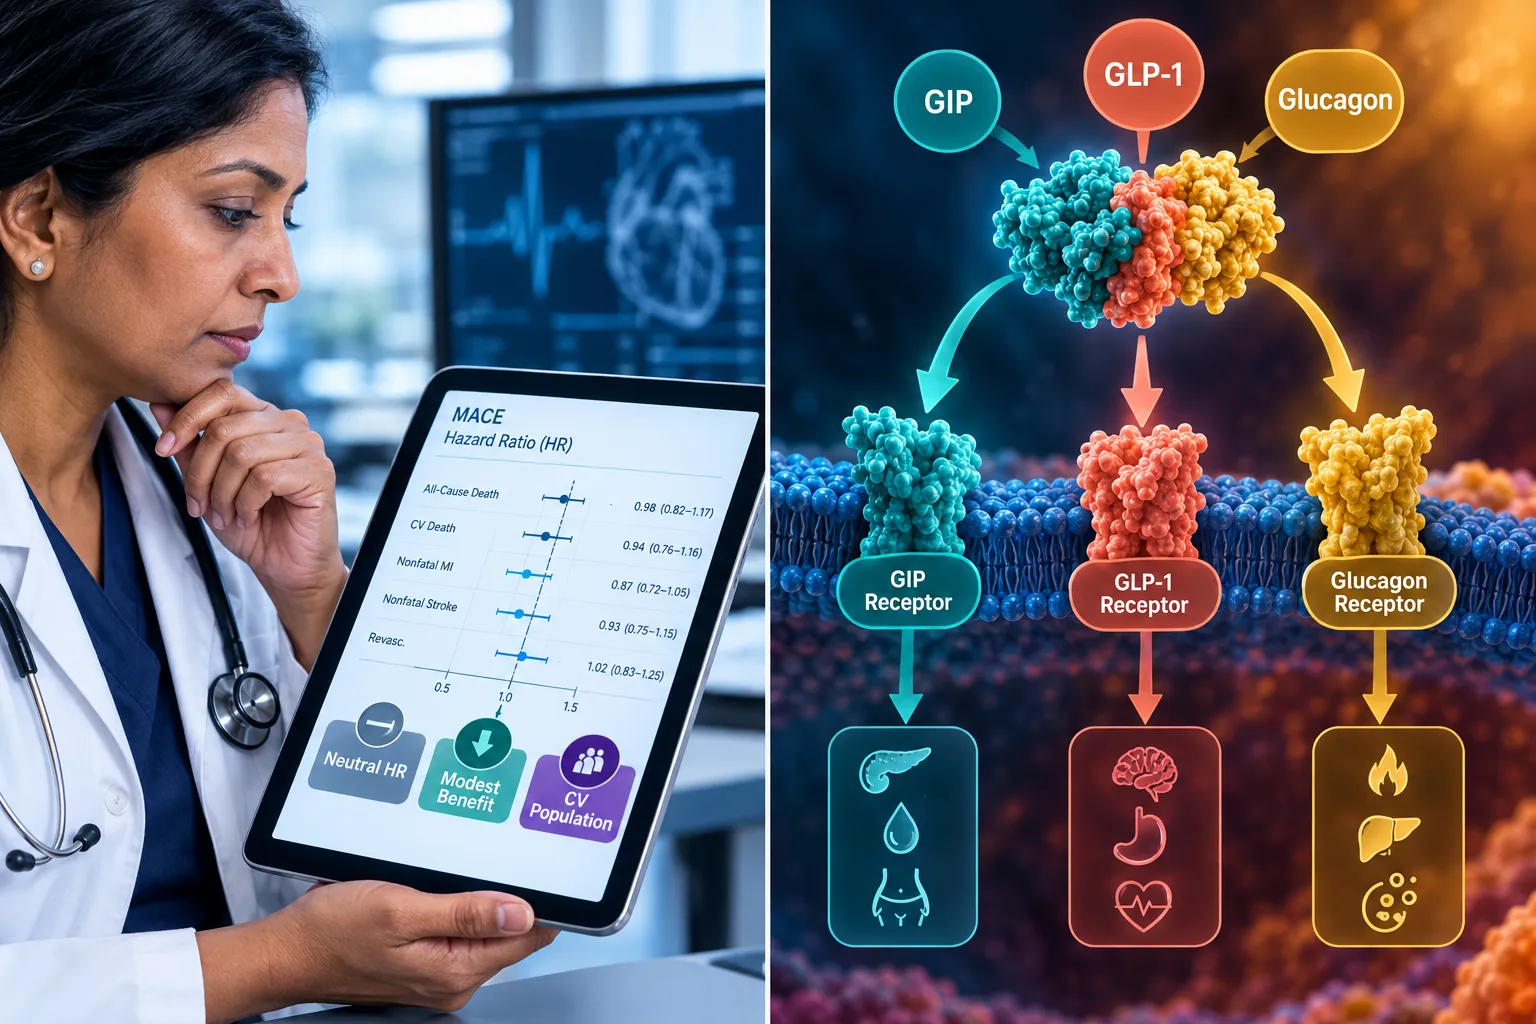
Retatrutide and cardiovascular disease research: interpreting weight, glycemic, and safety endpoints together has become one of the most consequential methodological questions in metabolic medicine as of 2026. The drug's triple agonist mechanism, targeting GIP, GLP-1, and glucagon receptors simultaneously, produces weight loss that surpasses nearly every prior pharmacological benchmark. But the population most likely to receive this therapy in clinical practice is not the uncomplicated obesity cohort studied in pivotal trials. It is the patient with prior myocardial infarction, heart failure, or advanced atherosclerosis, where surrogate endpoints and actual cardiovascular outcomes can diverge sharply.

Key Takeaways

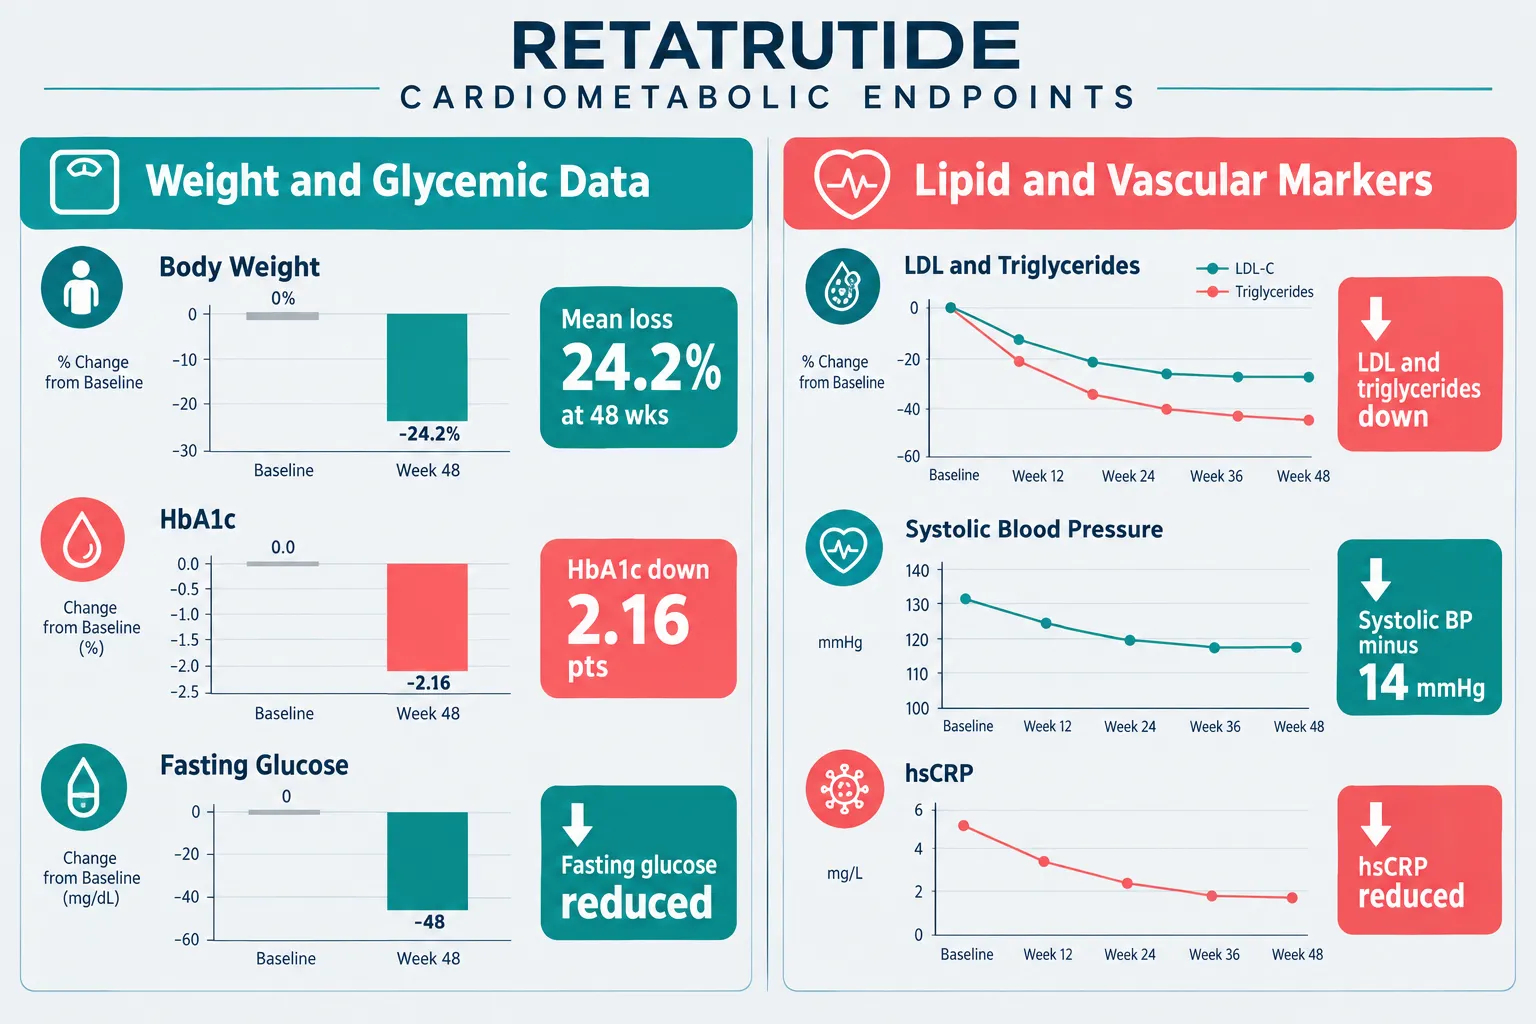
  • Retatrutide produced mean body weight reductions of up to 24.2% at 48 weeks in phase 2 trials, exceeding prior pharmacological benchmarks.
  • Glycemic improvements, including HbA1c reductions of approximately 2.16 percentage points, occurred alongside weight loss in both diabetic and non-diabetic populations.
  • Lipid panels, blood pressure, and inflammatory markers all shifted in a cardiovascular-favorable direction, but these remain surrogate endpoints.
  • No completed cardiovascular outcomes trials have yet confirmed reductions in major adverse cardiovascular events (MACE) for retatrutide.
  • Researchers must resist treating weight loss as a direct proxy for cardiovascular benefit, particularly in high-risk populations with established disease.

Why the Severe-Obesity CVD Population Demands a Different Analytical Frame

Why the Severe-Obesity CVD Population Demands a Different Analytical Frame

The distinction between uncomplicated obesity and obesity complicated by established cardiovascular disease is not semantic, it is mechanistically and statistically critical. In uncomplicated obesity cohorts, cardiovascular risk is largely driven by modifiable metabolic factors: insulin resistance, dyslipidemia, and hypertension. Meaningful weight loss reliably improves these factors, and the pathway from surrogate improvement to event reduction is relatively well-supported by prior evidence from bariatric surgery and GLP-1 receptor agonist outcomes trials.

In the severe-obesity CVD population, however, the risk architecture is different. Atherosclerotic plaques are already established. Inflammatory burden is higher. Cardiac remodeling may be present. The relationship between short-term biomarker improvement and long-term event reduction is less predictable, and the potential for adverse interactions, including changes in heart rate, volume shifts from rapid weight loss, or arrhythmia risk, requires independent evaluation rather than inference from surrogate data.

This is the central interpretive challenge for retatrutide and cardiovascular disease research: interpreting weight, glycemic, and safety endpoints together requires researchers to resist collapsing a multi-dimensional risk picture into a single headline number.

Researchers reviewing retatrutide endpoints data should note that the phase 2 obesity trial enrolled adults without diabetes and without prior cardiovascular events. Extrapolating those results to a post-MI population with preserved or reduced ejection fraction introduces assumptions that the data do not yet support.


What the Phase 2 Data Actually Show: Weight, Glycemic, and Lipid Endpoints

What the Phase 2 Data Actually Show: Weight, Glycemic, and Lipid Endpoints

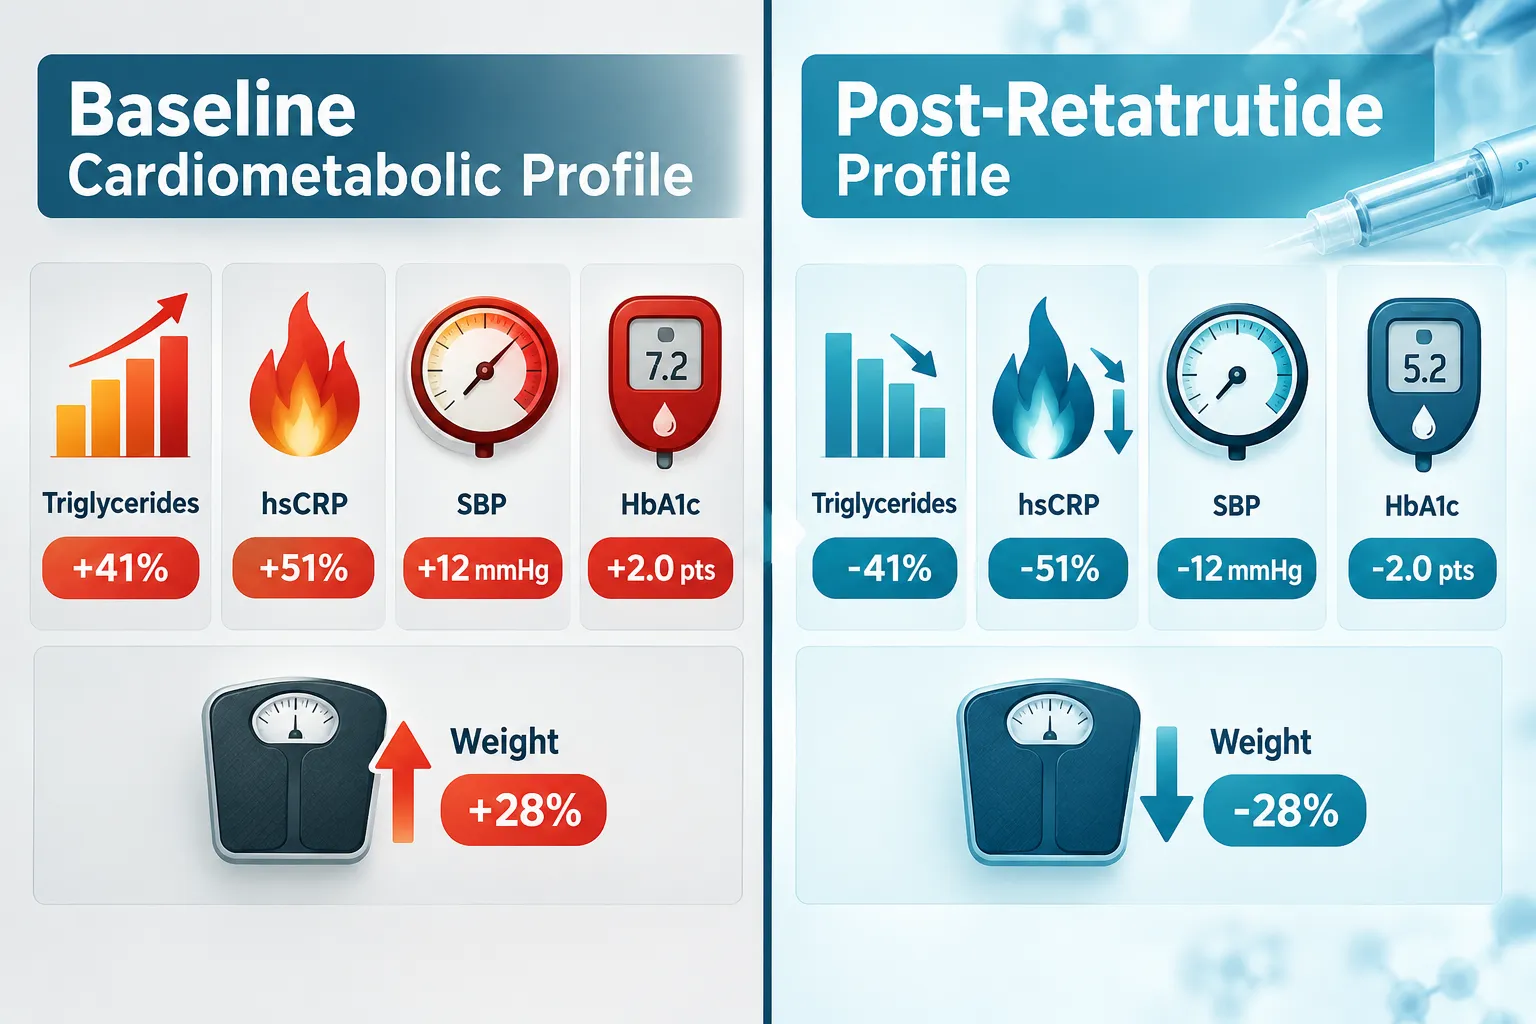
The phase 2 evidence base for retatrutide is genuinely impressive across multiple dimensions. In the pivotal obesity trial involving 338 adults, once-weekly retatrutide at 12 mg produced a mean body weight reduction of 24.2% at 48 weeks. The 8 mg dose achieved 22.8% mean loss. Placebo-adjusted weight reduction at 24 weeks was approximately 16%, with a continued downward trajectory through the trial period. Every participant receiving 8 or 12 mg weekly achieved at least 5% weight loss, a threshold widely cited in regulatory and guideline contexts as clinically meaningful for cardiovascular risk.

Glycemic endpoints reinforced the cardiometabolic signal. In a separate 36-week phase 2 study in adults with type 2 diabetes, the highest dose produced an average HbA1c decrease of approximately 2.16 percentage points alongside up to 16.9% weight reduction. Fasting glucose and fasting insulin also declined in parallel with weight loss in the obesity trial.

Key insight: A 2.16 percentage-point HbA1c reduction in a population with established type 2 diabetes is clinically substantial, but it is a surrogate marker for cardiovascular risk, not a direct measure of event prevention.

Lipid and inflammatory markers moved in favorable directions. Triglycerides, LDL cholesterol, non-HDL cholesterol, and total cholesterol all declined. HDL modestly improved. Systolic blood pressure fell by roughly 4-8 mmHg across effective dose arms in the obesity trial, and by approximately 14 mmHg at the highest dose in a manufacturer-reported analysis using an efficacy estimand. High-sensitivity C-reactive protein (hsCRP), a marker of systemic inflammation strongly associated with cardiovascular events, was also reduced.

Waist circumference decreased by approximately 10-15 cm across effective dose arms, a change relevant to visceral adiposity and its downstream effects on insulin sensitivity and hepatic lipid metabolism.

For researchers seeking GLP-3 Reta 30mg formulations for preclinical or translational research purposes, these multi-endpoint findings provide a rich framework for designing studies that go beyond single-biomarker outcomes.


Interpreting Safety Endpoints Alongside Efficacy: What Researchers Must Not Overlook

Interpreting Safety Endpoints Alongside Efficacy: What Researchers Must Not Overlook

Safety data from phase 2 trials show a profile broadly consistent with potent incretin-based therapies. Adverse events were predominantly gastrointestinal, nausea, vomiting, and diarrhea, and were more frequent at higher doses, consistent with dose-dependent receptor engagement. Serious adverse events were infrequent, and the overall safety profile was considered acceptable for continued development.

Critically, available phase 2 summaries do not signal major cardiovascular safety concerns over 36-48 weeks. But this observation carries an important caveat: 36-48 weeks is insufficient to characterize arrhythmia risk, heart failure decompensation risk, or ischemic event rates in a population with established cardiovascular disease.

Researchers must treat the absence of a safety signal as a starting point for investigation, not a conclusion.

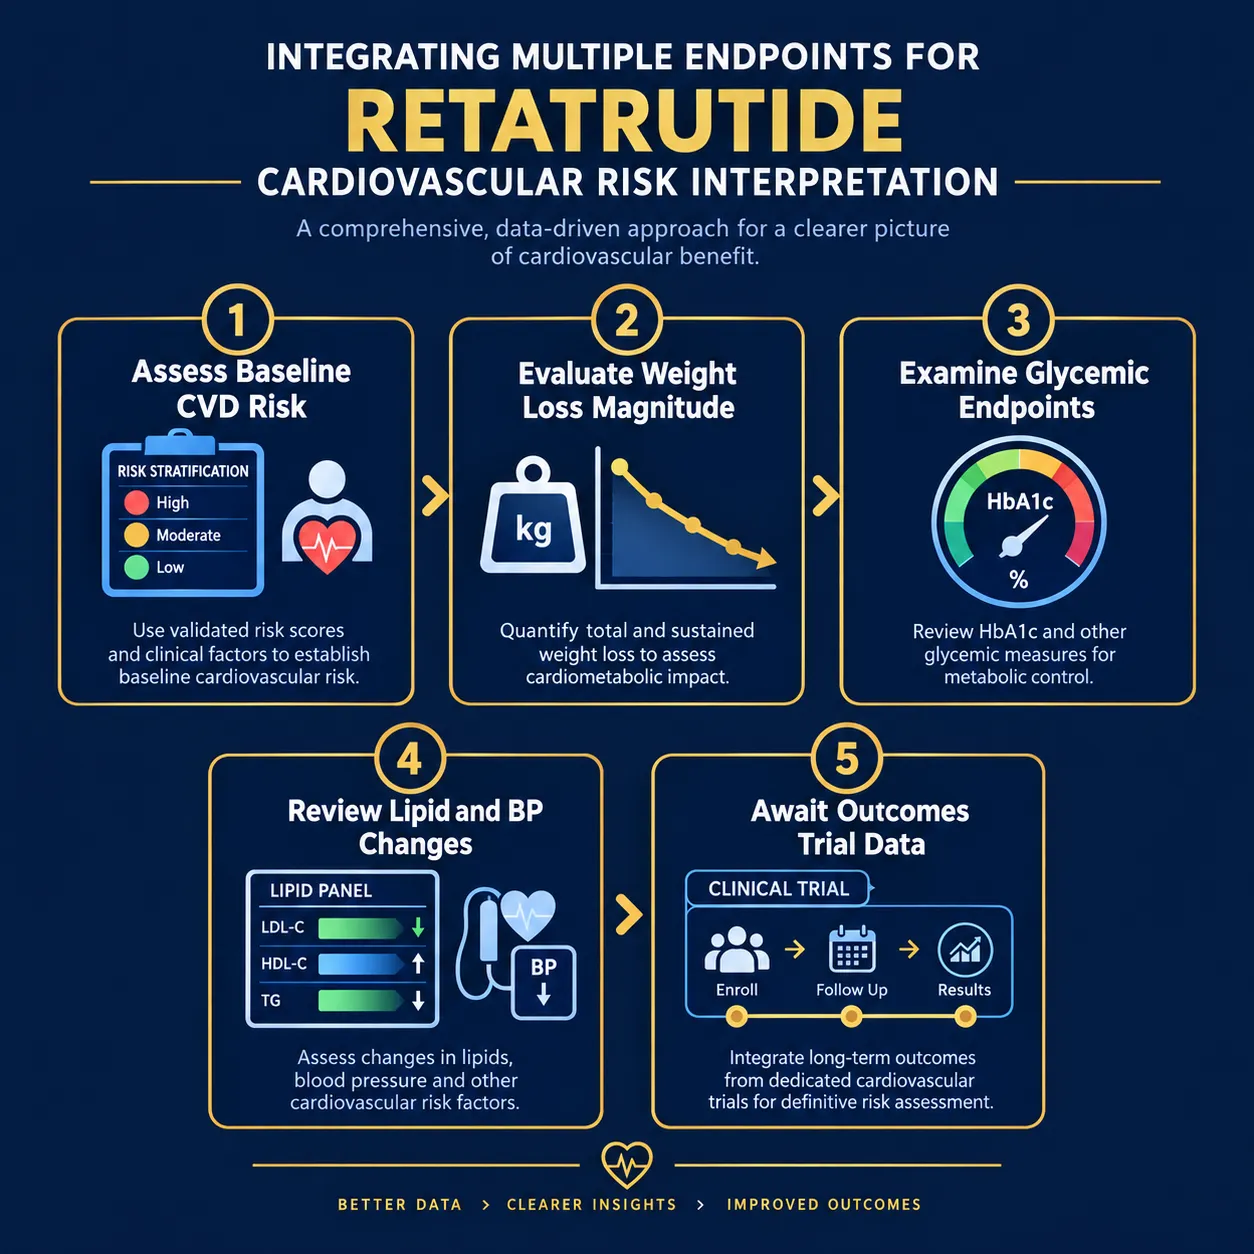
The integrated interpretation framework for retatrutide and cardiovascular disease research, interpreting weight, glycemic, and safety endpoints together, should follow a structured logic:

  1. Stratify baseline cardiovascular risk before interpreting any endpoint change.
  2. Evaluate weight loss magnitude in the context of rate and composition, not just percentage.
  3. Examine glycemic endpoints as independent contributors to risk, not simply as weight-loss correlates.
  4. Review lipid and blood pressure changes with attention to clinical significance thresholds.
  5. Identify gaps: no completed MACE outcomes trial exists for retatrutide as of 2026.

Researchers exploring adjacent cardiometabolic peptide research, including SS-31 kidney health research, will recognize this multi-endpoint interpretive discipline as standard practice in high-risk populations where organ-level interactions are complex.

Those sourcing compounds for translational research can review available Reta 20mg for sale options or GLP-3 Reta CAG 10mg for sale formulations through verified research-grade suppliers.


Conclusion

The surrogate endpoint data for retatrutide are among the most compelling seen in pharmacological obesity research. Weight loss of 24% at 48 weeks, combined with substantial HbA1c reduction, improved lipid panels, lower blood pressure, and reduced hsCRP, constructs a plausible and mechanistically coherent case for cardiovascular benefit.

But plausibility is not proof, particularly in the severe-obesity cardiovascular disease population where the stakes are highest and the biology is most complex.

Actionable next steps for researchers and clinicians:

  • Design studies that explicitly enroll patients with established cardiovascular disease, not just metabolic risk factors.
  • Pre-specify cardiovascular safety endpoints, including arrhythmia monitoring and heart failure hospitalization, as primary or co-primary outcomes, not secondary analyses.
  • Avoid reporting weight loss as a cardiovascular outcome; report it as one component of a multi-endpoint risk profile.
  • Track cardiovascular outcomes trial timelines for retatrutide and resist extrapolating event-level benefit from surrogate data until those trials report.
  • When reviewing buy Reta online options for preclinical research, ensure purity and dosing specifications align with the phase 2 protocols to maintain translational relevance.

The science surrounding retatrutide and cardiovascular disease research: interpreting weight, glycemic, and safety endpoints together is advancing rapidly. The discipline required to interpret that science rigorously, especially in high-risk populations, must advance at the same pace.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-and-cardiovascular-disease-research-interpreting-weight-glycemic-and.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-26 13:11:232026-09-26 13:11:23Retatrutide and Cardiovascular Disease Research: Interpreting Weight, Glycemic, and Safety Endpoints Together
Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation

Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation

September 26, 2026/0 Comments/in Uncategorized/by

Fewer than one in ten obesity drugs in history have produced mean weight loss exceeding 20 percent in a phase 3 trial. Retatrutide, a triple receptor agonist targeting GIP, GLP-1, and glucagon pathways simultaneously, has now cleared that threshold by a wide margin, and the implications reach far beyond a single efficacy number.

The full scope of Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation is still being absorbed by the research community. Topline data from the TRIUMPH master protocol and its obesity sub-programs show outcomes that reframe earlier phase 2 benchmarks, raise new questions about cardiovascular labeling, and complicate how scientists define a "weight-loss drug" in the first place.

Key Takeaways

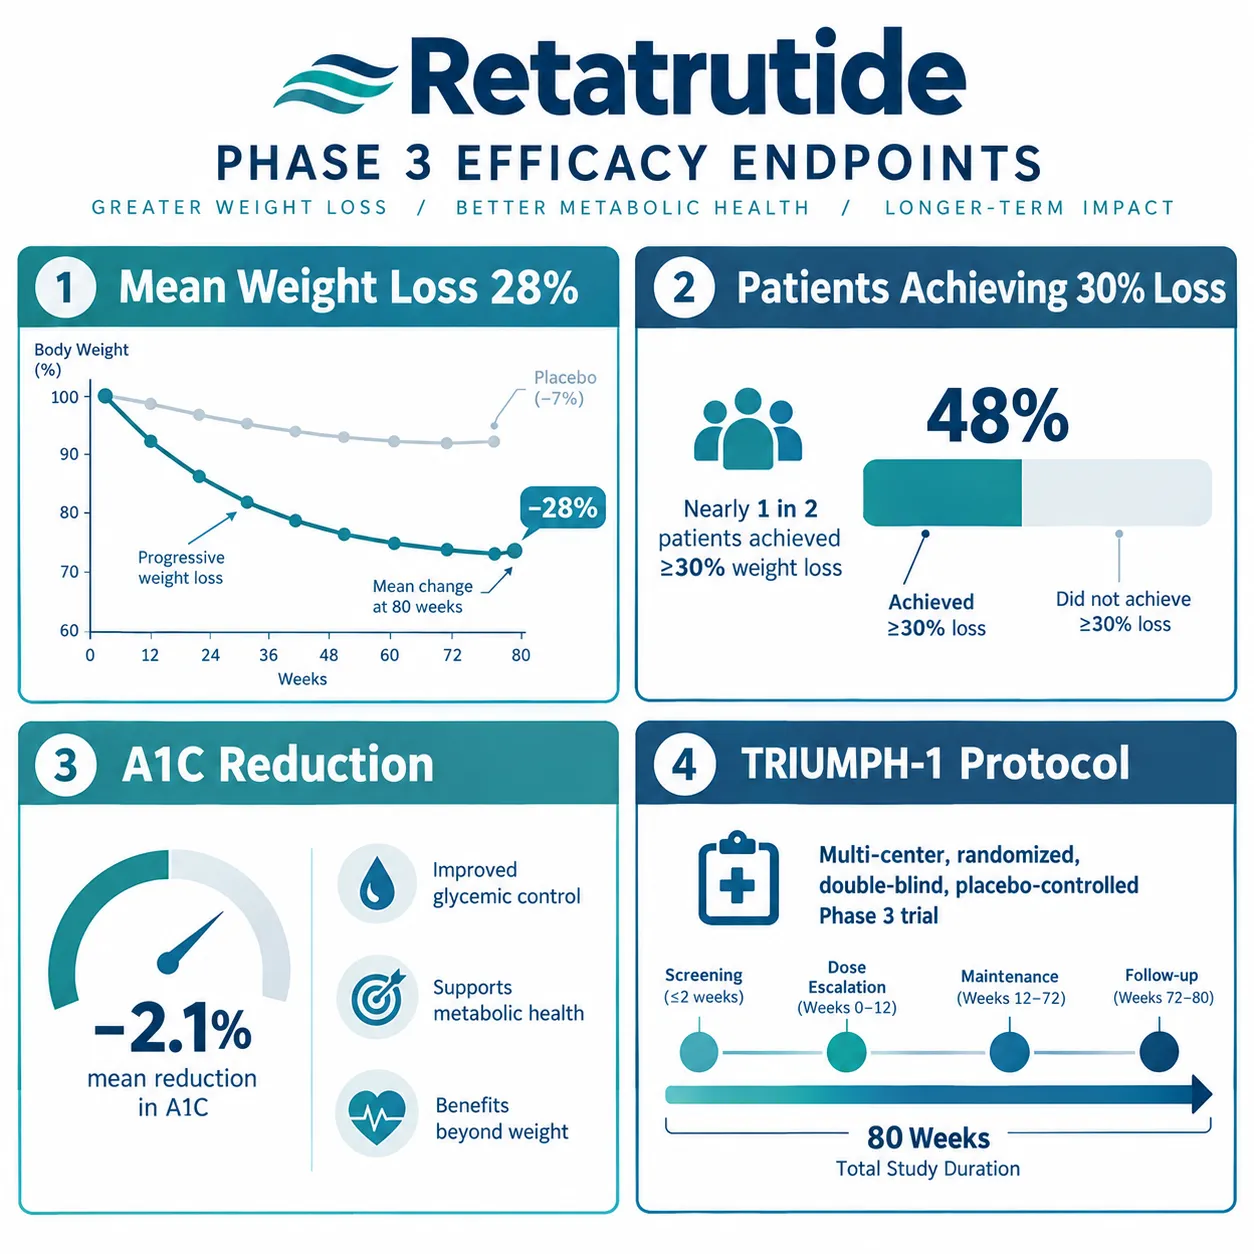
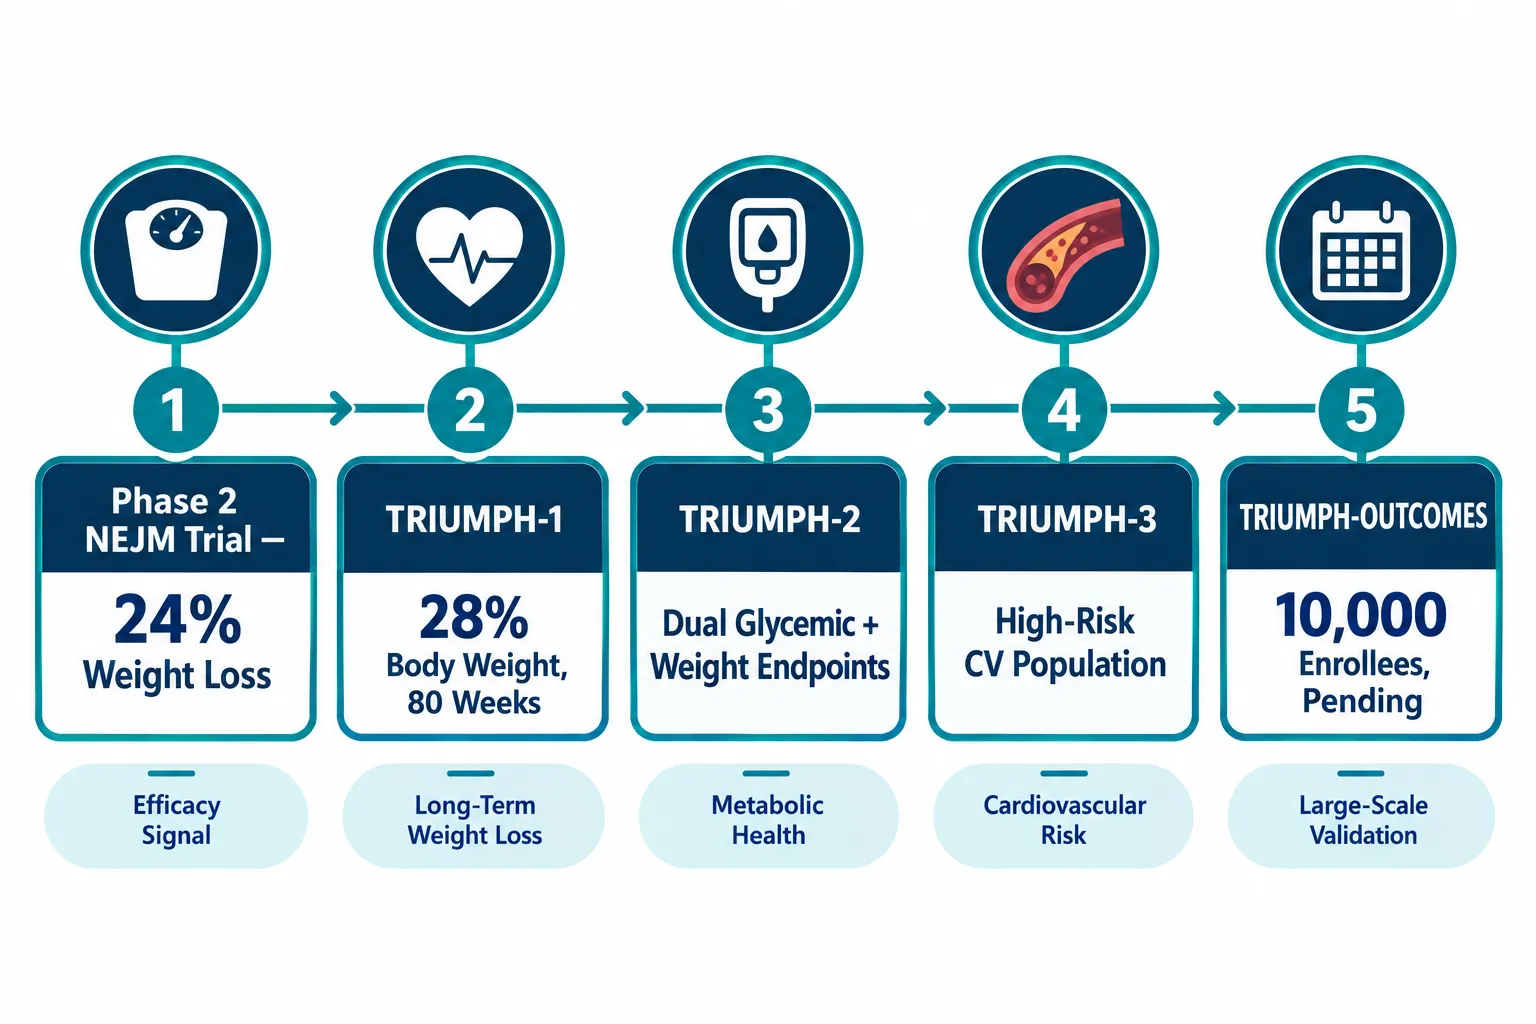
  • Phase 3 obesity data show approximately 28 percent mean weight loss at 80 weeks, with nearly 45 percent of participants achieving 30 percent or greater body weight reduction.
  • A1C improvements in the type 2 diabetes arm reinforce retatrutide's glycemic potential beyond weight loss alone.
  • Cardiovascular outcome data from the obesity-plus-established-CVD trial show MACE hazard ratios that are neutral to modestly favorable, but do not yet confirm a cardiovascular label claim.
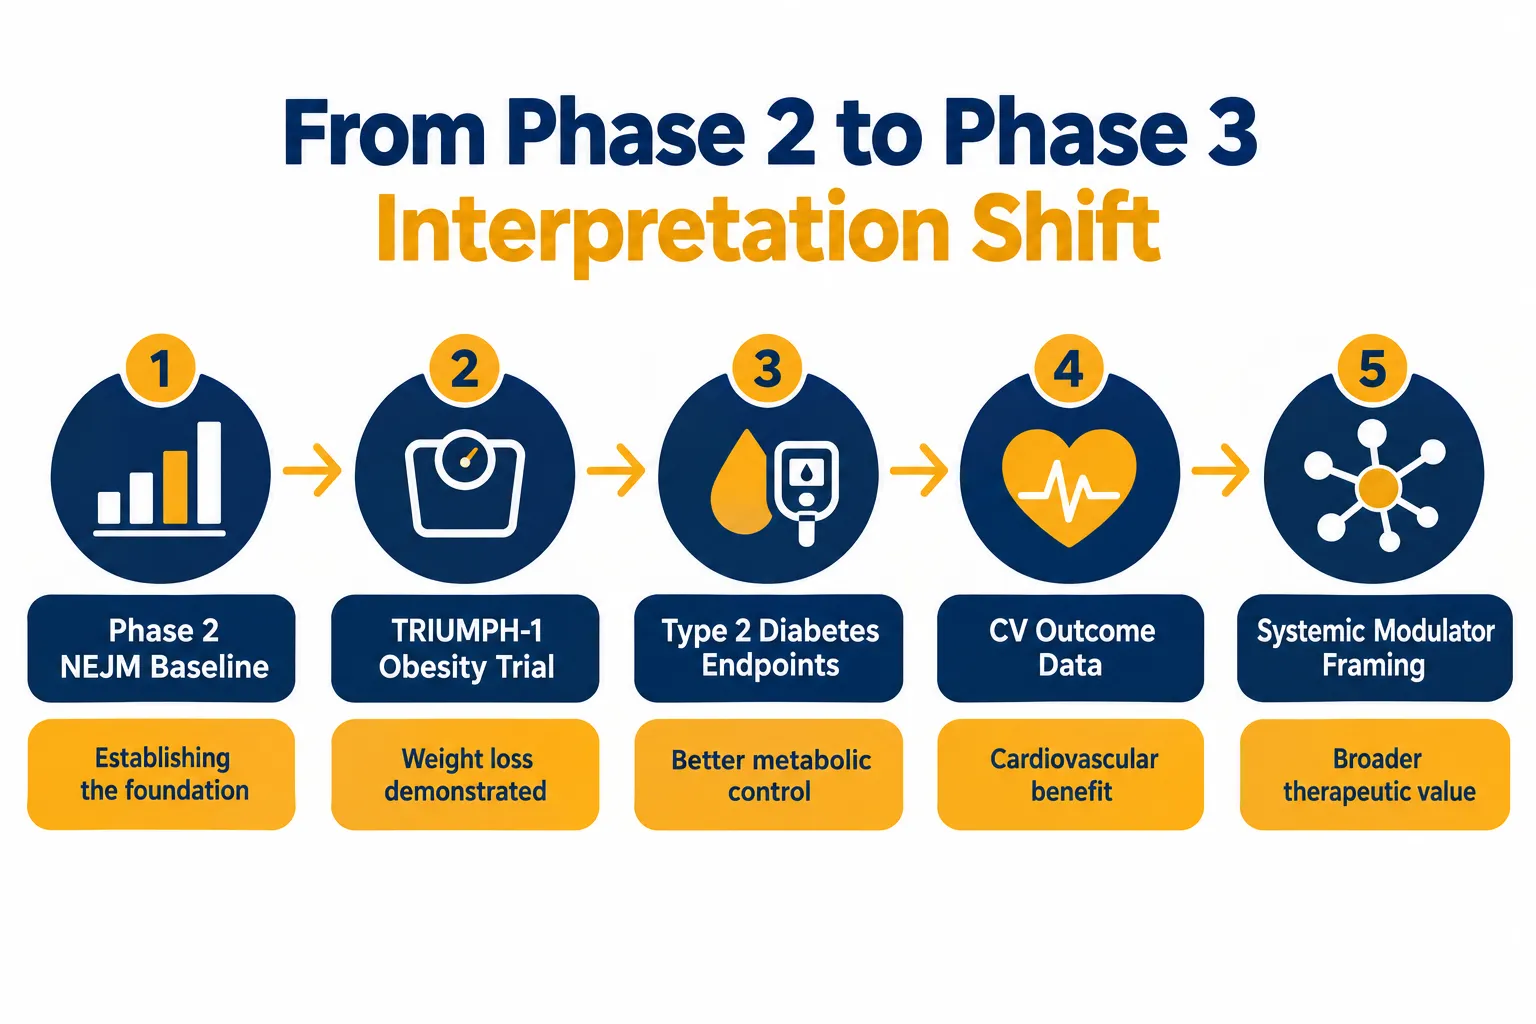
  • Phase 2 NEJM results are now viewed as a conservative baseline rather than a peak effect.
  • Retatrutide remains investigational; no regulatory approval has been granted as of 2026.

What the Obesity Efficacy Numbers Actually Mean

What the Obesity Efficacy Numbers Actually Mean

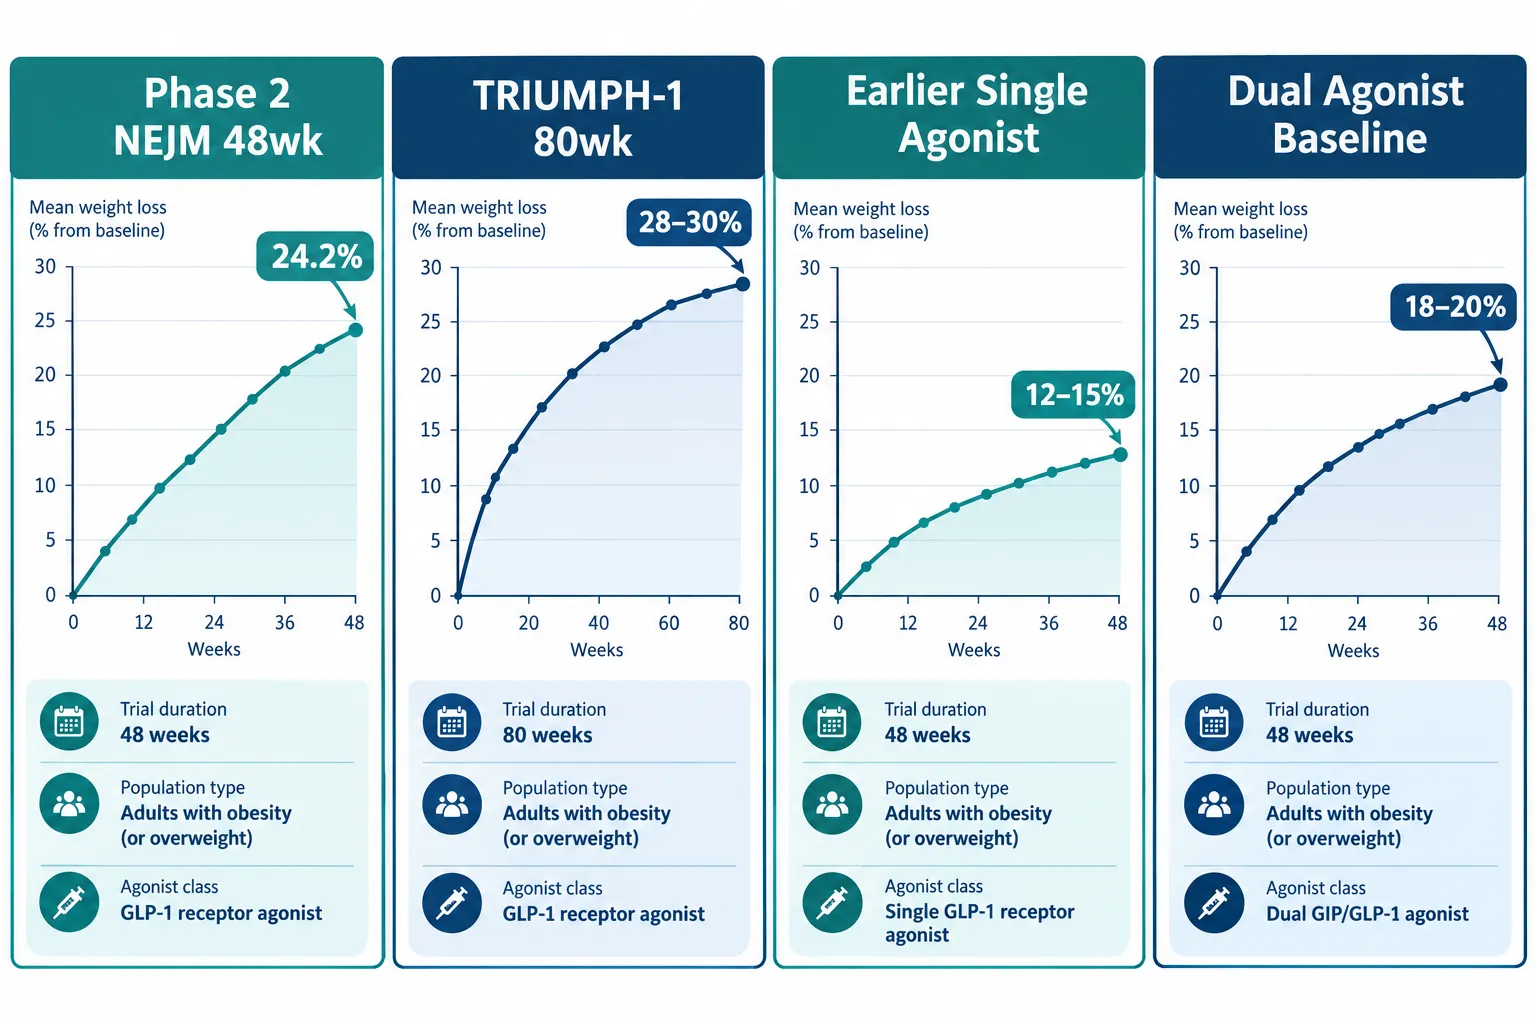
The headline figure from the pivotal obesity phase 3 program is approximately 28 percent mean body weight reduction at 80 weeks. That number demands context. Semaglutide 2.4 mg produced roughly 15 percent in its landmark trial; tirzepatide reached approximately 22 percent at its highest dose. Retatrutide's figure, if confirmed in peer-reviewed publication, would represent the largest mean weight loss ever reported for a pharmacological agent in a phase 3 obesity study.

Equally striking is the distribution of response. Roughly 45 percent of participants achieved 30 percent or greater weight loss, a threshold that, in earlier eras, was associated only with bariatric surgery. That figure matters because it shifts the clinical conversation from average outcomes to what a subset of patients might realistically expect.

"The ceiling for pharmacological weight loss may not have been reached yet, but retatrutide has moved it substantially higher."

Researchers tracking Retatrutide Clinical Trials note that discontinuation rates and tolerability data are critical to interpreting these numbers fairly. Gastrointestinal adverse events, nausea, vomiting, diarrhea, remain the most common side effects, consistent with the incretin class. Dropout rates tied to adverse events have not been negligible, which means the 28 percent figure reflects a population that tolerated the drug well enough to complete the protocol.


Glycemic and Cardiovascular Findings: Separating Signal from Claim

Glycemic and Cardiovascular Findings: Separating Signal from Claim

The type 2 diabetes arm of the phase 3 program adds a second layer of significance to the overall data picture. A1C reductions were clinically meaningful, and the breadth of cardiometabolic risk-factor improvements, including blood pressure, triglycerides, and waist circumference, reinforces the argument that retatrutide acts as a systemic cardiometabolic modulator rather than a simple appetite suppressant.

This distinction matters for research interpretation. When a compound simultaneously reduces body weight, lowers blood glucose, improves lipid panels, and reduces blood pressure, the mechanism of benefit becomes difficult to attribute to any single pathway. That complexity is scientifically valuable but also complicates regulatory discussions about labeling.

The cardiovascular outcome trial enrolled participants with obesity and established cardiovascular disease. MACE (major adverse cardiovascular events) hazard ratios came in neutral to modestly favorable, a result that is encouraging but not yet sufficient to support a dedicated cardiovascular risk-reduction label claim. Researchers reviewing Retatrutide Clinical Trial data consistently note that risk-factor improvement and hard cardiovascular event reduction are not interchangeable endpoints.

Key distinctions from the cardiovascular data:

  • Improved risk factors (blood pressure, lipids, weight) are confirmed across trials
  • MACE hazard ratios are neutral to modestly favorable, not definitively protective
  • A cardiovascular label claim would require additional event-driven data
  • Monitoring for cardiovascular and gastrointestinal signals remains active in ongoing maintenance studies

How Phase 3 Data Reshape Research Interpretation Going Forward

How Phase 3 Data Reshape Research Interpretation Going Forward

Understanding Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation requires stepping back from individual endpoints and examining what the data collectively signal about the incretin class ceiling.

Phase 2 results published in the New England Journal of Medicine were widely cited as evidence of exceptional efficacy. Phase 3 data now reframe those results as a conservative baseline, not a peak effect. That inversion is unusual in drug development, where phase 3 trials frequently show more modest outcomes than earlier studies due to broader, more heterogeneous populations.

Several interpretive questions now dominate expert commentary:

Research Question Why It Matters
Duration of effect Does weight loss plateau, reverse, or persist beyond 80 weeks?
Head-to-head trials How does retatrutide compare directly to tirzepatide or semaglutide?
Class generalizability Do triple agonism benefits extend to other compounds in development?
Real-world CV impact Will risk-factor gains translate to event reduction outside trial conditions?
Cost and access High efficacy is only meaningful if patients can sustain treatment

The TRIUMPH maintenance study is still active, and its results will be central to answering the durability question. Industry framing has leaned heavily on "next-generation" language, but researchers caution that approval timelines and cardiovascular label expectations remain separate conversations from efficacy data.

For those following the science of triple-receptor agonism alongside related peptide research, including work on IPA Sermorelin Stack Research and metabolic modulation, the retatrutide data set offers a rare opportunity to observe how mechanism-of-action complexity translates into clinical outcomes at scale.


Conclusion

Retatrutide Phase 3 Results represent a genuine inflection point in obesity and cardiometabolic research, not because any single number is record-breaking in isolation, but because the combination of weight loss magnitude, glycemic improvement, and cardiovascular signal breadth forces a reclassification of what this compound is and what it does.

Actionable next steps for researchers and clinicians following this space:

  1. Wait for peer-reviewed publication of full TRIUMPH-1 data before drawing conclusions from topline press releases.
  2. Distinguish between risk-factor improvements and hard cardiovascular event data when evaluating cardiovascular claims.
  3. Track the maintenance study for durability evidence beyond 80 weeks.
  4. Monitor head-to-head trial announcements, which will provide the most clinically relevant comparative data.
  5. Evaluate discontinuation and tolerability rates alongside efficacy figures to form a complete picture of real-world applicability.

Retatrutide remains investigational as of 2026. The data are compelling, the mechanistic rationale is strong, and the research interpretation is still evolving. That combination makes this one of the most closely watched drug development programs in metabolic medicine today.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-phase-3-results-how-weight-loss-a1c-and-cardiovascular-findings-chan.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-26 13:10:202026-09-26 13:10:20Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation
Retatrutide 2026 Trial Data vs Earlier Obesity Models: What Researchers Should Compare Before Drawing Conclusions

Retatrutide 2026 Trial Data vs Earlier Obesity Models: What Researchers Should Compare Before Drawing Conclusions

September 26, 2026/0 Comments/in Uncategorized/by

A single Phase 2 result, 24.2% mean body weight loss at 48 weeks, repositioned retatrutide as a potential turning point in obesity pharmacotherapy. Now, with the TRIUMPH program delivering Phase 3 data in 2026 and an FDA submission planned for early 2027, the research community faces a more demanding challenge: comparing these new numbers against earlier obesity models without letting headline figures obscure methodological differences that matter enormously.

Retatrutide 2026 trial data vs earlier obesity models: what researchers should compare before drawing conclusions is not simply a question of which drug produces a bigger number. It is a question of whether the numbers are even measuring the same thing across studies.

Key Takeaways

  • Retatrutide is a triple agonist (GLP-1, GIP, glucagon receptors), making direct comparisons to earlier single- or dual-agonist trials structurally complex.
  • TRIUMPH-1 reports up to 28-30% weight loss over 80 weeks, but population composition, baseline BMI, and trial duration differ from earlier benchmarks.
  • Estimand frameworks, dose escalation schedules, and completeness of adverse-event reporting vary significantly across generations of obesity trials.
  • Glycemic endpoints (A1C reduction) in TRIUMPH-2 require careful alignment with earlier diabetic-population studies before conclusions are drawn.
  • A transparent comparison framework covering at least seven variables is essential before any cross-trial efficacy claim holds scientific weight.

Why the Comparison Problem Is Harder Than It Looks

Why the Comparison Problem Is Harder Than It Looks

The excitement around retatrutide is understandable. The TRIUMPH-1 trial, targeting non-diabetic adults with obesity or overweight, reported weight reductions approaching 28-30% over 80 weeks, figures that have drawn frequent comparisons to bariatric surgery outcomes. TRIUMPH-2 extended the analysis to people with type 2 diabetes, and TRIUMPH-3 enrolled participants with severe obesity and established cardiovascular disease. A global registration trial completed enrollment in late 2025, broadening the population further.

Earlier obesity pharmacotherapy trials, including those for semaglutide and tirzepatide, ran for 68 weeks in many pivotal designs, enrolled populations with somewhat different baseline BMI distributions, and used dose escalation schedules that do not map cleanly onto retatrutide's protocol. Researchers exploring retatrutide clinical trial data will quickly notice that the surface-level weight-loss percentages are not the only variable worth examining.

Seven variables that demand alignment before cross-trial comparison:

Variable Why It Matters
Population baseline BMI Higher baseline BMI inflates absolute kg lost
Trial duration (weeks) Longer trials favor plateau-resistant compounds
Estimand framework Defines how dropouts and discontinuations are handled
Dose escalation schedule Steeper escalation can accelerate early weight loss
Completeness of AE reporting Affects tolerability profile comparisons
Glycemic endpoints (A1C) Critical for diabetic-population sub-analyses
Completers vs ITT analysis Changes the denominator and the headline figure

"A 30% weight loss figure means very little in isolation. The population, the protocol, and the statistical framework are the context that gives the number meaning."


Mechanism Differences That Complicate Direct Comparisons

Mechanism Differences That Complicate Direct Comparisons

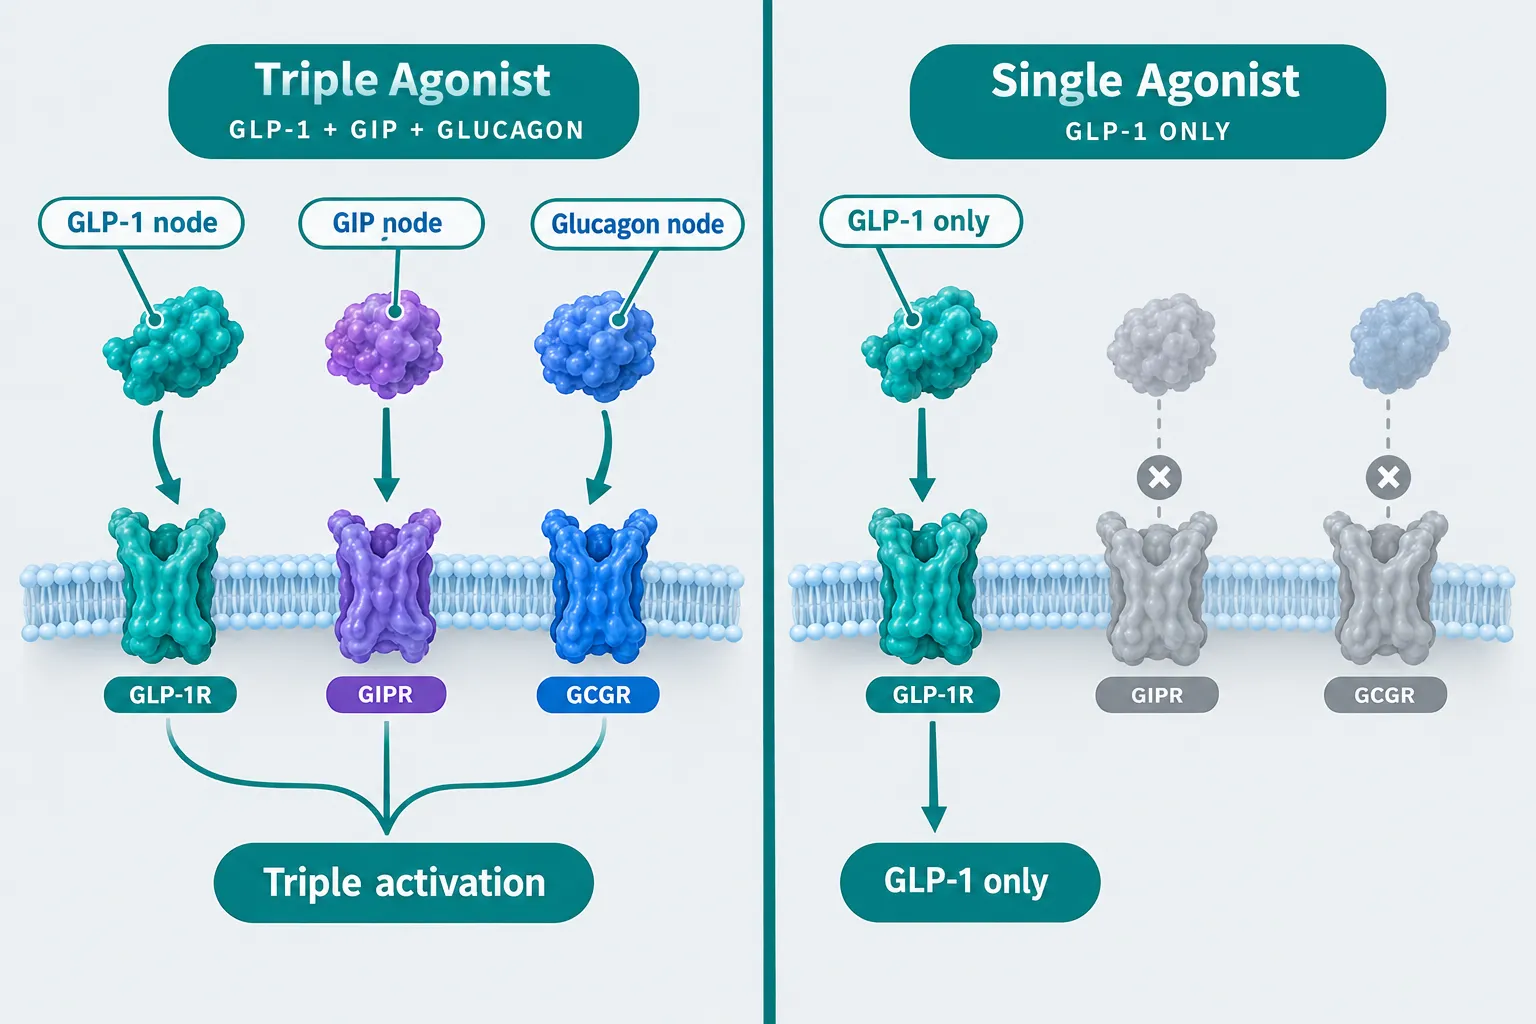
Retatrutide is a triple agonist, activating GLP-1, GIP, and glucagon receptors simultaneously. Earlier approved agents in this space are single agonists (GLP-1 only) or dual agonists (GLP-1 and GIP). This mechanistic distinction is not merely academic, it directly affects which endpoints are most informative and which adverse-event profiles are expected.

Glucagon receptor activation drives additional energy expenditure and lipolysis pathways that are absent in earlier models. This means that comparing retatrutide's weight-loss magnitude against a GLP-1 monotherapy trial without accounting for the additional metabolic burden on participants is methodologically incomplete. Researchers interested in the GLP-3 Reta product tag context will recognize that the triple-agonist classification is central to understanding why the efficacy signal appears larger.

Key mechanistic comparison points:

  • GLP-1 component: Shared with earlier agents; allows partial endpoint alignment on nausea, satiety, and gastric motility outcomes.
  • GIP component: Shared with tirzepatide; permits limited dual-agonist comparison, but retatrutide's GIP binding affinity differs.
  • Glucagon component: Unique to retatrutide in this class; drives hepatic fat reduction and thermogenesis outcomes not tracked in earlier trial designs.

For researchers also examining peptides with distinct metabolic profiles, the Tesamorelin science and sourcing overview offers a useful reference point for understanding how growth-hormone-releasing peptides address visceral fat through a separate mechanism, underscoring why mechanism-first framing matters in any comparative analysis.


Building a Transparent Framework for Cross-Trial Analysis

Building a Transparent Framework for Cross-Trial Analysis

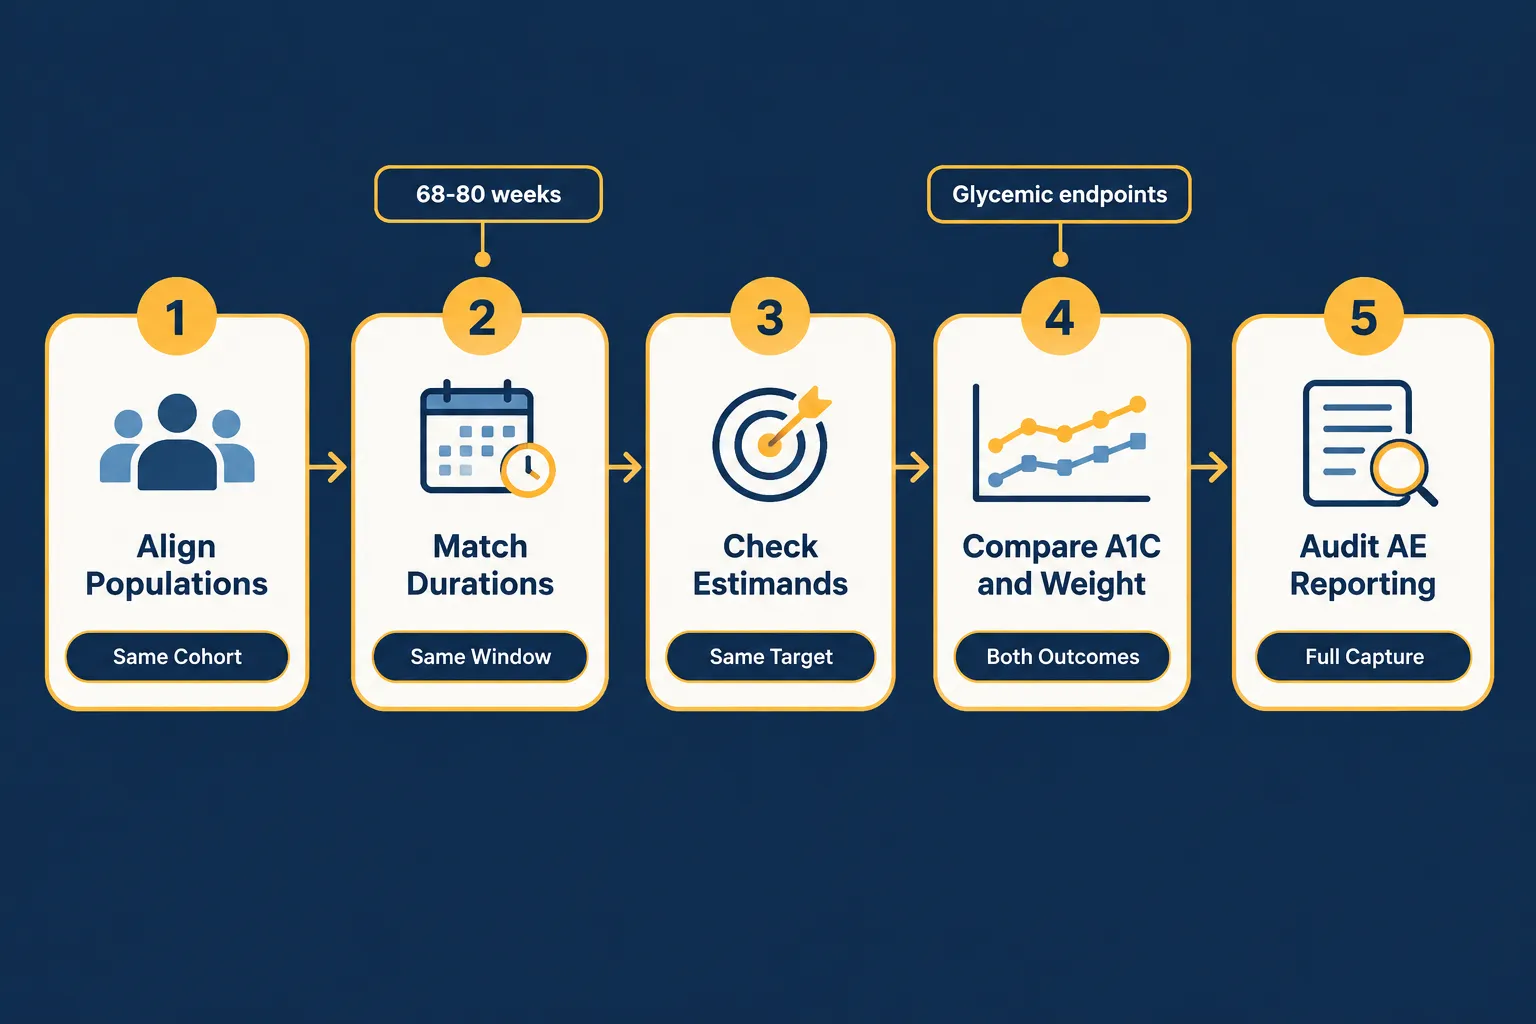
Retatrutide 2026 trial data vs earlier obesity models: what researchers should compare before drawing conclusions comes down to a structured, reproducible framework rather than selective headline matching. The following steps reflect best practice for cross-generational obesity trial comparison.

Step 1, Align populations. Confirm that baseline BMI, diabetes status, cardiovascular comorbidity burden, and geographic distribution are comparable. TRIUMPH-3's cardiovascular-disease population is not equivalent to a general overweight cohort.

Step 2, Match or adjust for duration. TRIUMPH-1's 80-week window exceeds the 68-week standard used in several earlier pivotal trials. Annualized weight-loss rates provide a more honest cross-trial metric than raw endpoint figures.

Step 3, Examine estimands explicitly. The treatment policy estimand (which includes all participants regardless of discontinuation) and the hypothetical estimand (which models outcomes assuming full adherence) produce materially different results. Earlier trials varied in which they pre-specified as primary.

Step 4, Compare A1C and glycemic outcomes in matched populations. TRIUMPH-2 data on weight and glycemic outcomes in type 2 diabetes must be benchmarked only against earlier trials that enrolled comparable diabetic populations with similar baseline A1C ranges.

Step 5, Audit adverse-event completeness. Gastrointestinal adverse events are consistently reported across generations, but cardiovascular safety signals, injection-site reactions, and lean mass loss data have not been uniformly collected. Retatrutide's glucagon component introduces a hepatic safety dimension that earlier single-agonist trial protocols did not systematically monitor.

Researchers building stacks or combination protocols may also find value in reviewing the IPA Sermorelin stack research resource for context on how multi-peptide frameworks are evaluated in research settings, and the SS-31 mitochondrial research tag for parallel work on metabolic and mitochondrial endpoints that may become relevant as retatrutide's full metabolic profile is characterized.

For researchers seeking the compound itself for preclinical work, the Reta 20mg product page provides sourcing details relevant to laboratory use.


Conclusion

The TRIUMPH program represents a genuine advance in obesity pharmacotherapy research, and the 2026 data deserve serious scientific attention. But the value of that data depends entirely on how carefully it is contextualized against earlier obesity models.

Actionable next steps for researchers:

  1. Build a comparison table that explicitly lists population baseline characteristics, trial duration, estimand type, and primary endpoint definition for each study being compared.
  2. Separate efficacy comparisons by population subgroup, non-diabetic, type 2 diabetes, and high-cardiovascular-risk cohorts require distinct reference studies.
  3. Request or locate full adverse-event appendices, not just summary tables, before drawing tolerability conclusions.
  4. Apply annualized weight-loss rates as a normalized cross-trial metric rather than relying on raw endpoint percentages.
  5. Track the FDA submission timeline (currently planned for Q1 2027) and review any agency briefing documents for additional population and estimand disclosures.

Retatrutide 2026 trial data vs earlier obesity models: what researchers should compare before drawing conclusions is ultimately a call for methodological discipline. The numbers are impressive, but the framework used to evaluate them will determine whether the conclusions hold.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-2026-trial-data-vs-earlier-obesity-models-what-researchers-should-co.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-26 13:05:022026-09-26 13:05:02Retatrutide 2026 Trial Data vs Earlier Obesity Models: What Researchers Should Compare Before Drawing Conclusions
GLP-3 Retatrutide vs. GLP2-T in Research: Metabolic Signaling Compared With Intestinal Epithelial Models

GLP-3 Retatrutide vs. GLP2-T in Research: Metabolic Signaling Compared With Intestinal Epithelial Models

September 25, 2026/0 Comments/in Uncategorized/by

Fewer than two decades separate the approval of the first GLP-2 analogue for short bowel syndrome and the emergence of a triple receptor agonist that some researchers are already calling the most potent pharmacologic weight-loss agent ever studied. These two compound classes share a naming convention that implies kinship, yet they address entirely different biological questions. Understanding the distinction between GLP-3 Retatrutide vs. GLP2-T in Research: Metabolic Signaling Compared With Intestinal Epithelial Models is not just a matter of terminology — it shapes which experimental models researchers choose, which readouts they measure, and how results should be interpreted.

Key Takeaways

  • The informal label "GLP-3" does not describe a recognized hormone; it is a colloquial term applied to retatrutide, a triple GLP-1/GIP/glucagon receptor agonist.
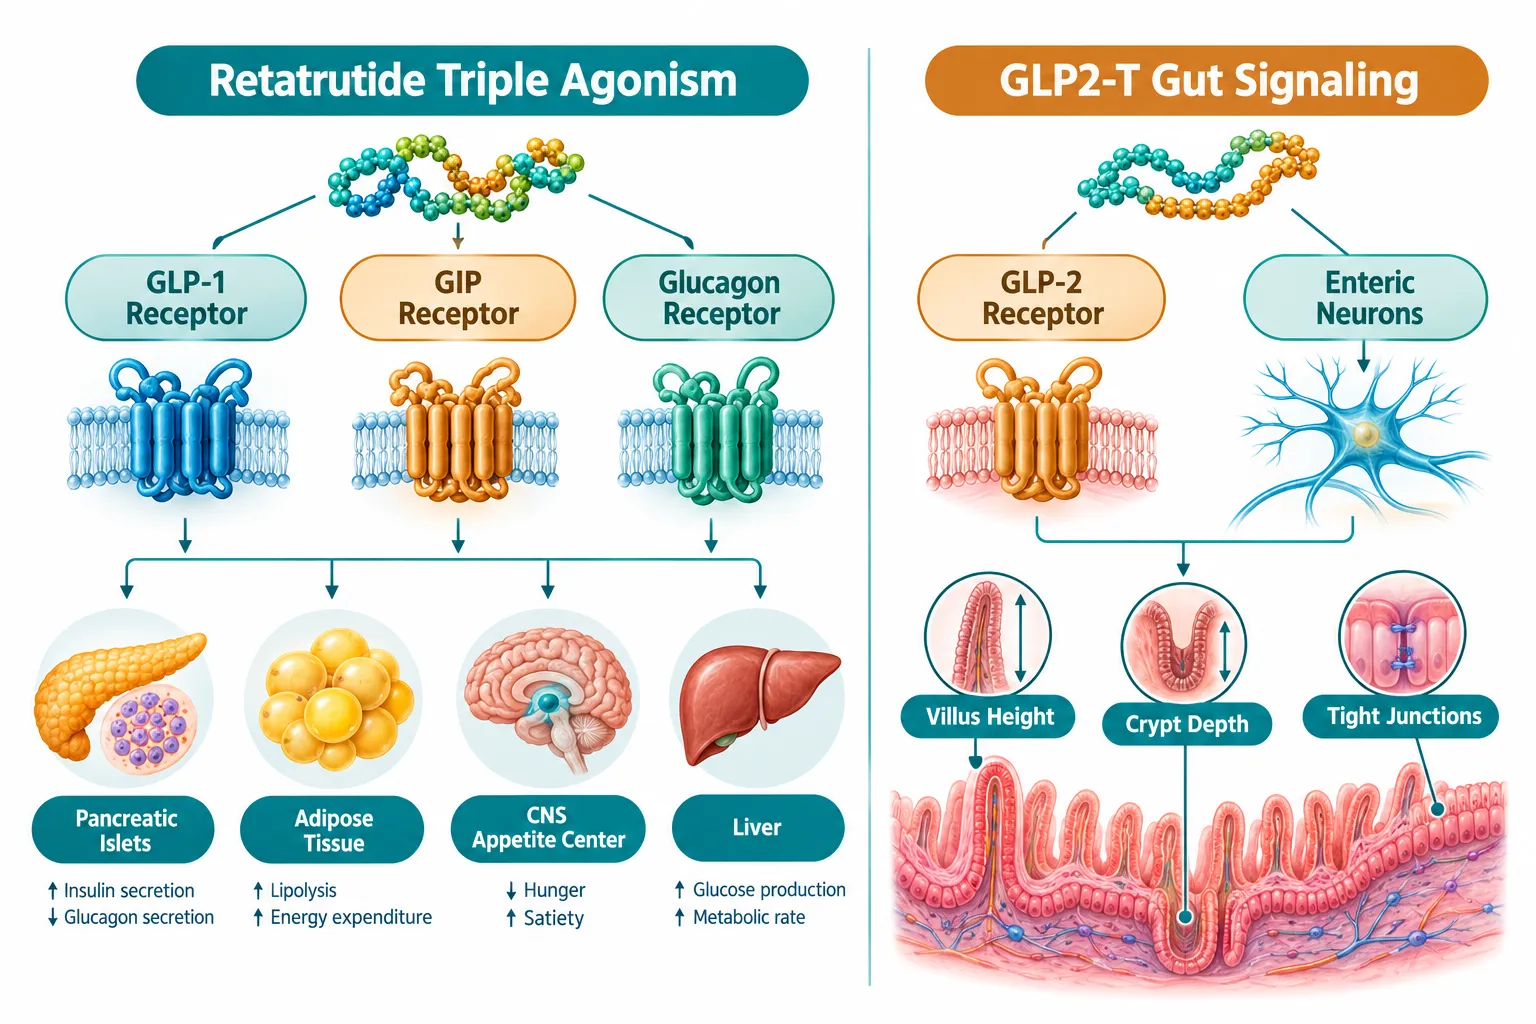
  • Retatrutide targets systemic metabolic signaling across the pancreas, adipose tissue, liver, and central nervous system.
  • GLP2-T (teduglutide) acts primarily through gut-localized GLP-2 receptors to support intestinal epithelial structure and barrier function.
  • These compounds require different preclinical and clinical model systems, and their readouts do not overlap.
  • Terminology precision matters: conflating these agents can lead to misaligned experimental design and misinterpretation of data.

Clarifying the "GLP-3" Label: What Retatrutide Actually Is

The phrase "GLP-3" circulates widely in media and consumer-facing content, but it does not correspond to a recognized incretin hormone or established drug class. Retatrutide — formally designated LY3437943 — is an investigational, once-weekly synthetic peptide engineered on a GIP backbone and conjugated to a C20 fatty di-acid moiety. That conjugation enables albumin binding, which extends the molecule's half-life and supports weekly dosing.

What makes retatrutide structurally and pharmacologically distinct is its simultaneous agonism at three receptors: the GLP-1 receptor, the GIP receptor, and the glucagon receptor. This triple agonism is not accidental. The molecule was designed through structure-based engineering to optimize activity at all three targets, creating a compound that simultaneously enhances insulin secretion, suppresses appetite through central pathways, and increases energy expenditure via glucagon-driven thermogenesis.

Clarifying the "GLP-3" Label: What Retatrutide Actually Is

For researchers exploring polypeptide peptides in cardiometabolic models, this triple mechanism positions retatrutide as a fundamentally systemic agent. Its receptor targets are distributed across pancreatic islets, adipose tissue, the liver, and the central nervous system — not concentrated in the intestinal epithelium.

Phase 2 clinical data published in the New England Journal of Medicine reported mean weight loss of up to 24.2% after 48 weeks in people with obesity without diabetes, and 16.9% after 36 weeks in those with type 2 diabetes. Emerging phase 3 data as of 2026 suggest average weight loss approaching 28% of baseline body weight. Gastrointestinal symptoms — nausea, diarrhea, vomiting — represent the most common adverse events, a profile broadly comparable to existing GLP-1 receptor agonists.

"Retatrutide's receptor targets span the pancreas, fat tissue, liver, and brain — not the intestinal epithelium."

Researchers sourcing material for preclinical work can review available GLP-3 Reta 10mg and Reta 20mg formats to understand dosing specifications relevant to experimental protocols.


GLP2-T: A Gut-Targeted Epithelial Biology Tool

GLP-2 and its primary clinical analogue teduglutide (GLP2-T) were developed to address a fundamentally different biological problem: intestinal structural failure. Foundational preclinical work established that GLP-2 analogues consistently enhanced mucosal growth, nutrient absorption, and functional recovery in animal models of gut epithelial injury. That work formed the scientific basis for teduglutide's approval in short bowel syndrome.

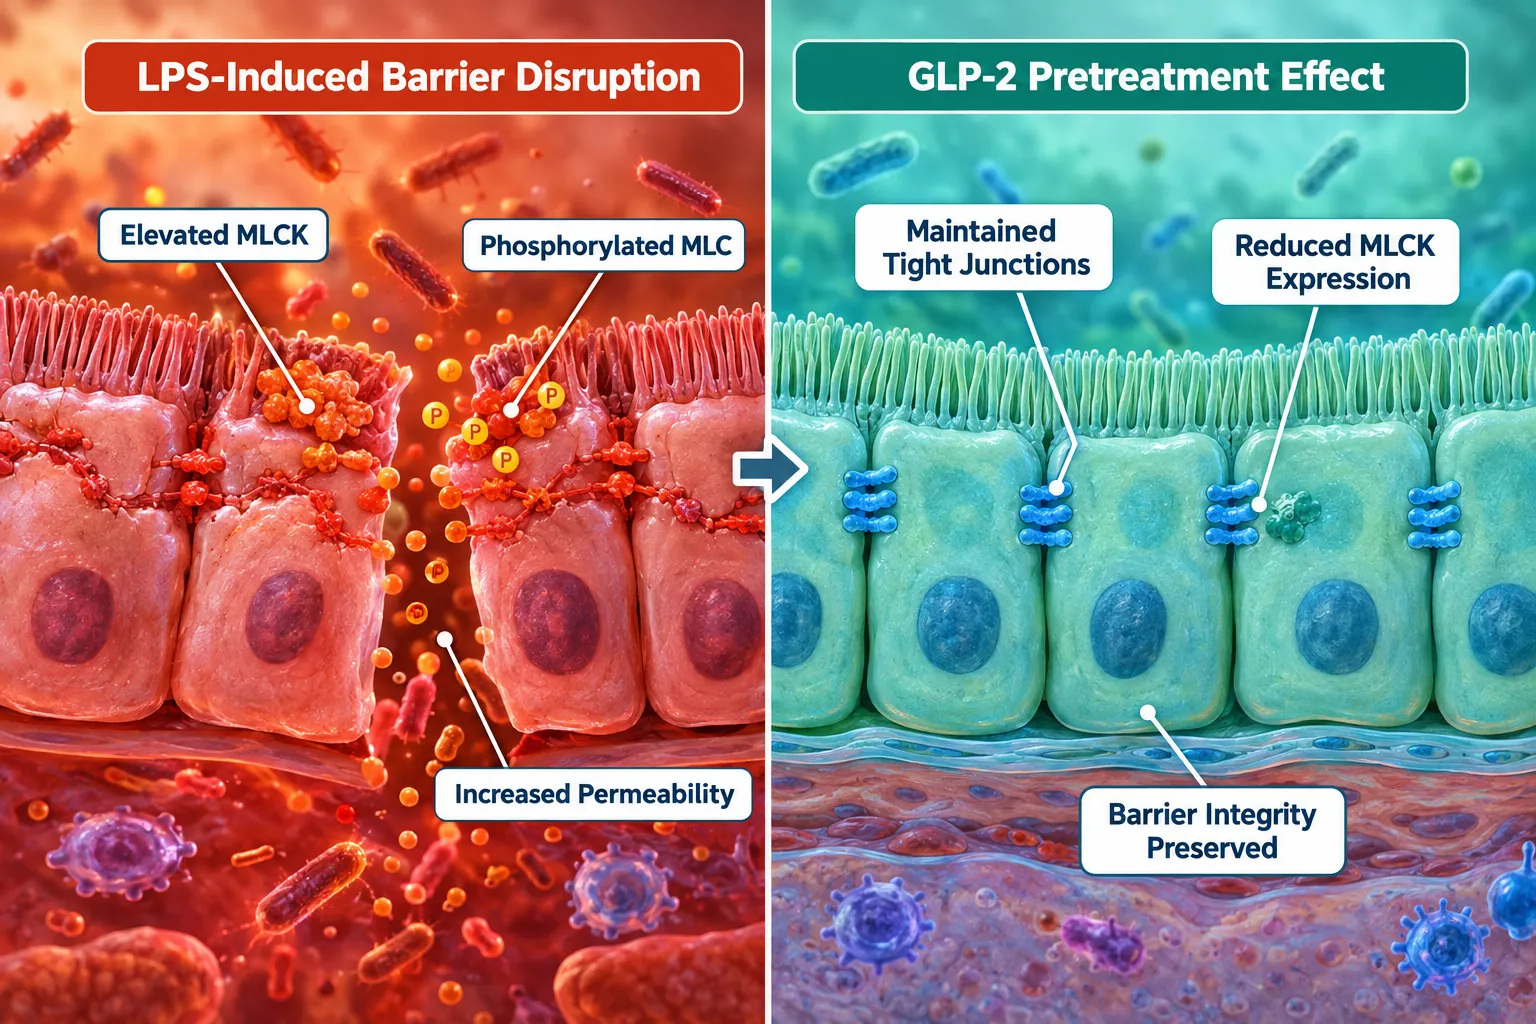
At the mechanistic level, GLP2-T acts through GLP-2 receptors located on enteric neurons and subepithelial cells. Downstream trophic signaling expands villus height and crypt depth, supporting absorptive surface area. Critically, GLP-2 signaling also helps maintain tight-junction integrity.

GLP2-T: A Gut-Targeted Epithelial Biology Tool

A well-characterized intestinal epithelial barrier study using piglet models and IPEC-J2 monolayer cultures demonstrated that GLP-2 pretreatment dose-dependently prevented lipopolysaccharide-induced increases in myosin light-chain kinase (MLCK) expression and phosphorylated myosin light chain (pMLC) across the duodenum, jejunum, and ileum. These findings point to a direct role for GLP-2 signaling in attenuating mucosal barrier injury at the cellular level.

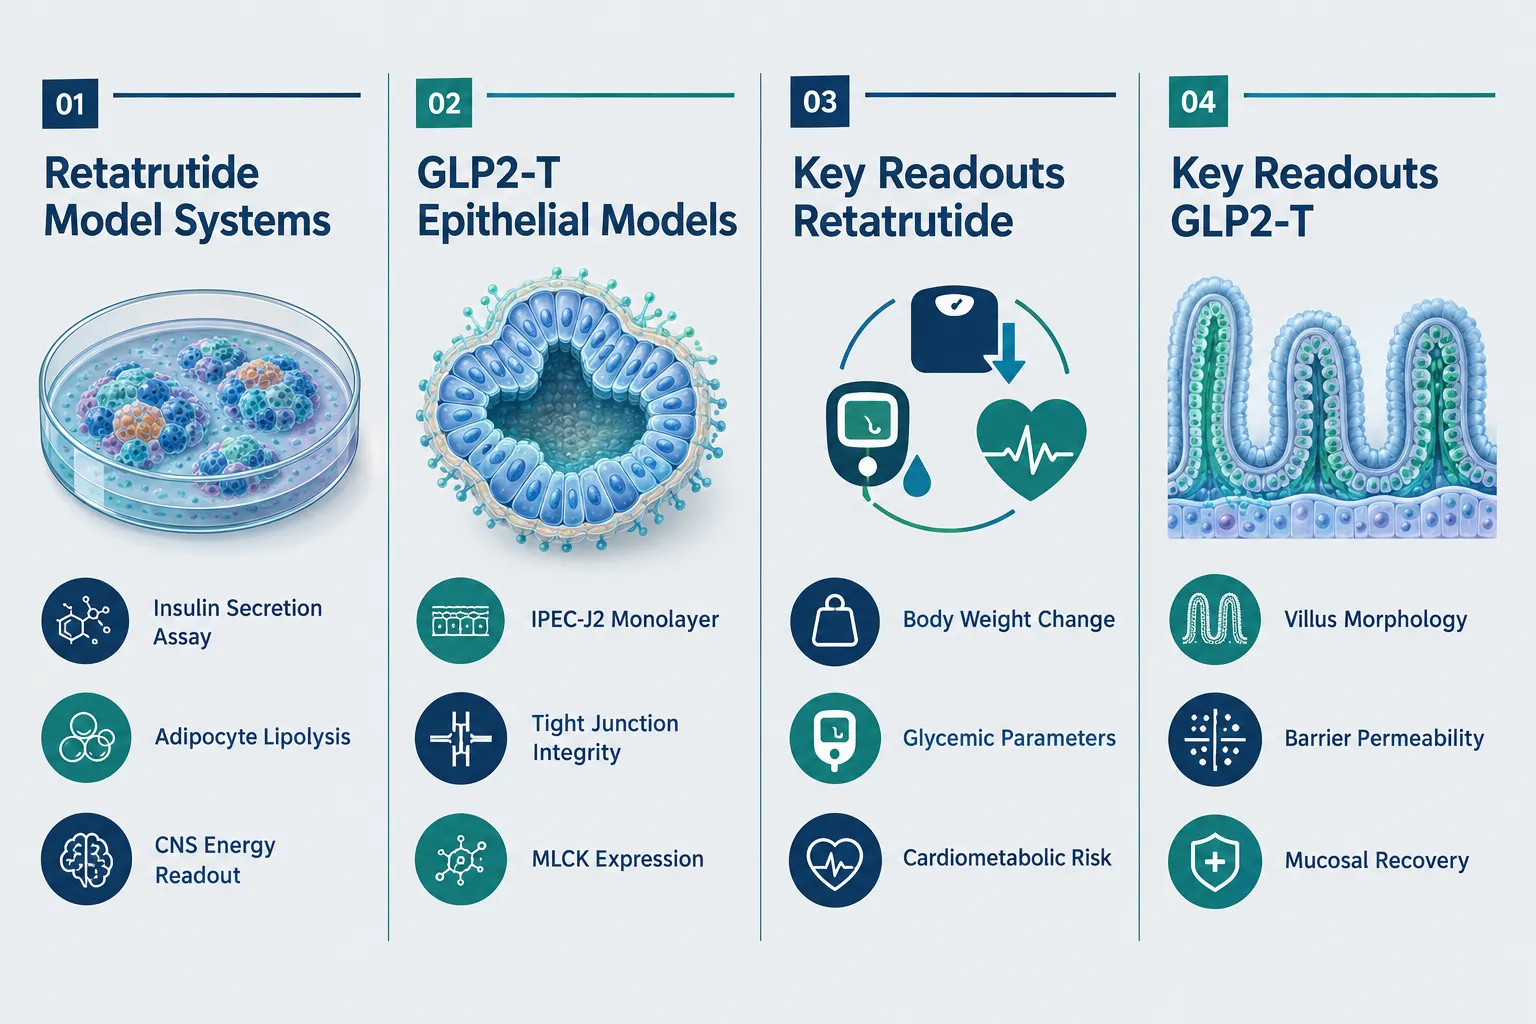
Relevant model systems for GLP2-T research include:

  • IPEC-J2 intestinal epithelial monolayer cultures
  • Piglet or rodent intestinal injury models
  • Organoid-based villus morphology assays
  • Transepithelial electrical resistance (TEER) measurements for barrier permeability

Key readouts center on villus height, crypt depth, tight-junction protein expression, MLCK activity, and barrier permeability — none of which are primary endpoints in retatrutide trials.


Comparing Model Selection and Readouts Across Both Research Contexts

The core distinction in GLP-3 Retatrutide vs. GLP2-T in Research: Metabolic Signaling Compared With Intestinal Epithelial Models lies in experimental design. Choosing the wrong model for either compound produces data that cannot be meaningfully interpreted.

Feature Retatrutide (GLP-3) GLP2-T (Teduglutide)
Receptor targets GLP-1R, GIPR, GcgR GLP-2R (enteric/subepithelial)
Primary tissue focus Pancreas, adipose, CNS, liver Intestinal epithelium
Preferred preclinical models Islet cell assays, adipocyte cultures, in vivo obesity models IPEC-J2 monolayers, piglet gut injury, organoids
Primary research readouts Body weight, glycemia, lipid profiles Villus height, tight-junction integrity, TEER
Regulatory status (2026) Investigational (Phase 3) Approved (short bowel syndrome)

For retatrutide, the Eli Lilly phase 3 program covers obesity with comorbidities, type 2 diabetes, knee osteoarthritis pain, obstructive sleep apnea, chronic low back pain, cardiovascular outcomes, renal outcomes, and metabolic dysfunction-associated steatotic liver disease. None of these endpoints involve direct measurement of intestinal epithelial morphology.

Comparing Model Selection and Readouts Across Both Research Contexts

Safety profiles also diverge. Retatrutide's adverse-event landscape is dominated by gastrointestinal symptoms tied to its GLP-1 component. GLP-2 analogues carry distinct concerns: fluid retention, intestinal mucosal hyperplasia, and potential neoplastic risk in susceptible patients. These differences drive continued research into epithelial signaling specificity and long-term histological effects for GLP2-T, while retatrutide's ongoing trials focus on cardiovascular and renal safety endpoints.

Researchers interested in broader peptide signaling contexts, including mitochondrial and renal biology, may find relevant background in SS-31 kidney health research and SS-31 mitochondrial research themes, which illustrate how mechanistic specificity shapes model selection across peptide classes.

For those specifically sourcing retatrutide analogs for research, the GLP-3 Reta CAG 10mg and GLP-3 Reta 20mg product pages provide specification details relevant to experimental planning.


Conclusion

The comparison of GLP-3 Retatrutide vs. GLP2-T in Research: Metabolic Signaling Compared With Intestinal Epithelial Models ultimately clarifies that these are not competing agents — they are tools designed for different scientific questions. Retatrutide is a systemic triple agonist built for cardiometabolic research, with clinical endpoints centered on body weight, glycemia, and organ-level outcomes. GLP2-T is a gut-targeted trophic agent built for epithelial biology, with readouts rooted in mucosal structure and barrier function.

Actionable steps for researchers:

  • Confirm receptor target distribution before selecting a model system; systemic metabolic signaling requires different assays than epithelial barrier biology.
  • Avoid applying the informal "GLP-3" label in formal research contexts — use the compound name retatrutide and specify its triple agonist mechanism.
  • Match readouts to mechanism: use TEER, MLCK, and villus morphology for GLP2-T work; use glycemic, lipolytic, and weight-related endpoints for retatrutide studies.
  • Monitor phase 3 data releases for retatrutide, as cardiovascular and renal safety data will significantly shape future research directions.
  • Recognize that teduglutide's approved status versus retatrutide's investigational status reflects different stages of translational development, not relative importance.

Precision in terminology and model selection is not bureaucratic caution — it is the foundation of reproducible, meaningful peptide research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/glp-3-retatrutide-vs-glp2-t-in-research-metabolic-signaling-compared-with-intest.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-25 13:03:582026-09-25 13:03:58GLP-3 Retatrutide vs. GLP2-T in Research: Metabolic Signaling Compared With Intestinal Epithelial Models
Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols

Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols

September 24, 2026/0 Comments/in Uncategorized/by

By August 2026, a key obesity Phase 3 study within the TRIUMPH program was officially marked as completed in clinical trial registries, a milestone that is already forcing researchers to rethink how they design, benchmark, and report nonclinical studies involving metabolic peptides. The Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols conversation is no longer speculative. The data are in, and they are reshaping the field.

Key Takeaways

  • Retatrutide's TRIUMPH Phase 3 program has produced weight-loss outcomes of up to 30% at 104 weeks, approaching bariatric surgery benchmarks.
  • Dual efficacy on body weight and glycemic control (up to 1.9-point A1c reduction) makes single-endpoint trial designs increasingly inadequate.
  • Conservative titration schedules and improved retention strategies are now a protocol necessity, not an option.
  • Multi-indication Phase 3 data covering knee OA, OSA, MASLD, and cardiovascular outcomes are expanding the scope of required comparator arms.
  • Retatrutide remains investigational as of late 2026, meaning all research use is subject to regulatory-oriented trial design standards.

The TRIUMPH Program: A Phase 3 Snapshot That Changes Benchmarks

Retatrutide is a first-in-class triple agonist targeting GIP, GLP-1, and glucagon receptors simultaneously. That triple mechanism is what separates it from existing approved therapies and from earlier dual-agonist candidates. For researchers working with retatrutide clinical trial data, the TRIUMPH program now provides the most complete Phase 3 picture available for any triple agonist.

The TRIUMPH Program: A Phase 3 Snapshot That Changes Benchmarks

The headline numbers are striking:

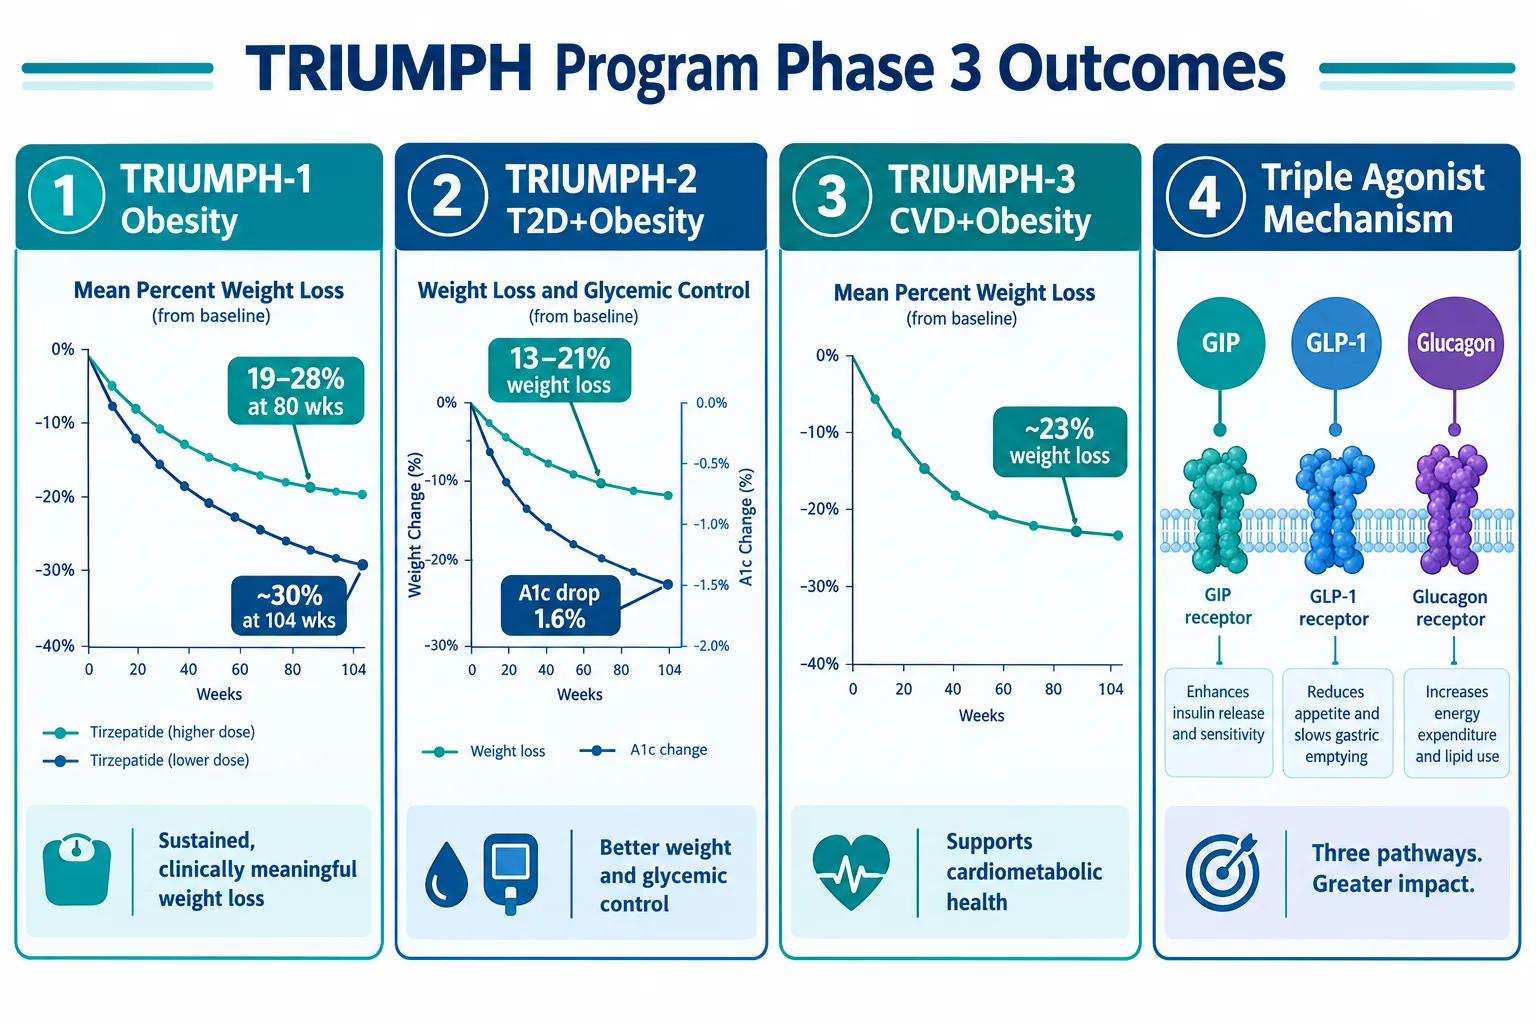
  • TRIUMPH-1 (obesity without diabetes): approximately 19-28% weight loss at 80 weeks, rising to roughly 30% at 104 weeks.
  • TRIUMPH-2 (obesity with type 2 diabetes): 13-21% weight loss plus up to a 1.6% A1c reduction over 80 weeks.
  • TRIUMPH-3 (severe obesity with established cardiovascular disease): approximately 23% weight loss with manageable discontinuation rates.

"Bariatric-like efficacy from a weekly injectable peptide is no longer a theoretical ceiling, TRIUMPH-3 data make it a documented outcome."

These figures introduce what some analysts are calling "de-obesification" endpoints, a term reflecting the normalization of BMI as a primary outcome rather than a secondary marker. For anyone reviewing GLP-1 Reta or GLP-3 Reta research-use compounds, understanding this endpoint shift is essential context.


How the 2026 Obesity and Diabetes Data Rewrites Protocol Design

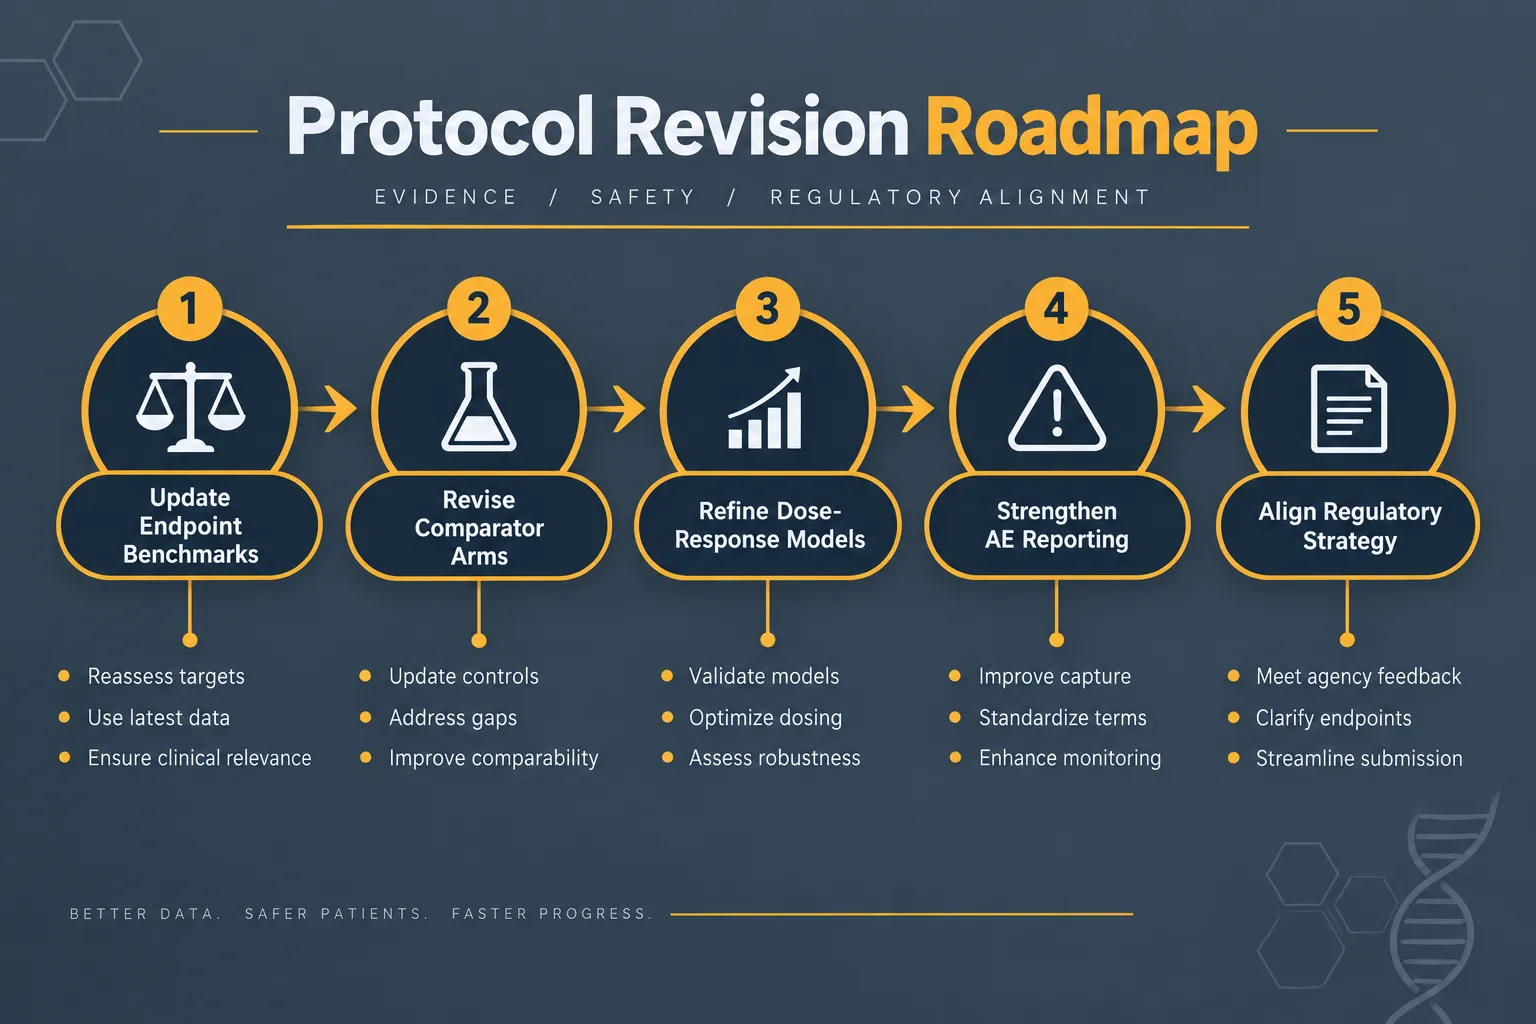
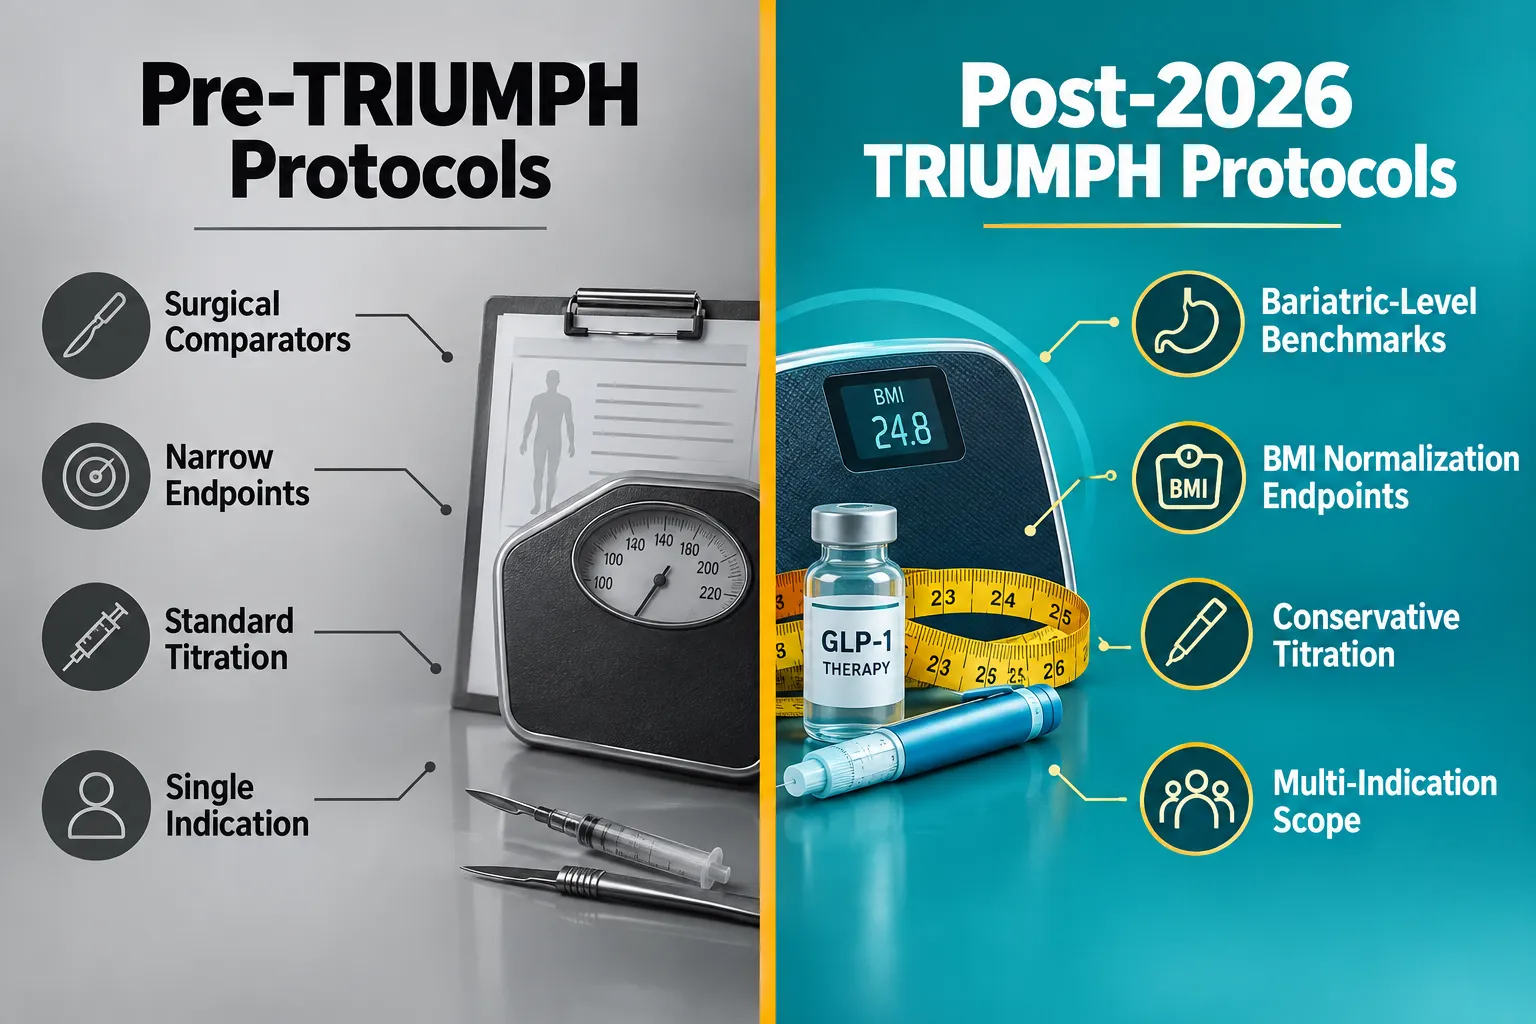
The Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols discussion centers on four concrete areas where existing study designs are now outdated.

1. Endpoint Selection

Single-endpoint designs that measure only weight or only glycemic control are no longer sufficient when the reference compound achieves both simultaneously. Researchers should now plan co-primary endpoints that capture:

  • Percent total body weight loss
  • A1c reduction
  • Cardiometabolic markers (blood pressure, lipids, inflammatory markers)
  • BMI normalization rates

2. Comparator Arm Selection

TRIUMPH data push the efficacy bar to near-surgical levels. Using older GLP-1 monotherapies as the sole active comparator now risks underestimating effect size. Protocol designers should consider:

Comparator Type Relevance Post-TRIUMPH
Older GLP-1 monotherapy Insufficient ceiling for effect-size modeling
Dual agonist (e.g., tirzepatide) Appropriate active comparator
Bariatric surgery outcomes Now a legitimate benchmark arm
Placebo only Acceptable but limits translational value

For broader context on how peptide mechanisms interact with metabolic pathways, the Peptides 101 for Research-Use Only Buyers resource provides a useful structural overview.

3. Dose-Response Modeling

3. Dose-Response Modeling

TRIUMPH safety data revealed that aggressive titration schedules drove higher discontinuation rates. This finding is directly actionable for nonclinical protocol design. Dose-response models should now incorporate:

  • Extended low-dose phases before escalation
  • Plateau detection windows to identify responders before maximum dosing
  • Dropout probability curves built from TRIUMPH discontinuation patterns

Researchers using Reta 10mg formulations in nonclinical settings should map titration schedules against TRIUMPH's published escalation timelines to ensure their models remain translatable.

4. Adverse-Event Reporting Standards

The TRIUMPH program's safety profile, primarily gastrointestinal events, has established a new floor for what must be captured and reported. Nonclinical adverse-event frameworks should now include structured tracking for:

  • Nausea and vomiting incidence by dose level
  • Time-to-onset relative to titration step
  • Severity grading aligned with TRIUMPH's published criteria

Expanding Scope: Multi-Indication Data and What Comes Next

The Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols story does not end with weight and glycemia. The TRIUMPH program includes at least seven additional Phase 3 datasets expected through 2026-2027, covering knee osteoarthritis, obstructive sleep apnea, metabolic-associated steatotic liver disease (MASLD), chronic pain, and cardiovascular-renal outcomes.

Expanding Scope: Multi-Indication Data and What Comes Next

This multi-indication expansion has two immediate implications for protocol designers:

  1. Organ-specific endpoints (liver stiffness scores, AHI reductions, joint function scales) will need to be incorporated into metabolic research designs that previously focused only on weight.
  2. Comparator arms will need to account for condition-specific active controls, not just metabolic benchmarks.

Researchers working in adjacent areas, such as mitochondrial function studies or growth hormone secretagogue research, should note that Tesamorelin data on visceral fat reduction may serve as a useful secondary comparator in MASLD-adjacent protocols.


Conclusion

The TRIUMPH Phase 3 program has fundamentally changed the reference frame for metabolic research protocols. Researchers who continue using pre-2026 endpoint structures, outdated comparator arms, or aggressive titration schedules will produce data that are difficult to interpret against the current evidence base.

Actionable next steps for protocol teams:

  1. Audit existing endpoint frameworks against TRIUMPH co-primary outcomes and add cardiometabolic markers where absent.
  2. Replace or supplement older GLP-1 monotherapy comparators with dual-agonist or bariatric-surgery benchmarks.
  3. Build conservative titration schedules into dose-response models and document dropout probability curves.
  4. Expand adverse-event capture to include time-to-onset data aligned with TRIUMPH's published safety criteria.
  5. Monitor the seven additional TRIUMPH Phase 3 readouts expected through 2027 and update protocols as each dataset publishes.

Retatrutide remains investigational as of late 2026. All research use must align with regulatory-oriented trial design standards. The data, however, are no longer a moving target, and protocol teams that adapt now will be best positioned when regulatory submissions begin.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-phase-3-results-in-2026-what-the-new-obesity-and-diabetes-data-chang.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-24 13:05:072026-09-24 13:05:07Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols
Retatrutide’s Triple-Agonist Data and Cardiometabolic Endpoints: Interpreting Weight, A1C, Lipids, Blood Pressure, and hsCRP Together

Retatrutide’s Triple-Agonist Data and Cardiometabolic Endpoints: Interpreting Weight, A1C, Lipids, Blood Pressure, and hsCRP Together

September 24, 2026/0 Comments/in Uncategorized/by

A single drug reducing body weight by nearly 28%, cutting triglycerides by 41%, lowering systolic blood pressure by more than 12 mmHg, and slashing an inflammatory marker by over 50%, all in the same trial, is not a routine clinical finding. That is the emerging picture from retatrutide's Phase 3 program, and it is reshaping how clinicians think about treating obesity-driven cardiometabolic disease. Understanding retatrutide's triple-agonist data and cardiometabolic endpoints means interpreting weight, A1C, lipids, blood pressure, and hsCRP together, not as separate outcomes, but as a coordinated metabolic signal.

Key Takeaways

  • Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, producing weight loss that substantially exceeds typical GLP-1 monotherapy.
  • Phase 3 trials report concurrent improvements in triglycerides, non-HDL cholesterol, systolic blood pressure, HbA1c, and hsCRP, suggesting system-wide metabolic remodeling.
  • An hsCRP reduction of roughly 51% at higher doses points to meaningful attenuation of systemic inflammation, a key driver of residual cardiovascular risk.
  • Hard cardiovascular outcome data remain pending from the TRIUMPH-OUTCOMES trial; current cardiometabolic benefits are surrogate endpoints, not confirmed event reductions.
  • The favorable data profile applies specifically to the regulated investigational compound; off-label, unregulated use carries serious safety risks.

How Triple Agonism Drives Broad Cardiometabolic Effects

How Triple Agonism Drives Broad Cardiometabolic Effects

Retatrutide is a once-weekly injectable peptide that activates three hormone receptors at once: GLP-1 (glucagon-like peptide-1), GIP (glucose-dependent insulinotropic polypeptide), and glucagon receptors. Most incretin-based drugs target one or two of these pathways. Adding glucagon receptor agonism is the key differentiator, because glucagon signaling increases energy expenditure in the liver and adipose tissue, a thermogenic effect that stacks on top of the appetite suppression and insulin sensitization driven by GLP-1 and GIP.

For a broader comparison of how polypeptide agents like retatrutide differ mechanistically from classic small-molecule drugs, see this detailed breakdown of polypeptide peptides in cardiometabolic models.

This three-pathway activation explains why the cardiometabolic effects observed in trials are so broad. Weight loss alone does not fully account for the lipid, blood pressure, and inflammatory improvements seen, the receptors targeted by retatrutide are expressed in the liver, heart, vasculature, and adipose tissue, meaning the drug acts on multiple organ systems simultaneously.

Key receptor targets and their primary metabolic roles:

Receptor Primary Metabolic Role
GLP-1 Appetite suppression, insulin secretion, gastric emptying
GIP Fat cell signaling, glucose uptake, insulin potentiation
Glucagon Hepatic fat oxidation, energy expenditure, lipolysis

Interpreting the Phase 3 Trial Data: Weight, A1C, Lipids, Blood Pressure, and hsCRP Together

Interpreting the Phase 3 Trial Data: Weight, A1C, Lipids, Blood Pressure, and hsCRP Together

The most rigorous way to evaluate retatrutide's triple-agonist data and cardiometabolic endpoints is to read the Phase 3 results as a unified dataset rather than isolated numbers.

TRIUMPH-1: Obesity Without Diabetes

In TRIUMPH-1, participants without type 2 diabetes lost approximately 28% of body weight, roughly 70 lb, over 80 weeks. The cardiometabolic secondary endpoints were equally striking:

  • Triglycerides: reduced by up to 41.0%
  • Non-HDL cholesterol: reduced by 24.2%
  • Systolic blood pressure: reduced by 12.3 mmHg
  • Waist circumference: reduced by 24.1 cm

These are not modest shifts. A 41% triglyceride reduction and a 24% non-HDL reduction represent clinically meaningful movement in atherogenic lipid burden.

TRIUMPH-2 and TRANSCEND-T2D-1: Adding Glycemic Control

In TRIUMPH-2 (obesity with type 2 diabetes), participants lost up to 20.8% of body weight while lowering HbA1c by up to 1.6 percentage points. TRANSCEND-T2D-1 showed HbA1c reductions of up to 2.0 percentage points from a mean baseline of 7.9%, alongside improvements in triglycerides, non-HDL cholesterol, blood pressure, and waist circumference.

The critical insight here: retatrutide improved glycemia and adiposity without forcing a trade-off between glucose control and weight loss, a common limitation with older diabetes drugs.

TRIUMPH-3: High-Risk Cardiovascular Population and the hsCRP Signal

TRIUMPH-3 enrolled patients with severe obesity and established cardiovascular disease. At the 12 mg dose, results included:

  • Weight loss: approximately 22-23% (~55 lb) at 80 weeks
  • Triglycerides: reduced by 37.0%
  • Non-HDL cholesterol: reduced by 16.5%
  • Systolic blood pressure: reduced by 9.3 mmHg
  • Waist circumference: reduced by 19.0 cm
  • hsCRP: reduced by 51.2%

The hsCRP finding deserves special attention. High-sensitivity C-reactive protein is a validated marker of systemic inflammation and an independent predictor of cardiovascular events. A reduction of more than 50% in a high-risk population suggests retatrutide may be addressing inflammatory cardiovascular risk, not just metabolic risk factors. Whether this translates into fewer heart attacks and strokes remains an open question until TRIUMPH-OUTCOMES reports.


What the Data Does, and Does Not, Confirm

What the Data Does, and Does Not, Confirm

Interpreting retatrutide's triple-agonist data and cardiometabolic endpoints together requires a clear distinction between what the trials have proven and what they suggest.

What is established from company-reported clinical data:

  • Large, sustained weight loss across diverse populations
  • Concurrent improvements in atherogenic lipids, glycemic control, blood pressure, and inflammatory markers
  • A safety profile broadly consistent with other incretin-based therapies, with gastrointestinal side effects being the most common

What remains hypothetical:

  • Whether surrogate endpoint improvements will translate into reduced major adverse cardiovascular events (MACE)
  • Long-term durability of cardiometabolic benefits beyond 80 weeks
  • Whether outcomes will match those of bariatric surgery in long-term cardiovascular and microvascular endpoints

The TRIUMPH-OUTCOMES trial, enrolling approximately 10,000 individuals with atherosclerotic cardiovascular disease and/or chronic kidney disease, is designed to answer the MACE question directly. Until those results are available, the combined weight, A1C, lipid, blood pressure, and hsCRP improvements are powerful surrogate signals, not confirmed outcome data.

Eli Lilly has indicated plans to file for obesity approval in 2027, with development extending to sleep apnea, osteoarthritis, chronic low back pain, and metabolic liver disease, reflecting confidence in the breadth of the cardiometabolic profile.

A note on research-use compounds: Intense interest in retatrutide has generated gray-market products marketed under its name. Regulators have documented cases of acute liver toxicity and serious esophageal injury linked to counterfeit peptide use. The favorable cardiometabolic data described throughout this article applies exclusively to the regulated investigational compound used in controlled clinical trials. Those interested in research-grade materials should consult verified sources such as the GLP-3 Reta CAG 10mg product or review available Reta 20mg research options through properly tested suppliers. Additional research compound options are available under buy Reta peptide and GLP-3 Reta listings for laboratory use only.


Conclusion

Retatrutide's Phase 3 data present a coherent cardiometabolic story: weight loss of 20-28%, triglyceride reductions exceeding 37-41%, HbA1c improvements of up to 2 percentage points, systolic blood pressure reductions of 9-12 mmHg, and hsCRP reductions above 50%, all occurring together in the same patients. Reading these endpoints in isolation understates the drug's potential; reading them together reveals a compound that may address multiple drivers of cardiovascular disease simultaneously.

Actionable next steps for clinicians and researchers:

  1. Follow TRIUMPH-OUTCOMES enrollment and interim analyses for MACE data, this is the trial that will confirm or qualify the surrogate endpoint story.
  2. Treat the hsCRP signal as a hypothesis-generating finding, not a proven anti-inflammatory outcome, until mechanistic and outcomes data are available.
  3. Distinguish clearly between company-reported Phase 3 data and extrapolations applicable to research-use compounds, which operate under entirely different regulatory and safety frameworks.
  4. Monitor Eli Lilly's anticipated 2027 regulatory filing for the full label scope, which will clarify approved indications and patient selection criteria.

The convergence of weight, glycemic, lipid, blood pressure, and inflammatory improvements in a single agent is scientifically significant. The next step is confirming that these numbers translate into longer, healthier lives.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutides-triple-agonist-data-and-cardiometabolic-endpoints-interpreting-weig.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-24 13:04:422026-09-24 13:04:42Retatrutide’s Triple-Agonist Data and Cardiometabolic Endpoints: Interpreting Weight, A1C, Lipids, Blood Pressure, and hsCRP Together
Atorvastatin, LDL Cholesterol, and Metabolic Peptides: Where MOTS-c, 5-Amino-1MQ, and GLP-3 Retatrutide Fit in Lipid Research

Atorvastatin, LDL Cholesterol, and Metabolic Peptides: Where MOTS-c, 5-Amino-1MQ, and GLP-3 Retatrutide Fit in Lipid Research

September 20, 2026/0 Comments/in Uncategorized/by

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'Atorvastatin, LDL Cholesterol' in crisp white modern sans-serif on a deep navy semi-transparent overlay panel, centered with 8% safe margins from every edge, no character touches the edge, two balanced lines. Background: high-resolution editorial medical illustration of a cross-section of a human artery with visible LDL cholesterol plaques, surrounded by floating molecular structures of statin compounds and peptide chains in teal and gold tones, clinical yet visually striking, magazine-cover aesthetic, sharp editorial lighting, professional 2-color palette of navy and teal with white typography.","content":["Annotated mechanism-of-action diagram (1536×1024 landscape) showing atorvastatin's HMG-CoA reductase inhibition pathway in a clean white-background infographic style. Four labeled stages arranged left to right: Stage 1 callout 'HMG-CoA Reductase Blocked' pointing to liver cell diagram, Stage 2 callout 'LDL Receptors Upregulated' with arrow to hepatocyte surface, Stage 3 callout 'LDL Cleared from Blood' showing artery cross-section, Stage 4 callout 'Target: <55 mg/dL ASCVD' with a bold threshold bar. Thin callout lines, teal-and-navy palette, numbered stages, editorial medical-guide polish, no pricing or dollar amounts.","Three-panel side-by-side comparison infographic (1536×1024 landscape) contrasting retatrutide, MOTS-c, and 5-Amino-1MQ as metabolic research agents. Left panel heading 'Retatrutide GLP-1/GIP/Glucagon' with bullet labels: Triple receptor agonist, LDL down ~15-20 percent, TG down ~40 mg/dL, Phase 3 trials. Center panel heading 'MOTS-c Mitochondrial Peptide' with bullet labels: NAD+ regulation, AMPK activation, Lipid oxidation, Preclinical stage. Right panel heading '5-Amino-1MQ NNMT Inhibitor' with bullet labels: NAD+ preservation, Lipogenesis suppressed, Fat oxidation shift, Animal models only. Clean white background, warm amber and teal accent colors, thin dividing lines, editorial infographic polish, callout lines to molecular icons per panel.","Split-screen editorial landscape image (1536×1024) illustrating layered cardiometabolic therapy concept. Left half: warm-lit clinical laboratory bench with statin pill bottles, a cholesterol panel blood report showing LDL values, and a molecular model of atorvastatin in amber studio lighting. Right half: cool-toned scientific research setting with peptide vials labeled MOTS-c and retatrutide, a digital screen showing triglyceride and metabolic pathway data, blue-white laboratory lighting. A bold center divider line with short label 'Established vs Investigational' separating the two halves. High-contrast magazine composition, deep focus, editorial quality."]

Professional landscape hero image () with a reading "Atorvastatin, LDL Cholesterol". CRITICAL TYPOGRAPHY RULES: render the

Cardiovascular disease remains the leading cause of death globally, yet only about half of high-risk patients reach their LDL-cholesterol targets even with statin therapy. That gap has driven intense research into metabolic peptides, molecules that act on mitochondrial signaling, NAD+ biology, and incretin receptors, as potential complements to classic lipid-lowering drugs. Understanding atorvastatin, LDL cholesterol, and metabolic peptides: where MOTS-c, 5-Amino-1MQ, and GLP-3 Retatrutide fit in lipid research requires a clear look at what each agent does, how the mechanisms compare, and what the current evidence actually supports.

Key Takeaways

  • Atorvastatin remains the primary pharmacological tool for reaching stringent LDL-C targets, with high-intensity dosing producing LDL reductions of 41-61%.
  • The 2026 ACC/AHA dyslipidemia guidelines set explicit LDL-C thresholds as low as less than 55 mg/dL for very-high-risk ASCVD patients.
  • Retatrutide, a triple receptor agonist targeting GLP-1, GIP, and glucagon pathways, shows meaningful lipid improvements in clinical trials but remains investigational with no regulatory approval as of 2026.
  • MOTS-c and 5-Amino-1MQ operate through mitochondrial and NAD+ pathways that influence lipid metabolism, but both remain in preclinical research stages.
  • Expert analysis increasingly frames future lipid management as layered therapy: statins for LDL targets plus metabolic peptides for residual cardiometabolic risk.

How Atorvastatin Shapes LDL-C Management in 2026

Atorvastatin works by blocking HMG-CoA reductase, the rate-limiting enzyme in hepatic cholesterol synthesis. When the liver produces less cholesterol internally, it upregulates LDL receptors on its surface, pulling more LDL particles out of circulation. The result is a dose-dependent and clinically significant reduction in atherogenic lipoproteins.

How Atorvastatin Shapes LDL-C Management in 2026

Dose, response data are well established. Depending on the dose and the patient's baseline risk profile, atorvastatin produces:

Lipid Marker Typical Reduction Range
Total Cholesterol 30-46%
LDL-C 41-61%
Triglycerides 14-33%
HDL-C Modest increase

The 2026 ACC/AHA multisociety dyslipidemia guideline has reintroduced explicit numeric LDL-C targets for the first time in over a decade. Very-high-risk ASCVD patients now have a target of less than 55 mg/dL, high-risk patients less than 70 mg/dL, and borderline-to-intermediate risk patients less than 100 mg/dL. High-intensity statins like atorvastatin are confirmed as the primary agents to reach these thresholds.

The core limitation: statins address LDL-C powerfully but leave residual risk from elevated triglycerides, visceral adiposity, insulin resistance, and inflammation. This is precisely where metabolic peptide research becomes relevant.

Retatrutide and GLP-Class Peptides: Lipid Effects Beyond Weight Loss

Retatrutide is a first-in-class investigational triple receptor agonist that activates GLP-1, GIP, and glucagon receptors simultaneously. While most public attention has focused on its dramatic weight loss results, its lipid effects are clinically noteworthy in their own right.

A 2026 systematic review and meta-analysis of randomized retatrutide trials found statistically significant improvements across multiple lipid markers. Total cholesterol fell by a weighted mean of approximately 21.88 mg/dL, LDL-C dropped by roughly 13.10 mg/dL, and triglycerides declined by about 40.90 mg/dL, all with p-values below 0.0001. HDL-C showed no meaningful change.

Phase 2 obesity trial data add further context. Non-HDL cholesterol fell approximately 15-17%, LDL declined around 15-20% in higher-dose regimens, and triglycerides dropped by roughly 32-44% across datasets. The mechanism appears to involve glucagon receptor agonism reducing circulating ANGPTL3 and ANGPTL8 concentrations, which in turn enhances lipoprotein lipase activity and alters hepatic lipoprotein production.

Important context: As of mid-2026, retatrutide has no approval from the FDA, EMA, or any other major regulator. Phase 3 TRIUMPH trial data are generating significant scientific interest, but retatrutide remains strictly investigational.

For researchers exploring the GLP peptide landscape, the GLP-3 peptides for sale category and retatrutide clinical trial resources provide useful context on current research-grade availability and trial status. Those interested in the broader incretin class can also review GLP-1 peptides research context for comparison.

MOTS-c and 5-Amino-1MQ: Mitochondrial Pathways in Lipid Research

This is where the science of atorvastatin, LDL cholesterol, and metabolic peptides diverges most sharply from conventional cardiology. MOTS-c and 5-Amino-1MQ do not lower LDL-C through receptor upregulation or incretin signaling. Instead, they act on the metabolic machinery inside cells.

MOTS-c and 5-Amino-1MQ: Mitochondrial Pathways in Lipid Research

MOTS-c is a mitochondria-derived peptide encoded within the 12S rRNA region of mitochondrial DNA. Research models show it activates AMPK, regulates NAD+ metabolism, and promotes fatty acid oxidation over lipid storage. In preclinical settings, MOTS-c treatment is associated with improved insulin sensitivity and reduced lipid accumulation in metabolic tissues. For researchers, MOTS-c 10mg is available as a research-grade compound, and the broader MOTS-c peptide category provides additional options.

5-Amino-1MQ is a selective nicotinamide N-methyltransferase (NNMT) inhibitor. By blocking NNMT, it preserves intracellular NAD+ levels, decreases N1-methylnicotinamide, suppresses lipogenesis, and shifts adipocytes toward fat oxidation. In diet-induced obese mouse models, these effects translate to reduced fat mass and improved metabolic markers, with triglycerides often the most sensitive lipid marker to change.

Critical regulatory note: Neither MOTS-c nor 5-Amino-1MQ has an FDA-approved indication. 5-Amino-1MQ has no publicly documented IND or registered Phase 1-3 human trial as of 2026. All efficacy and safety data remain confined to cell culture and animal models.

No major 2025-2026 guideline integrates MOTS-c or 5-Amino-1MQ into formal LDL-cholesterol management pathways. Their role in lipid research is mechanistic and exploratory, not clinical.

For a broader grounding in how these peptide classes relate to each other mechanistically, the Peptides 101 for research-use only buyers guide covers structure, mechanisms, and classification in accessible detail.

Layered Therapy: How These Agents Complement Each Other in Research Models

The emerging framework in expert and industry analysis is one of layered cardiometabolic management:

  1. High-intensity statins (atorvastatin) address the primary LDL-C target mandated by guidelines.
  2. GLP-class investigational agents (retatrutide) tackle residual risk from weight, blood pressure, triglycerides, and glycemic status.
  3. Mitochondrial and NAD+ pathway agents (MOTS-c, 5-Amino-1MQ) represent a third layer focused on cellular metabolic efficiency, still preclinical, but scientifically compelling.

Layered Therapy: How These Agents Complement Each Other in Research Models

This layered model does not imply clinical equivalence. Atorvastatin has decades of randomized controlled trial data and guideline endorsement. Retatrutide has Phase 2 and emerging Phase 3 data. MOTS-c and 5-Amino-1MQ have preclinical data only. Researchers and clinicians must weigh evidence tiers carefully.

The intersection of atorvastatin, LDL cholesterol, and metabolic peptides: where MOTS-c, 5-Amino-1MQ, and GLP-3 Retatrutide fit in lipid research is ultimately a question about mechanism, evidence quality, and therapeutic stage, not a single unified treatment protocol.

For those exploring adjacent peptide research areas, resources on peptides and polypeptides in endocrine pharmacology provide useful mechanistic context on how different peptide classes interface with metabolic signaling systems.

Conclusion

Atorvastatin remains the cornerstone of LDL-C reduction in 2026, backed by robust dose-response data and explicit guideline targets that demand aggressive lipid lowering in high-risk patients. Retatrutide adds a meaningful investigational layer with documented lipid improvements, particularly for triglycerides, through a distinct incretin and glucagon receptor mechanism. MOTS-c and 5-Amino-1MQ represent the frontier of mitochondrial and NAD+ biology in lipid research, with scientifically interesting preclinical profiles but no clinical validation yet.

Actionable next steps for researchers:

  • Use current ACC/AHA LDL-C targets as the benchmark when designing lipid-focused research protocols.
  • Distinguish clearly between agents with clinical trial data (retatrutide) and those with only preclinical data (MOTS-c, 5-Amino-1MQ) when framing research questions.
  • Monitor Phase 3 TRIUMPH retatrutide data and ADA presentations for updated lipid endpoints.
  • Ensure all peptide compounds used in research settings are sourced from verified, high-purity suppliers with documented testing.
  • Consult regulatory guidance before any translational or human-adjacent research involving investigational peptides.

The science connecting statins, incretin-class peptides, and mitochondrial signaling molecules is evolving rapidly. Staying current with both guideline updates and preclinical mechanistic literature is essential for anyone working at this intersection.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/atorvastatin-ldl-cholesterol-and-metabolic-peptides-where-mots-c-5-amino-1mq-and.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-20 13:06:502026-09-20 13:06:50Atorvastatin, LDL Cholesterol, and Metabolic Peptides: Where MOTS-c, 5-Amino-1MQ, and GLP-3 Retatrutide Fit in Lipid Research
Metoprolol, Beta-Blockers, and Incretin Peptide Research: What Labs Track When Combining GLP-3 Retatrutide With Cardioactive Drugs

Metoprolol, Beta-Blockers, and Incretin Peptide Research: What Labs Track When Combining GLP-3 Retatrutide With Cardioactive Drugs

September 20, 2026/0 Comments/in Uncategorized/by

Roughly 40% of adults with obesity also carry a diagnosis of cardiovascular disease, making the overlap between metabolic therapies and heart-active medications not a niche concern but a near-universal research challenge. As retatrutide advances through Phase 3 TRIUMPH trials with striking cardiometabolic data, the question of how this triple-incretin agonist interacts with beta-blockers like metoprolol has become one of the most pressing topics in preclinical and translational lab design for 2026.

This guide addresses the core of that challenge: what measurements, markers, and safety checkpoints researchers track when studying metoprolol, beta-blockers, and incretin peptide research, specifically what labs track when combining GLP-3 retatrutide with cardioactive drugs in structured experimental frameworks.

Key Takeaways

  • Retatrutide activates GLP-1, GIP, and glucagon receptors simultaneously, creating a multi-axis effect on heart rate, blood pressure, and glucose that overlaps directly with beta-blocker pharmacology.
  • Metoprolol and other beta-blockers can mask hypoglycemia symptoms, a risk that becomes more complex when combined with incretin agents that lower glucose through multiple pathways.
  • Researchers tracking this combination should monitor cardiac rhythm, hemodynamics, glucose metabolism, and renal function as a minimum panel.
  • Emerging arrhythmia signals from triple-incretin agonist data make QTc interval and Holter monitoring critical additions to any lab protocol.
  • Purity and consistency of research-grade peptides are foundational to reproducible results in this interaction space.

Understanding the Pharmacological Overlap

Understanding the Pharmacological Overlap

Retatrutide is a triple-receptor agonist targeting GLP-1R, GIPR, and glucagon receptors. Each of these pathways carries cardiovascular relevance. GLP-1 receptor activation raises cyclic AMP in cardiac tissue, which increases heart rate and cardiac output. Glucagon receptor activation has similar chronotropic effects. In isolation, these actions are manageable. When layered onto a beta-blocker framework, the dynamics shift.

Metoprolol is a selective beta-1 adrenergic antagonist. Its primary cardiac effects include reduced heart rate, lower blood pressure, and decreased myocardial oxygen demand. When a researcher or clinician introduces a GLP-class incretin peptide alongside metoprolol, the two agents are working on overlapping but mechanistically distinct pathways, one suppressing adrenergic drive, the other stimulating cAMP-mediated chronotropy.

The result is not simply additive or subtractive. The net heart rate effect depends on receptor density, dose, and individual variability. In vitro models studying GLP-3 peptide interactions need to account for this bidirectional tension explicitly in their experimental design.

A second layer of complexity involves glucose regulation. Beta-blockers are known to blunt the sympathoadrenal response to hypoglycemia, the very response that triggers awareness of low blood sugar. Incretin peptides lower glucose through multiple mechanisms. When combined, the hypoglycemia masking effect of metoprolol can obscure a glucose drop that the incretin agent has contributed to, creating a safety blind spot that labs must monitor actively.

Core Lab Panels for Metoprolol, Beta-Blockers, and Incretin Peptide Research

Core Lab Panels for Metoprolol, Beta-Blockers, and Incretin Peptide Research

Designing a rigorous monitoring protocol for this combination requires tracking across four domains: cardiac rhythm, hemodynamics, metabolic markers, and safety biomarkers.

Cardiac Rhythm and Electrophysiology

The most immediate concern when combining GLP-3 retatrutide with cardioactive drugs is arrhythmia risk. Emerging data from triple-incretin agonist research has flagged QTc prolongation as a signal requiring active surveillance. Labs should include:

  • 12-lead ECG at baseline and at defined intervals
  • QTc interval measurement using Fridericia or Bazett correction
  • Holter monitoring for continuous rhythm capture over 24-48 hours
  • Resting heart rate tracked across all time points

When peptide dosing protocols are adjusted, rhythm data should be recaptured to identify dose-dependent changes.

Hemodynamic Monitoring

Blood pressure response is a critical variable. Retatrutide has shown meaningful reductions in systolic blood pressure in TRIUMPH trial data. Metoprolol compounds this effect. Labs should record:

Measurement Frequency
Systolic blood pressure Every experimental session
Diastolic blood pressure Every experimental session
Mean arterial pressure Calculated at each time point
Orthostatic BP change Standing vs. supine, at peak drug effect

Orthostatic hypotension is a real concern in this combination and should not be treated as a secondary endpoint.

Metabolic and Glucose Panel

Given the hypoglycemia masking risk described above, glucose monitoring must be granular:

  • Fasting glucose at baseline and post-dose
  • Insulin and C-peptide levels
  • HbA1c for longer study windows
  • Glucagon levels, given retatrutide's direct glucagon receptor activity

Researchers sourcing GLP-3 retatrutide for lab use should confirm purity documentation, as impurities in the peptide can introduce confounding metabolic signals.

Safety Biomarkers

A complete panel also includes:

  • Serum electrolytes (potassium and magnesium, given arrhythmia risk)
  • Catecholamine levels (epinephrine, norepinephrine) to detect suppressed stress response
  • Renal function markers (creatinine, eGFR) given the renal clearance pathways of both drug classes
  • Liver enzymes for hepatic safety tracking

Designing the Monitoring Protocol: What Labs Track When Combining GLP-3 Retatrutide With Cardioactive Drugs

Designing the Monitoring Protocol: What Labs Track When Combining GLP-3 Retatrutide With Cardioactive Drugs

A well-structured protocol for studying metoprolol, beta-blockers, and incretin peptide research does not treat these measurements as isolated checkboxes. It builds them into a timeline that reflects the pharmacokinetics of both agents.

Retatrutide has a long half-life, approximately 6 days in clinical data, which means steady-state effects accumulate across a study window. Metoprolol, by contrast, has a much shorter half-life of 3-7 hours for standard formulations. This mismatch means:

  1. Baseline measurements must be captured before either agent is introduced.
  2. Acute monitoring should align with metoprolol's peak effect window (1-2 hours post-dose).
  3. Trough monitoring should capture the period when metoprolol is at its lowest plasma level but retatrutide remains pharmacologically active.
  4. Washout tracking should extend beyond retatrutide's half-life to confirm return to baseline cardiac and metabolic parameters.

Researchers working with GLP-3 nasal spray formulations or alternative delivery formats should adjust absorption timing windows accordingly, as pharmacokinetic profiles differ from injectable preparations.

For labs using complementary cardioprotective peptides alongside this combination, resources on SS-31 peptide research considerations may provide useful parallel monitoring frameworks, given SS-31's mitochondrial cardioprotective mechanism.

Sensory and Neurological Safety Signals

Phase 3 retatrutide data has introduced a newer sensory safety signal, peripheral sensory changes in a subset of subjects. While the mechanism is not fully characterized, labs studying this combination should include basic neurological assessments and track any reported sensory changes systematically. This is particularly relevant when beta-blockers are co-administered, as they can independently affect peripheral circulation.

Conclusion

The intersection of GLP-3 retatrutide and beta-blocker pharmacology is not a simple additive equation. For researchers designing protocols around metoprolol, beta-blockers, and incretin peptide research, what labs track when combining GLP-3 retatrutide with cardioactive drugs must span cardiac rhythm, hemodynamics, glucose metabolism, electrolytes, and emerging sensory signals, all mapped against the distinct pharmacokinetic timelines of each agent.

Actionable next steps for research teams in 2026:

  • Establish a pre-study baseline panel covering all four monitoring domains before any agent is introduced.
  • Build time-matched monitoring windows that reflect both the short half-life of metoprolol and the extended half-life of retatrutide.
  • Treat hypoglycemia masking as a primary, not secondary, safety concern in any protocol combining beta-blockers with incretin peptides.
  • Confirm third-party purity testing on all research-grade peptides used; explore GLP-3 peptide options with documented quality assurance.
  • Document sensory safety signals as a standard endpoint given the emerging data from triple-incretin agonist trials.

Rigorous lab design in this space is not just a procedural formality, it is the foundation for generating data that can meaningfully inform the next generation of cardiometabolic research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/metoprolol-beta-blockers-and-incretin-peptide-research-what-labs-track-when-comb.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-20 13:06:342026-09-20 13:06:34Metoprolol, Beta-Blockers, and Incretin Peptide Research: What Labs Track When Combining GLP-3 Retatrutide With Cardioactive Drugs
Page 4 of 8«‹23456›»
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top