Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: retatrutide

GLP3 Peptide vs Retatrutide: Why the Naming Confusion Matters in Obesity Research

GLP3 Peptide vs Retatrutide: Why the Naming Confusion Matters in Obesity Research

June 11, 2026/0 Comments/by Pure Tested

Over 1 billion adults worldwide live with obesity, and the race to find more effective treatments has never moved faster. Yet one of the biggest obstacles in 2026 is not a scientific one — it is a language problem. The debate around GLP3 Peptide vs Retatrutide: Why the Naming Confusion Matters in Obesity Research is more than a semantic argument. When researchers, clinicians, and consumers use the same term to mean different things, the consequences range from misread study data to misguided purchasing decisions.
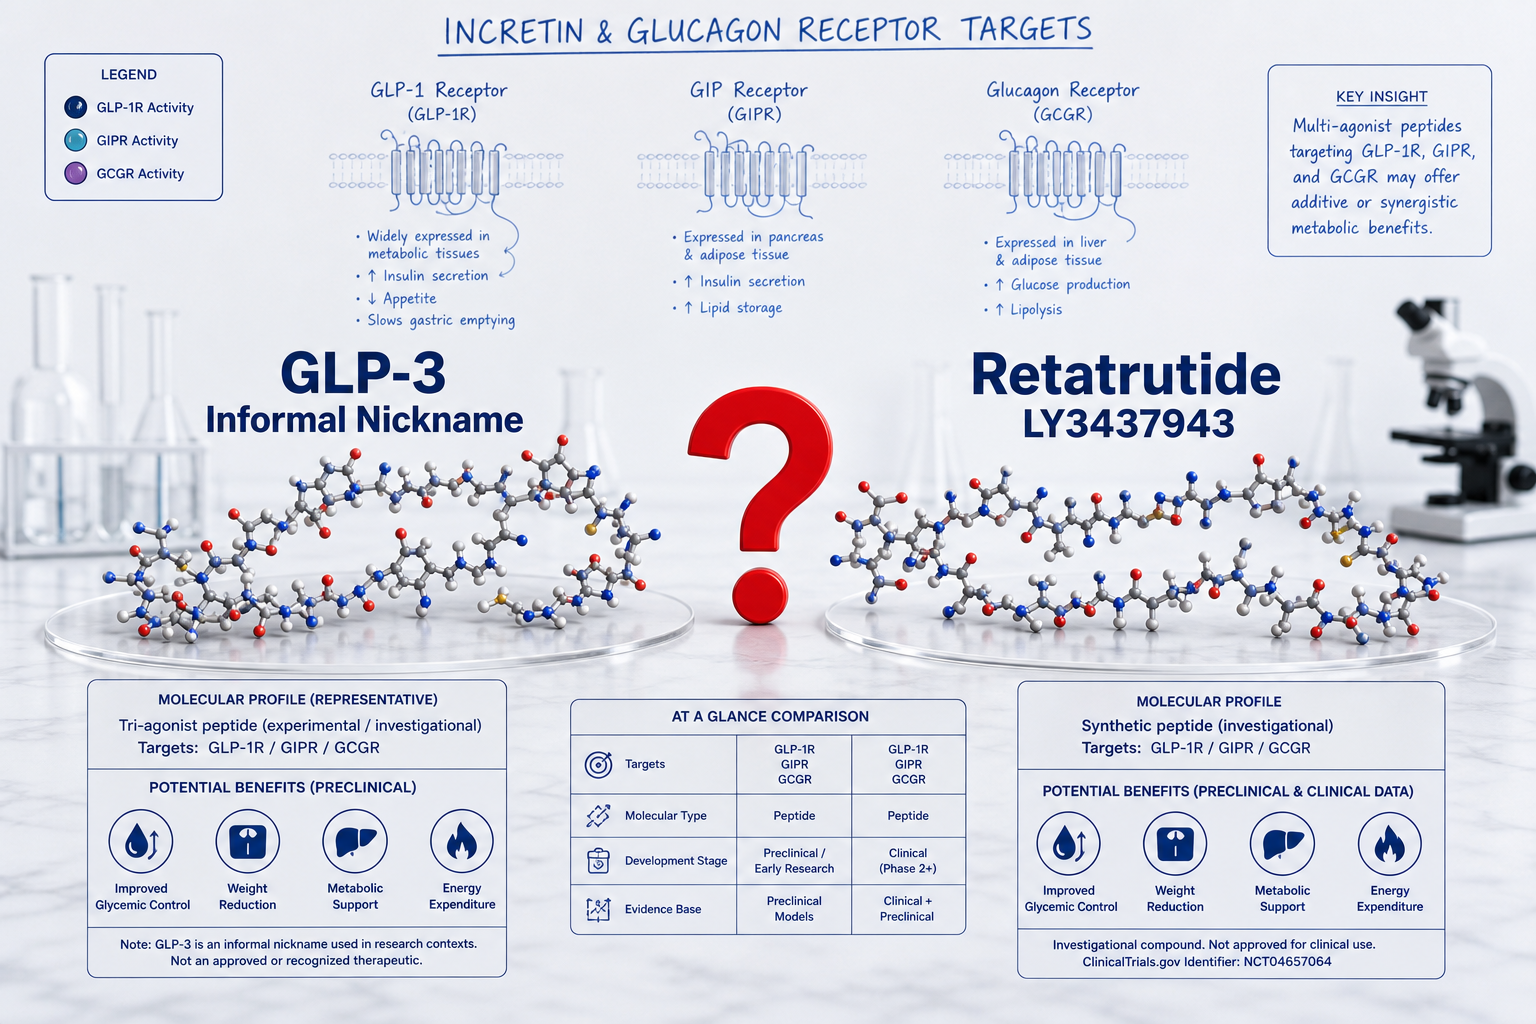
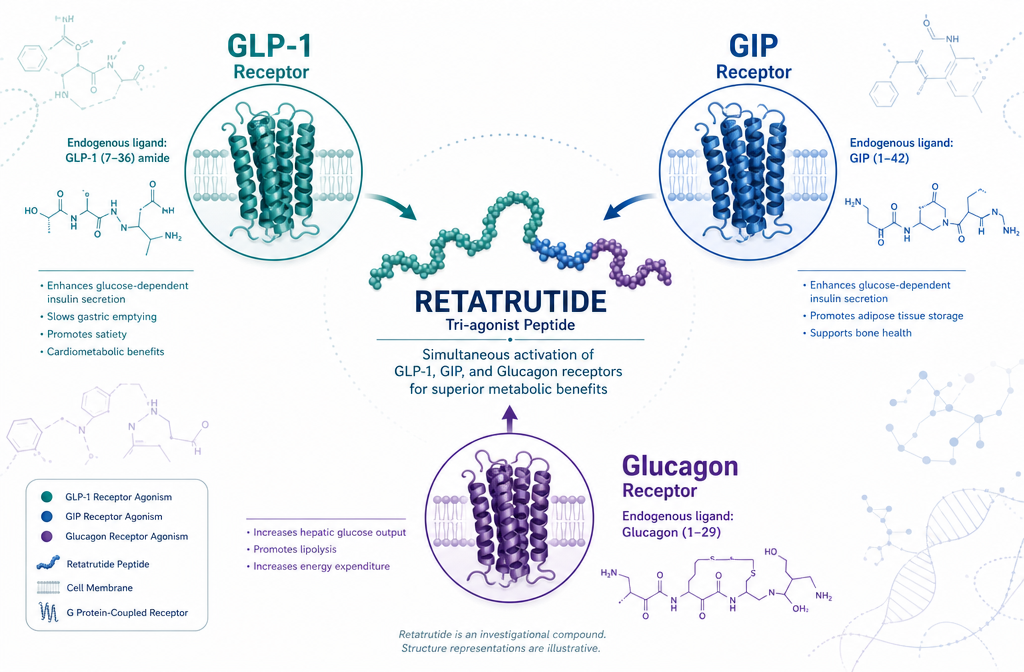
() scientific infographic-style illustration showing two labeled molecular structures side by side — one labeled 'GLP-3

Key Takeaways

  • "GLP-3" is an informal, consumer-driven nickname — not a recognized scientific classification for retatrutide.
  • Retatrutide (LY3437943) is a triple-receptor agonist targeting GLP-1, GIP, and glucagon receptors simultaneously.
  • Phase 3 trials have shown weight loss results as high as 28.7%, the highest ever recorded in an obesity drug trial.
  • Terminology confusion can distort research interpretation, marketplace trust, and regulatory understanding.
  • Researchers and buyers should verify compound identity by chemical name or CAS number, not informal labels.

What Is Retatrutide and Where Does "GLP-3" Come From

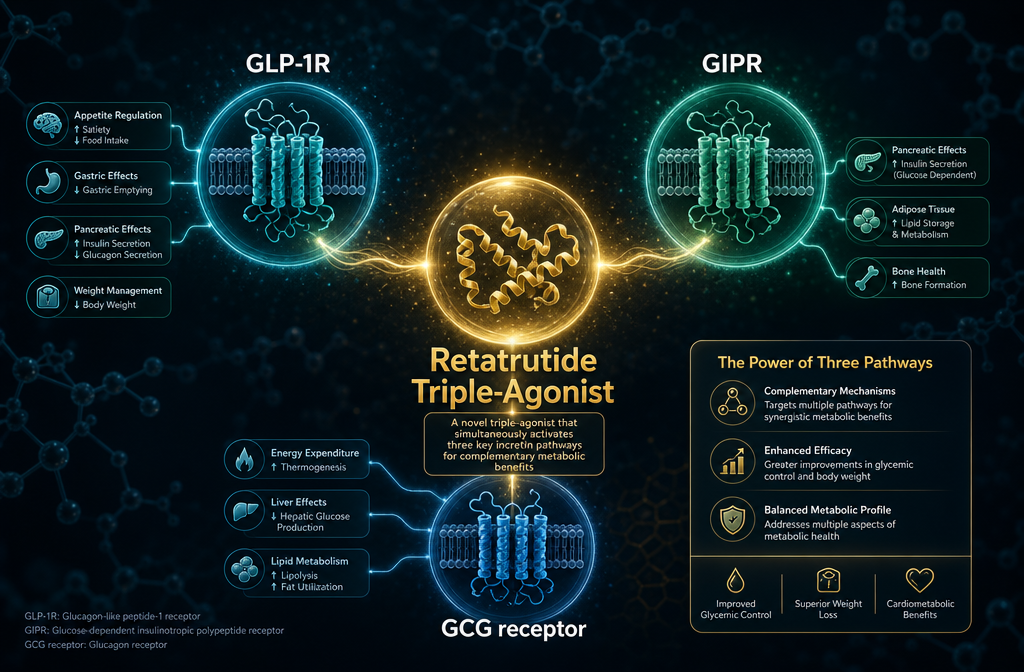
Retatrutide, developed by Eli Lilly under the code name LY3437943, is a first-in-class triple-receptor agonist. It activates three distinct hormone receptors at once:

Receptor Role in Metabolism
GLP-1 Appetite suppression, insulin secretion
GIP Fat metabolism, insulin sensitivity
Glucagon Energy expenditure, liver fat reduction

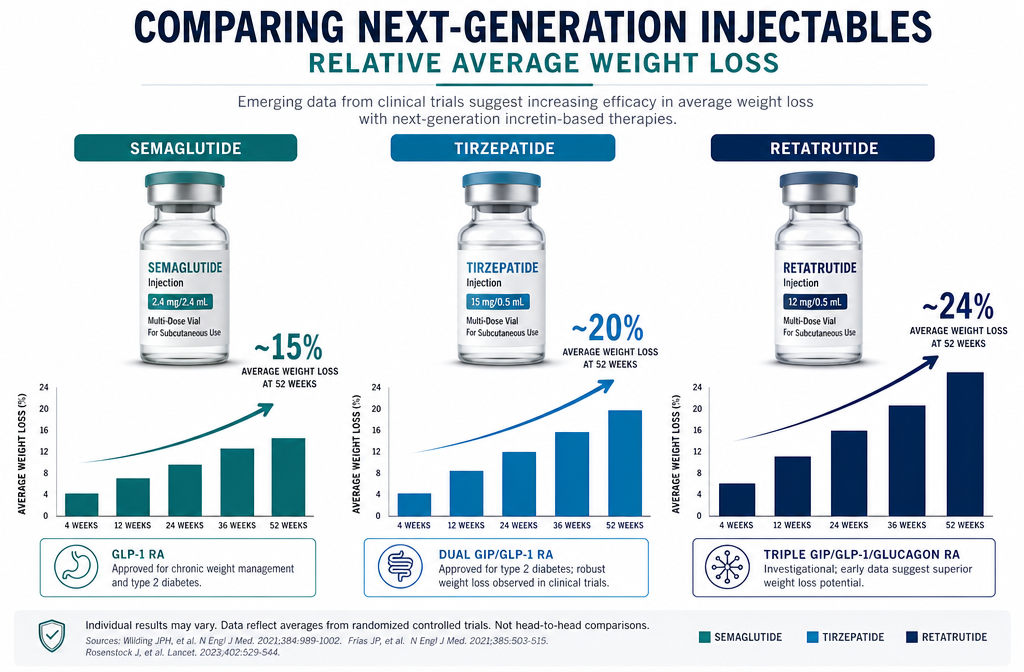
No approved drug before retatrutide has hit all three targets simultaneously. Semaglutide (Ozempic, Wegovy) targets only GLP-1. Tirzepatide (Mounjaro, Zepbound) targets GLP-1 and GIP. Retatrutide adds glucagon to the mix.

The nickname "GLP-3" emerged organically in consumer forums and social media. The logic was simple: GLP-1 targets one receptor, tirzepatide targets two, so this "third generation" drug must be GLP-3. The label stuck — but it is scientifically inaccurate.

"GLP-3" does not describe a receptor, a peptide family, or a drug class. It is marketing shorthand that has migrated into research discussions where precision is critical.

For a broader look at where peptide research is heading, the latest updates in peptide research provide useful context on how naming conventions evolve in this space.


Why the Naming Confusion Matters in Obesity Research and Clinical Trials

Why the Naming Confusion Matters in Obesity Research and Clinical Trials

The stakes of this terminology gap become clear when looking at the trial data. In the TRIUMPH-4 Phase 3 trial, retatrutide produced a mean weight loss of 28.7% at 68 weeks in adults with obesity and knee osteoarthritis — the highest figure ever recorded in any Phase 3 obesity drug trial. The TRIUMPH-3 trial, presented at the American College of Cardiology Annual Scientific Session in March 2026, reported 24.2% mean weight loss at 72 weeks in adults with elevated cardiovascular risk.

These are landmark numbers. But when a researcher searches for "GLP-3 trial results" and finds a mix of retatrutide data alongside unrelated GLP receptor biology, the confusion compounds.

Three specific risks created by the GLP-3 label:

  • Research misattribution: Studies on actual GLP receptor peptide biology get conflated with retatrutide clinical outcomes.
  • Regulatory misunderstanding: Eli Lilly plans to file a New Drug Application in late 2026 or early 2027. Informal naming can create confusion in public commentary on regulatory submissions.
  • Marketplace errors: Buyers searching for research-grade retatrutide may encounter mislabeled products. Reviewing a detailed GLP-3 and retatrutide compound overview helps clarify what is actually being sourced.

For those researching metabolic peptides more broadly, resources on AOD9604 metabolic research and tesa benefits show how naming precision matters across the entire category.


How Researchers and Buyers Can Navigate the GLP3 Peptide vs Retatrutide Naming Issue

How Researchers and Buyers Can Navigate the GLP3 Peptide vs Retatrutide Naming Issue

The clearest solution is to anchor every discussion to the compound's chemical identity, not its nickname.

Best practices for accurate identification:

  • Always reference retatrutide by its INN (International Nonproprietary Name) or Eli Lilly's code: LY3437943.
  • Cross-check any "GLP-3" product listing against verified chemical specifications.
  • Use peer-reviewed databases rather than consumer forums as primary sources.
  • When sourcing for research, prioritize suppliers with transparent quality testing protocols and third-party verification.

The GLP-3 retatrutide product page and the RETA GLP-3 research overview are examples of how suppliers can bridge the naming gap by providing both the informal label and the verified compound name together.

For researchers exploring related metabolic compounds, the 5-Amino-1MQ research overview offers a useful parallel on how novel compounds gain informal names before formal classification catches up.


Conclusion

The GLP3 Peptide vs Retatrutide naming confusion is not a trivial issue. It shapes how clinical trial data is interpreted, how regulatory conversations unfold, and how research-grade compounds are sourced. Retatrutide is a precisely defined triple-receptor agonist with Phase 3 data that sets a new benchmark for obesity pharmacology. "GLP-3" is a convenient shorthand that, when used carelessly, undermines that precision.

Actionable next steps:

  • Replace "GLP-3" with "retatrutide" or "LY3437943" in all research documentation.
  • Verify any compound labeled "GLP-3" against its full chemical specification before use.
  • Stay current with TRIUMPH trial publications and the anticipated NDA filing timeline.
  • Source research peptides only from suppliers who publish verified testing data alongside both the common and scientific names.

Precision in language is the foundation of precision in science. In obesity research, where the stakes are high and the compounds are complex, that foundation matters more than ever.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/GLP3-Peptide-vs-Retatrutide-Why-the-Naming-Confusion-Matters-in-Obesity-Research.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-11 13:06:552026-07-20 15:03:30GLP3 Peptide vs Retatrutide: Why the Naming Confusion Matters in Obesity Research
What Is the GLP3 Peptide? Research Distinctions, Naming Confusion, and How It Relates to Retatrutide

What Is the GLP3 Peptide? Research Distinctions, Naming Confusion, and How It Relates to Retatrutide

June 10, 2026/0 Comments/by Pure Tested

A single informal label is causing genuine confusion across research communities, patient forums, and peptide catalogs in 2026: "GLP-3." Researchers searching for this term are often looking for something very different from what the name implies. Understanding what the GLP-3 peptide actually refers to — and why that label is scientifically inaccurate — matters for anyone tracking the latest developments in metabolic research.

Key Takeaways

  • There is no hormone called "GLP-3." The term is an informal nickname, not a recognized scientific designation.
  • "GLP-3" almost always refers to retatrutide (LY3437943), a triple-agonist investigational compound developed by Eli Lilly.
  • Retatrutide simultaneously targets three receptors: GLP-1, GIP, and glucagon.
  • Phase 3 trial data shows approximately 28% average weight loss over 18 months — results comparable to bariatric surgery.
  • As of 2026, retatrutide is not FDA-approved and remains under active clinical investigation.

Key Takeaways

Understanding the Naming Confusion Around "GLP-3"

The phrase "GLP-3 peptide" does not correspond to any recognized hormone in human physiology. The glucagon-like peptide family includes GLP-1 and GLP-2, both derived from the proglucagon gene. GLP-1 is well-established for its role in insulin secretion and appetite regulation. GLP-2 supports intestinal growth. No GLP-3 exists in the official scientific literature.

So where does the term come from? It appears to have emerged organically from online communities and informal research discussions as shorthand for retatrutide — a compound that acts on three separate receptor pathways. The logic is loose: "triple action" became "GLP-3" in casual usage. The label stuck, even though it misrepresents the compound's actual mechanism.

This kind of naming drift is not unusual in peptide research. For a broader look at how terminology evolves in this field, the ultimate guide to peptide therapy provides useful context on how compounds are classified and discussed.


What Is the GLP3 Peptide? Research Distinctions, Naming Confusion, and How It Relates to Retatrutide — The Core Answer

Retatrutide (development code LY3437943) is the compound most commonly referenced when someone asks about the "GLP-3 peptide." It is an investigational drug developed by Eli Lilly that activates three distinct hormone receptors simultaneously:

Receptor Primary Research Function
GLP-1 Reduces appetite, slows gastric emptying
GIP Improves insulin sensitivity, supports fat distribution
Glucagon Increases energy expenditure, promotes fat breakdown via thermogenesis

This triple-agonist profile is what separates retatrutide from earlier-generation compounds. Semaglutide targets GLP-1 alone. Tirzepatide targets GLP-1 and GIP. Retatrutide adds glucagon receptor activation on top of both, creating a broader metabolic effect.

For researchers already familiar with the GLP-1 peptide research landscape, retatrutide represents a meaningful step forward in receptor-targeting strategy. Those planning research with this compound should also review GLP-3 triple agonist research planning resources before sourcing.


What Is the GLP3 Peptide? Research Distinctions, Naming Confusion, and How It Relates to Retatrutide — The Core Answer

Phase 3 Data and Regulatory Status in 2026

The clinical results for retatrutide are among the most discussed in metabolic medicine this year. In Phase 3 trials, participants achieved an average weight loss of approximately 28% over 18 months — a figure that rivals outcomes typically seen with bariatric surgery. No other injectable medication has produced comparable numbers in trial data to date.

"Retatrutide's Phase 3 results represent the highest weight loss figures recorded for any injectable medication in clinical trials."

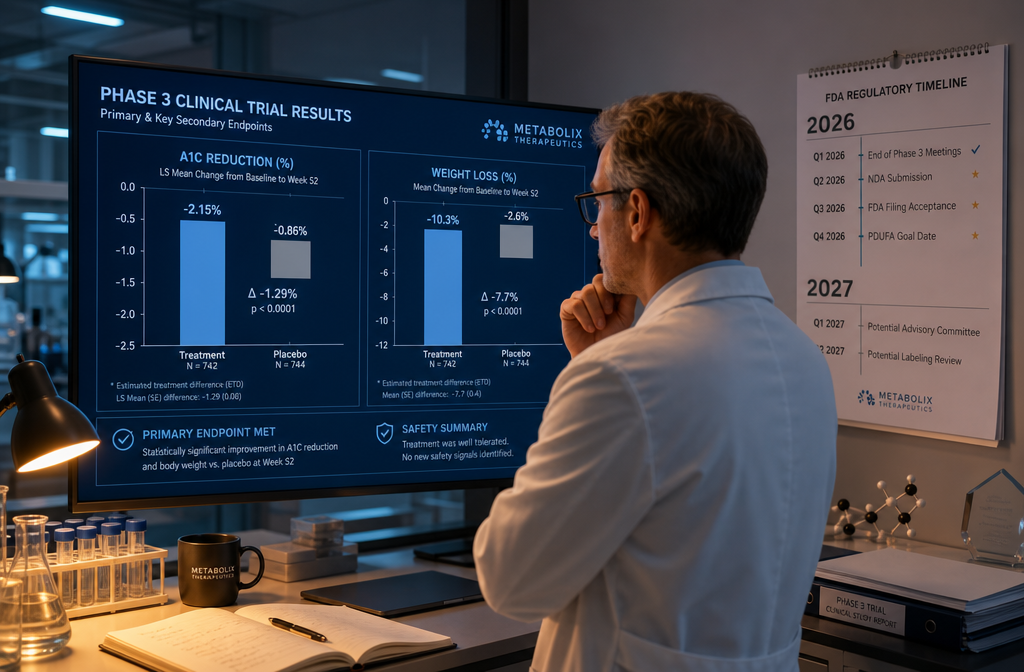
Despite these results, retatrutide is not FDA-approved as of 2026. Eli Lilly anticipates filing for FDA approval in 2026–2027, with potential commercial availability projected for late 2027 or 2028, contingent on successful trial completion and regulatory review.

Beyond weight loss, researchers are examining retatrutide's potential influence on type 2 diabetes, cardiovascular risk factors, and metabolic liver disease. The GIP receptor and its importance in metabolic signaling provides additional background on one of the three pathways retatrutide engages.


What Is the GLP3 Peptide? Research Distinctions, Naming Confusion, and How It Relates to Retatrutide — Practical Implications for Researchers

For researchers navigating this space, the terminology distinction has real consequences. Searching for "GLP-3 peptide" may return inconsistent results across databases, catalogs, and literature because the label is not standardized. Using the correct terminology — triple agonist, GLP-1/GIP/glucagon receptor agonist, or retatrutide/LY3437943 — will yield more reliable and reproducible search results.

Retatrutide is administered as a once-weekly subcutaneous injection, a delivery format consistent with other compounds in the GLP-1 class. Researchers interested in innovative peptide delivery systems will find the subcutaneous format familiar, though the triple-receptor profile introduces unique considerations for study design.

Those tracking the broader metabolic peptide landscape may also find value in reviewing AOD-9604 metabolic research and SLU-PP-332 metabolic research themes for comparative context on fat metabolism pathways.


What Is the GLP3 Peptide? Research Distinctions, Naming Confusion, and How It Relates to Retatrutide — Practical Implications

Conclusion

The "GLP-3 peptide" is not a real hormone — it is a widely circulated misnomer for retatrutide, a triple-agonist compound targeting GLP-1, GIP, and glucagon receptors. Clarifying this distinction is essential for accurate research planning, catalog navigation, and literature review.

Actionable next steps for researchers:

  • Use "retatrutide," "LY3437943," or "triple agonist" in database and catalog searches instead of "GLP-3."
  • Review the GIP receptor pathway alongside GLP-1 mechanisms before designing studies.
  • Monitor FDA filing updates from Eli Lilly, expected in the 2026–2027 window.
  • Consult what is new in peptide research for ongoing developments in this fast-moving field.

Precise terminology is not a minor detail in peptide research — it directly affects sourcing accuracy, study reproducibility, and regulatory compliance awareness.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/What-Is-the-GLP3-Peptide-Research-Distinctions-Naming-Confusion-and-How-It-Relates-to-Retatrutide.png 672 1024 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-10 13:06:532026-07-20 15:03:32What Is the GLP3 Peptide? Research Distinctions, Naming Confusion, and How It Relates to Retatrutide
What Is GLP-3 Retatrutide? Triple-Agonist Biology, Receptor Targets, and Why It Is Different From GLP-1

What Is GLP-3 Retatrutide? Triple-Agonist Biology, Receptor Targets, and Why It Is Different From GLP-1

June 9, 2026/0 Comments/by Pure Tested

Forty-five percent of participants in a Phase 3 clinical trial lost at least 30% of their body weight — a result once reserved for bariatric surgery. That single data point from the TRIUMPH-1 trial has made retatrutide one of the most closely watched compounds in metabolic medicine today. Understanding what is GLP-3 retatrutide, its triple-agonist biology, receptor targets, and why it is different from GLP-1 drugs already on the market is the essential first step for any researcher or clinician tracking this space.

Key Takeaways

  • Retatrutide simultaneously activates three hormone receptors: GLP-1R, GIPR, and the glucagon receptor (GCG-R).
  • The informal label "GLP-3" is not a scientific hormone classification — it is shorthand for the compound's triple-receptor profile.
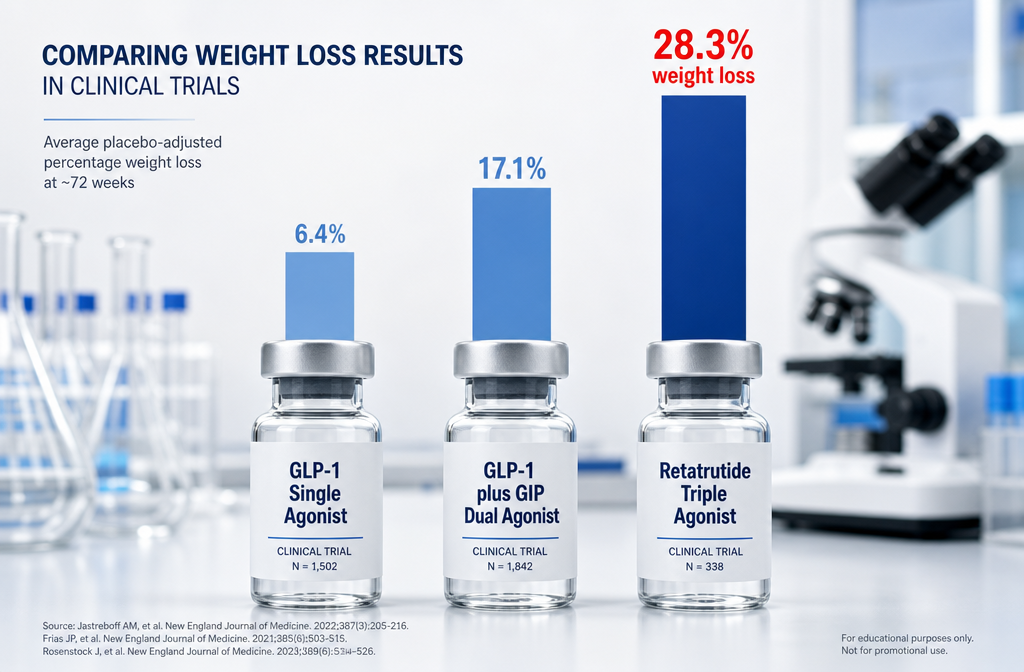
  • In the TRIUMPH-1 Phase 3 trial, participants on 12 mg weekly lost an average of 28.3% of body weight over 80 weeks.
  • Retatrutide outperforms single-agonist (semaglutide) and dual-agonist (tirzepatide) therapies in early head-to-head comparisons.
  • As of 2026, retatrutide has not received FDA approval and remains in Phase 3 development under Eli Lilly.

Key Takeaways

The Triple-Agonist Biology Behind Retatrutide

Retatrutide is a synthetic peptide engineered to bind and activate three distinct incretin and metabolic hormone receptors at the same time. Each receptor plays a separate but complementary role in energy regulation.

Receptor Primary Role Contribution to Retatrutide's Effect
GLP-1R (Glucagon-Like Peptide-1) Insulin secretion, appetite suppression Reduces hunger, slows gastric emptying
GIPR (Glucose-Dependent Insulinotropic Polypeptide) Insulin amplification, fat metabolism Enhances insulin response, supports fat tissue signaling
GCG-R (Glucagon Receptor) Energy expenditure, hepatic glucose output Increases calorie burn, reduces liver fat

This simultaneous three-receptor engagement is what separates retatrutide from every approved obesity drug on the market. The glucagon receptor component is particularly significant: glucagon typically raises blood sugar, but when its receptor is activated alongside GLP-1R and GIPR, the net effect shifts toward increased thermogenesis and fat oxidation rather than hyperglycemia.

Researchers exploring the GLP-1 generations overview will recognize this as a logical progression from first-generation single-agonist molecules toward increasingly complex multi-receptor strategies.

Why the "GLP-3" Label Is Informal — and What It Actually Means

The term "GLP-3" does not refer to a real hormone. No such molecule exists in human physiology. The label emerged informally to describe retatrutide's position as the third generation of GLP-based obesity therapies:

  • Generation 1: GLP-1 single agonists (e.g., semaglutide / Wegovy)
  • Generation 2: GLP-1 + GIP dual agonists (e.g., tirzepatide / Zepbound)
  • Generation 3: GLP-1 + GIP + Glucagon triple agonists (retatrutide)

The correct scientific description is triple hormone receptor agonist. Researchers browsing retatrutide research and catalog resources or the GLP-1 Reta product tag will encounter both terms, but the informal "GLP-3" label should always be understood as generational shorthand rather than pharmacological classification.

Why the "GLP-3" Label Is Informal — and What It Actually Means

How Retatrutide Differs From GLP-1 Drugs: Receptor Targets and Clinical Outcomes

This is the core question for anyone asking what is GLP-3 retatrutide and why it is different from GLP-1. The differences operate on two levels: mechanistic and clinical.

Mechanistically, semaglutide targets only GLP-1R. Tirzepatide adds GIPR. Retatrutide adds the glucagon receptor on top of both. That third receptor drives a meaningful increase in resting energy expenditure — the body burns more calories even at rest — which neither of the earlier drugs can replicate.

Clinically, the TRIUMPH-1 Phase 3 trial reported an average weight loss of 28.3% (approximately 70.3 pounds) over 80 weeks at the 12 mg weekly dose. By comparison, semaglutide typically produces roughly 15% weight loss, and tirzepatide reaches approximately 20-22%. Retatrutide also demonstrated an A1C reduction of up to 2.0% over 40 weeks in participants with type 2 diabetes, suggesting strong glycemic benefit beyond weight loss alone.

"Retatrutide's glucagon receptor component is the differentiating factor — it converts what would otherwise be a pure appetite-suppression strategy into a genuine energy-expenditure intervention."

Side effects remain consistent with the incretin drug class: nausea, diarrhea, constipation, and vomiting, all dose-dependent and generally manageable. Those interested in how metabolic peptides interact with energy systems may also find value in reviewing mitochondrial longevity research and AOD9604 metabolic research for broader context.

For researchers sourcing compounds for study, reviewing lab-tested peptide standards and certificate of analysis documentation ensures quality benchmarks are met before any research protocol begins.

As of 2026, retatrutide is not FDA-approved. Eli Lilly anticipates filing for approval in 2026-2027, with potential market availability by 2027 or 2028. Those planning research timelines can consult the GLP-3 research planning and catalog navigation guide for sourcing and protocol considerations.

How Retatrutide Differs From GLP-1 Drugs: Receptor Targets and Clinical Outcomes

Conclusion

Retatrutide represents a genuine structural advance over existing GLP-1 therapies. Its triple-agonist biology — engaging GLP-1R, GIPR, and the glucagon receptor simultaneously — produces weight loss outcomes that approach bariatric surgery benchmarks and glycemic improvements that matter for type 2 diabetes management. The informal "GLP-3" label is a useful shorthand, but researchers should understand it as a generational marker, not a hormone designation.

Actionable next steps for researchers in 2026:

  • Review the TRIUMPH-1 Phase 3 trial data in detail to understand dose-response relationships.
  • Compare retatrutide's receptor profile against tirzepatide using the GLP-1 peptide generational research overview.
  • Verify compound purity standards before initiating any research protocol by consulting available COA documentation.
  • Monitor FDA filing timelines, currently projected for 2026-2027, to align research planning accordingly.
https://www.puretestedpeptides.com/wp-content/uploads/2026/06/What-Is-GLP-3-Retatrutide-Triple-Agonist-Biology-Receptor-Targets-and-Why-It-Is-Different-From-GLP-1.png 672 1024 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-09 13:05:142026-07-20 15:03:37What Is GLP-3 Retatrutide? Triple-Agonist Biology, Receptor Targets, and Why It Is Different From GLP-1
Retatrutide vs GLP-1 and GLP-2 Pathways: How Triple Agonism Changes the Research Conversation

Retatrutide vs GLP-1 and GLP-2 Pathways: How Triple Agonism Changes the Research Conversation

June 6, 2026/0 Comments/by Pure Tested

A single peptide producing nearly 29% body weight reduction in a Phase 3 trial is not an incremental advance — it is a structural shift in how researchers think about metabolic intervention. That result, recorded in the TRIUMPH-4 trial with retatrutide, has forced a direct comparison between the emerging triple agonist approach and the narrower incretin pathways that have defined obesity pharmacology for the past decade. The discussion around Retatrutide vs GLP-1 and GLP-2 Pathways: How Triple Agonism Changes the Research Conversation is no longer speculative; it is grounded in late-stage clinical data that demands a closer look at mechanism.

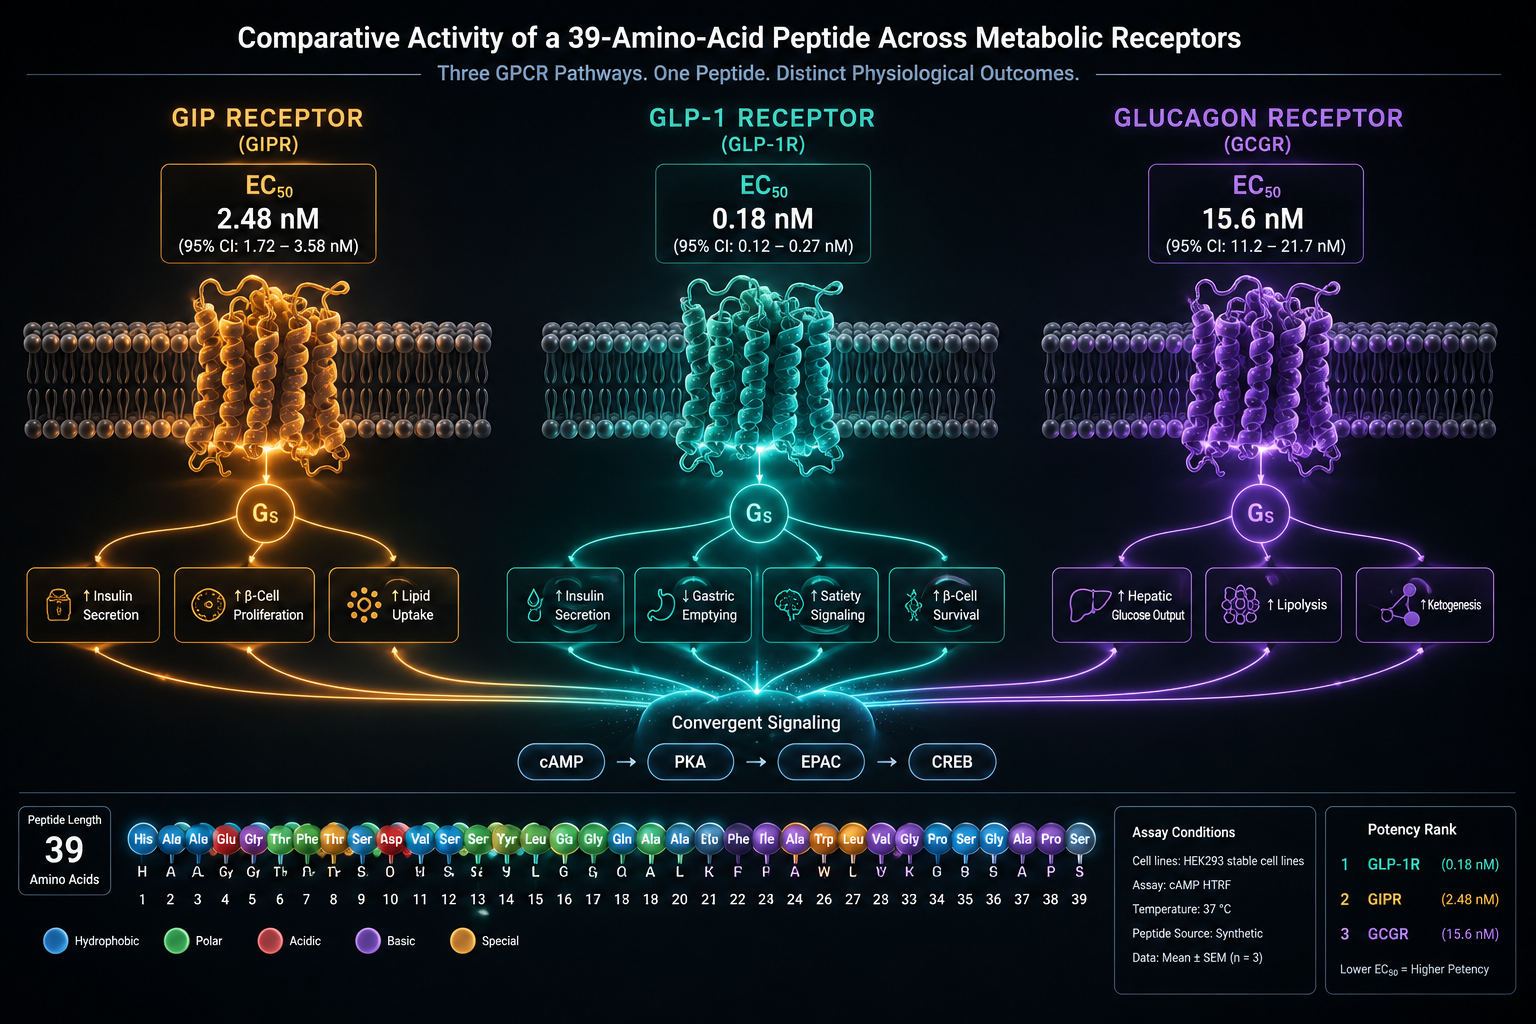
() scientific infographic showing a side-by-side molecular comparison of three peptide receptor pathways: GIP receptor node

Key Takeaways

  • Retatrutide activates three receptors — GIP, GLP-1, and glucagon — making it mechanistically distinct from both semaglutide (single agonist) and tirzepatide (dual agonist).
  • Its receptor potency is GIP-primary, with EC50 values of 0.0643 nM at GIP, 0.775 nM at GLP-1, and 5.79 nM at glucagon.
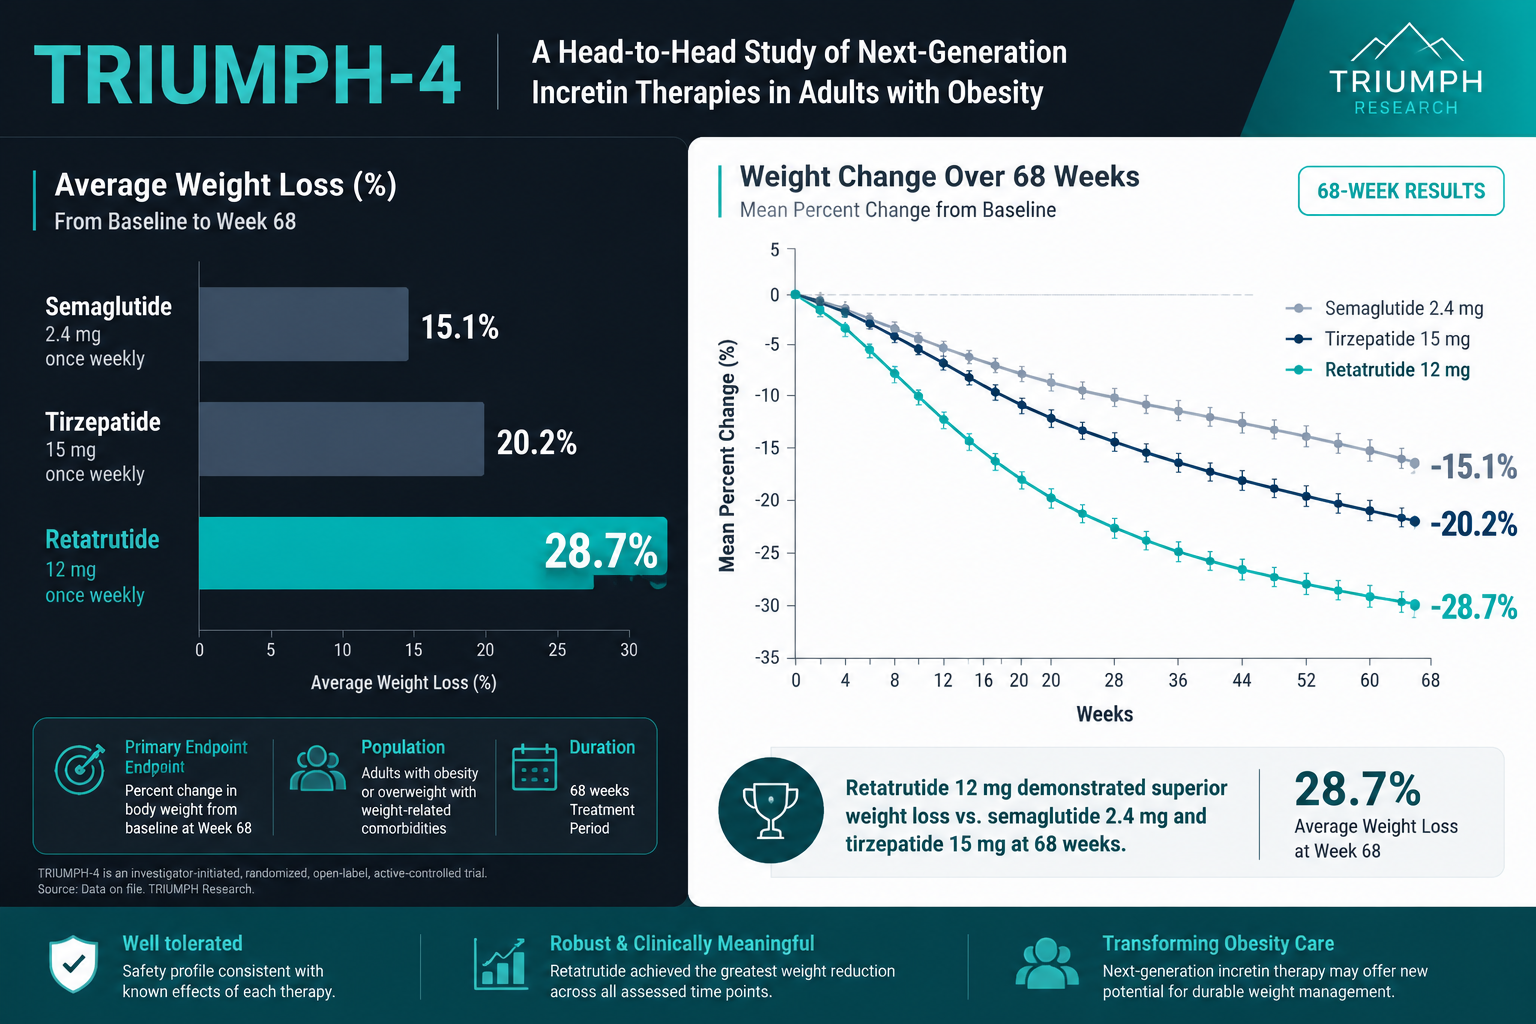
  • TRIUMPH-4 Phase 3 data showed an average weight loss of 28.7% over 68 weeks, roughly 71 pounds from a baseline of 249 pounds.
  • Glucagon receptor activity is considered a key driver of enhanced energy expenditure, separating retatrutide from pure incretin strategies.
  • As of 2026, retatrutide is not FDA-approved, with Eli Lilly targeting a regulatory submission by late 2026.

What Separates Triple Agonism from Incretin-Only Approaches

The GLP-1 receptor pathway has been the dominant target in metabolic research since the early success of semaglutide. GLP-1 agonism reduces appetite, slows gastric emptying, and improves insulin secretion. Adding GIP receptor activation — as tirzepatide does — brought a meaningful improvement in both glucose control and weight outcomes. However, both approaches remain within the incretin framework.

Retatrutide steps outside that framework. As a 39-amino acid peptide, it simultaneously activates the GIP, GLP-1, and glucagon receptors. The glucagon component is what most fundamentally changes the research conversation. Glucagon receptor activation increases energy expenditure and promotes fat breakdown in the liver, effects that incretin-only molecules cannot replicate. Researchers exploring GLP-3 and incretin research themes have noted that this third receptor engagement may explain why retatrutide's weight loss outcomes exceed what dual agonists have produced.

"The inclusion of glucagon receptor activity may represent the ceiling-raising mechanism that separates retatrutide from every prior pharmacological approach to obesity."

The potency hierarchy matters here. Retatrutide's EC50 values place GIP activation as the primary driver (0.0643 nM), followed by GLP-1 (0.775 nM), then glucagon (5.79 nM). This graduated profile is intentional — high glucagon activity without GLP-1 co-activation would raise blood sugar, so the balance is a deliberate design feature, not a side effect.

For researchers comparing generational differences in GLP-1 receptor approaches, this receptor hierarchy represents a fundamentally new design philosophy rather than a refinement of existing ones.


Retatrutide vs GLP-1 and GLP-2 Pathways: What the Phase 3 Data Reveals

Retatrutide vs GLP-1 and GLP-2 Pathways: What the Phase 3 Data Reveals

The TRIUMPH-4 trial enrolled participants with obesity and knee osteoarthritis. Over 68 weeks, the average participant lost 28.7% of body weight — approximately 71 pounds from a starting weight of 249 pounds. No approved pharmacological therapy has produced comparable results in a controlled Phase 3 setting.

Comparison of key obesity drug mechanisms:

Drug Receptors Targeted Avg. Weight Loss (Phase 3)
Semaglutide GLP-1 ~15%
Tirzepatide GIP + GLP-1 ~20-22%
Retatrutide GIP + GLP-1 + Glucagon ~28.7%

The TRIUMPH program spans multiple indications, including type 2 diabetes and metabolic liver disease, reflecting the breadth of conditions that researchers believe triple agonism may address. Eli Lilly is targeting an FDA submission by late 2026, though as of 2026 the compound remains investigational.

Side effects reported in trials include nausea, vomiting, constipation, and diarrhea — a profile consistent with other GLP-class peptides. Researchers sourcing compounds for preclinical models can review the retatrutide research compound page for current availability context.

Those tracking the broader landscape of what is new in peptide research will recognize that retatrutide's data has elevated expectations across the entire metabolic peptide category.


How Triple Agonism Reshapes Metabolic Research Models

The Retatrutide vs GLP-1 and GLP-2 Pathways conversation extends beyond weight loss percentages. It raises questions about how researchers should model metabolic intervention going forward. Single-pathway models are increasingly insufficient for studying complex conditions like obesity-related liver disease or insulin resistance, where energy expenditure, appetite, and hepatic fat metabolism must be addressed simultaneously.

How Triple Agonism Reshapes Metabolic Research Models

Researchers working with metabolic modulation research lines are already integrating multi-receptor thinking into their experimental designs. The question is no longer whether multi-agonism outperforms single-agonism — the data answers that — but which receptor combinations produce the most favorable benefit-to-risk profiles for specific conditions.

Complementary research areas are also gaining attention. Compounds like MOTS-c, studied for metabolic flexibility, and SLU-PP-332, explored for metabolic modulation, represent parallel lines of inquiry that may eventually intersect with incretin-based approaches in combination research models.

The GLP-1 receptor remains central, but retatrutide's data suggests that anchoring research exclusively to that pathway may limit what is discoverable. For researchers sourcing GLP-1 class compounds, the GLP-1 peptide research and sourcing notes page provides useful context on how this category has evolved.


Conclusion

The evidence from retatrutide's Phase 3 program makes the case clearly: triple agonism is not a variation on existing GLP-1 therapy — it is a different category of metabolic intervention. The glucagon receptor component adds an energy expenditure dimension that incretin-only approaches cannot replicate, and the clinical outcomes reflect that mechanistic difference.

For researchers, the actionable steps are straightforward. First, review the TRIUMPH trial data to understand how the three-receptor model performs across different patient populations. Second, evaluate whether current research models account for glucagon receptor activity alongside incretin pathways. Third, monitor the regulatory timeline, as Eli Lilly's planned FDA submission by late 2026 will bring additional data into the public domain. The research conversation has shifted — and the mechanism is the reason why.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Retatrutide-vs-GLP-1-and-GLP-2-Pathways-How-Triple-Agonism-Changes-the-Research-Conversation.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-06 13:04:302026-07-20 15:03:51Retatrutide vs GLP-1 and GLP-2 Pathways: How Triple Agonism Changes the Research Conversation
How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models

How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models

June 4, 2026/0 Comments/by Pure Tested

Triple agonism has quietly shifted the center of gravity in metabolic peptide research. While single-receptor approaches dominated the conversation for years, a 39-amino acid compound called retatrutide now sits at the intersection of three distinct signaling pathways — and the weight-loss data from preclinical and clinical obesity models is unlike anything seen before in this class.

Understanding how retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models requires a clear look at receptor biology, efficacy endpoints, and the structural differences that separate these compounds at the molecular level.

Key Takeaways

  • Retatrutide is a triple agonist activating GLP-1, GIP, and glucagon receptors simultaneously, producing greater metabolic effects than single or dual agonists.
  • Phase 3 TRIUMPH-4 data showed 28.7% average weight loss at 68 weeks — the highest recorded in any obesity trial to date.
  • GLP-2 peptides act primarily on intestinal repair and growth, not on adipose tissue or appetite suppression, making them functionally distinct from GLP-1 class agents.
  • Retatrutide's glucagon receptor component raises resting metabolic rate and promotes lipolysis, a mechanism absent in GLP-1-only agents.
  • As of 2026, retatrutide remains in Phase 3 trials, with a New Drug Application filing anticipated in late 2026 or early 2027.

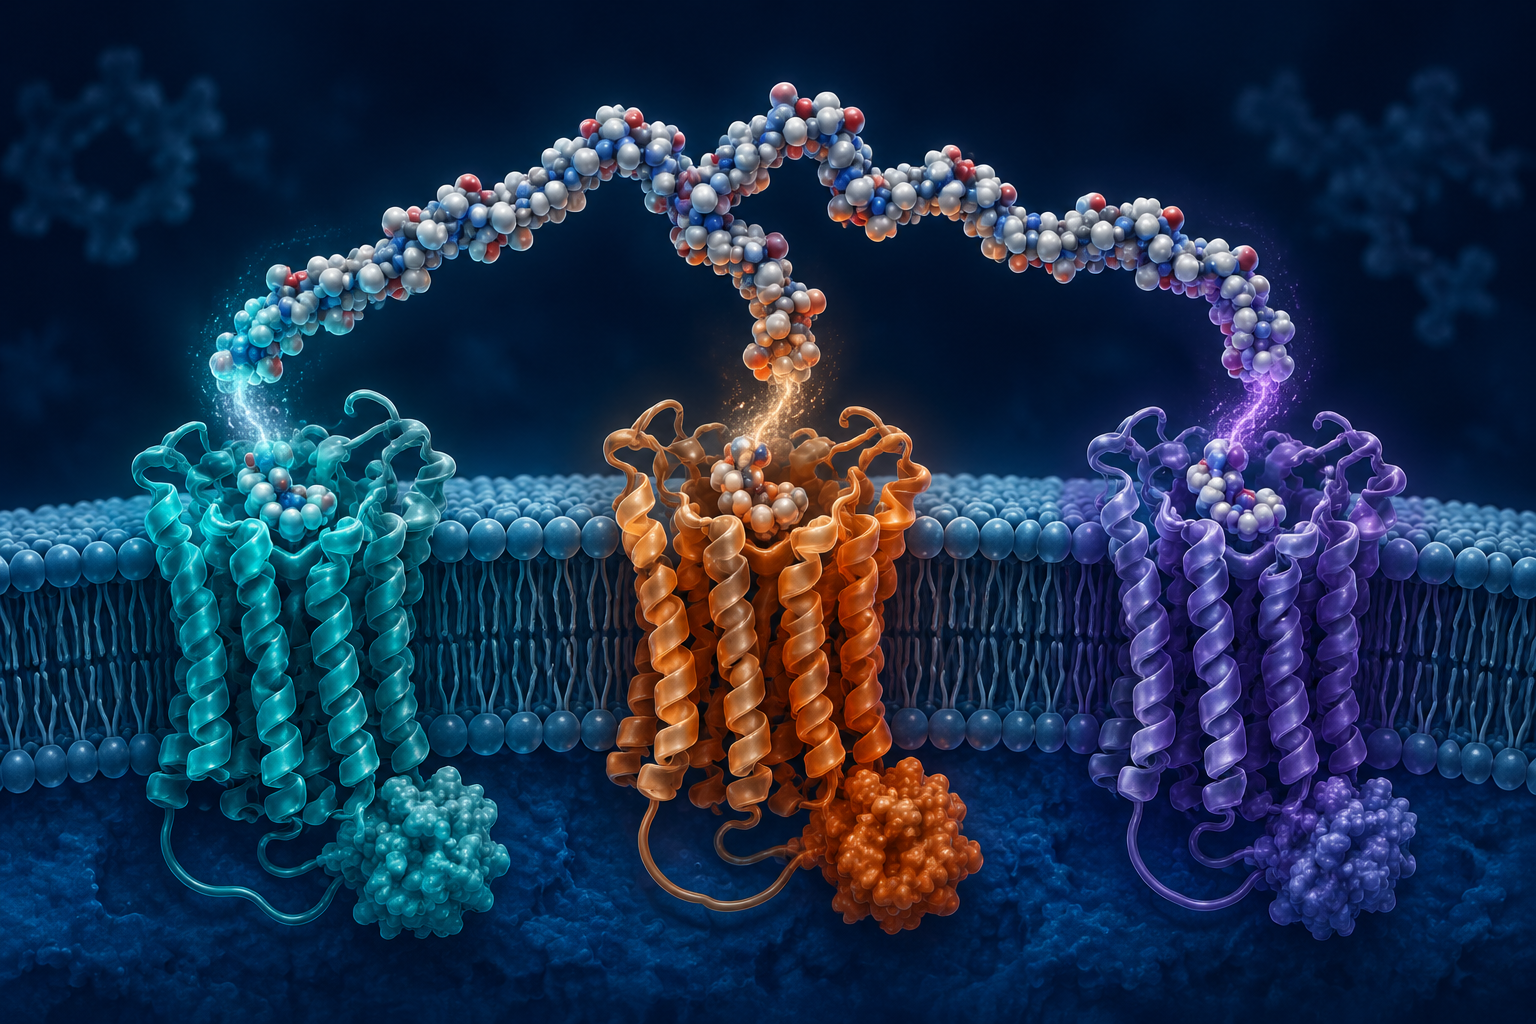
Retatrutide triple receptor agonist mechanism diagram

The Receptor Architecture Behind Triple Agonism

How retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models starts with a fundamental structural distinction. Retatrutide is built on a GIP backbone, modified to resist DPP-4 enzymatic degradation, and conjugated to a C20 fatty diacid moiety that extends its half-life. This architecture allows it to engage three receptors simultaneously:

Receptor Primary Effect
GLP-1R Insulin secretion, appetite suppression
GIPR Enhanced insulin response, fat metabolism
GCG-R Increased resting metabolic rate, lipolysis

GLP-1 agonists like semaglutide activate only the GLP-1 receptor. This reduces appetite and improves glycemic control but leaves energy expenditure largely unchanged. Dual agonists such as tirzepatide add GIP receptor activation, improving insulin sensitivity and fat metabolism. Retatrutide layers glucagon receptor agonism on top of both, actively raising the rate at which the body burns stored fat.

GLP-2 peptides occupy a completely different functional space. Their primary role is intestinal epithelial growth, mucosal repair, and nutrient absorption regulation. In obesity models, GLP-2 analogs show minimal direct impact on body weight or adipose tissue reduction. Researchers studying gut-barrier integrity or inflammatory bowel conditions find GLP-2 highly relevant, but it does not compete with GLP-1 class agents on weight-loss endpoints.

For those exploring the broader landscape of incretin-related research, the GLP-3 and retatrutide incretin research themes page provides useful context on how these receptor classes are being studied in parallel.


Weight loss comparison bar chart: Retatrutide vs GLP-1 agents

Efficacy Data Across Obesity Models: Where the Numbers Diverge

The clinical weight-loss data illustrates the gap between these approaches with precision.

  • Semaglutide (GLP-1 only): approximately 14.9% body weight reduction over 68 weeks
  • Tirzepatide (GLP-1 + GIP): approximately 22.5% over 72 weeks
  • Retatrutide 12 mg (GLP-1 + GIP + GCG): 28.7% over 68 weeks in the TRIUMPH-4 Phase 3 trial

"Retatrutide's triple-agonist approach may redefine obesity treatment by offering weight loss results approaching those of bariatric surgery."

In Phase 2 trials, participants at the 12 mg dose also showed a 2.2% reduction in HbA1c from a baseline of approximately 8.3%, with 82% reaching HbA1c levels at or below 6.5%. This dual impact on both body weight and glycemic control strengthens retatrutide's research profile considerably.

The glucagon receptor component deserves particular attention. By increasing resting metabolic rate and driving lipolysis, it creates an energy-expenditure advantage that neither GLP-1 nor GLP-2 agents can replicate. This is why researchers tracking AOD-9604 metabolic research and lipolytic peptide mechanisms are increasingly interested in how glucagon co-agonism fits into broader fat-loss models.

For context on how GLP-1 peptides are currently categorized and studied, that resource outlines the foundational receptor class from which retatrutide diverges.


Researcher reviewing peptide molecular data in laboratory

How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models: Safety and Research Outlook

The side-effect profile of retatrutide largely mirrors that of other GLP-1 class agents. Nausea, diarrhea, vomiting, and constipation are the most commonly reported issues. One notable distinction is dysesthesia — tingling or burning sensations — reported in approximately 20.9% of participants at the 12 mg dose in TRIUMPH-4. This is not commonly observed with GLP-1-only or GLP-2 agents and likely reflects glucagon receptor activity.

As of 2026, retatrutide remains in Phase 3 trials. An NDA filing is anticipated in late 2026 or early 2027. Researchers sourcing compounds for preclinical work can review the GLP-3 Retatrutide 10mg research product for current availability.

Those building a broader metabolic research framework may also find value in exploring what is new in peptide research to understand how retatrutide fits alongside other emerging compounds, or reviewing NAD research and GLP-3 online resources for complementary metabolic pathways under investigation.

For researchers studying peptide blends in research contexts, the triple-agonist design of retatrutide also raises questions about whether combination approaches in preclinical models could replicate or extend its receptor-engagement profile.


Conclusion

How retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models comes down to receptor breadth and metabolic reach. GLP-1 agents suppress appetite and improve insulin response. GLP-2 agents repair intestinal tissue. Retatrutide does something categorically different: it activates three complementary pathways at once, producing weight-loss outcomes that exceed all prior pharmacological benchmarks and approach the efficacy of surgical intervention.

Actionable next steps for researchers:

  • Review Phase 2 and TRIUMPH-4 Phase 3 trial data to understand dose-response relationships at the 4 mg, 8 mg, and 12 mg levels.
  • Distinguish GLP-2 research models (gut repair, nutrient absorption) from GLP-1/GCG co-agonism models before designing obesity endpoints.
  • Monitor NDA filing timelines in late 2026 and early 2027 for regulatory developments that may affect research access.
  • Evaluate glucagon receptor co-agonism as a distinct variable when comparing metabolic outcomes across peptide classes.

The research conversation around obesity pharmacology has changed. Triple agonism is no longer a theoretical advantage — the data has made it a measurable one.


https://www.puretestedpeptides.com/wp-content/uploads/2026/06/How-Retatrutide-Compares-With-GLP-1-and-GLP-2-Research-Peptides-in-Obesity-Models-1.png 672 1024 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-04 13:18:082026-07-20 15:03:56How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models
How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models

How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models

June 4, 2026/0 Comments/by Pure Tested

Triple agonism has quietly shifted the center of gravity in metabolic peptide research. While single-receptor approaches dominated the conversation for years, a 39-amino acid compound called retatrutide now sits at the intersection of three distinct signaling pathways — and the weight-loss data from preclinical and clinical obesity models is unlike anything seen before in this class.

Understanding how retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models requires a clear look at receptor biology, efficacy endpoints, and the structural differences that separate these compounds at the molecular level.

Key Takeaways

  • Retatrutide is a triple agonist activating GLP-1, GIP, and glucagon receptors simultaneously, producing greater metabolic effects than single or dual agonists.
  • Phase 3 TRIUMPH-4 data showed 28.7% average weight loss at 68 weeks — the highest recorded in any obesity trial to date.
  • GLP-2 peptides act primarily on intestinal repair and growth, not on adipose tissue or appetite suppression, making them functionally distinct from GLP-1 class agents.
  • Retatrutide's glucagon receptor component raises resting metabolic rate and promotes lipolysis, a mechanism absent in GLP-1-only agents.
  • As of 2026, retatrutide remains in Phase 3 trials, with a New Drug Application filing anticipated in late 2026 or early 2027.

Retatrutide triple receptor agonist mechanism diagram

The Receptor Architecture Behind Triple Agonism

How retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models starts with a fundamental structural distinction. Retatrutide is built on a GIP backbone, modified to resist DPP-4 enzymatic degradation, and conjugated to a C20 fatty diacid moiety that extends its half-life. This architecture allows it to engage three receptors simultaneously:

Receptor Primary Effect
GLP-1R Insulin secretion, appetite suppression
GIPR Enhanced insulin response, fat metabolism
GCG-R Increased resting metabolic rate, lipolysis

GLP-1 agonists like semaglutide activate only the GLP-1 receptor. This reduces appetite and improves glycemic control but leaves energy expenditure largely unchanged. Dual agonists such as tirzepatide add GIP receptor activation, improving insulin sensitivity and fat metabolism. Retatrutide layers glucagon receptor agonism on top of both, actively raising the rate at which the body burns stored fat.

GLP-2 peptides occupy a completely different functional space. Their primary role is intestinal epithelial growth, mucosal repair, and nutrient absorption regulation. In obesity models, GLP-2 analogs show minimal direct impact on body weight or adipose tissue reduction. Researchers studying gut-barrier integrity or inflammatory bowel conditions find GLP-2 highly relevant, but it does not compete with GLP-1 class agents on weight-loss endpoints.

For those exploring the broader landscape of incretin-related research, the GLP-3 and retatrutide incretin research themes page provides useful context on how these receptor classes are being studied in parallel.


Weight loss comparison bar chart: Retatrutide vs GLP-1 agents

Efficacy Data Across Obesity Models: Where the Numbers Diverge

The clinical weight-loss data illustrates the gap between these approaches with precision.

  • Semaglutide (GLP-1 only): approximately 14.9% body weight reduction over 68 weeks
  • Tirzepatide (GLP-1 + GIP): approximately 22.5% over 72 weeks
  • Retatrutide 12 mg (GLP-1 + GIP + GCG): 28.7% over 68 weeks in the TRIUMPH-4 Phase 3 trial

"Retatrutide's triple-agonist approach may redefine obesity treatment by offering weight loss results approaching those of bariatric surgery."

In Phase 2 trials, participants at the 12 mg dose also showed a 2.2% reduction in HbA1c from a baseline of approximately 8.3%, with 82% reaching HbA1c levels at or below 6.5%. This dual impact on both body weight and glycemic control strengthens retatrutide's research profile considerably.

The glucagon receptor component deserves particular attention. By increasing resting metabolic rate and driving lipolysis, it creates an energy-expenditure advantage that neither GLP-1 nor GLP-2 agents can replicate. This is why researchers tracking AOD-9604 metabolic research and lipolytic peptide mechanisms are increasingly interested in how glucagon co-agonism fits into broader fat-loss models.

For context on how GLP-1 peptides are currently categorized and studied, that resource outlines the foundational receptor class from which retatrutide diverges.


Researcher reviewing peptide molecular data in laboratory

How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models: Safety and Research Outlook

The side-effect profile of retatrutide largely mirrors that of other GLP-1 class agents. Nausea, diarrhea, vomiting, and constipation are the most commonly reported issues. One notable distinction is dysesthesia — tingling or burning sensations — reported in approximately 20.9% of participants at the 12 mg dose in TRIUMPH-4. This is not commonly observed with GLP-1-only or GLP-2 agents and likely reflects glucagon receptor activity.

As of 2026, retatrutide remains in Phase 3 trials. An NDA filing is anticipated in late 2026 or early 2027. Researchers sourcing compounds for preclinical work can review the GLP-3 Retatrutide 10mg research product for current availability.

Those building a broader metabolic research framework may also find value in exploring what is new in peptide research to understand how retatrutide fits alongside other emerging compounds, or reviewing NAD research and GLP-3 online resources for complementary metabolic pathways under investigation.

For researchers studying peptide blends in research contexts, the triple-agonist design of retatrutide also raises questions about whether combination approaches in preclinical models could replicate or extend its receptor-engagement profile.


Conclusion

How retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models comes down to receptor breadth and metabolic reach. GLP-1 agents suppress appetite and improve insulin response. GLP-2 agents repair intestinal tissue. Retatrutide does something categorically different: it activates three complementary pathways at once, producing weight-loss outcomes that exceed all prior pharmacological benchmarks and approach the efficacy of surgical intervention.

Actionable next steps for researchers:

  • Review Phase 2 and TRIUMPH-4 Phase 3 trial data to understand dose-response relationships at the 4 mg, 8 mg, and 12 mg levels.
  • Distinguish GLP-2 research models (gut repair, nutrient absorption) from GLP-1/GCG co-agonism models before designing obesity endpoints.
  • Monitor NDA filing timelines in late 2026 and early 2027 for regulatory developments that may affect research access.
  • Evaluate glucagon receptor co-agonism as a distinct variable when comparing metabolic outcomes across peptide classes.

The research conversation around obesity pharmacology has changed. Triple agonism is no longer a theoretical advantage — the data has made it a measurable one.


https://www.puretestedpeptides.com/wp-content/uploads/2026/06/How-Retatrutide-Compares-With-GLP-1-and-GLP-2-Research-Peptides-in-Obesity-Models.png 672 1024 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-04 13:18:082026-07-20 15:03:57How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models
How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models

How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models

June 4, 2026/0 Comments/by Pure Tested

Triple agonism has quietly shifted the center of gravity in metabolic peptide research. While single-receptor approaches dominated the conversation for years, a 39-amino acid compound called retatrutide now sits at the intersection of three distinct signaling pathways — and the weight-loss data from preclinical and clinical obesity models is unlike anything seen before in this class.

Understanding how retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models requires a clear look at receptor biology, efficacy endpoints, and the structural differences that separate these compounds at the molecular level.

Key Takeaways

  • Retatrutide is a triple agonist activating GLP-1, GIP, and glucagon receptors simultaneously, producing greater metabolic effects than single or dual agonists.
  • Phase 3 TRIUMPH-4 data showed 28.7% average weight loss at 68 weeks — the highest recorded in any obesity trial to date.
  • GLP-2 peptides act primarily on intestinal repair and growth, not on adipose tissue or appetite suppression, making them functionally distinct from GLP-1 class agents.
  • Retatrutide's glucagon receptor component raises resting metabolic rate and promotes lipolysis, a mechanism absent in GLP-1-only agents.
  • As of 2026, retatrutide remains in Phase 3 trials, with a New Drug Application filing anticipated in late 2026 or early 2027.

Retatrutide triple receptor agonist mechanism diagram

The Receptor Architecture Behind Triple Agonism

How retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models starts with a fundamental structural distinction. Retatrutide is built on a GIP backbone, modified to resist DPP-4 enzymatic degradation, and conjugated to a C20 fatty diacid moiety that extends its half-life. This architecture allows it to engage three receptors simultaneously:

Receptor Primary Effect
GLP-1R Insulin secretion, appetite suppression
GIPR Enhanced insulin response, fat metabolism
GCG-R Increased resting metabolic rate, lipolysis

GLP-1 agonists like semaglutide activate only the GLP-1 receptor. This reduces appetite and improves glycemic control but leaves energy expenditure largely unchanged. Dual agonists such as tirzepatide add GIP receptor activation, improving insulin sensitivity and fat metabolism. Retatrutide layers glucagon receptor agonism on top of both, actively raising the rate at which the body burns stored fat.

GLP-2 peptides occupy a completely different functional space. Their primary role is intestinal epithelial growth, mucosal repair, and nutrient absorption regulation. In obesity models, GLP-2 analogs show minimal direct impact on body weight or adipose tissue reduction. Researchers studying gut-barrier integrity or inflammatory bowel conditions find GLP-2 highly relevant, but it does not compete with GLP-1 class agents on weight-loss endpoints.

For those exploring the broader landscape of incretin-related research, the GLP-3 and retatrutide incretin research themes page provides useful context on how these receptor classes are being studied in parallel.


Weight loss comparison bar chart: Retatrutide vs GLP-1 agents

Efficacy Data Across Obesity Models: Where the Numbers Diverge

The clinical weight-loss data illustrates the gap between these approaches with precision.

  • Semaglutide (GLP-1 only): approximately 14.9% body weight reduction over 68 weeks
  • Tirzepatide (GLP-1 + GIP): approximately 22.5% over 72 weeks
  • Retatrutide 12 mg (GLP-1 + GIP + GCG): 28.7% over 68 weeks in the TRIUMPH-4 Phase 3 trial

"Retatrutide's triple-agonist approach may redefine obesity treatment by offering weight loss results approaching those of bariatric surgery."

In Phase 2 trials, participants at the 12 mg dose also showed a 2.2% reduction in HbA1c from a baseline of approximately 8.3%, with 82% reaching HbA1c levels at or below 6.5%. This dual impact on both body weight and glycemic control strengthens retatrutide's research profile considerably.

The glucagon receptor component deserves particular attention. By increasing resting metabolic rate and driving lipolysis, it creates an energy-expenditure advantage that neither GLP-1 nor GLP-2 agents can replicate. This is why researchers tracking AOD-9604 metabolic research and lipolytic peptide mechanisms are increasingly interested in how glucagon co-agonism fits into broader fat-loss models.

For context on how GLP-1 peptides are currently categorized and studied, that resource outlines the foundational receptor class from which retatrutide diverges.


Researcher reviewing peptide molecular data in laboratory

How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models: Safety and Research Outlook

The side-effect profile of retatrutide largely mirrors that of other GLP-1 class agents. Nausea, diarrhea, vomiting, and constipation are the most commonly reported issues. One notable distinction is dysesthesia — tingling or burning sensations — reported in approximately 20.9% of participants at the 12 mg dose in TRIUMPH-4. This is not commonly observed with GLP-1-only or GLP-2 agents and likely reflects glucagon receptor activity.

As of 2026, retatrutide remains in Phase 3 trials. An NDA filing is anticipated in late 2026 or early 2027. Researchers sourcing compounds for preclinical work can review the GLP-3 Retatrutide 10mg research product for current availability.

Those building a broader metabolic research framework may also find value in exploring what is new in peptide research to understand how retatrutide fits alongside other emerging compounds, or reviewing NAD research and GLP-3 online resources for complementary metabolic pathways under investigation.

For researchers studying peptide blends in research contexts, the triple-agonist design of retatrutide also raises questions about whether combination approaches in preclinical models could replicate or extend its receptor-engagement profile.


Conclusion

How retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models comes down to receptor breadth and metabolic reach. GLP-1 agents suppress appetite and improve insulin response. GLP-2 agents repair intestinal tissue. Retatrutide does something categorically different: it activates three complementary pathways at once, producing weight-loss outcomes that exceed all prior pharmacological benchmarks and approach the efficacy of surgical intervention.

Actionable next steps for researchers:

  • Review Phase 2 and TRIUMPH-4 Phase 3 trial data to understand dose-response relationships at the 4 mg, 8 mg, and 12 mg levels.
  • Distinguish GLP-2 research models (gut repair, nutrient absorption) from GLP-1/GCG co-agonism models before designing obesity endpoints.
  • Monitor NDA filing timelines in late 2026 and early 2027 for regulatory developments that may affect research access.
  • Evaluate glucagon receptor co-agonism as a distinct variable when comparing metabolic outcomes across peptide classes.

The research conversation around obesity pharmacology has changed. Triple agonism is no longer a theoretical advantage — the data has made it a measurable one.


https://www.puretestedpeptides.com/wp-content/uploads/2026/06/How-Retatrutide-Compares-With-GLP-1-and-GLP-2-Research-Peptides-in-Obesity-Models.png 672 1024 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-04 13:18:082026-07-20 15:04:06How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models
How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models

How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models

June 4, 2026/0 Comments/by Pure Tested

Triple agonism has quietly shifted the center of gravity in metabolic peptide research. While single-receptor approaches dominated the conversation for years, a 39-amino acid compound called retatrutide now sits at the intersection of three distinct signaling pathways — and the weight-loss data from preclinical and clinical obesity models is unlike anything seen before in this class.

Understanding how retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models requires a clear look at receptor biology, efficacy endpoints, and the structural differences that separate these compounds at the molecular level.

Key Takeaways

  • Retatrutide is a triple agonist activating GLP-1, GIP, and glucagon receptors simultaneously, producing greater metabolic effects than single or dual agonists.
  • Phase 3 TRIUMPH-4 data showed 28.7% average weight loss at 68 weeks — the highest recorded in any obesity trial to date.
  • GLP-2 peptides act primarily on intestinal repair and growth, not on adipose tissue or appetite suppression, making them functionally distinct from GLP-1 class agents.
  • Retatrutide's glucagon receptor component raises resting metabolic rate and promotes lipolysis, a mechanism absent in GLP-1-only agents.
  • As of 2026, retatrutide remains in Phase 3 trials, with a New Drug Application filing anticipated in late 2026 or early 2027.

Retatrutide triple receptor agonist mechanism diagram

The Receptor Architecture Behind Triple Agonism

How retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models starts with a fundamental structural distinction. Retatrutide is built on a GIP backbone, modified to resist DPP-4 enzymatic degradation, and conjugated to a C20 fatty diacid moiety that extends its half-life. This architecture allows it to engage three receptors simultaneously:

Receptor Primary Effect
GLP-1R Insulin secretion, appetite suppression
GIPR Enhanced insulin response, fat metabolism
GCG-R Increased resting metabolic rate, lipolysis

GLP-1 agonists like semaglutide activate only the GLP-1 receptor. This reduces appetite and improves glycemic control but leaves energy expenditure largely unchanged. Dual agonists such as tirzepatide add GIP receptor activation, improving insulin sensitivity and fat metabolism. Retatrutide layers glucagon receptor agonism on top of both, actively raising the rate at which the body burns stored fat.

GLP-2 peptides occupy a completely different functional space. Their primary role is intestinal epithelial growth, mucosal repair, and nutrient absorption regulation. In obesity models, GLP-2 analogs show minimal direct impact on body weight or adipose tissue reduction. Researchers studying gut-barrier integrity or inflammatory bowel conditions find GLP-2 highly relevant, but it does not compete with GLP-1 class agents on weight-loss endpoints.

For those exploring the broader landscape of incretin-related research, the GLP-3 and retatrutide incretin research themes page provides useful context on how these receptor classes are being studied in parallel.


Weight loss comparison bar chart: Retatrutide vs GLP-1 agents

Efficacy Data Across Obesity Models: Where the Numbers Diverge

The clinical weight-loss data illustrates the gap between these approaches with precision.

  • Semaglutide (GLP-1 only): approximately 14.9% body weight reduction over 68 weeks
  • Tirzepatide (GLP-1 + GIP): approximately 22.5% over 72 weeks
  • Retatrutide 12 mg (GLP-1 + GIP + GCG): 28.7% over 68 weeks in the TRIUMPH-4 Phase 3 trial

"Retatrutide's triple-agonist approach may redefine obesity treatment by offering weight loss results approaching those of bariatric surgery."

In Phase 2 trials, participants at the 12 mg dose also showed a 2.2% reduction in HbA1c from a baseline of approximately 8.3%, with 82% reaching HbA1c levels at or below 6.5%. This dual impact on both body weight and glycemic control strengthens retatrutide's research profile considerably.

The glucagon receptor component deserves particular attention. By increasing resting metabolic rate and driving lipolysis, it creates an energy-expenditure advantage that neither GLP-1 nor GLP-2 agents can replicate. This is why researchers tracking AOD-9604 metabolic research and lipolytic peptide mechanisms are increasingly interested in how glucagon co-agonism fits into broader fat-loss models.

For context on how GLP-1 peptides are currently categorized and studied, that resource outlines the foundational receptor class from which retatrutide diverges.


Researcher reviewing peptide molecular data in laboratory

How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models: Safety and Research Outlook

The side-effect profile of retatrutide largely mirrors that of other GLP-1 class agents. Nausea, diarrhea, vomiting, and constipation are the most commonly reported issues. One notable distinction is dysesthesia — tingling or burning sensations — reported in approximately 20.9% of participants at the 12 mg dose in TRIUMPH-4. This is not commonly observed with GLP-1-only or GLP-2 agents and likely reflects glucagon receptor activity.

As of 2026, retatrutide remains in Phase 3 trials. An NDA filing is anticipated in late 2026 or early 2027. Researchers sourcing compounds for preclinical work can review the GLP-3 Retatrutide 10mg research product for current availability.

Those building a broader metabolic research framework may also find value in exploring what is new in peptide research to understand how retatrutide fits alongside other emerging compounds, or reviewing NAD research and GLP-3 online resources for complementary metabolic pathways under investigation.

For researchers studying peptide blends in research contexts, the triple-agonist design of retatrutide also raises questions about whether combination approaches in preclinical models could replicate or extend its receptor-engagement profile.


Conclusion

How retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models comes down to receptor breadth and metabolic reach. GLP-1 agents suppress appetite and improve insulin response. GLP-2 agents repair intestinal tissue. Retatrutide does something categorically different: it activates three complementary pathways at once, producing weight-loss outcomes that exceed all prior pharmacological benchmarks and approach the efficacy of surgical intervention.

Actionable next steps for researchers:

  • Review Phase 2 and TRIUMPH-4 Phase 3 trial data to understand dose-response relationships at the 4 mg, 8 mg, and 12 mg levels.
  • Distinguish GLP-2 research models (gut repair, nutrient absorption) from GLP-1/GCG co-agonism models before designing obesity endpoints.
  • Monitor NDA filing timelines in late 2026 and early 2027 for regulatory developments that may affect research access.
  • Evaluate glucagon receptor co-agonism as a distinct variable when comparing metabolic outcomes across peptide classes.

The research conversation around obesity pharmacology has changed. Triple agonism is no longer a theoretical advantage — the data has made it a measurable one.


https://www.puretestedpeptides.com/wp-content/uploads/2026/06/How-Retatrutide-Compares-With-GLP-1-and-GLP-2-Research-Peptides-in-Obesity-Models.png 672 1024 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-04 13:18:082026-07-20 15:03:57How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models
How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models

How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models

June 4, 2026/0 Comments/by Pure Tested

Triple agonism has quietly shifted the center of gravity in metabolic peptide research. While single-receptor approaches dominated the conversation for years, a 39-amino acid compound called retatrutide now sits at the intersection of three distinct signaling pathways — and the weight-loss data from preclinical and clinical obesity models is unlike anything seen before in this class.

Understanding how retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models requires a clear look at receptor biology, efficacy endpoints, and the structural differences that separate these compounds at the molecular level.

Key Takeaways

  • Retatrutide is a triple agonist activating GLP-1, GIP, and glucagon receptors simultaneously, producing greater metabolic effects than single or dual agonists.
  • Phase 3 TRIUMPH-4 data showed 28.7% average weight loss at 68 weeks — the highest recorded in any obesity trial to date.
  • GLP-2 peptides act primarily on intestinal repair and growth, not on adipose tissue or appetite suppression, making them functionally distinct from GLP-1 class agents.
  • Retatrutide's glucagon receptor component raises resting metabolic rate and promotes lipolysis, a mechanism absent in GLP-1-only agents.
  • As of 2026, retatrutide remains in Phase 3 trials, with a New Drug Application filing anticipated in late 2026 or early 2027.

Retatrutide triple receptor agonist mechanism diagram

The Receptor Architecture Behind Triple Agonism

How retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models starts with a fundamental structural distinction. Retatrutide is built on a GIP backbone, modified to resist DPP-4 enzymatic degradation, and conjugated to a C20 fatty diacid moiety that extends its half-life. This architecture allows it to engage three receptors simultaneously:

Receptor Primary Effect
GLP-1R Insulin secretion, appetite suppression
GIPR Enhanced insulin response, fat metabolism
GCG-R Increased resting metabolic rate, lipolysis

GLP-1 agonists like semaglutide activate only the GLP-1 receptor. This reduces appetite and improves glycemic control but leaves energy expenditure largely unchanged. Dual agonists such as tirzepatide add GIP receptor activation, improving insulin sensitivity and fat metabolism. Retatrutide layers glucagon receptor agonism on top of both, actively raising the rate at which the body burns stored fat.

GLP-2 peptides occupy a completely different functional space. Their primary role is intestinal epithelial growth, mucosal repair, and nutrient absorption regulation. In obesity models, GLP-2 analogs show minimal direct impact on body weight or adipose tissue reduction. Researchers studying gut-barrier integrity or inflammatory bowel conditions find GLP-2 highly relevant, but it does not compete with GLP-1 class agents on weight-loss endpoints.

For those exploring the broader landscape of incretin-related research, the GLP-3 and retatrutide incretin research themes page provides useful context on how these receptor classes are being studied in parallel.


Weight loss comparison bar chart: Retatrutide vs GLP-1 agents

Efficacy Data Across Obesity Models: Where the Numbers Diverge

The clinical weight-loss data illustrates the gap between these approaches with precision.

  • Semaglutide (GLP-1 only): approximately 14.9% body weight reduction over 68 weeks
  • Tirzepatide (GLP-1 + GIP): approximately 22.5% over 72 weeks
  • Retatrutide 12 mg (GLP-1 + GIP + GCG): 28.7% over 68 weeks in the TRIUMPH-4 Phase 3 trial

"Retatrutide's triple-agonist approach may redefine obesity treatment by offering weight loss results approaching those of bariatric surgery."

In Phase 2 trials, participants at the 12 mg dose also showed a 2.2% reduction in HbA1c from a baseline of approximately 8.3%, with 82% reaching HbA1c levels at or below 6.5%. This dual impact on both body weight and glycemic control strengthens retatrutide's research profile considerably.

The glucagon receptor component deserves particular attention. By increasing resting metabolic rate and driving lipolysis, it creates an energy-expenditure advantage that neither GLP-1 nor GLP-2 agents can replicate. This is why researchers tracking AOD-9604 metabolic research and lipolytic peptide mechanisms are increasingly interested in how glucagon co-agonism fits into broader fat-loss models.

For context on how GLP-1 peptides are currently categorized and studied, that resource outlines the foundational receptor class from which retatrutide diverges.


Researcher reviewing peptide molecular data in laboratory

How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models: Safety and Research Outlook

The side-effect profile of retatrutide largely mirrors that of other GLP-1 class agents. Nausea, diarrhea, vomiting, and constipation are the most commonly reported issues. One notable distinction is dysesthesia — tingling or burning sensations — reported in approximately 20.9% of participants at the 12 mg dose in TRIUMPH-4. This is not commonly observed with GLP-1-only or GLP-2 agents and likely reflects glucagon receptor activity.

As of 2026, retatrutide remains in Phase 3 trials. An NDA filing is anticipated in late 2026 or early 2027. Researchers sourcing compounds for preclinical work can review the GLP-3 Retatrutide 10mg research product for current availability.

Those building a broader metabolic research framework may also find value in exploring what is new in peptide research to understand how retatrutide fits alongside other emerging compounds, or reviewing NAD research and GLP-3 online resources for complementary metabolic pathways under investigation.

For researchers studying peptide blends in research contexts, the triple-agonist design of retatrutide also raises questions about whether combination approaches in preclinical models could replicate or extend its receptor-engagement profile.


Conclusion

How retatrutide compares with GLP-1 and GLP-2 research peptides in obesity models comes down to receptor breadth and metabolic reach. GLP-1 agents suppress appetite and improve insulin response. GLP-2 agents repair intestinal tissue. Retatrutide does something categorically different: it activates three complementary pathways at once, producing weight-loss outcomes that exceed all prior pharmacological benchmarks and approach the efficacy of surgical intervention.

Actionable next steps for researchers:

  • Review Phase 2 and TRIUMPH-4 Phase 3 trial data to understand dose-response relationships at the 4 mg, 8 mg, and 12 mg levels.
  • Distinguish GLP-2 research models (gut repair, nutrient absorption) from GLP-1/GCG co-agonism models before designing obesity endpoints.
  • Monitor NDA filing timelines in late 2026 and early 2027 for regulatory developments that may affect research access.
  • Evaluate glucagon receptor co-agonism as a distinct variable when comparing metabolic outcomes across peptide classes.

The research conversation around obesity pharmacology has changed. Triple agonism is no longer a theoretical advantage — the data has made it a measurable one.


https://www.puretestedpeptides.com/wp-content/uploads/2026/06/How-Retatrutide-Compares-With-GLP-1-and-GLP-2-Research-Peptides-in-Obesity-Models.png 672 1024 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-04 13:18:082026-07-20 15:04:07How Retatrutide Compares With GLP-1 and GLP-2 Research Peptides in Obesity Models
Retatrutide Safety, Side Effects, and Study Design: What Researchers Should Watch in Ongoing Obesity Trials

Retatrutide Safety, Side Effects, and Study Design: What Researchers Should Watch in Ongoing Obesity Trials

June 3, 2026/0 Comments/by Pure Tested

Ninety-two percent of participants in a 48-week Phase 2 trial achieved at least 5% body weight loss with retatrutide — a figure that immediately set this triple-receptor agonist apart from earlier obesity pharmacotherapies. For researchers tracking the evolving landscape of investigational peptides, understanding retatrutide safety, side effects, and study design in ongoing obesity trials is now essential groundwork.

Scientific infographic-style landscape image () showing a detailed cross-section diagram of three hormone receptors — GIP,

Key Takeaways

  • Retatrutide simultaneously activates GIP, GLP-1, and glucagon receptors, producing weight loss superior to earlier single or dual agonists.
  • Gastrointestinal side effects are the most common adverse events and are dose-dependent and generally mild to moderate.
  • A structured dose-escalation schedule starting at 2 mg has been shown to reduce early tolerability issues.
  • The Phase 3 TRIUMPH program enrolls over 5,800 participants across four trials, including cardiovascular and musculoskeletal subpopulations.
  • Adverse event-related discontinuation rates in Phase 2 ranged from 6% to 16%, a critical tolerability signal for Phase 3 monitoring.

How Retatrutide Works: Triple Agonism and Its Research Implications

Retatrutide is a once-weekly subcutaneous peptide that activates three hormone receptors: glucose-dependent insulinotropic polypeptide (GIP), glucagon-like peptide-1 (GLP-1), and glucagon. This triple mechanism distinguishes it from earlier agents. Researchers familiar with GLP-1 peptide sourcing and generational research concepts will recognize how each successive generation of receptor agonists has broadened metabolic targets.

The glucagon receptor component is particularly notable. It drives energy expenditure and lipolysis in ways that GLP-1 alone does not. Understanding the GIP receptor and its importance alongside GLP-1 activity helps explain why retatrutide outperformed other glucagon receptor agonists in a network meta-analysis, showing a mean weight reduction of 13.44 kg compared to placebo.

A 2024 systematic review and meta-analysis of randomized controlled trials confirmed retatrutide reduced body weight by an average of 10.66 kg versus placebo, with additional improvements in waist circumference and BMI. These metabolic marker changes matter for researchers designing endpoints that go beyond simple weight outcomes.

For context on how this compares to other investigational metabolic peptides, the SLU-PP-332 metabolic modulation research overview provides useful framing on alternative pathways under investigation.


Retatrutide Safety and Side Effects: Tolerability Signals Researchers Must Track

Retatrutide Safety and Side Effects: Tolerability Signals Researchers Must Track

The most consistent finding across retatrutide trials is that gastrointestinal adverse events dominate the safety profile. Nausea, diarrhea, vomiting, and constipation are the primary concerns. These effects are dose-related, meaning higher doses produce more frequent and more intense symptoms.

Key tolerability data from Phase 2:

Adverse Event Category Frequency
Any gastrointestinal event Most common across all dose groups
Discontinuation due to adverse events 6% to 16% in retatrutide arms
Discontinuation in placebo group 0%
Serious adverse events (SAEs) 4% overall; 0%–6% by dose group

The SAE rate of 4% in retatrutide groups matched the 4% rate in placebo groups, which is an important signal: serious events were not meaningfully elevated above background rates. However, the gap in discontinuation rates — up to 16% versus 0% in placebo — indicates that tolerability, not safety in the traditional sense, is the primary challenge.

Dose-escalation as a mitigation strategy has been central to retatrutide's development. Starting participants at 2 mg before escalating to target doses partially reduced early gastrointestinal burden. This titration logic is now embedded in Phase 3 protocols and represents a key variable researchers should monitor when interpreting trial results.

Researchers comparing tolerability across investigational peptides may also find value in reviewing selank side effects research and BPC-157 core peptide documentation for contrast in adverse event profiles across different peptide classes.

"Tolerability, not toxicity, is the primary research question in retatrutide's Phase 3 program."


Phase 3 TRIUMPH Trial Design: What Researchers Should Watch in Ongoing Obesity Trials

Phase 3 TRIUMPH Trial Design: What Researchers Should Watch in Ongoing Obesity Trials

The TRIUMPH program is the definitive test of retatrutide safety, side effects, and study design in ongoing obesity trials. Four multicenter, randomized, double-blind Phase 3 studies enroll more than 5,800 participants receiving weekly subcutaneous retatrutide. The program spans standard obesity populations and extends into clinically complex subgroups.

Trial design features researchers should monitor:

  • Cardiovascular subpopulation (TRIUMPH-3): Specifically evaluates retatrutide in participants with established cardiovascular disease. This endpoint mirrors the cardiovascular outcomes trial model used with earlier GLP-1 agents.
  • Comorbidity expansion: Trials address obstructive sleep apnea and knee osteoarthritis alongside weight outcomes, broadening the clinical relevance of findings.
  • Dose-titration schedules: How Phase 3 protocols handle dose escalation will directly affect both efficacy outcomes and adverse event rates.
  • MASLD investigation: A separate Phase 2a trial is examining retatrutide's potential in metabolic dysfunction-associated steatotic liver disease, with results still pending in 2026.

Researchers following GLP-3 triple agonist research planning and the broader RETA GLP-3 research framework will find the TRIUMPH design choices instructive for understanding how trial architects balance efficacy ambition against tolerability risk.

The generations of GLP-1 differences resource also contextualizes why TRIUMPH's multi-indication design represents a meaningful evolution from earlier single-endpoint obesity trials.


Conclusion

Retatrutide's Phase 2 data established a compelling efficacy signal. The Phase 3 TRIUMPH program now carries the burden of confirming whether that signal holds across diverse populations while maintaining an acceptable tolerability profile. For researchers in 2026, the most actionable focus areas are:

  1. Track discontinuation rates by dose group as the primary tolerability benchmark.
  2. Monitor dose-escalation protocol adherence and its effect on gastrointestinal event frequency.
  3. Watch TRIUMPH-3 cardiovascular outcomes as the highest-stakes safety dataset in the program.
  4. Follow the MASLD Phase 2a results for evidence of retatrutide's reach beyond weight management.
  5. Compare SAE rates across subpopulations to identify whether cardiovascular or musculoskeletal comorbidities alter the safety profile.

The evidence base for retatrutide is maturing rapidly. Researchers who understand both the mechanism and the methodological choices embedded in its trial design will be best positioned to interpret findings as they emerge.


https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Retatrutide-Safety-Side-Effects-and-Study-Design-What-Researchers-Should-Watch-in-Ongoing-Obesity-Trials.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-03 13:06:002026-07-20 15:04:10Retatrutide Safety, Side Effects, and Study Design: What Researchers Should Watch in Ongoing Obesity Trials
Page 5 of 6«‹3456›
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top