Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: retatrutide

Retatrutide Phase 3 Diabetes Data: Designing Research Models Around A1C, Glucose Exposure, Weight Loss, and Dose Escalation

Retatrutide Phase 3 Diabetes Data: Designing Research Models Around A1C, Glucose Exposure, Weight Loss, and Dose Escalation

October 8, 2026/0 Comments/in Uncategorized/by

Only one drug in the current cardiometabolic pipeline simultaneously activates GLP-1, GIP, and glucagon receptors, and its Phase 3 data are now reshaping how researchers design glycemic studies. Retatrutide Phase 3 diabetes data, drawn from the TRANSCEND and TRIUMPH trial programs, offer an unusually rich dataset for modeling the relationship between A1C reduction, glucose area under the curve (AUC), body weight loss, and structured dose escalation. For researchers building preclinical or translational models, understanding how to separate direct glycemic effects from weight-mediated effects is now a central methodological challenge.

Key Takeaways

  • Retatrutide Phase 3 diabetes data from TRANSCEND-T2D and TRIUMPH-2 provide robust endpoints for A1C, fasting glucose, and body weight in type 2 diabetes populations.
  • Glucose AUC and A1C timing data allow researchers to model direct glycemic receptor effects independently of body-weight-mediated insulin sensitization.
  • Dose escalation protocols in Phase 3 trials (ranging from 2 mg to 24 mg weekly) are critical variables when designing exposure-response research models.
  • Placebo-adjusted analysis is essential for isolating the true pharmacodynamic signal in both glycemic and weight outcomes.
  • The dual burden of hyperglycemia and obesity in trial populations makes retatrutide a uniquely informative compound for integrated cardiometabolic research.

Understanding the Phase 3 Trial Architecture

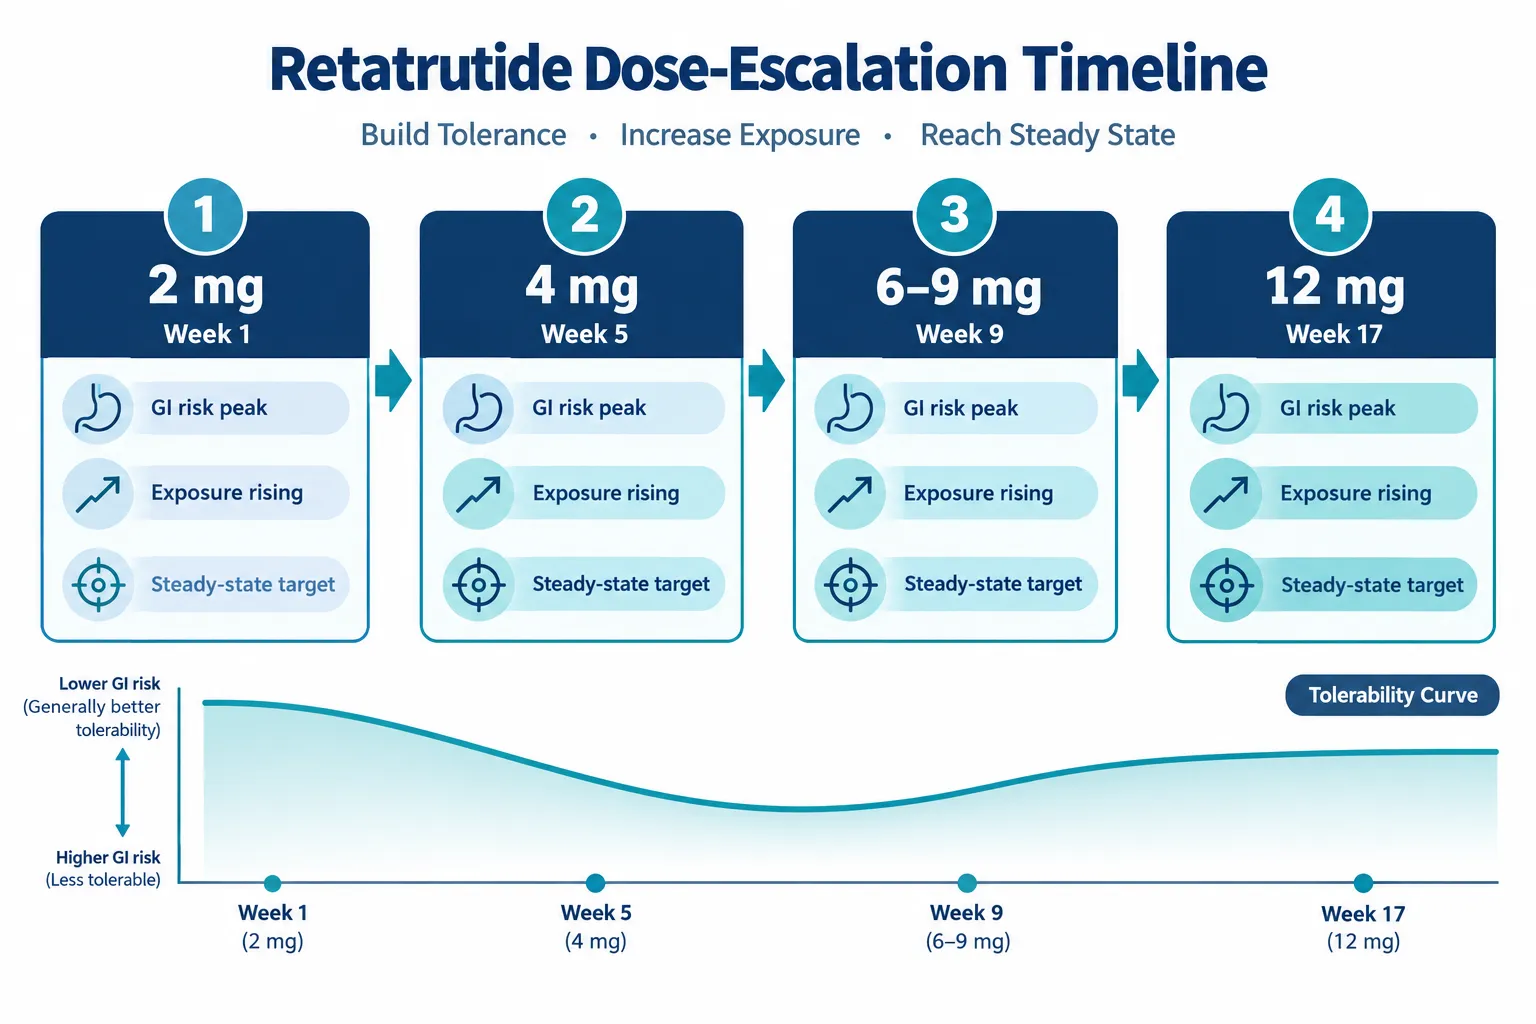
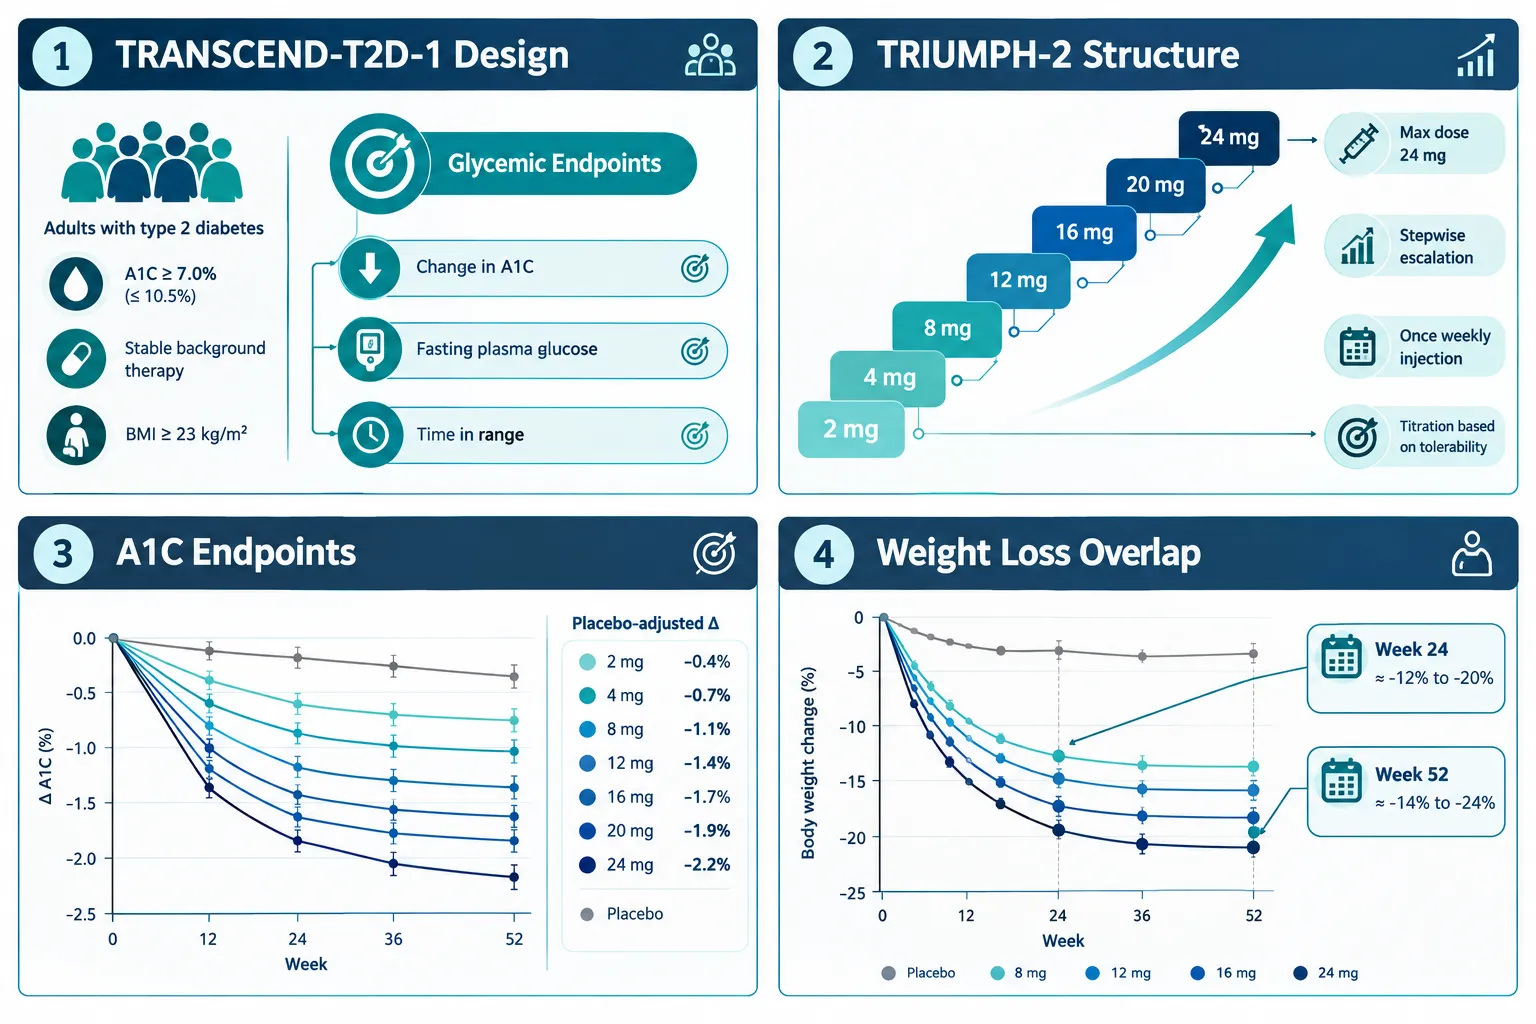
The TRANSCEND-T2D program is the dedicated diabetes efficacy arm of retatrutide's Phase 3 development. TRANSCEND-T2D-1 enrolled adults with type 2 diabetes and suboptimal glycemic control, using A1C reduction as the primary endpoint alongside fasting plasma glucose and body weight. The trial design included a structured dose escalation schedule, beginning at 2 mg weekly and titrating upward over several weeks to target maintenance doses of 8 mg or 12 mg.
Understanding the Phase 3 Trial Architecture

What makes this data particularly valuable for research modeling is the granularity of glycemic endpoints. A1C was measured at multiple timepoints, and continuous glucose monitoring data in select cohorts provided glucose AUC profiles across fasting and postprandial windows. This allows researchers to distinguish early pharmacodynamic effects, driven by direct receptor activation, from later improvements that correlate more closely with cumulative weight loss.

The broader TRANSCEND-T2D program extends follow-up to 52 weeks and beyond, providing chronic exposure data that are essential for modeling long-term glucose normalization trajectories. Researchers exploring Retatrutide Endpoints will find the TRANSCEND dataset particularly useful for establishing dose-response relationships across glycemic variables.


Separating Glycemic Effects from Weight-Mediated Effects in Retatrutide Phase 3 Diabetes Data

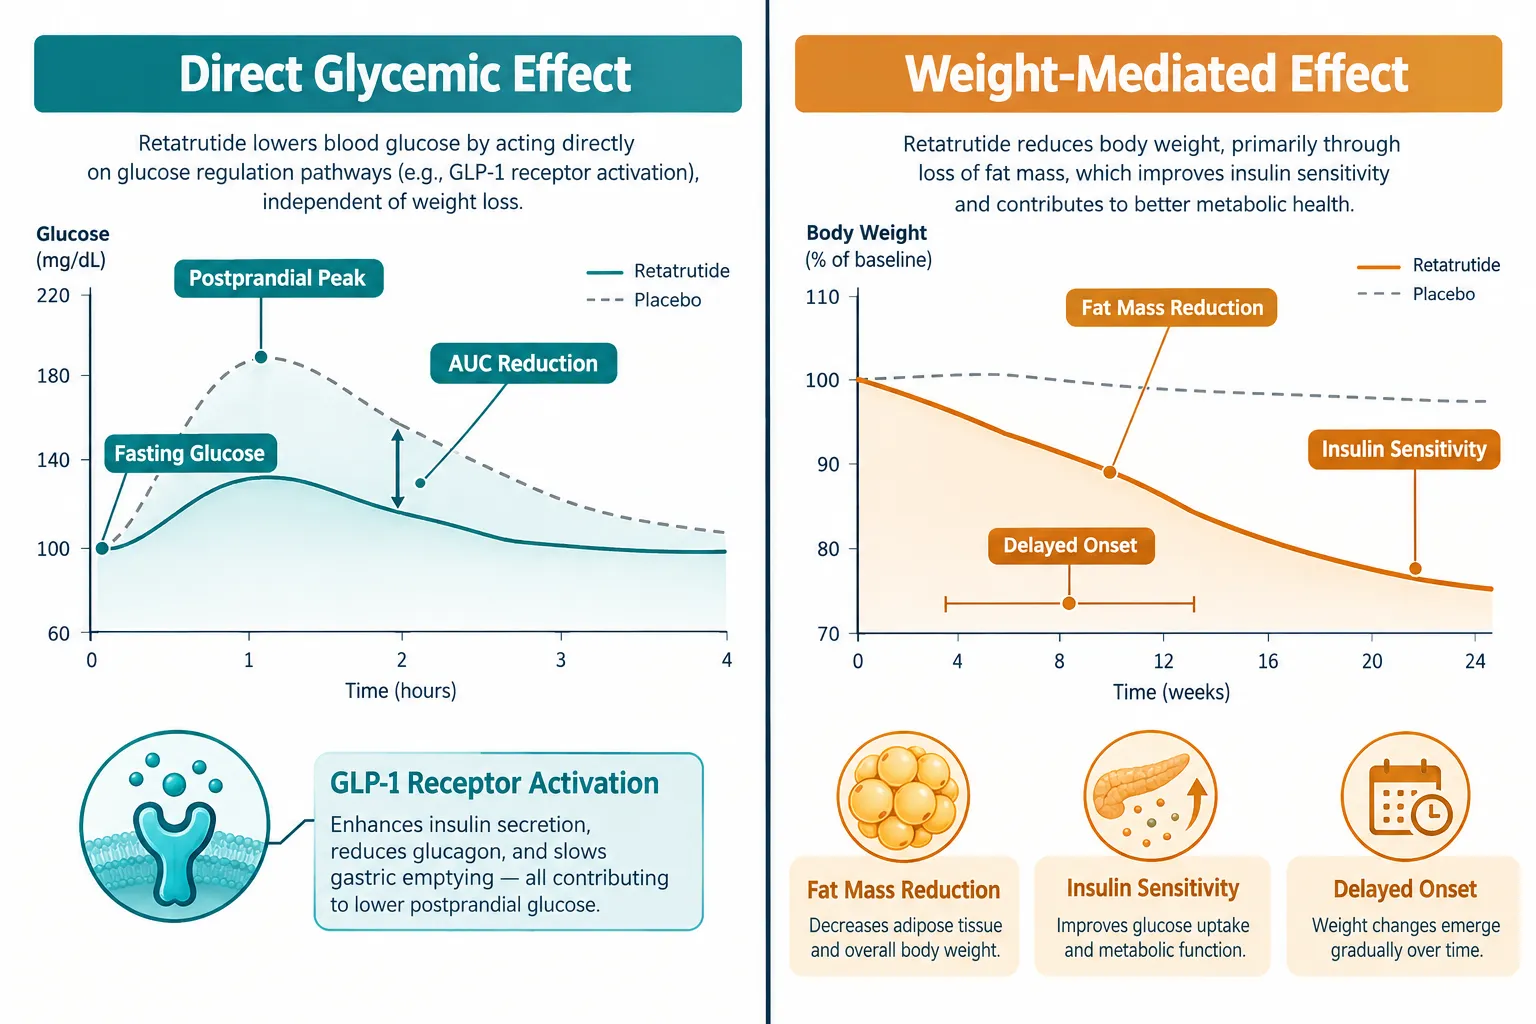
This is the core methodological question that Retatrutide Phase 3 diabetes data: designing research models around A1C, glucose exposure, weight loss, and dose escalation must address. Retatrutide produces two partially overlapping but mechanistically distinct effects: direct incretin-mediated glycemic control and indirect glycemic improvement driven by fat mass reduction and restored insulin sensitivity.
Separating Glycemic Effects from Weight-Mediated Effects in Retatrutide Phase 3 Diabetes Data

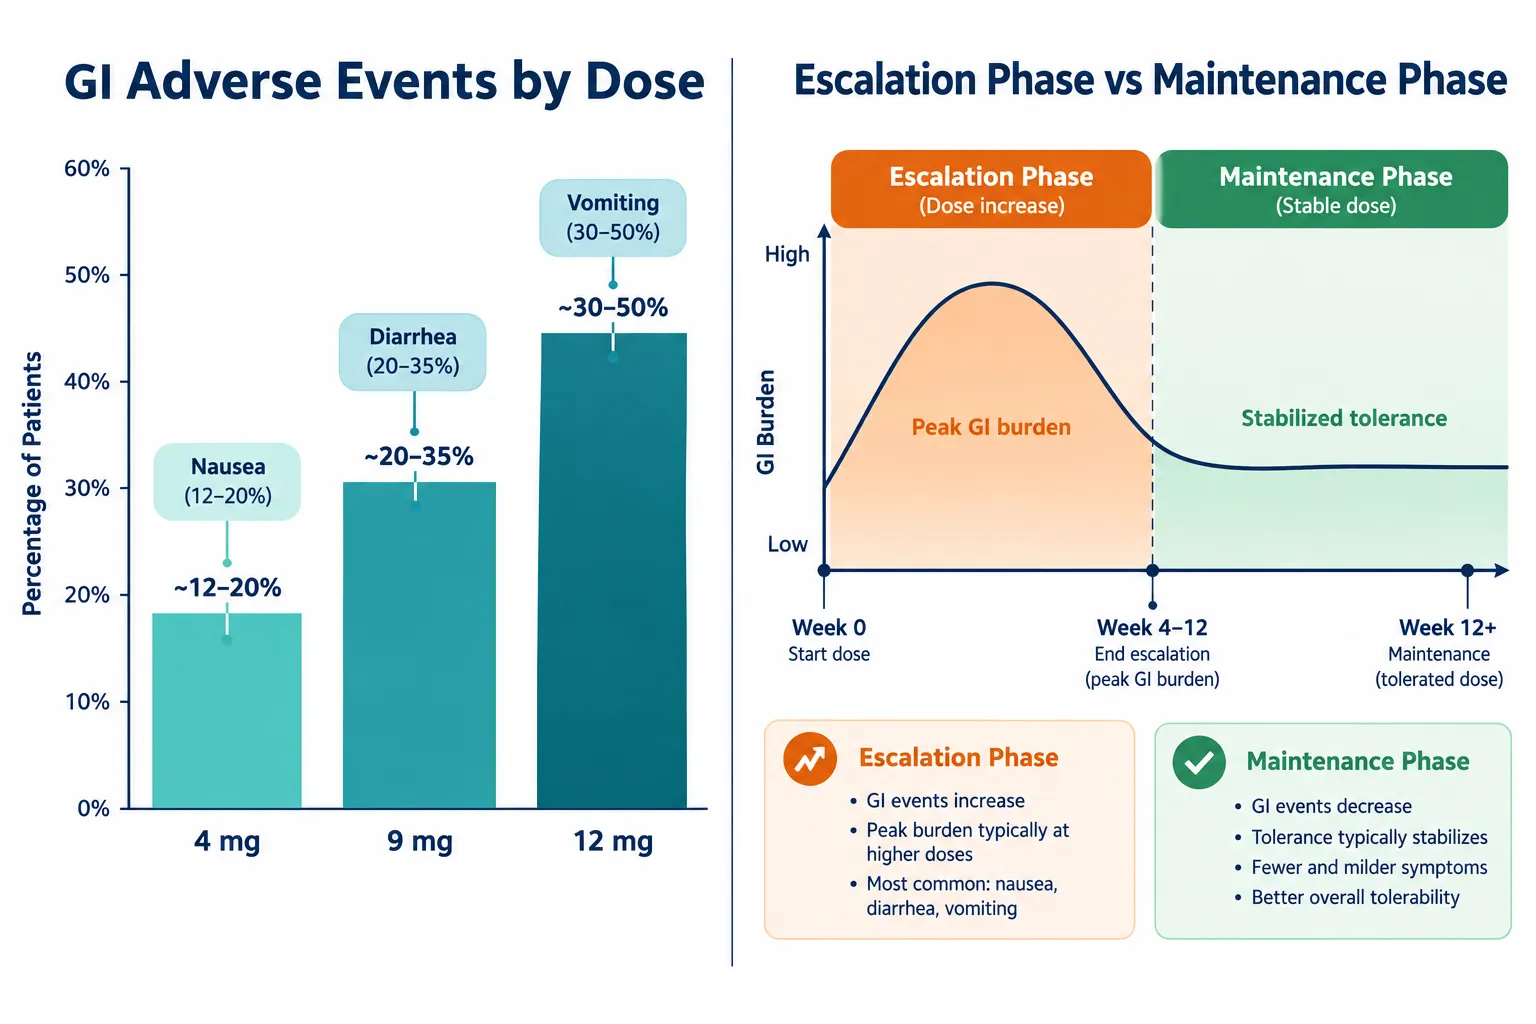
Direct glycemic effects are detectable early, often within the first four weeks, before significant weight loss has accumulated. These include:

  • Reduced fasting plasma glucose via GLP-1 receptor-mediated insulin secretion
  • Suppressed glucagon secretion through glucagon receptor agonism at pharmacological doses
  • Improved postprandial glucose AUC through slowed gastric emptying

Weight-mediated glycemic effects emerge later and are characterized by:

  • Progressive improvement in insulin sensitivity correlated with fat mass reduction
  • Declining HOMA-IR scores tracking body weight trajectory
  • A1C reductions that continue after glucose-lowering receptor effects plateau

"Placebo-adjusted A1C delta at Week 12 versus Week 52 provides a practical window for separating these two mechanisms in research model design."

The TRIUMPH-2 trial, which enrolled participants with both obesity and type 2 diabetes, is especially informative here. TRIUMPH-2 reported substantial A1C reductions alongside body weight losses exceeding 20% from baseline at higher doses. By comparing A1C trajectories against weight-loss kinetics, researchers can use time-lagged regression models to quantify the independent glycemic contribution of the drug's receptor activity.

For researchers interested in related dual-mechanism compounds, the Cagrilintide And Retatrutide combination data offer a complementary framework for modeling additive glycemic and weight effects.


Dose Escalation as a Research Variable: Modeling Exposure-Response Relationships

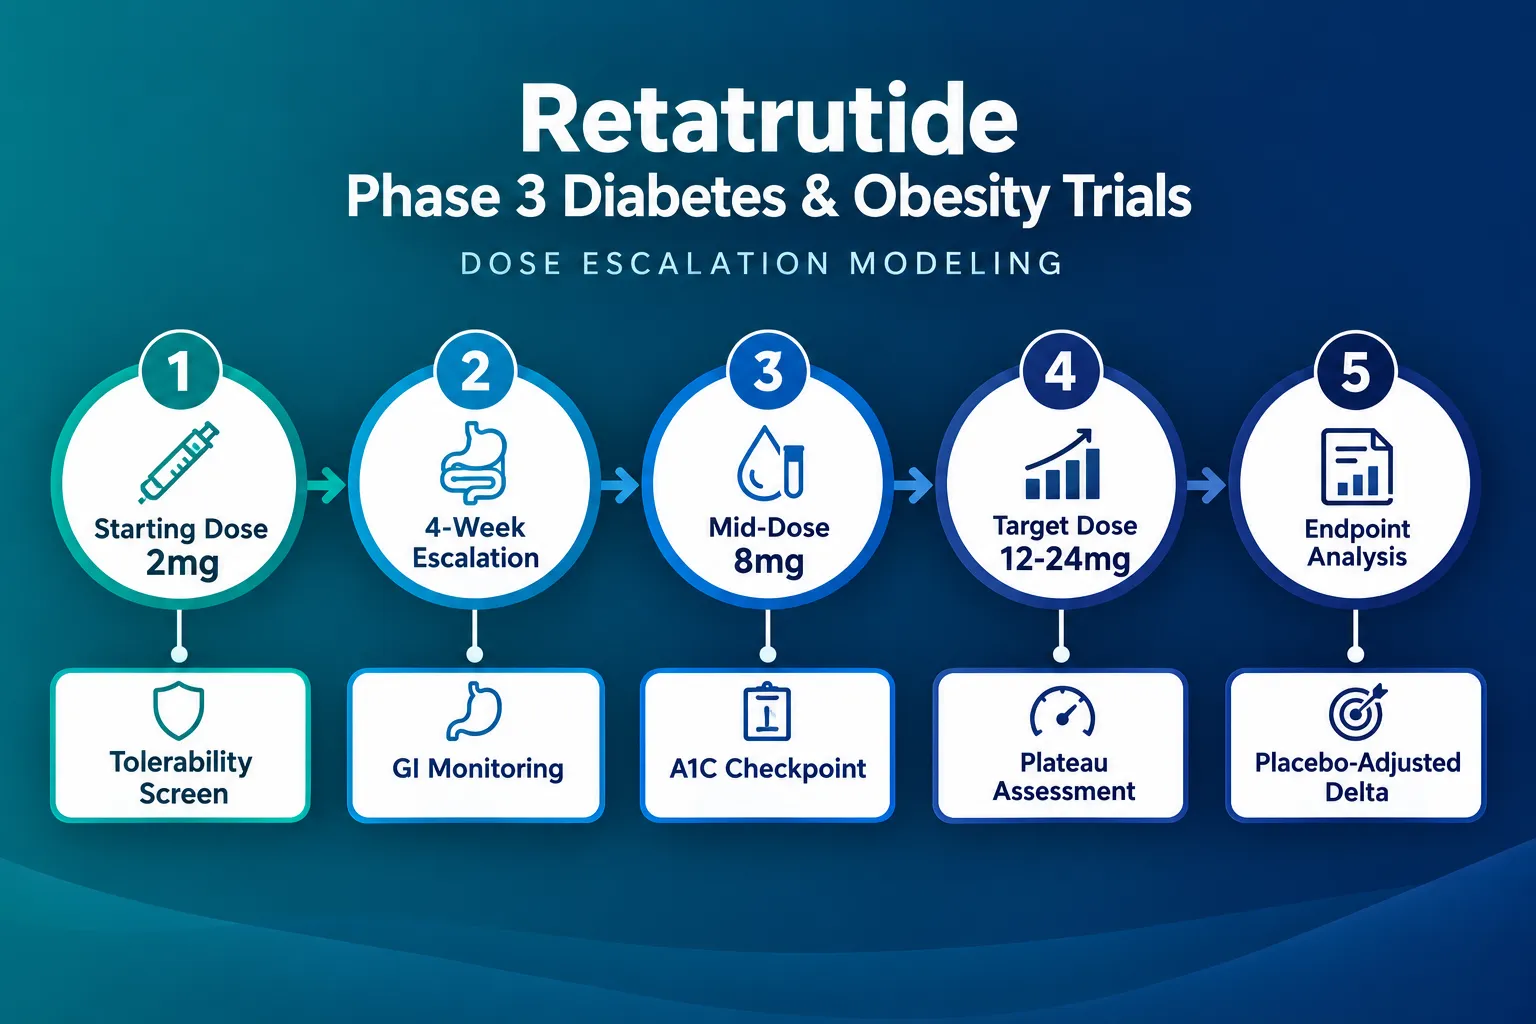
Dose escalation design is not merely a safety protocol, it is a primary research variable in Retatrutide Phase 3 diabetes data: designing research models around A1C, glucose exposure, weight loss, and dose escalation. The Phase 3 programs used weekly subcutaneous dosing with escalation steps at defined intervals, creating a natural dose-exposure ladder that researchers can exploit for pharmacokinetic-pharmacodynamic (PK-PD) modeling.
Dose Escalation as a Research Variable: Modeling Exposure-Response Relationships

Key dose escalation parameters from Phase 3 data include:

Escalation Stage Weekly Dose Primary Research Signal
Initiation 2 mg Tolerability, early GLP-1 effect
Mid-escalation 4-8 mg A1C inflection, glucose AUC shift
Maintenance 12-24 mg Maximum weight loss, sustained A1C

Phase 3b studies without diabetes populations provide a useful comparator, allowing researchers to isolate the weight-loss contribution to glycemic improvement by modeling the delta between diabetic and non-diabetic cohorts at equivalent doses.

For researchers sourcing compounds for preclinical work, GLP-1 Retatrutide and GLP-3 Retatrutide Buy Online USA pages provide relevant product information. Those evaluating quantity options may also review Reta 20mg For Sale and GLP-3 Reta 30mg For Sale for research-grade availability.

The TRIUMPH-1 and TRIUMPH-4 trials, focused primarily on obesity without diabetes, extend the dose-response dataset by providing weight-loss curves at equivalent dose levels without the confounding variable of baseline hyperglycemia. This cross-trial comparison is a powerful tool for building research models that quantify the glycemic benefit attributable solely to weight reduction.


Conclusion

Retatrutide Phase 3 diabetes data: designing research models around A1C, glucose exposure, weight loss, and dose escalation represents one of the most data-rich opportunities in current cardiometabolic research. The TRANSCEND and TRIUMPH programs together provide a structured, multi-dose, multi-timepoint dataset that enables researchers to disentangle direct receptor-mediated glycemic effects from weight-loss-driven improvements.

Actionable next steps for researchers:

  1. Use early-timepoint A1C and glucose AUC data (Weeks 4-12) to establish direct glycemic receptor effect baselines before significant weight loss accumulates.
  2. Apply placebo-adjusted analysis at each dose level to isolate the true pharmacodynamic signal from regression to the mean.
  3. Leverage the TRIUMPH-2 versus TRIUMPH-1 cross-trial comparison to quantify the weight-mediated glycemic contribution at matched dose levels.
  4. Incorporate dose escalation timing as a covariate in PK-PD models to account for exposure-dependent receptor desensitization.
  5. Validate preclinical models against the Phase 3 dose-response ladder before extrapolating to novel endpoints.

The depth of available Phase 3 data makes retatrutide a uniquely powerful reference compound for integrated glycemic and metabolic research model design in 2026.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-phase-3-diabetes-data-designing-research-models-around-a1c-glucose-e.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-08 13:11:152026-10-08 13:11:15Retatrutide Phase 3 Diabetes Data: Designing Research Models Around A1C, Glucose Exposure, Weight Loss, and Dose Escalation
Atorvastatin and Research Peptides: Designing Lipid and Liver-Control Groups for Metabolic Studies

Atorvastatin and Research Peptides: Designing Lipid and Liver-Control Groups for Metabolic Studies

October 6, 2026/0 Comments/in Uncategorized/by

Cardiovascular disease remains the leading cause of death worldwide, yet fewer than half of high-risk research subjects in preclinical metabolic models reach target lipid endpoints without a standardized control framework. Designing rigorous control groups is where most metabolic studies succeed or fail, and the intersection of Atorvastatin and Research Peptides: Designing Lipid and Liver-Control Groups for Metabolic Studies sits at the center of that challenge. As novel peptides such as retatrutide, MOTS-c, and 5-amino-1MQ enter metabolic research pipelines, pairing them against a well-characterized statin benchmark like atorvastatin is no longer optional, it is methodologically essential.

Key Takeaways

  • Atorvastatin reliably lowers LDL, triglycerides, and non-HDL cholesterol, making it the gold-standard lipid control comparator in metabolic studies.
  • Liver safety endpoints, particularly ALT, AST, and histological steatosis scores, must be tracked in every atorvastatin-containing control arm.
  • Peptide arms (retatrutide, MOTS-c, 5-amino-1MQ) require a statin-exposed control group to isolate peptide-specific metabolic contributions.
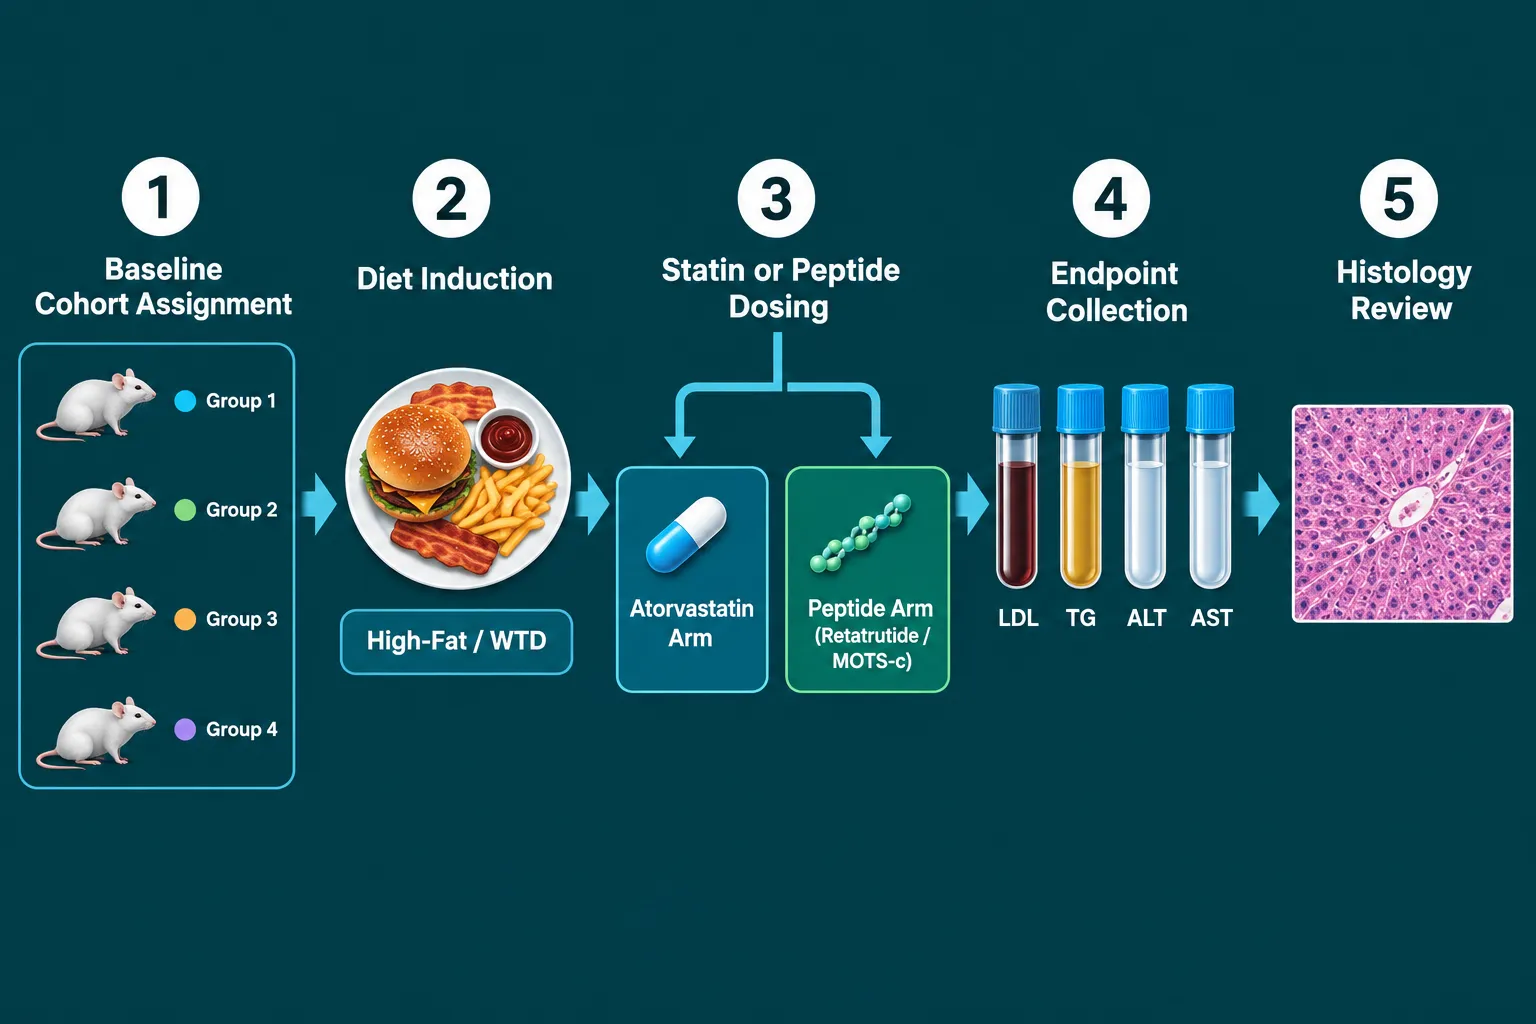
  • Western-type diet (WTD) models with and without atorvastatin remain the canonical structure for NAFLD and hyperlipidemia research designs.
  • Multi-arm study designs that combine diet, statin exposure, and peptide co-therapy now represent the evolving standard in 2026 metabolic research.

Why Atorvastatin Anchors Lipid and Liver-Control Group Design

Why Atorvastatin Anchors Lipid and Liver-Control Group Design

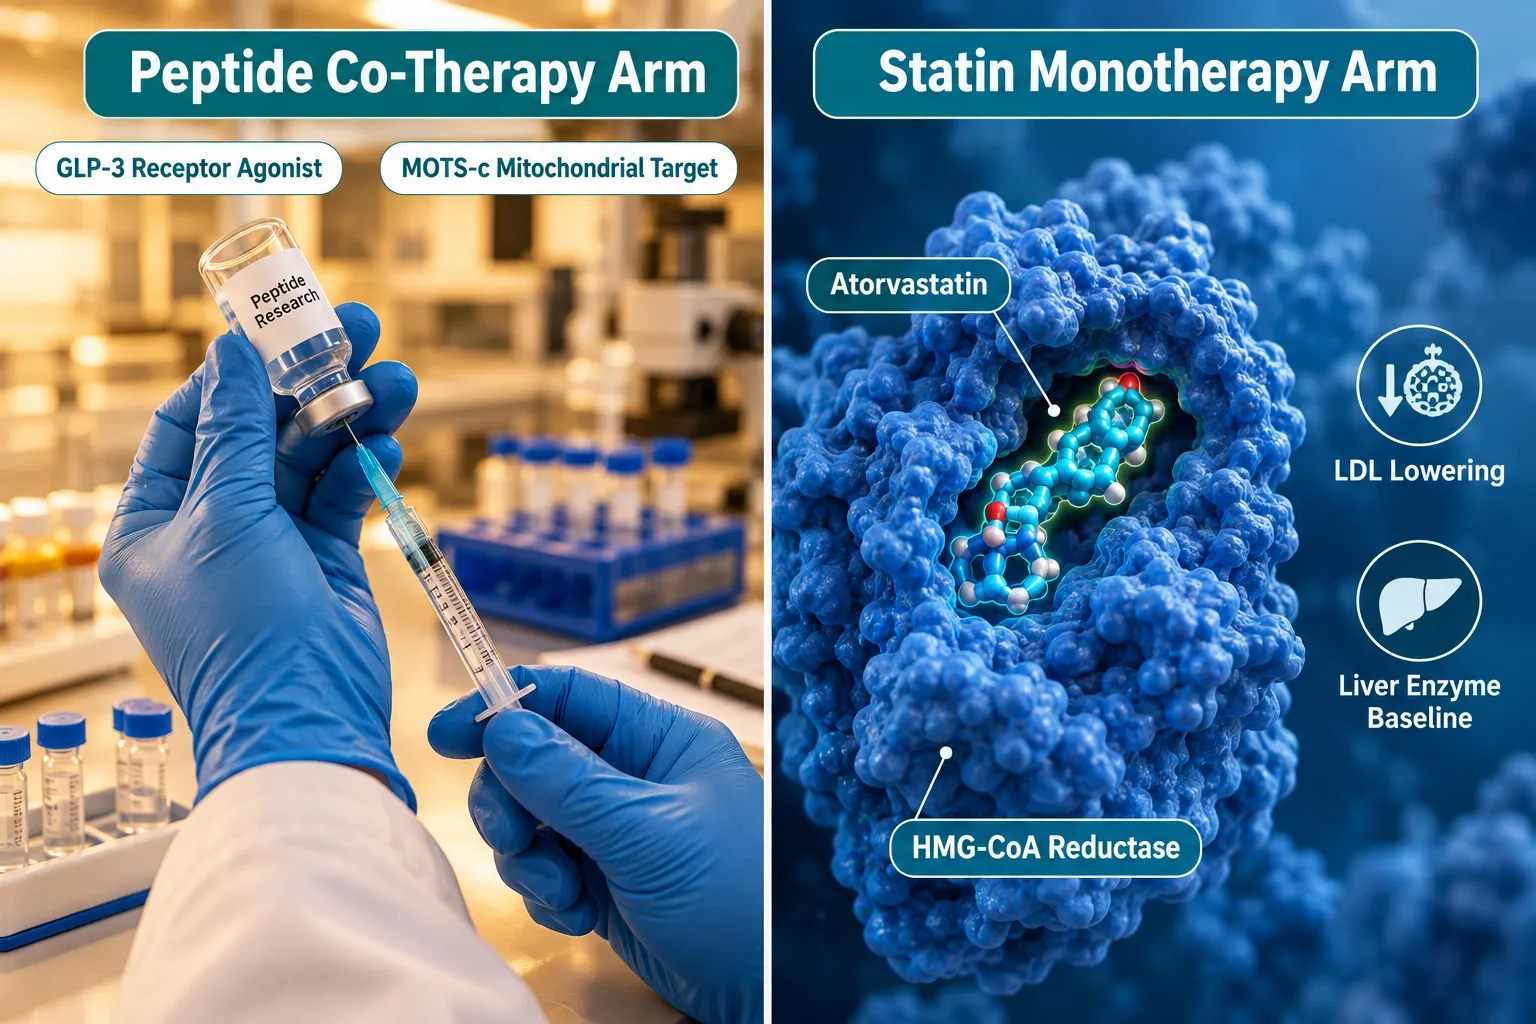
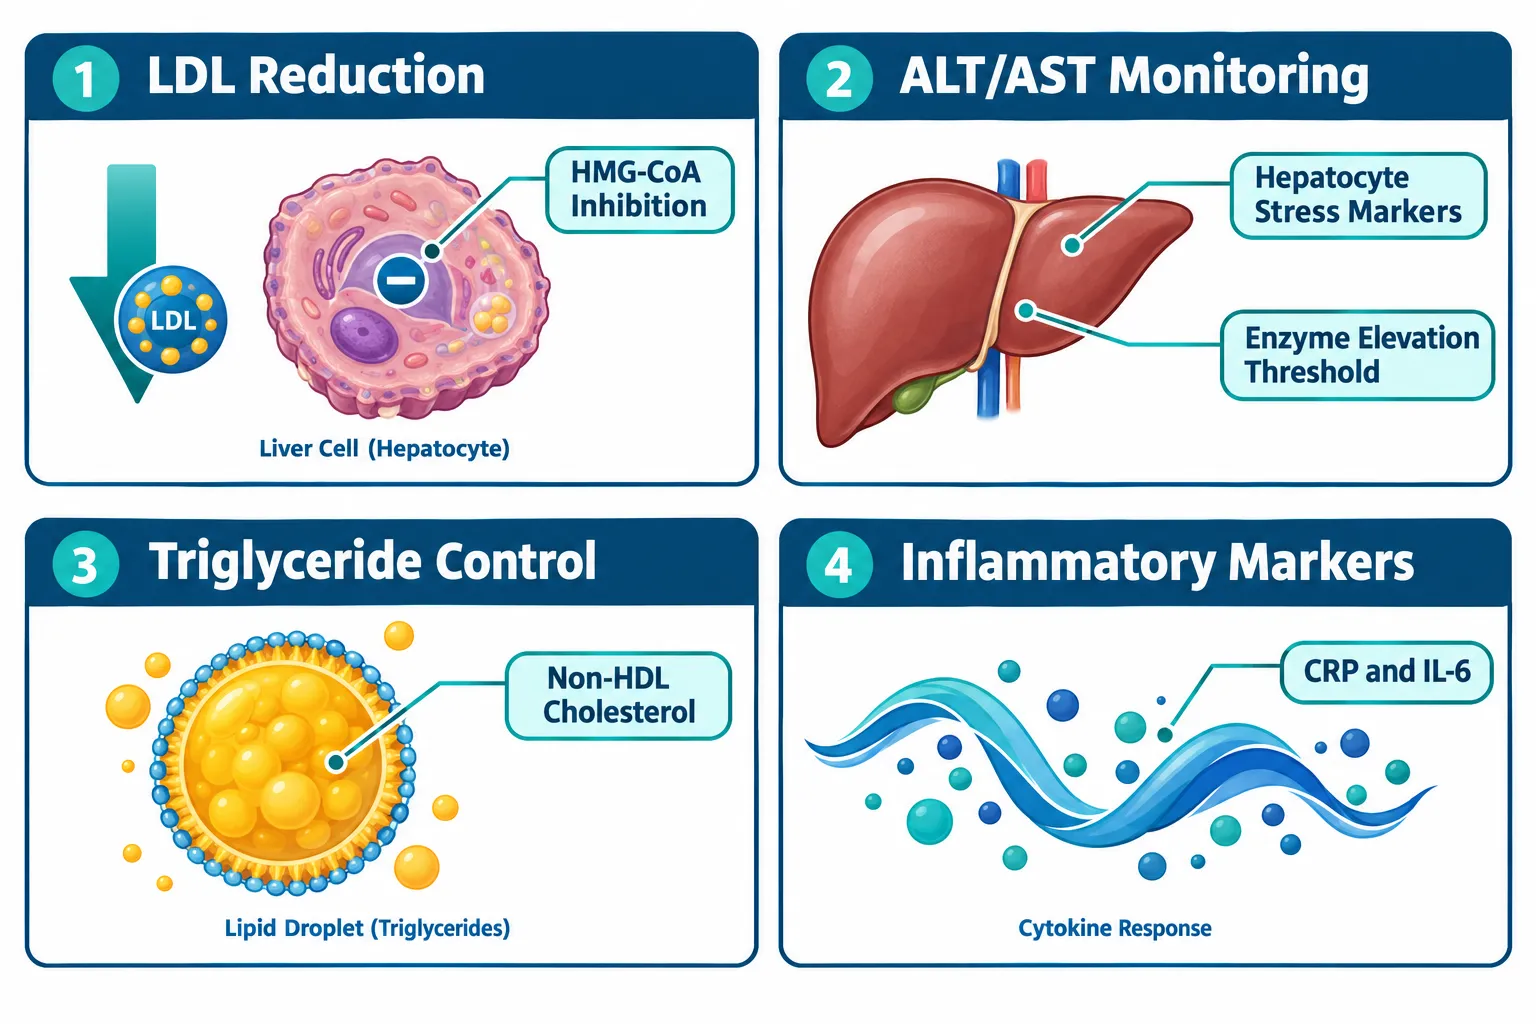
Atorvastatin is a high-intensity HMG-CoA reductase inhibitor with a well-mapped pharmacological profile. In metabolic research, that predictability is an asset. When a study introduces a novel peptide, researchers need a control arm whose lipid and liver effects are already understood, atorvastatin provides exactly that anchor.

Key lipid biomarkers affected by atorvastatin exposure include:

  • LDL cholesterol, typically reduced 40-55% at standard research doses
  • Triglycerides, modestly lowered, relevant in high-fat diet models
  • Non-HDL cholesterol, a composite marker that captures atherogenic particle burden
  • HDL cholesterol, marginally elevated, though not the primary endpoint

On the liver side, atorvastatin is metabolized extensively through CYP3A4 hepatic pathways. This makes ALT (alanine aminotransferase) and AST (aspartate aminotransferase) critical safety and efficacy readouts in every control arm. Current evidence from 2026 confirms that atorvastatin is safe even in subjects with advanced chronic liver disease, though transient enzyme elevations can occur and must be tracked systematically.

"A control group without liver enzyme monitoring is not a control group, it is an incomplete experiment."

For NAFLD and NASH models, atorvastatin also reduces hepatic steatosis scores and portal pressure markers. This means the "normal + atorvastatin" control arm carries meaningful liver biology, not just a lipid signal.


Structuring Multi-Arm Designs for Retatrutide, MOTS-c, and 5-Amino-1MQ Studies

Structuring Multi-Arm Designs for Retatrutide, MOTS-c, and 5-Amino-1MQ Studies

When Atorvastatin and Research Peptides: Designing Lipid and Liver-Control Groups for Metabolic Studies are combined in a multi-arm preclinical model, the architecture of the study determines what conclusions are actually possible. A poorly structured design cannot separate statin effects from peptide effects, and that ambiguity destroys interpretive value.

Recommended Multi-Arm Framework

Arm Diet Statin Peptide Primary Readouts
Vehicle Control Standard chow None None Baseline LDL, ALT, AST
Lipid Control WTD Atorvastatin None LDL, TG, non-HDL, ALT
Peptide Arm A WTD None Retatrutide GLP receptor activity, lipids
Peptide Arm B WTD None MOTS-c Mitochondrial markers, AST
Combination Arm WTD Atorvastatin Retatrutide or MOTS-c All lipid + liver endpoints

Retatrutide targets GLP-1, GIP, and glucagon receptors simultaneously, producing meaningful reductions in body weight and triglycerides. For researchers exploring this compound, the Buy Retatrutide Peptide resource provides relevant formulation context. When placed against an atorvastatin lipid-control arm, the incremental triglyceride and non-HDL reduction attributable to retatrutide becomes statistically isolatable.

MOTS-c operates through mitochondrial AMPK activation, influencing glucose metabolism and fatty acid oxidation. Its liver effects, particularly on hepatic lipid accumulation, overlap with atorvastatin's steatosis-reducing properties. Researchers sourcing this compound can reference the Buy MOTS-c Peptide page for purity and dosing specifications. The MOTS-c Peptide Dosage Calculator is also a practical tool for designing consistent dosing protocols.

5-amino-1MQ inhibits NNMT (nicotinamide N-methyltransferase), shifting cellular metabolism toward fat oxidation. Its inflammatory marker profile, including CRP and IL-6, makes it particularly important to track alongside ALT and AST in the atorvastatin control arm, since both compounds affect hepatic inflammatory tone.

For broader context on how these peptides compare mechanistically to small-molecule drugs, the article on Polypeptide Peptides in Cardiometabolic Models provides a strong conceptual foundation.


Liver-Centric Endpoints and Inflammatory Marker Integration

Liver-Centric Endpoints and Inflammatory Marker Integration

The most common failure in Atorvastatin and Research Peptides: Designing Lipid and Liver-Control Groups for Metabolic Studies is treating liver safety as secondary. In 2026, the evidence base has shifted firmly: liver endpoints are co-primary, not supplementary.

Liver-centric endpoints to include in every control arm:

  1. ALT and AST, tracked at baseline, mid-study, and endpoint; atorvastatin can cause transient elevations that must be distinguished from peptide-induced changes
  2. Hepatic steatosis score, histological grading from liver biopsy or MRI-based fat fraction
  3. Portal pressure markers, relevant in advanced NAFLD/NASH models
  4. Liver-to-body weight ratio, a rapid structural readout in rodent models

Inflammatory markers add a second interpretive layer. CRP, IL-6, and TNF-alpha are all modulated by atorvastatin through pleiotropic anti-inflammatory mechanisms. When a peptide like MOTS-c or GLP-3 peptide also reduces inflammatory load, the atorvastatin control arm provides the benchmark against which that reduction is measured.

Combination therapy designs, such as "phosphatidylcholine (PPC) alone" versus "PPC + atorvastatin", demonstrate how isolating statin-specific contributions requires a clean single-agent control. The same logic applies when adding SS-31 peptides to a metabolic model: the mitochondria-targeted antioxidant effects of SS-31 must be separated from atorvastatin's lipid-lowering signal through deliberate arm structure.

Monitoring schedule best practices:

  • Collect lipid panels at weeks 0, 4, 8, and 12 minimum
  • Run liver enzyme panels at the same intervals
  • Reserve histology for endpoint only (terminal in rodent models)
  • Include fasting insulin and HOMA-IR as metabolic co-endpoints

Conclusion

Designing rigorous control groups for metabolic peptide research is not a procedural formality, it is the scientific foundation on which every meaningful comparison rests. Atorvastatin's well-characterized effects on LDL, triglycerides, non-HDL cholesterol, ALT, and AST make it the most defensible lipid and liver-control comparator available for studies involving retatrutide, MOTS-c, or 5-amino-1MQ.

Actionable next steps for researchers in 2026:

  • Build a minimum five-arm design that separates vehicle, statin, peptide, and combination conditions
  • Pre-specify all liver enzyme thresholds as stopping rules and safety endpoints
  • Use Western-type diet induction as the metabolic stressor to activate both lipid and hepatic pathways
  • Align inflammatory marker panels (CRP, IL-6) with lipid and liver readouts for mechanistic depth
  • Consult formulation-specific resources for peptide purity verification before dosing begins

A well-structured control group does not slow research down, it makes the data worth publishing.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/atorvastatin-and-research-peptides-designing-lipid-and-liver-control-groups-for.webp 672 1008 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-06 13:10:132026-10-06 13:10:13Atorvastatin and Research Peptides: Designing Lipid and Liver-Control Groups for Metabolic Studies
Metoprolol in Peptide Experiments: Controlling Heart Rate, Blood Pressure, and Adrenergic Confounding

Metoprolol in Peptide Experiments: Controlling Heart Rate, Blood Pressure, and Adrenergic Confounding

October 6, 2026/0 Comments/in Uncategorized/by

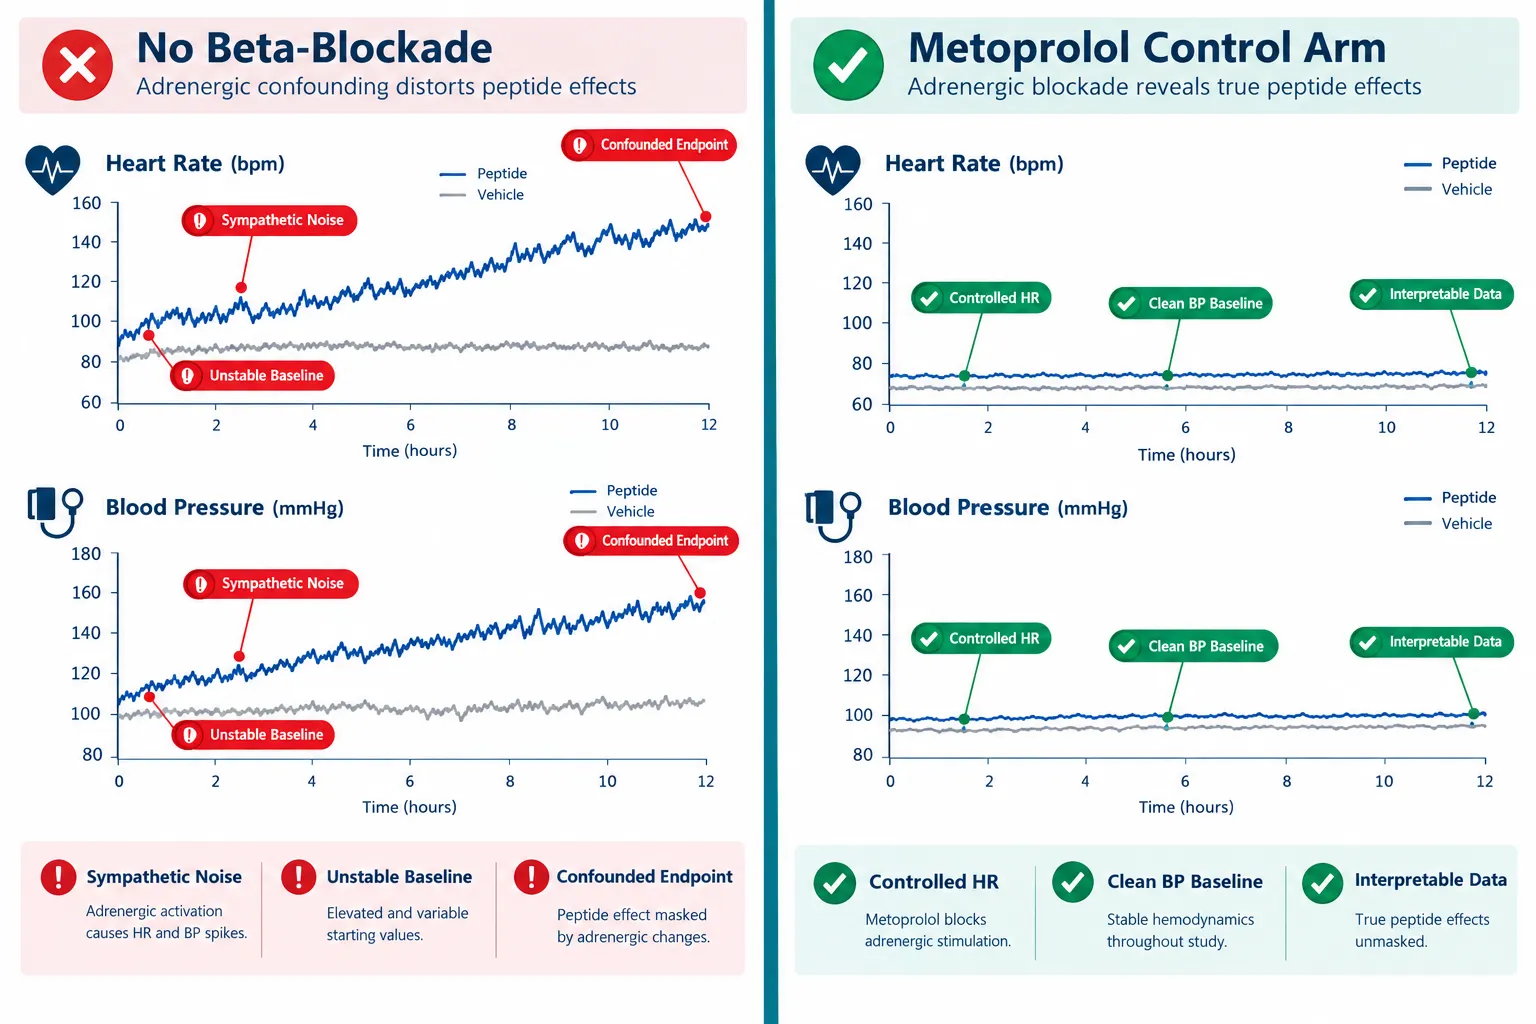
Cardiovascular endpoints fail silently when sympathetic noise is not controlled. Across retatrutide trials, growth-hormone-secretagogue models, and metabolic peptide studies, unmanaged adrenergic tone can shift heart rate by five to ten beats per minute and systolic blood pressure by several millimeters of mercury, differences large enough to obscure or mimic a genuine peptide effect. Understanding the role of metoprolol in peptide experiments for controlling heart rate, blood pressure, and adrenergic confounding is therefore not a minor methodological footnote; it is a foundational design decision.

Key Takeaways

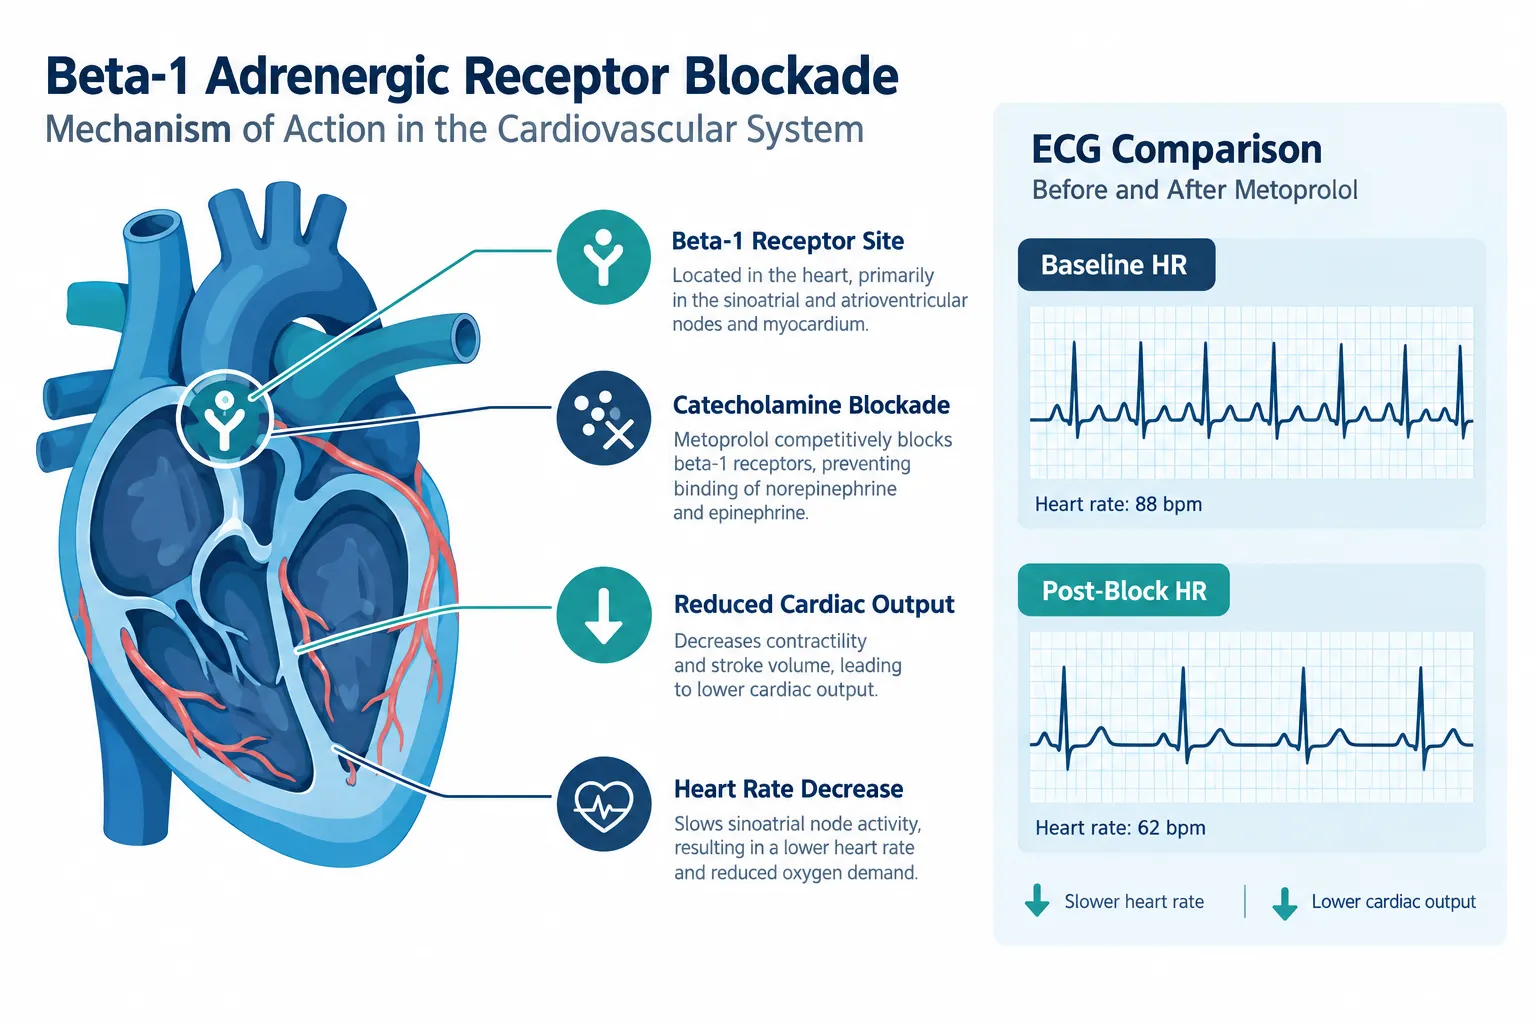
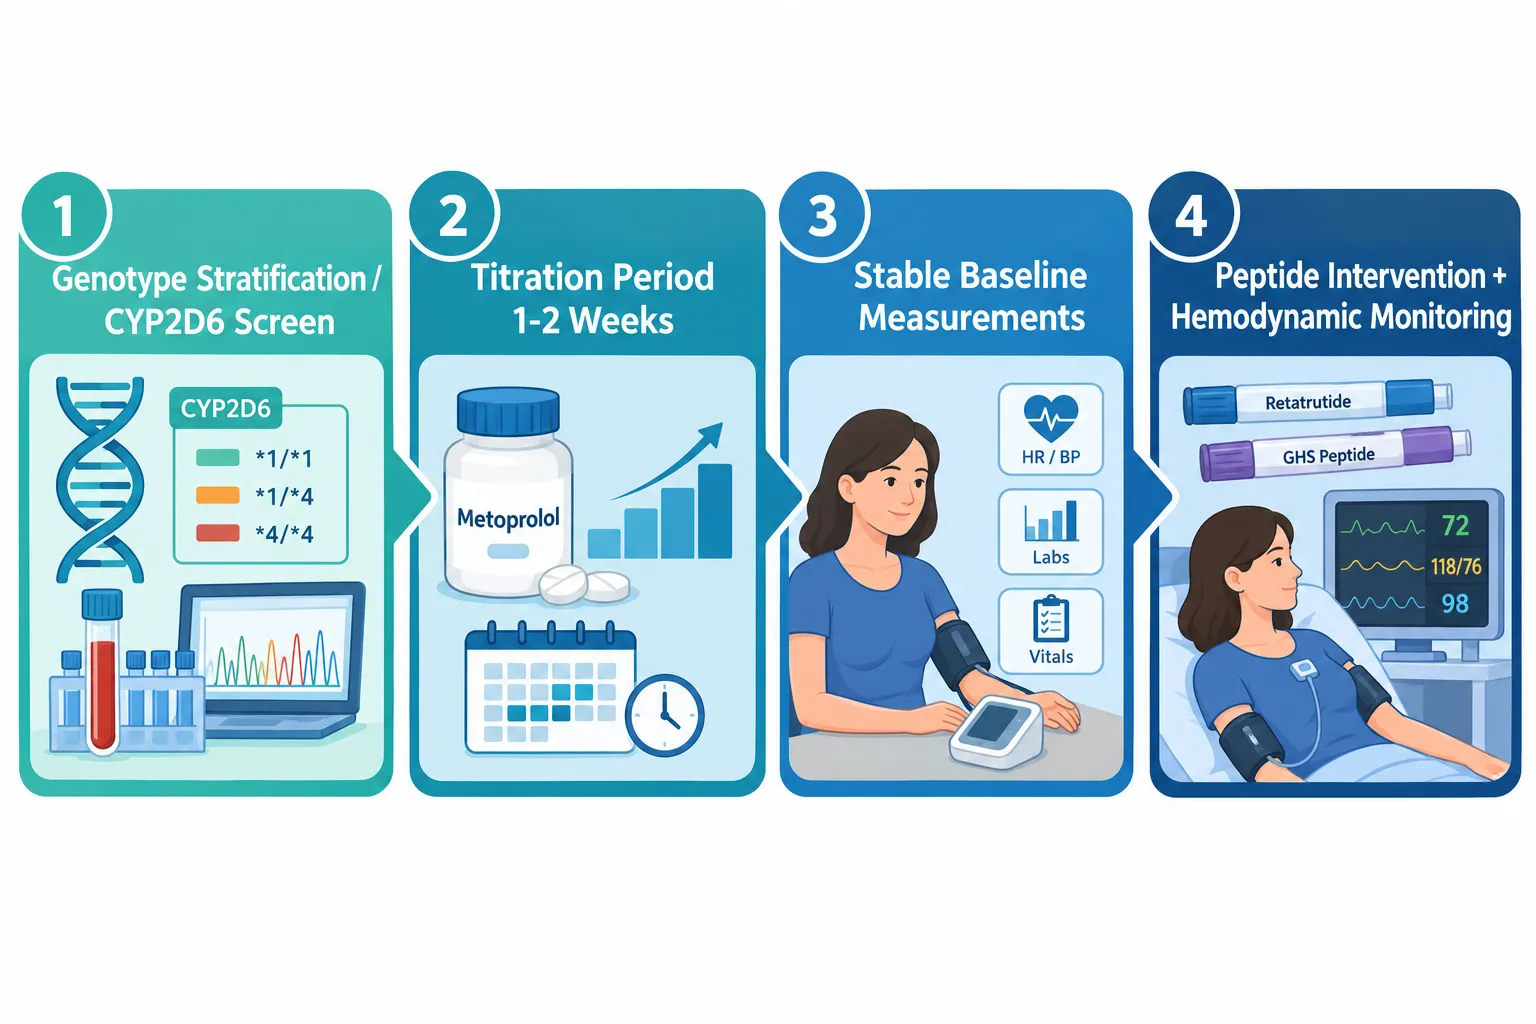
  • Metoprolol is a beta-1 selective blocker that reduces heart rate, systolic blood pressure, and cardiac output without raising peripheral resistance, making it a precise tool for quieting adrenergic noise.
  • Placebo-corrected reductions of 3-6 mmHg systolic and 5-7 beats per minute are typical, but inter-subject variability, partly driven by CYP2D6 metabolizer status, can be substantial.
  • Stable beta-blockade takes approximately one week of oral dosing; acute sympathetic blockade begins within 15 minutes of a single dose, so experimental timing must match the intended control strategy.
  • Metoprolol controls adrenergic tone but does not normalize all advanced structural or functional endpoints, meaning it cannot substitute for a peptide's mechanism of action.
  • Proper use requires genotype stratification, defined titration periods, and both resting and exercise-state baseline measurements before any peptide intervention begins.

Why Adrenergic Tone Confounds Peptide Cardiovascular Readouts

Why Adrenergic Tone Confounds Peptide Cardiovascular Readouts

Many peptides under active investigation, including metabolic agents like retatrutide and GLP-3 class compounds, exert direct or indirect effects on the cardiovascular system. Growth-hormone secretagogues, vasoactive intestinal peptides such as VIP-5, and mitochondria-targeted peptides like SS-31 all operate in physiological environments where sympathetic tone fluctuates with stress, fasting state, exercise, and even the act of venipuncture.

Catecholamines, adrenaline and noradrenaline, bind beta-1 receptors on the myocardium and raise heart rate, contractility, and blood pressure. If a peptide also raises or lowers these parameters through a separate pathway, the two signals overlap. Without a pharmacological anchor, investigators cannot cleanly attribute observed hemodynamic changes to the peptide alone.

This is the core problem metoprolol solves. By selectively blocking beta-1 adrenergic receptors, it attenuates catecholamine-driven cardiovascular fluctuations, providing a more stable hemodynamic backdrop against which peptide-specific effects can be measured.

"Metoprolol does not eliminate cardiovascular physiology, it standardizes the sympathetic component of it, allowing other signals to emerge more clearly."

Key adrenergic phenomena that metoprolol suppresses include:

  • Resting tachycardia driven by anxiety or metabolic stimulation
  • Exercise-induced heart rate overshoot
  • Isoproterenol-provoked tachycardia used in challenge protocols
  • Reflex orthostatic tachycardia during postural changes

Each of these can appear as a false-positive or false-negative peptide effect if left uncontrolled.


Practical Application of Metoprolol in Peptide Experiments: Controlling Heart Rate, Blood Pressure, and Adrenergic Confounding

Practical Application of Metoprolol in Peptide Experiments: Controlling Heart Rate, Blood Pressure, and Adrenergic Confoundin

Dose Range and Titration Timing

Oral metoprolol doses in hypertension and heart-rate control protocols typically range from 100 to 450 mg per day, titrated at weekly intervals. A single 50-80 mg dose begins reducing exercise systolic blood pressure within approximately 15 minutes, but stable, chronic antihypertensive effect requires roughly one week of consistent dosing.

This distinction matters enormously for experimental design:

Control Strategy Onset Use Case
Acute single dose ~15 minutes Rapid sympathetic stabilization before a one-time challenge
Chronic titration (1 week+) ~7 days Stable baseline for multi-day peptide dosing protocols

For most mechanistic peptide trials, including those assessing cardiometabolic polypeptide models, chronic titration is preferred because it removes day-to-day adrenergic variability rather than just blunting a single measurement window.

Accounting for CYP2D6 Metabolizer Status

A critical and often overlooked source of confounding within the metoprolol control arm itself is pharmacogenomic variability. Poor CYP2D6 metabolizers accumulate significantly higher serum metoprolol concentrations, producing greater and more consistent reductions in heart rate, diastolic blood pressure, and mean arterial pressure compared to extensive metabolizers at the same dose.

If subjects are not stratified by CYP2D6 status, the beta-blockade "control" becomes a new source of variance. Practical steps include:

  1. Pre-screen subjects for CYP2D6 poor-metabolizer status
  2. Stratify randomization accordingly
  3. Monitor resting and exercise heart rate at baseline, after titration, and at each peptide dosing interval

Baseline Measurement Protocol

Baseline measurements must capture both resting and dynamic (exercise) cardiovascular state. Metoprolol reduces heart rate and systolic blood pressure at rest and during exercise, these are separate physiological states that peptides may affect differently. Recording only resting values misses exercise-induced adrenergic surges that some metabolic peptides, including growth-hormone secretagogues, actively modulate.


Interpretation Cautions: What Metoprolol Cannot Control

Interpretation Cautions: What Metoprolol Cannot Control

Metoprolol's selectivity is both its strength and its limitation. As a beta-1 selective agent, it does not block alpha-1 receptors or beta-2 receptors. Contrast this with carvedilol, a non-selective blocker with additional alpha-1 antagonism, which suppresses adrenergic activity through a broader mechanism. The choice between these agents changes the nature of residual adrenergic confounding, a distinction highlighted in comparative cardiovascular outcome protocols.

For researchers working with peptides in endocrine pharmacology contexts or GH-analogue peptides, additional considerations include:

  • Structural endpoints: Beta-blockade does not normalize advanced structural or functional cardiac endpoints. Recent data from myosin inhibitor trials confirm that metoprolol, despite controlling heart rate and blood pressure, did not replicate the specific functional improvements seen with next-generation myosin-targeted agents. Peptide trials must not assume that hemodynamic control equals functional equivalence.
  • Peripheral vascular effects: Metoprolol does not increase peripheral resistance, but it also does not reduce it. Peptides with vasodilatory mechanisms, such as VIP-class agents, will still show vascular effects that metoprolol leaves unmasked.
  • Metabolic interactions: Some metabolic peptides affect insulin sensitivity and glucose metabolism in ways that secondarily alter sympathetic tone. Metoprolol blunts the cardiovascular expression of this interaction but does not eliminate the underlying metabolic signal.

Conclusion

Metoprolol in peptide experiments for controlling heart rate, blood pressure, and adrenergic confounding represents one of the most practical pharmacological tools available to cardiovascular researchers in 2026. Its beta-1 selectivity, well-characterized dose-response profile, and rapid onset make it well suited for both acute challenge designs and chronic multi-week protocols.
Actionable next steps for research teams:

  • Determine whether acute or chronic beta-blockade better matches the experimental timeline before dosing begins
  • Screen and stratify subjects by CYP2D6 metabolizer status to prevent pharmacogenomic variance from contaminating the control arm
  • Collect resting and exercise-state hemodynamic baselines after titration, not before
  • Document which adrenergic phenomena remain unblocked (alpha-1, beta-2 pathways) and account for them in statistical models
  • Avoid interpreting stable hemodynamic readings as evidence that all cardiovascular endpoints are normalized, structural and functional parameters require independent assessment

Selecting high-purity, well-characterized peptides from a reliable peptide supplier is equally important; compound variability introduces its own confounding that no pharmacological control can fully correct.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/metoprolol-in-peptide-experiments-controlling-heart-rate-blood-pressure-and-adre.webp 672 1008 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-06 13:10:002026-10-06 13:10:00Metoprolol in Peptide Experiments: Controlling Heart Rate, Blood Pressure, and Adrenergic Confounding
What Is a GLP-1 Pill? Comparing Oral Delivery Concepts With Research-Use GLP-3 Retatrutide Models

What Is a GLP-1 Pill? Comparing Oral Delivery Concepts With Research-Use GLP-3 Retatrutide Models

October 6, 2026/0 Comments/in Uncategorized/by

An oral tablet approved for weight loss sounds like a major leap forward, and in 2026, that leap has officially happened. But the question researchers, clinicians, and informed consumers are now asking is whether a GLP-1 pill and an injectable triple agonist like retatrutide are even playing the same game. Understanding what is a GLP-1 pill, comparing oral delivery concepts with research-use GLP-3 retatrutide models, reveals a surprisingly wide gap between two approaches that share a name but differ sharply in mechanism, scope, and research application.

Key Takeaways

  • GLP-1 pills are oral small-molecule drugs that activate the GLP-1 receptor; two were approved in the U.S. in 2026 for obesity.
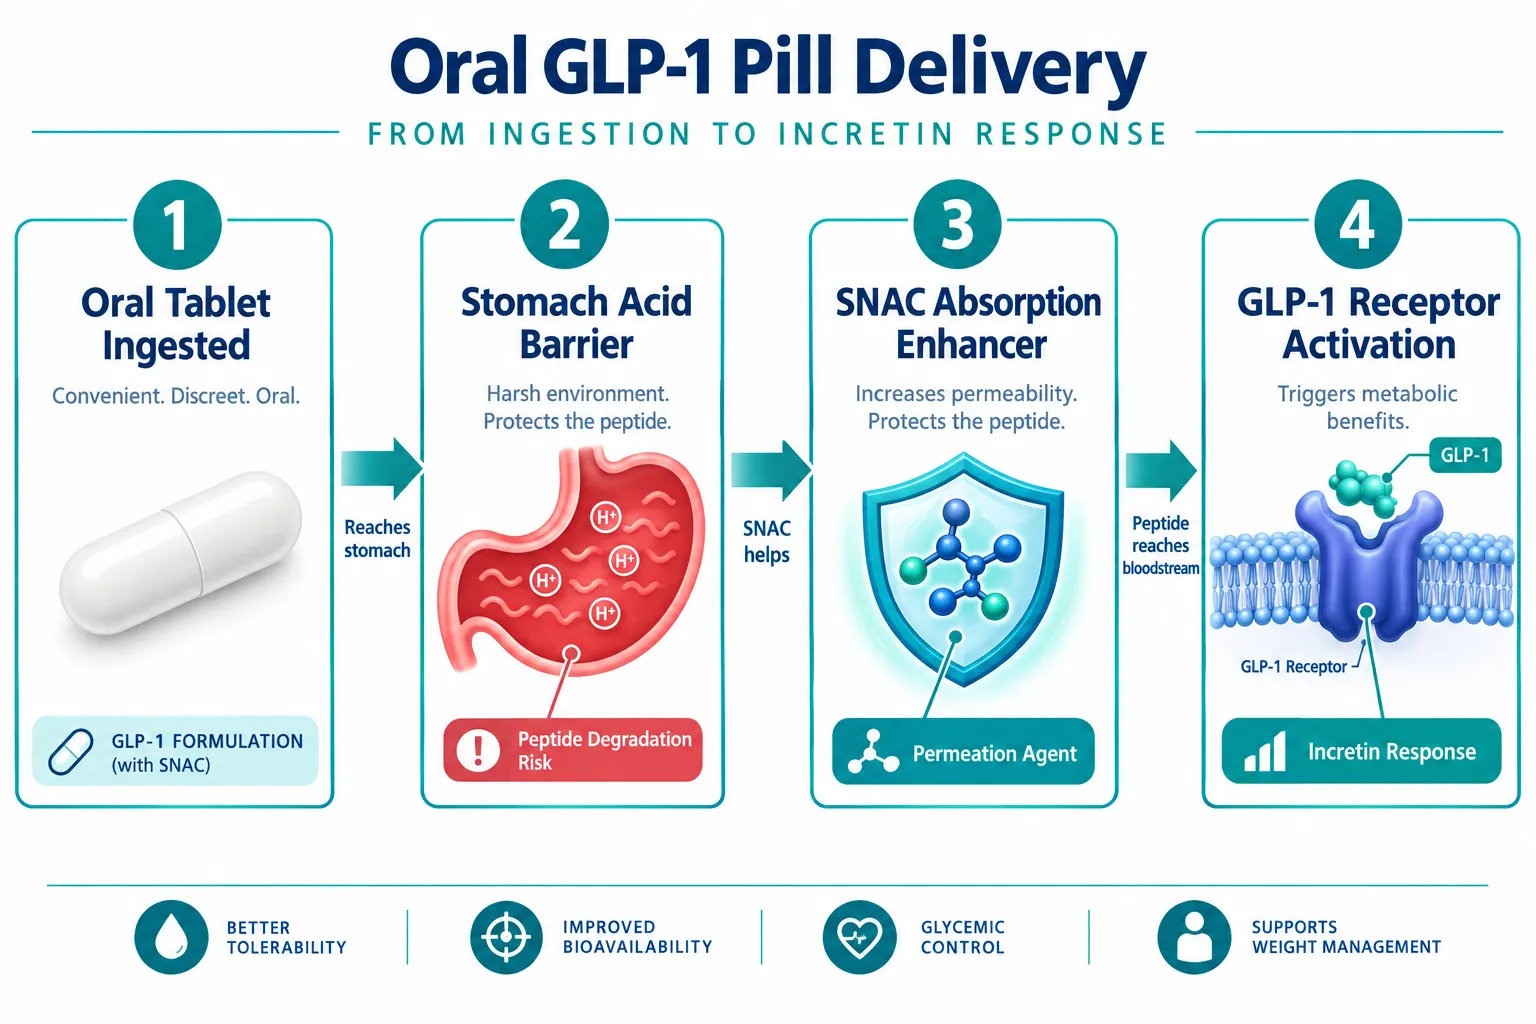
  • Oral delivery faces significant biochemical barriers, requiring absorption enhancers to survive the digestive tract.
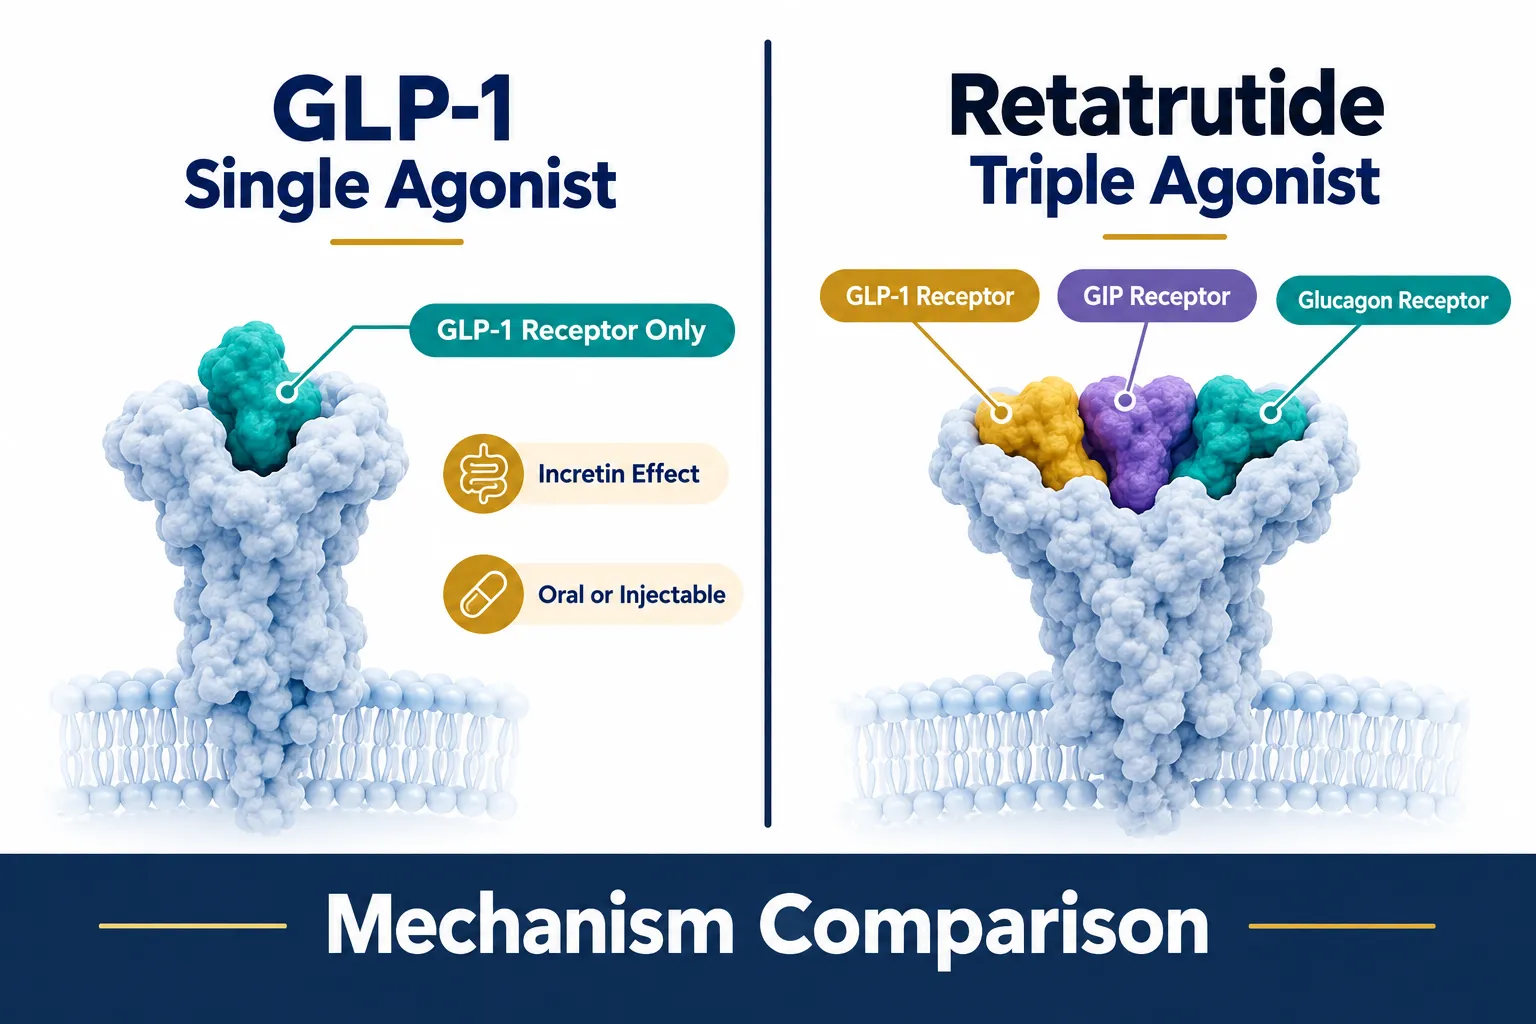
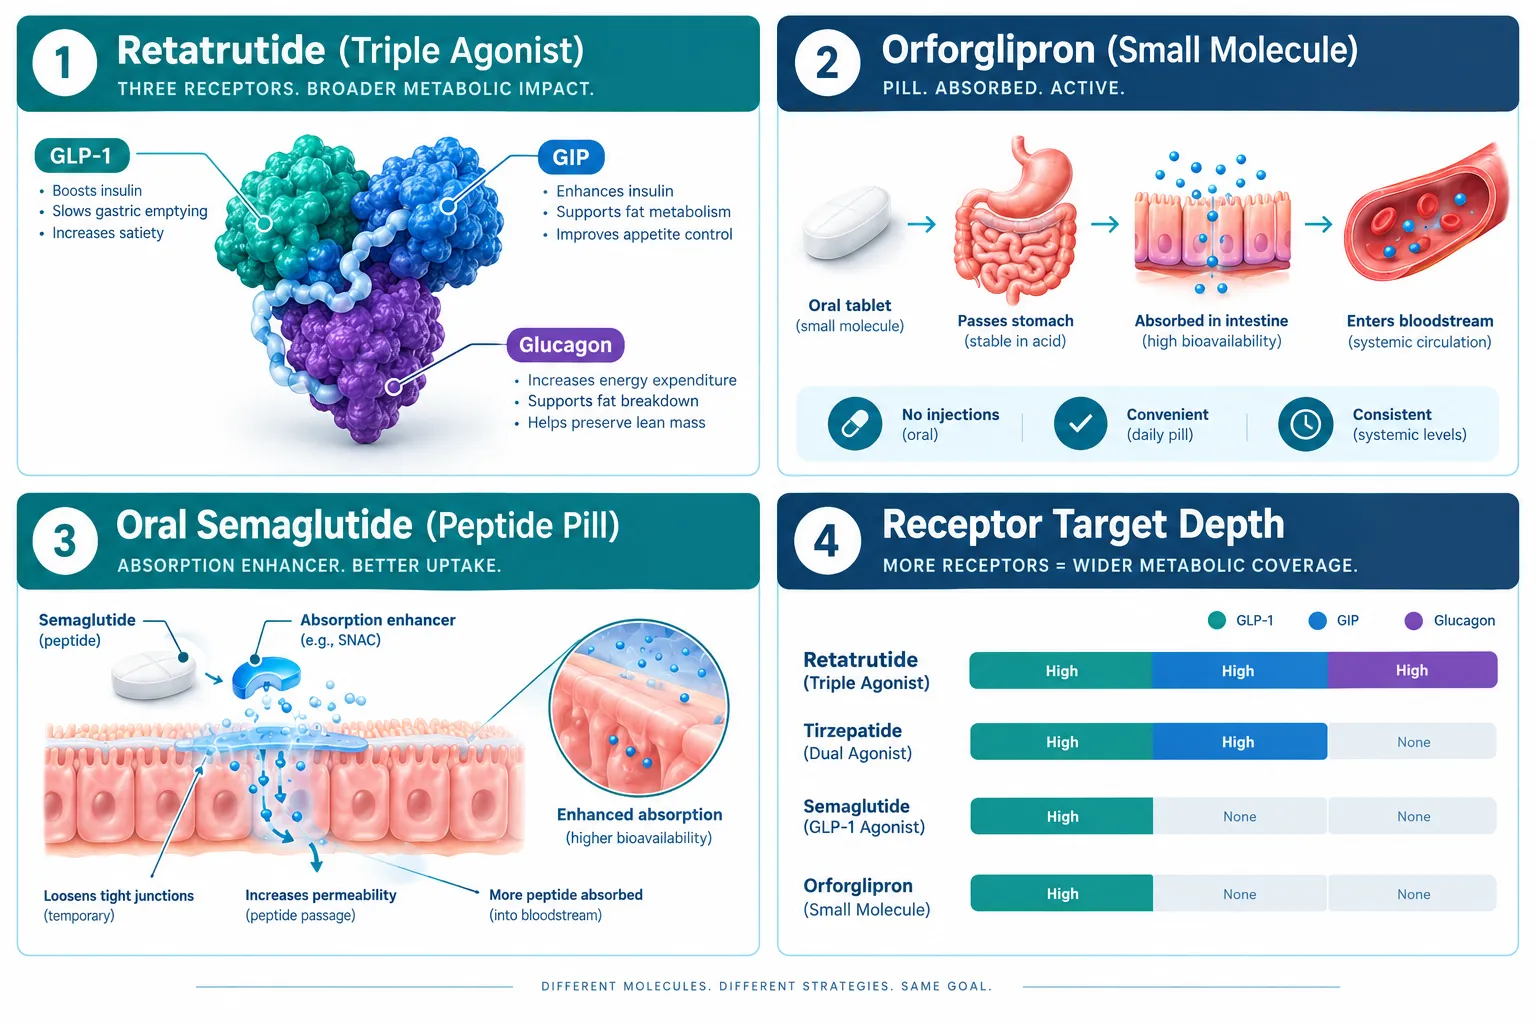
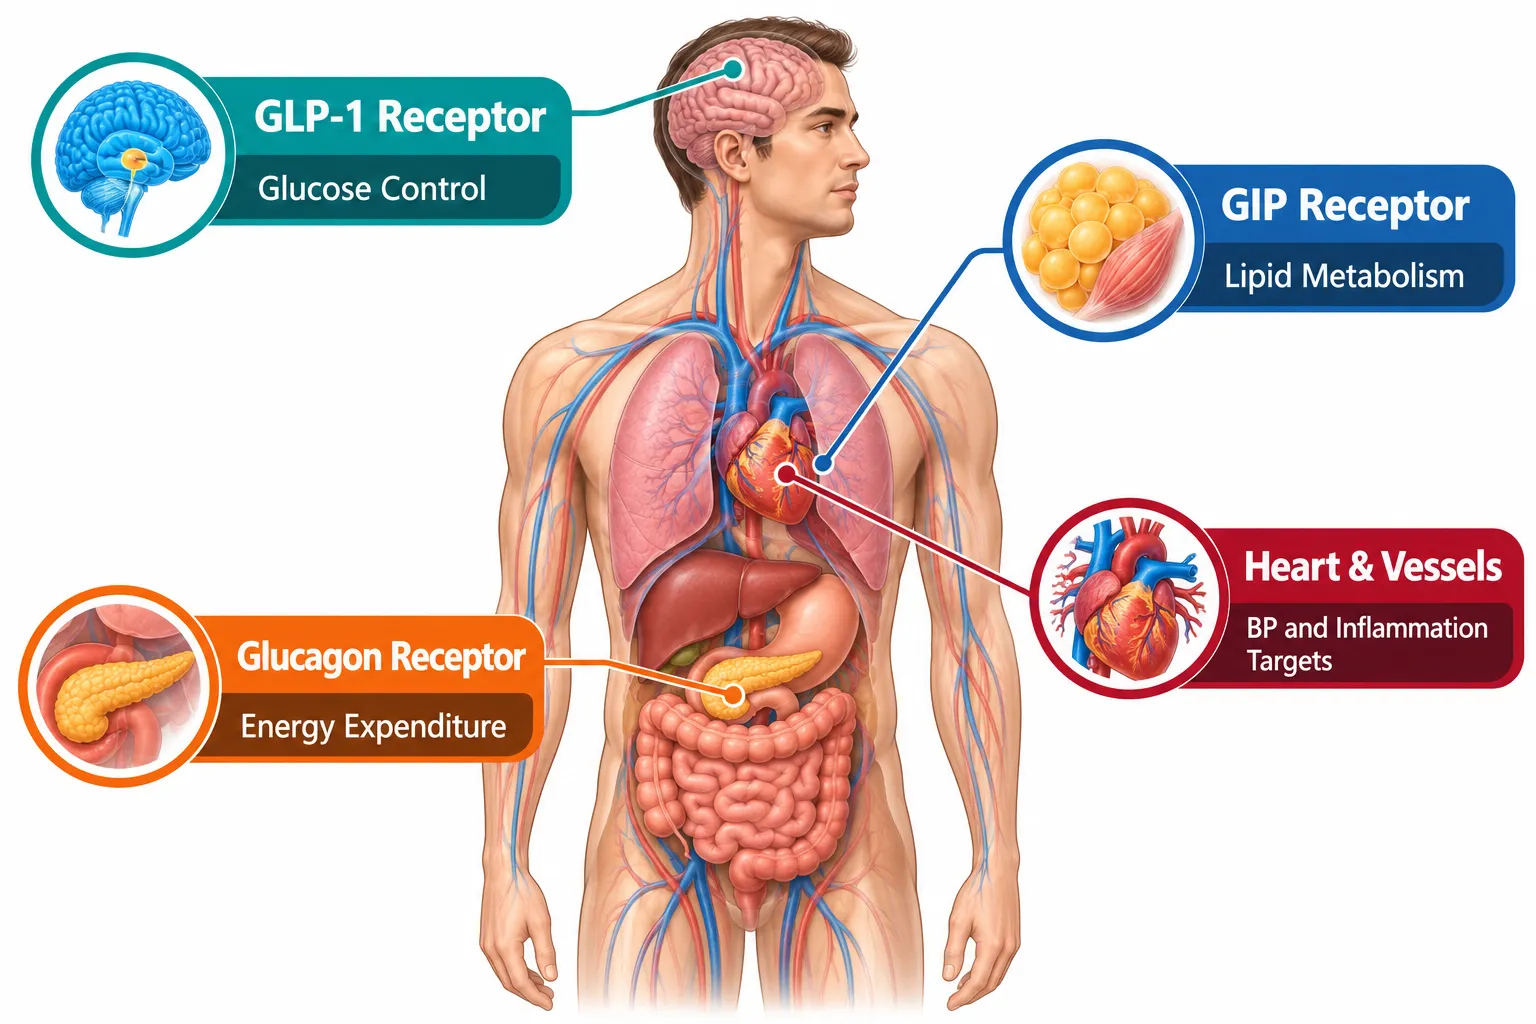
  • Retatrutide is a triple agonist targeting GLP-1, GIP, and glucagon receptors simultaneously, making it mechanistically distinct from any single-agonist pill.
  • The TRIUMPH Phase 3 program is testing retatrutide across obesity, type 2 diabetes, cardiovascular disease, and osteoarthritis populations.
  • An oral GLP-1 pill is not a substitute for a triple-agonist injectable in research or clinical contexts.

How a GLP-1 Pill Actually Works

The glucagon-like peptide-1 (GLP-1) receptor is a well-validated target for metabolic disease. When activated, it slows gastric emptying, reduces appetite, and stimulates insulin secretion in a glucose-dependent manner. Injectable GLP-1 receptor agonists have dominated this space for years, but 2026 marks a turning point for oral delivery.

How a GLP-1 Pill Actually Works

Two oral GLP-1 agents reached U.S. approval in 2026. Eli Lilly's orforglipron (brand name Foundayo) became the first approved oral-only GLP-1 pill specifically indicated for obesity. Novo Nordisk's semaglutide pill, already available for type 2 diabetes, also received approval for weight loss in adults in both the U.S. and EU markets. These are not peptide-based tablets, they are small-molecule non-peptide compounds or peptide formulations engineered to survive the hostile environment of the gastrointestinal tract.
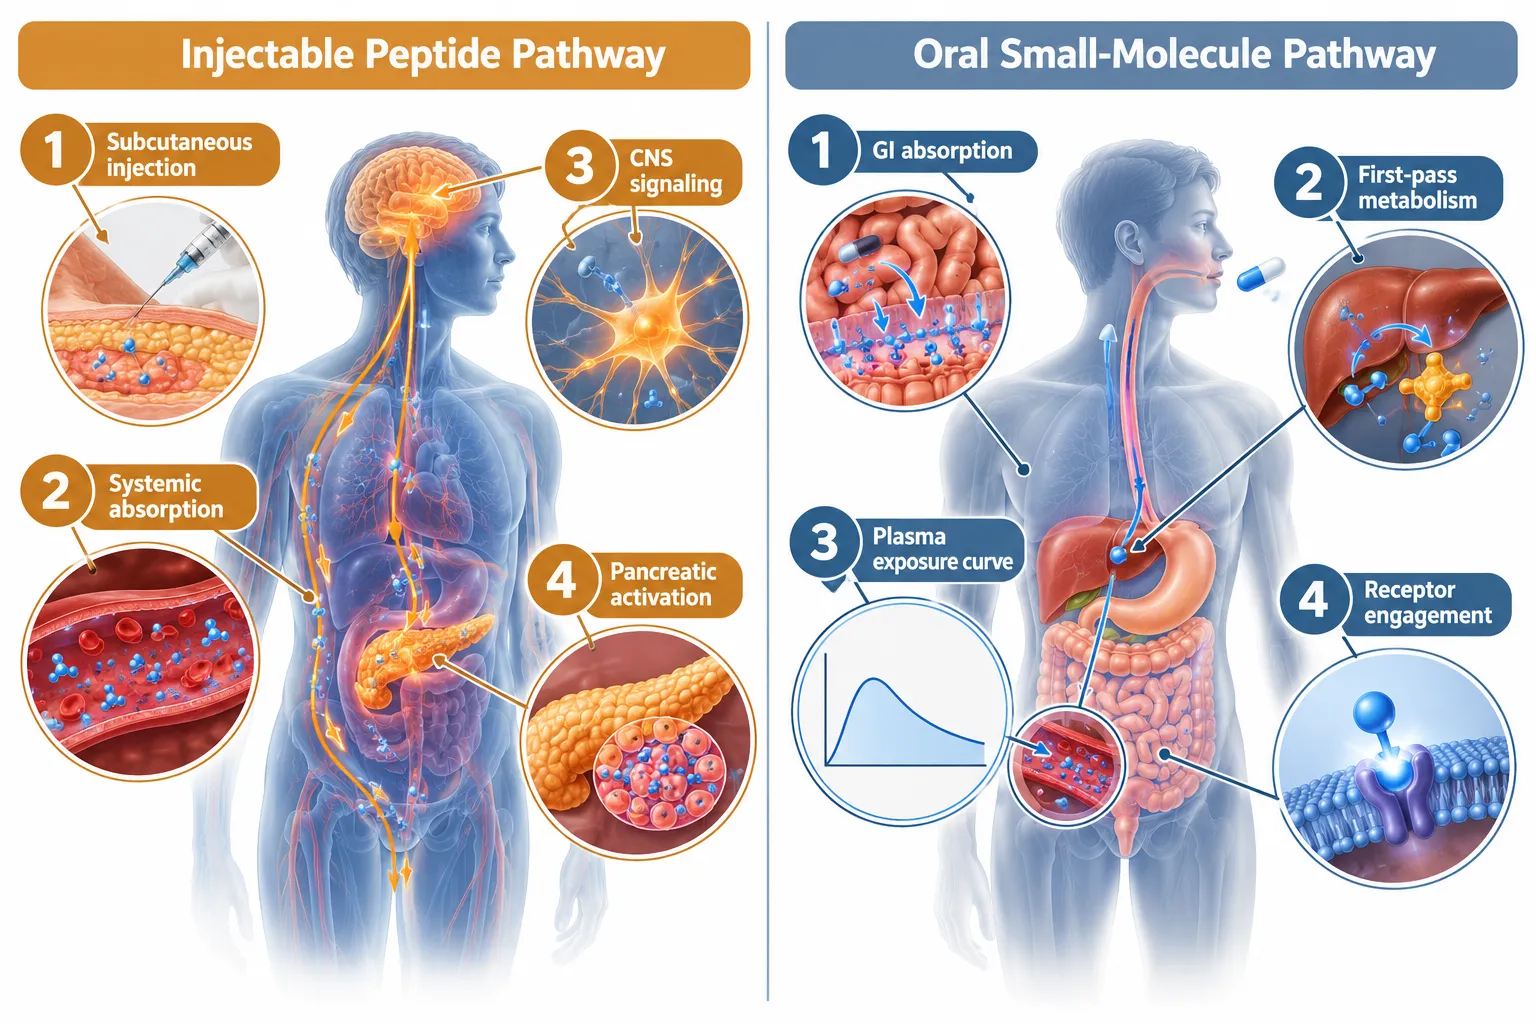
The core challenge with oral peptide delivery is enzymatic degradation. Stomach acid and proteases break down peptide chains before they can reach systemic circulation. Semaglutide tablets overcome this using a co-formulation with sodium N-(8-[2-hydroxybenzoyl] amino) caprylate (SNAC), an absorption enhancer that temporarily raises local gastric pH and facilitates mucosal permeation. Orforglipron sidesteps this problem entirely by being a small-molecule compound that does not require an absorption enhancer.

Key oral delivery constraints include:

  • Low bioavailability compared to subcutaneous injection
  • Strict fasting requirements before dosing (for semaglutide tablets)
  • Narrower therapeutic window due to absorption variability
  • No flexibility in dose titration beyond what the formulation allows

For those exploring the broader landscape of peptides used in metabolic and weight-loss research, what is the strongest peptide for weight loss provides useful context on how different compound classes compare.


Retatrutide: The Triple-Agonist Model That Changes the Comparison

Calling retatrutide a "GLP-3" is a colloquial shorthand that has gained traction in research communities, but it is worth clarifying what that label actually means. Retatrutide is a single peptide molecule that simultaneously activates three receptors: GLP-1, glucose-dependent insulinotropic polypeptide (GIP), and glucagon. This triple agonism is why it is sometimes distinguished from standard GLP-1 agents with the informal "GLP-3" designation.

Retatrutide: The Triple-Agonist Model That Changes the Comparison

This mechanistic distinction is critical when comparing oral delivery concepts with research-use GLP-3 retatrutide models. A GLP-1 pill activates one receptor pathway. Retatrutide activates three, producing overlapping and synergistic metabolic effects that include:

  • GLP-1 activity: appetite suppression, insulin secretion, slowed gastric emptying
  • GIP activity: enhanced insulin response, potential adipose tissue effects
  • Glucagon activity: increased energy expenditure, hepatic fat mobilization

Phase 2 data for retatrutide showed weight reductions exceeding 24% of body weight at the highest dose over 48 weeks, a benchmark that no single GLP-1 agonist, oral or injectable, has matched in head-to-head comparisons at similar timepoints.

For more background on how retatrutide fits within the GLP-1 research landscape, see the GLP-1 retatrutide overview. Researchers seeking access to standardized research-grade material can also review GLP3 Reta 10mg and GLP-3 Reta 30mg for sale options for preclinical study use.


The TRIUMPH Phase 3 Program and What It Tells Researchers

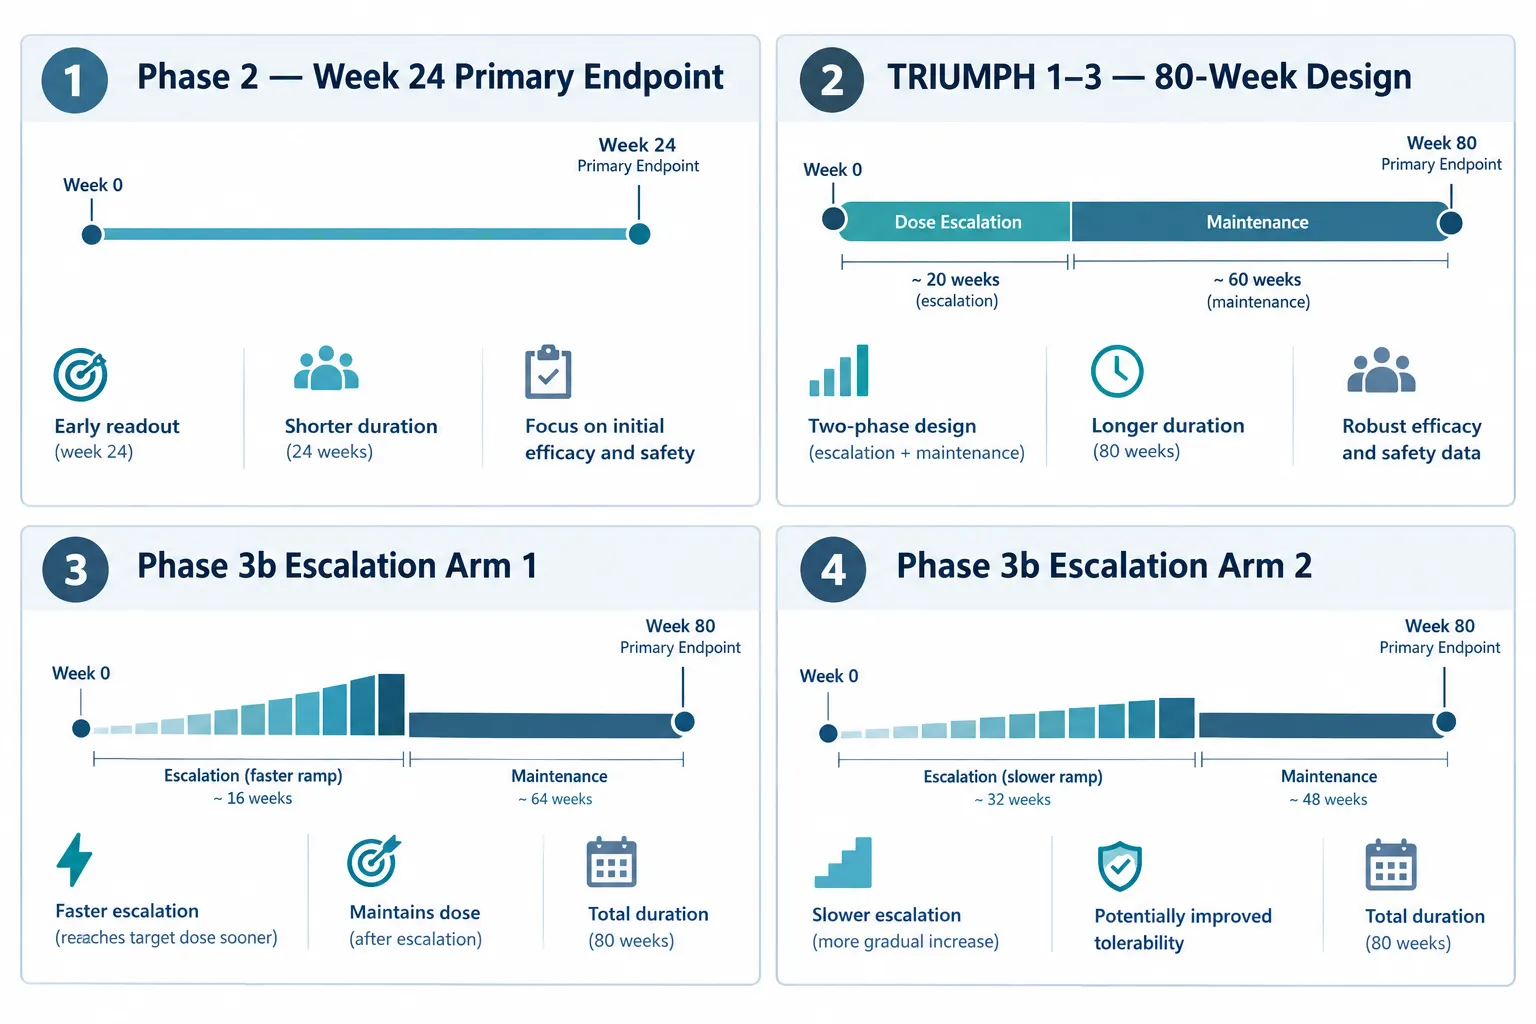
The most comprehensive data set currently being generated on retatrutide comes from the TRIUMPH Phase 3 program, a suite of large-scale trials running across 2025 and 2026. These trials are designed to test retatrutide across multiple disease populations, not just general obesity.

The TRIUMPH Phase 3 Program and What It Tells Researchers

Trial Population Duration Primary Focus
TRIUMPH-1 Obesity or overweight (no T2D) 80 weeks Weight loss efficacy and safety
TRIUMPH-2 Type 2 diabetes + obesity 80 weeks Weight loss and glycemic control
TRIUMPH-3 Severe obesity + CVD (BMI 35+) 80 weeks Cardiovascular and weight outcomes
TRIUMPH-4 Obesity + knee osteoarthritis 68 weeks Weight loss and knee pain reduction

Topline 2026 results from the TRIUMPH program and the parallel TRANSCEND-T2D-1 diabetes trial have shown meaningful reductions in A1C, body weight, and comorbidity burden. These outcomes extend well beyond what a single-receptor oral pill is designed to achieve.

For researchers tracking the evolution of this compound, the retatrutide clinical trials resource aggregates ongoing study data in one place.

"Retatrutide's triple-receptor mechanism produces metabolic effects that are qualitatively different from those of any approved oral GLP-1 agent, not just quantitatively larger."

It is also worth noting that retatrutide remains an injectable peptide in all clinical and research settings. There is no oral formulation in development at this stage, which means the oral vs. injectable distinction is not merely a delivery preference, it reflects a fundamental difference in what each compound can do.

For researchers interested in combinatorial peptide approaches in metabolic contexts, the article on combining Tesamorelin with CDC Ipamorelin offers relevant mechanistic parallels.


Conclusion

Understanding what is a GLP-1 pill, comparing oral delivery concepts with research-use GLP-3 retatrutide models, makes one conclusion unavoidable: these are fundamentally different tools. The 2026 approvals of orforglipron and oral semaglutide for obesity represent a genuine advance in patient convenience and access. However, their single-receptor mechanism, oral bioavailability constraints, and narrower metabolic scope place them in a separate category from retatrutide's triple-agonist profile.

Actionable next steps for researchers and informed readers:

  1. Review the TRIUMPH trial registry entries to follow Phase 3 retatrutide data as it becomes available.
  2. Distinguish between oral GLP-1 agents (small-molecule or SNAC-formulated peptide) and injectable triple agonists before drawing efficacy comparisons.
  3. If evaluating retatrutide for preclinical research, source only verified, tested-grade material and consult current retatrutide clinical trial literature before designing protocols.
  4. Do not assume that oral availability implies equivalent biological activity, receptor breadth, bioavailability, and dosing pharmacokinetics all differ substantially between compound classes.

The GLP-1 pill is a meaningful milestone. Retatrutide is a different kind of milestone entirely.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/what-is-a-glp-1-pill-comparing-oral-delivery-concepts-with-research-use-glp-3-re.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-06 13:05:492026-10-06 13:05:49What Is a GLP-1 Pill? Comparing Oral Delivery Concepts With Research-Use GLP-3 Retatrutide Models
GLP-3 Retatrutide vs GLP-2-T: Choosing Metabolic, Intestinal, and Organoid Readouts for Comparative Research

GLP-3 Retatrutide vs GLP-2-T: Choosing Metabolic, Intestinal, and Organoid Readouts for Comparative Research

October 5, 2026/0 Comments/in Uncategorized/by

Retatrutide produced mean weight reductions exceeding 24% over 48 weeks in phase 2 trials, a figure that no single-receptor incretin therapy had previously achieved. That single data point signals why researchers face a genuine decision problem when designing comparative studies: retatrutide operates through a fundamentally different biological model than GLP-2-type agents, and conflating their readout frameworks produces unreliable conclusions.

This article builds a practical decision framework for GLP-3 Retatrutide vs GLP-2-T: Choosing Metabolic, Intestinal, and Organoid Readouts for Comparative Research. The goal is to separate retatrutide's multi-receptor systemic model from GLP-2-T's intestinal-repair context, then map each to the endpoints, assay systems, and interpretation boundaries that fit them best.

Key Takeaways

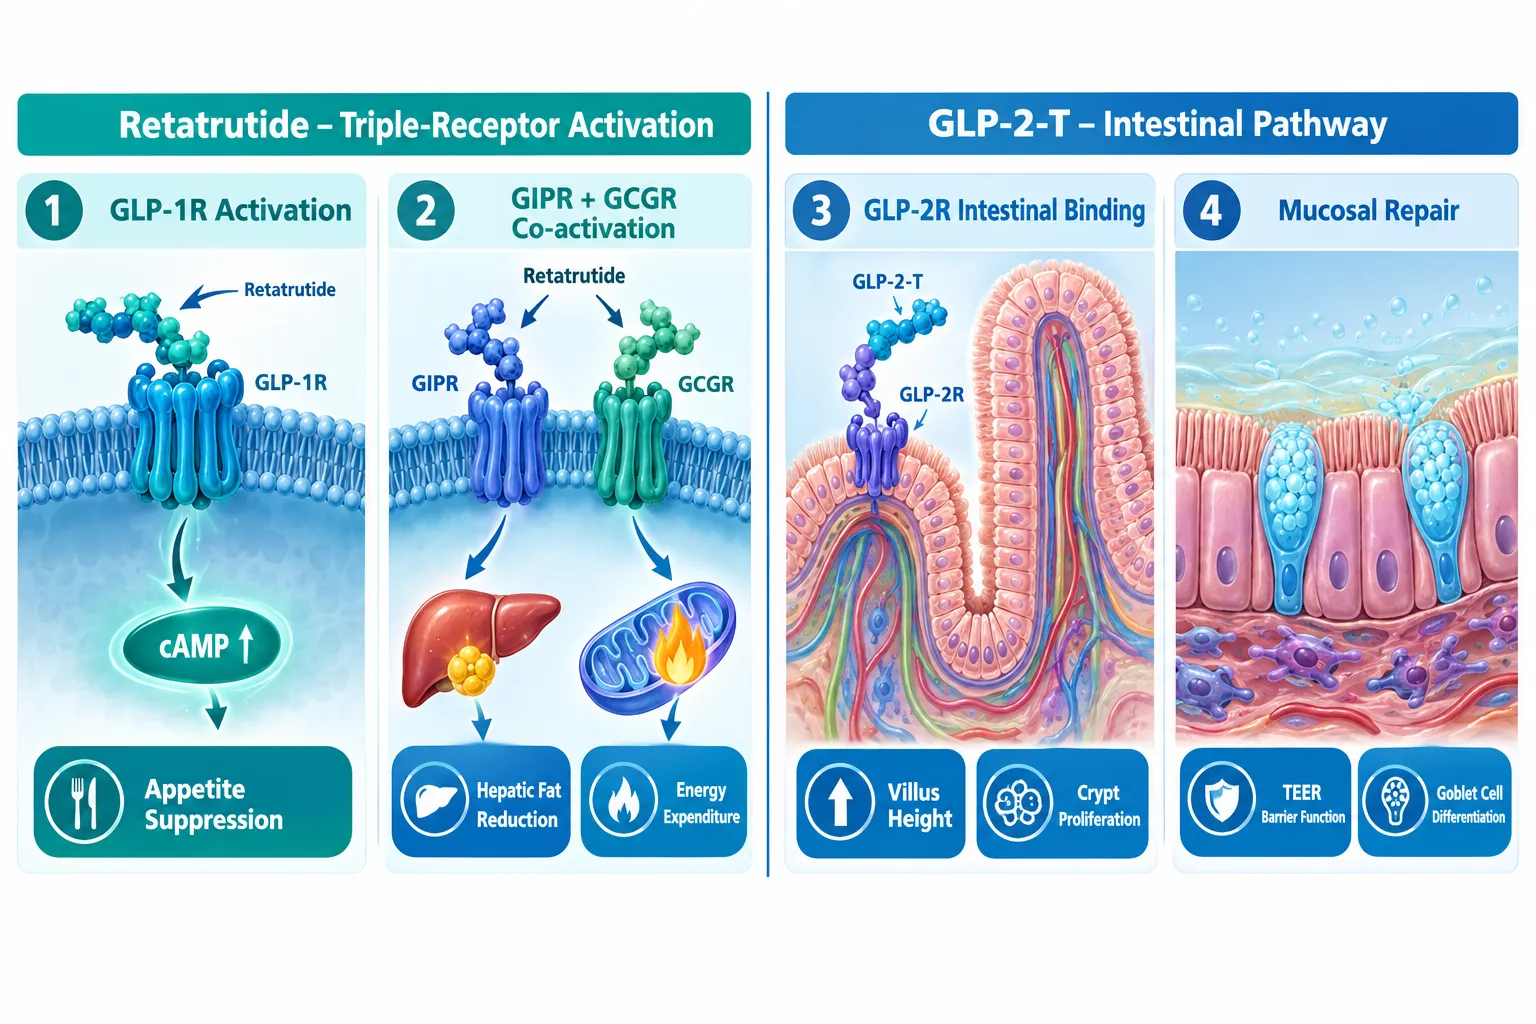
  • Retatrutide simultaneously activates GLP-1R, GIPR, and GCGR, making systemic metabolic endpoints the primary readout domain.
  • GLP-2-type agents act principally on intestinal GLP-2 receptors; their readouts center on mucosal structure, barrier function, and organoid proliferation.
  • Mixing readout frameworks across these two agent classes introduces mechanistic confounds that weaken comparative data.
  • Receptor expression confirmation is a non-negotiable first step before running any parallel assay.
  • Organoid platforms can serve both arms only when receptor expression and endpoint domains are kept strictly separate.

Understanding the Mechanistic Divide

Understanding the Mechanistic Divide

The core challenge in GLP-3 Retatrutide vs GLP-2-T comparative research is that these two agent classes do not share a primary tissue target. Retatrutide (LY3437943) is the first GLP-1/GIP/glucagon triple agonist to complete phase 2 trials in both obesity and type 2 diabetes. It engages three distinct receptors, GLP-1R, GIPR, and GCGR, through a single peptide conjugated to a fatty diacid moiety. The downstream effects span appetite suppression, hepatic fat reduction, and systemic energy expenditure.

GLP-2-type agents (GLP-2-T), by contrast, bind the GLP-2 receptor expressed predominantly on intestinal subepithelial myofibroblasts and enteroendocrine cells. Their documented effects are gut-trophic: increased villus height, crypt cell proliferation, improved mucosal barrier integrity, and enhanced nutrient absorption. These are the readouts that define clinical use cases such as short bowel syndrome and intestinal failure.

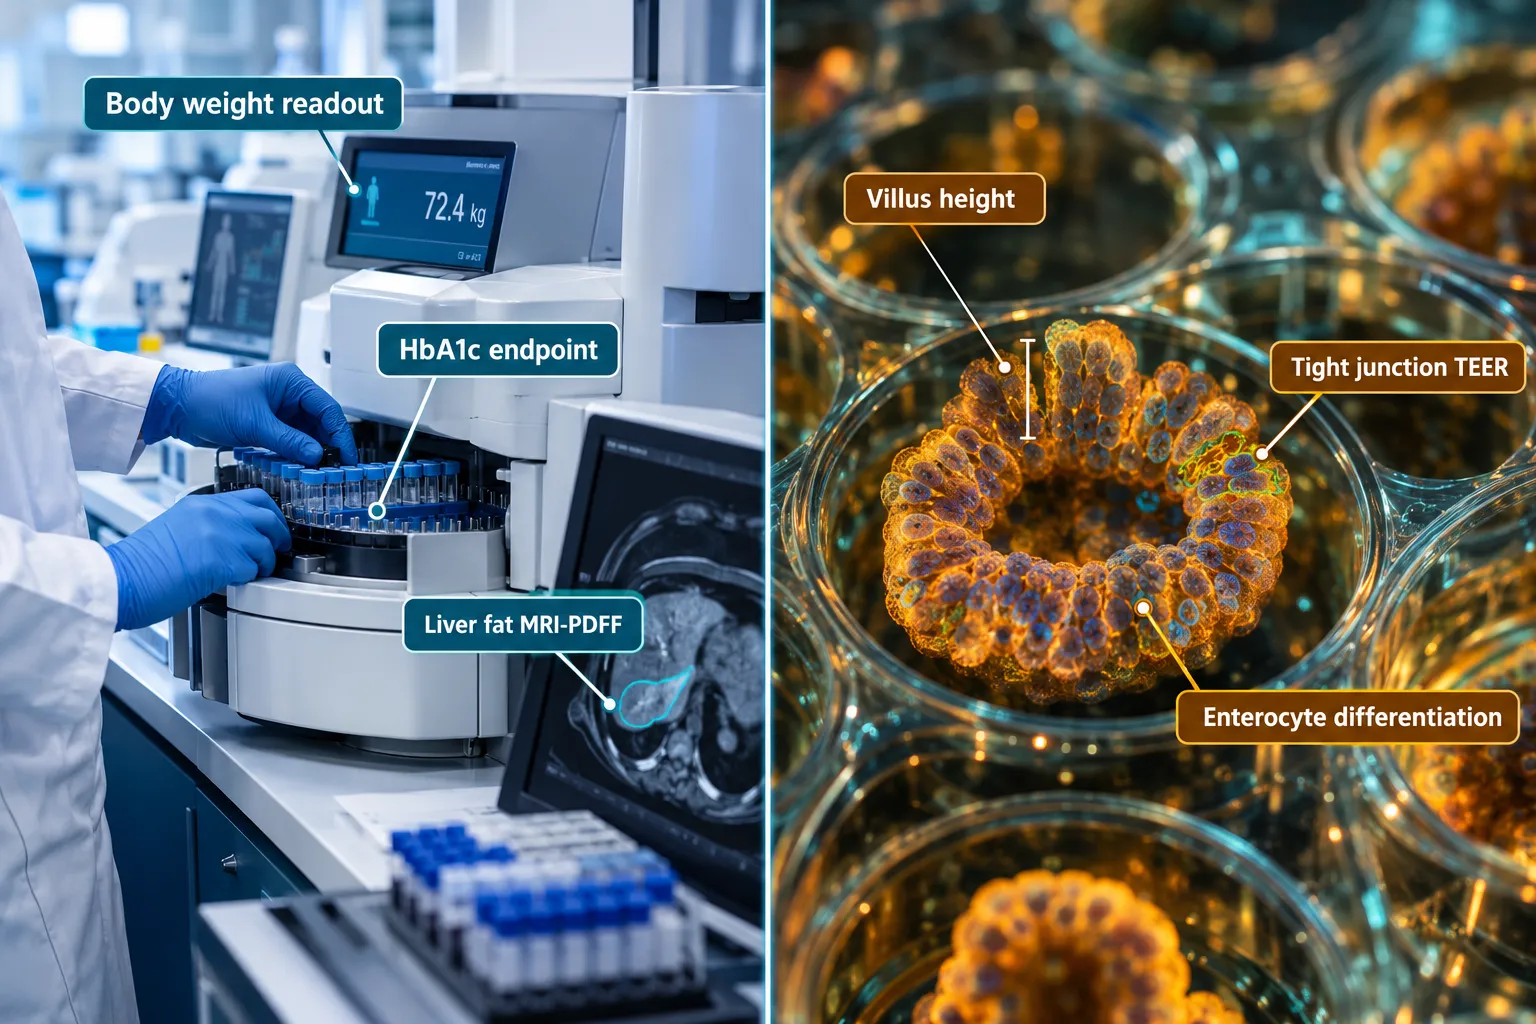
The mechanistic divide is not a matter of degree, it is a matter of tissue domain. Retatrutide's phase 2 MASLD trial reinforced this by demonstrating meaningful reductions in liver fat measured by MRI-proton density fat fraction (MRI-PDFF), alongside improvements in hepatic enzymes and non-invasive fibrosis markers. None of those endpoints are relevant to GLP-2-T's primary mechanism.

"Choosing the wrong readout domain does not just weaken a study, it actively misrepresents the biology of both agents."

Researchers looking to source well-characterized material for this work can review options through the Buy Retatrutide Peptide page or explore the broader GLP-3 Retatrutide buy online USA resource for purity and specification details.


Building the Readout Decision Framework

Building the Readout Decision Framework

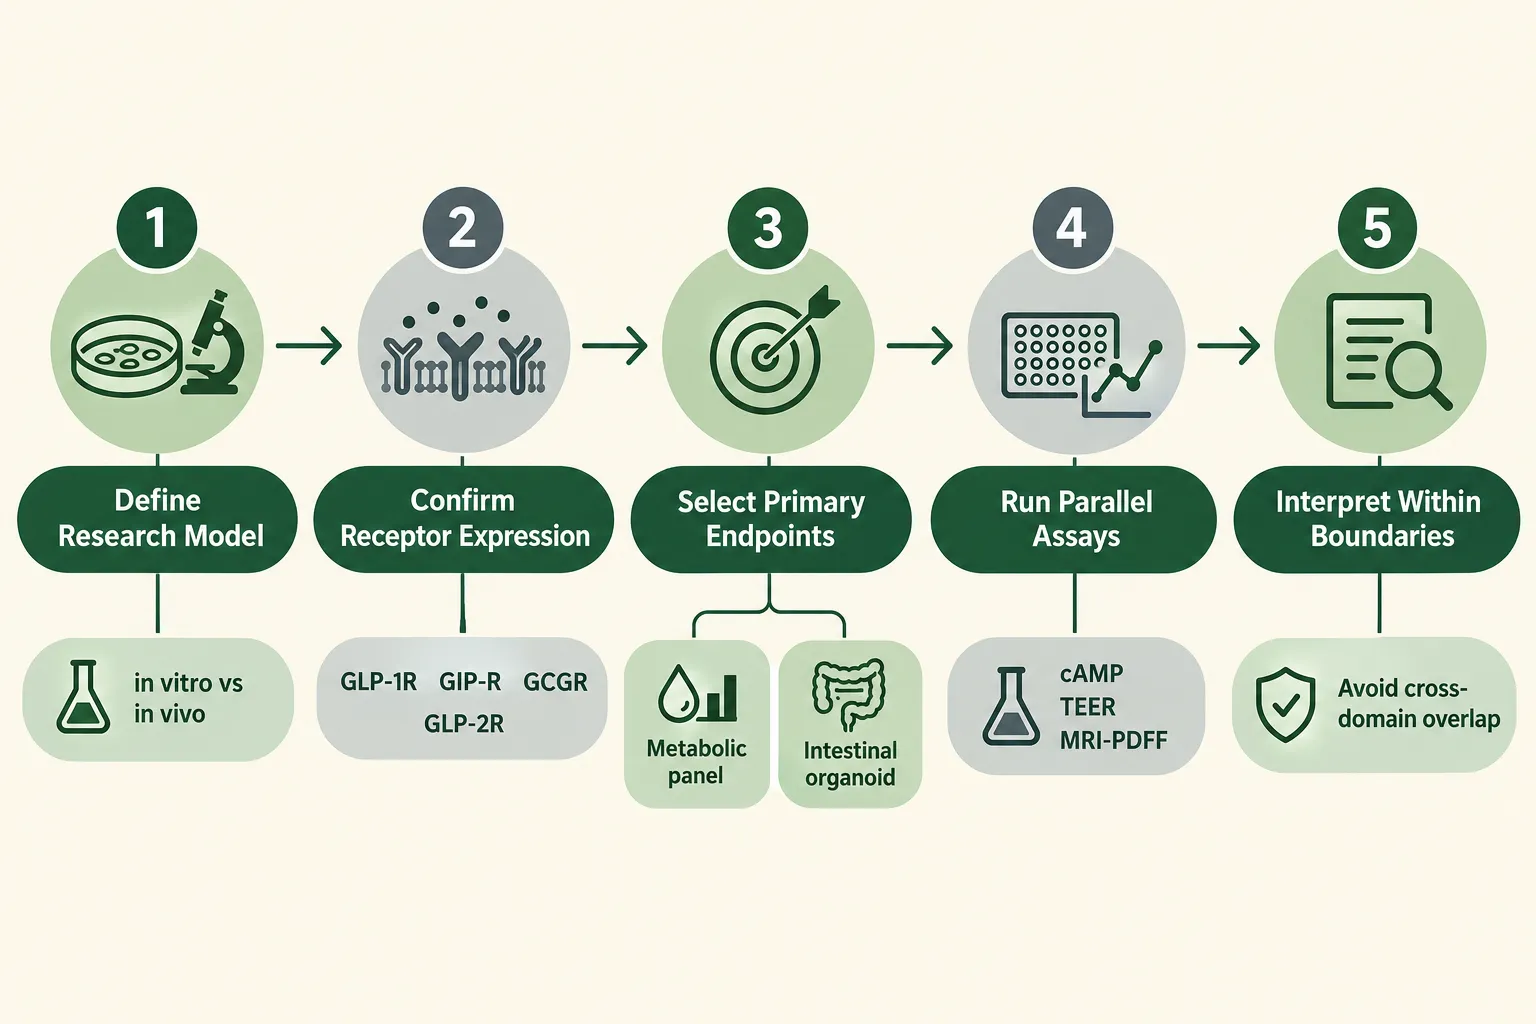
A structured five-step decision process reduces the risk of endpoint misalignment when designing GLP-3 Retatrutide vs GLP-2-T: Choosing Metabolic, Intestinal, and Organoid Readouts for Comparative Research studies.

Step 1: Define the Research Model

Choose whether the study is in vitro, ex vivo, or in vivo before selecting any endpoint. Retatrutide's receptor profile requires models that co-express GLP-1R, GIPR, and GCGR, hepatocyte lines, adipocyte cultures, pancreatic islet preparations, or diet-induced obesity rodent models. GLP-2-T studies require intestinal epithelial models: primary organoids derived from small intestinal crypts, Caco-2 monolayers, or murine intestinal preparations.

Step 2: Confirm Receptor Expression

This step is non-negotiable. Structural work published in 2024 clarified that retatrutide engages all three receptors with defined binding modes and biased signaling profiles. Before running any assay, confirm receptor expression using qPCR or immunofluorescence. A GLP-2-T study run in a model lacking adequate GLP-2R expression produces noise, not data.

Step 3: Select Primary Endpoints by Agent Class

Endpoint Category Retatrutide (GLP-3-like) GLP-2-T
Primary metabolic Body weight, HbA1c, fasting glucose, lipids Not applicable as primary
Hepatic MRI-PDFF, ALT/AST, fibrosis markers Minimal relevance
Intestinal structure Secondary / safety monitoring Villus height, crypt depth, cell proliferation
Barrier function GI tolerability (adverse event tracking) TEER, tight junction proteins (ZO-1, claudin)
Receptor signaling cAMP, beta-arrestin, downstream kinase activity cAMP via GLP-2R, PI3K/Akt pathway
Organoid readouts Hepatic organoid fat accumulation, glucose uptake Enterocyte and goblet cell differentiation, proliferation index

Step 4: Run Parallel Assays With Separated Domains

Phase 2 safety data for retatrutide identified dose-dependent gastrointestinal adverse events, nausea and diarrhea, alongside signals for lean mass changes and modest heart rate increases. These findings make body composition and heart rate monitoring essential safety-related readouts for the retatrutide arm. They are not shared endpoints with GLP-2-T, which does not produce systemic energy expenditure effects. Running parallel assays only works when each arm's endpoint set remains internally consistent.

Step 5: Interpret Within Defined Boundaries

No published 2025-2026 literature presents a formal GLP-3 vs GLP-2-T comparative schema. The framework described here is constructed from separate evidence streams. Researchers must therefore resist interpreting GLP-2-T intestinal organoid results as informative about systemic metabolic efficacy, and vice versa.

For additional context on related peptide research methodologies, the SLUPP332 oral versus injectable research resource offers useful parallel considerations on route-of-administration variables that affect readout selection.


Organoid Platforms: Where the Two Frameworks Can Intersect

Organoid Platforms: Where the Two Frameworks Can Intersect

Organoid technology is the one research context where GLP-3 Retatrutide vs GLP-2-T: Choosing Metabolic, Intestinal, and Organoid Readouts for Comparative Research can share a platform, but only with strict compartmentalization.

For retatrutide, hepatic organoids derived from primary hepatocytes or iPSC-derived liver cells provide a controlled system for measuring fat accumulation (lipid droplet quantification), glucose output, and receptor-level signaling (cAMP production, beta-arrestin recruitment). These models mirror the liver-fat and glycemic endpoints validated in the MASLD phase 2a trial.

For GLP-2-T, intestinal organoids derived from small intestinal crypts are the gold-standard platform. Key readouts include:

  • Organoid surface area expansion as a proxy for villus-like growth
  • Goblet cell and enterocyte differentiation ratios
  • Tight junction protein expression (ZO-1, occludin, claudin-3)
  • Transepithelial electrical resistance (TEER) as a barrier integrity measure
  • Nutrient transporter expression (SGLT1, GLUT2)

The intersection point is co-culture or multi-organ chip systems that link hepatic and intestinal compartments. In that setting, retatrutide's hepatic effects and GLP-2-T's intestinal effects can be observed in the same platform without conflating their primary readout domains. This remains a speculative but scientifically grounded direction for 2026 research programs.

Researchers sourcing material for organoid-based work should verify purity documentation carefully. The GLP3 RETA CAG 10mg for sale and GLP3 RETA CAG 10mg GA5 product pages provide specification details relevant to in vitro dosing decisions. For broader sourcing considerations, the GLP-3 Retatrutide buy online USA cheap resource addresses cost-quality tradeoffs that matter in multi-arm organoid studies.


Conclusion

The central lesson from aligning retatrutide's clinical trial evidence with GLP-2-T's intestinal biology is straightforward: these agents require separate readout frameworks, not a shared one. Retatrutide's primary endpoints are systemic, body weight, HbA1c, liver fat, lipids, and cardiometabolic markers. GLP-2-T's primary endpoints are structural and functional at the intestinal level, villus morphology, barrier integrity, and organoid proliferation.

Actionable next steps for research teams in 2026:

  1. Audit existing assay panels and remove any endpoints that do not align with the receptor biology of the agent being tested.
  2. Confirm GLP-1R, GIPR, and GCGR co-expression in every model used for retatrutide; confirm GLP-2R expression in every model used for GLP-2-T.
  3. Use MRI-PDFF, ALT/AST, and body composition as the metabolic arm's anchor endpoints.
  4. Use TEER, tight junction protein quantification, and organoid proliferation index as the intestinal arm's anchor endpoints.
  5. Consider multi-organ chip platforms only after single-domain validation is complete.

Maintaining this discipline protects the interpretive value of comparative data and positions research outputs for stronger translational relevance as triple-agonist therapies move through phase 3 development.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/glp-3-retatrutide-vs-glp-2-t-choosing-metabolic-intestinal-and-organoid-readouts.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-05 13:04:282026-10-05 13:04:28GLP-3 Retatrutide vs GLP-2-T: Choosing Metabolic, Intestinal, and Organoid Readouts for Comparative Research
Atorvastatin in Metabolic Peptide Experiments: Controlling Lipid-Lowering Effects in Retatrutide and Mitochondrial Models

Atorvastatin in Metabolic Peptide Experiments: Controlling Lipid-Lowering Effects in Retatrutide and Mitochondrial Models

October 4, 2026/0 Comments/in Uncategorized/by

Fewer than 10% of metabolic peptide experiments pre-specify how concurrent statin therapy will be handled, yet that omission can quietly invalidate a study's entire lipid endpoint. When the compound under investigation is a triple agonist as potent as retatrutide, and when mitochondrial probes such as MOTS-c or 5-Amino-1MQ are added to the design, the presence or absence of atorvastatin in the background becomes a variable that can dwarf the signal researchers are actually trying to measure. Understanding how to account for atorvastatin in metabolic peptide experiments, controlling lipid-lowering effects in retatrutide and mitochondrial models, is therefore not a minor procedural detail. It is a core element of experimental validity.

Key Takeaways

  • Atorvastatin's HMG-CoA reductase inhibition and pleiotropic effects can confound lipid endpoints in retatrutide and mitochondrial peptide studies if not systematically controlled.
  • Baseline lipid matching and pre-specified washout windows are the two most critical design decisions when atorvastatin is present in a study population.
  • Retatrutide's triple agonism (GLP-1, GIP, glucagon) independently lowers LDL, triglycerides, and hepatic lipids, making statin co-exposure a genuine confound rather than a neutral background variable.
  • Mitochondrial peptides such as MOTS-c and 5-Amino-1MQ interact with pathways that atorvastatin also touches, requiring careful arm construction to isolate each compound's contribution.
  • No completed published trial as of 2026 has formally used atorvastatin as a deliberate modulator of retatrutide's lipid effects; current guidance is therefore grounded in pharmacological principles and experimental design logic.

Why Atorvastatin Demands Attention in Metabolic Peptide Research

Why Atorvastatin Demands Attention in Metabolic Peptide Research

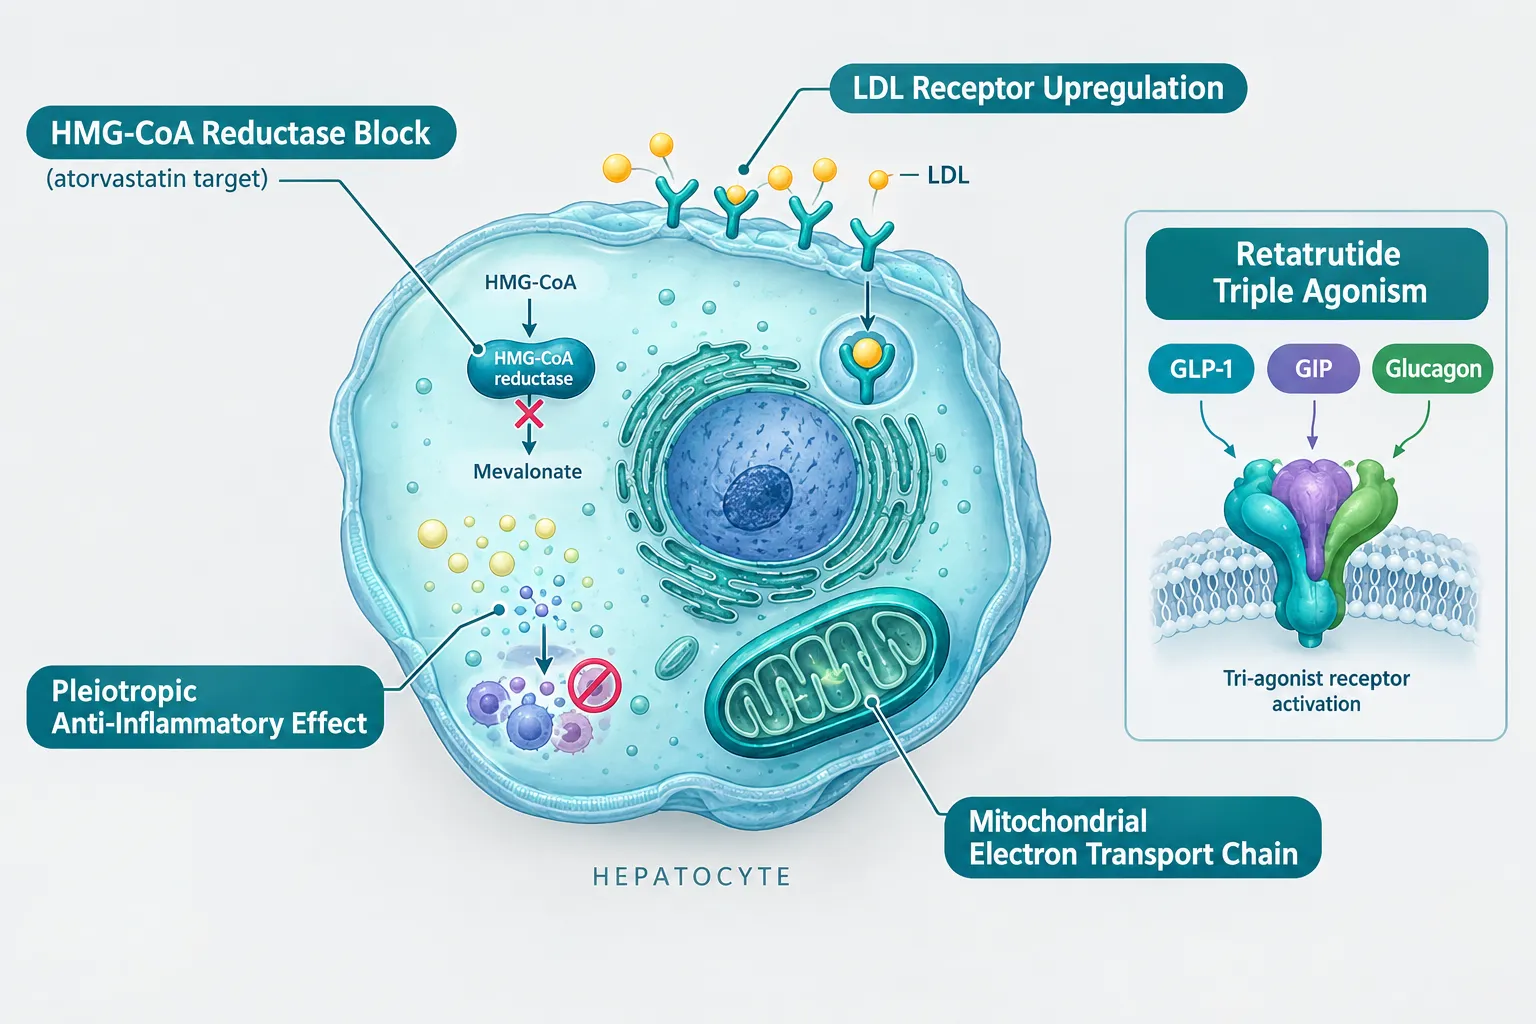
Atorvastatin is the world's most prescribed lipid-lowering drug. It blocks HMG-CoA reductase, the rate-limiting enzyme in hepatic cholesterol synthesis, and upregulates LDL receptors on liver cells. Beyond these primary actions, it exerts well-documented pleiotropic effects: reducing vascular inflammation, modulating endothelial nitric oxide, and influencing mitochondrial coenzyme Q10 levels. Each of these secondary actions intersects with pathways that metabolic peptides are designed to probe.

Retatrutide (LY3437943) activates GLP-1, GIP, and glucagon receptors simultaneously. Phase 2 trial data show mean weight reductions of approximately 22-24% over 48 weeks, accompanied by meaningful improvements in triglycerides, LDL cholesterol, and hepatic lipid content. Crucially, these lipid improvements arise from the peptide's own pharmacology, glucagon receptor agonism increases lipolysis and reduces lipogenesis, while GLP-1 and GIP components improve insulin sensitivity and reduce ectopic fat. When a participant is also taking atorvastatin, separating the statin's LDL effect from the peptide's LDL effect becomes statistically and mechanistically complex.

"The question is not whether atorvastatin matters, it clearly does. The question is whether the experimental design treats it as a known variable or an invisible confounder."

Researchers sourcing retatrutide peptide for preclinical work or reviewing GLP-3/retatrutide combination products should build statin status into their protocol from day one.


Experimental Design Principles for Atorvastatin in Metabolic Peptide Experiments

Experimental Design Principles for Atorvastatin in Metabolic Peptide Experiments

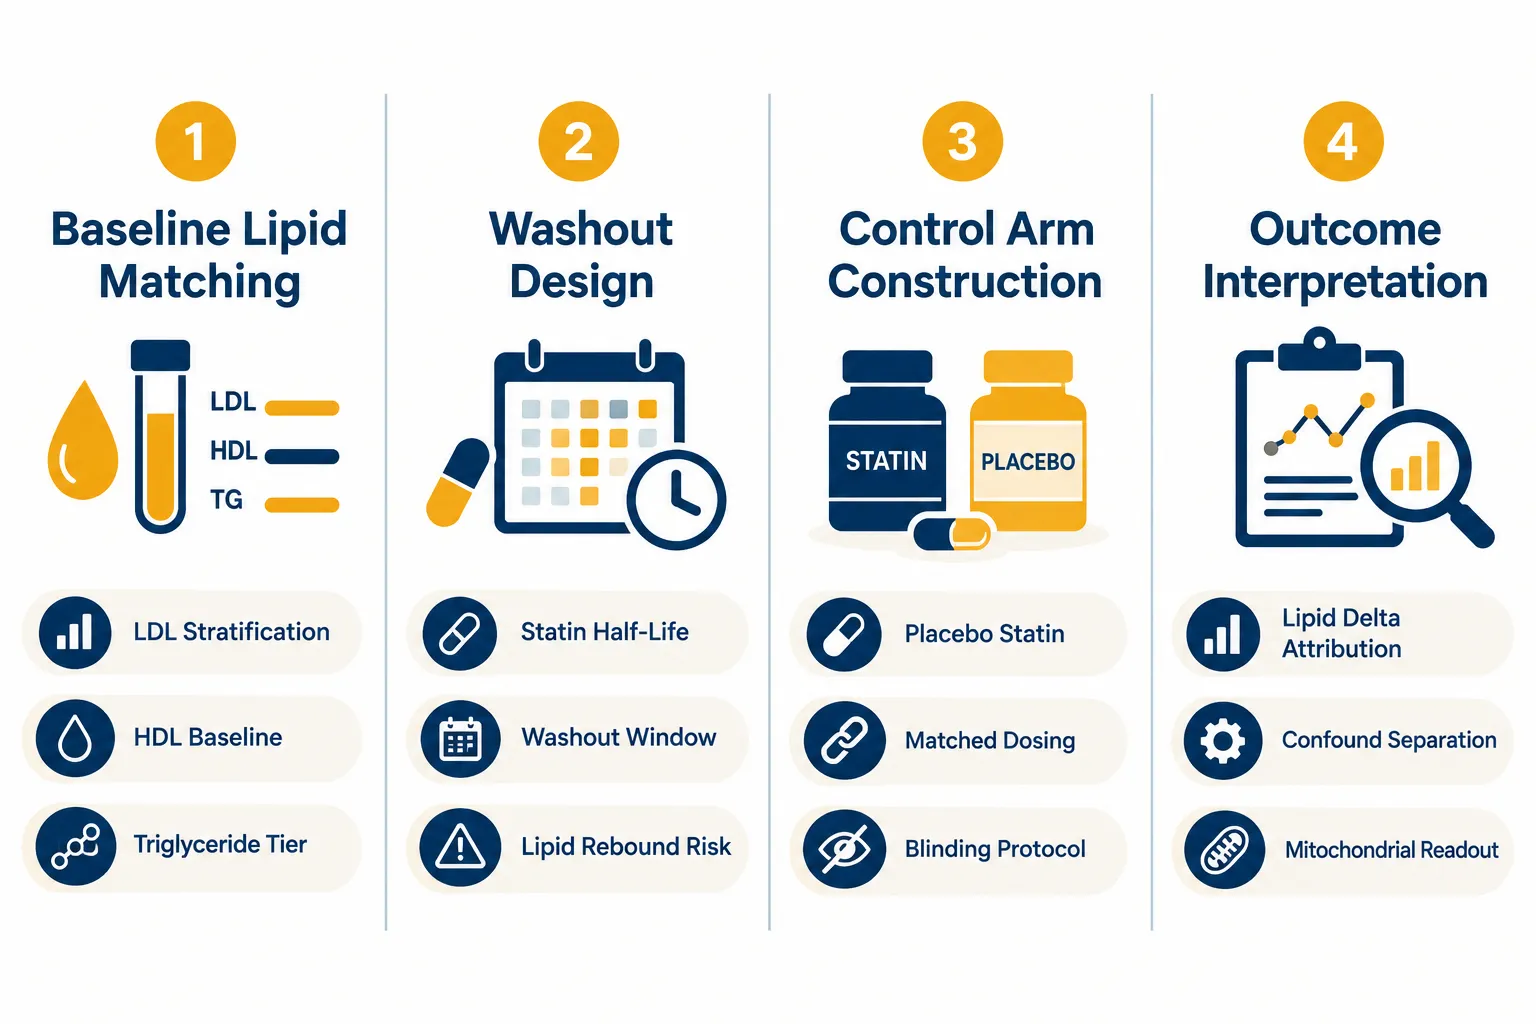
Rigorous control of atorvastatin's influence requires four interlocking design decisions.

Baseline Lipid Matching

Before randomization, participants or cell-line models should be stratified by:

  • LDL-C tier (optimal, borderline, elevated)
  • Triglyceride level (normal vs. elevated)
  • HDL-C baseline
  • Current statin dose (low, moderate, high intensity per ACC/AHA criteria)

Failure to match on these variables means that any observed lipid change could reflect pre-existing statin intensity differences rather than the peptide intervention. In retatrutide studies, where triglyceride reductions can exceed 30%, an unmatched high-intensity statin arm will produce misleading comparisons.

Washout Considerations

Atorvastatin has a plasma half-life of roughly 14 hours, but its pharmacodynamic effects on LDL receptor expression persist for several days after the last dose. A minimum two-week washout is generally recommended before lipid baseline measurements are taken in studies where statin use must be paused. However, washout carries its own risk: LDL rebound can occur within days, which may introduce a time-dependent confound if baseline measurements are taken at different points post-washout across participants.

Practical options:

Design Choice Advantage Risk
Full washout before baseline Clean lipid baseline LDL rebound, ethical concern in high-risk subjects
Stable dose maintained throughout Ethically safer Statin effect folded into all arms equally
Stratified by statin status (no washout) Preserves safety, enables subgroup analysis Requires larger sample size

Control Arm Construction

When atorvastatin cannot be washed out, as is often the case in cardiovascular-risk populations, the cleanest approach is to stratify randomization by statin use and ensure each treatment arm contains an equal proportion of statin users. This transforms atorvastatin from a confounder into a pre-specified effect modifier, allowing subgroup analyses to test whether the peptide's lipid effects differ by statin background.

Interpreting Outcomes Under Dual Therapy

In a dual-therapy scenario, the observed LDL reduction is a composite of atorvastatin's HMG-CoA blockade and retatrutide's glucagon-driven lipolysis and reduced hepatic lipogenesis. Statistical models should include statin dose as a covariate. Researchers interested in the GLP-3 peptide signaling pathway will recognize that receptor-level effects on lipid metabolism are distinct from enzyme-level inhibition, making additive versus synergistic modeling a meaningful analytical choice.


Mitochondrial Models: Where MOTS-c, 5-Amino-1MQ, and Atorvastatin Intersect

Mitochondrial Models: Where MOTS-c, 5-Amino-1MQ, and Atorvastatin Intersect

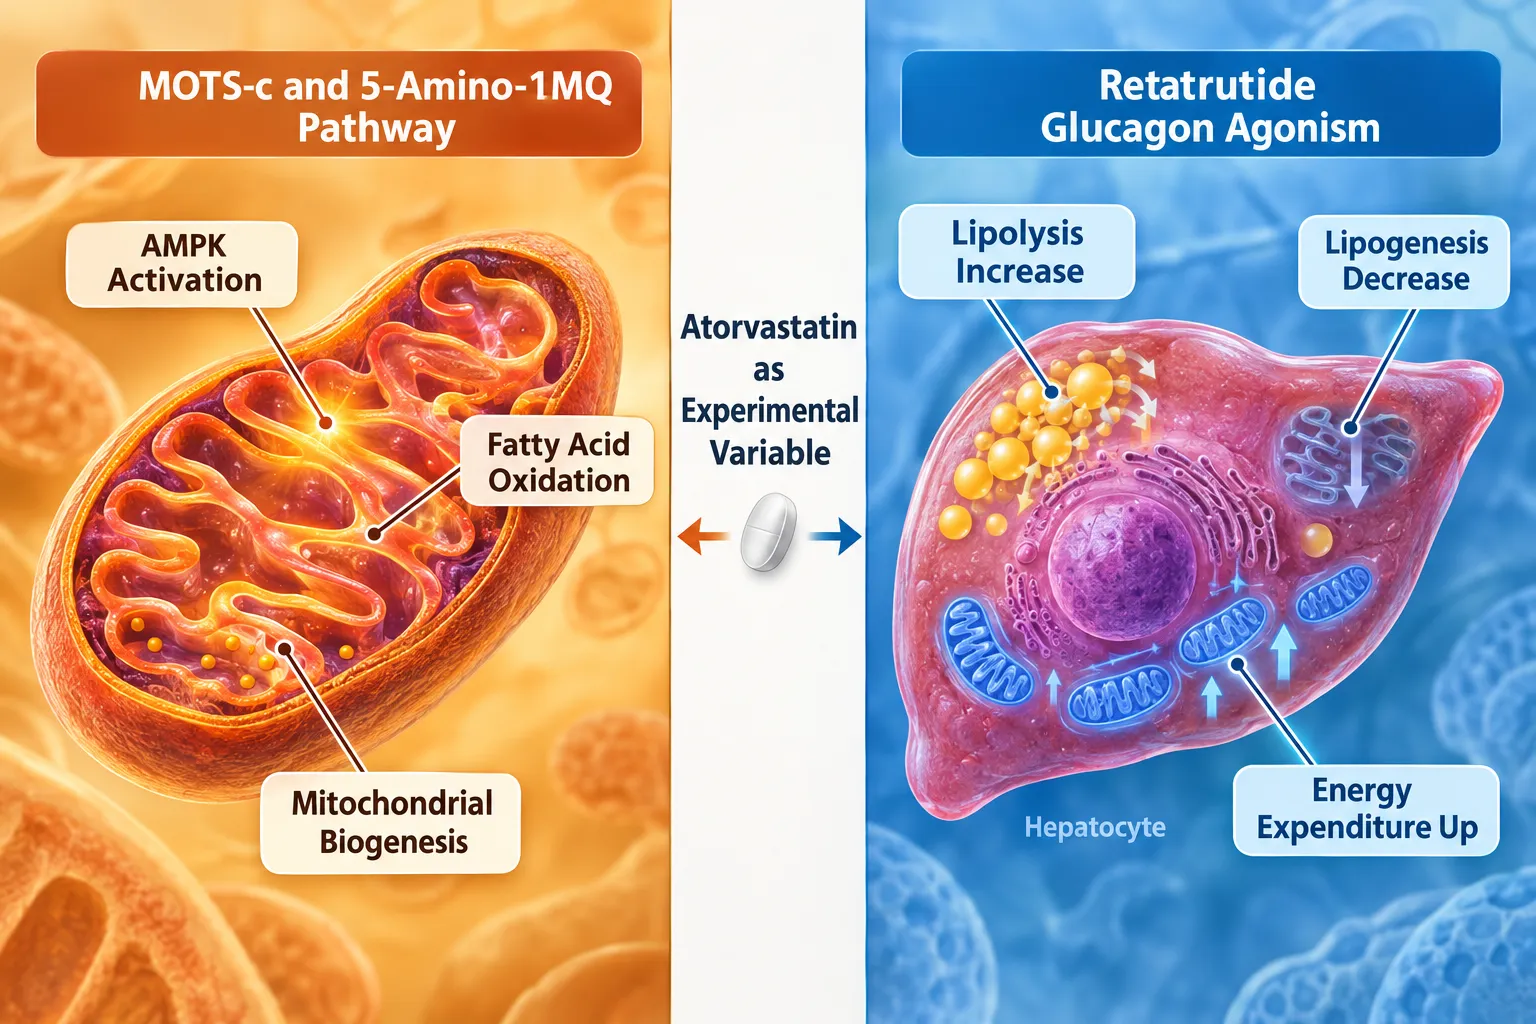
The complexity deepens considerably when mitochondrial peptides enter the experimental frame. MOTS-c is a mitochondria-derived peptide that activates AMPK, promotes fatty acid oxidation, and enhances mitochondrial biogenesis. 5-Amino-1MQ is a small-molecule inhibitor of NNMT (nicotinamide N-methyltransferase) that shifts cellular metabolism toward oxidative phosphorylation and reduces lipid accumulation. Both compounds operate on pathways that atorvastatin also touches, particularly through the coenzyme Q10 axis and mitochondrial electron transport chain dynamics.

Atorvastatin reduces endogenous coenzyme Q10 synthesis as a downstream consequence of HMG-CoA reductase inhibition. This can subtly impair mitochondrial respiratory chain efficiency, which is precisely the readout that MOTS-c and 5-Amino-1MQ experiments are designed to measure. An experiment that does not account for atorvastatin's CoQ10 effect may attribute impaired mitochondrial respiration to the peptide when the statin is the actual driver.

Key mitochondrial confounds introduced by atorvastatin:

  • Reduced CoQ10 availability in Complex I/III of the electron transport chain
  • Altered mitochondrial membrane potential in hepatocytes and myocytes
  • Possible upregulation of mitochondrial biogenesis as a compensatory response

For researchers working with SS-31 mitochondrial research models or reviewing SS-31 10mg research peptide considerations, the same logic applies: any statin in the background must be pre-specified, dose-recorded, and statistically controlled. Those exploring MOTS-c peptide for sale for metabolic research should document statin co-exposure in their experimental logs as a standard practice.

When retatrutide is layered on top of this mitochondrial model, the glucagon receptor agonism adds a third metabolic signal, increased hepatic fatty acid oxidation and energy expenditure, that further overlaps with both the peptide probes and the statin background. Isolating each compound's contribution requires:

  1. Pre-specified factorial or stratified designs
  2. Mitochondrial respiration assays (Seahorse XF or equivalent) run in statin-exposed versus statin-naive conditions
  3. CoQ10 plasma levels measured as a mechanistic covariate
  4. AMPK phosphorylation status as a shared downstream readout for MOTS-c, 5-Amino-1MQ, and glucagon agonism

Conclusion

Atorvastatin in metabolic peptide experiments, controlling lipid-lowering effects in retatrutide and mitochondrial models, is not a pharmacological afterthought. It is a design variable that, if ignored, can corrupt lipid endpoints, misattribute mitochondrial readouts, and produce irreproducible results. The actionable steps are clear:

  • Stratify by statin status at randomization, or pre-specify washout windows with lipid rebound monitoring.
  • Record atorvastatin dose intensity and include it as a covariate in all lipid and mitochondrial outcome models.
  • Measure CoQ10 levels when mitochondrial peptides such as MOTS-c, SS-31, or 5-Amino-1MQ are in the experimental design.
  • Use factorial subgroup analyses to test whether retatrutide's lipid effects differ by statin background, rather than assuming homogeneity.
  • Consult current phase 3 trial protocols as they become available; as of 2026, no completed study has formally used atorvastatin as a deliberate modulator of retatrutide's lipid effects, but the mechanistic rationale for doing so is strong.

Researchers who build these controls into their protocols from the outset will produce data that is interpretable, reproducible, and genuinely informative about the independent and combined contributions of each compound. Those who do not will spend far more time explaining away confounds than advancing the science.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/atorvastatin-in-metabolic-peptide-experiments-controlling-lipid-lowering-effects.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-04 13:04:572026-10-04 13:04:57Atorvastatin in Metabolic Peptide Experiments: Controlling Lipid-Lowering Effects in Retatrutide and Mitochondrial Models
Retatrutide Phase 3 Results in 2026: How Researchers Should Interpret Weight Loss, A1C, and Cardiometabolic Endpoints

Retatrutide Phase 3 Results in 2026: How Researchers Should Interpret Weight Loss, A1C, and Cardiometabolic Endpoints

October 3, 2026/0 Comments/in Uncategorized/by

Fewer than five years after GLP-1 receptor agonists reshaped obesity medicine, a triple-receptor agonist is now producing weight loss figures that exceed nearly every benchmark set by its predecessors. Retatrutide Phase 3 Results in 2026, specifically from Eli Lilly's TRIUMPH program, have placed the research and clinical communities in the unusual position of needing new interpretive frameworks rather than simply updated numbers. Understanding what these results mean, how the trials were designed, and where the data should not be extrapolated is essential for any researcher working with this compound.

Key Takeaways

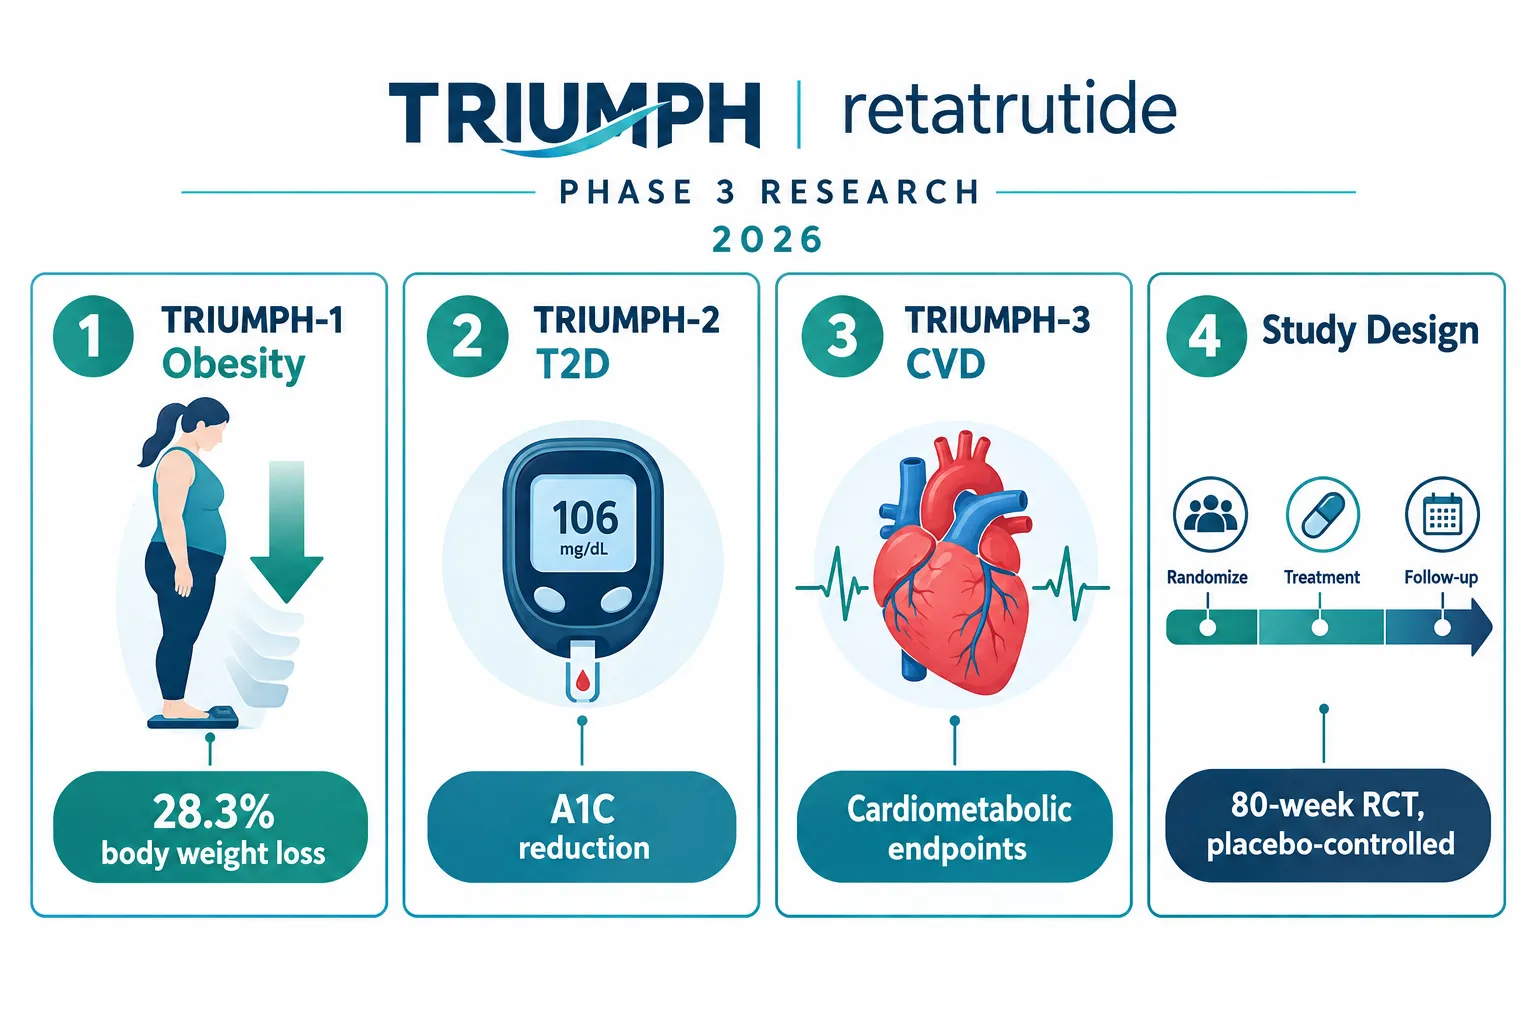
  • TRIUMPH-1 showed average body weight reductions of up to 28.3% at 80 weeks on the 12 mg dose, with roughly 45% of participants achieving at least 30% weight loss.
  • TRIUMPH-2 demonstrated meaningful A1C reductions alongside weight loss in adults with type 2 diabetes and obesity or overweight.
  • TRIUMPH-3 targeted adults with severe obesity and established cardiovascular disease, expanding the cardiometabolic endpoint dataset.
  • All three trials were 80-week, randomized, double-blind, placebo-controlled studies, setting a high methodological standard for interpretation.
  • Phase 3 clinical findings should not be directly extrapolated to research-use peptide materials without accounting for purity, formulation, and dosing differences.

Understanding the TRIUMPH Trial Architecture

The TRIUMPH program consists of three pivotal Phase 3 trials, each enrolling distinct populations to isolate different aspects of retatrutide's effects. TRIUMPH-1 enrolled adults with obesity or overweight without type 2 diabetes. TRIUMPH-2 enrolled adults who had both type 2 diabetes and obesity or overweight. TRIUMPH-3 focused on adults with severe obesity and established cardiovascular disease. Each trial ran for 80 weeks under a randomized, double-blind, placebo-controlled design, the gold standard for regulatory-grade evidence.

Understanding the TRIUMPH Trial Architecture

Retatrutide itself is a triple agonist acting simultaneously on GLP-1, GIP, and glucagon receptors. This mechanism distinguishes it from dual agonists like tirzepatide and single-receptor agents like semaglutide. Researchers reviewing the retatrutide clinical trial literature should note that the multi-receptor activity complicates direct comparisons with earlier compounds, since each receptor pathway contributes differently to energy expenditure, appetite suppression, and glucose metabolism.

Key dose arms tested across TRIUMPH trials:

Dose Trial Inclusion Primary Role
4 mg once weekly TRIUMPH-1, TRIUMPH-2 Lower-dose comparator
8 mg once weekly TRIUMPH-1, TRIUMPH-2 Mid-range efficacy arm
9 mg once weekly TRIUMPH-1 High-dose efficacy arm
12 mg once weekly TRIUMPH-1, TRIUMPH-2, TRIUMPH-3 Maximum dose efficacy arm

Interpreting Weight Loss Endpoints from Retatrutide Phase 3 Results in 2026

TRIUMPH-1 produced the most widely cited weight loss figures. Participants on the 9 mg dose lost an average of 64.4 lb, representing 25.9% of baseline body weight. Those on the 12 mg dose lost an average of 70.3 lb, or 28.3% of baseline weight. The placebo group lost approximately 2.2%. Approximately 45% of the roughly 2,500 participants achieved at least 30% weight loss, a threshold that had rarely appeared in prior obesity pharmacotherapy trials.

An extension to 104 weeks showed that participants with a BMI of 35 kg/m² or higher on the highest dose lost approximately 30.3% of body weight on average, suggesting the effect is durable rather than plateauing early.

"A 28% average weight reduction in a randomized controlled trial is not a ceiling, it is a new baseline expectation for next-generation obesity pharmacotherapy."

Researchers reviewing these figures alongside retatrutide endpoints data should apply several interpretive cautions:

  • Responder heterogeneity: Mean weight loss masks a wide distribution. Some participants lost far less; others exceeded 35%.
  • Baseline BMI matters: Higher baseline BMI was associated with greater absolute weight loss but not always greater percentage loss.
  • Titration schedules: The dose escalation protocol used in TRIUMPH trials is specific and structured. Rapid titration in research settings produces different tolerability profiles.
  • Placebo subtraction: The net treatment effect, not the absolute loss, is the relevant efficacy signal for mechanistic research.

A1C, Glycemic Control, and Cardiometabolic Endpoints: What the Data Show

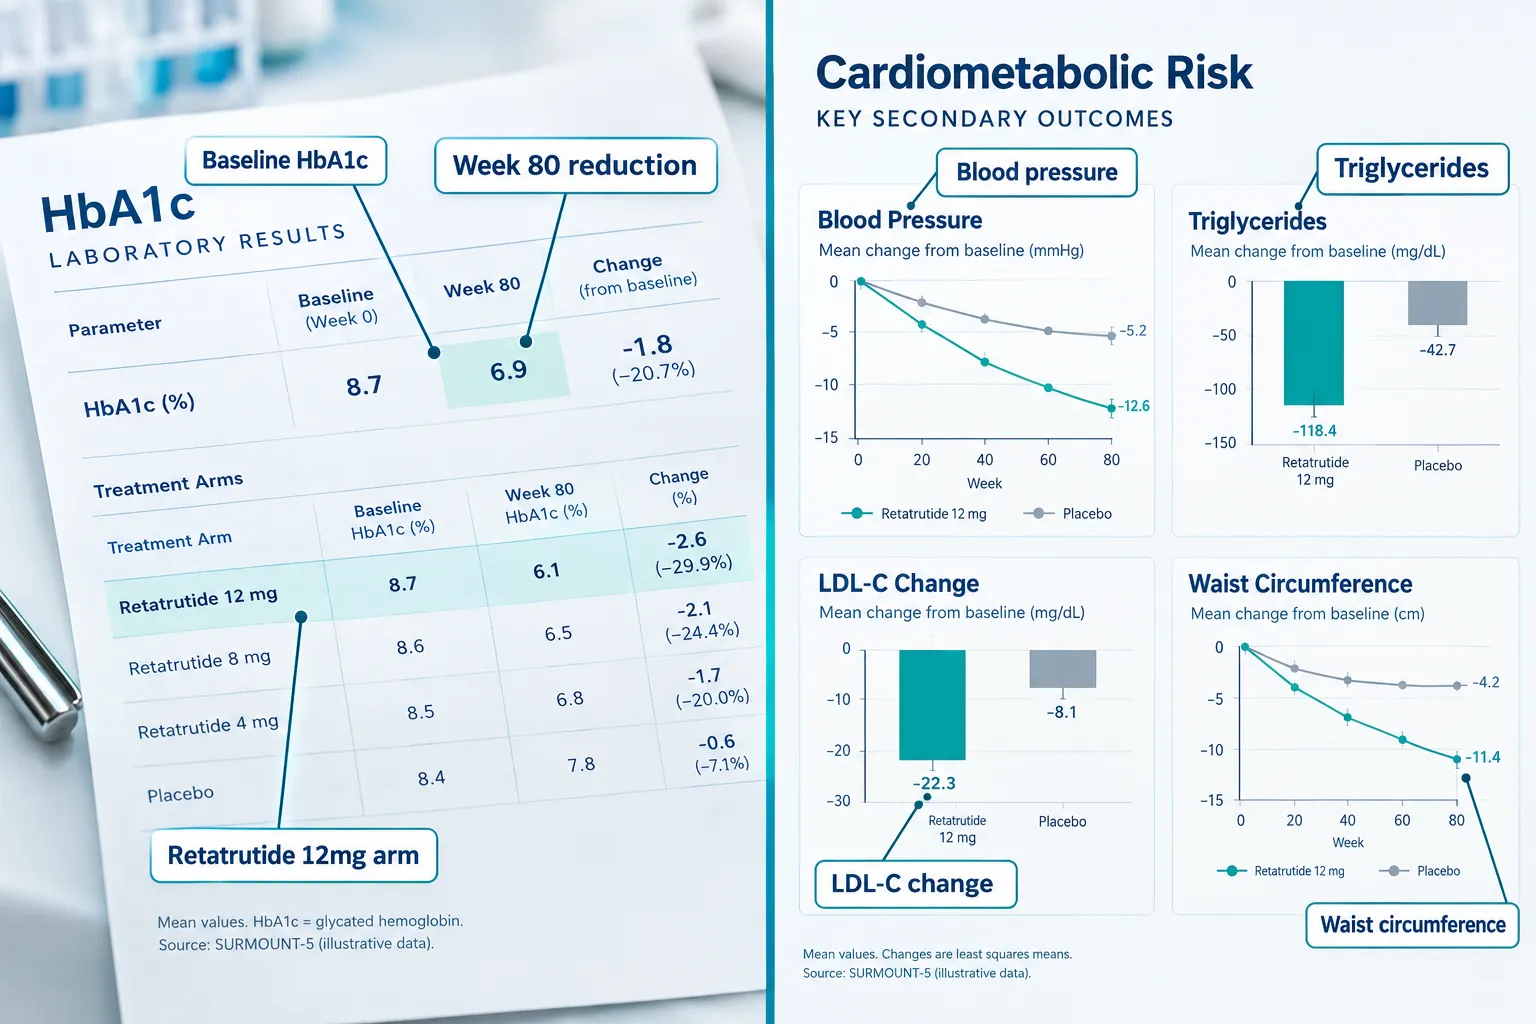
TRIUMPH-2 specifically addressed glycemic outcomes in adults with type 2 diabetes. Retatrutide produced substantial A1C reductions across all active dose arms, with the 12 mg arm achieving the largest decreases from baseline. These reductions were accompanied by meaningful weight loss, making it difficult to isolate the glycemic effect of the receptor agonism from the indirect benefit of fat mass reduction, a distinction that matters significantly for mechanistic researchers.

A1C, Glycemic Control, and Cardiometabolic Endpoints: What the Data Show

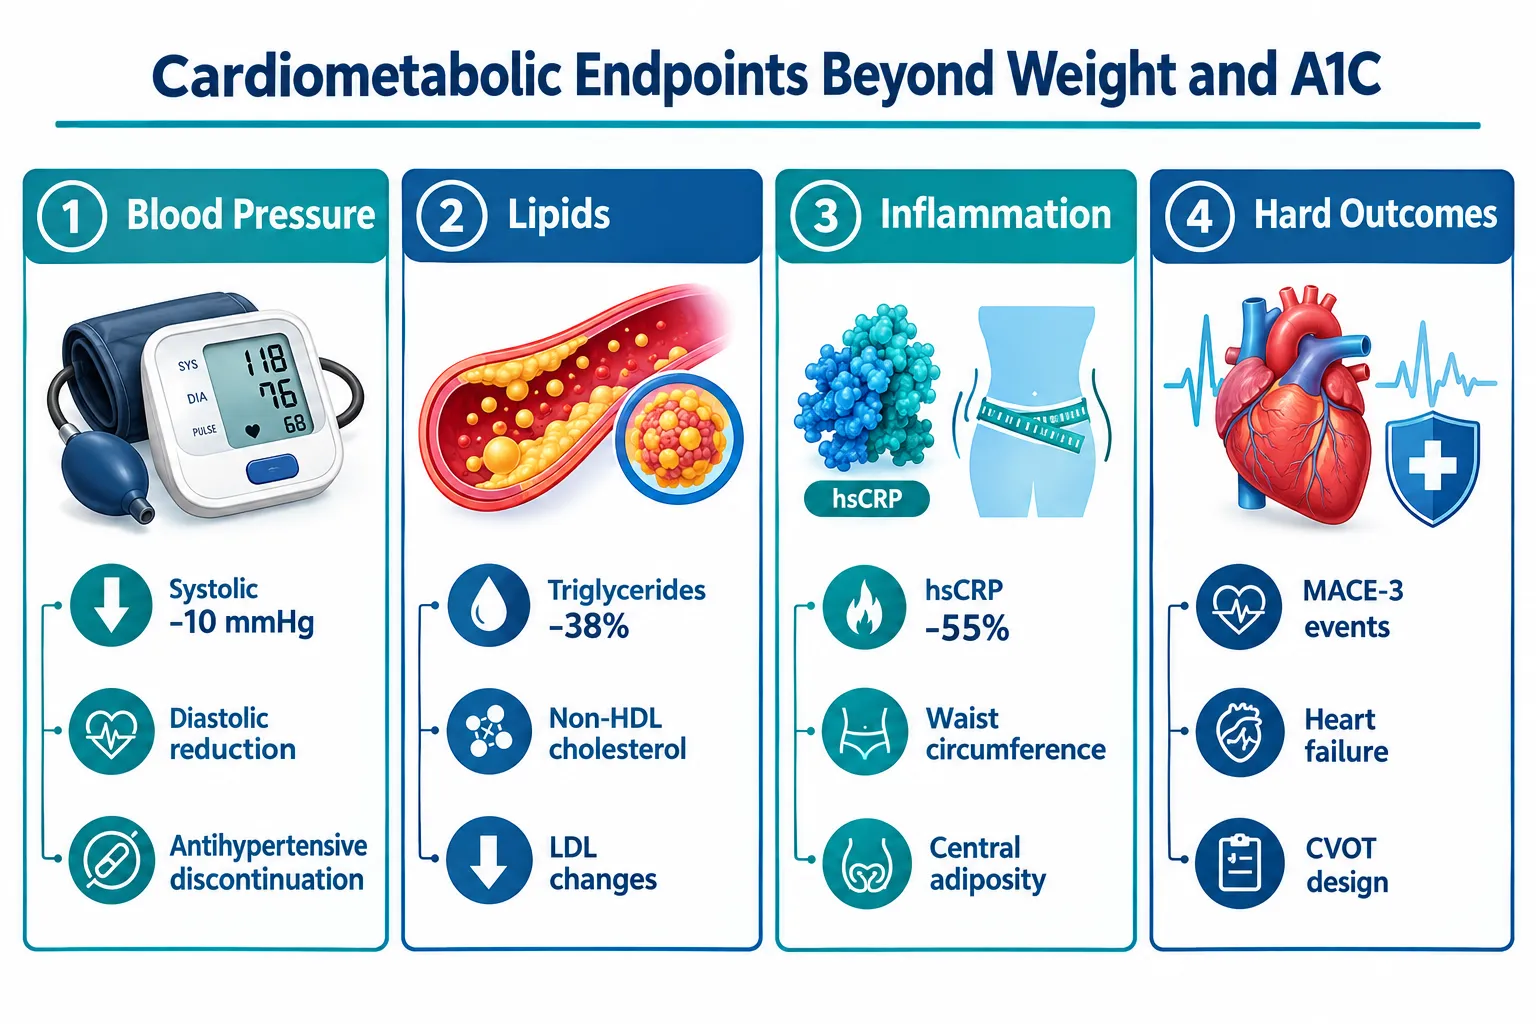
TRIUMPH-3 extended the dataset to cardiometabolic markers in a higher-risk population. Reported endpoints included changes in blood pressure, triglycerides, LDL-C, and waist circumference. While full cardiovascular outcomes data from a dedicated MACE trial are still pending as of 2026, the surrogate marker improvements observed in TRIUMPH-3 are consistent with the metabolic effects predicted by the triple-receptor mechanism.

Cardiometabolic endpoints researchers should track:

  • Systolic and diastolic blood pressure reduction
  • Fasting triglyceride change from baseline
  • HDL-C and LDL-C shifts
  • Waist circumference as a visceral adiposity proxy
  • Liver enzyme normalization in participants with metabolic-associated steatotic liver disease

How Researchers Should Avoid Misextrapolating Phase 3 Findings

Retatrutide Phase 3 Results in 2026 represent pharmaceutical-grade, GMP-manufactured material administered under controlled clinical conditions. Research-use peptide materials, such as those available as GLP-3 Reta 30mg or GLP-3 Reta 20mg for laboratory use, differ in formulation, excipient profile, and intended application. Researchers sourcing material should consult verified retatrutide peptide buy online resources that provide third-party purity documentation.

How Researchers Should Avoid Misextrapolating Phase 3 Findings

The following extrapolation errors are most common in the literature:

  1. Assuming equivalent bioavailability between pharmaceutical formulations and research-grade lyophilized peptides
  2. Applying TRIUMPH dose arms directly to non-human or in vitro research models without allometric scaling
  3. Conflating A1C reduction with direct receptor-mediated glycemic control when weight loss itself accounts for a significant portion of the glycemic benefit
  4. Ignoring the titration variable, TRIUMPH participants were dose-escalated over weeks, not started at maximum dose
  5. Overstating cardiovascular conclusions before dedicated MACE trial data are published

For researchers comparing retatrutide to other metabolic peptides, reviewing Tesamorelin dosage for fat loss frameworks offers a useful methodological contrast, since Tesamorelin's visceral fat reduction mechanism and endpoint structure differ substantially from triple-receptor agonism.


Conclusion

The Retatrutide Phase 3 Results in 2026 represent a landmark dataset for obesity, diabetes, and cardiometabolic research. The TRIUMPH program's three-trial architecture provides layered evidence across distinct populations, dose arms, and outcome categories. For researchers, the actionable steps are clear:

  • Treat the 80-week, placebo-controlled TRIUMPH data as the interpretive anchor for all mechanistic hypotheses involving retatrutide.
  • Distinguish between mean efficacy signals and responder distributions before drawing mechanistic conclusions.
  • Separate glycemic benefits attributable to weight loss from those attributable to direct receptor agonism when designing downstream studies.
  • Source research-grade material only from suppliers providing verified purity documentation, and never apply clinical dose arms directly to preclinical models without appropriate scaling.
  • Monitor the emerging MACE trial data before drawing cardiovascular outcome conclusions from surrogate markers alone.

The TRIUMPH results do not simply update a number, they reframe what metabolic pharmacotherapy can achieve and raise the methodological bar for how researchers must interpret, contextualize, and apply the data responsibly.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-phase-3-results-in-2026-how-researchers-should-interpret-weight-loss.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-03 13:08:402026-10-03 13:08:40Retatrutide Phase 3 Results in 2026: How Researchers Should Interpret Weight Loss, A1C, and Cardiometabolic Endpoints
Retatrutide Dose-Escalation Research: Comparing Exposure, Tolerability, and Endpoint Timing Across Study Designs

Retatrutide Dose-Escalation Research: Comparing Exposure, Tolerability, and Endpoint Timing Across Study Designs

October 3, 2026/0 Comments/in Uncategorized/by

Roughly 26% of adults worldwide meet clinical criteria for obesity, yet fewer than half of those enrolled in weight-loss drug trials complete the full escalation phase without a dose reduction or dropout. That gap between protocol intent and real-world completion sits at the center of retatrutide dose-escalation research: comparing exposure, tolerability, and endpoint timing across study designs, and it is now driving a new generation of deliberately structured trials.

Key Takeaways

  • Retatrutide is titrated stepwise from 2 mg once weekly to target doses of 4, 9, or 12 mg, with escalation lasting approximately 16 weeks before a prolonged maintenance phase.
  • Gastrointestinal adverse events, nausea, diarrhea, and vomiting, are clearly dose-dependent and concentrate during the escalation phase rather than maintenance.
  • A dedicated phase 3b trial is directly comparing alternative escalation schedules to determine whether slower titration improves the efficacy-tolerability balance without sacrificing weight-loss outcomes.
  • Endpoint timing across studies is deliberately staggered: Week 24 captures early escalation impact, while 80-week designs assess long-term durability at steady-state exposure.
  • Emerging non-GI signals, including dysesthesia at the highest doses, are beginning to shape thinking about maximum recommended doses and future flexible titration labels.

How Escalation Schedules Shape Drug Exposure

The pharmacological foundation of any retatrutide dose-escalation study rests on a straightforward principle: the rate at which a participant reaches their target dose directly determines how quickly and how intensely the body is exposed to the drug's full activity. Retatrutide is a triple GIP, GLP-1, and glucagon receptor agonist, and its cardiometabolic mechanism differs meaningfully from classic small-molecule drugs.

How Escalation Schedules Shape Drug Exposure

In the TRIUMPH program trials, the standard titration schedule moves participants from 2 mg once weekly to their assigned maintenance dose in four-weekly steps. The 4 mg arm requires only one step up (2 mg to 4 mg). The 9 mg arm moves through 2, 4, 6, and 9 mg over approximately 12 weeks. The 12 mg arm adds one further step to reach the ceiling dose, with escalation spanning roughly 16 weeks in total before a 64-week maintenance period begins.

This design has an important implication for exposure measurement. Participants spend a relatively short time in the escalation phase and a much longer time at steady-state. Any pharmacokinetic or pharmacodynamic endpoint measured early in the study reflects a rapidly changing exposure environment, while endpoints measured later reflect stable, high-exposure conditions. Comparing results across studies that use different escalation speeds therefore requires careful attention to when in the titration curve each measurement was taken.

Key exposure variables across escalation designs:

Design Feature Faster Escalation Slower Escalation
Time to target dose Shorter Longer
Peak early exposure Higher Lower
GI adverse event timing Earlier, more intense Spread over more weeks
Steady-state onset Earlier Delayed
Week 24 endpoint context Near or at maintenance Still escalating

Tolerability Data Across Dose Levels and Titration Speeds

The tolerability profile of retatrutide is one of the most closely tracked variables in current dose-escalation research. Across TRIUMPH program data, nausea was reported in approximately 16%, 20%, and 27% of participants at 4, 9, and 12 mg respectively, compared with under 4% on placebo. Diarrhea followed a similar gradient, rising from roughly 19% at 4 mg to 23% at 12 mg. Vomiting appeared in 16% to 18% of actively treated participants across dose levels.

Tolerability Data Across Dose Levels and Titration Speeds

At the highest tested doses, pooled safety analyses report nausea in up to 43% of participants, diarrhea in approximately 33%, and vomiting in around 21%. These figures are substantial, but discontinuation rates remained relatively low, 2.2% at 4 mg, 4.5% at 9 mg, and 5.1% at 12 mg, suggesting that most participants tolerate the burden, particularly when escalation is gradual.

The phase 2 obesity trial published in the New England Journal of Medicine provided early evidence that starting at 2 mg or 4 mg and increasing every four weeks meaningfully reduced GI symptom severity compared with more aggressive approaches. This finding now underpins the entire TRIUMPH escalation framework.

"Gastrointestinal adverse events are not only dose-related but also mitigated by starting at a lower dose and escalating gradually, a principle that is now being tested head-to-head in dedicated escalation-comparison trials."

Beyond GI symptoms, emerging data from TRIUMPH-4 topline results identified dysesthesia, abnormal skin sensations, in approximately 21% of participants at the highest dose. While GI events remain the primary tolerability concern, this non-GI signal is beginning to inform discussions about maximum recommended doses and the design of future long-duration studies.


Endpoint Timing and Study Design Across Current Trials

The most direct test of retatrutide dose-escalation research: comparing exposure, tolerability, and endpoint timing across study designs is now underway in a phase 3b trial registered in June 2026. This randomized, double-blind, parallel-assignment study includes at least two experimental arms, labeled "Retatrutide Dose Escalation 1" and "Retatrutide Dose Escalation 2", specifically designed to determine whether alternative titration schedules can shift the efficacy-tolerability balance without reducing the final maintenance dose.

Endpoint Timing and Study Design Across Current Trials

A multicenter phase 2 study adds further granularity. Participants are randomized to maintenance doses of 1, 4, 8, and 12 mg, but the 4 mg and 8 mg arms each include alternative escalation schedules to isolate the effect of titration speed from the effect of final dose. The primary endpoint, percent body weight change at Week 24, is strategically placed at a point when some participants will have just reached maintenance while others, on slower schedules, may still be escalating. This deliberate misalignment is not a flaw; it is the research question.

Why endpoint timing matters for interpretation:

  • Week 24 endpoints capture the combined effect of escalation intensity and early maintenance exposure, making them sensitive to titration speed differences.
  • Week 48 assessments provide extended anthropometric and safety data that reflect more stable exposure conditions.
  • 80-week TRIUMPH designs (16 weeks escalation plus 64 weeks maintenance) are built to evaluate long-term durability, metabolic improvements, and safety at sustained high-dose exposure.

This staggered endpoint strategy allows researchers and regulators to distinguish between the short-term impact of how fast a patient escalates and the long-term consequences of sustained high-dose therapy, two questions that earlier single-arm trials could not cleanly separate.

For context on how other research peptides approach dosing and timing considerations, the literature on SS-31 ideal dosage and timing illustrates how titration decisions affect both tolerability and endpoint interpretation across different compound classes. Similarly, CJC-1295 pharmacokinetic comparison research demonstrates how half-life and exposure curves shape study design choices more broadly.

Researchers interested in the broader RETA 10mg research context or the GLP3-RETA 20mg formulation will find that these product-level considerations connect directly to the dose-level questions being tested in current escalation trials.


Conclusion

Retatrutide dose-escalation research: comparing exposure, tolerability, and endpoint timing across study designs has moved from a secondary consideration to the central question of the current trial generation. The evidence is clear that slower titration reduces early GI burden without eliminating it, that adverse events are dose-dependent and concentrated in the escalation phase, and that endpoint timing must be interpreted relative to where each participant sits on their titration curve.

Actionable next steps for researchers and clinicians following this space:

  1. Track the phase 3b escalation-comparison trial results, which will provide the first head-to-head data on alternative titration schedules at identical maintenance doses.
  2. When reviewing published trial data, note the escalation schedule used and the timing of primary endpoints relative to when participants reached maintenance dose.
  3. Anticipate that future regulatory labels for retatrutide at 9-12 mg may embed flexible titration options rather than a single fixed schedule, based on the tolerability evidence accumulating in 2026 trials.
  4. Consider non-GI signals, particularly dysesthesia at the highest doses, as part of the full exposure-tolerability profile when evaluating study designs.

The field is moving toward individualized titration, not as a clinical convenience, but as a scientifically validated strategy supported by rigorously designed comparative trials.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-dose-escalation-research-comparing-exposure-tolerability-and-endpoin.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-03 13:08:342026-10-03 13:08:34Retatrutide Dose-Escalation Research: Comparing Exposure, Tolerability, and Endpoint Timing Across Study Designs
Retatrutide and Cardiovascular Disease Research: Designing Endpoints Beyond Weight Loss and A1C

Retatrutide and Cardiovascular Disease Research: Designing Endpoints Beyond Weight Loss and A1C

October 3, 2026/0 Comments/in Uncategorized/by

"

Professional () hero image with 'Retatrutide and Cardiovascular Disease' in crisp white on a deep navy semi-transparent

Cardiovascular disease kills more people with obesity and type 2 diabetes than any other complication, yet most obesity drug trials still define success almost entirely by the number on a scale or a single blood sugar marker. Retatrutide and cardiovascular disease research is now forcing a rethink of that narrow framework, pushing investigators to design endpoints that capture blood pressure, lipid profiles, inflammatory biomarkers, and hard cardiovascular events alongside weight and A1C.

Key Takeaways

  • Retatrutide, a GLP-1/GIP/glucagon triple agonist, produces striking reductions in blood pressure, triglycerides, waist circumference, and high-sensitivity C-reactive protein (hsCRP), signals that go well beyond weight loss and glycemic control.
  • Phase 3 TRIUMPH-3 data showed roughly 22-25% weight reduction at 12 mg, with systolic blood pressure falling up to 10.8 mmHg and hsCRP dropping up to 58%, but cardiovascular event rates did not reach statistical significance.
  • A dedicated cardiovascular outcomes trial (CVOT) is underway, designed specifically to evaluate major adverse cardiovascular events (MACE) in high-risk populations.
  • Distinguishing exploratory cardiometabolic signals from validated cardiovascular-outcome evidence is essential for sound protocol planning and regulatory strategy.
  • Future endpoint frameworks will likely use integrated cardiometabolic composites, covering lipids, inflammation, central adiposity, and organ-specific outcomes, rather than relying on weight and A1C alone.

Why Triple-Agonist Biology Demands Broader Endpoint Thinking

Why Triple-Agonist Biology Demands Broader Endpoint Thinking

Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, a pharmacological profile that creates metabolic effects across multiple organ systems at once. This broad reach is precisely why retatrutide clinical trials have moved quickly to incorporate cardiometabolic measures as prespecified exploratory endpoints rather than afterthoughts.

In the pivotal phase 2 obesity trial published in the New England Journal of Medicine, once-weekly retatrutide produced a mean weight reduction of 24.2% at 48 weeks at higher doses. Alongside that headline figure, investigators tracked systolic and diastolic blood pressure, waist circumference, fasting glucose, insulin, glycated hemoglobin, and most lipid parameters. That multi-factor design reflected an early recognition that glucagon receptor agonism affects hepatic lipid metabolism and energy expenditure in ways that GLP-1 alone does not.

A 2024 meta-analysis confirmed statistically significant reductions in systolic blood pressure (pooled weighted mean difference of approximately -4.70 mmHg) and diastolic blood pressure (-1.73 mmHg) across retatrutide studies. Complementary Lancet data showed systolic blood pressure falling roughly 5 mmHg with active doses versus about 1.5 mmHg on placebo over 40 weeks. These consistent signals across studies support blood pressure as a reliable intermediate endpoint, one that is biologically plausible, measurable, and clinically meaningful.

Protocol planning note: Blood pressure and lipid changes are reproducible across retatrutide studies, making them strong candidates for secondary or co-primary endpoints in future trials. They should not be treated as incidental observations.

Researchers designing studies around GLP-1 Reta compounds increasingly recognize that a single surrogate endpoint misrepresents the drug's full cardiometabolic footprint.


Cardiometabolic Endpoint Design: From Signals to Evidence

Cardiometabolic Endpoint Design: From Signals to Evidence

The TRIUMPH-3 phase 3 trial, which enrolled nearly 2,000 adults with severe obesity (BMI 35 or higher) and established cardiovascular disease, generated the most comprehensive cardiometabolic endpoint data to date. Results released in late September 2026 showed the following at the highest 12 mg dose:

Endpoint Approximate Change vs. Placebo
Systolic blood pressure -9.3 to -10.8 mmHg
Triglycerides -37 to -39.5%
Non-HDL cholesterol -16.5 to -19.6%
Waist circumference -16.9 to -19.0 cm
hsCRP -51 to -58%

These figures represent a multi-dimensional risk-modification profile that no single endpoint could capture. The hsCRP reduction in particular is notable: chronic low-grade inflammation is an independent cardiovascular risk factor, and a 51-58% drop in this marker suggests retatrutide may be modifying vascular biology beyond what weight loss alone would explain.

Equally important is the medication-burden signal. In the NEJM phase 2 trial, 41% of patients in the 8 mg group and 30% in the 12 mg group were able to discontinue at least one antihypertensive medication. This is a clinically relevant endpoint that regulatory agencies and payers increasingly value, it reflects real-world health impact, not just a surrogate number.

However, a critical distinction must be made. Despite these striking risk-factor improvements, TRIUMPH-3 did not show statistically significant reductions in major cardiovascular events. There were 44 MACE-5 events in the retatrutide group versus 52 in the placebo group, yielding a hazard ratio of 0.82 (95% CI 0.55-1.22). The MACE-3 hazard ratio was 1.12 (95% CI 0.64-1.96). The trial was not powered to detect event-level differences, and event counts were lower than projected. This is the essential gap between exploratory cardiometabolic signals and validated cardiovascular-outcome evidence.

For researchers working with related peptide frameworks such as SS-31 mitochondrial research or tesa dosage for fat loss protocols, this distinction between surrogate improvements and hard event outcomes is a recurring methodological challenge across the field.


Designing the Next Generation of Retatrutide Cardiovascular Endpoints

Designing the Next Generation of Retatrutide Cardiovascular Endpoints

A dedicated CVOT for retatrutide is now underway, targeting adults with overweight or obesity and established cardiovascular disease. This trial is explicitly designed to answer the question that TRIUMPH-3 could not: does retatrutide reduce major adverse cardiovascular events at a statistically powered level?

Recommended endpoint architecture for future retatrutide CVOTs:

  • Primary endpoint: MACE-3 (cardiovascular death, non-fatal myocardial infarction, non-fatal stroke) as the regulatory standard
  • Key secondary endpoints: Heart failure hospitalizations, kidney function trajectories, all-cause mortality
  • Exploratory biomarker endpoints: hsCRP, NT-proBNP, albuminuria, imaging-based myocardial structure measures
  • Safety hemodynamic monitoring: Pulse rate, arrhythmia surveillance, autonomic function, early diabetes studies showed increased pulse rate despite lower blood pressure, underscoring the need for comprehensive hemodynamic tracking

The inflammatory marker data from TRIUMPH-3 strengthens the case for including hsCRP and other inflammatory endpoints as prespecified secondary measures. A 51-58% reduction in hsCRP is not a minor signal; it warrants formal hypothesis testing in a powered trial.

Renal outcomes deserve explicit attention given the overlap between obesity, type 2 diabetes, and chronic kidney disease in high-risk populations. Albuminuria and estimated glomerular filtration rate trajectories should be incorporated as secondary endpoints, consistent with the approach taken in GLP-1 CVOT designs. For context on how related peptide research approaches multi-system endpoints, the GLP3 Reta compound research framework offers a useful parallel.

Lilly's March 2026 release on retatrutide in people with obesity and type 2 diabetes explicitly framed non-HDL cholesterol, triglyceride, and blood pressure improvements as key differentiating endpoints alongside glycemic control, signaling that the company's own endpoint strategy has already moved beyond weight and A1C.


Conclusion

Retatrutide and cardiovascular disease research is at a pivotal inflection point in 2026. The cardiometabolic signal is strong: blood pressure reductions of up to 10.8 mmHg, triglyceride drops approaching 40%, hsCRP reductions exceeding 50%, and clinically meaningful antihypertensive medication discontinuation rates all point to a drug with broad cardiovascular risk-modification potential.

What the evidence does not yet support is a validated claim of cardiovascular event reduction. TRIUMPH-3 was not powered for that conclusion, and the ongoing CVOT must deliver that answer before a formal cardiovascular risk-reduction indication can be pursued.

Actionable next steps for protocol designers and researchers:

  1. Build composite cardiometabolic endpoints into study designs from the start, do not treat blood pressure, lipids, and inflammation as secondary afterthoughts.
  2. Power dedicated CVOTs specifically for MACE, not just for weight loss, and include heart failure and renal outcomes as key secondary endpoints.
  3. Monitor hemodynamic safety comprehensively, including pulse rate and arrhythmia surveillance, given the mixed blood pressure and heart rate signals seen in early studies.
  4. Use inflammatory biomarkers such as hsCRP as prespecified exploratory endpoints to build the evidence base for future mechanistic claims.
  5. Follow retatrutide clinical trials progress closely, as CVOT results will determine whether the robust risk-factor improvements seen to date translate into the event-level cardiovascular benefit that patients and regulators require.

The science is compelling. The endpoint design must now match the ambition of the biology.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-and-cardiovascular-disease-research-designing-endpoints-beyond-weigh.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-03 13:04:482026-10-03 13:04:48Retatrutide and Cardiovascular Disease Research: Designing Endpoints Beyond Weight Loss and A1C
Retatrutide, GLP-1 Pills, and Small-Molecule Weight-Loss Options: What Researchers Should Compare Before Selecting a Model

Retatrutide, GLP-1 Pills, and Small-Molecule Weight-Loss Options: What Researchers Should Compare Before Selecting a Model

October 1, 2026/0 Comments/in Uncategorized/by

Fewer than five years ago, the only oral option for metabolic research was a single approved peptide formulation with modest weight-loss signals. By mid-2026, the landscape includes a triple-receptor injectable peptide, a first-in-class non-peptide oral GLP-1 agonist, and a reformulated oral semaglutide, each with a distinct mechanism, tolerability profile, and regulatory standing. Choosing the wrong model for a given research question wastes resources and produces data that cannot be compared across studies. Understanding the key variables in Retatrutide, GLP-1 Pills, and Small-Molecule Weight-Loss Options is the first step toward designing a rigorous protocol.

Key Takeaways

  • Retatrutide is a triple agonist (GLP-1, GIP, glucagon receptors) with phase 3 data showing substantially higher weight-loss magnitude than single-agonist comparators.
  • Orforglipron (Foundayo) is a non-peptide small molecule that achieves oral bioavailability without an absorption enhancer, making it mechanistically distinct from oral semaglutide.
  • Oral semaglutide (Wegovy pill) is a peptide formulation requiring a specific absorption agent; it is broadly available in the US but shows more modest weight-loss numbers in smaller patient cohorts.
  • Regulatory status differs sharply: some agents are approved, others remain in late-stage trials or are available only for research purposes.
  • Researchers must explicitly encode receptor target depth, delivery route, glycemic endpoints, and tolerability variables before selecting any model.

Understanding the Compound Classes in Play

Understanding the Compound Classes in Play

Not all weight-loss agents work the same way, and conflating them in a research design leads to flawed conclusions. The current field breaks into three meaningful categories.

Retatrutide is a single-molecule triple agonist that activates GLP-1, GIP, and glucagon receptors simultaneously. Phase 3 data from the TRIUMPH-1 trial in obesity showed weight reductions that outpaced earlier dual-agonist benchmarks. In a separate type 2 diabetes cohort, weight loss was more modest and gastrointestinal adverse events were notably more frequent, a signal researchers must account for when selecting a population model. The broader TRIUMPH program also covers comorbidity-focused indications including obstructive sleep apnea, knee osteoarthritis, and cardiovascular disease, making it one of the most expansive obesity drug programs currently running. The planned TRIUMPH-5 head-to-head against tirzepatide will eventually serve as a key benchmark, but that data is not yet available. Researchers interested in the evidence base can review Retatrutide clinical trial summaries and Retatrutide clinical trials data as the program evolves.

Orforglipron (Foundayo) is a non-peptide small molecule, meaning it is not built from amino acids and does not require an absorption enhancer to survive the GI tract. ATTAIN-1 phase 3 data for obesity showed meaningful weight loss with an all-oral dosing schedule. Because it engages only the GLP-1 receptor, its appetite and glycemic effects are narrower than retatrutide's triple-agonist profile.

Oral semaglutide (Wegovy pill) is a peptide reformulated with the absorption enhancer SNAC. It is broadly available in the US market as of 2026 but carries more modest weight-loss numbers in published cohorts compared to injectable semaglutide or the newer agents. Its primary research value lies in head-to-head oral comparisons.

For a broader orientation to peptide classes and how GLP-3 compounds fit alongside these agents, the Peptides 101 for research-use only buyers resource provides useful structural context.


Core Variables Researchers Must Encode When Comparing Retatrutide, GLP-1 Pills, and Small-Molecule Weight-Loss Options

Core Variables Researchers Must Encode When Comparing Retatrutide, GLP-1 Pills, and Small-Molecule Weight-Loss Options

Selecting a model without explicitly defining the following variables produces data that cannot be interpreted cleanly.

Receptor Target Depth

"A single receptor target and a triple receptor target are not interchangeable models, even when the primary endpoint is body weight."

The table below summarizes receptor engagement across the three compound classes:

Compound GLP-1 GIP Glucagon Delivery
Retatrutide Yes Yes Yes Injectable
Orforglipron Yes No No Oral (non-peptide)
Oral Semaglutide Yes No No Oral (peptide + SNAC)

Glucagon receptor activation drives additional energy expenditure beyond appetite suppression. Researchers modeling thermogenic pathways must account for this difference. Researchers sourcing retatrutide for in-vitro or preclinical work can reference GLP-3 Reta 10mg 99% pure third-party tested or GLP-3 Reta 30mg for sale for research-grade supply options.

Oral Exposure and Bioavailability

Oral bioavailability varies dramatically between a non-peptide small molecule and a peptide-based oral agent. Orforglipron achieves systemic exposure without an absorption enhancer, producing a cleaner pharmacokinetic curve. Oral semaglutide depends on SNAC to open tight junctions in the gastric mucosa, which introduces variability based on food timing and gastric pH. Researchers designing oral exposure models must encode this difference explicitly in their protocols.

Glycemic vs. Weight Endpoints

Retatrutide's type 2 diabetes cohort showed that glycemic and weight outcomes do not move in parallel. Models built around HbA1c reduction require different dose-escalation assumptions than models built around percent body weight change. Researchers should not assume that a compound's obesity-trial weight-loss magnitude will replicate in a glycemic-focused design.

Tolerability Variables

Gastrointestinal adverse events, nausea, vomiting, diarrhea, appear across all three agents but with different frequency profiles. Retatrutide's diabetes cohort showed notably higher GI event rates than its obesity cohort, likely reflecting dose-escalation speed and baseline metabolic status. Any comparative model must pre-specify tolerability endpoints rather than treating them as secondary observations.


Regulatory Status and Research-Use Considerations in 2026

Regulatory Status and Research-Use Considerations in 2026

As of 2026, orforglipron (Foundayo) has received regulatory approval for obesity, making it the first non-peptide oral GLP-1 agonist to reach that status. Oral semaglutide for obesity is also approved and commercially available in the US. Retatrutide remains in phase 3 trials and has not yet received approval; it is available only as a research compound through verified research-grade suppliers.

This distinction matters for study design. Approved agents can be studied in clinical settings with standard IRB frameworks. Research compounds require additional documentation, sourcing from qualified suppliers, and strict adherence to research-use-only protocols.

Researchers building comparative models should also consider how retatrutide's comorbidity-focused TRIUMPH sub-studies (OSA, knee OA, CVD) may eventually generate approval pathways beyond obesity, expanding the range of valid research questions.

For researchers exploring related peptide mechanisms, resources on Tesamorelin dosage for fat loss and Tesamorelin before and after offer useful comparisons for growth-hormone-mediated fat metabolism models alongside GLP-1-axis compounds.


Conclusion

The question of which model to select from Retatrutide, GLP-1 Pills, and Small-Molecule Weight-Loss Options is not answered by weight-loss magnitude alone. Receptor target depth, oral bioavailability mechanism, glycemic versus weight endpoints, tolerability profiles, and current regulatory status all shape what a given compound can and cannot tell a researcher.

Actionable next steps for researchers:

  1. Define the primary endpoint first, weight loss, glycemic control, or comorbidity reduction, before selecting a compound.
  2. Map receptor targets explicitly; do not treat GLP-1-only agents as equivalent to triple agonists in mechanistic models.
  3. Account for oral exposure variability when designing pharmacokinetic comparisons between peptide-based and non-peptide oral agents.
  4. Pre-specify tolerability endpoints, particularly in diabetic population models where GI event rates differ from obesity cohorts.
  5. Verify regulatory status before sourcing; approved agents and research-stage compounds require different procurement and documentation protocols.

The TRIUMPH-5 head-to-head data, when available, will provide the most direct comparative benchmark in this field. Until then, rigorous model selection depends on encoding the variables above with precision.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-glp-1-pills-and-small-molecule-weight-loss-options-what-researchers.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-01 13:05:002026-10-01 13:05:00Retatrutide, GLP-1 Pills, and Small-Molecule Weight-Loss Options: What Researchers Should Compare Before Selecting a Model
Page 3 of 8‹12345›»
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top