Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: glp-1 triple agonist

Retatrutide and Sleep Apnea Research: Separating AHI, Body-Weight, Glycemic, and Respiratory Endpoints

Retatrutide and Sleep Apnea Research: Separating AHI, Body-Weight, Glycemic, and Respiratory Endpoints

November 3, 2026/0 Comments/in Uncategorized/by

Roughly one billion adults worldwide live with obstructive sleep apnea, yet until 2026 no pharmacologic agent had demonstrated large, sustained reductions in the apnea-hypopnea index (AHI) across a rigorous phase 3 program. The phase 3 TRIUMPH-1-OSA and TRIUMPH-2-OSA trials changed that picture dramatically. For researchers tracking Retatrutide and Sleep Apnea Research: Separating AHI, Body-Weight, Glycemic, and Respiratory Endpoints, the central challenge is not whether the drug works, the trial data make a strong case that it does, but how to determine why it works and which benefits are truly independent of weight loss.

Key Takeaways

  • Retatrutide, a triple GIP/GLP-1/glucagon receptor agonist, reduced AHI by up to 34.3 events/hour in participants without diabetes and up to 25.4 events/hour in those with type 2 diabetes versus placebo.
  • AHI is the prespecified primary endpoint in the TRIUMPH OSA trials; body-weight and glycemic measures are separate secondary or exploratory endpoints.
  • Researchers must model AHI changes after adjusting for concurrent weight loss and glycemic improvements to identify direct respiratory effects.
  • Additional respiratory endpoints, hypoxic burden, PROMIS sleep impairment scores, and functional-cure proportions, capture symptom relief independent of scale readouts.
  • As of late 2026, retatrutide has no regulatory approval for OSA or obesity; all findings remain investigational.

What Makes Retatrutide Uniquely Relevant to Sleep Apnea
What Makes Retatrutide Uniquely Relevant to Sleep Apnea

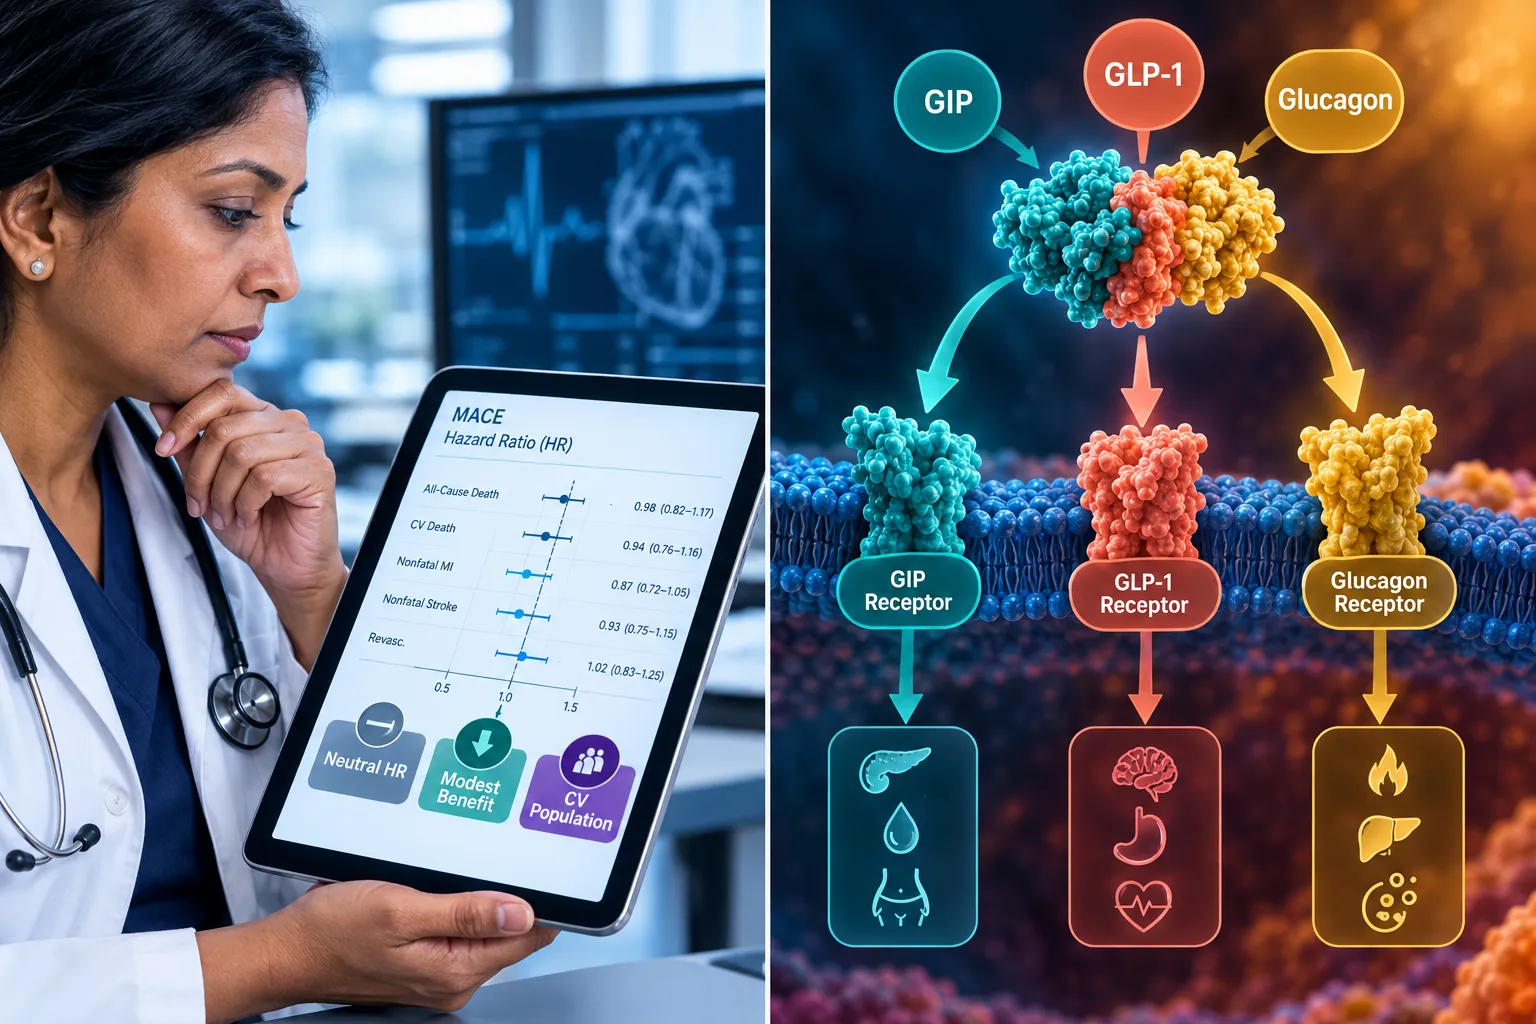
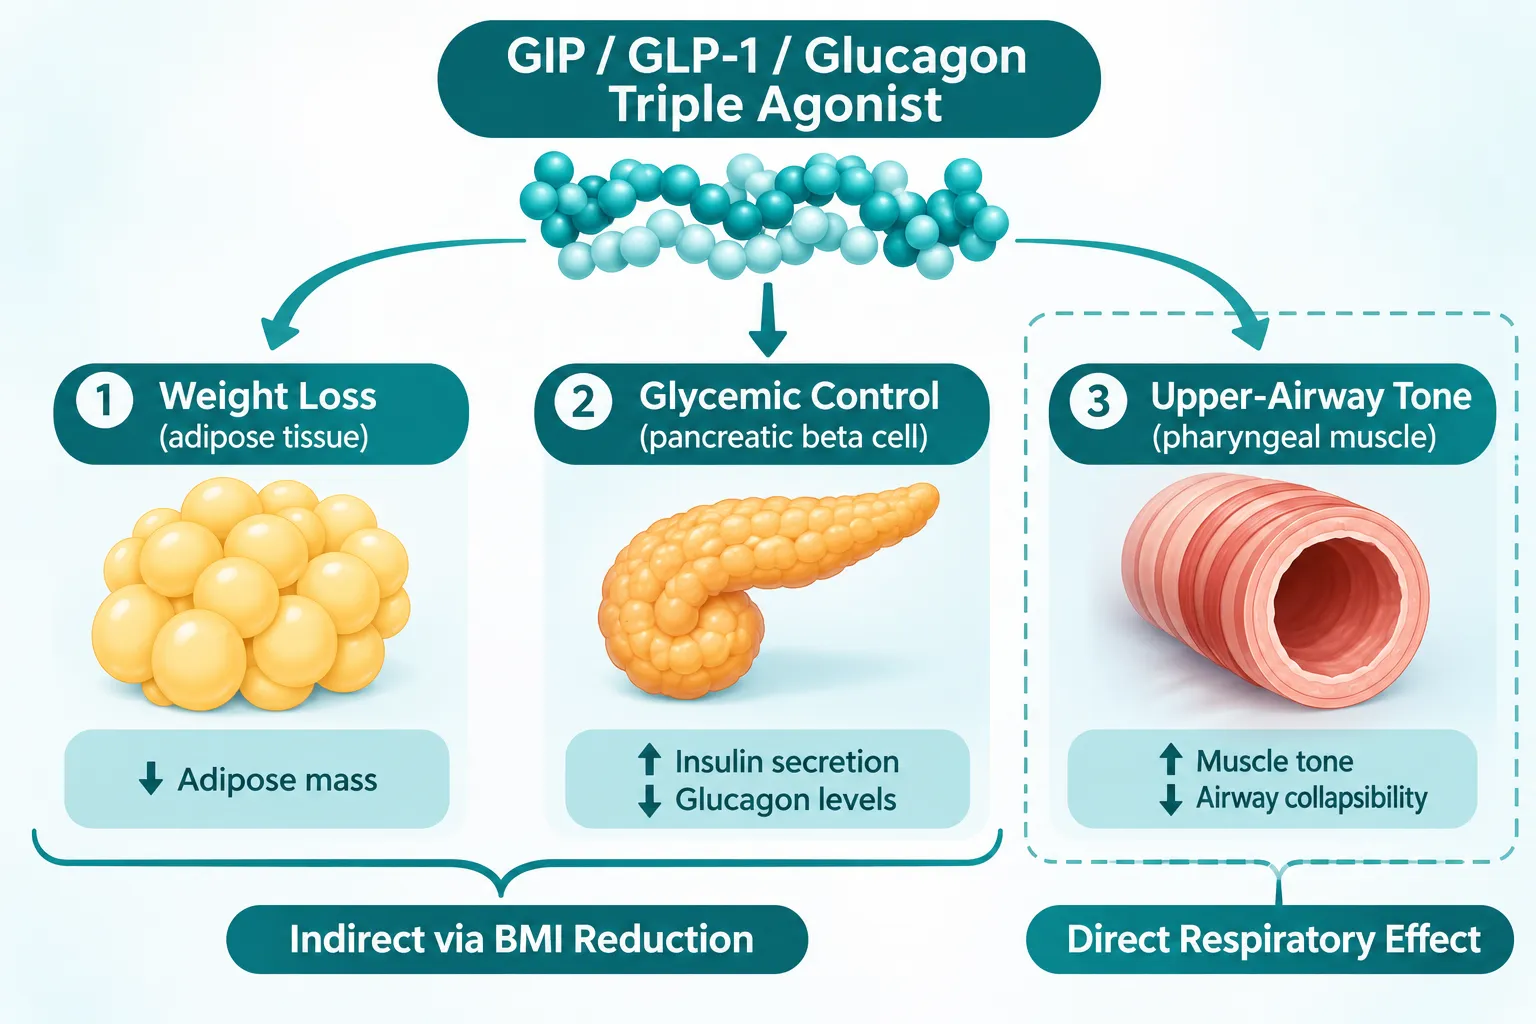
Retatrutide is a once-weekly injectable peptide that activates three receptors simultaneously: glucose-dependent insulinotropic polypeptide (GIP), glucagon-like peptide-1 (GLP-1), and glucagon. This triple mechanism drives potent weight loss, improves insulin sensitivity, and enhances fat oxidation. Phase 2 data showed roughly 24% mean weight loss at 48 weeks with the 12 mg dose, one of the largest reductions ever recorded for a pharmacologic agent.

That weight-loss magnitude matters for sleep apnea because upper-airway collapsibility is closely tied to parapharyngeal fat deposition and body mass. However, the GLP-1 and glucagon arms of the molecule may also affect ventilatory control and airway muscle tone through pathways that do not require weight change. This is the core question driving the endpoint-separation framework in retatrutide OSA research.

For context on how this agent fits within the broader incretin-peptide research landscape, see the overview of GLP-1 peptide generational research concepts and sourcing notes.


The TRIUMPH OSA Endpoint Architecture: AHI, Body-Weight, Glycemic, and Respiratory Outcomes Defined Separately
The TRIUMPH OSA Endpoint Architecture: AHI, Body-Weight, Glycemic, and Respiratory Outcomes Defined Separately

Understanding the trial design is essential before interpreting any single number.

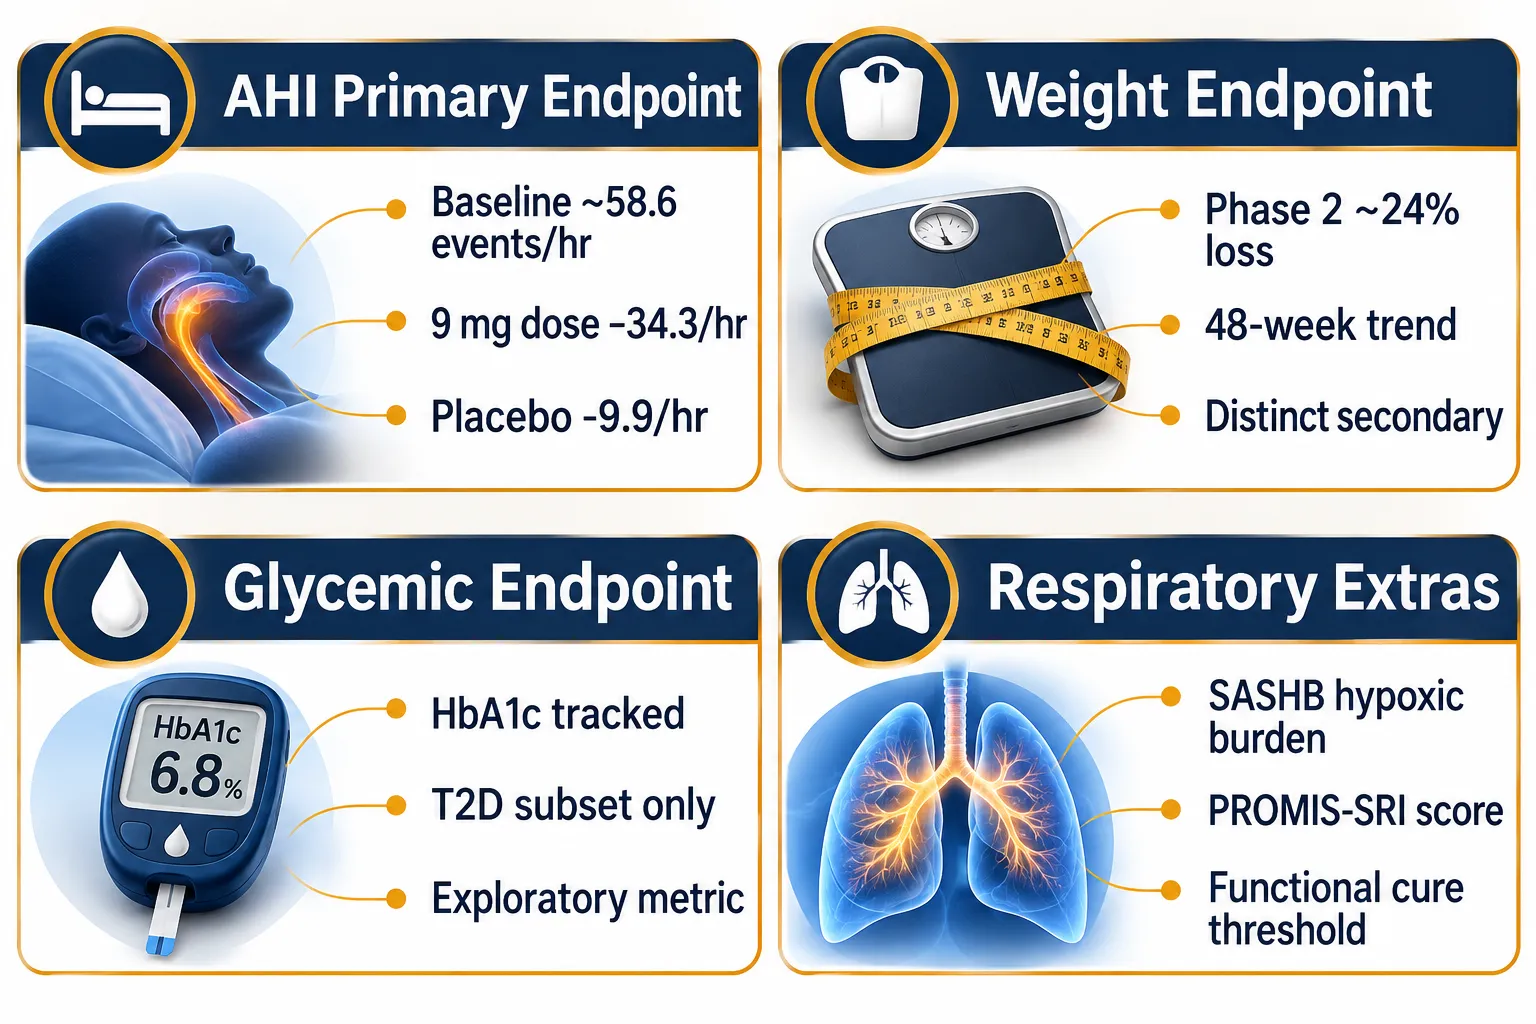
TRIUMPH-1-OSA enrolled participants with obesity or overweight plus moderate-to-severe OSA but without type 2 diabetes. TRIUMPH-2-OSA enrolled participants with obesity/overweight, OSA, and type 2 diabetes. Both trials ran for 80 weeks with three active doses (4, 9, and 12 mg) plus placebo.

Primary Endpoint: AHI

AHI, the number of apnea and hypopnea events per hour of sleep, is the prespecified primary endpoint. Results were striking:

Trial Dose AHI Change (events/hr) Placebo Change
TRIUMPH-1-OSA 4 mg -22.9 -9.9
TRIUMPH-1-OSA 9 mg -34.3 -9.9
TRIUMPH-1-OSA 12 mg -31.7 -9.9
TRIUMPH-2-OSA 9 mg -24.7 -10.3
TRIUMPH-2-OSA 12 mg -25.4 -10.3

In participants with moderate-to-severe OSA at baseline (mean ~58.6 events/hour), retatrutide reduced AHI by up to 36.1 events/hour, a 60.6% reduction from baseline.

Secondary and Exploratory Endpoints

The trial structure deliberately keeps weight and glycemic outcomes analytically distinct from sleep-apnea outcomes:

  • Weight endpoints: Percentage body-weight change from baseline, proportion achieving 5%, 10%, and 15% weight loss thresholds.
  • Glycemic endpoints (TRIUMPH-2-OSA only): HbA1c change from baseline, fasting glucose.
  • Respiratory endpoints beyond AHI: Sleep Apnea-Specific Hypoxic Burden (SASHB), proportion achieving ≥50% AHI reduction, and proportion reaching a "functional cure" (AHI below 5, or AHI 5-14 combined with Epworth Sleepiness Scale score of 10 or lower).
  • Patient-reported outcomes: PROMIS Sleep-Related Impairment (PROMIS-SRI) scores.

This separation means a participant who loses 20% of body weight and simultaneously halves their AHI can be analyzed for both outcomes, but neither is used as a covariate to define the other unless a mediation analysis is explicitly run.

Researchers interested in ongoing retatrutide clinical trial updates will find that this endpoint architecture also mirrors the master protocol entries covering knee osteoarthritis subsets, where musculoskeletal and metabolic outcomes are similarly separated.


Separating Direct Respiratory Effects from Weight-Mediated Benefits
Separating Direct Respiratory Effects from Weight-Mediated Benefits

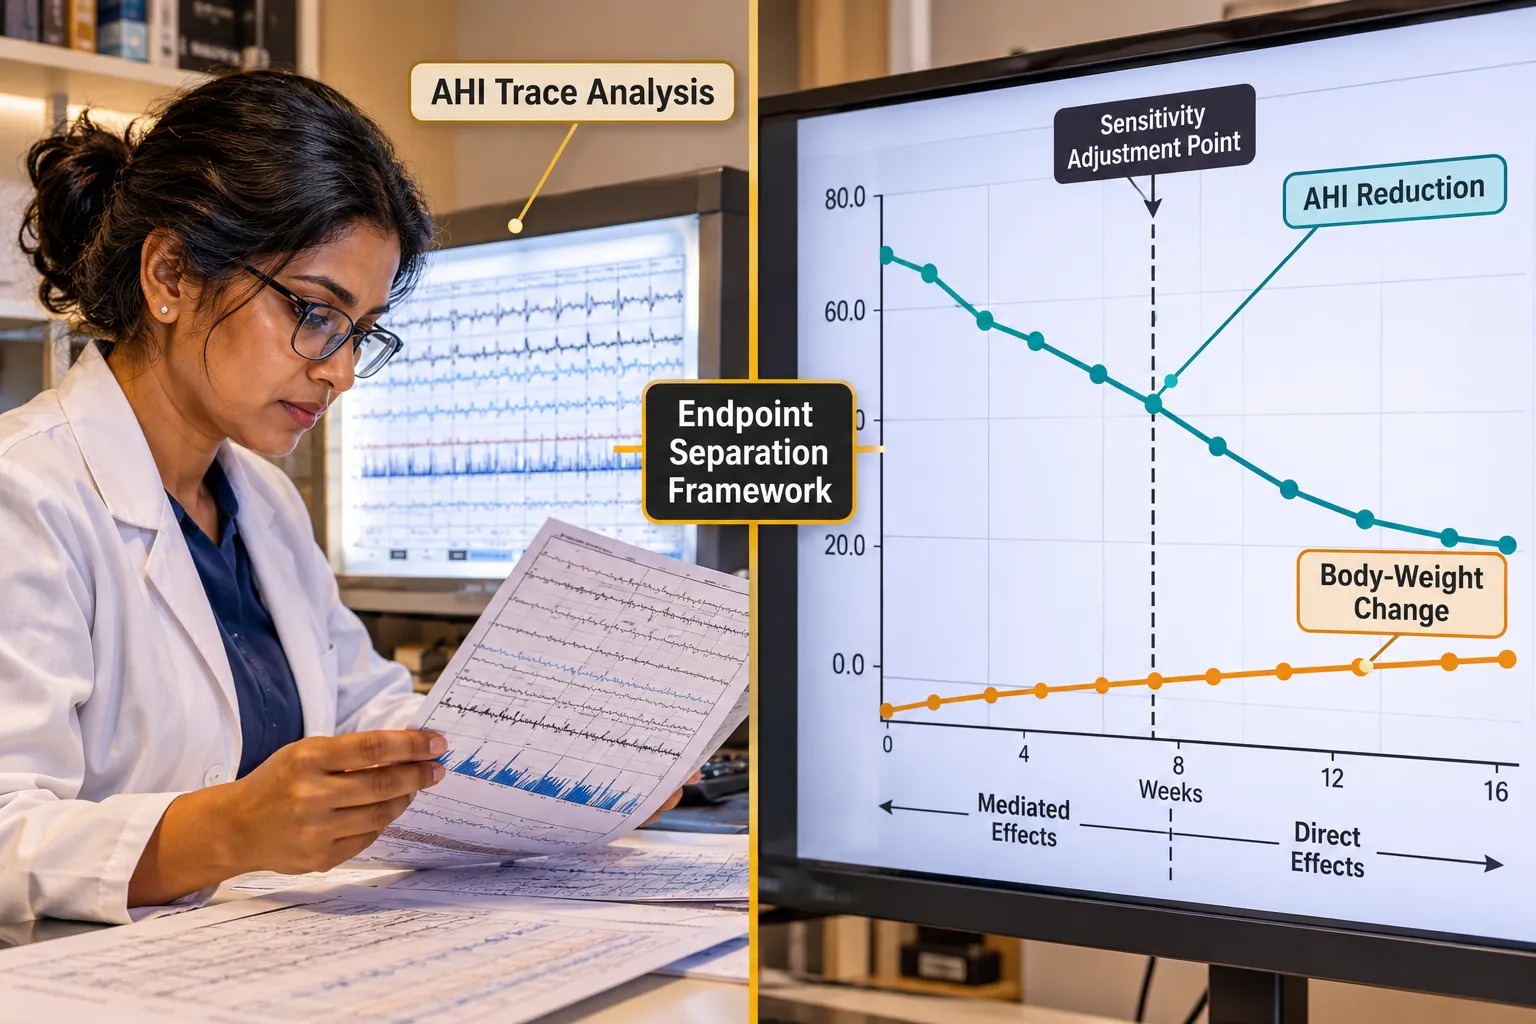
The most scientifically important question in Retatrutide and Sleep Apnea Research: Separating AHI, Body-Weight, Glycemic, and Respiratory Endpoints is whether AHI improvements persist after statistically accounting for weight loss and glycemic change.

Why This Matters

If AHI reduction is entirely explained by weight loss, retatrutide's respiratory profile is essentially identical to any potent anti-obesity agent. If AHI improves beyond what weight loss alone would predict, direct neurochemical or mechanical effects on the upper airway are implicated, a meaningfully different clinical story.

"Modeling AHI changes after adjusting for concurrent weight loss and glycemic improvements is the definitive test of whether retatrutide exerts independent effects on upper-airway collapsibility or ventilatory control."

Tools for Endpoint Separation

Researchers and trial statisticians use several approaches:

  1. Covariate-adjusted models: Include percentage weight change and HbA1c change as covariates when modeling AHI; residual AHI improvement represents the weight- and glycemia-independent fraction.
  2. Mediation analysis: Formally partition total AHI effect into a portion mediated by weight loss versus a direct pathway.
  3. Subgroup analyses by weight-loss tertile: Compare AHI outcomes among participants with minimal, moderate, and large weight loss to visualize dose-response separation.
  4. Hypoxic burden as a companion metric: SASHB captures oxygen desaturation severity in a way that is less confounded by body habitus than raw AHI, offering an additional independent respiratory signal.

The proportion achieving ≥50% AHI reduction and the functional-cure threshold are also valuable here because they represent all-or-nothing categorical outcomes that can be modeled with logistic regression including weight change as a covariate.

For researchers exploring additional metabolic-protection tools alongside this work, the SS-31 mitochondrial research themes page outlines complementary cellular-energy approaches sometimes studied in parallel with metabolic interventions.


Regulatory and Research Implications for 2026 and Beyond

Eli Lilly's likely regulatory strategy, based on publicly available investor communications and trial registrations, involves seeking multi-indication labeling covering obesity/overweight and OSA, potentially alongside knee osteoarthritis. For an OSA submission, regulators will likely scrutinize:

  • Magnitude and durability of AHI reduction over 80 weeks
  • Independence of AHI benefit from weight and glycemic changes in prespecified sensitivity analyses
  • Hypoxic burden and patient-reported sleep impairment as supporting endpoints capturing meaningful symptom relief

For researchers sourcing the compound for preclinical endpoint-testing work, the Reta 10mg product page and GLP3 RETA CAG 10mg product listing provide formulation details relevant to study design. Those planning longer-term procurement can also review how to buy Reta for sourcing guidance.

As of late 2026, retatrutide has no approved indication for OSA or obesity. All data discussed here are from investigational trials and should not be interpreted as clinical guidance.


Conclusion

Retatrutide and Sleep Apnea Research: Separating AHI, Body-Weight, Glycemic, and Respiratory Endpoints is not merely an academic exercise, it defines how the field will understand, approve, and eventually prescribe this class of agent for sleep-disordered breathing. The TRIUMPH trial architecture is explicitly built for this separation, with AHI as the primary outcome and weight/glycemic metrics tracked in parallel rather than conflated.

Actionable next steps for researchers:

  • Design mediation and covariate-adjustment analyses before unblinding to avoid post-hoc inflation.
  • Treat SASHB and PROMIS-SRI as primary companion metrics alongside raw AHI, since they capture aspects of respiratory impairment that body-weight change does not explain.
  • Monitor Lilly's regulatory submissions closely; the sensitivity analyses submitted to the FDA will be the definitive public record of how much AHI benefit survives weight-loss adjustment.
  • Preclinical researchers should align endpoint panels to mirror trial endpoints, AHI analogs, hypoxic-burden surrogates, and metabolic markers, so translational comparisons remain valid.

The convergence of triple-receptor pharmacology, rigorous endpoint separation, and 80-week durability data positions retatrutide as a potential landmark in sleep-apnea pharmacotherapy. Whether that potential translates into regulatory approval depends squarely on how cleanly the respiratory endpoints stand apart from the weight story.

https://www.puretestedpeptides.com/wp-content/uploads/2026/11/retatrutide-and-sleep-apnea-research-separating-ahi-body-weight-glycemic-and-res.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-11-03 14:06:552026-11-03 14:06:55Retatrutide and Sleep Apnea Research: Separating AHI, Body-Weight, Glycemic, and Respiratory Endpoints

Retatrutide Research After New Trial Readouts: Which Biomarkers Should Be Added Beyond Weight and A1C?

November 2, 2026/0 Comments/in Uncategorized/by

Retatrutide Research After New Trial Readouts: Which Biomarkers Should Be Added Beyond Weight and A1C?

Phase 3 trial data released throughout 2026 confirmed what early observers suspected: retatrutide is not simply another incremental obesity drug. Adults without diabetes lost up to 25% of body weight over 80 weeks, while those with type 2 diabetes lost nearly 21%, more than double the reduction seen with semaglutide in a head-to-head comparison. With results this dramatic, the conversation around retatrutide research after new trial readouts must now move beyond weight and A1C toward the broader biomarker landscape these outcomes demand.

Key Takeaways

  • Retatrutide Phase 3 trials show weight losses up to 25% and A1C reductions up to 2.2%, setting a new efficacy bar.
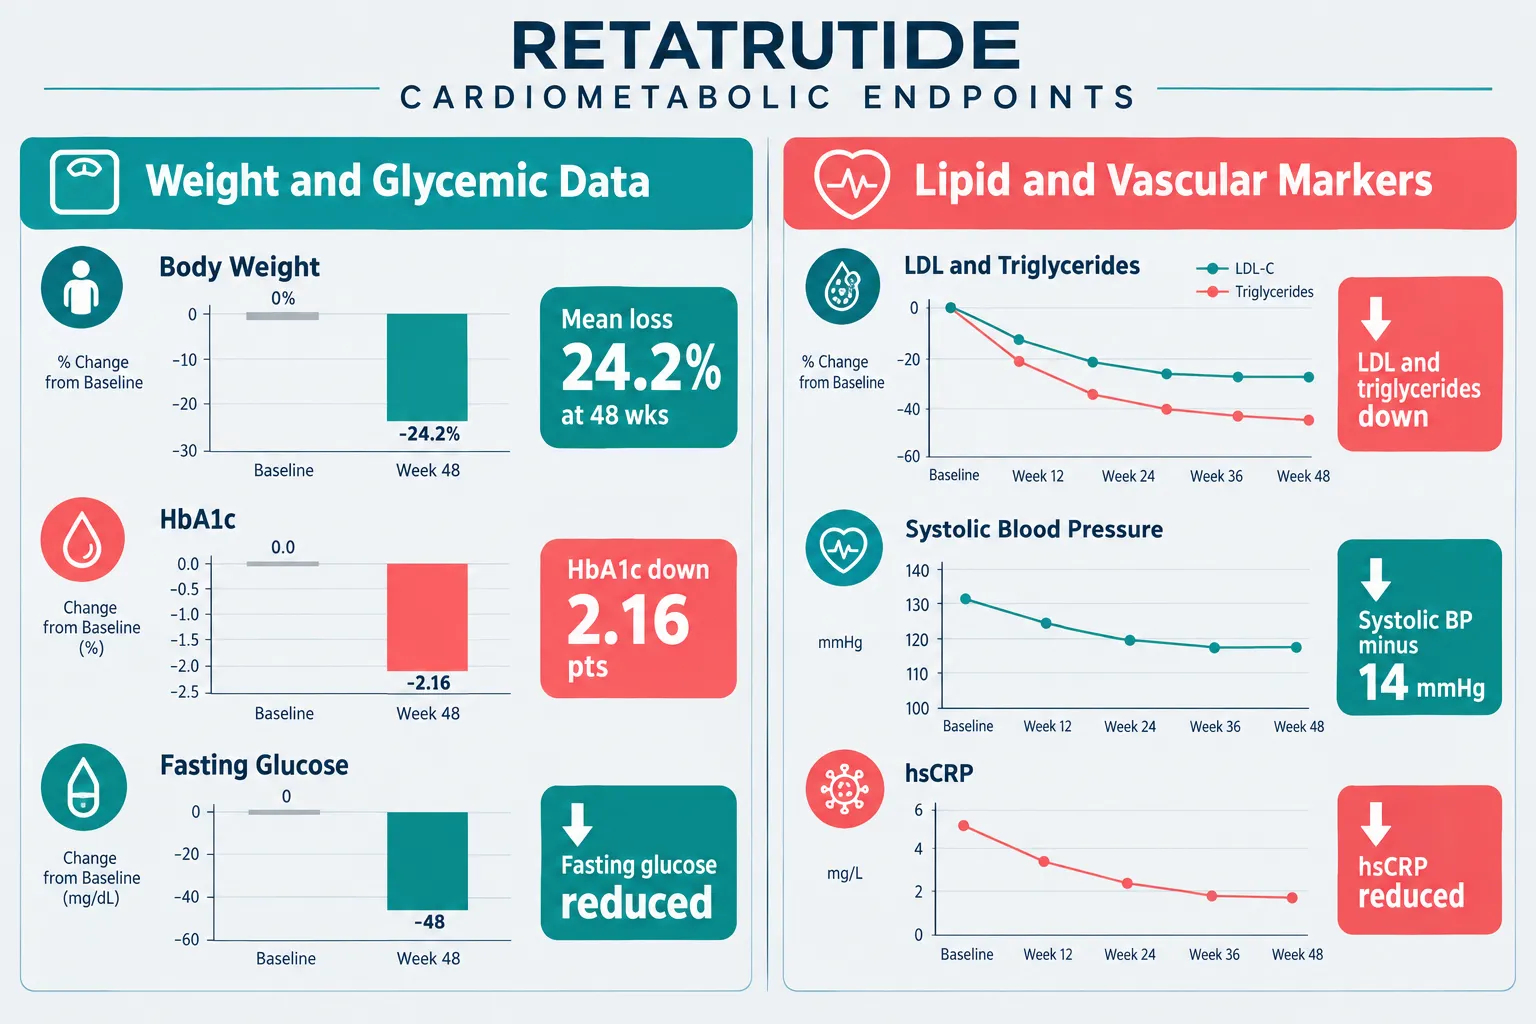
  • Triglycerides fell by up to 41%, non-HDL cholesterol by 24%, and systolic blood pressure by over 12 mmHg, these should become standard secondary endpoints.
  • Liver fat, kidney function, body composition, and inflammatory markers are critical gaps in current reporting.
  • Gastrointestinal tolerability biomarkers and appetite hormone panels add mechanistic depth that weight alone cannot capture.
  • Systematic biomarker expansion will determine whether retatrutide's weight effect translates into long-term organ protection.

Why Weight and A1C Alone Are No Longer Sufficient

Retatrutide triple receptor mechanism infographic

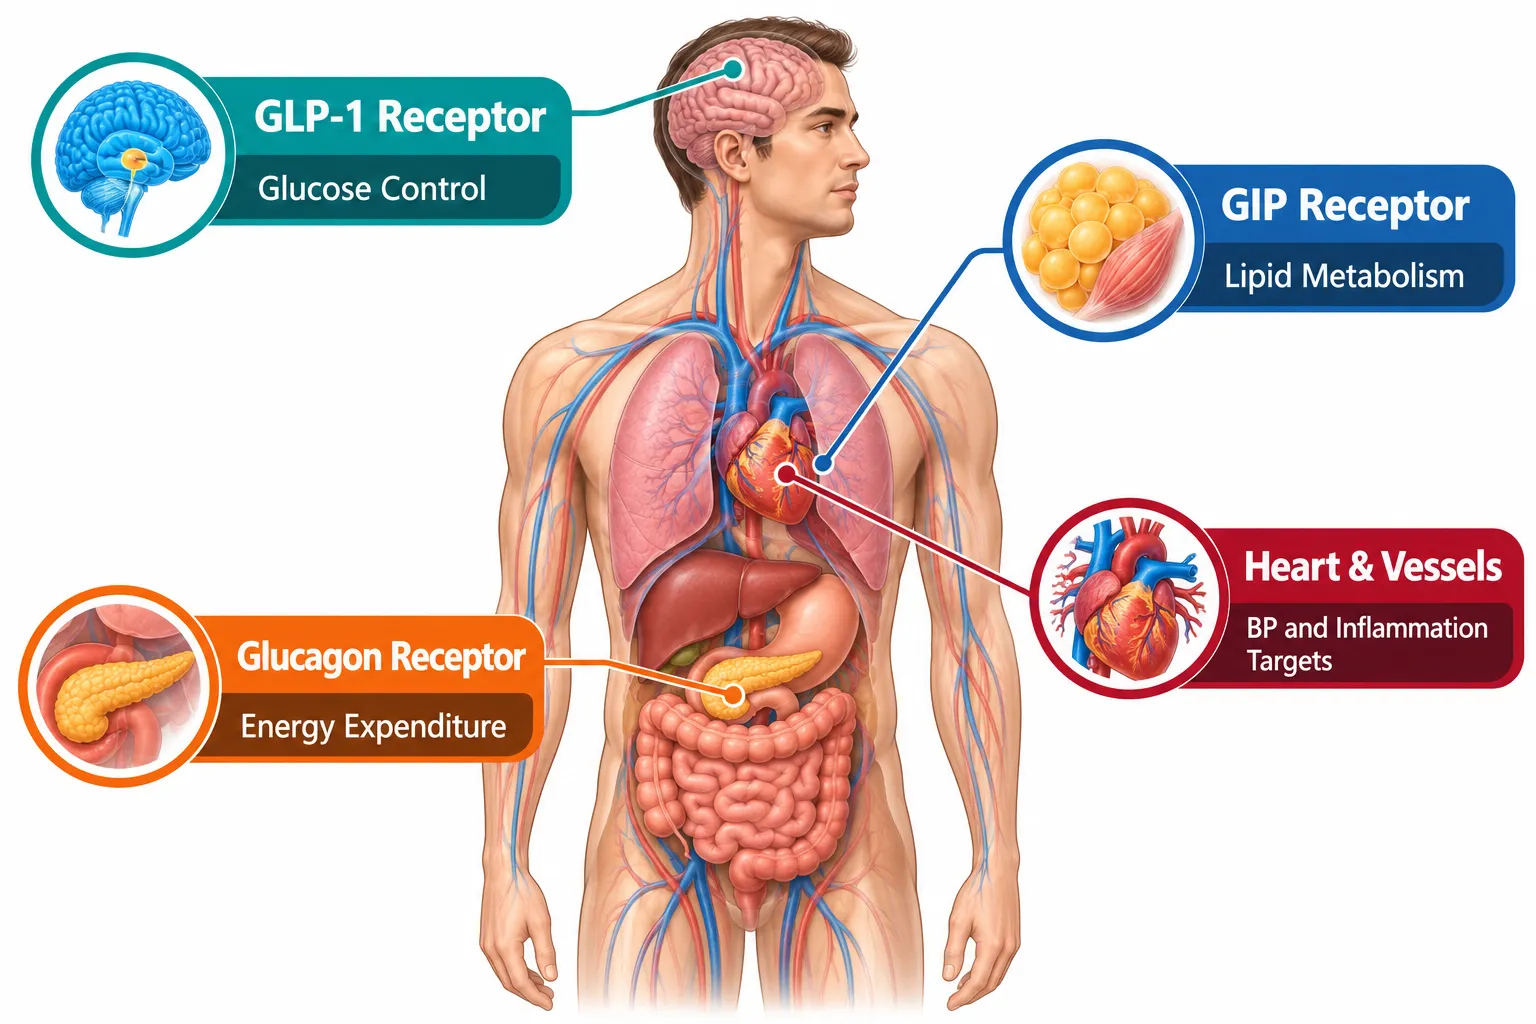
Retatrutide is a triple agonist, it activates GLP-1, GIP, and glucagon receptors simultaneously. That multi-receptor profile drives effects far beyond glycemic control and caloric regulation. Focusing only on weight and A1C in ongoing retatrutide research after new trial readouts leaves a large portion of the drug's biological footprint unmeasured.

Consider the cardiovascular signal already visible in published data. In the TRIUMPH-1 program, retatrutide reduced systolic blood pressure by 12.3 mmHg and trimmed waist circumference significantly alongside its weight effect. These are not secondary curiosities, they are independent cardiovascular risk factors. Researchers and clinicians tracking only scale weight and fasting glucose are missing the variables that will ultimately determine whether this drug reduces heart attacks and strokes.

For researchers sourcing the peptide, options like GLP3 Reta 20mg are available for preclinical investigation contexts, with additional formats catalogued under Reta 30mg for varying study designs.


Cardiometabolic Biomarkers: The Most Urgent Addition

Cardiometabolic biomarker monitoring protocol flowchart

The lipid data from retatrutide trials is striking. Across both the obesity-only and type 2 diabetes populations, triglycerides dropped by 39-41% and non-HDL cholesterol fell by approximately 20-24%. In the head-to-head comparison with semaglutide, retatrutide produced greater reductions in both of these atherogenic markers, as well as greater blood pressure lowering.

Why non-HDL cholesterol matters more than LDL alone: Non-HDL cholesterol captures all atherogenic lipoprotein particles, LDL, VLDL, IDL, and remnant lipoproteins. It is a stronger predictor of cardiovascular events than LDL in people with elevated triglycerides, which is precisely the population most likely to use retatrutide.

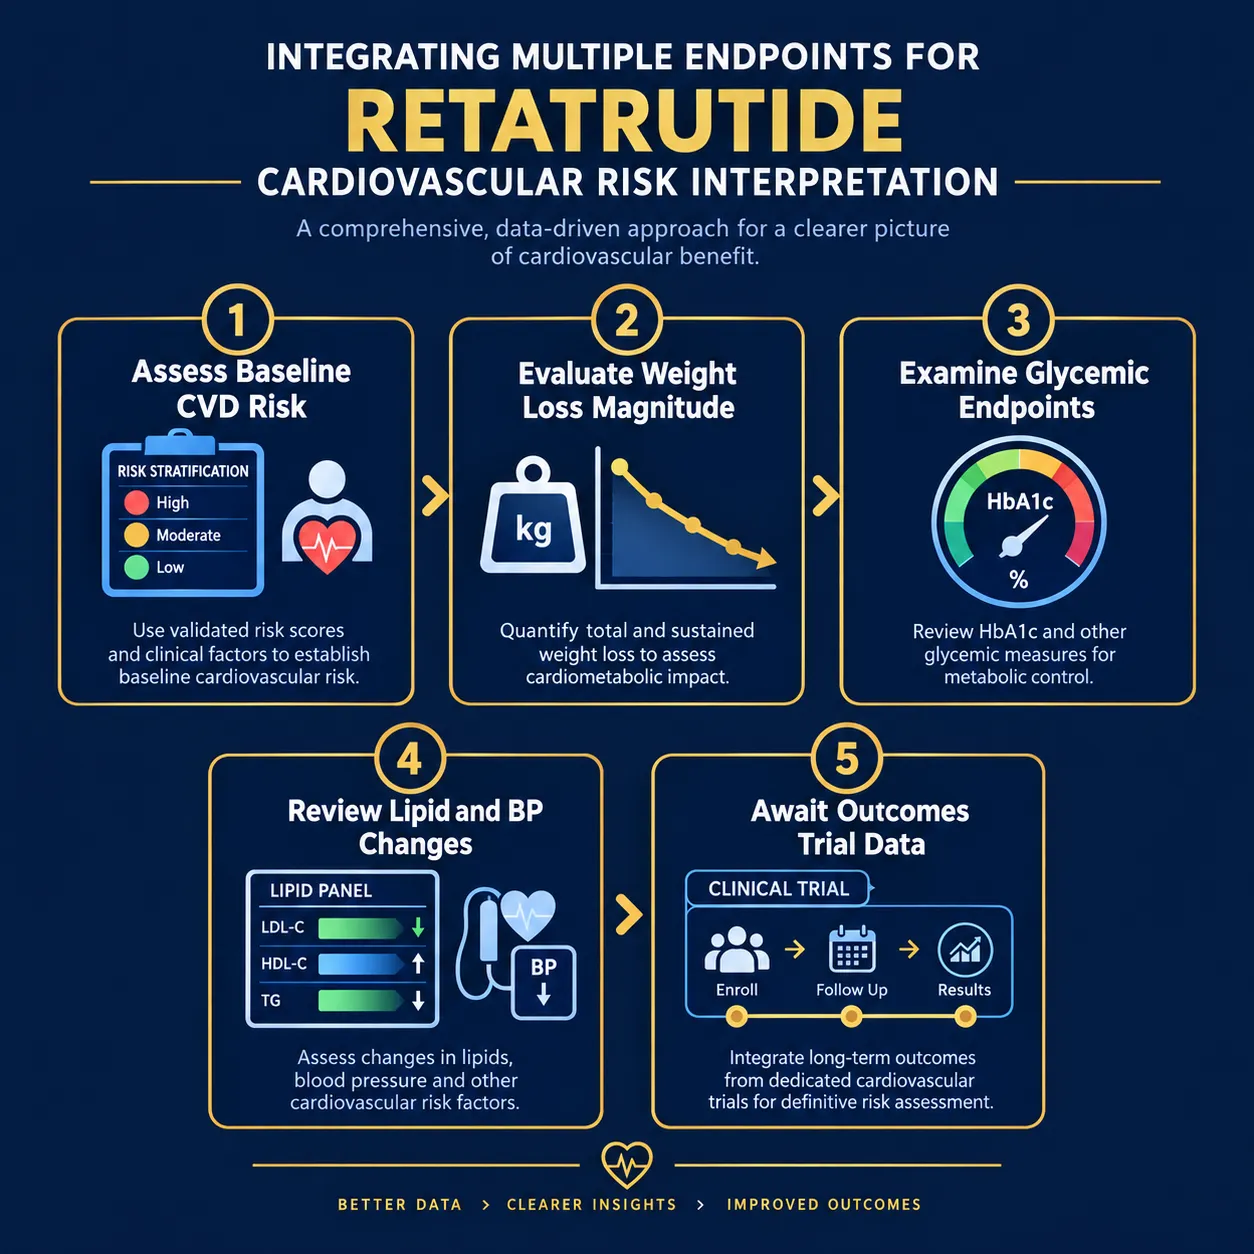
Recommended Cardiometabolic Biomarker Panel

Biomarker Why It Matters Measurement Method
Triglycerides Direct atherogenic risk; already showing 40%+ drops Fasting blood panel
Non-HDL Cholesterol Captures all atherogenic particles Calculated from lipid panel
ApoB Particle count; gold standard for CV risk Blood draw
Systolic Blood Pressure Independent CV risk factor Office/ambulatory reading
hsCRP Low-grade inflammation marker Blood draw

Apolipoprotein B (ApoB) deserves special mention. It provides a direct particle count that neither LDL-C nor non-HDL fully captures. Given retatrutide's glucagon receptor activity, which stimulates hepatic lipid metabolism, ApoB tracking would reveal whether the drug is genuinely clearing atherogenic particles or simply shifting lipid fractions.


Body Composition, Liver, and Kidney Biomarkers

Lean Mass Preservation

Large weight losses raise an important question: how much of what is lost is fat versus muscle? Standard scales cannot answer this. DEXA (dual-energy X-ray absorptiometry) scanning separates fat mass, lean mass, and bone density. Without it, a 25% reduction in body weight could mask significant muscle loss, a concern especially relevant in older adults.

Liver Fat: A Critical Gap

The glucagon receptor component of retatrutide has direct hepatic effects. Glucagon agonism stimulates fatty acid oxidation in the liver and may reduce hepatic fat independently of weight loss. Yet liver fat measured by MRI-PDFF (proton density fat fraction) has not been a primary endpoint in the published Phase 3 trials. Given the epidemic prevalence of metabolic dysfunction-associated steatotic liver disease (MASLD) in the obese and diabetic populations targeted by this drug, this is a significant omission.

Kidney Function

Weight loss itself improves kidney filtration, but glucagon receptor agonism also has direct renal effects. eGFR (estimated glomerular filtration rate) and UACR (urine albumin-to-creatinine ratio) should be tracked at baseline and at regular intervals. Early data suggest GLP-1 agonists have nephroprotective properties; whether retatrutide's triple mechanism amplifies this signal requires dedicated biomarker tracking.

For researchers studying mitochondrial and cellular health alongside metabolic peptides, the SS-31 mitochondrial research themes resource offers relevant mechanistic context, as does the SS-31 mechanism and research overview.


Appetite Hormones, Inflammation, and GI Tolerability

Standard vs expanded biomarker suite comparison chart

Appetite and Satiety Hormones

Retatrutide's GLP-1 and GIP components both influence appetite signaling through distinct but complementary pathways. Tracking fasting ghrelin, GLP-1, GIP, and peptide YY (PYY) levels would help explain inter-individual variability in weight response. Some patients lose 10%; others lose 25%. Hormone panel data could identify responders earlier and guide dose optimization.

Inflammatory Biomarkers

IL-6 and hsCRP are markers of systemic low-grade inflammation, a key driver of insulin resistance and cardiovascular disease. Both are elevated in obesity. If retatrutide's weight reduction is accompanied by genuine anti-inflammatory effects (separate from the mechanical effect of losing fat tissue), this would strengthen the case for its use as a cardiometabolic therapy, not just an obesity drug.

Gastrointestinal Tolerability

Nausea and vomiting are the most common reasons participants reduce or discontinue GLP-1-based therapies. Patient-reported outcome (PRO) scales, such as the Nausea and Vomiting Symptom Questionnaire, alongside caloric intake diaries would allow researchers to distinguish drug-driven appetite suppression from drug-induced GI distress. These are clinically different mechanisms with very different long-term implications.

Researchers interested in complementary peptide research may also find value in reviewing IPA Sermorelin stack research for context on growth hormone-adjacent hormonal signaling.


Conclusion

The 2026 Phase 3 readouts for retatrutide have set a new benchmark for metabolic intervention. But retatrutide research after new trial readouts: which biomarkers should be added beyond weight and A1C?, is now the defining question for the next phase of study. The drug's triple receptor mechanism touches lipid metabolism, hepatic fat, kidney function, blood pressure, lean mass, and inflammatory pathways simultaneously. Measuring only weight and A1C leaves the majority of that biological activity undocumented.

Actionable next steps for researchers and clinicians:

  • Add full fasting lipid panels (including ApoB and non-HDL) and ambulatory blood pressure as standard secondary endpoints in all retatrutide protocols.
  • Incorporate DEXA body composition scans to distinguish fat loss from lean mass loss.
  • Use MRI-PDFF to quantify liver fat changes, particularly given the glucagon receptor's hepatic activity.
  • Track eGFR and UACR at baseline, 24 weeks, and study end.
  • Include hsCRP, IL-6, and appetite hormone panels to capture anti-inflammatory and appetite-regulating mechanisms.
  • Standardize GI tolerability PRO instruments to separate nausea-driven intake reduction from true appetite suppression.

Researchers sourcing retatrutide for preclinical study can explore options such as buy Reta online or review Reta peptide for sale listings for research-grade material.

The biomarker framework built now will define how thoroughly this drug's full clinical value, or risk, is understood for years to come.

https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 0 0 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-11-02 14:27:042026-11-02 14:27:04Retatrutide Research After New Trial Readouts: Which Biomarkers Should Be Added Beyond Weight and A1C?
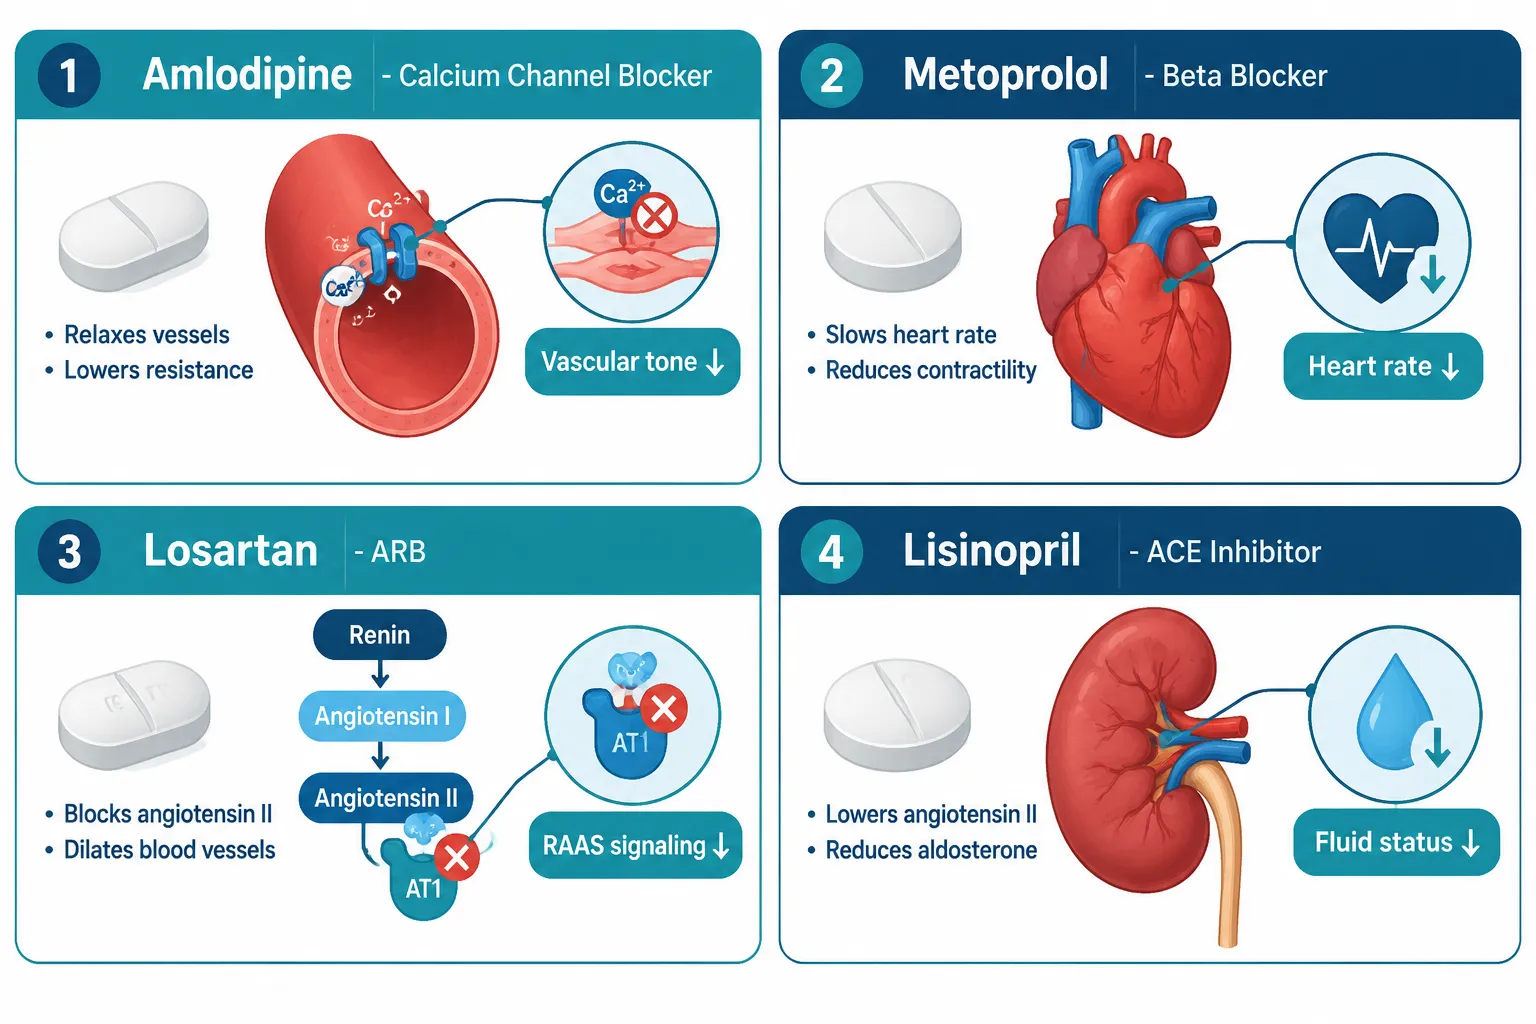
Retatrutide Research and Blood-Pressure Medications: Designing Controls for Amlodipine, Metoprolol, Losartan, and Lisinopril

Retatrutide Research and Blood-Pressure Medications: Designing Controls for Amlodipine, Metoprolol, Losartan, and Lisinopril

October 24, 2026/0 Comments/in Uncategorized/by

More than 70% of adults with obesity also carry a diagnosis of hypertension, making antihypertensive polypharmacy the statistical norm in any retatrutide clinical trial cohort. That single overlap creates a layered confounding problem: four drug classes, calcium channel blockers, beta blockers, angiotensin receptor blockers, and ACE inhibitors, each manipulate the same physiological axes that retatrutide itself perturbs. Researchers who fail to account for concurrent use of amlodipine, metoprolol, losartan, and lisinopril risk misattributing drug-class effects and producing endpoints that cannot replicate. Retatrutide research and blood-pressure medications: designing controls for amlodipine, metoprolol, losartan, and lisinopril is therefore not a secondary concern, it is a foundational methodological requirement.

Key Takeaways

  • Retatrutide independently lowers systolic blood pressure, creating overlap with antihypertensive drug effects that must be statistically separated.
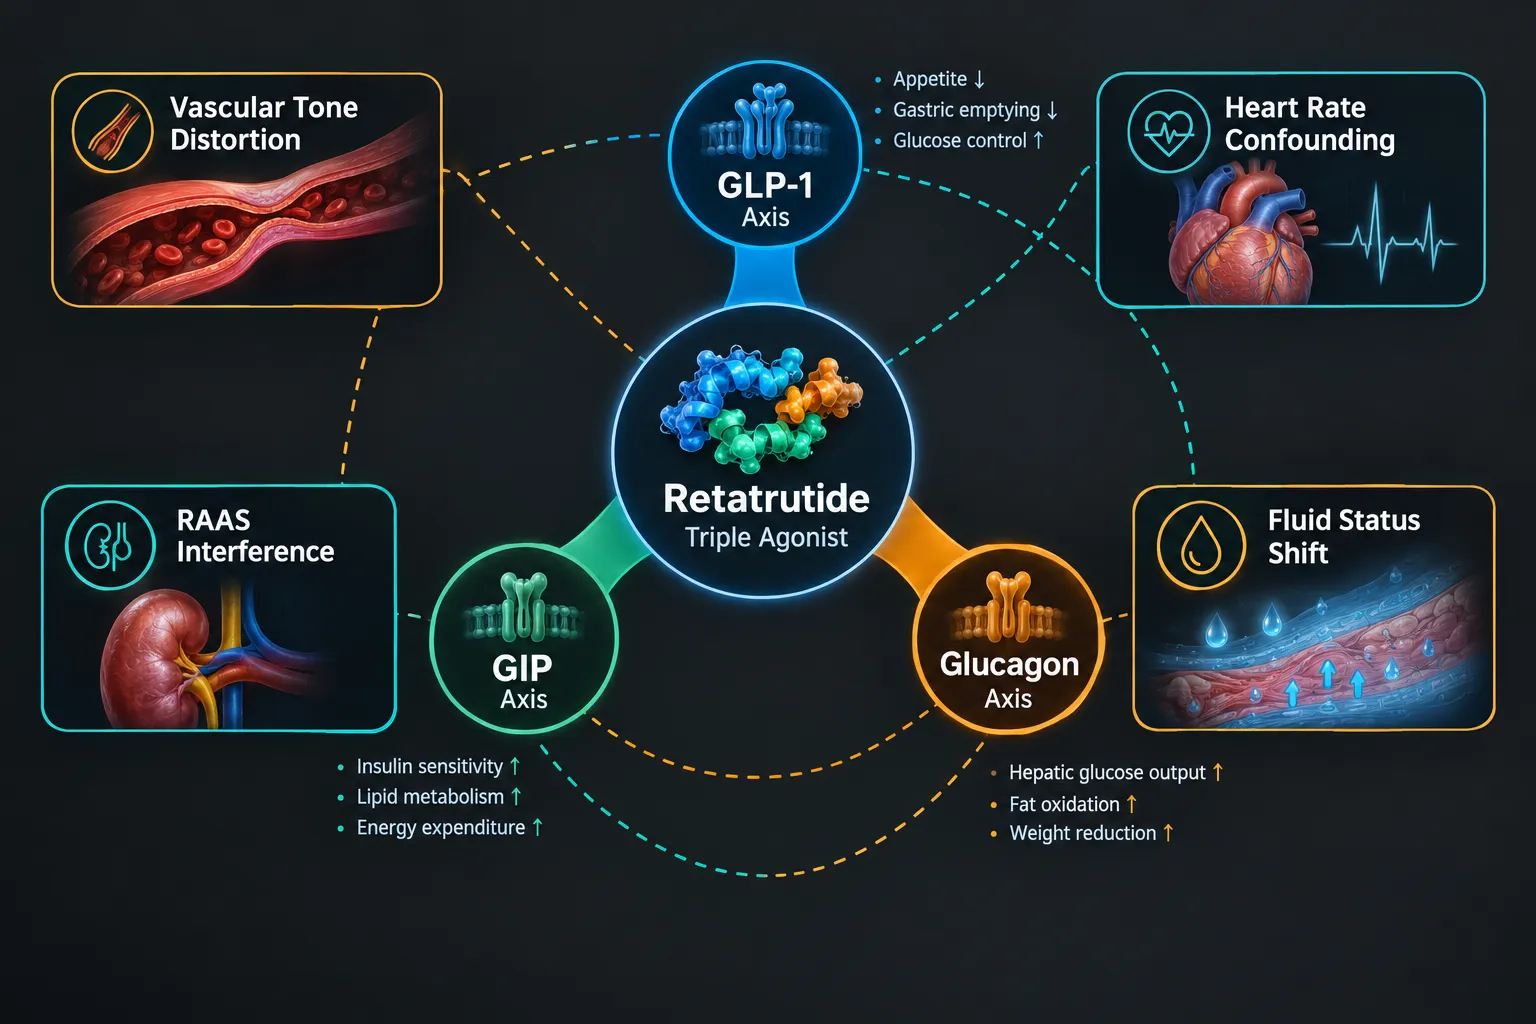
  • Amlodipine, metoprolol, losartan, and lisinopril each distort a different physiological axis, vascular tone, heart rate, renin-angiotensin signaling, and fluid status, relevant to incretin-peptide endpoints.
  • A pre-specified medication-control matrix, stratified by drug class, is essential before randomization in Phase 3 basket designs.
  • Operational hypotension monitoring protocols must be embedded into any trial combining retatrutide with multiple antihypertensive agents.
  • Analytic covariate adjustment alone is insufficient; background BP therapy must be controlled at the design stage.

Why Retatrutide's Cardiovascular Footprint Complicates Antihypertensive Controls

Retatrutide is a triple agonist at GLP-1, GIP, and glucagon receptors. In the TRIUMPH-1 obesity trial, participants achieved mean body-weight reductions exceeding 24% over 48 weeks, results that exceeded tirzepatide benchmarks and drew immediate cardiovascular attention. Weight loss of that magnitude predictably reduces systolic blood pressure through multiple downstream mechanisms: lower cardiac output demand, improved arterial compliance, reduced sympathetic tone, and natriuresis from fat-mass loss.

The problem is that each of those mechanisms shares a pathway with one or more of the four antihypertensive classes most prevalent in obese, hypertensive patients.

Why Retatrutide's Cardiovascular Footprint Complicates Antihypertensive Controls

The medication-control matrix below maps the collision points:

Drug Class Primary Axis Retatrutide Overlap Risk
Amlodipine CCB Vascular tone High, both reduce peripheral resistance
Metoprolol Beta blocker Heart rate / cardiac output Moderate, blunts GLP-1-mediated tachycardia signal
Losartan ARB Renin-angiotensin signaling High, glucagon agonism interacts with RAAS
Lisinopril ACE inhibitor Fluid status / bradykinin Moderate-High, natriuretic effects compound

GLP-1 receptor activation has well-documented vasodilatory and natriuretic properties. Adding glucagon agonism, retatrutide's distinguishing feature relative to semaglutide or tirzepatide, amplifies renin suppression, which directly collides with the mechanism of both losartan and lisinopril. Researchers sourcing material for these protocols can review GLP-3 triple agonist research planning and catalog navigation for context on how triple-agonist scaffolds are characterized ahead of controlled trials.


Designing the Control Strategy: A Drug-Class-by-Drug-Class Framework

Effective control strategy for retatrutide research and blood-pressure medications, designing controls for amlodipine, metoprolol, losartan, and lisinopril, requires intervention at three levels: study design, randomization stratification, and statistical analysis.

Designing the Control Strategy: A Drug-Class-by-Drug-Class Framework

Design-Level Controls

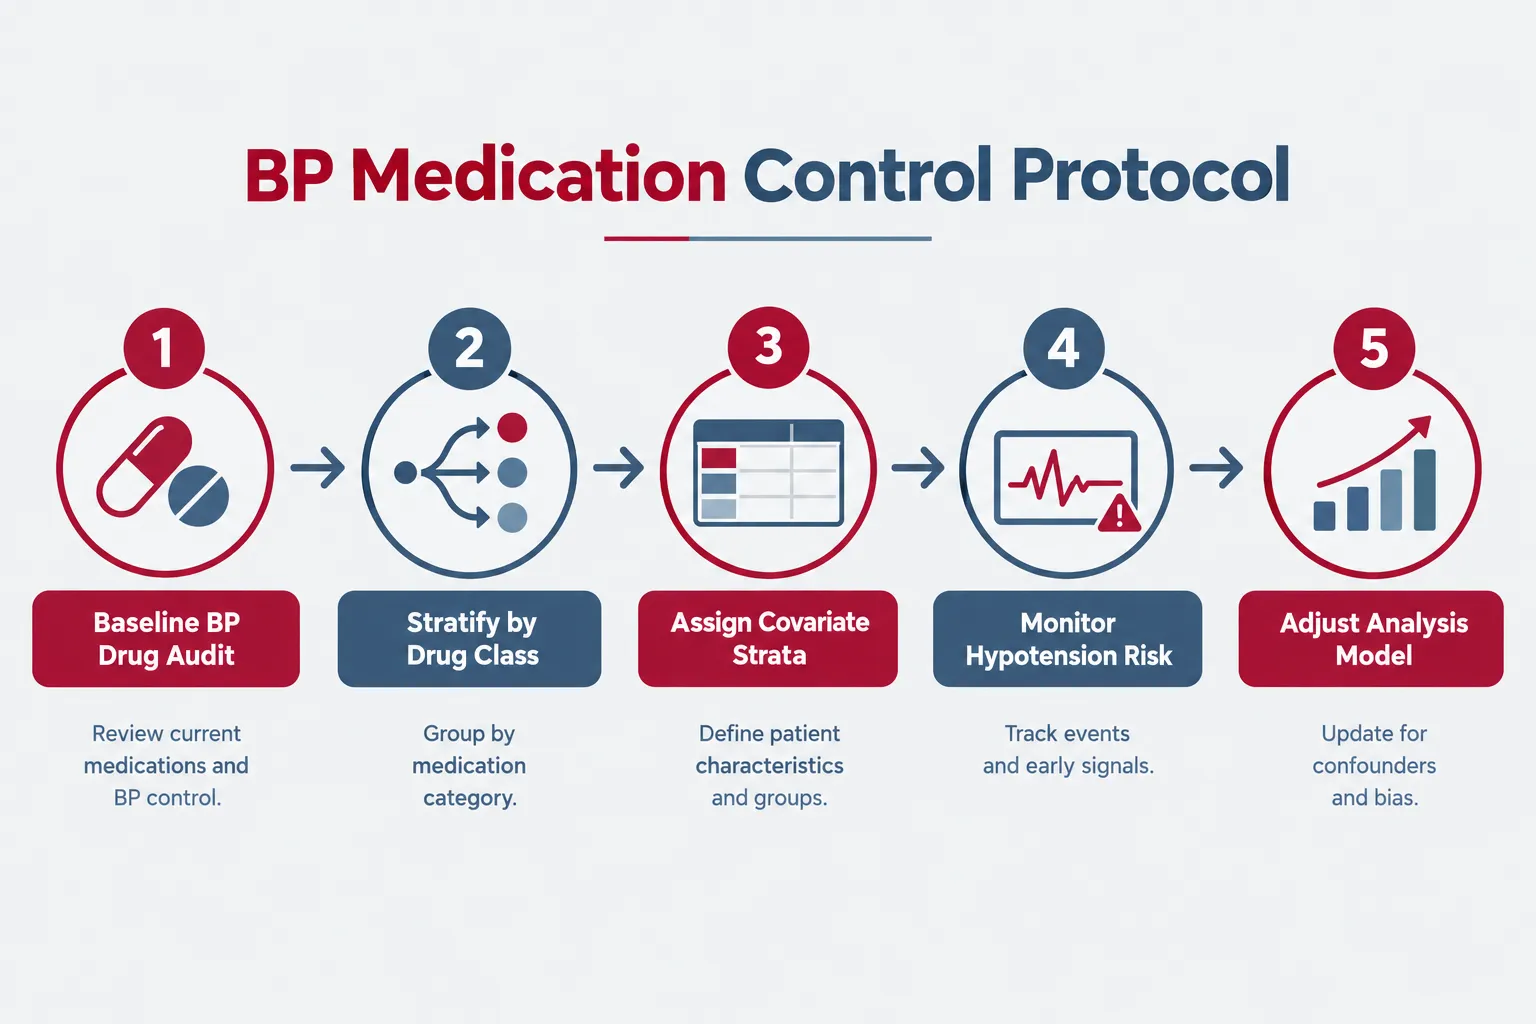
Stratified randomization is the highest-value lever. Before enrollment, participants should be classified by background antihypertensive regimen:

  • Stratum A: No BP medication
  • Stratum B: Single agent (any class)
  • Stratum C: Dual therapy including a RAAS agent (losartan or lisinopril)
  • Stratum D: Triple therapy or amlodipine plus RAAS combination

This prevents imbalanced distribution of high-overlap regimens across treatment arms. The Phase 3 TRANSCEND-T2D-1 diabetes trial highlighted cardiometabolic endpoints as primary outcomes, reinforcing the need for prospective BP-medication stratification rather than retrospective covariate adjustment.

"Retrospective covariate adjustment captures association but cannot recover the randomization balance that pre-stratification provides. For blood-pressure endpoints in retatrutide trials, design-stage control is non-negotiable."

Randomization and Analytic Controls

Pre-specified analytic models should include:

  1. Background BP drug class as a fixed effect
  2. Baseline systolic blood pressure as a continuous covariate
  3. Number of antihypertensive agents as an ordinal covariate
  4. Interaction terms for retatrutide dose × RAAS-agent use

An interaction term between retatrutide dose and concurrent RAAS blockade is especially critical. Glucagon receptor agonism reduces angiotensin II-mediated vasoconstriction independently; when layered over losartan or lisinopril, the combined systolic reduction may exceed 15-20 mmHg in high-risk participants, a magnitude that becomes a safety signal rather than an efficacy finding.

Researchers reviewing SS-31 mechanism and research context will note parallels in how mitochondrially targeted peptides also require careful cardiovascular covariate control, a reminder that this challenge extends across the incretin and peptide research landscape.

For teams sourcing research-grade material, RETA 20mg for sale and GLP-3 RETA 10mg, 99% pure, third-party tested represent catalog options with documented purity specifications relevant to preclinical control design.


Operational Safeguards Against Compounded Hypotension

The third pillar of retatrutide research and blood-pressure medications: designing controls for amlodipine, metoprolol, losartan, and lisinopril is operational, the real-time monitoring architecture embedded in trial procedures.

Operational Safeguards Against Compounded Hypotension

Retatrutide's safety profile through Phase 2 showed no prominent BP-related adverse events at standard doses. However, that data emerged from populations that were not universally on triple antihypertensive therapy. Basket-design Phase 3 programs deliberately enroll high-risk cardiovascular populations, populations where polypharmacy is the rule.

Key operational safeguards include:

  • Mandatory seated and standing BP measurement at every visit to detect orthostatic drops, especially when amlodipine (a potent peripheral vasodilator) is co-prescribed.
  • Metoprolol-specific heart rate floor monitoring, because beta blockade masks the compensatory tachycardia that would otherwise signal hypotension onset.
  • Dose-reduction decision trees for participants on dual RAAS blockade (losartan plus lisinopril combinations, though rare, do appear in real-world cohorts).
  • Electrolyte surveillance panels at baseline and weeks 4, 12, and 24 when lisinopril or losartan is present, given retatrutide's natriuretic properties.

Metoprolol deserves specific attention. Beta-1 blockade suppresses the reflex tachycardia that normally warns both patient and clinician of falling perfusion pressure. In retatrutide trials, this means heart rate cannot serve as a hypotension early-warning indicator for participants on metoprolol. Protocols must substitute automated blood pressure trending and symptom-based triggers.

Teams building these frameworks may also find relevant control-design parallels in PT-141 peptide research context, Q&A, and controls, where receptor-specific background medications similarly alter primary endpoints.

Additional catalog resources for trial planning include buy RETA peptide and the GLP-3 RETA 20mg GSF format for researchers working across dosing ranges.


Conclusion

Retatrutide's triple-agonist mechanism produces meaningful, independent blood-pressure reduction, a genuine therapeutic signal that becomes a methodological liability when study participants arrive on amlodipine, metoprolol, losartan, lisinopril, or combinations thereof. The medication-control matrix presented here maps four distinct physiological axes, vascular tone, heart rate, renin-angiotensin signaling, and fluid status, each capable of distorting incretin-peptide endpoints if left uncontrolled.

Actionable next steps for research teams:

  1. Audit enrollment databases for antihypertensive prevalence before finalizing stratification variables.
  2. Pre-specify drug-class strata in randomization algorithms, not solely in statistical analysis plans.
  3. Embed orthostatic BP measurement and heart-rate floor monitoring in all visit procedures.
  4. Include interaction terms for RAAS-agent use in primary and sensitivity models.
  5. Plan for dose-reduction decision trees that account for compounded vasodilation from amlodipine plus retatrutide co-exposure.

As Phase 3 data mature and cardiovascular outcomes trials expand, regulatory guidance on antihypertensive co-medication controls for incretin-class agents is expected to become more prescriptive. Research teams that build these controls into their designs now will be best positioned to produce replicable, interpretable blood-pressure endpoints.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-research-and-blood-pressure-medications-designing-controls-for-amlod.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-24 13:05:222026-10-24 13:05:22Retatrutide Research and Blood-Pressure Medications: Designing Controls for Amlodipine, Metoprolol, Losartan, and Lisinopril
Retatrutide 2026 Trial Data: Research Implications for Sleep Apnea, Osteoarthritis, and Metabolic Endpoints

Retatrutide 2026 Trial Data: Research Implications for Sleep Apnea, Osteoarthritis, and Metabolic Endpoints

October 20, 2026/0 Comments/in Uncategorized/by

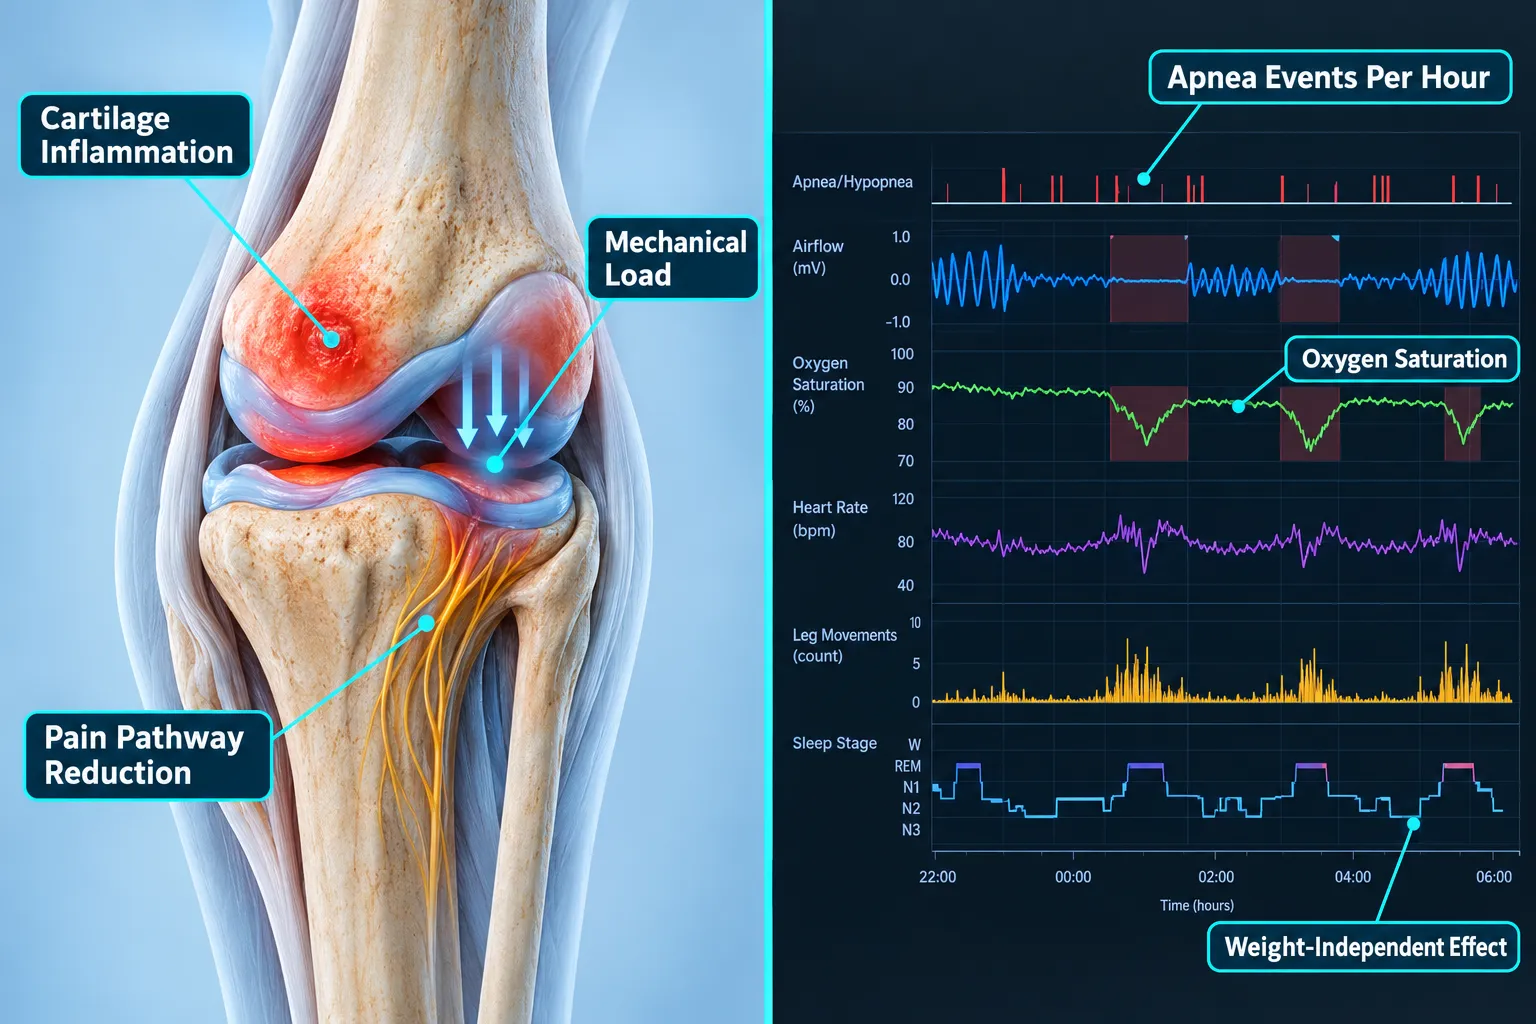
Obese adults with severe obstructive sleep apnea saw apnea event frequencies drop by more than half in the TRIUMPH-1 trial, a result that researchers say cannot be explained by weight loss alone. This single finding reframes how scientists and clinicians should interpret Retatrutide 2026 Trial Data: Research Implications for Sleep Apnea, Osteoarthritis, and Metabolic Endpoints, pushing the field toward measuring weight-independent biological effects alongside the expected metabolic gains.

Key Takeaways

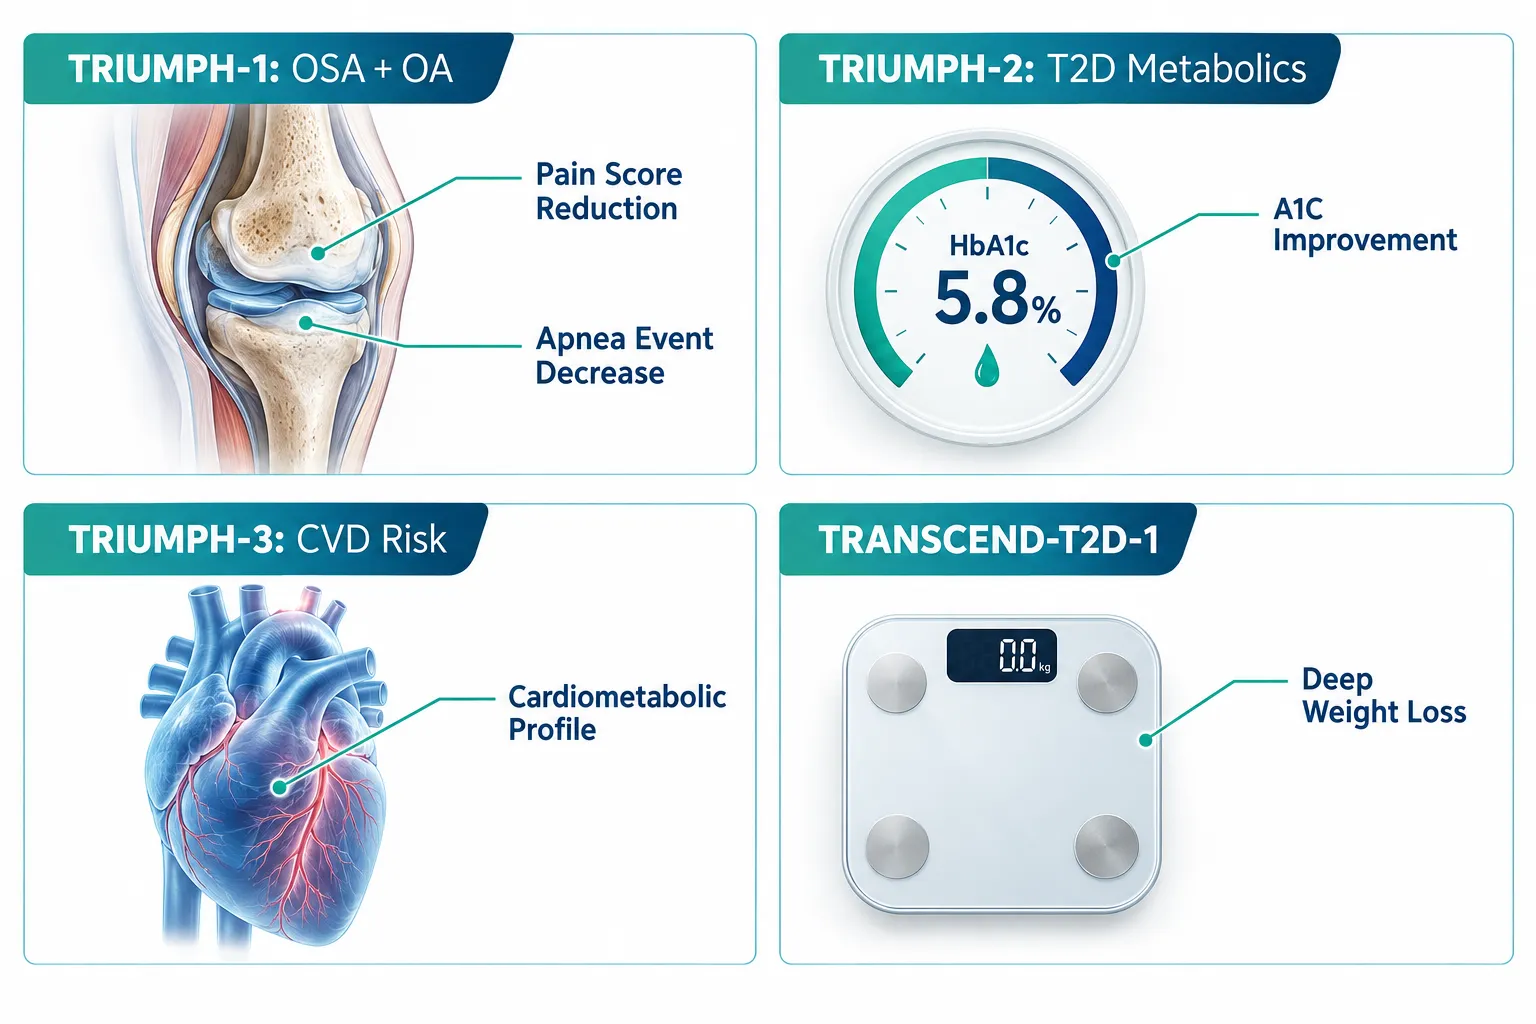
  • Retatrutide's TRIUMPH program covers sleep apnea, knee osteoarthritis, type 2 diabetes, and cardiovascular disease as distinct trial endpoints.
  • TRIUMPH-1 showed large improvements in OSA severity and knee pain that appear to exceed what weight reduction alone would predict.
  • Metabolic endpoints including A1C, fasting glucose, and lipid panels showed clinically meaningful changes across TRIUMPH-2, TRIUMPH-3, and TRANSCEND-T2D-1.
  • Researchers are now encouraged to track patient-reported outcomes, apnea event indices, and joint pain scores as primary endpoints, not secondary measures.
  • Regulatory momentum is building toward a Biologics License Application, making 2026 a pivotal year for retatrutide research translation.

What the TRIUMPH Program Reveals About Retatrutide's Scope

The TRIUMPH program is the largest coordinated effort to evaluate retatrutide across multiple comorbidity domains. Spanning more than 80 weeks in its primary arm, TRIUMPH-1 enrolled adults with obesity, confirmed obstructive sleep apnea, and knee osteoarthritis, three conditions that frequently cluster together but have rarely been studied as co-primary endpoints in a single trial.

What the TRIUMPH Program Reveals About Retatrutide's Scope

Retatrutide is a triple agonist that activates GIP, GLP-1, and glucagon receptors simultaneously. This mechanism goes beyond the dual-agonist approach used by tirzepatide and produces deeper, faster weight reduction in early dose-escalation studies. Explore ongoing retatrutide clinical trial summaries for a broader view of the trial landscape.

Why this matters for researchers: Most obesity trials treat comorbidity improvement as a secondary benefit. The TRIUMPH design elevates sleep apnea severity and osteoarthritis pain to co-primary status, creating a richer dataset for isolating which effects are driven by fat loss and which may reflect direct receptor-mediated tissue responses.


Sleep Apnea and Osteoarthritis: Reading the Weight-Independent Signals

OSA Findings From TRIUMPH-1

In TRIUMPH-1, participants experienced reductions in the Apnea-Hypopnea Index (AHI) that exceeded what previous bariatric surgery literature would predict for equivalent weight loss. Specifically, the magnitude of OSA improvement tracked ahead of the weight-loss curve at interim time points, suggesting early receptor-level effects on upper airway tone or inflammatory signaling.

Researchers should note three things:

  1. AHI reductions were sustained through week 80, not just at peak weight loss.
  2. Patient-reported sleep quality scores improved independently of polysomnography-confirmed AHI changes.
  3. A subset of participants with only moderate weight loss still showed clinically significant OSA improvement.

This pattern calls for future trials to include continuous oxygen saturation monitoring and patient-reported outcome measures (PROMs) as standard endpoints rather than optional add-ons.

Osteoarthritis Pain and Mechanical Load

Knee osteoarthritis results from TRIUMPH-1 showed statistically significant reductions in WOMAC pain scores. While reduced body weight lowers mechanical joint load, the improvement rate at early time points, before substantial weight loss had occurred, suggests an anti-inflammatory component tied to GLP-1 receptor activity in synovial tissue.

For the broader research community, this implies that visceral fat research frameworks need to account for adipokine changes as a separate causal pathway from mechanical unloading.

Pull Quote: "Osteoarthritis pain improved before the scale moved significantly, a signal researchers cannot afford to ignore."

Osteoarthritis Pain and Mechanical Load


Metabolic Endpoints Across TRIUMPH-2, TRIUMPH-3, and TRANSCEND-T2D-1

The Retatrutide 2026 Trial Data: Research Implications for Sleep Apnea, Osteoarthritis, and Metabolic Endpoints landscape extends well beyond structural comorbidities. Three additional trials address metabolic disease directly.

Trial Population Key Metabolic Endpoints
TRIUMPH-2 Obesity + Type 2 Diabetes A1C, fasting glucose, body weight
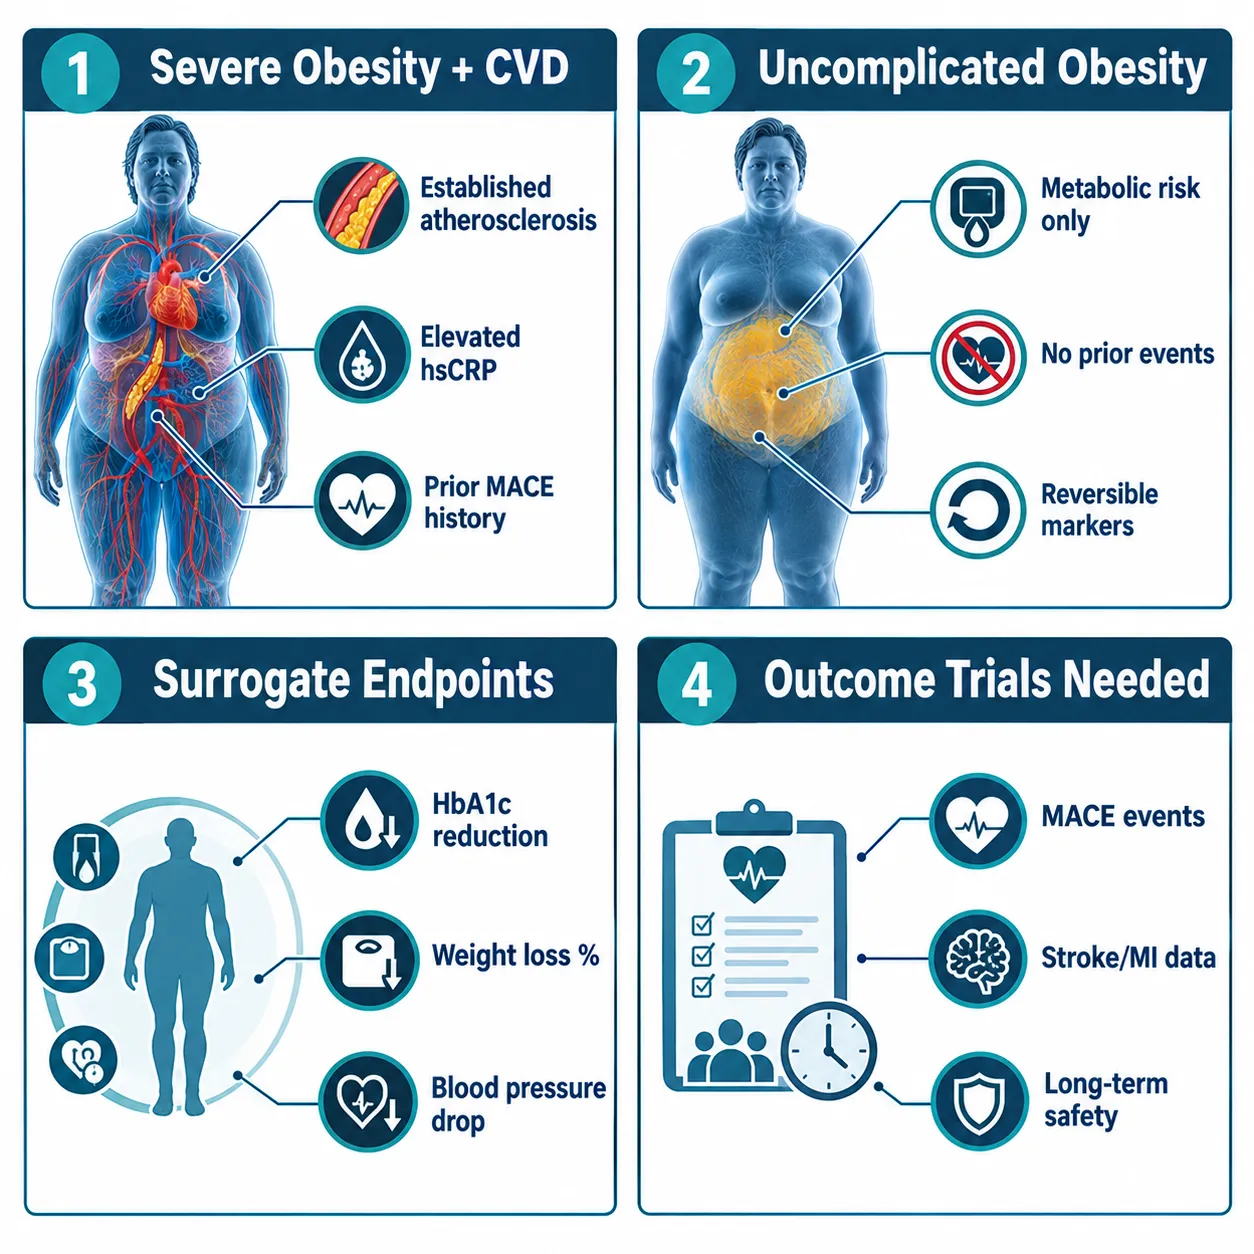
TRIUMPH-3 Severe obesity + CVD Lipids, blood pressure, cardiometabolic risk
TRANSCEND-T2D-1 Type 2 Diabetes (primary) Glycemic control, insulin sensitivity

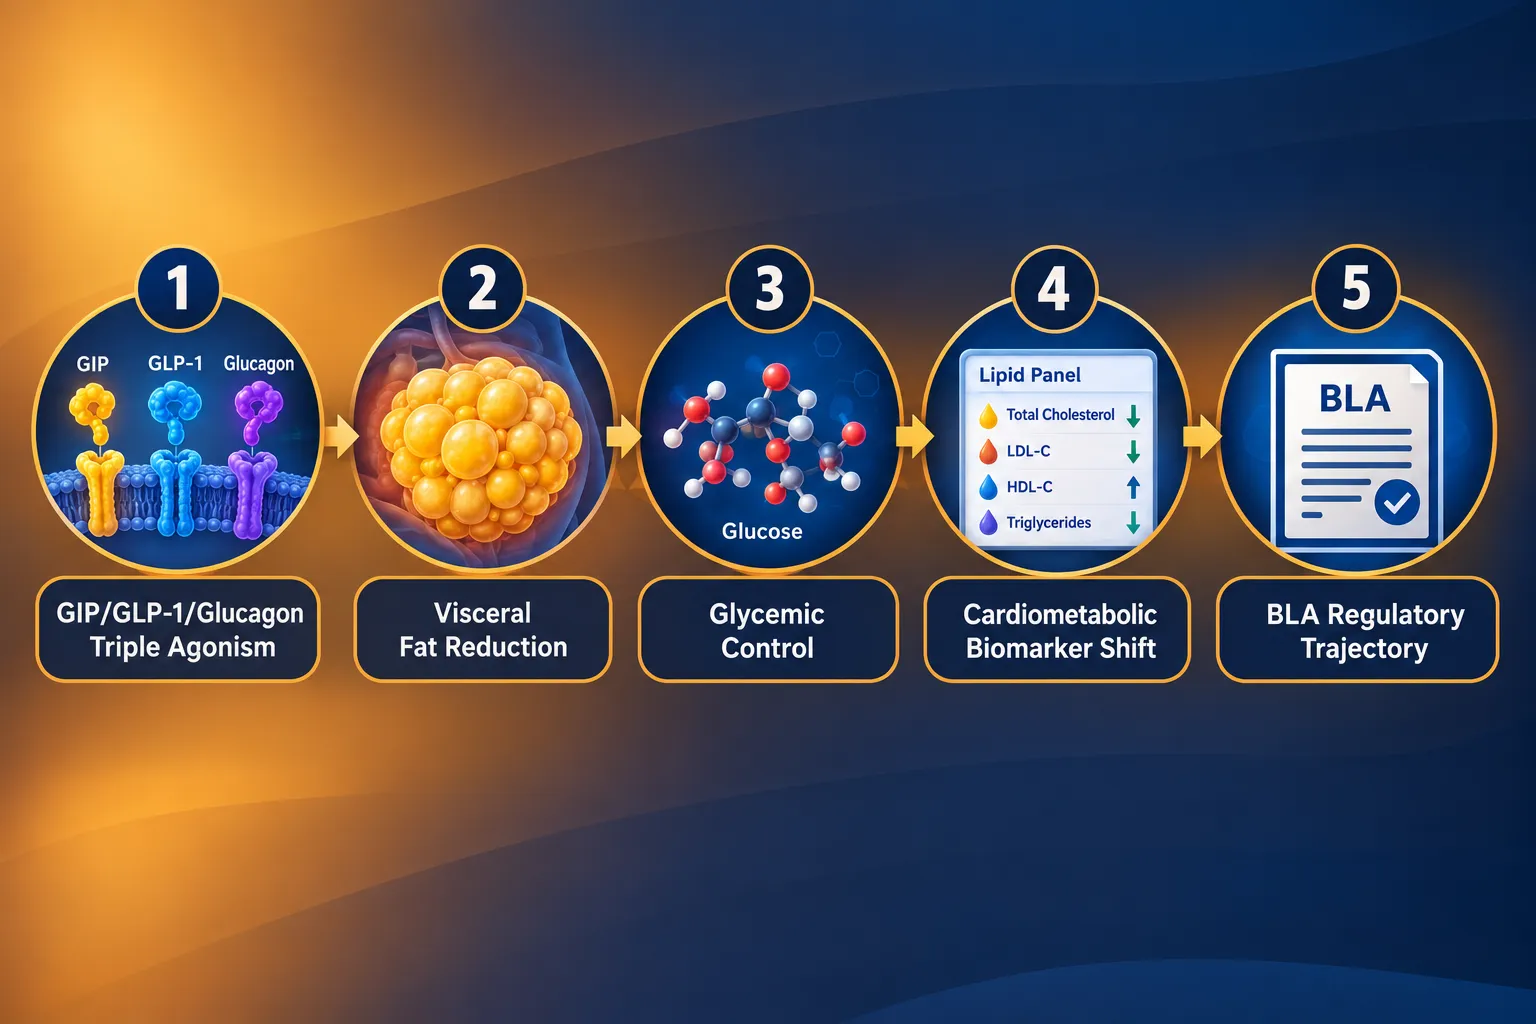
TRIUMPH-2 demonstrated A1C reductions exceeding 2 percentage points in participants with baseline A1C above 8%, alongside weight loss averaging over 20% of body weight. Importantly, glycemic improvements appeared early, within the first 12 weeks, before maximum weight loss was achieved, supporting a direct glucagon-receptor contribution to glucose regulation.

TRIUMPH-3 focused on adults with established cardiovascular disease. The cardiometabolic profile showed improvements in LDL cholesterol, triglycerides, and systolic blood pressure, providing a safety and efficacy foundation relevant to populations typically excluded from obesity trials. Those interested in metabolic peptide research may also find value in reviewing SS-31 mechanism and mitochondrial research as a parallel area of cellular energy investigation.

TRANSCEND-T2D-1 enrolled patients for whom glycemic control was the primary goal. Results aligned with TRIUMPH-2 data, reinforcing that retatrutide's triple-agonist mechanism provides additive glycemic benefit beyond what GLP-1-only agents achieve.

Metabolic Endpoints Across TRIUMPH-2, TRIUMPH-3, and TRANSCEND-T2D-1


Regulatory Trajectory and Research Implications for 2026

The accumulation of phase 2 and phase 3 data positions retatrutide for a Biologics License Application filing. In 2026, regulatory reviewers will likely examine whether the co-primary endpoint design of TRIUMPH-1 supports labeling claims beyond weight management alone, a precedent that would expand how obesity drugs are evaluated industry-wide.

Key implications for researchers and trial designers:

  • Prioritize patient-reported outcomes alongside device-measured endpoints (polysomnography, goniometry).
  • Design analysis plans that test for weight-independent effect modification.
  • Include cardiovascular disease subpopulations in expanded safety monitoring.
  • Benchmark against head-to-head comparator arms as planned follow-on trials come online.

For research teams sourcing reference material on the compound, the GLP-3 Reta 20mg product page provides formulation context relevant to preclinical study design.

Safety data across all TRIUMPH arms showed a tolerability profile consistent with GLP-1 class effects, primarily gastrointestinal events that were dose-dependent and time-limited. No new safety signals emerged in the cardiovascular subpopulation through the 80-week mark, though long-term surveillance remains an open research question.


Conclusion

The Retatrutide 2026 Trial Data: Research Implications for Sleep Apnea, Osteoarthritis, and Metabolic Endpoints signal a shift in how obesity pharmacotherapy trials should be designed and interpreted. Weight loss remains a central outcome, but the TRIUMPH data make a strong case that apnea event indices, joint pain scores, and glycemic biomarkers deserve co-primary status in future protocols.

Actionable next steps for researchers:

  • Incorporate AHI and WOMAC scores as primary endpoints in future obesity-comorbidity trials, not secondary measures.
  • Analyze early-treatment time points to distinguish direct receptor effects from weight-mediated changes.
  • Follow regulatory filings closely, as labeling decisions will shape what endpoints are considered standard in next-generation obesity trials.
  • Monitor head-to-head trial data as it emerges to contextualize retatrutide's position relative to existing GLP-1 agents.

Researchers seeking further background on buy GLP-3 Reta formulations for preclinical reference, or those reviewing buy Reta online sourcing for laboratory use, should cross-reference current institutional guidelines on peptide procurement standards.

The 2026 data cycle is not just about weight numbers. It is about whether a single compound can meaningfully shift the trajectory of three of the most burdensome chronic conditions in modern medicine, simultaneously.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-2026-trial-data-research-implications-for-sleep-apnea-osteoarthritis.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-20 13:05:402026-10-20 13:05:40Retatrutide 2026 Trial Data: Research Implications for Sleep Apnea, Osteoarthritis, and Metabolic Endpoints
Trazodone in Appetite and Sleep Experiments: Controlling Sedation When Testing Tesofensine or Retatrutide

Trazodone in Appetite and Sleep Experiments: Controlling Sedation When Testing Tesofensine or Retatrutide

October 16, 2026/0 Comments/in Uncategorized/by

Sedation is one of the most underestimated confounders in metabolic research. When a compound reduces food intake and body weight, investigators need to know whether that effect stems from genuine appetite suppression or from a drug-induced reduction in activity, alertness, and feeding motivation. That distinction becomes especially difficult when trazodone is used as a sleep adjunct alongside potent appetite-modifying agents. This article serves as a confounder guide for studies where sleep, feeding, and body weight are primary endpoints, with a direct focus on trazodone in appetite and sleep experiments: controlling sedation when testing tesofensine or retatrutide.

Key Takeaways

  • Trazodone improves objective sleep continuity but carries a meaningful sedation and dizziness burden that can confound activity and feeding endpoints.
  • Tesofensine acts through monoamine reuptake inhibition; its CNS stimulant profile may mask or interact with trazodone-induced sedation in unpredictable ways.
  • Retatrutide, a triple GLP-1/GIP/glucagon receptor agonist, shows no major sedation signal in phase 2 data, making trazodone co-administration particularly risky as a confounder.
  • Experimental designs must separate pharmacologic appetite effects from circadian disruption and sedation-driven reductions in feeding behavior.
  • Standardized polysomnography, actigraphy, and validated daytime alertness scales are essential tools for isolating trazodone's contribution to any observed outcome.

Pharmacological Profiles: Why the Combination Creates Complexity

Pharmacological Profiles: Why the Combination Creates Complexity

Understanding why trazodone in appetite and sleep experiments creates methodological tension requires a clear picture of each agent's mechanism.

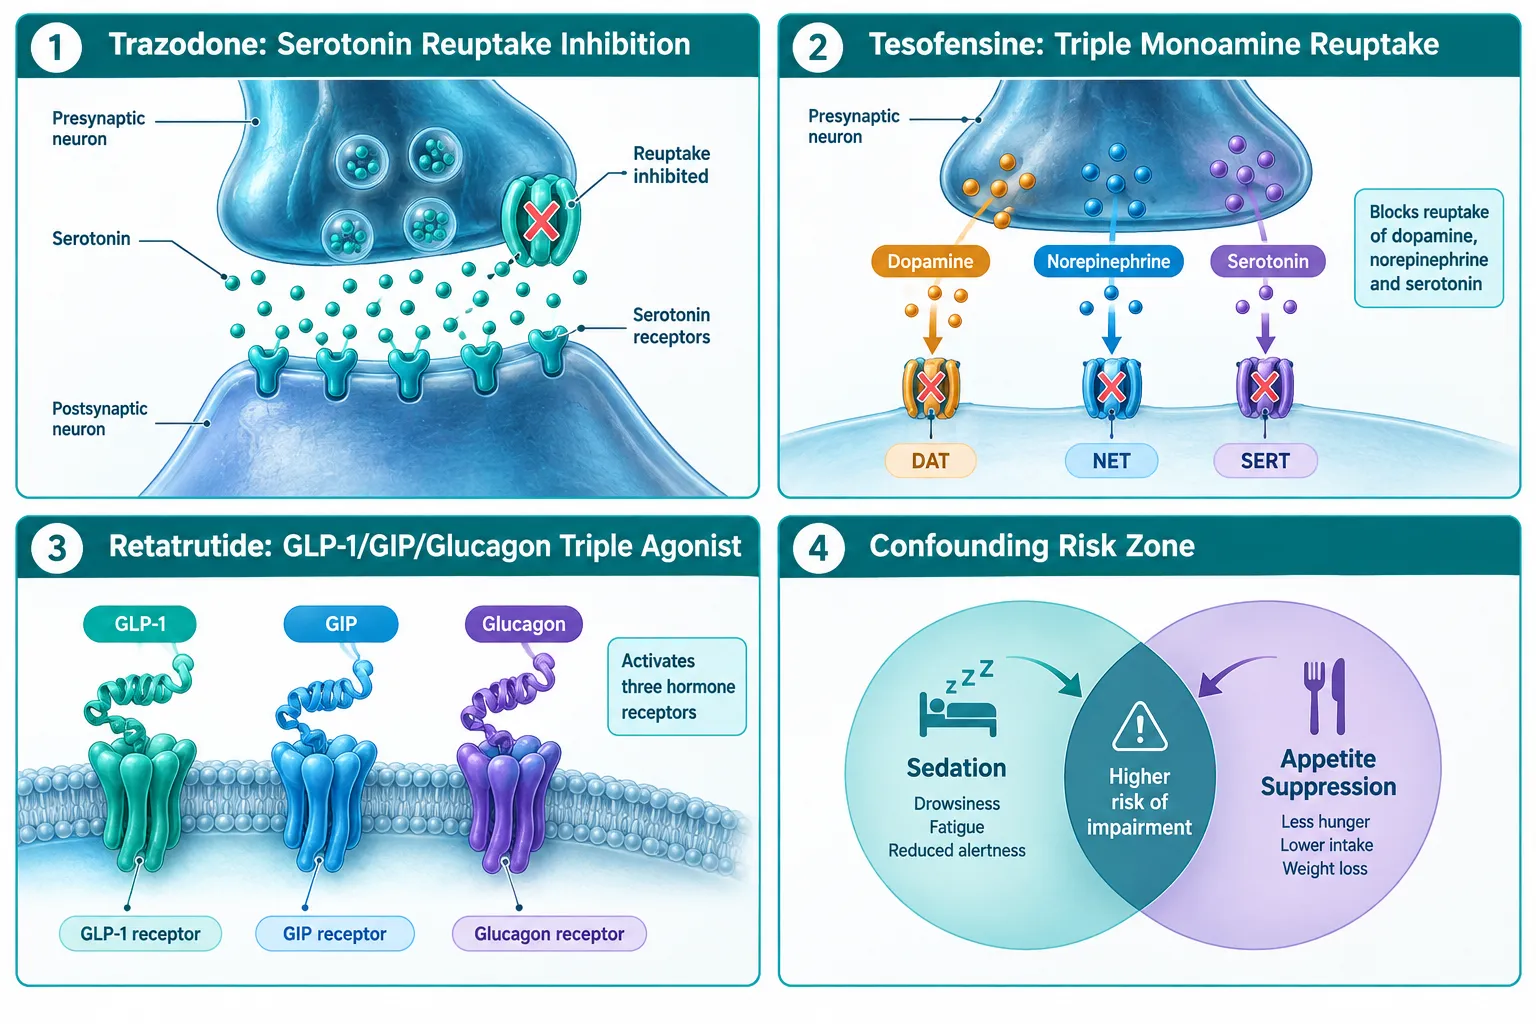
Trazodone is a serotonin antagonist and reuptake inhibitor (SARI). At low doses (50-150 mg), its histamine H1 and alpha-1 adrenergic antagonism produces sedation. At doses approaching 180 mg/day, where aggregated RCT data show the strongest improvements in subjective sleep quality, somnolence, dizziness, and next-day cognitive blunting become clinically significant. Importantly, trazodone alters sleep architecture even when it improves sleep continuity, reducing slow-wave and REM proportions in some polysomnographic analyses.

Tesofensine inhibits the reuptake of serotonin, dopamine, and norepinephrine. This triple monoamine mechanism produces appetite suppression but also increases arousal, heart rate, and locomotor activity. Pairing a stimulant-profile compound with a sedating one creates a pharmacodynamic tug-of-war that is nearly impossible to model cleanly.

Retatrutide is a triple agonist at GLP-1, GIP, and glucagon receptors. Phase 2 obesity trial data show substantial weight loss and GI side effects but no major sedation signal. Ongoing phase 3 TRIUMPH trials do not include standardized sedative adjuncts, which means adding trazodone to a retatrutide study introduces a variable absent from the pivotal evidence base. Researchers interested in the compound's dosing range can review options such as Reta 10mg and Reta 30mg for context on experimental formulations.


Separating Appetite Effects from Sedation: The Core Confounder Problem

Separating Appetite Effects from Sedation: The Core Confounder Problem

The central challenge in controlling sedation when testing tesofensine or retatrutide is that sedation reduces feeding through at least three independent pathways that have nothing to do with appetite:

Sedation-Driven Feeding Reduction Pharmacologic Appetite Suppression
Reduced locomotor activity lowers caloric demand Direct action on hypothalamic hunger circuits
Shortened waking window decreases meal opportunities Delayed gastric emptying reduces hunger signals
Cognitive blunting impairs food-seeking motivation GLP-1 receptor activation modulates reward pathways
Circadian phase shift alters meal timing Monoamine reuptake inhibition reduces hedonic eating

When trazodone is present, any reduction in food intake could reflect sedation-driven behavioral suppression rather than the test compound's pharmacologic action. This is not a theoretical concern. A head-to-head comparison of trazodone against zolpidem found trazodone to be less potent as a hypnotic yet more broadly sedating at standard doses, suggesting its sedation profile extends well beyond the sleep window.

Circadian disruption adds another layer. Trazodone shifts sleep architecture and may alter the timing of cortisol, ghrelin, and leptin secretion, all of which directly regulate appetite. An experiment that records feeding behavior without accounting for these hormonal shifts will misattribute circadian-driven appetite changes to the test compound.

For studies using retatrutide, which researchers can explore in formulations such as GLP3 Reta 20mg GSF or the Buy GLP-3 Peptide GLP3 Reta 10mg 99% Pure Third Party Tested option, the absence of a sedation signal in existing data makes any trazodone-induced sedation especially visible as a confound.


Designing Around the Confounder: A Practical Protocol Framework

Designing Around the Confounder: A Practical Protocol Framework

Applying trazodone in appetite and sleep experiments: controlling sedation when testing tesofensine or retatrutide responsibly requires a structured approach to experimental design. The following framework addresses the most common methodological gaps.

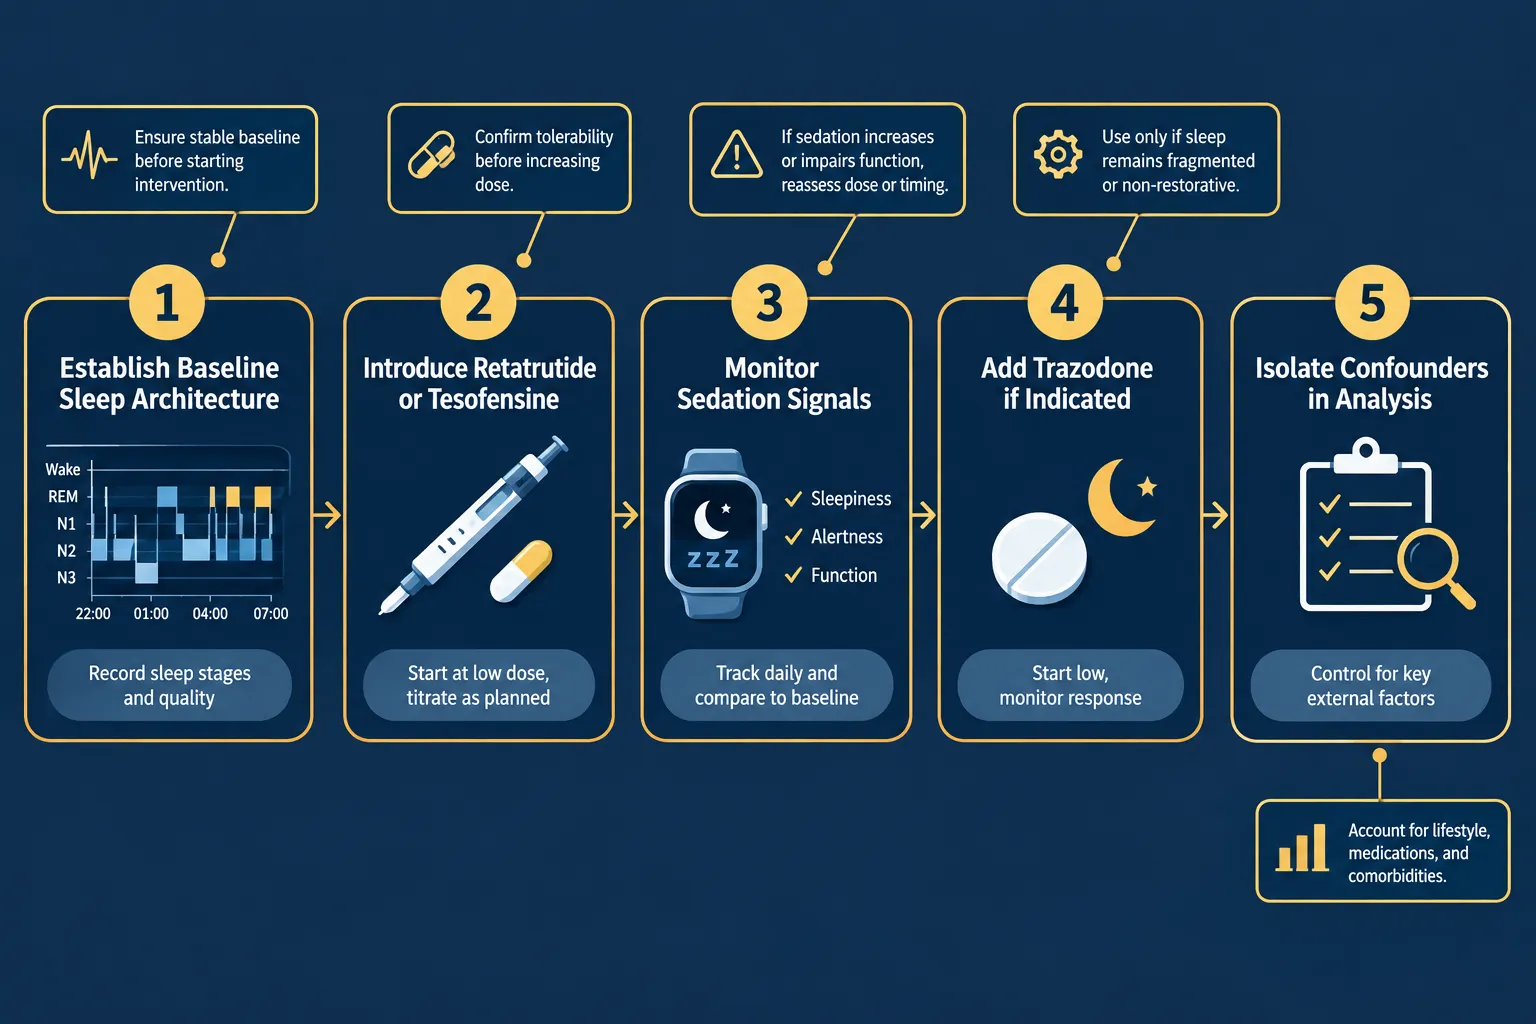
Establish a Trazodone-Only Baseline Period

Before introducing the test compound, run a washout and then a trazodone-alone phase of at least two weeks. Collect polysomnography, actigraphy, daytime alertness scores (Epworth Sleepiness Scale), and 24-hour food intake diaries. This baseline isolates trazodone's independent contribution to sedation and feeding behavior.

Use Objective Sleep Architecture Monitoring

Subjective sleep quality ratings are insufficient. Full polysomnography or validated wrist actigraphy must be used to document changes in sleep efficiency, wake-after-sleep-onset, and REM latency. A 2026 polysomnographic meta-analysis confirmed that trazodone improves objective sleep continuity but alters architecture, a finding that demands continuous monitoring rather than endpoint-only assessment.

Separate Daytime Alertness from Nighttime Sleep Metrics

Collect alertness data at fixed intervals during the active phase using validated tools such as the Psychomotor Vigilance Task (PVT) and the Karolinska Sleepiness Scale. This separates residual sedation from genuine improvements in sleep quality and prevents daytime hypoactivity from being recorded as reduced appetite.

Pre-register Sedation as a Competing Endpoint

Any protocol testing retatrutide or tesofensine alongside trazodone should pre-register sedation-related outcomes, somnolence, dizziness, activity counts, as competing endpoints. This forces statistical models to account for sedation's independent contribution to weight and feeding outcomes. Researchers sourcing retatrutide for such studies may find the Buy Reta and Buy GLP-3 Reta resources useful for procurement context.

Consider Non-Sedating Sleep Alternatives

Where sleep stabilization is needed but sedation confounding is unacceptable, low-dose melatonin or cognitive behavioral therapy for insomnia (CBT-I) protocols offer sleep support with minimal pharmacodynamic interference. These alternatives do not carry trazodone's alpha-1 and H1 antagonism burden.


Conclusion

The intersection of trazodone and novel metabolic agents like tesofensine or retatrutide is a genuine methodological minefield. Trazodone's sedation profile, well-documented across meta-analyses and head-to-head trials, can suppress activity, shift circadian hormone timing, and reduce meal frequency through mechanisms entirely independent of the test compound's appetite pharmacology. For studies where sleep, feeding, and body weight are primary endpoints, this is not a minor nuisance; it is a threat to internal validity.

Actionable next steps for researchers:

  • Implement a trazodone-only baseline phase before introducing the test compound.
  • Use polysomnography and actigraphy rather than self-report alone.
  • Pre-register sedation as a competing endpoint in every protocol.
  • Evaluate whether a non-sedating sleep intervention can replace trazodone without compromising sleep quality goals.
  • Review the existing phase 3 TRIUMPH trial design for retatrutide to align sedation monitoring approaches with the emerging gold standard.

Separating pharmacologic appetite suppression from sedation-driven behavioral changes is not optional in high-quality metabolic research. It is the difference between a publishable finding and a confounded dataset.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/trazodone-in-appetite-and-sleep-experiments-controlling-sedation-when-testing-te.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-16 13:04:162026-10-16 13:04:16Trazodone in Appetite and Sleep Experiments: Controlling Sedation When Testing Tesofensine or Retatrutide
Retatrutide Phase 3 Cardiometabolic Monitoring: Designing Research Panels for Triglycerides, Blood Pressure, hsCRP, and A1C

Retatrutide Phase 3 Cardiometabolic Monitoring: Designing Research Panels for Triglycerides, Blood Pressure, hsCRP, and A1C

October 12, 2026/0 Comments/in Uncategorized/by

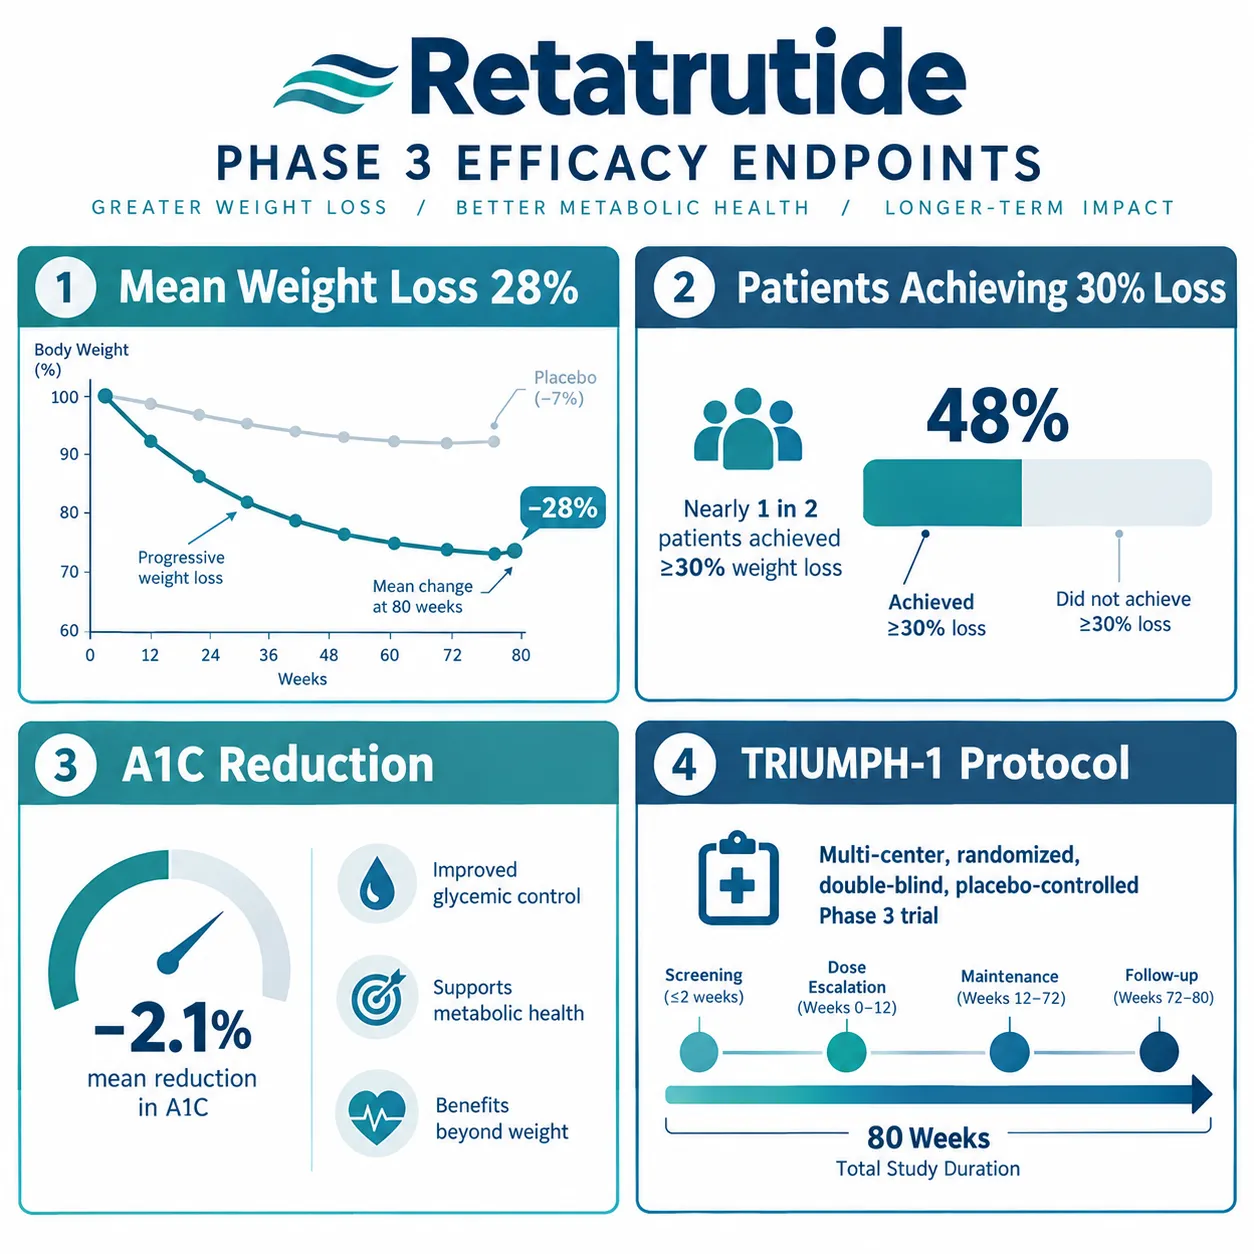
By mid-2026, five pivotal Phase 3 readouts from Eli Lilly's TRIUMPH program had confirmed that retatrutide produces weight loss exceeding 28% of body weight, a figure that surpasses every previously reported pharmacological result in humans. Yet the most consequential design challenge for researchers is not tracking weight. It is building a cardiometabolic panel rigorous enough to separate the independent effects of retatrutide on lipids, blood pressure, inflammation, and glycemic control from the cascade of changes that weight loss alone would produce. Retatrutide Phase 3 cardiometabolic monitoring: designing research panels for triglycerides, blood pressure, hsCRP, and A1C demands a structured, multi-domain approach grounded in the latest TRIUMPH data.

Key Takeaways

  • TRIUMPH Phase 3 trials prespecify fasting triglycerides, non-HDL cholesterol, systolic blood pressure, hsCRP, A1C, and waist circumference as core cardiometabolic endpoints alongside weight loss.
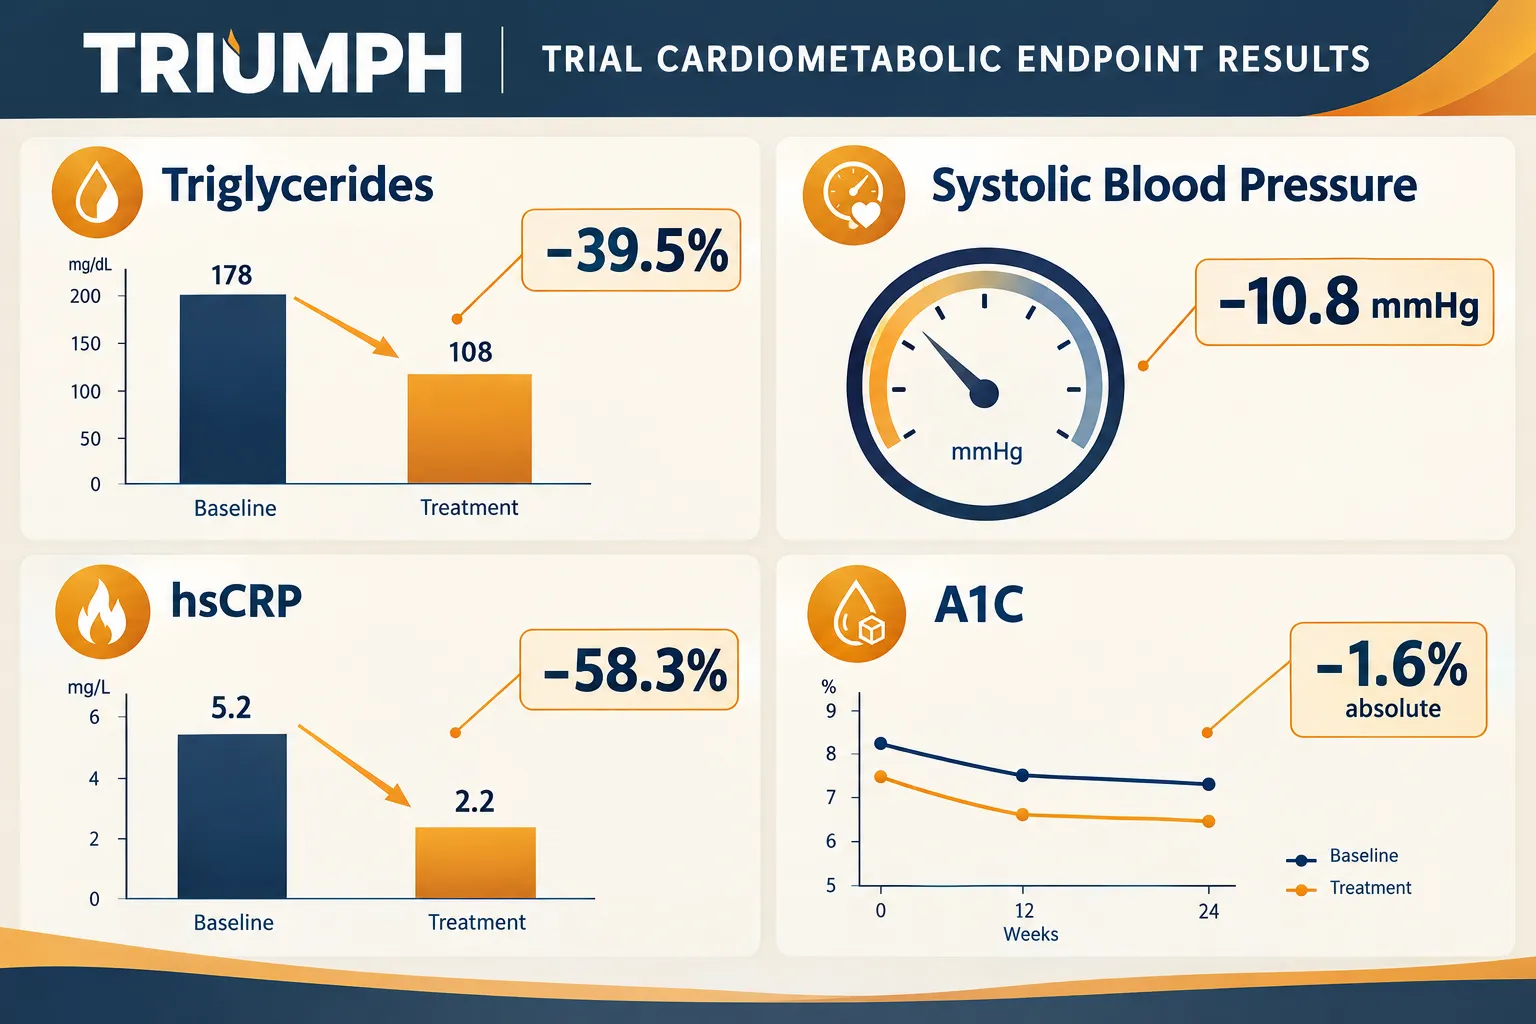
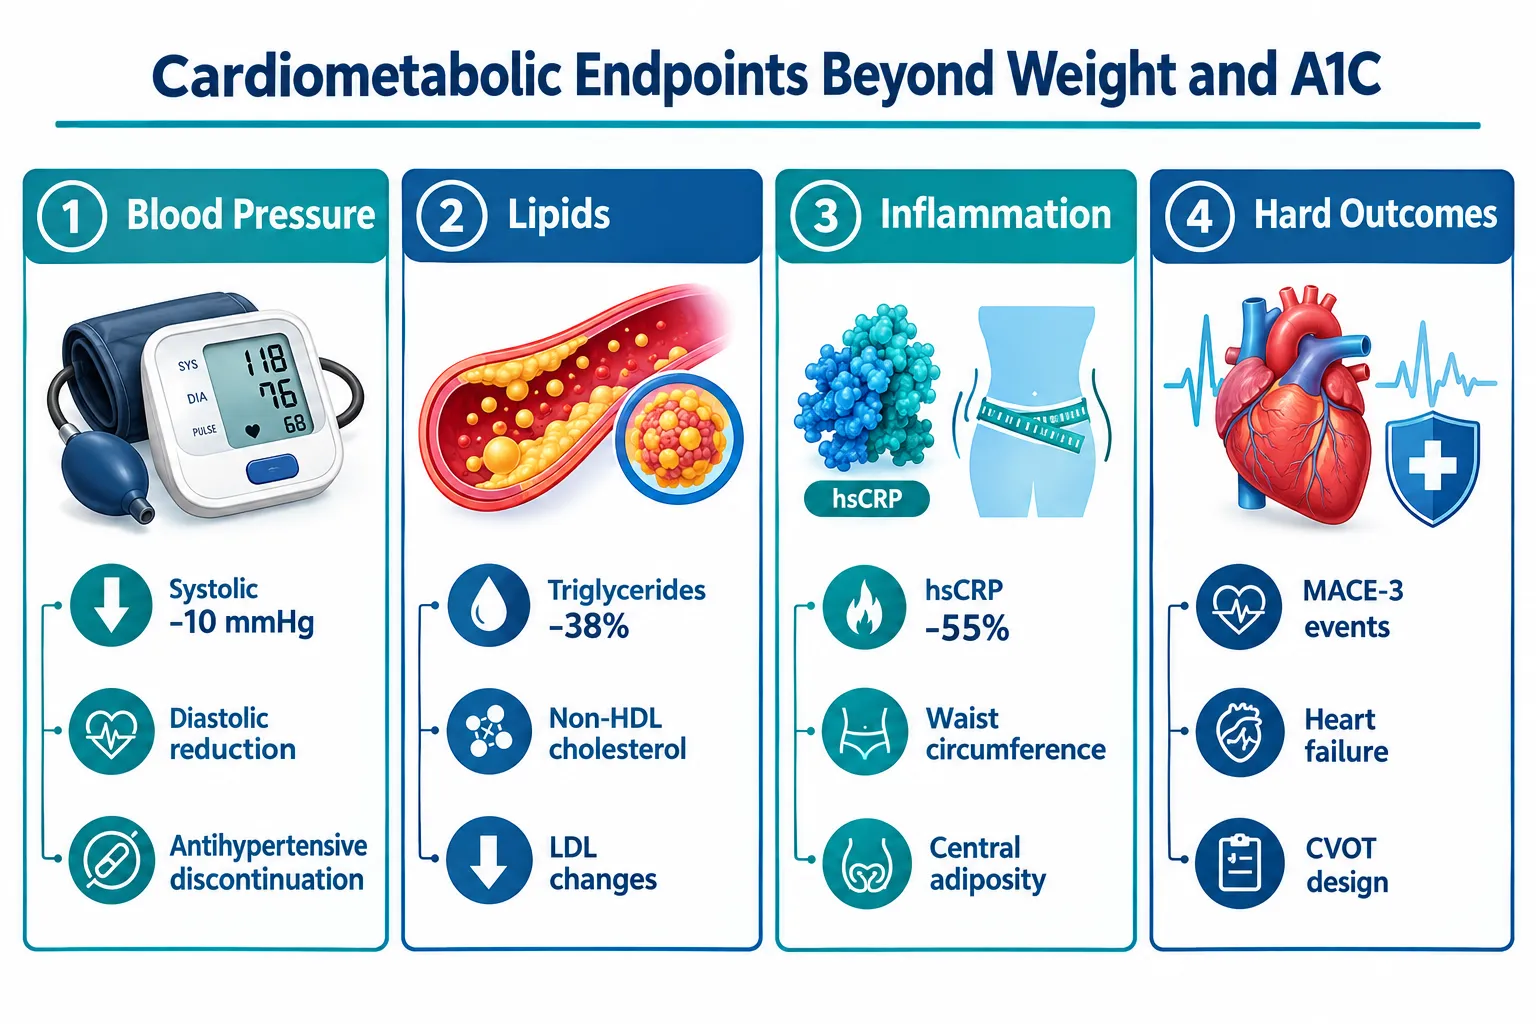
  • Triglyceride reductions of up to 39.5%, hsCRP reductions of up to 58.3%, and systolic blood pressure drops of up to 10.8 mmHg were recorded at 80 weeks in TRIUMPH-2.
  • Baseline stratification by diabetes status, cardiovascular disease history, and baseline triglyceride level is essential for interpreting correlated outcomes.
  • A1C is a primary endpoint in diabetes-focused arms (TRIUMPH-2, TRANSCEND-T2D-1) and must be paired with lipid and inflammatory markers to capture the full cardiometabolic picture.
  • The ongoing TRIUMPH-Outcomes CV/renal trial signals that future panels will expand to include kidney function markers such as eGFR and albuminuria.

Why the TRIUMPH Data Demand a Multi-Domain Panel

Why the TRIUMPH Data Demand a Multi-Domain Panel

The TRIUMPH program is not a single study. It is a coordinated set of 80-week, randomized, double-blind, placebo-controlled trials targeting distinct populations: TRIUMPH-1 in adults with obesity or overweight, TRIUMPH-2 in adults with obesity or overweight plus type 2 diabetes, and TRIUMPH-3 in 1,949 adults with BMI of 35 or higher and established cardiovascular disease. Each trial prespecifies cardiometabolic endpoints beyond weight, and the consistency of those endpoints across trials is itself a design signal.

In TRIUMPH-3, participants on retatrutide 12 mg achieved a 22.6% reduction in body weight versus 3.2% on placebo. Alongside that, triglycerides fell 37.0%, non-HDL cholesterol dropped 16.5%, systolic blood pressure decreased 9.3 mmHg, waist circumference shrank 19.0 cm, and hsCRP fell 51.2%. The MACE-5 hazard ratio of 0.82 did not reach statistical significance, which is a critical interpretive point: robust improvements in surrogate biomarkers did not automatically translate into a proven reduction in hard cardiovascular events. This finding directly shapes panel philosophy, these markers must be tracked as risk-factor indicators, not as proxies for confirmed outcome benefit.

Researchers sourcing the compound for preclinical or translational work can explore GLP-1 Reta and Reta peptide for sale options to understand the molecular context before designing monitoring frameworks.

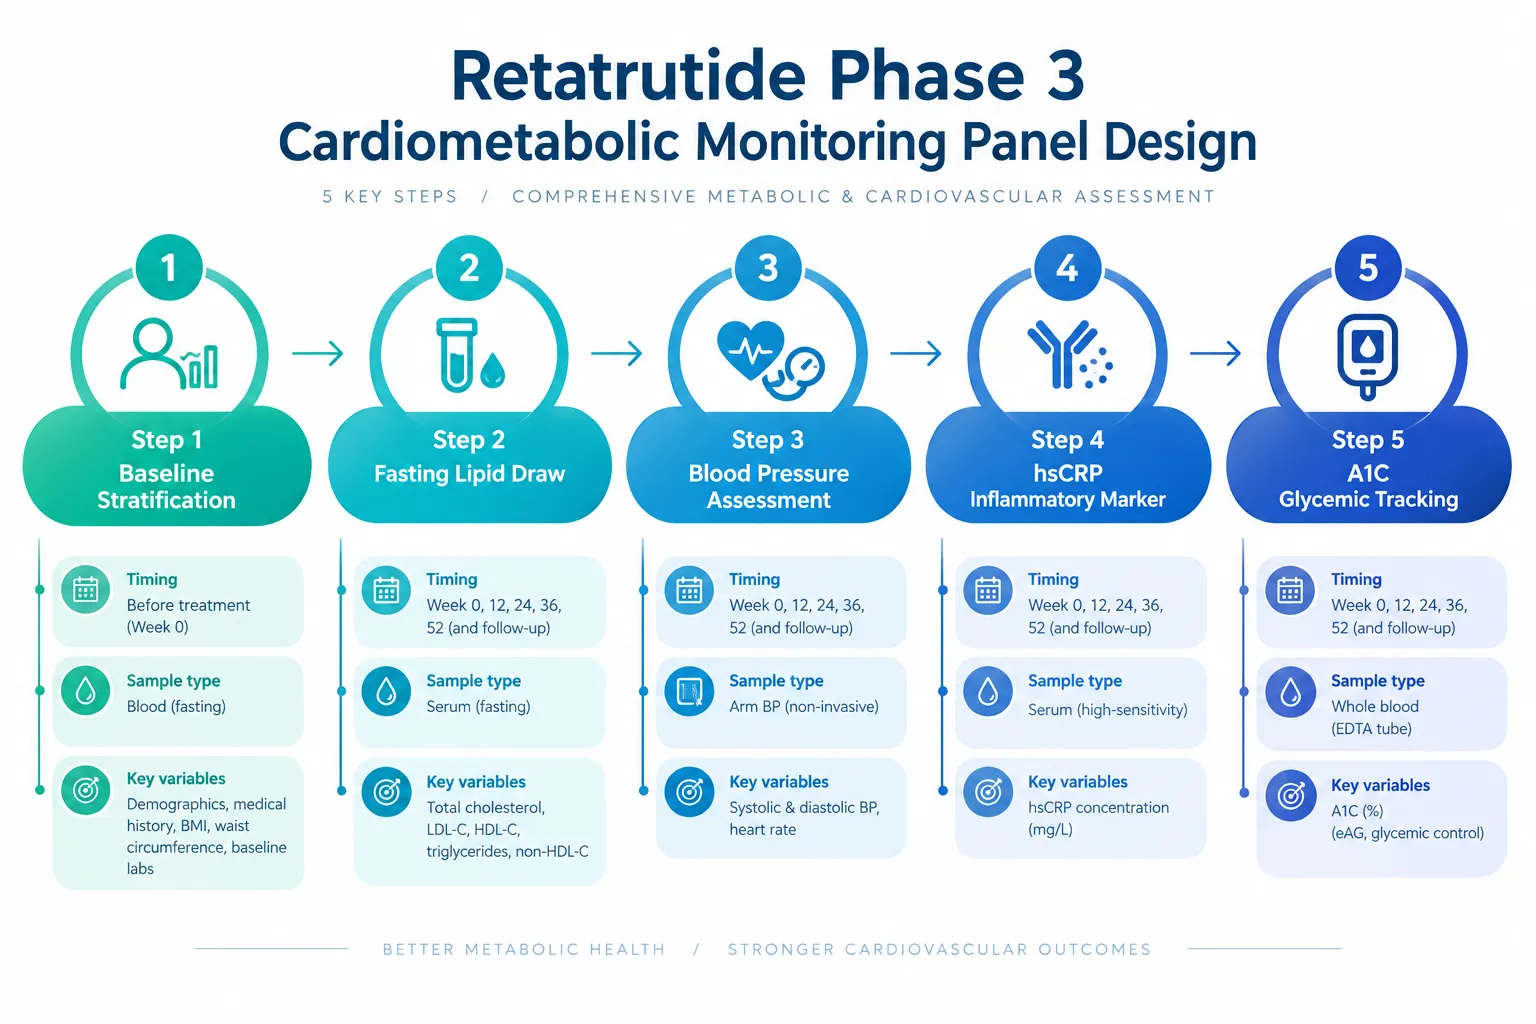
Core panel elements supported by TRIUMPH data:

Biomarker TRIUMPH-2 Change (12 mg) TRIUMPH-3 Change (12 mg)
Triglycerides -39.5% -37.0%
Non-HDL Cholesterol -19.6% -16.5%
Systolic Blood Pressure -10.8 mmHg -9.3 mmHg
hsCRP -58.3% -51.2%
Waist Circumference Significant -19.0 cm
A1C -1.6% absolute Not primary

Baseline Stratification and Sampling Schedules

Baseline Stratification and Sampling Schedules

Effective retatrutide Phase 3 cardiometabolic monitoring, designing research panels for triglycerides, blood pressure, hsCRP, and A1C, begins before the first dose. Baseline stratification is the mechanism that allows researchers to disentangle weight-mediated effects from direct receptor-driven changes.

Stratification variables to define at enrollment:

  • Diabetes status: TRIUMPH-2 and TRANSCEND-T2D-1 demonstrate that A1C trajectories in diabetes populations diverge meaningfully from non-diabetes arms. Separate strata prevent dilution of glycemic signals.
  • Baseline triglyceride level: Participants with hypertriglyceridemia at baseline show proportionally larger reductions. Stratifying by fasting triglycerides above or below 200 mg/dL allows dose-response analysis that is not confounded by regression to the mean.
  • Cardiovascular disease history: TRIUMPH-3's CVD-enriched cohort produced the largest absolute hsCRP reductions. Mixing CVD and non-CVD participants without stratification obscures inflammation response patterns.
  • Baseline BMI tier: Weight loss magnitude correlates with baseline BMI, and since triglycerides and blood pressure both respond to weight loss, BMI strata help isolate pharmacological signal.

"The consistent use of fasting triglycerides, non-HDL cholesterol, systolic blood pressure, hsCRP, A1C, and waist circumference over 40-to-80-week windows across five Phase 3 trials represents an emerging standard for retatrutide cardiometabolic panel design."

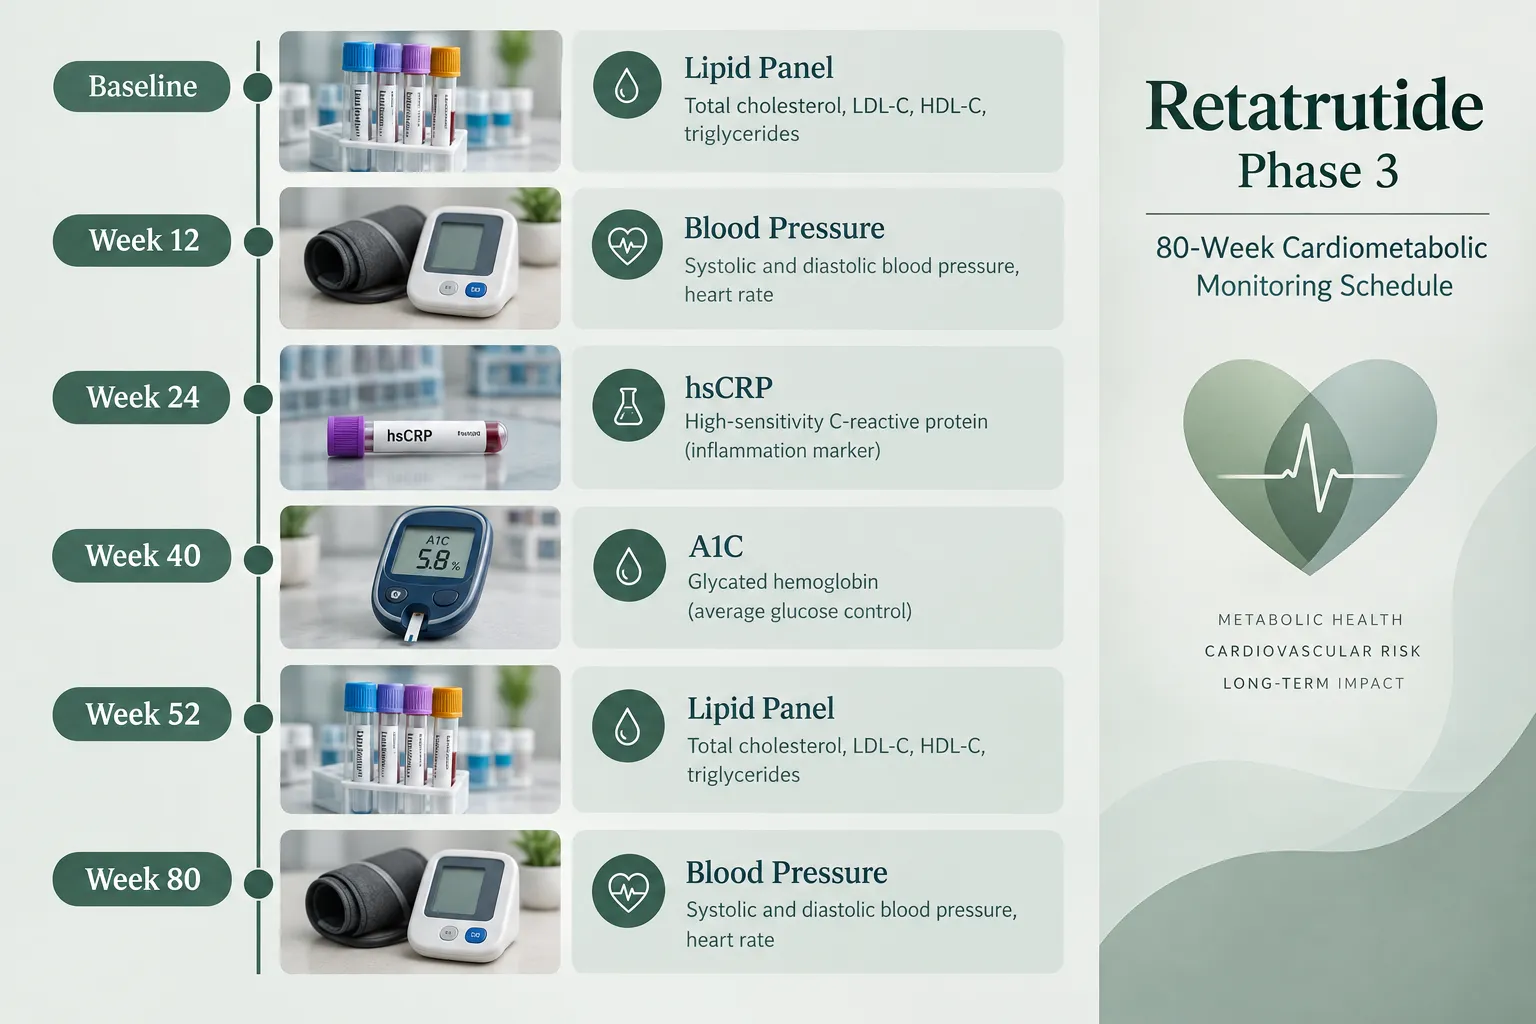
Recommended sampling schedule for an 80-week protocol:

  • Baseline (Week 0): Full fasting lipid panel, hsCRP, A1C, blood pressure (triplicate), waist circumference, eGFR, albuminuria
  • Week 12: Fasting triglycerides, blood pressure, body weight
  • Week 24: Full panel repeat
  • Week 40: Full panel repeat (aligns with TRANSCEND-T2D-1 primary endpoint)
  • Week 52: Fasting triglycerides, hsCRP, blood pressure, A1C
  • Week 80: Full panel repeat, primary endpoint analysis

Fasting status for lipid draws must be standardized at 10-12 hours. Blood pressure should follow a three-reading protocol with the participant seated for five minutes, using the average of readings two and three. hsCRP should use the high-sensitivity assay (hs-CRP) to detect low-grade inflammation changes relevant to cardiovascular risk.

For researchers exploring related metabolic pathways, visceral fat research resources provide useful context on adipose-driven inflammation that intersects with hsCRP monitoring. Those studying growth hormone secretagogue stacks may also find the IPA Sermorelin stack research reference helpful for understanding parallel metabolic endpoints.


Interpreting Correlated Outcomes Without Overclaiming

Interpreting Correlated Outcomes Without Overclaiming

The central interpretive challenge in retatrutide Phase 3 cardiometabolic monitoring, designing research panels for triglycerides, blood pressure, hsCRP, and A1C, is that all four major endpoints are correlated with each other and with weight loss. A 28% reduction in body weight alone would be expected to lower triglycerides, reduce systolic blood pressure, decrease hsCRP, and improve insulin sensitivity. Attributing the observed changes solely to receptor agonism requires deliberate analytical design.

Three analytical strategies to separate effects:

  1. Mediation analysis: Model weight loss as a mediator between retatrutide dose and each cardiometabolic endpoint. The residual direct effect after accounting for weight change estimates the weight-independent pharmacological contribution.
  2. Matched-weight comparator: Identify placebo participants who achieved similar weight loss through caloric restriction and compare their lipid and inflammatory trajectories to retatrutide-treated participants at the same weight-loss magnitude.
  3. Time-course divergence: Triglyceride and hsCRP reductions in TRIUMPH trials appear early and disproportionately large relative to the weight-loss timeline, suggesting direct receptor-mediated effects. Plotting biomarker change against cumulative weight loss at each time point can reveal non-linear relationships that indicate independent mechanisms.

A1C interpretation in mixed populations requires particular care. In TRIUMPH-2, the 1.6% absolute A1C reduction at the highest dose reflects both weight-mediated insulin sensitization and potential direct GLP-1 receptor-driven beta-cell effects. Panels that include fasting insulin and HOMA-IR alongside A1C allow researchers to partition these contributions.

Researchers interested in mitochondrial and cellular stress pathways that intersect with cardiometabolic function may find the SS-31 mitochondrial research tag and the detailed SS-31 mechanism and research guide useful for understanding complementary biomarker frameworks.

The TRIUMPH-Outcomes CV/renal trial (active as of October 2026) extends this logic further by enrolling adults with atherosclerotic cardiovascular disease and/or chronic kidney disease. Its design implies that future standard panels will add eGFR and albuminuria as kidney-function domains, creating a true multi-system cardiometabolic bundle rather than a lipid-and-pressure-only framework.

Avoid these common panel design errors:

  • Using non-fasting lipid draws at inconsistent time points
  • Measuring blood pressure immediately after physical activity or within 30 minutes of caffeine intake
  • Reporting A1C without concurrent fasting glucose, which limits mechanistic interpretation
  • Treating hsCRP as a hard outcome rather than a risk-factor surrogate

For those examining how to source research-grade retatrutide for preclinical panel validation studies, the how to buy Reta and Reta 10mg product tag pages provide relevant procurement context.


Conclusion

The TRIUMPH program has produced a clear, reproducible cardiometabolic signal: fasting triglycerides, non-HDL cholesterol, systolic blood pressure, hsCRP, A1C, and waist circumference all improve substantially with retatrutide across obesity, diabetes, and high-CVD-risk populations. The actionable next steps for researchers designing monitoring panels are straightforward.

Act on these priorities:

  • Standardize baseline stratification by diabetes status, CVD history, and baseline triglyceride level before randomization.
  • Implement a minimum six-timepoint sampling schedule across 80 weeks, with full fasting panels at baseline, week 24, week 40, and week 80.
  • Build mediation analysis into the statistical analysis plan from the outset to separate weight-mediated from direct pharmacological effects.
  • Add eGFR and albuminuria to panels that enroll participants with chronic kidney disease, anticipating the TRIUMPH-Outcomes readout framework.
  • Treat all biomarker improvements as risk-factor endpoints, not as evidence of hard cardiovascular event reduction, until outcomes trial data are available.

Rigorous panel design is what will allow the field to move from observing that retatrutide changes biomarkers to understanding precisely how, in whom, and through which mechanisms those changes occur.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-phase-3-cardiometabolic-monitoring-designing-research-panels-for-tri.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-12 13:05:412026-10-12 13:05:41Retatrutide Phase 3 Cardiometabolic Monitoring: Designing Research Panels for Triglycerides, Blood Pressure, hsCRP, and A1C
Atorvastatin in Metabolic Peptide Experiments: Controlling Lipid-Lowering Effects in Retatrutide and Mitochondrial Models

Atorvastatin in Metabolic Peptide Experiments: Controlling Lipid-Lowering Effects in Retatrutide and Mitochondrial Models

October 4, 2026/0 Comments/in Uncategorized/by

Fewer than 10% of metabolic peptide experiments pre-specify how concurrent statin therapy will be handled, yet that omission can quietly invalidate a study's entire lipid endpoint. When the compound under investigation is a triple agonist as potent as retatrutide, and when mitochondrial probes such as MOTS-c or 5-Amino-1MQ are added to the design, the presence or absence of atorvastatin in the background becomes a variable that can dwarf the signal researchers are actually trying to measure. Understanding how to account for atorvastatin in metabolic peptide experiments, controlling lipid-lowering effects in retatrutide and mitochondrial models, is therefore not a minor procedural detail. It is a core element of experimental validity.

Key Takeaways

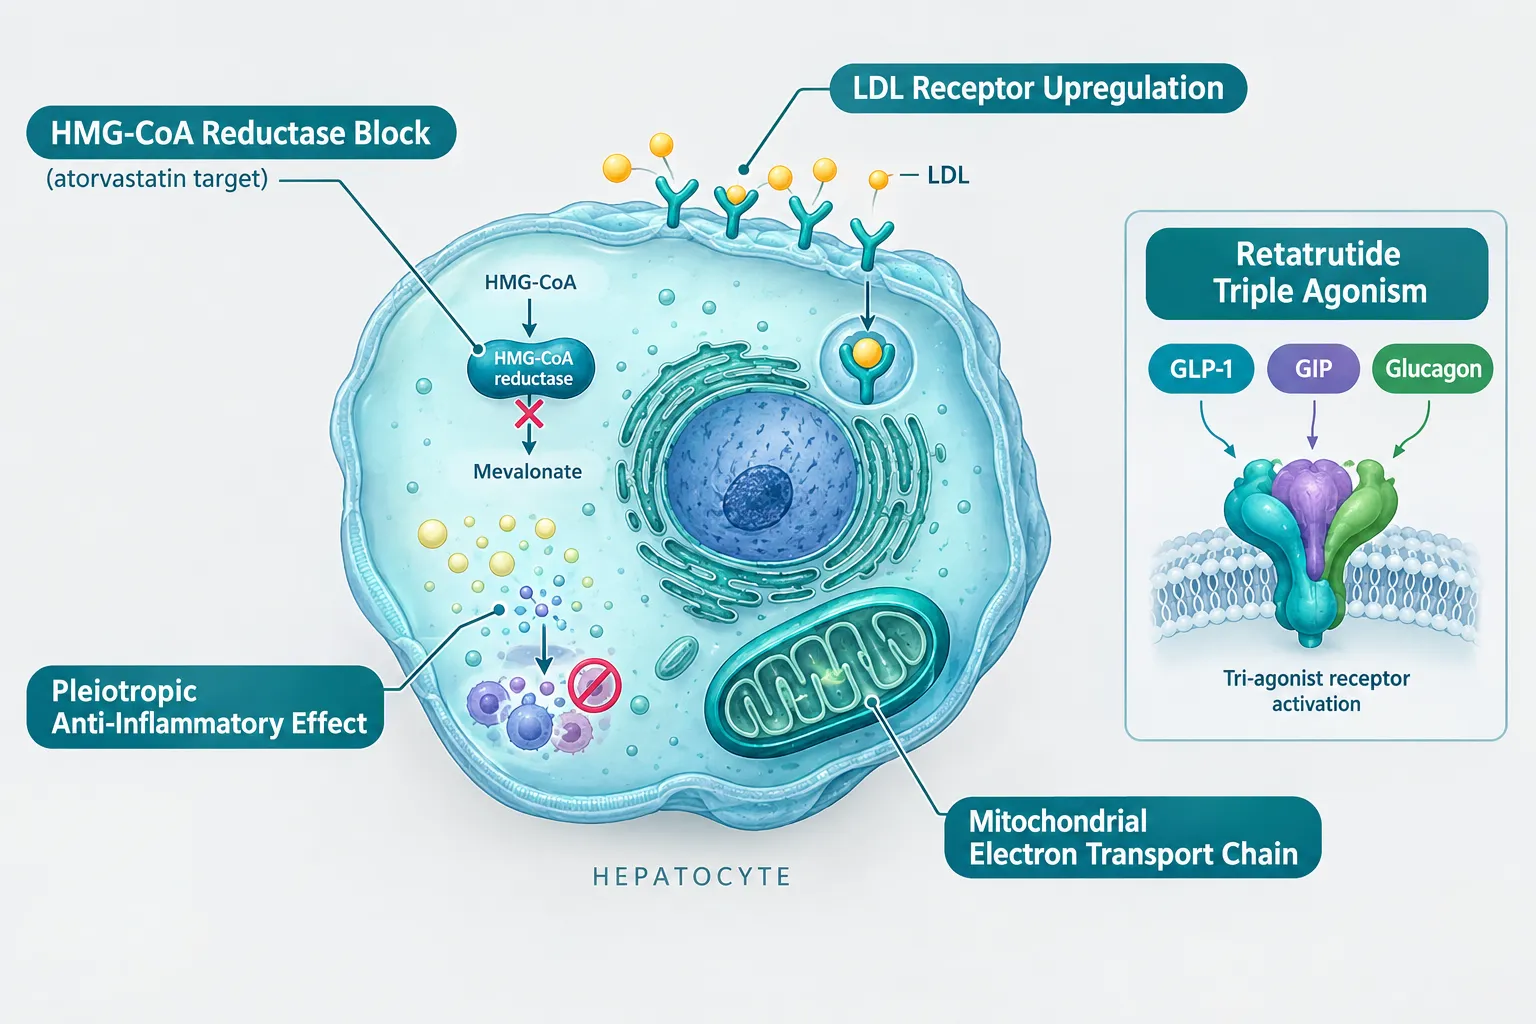
  • Atorvastatin's HMG-CoA reductase inhibition and pleiotropic effects can confound lipid endpoints in retatrutide and mitochondrial peptide studies if not systematically controlled.
  • Baseline lipid matching and pre-specified washout windows are the two most critical design decisions when atorvastatin is present in a study population.
  • Retatrutide's triple agonism (GLP-1, GIP, glucagon) independently lowers LDL, triglycerides, and hepatic lipids, making statin co-exposure a genuine confound rather than a neutral background variable.
  • Mitochondrial peptides such as MOTS-c and 5-Amino-1MQ interact with pathways that atorvastatin also touches, requiring careful arm construction to isolate each compound's contribution.
  • No completed published trial as of 2026 has formally used atorvastatin as a deliberate modulator of retatrutide's lipid effects; current guidance is therefore grounded in pharmacological principles and experimental design logic.

Why Atorvastatin Demands Attention in Metabolic Peptide Research

Why Atorvastatin Demands Attention in Metabolic Peptide Research

Atorvastatin is the world's most prescribed lipid-lowering drug. It blocks HMG-CoA reductase, the rate-limiting enzyme in hepatic cholesterol synthesis, and upregulates LDL receptors on liver cells. Beyond these primary actions, it exerts well-documented pleiotropic effects: reducing vascular inflammation, modulating endothelial nitric oxide, and influencing mitochondrial coenzyme Q10 levels. Each of these secondary actions intersects with pathways that metabolic peptides are designed to probe.

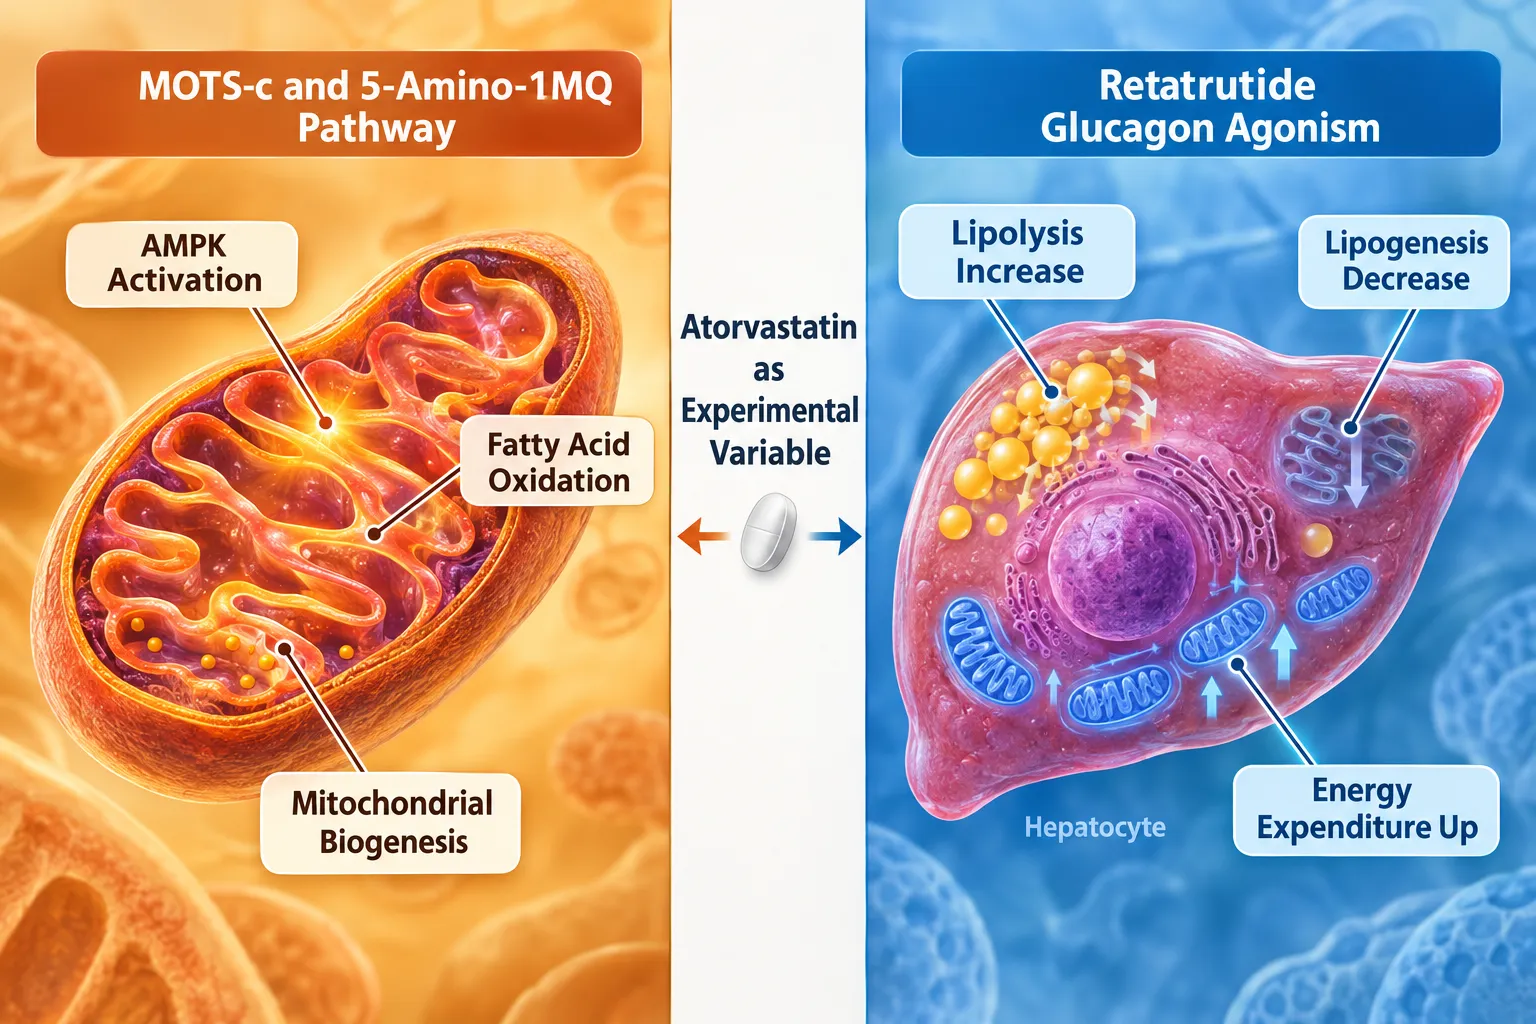
Retatrutide (LY3437943) activates GLP-1, GIP, and glucagon receptors simultaneously. Phase 2 trial data show mean weight reductions of approximately 22-24% over 48 weeks, accompanied by meaningful improvements in triglycerides, LDL cholesterol, and hepatic lipid content. Crucially, these lipid improvements arise from the peptide's own pharmacology, glucagon receptor agonism increases lipolysis and reduces lipogenesis, while GLP-1 and GIP components improve insulin sensitivity and reduce ectopic fat. When a participant is also taking atorvastatin, separating the statin's LDL effect from the peptide's LDL effect becomes statistically and mechanistically complex.

"The question is not whether atorvastatin matters, it clearly does. The question is whether the experimental design treats it as a known variable or an invisible confounder."

Researchers sourcing retatrutide peptide for preclinical work or reviewing GLP-3/retatrutide combination products should build statin status into their protocol from day one.


Experimental Design Principles for Atorvastatin in Metabolic Peptide Experiments

Experimental Design Principles for Atorvastatin in Metabolic Peptide Experiments

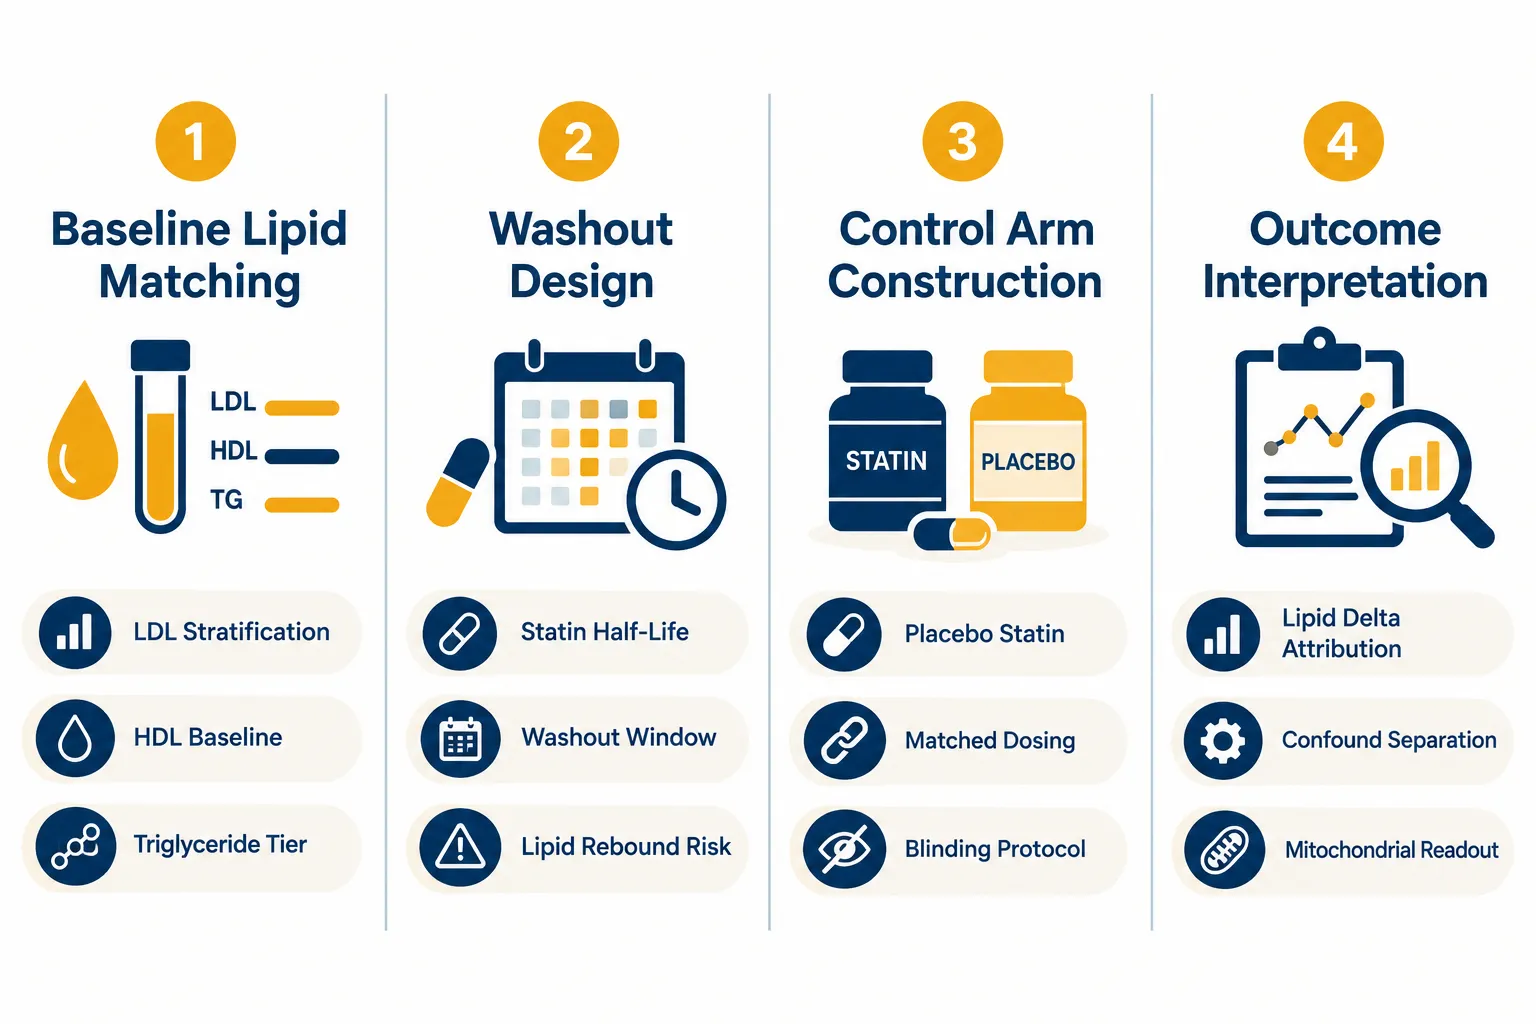
Rigorous control of atorvastatin's influence requires four interlocking design decisions.

Baseline Lipid Matching

Before randomization, participants or cell-line models should be stratified by:

  • LDL-C tier (optimal, borderline, elevated)
  • Triglyceride level (normal vs. elevated)
  • HDL-C baseline
  • Current statin dose (low, moderate, high intensity per ACC/AHA criteria)

Failure to match on these variables means that any observed lipid change could reflect pre-existing statin intensity differences rather than the peptide intervention. In retatrutide studies, where triglyceride reductions can exceed 30%, an unmatched high-intensity statin arm will produce misleading comparisons.

Washout Considerations

Atorvastatin has a plasma half-life of roughly 14 hours, but its pharmacodynamic effects on LDL receptor expression persist for several days after the last dose. A minimum two-week washout is generally recommended before lipid baseline measurements are taken in studies where statin use must be paused. However, washout carries its own risk: LDL rebound can occur within days, which may introduce a time-dependent confound if baseline measurements are taken at different points post-washout across participants.

Practical options:

Design Choice Advantage Risk
Full washout before baseline Clean lipid baseline LDL rebound, ethical concern in high-risk subjects
Stable dose maintained throughout Ethically safer Statin effect folded into all arms equally
Stratified by statin status (no washout) Preserves safety, enables subgroup analysis Requires larger sample size

Control Arm Construction

When atorvastatin cannot be washed out, as is often the case in cardiovascular-risk populations, the cleanest approach is to stratify randomization by statin use and ensure each treatment arm contains an equal proportion of statin users. This transforms atorvastatin from a confounder into a pre-specified effect modifier, allowing subgroup analyses to test whether the peptide's lipid effects differ by statin background.

Interpreting Outcomes Under Dual Therapy

In a dual-therapy scenario, the observed LDL reduction is a composite of atorvastatin's HMG-CoA blockade and retatrutide's glucagon-driven lipolysis and reduced hepatic lipogenesis. Statistical models should include statin dose as a covariate. Researchers interested in the GLP-3 peptide signaling pathway will recognize that receptor-level effects on lipid metabolism are distinct from enzyme-level inhibition, making additive versus synergistic modeling a meaningful analytical choice.


Mitochondrial Models: Where MOTS-c, 5-Amino-1MQ, and Atorvastatin Intersect

Mitochondrial Models: Where MOTS-c, 5-Amino-1MQ, and Atorvastatin Intersect

The complexity deepens considerably when mitochondrial peptides enter the experimental frame. MOTS-c is a mitochondria-derived peptide that activates AMPK, promotes fatty acid oxidation, and enhances mitochondrial biogenesis. 5-Amino-1MQ is a small-molecule inhibitor of NNMT (nicotinamide N-methyltransferase) that shifts cellular metabolism toward oxidative phosphorylation and reduces lipid accumulation. Both compounds operate on pathways that atorvastatin also touches, particularly through the coenzyme Q10 axis and mitochondrial electron transport chain dynamics.

Atorvastatin reduces endogenous coenzyme Q10 synthesis as a downstream consequence of HMG-CoA reductase inhibition. This can subtly impair mitochondrial respiratory chain efficiency, which is precisely the readout that MOTS-c and 5-Amino-1MQ experiments are designed to measure. An experiment that does not account for atorvastatin's CoQ10 effect may attribute impaired mitochondrial respiration to the peptide when the statin is the actual driver.

Key mitochondrial confounds introduced by atorvastatin:

  • Reduced CoQ10 availability in Complex I/III of the electron transport chain
  • Altered mitochondrial membrane potential in hepatocytes and myocytes
  • Possible upregulation of mitochondrial biogenesis as a compensatory response

For researchers working with SS-31 mitochondrial research models or reviewing SS-31 10mg research peptide considerations, the same logic applies: any statin in the background must be pre-specified, dose-recorded, and statistically controlled. Those exploring MOTS-c peptide for sale for metabolic research should document statin co-exposure in their experimental logs as a standard practice.

When retatrutide is layered on top of this mitochondrial model, the glucagon receptor agonism adds a third metabolic signal, increased hepatic fatty acid oxidation and energy expenditure, that further overlaps with both the peptide probes and the statin background. Isolating each compound's contribution requires:

  1. Pre-specified factorial or stratified designs
  2. Mitochondrial respiration assays (Seahorse XF or equivalent) run in statin-exposed versus statin-naive conditions
  3. CoQ10 plasma levels measured as a mechanistic covariate
  4. AMPK phosphorylation status as a shared downstream readout for MOTS-c, 5-Amino-1MQ, and glucagon agonism

Conclusion

Atorvastatin in metabolic peptide experiments, controlling lipid-lowering effects in retatrutide and mitochondrial models, is not a pharmacological afterthought. It is a design variable that, if ignored, can corrupt lipid endpoints, misattribute mitochondrial readouts, and produce irreproducible results. The actionable steps are clear:

  • Stratify by statin status at randomization, or pre-specify washout windows with lipid rebound monitoring.
  • Record atorvastatin dose intensity and include it as a covariate in all lipid and mitochondrial outcome models.
  • Measure CoQ10 levels when mitochondrial peptides such as MOTS-c, SS-31, or 5-Amino-1MQ are in the experimental design.
  • Use factorial subgroup analyses to test whether retatrutide's lipid effects differ by statin background, rather than assuming homogeneity.
  • Consult current phase 3 trial protocols as they become available; as of 2026, no completed study has formally used atorvastatin as a deliberate modulator of retatrutide's lipid effects, but the mechanistic rationale for doing so is strong.

Researchers who build these controls into their protocols from the outset will produce data that is interpretable, reproducible, and genuinely informative about the independent and combined contributions of each compound. Those who do not will spend far more time explaining away confounds than advancing the science.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/atorvastatin-in-metabolic-peptide-experiments-controlling-lipid-lowering-effects.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-04 13:04:572026-10-04 13:04:57Atorvastatin in Metabolic Peptide Experiments: Controlling Lipid-Lowering Effects in Retatrutide and Mitochondrial Models
Retatrutide and Cardiovascular Disease Research: Designing Endpoints Beyond Weight Loss and A1C

Retatrutide and Cardiovascular Disease Research: Designing Endpoints Beyond Weight Loss and A1C

October 3, 2026/0 Comments/in Uncategorized/by

"

Professional () hero image with 'Retatrutide and Cardiovascular Disease' in crisp white on a deep navy semi-transparent

Cardiovascular disease kills more people with obesity and type 2 diabetes than any other complication, yet most obesity drug trials still define success almost entirely by the number on a scale or a single blood sugar marker. Retatrutide and cardiovascular disease research is now forcing a rethink of that narrow framework, pushing investigators to design endpoints that capture blood pressure, lipid profiles, inflammatory biomarkers, and hard cardiovascular events alongside weight and A1C.

Key Takeaways

  • Retatrutide, a GLP-1/GIP/glucagon triple agonist, produces striking reductions in blood pressure, triglycerides, waist circumference, and high-sensitivity C-reactive protein (hsCRP), signals that go well beyond weight loss and glycemic control.
  • Phase 3 TRIUMPH-3 data showed roughly 22-25% weight reduction at 12 mg, with systolic blood pressure falling up to 10.8 mmHg and hsCRP dropping up to 58%, but cardiovascular event rates did not reach statistical significance.
  • A dedicated cardiovascular outcomes trial (CVOT) is underway, designed specifically to evaluate major adverse cardiovascular events (MACE) in high-risk populations.
  • Distinguishing exploratory cardiometabolic signals from validated cardiovascular-outcome evidence is essential for sound protocol planning and regulatory strategy.
  • Future endpoint frameworks will likely use integrated cardiometabolic composites, covering lipids, inflammation, central adiposity, and organ-specific outcomes, rather than relying on weight and A1C alone.

Why Triple-Agonist Biology Demands Broader Endpoint Thinking

Why Triple-Agonist Biology Demands Broader Endpoint Thinking

Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, a pharmacological profile that creates metabolic effects across multiple organ systems at once. This broad reach is precisely why retatrutide clinical trials have moved quickly to incorporate cardiometabolic measures as prespecified exploratory endpoints rather than afterthoughts.

In the pivotal phase 2 obesity trial published in the New England Journal of Medicine, once-weekly retatrutide produced a mean weight reduction of 24.2% at 48 weeks at higher doses. Alongside that headline figure, investigators tracked systolic and diastolic blood pressure, waist circumference, fasting glucose, insulin, glycated hemoglobin, and most lipid parameters. That multi-factor design reflected an early recognition that glucagon receptor agonism affects hepatic lipid metabolism and energy expenditure in ways that GLP-1 alone does not.

A 2024 meta-analysis confirmed statistically significant reductions in systolic blood pressure (pooled weighted mean difference of approximately -4.70 mmHg) and diastolic blood pressure (-1.73 mmHg) across retatrutide studies. Complementary Lancet data showed systolic blood pressure falling roughly 5 mmHg with active doses versus about 1.5 mmHg on placebo over 40 weeks. These consistent signals across studies support blood pressure as a reliable intermediate endpoint, one that is biologically plausible, measurable, and clinically meaningful.

Protocol planning note: Blood pressure and lipid changes are reproducible across retatrutide studies, making them strong candidates for secondary or co-primary endpoints in future trials. They should not be treated as incidental observations.

Researchers designing studies around GLP-1 Reta compounds increasingly recognize that a single surrogate endpoint misrepresents the drug's full cardiometabolic footprint.


Cardiometabolic Endpoint Design: From Signals to Evidence

Cardiometabolic Endpoint Design: From Signals to Evidence

The TRIUMPH-3 phase 3 trial, which enrolled nearly 2,000 adults with severe obesity (BMI 35 or higher) and established cardiovascular disease, generated the most comprehensive cardiometabolic endpoint data to date. Results released in late September 2026 showed the following at the highest 12 mg dose:

Endpoint Approximate Change vs. Placebo
Systolic blood pressure -9.3 to -10.8 mmHg
Triglycerides -37 to -39.5%
Non-HDL cholesterol -16.5 to -19.6%
Waist circumference -16.9 to -19.0 cm
hsCRP -51 to -58%

These figures represent a multi-dimensional risk-modification profile that no single endpoint could capture. The hsCRP reduction in particular is notable: chronic low-grade inflammation is an independent cardiovascular risk factor, and a 51-58% drop in this marker suggests retatrutide may be modifying vascular biology beyond what weight loss alone would explain.

Equally important is the medication-burden signal. In the NEJM phase 2 trial, 41% of patients in the 8 mg group and 30% in the 12 mg group were able to discontinue at least one antihypertensive medication. This is a clinically relevant endpoint that regulatory agencies and payers increasingly value, it reflects real-world health impact, not just a surrogate number.

However, a critical distinction must be made. Despite these striking risk-factor improvements, TRIUMPH-3 did not show statistically significant reductions in major cardiovascular events. There were 44 MACE-5 events in the retatrutide group versus 52 in the placebo group, yielding a hazard ratio of 0.82 (95% CI 0.55-1.22). The MACE-3 hazard ratio was 1.12 (95% CI 0.64-1.96). The trial was not powered to detect event-level differences, and event counts were lower than projected. This is the essential gap between exploratory cardiometabolic signals and validated cardiovascular-outcome evidence.

For researchers working with related peptide frameworks such as SS-31 mitochondrial research or tesa dosage for fat loss protocols, this distinction between surrogate improvements and hard event outcomes is a recurring methodological challenge across the field.


Designing the Next Generation of Retatrutide Cardiovascular Endpoints

Designing the Next Generation of Retatrutide Cardiovascular Endpoints

A dedicated CVOT for retatrutide is now underway, targeting adults with overweight or obesity and established cardiovascular disease. This trial is explicitly designed to answer the question that TRIUMPH-3 could not: does retatrutide reduce major adverse cardiovascular events at a statistically powered level?

Recommended endpoint architecture for future retatrutide CVOTs:

  • Primary endpoint: MACE-3 (cardiovascular death, non-fatal myocardial infarction, non-fatal stroke) as the regulatory standard
  • Key secondary endpoints: Heart failure hospitalizations, kidney function trajectories, all-cause mortality
  • Exploratory biomarker endpoints: hsCRP, NT-proBNP, albuminuria, imaging-based myocardial structure measures
  • Safety hemodynamic monitoring: Pulse rate, arrhythmia surveillance, autonomic function, early diabetes studies showed increased pulse rate despite lower blood pressure, underscoring the need for comprehensive hemodynamic tracking

The inflammatory marker data from TRIUMPH-3 strengthens the case for including hsCRP and other inflammatory endpoints as prespecified secondary measures. A 51-58% reduction in hsCRP is not a minor signal; it warrants formal hypothesis testing in a powered trial.

Renal outcomes deserve explicit attention given the overlap between obesity, type 2 diabetes, and chronic kidney disease in high-risk populations. Albuminuria and estimated glomerular filtration rate trajectories should be incorporated as secondary endpoints, consistent with the approach taken in GLP-1 CVOT designs. For context on how related peptide research approaches multi-system endpoints, the GLP3 Reta compound research framework offers a useful parallel.

Lilly's March 2026 release on retatrutide in people with obesity and type 2 diabetes explicitly framed non-HDL cholesterol, triglyceride, and blood pressure improvements as key differentiating endpoints alongside glycemic control, signaling that the company's own endpoint strategy has already moved beyond weight and A1C.


Conclusion

Retatrutide and cardiovascular disease research is at a pivotal inflection point in 2026. The cardiometabolic signal is strong: blood pressure reductions of up to 10.8 mmHg, triglyceride drops approaching 40%, hsCRP reductions exceeding 50%, and clinically meaningful antihypertensive medication discontinuation rates all point to a drug with broad cardiovascular risk-modification potential.

What the evidence does not yet support is a validated claim of cardiovascular event reduction. TRIUMPH-3 was not powered for that conclusion, and the ongoing CVOT must deliver that answer before a formal cardiovascular risk-reduction indication can be pursued.

Actionable next steps for protocol designers and researchers:

  1. Build composite cardiometabolic endpoints into study designs from the start, do not treat blood pressure, lipids, and inflammation as secondary afterthoughts.
  2. Power dedicated CVOTs specifically for MACE, not just for weight loss, and include heart failure and renal outcomes as key secondary endpoints.
  3. Monitor hemodynamic safety comprehensively, including pulse rate and arrhythmia surveillance, given the mixed blood pressure and heart rate signals seen in early studies.
  4. Use inflammatory biomarkers such as hsCRP as prespecified exploratory endpoints to build the evidence base for future mechanistic claims.
  5. Follow retatrutide clinical trials progress closely, as CVOT results will determine whether the robust risk-factor improvements seen to date translate into the event-level cardiovascular benefit that patients and regulators require.

The science is compelling. The endpoint design must now match the ambition of the biology.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-and-cardiovascular-disease-research-designing-endpoints-beyond-weigh.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-03 13:04:482026-10-03 13:04:48Retatrutide and Cardiovascular Disease Research: Designing Endpoints Beyond Weight Loss and A1C
Retatrutide and Cardiovascular Disease Research: Interpreting Weight, Glycemic, and Safety Endpoints Together

Retatrutide and Cardiovascular Disease Research: Interpreting Weight, Glycemic, and Safety Endpoints Together

September 26, 2026/0 Comments/in Uncategorized/by

Fewer than 40% of adults with severe obesity and established cardiovascular disease achieve meaningful, sustained weight loss through lifestyle intervention alone, yet researchers increasingly face a more complex challenge: determining whether the dramatic weight reductions produced by newer agents like retatrutide actually translate into reduced cardiovascular events, or whether they simply improve the numbers on a lab report.

Retatrutide and cardiovascular disease research: interpreting weight, glycemic, and safety endpoints together has become one of the most consequential methodological questions in metabolic medicine as of 2026. The drug's triple agonist mechanism, targeting GIP, GLP-1, and glucagon receptors simultaneously, produces weight loss that surpasses nearly every prior pharmacological benchmark. But the population most likely to receive this therapy in clinical practice is not the uncomplicated obesity cohort studied in pivotal trials. It is the patient with prior myocardial infarction, heart failure, or advanced atherosclerosis, where surrogate endpoints and actual cardiovascular outcomes can diverge sharply.

Key Takeaways

  • Retatrutide produced mean body weight reductions of up to 24.2% at 48 weeks in phase 2 trials, exceeding prior pharmacological benchmarks.
  • Glycemic improvements, including HbA1c reductions of approximately 2.16 percentage points, occurred alongside weight loss in both diabetic and non-diabetic populations.
  • Lipid panels, blood pressure, and inflammatory markers all shifted in a cardiovascular-favorable direction, but these remain surrogate endpoints.
  • No completed cardiovascular outcomes trials have yet confirmed reductions in major adverse cardiovascular events (MACE) for retatrutide.
  • Researchers must resist treating weight loss as a direct proxy for cardiovascular benefit, particularly in high-risk populations with established disease.

Why the Severe-Obesity CVD Population Demands a Different Analytical Frame

Why the Severe-Obesity CVD Population Demands a Different Analytical Frame

The distinction between uncomplicated obesity and obesity complicated by established cardiovascular disease is not semantic, it is mechanistically and statistically critical. In uncomplicated obesity cohorts, cardiovascular risk is largely driven by modifiable metabolic factors: insulin resistance, dyslipidemia, and hypertension. Meaningful weight loss reliably improves these factors, and the pathway from surrogate improvement to event reduction is relatively well-supported by prior evidence from bariatric surgery and GLP-1 receptor agonist outcomes trials.

In the severe-obesity CVD population, however, the risk architecture is different. Atherosclerotic plaques are already established. Inflammatory burden is higher. Cardiac remodeling may be present. The relationship between short-term biomarker improvement and long-term event reduction is less predictable, and the potential for adverse interactions, including changes in heart rate, volume shifts from rapid weight loss, or arrhythmia risk, requires independent evaluation rather than inference from surrogate data.

This is the central interpretive challenge for retatrutide and cardiovascular disease research: interpreting weight, glycemic, and safety endpoints together requires researchers to resist collapsing a multi-dimensional risk picture into a single headline number.

Researchers reviewing retatrutide endpoints data should note that the phase 2 obesity trial enrolled adults without diabetes and without prior cardiovascular events. Extrapolating those results to a post-MI population with preserved or reduced ejection fraction introduces assumptions that the data do not yet support.


What the Phase 2 Data Actually Show: Weight, Glycemic, and Lipid Endpoints

What the Phase 2 Data Actually Show: Weight, Glycemic, and Lipid Endpoints

The phase 2 evidence base for retatrutide is genuinely impressive across multiple dimensions. In the pivotal obesity trial involving 338 adults, once-weekly retatrutide at 12 mg produced a mean body weight reduction of 24.2% at 48 weeks. The 8 mg dose achieved 22.8% mean loss. Placebo-adjusted weight reduction at 24 weeks was approximately 16%, with a continued downward trajectory through the trial period. Every participant receiving 8 or 12 mg weekly achieved at least 5% weight loss, a threshold widely cited in regulatory and guideline contexts as clinically meaningful for cardiovascular risk.

Glycemic endpoints reinforced the cardiometabolic signal. In a separate 36-week phase 2 study in adults with type 2 diabetes, the highest dose produced an average HbA1c decrease of approximately 2.16 percentage points alongside up to 16.9% weight reduction. Fasting glucose and fasting insulin also declined in parallel with weight loss in the obesity trial.

Key insight: A 2.16 percentage-point HbA1c reduction in a population with established type 2 diabetes is clinically substantial, but it is a surrogate marker for cardiovascular risk, not a direct measure of event prevention.

Lipid and inflammatory markers moved in favorable directions. Triglycerides, LDL cholesterol, non-HDL cholesterol, and total cholesterol all declined. HDL modestly improved. Systolic blood pressure fell by roughly 4-8 mmHg across effective dose arms in the obesity trial, and by approximately 14 mmHg at the highest dose in a manufacturer-reported analysis using an efficacy estimand. High-sensitivity C-reactive protein (hsCRP), a marker of systemic inflammation strongly associated with cardiovascular events, was also reduced.

Waist circumference decreased by approximately 10-15 cm across effective dose arms, a change relevant to visceral adiposity and its downstream effects on insulin sensitivity and hepatic lipid metabolism.

For researchers seeking GLP-3 Reta 30mg formulations for preclinical or translational research purposes, these multi-endpoint findings provide a rich framework for designing studies that go beyond single-biomarker outcomes.


Interpreting Safety Endpoints Alongside Efficacy: What Researchers Must Not Overlook

Interpreting Safety Endpoints Alongside Efficacy: What Researchers Must Not Overlook

Safety data from phase 2 trials show a profile broadly consistent with potent incretin-based therapies. Adverse events were predominantly gastrointestinal, nausea, vomiting, and diarrhea, and were more frequent at higher doses, consistent with dose-dependent receptor engagement. Serious adverse events were infrequent, and the overall safety profile was considered acceptable for continued development.

Critically, available phase 2 summaries do not signal major cardiovascular safety concerns over 36-48 weeks. But this observation carries an important caveat: 36-48 weeks is insufficient to characterize arrhythmia risk, heart failure decompensation risk, or ischemic event rates in a population with established cardiovascular disease.

Researchers must treat the absence of a safety signal as a starting point for investigation, not a conclusion.

The integrated interpretation framework for retatrutide and cardiovascular disease research, interpreting weight, glycemic, and safety endpoints together, should follow a structured logic:

  1. Stratify baseline cardiovascular risk before interpreting any endpoint change.
  2. Evaluate weight loss magnitude in the context of rate and composition, not just percentage.
  3. Examine glycemic endpoints as independent contributors to risk, not simply as weight-loss correlates.
  4. Review lipid and blood pressure changes with attention to clinical significance thresholds.
  5. Identify gaps: no completed MACE outcomes trial exists for retatrutide as of 2026.

Researchers exploring adjacent cardiometabolic peptide research, including SS-31 kidney health research, will recognize this multi-endpoint interpretive discipline as standard practice in high-risk populations where organ-level interactions are complex.

Those sourcing compounds for translational research can review available Reta 20mg for sale options or GLP-3 Reta CAG 10mg for sale formulations through verified research-grade suppliers.


Conclusion

The surrogate endpoint data for retatrutide are among the most compelling seen in pharmacological obesity research. Weight loss of 24% at 48 weeks, combined with substantial HbA1c reduction, improved lipid panels, lower blood pressure, and reduced hsCRP, constructs a plausible and mechanistically coherent case for cardiovascular benefit.

But plausibility is not proof, particularly in the severe-obesity cardiovascular disease population where the stakes are highest and the biology is most complex.

Actionable next steps for researchers and clinicians:

  • Design studies that explicitly enroll patients with established cardiovascular disease, not just metabolic risk factors.
  • Pre-specify cardiovascular safety endpoints, including arrhythmia monitoring and heart failure hospitalization, as primary or co-primary outcomes, not secondary analyses.
  • Avoid reporting weight loss as a cardiovascular outcome; report it as one component of a multi-endpoint risk profile.
  • Track cardiovascular outcomes trial timelines for retatrutide and resist extrapolating event-level benefit from surrogate data until those trials report.
  • When reviewing buy Reta online options for preclinical research, ensure purity and dosing specifications align with the phase 2 protocols to maintain translational relevance.

The science surrounding retatrutide and cardiovascular disease research: interpreting weight, glycemic, and safety endpoints together is advancing rapidly. The discipline required to interpret that science rigorously, especially in high-risk populations, must advance at the same pace.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-and-cardiovascular-disease-research-interpreting-weight-glycemic-and.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-26 13:11:232026-09-26 13:11:23Retatrutide and Cardiovascular Disease Research: Interpreting Weight, Glycemic, and Safety Endpoints Together
Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation

Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation

September 26, 2026/0 Comments/in Uncategorized/by

Fewer than one in ten obesity drugs in history have produced mean weight loss exceeding 20 percent in a phase 3 trial. Retatrutide, a triple receptor agonist targeting GIP, GLP-1, and glucagon pathways simultaneously, has now cleared that threshold by a wide margin, and the implications reach far beyond a single efficacy number.

The full scope of Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation is still being absorbed by the research community. Topline data from the TRIUMPH master protocol and its obesity sub-programs show outcomes that reframe earlier phase 2 benchmarks, raise new questions about cardiovascular labeling, and complicate how scientists define a "weight-loss drug" in the first place.

Key Takeaways

  • Phase 3 obesity data show approximately 28 percent mean weight loss at 80 weeks, with nearly 45 percent of participants achieving 30 percent or greater body weight reduction.
  • A1C improvements in the type 2 diabetes arm reinforce retatrutide's glycemic potential beyond weight loss alone.
  • Cardiovascular outcome data from the obesity-plus-established-CVD trial show MACE hazard ratios that are neutral to modestly favorable, but do not yet confirm a cardiovascular label claim.
  • Phase 2 NEJM results are now viewed as a conservative baseline rather than a peak effect.
  • Retatrutide remains investigational; no regulatory approval has been granted as of 2026.

What the Obesity Efficacy Numbers Actually Mean

What the Obesity Efficacy Numbers Actually Mean

The headline figure from the pivotal obesity phase 3 program is approximately 28 percent mean body weight reduction at 80 weeks. That number demands context. Semaglutide 2.4 mg produced roughly 15 percent in its landmark trial; tirzepatide reached approximately 22 percent at its highest dose. Retatrutide's figure, if confirmed in peer-reviewed publication, would represent the largest mean weight loss ever reported for a pharmacological agent in a phase 3 obesity study.

Equally striking is the distribution of response. Roughly 45 percent of participants achieved 30 percent or greater weight loss, a threshold that, in earlier eras, was associated only with bariatric surgery. That figure matters because it shifts the clinical conversation from average outcomes to what a subset of patients might realistically expect.

"The ceiling for pharmacological weight loss may not have been reached yet, but retatrutide has moved it substantially higher."

Researchers tracking Retatrutide Clinical Trials note that discontinuation rates and tolerability data are critical to interpreting these numbers fairly. Gastrointestinal adverse events, nausea, vomiting, diarrhea, remain the most common side effects, consistent with the incretin class. Dropout rates tied to adverse events have not been negligible, which means the 28 percent figure reflects a population that tolerated the drug well enough to complete the protocol.


Glycemic and Cardiovascular Findings: Separating Signal from Claim

Glycemic and Cardiovascular Findings: Separating Signal from Claim

The type 2 diabetes arm of the phase 3 program adds a second layer of significance to the overall data picture. A1C reductions were clinically meaningful, and the breadth of cardiometabolic risk-factor improvements, including blood pressure, triglycerides, and waist circumference, reinforces the argument that retatrutide acts as a systemic cardiometabolic modulator rather than a simple appetite suppressant.

This distinction matters for research interpretation. When a compound simultaneously reduces body weight, lowers blood glucose, improves lipid panels, and reduces blood pressure, the mechanism of benefit becomes difficult to attribute to any single pathway. That complexity is scientifically valuable but also complicates regulatory discussions about labeling.

The cardiovascular outcome trial enrolled participants with obesity and established cardiovascular disease. MACE (major adverse cardiovascular events) hazard ratios came in neutral to modestly favorable, a result that is encouraging but not yet sufficient to support a dedicated cardiovascular risk-reduction label claim. Researchers reviewing Retatrutide Clinical Trial data consistently note that risk-factor improvement and hard cardiovascular event reduction are not interchangeable endpoints.

Key distinctions from the cardiovascular data:

  • Improved risk factors (blood pressure, lipids, weight) are confirmed across trials
  • MACE hazard ratios are neutral to modestly favorable, not definitively protective
  • A cardiovascular label claim would require additional event-driven data
  • Monitoring for cardiovascular and gastrointestinal signals remains active in ongoing maintenance studies

How Phase 3 Data Reshape Research Interpretation Going Forward

How Phase 3 Data Reshape Research Interpretation Going Forward

Understanding Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation requires stepping back from individual endpoints and examining what the data collectively signal about the incretin class ceiling.

Phase 2 results published in the New England Journal of Medicine were widely cited as evidence of exceptional efficacy. Phase 3 data now reframe those results as a conservative baseline, not a peak effect. That inversion is unusual in drug development, where phase 3 trials frequently show more modest outcomes than earlier studies due to broader, more heterogeneous populations.

Several interpretive questions now dominate expert commentary:

Research Question Why It Matters
Duration of effect Does weight loss plateau, reverse, or persist beyond 80 weeks?
Head-to-head trials How does retatrutide compare directly to tirzepatide or semaglutide?
Class generalizability Do triple agonism benefits extend to other compounds in development?
Real-world CV impact Will risk-factor gains translate to event reduction outside trial conditions?
Cost and access High efficacy is only meaningful if patients can sustain treatment

The TRIUMPH maintenance study is still active, and its results will be central to answering the durability question. Industry framing has leaned heavily on "next-generation" language, but researchers caution that approval timelines and cardiovascular label expectations remain separate conversations from efficacy data.

For those following the science of triple-receptor agonism alongside related peptide research, including work on IPA Sermorelin Stack Research and metabolic modulation, the retatrutide data set offers a rare opportunity to observe how mechanism-of-action complexity translates into clinical outcomes at scale.


Conclusion

Retatrutide Phase 3 Results represent a genuine inflection point in obesity and cardiometabolic research, not because any single number is record-breaking in isolation, but because the combination of weight loss magnitude, glycemic improvement, and cardiovascular signal breadth forces a reclassification of what this compound is and what it does.

Actionable next steps for researchers and clinicians following this space:

  1. Wait for peer-reviewed publication of full TRIUMPH-1 data before drawing conclusions from topline press releases.
  2. Distinguish between risk-factor improvements and hard cardiovascular event data when evaluating cardiovascular claims.
  3. Track the maintenance study for durability evidence beyond 80 weeks.
  4. Monitor head-to-head trial announcements, which will provide the most clinically relevant comparative data.
  5. Evaluate discontinuation and tolerability rates alongside efficacy figures to form a complete picture of real-world applicability.

Retatrutide remains investigational as of 2026. The data are compelling, the mechanistic rationale is strong, and the research interpretation is still evolving. That combination makes this one of the most closely watched drug development programs in metabolic medicine today.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-phase-3-results-how-weight-loss-a1c-and-cardiovascular-findings-chan.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-26 13:10:202026-09-26 13:10:20Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation
Page 1 of 212
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top