

Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation
Fewer than one in ten obesity drugs in history have produced mean weight loss exceeding 20 percent in a phase 3 trial. Retatrutide, a triple receptor agonist targeting GIP, GLP-1, and glucagon pathways simultaneously, has now cleared that threshold by a wide margin, and the implications reach far beyond a single efficacy number.
The full scope of Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation is still being absorbed by the research community. Topline data from the TRIUMPH master protocol and its obesity sub-programs show outcomes that reframe earlier phase 2 benchmarks, raise new questions about cardiovascular labeling, and complicate how scientists define a "weight-loss drug" in the first place.
Key Takeaways
- Phase 3 obesity data show approximately 28 percent mean weight loss at 80 weeks, with nearly 45 percent of participants achieving 30 percent or greater body weight reduction.
- A1C improvements in the type 2 diabetes arm reinforce retatrutide's glycemic potential beyond weight loss alone.
- Cardiovascular outcome data from the obesity-plus-established-CVD trial show MACE hazard ratios that are neutral to modestly favorable, but do not yet confirm a cardiovascular label claim.
- Phase 2 NEJM results are now viewed as a conservative baseline rather than a peak effect.
- Retatrutide remains investigational; no regulatory approval has been granted as of 2026.
What the Obesity Efficacy Numbers Actually Mean
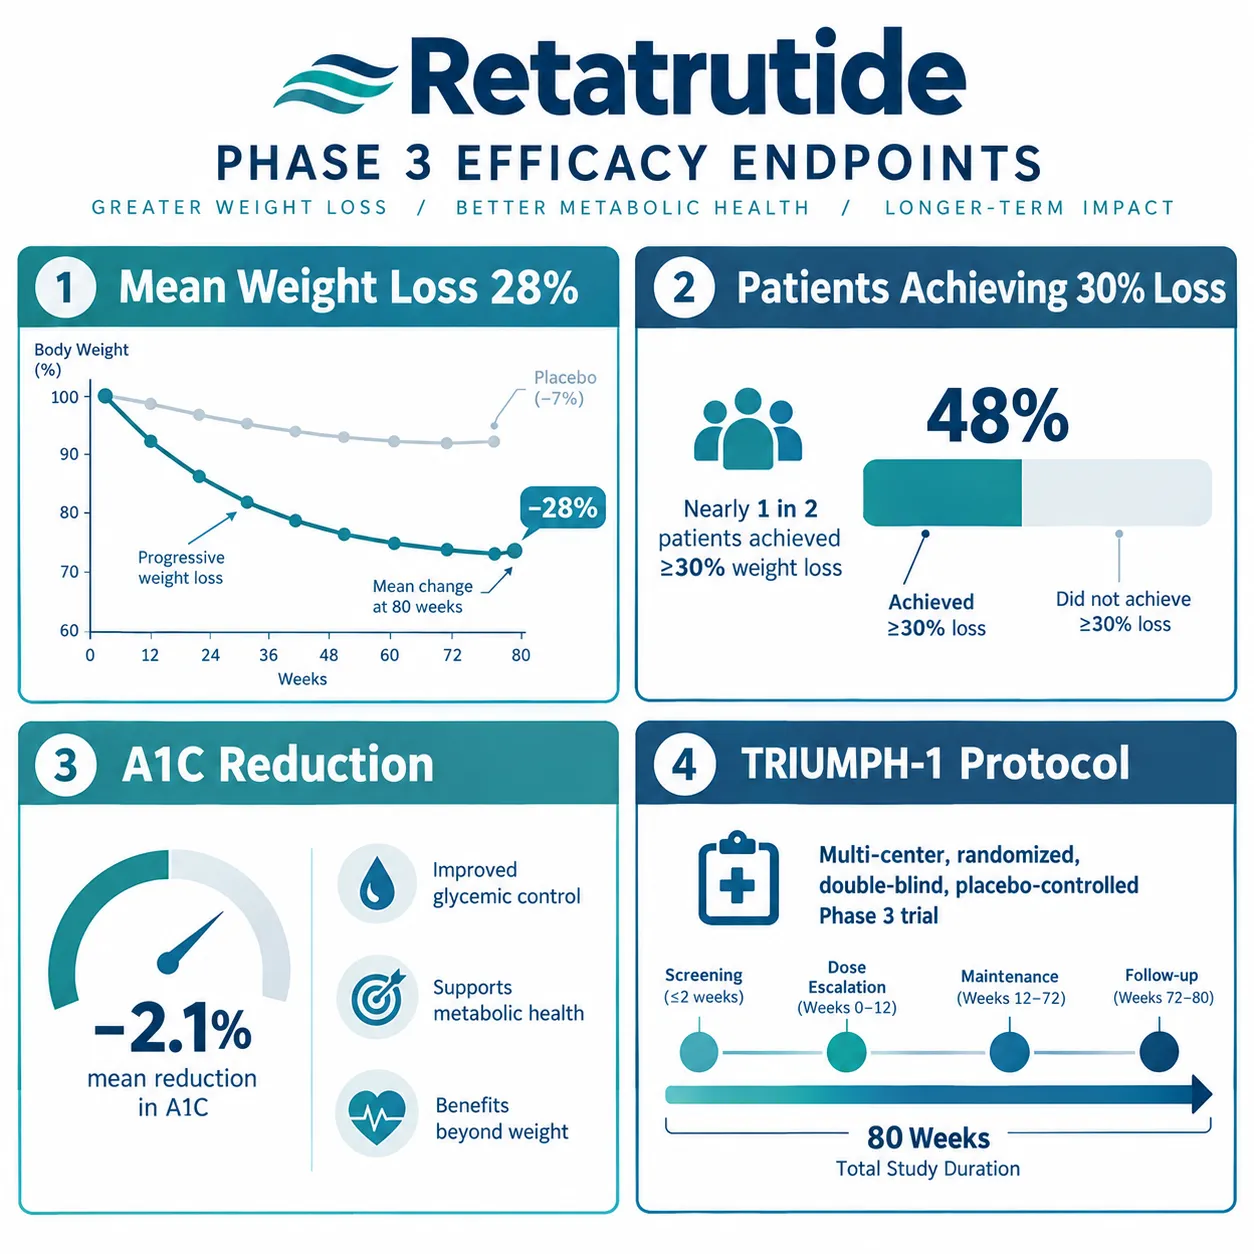
The headline figure from the pivotal obesity phase 3 program is approximately 28 percent mean body weight reduction at 80 weeks. That number demands context. Semaglutide 2.4 mg produced roughly 15 percent in its landmark trial; tirzepatide reached approximately 22 percent at its highest dose. Retatrutide's figure, if confirmed in peer-reviewed publication, would represent the largest mean weight loss ever reported for a pharmacological agent in a phase 3 obesity study.
Equally striking is the distribution of response. Roughly 45 percent of participants achieved 30 percent or greater weight loss, a threshold that, in earlier eras, was associated only with bariatric surgery. That figure matters because it shifts the clinical conversation from average outcomes to what a subset of patients might realistically expect.
"The ceiling for pharmacological weight loss may not have been reached yet, but retatrutide has moved it substantially higher."
Researchers tracking Retatrutide Clinical Trials note that discontinuation rates and tolerability data are critical to interpreting these numbers fairly. Gastrointestinal adverse events, nausea, vomiting, diarrhea, remain the most common side effects, consistent with the incretin class. Dropout rates tied to adverse events have not been negligible, which means the 28 percent figure reflects a population that tolerated the drug well enough to complete the protocol.
Glycemic and Cardiovascular Findings: Separating Signal from Claim
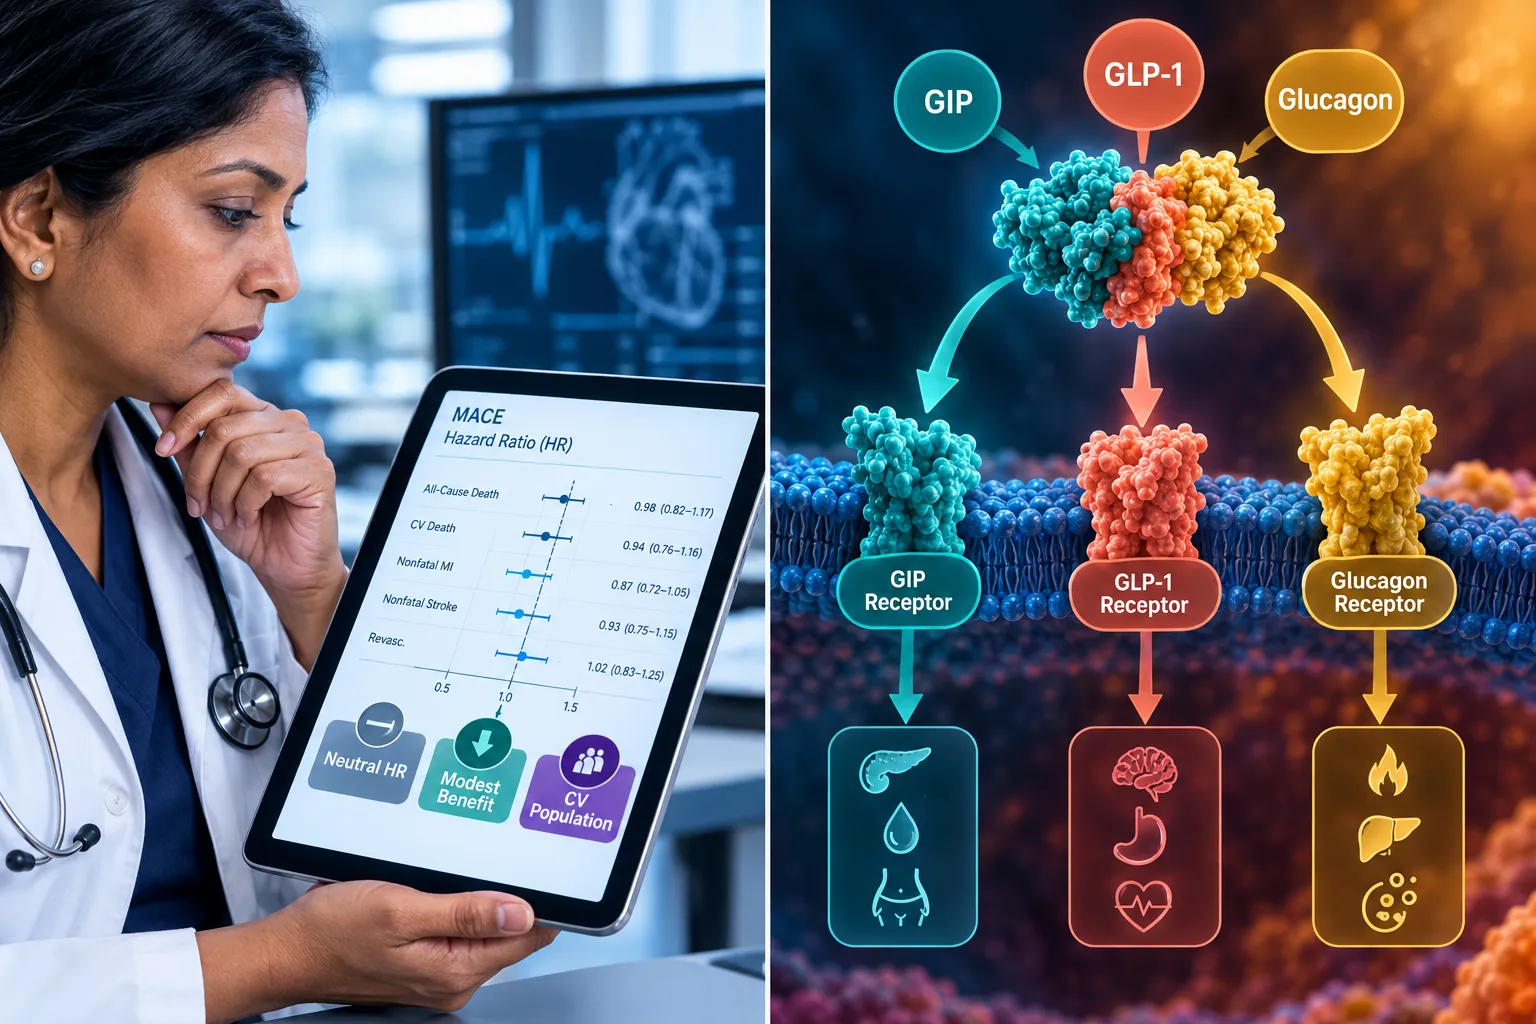
The type 2 diabetes arm of the phase 3 program adds a second layer of significance to the overall data picture. A1C reductions were clinically meaningful, and the breadth of cardiometabolic risk-factor improvements, including blood pressure, triglycerides, and waist circumference, reinforces the argument that retatrutide acts as a systemic cardiometabolic modulator rather than a simple appetite suppressant.
This distinction matters for research interpretation. When a compound simultaneously reduces body weight, lowers blood glucose, improves lipid panels, and reduces blood pressure, the mechanism of benefit becomes difficult to attribute to any single pathway. That complexity is scientifically valuable but also complicates regulatory discussions about labeling.
The cardiovascular outcome trial enrolled participants with obesity and established cardiovascular disease. MACE (major adverse cardiovascular events) hazard ratios came in neutral to modestly favorable, a result that is encouraging but not yet sufficient to support a dedicated cardiovascular risk-reduction label claim. Researchers reviewing Retatrutide Clinical Trial data consistently note that risk-factor improvement and hard cardiovascular event reduction are not interchangeable endpoints.
Key distinctions from the cardiovascular data:
- Improved risk factors (blood pressure, lipids, weight) are confirmed across trials
- MACE hazard ratios are neutral to modestly favorable, not definitively protective
- A cardiovascular label claim would require additional event-driven data
- Monitoring for cardiovascular and gastrointestinal signals remains active in ongoing maintenance studies
How Phase 3 Data Reshape Research Interpretation Going Forward
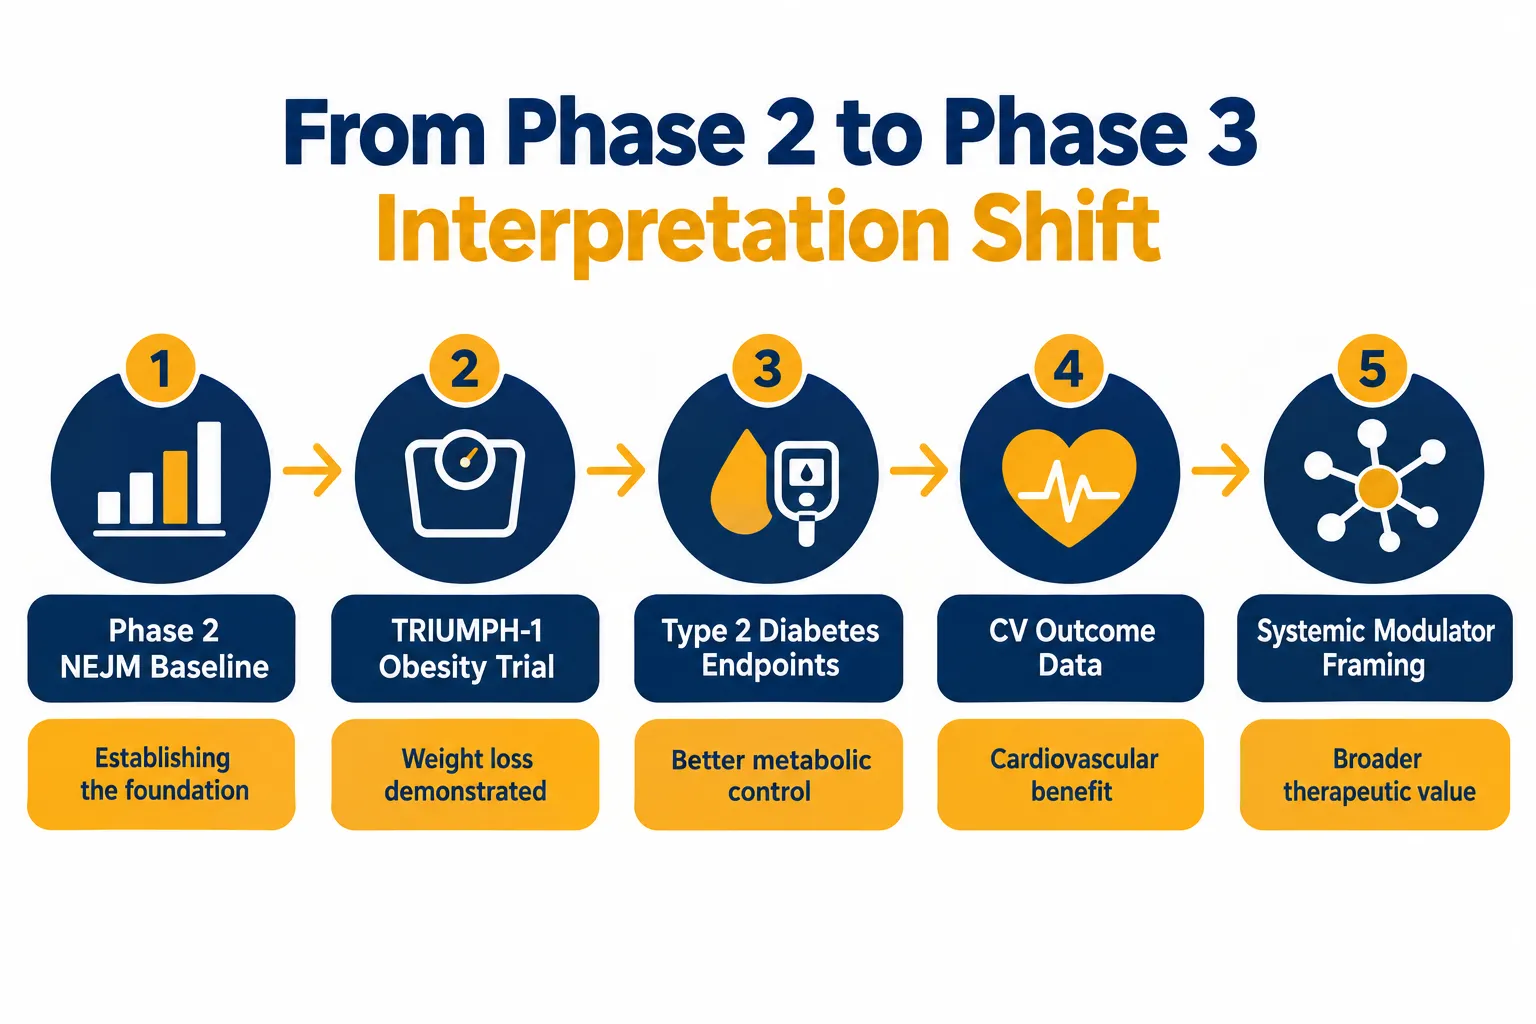
Understanding Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation requires stepping back from individual endpoints and examining what the data collectively signal about the incretin class ceiling.
Phase 2 results published in the New England Journal of Medicine were widely cited as evidence of exceptional efficacy. Phase 3 data now reframe those results as a conservative baseline, not a peak effect. That inversion is unusual in drug development, where phase 3 trials frequently show more modest outcomes than earlier studies due to broader, more heterogeneous populations.
Several interpretive questions now dominate expert commentary:
| Research Question | Why It Matters |
|---|---|
| Duration of effect | Does weight loss plateau, reverse, or persist beyond 80 weeks? |
| Head-to-head trials | How does retatrutide compare directly to tirzepatide or semaglutide? |
| Class generalizability | Do triple agonism benefits extend to other compounds in development? |
| Real-world CV impact | Will risk-factor gains translate to event reduction outside trial conditions? |
| Cost and access | High efficacy is only meaningful if patients can sustain treatment |
The TRIUMPH maintenance study is still active, and its results will be central to answering the durability question. Industry framing has leaned heavily on "next-generation" language, but researchers caution that approval timelines and cardiovascular label expectations remain separate conversations from efficacy data.
For those following the science of triple-receptor agonism alongside related peptide research, including work on IPA Sermorelin Stack Research and metabolic modulation, the retatrutide data set offers a rare opportunity to observe how mechanism-of-action complexity translates into clinical outcomes at scale.
Conclusion
Retatrutide Phase 3 Results represent a genuine inflection point in obesity and cardiometabolic research, not because any single number is record-breaking in isolation, but because the combination of weight loss magnitude, glycemic improvement, and cardiovascular signal breadth forces a reclassification of what this compound is and what it does.
Actionable next steps for researchers and clinicians following this space:
- Wait for peer-reviewed publication of full TRIUMPH-1 data before drawing conclusions from topline press releases.
- Distinguish between risk-factor improvements and hard cardiovascular event data when evaluating cardiovascular claims.
- Track the maintenance study for durability evidence beyond 80 weeks.
- Monitor head-to-head trial announcements, which will provide the most clinically relevant comparative data.
- Evaluate discontinuation and tolerability rates alongside efficacy figures to form a complete picture of real-world applicability.
Retatrutide remains investigational as of 2026. The data are compelling, the mechanistic rationale is strong, and the research interpretation is still evolving. That combination makes this one of the most closely watched drug development programs in metabolic medicine today.


Leave a Reply
Want to join the discussion?Feel free to contribute!