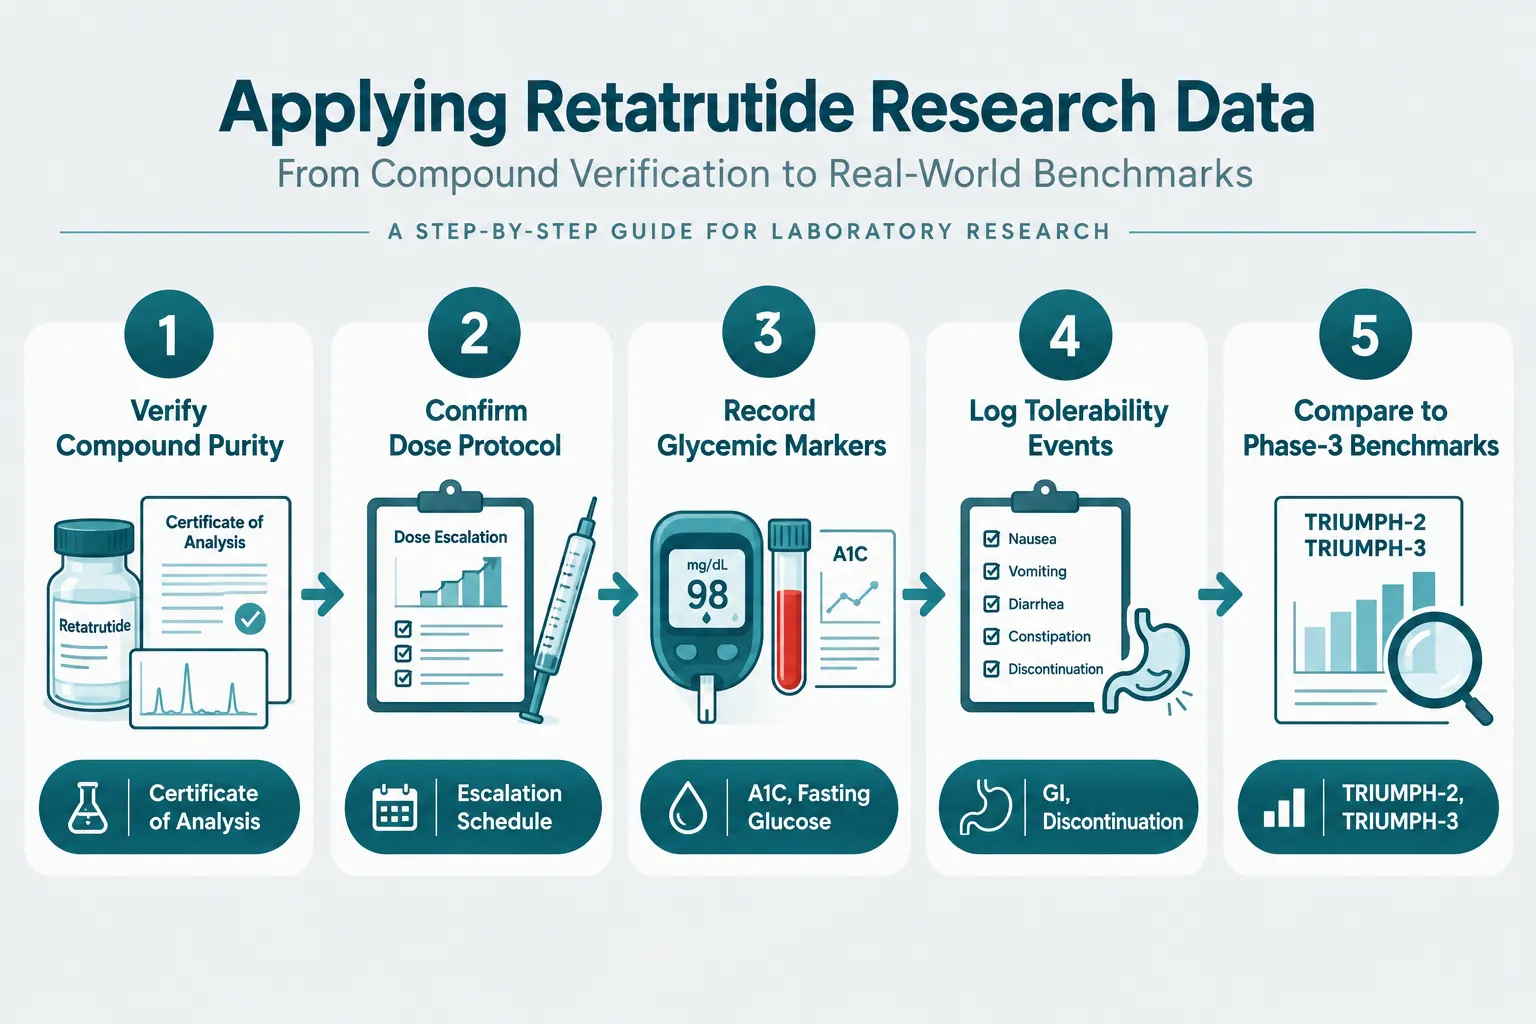
Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: retatrutide phase 3

Retatrutide Phase 3 Data: How Researchers Should Separate Appetite, Energy Expenditure, and Glycemic Effects

October 31, 2026/0 Comments/in Uncategorized/by

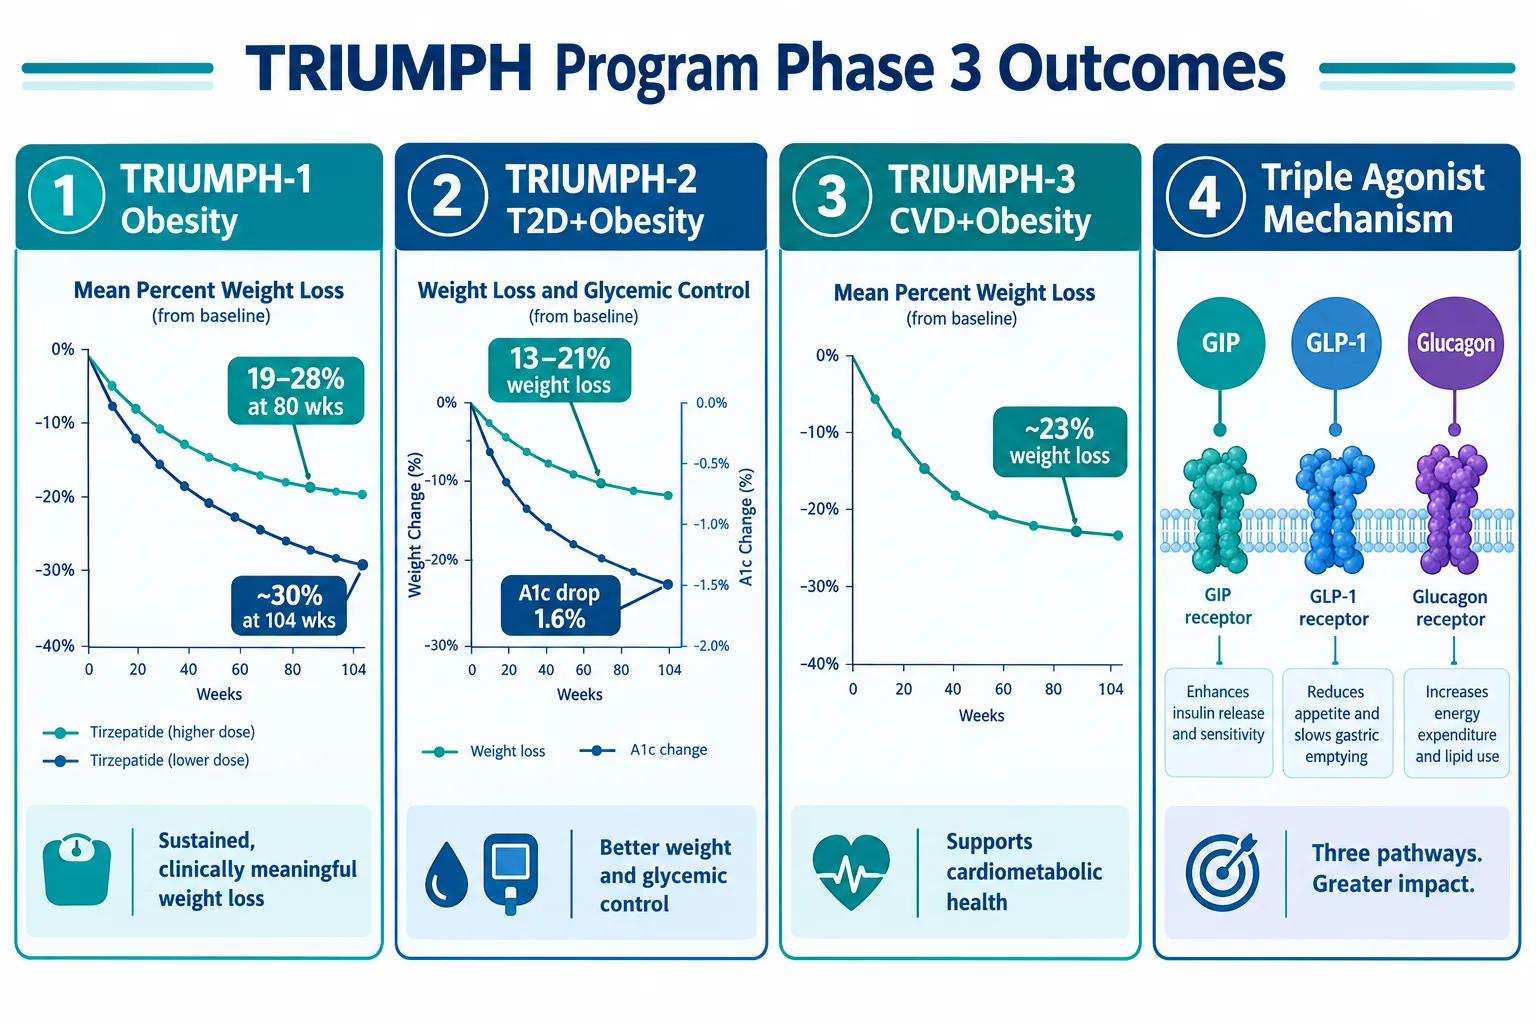
Weight loss of nearly 21% of body weight in adults with type 2 diabetes is not a single-mechanism story. Yet that is precisely what Lilly's TRIUMPH-2 trial reported for the highest dose of retatrutide at 80 weeks. When a drug simultaneously activates GLP-1, GIP, and glucagon receptors, late-stage outcomes collapse three distinct physiological pathways into one number. Understanding Retatrutide Phase 3 Data: How Researchers Should Separate Appetite, Energy Expenditure, and Glycemic Effects is therefore less a statistical exercise and more a fundamental design imperative for anyone working with this compound.

Key Takeaways

  • Retatrutide's TRIUMPH program spans four long-duration Phase 3 trials targeting obesity, type 2 diabetes, cardiovascular disease, and osteoarthritis.
  • Composite endpoints, weight and A1c, integrate appetite, energy expenditure, and glucose effects rather than measuring each independently.
  • Separating the three pathways requires dose-response modeling, indirect calorimetry substudies, and careful covariate design.
  • TRIUMPH-2 reported up to 20.8% weight loss and A1c reductions of 1.6 percentage points, underscoring the magnitude of intertwined effects.
  • Researchers sourcing this peptide for mechanistic study should prioritize verified purity and documented traceability.

The TRIUMPH Program: What the Phase 3 Architecture Looks Like

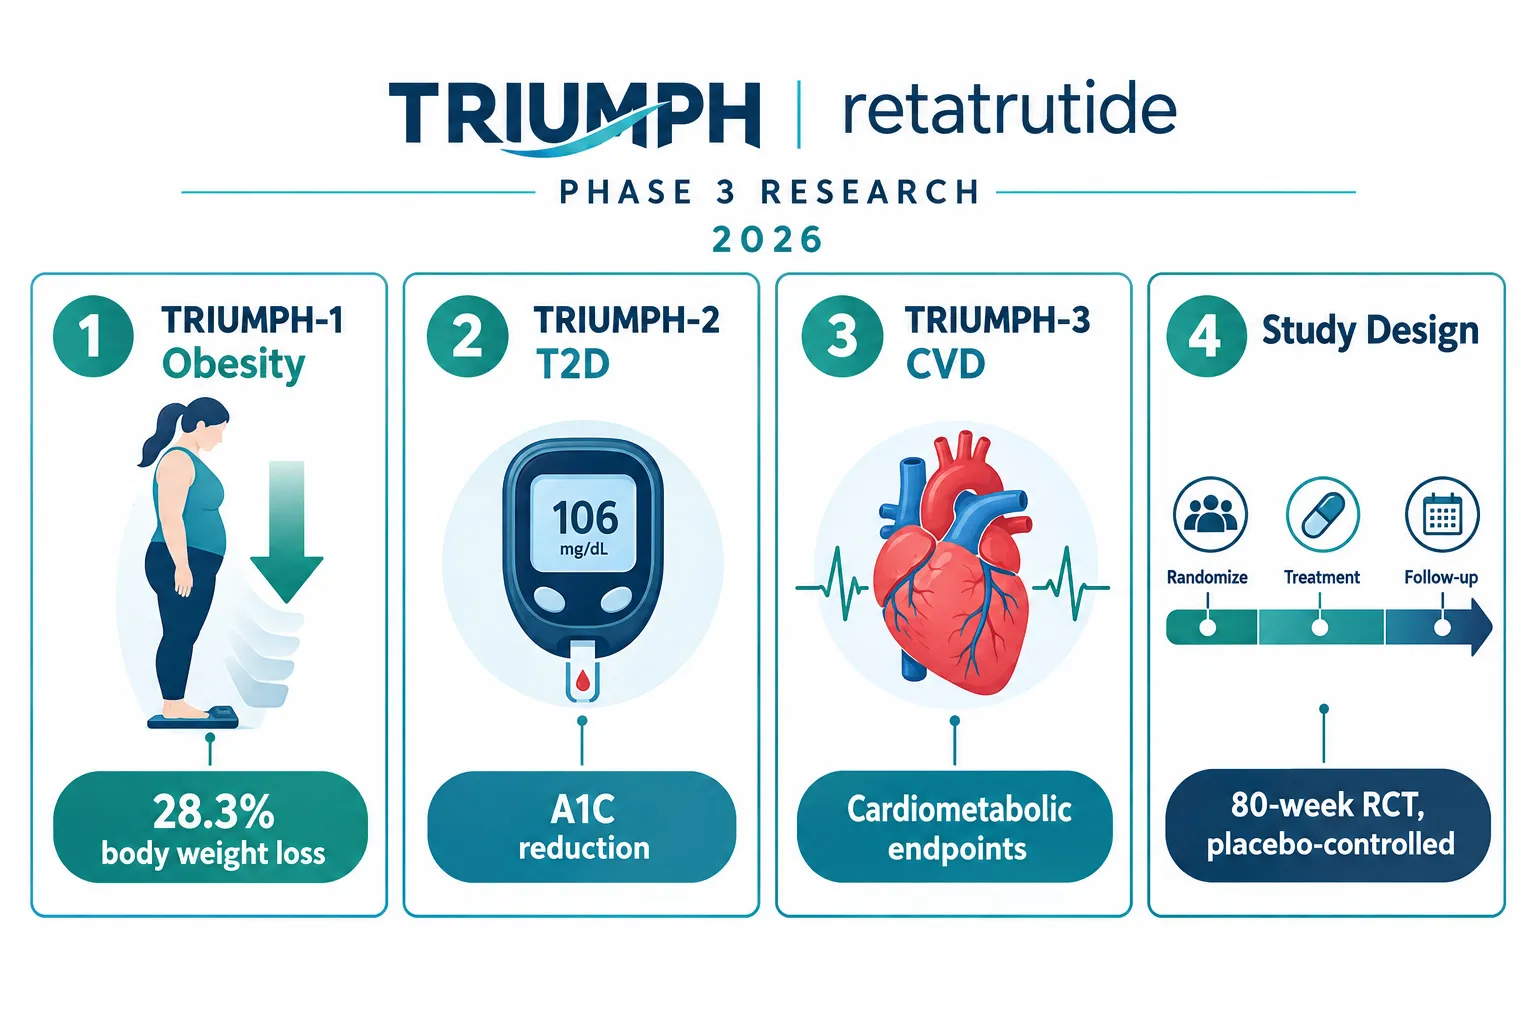
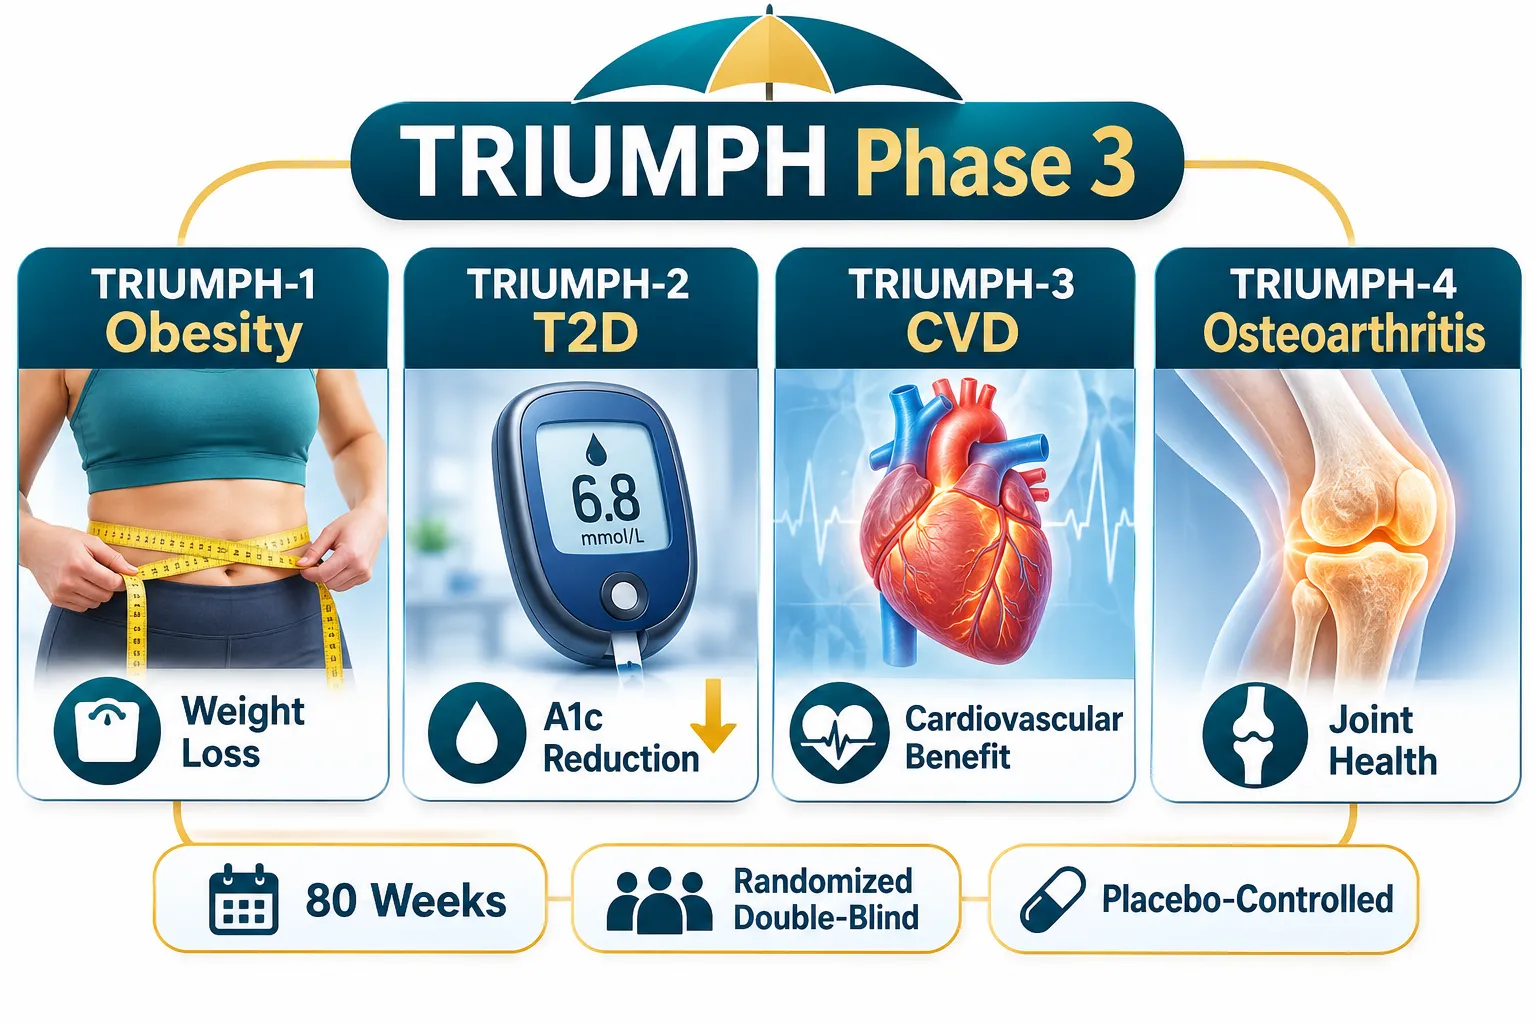
Lilly built the TRIUMPH umbrella around four registrational trials: TRIUMPH-1 for obesity and overweight, TRIUMPH-2 for obesity plus type 2 diabetes, TRIUMPH-3 for severe obesity with established cardiovascular disease, and TRIUMPH-4 for obesity with knee osteoarthritis.
The TRIUMPH Program: What the Phase 3 Architecture Looks Like

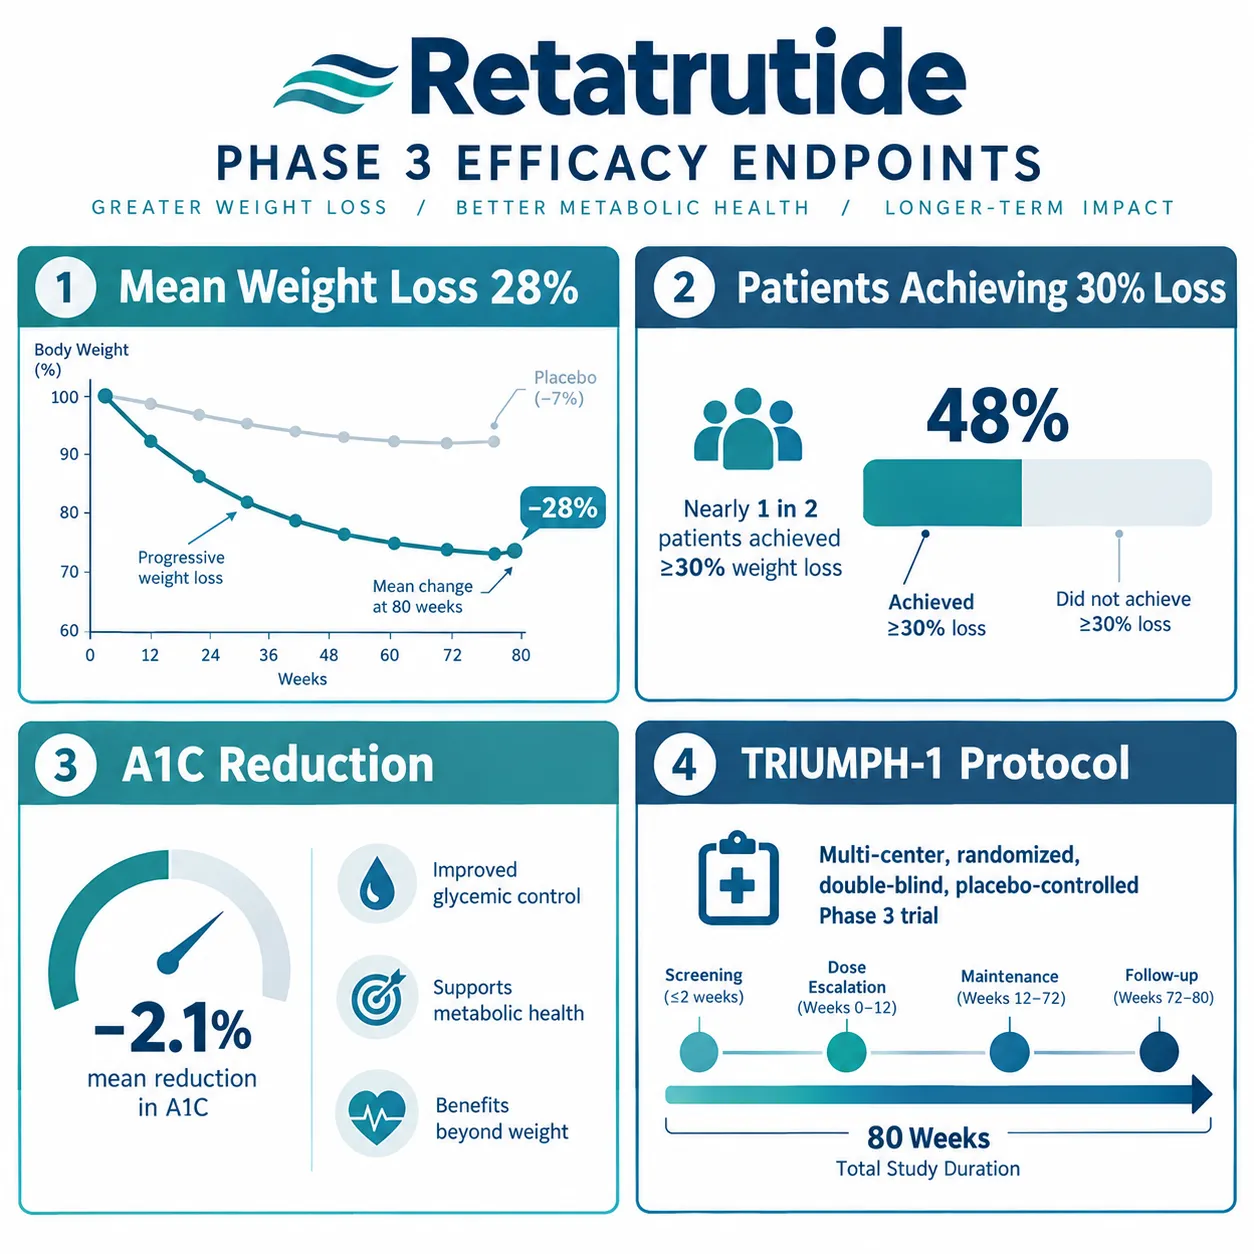
Every trial uses an 80-week (TRIUMPH-1) or similarly long randomized, double-blind, placebo-controlled design. All three weekly doses, 4 mg, 9 mg, and 12 mg, met primary and key secondary endpoints in TRIUMPH-1, delivering clinically meaningful reductions across the board. In TRIUMPH-2, those doses produced average weight reductions of 12.7%, 19.1%, and 20.8%, respectively, paired with A1c drops reaching 1.6 percentage points at 80 weeks.

This breadth positions retatrutide as a system-level metabolic intervention rather than a narrowly targeted weight drug. That ambition is also the core measurement challenge. For researchers exploring visceral fat research endpoints, a single composite outcome obscures which receptor arm is driving depot-specific fat loss.


Why Composite Endpoints Obscure Mechanism in Retatrutide Phase 3 Data

Registrational trials are optimized for regulatory approval, not mechanistic precision. TRIUMPH-2 uses weight and A1c as primary readouts across fixed doses over 80 weeks. This design is efficient but it integrates appetite suppression, altered energy expenditure, and improved glucose metabolism into a single output stream.

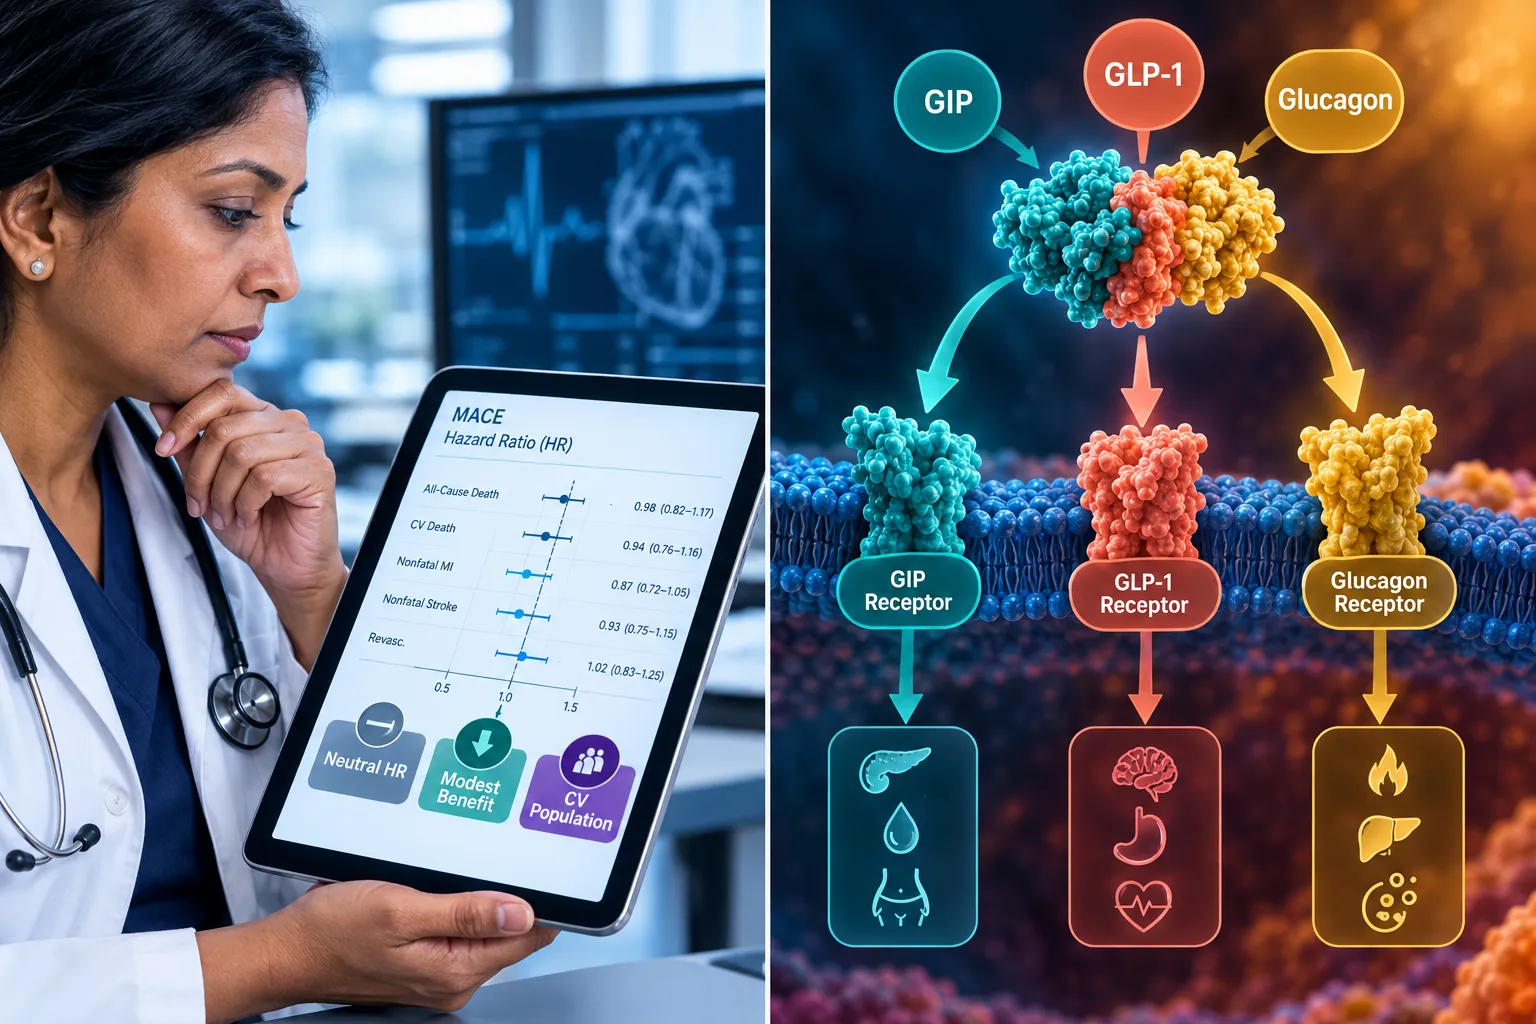
Consider what each receptor arm contributes:

Receptor Primary Metabolic Role Expected Measurable Output
GLP-1 Satiety signaling, gastric emptying, insulin secretion Reduced caloric intake, A1c improvement
GIP Adipose energy storage, insulin potentiation Enhanced fat oxidation, energy expenditure
Glucagon Hepatic glucose output, lipolysis, thermogenesis Fasting glucose reduction, resting metabolic rate

When a 12 mg dose produces 49.6 lbs of weight loss, researchers cannot determine from that number alone how much came from eating less versus burning more versus normalizing glucose flux. This is the central problem when interpreting Retatrutide Phase 3 Data: How Researchers Should Separate Appetite, Energy Expenditure, and Glycemic Effects.

"A triple agonist produces a triple blind spot in composite outcomes, each mechanism borrows statistical credit from the others."

Researchers working with GLP-3 Reta in pre-clinical or mechanistic contexts face this same layering problem at a smaller scale.


A Measurement Framework for Disaggregating the Three Pathways

Properly interpreting Retatrutide Phase 3 Data: How Researchers Should Separate Appetite, Energy Expenditure, and Glycemic Effects demands a layered analytical strategy built around three pillars.

Pillar 1: Appetite, Caloric Intake Substudies

Appetite effects are best captured through:

  • Validated food diaries or doubly-labeled water intake estimates nested within the main trial
  • Appetite visual-analogue scales at standardized time points
  • Gastric emptying scintigraphy to separate mechanical slowing from central satiety

GLP-1 receptor activity is the dominant driver here. Isolating intake data from weight change requires holding physical activity constant as a covariate.

Pillar 2: Energy Expenditure, Metabolic Rate Substudies

Glucagon receptor agonism raises resting metabolic rate through hepatic and brown adipose thermogenesis. Measuring this requires:

  • Indirect calorimetry at fasting baseline and post-dose intervals
  • Respiratory quotient tracking to detect substrate oxidation shifts
  • Lean mass preservation data (DEXA) to separate fat loss from muscle catabolism

Researchers interested in parallel mitochondrial mechanisms may find context in SS-31 mitochondrial research frameworks, which use similar calorimetric substudies.

Pillar 3: Glycemic Control, Glucose Kinetics

A1c is a lagging average. More granular separation requires:

  • Fasting plasma glucose and 2-hour post-load glucose at each visit
  • Homeostatic model assessment of insulin resistance (HOMA-IR)
  • Continuous glucose monitoring substudies to capture time-in-range independently of weight-driven improvement

Because TRIUMPH-2 already embeds A1c as a primary endpoint, researchers can build co-primary models that partial out glycemic improvement from the weight-loss coefficient using mediation analysis.

Practical Design Additions

  • Dose-response modeling across the 4/9/12 mg arms provides natural variation to test pathway dominance at different receptor occupancy levels.
  • Covariate-adjusted mixed-effects models that include baseline insulin sensitivity, lean mass, and physical activity can attribute variance to each pathway.

For investigators sourcing research-grade material, verified purity matters enormously. Options such as GLP3 Reta 10mg and suppliers with buy Reta peptide documentation provide a starting point, though independent assay confirmation remains essential. Researchers seeking sourcing context can also review GLP-1 peptide buy: generational research concepts and sourcing notes for broader traceability considerations.


Applying the Framework Across TRIUMPH Subpopulations

TRIUMPH-3 targets adults with severe obesity (BMI 35 kg/m² or higher) and established cardiovascular disease. In this population, the glucagon-driven thermogenic arm becomes especially relevant because baseline resting metabolic rate is often suppressed. Separating energy expenditure gains from appetite-driven intake reductions is clinically critical when cardiovascular safety depends on muscle-preserving fat loss rather than lean mass wasting.

TRIUMPH-4's osteoarthritis cohort adds a functional dimension: weight loss improves joint load, but glycemic normalization also reduces inflammatory cytokines. Attributing pain score improvements requires knowing how much of the weight loss is adipose-driven (energy balance) versus inflammation-driven (glycemic control).

The master protocol structure of TRIUMPH-1, which nests sleep apnea and osteoarthritis subsets within the core obesity design, actually offers a methodological advantage. Researchers can exploit these nested groups as natural experiments, comparing pathway-level effects across populations with different baseline metabolic phenotypes.


Conclusion

Retatrutide's Phase 3 data represent a landmark in multi-receptor metabolic pharmacology. However, the same breadth that makes TRIUMPH's outcomes impressive makes mechanistic interpretation difficult without deliberate disaggregation.

Actionable next steps for researchers:

  1. Design or lobby for substudies that capture indirect calorimetry and caloric intake within the existing TRIUMPH framework.
  2. Apply mediation analysis to published TRIUMPH-2 data to partial out A1c improvement from weight-loss-mediated glycemic change.
  3. Use dose-response variation across the 4/9/12 mg arms as a natural instrument for identifying receptor-dominant pathway effects.
  4. Prioritize sourcing from suppliers with documented assay data when conducting independent mechanistic studies. Resources on AOD 9604 research method notes, storage and traceability offer a useful model for traceability standards to apply to retatrutide as well.

Separating appetite, energy expenditure, and glycemic effects in Retatrutide Phase 3 Data is not optional for researchers who want to understand what this molecule actually does, it is the scientific obligation that late-stage composite endpoints leave unfinished.

https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 0 0 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-31 13:05:132026-10-31 13:05:13Retatrutide Phase 3 Data: How Researchers Should Separate Appetite, Energy Expenditure, and Glycemic Effects
Retatrutide Phase 3 Results for Sleep Apnea and Osteoarthritis: How Researchers Should Select Disease-Specific Endpoints

Retatrutide Phase 3 Results for Sleep Apnea and Osteoarthritis: How Researchers Should Select Disease-Specific Endpoints

October 21, 2026/0 Comments/in Uncategorized/by

A drug that cuts dangerous breathing pauses by more than 60 percent and slashes knee pain scores by nearly three-quarters, those are not typical weight-loss numbers. They are disease-specific signals, and they only appear when researchers choose the right endpoint from the start. The retatrutide Phase 3 results for sleep apnea and osteoarthritis: how researchers should select disease-specific endpoints is exactly the question that the TRIUMPH program answers in 2026, offering a practical blueprint for endpoint strategy across multi-system obesity-related conditions.

Key Takeaways

  • Retatrutide's TRIUMPH Phase 3 program met primary endpoints across obesity, obstructive sleep apnea (OSA), and knee osteoarthritis (OA) at approximately 80 weeks.
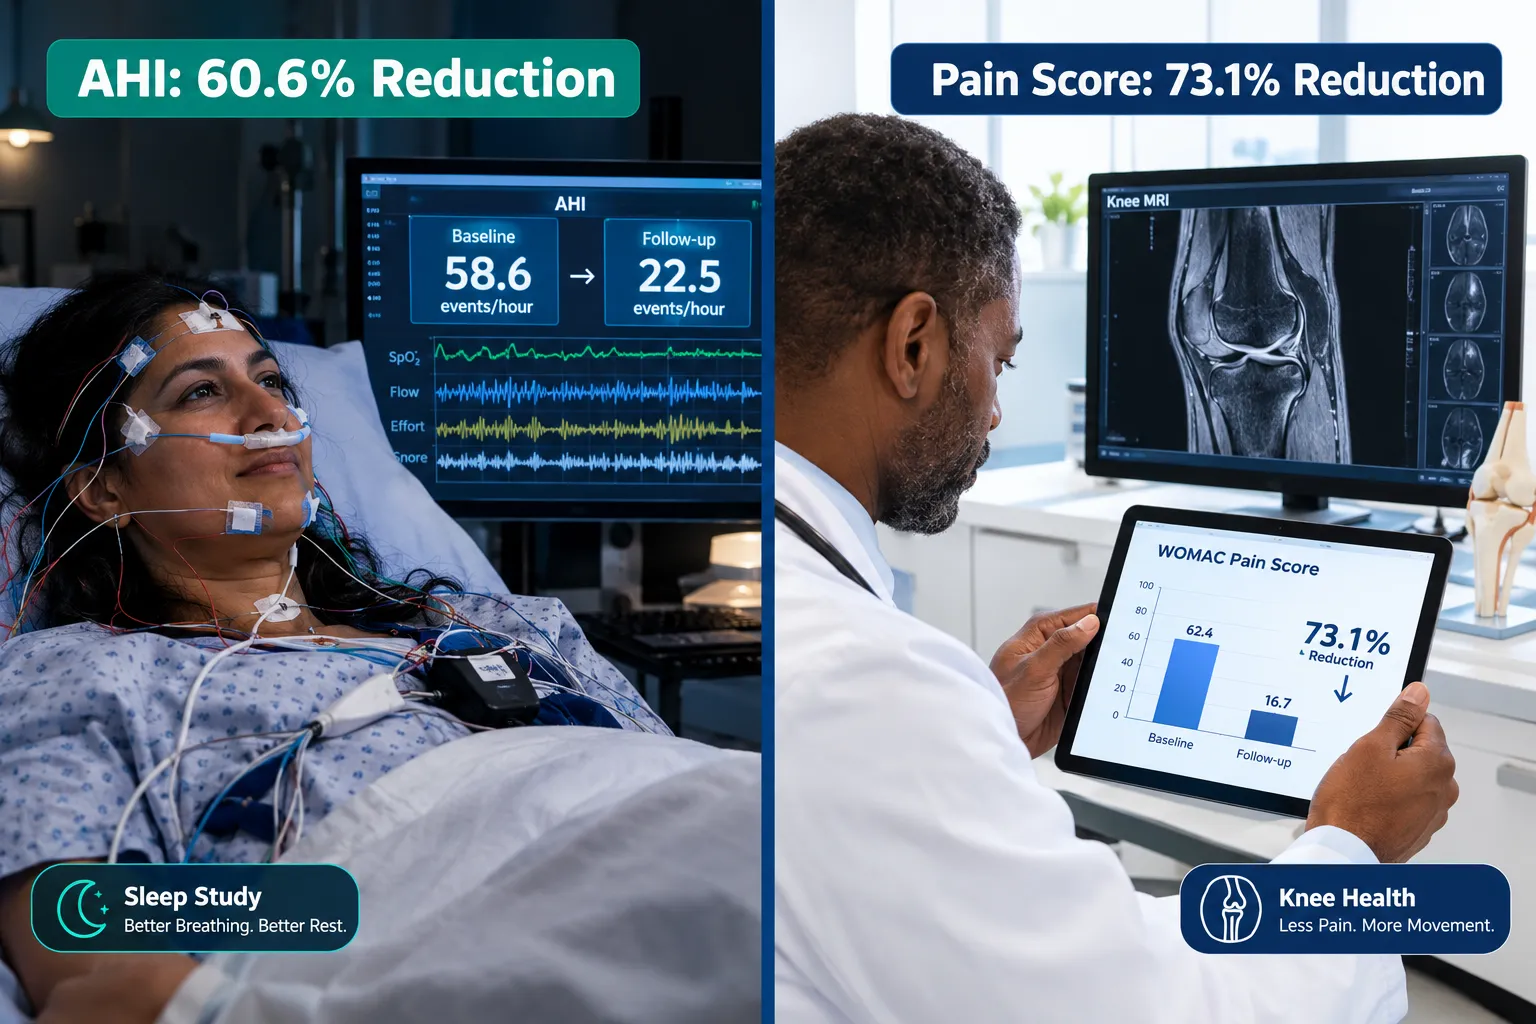
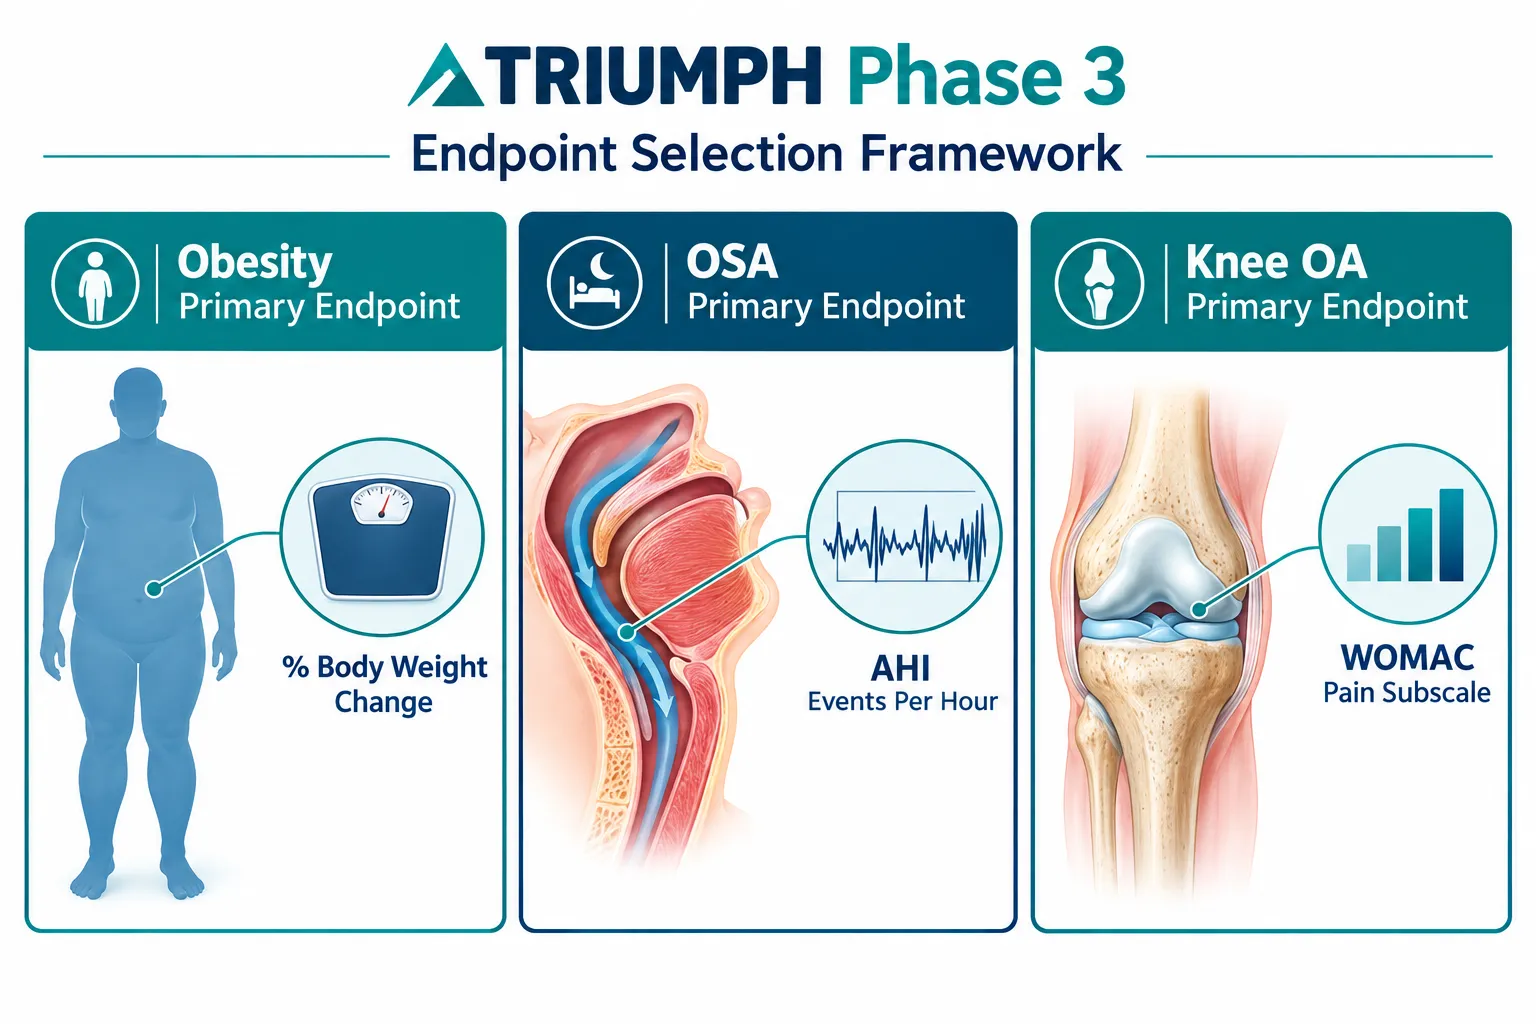
  • The Apnea-Hypopnea Index (AHI) and the WOMAC pain subscale were chosen as disease-specific primary endpoints for OSA and knee OA, respectively, capturing benefits that go beyond weight loss alone.
  • In knee OA, retatrutide reduced WOMAC pain scores by 73.1%; in OSA, AHI fell by 60.6%, roughly 36 fewer breathing pauses per hour.
  • Co-primary endpoint designs (pairing a disease-specific measure with percent body weight change) are now a model strategy for obesity-linked comorbidities.
  • Full peer-reviewed publications are still pending; most detailed data currently come from company releases and congress presentations.

Why Endpoint Choice Defines What a Trial Can Prove

Clinical trials answer only the questions their endpoints ask. In obesity research, percent change in body weight is a well-validated primary measure, but it cannot tell a regulator whether a patient's knee hurts less or whether their airway stays open at night. That gap is exactly why the retatrutide Phase 3 results for sleep apnea and osteoarthritis demand a closer look at endpoint selection methodology.

The TRIUMPH program enrolled 2,339 adults in its flagship obesity trial (TRIUMPH-1), with predefined subsets for knee OA and OSA. Mean weight loss reached 25.9% at the 9 mg dose and 28.3% at 12 mg over 80 weeks. Those figures are powerful, but they served as the platform from which disease-specific endpoints could be evaluated, not as a substitute for them.

Why Endpoint Choice Defines What a Trial Can Prove

Researchers working with GLP-3 Reta peptide materials in preclinical settings face a comparable decision: a biomarker of metabolic activity alone will not capture tissue-level or airway-level outcomes without a purpose-built measurement tool.


Retatrutide Phase 3 Results for Sleep Apnea: The AHI as a Precision Tool

The AHI counts how many times per hour breathing stops or becomes dangerously shallow during sleep. It is the gold-standard disease-specific endpoint for OSA trials because it directly quantifies the pathology, not just a correlate of it.

In participants with moderate-to-severe OSA and obesity, retatrutide reduced AHI by approximately 36.1 events per hour, a 60.6% drop from a baseline of 58.6 events per hour. Clinical commentary from 2026 notes that this reduction appears larger than what weight loss alone would predict, suggesting the AHI was sensitive enough to detect both respiratory and weight-mediated mechanisms simultaneously.

Why AHI worked here:

  • It is continuous, allowing detection of graded improvement.
  • It has established regulatory precedent as a primary endpoint in sleep apnea device and drug trials.
  • It separates responders from non-responders in a way that subjective sleepiness scores cannot.

Secondary measures that strengthen AHI data:

Endpoint Category Example Measure What It Adds
Subjective sleep quality Epworth Sleepiness Scale Patient-reported burden
Cardiometabolic safety Blood pressure, HbA1c Systemic risk context
Body composition Percent fat mass Weight-mediated pathway
Daytime function Patient global impression Functional relevance

Retatrutide Phase 3 Results for Sleep Apnea: The AHI as a Precision Tool

Researchers evaluating retatrutide through the GLP1-Reta research overview will recognize that the triple agonist mechanism, targeting GIP, GLP-1, and glucagon receptors, creates multiple physiological pathways, each of which may need its own measurement instrument.


Retatrutide Phase 3 Results for Osteoarthritis: Applying the WOMAC Subscale Correctly

Knee osteoarthritis endpoints present a different challenge: pain is subjective, functional limitation varies by patient, and structural changes on imaging may not correlate with symptoms in the short term. The TRIUMPH-4 trial addressed this by selecting the WOMAC pain subscale as one co-primary endpoint alongside percent body weight change.

Results showed a mean reduction of 4.3 points (73.1%) from a baseline WOMAC pain score of 6.0. That magnitude is clinically meaningful by any established threshold for minimal clinically important difference (MCID) in knee OA research.

What makes the WOMAC pain subscale the right choice:

  • Disease specificity: It targets pain in the knee joint, not global pain or mood.
  • Regulatory familiarity: Accepted by the FDA and EMA in prior OA drug approvals.
  • Sensitivity to change: Its five-item format detects graded improvement across activities.
  • Patient relevance: Items map directly to daily-life tasks like stair climbing and walking.

The co-primary design, requiring both the WOMAC pain subscale and percent body weight change to meet significance, is particularly important. It forces the trial to demonstrate that symptom relief is not simply a product of patients moving more because they weigh less. It separates the mechanical unloading benefit from any direct anti-inflammatory or analgesic effect.

Researchers interested in complementary tissue-level mechanisms can review related work on SS-31 mitochondrial research themes and SS-31 10mg research peptide considerations as examples of how endpoint granularity differs across biological pathways.


Building a Dual-Endpoint Strategy: A Practical Framework for Researchers

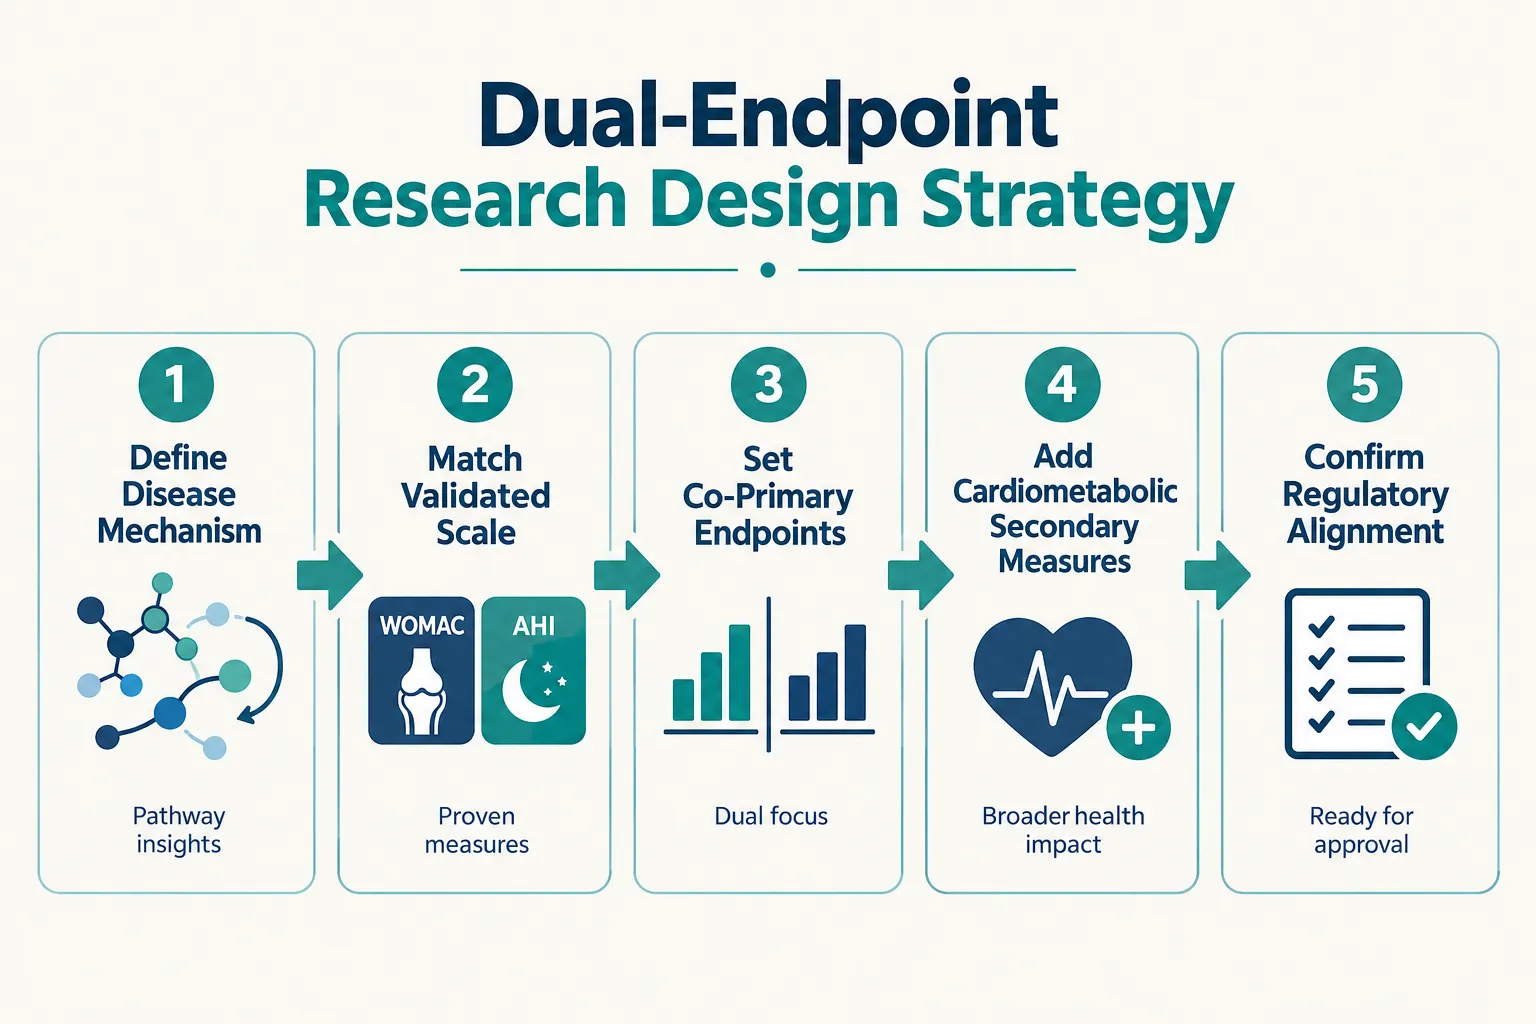
The TRIUMPH program's most transferable contribution may be its endpoint architecture. Across all four trials, Lilly paired a disease-specific primary measure with percent body weight change, then added cardiometabolic and functional secondary endpoints.

Building a Dual-Endpoint Strategy: A Practical Framework for Researchers

Researchers designing their own studies can apply this logic in five steps:

  1. Identify the dominant disease mechanism, airway collapse, joint degradation, glycemic dysregulation, or another target.
  2. Select a validated, regulatory-precedented instrument, AHI for OSA, WOMAC for OA, HbA1c for diabetes.
  3. Pair it with a weight-change measure when obesity is a contributing factor, creating a co-primary structure.
  4. Add functional and patient-reported secondary outcomes to capture daily-life impact.
  5. Include cardiometabolic safety endpoints to satisfy regulatory risk-benefit expectations.

This framework is relevant not only for large Phase 3 programs but for any investigator planning endpoint-driven preclinical or early-phase research. Resources on how to buy Reta and where to buy Reta for research-grade supply are available for investigators setting up controlled studies.

A key principle drawn from the TRIUMPH data: if the chosen endpoint is not sensitive enough to detect the full mechanism of action, a genuinely effective intervention can appear weaker than it is. The 60.6% AHI reduction likely would have been invisible if the trial had used body weight alone as its primary measure.


Conclusion

The retatrutide Phase 3 results for sleep apnea and osteoarthritis: how researchers should select disease-specific endpoints is not an abstract methodological question, it has direct consequences for what regulators see, what clinicians can act on, and what patients ultimately receive. The TRIUMPH program demonstrates that a triple agonist targeting metabolic pathways can produce profound, measurable improvements in OSA and knee OA, but only because the trials were designed to look for those improvements with the right tools.

Actionable next steps for researchers:

  • Use AHI as the primary endpoint for any OSA-adjacent intervention study; pair it with at least one cardiometabolic secondary measure.
  • Apply the WOMAC pain subscale as a co-primary alongside body weight change when studying obesity-related joint disease.
  • Review the TRIUMPH co-primary design structure before finalizing any protocol that addresses an obesity comorbidity.
  • Monitor peer-reviewed publications from the TRIUMPH program as they become available, since full datasets will refine secondary endpoint interpretations.
  • Consult the Reta 30mg research tag and GLP-3 Reta 20mg product page for research-grade material specifications relevant to dose-ranging studies.

Disease-specific endpoints do not just measure outcomes, they define what a drug is allowed to become.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-phase-3-results-for-sleep-apnea-and-osteoarthritis-how-researchers-s.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-21 13:05:412026-10-21 13:05:41Retatrutide Phase 3 Results for Sleep Apnea and Osteoarthritis: How Researchers Should Select Disease-Specific Endpoints
How to Interpret Weight Loss, A1C, and Discontinuation Rates in Retatrutide Research

How to Interpret Weight Loss, A1C, and Discontinuation Rates in Retatrutide Research

October 17, 2026/0 Comments/in Uncategorized/by

"

Professional () hero image with 'How to Interpret Weight Loss, A1C' in crisp white modern centered on a deep navy

A single phase-2 trial published in the New England Journal of Medicine reported mean body-weight reductions exceeding 17% at 24 weeks, a number that reshaped expectations for the entire incretin drug class. Yet that headline figure conceals at least six methodological layers that any serious researcher must unpack before drawing conclusions. Understanding how to interpret weight loss, A1C, and discontinuation rates in retatrutide research is not optional; it is the difference between actionable data and misleading benchmarks.

Key Takeaways

  • Percent weight loss and absolute weight loss tell different stories; always identify which metric a study reports.
  • A1C reductions must be read alongside baseline glycemic status, exposure duration, and dose level.
  • Discontinuation rates introduce survivorship bias; completer-only analyses inflate efficacy estimates.
  • Dose-escalation schedules vary across trials and directly affect both tolerability and endpoint timing.
  • Missing-data handling methods, such as last observation carried forward versus modified intent-to-treat, materially change how results should be interpreted.

Understanding the Metrics: A Research Checklist for Retatrutide Trials

Understanding the Metrics: A Research Checklist for Retatrutide Trials

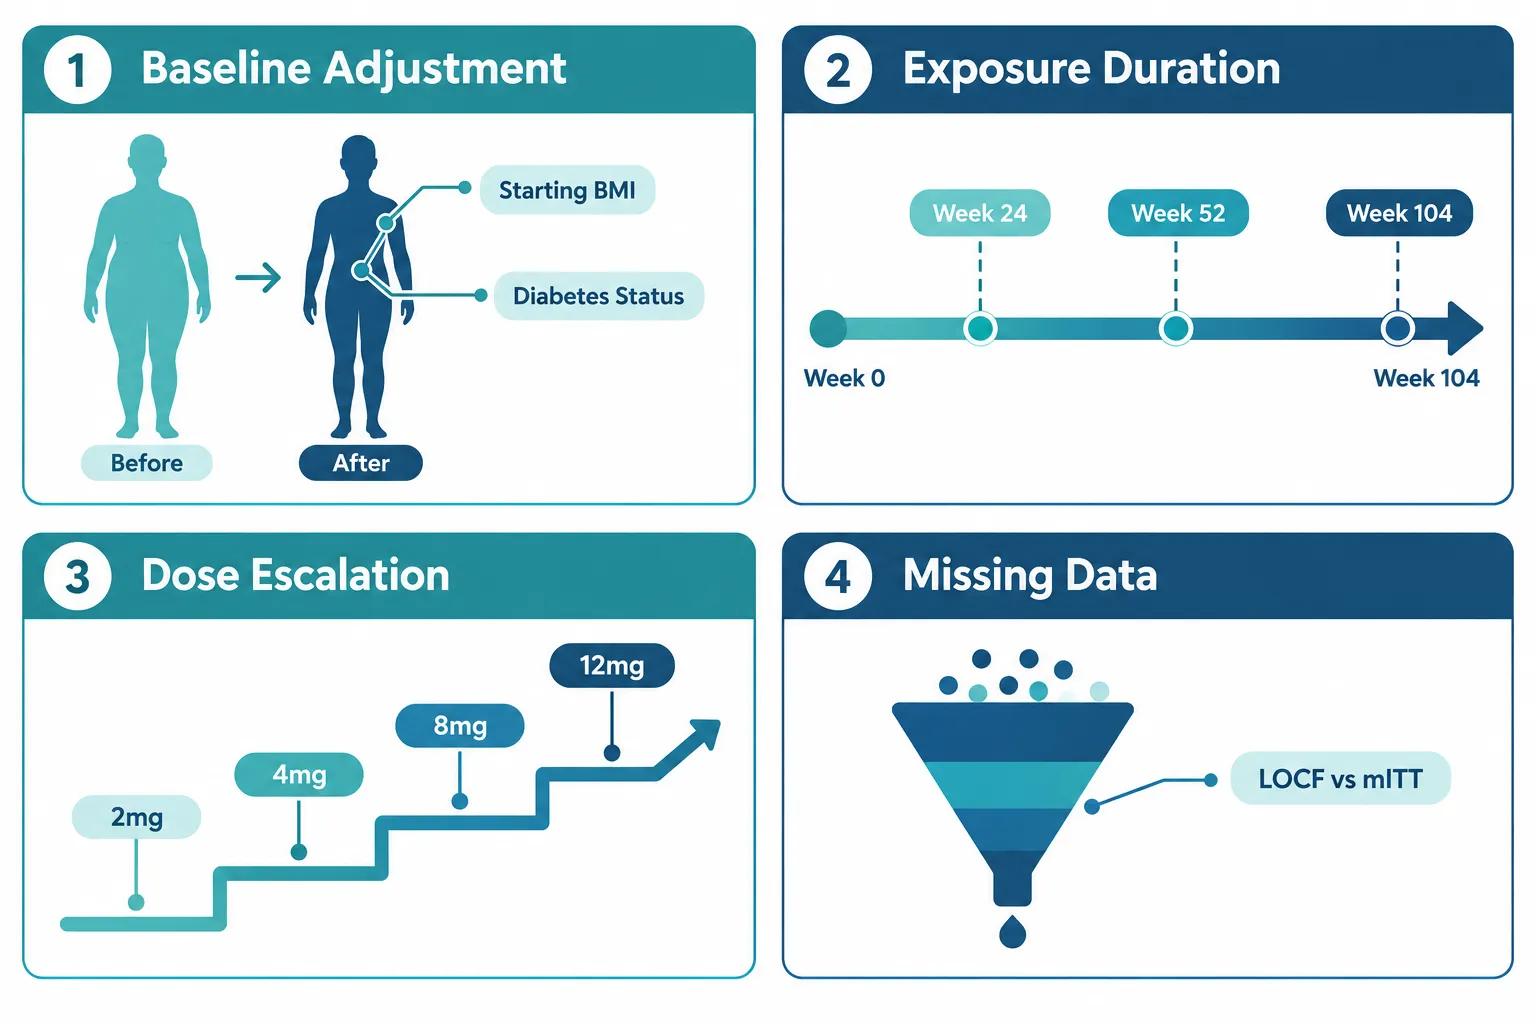
Before examining any specific endpoint, researchers reviewing retatrutide clinical trial data should build a structured checklist. Six variables consistently determine whether a reported number is comparable across studies.

1. Baseline adjustment. Weight-loss figures are meaningful only when the starting population is defined. TRIUMPH-3, the phase-3 obesity trial, enrolled adults with BMI of 30 or above without type 2 diabetes. TRIUMPH-2 enrolled adults with established type 2 diabetes, a population that typically shows attenuated weight loss due to disease-related metabolic differences. Comparing raw percentage figures between these two cohorts without baseline adjustment produces misleading conclusions.

2. Exposure duration. Long-term extension data from 2026 show approximately 30% mean weight loss at 104 weeks, roughly double the 24-week phase-2 figure. Researchers must anchor every efficacy claim to the exact week of assessment. A "24-week result" and a "2-year result" are not interchangeable data points.

3. Dose-escalation protocol. Retatrutide is titrated upward through multiple dose levels (commonly 2 mg, 4 mg, 8 mg, and 12 mg). Studies that terminate at lower doses or that allow slower escalation will report lower efficacy and potentially different tolerability profiles. Always confirm which dose was active at the time of the reported endpoint.

4. Missing-data handling. The modified intent-to-treat (mITT) population includes all randomized participants who received at least one dose. Last observation carried forward (LOCF) substitutes the final recorded value for participants who dropped out. These two approaches can shift reported weight loss by several percentage points. TRIUMPH-3 used mITT analysis; researchers comparing it to earlier phase-2 data should verify that the same convention was applied.

5. Responder rates versus mean change. A mean weight loss of 24% can mask a bimodal distribution where a subset of participants lost 40% and another subset lost less than 10%. Responder analyses, reporting the proportion achieving at least 5%, 10%, or 15% body-weight reduction, provide a more complete picture for visceral fat research contexts.

6. Tolerability and its interaction with efficacy. Gastrointestinal adverse events are the primary driver of early discontinuation. Participants who tolerate the drug long enough to reach maximum dose will inevitably show better outcomes than the full randomized group. This creates a systematic upward bias in completer analyses.


How to Interpret A1C Data in Retatrutide Research

How to Interpret A1C Data in Retatrutide Research

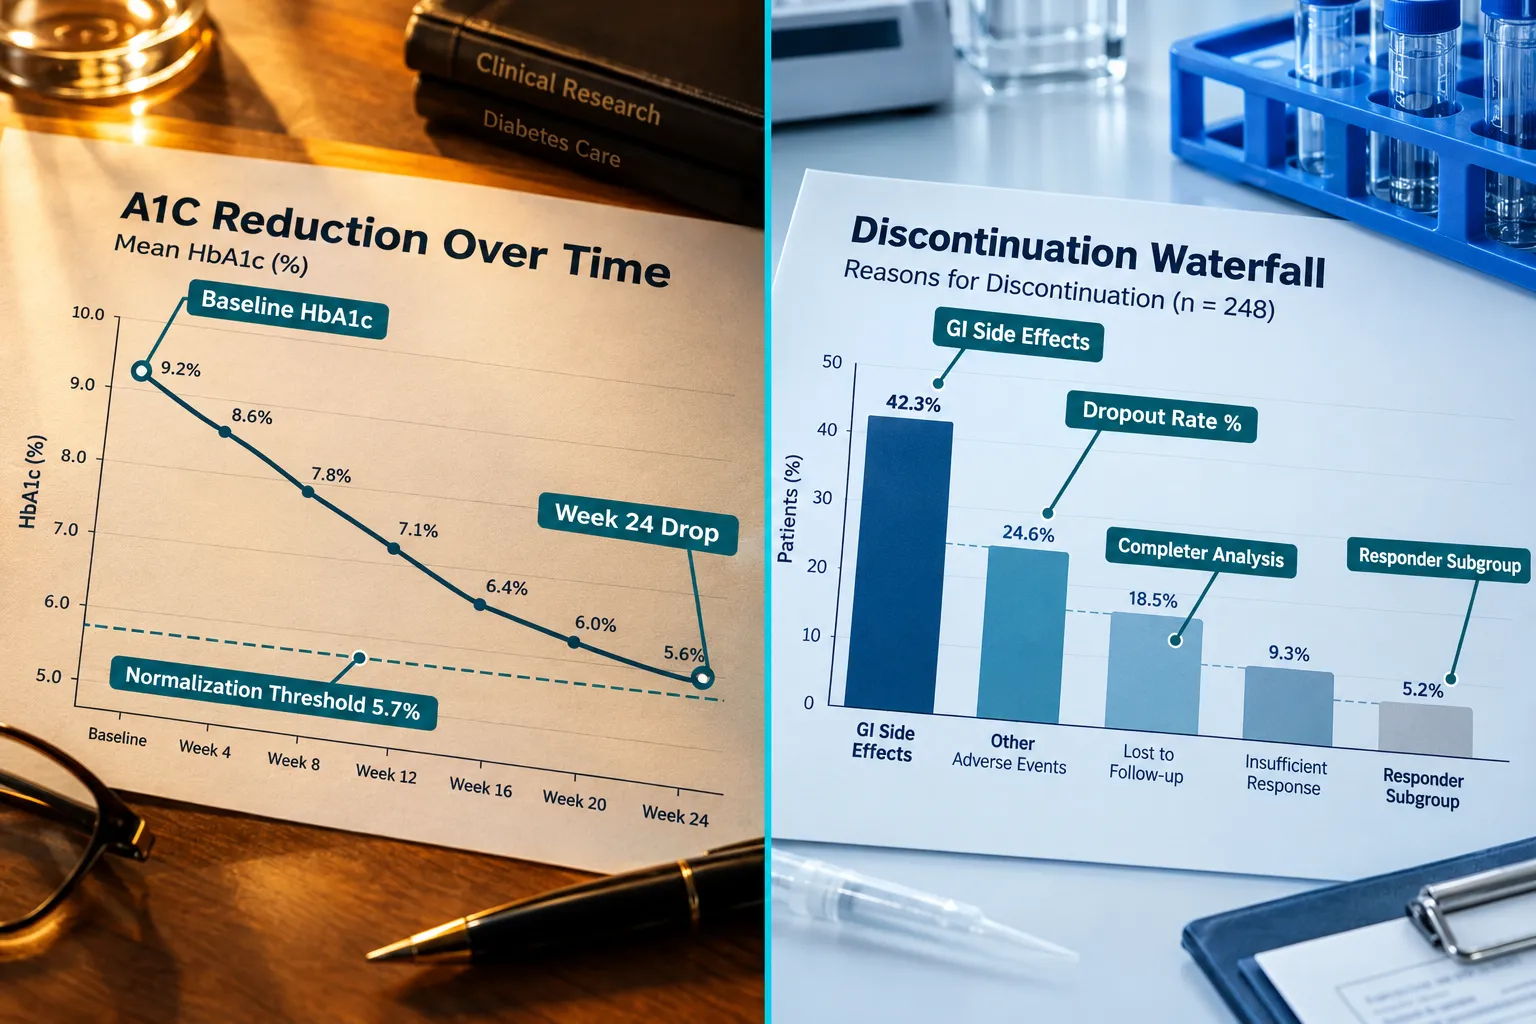
TRIUMPH-2 and the TRANSCEND-T2D-1 trial provide the most detailed glycemic data available as of 2026. TRANSCEND-T2D-1 reported A1C normalization, defined as reaching below 5.7%, in a substantial proportion of participants with type 2 diabetes, a result that positions retatrutide well above standard-of-care benchmarks. However, interpreting these numbers requires the same checklist discipline applied to weight-loss data.

"An A1C reduction from 8.5% to 6.2% and a reduction from 7.1% to 5.6% both represent meaningful clinical change, but they are not equivalent achievements and should never be averaged without stratification."

Baseline glycemic status matters most. A participant entering a trial with an A1C of 9% has more room to show a dramatic reduction than one starting at 7.2%. Meta-analytic reviews from 2025 and 2026 consistently flag this as the largest source of heterogeneity across retatrutide glycemic studies.

Concurrent weight loss confounds attribution. Because retatrutide acts on GLP-1, GIP, and glucagon receptors simultaneously, A1C improvements reflect both direct receptor-mediated effects and indirect benefits from weight reduction. Researchers should look for subgroup analyses that isolate glycemic response in participants with minimal weight loss to disentangle these mechanisms.

Dose level and A1C. Higher doses correlate with greater A1C reductions, but the dose-response curve flattens above 8 mg in most reported analyses. Citing an A1C result without specifying the active dose renders the figure nearly uninterpretable.

For researchers exploring related GLP-1 Reta receptor agonist mechanisms, understanding how triple-agonist activity differs from dual-agonist comparators is essential context for any glycemic endpoint.


Discontinuation Rates and What They Mean for Research Validity

Discontinuation Rates and What They Mean for Research Validity

TRIUMPH-3 reported discontinuation rates that, while lower than some earlier incretin trials, still warrant careful analysis. Approximately 10 to 16% of participants discontinued due to adverse events, primarily nausea, vomiting, and diarrhea, rates consistent with the class but not trivial.

Why discontinuation bias matters. When a trial reports efficacy only in completers, the remaining sample is systematically healthier and more tolerant. This is survivorship bias in its most direct form. A rigorous reading of how to interpret weight loss, A1C, and discontinuation rates in retatrutide research demands that readers identify whether the primary endpoint was calculated on the full mITT population or on completers only.

Sensitivity analyses are the gold standard. Well-designed trials include sensitivity analyses that model what outcomes would have looked like if all dropouts had remained on treatment. When sensitivity analyses produce results close to the primary analysis, confidence in the headline number increases substantially.

Safety signals from uncontrolled sources. Independent reporting in late 2026 highlighted safety concerns associated with counterfeit or improperly dosed buy Reta products circulating outside regulated research channels. These cases introduce noise into any real-world interpretation of tolerability data and underscore why sourcing integrity matters for laboratory use. Researchers seeking verified material should consult resources on where to buy Reta from tested, documented suppliers.

Regulatory implications. The FDA and other agencies evaluating retatrutide's approval pathway in 2026 have emphasized that labeling will reflect the full randomized population's outcomes, not completer subgroups. This distinction will directly affect how prescribing information frames expected weight loss and glycemic benefit in clinical practice.


Conclusion

Interpreting retatrutide research accurately requires more than reading the abstract. Researchers should apply a six-point checklist, baseline adjustment, exposure duration, dose escalation, missing-data method, responder rates, and discontinuation analysis, to every efficacy claim before drawing comparisons or designing follow-on studies.

Actionable next steps for researchers in 2026:

  • Obtain the full statistical analysis plan for any trial before interpreting its primary endpoint.
  • Cross-reference weight-loss figures against the specific week, dose level, and analysis population reported.
  • Treat completer-only A1C data as hypothesis-generating rather than confirmatory.
  • Verify that any retatrutide compound used in laboratory settings comes from a documented, purity-tested source to prevent contaminated data.
  • Review long-term extension data alongside short-term phase-2 benchmarks to contextualize trajectory, not just magnitude.

The science behind this triple-receptor agonist is advancing rapidly. Applying rigorous interpretive standards now ensures that research contributions to this field remain credible and reproducible.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/how-to-interpret-weight-loss-a1c-and-discontinuation-rates-in-retatrutide-resear.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-17 13:05:092026-10-17 13:05:09How to Interpret Weight Loss, A1C, and Discontinuation Rates in Retatrutide Research
Retatrutide Phase 3 Diabetes Results: How Researchers Should Interpret Dose, A1C, Weight, and Discontinuation Data

Retatrutide Phase 3 Diabetes Results: How Researchers Should Interpret Dose, A1C, Weight, and Discontinuation Data

October 12, 2026/0 Comments/in Uncategorized/by

Fewer than 1 in 10 glucose-lowering drugs tested in Phase 2 trials ever produce weight loss exceeding 15% of body weight in people with type 2 diabetes. Retatrutide, a triple GIP/GLP-1/glucagon receptor agonist, has now done exactly that across two large Phase 3 programs, making the Retatrutide Phase 3 Diabetes Results: How Researchers Should Interpret Dose, A1C, Weight, and Discontinuation Data question one of the most important analytical tasks in metabolic research in 2026.

This guide is written for researchers, clinicians, and evidence reviewers who need a structured framework for reading the trial data accurately, not as a clinical recommendation or treatment guide.


Key Takeaways

  • Two Phase 3 trials, TRANSCEND-T2D-1 and TRIUMPH-2, provide the core evidence base for retatrutide in type 2 diabetes.
  • A1C reductions showed a clear dose-response pattern, roughly doubling the effect of placebo at the highest dose.
  • Weight loss was substantial and, in the 40-week trial, had not yet plateaued at study end.
  • Discontinuation due to adverse events was dose-dependent and driven primarily by gastrointestinal symptoms.
  • Tolerability, not efficacy, is likely to determine real-world dose selection and patient retention.

Understanding the Two Core Phase 3 Trials

Before analyzing any endpoint, researchers must distinguish between the two trials, because they enrolled different populations and ran for different durations.

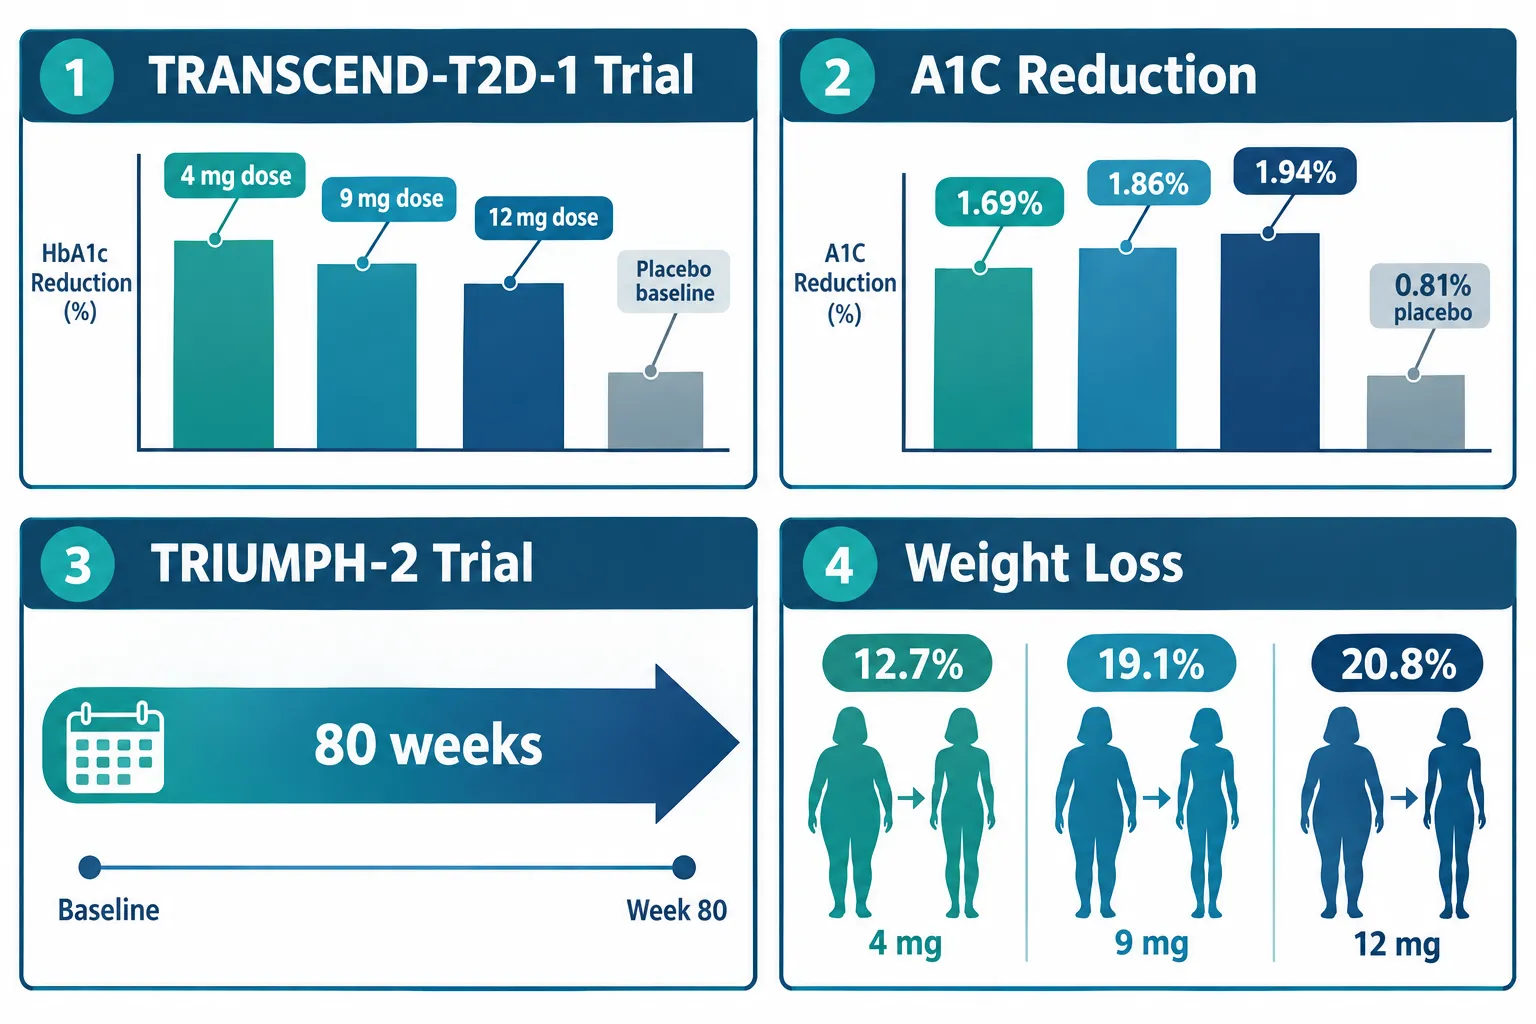
TRANSCEND-T2D-1 enrolled 537 adults with recent-onset type 2 diabetes, A1C between 7.0% and 9.5%, and BMI of 23 or higher. Participants received retatrutide monotherapy at 4, 9, or 12 mg once weekly for 40 weeks, with no background glucose-lowering medications. This design isolates the drug's intrinsic glycemic effect.

TRIUMPH-2 enrolled adults with established type 2 diabetes plus obesity or overweight and ran for 80 weeks. This longer trial captures durability and applies to a more complex metabolic phenotype seen frequently in clinical practice.

Conflating results from these two trials is one of the most common analytical errors. Baseline disease severity, background therapy status, and trial duration all affect the magnitude of observed A1C and weight outcomes.

Understanding the Two Core Phase 3 Trials

Researchers reviewing GLP-3 receptor agonist peptide research should note that retatrutide's triple-agonist mechanism distinguishes it from dual or single-target agents, which affects how dose-response curves should be modeled.


Interpreting A1C and Weight Data From Retatrutide Phase 3 Diabetes Results

A1C Reduction: Reading the Dose-Response Signal

In TRANSCEND-T2D-1, mean A1C reductions from a baseline of approximately 7.9% were:

Dose Mean A1C Reduction vs. Placebo
4 mg ~1.69% ~2x placebo
9 mg ~1.86% ~2.3x placebo
12 mg ~1.94% ~2.4x placebo
Placebo ~0.81% Reference

The incremental gain between 9 mg and 12 mg is small (roughly 0.08 percentage points), which researchers should weigh carefully against the larger jump in discontinuation risk at the highest dose.

In TRIUMPH-2, A1C reductions were somewhat smaller (approximately 1.4% to 1.6%), consistent with the more established disease state and likely background medication use in that population. Notably, up to 79.2% of participants achieved A1C at or below 6.5% on retatrutide versus roughly 26.3% on placebo, a clinically meaningful responder-rate difference.

Key analytical point: Absolute A1C reduction and responder rates (percentage reaching target) are different estimands. Both should be reported to avoid misleading summaries.

Weight Loss: A Metabolic Signal That Deserves Separate Analysis

Weight loss in these trials is not merely a secondary benefit. It is a primary metabolic outcome that may independently drive glycemic improvement.

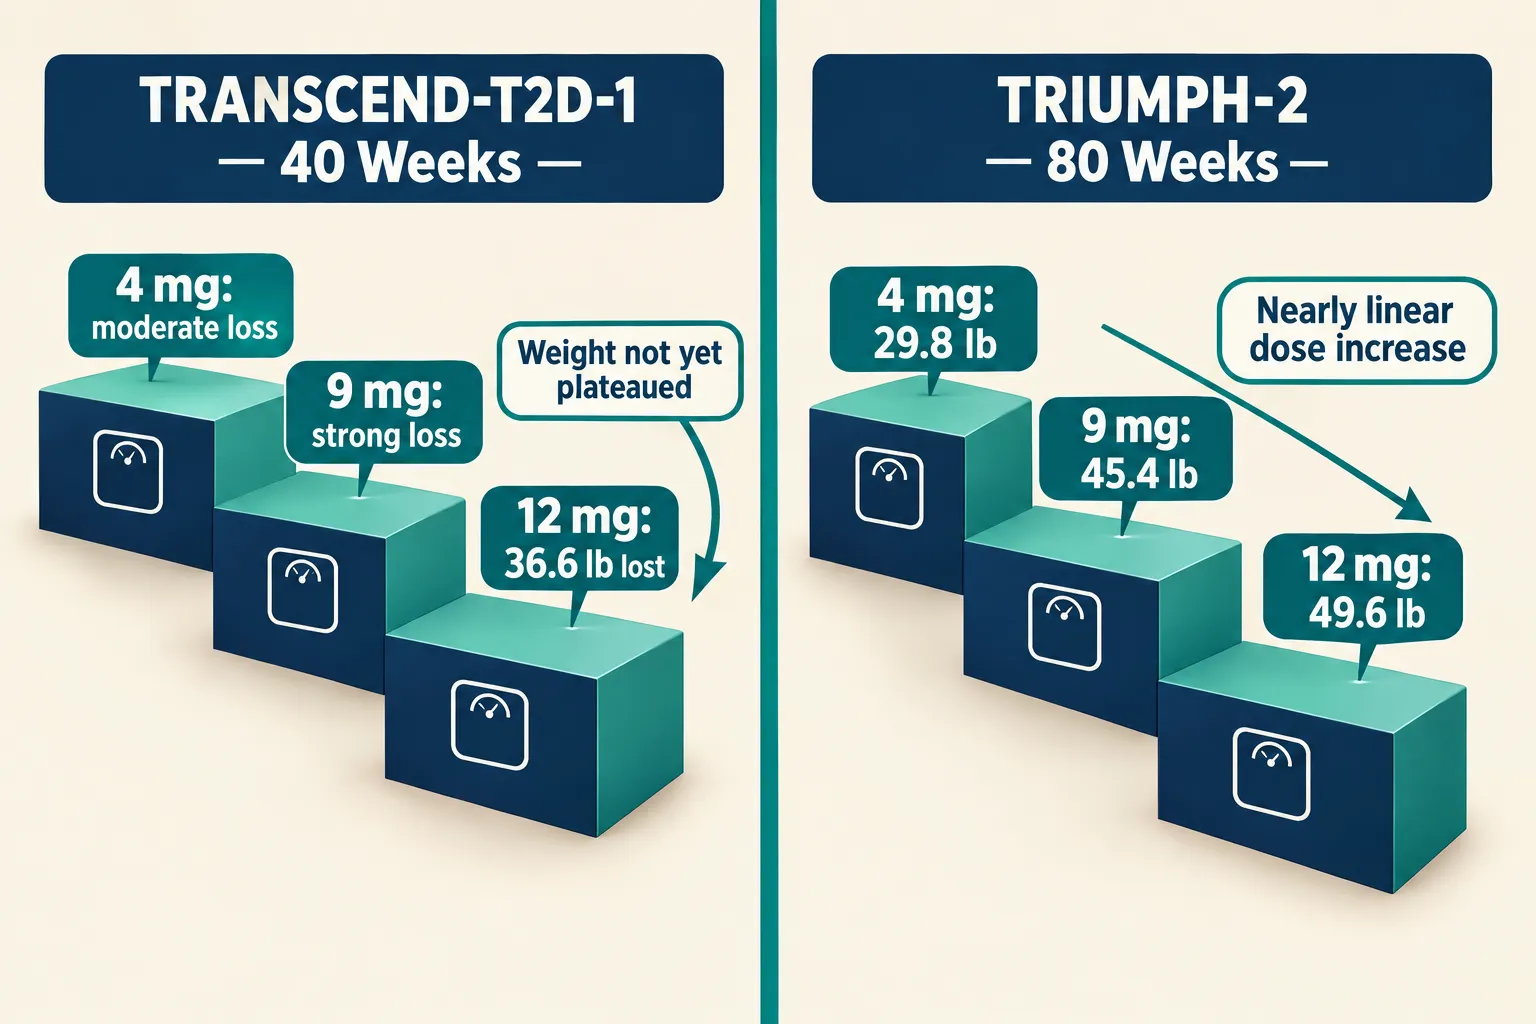
In TRANSCEND-T2D-1 at 40 weeks:

  • 12 mg: approximately 36.6 lb (16.8% of body weight)
  • Weight loss curves had not plateaued, meaning the 40-week figure likely underestimates the drug's full effect.

In TRIUMPH-2 at 80 weeks:

  • 4 mg: approximately 29.8 lb (12.7%)
  • 9 mg: approximately 45.4 lb (19.1%)
  • 12 mg: approximately 49.6 lb (20.8%)

This near-linear dose-weight relationship positions retatrutide among the most potent pharmacologic weight-loss agents tested in diabetic populations. Researchers studying visceral fat reduction mechanisms will find the 80-week TRIUMPH-2 data particularly relevant for modeling adipose tissue dynamics.

For those sourcing research-grade material, GLP-3 Reta 30mg and GLP-3 Reta 20mg represent formulation options used in preclinical and translational research contexts.

Weight Loss: A Metabolic Signal That Deserves Separate Analysis


Discontinuation Data: The Critical Safety Estimand in Retatrutide Phase 3 Diabetes Results

Discontinuation due to adverse events is often under-analyzed in metabolic drug trials. For retatrutide, it is arguably the most important variable for predicting real-world uptake.

TRANSCEND-T2D-1 Discontinuation Rates

  • 4 mg: ~4.1%
  • 9 mg: ~6.9%
  • 12 mg: ~11.3%
  • Placebo: ~4.9%

The 12 mg arm saw discontinuation more than double the placebo rate. Gastrointestinal symptoms, primarily nausea, vomiting, and diarrhea, were the dominant drivers, consistent with other incretin-based agents.

TRIUMPH-2 Discontinuation Pattern

  • 4 mg: ~3.8%
  • 9 mg: ~11.6%
  • 12 mg: ~7.7%
  • Placebo: ~4.9%

A critical observation: In TRIUMPH-2, the 9 mg dose showed higher discontinuation than the 12 mg dose. This non-monotonic pattern suggests that intermediate doses may carry the greatest early tolerability burden, possibly because titration schedules at 9 mg produced faster GI exposure than at 12 mg. Researchers should not assume a simple linear relationship between dose and dropout risk.

Researchers examining peptide tolerability profiles, including those reviewing Reta peptide research formulations, should factor titration speed into any safety analysis. The Glp3 Reta 10mg formulation is relevant for lower-dose preclinical work where tolerability thresholds are being established.

A Framework for Benefit-Risk Modeling

When synthesizing Retatrutide Phase 3 Diabetes Results: How Researchers Should Interpret Dose, A1C, Weight, and Discontinuation Data into a coherent benefit-risk model, the following structure is recommended:

  1. Separate efficacy estimands – Distinguish A1C reduction, responder rates, and weight loss as distinct outcomes.
  2. Account for trial duration – 40-week data underestimates long-term weight outcomes.
  3. Model incremental gains vs. incremental risk – The 9-to-12 mg A1C gain is small; the discontinuation increase is not.
  4. Examine non-monotonic safety signals – TRIUMPH-2 discontinuation data requires dose-specific, not dose-linear, interpretation.
  5. Apply population context – Early monotherapy results do not transfer directly to established diabetes with obesity.

Expert commentary has characterized retatrutide as a breakthrough triple-hormone therapy whose tolerability profile, rather than its efficacy ceiling, will determine preferred clinical doses. Future research priorities include optimized titration schedules, head-to-head comparisons with tirzepatide and semaglutide, and structured evaluation in populations with chronic kidney disease and obstructive sleep apnea.


Conclusion

The Retatrutide Phase 3 Diabetes Results: How Researchers Should Interpret Dose, A1C, Weight, and Discontinuation Data evidence base is both robust and nuanced. The TRANSCEND-T2D-1 and TRIUMPH-2 trials confirm a strong, consistent efficacy signal, but accurate interpretation demands attention to trial design differences, the gap between absolute and responder-rate endpoints, the non-linear discontinuation pattern across doses, and the fact that weight loss curves had not plateaued at 40 weeks.

Actionable next steps for researchers:

  • Apply separate analytical frameworks to each trial rather than pooling results.
  • Report both mean A1C reduction and the percentage of participants reaching glycemic targets.
  • Treat the TRIUMPH-2 discontinuation pattern as a titration-schedule hypothesis, not a dose-safety anomaly.
  • Prioritize long-term follow-up data as it becomes available, particularly for weight plateau and cardiovascular outcomes.
  • When sourcing research-grade retatrutide formulations, consult verified suppliers such as those offering GLP-3 Reta 20mg Ga1 for structured preclinical protocols.

The data is strong. The interpretation requires precision.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-phase-3-diabetes-results-how-researchers-should-interpret-dose-a1c-w.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-12 13:13:532026-10-12 13:13:53Retatrutide Phase 3 Diabetes Results: How Researchers Should Interpret Dose, A1C, Weight, and Discontinuation Data
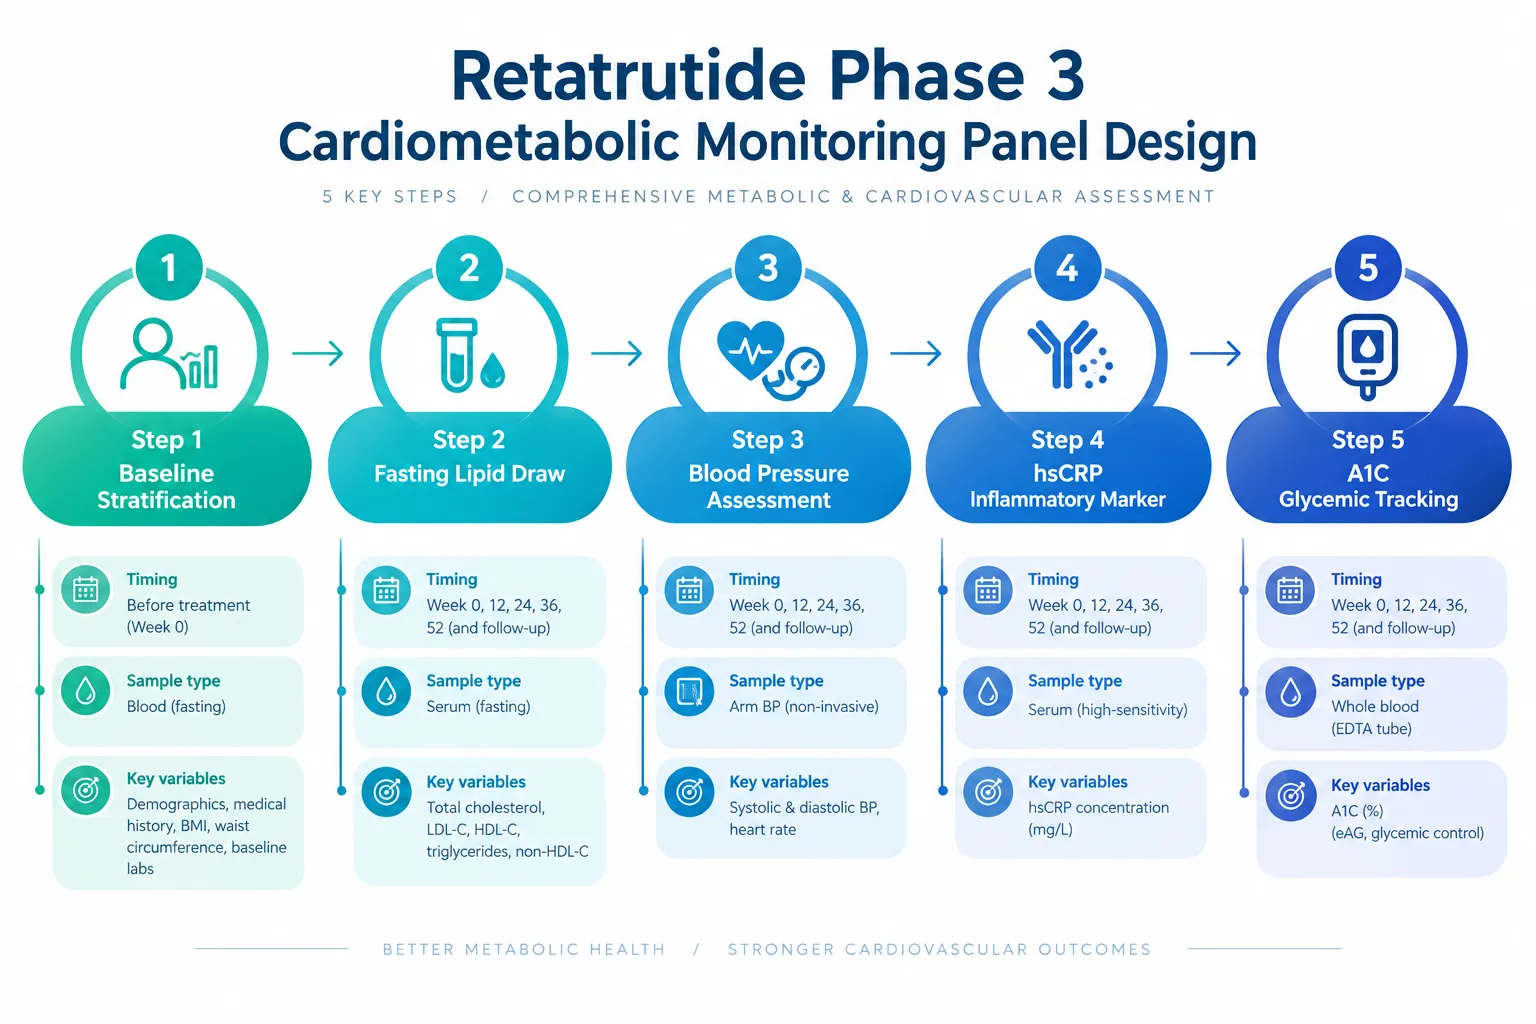
Retatrutide Phase 3 Cardiometabolic Monitoring: Designing Research Panels for Triglycerides, Blood Pressure, hsCRP, and A1C

Retatrutide Phase 3 Cardiometabolic Monitoring: Designing Research Panels for Triglycerides, Blood Pressure, hsCRP, and A1C

October 12, 2026/0 Comments/in Uncategorized/by

By mid-2026, five pivotal Phase 3 readouts from Eli Lilly's TRIUMPH program had confirmed that retatrutide produces weight loss exceeding 28% of body weight, a figure that surpasses every previously reported pharmacological result in humans. Yet the most consequential design challenge for researchers is not tracking weight. It is building a cardiometabolic panel rigorous enough to separate the independent effects of retatrutide on lipids, blood pressure, inflammation, and glycemic control from the cascade of changes that weight loss alone would produce. Retatrutide Phase 3 cardiometabolic monitoring: designing research panels for triglycerides, blood pressure, hsCRP, and A1C demands a structured, multi-domain approach grounded in the latest TRIUMPH data.

Key Takeaways

  • TRIUMPH Phase 3 trials prespecify fasting triglycerides, non-HDL cholesterol, systolic blood pressure, hsCRP, A1C, and waist circumference as core cardiometabolic endpoints alongside weight loss.
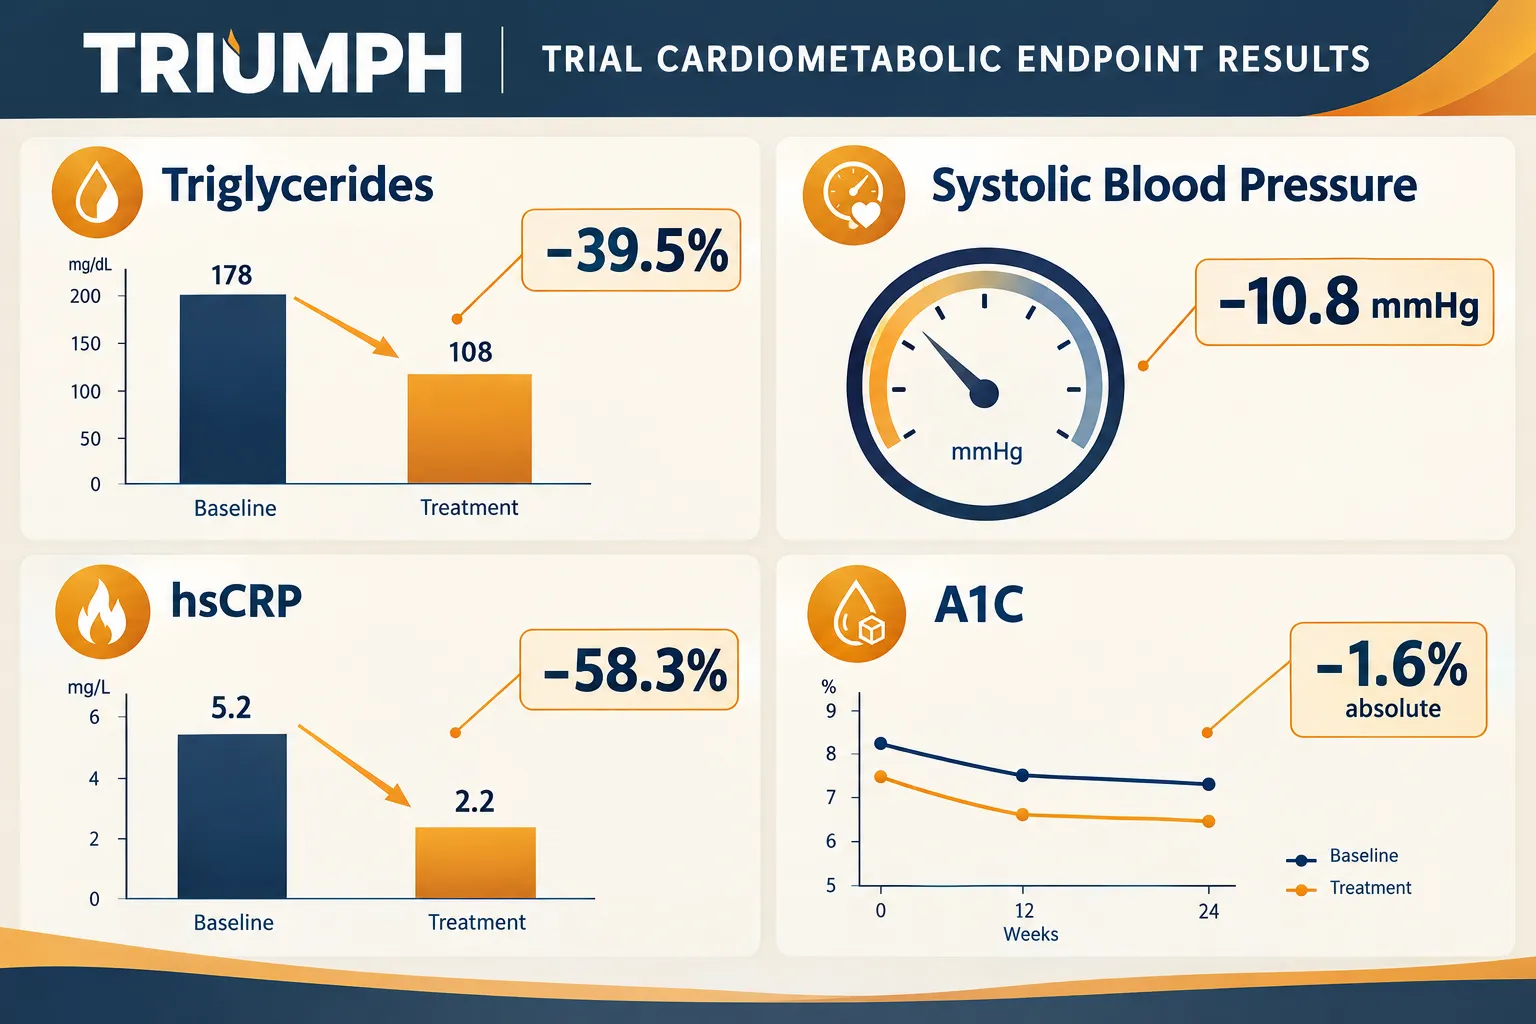
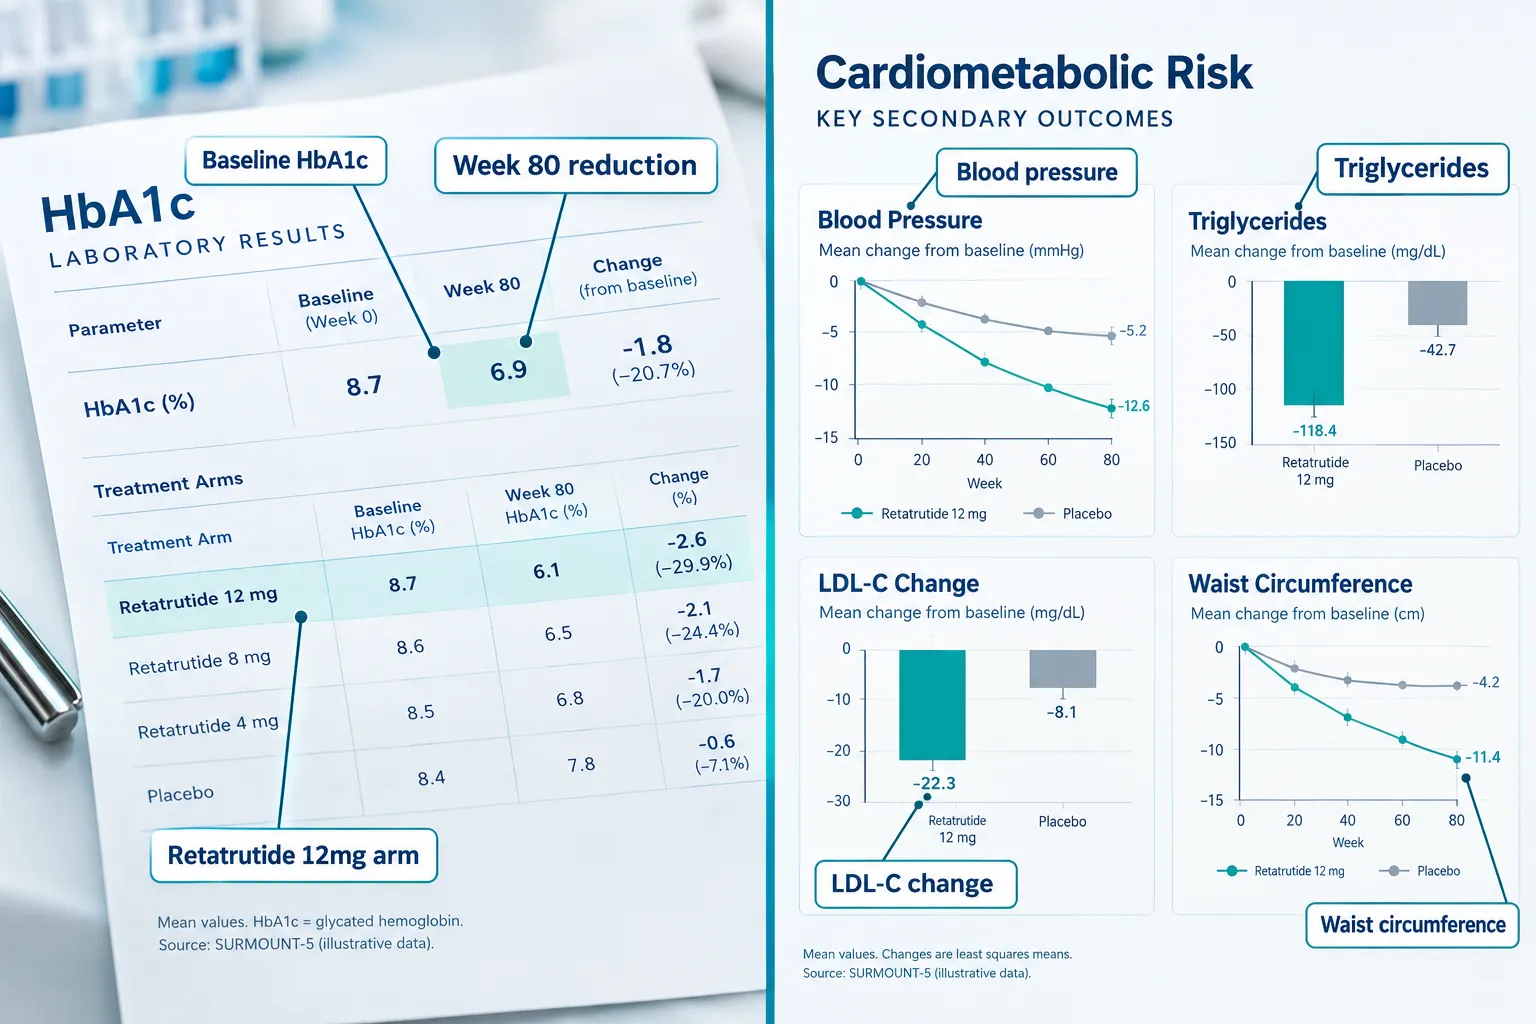
  • Triglyceride reductions of up to 39.5%, hsCRP reductions of up to 58.3%, and systolic blood pressure drops of up to 10.8 mmHg were recorded at 80 weeks in TRIUMPH-2.
  • Baseline stratification by diabetes status, cardiovascular disease history, and baseline triglyceride level is essential for interpreting correlated outcomes.
  • A1C is a primary endpoint in diabetes-focused arms (TRIUMPH-2, TRANSCEND-T2D-1) and must be paired with lipid and inflammatory markers to capture the full cardiometabolic picture.
  • The ongoing TRIUMPH-Outcomes CV/renal trial signals that future panels will expand to include kidney function markers such as eGFR and albuminuria.

Why the TRIUMPH Data Demand a Multi-Domain Panel

Why the TRIUMPH Data Demand a Multi-Domain Panel

The TRIUMPH program is not a single study. It is a coordinated set of 80-week, randomized, double-blind, placebo-controlled trials targeting distinct populations: TRIUMPH-1 in adults with obesity or overweight, TRIUMPH-2 in adults with obesity or overweight plus type 2 diabetes, and TRIUMPH-3 in 1,949 adults with BMI of 35 or higher and established cardiovascular disease. Each trial prespecifies cardiometabolic endpoints beyond weight, and the consistency of those endpoints across trials is itself a design signal.

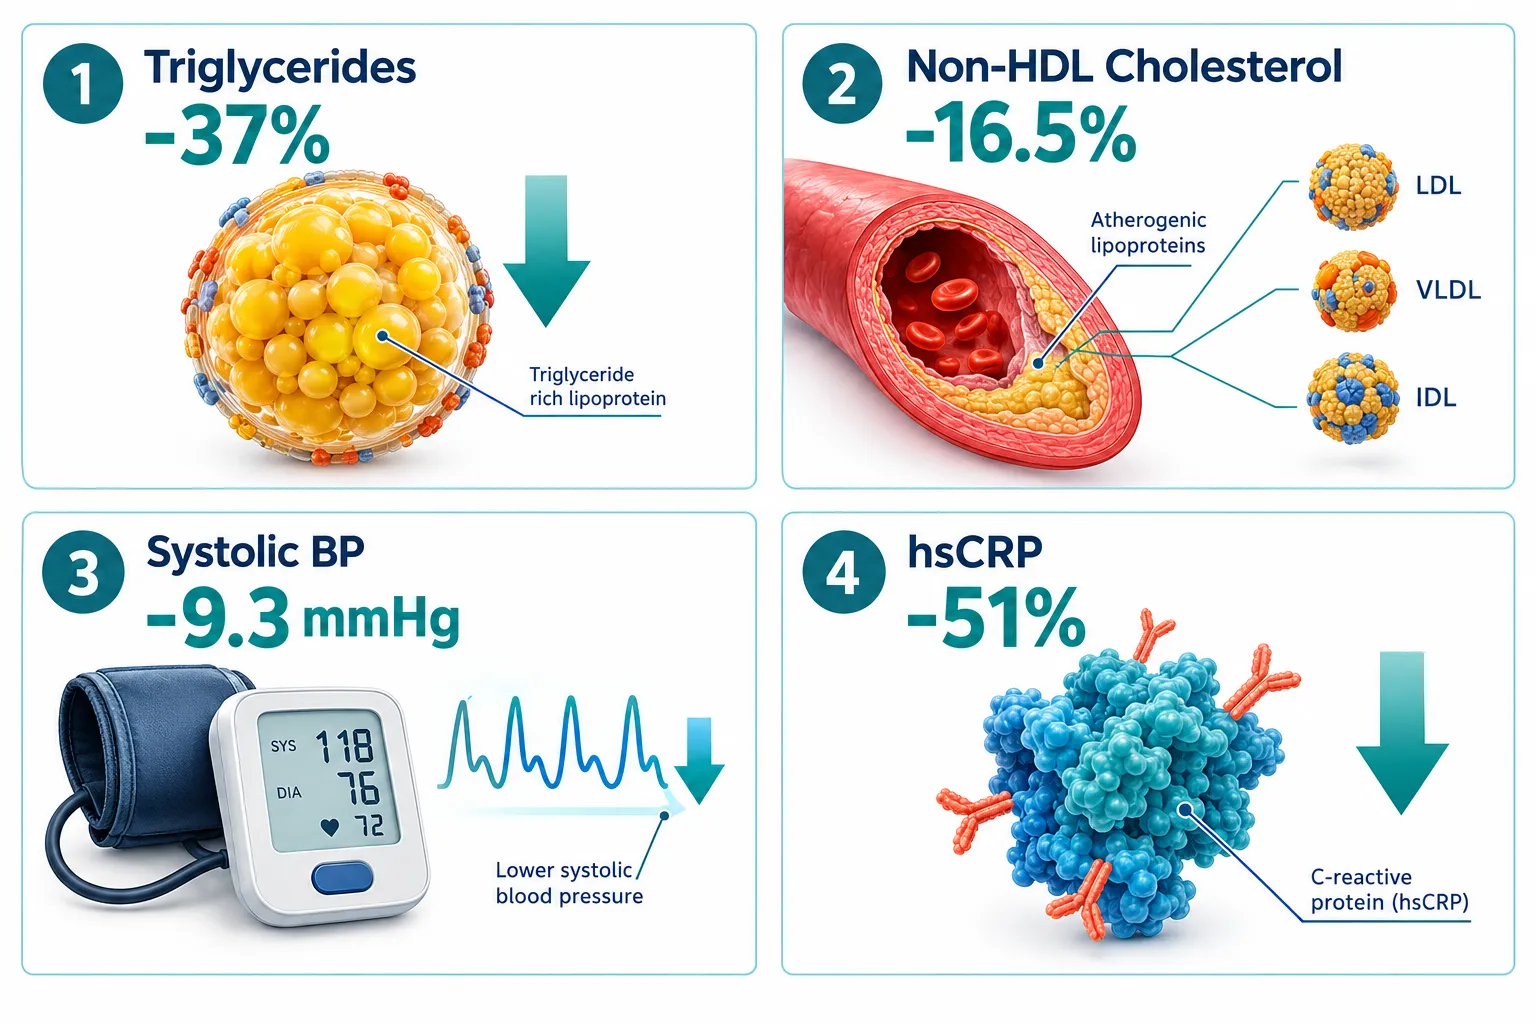
In TRIUMPH-3, participants on retatrutide 12 mg achieved a 22.6% reduction in body weight versus 3.2% on placebo. Alongside that, triglycerides fell 37.0%, non-HDL cholesterol dropped 16.5%, systolic blood pressure decreased 9.3 mmHg, waist circumference shrank 19.0 cm, and hsCRP fell 51.2%. The MACE-5 hazard ratio of 0.82 did not reach statistical significance, which is a critical interpretive point: robust improvements in surrogate biomarkers did not automatically translate into a proven reduction in hard cardiovascular events. This finding directly shapes panel philosophy, these markers must be tracked as risk-factor indicators, not as proxies for confirmed outcome benefit.

Researchers sourcing the compound for preclinical or translational work can explore GLP-1 Reta and Reta peptide for sale options to understand the molecular context before designing monitoring frameworks.

Core panel elements supported by TRIUMPH data:

Biomarker TRIUMPH-2 Change (12 mg) TRIUMPH-3 Change (12 mg)
Triglycerides -39.5% -37.0%
Non-HDL Cholesterol -19.6% -16.5%
Systolic Blood Pressure -10.8 mmHg -9.3 mmHg
hsCRP -58.3% -51.2%
Waist Circumference Significant -19.0 cm
A1C -1.6% absolute Not primary

Baseline Stratification and Sampling Schedules

Baseline Stratification and Sampling Schedules

Effective retatrutide Phase 3 cardiometabolic monitoring, designing research panels for triglycerides, blood pressure, hsCRP, and A1C, begins before the first dose. Baseline stratification is the mechanism that allows researchers to disentangle weight-mediated effects from direct receptor-driven changes.

Stratification variables to define at enrollment:

  • Diabetes status: TRIUMPH-2 and TRANSCEND-T2D-1 demonstrate that A1C trajectories in diabetes populations diverge meaningfully from non-diabetes arms. Separate strata prevent dilution of glycemic signals.
  • Baseline triglyceride level: Participants with hypertriglyceridemia at baseline show proportionally larger reductions. Stratifying by fasting triglycerides above or below 200 mg/dL allows dose-response analysis that is not confounded by regression to the mean.
  • Cardiovascular disease history: TRIUMPH-3's CVD-enriched cohort produced the largest absolute hsCRP reductions. Mixing CVD and non-CVD participants without stratification obscures inflammation response patterns.
  • Baseline BMI tier: Weight loss magnitude correlates with baseline BMI, and since triglycerides and blood pressure both respond to weight loss, BMI strata help isolate pharmacological signal.

"The consistent use of fasting triglycerides, non-HDL cholesterol, systolic blood pressure, hsCRP, A1C, and waist circumference over 40-to-80-week windows across five Phase 3 trials represents an emerging standard for retatrutide cardiometabolic panel design."

Recommended sampling schedule for an 80-week protocol:

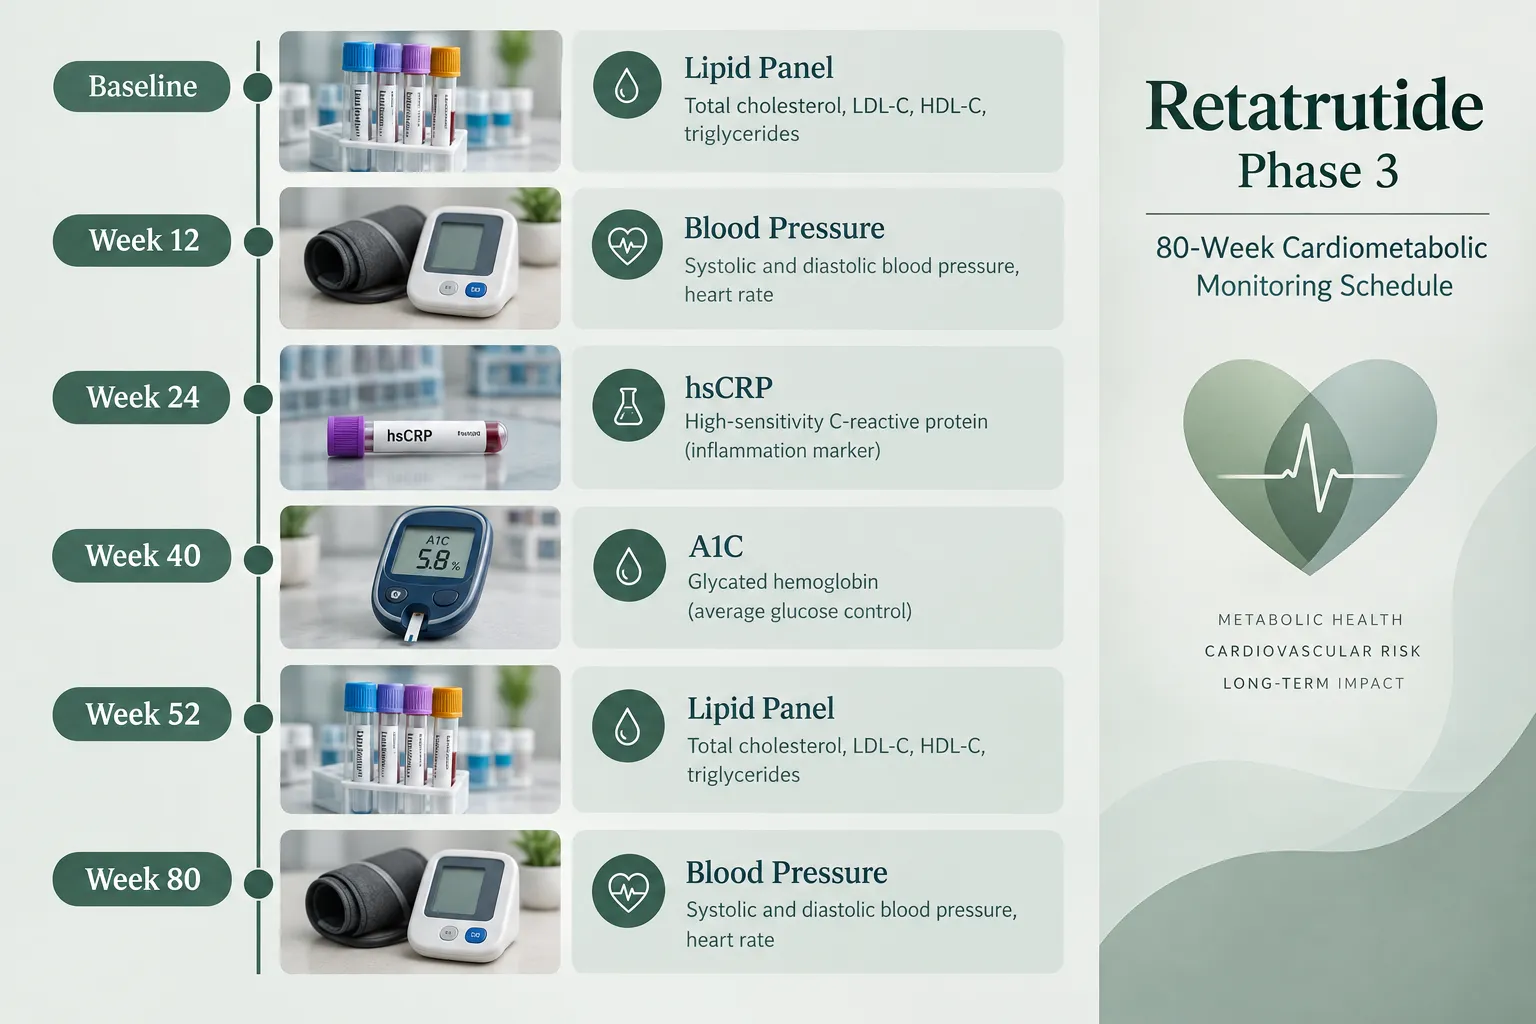
  • Baseline (Week 0): Full fasting lipid panel, hsCRP, A1C, blood pressure (triplicate), waist circumference, eGFR, albuminuria
  • Week 12: Fasting triglycerides, blood pressure, body weight
  • Week 24: Full panel repeat
  • Week 40: Full panel repeat (aligns with TRANSCEND-T2D-1 primary endpoint)
  • Week 52: Fasting triglycerides, hsCRP, blood pressure, A1C
  • Week 80: Full panel repeat, primary endpoint analysis

Fasting status for lipid draws must be standardized at 10-12 hours. Blood pressure should follow a three-reading protocol with the participant seated for five minutes, using the average of readings two and three. hsCRP should use the high-sensitivity assay (hs-CRP) to detect low-grade inflammation changes relevant to cardiovascular risk.

For researchers exploring related metabolic pathways, visceral fat research resources provide useful context on adipose-driven inflammation that intersects with hsCRP monitoring. Those studying growth hormone secretagogue stacks may also find the IPA Sermorelin stack research reference helpful for understanding parallel metabolic endpoints.


Interpreting Correlated Outcomes Without Overclaiming

Interpreting Correlated Outcomes Without Overclaiming

The central interpretive challenge in retatrutide Phase 3 cardiometabolic monitoring, designing research panels for triglycerides, blood pressure, hsCRP, and A1C, is that all four major endpoints are correlated with each other and with weight loss. A 28% reduction in body weight alone would be expected to lower triglycerides, reduce systolic blood pressure, decrease hsCRP, and improve insulin sensitivity. Attributing the observed changes solely to receptor agonism requires deliberate analytical design.

Three analytical strategies to separate effects:

  1. Mediation analysis: Model weight loss as a mediator between retatrutide dose and each cardiometabolic endpoint. The residual direct effect after accounting for weight change estimates the weight-independent pharmacological contribution.
  2. Matched-weight comparator: Identify placebo participants who achieved similar weight loss through caloric restriction and compare their lipid and inflammatory trajectories to retatrutide-treated participants at the same weight-loss magnitude.
  3. Time-course divergence: Triglyceride and hsCRP reductions in TRIUMPH trials appear early and disproportionately large relative to the weight-loss timeline, suggesting direct receptor-mediated effects. Plotting biomarker change against cumulative weight loss at each time point can reveal non-linear relationships that indicate independent mechanisms.

A1C interpretation in mixed populations requires particular care. In TRIUMPH-2, the 1.6% absolute A1C reduction at the highest dose reflects both weight-mediated insulin sensitization and potential direct GLP-1 receptor-driven beta-cell effects. Panels that include fasting insulin and HOMA-IR alongside A1C allow researchers to partition these contributions.

Researchers interested in mitochondrial and cellular stress pathways that intersect with cardiometabolic function may find the SS-31 mitochondrial research tag and the detailed SS-31 mechanism and research guide useful for understanding complementary biomarker frameworks.

The TRIUMPH-Outcomes CV/renal trial (active as of October 2026) extends this logic further by enrolling adults with atherosclerotic cardiovascular disease and/or chronic kidney disease. Its design implies that future standard panels will add eGFR and albuminuria as kidney-function domains, creating a true multi-system cardiometabolic bundle rather than a lipid-and-pressure-only framework.

Avoid these common panel design errors:

  • Using non-fasting lipid draws at inconsistent time points
  • Measuring blood pressure immediately after physical activity or within 30 minutes of caffeine intake
  • Reporting A1C without concurrent fasting glucose, which limits mechanistic interpretation
  • Treating hsCRP as a hard outcome rather than a risk-factor surrogate

For those examining how to source research-grade retatrutide for preclinical panel validation studies, the how to buy Reta and Reta 10mg product tag pages provide relevant procurement context.


Conclusion

The TRIUMPH program has produced a clear, reproducible cardiometabolic signal: fasting triglycerides, non-HDL cholesterol, systolic blood pressure, hsCRP, A1C, and waist circumference all improve substantially with retatrutide across obesity, diabetes, and high-CVD-risk populations. The actionable next steps for researchers designing monitoring panels are straightforward.

Act on these priorities:

  • Standardize baseline stratification by diabetes status, CVD history, and baseline triglyceride level before randomization.
  • Implement a minimum six-timepoint sampling schedule across 80 weeks, with full fasting panels at baseline, week 24, week 40, and week 80.
  • Build mediation analysis into the statistical analysis plan from the outset to separate weight-mediated from direct pharmacological effects.
  • Add eGFR and albuminuria to panels that enroll participants with chronic kidney disease, anticipating the TRIUMPH-Outcomes readout framework.
  • Treat all biomarker improvements as risk-factor endpoints, not as evidence of hard cardiovascular event reduction, until outcomes trial data are available.

Rigorous panel design is what will allow the field to move from observing that retatrutide changes biomarkers to understanding precisely how, in whom, and through which mechanisms those changes occur.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-phase-3-cardiometabolic-monitoring-designing-research-panels-for-tri.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-12 13:05:412026-10-12 13:05:41Retatrutide Phase 3 Cardiometabolic Monitoring: Designing Research Panels for Triglycerides, Blood Pressure, hsCRP, and A1C
Retatrutide Phase 3 Cardiometabolic Endpoints: How to Interpret Triglycerides, Non-HDL Cholesterol, Blood Pressure, and hsCRP Together

Retatrutide Phase 3 Cardiometabolic Endpoints: How to Interpret Triglycerides, Non-HDL Cholesterol, Blood Pressure, and hsCRP Together

October 8, 2026/0 Comments/in Uncategorized/by

A 51% drop in high-sensitivity C-reactive protein alongside a 37% reduction in triglycerides, recorded in the same patients, at the same 80-week timepoint, is not a coincidence. It is a signal that demands careful interpretation. The TRIUMPH phase 3 program has now generated a dense cardiometabolic dataset around retatrutide, and understanding how to read Retatrutide Phase 3 Cardiometabolic Endpoints: How to Interpret Triglycerides, Non-HDL Cholesterol, Blood Pressure, and hsCRP Together requires separating what the numbers show from what they can, and cannot, prove about cardiovascular outcomes.

Key Takeaways

  • Retatrutide 12 mg produced mean weight loss of 22.6% in TRIUMPH-3, alongside reductions of 37% in triglycerides, 16.5% in non-HDL cholesterol, 9.3 mmHg in systolic blood pressure, and 51.2% in hsCRP at 80 weeks.
  • Across broader obesity populations in TRIUMPH-1 and TRIUMPH-4, these cardiometabolic effects were even larger, reaching 39.5% triglyceride reduction and 58.3% hsCRP reduction.
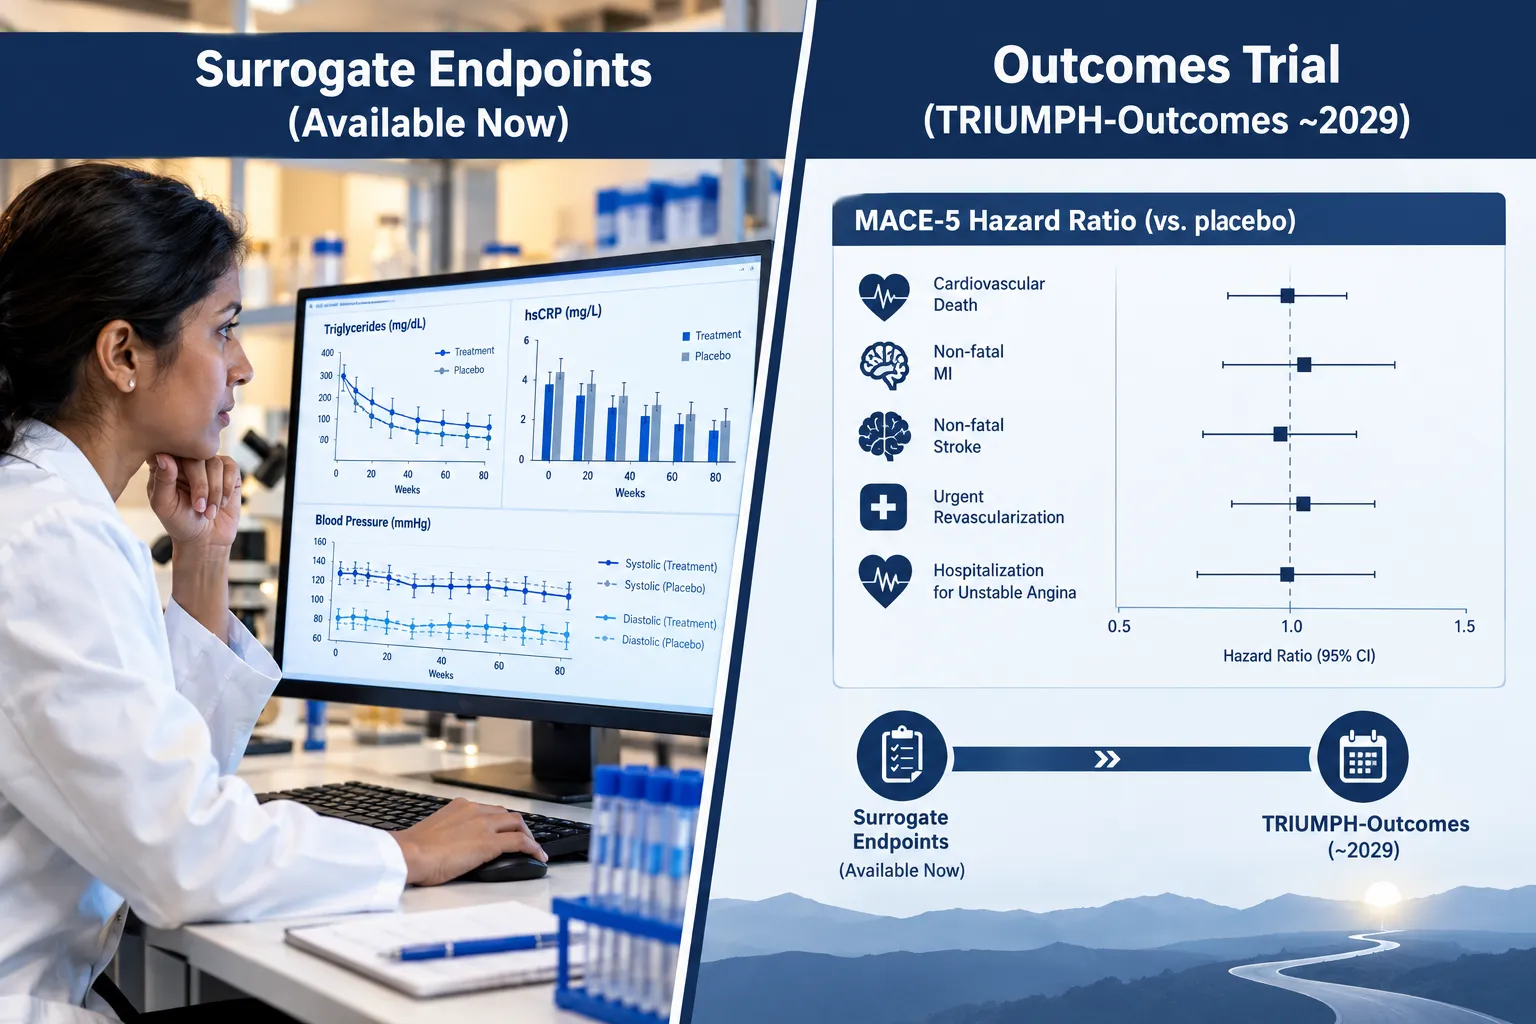
  • All four endpoints are surrogate markers, not clinical event data. The composite MACE-5 hazard ratio in TRIUMPH-3 was 0.82 but did not reach statistical significance.
  • Interpreting correlated endpoints requires understanding covariate adjustment, endpoint timing, and the distinction between weight-mediated and weight-independent effects.
  • The dedicated TRIUMPH-Outcomes cardiovascular trial is underway, with results not expected until approximately 2029 or later.

What the TRIUMPH Phase 3 Data Actually Show

The TRIUMPH program spans multiple pivotal trials. TRIUMPH-3 enrolled 1,949 adults with a BMI of 35 or higher and established cardiovascular disease. Over 80 weeks, retatrutide 12 mg delivered mean weight loss of 22.6% versus 3.2% in the control group. The cardiometabolic secondary endpoints moved in parallel:

What the TRIUMPH Phase 3 Data Actually Show

Endpoint TRIUMPH-3 (12 mg) TRIUMPH-1/TRIUMPH-4 (High Dose)
Triglycerides -37.0% -39.5%
Non-HDL Cholesterol -16.5% -19.6%
Systolic Blood Pressure -9.3 mmHg -10.8 mmHg
hsCRP -51.2% -58.3%
Waist Circumference -19.0 cm Significant reduction

In TRIUMPH-2, which studied adults with obesity or overweight and type 2 diabetes, retatrutide at 4, 9, and 12 mg produced weight losses of 12.7%, 19.1%, and 20.8%, respectively, with A1C reductions up to 1.6 percentage points. At the highest dose, systolic blood pressure fell by up to 14.0 mmHg, reinforcing that the blood pressure effect is dose-dependent and present even in a metabolically distinct population.

These findings are consistent with phase 2 data published in the NEJM, where retatrutide showed dose-dependent improvements in triglycerides, LDL cholesterol, HbA1c, and blood pressure, foreshadowing the larger phase 3 reductions across the full TRIUMPH program. Researchers following Retatrutide Clinical Trials have noted the reproducibility of these signals across different obesity phenotypes.


How to Interpret Correlated Endpoints: Separating Weight Loss from Direct Effects

This is the central interpretive challenge in Retatrutide Phase 3 Cardiometabolic Endpoints: How to Interpret Triglycerides, Non-HDL Cholesterol, Blood Pressure, and hsCRP Together. Because weight loss itself improves all four markers, it is tempting to attribute every improvement to fat mass reduction. The data suggest a more nuanced picture.

How to Interpret Correlated Endpoints: Separating Weight Loss from Direct Effects

Three interpretive principles matter here:

1. Endpoint timing relative to weight loss trajectory. Triglyceride reductions in GLP-1-class agents tend to appear early, often before peak weight loss is achieved. hsCRP reductions, by contrast, may continue to deepen as adipose-driven inflammation resolves over months. When all four endpoints are measured at the same 80-week timepoint, early and late responders are collapsed into a single number.

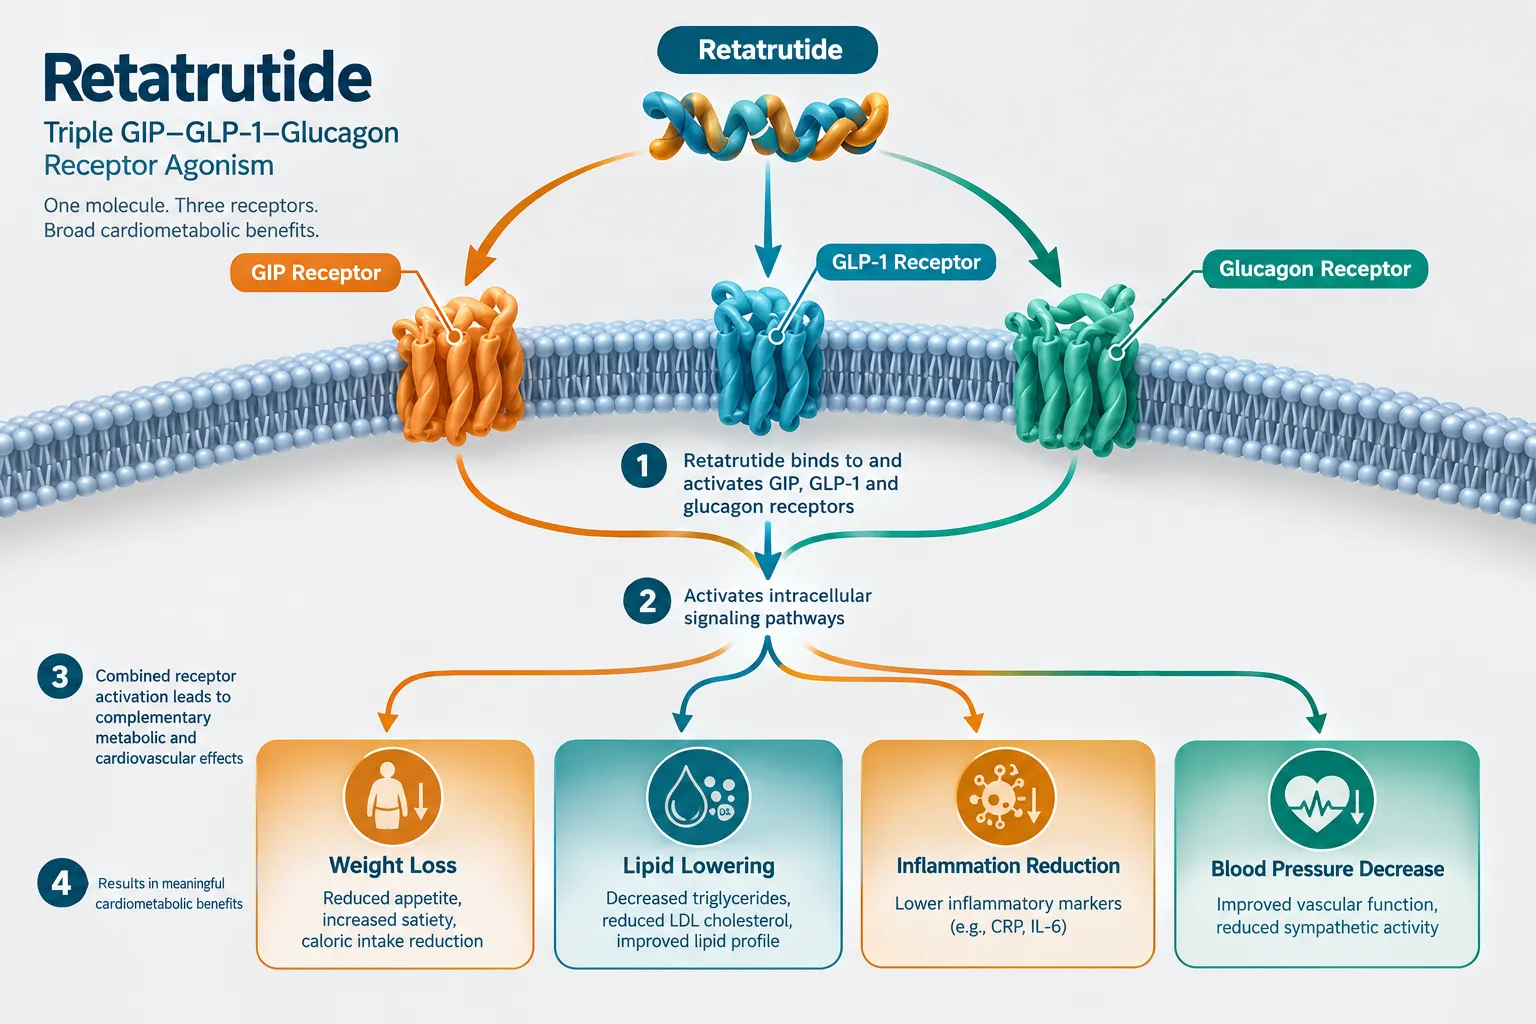
2. Covariate adjustment for weight change. Phase 3 secondary analyses that adjust for weight loss as a covariate can isolate the weight-independent component of each effect. Retatrutide is a triple agonist at GIP, GLP-1, and glucagon receptors. The glucagon receptor pathway has independent effects on hepatic lipid metabolism, particularly relevant to triglyceride clearance, that are not fully explained by adiposity reduction alone. Understanding GLP-1 retatrutide receptor pharmacology helps contextualize why lipid effects may exceed what weight loss alone would predict.

3. Correlation among endpoints does not imply redundancy. A patient showing large triglyceride reduction, moderate non-HDL reduction, meaningful blood pressure lowering, and substantial hsCRP reduction is experiencing improvements across three distinct cardiovascular risk axes simultaneously: atherogenic dyslipidemia, hemodynamic stress, and systemic inflammation. These are additive risk factors in atherosclerotic cardiovascular disease, and their simultaneous reduction is clinically meaningful, even before outcomes data are available.

Key distinction: Non-HDL cholesterol captures all atherogenic lipoproteins (LDL, VLDL, IDL, Lp(a)-associated particles), making it a broader risk marker than LDL alone. A 16.5% to 19.6% reduction in non-HDL represents a meaningful shift in atherogenic burden, particularly relevant in patients with residual risk despite statin therapy.


The Surrogate-to-Outcomes Gap: What the MACE Data Mean for 2026

Understanding Retatrutide Phase 3 Cardiometabolic Endpoints: How to Interpret Triglycerides, Non-HDL Cholesterol, Blood Pressure, and hsCRP Together requires honest engagement with the limits of surrogate data.

The Surrogate-to-Outcomes Gap: What the MACE Data Mean for 2026

In TRIUMPH-3, the composite MACE-5 hazard ratio was 0.82 versus control. This is a numerically encouraging signal. However, it did not reach statistical significance at 80 weeks. This means retatrutide cannot yet be claimed to reduce clinical cardiovascular events, heart attacks, strokes, or cardiovascular deaths, even in a very high-risk population with established cardiovascular disease.

All cardiovascular data available as of 2026 are based on surrogate markers. The dedicated TRIUMPH-Outcomes trial is currently underway to test whether retatrutide lowers major adverse cardiovascular events in adults with overweight or obesity and established cardiovascular disease. Results are not expected until approximately 2029 or later.

What this means for interpretation:

  • Triglyceride, non-HDL, blood pressure, and hsCRP reductions are secondary endpoints in trials designed primarily around weight management and glycemic control.
  • Expert commentaries frame the multi-axis profile as targeting atherogenic lipoproteins, hemodynamic stress, and systemic inflammation simultaneously, a potentially important profile for residual cardiovascular risk.
  • Any expectation of event reduction remains speculative pending the outcomes trial.
  • If TRIUMPH-Outcomes demonstrates meaningful MACE reduction, formal cardiovascular risk-reduction labeling would likely not be possible before the early 2030s.

Researchers tracking Retatrutide Clinical Trial developments should note that the consistency of surrogate endpoint data across TRIUMPH-1, TRIUMPH-2, TRIUMPH-3, and TRIUMPH-4 strengthens confidence in the reliability of these secondary findings, even as the outcomes question remains open. Those interested in the combination pipeline can also review data on Cagrilintide and Retatrutide for context on next-generation cardiometabolic approaches.


Conclusion

The TRIUMPH phase 3 program has produced one of the most comprehensive cardiometabolic secondary endpoint datasets in obesity pharmacology to date. Triglycerides falling 37-39%, non-HDL cholesterol declining 16-20%, systolic blood pressure dropping 9-14 mmHg, and hsCRP reducing by more than half, all at 80 weeks, represent a reproducible, multi-axis cardiometabolic signal across different obesity phenotypes and comorbidity profiles.

Actionable next steps for researchers and clinicians reviewing this data:

  • Examine covariate-adjusted analyses that isolate weight-independent lipid and inflammatory effects before attributing all improvement to fat mass reduction.
  • Treat the four endpoints as complementary axes, not redundant measures, each captures a distinct cardiovascular risk pathway.
  • Apply appropriate interpretive caution: surrogate improvements do not confirm event reduction until TRIUMPH-Outcomes reports.
  • Monitor Eli Lilly's ongoing regulatory submissions and TRIUMPH-Outcomes enrollment milestones, expected to be decisive around 2029.

The cardiometabolic profile of retatrutide is now a central part of its value proposition, not an exploratory footnote. Reading it correctly, with attention to endpoint timing, covariate structure, and the surrogate-to-outcomes gap, is essential for any rigorous assessment of this triple agonist's place in cardiovascular risk management.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-phase-3-cardiometabolic-endpoints-how-to-interpret-triglycerides-non.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-08 13:12:122026-10-08 13:12:12Retatrutide Phase 3 Cardiometabolic Endpoints: How to Interpret Triglycerides, Non-HDL Cholesterol, Blood Pressure, and hsCRP Together
Retatrutide Phase 3 Diabetes Data: Designing Research Models Around A1C, Glucose Exposure, Weight Loss, and Dose Escalation

Retatrutide Phase 3 Diabetes Data: Designing Research Models Around A1C, Glucose Exposure, Weight Loss, and Dose Escalation

October 8, 2026/0 Comments/in Uncategorized/by

Only one drug in the current cardiometabolic pipeline simultaneously activates GLP-1, GIP, and glucagon receptors, and its Phase 3 data are now reshaping how researchers design glycemic studies. Retatrutide Phase 3 diabetes data, drawn from the TRANSCEND and TRIUMPH trial programs, offer an unusually rich dataset for modeling the relationship between A1C reduction, glucose area under the curve (AUC), body weight loss, and structured dose escalation. For researchers building preclinical or translational models, understanding how to separate direct glycemic effects from weight-mediated effects is now a central methodological challenge.

Key Takeaways

  • Retatrutide Phase 3 diabetes data from TRANSCEND-T2D and TRIUMPH-2 provide robust endpoints for A1C, fasting glucose, and body weight in type 2 diabetes populations.
  • Glucose AUC and A1C timing data allow researchers to model direct glycemic receptor effects independently of body-weight-mediated insulin sensitization.
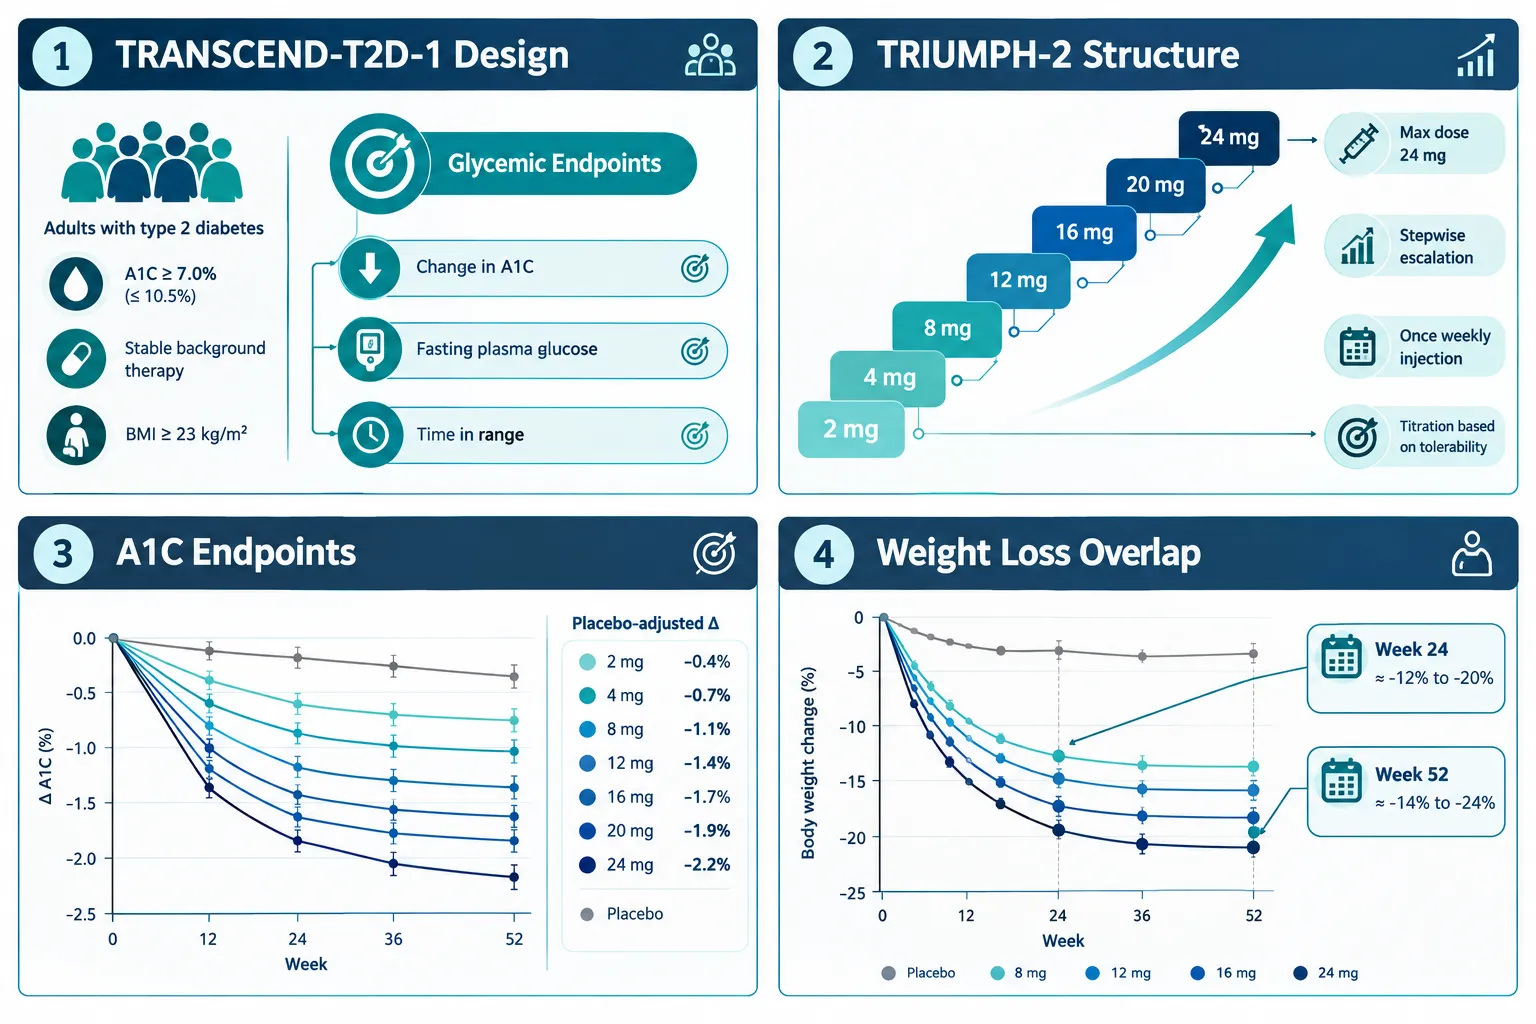
  • Dose escalation protocols in Phase 3 trials (ranging from 2 mg to 24 mg weekly) are critical variables when designing exposure-response research models.
  • Placebo-adjusted analysis is essential for isolating the true pharmacodynamic signal in both glycemic and weight outcomes.
  • The dual burden of hyperglycemia and obesity in trial populations makes retatrutide a uniquely informative compound for integrated cardiometabolic research.

Understanding the Phase 3 Trial Architecture

The TRANSCEND-T2D program is the dedicated diabetes efficacy arm of retatrutide's Phase 3 development. TRANSCEND-T2D-1 enrolled adults with type 2 diabetes and suboptimal glycemic control, using A1C reduction as the primary endpoint alongside fasting plasma glucose and body weight. The trial design included a structured dose escalation schedule, beginning at 2 mg weekly and titrating upward over several weeks to target maintenance doses of 8 mg or 12 mg.

Understanding the Phase 3 Trial Architecture

What makes this data particularly valuable for research modeling is the granularity of glycemic endpoints. A1C was measured at multiple timepoints, and continuous glucose monitoring data in select cohorts provided glucose AUC profiles across fasting and postprandial windows. This allows researchers to distinguish early pharmacodynamic effects, driven by direct receptor activation, from later improvements that correlate more closely with cumulative weight loss.

The broader TRANSCEND-T2D program extends follow-up to 52 weeks and beyond, providing chronic exposure data that are essential for modeling long-term glucose normalization trajectories. Researchers exploring Retatrutide Endpoints will find the TRANSCEND dataset particularly useful for establishing dose-response relationships across glycemic variables.


Separating Glycemic Effects from Weight-Mediated Effects in Retatrutide Phase 3 Diabetes Data

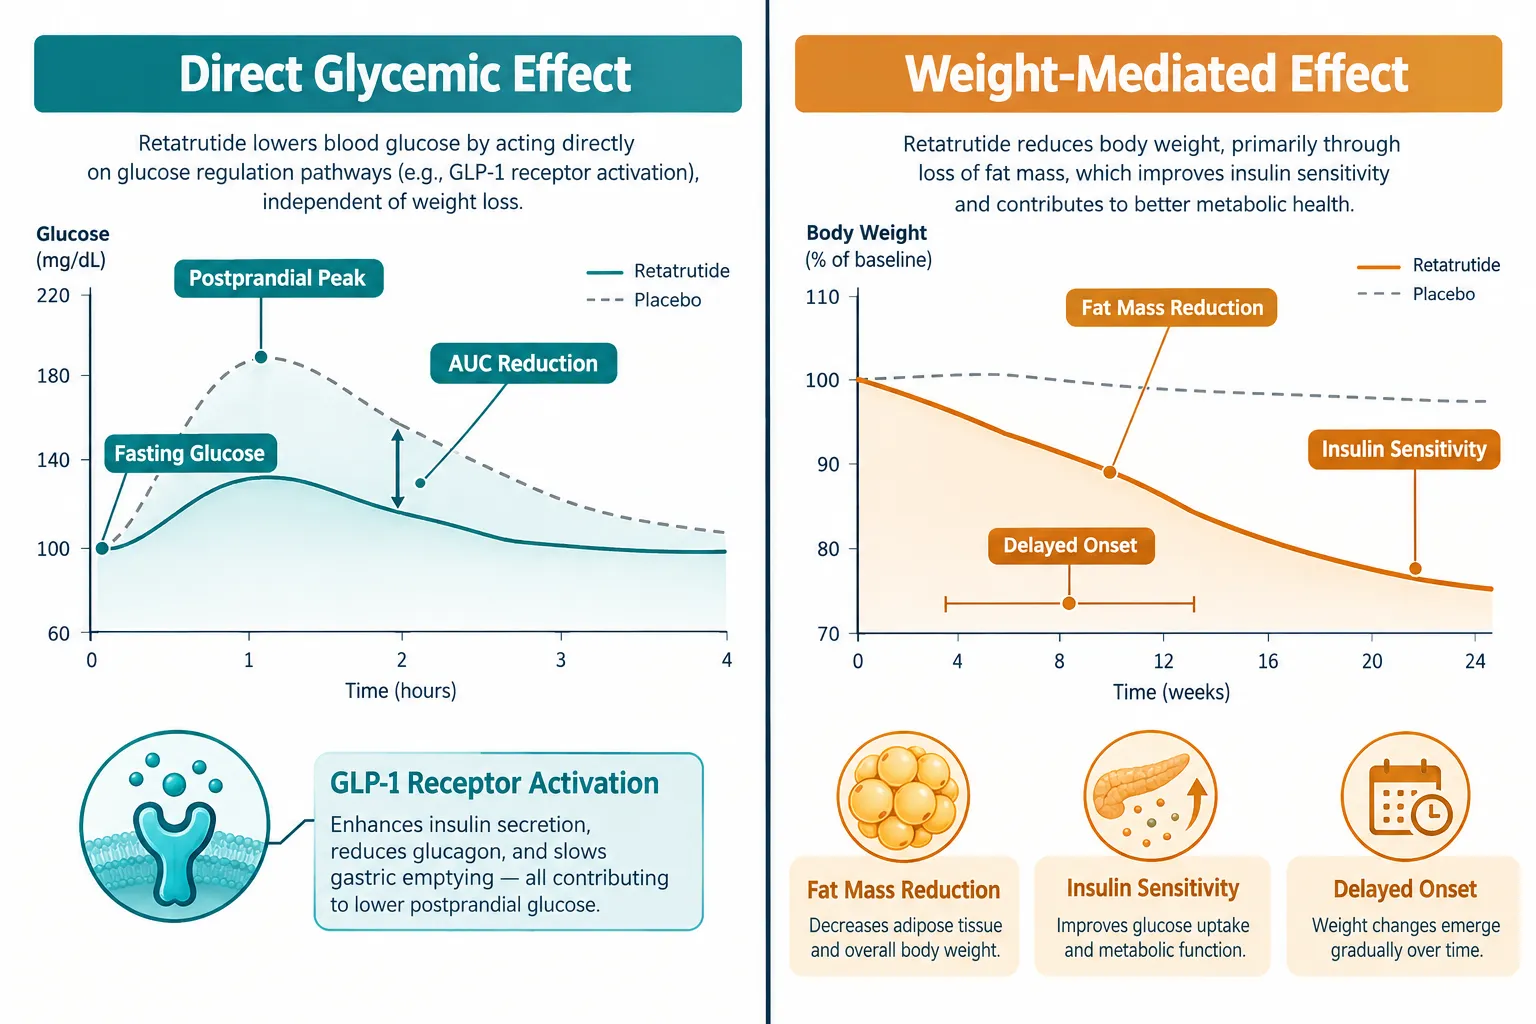
This is the core methodological question that Retatrutide Phase 3 diabetes data: designing research models around A1C, glucose exposure, weight loss, and dose escalation must address. Retatrutide produces two partially overlapping but mechanistically distinct effects: direct incretin-mediated glycemic control and indirect glycemic improvement driven by fat mass reduction and restored insulin sensitivity.

Separating Glycemic Effects from Weight-Mediated Effects in Retatrutide Phase 3 Diabetes Data

Direct glycemic effects are detectable early, often within the first four weeks, before significant weight loss has accumulated. These include:

  • Reduced fasting plasma glucose via GLP-1 receptor-mediated insulin secretion
  • Suppressed glucagon secretion through glucagon receptor agonism at pharmacological doses
  • Improved postprandial glucose AUC through slowed gastric emptying

Weight-mediated glycemic effects emerge later and are characterized by:

  • Progressive improvement in insulin sensitivity correlated with fat mass reduction
  • Declining HOMA-IR scores tracking body weight trajectory
  • A1C reductions that continue after glucose-lowering receptor effects plateau

"Placebo-adjusted A1C delta at Week 12 versus Week 52 provides a practical window for separating these two mechanisms in research model design."

The TRIUMPH-2 trial, which enrolled participants with both obesity and type 2 diabetes, is especially informative here. TRIUMPH-2 reported substantial A1C reductions alongside body weight losses exceeding 20% from baseline at higher doses. By comparing A1C trajectories against weight-loss kinetics, researchers can use time-lagged regression models to quantify the independent glycemic contribution of the drug's receptor activity.

For researchers interested in related dual-mechanism compounds, the Cagrilintide And Retatrutide combination data offer a complementary framework for modeling additive glycemic and weight effects.


Dose Escalation as a Research Variable: Modeling Exposure-Response Relationships

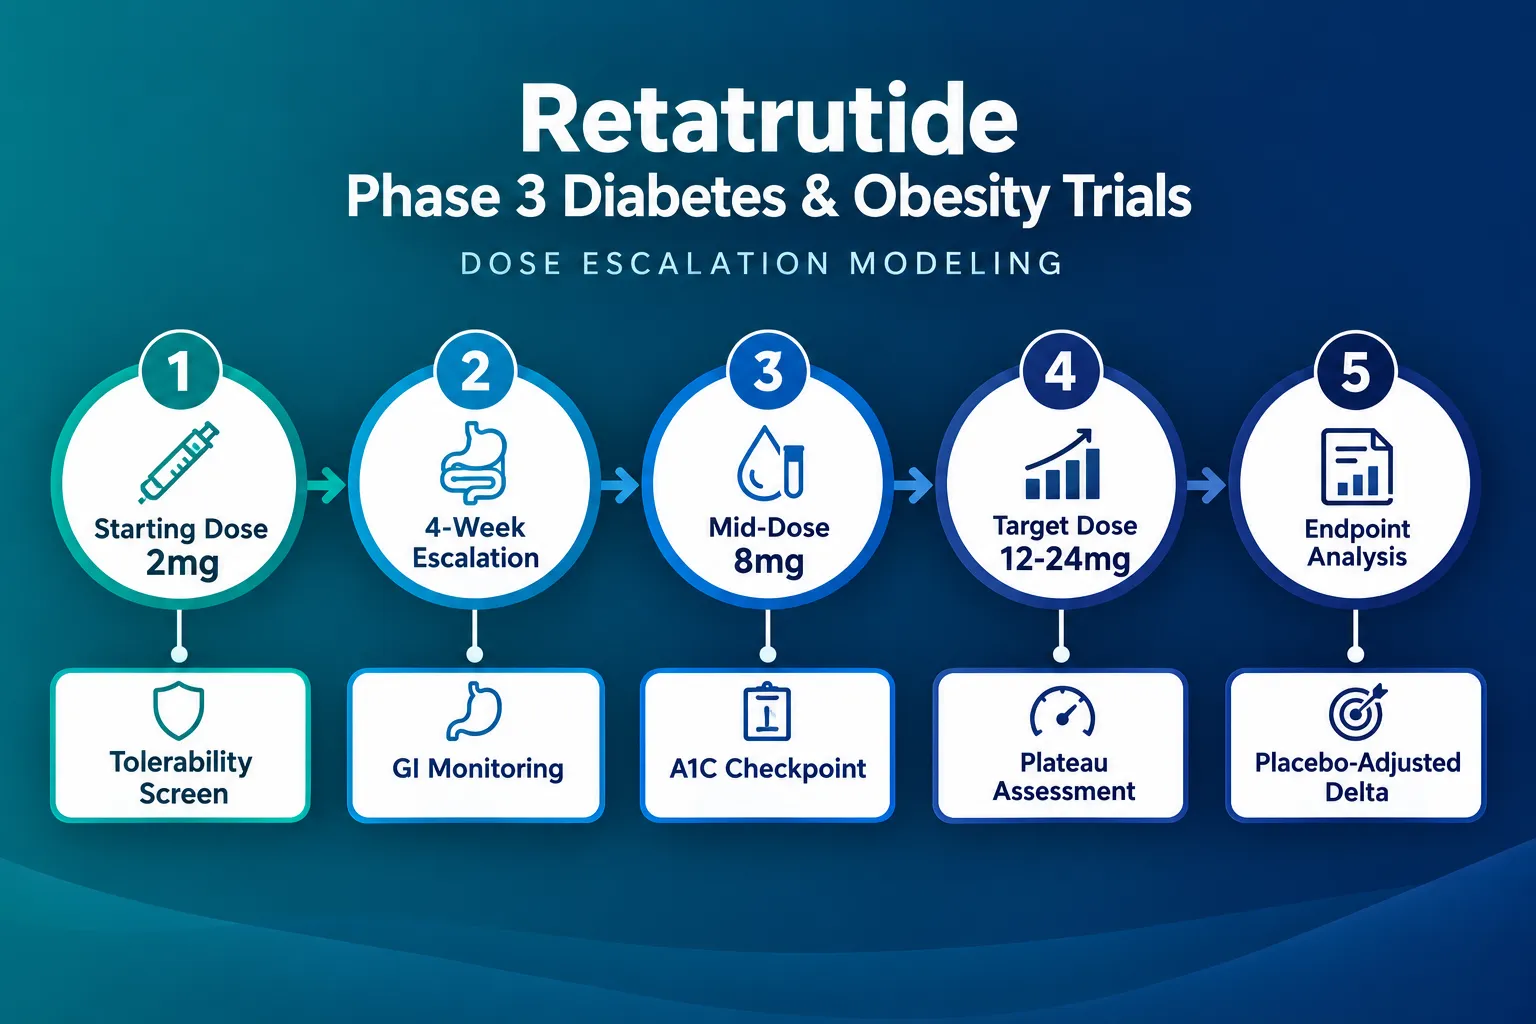
Dose escalation design is not merely a safety protocol, it is a primary research variable in Retatrutide Phase 3 diabetes data: designing research models around A1C, glucose exposure, weight loss, and dose escalation. The Phase 3 programs used weekly subcutaneous dosing with escalation steps at defined intervals, creating a natural dose-exposure ladder that researchers can exploit for pharmacokinetic-pharmacodynamic (PK-PD) modeling.

Dose Escalation as a Research Variable: Modeling Exposure-Response Relationships

Key dose escalation parameters from Phase 3 data include:

Escalation Stage Weekly Dose Primary Research Signal
Initiation 2 mg Tolerability, early GLP-1 effect
Mid-escalation 4-8 mg A1C inflection, glucose AUC shift
Maintenance 12-24 mg Maximum weight loss, sustained A1C

Phase 3b studies without diabetes populations provide a useful comparator, allowing researchers to isolate the weight-loss contribution to glycemic improvement by modeling the delta between diabetic and non-diabetic cohorts at equivalent doses.

For researchers sourcing compounds for preclinical work, GLP-1 Retatrutide and GLP-3 Retatrutide Buy Online USA pages provide relevant product information. Those evaluating quantity options may also review Reta 20mg For Sale and GLP-3 Reta 30mg For Sale for research-grade availability.

The TRIUMPH-1 and TRIUMPH-4 trials, focused primarily on obesity without diabetes, extend the dose-response dataset by providing weight-loss curves at equivalent dose levels without the confounding variable of baseline hyperglycemia. This cross-trial comparison is a powerful tool for building research models that quantify the glycemic benefit attributable solely to weight reduction.


Conclusion

Retatrutide Phase 3 diabetes data: designing research models around A1C, glucose exposure, weight loss, and dose escalation represents one of the most data-rich opportunities in current cardiometabolic research. The TRANSCEND and TRIUMPH programs together provide a structured, multi-dose, multi-timepoint dataset that enables researchers to disentangle direct receptor-mediated glycemic effects from weight-loss-driven improvements.

Actionable next steps for researchers:

  1. Use early-timepoint A1C and glucose AUC data (Weeks 4-12) to establish direct glycemic receptor effect baselines before significant weight loss accumulates.
  2. Apply placebo-adjusted analysis at each dose level to isolate the true pharmacodynamic signal from regression to the mean.
  3. Leverage the TRIUMPH-2 versus TRIUMPH-1 cross-trial comparison to quantify the weight-mediated glycemic contribution at matched dose levels.
  4. Incorporate dose escalation timing as a covariate in PK-PD models to account for exposure-dependent receptor desensitization.
  5. Validate preclinical models against the Phase 3 dose-response ladder before extrapolating to novel endpoints.

The depth of available Phase 3 data makes retatrutide a uniquely powerful reference compound for integrated glycemic and metabolic research model design in 2026.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-phase-3-diabetes-data-designing-research-models-around-a1c-glucose-e.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-08 13:11:152026-10-08 13:11:15Retatrutide Phase 3 Diabetes Data: Designing Research Models Around A1C, Glucose Exposure, Weight Loss, and Dose Escalation
Retatrutide Phase 3 Results in 2026: How Researchers Should Interpret Weight Loss, A1C, and Cardiometabolic Endpoints

Retatrutide Phase 3 Results in 2026: How Researchers Should Interpret Weight Loss, A1C, and Cardiometabolic Endpoints

October 3, 2026/0 Comments/in Uncategorized/by

Fewer than five years after GLP-1 receptor agonists reshaped obesity medicine, a triple-receptor agonist is now producing weight loss figures that exceed nearly every benchmark set by its predecessors. Retatrutide Phase 3 Results in 2026, specifically from Eli Lilly's TRIUMPH program, have placed the research and clinical communities in the unusual position of needing new interpretive frameworks rather than simply updated numbers. Understanding what these results mean, how the trials were designed, and where the data should not be extrapolated is essential for any researcher working with this compound.

Key Takeaways

  • TRIUMPH-1 showed average body weight reductions of up to 28.3% at 80 weeks on the 12 mg dose, with roughly 45% of participants achieving at least 30% weight loss.
  • TRIUMPH-2 demonstrated meaningful A1C reductions alongside weight loss in adults with type 2 diabetes and obesity or overweight.
  • TRIUMPH-3 targeted adults with severe obesity and established cardiovascular disease, expanding the cardiometabolic endpoint dataset.
  • All three trials were 80-week, randomized, double-blind, placebo-controlled studies, setting a high methodological standard for interpretation.
  • Phase 3 clinical findings should not be directly extrapolated to research-use peptide materials without accounting for purity, formulation, and dosing differences.

Understanding the TRIUMPH Trial Architecture

The TRIUMPH program consists of three pivotal Phase 3 trials, each enrolling distinct populations to isolate different aspects of retatrutide's effects. TRIUMPH-1 enrolled adults with obesity or overweight without type 2 diabetes. TRIUMPH-2 enrolled adults who had both type 2 diabetes and obesity or overweight. TRIUMPH-3 focused on adults with severe obesity and established cardiovascular disease. Each trial ran for 80 weeks under a randomized, double-blind, placebo-controlled design, the gold standard for regulatory-grade evidence.

Understanding the TRIUMPH Trial Architecture

Retatrutide itself is a triple agonist acting simultaneously on GLP-1, GIP, and glucagon receptors. This mechanism distinguishes it from dual agonists like tirzepatide and single-receptor agents like semaglutide. Researchers reviewing the retatrutide clinical trial literature should note that the multi-receptor activity complicates direct comparisons with earlier compounds, since each receptor pathway contributes differently to energy expenditure, appetite suppression, and glucose metabolism.

Key dose arms tested across TRIUMPH trials:

Dose Trial Inclusion Primary Role
4 mg once weekly TRIUMPH-1, TRIUMPH-2 Lower-dose comparator
8 mg once weekly TRIUMPH-1, TRIUMPH-2 Mid-range efficacy arm
9 mg once weekly TRIUMPH-1 High-dose efficacy arm
12 mg once weekly TRIUMPH-1, TRIUMPH-2, TRIUMPH-3 Maximum dose efficacy arm

Interpreting Weight Loss Endpoints from Retatrutide Phase 3 Results in 2026

TRIUMPH-1 produced the most widely cited weight loss figures. Participants on the 9 mg dose lost an average of 64.4 lb, representing 25.9% of baseline body weight. Those on the 12 mg dose lost an average of 70.3 lb, or 28.3% of baseline weight. The placebo group lost approximately 2.2%. Approximately 45% of the roughly 2,500 participants achieved at least 30% weight loss, a threshold that had rarely appeared in prior obesity pharmacotherapy trials.

An extension to 104 weeks showed that participants with a BMI of 35 kg/m² or higher on the highest dose lost approximately 30.3% of body weight on average, suggesting the effect is durable rather than plateauing early.

"A 28% average weight reduction in a randomized controlled trial is not a ceiling, it is a new baseline expectation for next-generation obesity pharmacotherapy."

Researchers reviewing these figures alongside retatrutide endpoints data should apply several interpretive cautions:

  • Responder heterogeneity: Mean weight loss masks a wide distribution. Some participants lost far less; others exceeded 35%.
  • Baseline BMI matters: Higher baseline BMI was associated with greater absolute weight loss but not always greater percentage loss.
  • Titration schedules: The dose escalation protocol used in TRIUMPH trials is specific and structured. Rapid titration in research settings produces different tolerability profiles.
  • Placebo subtraction: The net treatment effect, not the absolute loss, is the relevant efficacy signal for mechanistic research.

A1C, Glycemic Control, and Cardiometabolic Endpoints: What the Data Show

TRIUMPH-2 specifically addressed glycemic outcomes in adults with type 2 diabetes. Retatrutide produced substantial A1C reductions across all active dose arms, with the 12 mg arm achieving the largest decreases from baseline. These reductions were accompanied by meaningful weight loss, making it difficult to isolate the glycemic effect of the receptor agonism from the indirect benefit of fat mass reduction, a distinction that matters significantly for mechanistic researchers.

A1C, Glycemic Control, and Cardiometabolic Endpoints: What the Data Show

TRIUMPH-3 extended the dataset to cardiometabolic markers in a higher-risk population. Reported endpoints included changes in blood pressure, triglycerides, LDL-C, and waist circumference. While full cardiovascular outcomes data from a dedicated MACE trial are still pending as of 2026, the surrogate marker improvements observed in TRIUMPH-3 are consistent with the metabolic effects predicted by the triple-receptor mechanism.

Cardiometabolic endpoints researchers should track:

  • Systolic and diastolic blood pressure reduction
  • Fasting triglyceride change from baseline
  • HDL-C and LDL-C shifts
  • Waist circumference as a visceral adiposity proxy
  • Liver enzyme normalization in participants with metabolic-associated steatotic liver disease

How Researchers Should Avoid Misextrapolating Phase 3 Findings

Retatrutide Phase 3 Results in 2026 represent pharmaceutical-grade, GMP-manufactured material administered under controlled clinical conditions. Research-use peptide materials, such as those available as GLP-3 Reta 30mg or GLP-3 Reta 20mg for laboratory use, differ in formulation, excipient profile, and intended application. Researchers sourcing material should consult verified retatrutide peptide buy online resources that provide third-party purity documentation.

How Researchers Should Avoid Misextrapolating Phase 3 Findings

The following extrapolation errors are most common in the literature:

  1. Assuming equivalent bioavailability between pharmaceutical formulations and research-grade lyophilized peptides
  2. Applying TRIUMPH dose arms directly to non-human or in vitro research models without allometric scaling
  3. Conflating A1C reduction with direct receptor-mediated glycemic control when weight loss itself accounts for a significant portion of the glycemic benefit
  4. Ignoring the titration variable, TRIUMPH participants were dose-escalated over weeks, not started at maximum dose
  5. Overstating cardiovascular conclusions before dedicated MACE trial data are published

For researchers comparing retatrutide to other metabolic peptides, reviewing Tesamorelin dosage for fat loss frameworks offers a useful methodological contrast, since Tesamorelin's visceral fat reduction mechanism and endpoint structure differ substantially from triple-receptor agonism.


Conclusion

The Retatrutide Phase 3 Results in 2026 represent a landmark dataset for obesity, diabetes, and cardiometabolic research. The TRIUMPH program's three-trial architecture provides layered evidence across distinct populations, dose arms, and outcome categories. For researchers, the actionable steps are clear:

  • Treat the 80-week, placebo-controlled TRIUMPH data as the interpretive anchor for all mechanistic hypotheses involving retatrutide.
  • Distinguish between mean efficacy signals and responder distributions before drawing mechanistic conclusions.
  • Separate glycemic benefits attributable to weight loss from those attributable to direct receptor agonism when designing downstream studies.
  • Source research-grade material only from suppliers providing verified purity documentation, and never apply clinical dose arms directly to preclinical models without appropriate scaling.
  • Monitor the emerging MACE trial data before drawing cardiovascular outcome conclusions from surrogate markers alone.

The TRIUMPH results do not simply update a number, they reframe what metabolic pharmacotherapy can achieve and raise the methodological bar for how researchers must interpret, contextualize, and apply the data responsibly.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-phase-3-results-in-2026-how-researchers-should-interpret-weight-loss.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-03 13:08:402026-10-03 13:08:40Retatrutide Phase 3 Results in 2026: How Researchers Should Interpret Weight Loss, A1C, and Cardiometabolic Endpoints
Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation

Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation

September 26, 2026/0 Comments/in Uncategorized/by

Fewer than one in ten obesity drugs in history have produced mean weight loss exceeding 20 percent in a phase 3 trial. Retatrutide, a triple receptor agonist targeting GIP, GLP-1, and glucagon pathways simultaneously, has now cleared that threshold by a wide margin, and the implications reach far beyond a single efficacy number.

The full scope of Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation is still being absorbed by the research community. Topline data from the TRIUMPH master protocol and its obesity sub-programs show outcomes that reframe earlier phase 2 benchmarks, raise new questions about cardiovascular labeling, and complicate how scientists define a "weight-loss drug" in the first place.

Key Takeaways

  • Phase 3 obesity data show approximately 28 percent mean weight loss at 80 weeks, with nearly 45 percent of participants achieving 30 percent or greater body weight reduction.
  • A1C improvements in the type 2 diabetes arm reinforce retatrutide's glycemic potential beyond weight loss alone.
  • Cardiovascular outcome data from the obesity-plus-established-CVD trial show MACE hazard ratios that are neutral to modestly favorable, but do not yet confirm a cardiovascular label claim.
  • Phase 2 NEJM results are now viewed as a conservative baseline rather than a peak effect.
  • Retatrutide remains investigational; no regulatory approval has been granted as of 2026.

What the Obesity Efficacy Numbers Actually Mean

What the Obesity Efficacy Numbers Actually Mean

The headline figure from the pivotal obesity phase 3 program is approximately 28 percent mean body weight reduction at 80 weeks. That number demands context. Semaglutide 2.4 mg produced roughly 15 percent in its landmark trial; tirzepatide reached approximately 22 percent at its highest dose. Retatrutide's figure, if confirmed in peer-reviewed publication, would represent the largest mean weight loss ever reported for a pharmacological agent in a phase 3 obesity study.

Equally striking is the distribution of response. Roughly 45 percent of participants achieved 30 percent or greater weight loss, a threshold that, in earlier eras, was associated only with bariatric surgery. That figure matters because it shifts the clinical conversation from average outcomes to what a subset of patients might realistically expect.

"The ceiling for pharmacological weight loss may not have been reached yet, but retatrutide has moved it substantially higher."

Researchers tracking Retatrutide Clinical Trials note that discontinuation rates and tolerability data are critical to interpreting these numbers fairly. Gastrointestinal adverse events, nausea, vomiting, diarrhea, remain the most common side effects, consistent with the incretin class. Dropout rates tied to adverse events have not been negligible, which means the 28 percent figure reflects a population that tolerated the drug well enough to complete the protocol.


Glycemic and Cardiovascular Findings: Separating Signal from Claim

Glycemic and Cardiovascular Findings: Separating Signal from Claim

The type 2 diabetes arm of the phase 3 program adds a second layer of significance to the overall data picture. A1C reductions were clinically meaningful, and the breadth of cardiometabolic risk-factor improvements, including blood pressure, triglycerides, and waist circumference, reinforces the argument that retatrutide acts as a systemic cardiometabolic modulator rather than a simple appetite suppressant.

This distinction matters for research interpretation. When a compound simultaneously reduces body weight, lowers blood glucose, improves lipid panels, and reduces blood pressure, the mechanism of benefit becomes difficult to attribute to any single pathway. That complexity is scientifically valuable but also complicates regulatory discussions about labeling.

The cardiovascular outcome trial enrolled participants with obesity and established cardiovascular disease. MACE (major adverse cardiovascular events) hazard ratios came in neutral to modestly favorable, a result that is encouraging but not yet sufficient to support a dedicated cardiovascular risk-reduction label claim. Researchers reviewing Retatrutide Clinical Trial data consistently note that risk-factor improvement and hard cardiovascular event reduction are not interchangeable endpoints.

Key distinctions from the cardiovascular data:

  • Improved risk factors (blood pressure, lipids, weight) are confirmed across trials
  • MACE hazard ratios are neutral to modestly favorable, not definitively protective
  • A cardiovascular label claim would require additional event-driven data
  • Monitoring for cardiovascular and gastrointestinal signals remains active in ongoing maintenance studies

How Phase 3 Data Reshape Research Interpretation Going Forward

How Phase 3 Data Reshape Research Interpretation Going Forward

Understanding Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation requires stepping back from individual endpoints and examining what the data collectively signal about the incretin class ceiling.

Phase 2 results published in the New England Journal of Medicine were widely cited as evidence of exceptional efficacy. Phase 3 data now reframe those results as a conservative baseline, not a peak effect. That inversion is unusual in drug development, where phase 3 trials frequently show more modest outcomes than earlier studies due to broader, more heterogeneous populations.

Several interpretive questions now dominate expert commentary:

Research Question Why It Matters
Duration of effect Does weight loss plateau, reverse, or persist beyond 80 weeks?
Head-to-head trials How does retatrutide compare directly to tirzepatide or semaglutide?
Class generalizability Do triple agonism benefits extend to other compounds in development?
Real-world CV impact Will risk-factor gains translate to event reduction outside trial conditions?
Cost and access High efficacy is only meaningful if patients can sustain treatment

The TRIUMPH maintenance study is still active, and its results will be central to answering the durability question. Industry framing has leaned heavily on "next-generation" language, but researchers caution that approval timelines and cardiovascular label expectations remain separate conversations from efficacy data.

For those following the science of triple-receptor agonism alongside related peptide research, including work on IPA Sermorelin Stack Research and metabolic modulation, the retatrutide data set offers a rare opportunity to observe how mechanism-of-action complexity translates into clinical outcomes at scale.


Conclusion

Retatrutide Phase 3 Results represent a genuine inflection point in obesity and cardiometabolic research, not because any single number is record-breaking in isolation, but because the combination of weight loss magnitude, glycemic improvement, and cardiovascular signal breadth forces a reclassification of what this compound is and what it does.

Actionable next steps for researchers and clinicians following this space:

  1. Wait for peer-reviewed publication of full TRIUMPH-1 data before drawing conclusions from topline press releases.
  2. Distinguish between risk-factor improvements and hard cardiovascular event data when evaluating cardiovascular claims.
  3. Track the maintenance study for durability evidence beyond 80 weeks.
  4. Monitor head-to-head trial announcements, which will provide the most clinically relevant comparative data.
  5. Evaluate discontinuation and tolerability rates alongside efficacy figures to form a complete picture of real-world applicability.

Retatrutide remains investigational as of 2026. The data are compelling, the mechanistic rationale is strong, and the research interpretation is still evolving. That combination makes this one of the most closely watched drug development programs in metabolic medicine today.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-phase-3-results-how-weight-loss-a1c-and-cardiovascular-findings-chan.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-26 13:10:202026-09-26 13:10:20Retatrutide Phase 3 Results: How Weight Loss, A1C, and Cardiovascular Findings Change Research Interpretation
Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols

Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols

September 24, 2026/0 Comments/in Uncategorized/by

By August 2026, a key obesity Phase 3 study within the TRIUMPH program was officially marked as completed in clinical trial registries, a milestone that is already forcing researchers to rethink how they design, benchmark, and report nonclinical studies involving metabolic peptides. The Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols conversation is no longer speculative. The data are in, and they are reshaping the field.

Key Takeaways

  • Retatrutide's TRIUMPH Phase 3 program has produced weight-loss outcomes of up to 30% at 104 weeks, approaching bariatric surgery benchmarks.
  • Dual efficacy on body weight and glycemic control (up to 1.9-point A1c reduction) makes single-endpoint trial designs increasingly inadequate.
  • Conservative titration schedules and improved retention strategies are now a protocol necessity, not an option.
  • Multi-indication Phase 3 data covering knee OA, OSA, MASLD, and cardiovascular outcomes are expanding the scope of required comparator arms.
  • Retatrutide remains investigational as of late 2026, meaning all research use is subject to regulatory-oriented trial design standards.

The TRIUMPH Program: A Phase 3 Snapshot That Changes Benchmarks

Retatrutide is a first-in-class triple agonist targeting GIP, GLP-1, and glucagon receptors simultaneously. That triple mechanism is what separates it from existing approved therapies and from earlier dual-agonist candidates. For researchers working with retatrutide clinical trial data, the TRIUMPH program now provides the most complete Phase 3 picture available for any triple agonist.

The TRIUMPH Program: A Phase 3 Snapshot That Changes Benchmarks

The headline numbers are striking:

  • TRIUMPH-1 (obesity without diabetes): approximately 19-28% weight loss at 80 weeks, rising to roughly 30% at 104 weeks.
  • TRIUMPH-2 (obesity with type 2 diabetes): 13-21% weight loss plus up to a 1.6% A1c reduction over 80 weeks.
  • TRIUMPH-3 (severe obesity with established cardiovascular disease): approximately 23% weight loss with manageable discontinuation rates.

"Bariatric-like efficacy from a weekly injectable peptide is no longer a theoretical ceiling, TRIUMPH-3 data make it a documented outcome."

These figures introduce what some analysts are calling "de-obesification" endpoints, a term reflecting the normalization of BMI as a primary outcome rather than a secondary marker. For anyone reviewing GLP-1 Reta or GLP-3 Reta research-use compounds, understanding this endpoint shift is essential context.


How the 2026 Obesity and Diabetes Data Rewrites Protocol Design

The Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols discussion centers on four concrete areas where existing study designs are now outdated.

1. Endpoint Selection

Single-endpoint designs that measure only weight or only glycemic control are no longer sufficient when the reference compound achieves both simultaneously. Researchers should now plan co-primary endpoints that capture:

  • Percent total body weight loss
  • A1c reduction
  • Cardiometabolic markers (blood pressure, lipids, inflammatory markers)
  • BMI normalization rates

2. Comparator Arm Selection

TRIUMPH data push the efficacy bar to near-surgical levels. Using older GLP-1 monotherapies as the sole active comparator now risks underestimating effect size. Protocol designers should consider:

Comparator Type Relevance Post-TRIUMPH
Older GLP-1 monotherapy Insufficient ceiling for effect-size modeling
Dual agonist (e.g., tirzepatide) Appropriate active comparator
Bariatric surgery outcomes Now a legitimate benchmark arm
Placebo only Acceptable but limits translational value

For broader context on how peptide mechanisms interact with metabolic pathways, the Peptides 101 for Research-Use Only Buyers resource provides a useful structural overview.

3. Dose-Response Modeling

3. Dose-Response Modeling

TRIUMPH safety data revealed that aggressive titration schedules drove higher discontinuation rates. This finding is directly actionable for nonclinical protocol design. Dose-response models should now incorporate:

  • Extended low-dose phases before escalation
  • Plateau detection windows to identify responders before maximum dosing
  • Dropout probability curves built from TRIUMPH discontinuation patterns

Researchers using Reta 10mg formulations in nonclinical settings should map titration schedules against TRIUMPH's published escalation timelines to ensure their models remain translatable.

4. Adverse-Event Reporting Standards

The TRIUMPH program's safety profile, primarily gastrointestinal events, has established a new floor for what must be captured and reported. Nonclinical adverse-event frameworks should now include structured tracking for:

  • Nausea and vomiting incidence by dose level
  • Time-to-onset relative to titration step
  • Severity grading aligned with TRIUMPH's published criteria

Expanding Scope: Multi-Indication Data and What Comes Next

The Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols story does not end with weight and glycemia. The TRIUMPH program includes at least seven additional Phase 3 datasets expected through 2026-2027, covering knee osteoarthritis, obstructive sleep apnea, metabolic-associated steatotic liver disease (MASLD), chronic pain, and cardiovascular-renal outcomes.

Expanding Scope: Multi-Indication Data and What Comes Next

This multi-indication expansion has two immediate implications for protocol designers:

  1. Organ-specific endpoints (liver stiffness scores, AHI reductions, joint function scales) will need to be incorporated into metabolic research designs that previously focused only on weight.
  2. Comparator arms will need to account for condition-specific active controls, not just metabolic benchmarks.

Researchers working in adjacent areas, such as mitochondrial function studies or growth hormone secretagogue research, should note that Tesamorelin data on visceral fat reduction may serve as a useful secondary comparator in MASLD-adjacent protocols.


Conclusion

The TRIUMPH Phase 3 program has fundamentally changed the reference frame for metabolic research protocols. Researchers who continue using pre-2026 endpoint structures, outdated comparator arms, or aggressive titration schedules will produce data that are difficult to interpret against the current evidence base.

Actionable next steps for protocol teams:

  1. Audit existing endpoint frameworks against TRIUMPH co-primary outcomes and add cardiometabolic markers where absent.
  2. Replace or supplement older GLP-1 monotherapy comparators with dual-agonist or bariatric-surgery benchmarks.
  3. Build conservative titration schedules into dose-response models and document dropout probability curves.
  4. Expand adverse-event capture to include time-to-onset data aligned with TRIUMPH's published safety criteria.
  5. Monitor the seven additional TRIUMPH Phase 3 readouts expected through 2027 and update protocols as each dataset publishes.

Retatrutide remains investigational as of late 2026. All research use must align with regulatory-oriented trial design standards. The data, however, are no longer a moving target, and protocol teams that adapt now will be best positioned when regulatory submissions begin.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/retatrutide-phase-3-results-in-2026-what-the-new-obesity-and-diabetes-data-chang.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-24 13:05:072026-09-24 13:05:07Retatrutide Phase 3 Results in 2026: What the New Obesity and Diabetes Data Changes for Research Protocols
Page 1 of 212
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top