

Amlodipine, Metoprolol, and Losartan in Peptide Experiments: Choosing Cardiovascular Control Arms
Fewer than one in five published peptide cardiovascular studies include a mechanistically matched small-molecule control arm, a gap that makes it nearly impossible to separate a peptide's novel activity from effects shared with established drugs. For researchers working with retatrutide, growth-hormone secretagogues, natriuretic peptides, or any vascular-active compound, the choice between amlodipine, metoprolol, and losartan in peptide experiments is not a formality. It is a core design decision that determines whether the data can actually answer a mechanistic question.
Key Takeaways
- Amlodipine, metoprolol, and losartan target three distinct cardiovascular axes, calcium influx, beta-adrenergic signaling, and RAAS, so the right control depends entirely on the peptide's suspected pathway.
- Mismatching a control drug to a peptide target confounds results; a beta-blocker control is irrelevant in a calcium-handling study.
- Standard in vitro concentration ranges for these agents are well-established and should bracket the peptide's tested range.
- Shared readouts (force of contraction, cAMP levels, BNP secretion) allow direct comparison between drug controls and peptide effects.
- Building rigorous reference benchmarks around control arms strengthens the experimental framework for any cardiovascular peptide study.
Why Mechanistic Matching Is the First Rule
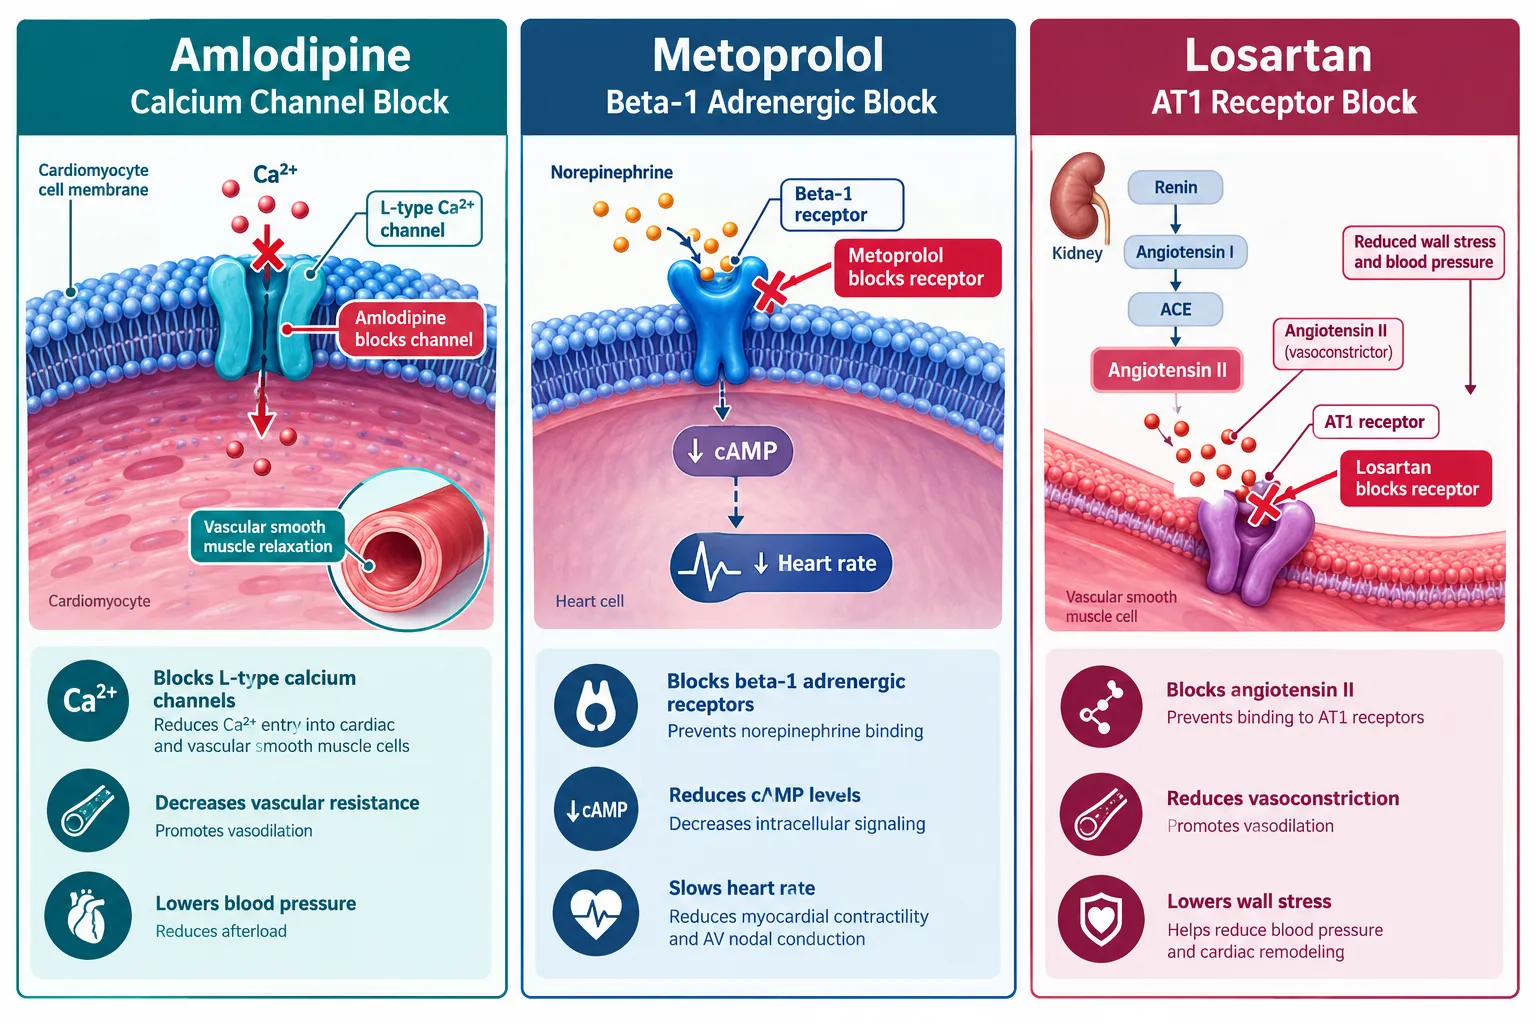
The phrase "positive control" is often used loosely in peptide research. In cardiovascular contexts, a true control arm must share the target pathway of the experimental compound, not merely produce a measurable hemodynamic effect. Amlodipine, metoprolol, and losartan in peptide experiments serve as mechanistic anchors, each isolating a separate axis of cardiovascular regulation.
Amlodipine blocks L-type voltage-gated calcium channels in cardiomyocytes and vascular smooth muscle. It is the appropriate control when a peptide is expected to alter intracellular calcium handling, reduce vascular tone through calcium-dependent mechanisms, or modulate excitation-contraction coupling. Studies examining SS-31 analogs or mitochondria-targeted peptides with cardiac calcium implications, for example, benefit directly from an amlodipine reference arm. For researchers sourcing materials for such models, reviewing SS-31 10mg research peptide considerations provides useful background on experimental framing.
Metoprolol, a selective beta-1 adrenergic receptor antagonist, is the logical control for peptides that intersect sympathetic nervous system signaling, heart rate, cAMP-PKA pathways, or cardiomyocyte survival under adrenergic stress. Growth-hormone secretagogues and ghrelin-axis peptides can activate signaling cascades that overlap with adrenergic pathways, making metoprolol a relevant comparator. Understanding peptide half-life considerations also informs dosing schedules when aligning a peptide's exposure window with metoprolol's pharmacodynamic duration.
Losartan, an angiotensin II type-1 receptor antagonist, belongs in experiments involving natriuretic peptides, wall-stress signaling, or RAAS-interacting compounds. Retatrutide and other multi-receptor peptides show hemodynamic effects that partially overlap with RAAS modulation; losartan quantifies that component. Researchers exploring the GLP-3 peptide signaling pathway will find that angiotensin-receptor control arms help isolate GLP-receptor-specific effects from broader vasoregulatory noise.
Concentration Ranges and Key Readouts
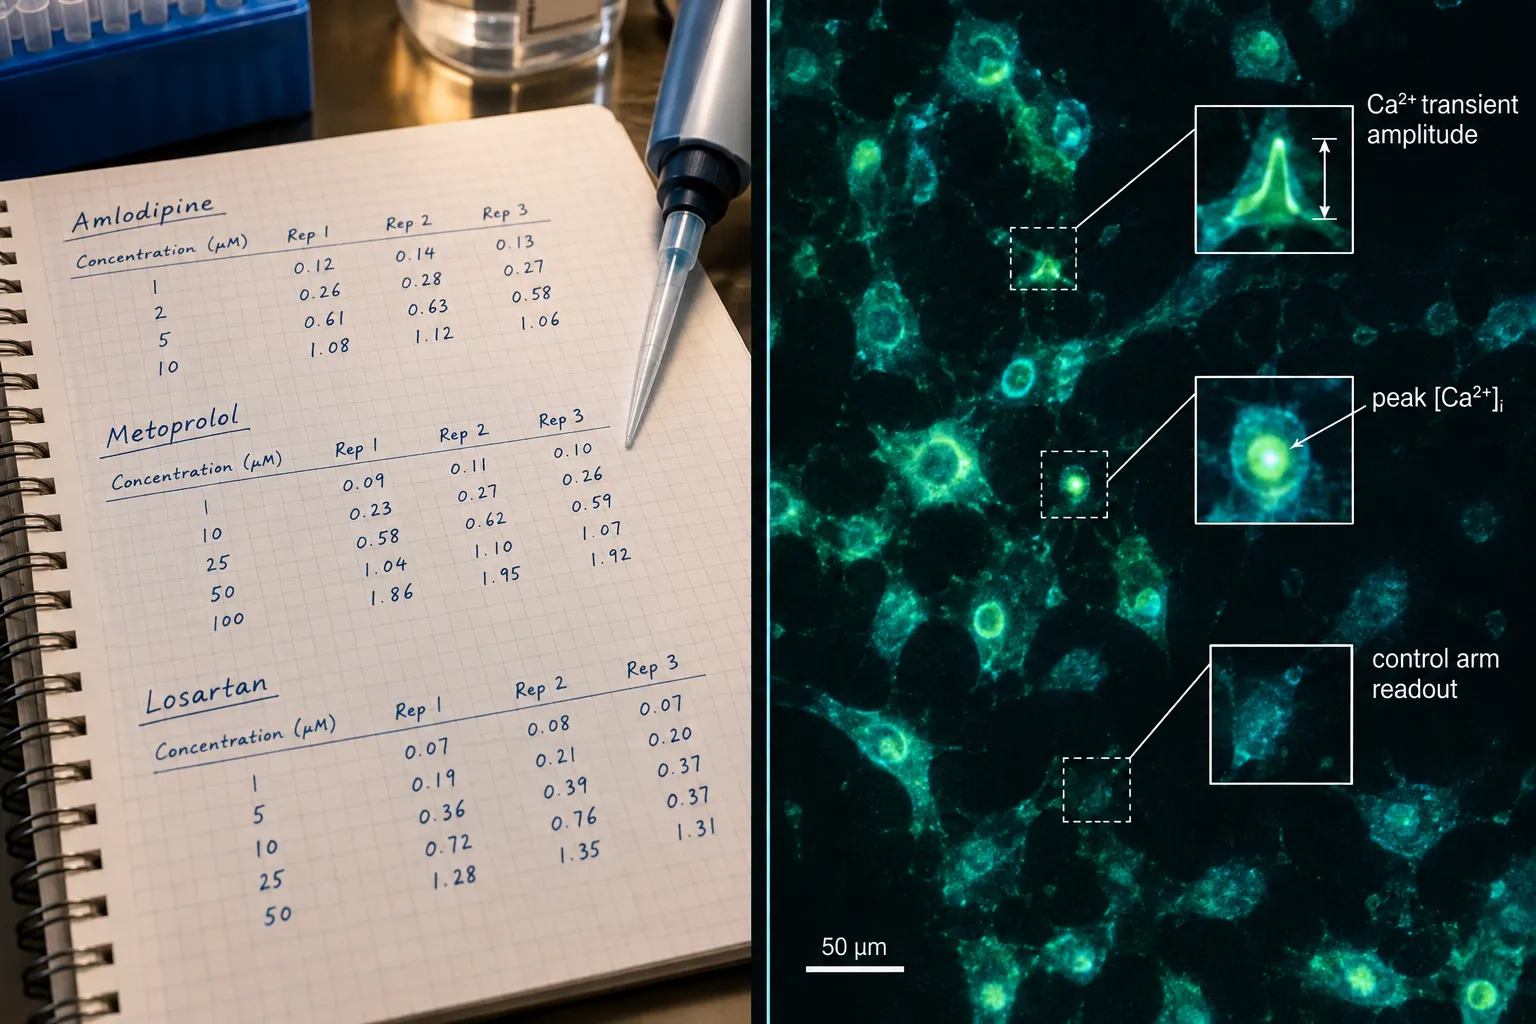
Selecting the right drug is only half the problem. Using it at a physiologically and experimentally relevant concentration is equally critical.
Standard in vitro working ranges:
| Drug | Typical In Vitro Range | Primary Readout |
|---|---|---|
| Amlodipine | 1-10 µM | Peak [Ca2+]i, L-type current amplitude |
| Metoprolol | 1-100 µM | cAMP levels, heart rate (in intact preparations) |
| Losartan | 1-50 µM | BNP/ANP secretion, MAPK phosphorylation |
These ranges should bracket the concentration-response curve of the experimental peptide. If a peptide is tested at 10 nM to 1 µM, the control drug should also span a comparable effect range so that the comparison is meaningful rather than arbitrary.
Readouts deserve equal attention. For calcium-handling studies, peak calcium transient amplitude and sarcoplasmic reticulum load mirror the readouts used with amlodipine directly. For beta-adrenergic work, cAMP quantification and phospholamban phosphorylation status are standard. For RAAS-oriented experiments, brain natriuretic peptide secretion and ERK1/2 activation are well-validated endpoints.
Researchers building rigorous benchmarking workflows should consult resources on Bachem and reference standards for building robust peptide benchmarks to ensure the purity and characterization of both control and experimental compounds meet publication-grade standards.
Practical Framework for Choosing Among the Three Agents
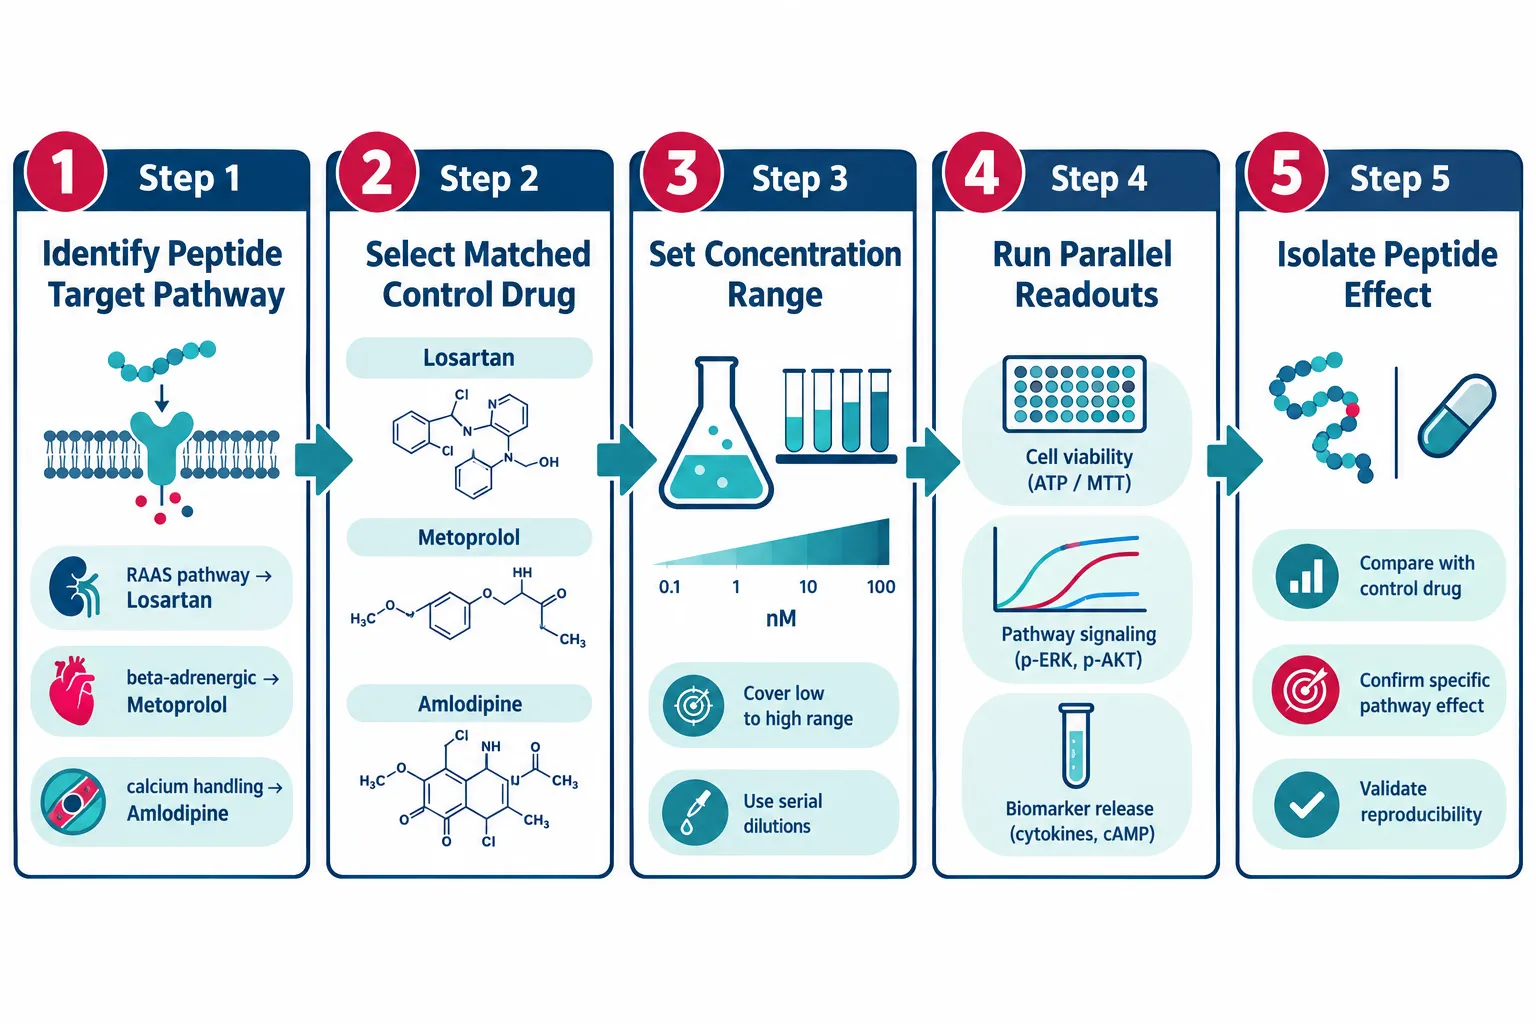
The following decision logic applies when designing control arms for cardiovascular peptide experiments:
- Map the peptide's suspected receptor target. Does it bind a GPCR linked to Gq/calcium, Gs/cAMP, or a receptor tyrosine kinase with downstream RAAS crosstalk?
- Select the drug that blocks the same downstream node. Calcium node → amlodipine. cAMP/adrenergic node → metoprolol. Angiotensin/wall-stress node → losartan.
- Consider multi-pathway peptides. Retatrutide acts on GLP-1R, GIP-R, and glucagon receptors simultaneously. Its hemodynamic profile may require both a losartan arm (for RAAS overlap) and a metoprolol arm (for sympathetic activation overlap). Using a single control drug in a multi-receptor study risks misattributing effects.
- Avoid confounded control arms. Running amlodipine alongside a peptide that has no known calcium-channel interaction adds noise without interpretive value. Worse, a pharmacodynamically mismatched control can create an apparent "superiority" for the peptide that reflects the control's irrelevance rather than the peptide's potency.
For GLP-axis peptides specifically, cross-referencing the GLP-1 peptide buy: generational research concepts and sourcing notes page helps contextualize which receptor subtypes are relevant when choosing angiotensin versus adrenergic controls.
Similarly, researchers working on BPC-157 or TB-500 vascular regeneration studies should align control arm selection with documented angiogenic and adrenergic crosstalk. The TB-500 buy: controlled experimental models and QC workflow resource addresses model-selection principles that apply directly to control arm design.
Key principle: A control arm that cannot be mechanistically explained in the methods section is not a control arm, it is a variable.
Conclusion
Implementing amlodipine, metoprolol, and losartan in peptide experiments is most effective when each agent is matched precisely to the target pathway under investigation. Amlodipine anchors calcium-handling studies, metoprolol isolates adrenergic and survival signaling comparisons, and losartan controls for RAAS and natriuretic peptide pathway contributions.
Actionable next steps for researchers in 2026:
- Before finalizing a protocol, map the peptide's receptor-to-effector cascade and identify which of the three drug mechanisms overlaps with it.
- Use published concentration-response data for each control drug to set bracketing doses that match the peptide's tested range.
- For multi-receptor peptides like retatrutide, consider running two control arms in parallel rather than choosing a single agent.
- Document the mechanistic rationale for control arm selection explicitly in the methods section to satisfy peer-review scrutiny.
- Maintain compound purity documentation for both control drugs and experimental peptides to ensure readout differences reflect biology, not chemistry.
Rigorous control arm selection does not slow experiments, it is what makes their results interpretable.


Leave a Reply
Want to join the discussion?Feel free to contribute!