Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu
CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifacts

CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifacts

October 5, 2026/0 Comments/in Uncategorized/by

Clinic-based reports consistently describe 3- to 5-fold increases in GH pulse amplitude when CJC-1295 is paired with ipamorelin, yet as of 2026, not a single published randomized controlled trial has tested the combination in humans. That gap between widespread clinical use and rigorous experimental evidence is not a minor footnote. It means that nearly every claim about "synergistic" or "additive" GH pulses from this blend is built on data that cannot cleanly distinguish true pharmacodynamic interaction from artifacts of dosing schedule, peptide form, meal timing, and background GH status.

Understanding CJC-1295 with ipamorelin: how to separate additive GH-pulse effects from blend and timing artifacts requires a disciplined study-design framework, one that treats synergy as a hypothesis to test, not a starting assumption.

Key Takeaways

  • No RCT has directly tested the CJC-1295 plus ipamorelin combination; all GH-pulse data are clinic-based or extrapolated from single-agent studies.
  • Using CJC-1295 with DAC creates a sustained GH elevation lasting days, which can masquerade as pulse synergy and must be avoided in pulse-focused research.
  • A 2×2 factorial design with vehicle controls is the minimum study architecture needed to isolate true additive GH-pulse effects from timing and exposure artifacts.
  • Fasted pre-sleep dosing and consistent circadian phase-locking reduce meal- and sleep-related variability that inflates apparent pulse amplitude.
  • Staggered dosing intervals (CJC-1295 first, ipamorelin 15-30 minutes later) versus simultaneous injection offer a practical within-subject comparison of pulse shape and kinetics.

Why the Peptide Form Changes Everything
Why the Peptide Form Changes Everything

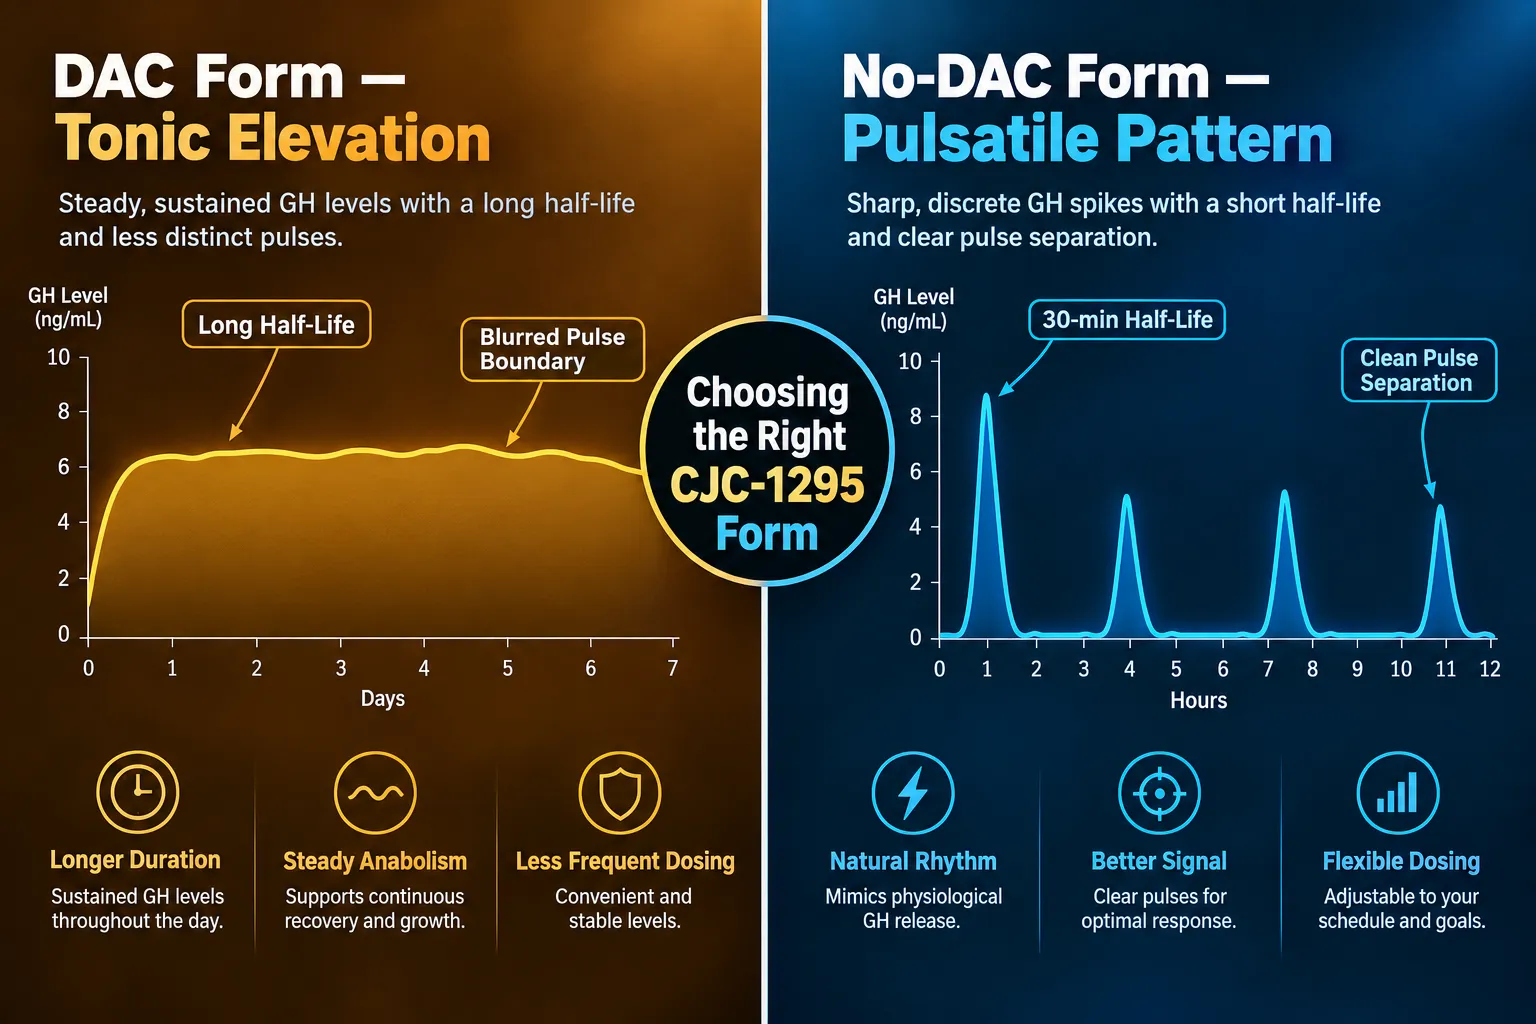
The first design decision, and the most consequential, is which form of CJC-1295 is used. The DAC (Drug Affinity Complex) version binds albumin after injection, extending its half-life to several days. Single subcutaneous doses have produced 2- to 10-fold increases in mean plasma GH lasting six or more days, with IGF-1 elevations persisting 9-11 days. That pharmacokinetic profile is incompatible with pulsatile GH research. When baseline GH is elevated for nearly two weeks, any ipamorelin-triggered spike departs from an already-raised platform, making the combined peak appear larger than it actually is relative to a true resting state.

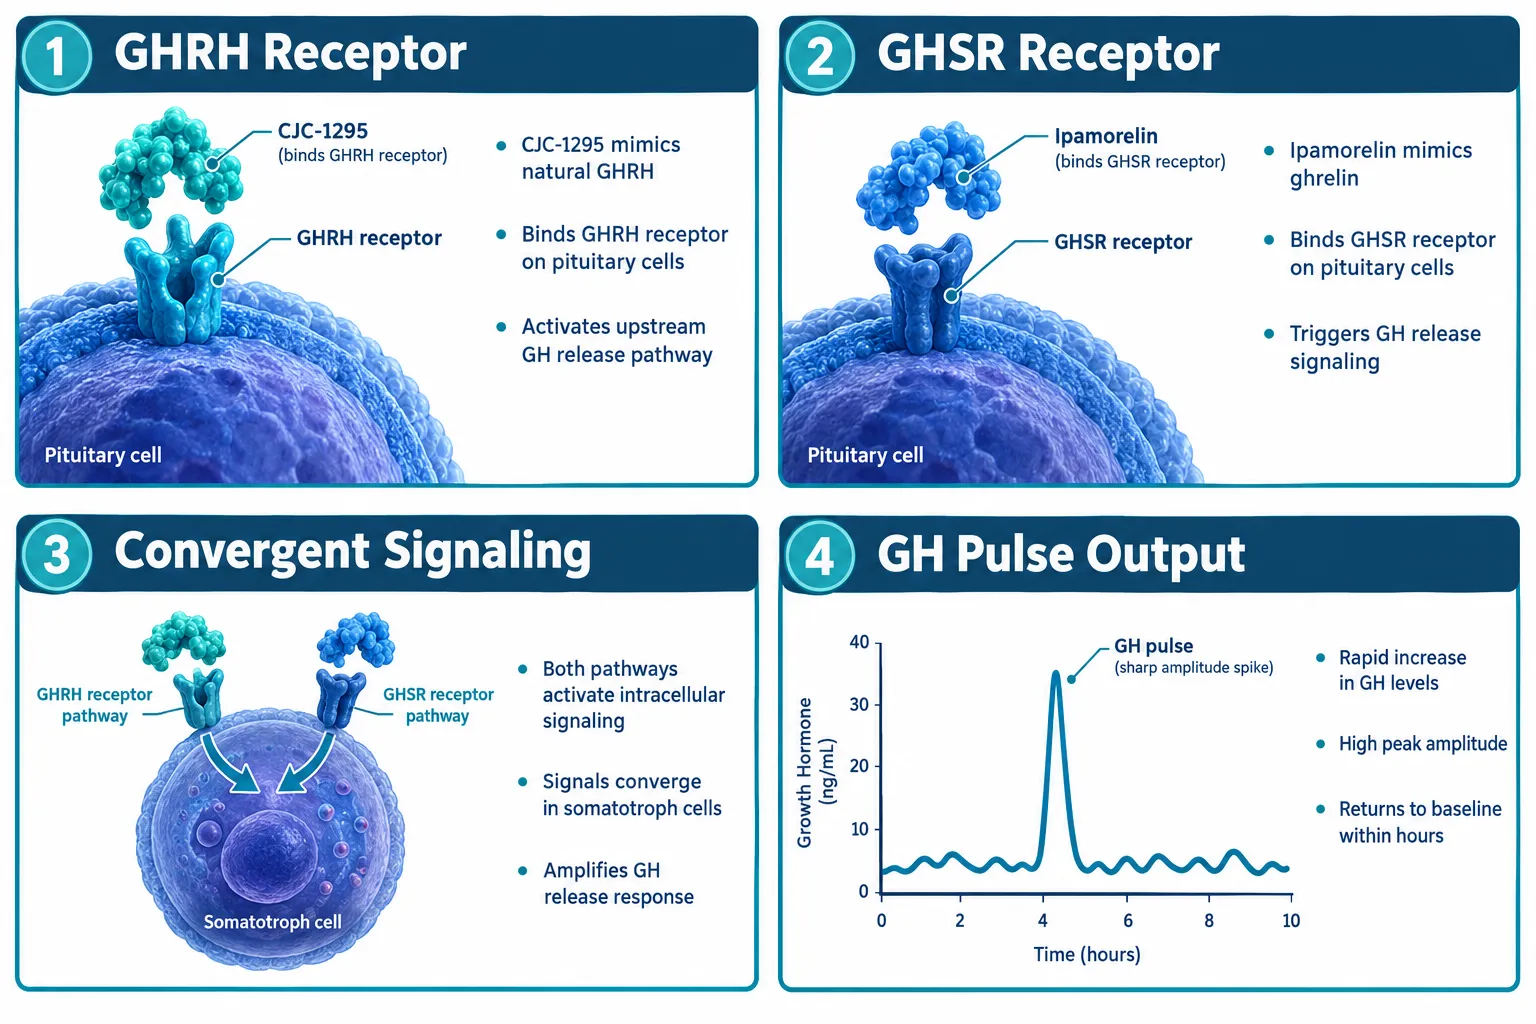
CJC-1295 no-DAC (mod-GRF 1-29) solves this problem. Its reported half-life is roughly 30 minutes. Ipamorelin's half-life is approximately 2 hours. Co-administering the two creates a short, overlapping signaling window that preserves a discrete pulsatile pattern. The GHRH receptor (targeted by CJC-1295) and the growth hormone secretagogue receptor (targeted by ipamorelin) are distinct but convergent pathways at the somatotroph cell. Activating both simultaneously amplifies GH release beyond what either agent achieves alone, but only the no-DAC form keeps that interaction measurable as a clean pulse rather than a tonic elevation.

Anyone exploring the Tesamorelin CJC-1295 Ipamorelin 12mg blend should understand this distinction before interpreting any GH data from a multi-peptide formulation.


A Factorial Study Design for CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifacts
A Factorial Study Design for CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifa

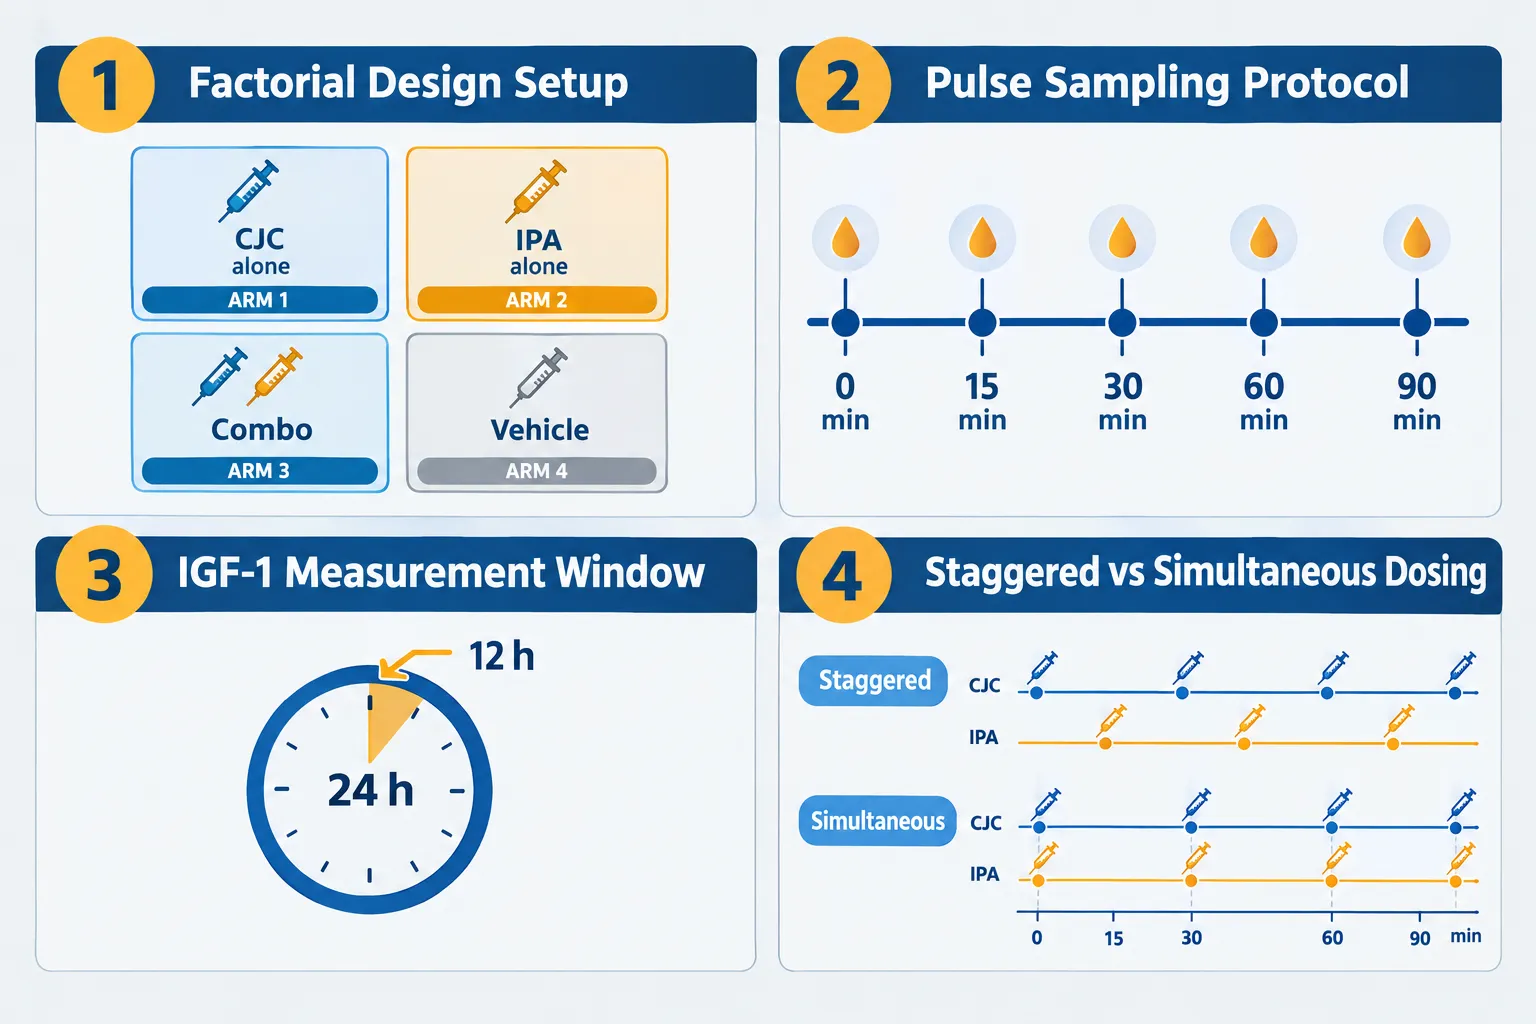
The minimum credible architecture for testing this combination is a 2×2 factorial design with four arms:

Arm CJC-1295 no-DAC Ipamorelin
1 Active Placebo
2 Placebo Active
3 Active Active
4 Placebo Placebo

This structure separates three distinct effects: the CJC-1295 main effect, the ipamorelin main effect, and the interaction term. If the combination arm (Arm 3) produces a GH pulse significantly larger than the sum of Arms 1 and 2 above the vehicle baseline (Arm 4), that constitutes evidence of true synergy. If it simply equals the sum, the effect is additive. If it falls short, there is antagonism or receptor saturation.

Pulse Sampling Protocol

Frequent blood sampling is non-negotiable. A practical schedule draws samples at 0, 15, 30, 45, 60, 90, and 120 minutes post-injection. This captures peak GH amplitude, time-to-peak, and pulse duration, three variables that can each shift independently depending on which agent is used.

IGF-1 timing adds a second layer. Because IGF-1 responds to cumulative GH exposure over 12-24 hours rather than to individual pulses, it should be measured at a fixed interval (typically 12 hours post-injection) across all arms. Comparing IGF-1 across arms that differ only in injection timing, without standardizing this window, is one of the most common sources of artifact in clinic-based data.

Vehicle Controls and Blinding

Vehicle controls (the diluent used for reconstitution, without active peptide) must match the injection volume and subcutaneous route of the active arms. For those reviewing reconstitution protocols for blend formulations, the vehicle composition matters: bacteriostatic water alone versus a buffered saline vehicle can affect subcutaneous absorption rate and therefore pulse timing.


Timing Artifacts and How to Control Them
Timing Artifacts and How to Control Them

Timing is the single largest source of non-pharmacodynamic artifact in GH-pulse studies with this combination. Three variables dominate:

1. Meal timing and insulin. Elevated insulin suppresses GH secretion. Guides updated through late 2026 consistently recommend injecting at least 2 hours after the last meal, particularly after carbohydrate intake. Pre-sleep fasted dosing is the standard recommendation because it aligns with the endogenous nocturnal GH surge and removes meal variability from the equation.

2. Circadian phase-locking. Dosing CJC-1295 no-DAC with ipamorelin in the early evening (roughly 18:00-20:00) can generate a GH spike near 01:00 that mirrors the body's natural GHRH-driven nocturnal surge. When all subjects receive the blend at the same circadian phase, observed differences in pulse amplitude between arms are more likely attributable to receptor co-activation than to random variation in sleep onset or meal timing.

3. Staggered versus simultaneous injection. Because GHRH receptor signaling and GHSR signaling have different kinetic profiles, injecting CJC-1295 no-DAC first and ipamorelin 15-30 minutes later can alter peak height and pulse width compared to a simultaneous injection. Analyzing these patterns within the same subject, a crossover element embedded in the factorial design, is one of the few practical methods currently available to distinguish true additive GH-pulse effects from artifacts of an arbitrary "both-at-once" schedule.

"Synergy claims for this blend rely on modeled receptor interactions and clinic experience rather than direct pulse-profiling RCTs, a distinction that matters enormously for interpreting amplitude data."

Practical dosing ranges reported in protocol literature run from 100 to 300 mcg of each peptide per injection, with titration every 1-2 weeks starting near 100 mcg. Cycles of 8-12 weeks followed by approximately 4 weeks off help preserve receptor sensitivity, a relevant consideration because receptor desensitization between cycles can alter baseline GH and create pseudo-synergy in later measurements. Researchers interested in ipamorelin sourcing can review available ipamorelin products and IPA 10mg formulations for reference-grade material.

For broader context on how ipamorelin compares to other growth hormone secretagogues, the Tesamorelin vs Ipamorelin comparison and Tesamorelin benefits overview provide useful mechanistic background. Those evaluating multi-peptide stacks can also reference Tesamorelin CJC-1295 blend dosage guidance for formulation-specific considerations.

Regulatory Context in 2026

Neither CJC-1295 nor ipamorelin is FDA-approved. Both peptides have been nominated and subsequently withdrawn from the 503A compounding list, meaning the combination is not permitted as a standard compounded product in the U.S. as of 2026. An FDA advisory committee specifically voted against allowing either peptide in routine compounding. This regulatory status reinforces that any GH-pulse data with the blend come from research or off-label clinic use, not from approved therapeutic programs, which further underscores the need for rigorous experimental controls when interpreting those data.


Conclusion

The central challenge with CJC-1295 with ipamorelin, how to separate additive GH-pulse effects from blend and timing artifacts, is fundamentally a study-design problem, not just a dosing question. The actionable steps are clear:

  • Use CJC-1295 no-DAC, not the DAC form, to preserve discrete pulsatile kinetics and prevent sustained baseline elevation from inflating apparent synergy.
  • Implement a 2×2 factorial design with vehicle controls so that main effects and the interaction term can be estimated independently.
  • Standardize timing by phase-locking injections to a consistent circadian window and enforcing a minimum 2-hour post-meal fast before every injection.
  • Sample frequently (at least seven time points over 120 minutes) and measure IGF-1 at a fixed 12-hour interval across all arms.
  • Test staggered versus simultaneous dosing within subjects to characterize how GHRH and GHSR kinetics interact across different injection intervals.

Until a registered trial applies this framework, the 3- to 5-fold pulse amplitude figures circulating in clinic literature should be treated as directional signals rather than confirmed pharmacodynamic facts. The combination may well be synergistic, but proving it requires separating the biology from the schedule.

Tags: cjc-1295 with ipamorelin, gh pulse artifacts, gh pulse research, ghrh receptor agonist, growth hormone secretagogues, ipamorelin dosing, mod grf 1-29, peptide study design
https://www.puretestedpeptides.com/wp-content/uploads/2026/10/cjc-1295-with-ipamorelin-how-to-separate-additive-gh-pulse-effects-from-blend-an.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-05 13:04:402026-10-05 13:04:40CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifacts
You might also like
Amlodipine in Peptide Research: Separating Calcium-Channel Effects From Blood-Pressure and Vascular Readouts Amlodipine in Peptide Research: Separating Calcium-Channel Effects From Blood-Pressure and Vascular Readouts
Polypeptide Peptides in Cardiometabolic Models: How Tesofensine, GLP-3 Retatrutide, and GLP-2-T Differ From Classic Small-Molecule Drugs Polypeptide Peptides in Cardiometabolic Models: How Tesofensine, GLP-3 Retatrutide, and GLP-2-T Differ From Classic Small-Molecule Drugs
CJC-1295 With DAC in 2026 Research: Why Long-Acting GHRH Analogs Remain a Core Search Topic CJC-1295 With DAC in 2026 Research: Why Long-Acting GHRH Analogs Remain a Core Search Topic
ACE Inhibitors and Research Peptides: Designing Blood-Pressure Controls Around Lisinopril and Growth-Hormone Secretagogues ACE Inhibitors and Research Peptides: Designing Blood-Pressure Controls Around Lisinopril and Growth-Hormone Secretagogues
Tesamorelin, Ipamorelin, and CJC-1295 With DAC: How Different GHRH Mimetic Profiles Shape Growth Hormone Study Outcomes Tesamorelin, Ipamorelin, and CJC-1295 With DAC: How Different GHRH Mimetic Profiles Shape Growth Hormone Study Outcomes
Tesofensine and Metabolic Research: How a Noradrenergic Appetite Modulator Compares With GLP‑3 Peptides in Study Design Tesofensine and Metabolic Research: How a Noradrenergic Appetite Modulator Compares With GLP‑3 Peptides in Study Design
Lisinopril, ACE Pathways, and Growth Hormone Secretagogues: Designing Safe Peptide Research With Cardiovascular Readouts Lisinopril, ACE Pathways, and Growth Hormone Secretagogues: Designing Safe Peptide Research With Cardiovascular Readouts
Peptide Drug Interactions: How Research Peptides Interact With Common Medications Peptide Drug Interactions: How Research Peptides Interact With Common Medications
0 replies

Leave a Reply

Want to join the discussion?
Feel free to contribute!

Leave a Reply Cancel reply

Your email address will not be published. Required fields are marked *

×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Link to: GLP-3 Retatrutide vs GLP-2-T: Choosing Metabolic, Intestinal, and Organoid Readouts for Comparative Research Link to: GLP-3 Retatrutide vs GLP-2-T: Choosing Metabolic, Intestinal, and Organoid Readouts for Comparative Research GLP-3 Retatrutide vs GLP-2-T: Choosing Metabolic, Intestinal, and Organoid Readouts...GLP-3 Retatrutide vs GLP-2-T: Choosing Metabolic, Intestinal, and Organoid Readouts for Comparative Research Link to: Semax Nasal Spray Reviews for Research Use: How to Evaluate Concentration, Excipients, and Batch Documentation Link to: Semax Nasal Spray Reviews for Research Use: How to Evaluate Concentration, Excipients, and Batch Documentation Semax Nasal Spray Reviews for Research Use: How to Evaluate Concentration, Excipients, and Batch DocumentationSemax Nasal Spray Reviews for Research Use: How to Evaluate Concentration, Excipients,...
Scroll to top Scroll to top Scroll to top