Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: peptide study design

Lisinopril, Losartan, and Amlodipine: Selecting Cardiovascular Controls for Peptide Studies

Lisinopril, Losartan, and Amlodipine: Selecting Cardiovascular Controls for Peptide Studies

November 4, 2026/0 Comments/in Uncategorized/by

Fewer than 30% of published peptide cardiovascular trials explicitly justify their choice of active comparator drug, a gap that quietly undermines the validity of blood-pressure and vascular outcome data. When a study tests an investigational peptide alongside a poorly matched pharmacological control, it becomes nearly impossible to know whether observed effects are driven by the peptide, the control drug, or their interaction. A disciplined framework built around lisinopril, losartan, and amlodipine: selecting cardiovascular controls for peptide studies solves this problem by anchoring control selection to mechanism, tolerability, and guideline alignment.

Key Takeaways

  • Lisinopril (ACE inhibitor), losartan (ARB), and amlodipine (CCB) operate through distinct vascular pathways, making control selection a mechanistic decision, not a default one.
  • Combining lisinopril and losartan as dual RAS blockade is explicitly discouraged by current regulatory guidance due to increased adverse events without added benefit.
  • Amlodipine with losartan is a well-evidenced combination control that outperforms losartan monotherapy for blood-pressure reduction in trial settings.
  • Peptide interventions are adjuncts to, not replacements for, guideline-directed antihypertensive therapy; stable background regimens are required before randomization.
  • Class-specific side-effect profiles, particularly ACE inhibitor cough versus ARB tolerability, directly affect participant retention and data integrity.

Understanding the Three Drug Classes and Their Vascular Pathways

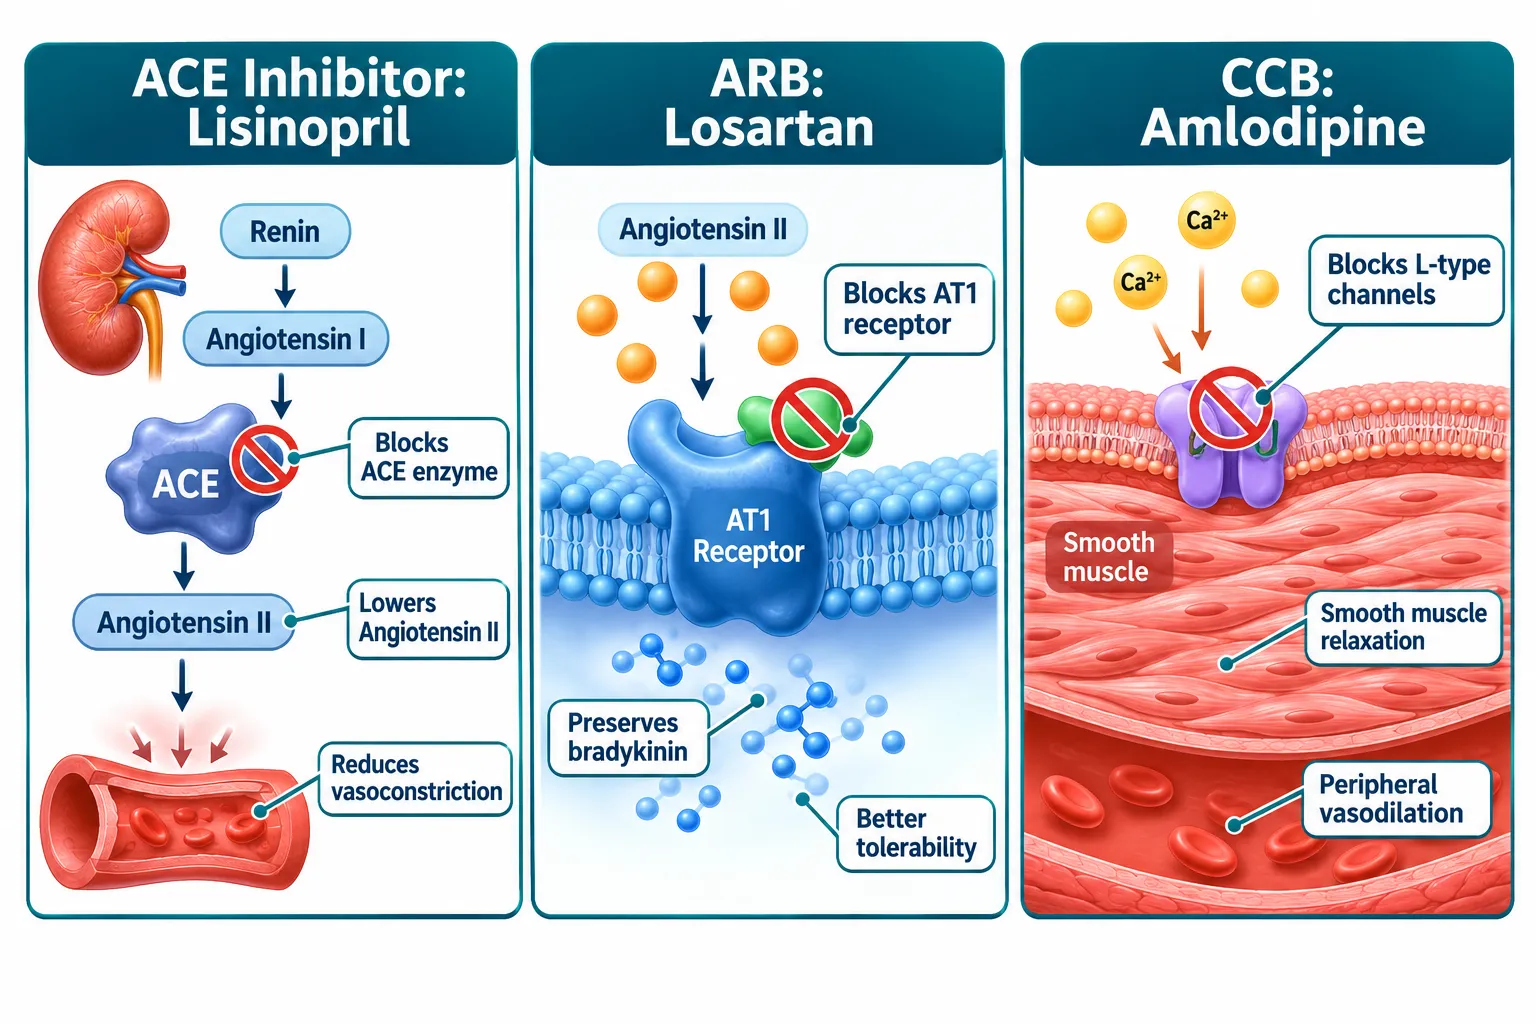
Before applying lisinopril, losartan, and amlodipine: selecting cardiovascular controls for peptide studies to a protocol, researchers must understand exactly where each agent intervenes in cardiovascular physiology.
Understanding the Three Drug Classes and Their Vascular Pathways

Lisinopril is an ACE inhibitor. It blocks the angiotensin-converting enzyme, preventing the conversion of angiotensin I to angiotensin II. The result is lower vasoconstriction, reduced aldosterone release, and a secondary rise in bradykinin, the last point being the primary cause of the dry cough reported in 10-15% of patients.

Losartan is an angiotensin II receptor blocker (ARB). Rather than blocking angiotensin II production, it blocks the AT1 receptor that angiotensin II binds to. Bradykinin is not affected, so cough rates are substantially lower. This tolerability advantage makes losartan the preferred RAS-targeting control when study dropout rates are a concern, as consistently noted in nephrology education materials.

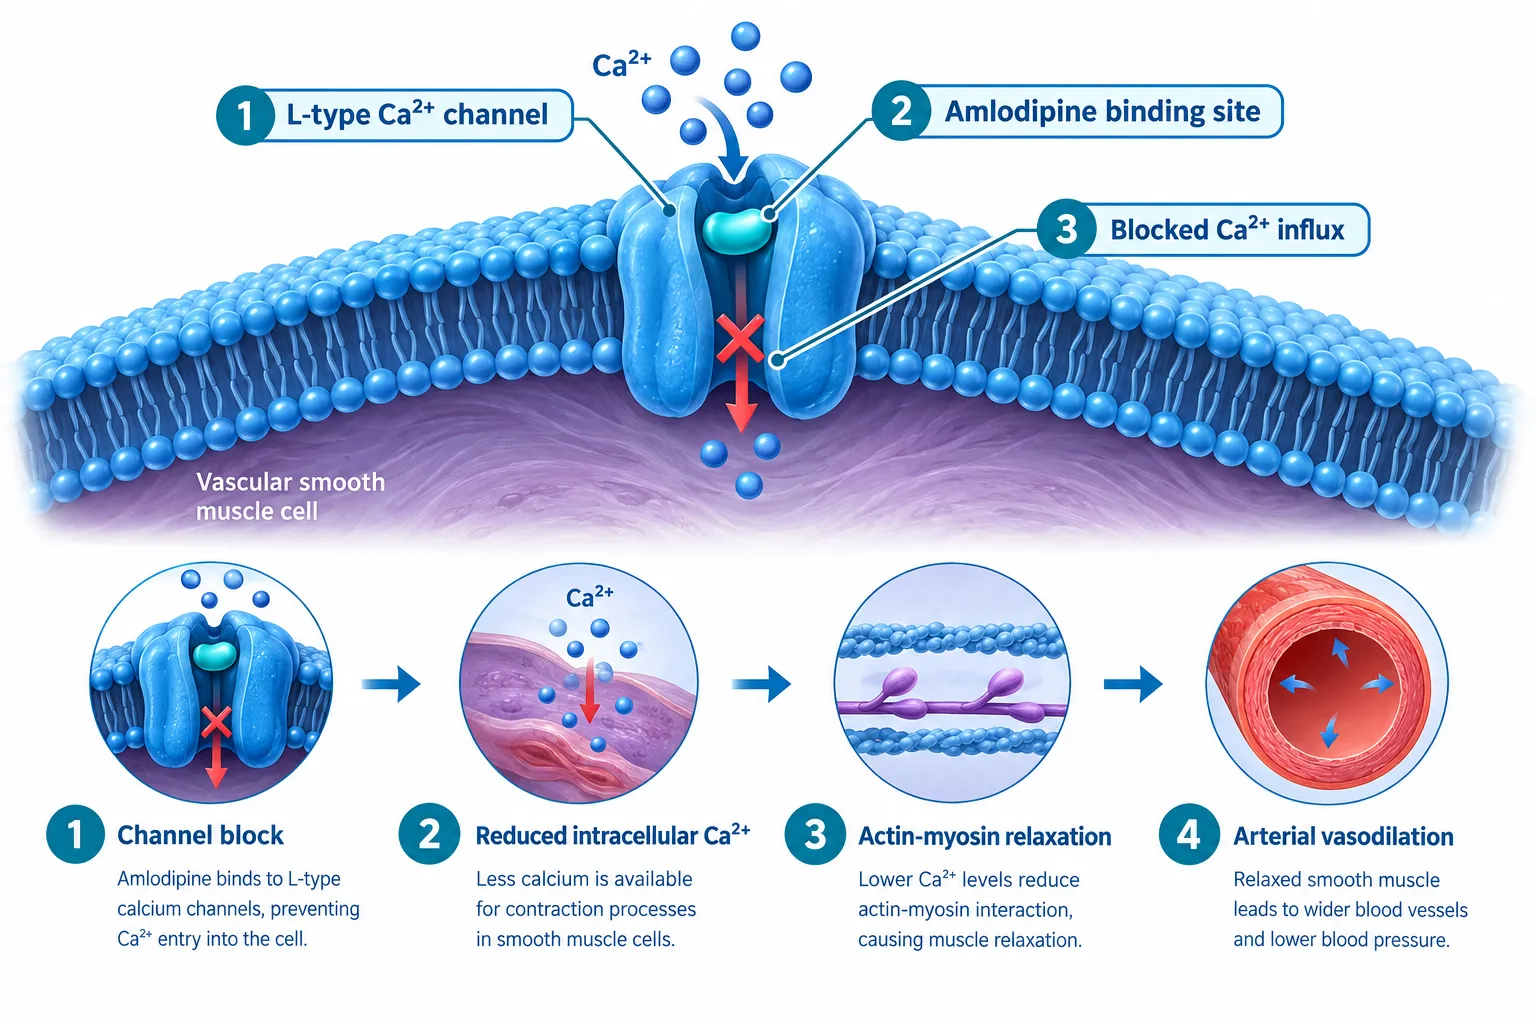
Amlodipine operates through an entirely different mechanism. As a dihydropyridine calcium-channel blocker (CCB), it inhibits L-type calcium channels in vascular smooth muscle, causing peripheral vasodilation without any direct effect on the renin-angiotensin system (RAS).

Drug Class Primary Target Key Side Effect
Lisinopril ACEi ACE enzyme Dry cough, hyperkalemia
Losartan ARB AT1 receptor Minimal; rare angioedema
Amlodipine CCB L-type Ca2+ channels Peripheral edema

This mechanistic separation is not merely academic. Any investigational peptide that modulates the RAS, such as peptides with angiotensin-like or natriuretic properties, will produce confounded results if placed alongside a lisinopril or losartan control without deliberate matching.


Applying the Framework: Lisinopril, Losartan, and Amlodipine in Peptide Study Design

Researchers studying cardioprotective peptides, including mitochondria-targeted compounds explored in SS-31 peptide research considerations and broader cardiovascular peptide lines, benefit from a structured decision process when choosing controls.

Applying the Framework: Lisinopril, Losartan, and Amlodipine in Peptide Study Design

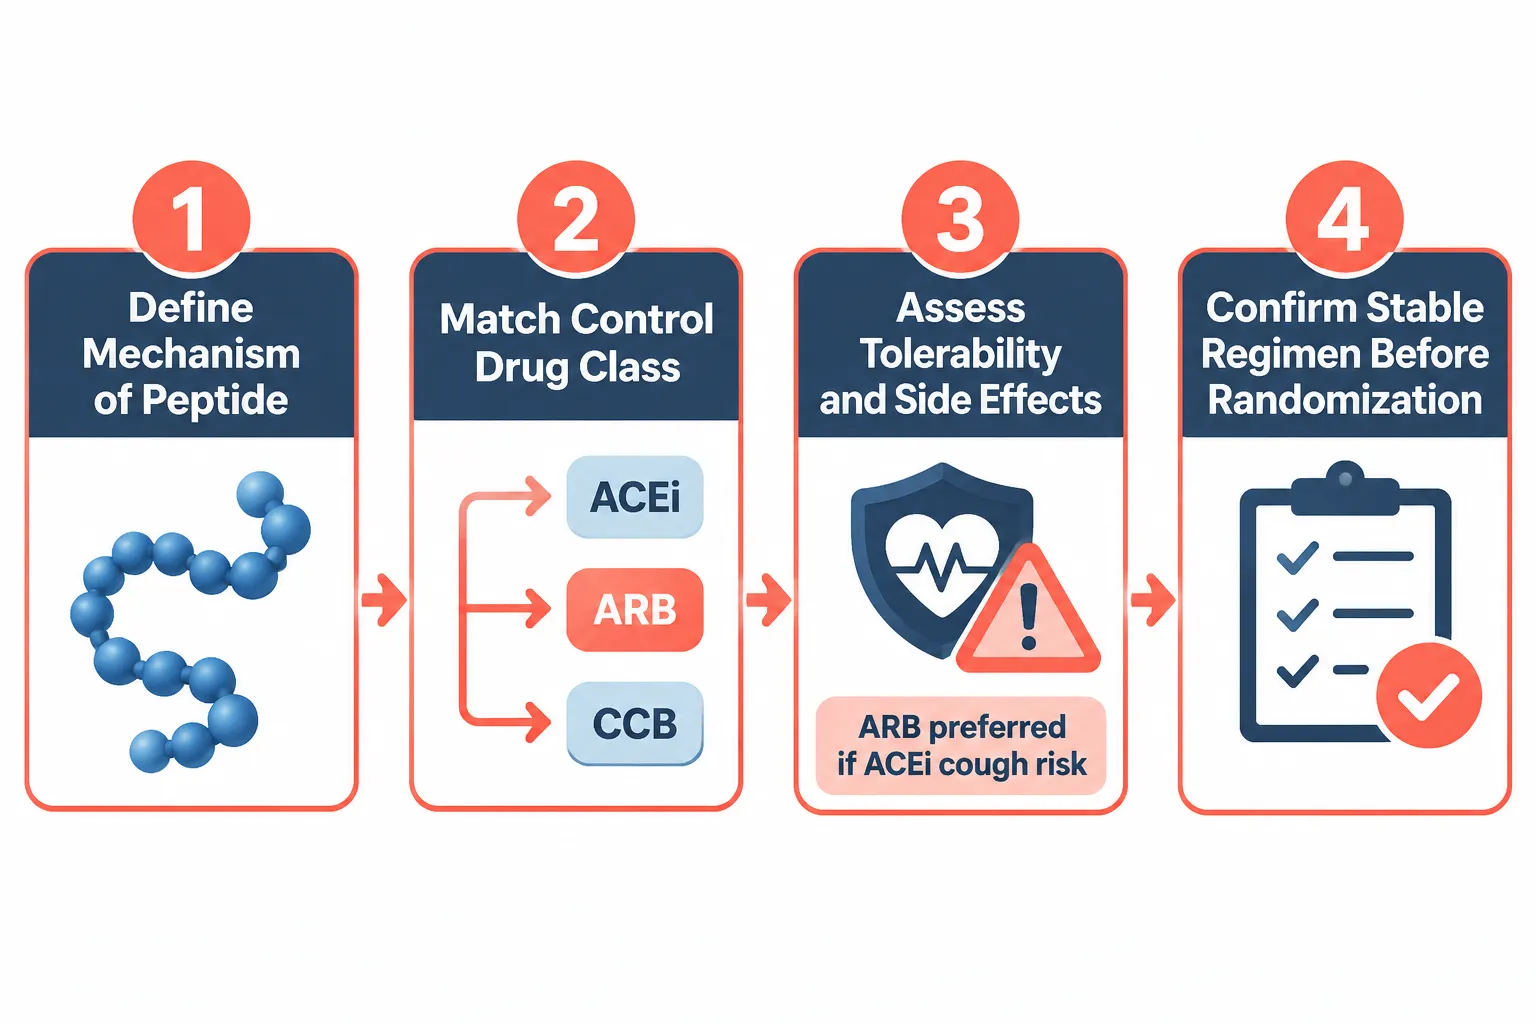
Step 1: Define the peptide's proposed mechanism. Does the investigational peptide affect vascular tone via the RAS, via calcium flux, via oxidative stress pathways, or via endothelial nitric oxide? This question determines which drug class can serve as a credible active comparator and which would introduce mechanistic overlap.

Step 2: Match the control class to the mechanism. A peptide hypothesized to act on oxidative vascular injury, as studied in contexts involving SS-31 peptide benefits, may legitimately pair with amlodipine as a control, since both reduce cardiovascular stress through non-RAS pathways. By contrast, pairing such a peptide with lisinopril would merge RAS-dependent and RAS-independent signals in ways difficult to disentangle.

Step 3: Avoid dual RAS blockade. Current regulatory labeling updated in 2026 reiterates that combining lisinopril and losartan increases adverse renal and cardiovascular events without added antihypertensive benefit. No peptide study design should incorporate this combination as a comparator arm.

Step 4: Consider the amlodipine-losartan combination for blood-pressure benchmarking. Evidence consistently shows the amlodipine/losartan combination produces superior blood-pressure reduction compared with losartan alone. When a study needs a robust active comparator to benchmark a peptide's antihypertensive effect, this combination offers a high-bar reference without RAS-overlap concerns.

"Peptide interventions are adjuncts to guideline-directed therapy, not replacements. Stable antihypertensive regimens must be established before randomization."

Studies examining compounds like those found in GLP peptide research or metabolic peptides with cardiovascular secondary endpoints similarly depend on stable background regimens to isolate peptide-specific signals. The GLP-3 peptide signaling pathway literature, for instance, illustrates how vascular endpoints can be confounded when background pharmacotherapy is inconsistent.


Practical Control Selection and Tolerability Considerations

Tolerability is not a secondary concern, it is a data integrity concern. A participant who stops taking lisinopril due to cough mid-trial introduces an uncontrolled variable. Nephrology education and pharmacology CE materials from 2025 uniformly recommend ARBs over ACE inhibitors when study population characteristics raise dropout risk.
Practical Control Selection and Tolerability Considerations

The ALLHAT trial framework, referenced in pharmacy committee analyses through 2025, demonstrated comparable primary coronary outcomes across chlorthalidone, amlodipine, and lisinopril arms. This equivalency supports using either amlodipine or lisinopril as a "reference" comparator without systematically disadvantaging one drug class over another from an efficacy standpoint.

For researchers sourcing lab-tested peptides intended for cardiovascular investigations, the principle is clear: the purity and characterization of the investigational compound must be matched by the rigor of control selection. Poorly chosen controls waste well-characterized peptides.

Preferred combinations by study type:

  • RAS-targeting peptide studies: Use amlodipine as solo control to avoid mechanistic overlap.
  • Vasodilatory/endothelial peptide studies: Use losartan or amlodipine; avoid lisinopril if cough is a concern.
  • Blood-pressure benchmarking studies: Use amlodipine + losartan combination as the high-bar active comparator.
  • Cardioprotective/oxidative peptide studies: Amlodipine preferred; losartan acceptable as secondary control.

For researchers exploring related cardiovascular peptides such as those comparing LL-37 versus SS-31 peptide benefits, the same framework applies: separate the drug-class pharmacology from the peptide-driven effects before drawing mechanistic conclusions.


Conclusion

Selecting cardiovascular controls is one of the most consequential methodological choices in peptide research. The discipline of lisinopril, losartan, and amlodipine: selecting cardiovascular controls for peptide studies provides a mechanistic, evidence-grounded framework that separates RAS-dependent, angiotensin-receptor, and calcium-channel effects from peptide-driven vascular changes.

Actionable next steps for researchers:

  1. Map the investigational peptide's mechanism before selecting any control drug.
  2. Default to losartan or amlodipine when participant tolerability could compromise retention.
  3. Never combine lisinopril and losartan in the same control arm.
  4. Use the amlodipine-losartan combination as the benchmark when rigorous blood-pressure comparisons are needed.
  5. Confirm stable antihypertensive background therapy for all participants at least four weeks before randomization.

A well-matched control does not compete with the peptide, it clarifies it.

https://www.puretestedpeptides.com/wp-content/uploads/2026/11/lisinopril-losartan-and-amlodipine-selecting-cardiovascular-controls-for-peptide.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-11-04 14:05:032026-11-04 14:05:03Lisinopril, Losartan, and Amlodipine: Selecting Cardiovascular Controls for Peptide Studies
Electrolytes in Peptide Studies: Designing Sodium, Potassium, and Fluid-Balance Controls for GLP and Growth-Hormone Models

Electrolytes in Peptide Studies: Designing Sodium, Potassium, and Fluid-Balance Controls for GLP and Growth-Hormone Models

October 9, 2026/0 Comments/in Uncategorized/by

Fluid retention of just 1-2 liters can add more than 1 kg to a subject's body weight overnight, a shift large enough to mask or mimic a meaningful treatment effect in a peptide study. When the compounds under investigation are GLP-1 agonists or growth-hormone analogues, both of which directly alter renal sodium handling and total body water, uncontrolled electrolyte variables are not a minor nuisance. They are a primary source of confounding. Designing rigorous electrolyte controls is therefore central to valid endpoint measurement in these models, and the field of electrolytes in peptide studies: designing sodium, potassium, and fluid-balance controls for GLP and growth-hormone models has matured considerably in 2026.

Key Takeaways

  • GLP-1 agonists suppress thirst and reduce fluid intake, creating real dehydration and hyponatremia risk that must be controlled prospectively.
  • Growth hormone is anti-natriuretic: it promotes sodium and water retention through direct renal mechanisms, altering body weight and blood pressure readouts.
  • Serum sodium and potassium can appear stable even when total-body balances are significantly altered, making urine and fluid-intake logs essential.
  • Sampling standardization, fixed fasting state, fixed hydration window, morning collection, is non-negotiable for reproducible electrolyte endpoints.
  • Exclusion criteria for baseline electrolyte abnormalities protect data integrity and reduce the risk of confounded renal and cardiovascular readouts.

Why Electrolyte Physiology Matters in GLP and GH Peptide Research

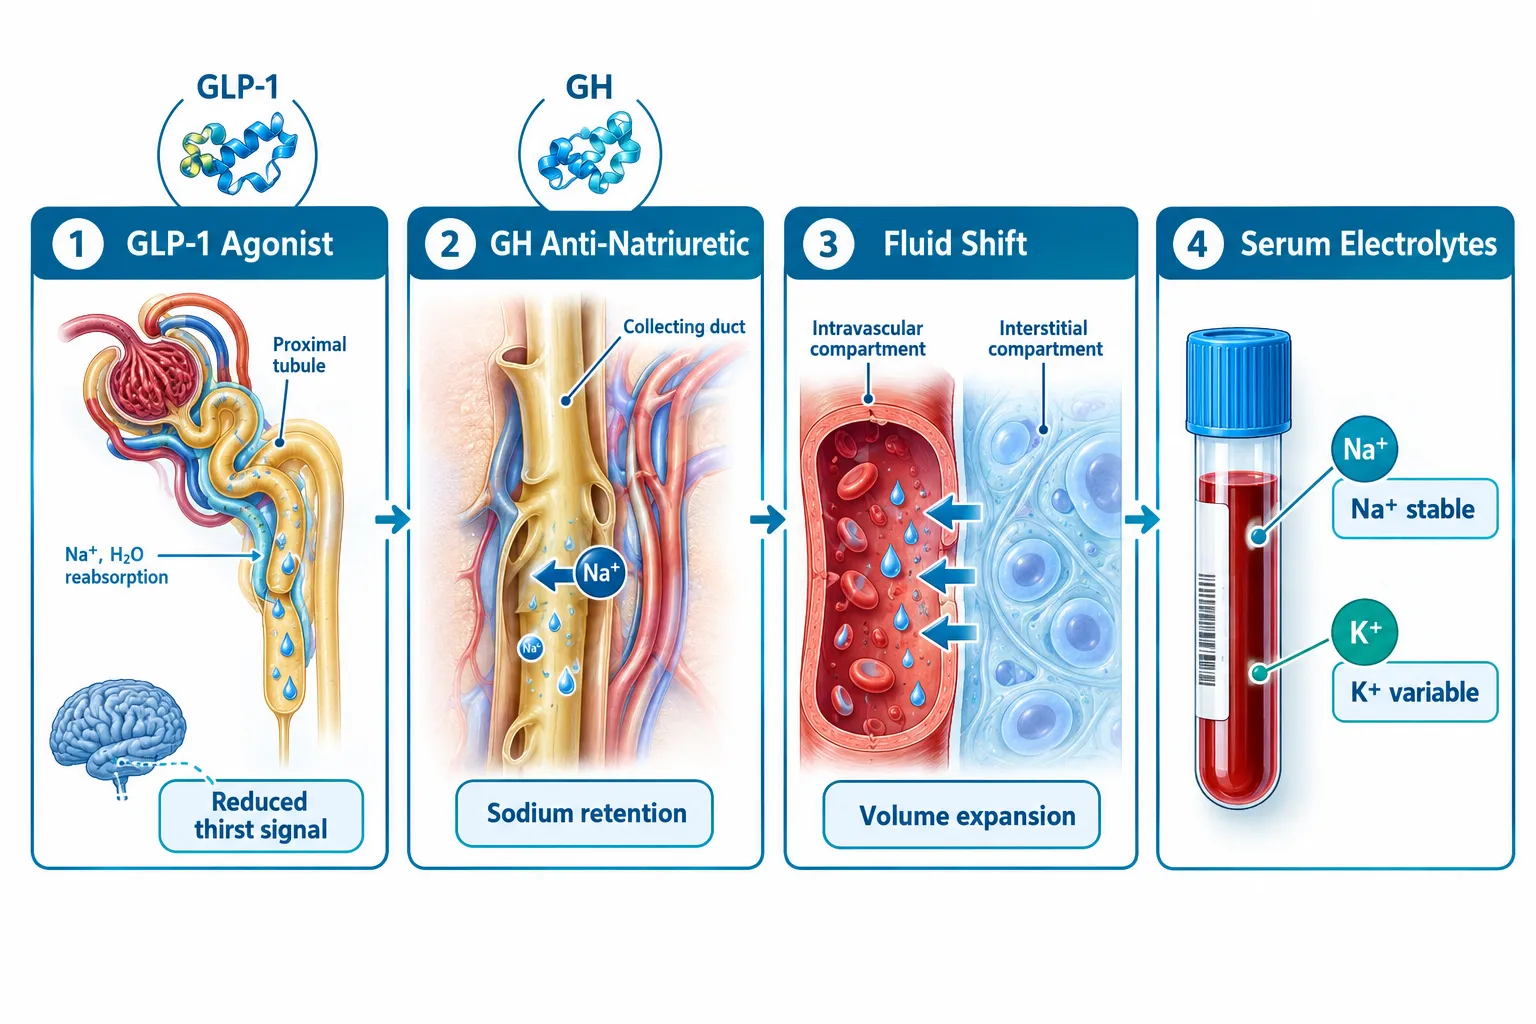
Both GLP-1 receptor agonists and growth-hormone-related peptides interact with the kidney in ways that directly alter sodium excretion, potassium distribution, and extracellular fluid volume. Understanding these mechanisms is the first step toward building controls that actually work.

Why Electrolyte Physiology Matters in GLP and GH Peptide Research

GLP-1 agonists reduce appetite and caloric intake, but they also suppress thirst, a phenomenon now described as hypodipsia. Subjects in GLP-1 models frequently show reduced spontaneous fluid consumption, raising the risk of mild-to-moderate dehydration. This matters because dehydration concentrates serum sodium, elevates hematocrit, and reduces glomerular filtration rate (GFR). If these changes are not tracked, a researcher may misattribute them to the peptide's metabolic action rather than to simple fluid deficit. Researchers working with GLP-3 R Peptide GA3 or GLP-3 R Peptide GA4 should treat hydration monitoring as a core protocol element, not an afterthought.

Growth hormone operates through a different but equally important mechanism. GH is anti-natriuretic: it increases renal tubular sodium reabsorption, expands extracellular fluid volume, and raises total body water. In GH-deficient subjects receiving replacement therapy, serum sodium and potassium often remain within normal reference ranges even as total-body sodium and water increase measurably. This dissociation between serum values and actual balance is a critical insight. Relying solely on a serum electrolyte panel will miss the fluid-volume shifts that inflate body weight and raise blood pressure, two of the most common endpoints in GH analogue studies.


Designing GLP-1 Models: Sodium, Potassium, and Hydration Controls

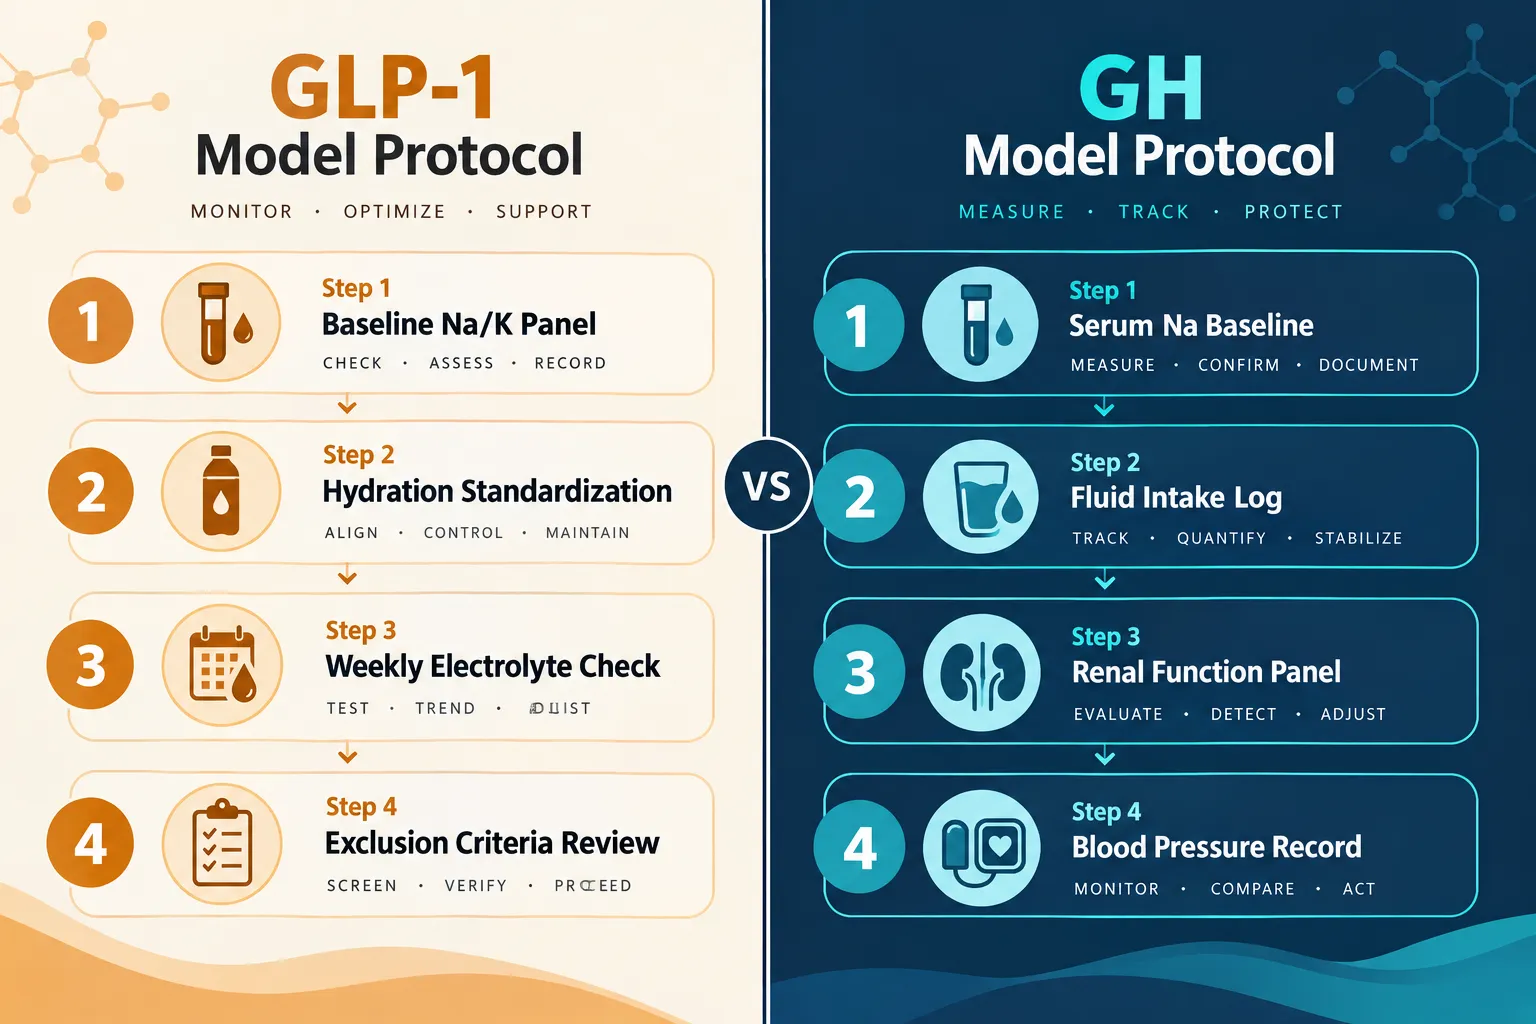
A well-designed GLP-1 model requires prospective hydration targets and a formalized electrolyte monitoring schedule built into the protocol from day one.

Hydration targets should be set at a defined minimum daily fluid intake, typically 30-35 mL per kilogram of body weight, and documented through daily fluid-intake logs. Subjects who fall below threshold on two or more consecutive days should trigger a protocol review. Urine-specific gravity measured at each morning sample collection provides a rapid, low-cost hydration proxy.

Sodium monitoring in GLP-1 models should include:

  • Baseline serum sodium before compound administration
  • Weekly serum sodium during active dosing
  • Urine sodium-to-creatinine ratio at baseline and at key timepoints
  • Dietary sodium standardization (target: 2,000-2,300 mg/day) or at minimum, a validated dietary recall at each visit

Potassium deserves separate attention. Rapid weight loss, which GLP-1 agonists can accelerate, increases the risk of hypokalemia through reduced dietary intake and increased renal losses. A serum potassium below 3.5 mEq/L should be a pre-specified action threshold: halt dose escalation, initiate dietary supplementation, and re-test within 72 hours.

"The most common electrolyte error in GLP-1 peptide models is treating hydration as a background variable rather than a controlled input."

For researchers sourcing compounds like Cagrilintide peptide or Retatrutide peptide, agents that combine GLP-1 and other receptor activity, the electrolyte burden is compounded, and monitoring frequency should increase accordingly.


Designing GH Models: Fluid Volume, Renal Endpoints, and Sampling Standards

Growth-hormone models present a different design challenge. Because GH expands extracellular fluid without reliably shifting serum sodium outside normal ranges, standard chemistry panels alone are insufficient as electrolyte controls.

Designing GH Models: Fluid Volume, Renal Endpoints, and Sampling Standards

Recommended control variables for GH models include:

Variable Measurement Method Frequency
Serum sodium Venous blood draw Baseline, weeks 2, 4, 8
Total body water Bioimpedance or deuterium dilution Baseline and end-of-study
Blood pressure Standardized seated measurement Every visit
Urine sodium Spot urine Na/Cr ratio Baseline and monthly
Body weight Morning, post-void, fasted Every visit

The key principle here is morning, post-void, fasted body weight. Because GH-driven fluid retention fluctuates with activity, posture, and dietary sodium intake, weight measurements taken at inconsistent times introduce noise that can easily exceed the magnitude of the treatment effect being studied.

Researchers using GH analogue peptides or PEG-MGF peptide should also pre-specify renal endpoints. GH's anti-natriuretic effect is mediated partly through IGF-1-dependent increases in GFR and partly through direct tubular action. Both pathways can alter creatinine clearance, so eGFR should be tracked alongside electrolytes rather than treated as a separate safety variable.


Sampling Standardization and Exclusion Criteria

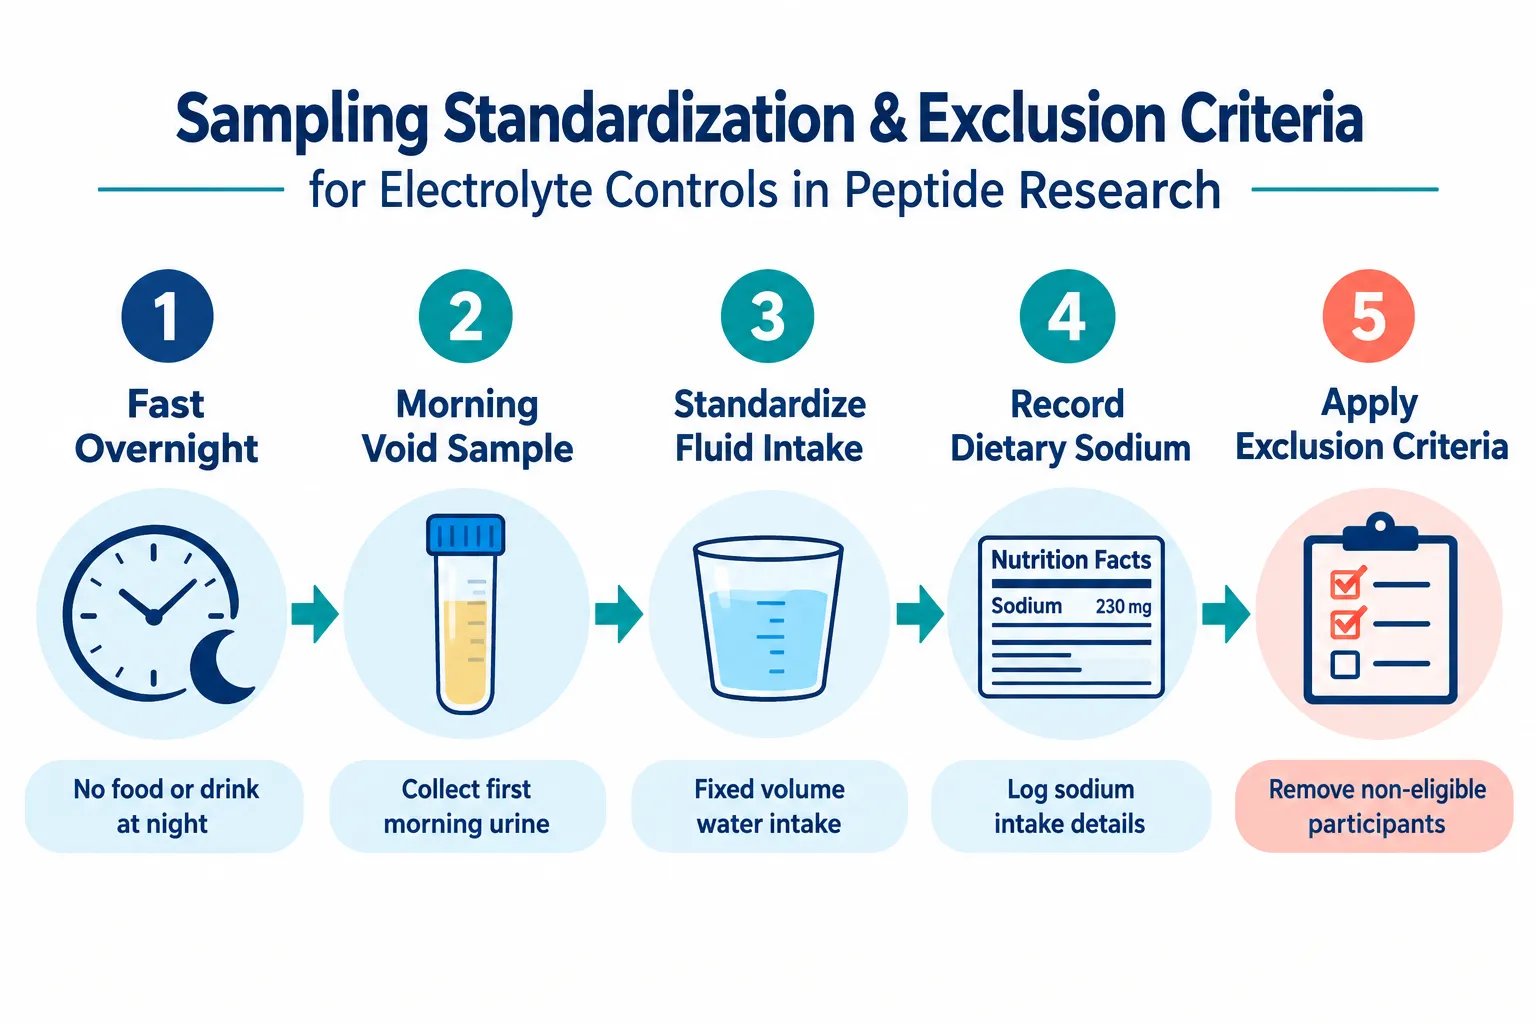
Reproducible electrolyte data requires standardized collection conditions. Variability in fasting duration, hydration state, or posture at blood draw can shift serum sodium by 2-4 mEq/L and potassium by 0.3-0.5 mEq/L, differences large enough to cross clinical action thresholds.

Sampling Standardization and Exclusion Criteria

Standardization checklist for every electrolyte sample:

  1. Overnight fast of at least 8 hours
  2. Morning collection (6:00-9:00 AM window)
  3. Seated rest for 10 minutes before venipuncture
  4. No strenuous exercise in the prior 24 hours
  5. Standardized fluid intake the evening before (250-500 mL water, no electrolyte beverages)
  6. Document any diuretic, laxative, or supplement use within 48 hours

Exclusion criteria should be applied at screening to protect endpoint validity. Subjects with baseline serum sodium below 135 or above 145 mEq/L, potassium below 3.5 or above 5.0 mEq/L, or eGFR below 60 mL/min/1.73 m² should be excluded from electrolyte-sensitive peptide models. These thresholds reduce the risk that a pre-existing imbalance will be misread as a compound effect.

For models involving MOTS-C peptide, which influences mitochondrial and metabolic function, or BPC-157 / TB-500 peptide in wound healing models, electrolyte controls serve a secondary but still meaningful role in ensuring that inflammatory and fluid shifts do not confound tissue-repair endpoints.


Conclusion

The integrity of GLP and growth-hormone peptide research depends on treating electrolytes and fluid balance as primary controlled variables, not secondary safety checks. Actionable next steps for researchers in 2026 include:

  • Build electrolyte monitoring into the protocol at study design, not as an amendment after data collection begins.
  • Set pre-specified action thresholds for sodium, potassium, and hydration markers with clear decision rules for dose adjustment or subject review.
  • Standardize all sampling conditions, fasting state, time of day, posture, and prior-evening fluid intake, and document deviations as protocol deviations, not minor notes.
  • Apply strict exclusion criteria at screening to remove subjects with baseline electrolyte abnormalities that would confound interpretation.
  • Separate serum values from total-body balance in GH models by adding bioimpedance or urine electrolyte measures alongside standard chemistry panels.

Electrolytes in peptide studies, specifically designing sodium, potassium, and fluid-balance controls for GLP and growth-hormone models, is no longer an optional refinement. It is a prerequisite for data that can withstand scrutiny and support meaningful conclusions.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/electrolytes-in-peptide-studies-designing-sodium-potassium-and-fluid-balance-con.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-09 13:05:152026-10-09 13:05:15Electrolytes in Peptide Studies: Designing Sodium, Potassium, and Fluid-Balance Controls for GLP and Growth-Hormone Models
Amlodipine in Peptide Research: Separating Calcium-Channel Effects From Blood-Pressure and Vascular Readouts

Amlodipine in Peptide Research: Separating Calcium-Channel Effects From Blood-Pressure and Vascular Readouts

October 6, 2026/0 Comments/in Uncategorized/by

Fewer than one in five preclinical peptide studies that co-administer a calcium-channel blocker formally account for the drug's independent vascular effects, a methodological gap that can quietly invalidate entire datasets. When amlodipine in peptide research enters the experimental picture, the challenge is not simply adjusting for lower blood pressure. It is disentangling at least three overlapping biological layers: direct L-type calcium-channel blockade, blood-pressure-dependent vascular changes, and blood-pressure-independent vascular remodeling. Getting these layers wrong means attributing amlodipine's known anti-proliferative and anti-atherosclerotic actions to the peptide under study, or, just as problematically, masking a real peptide signal behind the drug's dominant pharmacology.

Key Takeaways

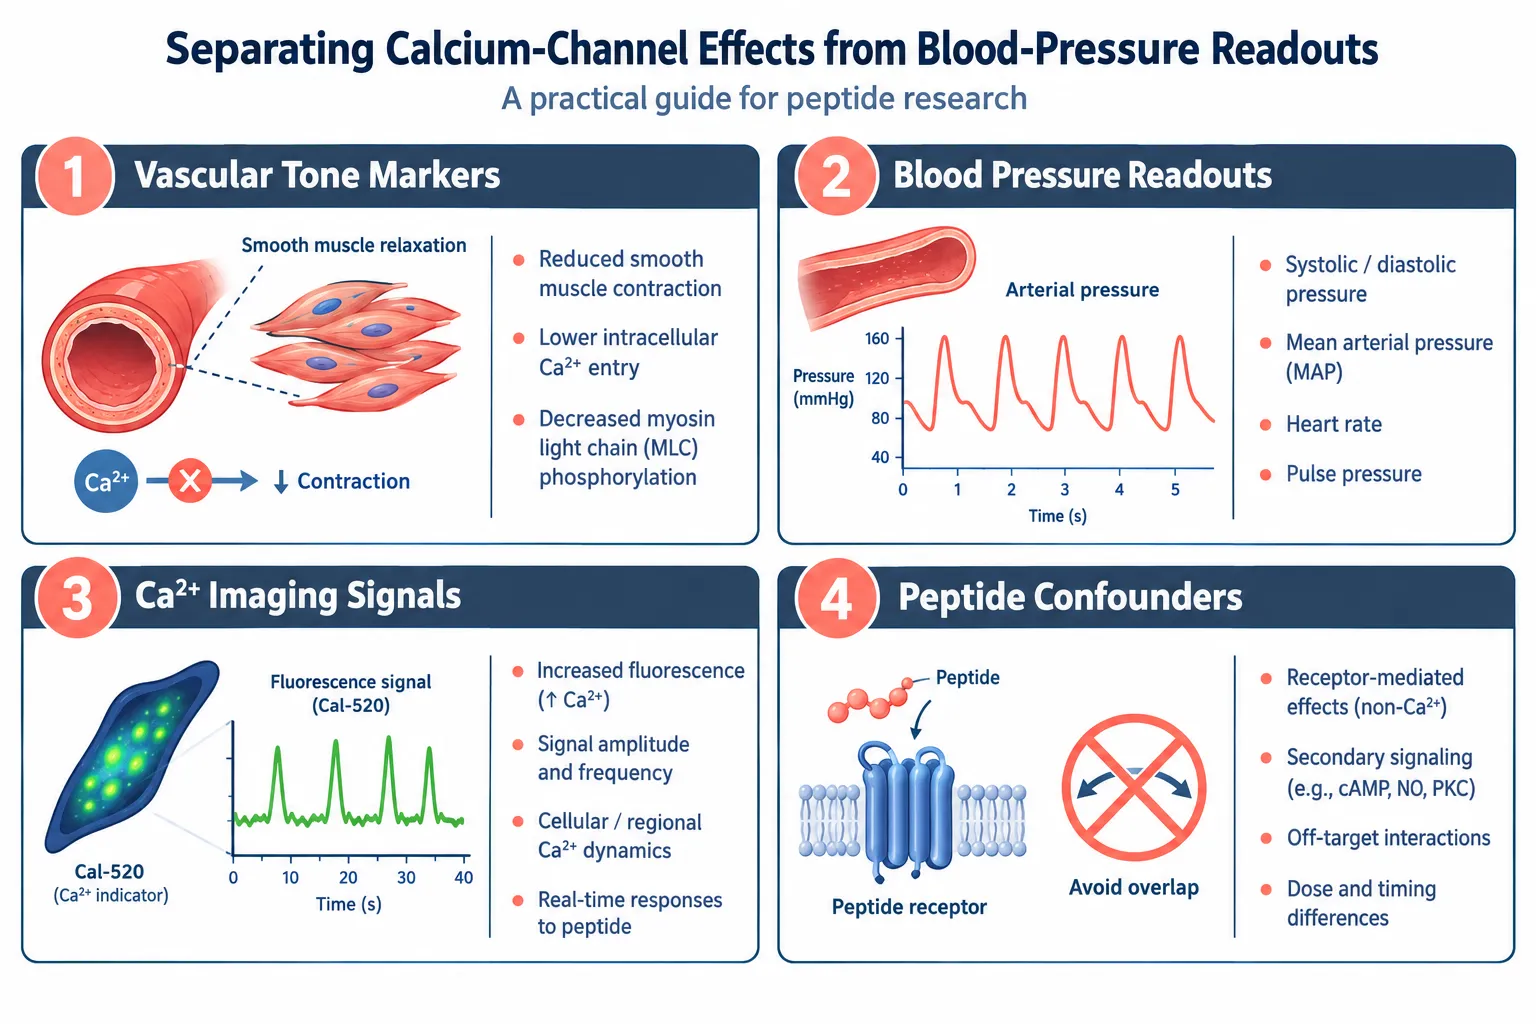
  • Amlodipine blocks L-type calcium channels in vascular smooth muscle, reducing intracellular Ca²⁺ and causing arterial relaxation independently of any peptide co-administered in a study.
  • The drug produces vascular benefits, including inhibited smooth-muscle cell proliferation and slowed atherosclerosis, that are separate from its blood-pressure-lowering effect.
  • At clinically relevant concentrations, amlodipine does not activate CRAC channels and does not interfere with fluorescence-based Ca²⁺ imaging dyes such as Cal-520, Fluo-4, or Fura-Red.
  • Researchers should pre-specify which readouts are calcium-channel-mediated, blood-pressure-dependent, or peptide-specific before data collection begins.
  • Orthogonal biomarkers, endothelial nitric oxide, arterial compliance, and vascular remodeling indices, can help isolate a peptide's contribution from amlodipine's background pharmacology.

How Amlodipine Works: The Calcium-Channel Mechanism Researchers Must Account For

How Amlodipine Works: The Calcium-Channel Mechanism Researchers Must Account For

Amlodipine is a dihydropyridine calcium antagonist. Its primary action is inhibiting the transmembrane influx of calcium ions through L-type voltage-gated channels, predominantly in vascular smooth muscle cells. The result is reduced intracellular Ca²⁺, diminished actin-myosin interaction, smooth-muscle relaxation, and arterial vasodilation. Its effect on vascular smooth muscle is substantially greater than its effect on cardiac muscle, a selectivity profile that matters when interpreting any cardiovascular or vascular readout in a peptide experiment.

This mechanism is not trivial background noise. It is a dominant pharmacological signal. Any peptide co-administered with amlodipine that also influences vascular tone, intracellular calcium, or smooth-muscle behavior will generate data that reflects both agents simultaneously unless the study design explicitly separates them.

What this means practically:

  • Vascular tone measurements (e.g., wire myography, pressure myography) will reflect amlodipine's baseline relaxation effect.
  • Intracellular Ca²⁺ flux assays will show a suppressed resting Ca²⁺ level before the peptide is even introduced.
  • Any peptide with vasodilatory properties may appear to have a blunted or absent effect simply because the vascular bed is already partially relaxed.

Researchers working with mitochondria-targeted peptides such as those explored in SS-31 10mg research peptide considerations should note that oxidative-stress and membrane-potential readouts can also be indirectly affected when intracellular calcium homeostasis is altered by a co-administered channel blocker.


Separating Calcium-Channel Effects From Blood-Pressure and Vascular Readouts: A Practical Framework

Separating Calcium-Channel Effects From Blood-Pressure and Vascular Readouts: A Practical Framework

The central challenge in amlodipine in peptide research, separating calcium-channel effects from blood-pressure and vascular readouts, requires a tiered classification of every endpoint before data collection begins.

Tier 1: Blood-Pressure-Dependent Readouts

These are endpoints that change because amlodipine lowers arterial pressure. They include:

  • Brachial or carotid blood pressure values
  • Cardiac afterload indices
  • Glomerular filtration rate changes driven by reduced perfusion pressure

Practical step: Include a vehicle-treated, amlodipine-only control group at the same dose. Any change in these readouts in that group represents the amlodipine baseline, not a peptide effect.

Tier 2: Blood-Pressure-Independent Vascular Effects

Contemporary cardiovascular literature consistently identifies a second category of amlodipine actions that persist even when blood pressure is matched to comparator agents. These include:

Effect Mechanism Research Implication
Smooth-muscle cell anti-proliferation Direct Ca²⁺ signaling suppression May confound peptide anti-proliferative claims
Anti-atherosclerotic remodeling Reduced oxidative stress in vessel wall Arterial stiffness data needs amlodipine-only control
Improved arterial compliance Structural vascular changes Central pulse-wave velocity requires correction

For peptide studies examining vascular remodeling, such as those involving VIP peptide mechanisms or vasoactive signaling pathways, these BP-independent effects represent the most likely source of confounding.

Tier 3: Calcium-Channel-Specific Molecular Readouts

This tier covers direct molecular measurements of L-type channel activity and downstream Ca²⁺ signaling. A key methodological advantage here: at therapeutic plasma concentrations of approximately 0.5 µM, amlodipine does not activate calcium-release-activated calcium (CRAC) channels. This means CRAC-mediated signaling events attributed to a peptide are not being driven by amlodipine itself.

Additionally, fluorescence-based Ca²⁺ imaging using dyes such as Cal-520, Fluo-4, and Fura-Red is not confounded by amlodipine fluorescence at these concentrations. This is a meaningful green light for researchers using live-cell calcium imaging alongside peptide stimulation assays.

"Knowing which calcium compartment amlodipine does and does not touch is the single most useful piece of information a peptide researcher can carry into experimental design."

Researchers examining peptide signaling pathways, including those studying GLP-3 peptide signaling pathway interactions, benefit from this CRAC-channel clarity because receptor-operated calcium entry can then be attributed with greater confidence to the peptide's receptor engagement rather than to the channel blocker.


Designing the Experiment: Isolating Peptide-Specific Signals

Designing the Experiment: Isolating Peptide-Specific Signals

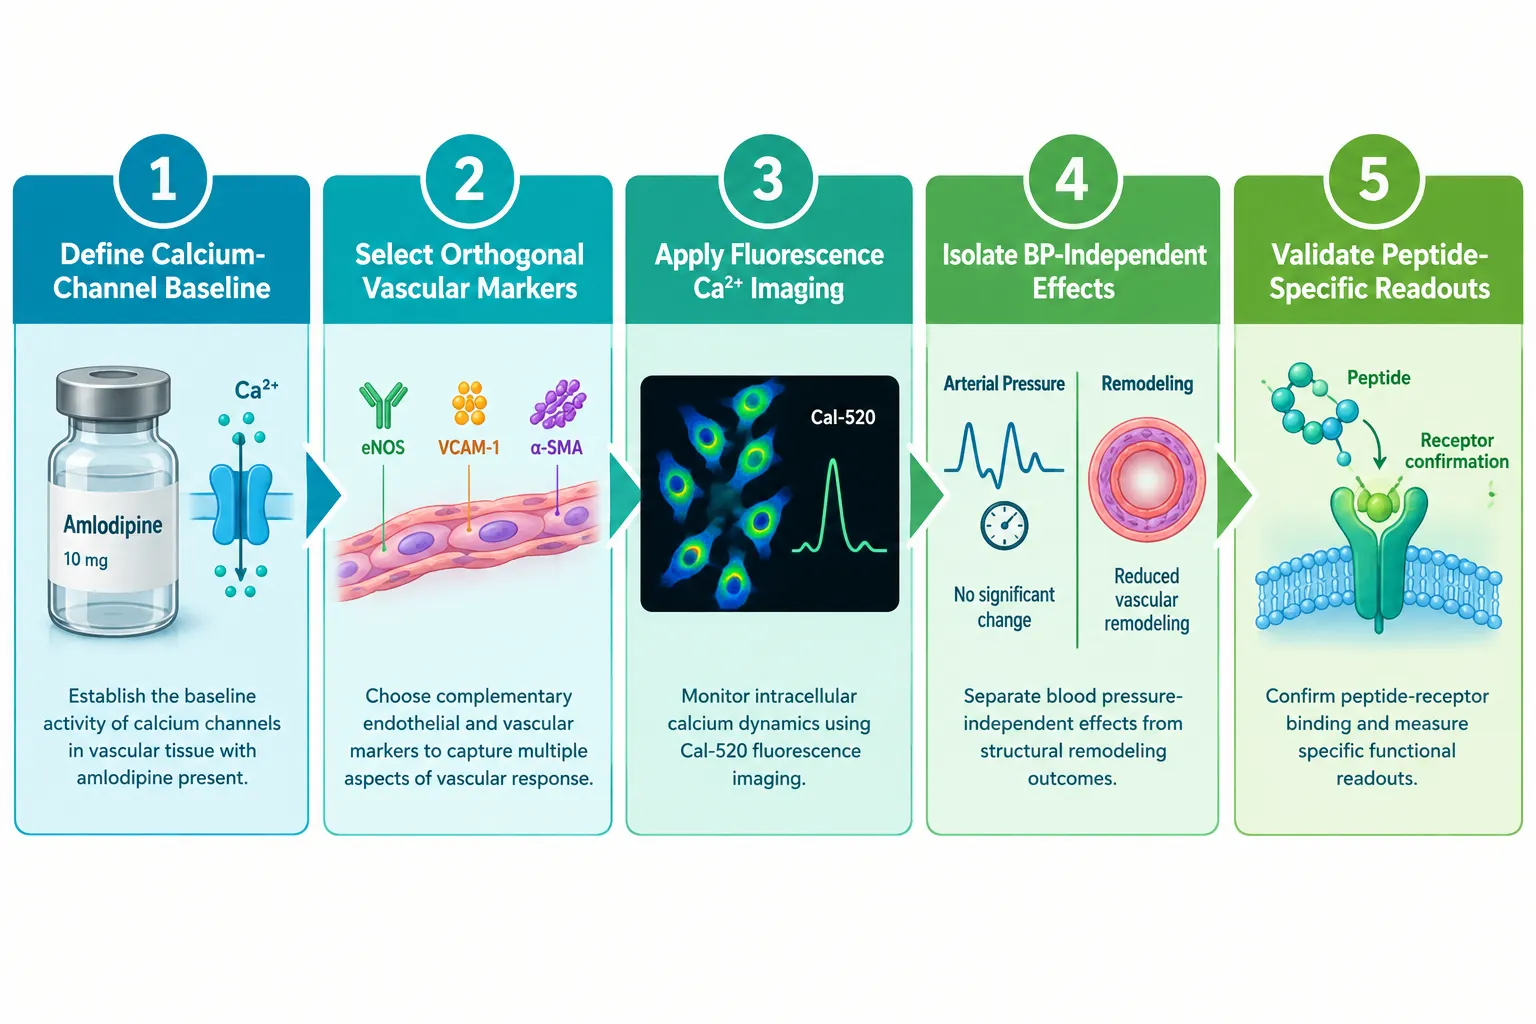
A rigorous experimental framework for amlodipine in peptide research, one that genuinely separates calcium-channel effects from blood-pressure and vascular readouts, involves five concrete design decisions.

Step 1, Define the calcium-channel baseline. Run amlodipine-only controls at the intended study concentration. Measure intracellular Ca²⁺, vascular tone, and any remodeling markers. This establishes the floor the peptide must be measured against.

Step 2, Select orthogonal vascular markers. Choose at least two endpoints that amlodipine does not directly regulate. Endothelial nitric oxide synthase (eNOS) activity, circulating endothelin-1 levels, and specific peptide receptor phosphorylation states are examples. These serve as peptide-specific signal channels.

Step 3, Apply fluorescence Ca²⁺ imaging with confidence. Given that amlodipine does not interfere with Cal-520, Fluo-4, or Fura-Red at relevant concentrations, live-cell imaging remains a valid tool. Pair it with a CRAC-channel inhibitor control to confirm that any observed Ca²⁺ flux is L-type-independent when the peptide is active.

Step 4, Separate central from peripheral blood pressure. Peripheral brachial pressure can be identical across treatment groups while central aortic pressure and pulse-wave velocity differ. Use central hemodynamic measurements to capture amlodipine's BP-independent arterial effects separately from peptide-driven changes.

Step 5, Validate with receptor-blocking controls. If the peptide of interest acts through a specific receptor, as is the case with many research peptides including those reviewed in LL-37 versus SS-31 benefits of each peptide comparisons, include a receptor-antagonist arm. Any vascular effect that disappears with receptor blockade but persists with amlodipine alone is attributable to the peptide.

Proper peptide dosing protocols also matter here: dose-response curves for the peptide should be generated in both the presence and absence of amlodipine to detect any shift in potency or efficacy caused by the background calcium-channel blockade.

For researchers sourcing compounds for controlled in vitro work, ensuring purity and verified composition is non-negotiable. Resources such as guidance on where to buy research-grade peptides evaluating purity underscore why compound quality directly affects the reliability of mechanistic conclusions.


Conclusion

Amlodipine is a well-characterized L-type calcium-channel blocker with a pharmacological footprint that extends well beyond simple blood-pressure reduction. In any peptide research context, failing to account for its anti-proliferative, anti-atherosclerotic, and Ca²⁺-suppressive actions risks misattributing drug effects to the peptide, or obscuring genuine peptide biology beneath a dominant pharmacological background.

Actionable next steps for researchers in 2026:

  1. Pre-classify every planned endpoint into one of the three tiers: blood-pressure-dependent, BP-independent vascular, or calcium-channel-specific molecular.
  2. Include an amlodipine-only control group at the study concentration in every experimental arm.
  3. Use fluorescence-based Ca²⁺ imaging with confidence at therapeutic concentrations, but pair it with CRAC-channel controls to confirm the signal source.
  4. Add orthogonal endothelial and receptor-specific biomarkers that amlodipine does not directly regulate.
  5. Run full dose-response curves for the peptide both with and without amlodipine present to detect potency shifts.

Rigorous separation of these layers does not complicate peptide research, it protects it. The result is data that can be defended, reproduced, and built upon.


https://www.puretestedpeptides.com/wp-content/uploads/2026/10/amlodipine-in-peptide-research-separating-calcium-channel-effects-from-blood-pre.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-06 13:05:532026-10-06 13:05:53Amlodipine in Peptide Research: Separating Calcium-Channel Effects From Blood-Pressure and Vascular Readouts
CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifacts

CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifacts

October 5, 2026/0 Comments/in Uncategorized/by

Clinic-based reports consistently describe 3- to 5-fold increases in GH pulse amplitude when CJC-1295 is paired with ipamorelin, yet as of 2026, not a single published randomized controlled trial has tested the combination in humans. That gap between widespread clinical use and rigorous experimental evidence is not a minor footnote. It means that nearly every claim about "synergistic" or "additive" GH pulses from this blend is built on data that cannot cleanly distinguish true pharmacodynamic interaction from artifacts of dosing schedule, peptide form, meal timing, and background GH status.

Understanding CJC-1295 with ipamorelin: how to separate additive GH-pulse effects from blend and timing artifacts requires a disciplined study-design framework, one that treats synergy as a hypothesis to test, not a starting assumption.

Key Takeaways

  • No RCT has directly tested the CJC-1295 plus ipamorelin combination; all GH-pulse data are clinic-based or extrapolated from single-agent studies.
  • Using CJC-1295 with DAC creates a sustained GH elevation lasting days, which can masquerade as pulse synergy and must be avoided in pulse-focused research.
  • A 2×2 factorial design with vehicle controls is the minimum study architecture needed to isolate true additive GH-pulse effects from timing and exposure artifacts.
  • Fasted pre-sleep dosing and consistent circadian phase-locking reduce meal- and sleep-related variability that inflates apparent pulse amplitude.
  • Staggered dosing intervals (CJC-1295 first, ipamorelin 15-30 minutes later) versus simultaneous injection offer a practical within-subject comparison of pulse shape and kinetics.

Why the Peptide Form Changes Everything

Why the Peptide Form Changes Everything

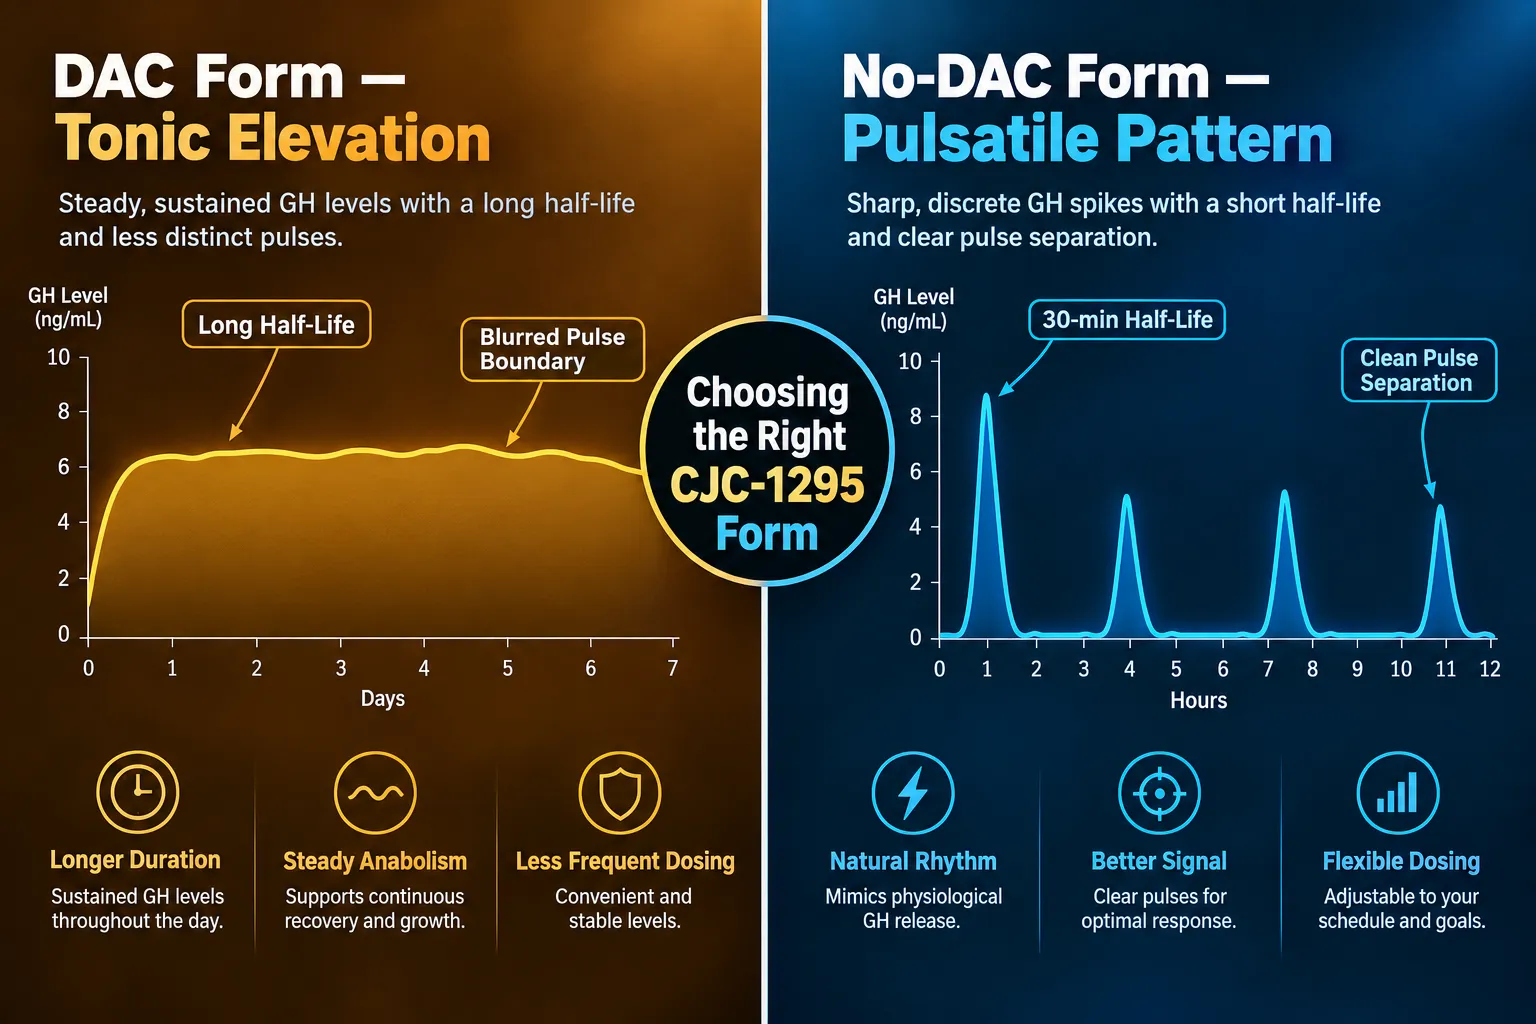
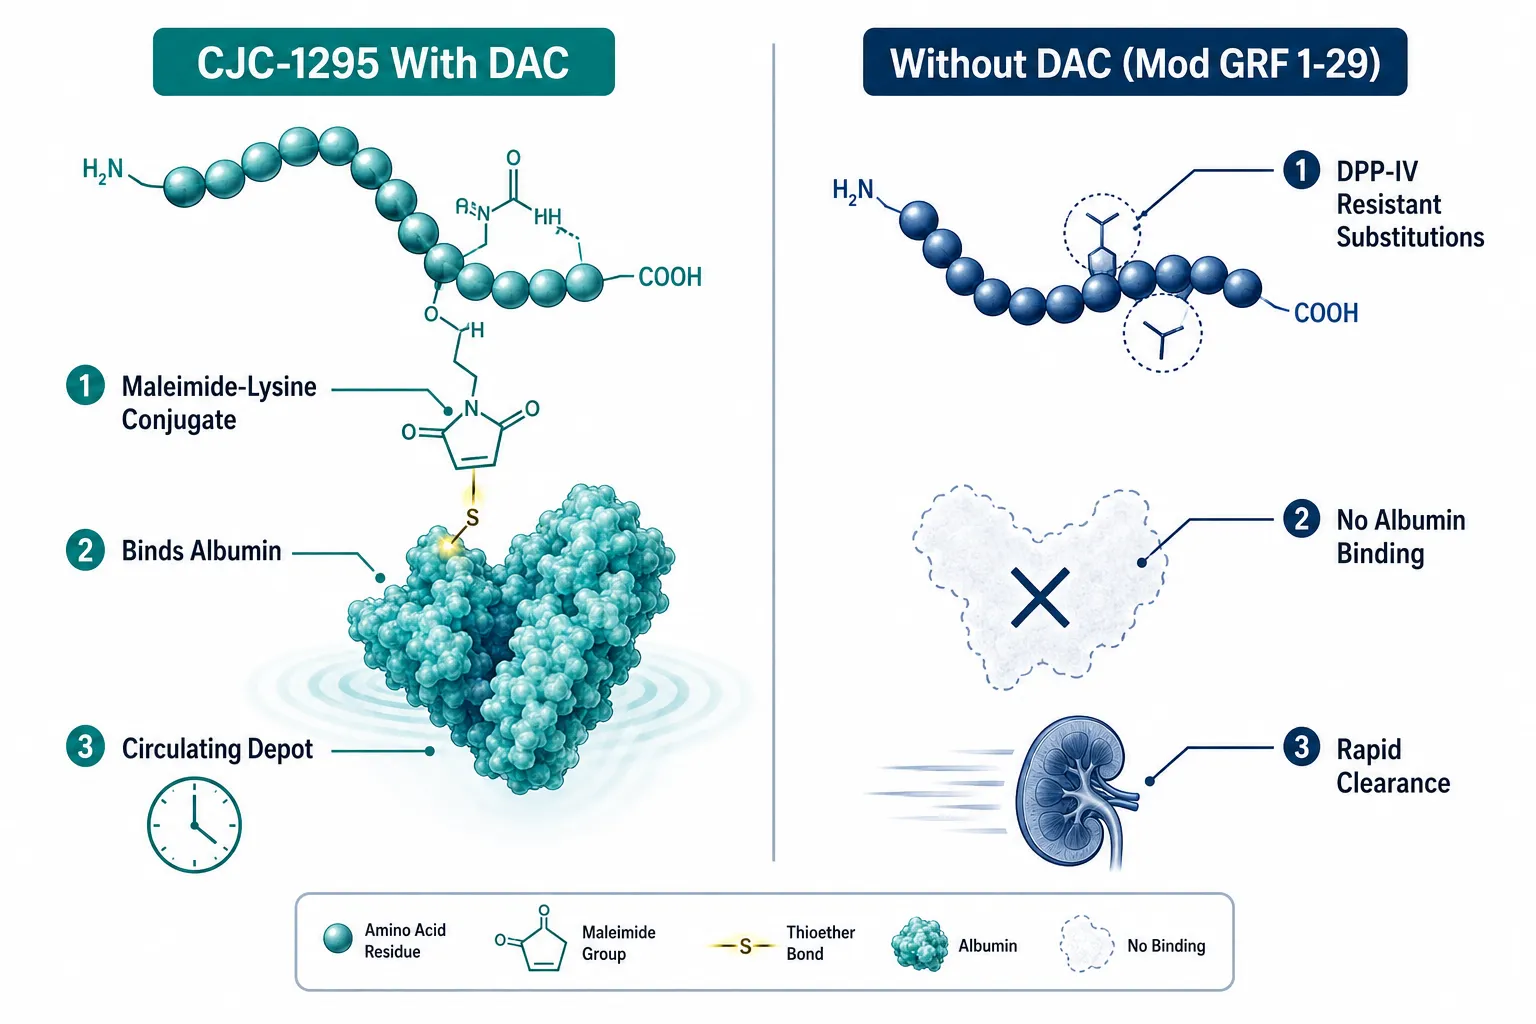
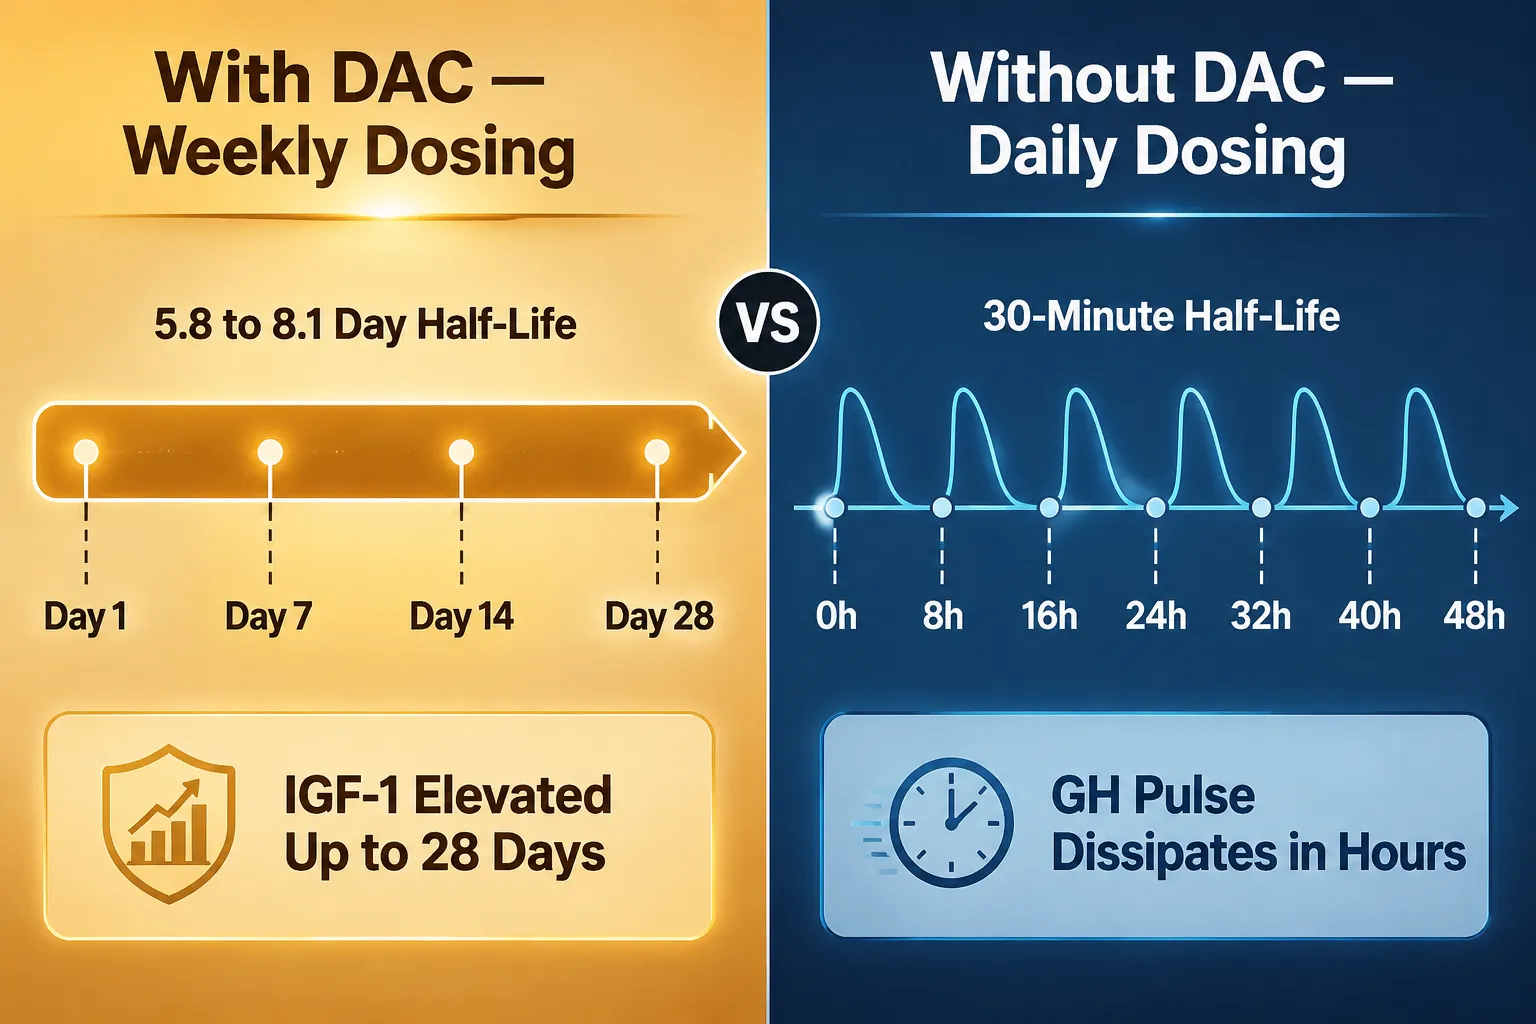
The first design decision, and the most consequential, is which form of CJC-1295 is used. The DAC (Drug Affinity Complex) version binds albumin after injection, extending its half-life to several days. Single subcutaneous doses have produced 2- to 10-fold increases in mean plasma GH lasting six or more days, with IGF-1 elevations persisting 9-11 days. That pharmacokinetic profile is incompatible with pulsatile GH research. When baseline GH is elevated for nearly two weeks, any ipamorelin-triggered spike departs from an already-raised platform, making the combined peak appear larger than it actually is relative to a true resting state.

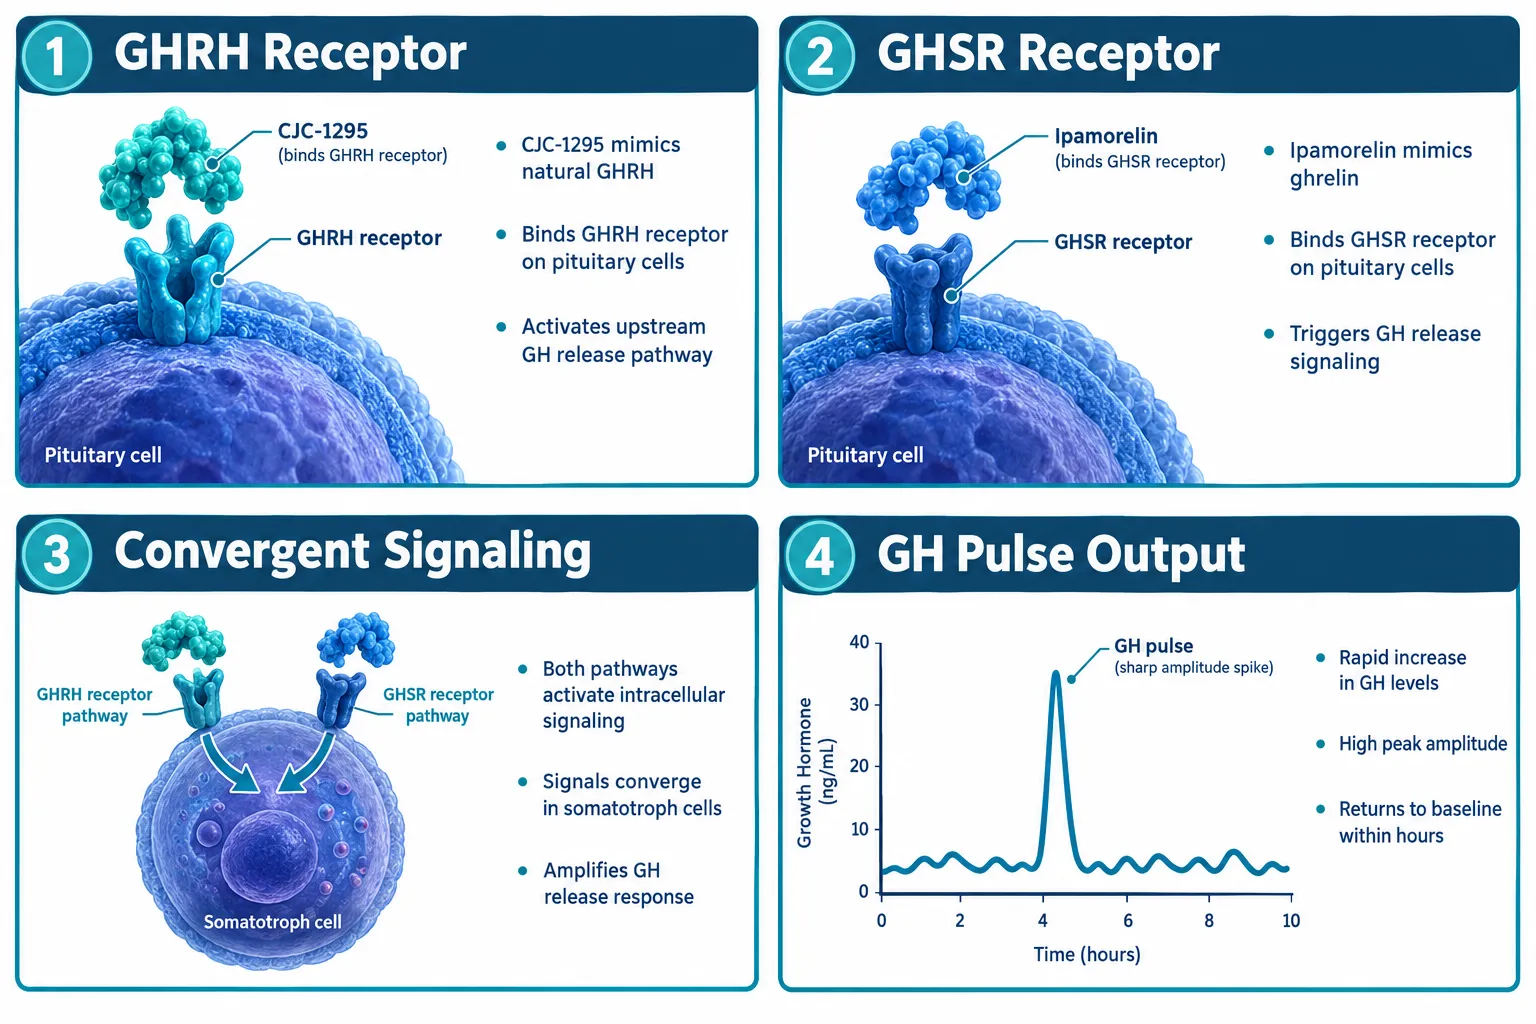
CJC-1295 no-DAC (mod-GRF 1-29) solves this problem. Its reported half-life is roughly 30 minutes. Ipamorelin's half-life is approximately 2 hours. Co-administering the two creates a short, overlapping signaling window that preserves a discrete pulsatile pattern. The GHRH receptor (targeted by CJC-1295) and the growth hormone secretagogue receptor (targeted by ipamorelin) are distinct but convergent pathways at the somatotroph cell. Activating both simultaneously amplifies GH release beyond what either agent achieves alone, but only the no-DAC form keeps that interaction measurable as a clean pulse rather than a tonic elevation.

Anyone exploring the Tesamorelin CJC-1295 Ipamorelin 12mg blend should understand this distinction before interpreting any GH data from a multi-peptide formulation.


A Factorial Study Design for CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifacts

A Factorial Study Design for CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifa

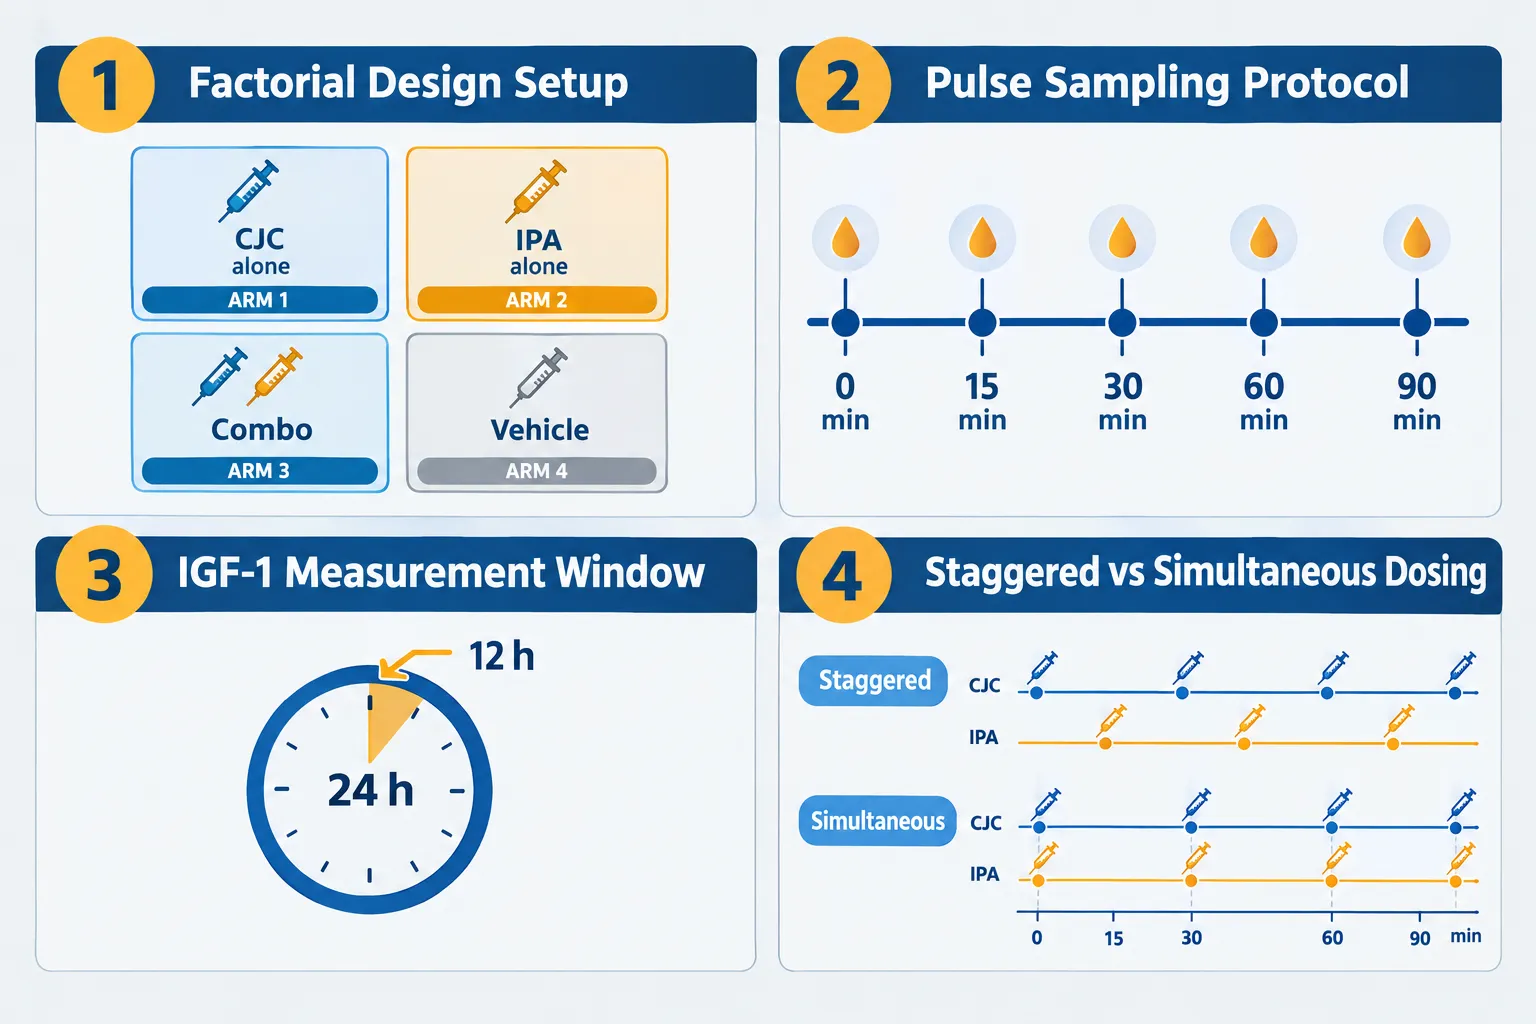
The minimum credible architecture for testing this combination is a 2×2 factorial design with four arms:

Arm CJC-1295 no-DAC Ipamorelin
1 Active Placebo
2 Placebo Active
3 Active Active
4 Placebo Placebo

This structure separates three distinct effects: the CJC-1295 main effect, the ipamorelin main effect, and the interaction term. If the combination arm (Arm 3) produces a GH pulse significantly larger than the sum of Arms 1 and 2 above the vehicle baseline (Arm 4), that constitutes evidence of true synergy. If it simply equals the sum, the effect is additive. If it falls short, there is antagonism or receptor saturation.

Pulse Sampling Protocol

Frequent blood sampling is non-negotiable. A practical schedule draws samples at 0, 15, 30, 45, 60, 90, and 120 minutes post-injection. This captures peak GH amplitude, time-to-peak, and pulse duration, three variables that can each shift independently depending on which agent is used.

IGF-1 timing adds a second layer. Because IGF-1 responds to cumulative GH exposure over 12-24 hours rather than to individual pulses, it should be measured at a fixed interval (typically 12 hours post-injection) across all arms. Comparing IGF-1 across arms that differ only in injection timing, without standardizing this window, is one of the most common sources of artifact in clinic-based data.

Vehicle Controls and Blinding

Vehicle controls (the diluent used for reconstitution, without active peptide) must match the injection volume and subcutaneous route of the active arms. For those reviewing reconstitution protocols for blend formulations, the vehicle composition matters: bacteriostatic water alone versus a buffered saline vehicle can affect subcutaneous absorption rate and therefore pulse timing.


Timing Artifacts and How to Control Them

Timing Artifacts and How to Control Them

Timing is the single largest source of non-pharmacodynamic artifact in GH-pulse studies with this combination. Three variables dominate:

1. Meal timing and insulin. Elevated insulin suppresses GH secretion. Guides updated through late 2026 consistently recommend injecting at least 2 hours after the last meal, particularly after carbohydrate intake. Pre-sleep fasted dosing is the standard recommendation because it aligns with the endogenous nocturnal GH surge and removes meal variability from the equation.

2. Circadian phase-locking. Dosing CJC-1295 no-DAC with ipamorelin in the early evening (roughly 18:00-20:00) can generate a GH spike near 01:00 that mirrors the body's natural GHRH-driven nocturnal surge. When all subjects receive the blend at the same circadian phase, observed differences in pulse amplitude between arms are more likely attributable to receptor co-activation than to random variation in sleep onset or meal timing.

3. Staggered versus simultaneous injection. Because GHRH receptor signaling and GHSR signaling have different kinetic profiles, injecting CJC-1295 no-DAC first and ipamorelin 15-30 minutes later can alter peak height and pulse width compared to a simultaneous injection. Analyzing these patterns within the same subject, a crossover element embedded in the factorial design, is one of the few practical methods currently available to distinguish true additive GH-pulse effects from artifacts of an arbitrary "both-at-once" schedule.

"Synergy claims for this blend rely on modeled receptor interactions and clinic experience rather than direct pulse-profiling RCTs, a distinction that matters enormously for interpreting amplitude data."

Practical dosing ranges reported in protocol literature run from 100 to 300 mcg of each peptide per injection, with titration every 1-2 weeks starting near 100 mcg. Cycles of 8-12 weeks followed by approximately 4 weeks off help preserve receptor sensitivity, a relevant consideration because receptor desensitization between cycles can alter baseline GH and create pseudo-synergy in later measurements. Researchers interested in ipamorelin sourcing can review available ipamorelin products and IPA 10mg formulations for reference-grade material.

For broader context on how ipamorelin compares to other growth hormone secretagogues, the Tesamorelin vs Ipamorelin comparison and Tesamorelin benefits overview provide useful mechanistic background. Those evaluating multi-peptide stacks can also reference Tesamorelin CJC-1295 blend dosage guidance for formulation-specific considerations.

Regulatory Context in 2026

Neither CJC-1295 nor ipamorelin is FDA-approved. Both peptides have been nominated and subsequently withdrawn from the 503A compounding list, meaning the combination is not permitted as a standard compounded product in the U.S. as of 2026. An FDA advisory committee specifically voted against allowing either peptide in routine compounding. This regulatory status reinforces that any GH-pulse data with the blend come from research or off-label clinic use, not from approved therapeutic programs, which further underscores the need for rigorous experimental controls when interpreting those data.


Conclusion

The central challenge with CJC-1295 with ipamorelin, how to separate additive GH-pulse effects from blend and timing artifacts, is fundamentally a study-design problem, not just a dosing question. The actionable steps are clear:

  • Use CJC-1295 no-DAC, not the DAC form, to preserve discrete pulsatile kinetics and prevent sustained baseline elevation from inflating apparent synergy.
  • Implement a 2×2 factorial design with vehicle controls so that main effects and the interaction term can be estimated independently.
  • Standardize timing by phase-locking injections to a consistent circadian window and enforcing a minimum 2-hour post-meal fast before every injection.
  • Sample frequently (at least seven time points over 120 minutes) and measure IGF-1 at a fixed 12-hour interval across all arms.
  • Test staggered versus simultaneous dosing within subjects to characterize how GHRH and GHSR kinetics interact across different injection intervals.

Until a registered trial applies this framework, the 3- to 5-fold pulse amplitude figures circulating in clinic literature should be treated as directional signals rather than confirmed pharmacodynamic facts. The combination may well be synergistic, but proving it requires separating the biology from the schedule.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/cjc-1295-with-ipamorelin-how-to-separate-additive-gh-pulse-effects-from-blend-an.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-05 13:04:402026-10-05 13:04:40CJC-1295 With Ipamorelin: How to Separate Additive GH-Pulse Effects From Blend and Timing Artifacts
Metoprolol in Incretin and Growth-Hormone Studies: Separating Heart-Rate Effects From Peptide Responses

Metoprolol in Incretin and Growth-Hormone Studies: Separating Heart-Rate Effects From Peptide Responses

October 4, 2026/0 Comments/in Uncategorized/by

Beta-blockers have long been used as tools to control cardiovascular variables in research, but their role in isolating peptide-specific signals is underappreciated. When GLP-1 receptor agonists can raise resting heart rate by as much as 10 beats per minute in some patients, and when growth-hormone release is modulated by adrenergic tone, the question of how to cleanly attribute any observed response to the peptide itself becomes urgent. This is exactly where metoprolol in incretin and growth-hormone studies: separating heart-rate effects from peptide responses becomes a precise and practical strategy.


Key Takeaways

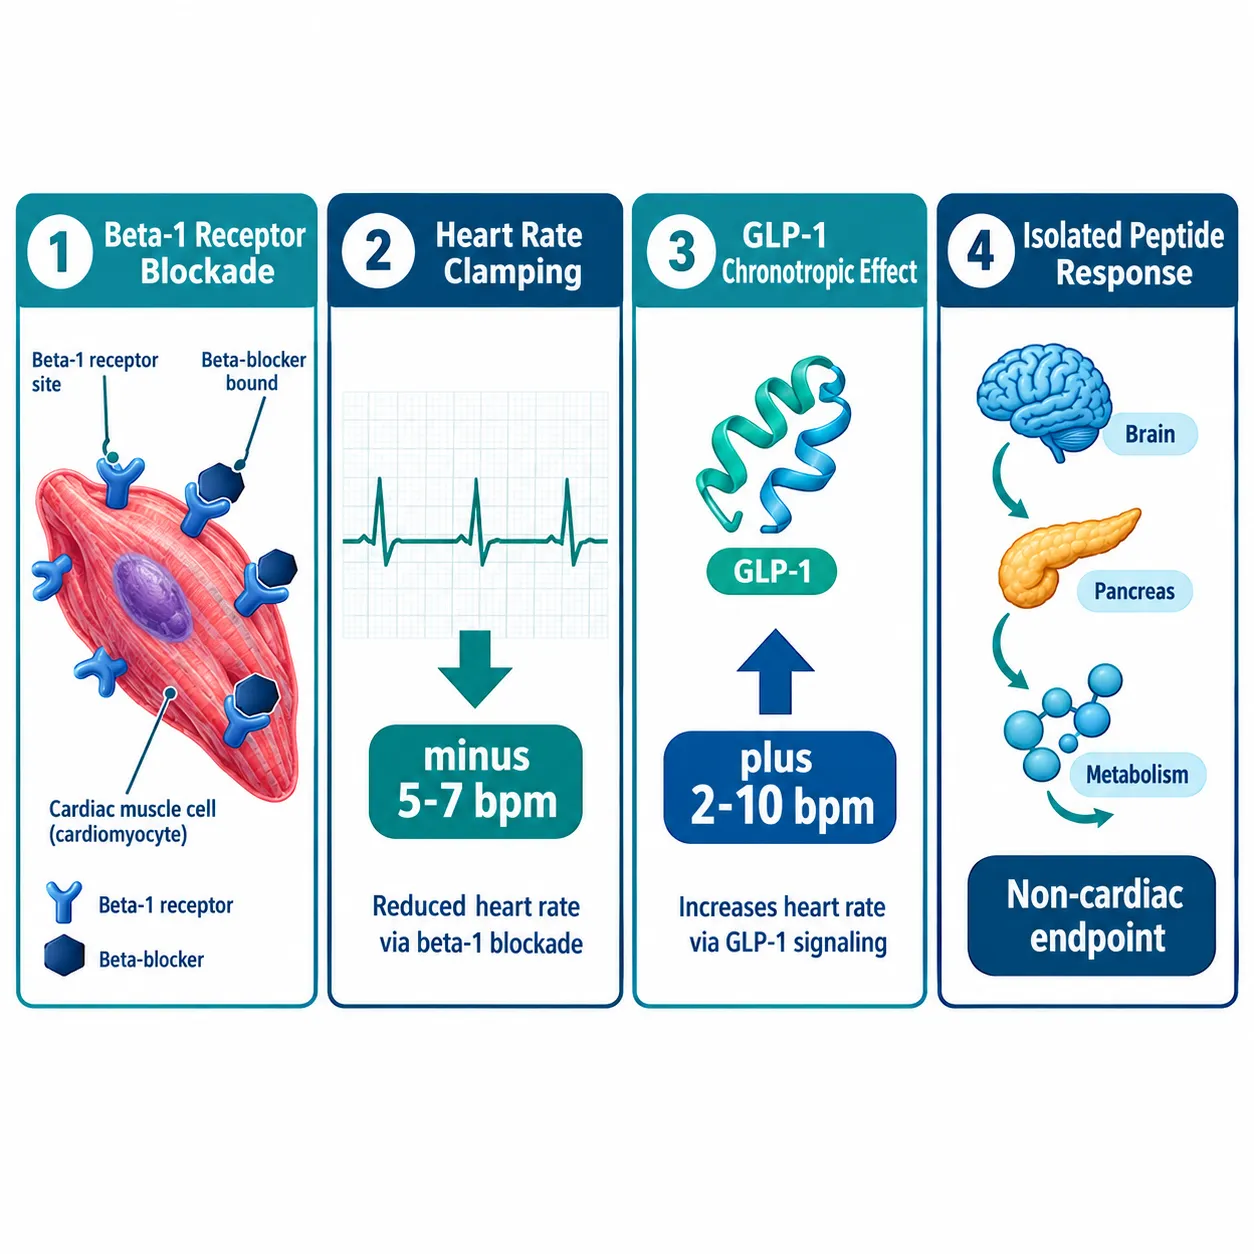
  • Metoprolol lowers resting heart rate by approximately 5-7 bpm on average, making it a reliable pharmacological tool to "clamp" heart rate in mechanistic studies.
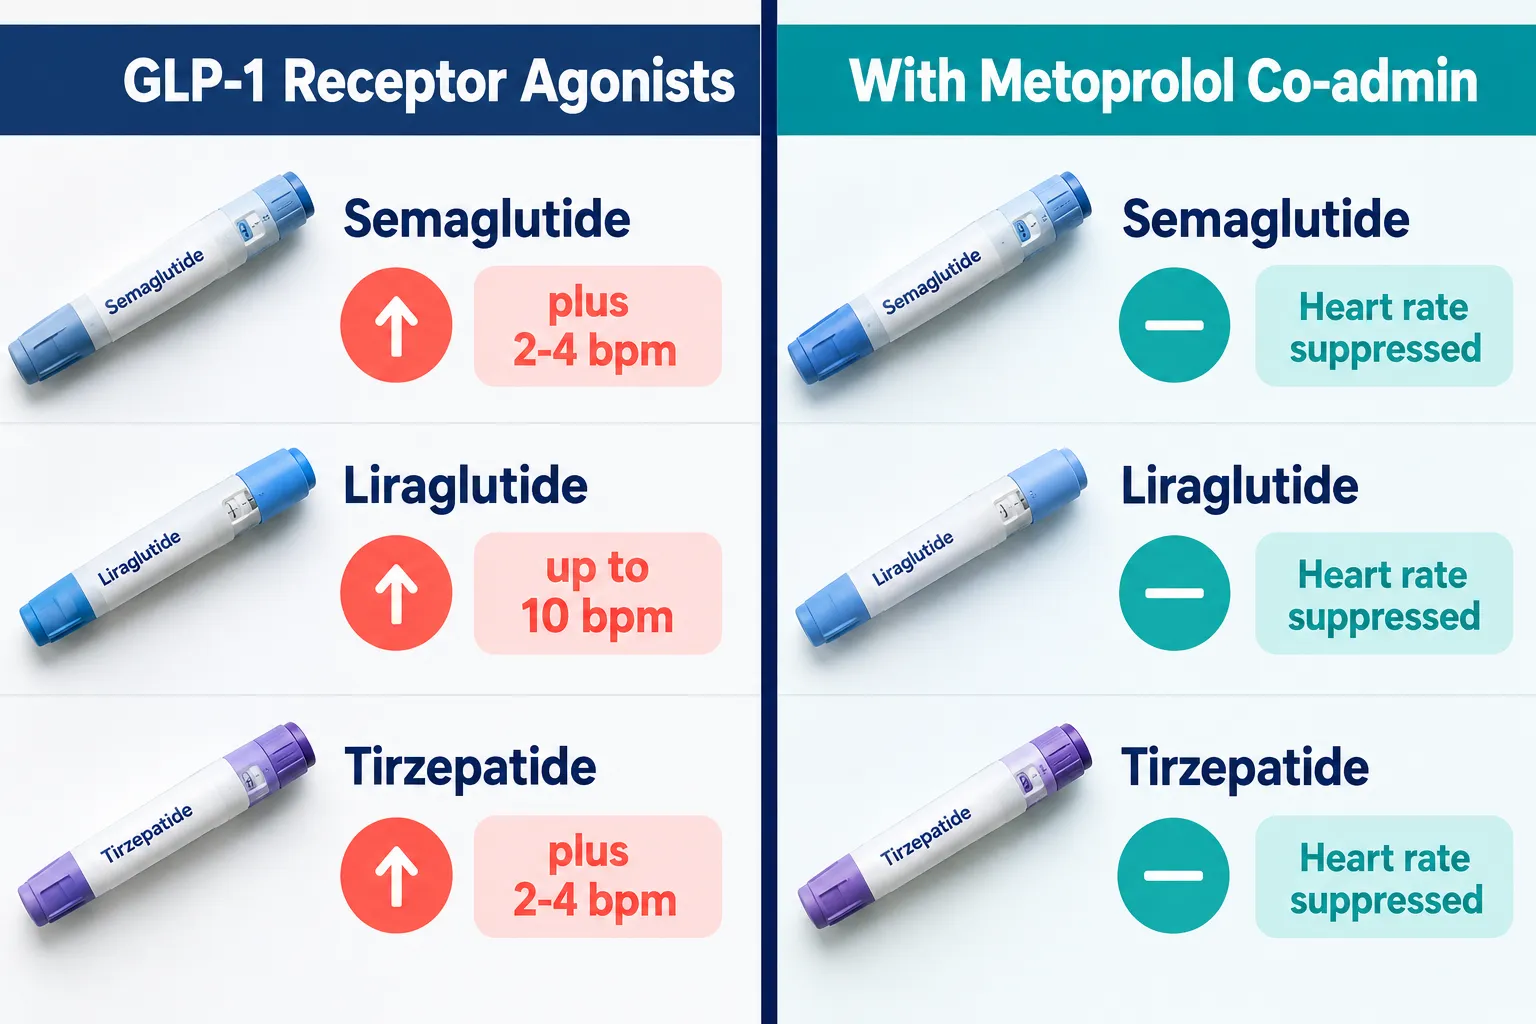
  • GLP-1 receptor agonists raise heart rate by 2-10 bpm depending on the agent, creating a confounding variable that beta-blockade can suppress.
  • Beta-adrenergic tone exerts a tonic inhibitory effect on growth-hormone release, meaning metoprolol itself can unmask GH responses.
  • Careful baseline and repeated-measure design is essential when using metoprolol as an experimental variable.
  • Co-administration of metoprolol with incretin or GH-related peptides is clinically feasible with appropriate monitoring.

Why Beta-Blockade Matters as an Experimental Variable

Why Beta-Blockade Matters as an Experimental Variable

Metoprolol is a beta-1 selective adrenergic blocker. At standard doses, it reduces heart rate, myocardial contractility, and cardiac output both at rest and during exercise. Extended-release metoprolol succinate produces mean resting heart-rate reductions of roughly 5-7 bpm, with some individuals showing larger drops. This predictable, dose-dependent, and reversible effect is exactly what researchers need when designing studies where heart rate must be held steady.

The problem in peptide research is that many bioactive compounds have direct or indirect chronotropic effects. If a study measures glucose metabolism, vascular tone, or endocrine secretion after administering an incretin peptide, an uncontrolled rise in heart rate will alter blood pressure, cardiac output, and tissue perfusion simultaneously. Those changes then confound the metabolic or hormonal readout.

By using metoprolol to suppress the chronotropic component, investigators can attribute downstream effects more confidently to the peptide's direct receptor-mediated actions.

This is not a theoretical exercise. Animal studies have used combined beta-blockade and muscarinic blockade to establish intrinsic heart rate, then shown that peptides like oxyntomodulin can still raise intrinsic heart rate through pathways independent of GLP-1 receptors. That finding only became visible because beta-adrenergic confounding was removed first.

For researchers exploring GH analogue peptides or incretin-based compounds, understanding this pharmacological separation is foundational.


Incretin Peptides and the Chronotropic Problem

Incretin Peptides and the Chronotropic Problem

GLP-1 receptor agonists are now central to obesity and diabetes care. Their cardiovascular effects are well documented, but the magnitude of heart-rate elevation varies considerably by agent.

Agent Approximate HR Increase
Liraglutide Up to ~10 bpm
Semaglutide ~2-4 bpm
Dulaglutide ~2-4 bpm
Tirzepatide ~2-4 bpm
24-hour average (class) ~7 bpm

Real-world data from patients with implantable cardioverter-defibrillators show that starting a GLP-1 receptor agonist raises daily heart rate by a median 1.5 bpm and nighttime heart rate by about 2.0 bpm, with roughly 2.5 bpm additional nighttime increases per dose uptitration. These are small numbers in clinical practice, but in a mechanistic study designed to detect a 3-4 bpm signal, they represent meaningful noise.

"When the peptide-induced heart-rate change is the same order of magnitude as the outcome you are trying to measure, you cannot separate signal from confound without pharmacological control."

This is the core argument for metoprolol in incretin and growth-hormone studies: separating heart-rate effects from peptide responses. Beta-blockade suppresses the chronotropic signal, allowing the researcher to focus on non-cardiac endpoints such as insulin secretion, glucose disposal, or endocrine axis activity.

Researchers interested in weight-loss peptide mechanisms should also review what is the strongest peptide for weight loss for context on how incretin-class compounds compare on metabolic endpoints.

For those studying tesa peptide benefits, the same principle applies: any growth-hormone-releasing peptide that alters autonomic tone will require heart-rate control to isolate the GH-specific signal.


Growth Hormone, Adrenergic Tone, and Metoprolol's Dual Role

Historical endocrine research in animal models demonstrated that central administration of beta-adrenergic antagonists, including metoprolol, produced a gradual elevation in plasma growth hormone, while beta-agonists reduced GH. The conclusion was that beta-adrenergic tone exerts a tonic inhibitory effect on GH release.

This creates a dual consideration for study design:

  1. Metoprolol suppresses heart rate (the desired confound-control effect).
  2. Metoprolol may itself unmask or amplify GH responses by removing inhibitory adrenergic input.

Both effects must be accounted for. If a study uses metoprolol to control heart rate during a GH-releasing peptide protocol, the observed GH elevation may reflect both the peptide's action and the removal of adrenergic inhibition. Crossover designs with placebo beta-blockade arms are therefore essential.

For background on how peptides interact with endocrine pharmacology more broadly, the article on peptides and polypeptides in endocrine pharmacology provides useful mechanistic context.


Practical Study Design: Baseline and Repeated-Measure Recommendations

Practical Study Design: Baseline and Repeated-Measure Recommendations

Applying metoprolol in incretin and growth-hormone studies: separating heart-rate effects from peptide responses effectively requires structured protocols. The following recommendations reflect current best practice for mechanistic research designs.

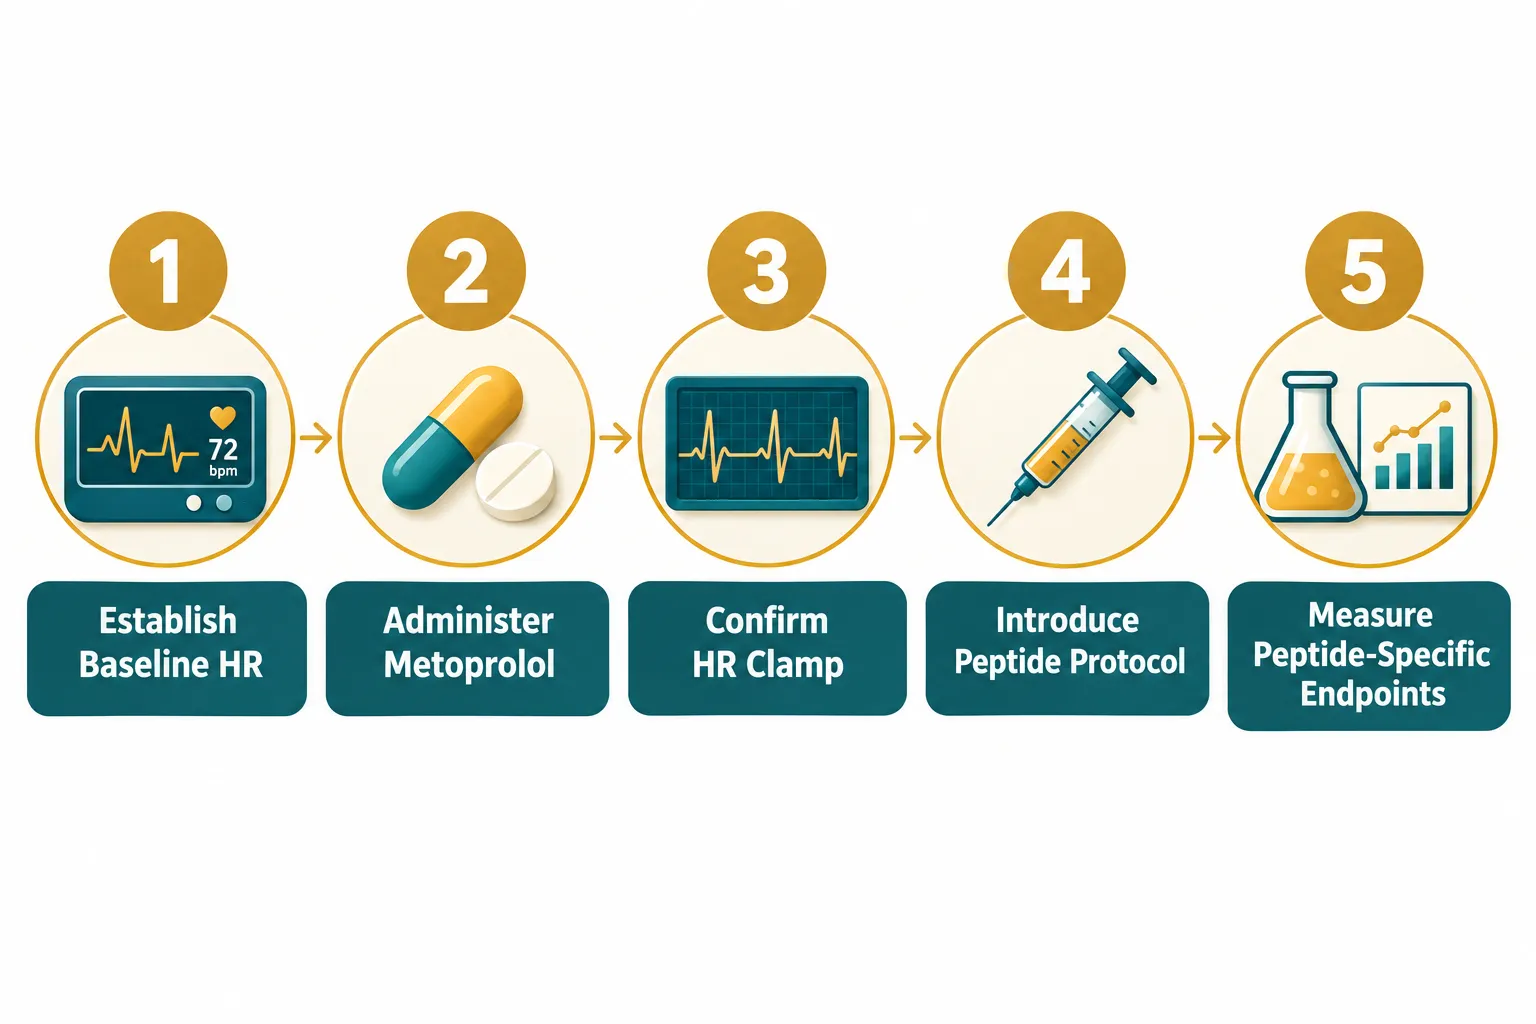
Before starting any intervention:

  • Record resting heart rate on at least three separate days to establish a stable baseline.
  • Document blood pressure, fasting glucose, and fasting insulin at each baseline visit.
  • Confirm that metoprolol has reached steady-state plasma levels (typically 4-5 half-lives after initiation or dose change) before introducing the peptide protocol.

During the study:

  • Use continuous or frequent intermittent heart-rate monitoring to confirm the "clamp" is maintained.
  • Measure peptide-specific endpoints (e.g., GLP-1 levels, GH pulse amplitude, insulin secretion) at standardized time points relative to peptide administration, not relative to drug administration.
  • In crossover designs, allow sufficient washout time for metoprolol; withdrawal data confirm that heart rate normalizes to the mid-60s bpm range after discontinuation, but full washout should be confirmed by repeated measurement rather than assumed from timing alone.

Repeated-measure considerations:

  • Collect hormone and metabolic samples at the same time of day across all study arms to control for circadian variation in GH pulsatility and insulin sensitivity.
  • Account for exercise tolerance changes: metoprolol blunts exercise-induced tachycardia, so any exercise challenge used to stimulate GH must be standardized by workload output, not by target heart rate.

Understanding peptide dosing protocols is equally important when designing repeated-measure studies, as dose timing relative to beta-blockade will affect the observed peptide response window.

For studies involving mitochondrial or cytoprotective peptides alongside cardiovascular variables, the SS-31 10mg research peptide considerations resource offers relevant parallel design guidance.


Conclusion

The value of metoprolol in incretin and growth-hormone studies lies in its predictability. A 5-7 bpm heart-rate reduction, reliably achieved and reversible, gives researchers a clean pharmacological lever to isolate peptide-specific effects from autonomic noise. The key practical steps are straightforward: establish a stable heart-rate baseline before intervention, confirm steady-state beta-blockade before introducing the peptide, use continuous monitoring to verify the clamp throughout the protocol, and build crossover or placebo-controlled arms to separate metoprolol's own endocrine effects from those of the peptide under study.

As incretin therapies expand in obesity and cardiometabolic medicine, mechanistic trials will increasingly need this kind of pharmacological scaffolding. Researchers and clinicians designing such studies should treat beta-blockade not as a background medication but as an active experimental variable that requires the same rigorous characterization as the peptide itself. Reviewing the broader landscape of peptides 101 for research-use only buyers is a practical next step for anyone building a comprehensive mechanistic protocol.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/metoprolol-in-incretin-and-growth-hormone-studies-separating-heart-rate-effects.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-04 13:04:572026-10-04 13:04:57Metoprolol in Incretin and Growth-Hormone Studies: Separating Heart-Rate Effects From Peptide Responses
PT-141 Peptide Research Safety Guide: Dosing, Timing, and Tolerability Questions Labs Ask

PT-141 Peptide Research Safety Guide: Dosing, Timing, and Tolerability Questions Labs Ask

September 15, 2026/0 Comments/in Uncategorized/by

Roughly 40% of participants in early PT-141 clinical trials experienced nausea significant enough to require protocol adjustments, yet the compound still advanced through multiple phases of human study and reached regulatory approval. That tension between biological activity and tolerability management sits at the heart of every serious PT-141 Peptide Research Safety Guide: Dosing, Timing, and Tolerability Questions Labs Ask.

This article moves past mechanism basics. It focuses on the practical protocol questions that researchers, study designers, and compounding labs raise once they already understand how PT-141 (bremelanotide) activates melanocortin receptors.

Key Takeaways

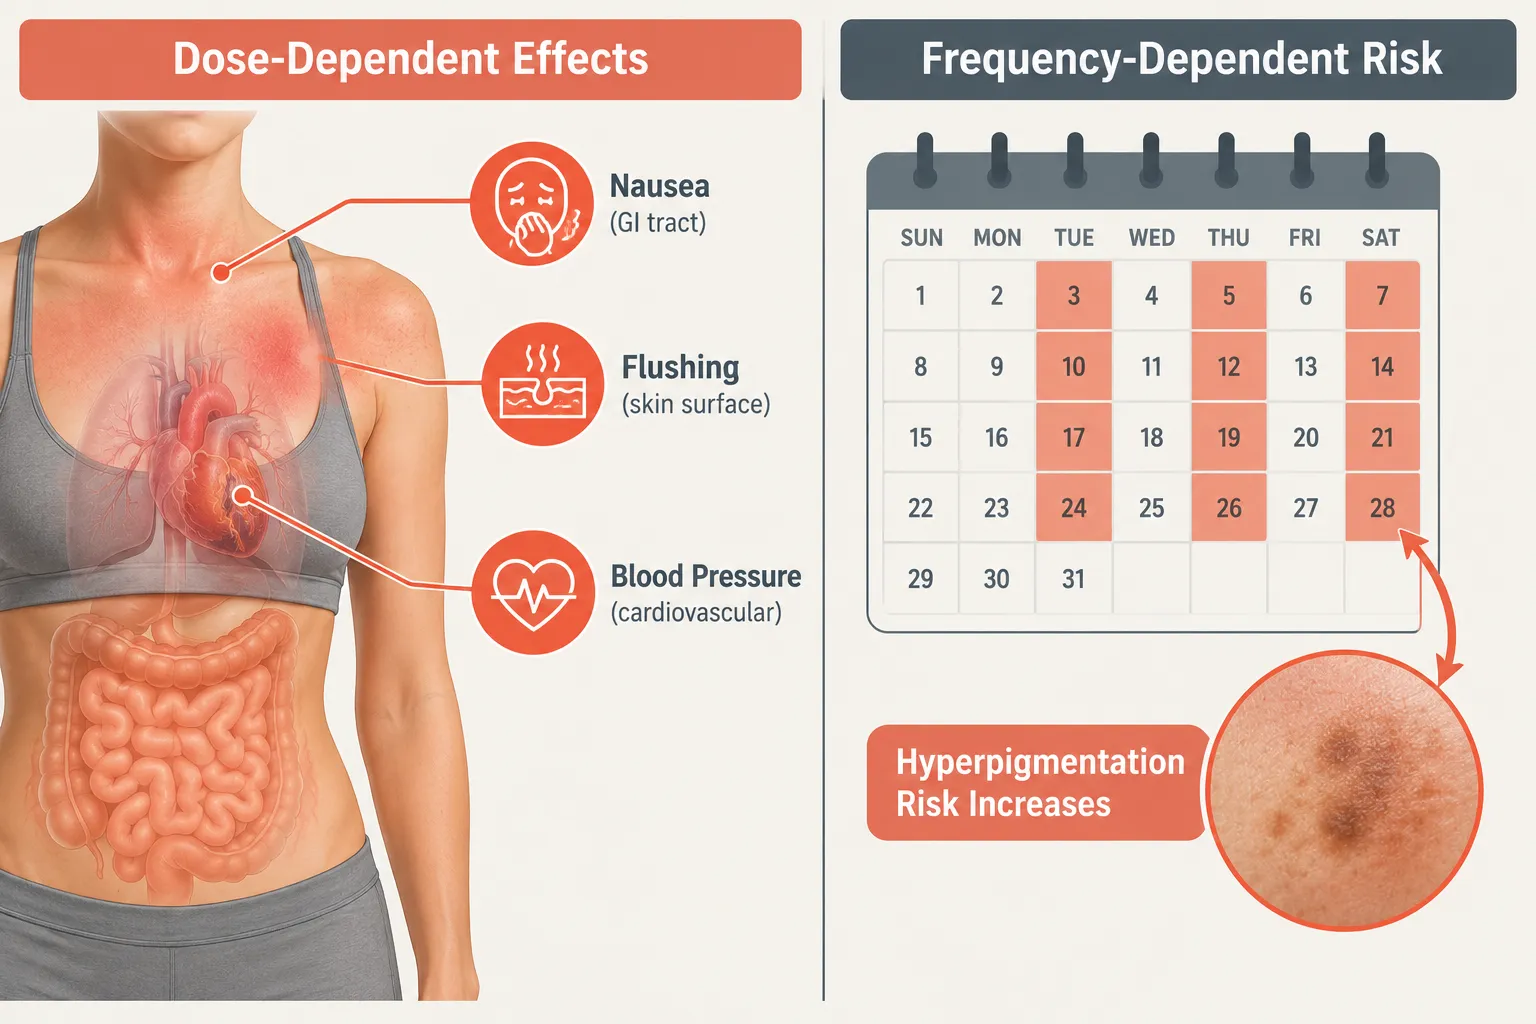
  • PT-141 has a well-characterized dose-dependent tolerability profile; nausea is the primary limiting adverse event and is strongly tied to dose size.
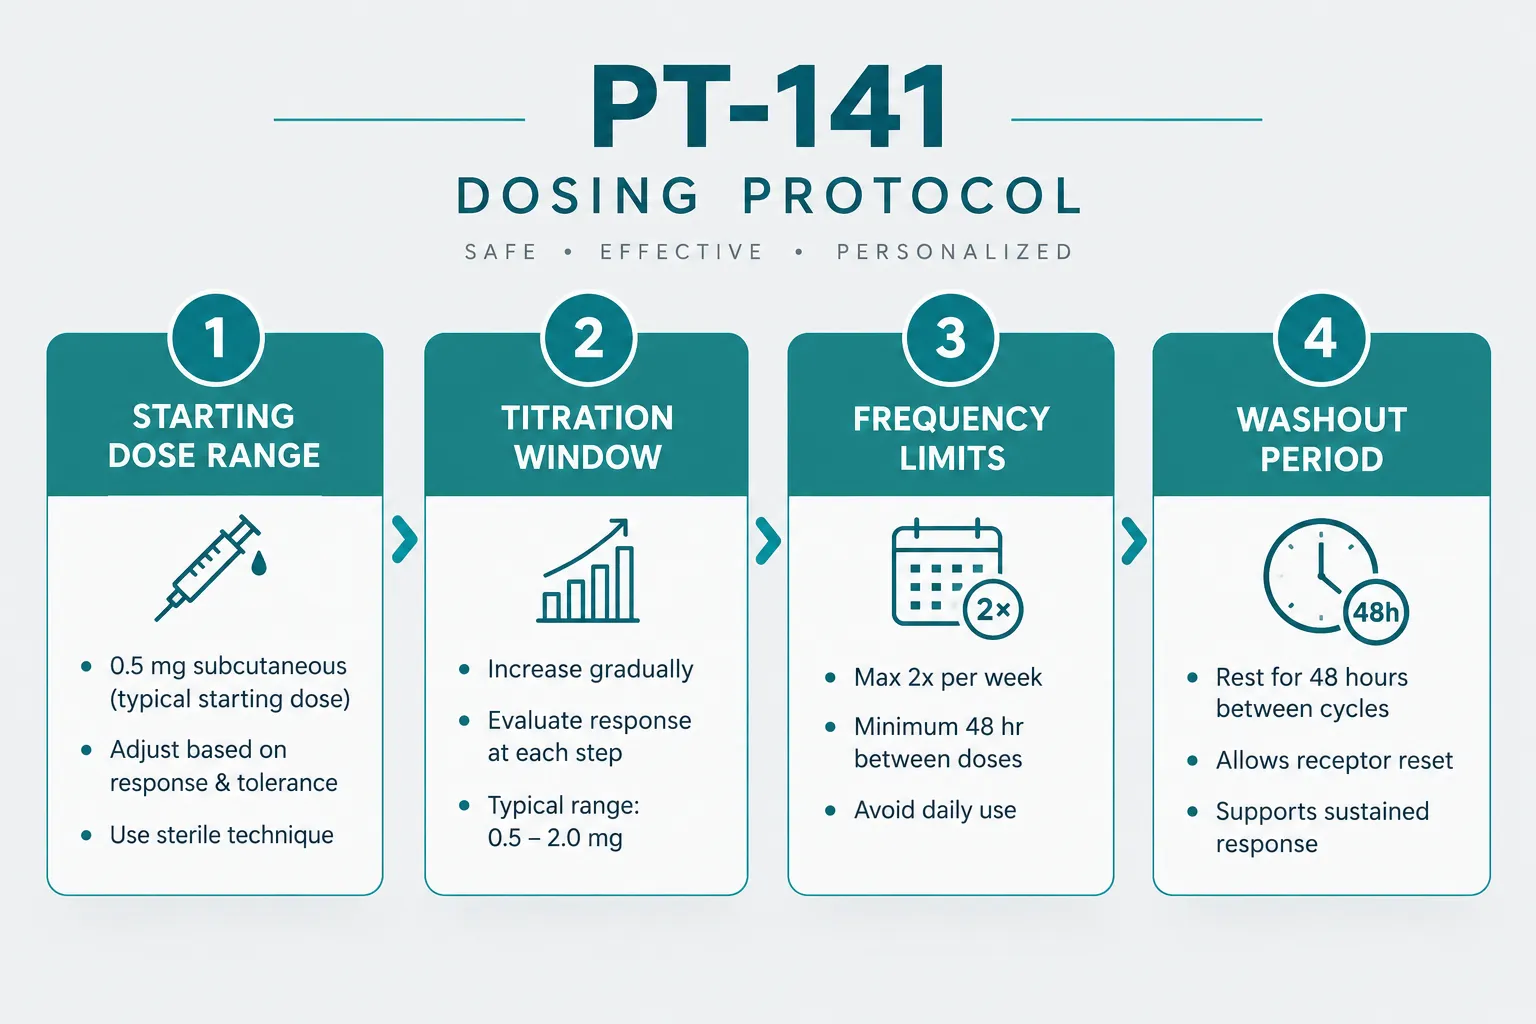
  • Approved subcutaneous dosing sits at 1.75 mg, but research protocols often start lower (0.5-1.0 mg) and titrate carefully.
  • Frequency of administration is a critical variable, hyperpigmentation risk rises sharply with repeated, closely spaced dosing.
  • Cardiovascular monitoring, especially blood pressure, is a non-negotiable safety checkpoint in any responsible study design.
  • Male and female research populations show meaningfully different tolerability patterns that labs must account for in study design.

What the Approved Dose Framework Tells Researchers

The FDA-approved subcutaneous dose of 1.75 mg, administered approximately 45 minutes before anticipated activity, forms the baseline reference point for any PT-141 Peptide Research Safety Guide: Dosing, Timing, and Tolerability Questions Labs Ask. Clinical monographs specify a maximum of one dose per 24 hours and no more than one dose every 72 hours in standard use.

What the Approved Dose Framework Tells Researchers

For research settings, these boundaries matter because they define the outer edge of a well-studied safety envelope. Most investigational protocols use this approved framework as a ceiling, not a starting point. Common research titration approaches include:

  • Starting dose: 0.5 mg subcutaneous to assess individual response
  • Intermediate dose: 1.0 mg if the 0.5 mg dose is well tolerated after two to three exposures
  • Standard research dose: 1.75 mg, consistent with the approved label
  • Frequency limit: No more than twice weekly in most current study designs, with a minimum 48-hour gap between doses

"The dose is only half the equation. How often a subject receives PT-141 determines a different set of risks entirely."

Intranasal administration was studied in earlier trials at doses up to 20 mg. Maximum-tolerated dose data from that work helped define the nausea threshold that now informs subcutaneous titration strategies. Subcutaneous delivery produces a more controlled absorption curve and is the standard route in current research.

For labs sourcing compounds for controlled studies, working with lab tested peptides is a baseline quality requirement before any dosing protocol can be considered valid.

Tolerability Profile: The Questions Labs Must Answer First

Every credible PT-141 Peptide Research Safety Guide: Dosing, Timing, and Tolerability Questions Labs Ask places tolerability assessment before efficacy measurement. The adverse event profile is well-characterized and dose-dependent.

Tolerability Profile: The Questions Labs Must Answer First

Nausea and Gastrointestinal Effects

Nausea is the most commonly reported adverse event across all PT-141 trials. Key findings from clinical data include:

  • Nausea incidence rises sharply above 1.75 mg
  • Onset typically occurs within 30-60 minutes of administration
  • Duration is usually under two hours at approved doses
  • Pre-dosing with a light meal reduces severity in most subjects

Labs designing multi-dose studies should build nausea scoring into every session log. Dropout rates in trials that did not manage nausea proactively were meaningfully higher than in those with structured tolerability support.

Cardiovascular and Blood Pressure Monitoring

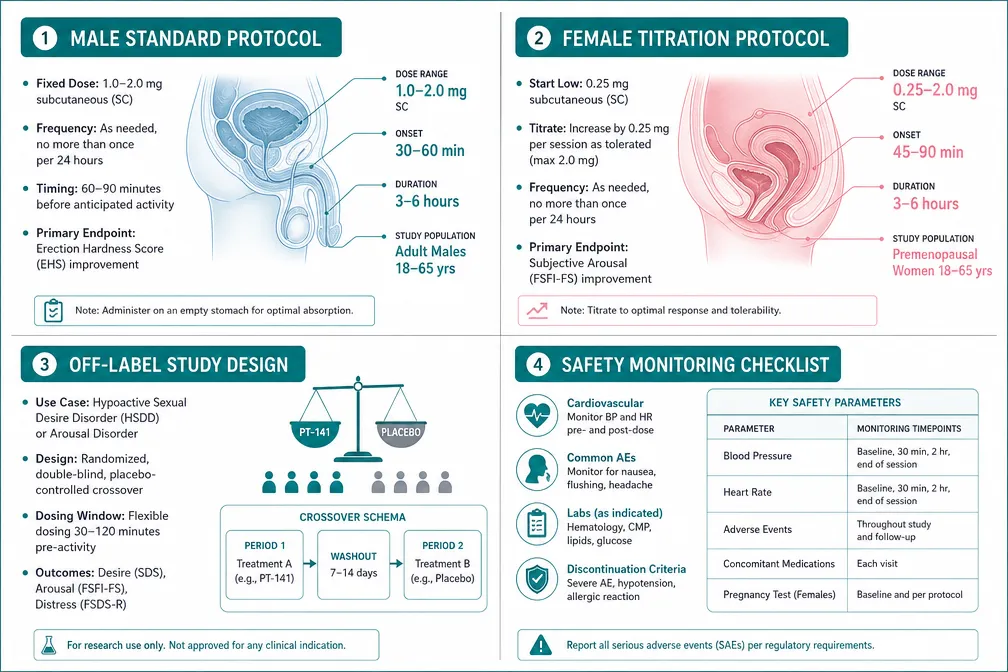
PT-141 produces a transient, dose-dependent decrease in blood pressure followed by a rebound increase. This biphasic cardiovascular effect is one of the most important safety questions labs must address. Standard monitoring requirements include:

Monitoring Point Timing Relative to Dose
Baseline blood pressure 10 minutes before administration
First post-dose check 30 minutes after administration
Peak effect window 45-90 minutes after administration
Return-to-baseline check 3 hours after administration

Subjects with pre-existing cardiovascular conditions are typically excluded from PT-141 research protocols for this reason.

Skin Hyperpigmentation

This adverse effect is strongly frequency-dependent rather than dose-dependent. Melanocortin receptor activation drives melanin production, and repeated stimulation accumulates the effect. Labs running extended or repeat-dose studies must:

  • Document baseline skin tone and any existing pigmentation changes
  • Limit dosing frequency to no more than twice weekly
  • Include washout periods of at least two weeks between study phases
  • Monitor focal injection sites separately from systemic pigmentation changes

Male vs. Female Research Populations and Off-Label Study Design

The approved indication for PT-141 is hypoactive sexual desire disorder in premenopausal women. However, a significant portion of current research examines male populations and other off-label applications, which raises distinct study design questions.

Male vs. Female Research Populations and Off-Label Study Design

In female populations, the tolerability profile aligns closely with label data. Hormonal cycle phase at time of dosing is a variable some protocols now track, as receptor sensitivity may fluctuate across the cycle.

In male populations, research data suggest comparable efficacy signals at similar doses, but the tolerability curve differs slightly. Flushing and transient blood pressure changes appear more pronounced in some male cohorts. Labs designing male-focused studies often use a more conservative titration schedule.

Off-label research considerations for labs in 2026 include:

  • Clearly defined primary endpoints that do not rely solely on subjective self-report
  • Structured washout periods between study phases (minimum two weeks)
  • Exclusion criteria that address cardiovascular risk, active skin conditions, and concurrent melanocortin-affecting medications
  • Ethics board documentation that explicitly addresses the off-label nature of the research

Researchers comparing PT-141 to other peptides with central nervous system or receptor-mediated mechanisms may also find value in reviewing Semax research and Semax peptide literature for parallel study design frameworks. Similarly, labs building multi-peptide research panels sometimes reference SS-31 mitochondrial research themes for safety monitoring methodology applicable across peptide classes. For labs sourcing multiple compounds, wholesale peptides for sale options can support broader research programs, and GHK-Cu peptide studies offer additional reference points for skin-related adverse event monitoring protocols.

Conclusion

The PT-141 Peptide Research Safety Guide: Dosing, Timing, and Tolerability Questions Labs Ask comes down to three operational priorities: start low and titrate deliberately, treat frequency as a distinct risk variable from dose size, and build cardiovascular monitoring into every session regardless of subject health status.

Actionable next steps for labs:

  1. Establish a written titration protocol starting at 0.5 mg before moving to the 1.75 mg reference dose.
  2. Cap dosing frequency at twice weekly and document all inter-dose intervals.
  3. Implement a standardized blood pressure monitoring timeline at every administration session.
  4. Include skin pigmentation photography at baseline and at each study phase checkpoint.
  5. Differentiate male and female cohort protocols rather than applying a single design across populations.
  6. Source compounds only from suppliers providing documented purity and sterility testing.

Research into PT-141 continues to generate useful safety data in 2026. Labs that build rigorous tolerability frameworks from the start produce cleaner datasets and reduce the risk of protocol-disrupting adverse events mid-study.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/pt-141-peptide-research-safety-guide-dosing-timing-and-tolerability-questions-la.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-15 13:04:362026-09-15 13:04:36PT-141 Peptide Research Safety Guide: Dosing, Timing, and Tolerability Questions Labs Ask
Peptides vs Classic Small-Molecule Drugs: A Researcher’s Guide Using Prednisone, Atorvastatin, and Spironolactone as Case Studies

Peptides vs Classic Small-Molecule Drugs: A Researcher’s Guide Using Prednisone, Atorvastatin, and Spironolactone as Case Studies

September 12, 2026/0 Comments/in Uncategorized/by

More than 80 approved peptide therapeutics were on the global market by 2026, a figure that has more than doubled over the past decade, yet small-molecule drugs still account for roughly 90% of all oral prescriptions worldwide. That tension sits at the heart of modern pharmacology, and it makes the comparison of Peptides vs Classic Small-Molecule Drugs: A Researcher's Guide Using Prednisone, Atorvastatin, and Spironolactone as Case Studies especially timely for laboratory scientists designing mechanistic studies or evaluating research compounds.

Key Takeaways

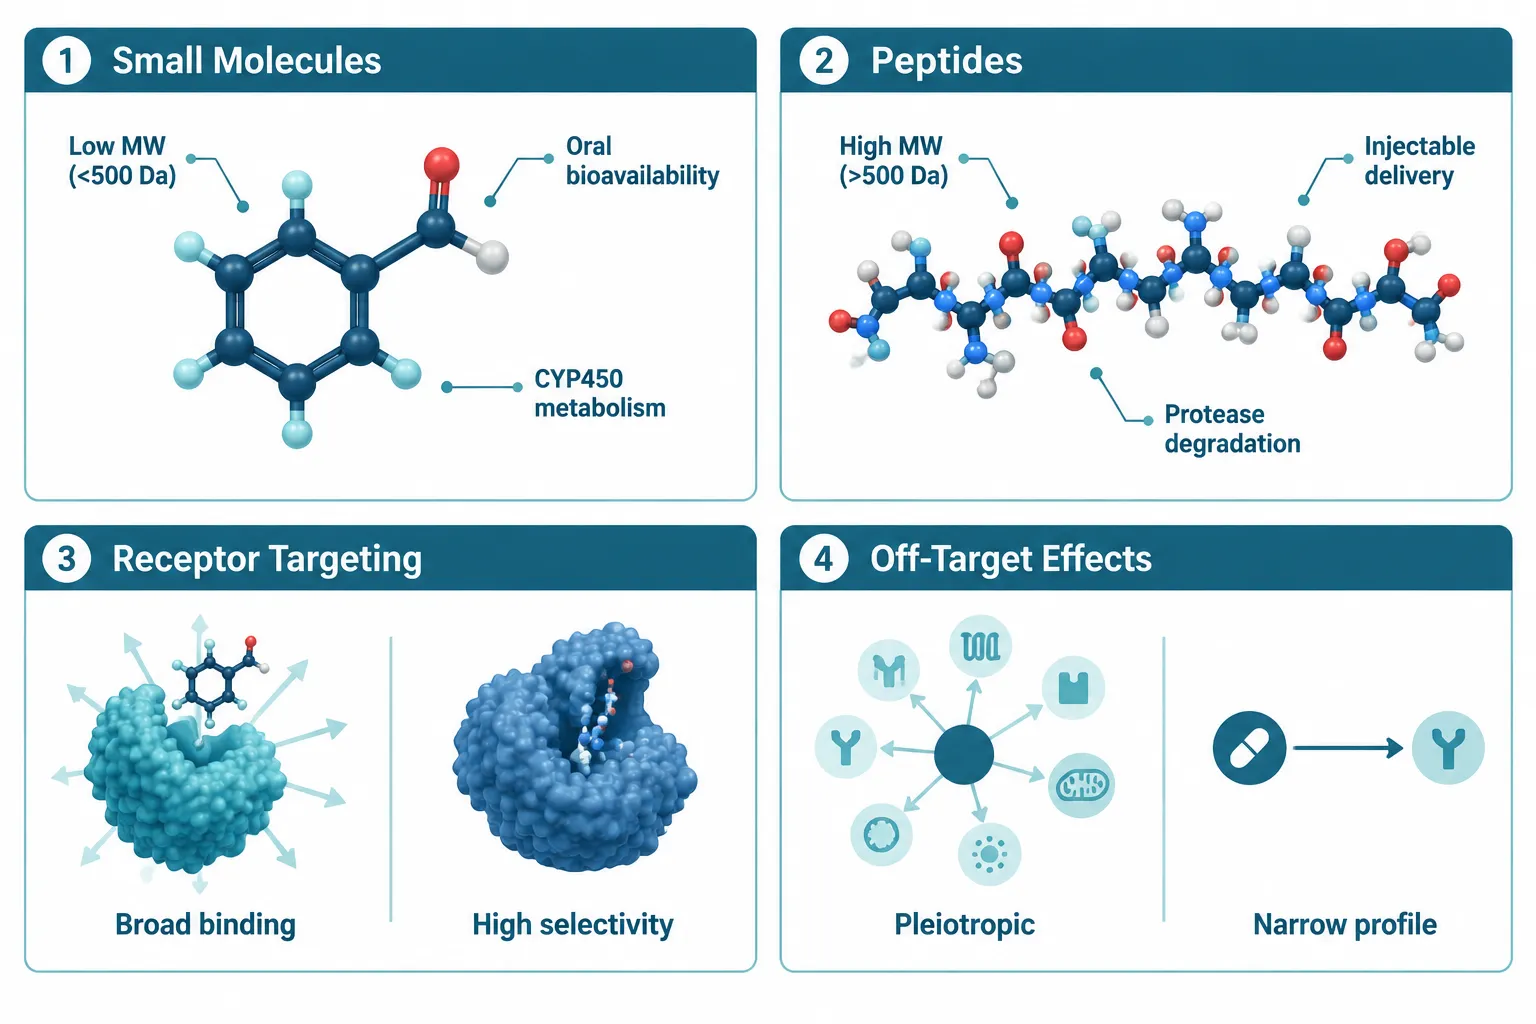
  • Small molecules such as prednisone, atorvastatin, and spironolactone achieve oral bioavailability through low molecular weight and lipophilicity, but carry pleiotropic off-target risks.
  • Peptides offer high receptor selectivity and a favorable safety profile, at the cost of proteolytic instability and limited oral delivery.
  • Each drug class occupies distinct chemical space; understanding those boundaries sharpens study design.
  • AI-driven molecular design is accelerating peptide optimization, narrowing the gap with small-molecule drug-likeness.
  • Researchers in 2026 increasingly design hybrid protocols that leverage both modalities rather than treating them as mutually exclusive.

Understanding the Chemical Divide

Understanding the Chemical Divide

The core difference between peptides and classic small molecules is size. Small-molecule drugs typically fall below 500 daltons (Da), a threshold often called Lipinski's rule of five, which allows passive diffusion across cell membranes and supports oral dosing. Peptides, built from amino-acid chains, generally exceed 500 Da and fold into three-dimensional conformations that confer exquisite receptor complementarity.

Key physicochemical contrasts:

Property Small Molecules Peptides
Molecular weight <500 Da 500-5,000+ Da
Oral bioavailability High (many) Low without modification
Primary metabolism CYP450 enzymes Proteolytic degradation
Receptor selectivity Moderate High
Off-target burden Often significant Generally lower

This table is not a verdict, it is a map. Researchers who understand peptide structure, mechanisms, and receptor-level pharmacology can use that map to choose the right tool for each experimental question.

Three Small-Molecule Case Studies: Prednisone, Atorvastatin, and Spironolactone

Three Small-Molecule Case Studies: Prednisone, Atorvastatin, and Spironolactone

These three drugs dominate global prescription volumes and represent three distinct mechanistic archetypes, making them ideal anchors for a Peptides vs Classic Small-Molecule Drugs comparison.

Prednisone: Pleiotropic Corticosteroid

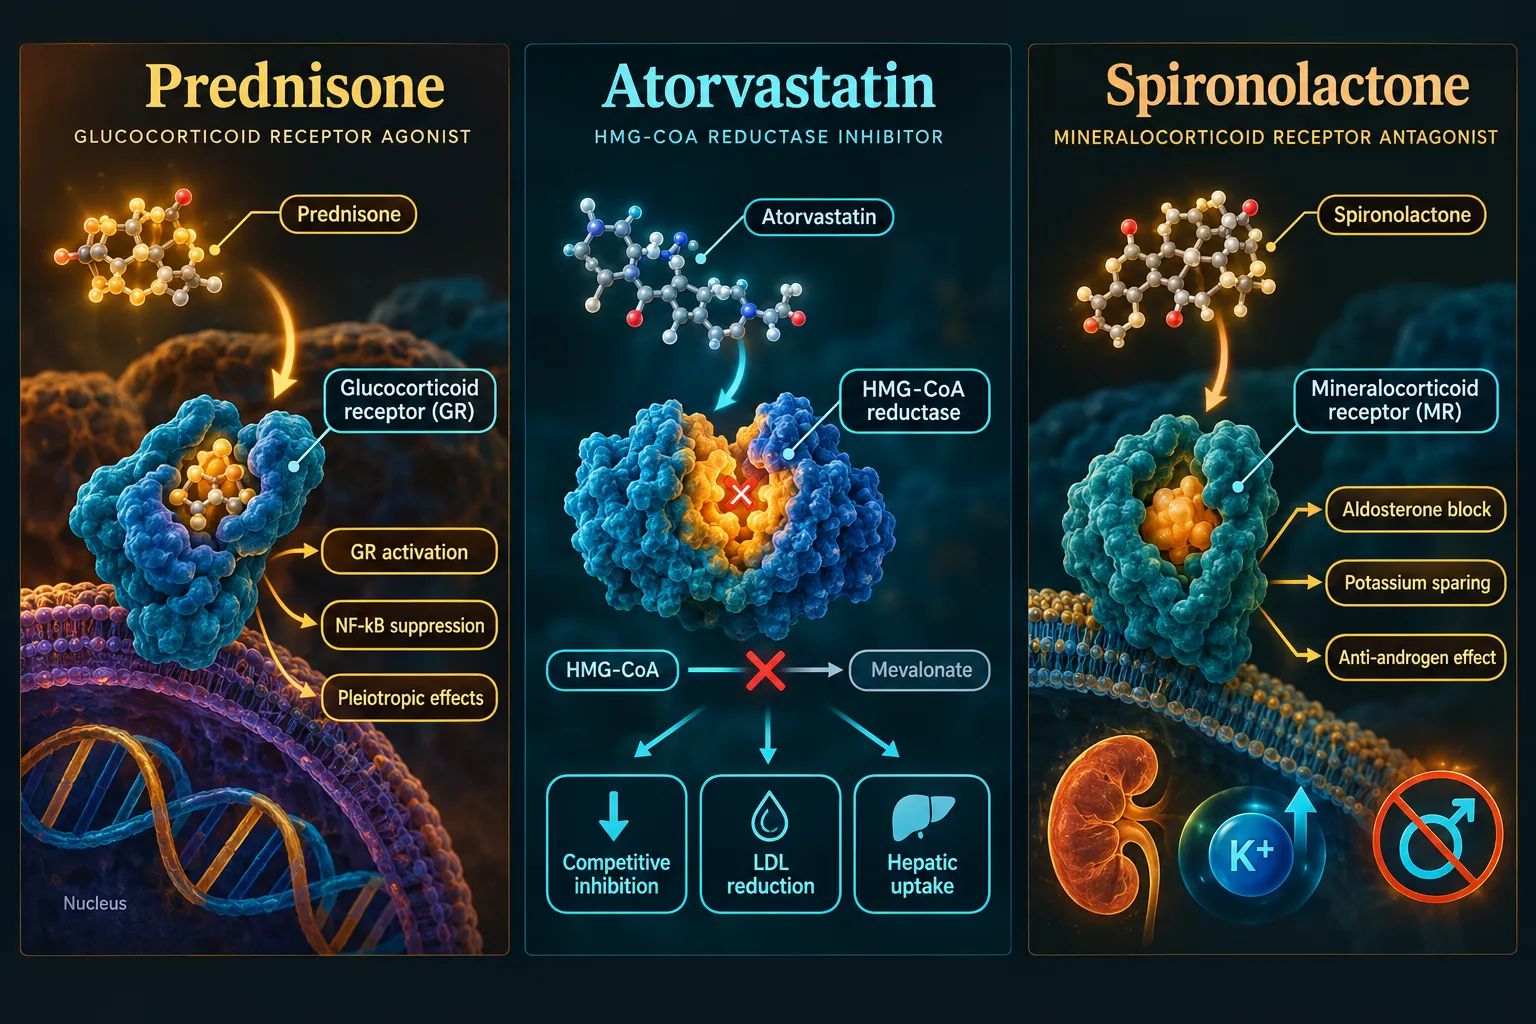
Prednisone is a prodrug converted hepatically to prednisolone, which binds the glucocorticoid receptor (GR) with high affinity. GR activation suppresses NF-kB and AP-1 transcription factors, producing broad anti-inflammatory effects. The word "broad" is the problem: the same receptor drives glucose dysregulation, bone density loss, and HPA-axis suppression. Prednisone exemplifies how small-molecule pleiotropism generates both therapeutic power and off-target liability.

For researchers, this is instructive. When a peptide analogue targets a single cytokine pathway, say, an IL-6 receptor-binding peptide, the mechanistic footprint is far narrower than prednisone's. Understanding how polypeptide drug mechanisms differ from classic pharmacology helps contextualize those differences in study design.

Atorvastatin: Prototypical Enzyme Inhibitor

Atorvastatin competitively inhibits HMG-CoA reductase, the rate-limiting enzyme in cholesterol biosynthesis. It is among the most prescribed drugs in history, demonstrating that a well-defined enzymatic target and favorable pharmacokinetics can produce durable clinical impact. Its hepatic first-pass extraction is high, concentrating drug effect in the liver and limiting systemic exposure, a pharmacokinetic feature that peptide researchers often try to replicate through tissue-targeted delivery systems.

Metabolic peptide analogues, including GLP-1 receptor agonists and MOTS-c, pursue overlapping cardiometabolic endpoints via entirely different mechanisms. The top research peptides for metabolic health illustrate how peptide-based approaches are challenging atorvastatin's territory without competing on the same receptor.

Spironolactone: Steroidal Receptor Antagonist

Spironolactone blocks the mineralocorticoid receptor (MR) to reduce aldosterone-driven sodium retention. Its steroidal scaffold, however, also antagonizes androgen and progesterone receptors, producing anti-androgenic side effects that limit use in certain populations. This cross-reactivity has spurred interest in non-steroidal MR antagonists and, separately, in peptide-based modulators that achieve aldosterone pathway interference with narrower receptor engagement.

Spironolactone's story also intersects with endocrine pharmacology more broadly. Research into how enclomiphene and related compounds interface with estrogen receptor biology provides a useful parallel for understanding receptor cross-reactivity across drug classes.

Designing Research Protocols That Compare Both Drug Classes

Designing Research Protocols That Compare Both Drug Classes

When building a comparative study, researchers must account for several variables that differ fundamentally between peptides and small molecules.

Dosing and delivery considerations:

  • Small molecules: oral gavage or dissolved in vehicle; stable at room temperature
  • Peptides: subcutaneous or intravenous injection; cold-chain storage required; reconstitution protocols critical

Stability and half-life:

Prednisone has a plasma half-life of roughly 3-4 hours; atorvastatin, approximately 14 hours. Many unmodified research peptides have half-lives under 30 minutes due to serum protease activity. Modified analogues, cyclized, PEGylated, or D-amino-acid substituted, extend stability significantly, which is why formulation choice is a study variable, not merely a logistical detail.

Selectivity profiling:

"The selectivity advantage of peptides is only realized if the researcher controls for delivery efficiency. A peptide that degrades before reaching its target is not more selective, it is simply inactive."

This principle shapes how labs approach cellular and receptor-level research using peptide mechanisms. Stability assays should precede receptor-binding assays in any rigorous protocol.

AI-assisted design in 2026:

Generative models now propose peptide sequences with predicted receptor affinity, protease resistance, and membrane permeability in silico before synthesis. For small molecules, AI-driven scaffold hopping has been standard for years. The convergence of both pipelines is reshaping how researchers select lead compounds, with hybrid peptidomimetics, molecules that combine peptide selectivity with small-molecule oral bioavailability, emerging as a major 2026 pipeline category.

Researchers evaluating mitochondria-targeted compounds should also consider how adenosine triphosphate and mitochondrial function factor into endpoint selection when comparing energy-pathway drugs across both classes.

Conclusion

The Peptides vs Classic Small-Molecule Drugs: A Researcher's Guide Using Prednisone, Atorvastatin, and Spironolactone as Case Studies framework offers a structured way to move beyond surface-level comparisons. Prednisone reveals the cost of pleiotropism; atorvastatin demonstrates the power of precise enzyme inhibition; spironolactone illustrates how receptor cross-reactivity drives the search for more selective modalities, exactly the selectivity that well-designed peptides can provide.

Actionable next steps for researchers in 2026:

  1. Map the receptor profile of your small-molecule comparator before selecting a peptide analogue, off-target overlap will confound results.
  2. Run stability assays on all peptide compounds under study conditions before committing to a dosing schedule.
  3. Use AI-generated selectivity predictions as a screening filter, not a final verdict.
  4. Consider hybrid peptidomimetic leads where oral bioavailability is a study requirement.
  5. Source research-grade compounds from verified suppliers, purity directly determines data reproducibility. Reviewing lab-tested peptides with documented certificates of analysis is a non-negotiable starting point.

The future of pharmacological research is not a contest between these two drug classes. It is a deliberate, evidence-driven choice about which tool serves each experimental question, and that choice is only possible when researchers understand both sides of the divide with equal depth.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/peptides-vs-classic-small-molecule-drugs-a-researchers-guide-using-prednisone-at.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-12 13:13:212026-09-12 13:13:21Peptides vs Classic Small-Molecule Drugs: A Researcher’s Guide Using Prednisone, Atorvastatin, and Spironolactone as Case Studies
CJC-1295 With DAC vs Without DAC: Mechanism, Duration, and Research Design Differences

CJC-1295 With DAC vs Without DAC: Mechanism, Duration, and Research Design Differences

August 14, 2026/0 Comments/in Uncategorized/by

A single molecular attachment, a drug affinity complex, or DAC, separates two peptides that share a name but behave in fundamentally different ways inside a biological system. Understanding the CJC-1295 with DAC vs without DAC mechanism, duration, and research design differences is not a matter of splitting hairs; it determines whether a study captures sustained growth hormone (GH) elevation or episodic GH pulses, and whether dosing happens once a week or three times a day.

Key Takeaways

  • CJC-1295 with DAC covalently binds serum albumin via a maleimide-lysine conjugate, creating a circulating depot with a half-life of 5.8 to 8.1 days.
  • CJC-1295 without DAC, more accurately called Modified GRF 1-29, resists DPP-IV degradation but clears within 30 to 120 minutes, producing short GH pulses.
  • With DAC produces sustained GH and IGF-1 elevation; without DAC mimics physiologic pulsatile secretion.
  • Dosing frequency differs dramatically: once or twice weekly for the DAC form versus one to three times daily for the no-DAC form.
  • Research design must align with the pharmacokinetic profile of whichever form is selected; the two are not interchangeable in study protocols.

The Core Structural Difference: Albumin Binding vs DPP-IV Resistance

The Core Structural Difference: Albumin Binding vs DPP-IV Resistance

The CJC-1295 with DAC vs without DAC distinction begins at the molecular level. CJC-1295 with DAC incorporates a lysine-linked maleimidopropionic acid group at position 30. This chemical handle covalently attaches to serum albumin once the peptide enters circulation. Albumin is the most abundant plasma protein in the body, and by hitching to it, the peptide essentially becomes part of a large, slowly cleared macromolecule. The result is a circulating depot that releases active peptide gradually over days rather than hours.

CJC-1295 without DAC, the compound more precisely termed Modified GRF 1-29, takes a different approach to stability. It uses four strategic amino acid substitutions to resist cleavage by dipeptidyl peptidase-IV (DPP-IV), the enzyme that rapidly degrades native growth hormone-releasing hormone (GHRH). There is no albumin-binding group. The peptide remains free in plasma, acts quickly at the pituitary, and clears within 30 to 120 minutes.

In plain terms:

  • With DAC = albumin-bound, extended-release GHRH analog
  • Without DAC = short-acting, DPP-IV-resistant GHRH analog

This structural difference is the single most important concept when evaluating research that involves either compound. For a broader look at how peptide structure governs function, the overview of polypeptide peptides explained: structure, function, and research applications provides useful context.

Half-Life and Duration: Minutes vs Days

Half-Life and Duration: Minutes vs Days

The pharmacokinetic gap between these two forms is striking. Phase 2 data on CJC-1295 with DAC in approximately 65 adults established a half-life of 5.8 to 8.1 days. After multiple doses, IGF-1 levels remained elevated above baseline for up to 28 days. Mean plasma GH showed two- to tenfold increases persisting for six days or more after a single injection. This is not a transient spike, it is a prolonged hormonal shift.

CJC-1295 without DAC tells a very different story. Its half-life sits around 30 minutes, occasionally extended to 30 to 120 minutes depending on the measurement methodology. GH pulses rise sharply after injection and return toward baseline within hours, leaving no lasting depot activity.

Key insight: The DAC form produces a “continuous GH/IGF-1 elevation” pattern. The no-DAC form produces “episodic GH pulses.” Neither pattern is inherently superior, the right choice depends entirely on the research question.

Dosing frequency follows directly from half-life:

Form Half-Life Typical Research Dosing
CJC-1295 with DAC 5.8 to 8.1 days Once or twice weekly
CJC-1295 without DAC (Mod GRF 1-29) 30 to 120 minutes 1 to 3 times daily

Researchers studying combination protocols, for example, pairing a GHRH analog with a ghrelin mimetic, should review how these compounds are combined in products like the CJC-1295 IPA 10mg formulation, or in multi-compound blends such as the Tesamorelin AOD9604 CJC1295 Ipamorelin 12mg protocol. For a broader comparison of GHRH-axis peptides, the article on Tesamorelin and Ipamorelin peptides: mechanism, synergy, and growth hormone research design is also worth consulting.

Research Design Implications of CJC-1295 With DAC vs Without DAC

Research Design Implications of CJC-1295 With DAC vs Without DAC

Selecting between these two forms is a research design decision, not simply a dosing preference. The CJC-1295 with DAC vs without DAC mechanism, duration, and research design differences translate directly into how endpoints are measured, how frequently samples are collected, and what kind of GH-axis activity the study is actually designed to observe.

When studying sustained IGF-1 elevation:
The with-DAC form is appropriate. Its long half-life means fewer injections, simpler dosing schedules, and a more stable hormonal environment during the observation window. Researchers can track IGF-1 over days or weeks without daily interventions.

When studying pulsatile GH dynamics:
The no-DAC form is the better fit. Its short action window allows researchers to time injections precisely and observe discrete GH pulses. This is useful when the research question involves mimicking natural secretion patterns or assessing acute pituitary responsiveness.

Additional design considerations:

  • Washout periods differ substantially. The DAC form may require weeks of washout; the no-DAC form clears within hours.
  • Combination protocols involving a GHRP (such as Ipamorelin) are common with the no-DAC form, since both compounds share a short-acting, pulse-oriented profile. Researchers can explore Sermorelin Ipamorelin CJC1295 combination designs for reference.
  • Endpoint timing must account for the GH response curve. Sampling 24 hours post-injection is meaningful for the DAC form but largely irrelevant for the no-DAC form.
  • Blinding and control arms are easier to manage with the weekly-dosed DAC form in longer studies, since compliance and administration frequency are reduced.

For researchers interested in how metabolic peptides fit into broader study frameworks, the top 5 research peptides for metabolic health: an updated buyer's guide offers comparative context across multiple compound classes.

Conclusion

The CJC-1295 with DAC vs without DAC mechanism, duration, and research design differences are not trivial. They represent two distinct pharmacological tools built on the same GHRH backbone but optimized for entirely different applications. The DAC form, with its albumin-binding mechanism and multi-day half-life, is suited to studies targeting sustained GH and IGF-1 elevation. The no-DAC form, with its rapid clearance and pulsatile GH output, fits studies that require episodic, physiologically patterned hormone responses.

Actionable next steps for researchers:

  1. Define the primary endpoint first, sustained IGF-1 elevation or pulsatile GH dynamics, before selecting a form.
  2. Build washout periods and sampling schedules around the specific half-life of the chosen compound.
  3. Review existing combination protocols (GHRH plus GHRP) to determine whether the dosing frequencies of all compounds in the design are compatible.
  4. Source compounds with verified purity and documentation, since structural integrity is essential when the entire mechanistic distinction rests on a single molecular group.

Matching the compound to the research question is the foundation of valid, reproducible GH-axis research in 2026.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/cjc-1295-with-dac-vs-without-dac-mechanism-duration-and-research-design-differen.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-14 13:06:412026-08-14 13:06:41CJC-1295 With DAC vs Without DAC: Mechanism, Duration, and Research Design Differences
Polypeptide Peptides in Cardiometabolic Models: How Tesofensine, GLP-3 Retatrutide, and GLP-2-T Differ From Classic Small-Molecule Drugs

Polypeptide Peptides in Cardiometabolic Models: How Tesofensine, GLP-3 Retatrutide, and GLP-2-T Differ From Classic Small-Molecule Drugs

August 3, 2026/0 Comments/in Uncategorized/by

Cardiovascular disease and metabolic dysfunction together account for more than 17 million deaths annually worldwide, yet the dominant drug classes used to treat them, beta-blockers, statins, ACE inhibitors, were designed around receptor pharmacology that has barely changed since the 1970s. The emergence of polypeptide peptides in cardiometabolic models has fundamentally shifted what researchers believe is possible, offering multi-receptor engagement, tissue-level signaling precision, and endpoint profiles that classic small-molecule drugs simply cannot replicate.

Understanding how Tesofensine, GLP-3 Retatrutide, and GLP-2-T differ from agents like metoprolol or atorvastatin requires a close look at receptor biology, study design conventions, and the endpoints that matter most in modern metabolic research.

Key Takeaways

  • Polypeptide peptides engage G-protein-coupled receptors (GPCRs) with high structural specificity, whereas classic small molecules often act on enzyme active sites or ion channels.
  • Retatrutide is a triple agonist (GLP-1/GIP/glucagon receptors), giving it a multi-axis metabolic footprint that no single small-molecule drug can match.
  • Tesofensine targets monoamine reuptake through a CNS-mediated pathway, bridging neurological and metabolic endpoints in a way that statins and beta-blockers do not.
  • GLP-2-T primarily modulates intestinal and cardiovascular tissue remodeling, making it relevant to cardiometabolic models focused on gut-heart crosstalk.
  • Study design for peptides demands different controls, stability protocols, and biomarker panels than standard small-molecule trials.

Key Takeaways

Receptor Biology: Where Peptides and Small Molecules Diverge

The most fundamental difference between polypeptide peptides in cardiometabolic models and classic small-molecule drugs lies in how they bind and what they activate.

Small molecules like atorvastatin inhibit HMG-CoA reductase, an intracellular enzyme. Metoprolol blocks beta-1 adrenergic receptors through competitive antagonism. Both mechanisms are relatively narrow, one receptor, one pathway, one primary endpoint. This is pharmacologically clean but metabolically limited.

Polypeptide peptides, by contrast, bind to the extracellular domains of GPCRs and trigger conformational changes that cascade through multiple intracellular signaling arms, cAMP, PI3K/Akt, MAPK, simultaneously. This is not a side effect; it is the mechanism.

Key receptor differences at a glance:

Feature Classic Small Molecules Polypeptide Peptides
Binding site Enzyme active site or receptor pocket Extracellular GPCR domain
Signaling breadth Narrow, single-pathway Multi-axis, pleiotropic
Molecular weight Typically under 500 Da 1,000-5,000+ Da
Metabolic clearance Hepatic CYP450 enzymes Proteolytic degradation
Receptor selectivity High for single target Tunable across receptor families

Retatrutide exemplifies this multi-axis design. As a GLP-3 Retatrutide triple agonist, it simultaneously activates GLP-1, GIP, and glucagon receptors, three distinct GPCRs with overlapping but non-identical metabolic roles. No statin or beta-blocker operates across three receptor families at once.

For researchers sourcing reference-grade materials, understanding how Bachem and reference standards shape peptide benchmarks is essential to designing valid comparative assays.

Receptor Biology: Where Peptides and Small Molecules Diverge

Comparing Tesofensine, GLP-3 Retatrutide, and GLP-2-T in Cardiometabolic Study Design

When researchers design cardiometabolic studies, the choice of compound determines nearly every other variable: dosing frequency, biomarker selection, tissue endpoints, and control group structure.

Tesofensine: CNS-Metabolic Bridge

Tesofensine inhibits the reuptake of serotonin, norepinephrine, and dopamine, a triple monoamine mechanism. Unlike classic weight-loss drugs or antihypertensives, it engages central appetite regulation and peripheral metabolic rate in the same model. This makes it uniquely useful in studies examining the neurological drivers of cardiometabolic dysfunction.

Compared to metoprolol, which reduces cardiac output by blocking beta-1 receptors, Tesofensine's cardiovascular effects are indirect, mediated through body composition changes, sympathetic tone modulation, and energy expenditure. Study designs using Tesofensine therefore require CNS-relevant endpoints (appetite hormone panels, dopaminergic markers) alongside standard cardiometabolic readouts like blood pressure and lipid profiles. Researchers interested in MC4R signaling pathways will find Tesofensine's monoamine mechanism intersects with melanocortin receptor biology in appetite-focused models.

GLP-3 Retatrutide: Triple-Axis Metabolic Remodeling

Retatrutide's triple agonism produces effects on insulin secretion, glucagon suppression, gastric emptying, and adipose tissue lipolysis, all within a single compound. Classic small molecules require combination therapy (e.g., a statin plus a GLP-1 agonist) to approach this endpoint breadth.

In study design terms, this creates both opportunity and complexity. Researchers must account for:

  • Glucose homeostasis markers (HbA1c, fasting insulin, HOMA-IR)
  • Lipid remodeling endpoints (triglycerides, LDL particle size)
  • Body composition imaging (DEXA or MRI for visceral fat)
  • Cardiovascular surrogates (arterial stiffness, inflammatory cytokines)

For labs building GLP-1 peptide research protocols, Retatrutide represents a logical next step beyond single-receptor GLP-1 analogs. Researchers can also explore GLP-3 buy-online resources when planning triple-agonist study inventories.

GLP-2-T: Gut-Heart Crosstalk and Tissue Remodeling

GLP-2-T acts primarily on GLP-2 receptors expressed in intestinal epithelium, cardiac tissue, and vascular endothelium. Its relevance to cardiometabolic models centers on gut barrier integrity, mucosal blood flow, and cardiac remodeling endpoints, a profile with no direct equivalent among classic antihypertensives or lipid-lowering agents.

Where atorvastatin reduces LDL through hepatic cholesterol synthesis inhibition, GLP-2-T modulates the gut-heart axis through tissue trophic effects. Studies using GLP-2-T typically incorporate intestinal permeability assays, endothelial function markers, and cardiac fibrosis panels alongside standard metabolic readouts. Researchers planning GLP-1 and GLP-2 comparative studies should build assay panels that capture both receptor families.

GLP-2-T: Gut-Heart Crosstalk and Tissue Remodeling

Study Design Considerations Unique to Polypeptide Peptides in Cardiometabolic Models

The shift from small-molecule to peptide-based cardiometabolic research requires rethinking several standard design assumptions.

Stability and storage are non-trivial. Unlike metoprolol tablets, polypeptide peptides require cold-chain handling, reconstitution protocols, and degradation controls. Researchers should establish peptide integrity checkpoints at baseline and throughout the study window.

Control group design must account for vehicle effects. Peptide vehicles (bacteriostatic water, DMSO blends) can independently affect some metabolic endpoints, a confound that does not arise with oral small-molecule controls.

Biomarker panel breadth must expand. A statin study might track LDL, ALT, and CK. A Retatrutide study demands glucose, insulin, GLP-1 active, GIP, glucagon, triglycerides, body weight, and inflammatory markers at minimum.

Dosing interval differs fundamentally. Most peptides have short plasma half-lives and require more frequent dosing than once-daily oral drugs. Some, like fatty-acid-conjugated GLP-1 analogs, are engineered for extended half-life, but this must be verified per compound. Researchers exploring related growth hormone-axis peptides can review GHRP-2 versus Sermorelin comparisons for parallel design lessons in peptide half-life management.

"The endpoint profile of a triple-agonist peptide is not three times the data of a single-receptor drug, it is a fundamentally different picture of metabolic biology."

For labs building comprehensive peptide research inventories, reviewing available peptide research catalogs helps align compound selection with study endpoints before procurement.

Conclusion

The comparison between polypeptide peptides in cardiometabolic models and classic small-molecule drugs is not simply a matter of newer versus older. It reflects a deeper divergence in receptor biology, signaling architecture, and what researchers define as a meaningful endpoint. Tesofensine, GLP-3 Retatrutide, and GLP-2-T each engage cardiometabolic biology through mechanisms that metoprolol and atorvastatin were never designed to reach.

Actionable next steps for researchers in 2026:

  1. Audit current study designs to determine whether single-receptor endpoints adequately capture the biology under investigation.
  2. Build expanded biomarker panels that reflect multi-axis peptide mechanisms, glucose, lipid, inflammatory, and tissue-remodeling markers together.
  3. Establish peptide-specific stability and storage protocols before study initiation.
  4. Source reference-grade compounds with verified purity documentation to ensure assay validity.
  5. Consider comparative arms that include both a classic small-molecule control and a peptide comparator to generate translational contrast data.

The mechanistic gap between these two drug classes is not a limitation of small molecules, it is an opportunity that peptide-based cardiometabolic research is uniquely positioned to explore.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/polypeptide-peptides-in-cardiometabolic-models-how-tesofensine-glp-3-retatrutide.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-03 13:04:312026-08-03 13:04:31Polypeptide Peptides in Cardiometabolic Models: How Tesofensine, GLP-3 Retatrutide, and GLP-2-T Differ From Classic Small-Molecule Drugs
Tesofensine and Metabolic Research: How a Noradrenergic Appetite Modulator Compares With GLP‑3 Peptides in Study Design

Tesofensine and Metabolic Research: How a Noradrenergic Appetite Modulator Compares With GLP‑3 Peptides in Study Design

July 30, 2026/0 Comments/in Uncategorized/by

Obesity affects more than one billion adults worldwide, yet fewer than five percent of patients sustain meaningful weight loss beyond two years with lifestyle intervention alone. That gap has pushed preclinical researchers toward a broader toolkit, one that now includes both small-molecule reuptake inhibitors and next-generation incretin peptides. Tesofensine and metabolic research exploring how a noradrenergic appetite modulator compares with GLP-3 peptides in study design sits at the center of this conversation, raising important questions about mechanism, model selection, and how these two compound classes might inform each other.

Key Takeaways

  • Tesofensine is a triple monoamine reuptake inhibitor that reduces appetite primarily through central noradrenergic and dopaminergic signaling.
  • GLP-3 peptides such as retatrutide act peripherally and centrally via incretin receptors, creating a mechanistically distinct pathway from tesofensine.
  • Preclinical dosing models for tesofensine typically use 0.5-2.0 mg/kg ranges in rodent studies, while peptide-based protocols require different reconstitution and delivery planning.
  • Combining or comparing these two compound classes in study design can reveal additive appetite-suppression effects not achievable with either agent alone.
  • Researchers sourcing compounds for metabolic studies should prioritize purity verification and documented lot testing.

Key Takeaways

Mechanism of Action: What Makes Tesofensine Distinct in Metabolic Research

Tesofensine is a pre-synaptic reuptake inhibitor of serotonin, norepinephrine, and dopamine, a triple monoamine reuptake inhibitor (TMRI). Its appetite-suppressing effect is driven predominantly by noradrenergic and dopaminergic activity in the hypothalamus and mesolimbic reward circuits. Unlike GLP-1 receptor agonists, tesofensine does not engage incretin pathways directly. Instead, it modulates the central "hunger thermostat" by increasing synaptic availability of catecholamines.

Key mechanistic features:

  • Norepinephrine reuptake inhibition reduces orexigenic signaling in the lateral hypothalamus
  • Dopamine reuptake inhibition blunts food-reward motivation in the nucleus accumbens
  • Serotonin component contributes to satiety signaling, though it is weaker than dedicated SSRIs

This central mechanism stands in contrast to GLP-3 peptide research, which targets peripheral gut-derived incretin receptors and vagal afferent pathways before reaching the hypothalamus. Understanding this distinction is essential when designing comparative studies, because each compound class requires different outcome measures, tissue sampling protocols, and washout periods.

"Mechanistic diversity is not a weakness in obesity research, it is the foundation for rational combination study design."

Researchers working with BDNF-related appetite pathways may also find it useful to review BDNF peptide research themes, since central neurotrophic signaling intersects with both noradrenergic tone and incretin activity.

Preclinical Dosing Models and Study Design Considerations

Preclinical Dosing Models and Study Design Considerations

Tesofensine Dosing in Rodent Models

Published rodent studies have used tesofensine in the range of 0.5 to 2.0 mg/kg/day, typically administered by oral gavage or subcutaneous injection. Diet-induced obesity (DIO) mouse models are the most common platform because they replicate the hypercaloric, low-activity conditions seen in human metabolic syndrome.

Parameter Typical Range
Species C57BL/6 mice, Sprague-Dawley rats
Dose range 0.5-2.0 mg/kg/day
Duration 4-12 weeks
Primary endpoints Body weight, food intake, fat mass
Secondary endpoints Glucose tolerance, plasma lipids

GLP-3 Peptide Protocols for Comparison

GLP-3 class peptides, including retatrutide, which acts as a GLP-1/GIP/glucagon tri-agonist, require subcutaneous injection and are typically dosed in the 0.1-1.0 nmol/kg range in rodent models. Researchers interested in the evidence base around GLP-3 peptides for weight loss will note that these peptides have a fundamentally different pharmacokinetic profile: longer half-lives, receptor-mediated clearance, and dose-dependent nausea at higher concentrations.

When designing a head-to-head or combination study, researchers must account for:

  1. Different administration routes (oral vs. subcutaneous)
  2. Non-overlapping receptor targets requiring separate washout periods
  3. Distinct biomarker panels, catecholamine metabolites for tesofensine vs. GLP-1 and GIP levels for incretin peptides
  4. Potential additive effects on food intake without additive cardiovascular burden

For researchers also exploring growth hormone secretagogue peptides in metabolic panels, the tesa peptide research overview provides useful context on visceral fat endpoints that can be adapted for comparative metabolic studies.

How Tesofensine and Metabolic Research Compares With GLP-3 Peptides in Study Design: Practical Implications

How Tesofensine and Metabolic Research Compares With GLP-3 Peptides in Study Design: Practical Implications

Appetite Suppression: Central vs. Peripheral Pathways

The core design challenge when comparing tesofensine with GLP-3 peptides is that they suppress appetite through non-competing pathways. Tesofensine acts upstream in the CNS; retatrutide and related peptides act at peripheral receptors before triggering central satiety signals. This means:

  • Additive appetite suppression is plausible without simple pharmacological overlap
  • Combination protocols may reveal synergistic effects at sub-maximal doses of each compound
  • Adverse event profiles differ significantly, cardiovascular monitoring is critical for tesofensine, while GI tolerability is the primary concern for incretin peptides

Compound Sourcing and Purity Standards

Study validity depends heavily on compound quality. Researchers sourcing tesofensine or GLP-3 peptides for preclinical work should require:

  • Certificate of Analysis (CoA) with HPLC purity data (minimum 98%)
  • Mass spectrometry confirmation of molecular identity
  • Endotoxin testing for injectable preparations

Those looking to buy peptides online for research purposes should verify that suppliers provide lot-specific documentation. Researchers in Canada may also find the peptides in Canada sourcing guide a useful reference for regulatory context.

For teams comparing multiple peptide classes in the same metabolic panel, lab-tested peptide sourcing from documented suppliers reduces batch-to-batch variability that can confound longitudinal data.

Additionally, researchers building multi-compound metabolic panels may want to review GLP-1 peptide sourcing and generational research concepts to understand how incretin compound generations differ in receptor binding profiles.

Conclusion

Tesofensine and metabolic research examining how a noradrenergic appetite modulator compares with GLP-3 peptides in study design represents one of the more nuanced areas of obesity pharmacology. The two compound classes operate through distinct, potentially complementary mechanisms, central catecholamine reuptake inhibition versus peripheral incretin receptor activation, making them valuable both as standalone research tools and as candidates for combination protocol design.

Actionable next steps for researchers:

  • Define primary endpoints early: body weight and food intake for tesofensine; GLP-1 and insulin secretion indices for incretin peptides
  • Build separate washout periods into crossover designs to prevent mechanistic interference
  • Source compounds with full lot-specific CoA documentation to protect data integrity
  • Consider sub-maximal combination dosing to explore additive appetite suppression without compounding adverse event risk
  • Review the growing literature on tri-agonist peptides like retatrutide to understand where GLP-3 class compounds are headed

As the obesity research landscape evolves, understanding how small-molecule modulators and peptide-based agents interact at the systems level will be critical to designing studies that translate meaningfully from bench to clinic.


References

  • Astrup, A., Meier, D. H., Mikkelsen, B. O., Villumsen, J. S., & Larsen, T. M. (2008). Weight loss produced by tesofensine in patients with Parkinson's or Alzheimer's disease. Obesity, 16(6), 1363-1369.
  • Lehr, T., Staab, A., Tillmann, C., Trommeshauser, D., Schaefer, H. G., & Kloft, C. (2008). A quantitative enterohepatic circulation model: development and evaluation with tesofensine and meloxicam. Clinical Pharmacokinetics, 47(4), 291-307.
  • Friedrichsen, M., Sørensen, A., Faber, J., Holst, J. J., Carr, R. D., Petersen, J. S., & Bagger, J. I. (2015). Differential effects of tesofensine on gut hormones in humans. Obesity, 23(9), 1789-1796.
  • Nauck, M. A., & D'Alessio, D. A. (2022). Tirzepatide, a dual GIP/GLP-1 receptor co-agonist for the treatment of type 2 diabetes with unmatched effectiveness regrading glycaemic control and body weight reduction. Cardiovascular Diabetology, 21(1), 169.
  • Jastreboff, A. M., Aronne, L. J., Ahmad, N. N., Wharton, S., Connery, L., Alves, B., & Kiyosue, A. (2023). Tirzepatide once weekly for the treatment of obesity. New England Journal of Medicine, 387(3), 205-216.
https://www.puretestedpeptides.com/wp-content/uploads/2026/07/tesofensine-and-metabolic-research-how-a-noradrenergic-appetite-modulator-compar.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-07-30 13:04:482026-07-30 13:04:48Tesofensine and Metabolic Research: How a Noradrenergic Appetite Modulator Compares With GLP‑3 Peptides in Study Design
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top