

ACE Inhibitors and Research Peptides: Designing Blood-Pressure Controls Around Lisinopril and Growth-Hormone Secretagogues
Nearly one billion adults worldwide live with hypertension, yet a growing number of researchers are simultaneously exploring growth-hormone secretagogue peptides whose hemodynamic effects remain poorly characterized. That overlap creates a real experimental design problem. When studying ACE inhibitors and research peptides, specifically designing blood-pressure controls around lisinopril and growth-hormone secretagogues, researchers must understand how ACE-pathway modulation shapes blood pressure, renal readouts, and fluid balance, and how those changes can confound or clarify CJC-1295, ipamorelin, and tesa experiments.
Key Takeaways
- Lisinopril is a long-acting, evidence-backed ACE inhibitor with well-defined effects on blood pressure, cardiac events, and kidney function.
- Growth-hormone secretagogues such as ipamorelin, CJC-1295, and tesa can cause fluid retention and potential blood-pressure elevation, particularly in stage 2 hypertension.
- No rigorous human study has directly measured blood-pressure changes attributable to ipamorelin alone, creating a significant data gap.
- ACE-pathway suppression alters aldosterone levels and glomerular filtration, which directly affects how renal endpoints are interpreted in peptide research.
- Designing valid research protocols requires establishing stable lisinopril dosing before introducing GH-axis peptides, then monitoring BP at every injection-period review.
How the ACE Pathway Controls Blood Pressure and Renal Readouts
The renin-angiotensin-aldosterone system (RAAS) is the body's primary long-term blood-pressure regulator. Angiotensin-converting enzyme (ACE) converts angiotensin I into angiotensin II, a potent vasoconstrictor that also stimulates aldosterone release. Aldosterone drives sodium and water retention, raising blood volume and pressure.
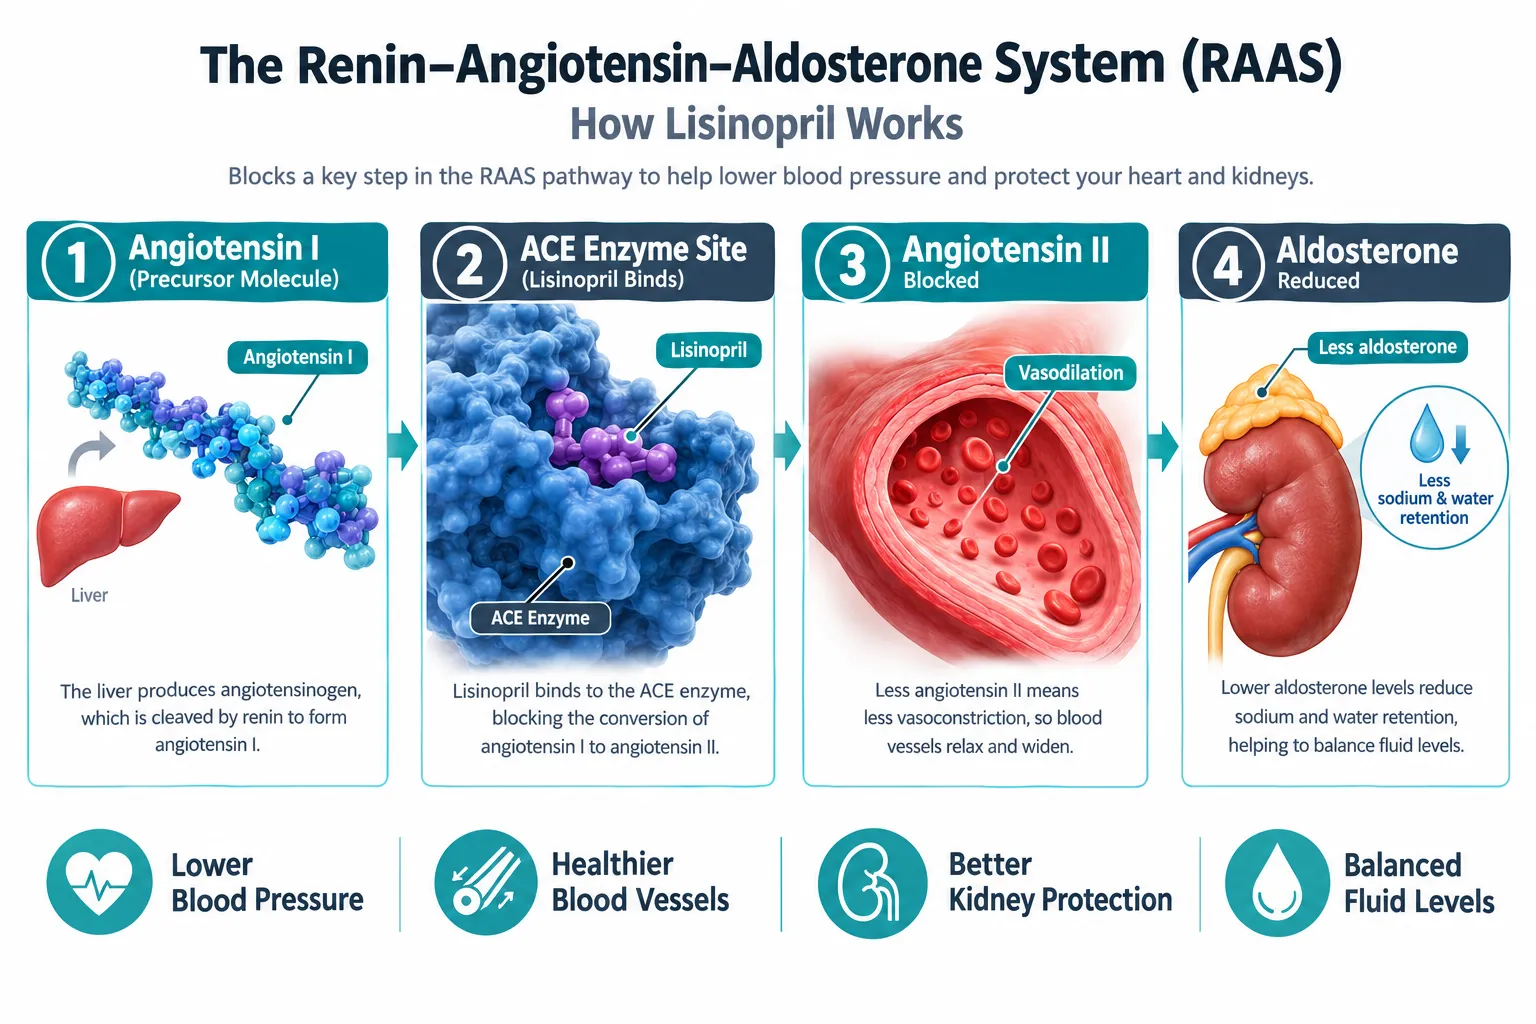
Lisinopril blocks this conversion step directly. As an oral, long-acting ACE inhibitor, it is indicated for hypertension, heart failure, post-myocardial infarction management, and proteinuric diabetic kidney disease. Its pharmacological footprint extends well beyond simple vasodilation:
| Effect | Mechanism | Research Relevance |
|---|---|---|
| Blood-pressure reduction | Reduced angiotensin II, lower vascular resistance | Establishes hemodynamic baseline |
| Natriuresis | Decreased aldosterone, increased sodium excretion | Alters fluid-balance readouts |
| Reduced GFR acutely | Efferent arteriole dilation | Affects creatinine and eGFR endpoints |
| Anti-proteinuric | Reduced intraglomerular pressure | Confounds albumin-to-creatinine ratio data |
For any experiment measuring renal or cardiovascular endpoints, these effects are not background noise, they are active variables. A researcher who introduces a GH secretagogue without first stabilizing ACE inhibitor dosing will be unable to separate peptide-driven changes from ongoing RAAS modulation.
Clinical Evidence Anchoring Lisinopril as the Control Agent
Understanding the evidentiary weight behind lisinopril matters when selecting it as a research control. Its role in ACE inhibitors and research peptides protocols, designing blood-pressure controls around lisinopril and growth-hormone secretagogues, is justified by decades of outcome data, not convention alone.
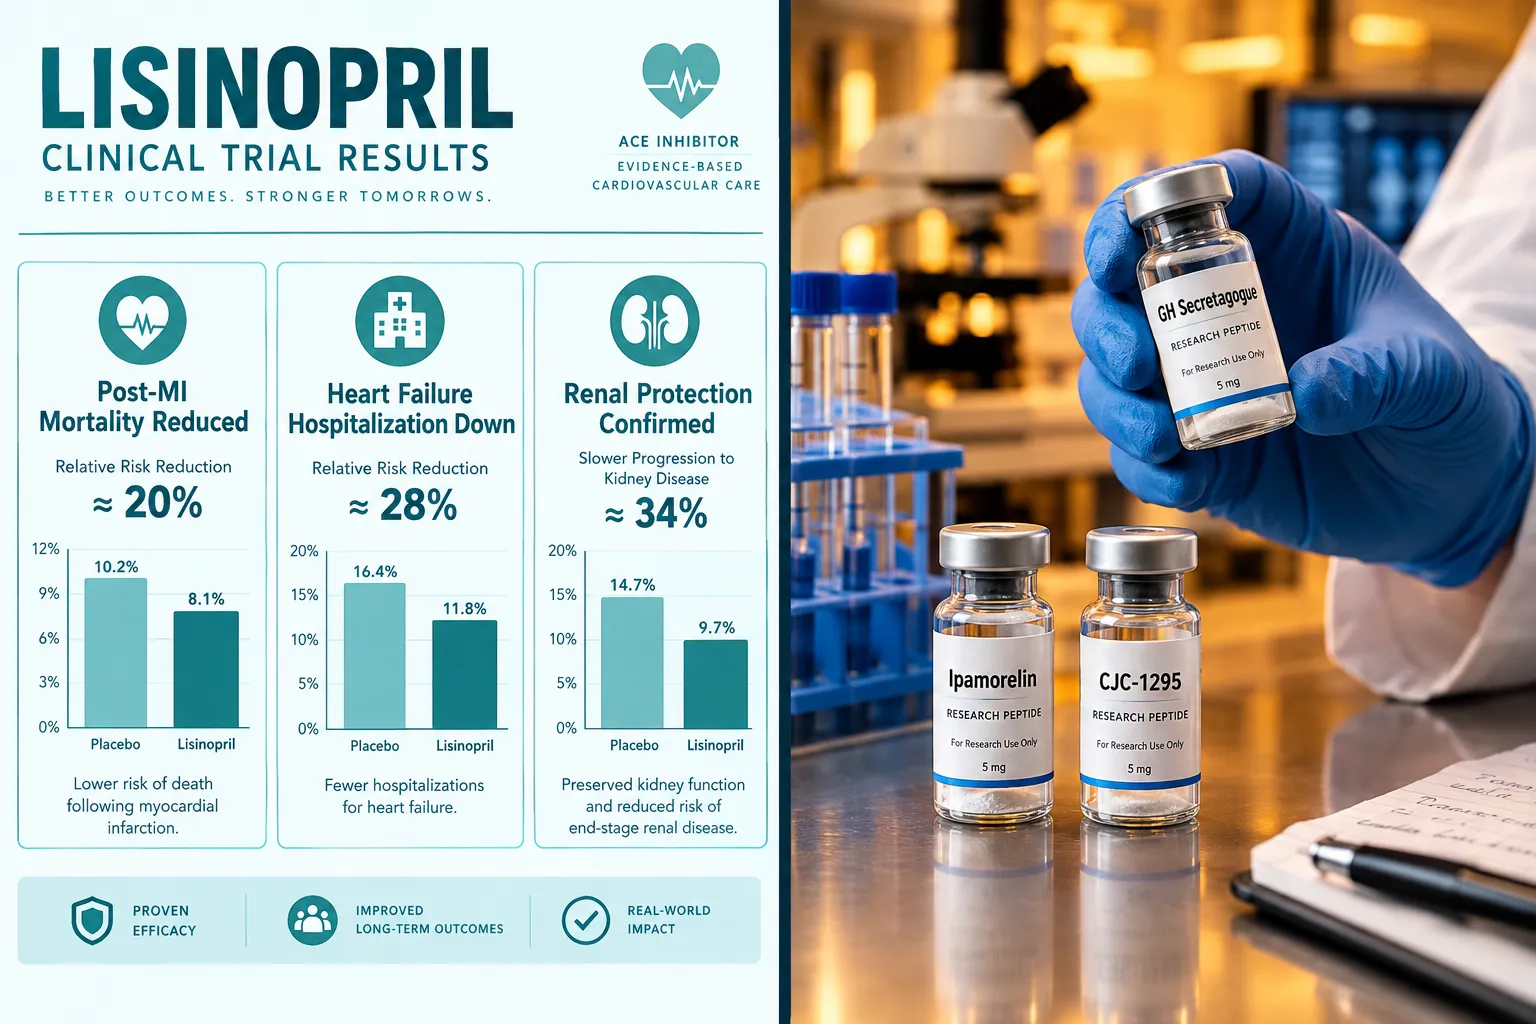
Post-MI data: In the GISSI-3 trial, nearly 19,400 acute myocardial infarction patients were randomized in a factorial design. Lisinopril-treated patients experienced roughly an 11% lower risk of death at six weeks compared with controls (6.4% versus 7.2%), establishing short-term ACE inhibition as a mortality-reducing intervention after cardiac events.
Heart failure dosing: A study in over 3,100 chronic heart-failure patients followed for a median of 46 months found that high-dose lisinopril produced a 12% risk reduction in the combined endpoint of all-cause mortality and hospitalization, and a 24% reduction in heart-failure hospitalizations specifically, compared with low-dose therapy. This supports titrating toward higher target doses when tolerated.
Renal protection: The VA NEPHRON trial enrolled 1,448 patients with type 2 diabetes, elevated urinary-albumin-to-creatinine ratios, and reduced eGFR (30-89.9 mL/min), randomizing them to lisinopril or placebo on a background of losartan. This underscores lisinopril's role in intensive renal-risk management.
Key point: Because lisinopril independently alters urinary albumin excretion and eGFR, any peptide experiment using renal endpoints must document lisinopril dose stability for at least four to six weeks before baseline measurements are taken.
For researchers exploring peptide fundamentals, the Peptides 101 for Research-Use Only Buyers guide provides useful structural and mechanistic context.
GH Secretagogues, Fluid Balance, and Blood-Pressure Risk
Growth-hormone secretagogues, including ipamorelin, CJC-1295, and tesa, stimulate the pituitary to release growth hormone, which in turn elevates IGF-1. This GH-axis activation carries hemodynamic consequences that directly complicate blood-pressure research design.
The fluid-retention problem: GH promotes sodium and water retention through IGF-1-mediated renal tubular effects. In a subject already on lisinopril, which promotes natriuresis, the opposing forces can mask or amplify fluid shifts, making weight and edema measurements unreliable without careful protocol design.
Blood-pressure uncertainty: No identified human study has directly measured blood-pressure changes attributable to ipamorelin alone. That data gap is critical. Safety reviews in 2026 flag that GH-axis secretagogues can raise blood pressure through both fluid retention and sympathomimetic effects of elevated GH. Specific concern exists at stage 2 hypertension (systolic BP above 160 mmHg), where persistent elevation refractory to standard management is considered a serious adverse event warranting reconsideration of peptide use.
Practical monitoring thresholds:
- Blood pressure should be checked at every injection-period review
- Persistent systolic BP above 160 mmHg flags a serious adverse event
- Patients with cardiovascular disease require cardiologist consultation before GH secretagogue exposure
- Fluid retention should be tracked via daily weight and ankle circumference measurements
Researchers interested in the IPA Sermorelin stack research protocols will find these monitoring principles directly applicable. For peptide sourcing considerations, the best peptide supplier resource is worth reviewing alongside purity documentation.
Designing a Valid Research Protocol
Translating the above into a workable experimental framework requires sequencing interventions carefully. The core principle in ACE inhibitors and research peptides design, blood-pressure controls around lisinopril and growth-hormone secretagogues, is that the ACE inhibitor must be the stable foundation, not an active variable.
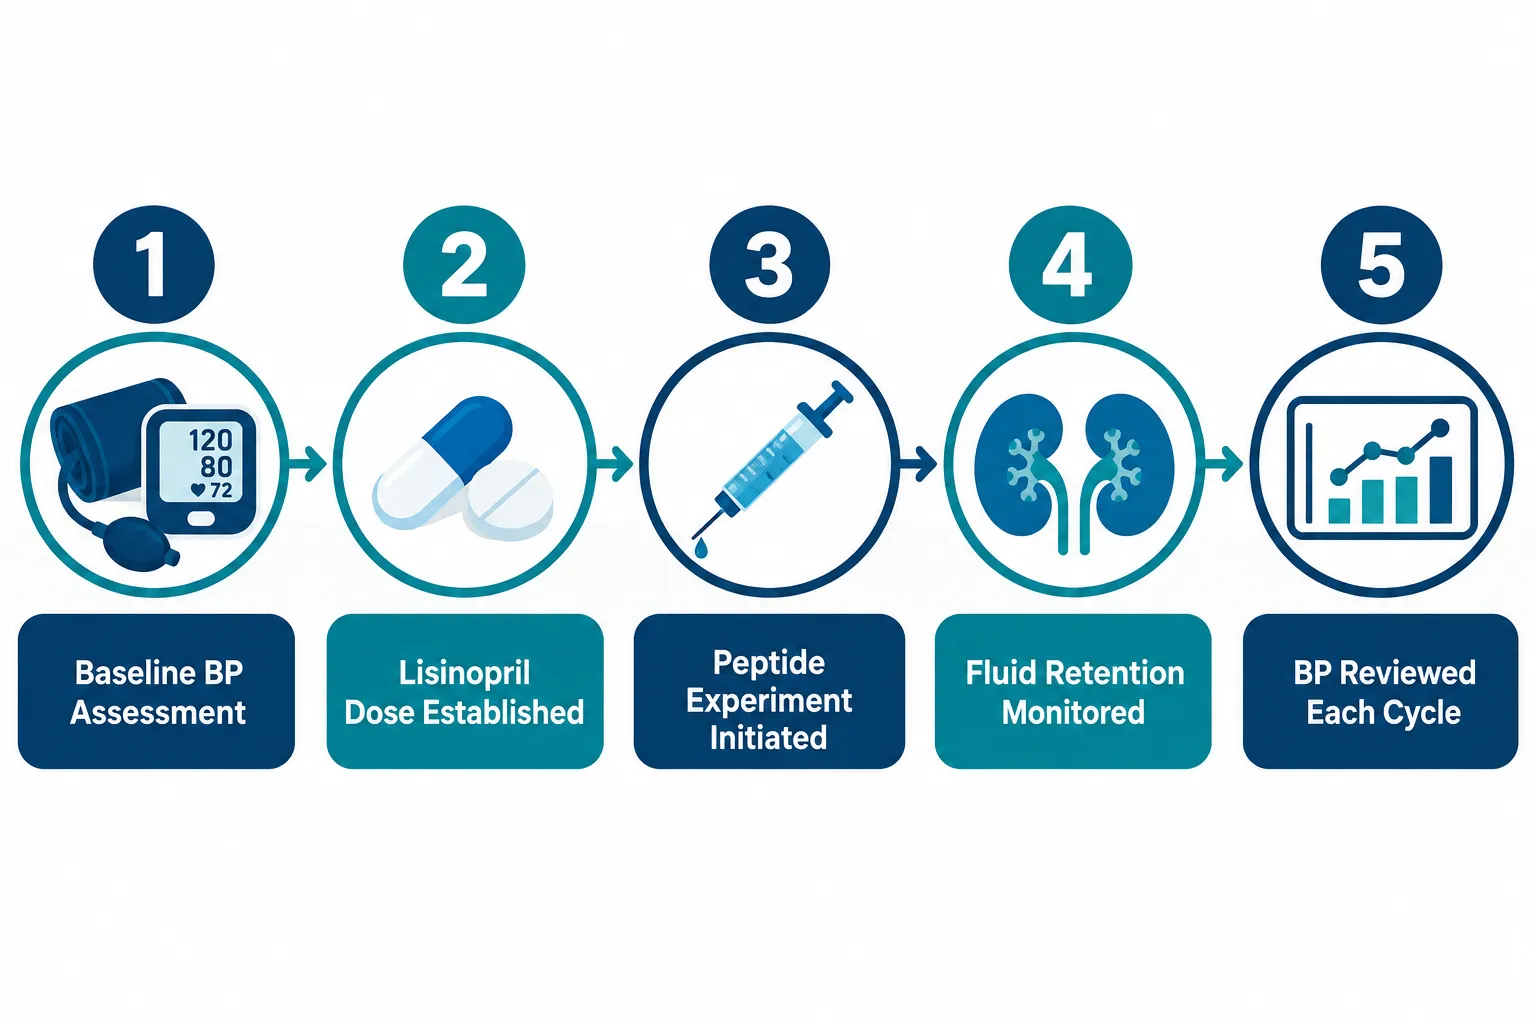
Recommended sequencing:
- Establish baseline hemodynamics, Record resting BP, eGFR, urinary albumin-to-creatinine ratio, and body weight before any intervention.
- Stabilize lisinopril dose, Allow four to six weeks at target dose with three consecutive BP readings within 10 mmHg of each other before proceeding.
- Document renal endpoints at steady state, Creatinine, eGFR, and urinary albumin reflect the lisinopril-stabilized baseline, not a moving target.
- Introduce the GH secretagogue, Begin ipamorelin, CJC-1295, or tesa at the lowest research dose.
- Monitor BP at every injection period, Flag any systolic reading above 160 mmHg as a protocol-defined serious event.
- Track fluid balance independently, Daily weight, edema scoring, and sodium intake logs separate peptide-driven fluid shifts from RAAS modulation.
Researchers studying mitochondrial or cytoprotective peptides alongside cardiovascular endpoints may also find the synergy of LL-37 and SS-31 research relevant, as SS-31 has distinct renal mitochondrial effects that interact with RAAS-modulated tissue. Similarly, SS-31 peptide benefits documentation provides useful comparative context when designing multi-peptide cardiovascular studies.
For researchers sourcing MOTS-c or related metabolic peptides alongside GH secretagogues, the MOTS-c peptide category offers additional product and mechanism information.
Conclusion
Designing rigorous blood-pressure controls in peptide research is not optional, it is the difference between interpretable data and noise. Lisinopril's well-characterized effects on RAAS, fluid balance, and renal endpoints make it a logical anchor for cardiovascular control arms, but only when its dose is stabilized before GH secretagogue introduction. Ipamorelin, CJC-1295, and tesa all carry real, if incompletely quantified, risks of fluid retention and blood-pressure elevation that can obscure experimental signals or create genuine safety events.
Actionable next steps for researchers in 2026:
- Audit existing protocols to confirm lisinopril dose stability windows are documented before baseline renal measurements
- Add systolic BP above 160 mmHg as a pre-specified serious adverse event criterion in any GH secretagogue study
- Track fluid balance with daily weight logs, not just clinical BP readings
- Consult cardiology input for any subject with pre-existing cardiovascular disease before GH-axis peptide exposure
- Review purity certificates for all research peptides to ensure experimental variables are limited to pharmacology, not contaminant effects


Leave a Reply
Want to join the discussion?Feel free to contribute!