

Peptide Drug Interactions: How Research Peptides Interact With Common Medications
Fewer than 20% of research peptides currently in active laboratory use have been formally evaluated for drug-drug interactions, a gap that carries real consequences as these compounds move closer to clinical and wellness applications. Understanding Peptide Drug Interactions: How Research Peptides Interact With Common Medications is no longer a niche concern for pharmacologists alone. Researchers, clinicians, and informed consumers need a clear, evidence-informed framework for thinking about these risks in 2026.
Key Takeaways
- Most research peptides have limited CYP enzyme involvement, but this does not mean they are interaction-free.
- GLP-1 type peptides and growth hormone secretagogues carry the highest real-world interaction risk, particularly with insulin and antidiabetic drugs.
- Peptide size, structural motifs, and route of administration all influence interaction potential.
- Formal regulatory guidance on peptide drug interactions remains incomplete as of mid-2026.
- Researchers and clinicians should apply a precautionary framework, especially in patients on anticoagulants, cardiovascular drugs, or CNS medications.
Why Peptide Drug Interactions Are Poorly Understood
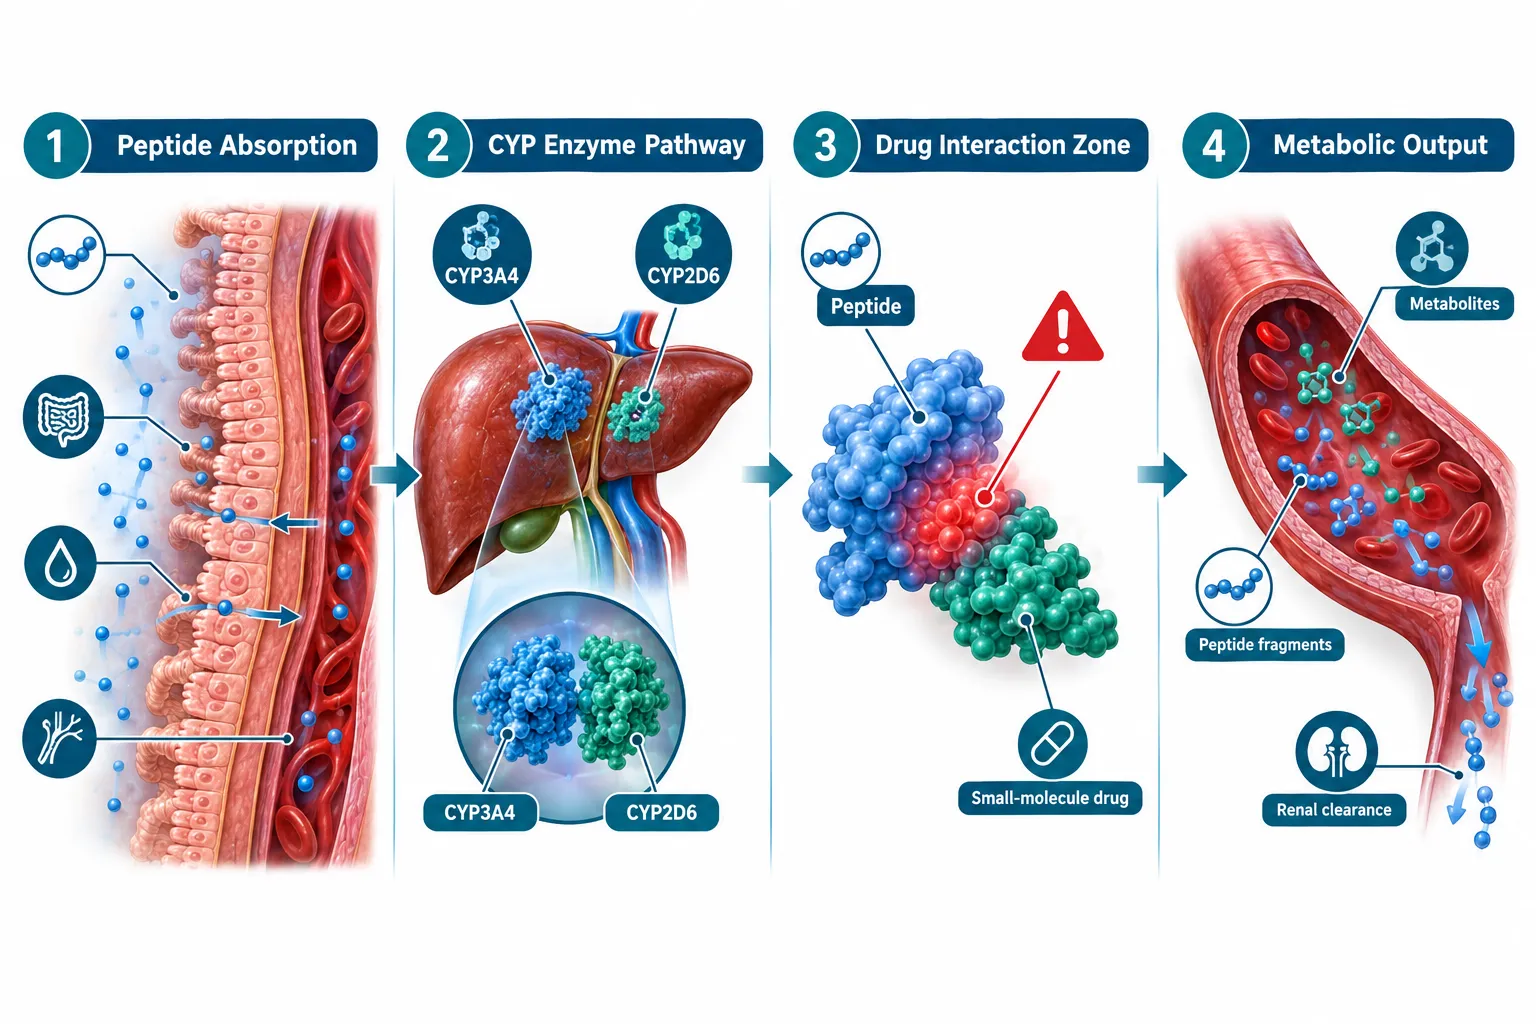
The science of peptide pharmacokinetics has advanced rapidly, but the field of peptide-drug interactions has not kept pace. A 2025 clinical review confirmed that formal guidance on this topic is still largely absent, leaving researchers to extrapolate from limited mechanistic data.
One reason for the knowledge gap is structural. Unlike small-molecule drugs, most peptides are broken down by proteases rather than by cytochrome P450 (CYP) liver enzymes. This means the classic drug interaction framework, built around CYP3A4, CYP2D6, and related pathways, does not map cleanly onto peptide pharmacology.
However, minimal CYP involvement is not the same as zero interaction risk. Peptides can still alter drug behavior through:
- Receptor-level competition or synergy
- Hormonal and metabolic downstream effects
- Changes in gastric emptying, fluid balance, or hemodynamics
- Indirect modulation of enzyme expression over time
A humanized mouse model published in 2025 confirmed low CYP-mediated drug-drug interaction (DDI) risk for larger peptides, and a 2024-2025 pharmacological interaction matrix analysis found that risk correlates with peptide size and the presence of non-peptide motifs. Smaller peptides with synthetic or hybrid structures carry meaningfully higher interaction potential.
For researchers exploring polypeptide peptides in cardiometabolic models, understanding this distinction is foundational.
"The absence of CYP involvement creates a false sense of safety. The real interaction risks for research peptides lie elsewhere, in hormonal cascades, receptor overlap, and hemodynamic shifts."
Peptide Drug Interactions: How Research Peptides Interact With Common Medications in Practice
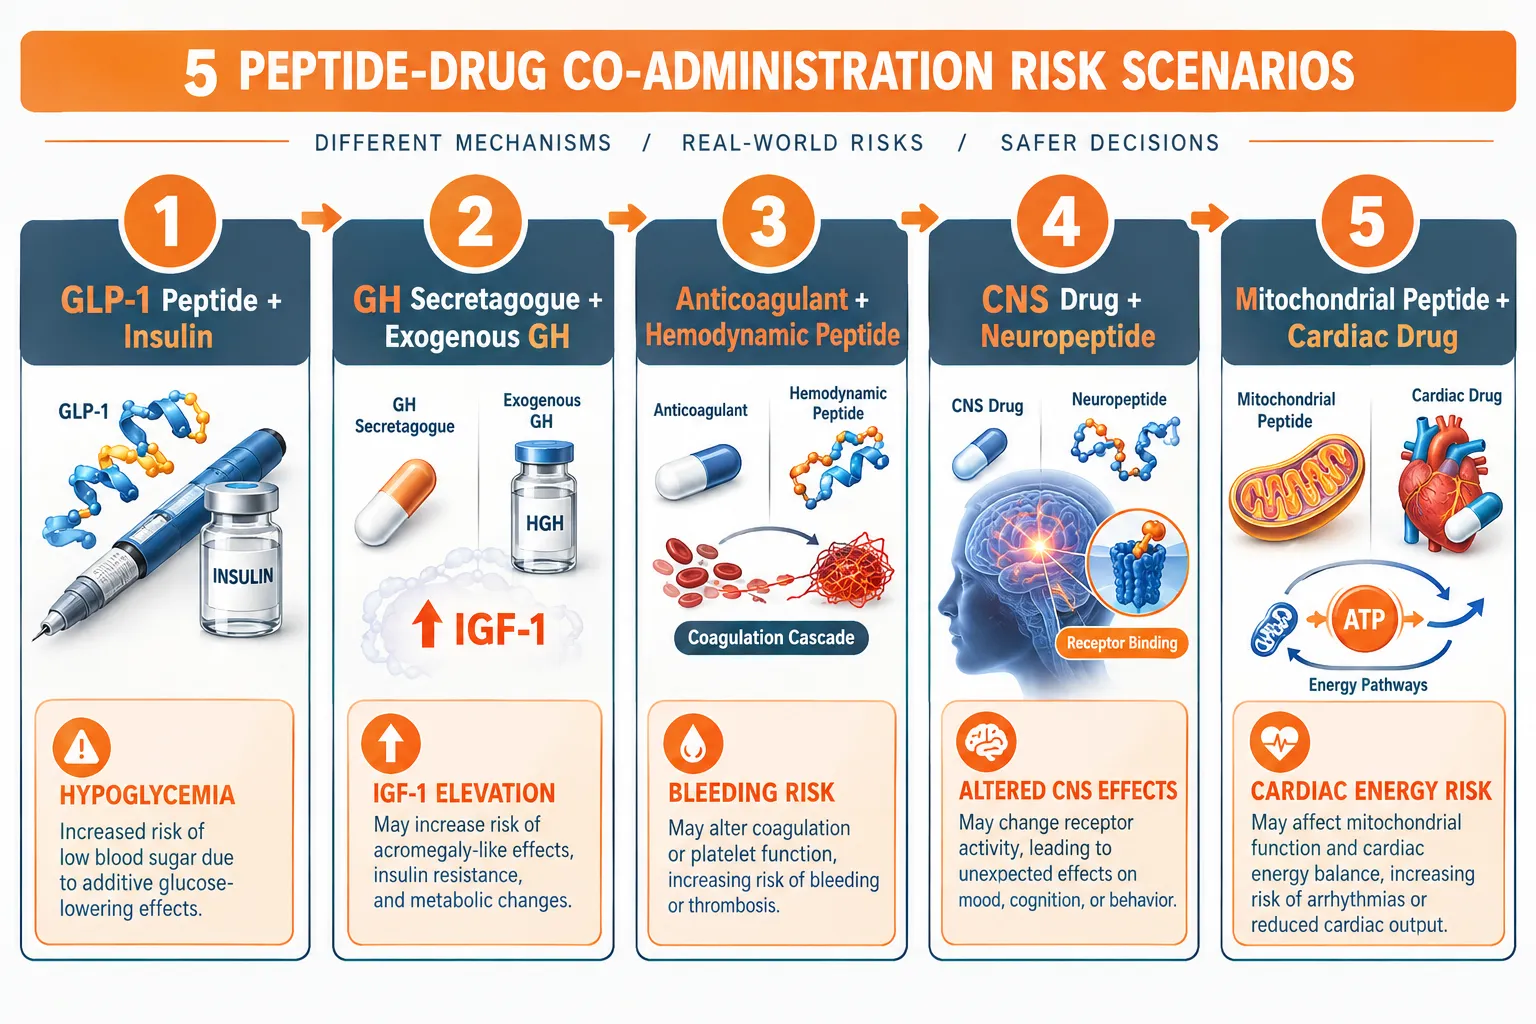
The most clinically significant interaction scenarios involve four major drug categories. Each presents a distinct mechanism and risk profile.
Insulin and Antidiabetic Drugs
GLP-1 peptides and growth hormone secretagogues can substantially amplify the glucose-lowering effects of insulin, metformin, and sulfonylureas. Co-administration creates a compounding hypoglycemia risk that is not always predictable from either agent alone. This is one of the best-documented interaction categories in the research peptide space.
Growth Hormone and IGF-1 Pathways
Peptides that stimulate endogenous growth hormone release, including several widely studied secretagogues, should generally not be combined with exogenous growth hormone. The additive effect on IGF-1 elevation carries metabolic and cardiovascular consequences. This combination is broadly flagged as one to avoid in research protocols.
For context on how one mitochondrial-targeted peptide is evaluated in isolation, see SS-31 10mg research peptide considerations.
Anticoagulants and Cardiovascular Medications
Even when CYP pathways are uninvolved, peptides that alter hemodynamics, endothelial function, or fluid balance can change the effective exposure of anticoagulants like warfarin or direct oral anticoagulants (DOACs). This is a pharmacodynamic interaction rather than a pharmacokinetic one, and it is frequently overlooked.
| Drug Class | Interaction Type | Risk Level |
|---|---|---|
| Insulin / Antidiabetics | Pharmacodynamic (additive) | High |
| Exogenous Growth Hormone | Hormonal cascade (additive) | High |
| Anticoagulants / CVD drugs | Hemodynamic / fluid balance | Moderate-High |
| CNS Medications | Receptor-level overlap | Moderate (context-dependent) |
CNS and Neurological Drugs
Neuropeptides and peptides with CNS activity, including some under active Semax research protocols, may interact with antidepressants, anxiolytics, or antiepileptics through receptor-level mechanisms. The interaction data here is sparse, and safety advocacy groups flagged in June 2026 that interaction risk for wellness and "PCAC" peptides remains largely unknown.
Regulatory Context and What It Means for Researchers

The regulatory landscape shifted meaningfully in the first half of 2026. In March and April 2026, the FDA took enforcement action against sellers of "research-use-only" GLP-1 analog peptides, signaling a harder line on compounds that blur the boundary between research chemicals and unapproved therapeutics. Then, in July 2026, a regulatory framework update confirmed that while CYP involvement for most peptides remains minimal, caution is warranted in high-risk patient populations.
On July 28, 2026, the FDA also shifted its scientific position on generic peptide products, a move with downstream implications for how interaction data will be required and evaluated going forward.
For researchers sourcing compounds, working with lab tested peptides that carry documented purity profiles is a baseline requirement. Impurities and degradation products can introduce interaction variables that are entirely separate from the peptide's intended pharmacology.
Researchers studying endocrine-active compounds should also review how peptides interface with receptor biology, as covered in the analysis of peptides and polypeptides in endocrine pharmacology.
Practical precautions for 2026 research contexts:
- Document all co-administered agents before initiating any peptide protocol
- Apply heightened scrutiny when subjects are on insulin, anticoagulants, or cardiovascular drugs
- Treat absence of CYP data as absence of evidence, not evidence of absence
- Monitor for pharmacodynamic interactions even when pharmacokinetic data is reassuring
- Consult updated FDA guidance before working with GLP-1 class analogs
Conclusion
Peptide Drug Interactions: How Research Peptides Interact With Common Medications represent a genuine and underappreciated safety domain. The low CYP involvement of most peptides does not eliminate interaction risk, it simply shifts where that risk lives. The highest-priority concerns in 2026 involve GLP-1 and growth hormone-related peptides combined with insulin or exogenous GH, anticoagulants in patients with hemodynamic-active peptides, and CNS drugs paired with neuropeptides.
Actionable next steps for researchers and practitioners:
- Build a complete co-medication profile before any peptide protocol begins.
- Prioritize compounds with documented purity and available pharmacological data.
- Monitor the FDA's evolving position on peptide classification, particularly for GLP-1 analogs.
- Apply pharmacodynamic interaction logic even when pharmacokinetic data is absent.
- Revisit interaction assumptions regularly, the evidence base is moving fast in 2026.
The field is advancing. Staying ahead of the interaction risk curve is not optional, it is foundational to responsible research practice.


Leave a Reply
Want to join the discussion?Feel free to contribute!