Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: enclomiphene citrate

Enclomiphene Base vs Enclomiphene Citrate: Solubility, Salt-Form Identity, and Analytical Method Selection

Enclomiphene Base vs Enclomiphene Citrate: Solubility, Salt-Form Identity, and Analytical Method Selection

November 1, 2026/0 Comments/in Uncategorized/by

A single misidentified salt form in a batch record can invalidate an entire HPLC assay, trigger potency miscalculations, and compromise regulatory filings. That is the practical stakes behind understanding Enclomiphene Base vs Enclomiphene Citrate: Solubility, Salt-Form Identity, and Analytical Method Selection, a topic that sits at the intersection of medicinal chemistry, formulation science, and quality control. Whether you are reviewing a certificate of analysis, developing a dissolution method, or selecting a reference standard, the distinction between these two chemical identities is not cosmetic. It is foundational.

Key Takeaways

  • Enclomiphene base and enclomiphene citrate share the same active stereoisomer but differ in molecular weight, counterion, and solubility profile, all of which affect assay calculations.
  • Enclomiphene citrate shows superior aqueous solubility and is the preferred pharmaceutical salt form; the base exhibits greater lipophilicity and requires organic solvents for reliable dissolution.
  • Reverse-phase HPLC with UV detection at 254 nm is the primary analytical platform for both forms, but mobile phase composition and reference standard selection must match the specific salt identity.
  • Salt-form identity must be confirmed before any quantitative analysis; using a base-form reference standard against a citrate-form sample introduces a systematic mass correction error if not accounted for.
  • Proper batch documentation should explicitly state salt form, CAS number, and conversion factor to prevent downstream analytical and formulation errors.

Salt-Form Identity: What Sets Enclomiphene Base Apart from Enclomiphene Citrate
Salt-Form Identity: What Sets Enclomiphene Base Apart from Enclomiphene Citrate

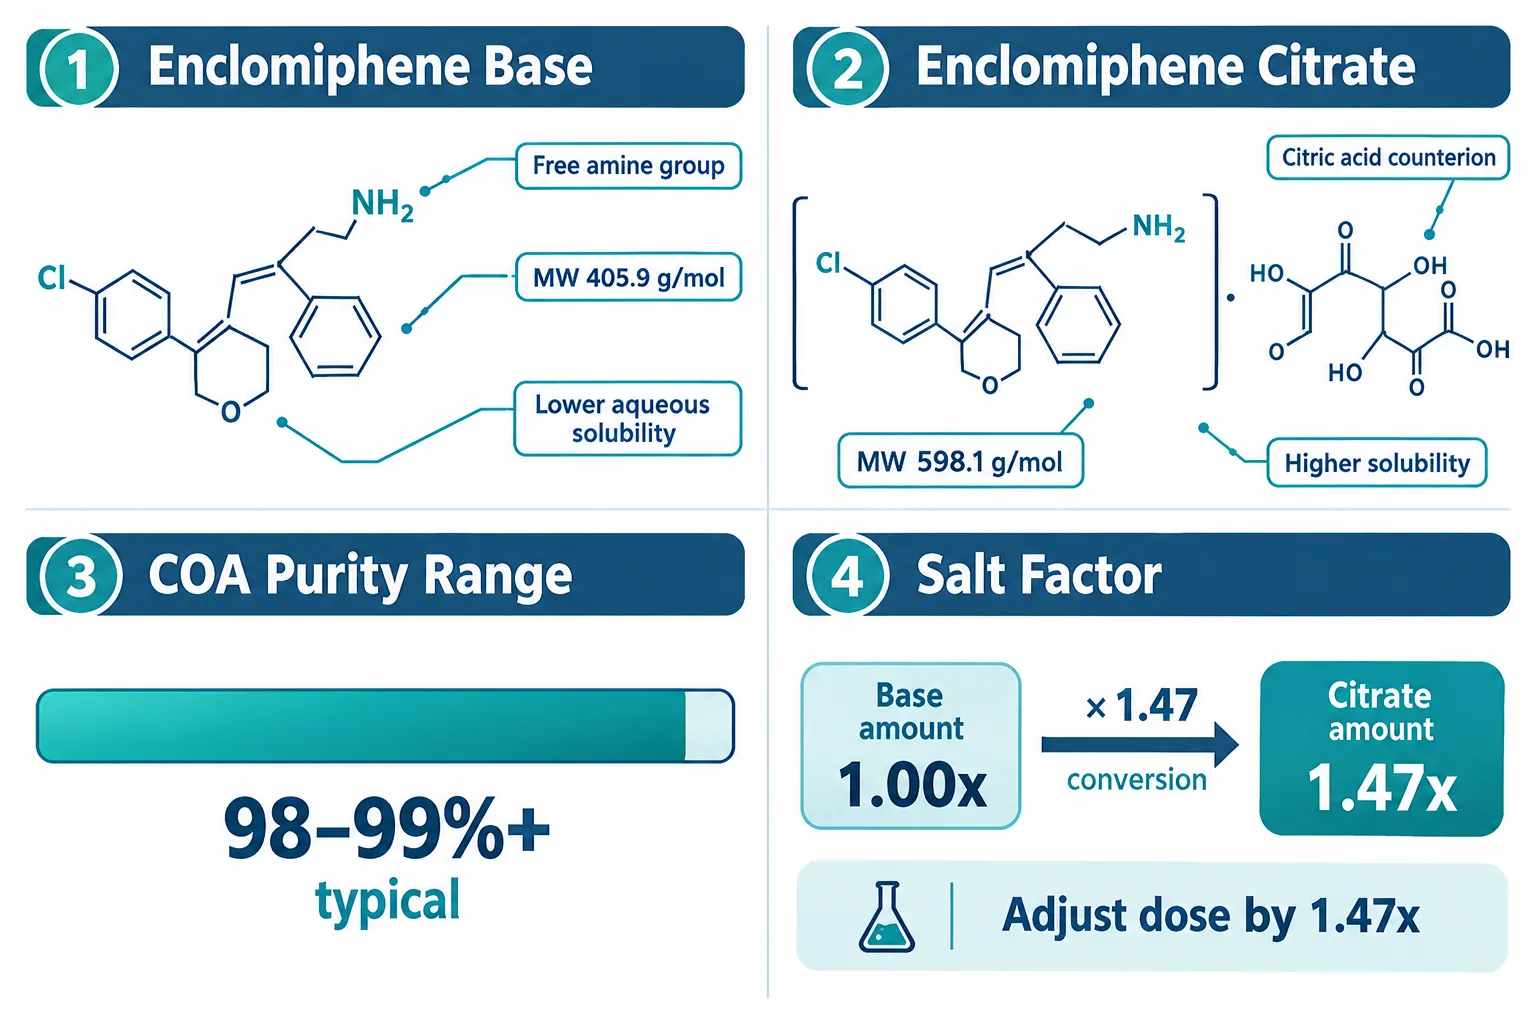
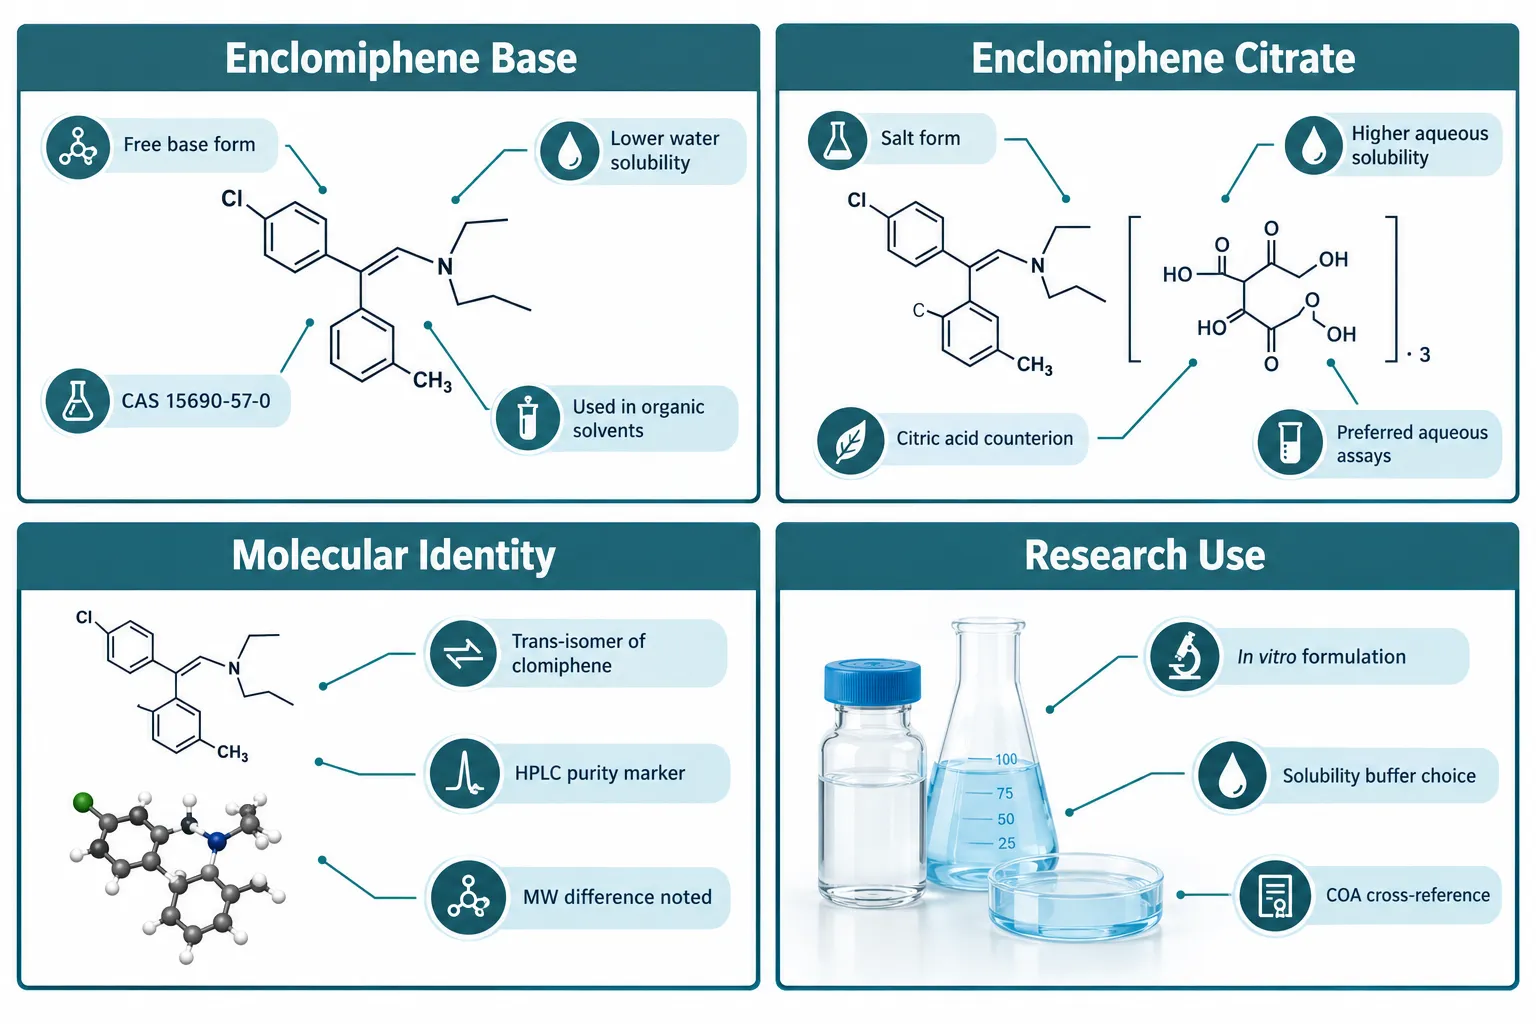
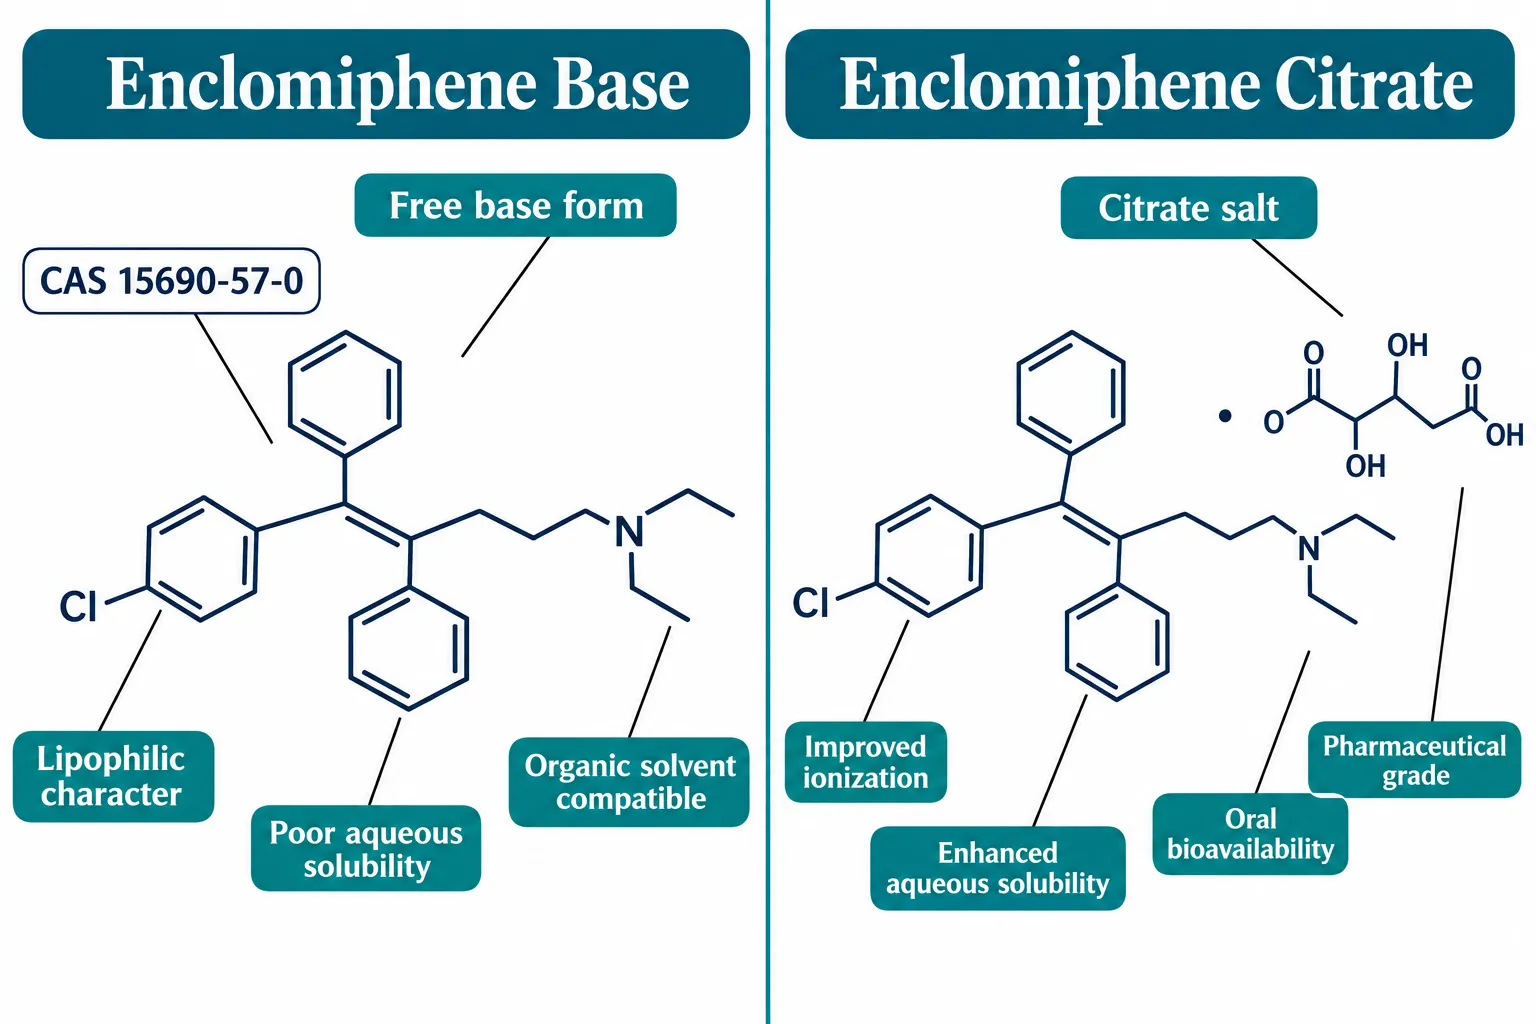
Enclomiphene is the trans-geometric isomer of clomiphene, a selective estrogen receptor modulator (serm) used in research and clinical contexts related to gonadotropin stimulation. The free base form (CAS 15690-57-0) is the parent compound, a lipophilic, crystalline solid with limited water solubility. Enclomiphene citrate is the pharmaceutically preferred salt formed by combining the base with citric acid, producing a more ionizable, water-compatible compound with a higher molecular weight.

This distinction in salt-form identity carries direct consequences for every downstream process:

Property Enclomiphene Base Enclomiphene Citrate
Molecular weight ~405.9 g/mol ~598.1 g/mol
Aqueous solubility Poor Moderate to good
Organic solvent solubility High Moderate
Ionization in acidic media Low Enhanced
Primary pharmaceutical use Reference, synthesis Oral formulation

The molecular weight difference alone, nearly 200 g/mol, means that a researcher who weighs 10 mg of citrate salt and calculates potency against a free-base standard will introduce a significant error unless a salt conversion factor is applied. This is not a theoretical concern; it is one of the most common analytical mistakes in compound characterization workflows.

Researchers working with serms and related hormonal compounds in research settings should also familiarize themselves with combined peptide protocols, such as those discussed in guides covering serm, Ipamorelin, and CJC-1295 combinations, where compound identity and purity have similar downstream relevance.


Solubility Profiles: Enclomiphene Base vs Enclomiphene Citrate in Aqueous and Organic Systems
Solubility Profiles: Enclomiphene Base vs Enclomiphene Citrate in Aqueous and Organic Systems

Solubility behavior is arguably the most consequential physicochemical difference between these two forms, affecting dissolution testing, formulation design, and analytical sample preparation.

Aqueous Solubility

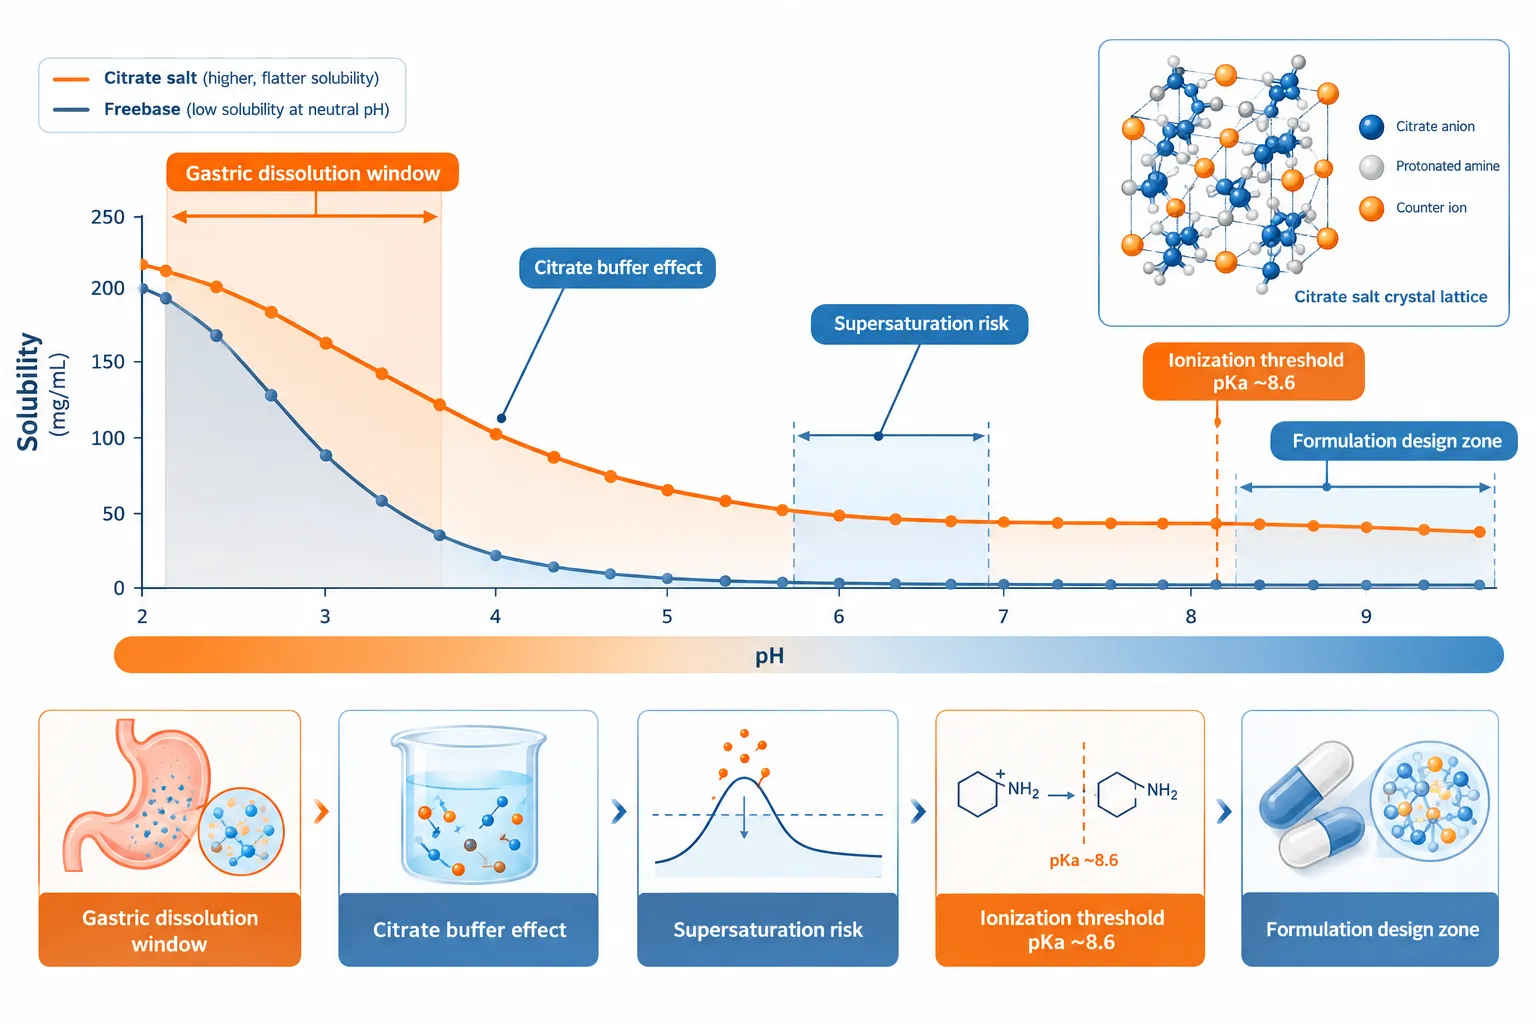
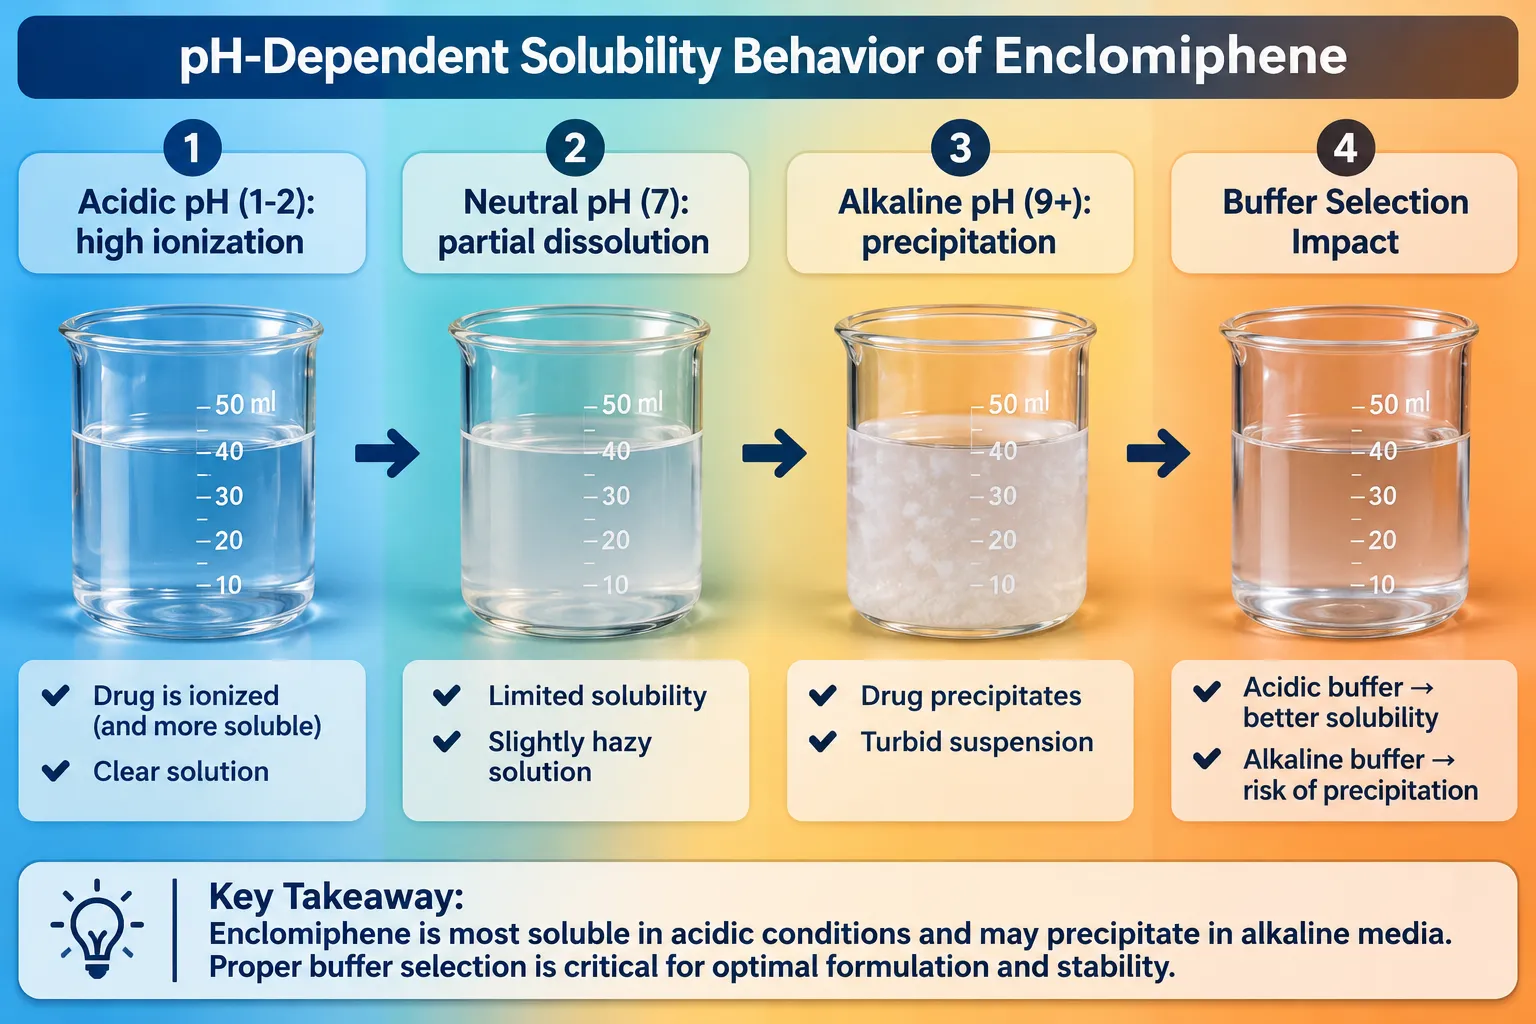
Enclomiphene citrate demonstrates meaningfully better water solubility compared to the base. This is a direct result of the citrate counterion improving ionization under acidic to neutral pH conditions. In simulated gastric fluid (pH ~1.2), enclomiphene citrate dissolves readily, which supports its use in oral solid dosage forms. As pH increases toward neutral and alkaline ranges, solubility decreases, a classic behavior for weak-base salt forms.

Enclomiphene base, by contrast, exhibits poor aqueous solubility across most physiologically relevant pH ranges. Its log P (lipophilicity index) is substantially higher, placing it firmly in the category of poorly water-soluble compounds that require solubility enhancement strategies for formulation.

Organic Solvent Solubility

The base form dissolves well in common organic solvents including methanol, ethanol, dimethyl sulfoxide (DMSO), and acetonitrile. Enclomiphene citrate is soluble in these solvents as well, though sometimes at lower concentrations due to the salt's greater polarity.

Practical implication: When preparing HPLC stock solutions, both forms are typically dissolved in methanol or acetonitrile. However, the diluent choice for final sample preparation, particularly in dissolution testing or bioavailability studies, must reflect the expected physiological environment, which favors aqueous systems compatible with the citrate salt form.

This parallels solubility considerations seen across other research compound classes. For researchers sourcing verified compounds, guidance on where to buy peptides and research compounds remains relevant context for understanding purity and salt-form documentation standards.


Analytical Method Selection for Enclomiphene Base vs Enclomiphene Citrate: Solubility, Salt-Form Identity, and Analytical Method Selection
Analytical Method Selection for Enclomiphene Base vs Enclomiphene Citrate: Solubility, Salt-Form Identity, and Analytical Met

Reverse-phase HPLC is the established analytical platform for enclomiphene quantification, applicable to both salt forms. However, several method parameters must be calibrated specifically to the salt form being analyzed.

Chromatographic Considerations

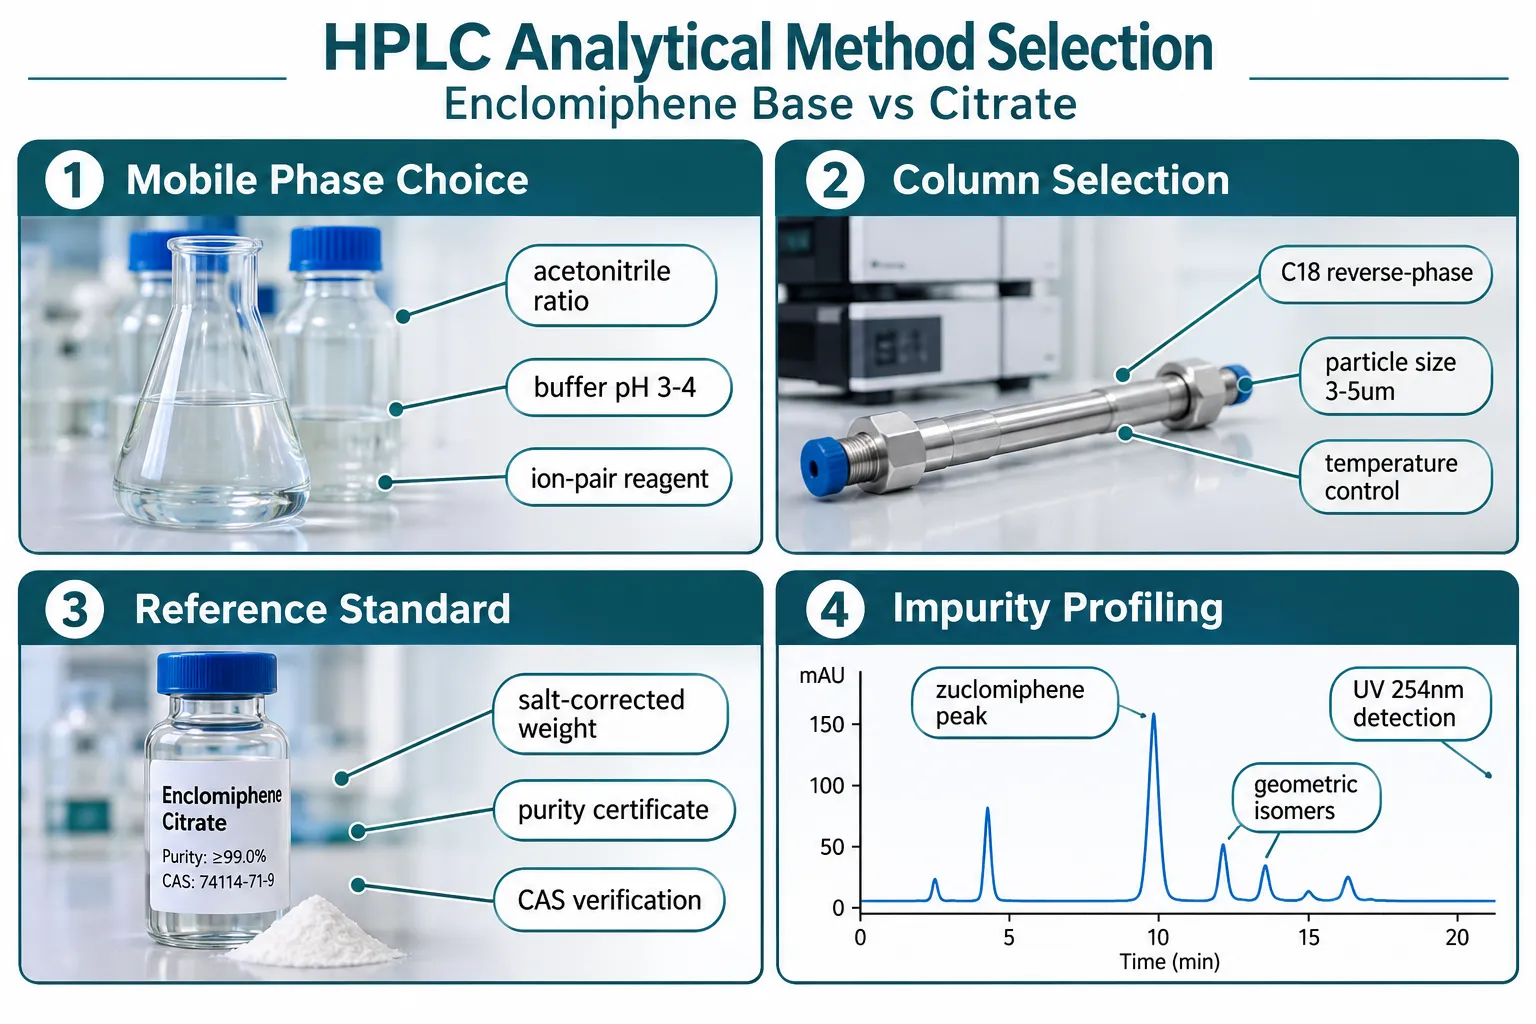
Column: A C18 reverse-phase column with 3-5 micron particle size is standard. The hydrophobic character of the enclomiphene core is well-retained under typical reversed-phase conditions.

Mobile phase: Gradient elution using acetonitrile and an aqueous buffer (pH 3.0-4.0, typically ammonium formate or phosphate-based) provides adequate resolution. The slightly acidic buffer suppresses ionization of the amine group, sharpening peak shape for both base and citrate forms.

Detection: UV detection at 254 nm exploits the compound's aromatic chromophore. Mass spectrometry (MS) detection adds specificity for isomer confirmation and impurity identification.

Reference Standard Selection and Salt Correction

This is the most critical method parameter. When the reference standard and the test sample are in different salt forms, the calculation must include a correction factor:

Correction factor = MW of sample salt form / MW of reference standard form

Failing to apply this factor when using a base standard to quantify a citrate sample will overstate purity by approximately 32%. Certificates of analysis should always state the salt form and any applied correction.

Isomer Control: Zuclomiphene Impurity

Because enclomiphene is the trans-isomer and zuclomiphene is the cis-isomer, isomeric purity testing is a regulatory and quality expectation. Both isomers elute under standard C18 conditions, but their resolution is method-dependent. A well-developed method should achieve baseline resolution between enclomiphene and zuclomiphene peaks. HPLC-MS allows definitive isomer confirmation where UV alone may be insufficient.

Researchers familiar with impurity profiling in peptide compounds, such as those reviewing peptide supplier comparisons and interpreting analytical data from PeptideTech and PeptideSC, will recognize that the same documentation rigor applies here. Similar QC principles apply when sourcing compounds like Sermorelin, where method-verified purity is essential.

Batch Documentation Requirements

Every batch record involving enclomiphene should include:

  • Full IUPAC name and CAS number for the specific salt form
  • Molecular weight used in all potency calculations
  • Salt conversion factor if reference standard and sample forms differ
  • HPLC method version tied to the validated salt form
  • Isomeric purity (enclomiphene vs zuclomiphene ratio)

These documentation standards are consistent with broader expectations for research-grade compounds, including GLP-class peptide compounds where identity confirmation is required before use.


Conclusion

The distinction between enclomiphene base and enclomiphene citrate is not a naming convention, it is a chemically and analytically significant difference that affects solubility, molecular weight, reference standard selection, and every quantitative calculation derived from HPLC data. In 2026, as research into selective estrogen receptor modulators continues to expand, getting salt-form identity right from the beginning of any analytical workflow is both a quality imperative and a practical necessity.

Actionable next steps:

  1. Confirm the exact salt form on your certificate of analysis before any gravimetric or volumetric preparation.
  2. Match your reference standard to your sample salt form, or apply and document a verified conversion factor.
  3. Validate your HPLC method specifically for the salt form in use, including resolution of the zuclomiphene impurity peak.
  4. Ensure all batch documentation explicitly records CAS number, molecular weight, and salt-form identity.
  5. When sourcing reference-grade compounds, request isomeric purity data alongside standard purity certificates.
https://www.puretestedpeptides.com/wp-content/uploads/2026/11/enclomiphene-base-vs-enclomiphene-citrate-solubility-salt-form-identity-and-anal.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-11-01 14:03:332026-11-01 14:03:33Enclomiphene Base vs Enclomiphene Citrate: Solubility, Salt-Form Identity, and Analytical Method Selection
Finasteride and Enclomiphene Co-Administration: Evaluating DHT, LH Pulsatility, and Spermatogenesis in Rodent Models

Finasteride and Enclomiphene Co-Administration: Evaluating DHT, LH Pulsatility, and Spermatogenesis in Rodent Models

October 27, 2026/0 Comments/in Uncategorized/by

Blocking 5-alpha reductase while simultaneously stimulating gonadotropin release creates a biochemical tension that preclinical researchers have not yet formally mapped. As of 2026, no published rodent study has directly examined finasteride and enclomiphene co-administration with concurrent measurement of DHT, LH pulsatility, and spermatogenesis, yet the mechanistic logic for doing so is compelling. Understanding how 5-alpha reductase inhibitors modify endocrine feedback loops when evaluating enclomiphene citrate gonadal restoration protocols is the central challenge this research gap presents.

Key Takeaways

  • No published rodent model to date has simultaneously tested finasteride and enclomiphene co-administration while tracking DHT, LH pulse dynamics, and spermatogenesis.
  • Finasteride suppresses conversion of testosterone to DHT, which preclinical data links to impaired spermatogenic recovery even when serum testosterone is preserved or elevated.
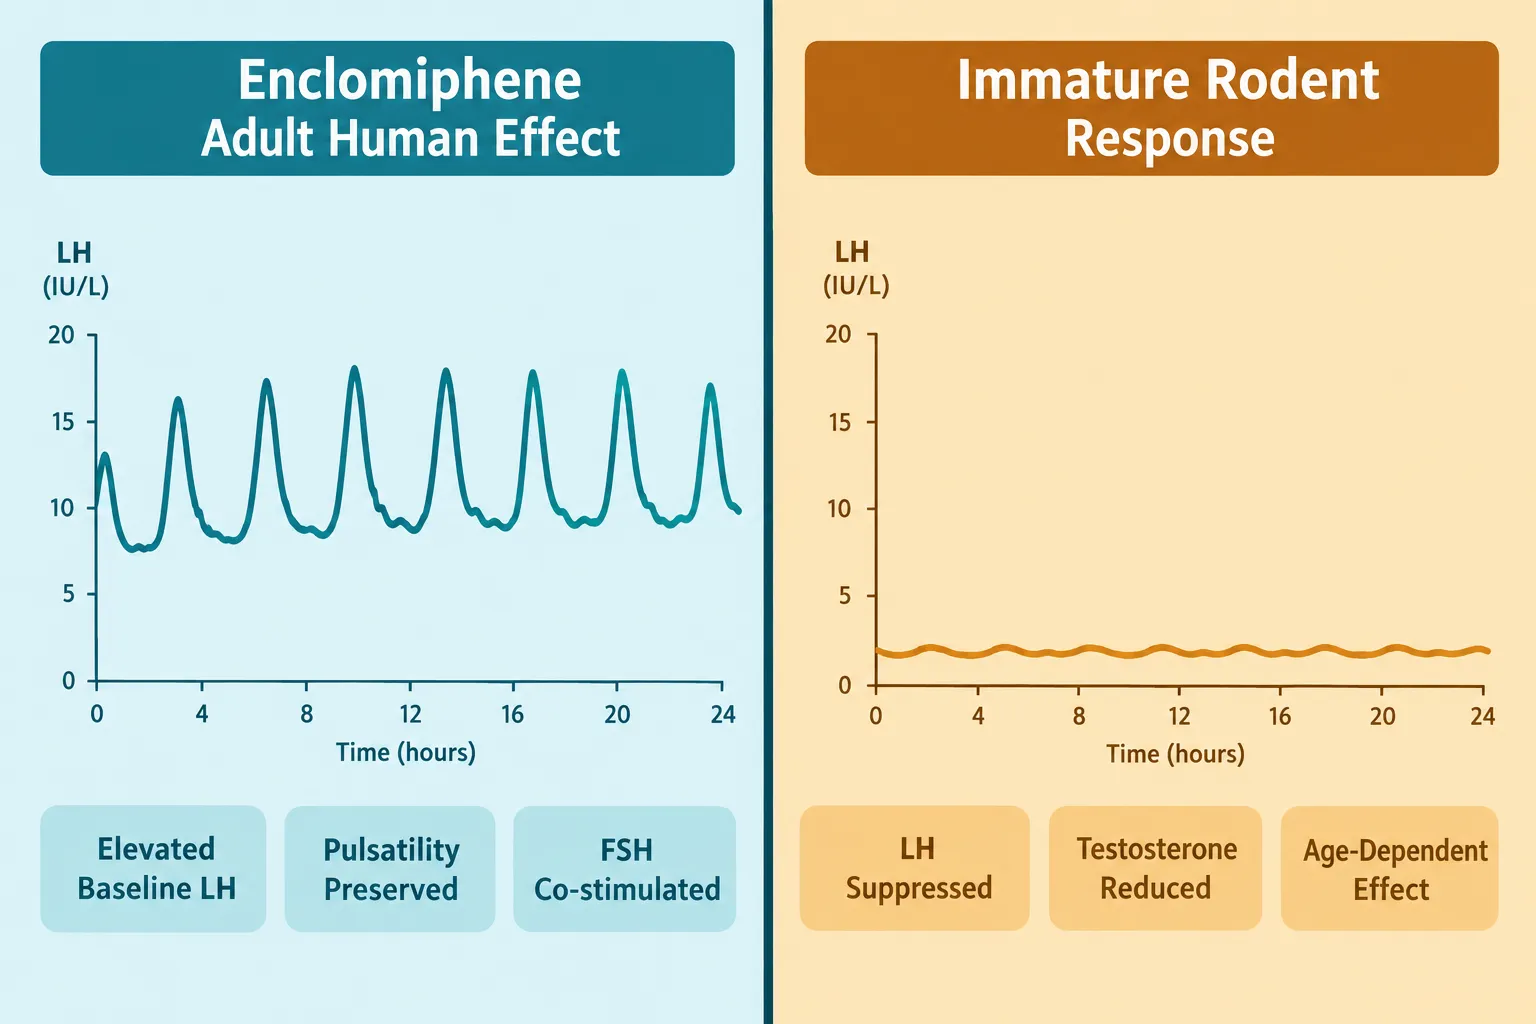
  • Enclomiphene's effect on LH is age- and species-dependent: it elevates LH in adult humans but suppresses it in immature rodents at certain doses.
  • Co-administration could produce elevated systemic testosterone alongside reduced intratesticular DHT, a combination with unpredictable net effects on sperm production.
  • Rigorous future studies require adult rodent models, frequent LH pulse sampling, intratesticular hormone measurements, and histologic evaluation of seminiferous tubules.

How 5-Alpha Reductase Inhibition Disrupts Endocrine Feedback Loops

How 5-Alpha Reductase Inhibition Disrupts Endocrine Feedback Loops

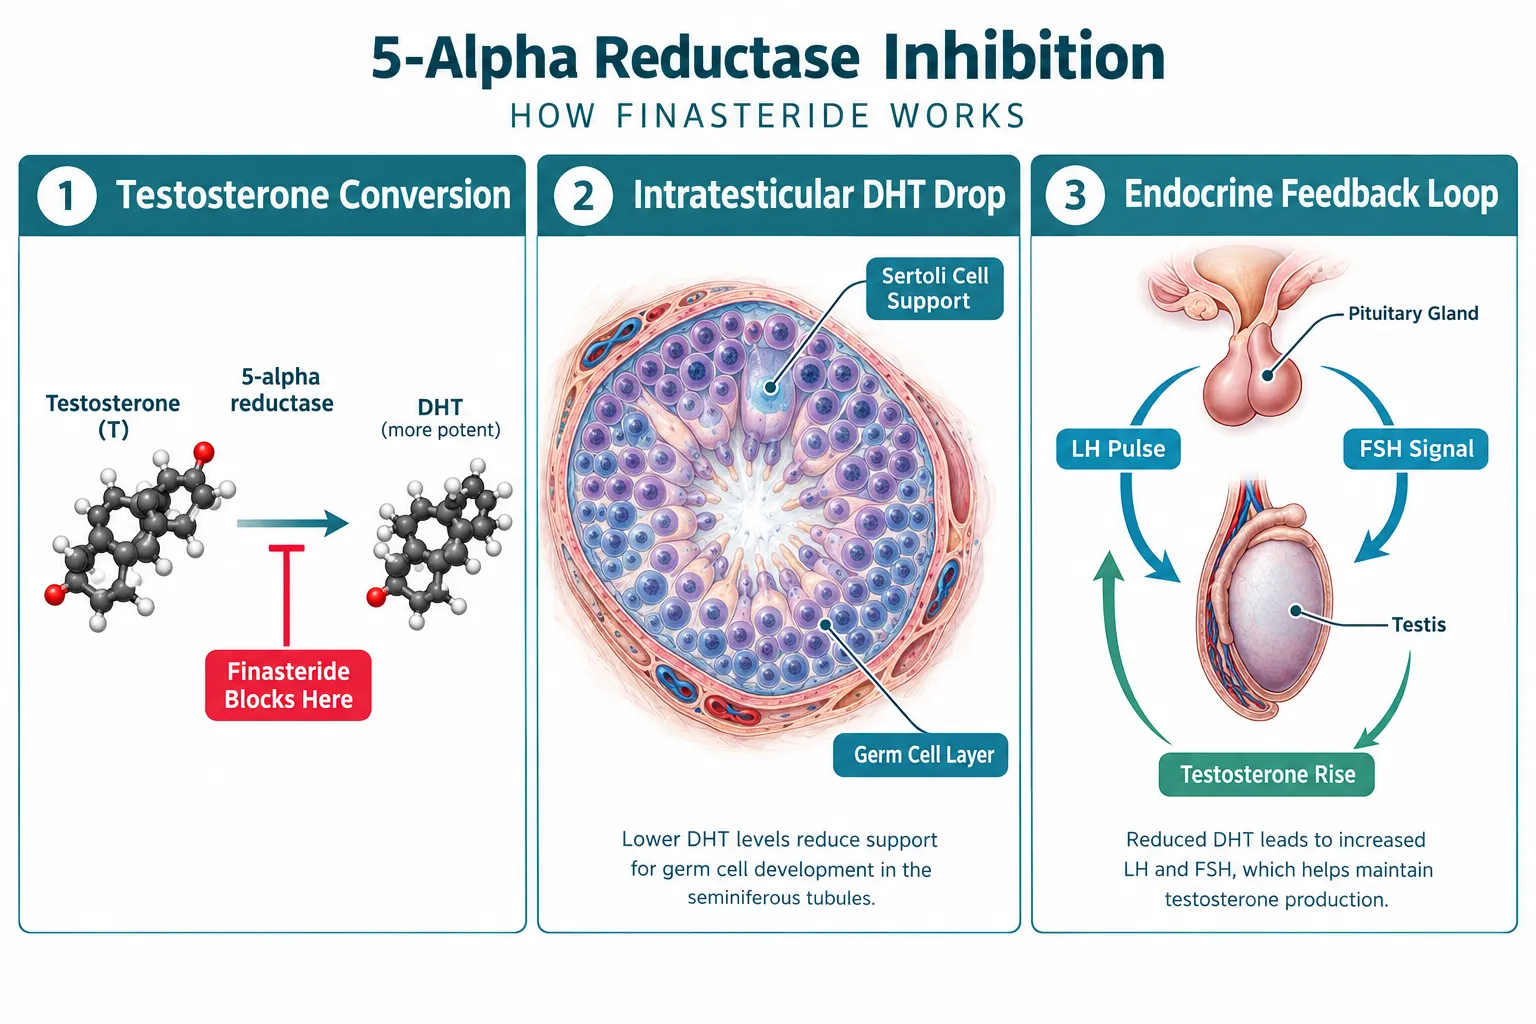
Finasteride works by blocking the enzyme 5-alpha reductase, which converts testosterone into dihydrotestosterone (DHT). In prostate and testicular tissue, DHT is a more potent androgen than testosterone. When finasteride reduces intratesticular DHT, it does not simply lower one hormone in isolation, it modifies the entire androgenic signaling environment that supports spermatogenesis.

In rat studies where 5-alpha reductase is inhibited, recovery of spermatogenesis after testosterone suppression is notably impaired. This implicates intratesticular DHT as a critical driver of normal germ cell development and tubular function, not merely a byproduct of testosterone metabolism. Rodent data also show that finasteride reduces the diameter of seminiferous and epididymal tubules in vitro, though in vivo effects are less consistent, an important distinction for study design.

At the clinical level, the dose matters. Studies using 1 mg finasteride daily found no significant changes in sperm concentration or motility in healthy adult men. Higher doses, 5 mg finasteride or combined with dutasteride, produced measurable reductions in sperm concentration and motility, with partial recovery at 12 months and full parameter restoration within six months of stopping treatment. These findings reinforce that DHT suppression along the HPG (hypothalamic-pituitary-gonadal) axis is dose-dependent and reversible, but still consequential for fertility planning.

Key point: Finasteride does not suppress LH or FSH directly. It acts downstream of gonadotropin signaling. This is why combining it with an agent that directly modulates gonadotropin output, like enclomiphene, creates a pharmacologically distinct scenario.


Enclomiphene, LH Pulsatility, and Spermatogenesis: What Rodent and Human Data Show

Enclomiphene, LH Pulsatility, and Spermatogenesis: What Rodent and Human Data Show

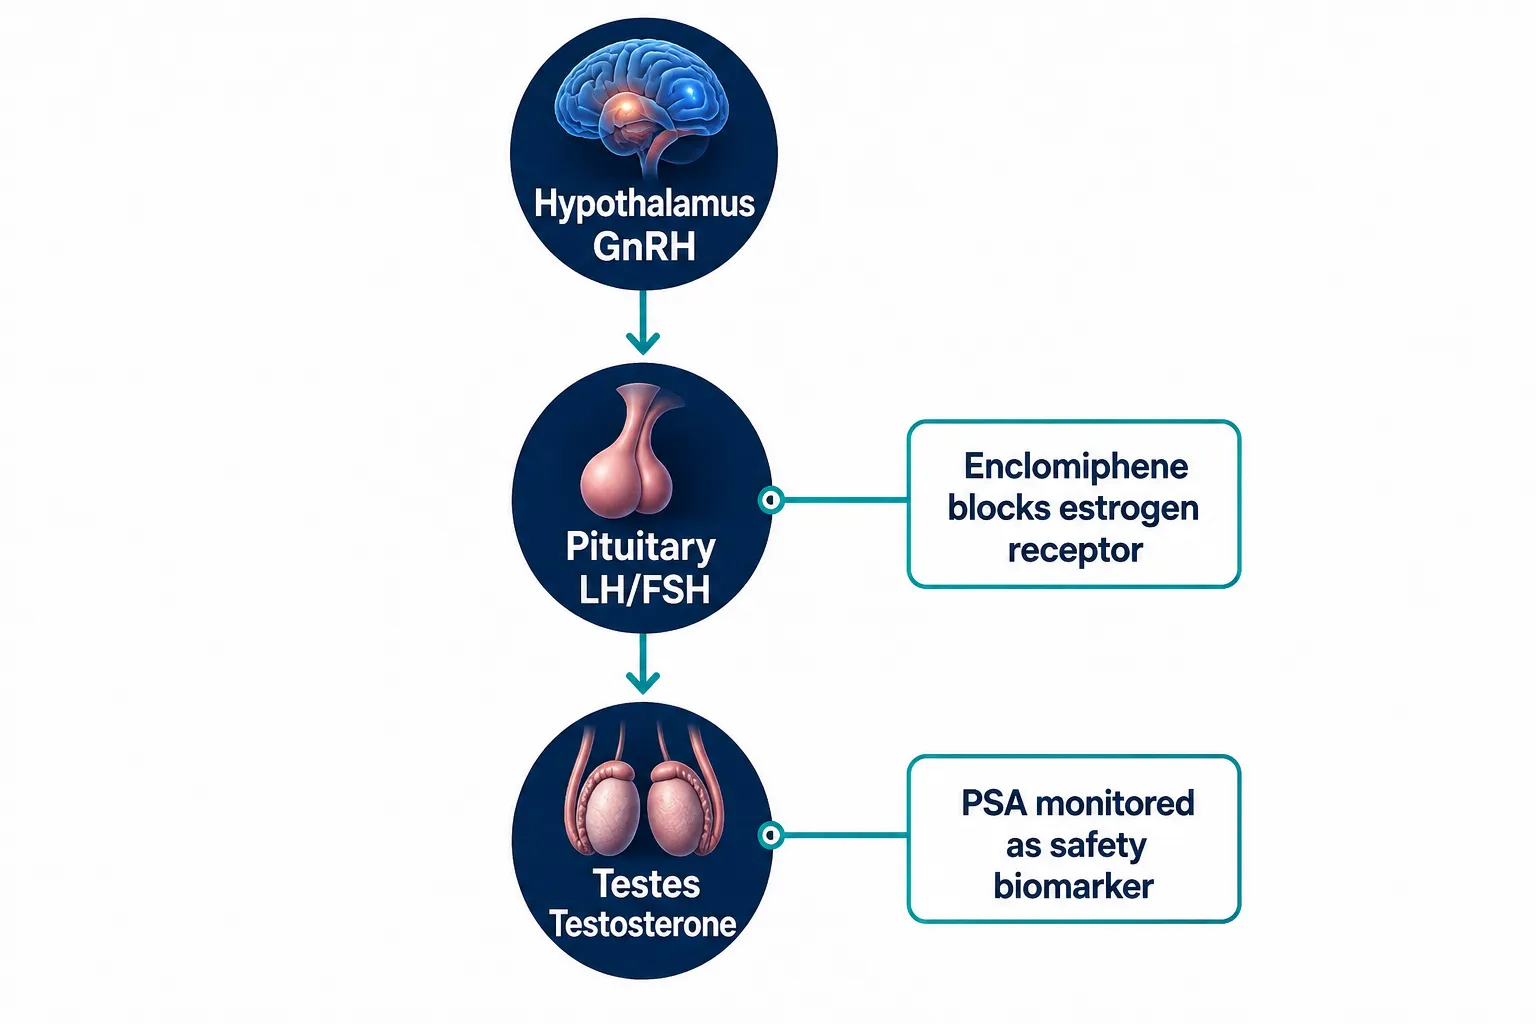
Enclomiphene is the trans-isomer of clomiphene citrate. Its primary mechanism involves antagonizing estrogen receptors at the pituitary, thereby reducing negative feedback and allowing LH and FSH secretion to rise. In adult men with secondary hypogonadism, clinical data confirm that enclomiphene increases LH, FSH, and total testosterone while preserving spermatogenesis, an advantage over exogenous testosterone replacement, which consistently suppresses sperm production.

A 2026 position statement from an andrology and urology society describes enclomiphene as capable of increasing total testosterone comparably to testosterone gels while maintaining or improving sperm counts. The statement calls for further mechanistic studies, specifically including detailed LH pulsatility assessment. Clinical pharmacokinetic data also show that serum enclomiphene peaks do not align precisely with LH pulses; instead, LH remains pulsatile but elevated overall. This suggests enclomiphene raises the tonic LH baseline without abolishing physiological pulse architecture.

However, immature rodent data tell a different story. In 21-day-old male rats given subcutaneous enclomiphene at 0.25-0.5 mg per animal daily for 24 days, the compound inhibited spermatogenesis and decreased serum LH and testosterone, in both intact and castrated animals. This means enclomiphene functioned as a functional anti-gonadotropic agent in immature rodents rather than a fertility-preserving serm. This species-, age-, and dose-dependent inversion is critical for any preclinical study design.

"Enclomiphene's effect on gonadotropins is not universal, adult and immature rodent models can produce opposite hormonal outcomes at comparable doses."

Researchers exploring serm-based protocols alongside other research compounds should treat this age-dependency as a primary variable in any study design. Those working with serm, ipamorelin, and CJC-1295 dosage protocols may also find that gonadotropin modulation interacts with growth hormone axis signaling in ways that complicate spermatogenic endpoints.


Evaluating Finasteride and Enclomiphene Co-Administration in Rodent Models: Research Gaps and Design Priorities

Evaluating Finasteride and Enclomiphene Co-Administration in Rodent Models: Research Gaps and Design Priorities

No existing study has placed finasteride and enclomiphene co-administration within a single controlled rodent experiment measuring DHT, LH pulsatility, and spermatogenesis together. Evaluating finasteride and enclomiphene co-administration in rodent models requires a framework that addresses each gap systematically.

Projected mechanistic interaction:

Variable Finasteride Effect Enclomiphene Effect (Adult) Combined, Predicted
Serum testosterone Slight increase (reduced DHT feedback) Significant increase High
Intratesticular DHT Decreased Indirect increase via LH Uncertain
LH pulsatility No direct change Elevated, pulsatility preserved Elevated baseline
Spermatogenesis May impair recovery Preserved or improved Unknown

The table above highlights that co-administration could produce elevated systemic testosterone alongside reduced intratesticular DHT, two outcomes working in opposite directions on sperm production. Net spermatogenic outcomes cannot be confidently predicted without direct experimental data.

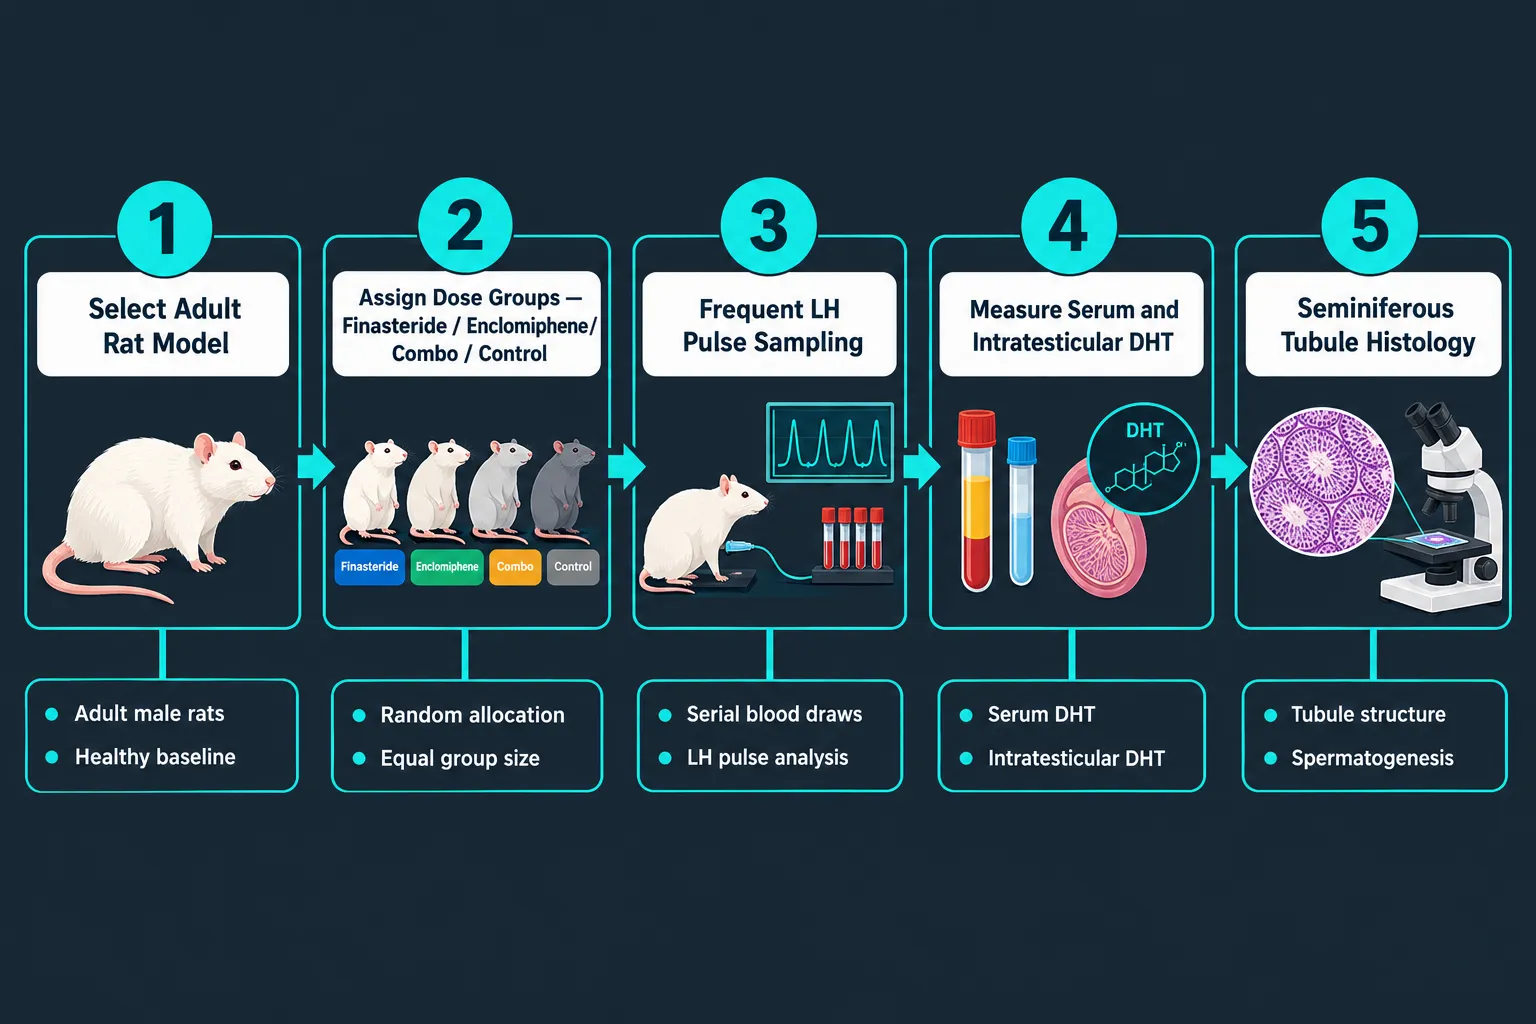
Recommended study design elements:

  • Use adult (not immature) rat or mouse models to avoid the anti-gonadotropic paradox seen in juvenile rodents
  • Assign four groups: finasteride only, enclomiphene only, combination, and vehicle control
  • Collect blood samples at high frequency (every 10-15 minutes for 6 hours) to characterize LH pulse amplitude and frequency
  • Measure both serum and intratesticular testosterone and DHT separately
  • Perform histologic analysis of seminiferous tubules to distinguish germ cell stage arrest from global spermatogenic suppression

Researchers interested in how peptide compounds interact with endocrine recovery may also find it useful to review SS-31 mitochondrial dynamics research, given that mitochondrial function in Leydig and Sertoli cells can influence steroidogenesis independently of gonadotropin signaling. Similarly, cellular energy demands in spermatogenic tissue have been explored in SS-31 kidney health research, which offers methodological parallels for assessing oxidative stress in endocrine tissues.

For those comparing growth hormone secretagogue protocols and their potential crossover with reproductive endocrinology research, resources on CJC-1295 and ipamorelin cycle protocols provide relevant background on pulsatile hormone release methodology. Understanding growth hormone pulse architecture can inform LH pulse measurement design, particularly around sampling frequency and assay sensitivity.

Finally, researchers sourcing research-grade compounds for preclinical use should consult peptide supplier comparison resources to ensure compound purity and lot-to-lot consistency, both of which are critical when measuring subtle hormonal endpoints like LH pulse amplitude.


Conclusion

The intersection of 5-alpha reductase inhibition and selective estrogen receptor modulation via enclomiphene represents one of the more underexplored areas in male reproductive endocrinology research. Finasteride and enclomiphene co-administration, when evaluated for effects on DHT, LH pulsatility, and spermatogenesis in rodent models, presents a mechanistic puzzle with real translational relevance for men using finasteride who also need fertility-preserving androgen support.

Actionable next steps for researchers:

  1. Design studies exclusively with adult rodent models to avoid confounding age-dependent enclomiphene anti-gonadotropic effects.
  2. Incorporate high-frequency LH sampling protocols to capture both pulse amplitude and frequency, not just mean LH levels.
  3. Measure intratesticular DHT separately from serum DHT, these can diverge significantly under dual drug exposure.
  4. Pre-register study designs in a public registry to reduce publication bias around negative or null spermatogenic findings.
  5. Plan for a recovery arm (post-drug washout) to assess reversibility, since both finasteride and enclomiphene effects on spermatogenesis appear dose- and duration-dependent.

Until controlled rodent data exist, any clinical extrapolation of combined finasteride and enclomiphene use in fertility contexts remains speculative. The field needs well-powered, mechanistically rigorous preclinical studies before co-administration protocols can be rationally evaluated or recommended.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/finasteride-and-enclomiphene-co-administration-evaluating-dht-lh-pulsatility-and.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-27 13:08:192026-10-27 13:08:19Finasteride and Enclomiphene Co-Administration: Evaluating DHT, LH Pulsatility, and Spermatogenesis in Rodent Models
Enclomiphene Research Materials: Base, Citrate, and Analytical Identity Checks for Hormone-Model Experiments

Enclomiphene Research Materials: Base, Citrate, and Analytical Identity Checks for Hormone-Model Experiments

October 7, 2026/0 Comments/in Uncategorized/by

Fewer than one in five commercial enclomiphene lots tested by independent analytical laboratories in recent years have carried full counterion confirmation alongside standard purity data, a gap that creates real problems when researchers try to compare results across batches or institutions. For anyone sourcing Enclomiphene Research Materials: Base, Citrate, and Analytical Identity Checks for Hormone-Model Experiments, that single oversight can invalidate dosing calculations, skew receptor-binding data, and make batch-to-batch reproducibility impossible.

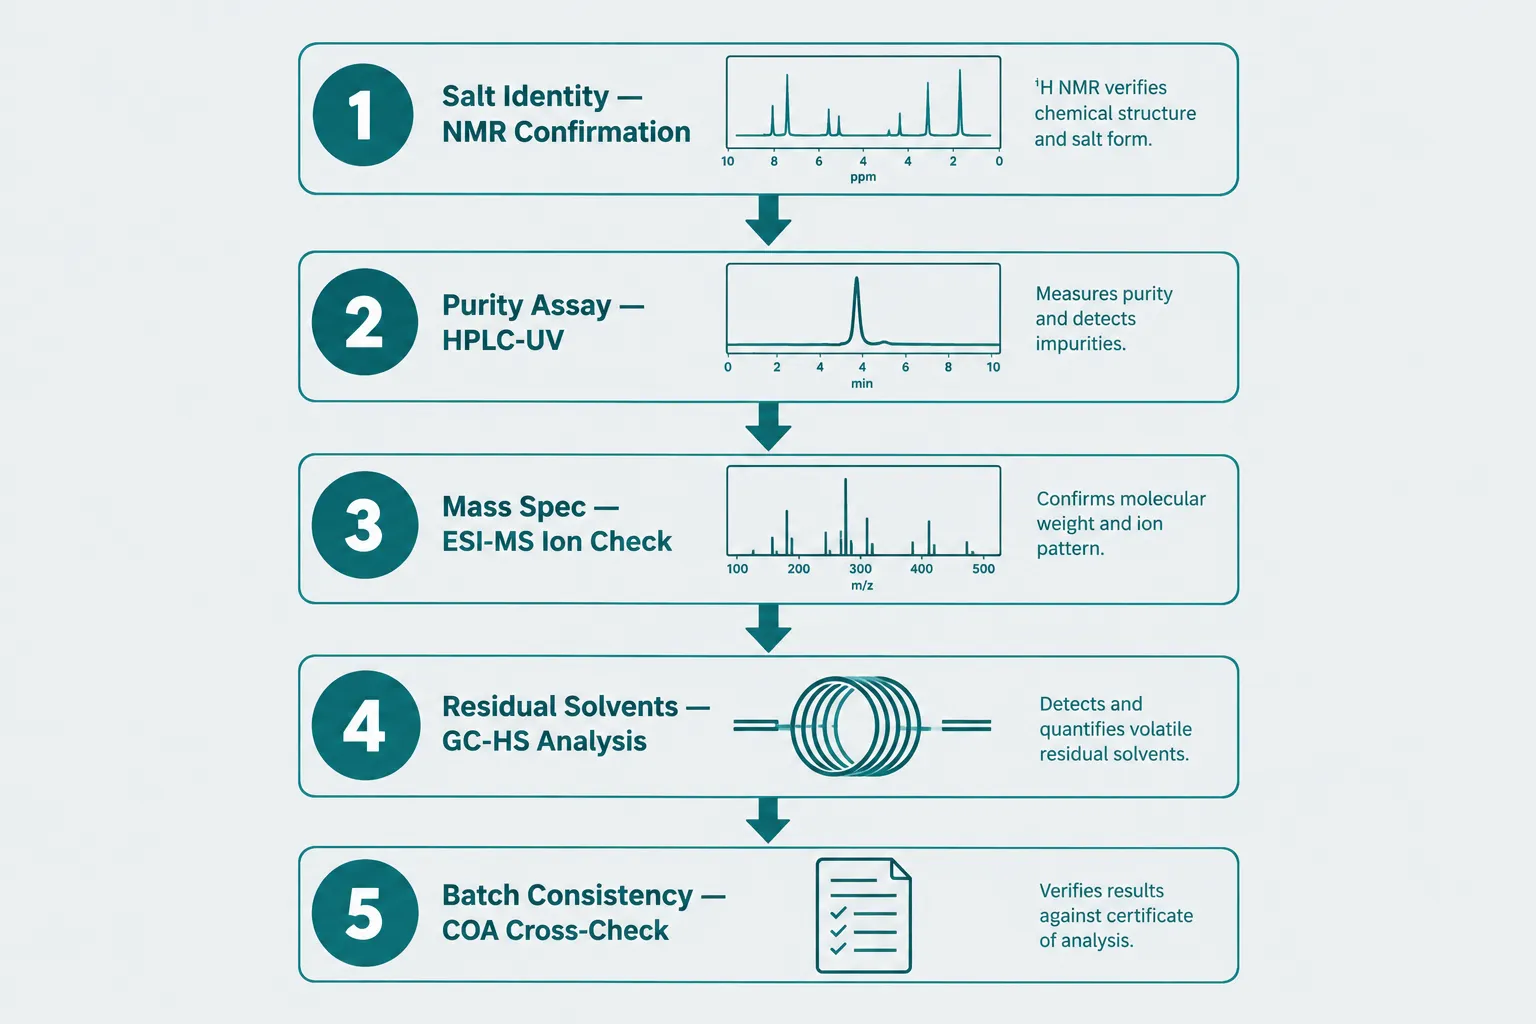
This guide moves beyond the basic base-versus-citrate comparison to give researchers a structured purchasing and verification checklist covering salt identity, assay method, residual solvents, counterion confirmation, and batch consistency.

Key Takeaways

  • Enclomiphene is supplied as either the free base or the citrate salt; the two forms carry different molecular weights, and failing to apply the correct salt factor corrupts dosing math in hormone-model experiments.
  • A complete Certificate of Analysis (COA) for research-grade material should include HPLC purity, NMR salt identity, ESI-MS confirmation, residual solvent data (GC headspace), and water content.
  • Counterion confirmation via NMR or ion chromatography is the most commonly missing data point in commercial COAs as of 2026.
  • Batch consistency checks, comparing COA values across at least two consecutive lots, are essential before committing to a long experimental series.
  • Enclomiphene is classified as a research-use-only compound in most jurisdictions; it is not approved for human use outside specific regulatory pathways.

Understanding the Two Chemical Forms: Base and Citrate

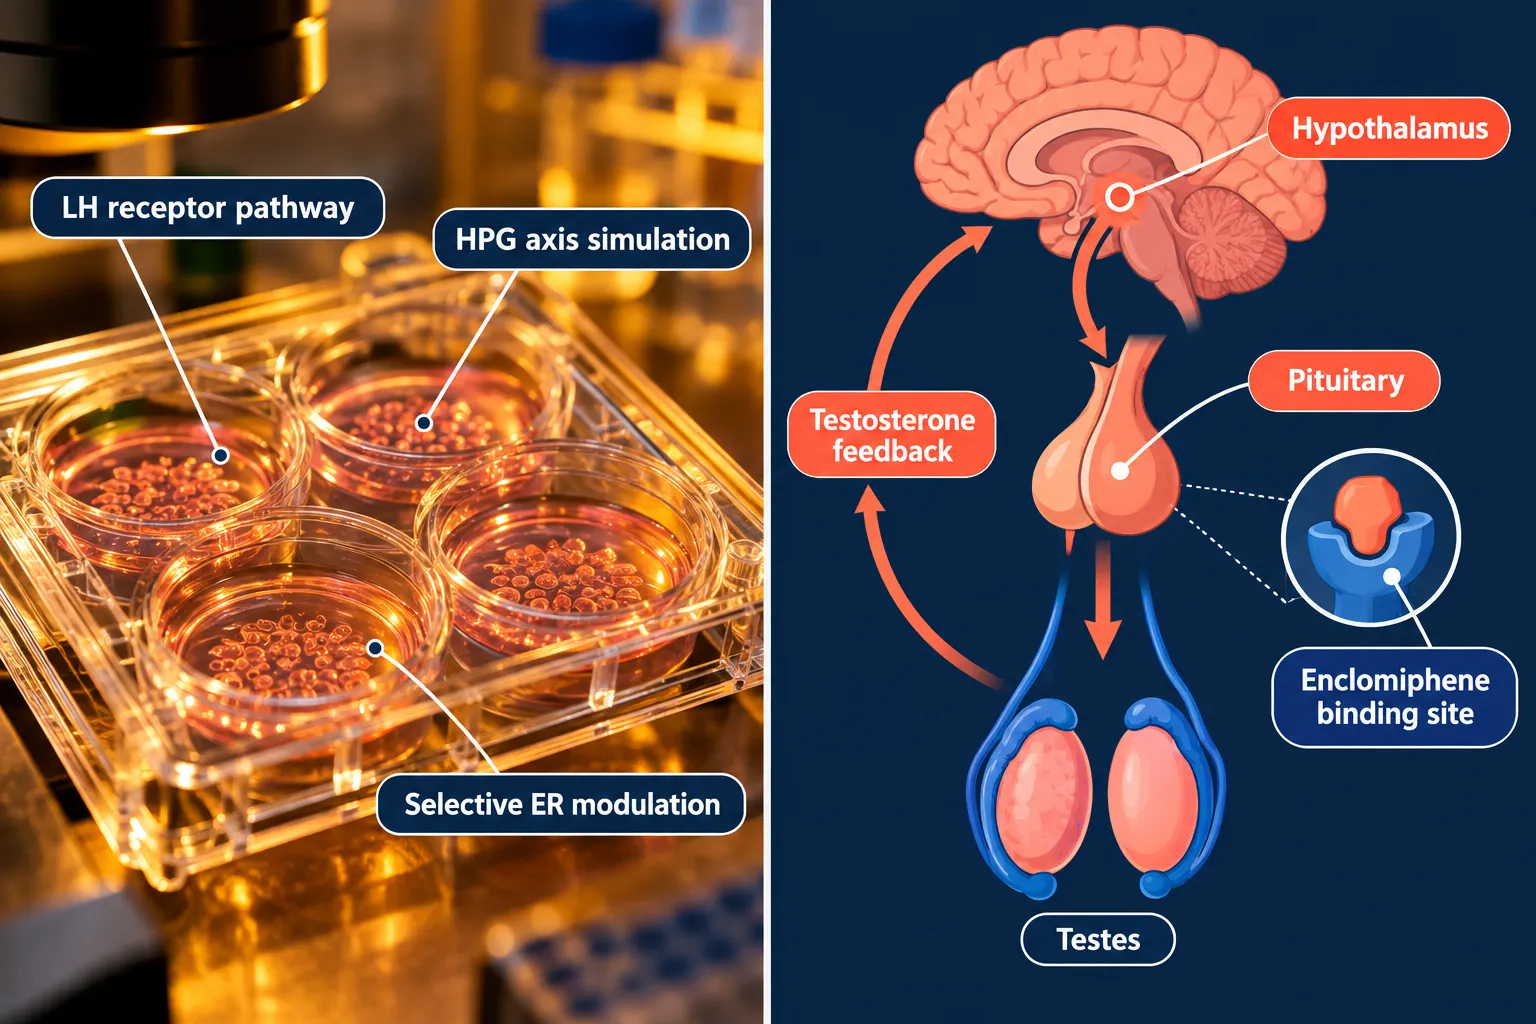
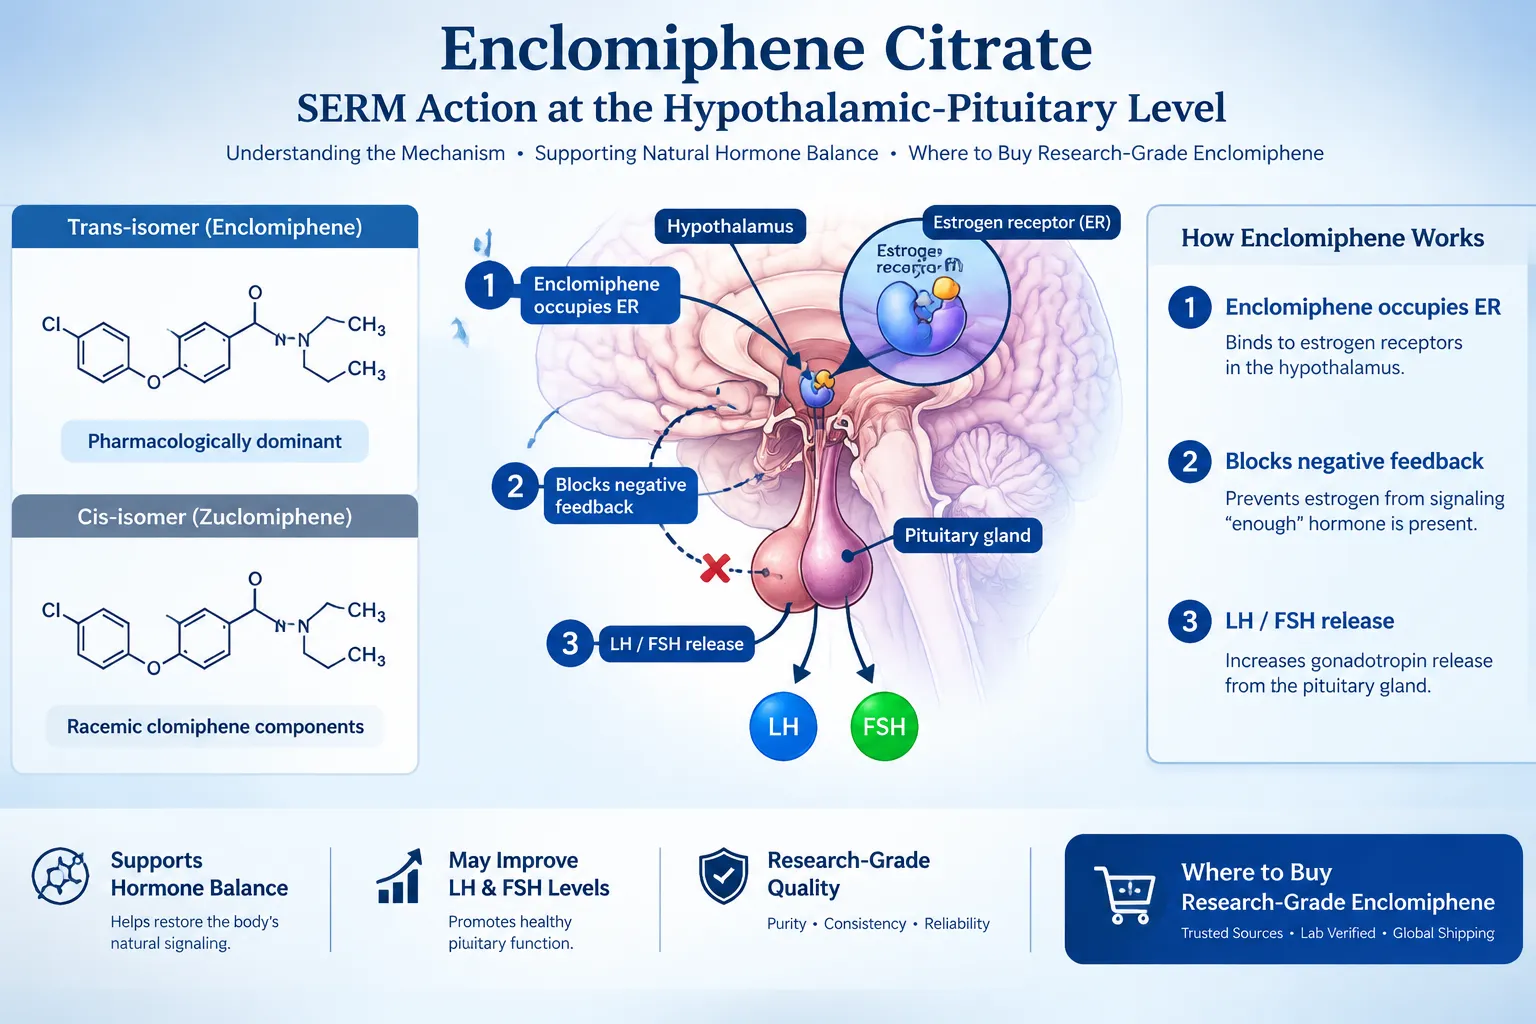
Enclomiphene is the trans-isomer of clomiphene, a selective estrogen receptor modulator (serm) that acts at hypothalamic estrogen receptors to reduce negative feedback on gonadotropin-releasing hormone. It reaches the market in two primary salt forms, and the distinction matters far more than many procurement workflows acknowledge.

Understanding the Two Chemical Forms: Base and Citrate

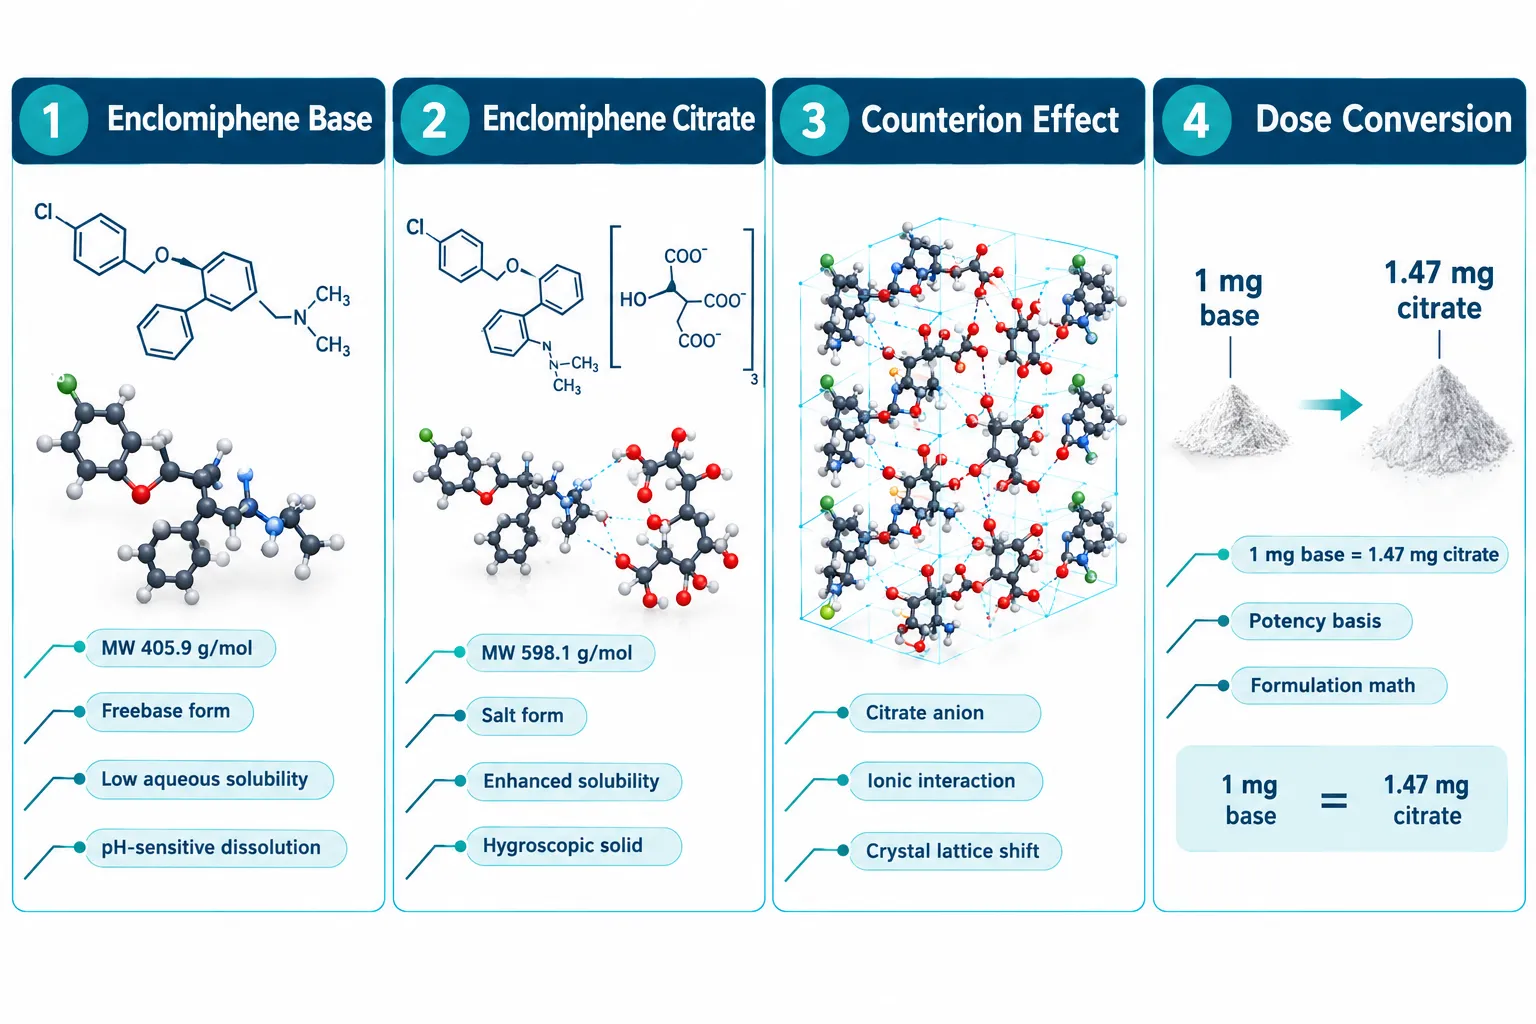
Enclomiphene free base carries a molecular weight of approximately 405.9 g/mol. It is less soluble in aqueous buffers, which makes it better suited to organic-solvent stock preparations (DMSO, ethanol) commonly used in cell-based assays. Enclomiphene citrate pairs the active molecule with citric acid as a counterion, raising the molecular weight to roughly 598.1 g/mol. The citrate form dissolves more readily in water, which is advantageous for in vitro hormone-model systems that require aqueous dosing vehicles.

The practical consequence: a researcher who assumes citrate when the material is actually the free base will underdose by approximately 32% relative to the active moiety. The conversion factor, roughly 1.47, must be applied whenever switching between forms or when a supplier's labeling is ambiguous.

Quick reference: key differences

Property Free Base Citrate Salt
Molecular weight ~405.9 g/mol ~598.1 g/mol
Aqueous solubility Low Moderate, high
Preferred vehicle DMSO / ethanol Aqueous buffer
Salt factor vs base 1.00 ~1.47
Counterion None Citric acid

Researchers building hormone-model systems, particularly hypothalamic-pituitary-gonadal (HPG) axis simulations, should document the chosen form in every experimental protocol. This is the same level of rigor applied when sourcing other structurally complex research agents; see the discussion of structural identity documentation in this overview of peptides 101 for research-use only buyers.


The Analytical Identity Checklist for Enclomiphene Research Materials

The core of responsible sourcing for Enclomiphene Research Materials: Base, Citrate, and Analytical Identity Checks for Hormone-Model Experiments is a structured verification checklist applied to every lot before it enters an experiment. The following five-point framework covers the most critical analytical dimensions.

The Analytical Identity Checklist for Enclomiphene Research Materials

1. Salt Identity via NMR

Proton NMR (1H-NMR) is the gold-standard method for confirming whether a lot is the free base or a specific salt form. For the citrate, characteristic citric acid proton signals appear in the 2.5-2.8 ppm region. A COA that reports only HPLC purity without NMR data cannot confirm salt identity. Suppliers who provide NMR spectra as part of their documentation package should be prioritized.

2. Purity Assay via HPLC-UV

High-performance liquid chromatography with UV detection (typically at 254 nm) remains the standard purity assay. Research-grade material in 2026 is expected to meet 98% or higher purity by HPLC. The COA should specify the column type, mobile phase, and integration method. A single broad purity figure without chromatographic conditions is insufficient for experimental validation.

3. Mass Spectrometry Confirmation (ESI-MS)

Electrospray ionization mass spectrometry (ESI-MS) provides molecular ion confirmation independent of chromatographic separation. For enclomiphene free base, the expected [M+H]+ ion appears at m/z 406.2; for the citrate, the spectrum should show both the enclomiphene cation and the citrate anion. ESI-MS data on a COA rules out structural analogs and degradation products that can co-elute on HPLC.

4. Residual Solvents via GC Headspace

Synthesis and recrystallization of enclomiphene typically involves chlorinated solvents or alcohols. ICH Q3C residual solvent limits apply to pharmaceutical-grade material, and research-grade suppliers increasingly adopt these thresholds as a quality benchmark. Gas chromatography headspace (GC-HS) analysis should be requested for any lot used in cell-viability or receptor-binding assays where solvent contamination could confound results.

5. Counterion Confirmation via Ion Chromatography

This is the most commonly absent data point. Ion chromatography (IC) or capillary electrophoresis can quantify the citrate counterion directly, confirming the correct stoichiometry of the salt. Without it, a lot labeled "citrate" may be a partial salt or a mixed form. Batch-to-batch counterion ratio variation is a known source of irreproducibility in serm research.

Checklist summary:

  • NMR spectrum confirming salt form
  • HPLC-UV purity (98%+ with stated conditions)
  • ESI-MS molecular ion confirmation
  • GC-HS residual solvent panel
  • IC or CE counterion quantification
  • Karl Fischer water content (relevant for hygroscopic citrate lots)

Applying Verified Materials in Hormone-Model Experiments

Once analytical identity is confirmed, the experimental design for HPG-axis hormone models can proceed with confidence. Enclomiphene's mechanism centers on competitive antagonism at hypothalamic estrogen receptors, which reduces estrogenic negative feedback and elevates luteinizing hormone (LH) and follicle-stimulating hormone (FSH) output. This makes it a useful tool in cell-based and ex vivo models studying gonadotropin regulation, male hypogonadism mechanisms, and fertility signaling.

Applying Verified Materials in Hormone-Model Experiments

For researchers working with aqueous dosing systems, the citrate form is generally preferred due to its superior solubility. For lipid-based or organic-vehicle assay systems, the free base dissolves more cleanly. In either case, stock solutions should be prepared fresh or stored under inert gas at -20°C to prevent oxidative degradation of the stilbene backbone.

Batch consistency across a multi-experiment series requires comparing COA values, purity, water content, and counterion ratio, across at least two consecutive lots before committing. A purity drop of even 1-2% between lots can translate to meaningful receptor-occupancy differences at low nanomolar concentrations typical of serm experiments.

The approach mirrors best practices seen in other research-grade compound categories. For example, the purity evaluation standards applied when sourcing research-grade Glow Blend Peptide materials follow the same logic: identity first, purity second, batch consistency third.

Researchers interested in broader hormone-axis modeling may also find value in reviewing growth hormone secretagogue mechanisms, such as the detailed pharmacokinetic profile covered in this CJC-1295 with and without DAC mechanism comparison, as multi-axis hormone models increasingly combine serm and GH-pathway tools.

For procurement teams evaluating supplier quality programs, the standards applied to wholesale peptides for sale at reputable suppliers, including third-party COA availability and batch traceability, provide a useful quality benchmark applicable to small-molecule research materials like enclomiphene as well.

"The counterion is not a footnote, it is half the molecule. Treating salt identity as an afterthought is one of the most preventable sources of irreproducibility in serm research."

As of mid-2026, regulatory positioning for enclomiphene remains research-use only in most jurisdictions outside specific approved clinical pathways. Researchers should confirm local regulatory status before procurement and ensure all use is confined to in vitro or appropriately approved in vivo model systems.


Conclusion

Sourcing Enclomiphene Research Materials: Base, Citrate, and Analytical Identity Checks for Hormone-Model Experiments responsibly requires more than checking a purity percentage. The five-point analytical checklist, NMR salt identity, HPLC-UV purity, ESI-MS molecular confirmation, GC-HS residual solvents, and IC counterion quantification, gives research teams the data needed to dose accurately, compare results across batches, and publish reproducible findings.

Actionable next steps for research teams in 2026:

  1. Request full COA documentation including NMR and ESI-MS before approving any new lot.
  2. Apply the 1.47 salt factor correction whenever switching between base and citrate forms.
  3. Implement a batch-consistency log comparing at least two consecutive lot COAs before starting a new experimental series.
  4. Specify the dosing vehicle (aqueous vs. organic) in the protocol and select the appropriate salt form accordingly.
  5. Confirm the regulatory classification of enclomiphene in your jurisdiction before procurement.

Analytical rigor at the purchasing stage is the cheapest insurance a research program can buy.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/enclomiphene-research-materials-base-citrate-and-analytical-identity-checks-for.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-07 13:04:082026-10-07 13:04:08Enclomiphene Research Materials: Base, Citrate, and Analytical Identity Checks for Hormone-Model Experiments
Enclomiphene Base vs Enclomiphene Citrate: Solubility, Counterion Effects, and Analytical Comparability

Enclomiphene Base vs Enclomiphene Citrate: Solubility, Counterion Effects, and Analytical Comparability

October 2, 2026/0 Comments/in Uncategorized/by

Salt form selection is not a footnote in pharmaceutical development, it determines whether two batches of the same active molecule will dissolve identically, measure identically, and dose identically. When researchers and formulators encounter enclomiphene base vs enclomiphene citrate: solubility, counterion effects, and analytical comparability, the differences between these two forms reach far beyond a simple name change. A mass discrepancy of roughly 47% between the freebase and salt forms means that a researcher who ignores salt-form identity risks systematic dosing errors, failed dissolution tests, and misinterpreted analytical results, all without any obvious red flag in the raw data.


Key Takeaways

  • Enclomiphene base (MW ~405.9 g/mol) and enclomiphene citrate (MW ~598.1 g/mol) differ by approximately 47% in molecular weight, requiring a dose conversion factor for any potency-based calculation.
  • The citrate counterion substantially increases aqueous solubility compared to the freebase form, which is nearly insoluble at physiological pH.
  • pH-dependent solubility profiles differ sharply between the two forms, with critical implications for dissolution testing and oral formulation design.
  • Chromatographic and spectroscopic identity tests must be calibrated to the specific salt form in use; otherwise, retention times, response factors, and concentration calculations will be systematically offset.
  • Batch-to-batch comparability studies must confirm salt form identity before interpreting any apparent potency or purity discrepancy.

Chemical Identity and the Molecular Weight Gap

Chemical Identity and the Molecular Weight Gap

Enclomiphene is the trans-isomer of clomiphene, a selective estrogen receptor modulator (serm). In its freebase state, enclomiphene carries a molecular weight of approximately 405.9 g/mol. When combined with citric acid to form enclomiphene citrate, the resulting salt reaches approximately 598.1 g/mol, an increase of roughly 192 g/mol attributable entirely to the citrate counterion.

This gap has immediate practical consequences. A 25 mg dose expressed as the base equivalent requires approximately 36.8 mg of the citrate salt to deliver the same molar quantity of active compound. The conversion factor (citrate MW divided by base MW, approximately 1.47) must be applied consistently across:

  • Label claims on research-grade materials
  • Stock solution preparation for in vitro assays
  • Dissolution specifications in quality control testing
  • Comparative potency calculations across studies using different salt forms

Failure to apply this factor is one of the most common sources of apparent "potency discrepancy" between batches that are, in chemical terms, identical. Researchers sourcing a serm 10mg product, for example, should always confirm whether the stated weight reflects the base or the salt form before preparing working concentrations.


Solubility Profiles and the Role of the Citrate Counterion

Solubility Profiles and the Role of the Citrate Counterion

The phrase enclomiphene base vs enclomiphene citrate: solubility, counterion effects, and analytical comparability captures a genuine formulation challenge. Enclomiphene freebase is classified as practically insoluble in water at neutral to basic pH. Its ionization pKa sits near 8.6, meaning that at physiological pH (approximately 7.4), the molecule exists predominantly in its unionized, lipophilic form, a state that strongly limits aqueous dissolution.

The citrate salt changes this picture in two ways:

  1. Direct counterion solubilization: The citrate anion creates an ionic lattice that disrupts the hydrophobic crystal packing of the freebase, allowing water molecules to penetrate more readily.
  2. Microenvironmental pH buffering: Citric acid is a weak triprotic acid. As the salt dissolves, the local microenvironment becomes mildly acidic, which promotes ionization of the enclomiphene amine and further drives dissolution.

"The counterion is not an inert passenger, it actively shapes the thermodynamic and kinetic solubility of the active molecule."

pH-dependent solubility comparison:

pH Enclomiphene Base Enclomiphene Citrate
1.2 (gastric) Moderate High
4.5 (intestinal) Low Moderate-High
6.8 (intestinal) Very Low Moderate
7.4 (physiological) Practically Insoluble Low-Moderate

This profile explains why oral formulations almost universally use the citrate salt. The freebase form would require solubilization strategies, co-solvents, surfactants, or amorphous dispersion, to achieve comparable bioavailability. Hygroscopicity is a related concern: enclomiphene citrate absorbs atmospheric moisture more readily than the freebase, which affects storage conditions, weighing accuracy, and long-term stability. Proper desiccant storage and tightly sealed containers are non-negotiable for the citrate form.


Analytical Comparability: Where Salt Form Errors Become Data Errors

Understanding enclomiphene base vs enclomiphene citrate: solubility, counterion effects, and analytical comparability in an analytical context requires examining three distinct testing domains.

Analytical Comparability: Where Salt Form Errors Become Data Errors

Chromatographic Methods (HPLC/UPLC)

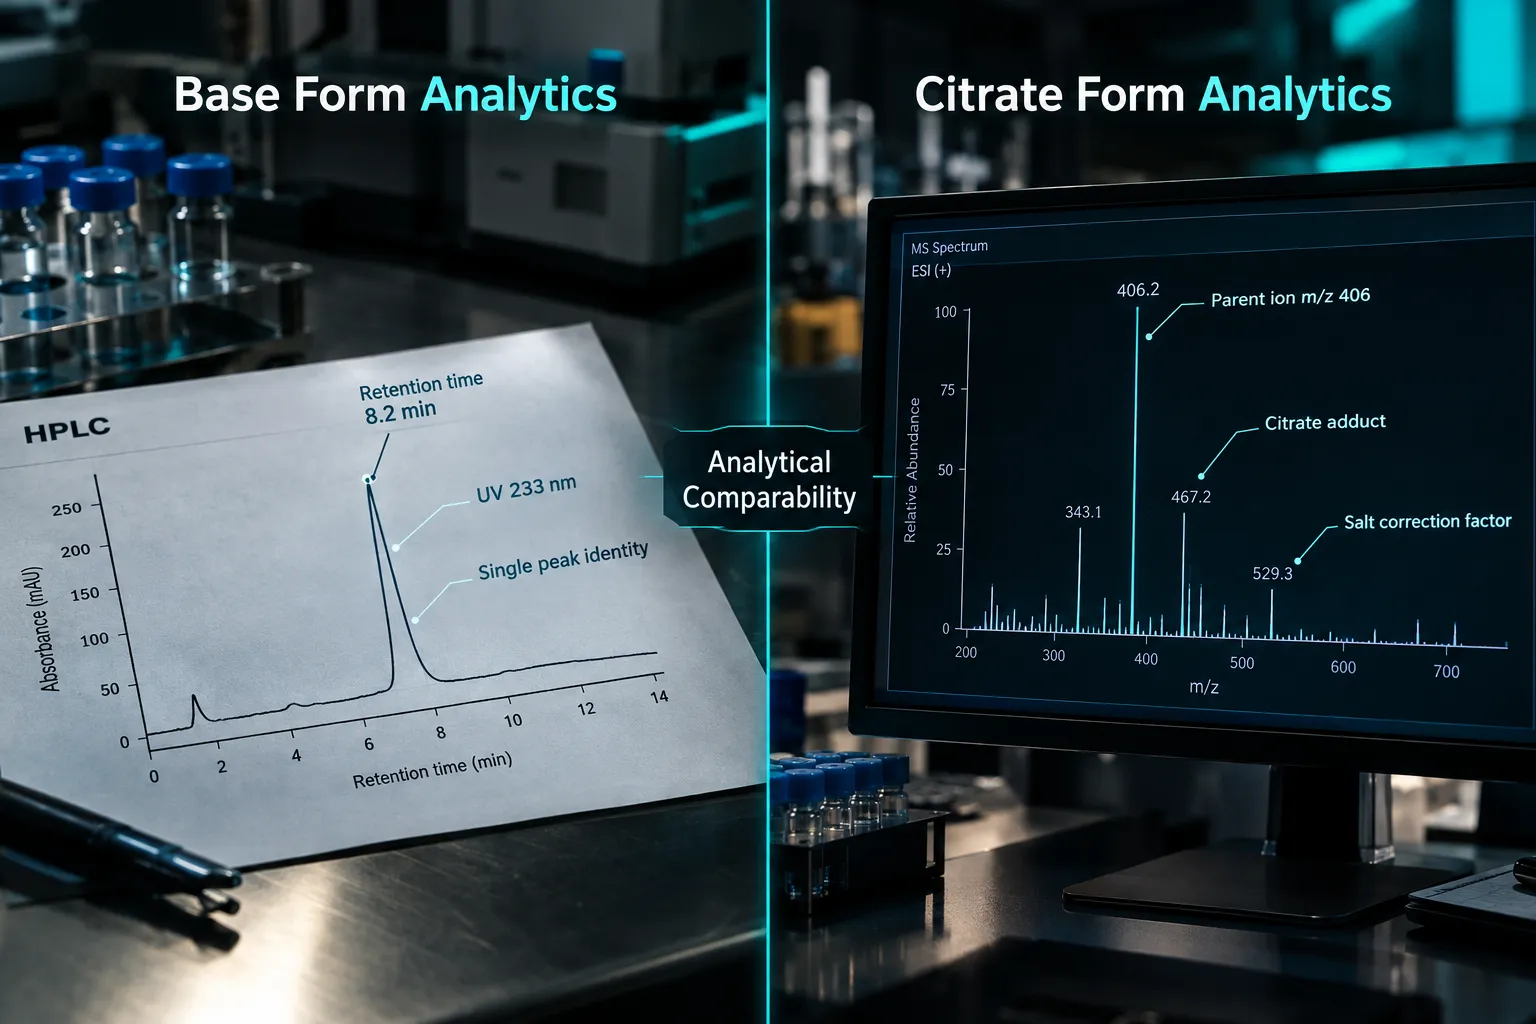
Both forms share the same enclomiphene chromophore and will produce UV absorbance at approximately 233 nm. However, the response factor, the relationship between peak area and concentration, must be calculated against a reference standard of matching salt form. Using a base-form reference standard to quantify a citrate-form sample introduces a systematic ~32% underestimation of true enclomiphene content (since the citrate sample contains proportionally less active molecule per unit mass).

Retention time is not affected by salt form under standard reversed-phase conditions, because the citrate counterion dissociates in aqueous mobile phases. This can mislead analysts into assuming the methods are fully interchangeable when they are not.

Mass Spectrometry

Electrospray ionization (ESI-MS) detects the enclomiphene molecular ion at m/z 406 regardless of salt form, since ionization strips the counterion. However, citrate adducts ([M + citrate]) can appear in negative-ion mode and may confuse automated library matching if the spectral database entry was built from the freebase.

Identity and Purity Testing

Infrared (IR) spectroscopy and X-ray powder diffraction (XRPD) will produce distinctly different spectra for the base and citrate forms. These are not interchangeable reference standards. A batch submitted with a base-form certificate of analysis but tested against a citrate-form IR reference will fail identity, not because the material is impure, but because the wrong reference was applied.

This is why well-designed analytical methods, much like the purity evaluation frameworks discussed in research-grade peptide purity evaluation, must explicitly state the salt form in every specification and reference standard description.

Stability and Forced Degradation

Enclomiphene citrate generates citric acid as a degradation-related impurity under hydrolytic stress conditions. This impurity is absent from freebase degradation profiles. Any forced degradation study or shelf-life specification must account for this difference, or citrate-derived impurities will be incorrectly flagged as enclomiphene-related degradants.


Practical Guidance for Batch Comparability

When two batches of enclomiphene appear to differ in potency or purity, the first diagnostic step is confirming salt form identity, not re-running the assay. A structured comparability checklist should include:

  • Confirm salt form via IR or XRPD before any quantitative comparison
  • Apply the correct MW conversion factor (base to citrate: multiply by 1.47; citrate to base: multiply by 0.679)
  • Match reference standards to the salt form of the test article
  • Adjust dissolution specifications to reflect the expected solubility profile of the specific form
  • Document hygroscopicity controls (desiccant storage, equilibration time before weighing)

Researchers working with peptide-based compounds face analogous salt-form and counterion considerations. Resources such as SS-31 10mg research peptide considerations and what is ideal dosage of SS31 illustrate how molecular weight and salt form affect concentration calculations across compound classes. Similarly, dosing frameworks for growth hormone secretagogues, such as those covered in tesa dosage for fat loss and tesa vs sermorelin, demonstrate how salt-form awareness is a universal analytical discipline, not specific to any single molecule.


Conclusion

The comparison of enclomiphene base vs enclomiphene citrate: solubility, counterion effects, and analytical comparability resolves into a single actionable principle: salt form is a primary analytical variable, not a secondary label detail. The ~47% molecular weight difference demands a consistent conversion factor in every concentration calculation. The citrate counterion's buffering and solubilization effects must be reflected in dissolution specifications and formulation design. And every analytical method, from HPLC quantitation to IR identity testing, must be explicitly validated against the salt form actually in use.

Actionable next steps for researchers and formulators in 2026:

  1. Audit all existing enclomiphene reference standards and certificates of analysis to confirm explicit salt form declaration.
  2. Recalculate any historical concentration data using the correct MW conversion factor for the form used.
  3. Establish separate XRPD or IR identity specifications for base and citrate forms and never cross-apply them.
  4. Implement moisture-control procedures specific to the hygroscopic citrate salt.
  5. Flag any batch comparability discrepancy for salt-form verification before concluding a purity or potency failure.

Treating these two forms as analytically equivalent is the fastest route to systematic, invisible error. Treating them as distinct chemical entities, which they are, is the foundation of reliable enclomiphene research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/enclomiphene-base-vs-enclomiphene-citrate-solubility-counterion-effects-and-anal.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-02 13:04:102026-10-02 13:04:10Enclomiphene Base vs Enclomiphene Citrate: Solubility, Counterion Effects, and Analytical Comparability
Enclomiphene Research Materials: Enclomiphene Base vs Citrate for Identity, Solubility, and COA Review

Enclomiphene Research Materials: Enclomiphene Base vs Citrate for Identity, Solubility, and COA Review

September 28, 2026/0 Comments/in Uncategorized/by

Fewer than a handful of small-molecule research compounds generate as much procurement confusion as enclomiphene, largely because researchers routinely receive materials labeled under two chemically distinct forms without clear guidance on how that distinction affects their assay design. Selecting the correct form from the outset, and then verifying it through proper documentation, is not a minor administrative step. For anyone sourcing enclomiphene research materials: enclomiphene base vs citrate for identity, solubility, and COA review, understanding the chemical and analytical differences between these two forms is the foundation of reproducible, well-documented laboratory work.

Key Takeaways

  • Enclomiphene base and enclomiphene citrate are chemically distinct forms with different molecular weights, solubility profiles, and documentation requirements.
  • Enclomiphene citrate offers meaningfully higher aqueous solubility, making it preferable for buffer-based in vitro assays.
  • Enclomiphene base is better suited to organic solvent systems such as DMSO or ethanol.
  • A high-quality Certificate of Analysis must explicitly state the salt form, CAS number, purity method, and solubility data, not just a percentage purity figure.
  • As of 2026, enclomiphene holds no FDA-approved indication in any form; all procurement and use remains within a research-only context.

Chemical Identity: What Separates Enclomiphene Base from Its Citrate Salt

Chemical Identity: What Separates Enclomiphene Base from Its Citrate Salt

Enclomiphene is the trans-isomer of clomiphene, a selective estrogen receptor modulator (serm) that has been studied for its effects on the hypothalamic-pituitary-gonadal axis. The base form (free base) carries CAS number 15690-57-0 and represents the compound in its uncharged, non-salt state. The citrate salt is formed when the base is combined with citric acid, producing a counterion pair that significantly alters the compound's physical and chemical behavior.

This distinction matters immediately at the procurement stage. A supplier listing "enclomiphene" without specifying salt form is providing incomplete information. Researchers should confirm:

  • Exact CAS number (base vs. citrate have different registry entries)
  • Molecular weight (the citrate salt is heavier due to the citric acid moiety)
  • IUPAC name or systematic name confirming the trans-configuration
  • Salt ratio (typically 1:1 for citrate salts, but this should be stated explicitly)

Clomiphene citrate, the racemic mixture containing both enclomiphene and zuclomiphene, has a long clinical history. Enclomiphene as an isolated isomer is a more refined research material, and its documentation standards should reflect that precision. Researchers comparing enclomiphene to other research-grade serms can find relevant context in the serm 10mg product documentation as a reference point for how salt-form labeling should appear on supplier listings.


Solubility Profiles: Matching the Form to the Assay

Solubility Profiles: Matching the Form to the Assay

Solubility is where the base-versus-citrate distinction has the most direct impact on experimental planning. The two forms behave very differently across common laboratory solvents.

Enclomiphene Base, Solubility Summary

Solvent Solubility
DMSO Moderate to good (~10-25 mg/mL typical)
Ethanol Moderate
Water Very low (practically insoluble)
Aqueous buffers Not suitable without co-solvent

Enclomiphene Citrate, Solubility Summary

Solvent Solubility
Water Measurably higher than base form
Aqueous buffers (pH 4-7) Acceptable for in vitro use
DMSO Also soluble
Ethanol Soluble

The citrate salt form improves aqueous solubility because the ionic character of the salt increases hydrophilicity. This is consistent with the broader pharmacology of clomiphene citrate, where the citrate counterion has historically been used precisely to improve handling in aqueous media. For researchers designing cell-based assays or receptor binding studies in aqueous buffer systems, enclomiphene citrate is the more practical choice. For organic solvent stock solutions intended for dilution into non-aqueous matrices, the base form is workable.

"Choosing the wrong salt form for an aqueous assay can introduce solubility artifacts that invalidate dose-response data, a problem that is entirely avoidable with upfront documentation review."

Researchers working with other peptides and small molecules that require careful solubility planning, such as those reviewing Bachem and reference standards for building robust peptide benchmarks, will recognize this as a standard quality-control consideration across compound classes.


COA Review: What a High-Quality Document Must Contain

COA Review: What a High-Quality Document Must Contain

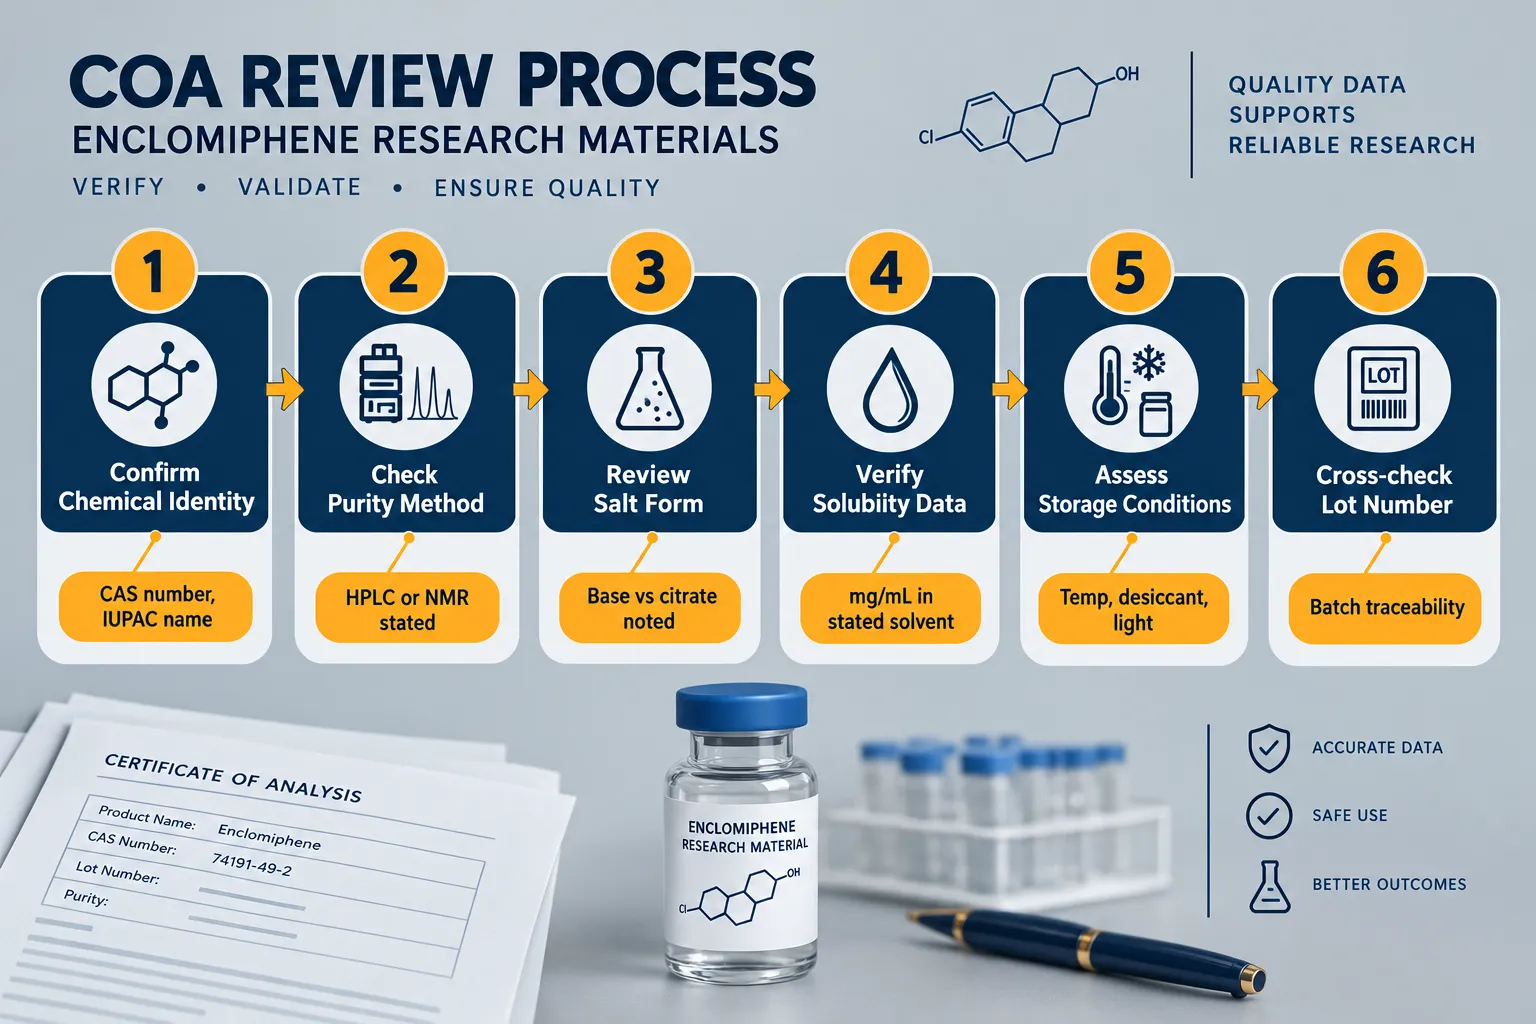
A Certificate of Analysis (COA) is not simply a purity number on a page. For enclomiphene research materials, whether base or citrate, a complete COA should contain the following elements, and researchers should decline materials where any of these are absent.

Required COA Elements for Enclomiphene Research Materials

  1. Chemical name and salt form, explicitly stating "enclomiphene citrate" or "enclomiphene free base," not just "enclomiphene"
  2. CAS number, matching the stated form
  3. Molecular formula and molecular weight, allowing the researcher to verify the correct form independently
  4. Purity method, HPLC is the standard; NMR is acceptable as a supplementary identity confirmation
  5. Purity result, expressed as area percentage from HPLC, with the method conditions (column type, mobile phase, wavelength) ideally referenced
  6. Isomeric confirmation, documentation that the material is the trans-isomer (enclomiphene), not the cis-isomer (zuclomiphene) or the racemate
  7. Solubility data, stated solvent, concentration, and whether the solution was clear or required sonication
  8. Lot or batch number, for traceability
  9. Storage conditions, temperature, desiccant requirement, light sensitivity
  10. Manufacturer or testing laboratory identity

As of 2026, enclomiphene citrate appears in some NDC (National Drug Code) listings, but this does not constitute FDA approval of any enclomiphene product. Researchers should not interpret an NDC listing as a regulatory clearance signal. All procurement of enclomiphene in any form remains strictly within research contexts, and COA documentation should be evaluated accordingly.

Researchers familiar with documentation standards for other well-characterized compounds, such as those reviewing SS-31 mechanism and research sourcing considerations, will find the same principles apply: supplier transparency, third-party testing, and explicit lot traceability are non-negotiable.


Formulation Strategies and Assay Planning Considerations

Knowing the form is only the first step. Translating that knowledge into a working formulation requires a few additional decisions.

For enclomiphene citrate in aqueous systems:

  • Prepare stock solutions in sterile water or phosphate-buffered saline
  • Confirm clarity visually and via UV absorbance baseline before use
  • Note that pH can affect solubility, acidic conditions (pH 4-5) generally favor dissolution

For enclomiphene base in organic solvent systems:

  • DMSO stocks at 10 mg/mL are a common starting point
  • Dilute into aqueous media at no more than 0.1% DMSO final concentration to avoid solvent cytotoxicity in cell assays
  • Sonication in a water bath (37°C, 15-30 minutes) can aid dissolution

Researchers sourcing other research-grade materials that require similar formulation planning, including those exploring IPA sermorelin stack research or reviewing tesa dosage considerations, will recognize that solvent compatibility and stock preparation protocols are just as important as compound identity.

For researchers also working with compounds in the aging support category, cross-referencing COA documentation practices across compound classes is a useful habit that strengthens overall laboratory quality standards.


Conclusion

Procuring enclomiphene research materials without first resolving the base-versus-citrate distinction is a preventable source of experimental error. The two forms differ in molecular weight, aqueous solubility, and the documentation that should accompany them. A COA that fails to specify salt form, purity method, or isomeric identity is insufficient for rigorous research use.

Actionable next steps for researchers in 2026:

  • Request full COA documentation before purchase, and verify that salt form and CAS number are explicitly stated
  • Match the form to the solvent system: citrate for aqueous assays, base for organic solvent stocks
  • Cross-check the stated molecular weight against published values for the specific form to catch mislabeling
  • Confirm isomeric purity (trans-enclomiphene vs. cis-zuclomiphene) through HPLC or NMR data on the COA
  • Treat any NDC listing as administrative, not as a regulatory approval signal

Rigorous identity verification and documentation review are the difference between reproducible data and ambiguous results. Applying these standards consistently, across enclomiphene and every other research compound in the laboratory, is the hallmark of credible, defensible research practice.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/enclomiphene-research-materials-enclomiphene-base-vs-citrate-for-identity-solubi.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-28 13:04:022026-09-28 13:04:02Enclomiphene Research Materials: Enclomiphene Base vs Citrate for Identity, Solubility, and COA Review
Enclomiphene Citrate vs Enclomiphene: Stability, Storage, and Research Handling

Enclomiphene Citrate vs Enclomiphene: Stability, Storage, and Research Handling

September 15, 2026/0 Comments/in Uncategorized/by

Most researchers who order enclomiphene for laboratory work assume the citrate salt and the free base are the same compound with a different label. That assumption can compromise data, shorten shelf life, and introduce variables that are difficult to trace back to the source material. Understanding the distinctions in Enclomiphene Citrate vs Enclomiphene: Stability, Storage, and Research Handling is not a minor technical footnote, it is foundational to reproducible science.

Key Takeaways

  • Enclomiphene citrate is a salt form of enclomiphene; the citrate counterion meaningfully changes solubility, crystalline stability, and handling requirements.
  • Research-grade powder in either form is significantly more stable than aqueous or organic solutions, which degrade faster under ambient conditions.
  • Both forms are sensitive to light, moisture, and heat; amber vials, desiccants, and cold storage are non-negotiable for long-term integrity.
  • Finished formulations such as capsules and liquid suspensions show acceptable stability at or below 25 °C when properly packaged.
  • Vendor quality documentation, including certificates of analysis and HPLC purity data, is a critical checkpoint before any research use.

What the Citrate Salt Actually Changes

What the Citrate Salt Actually Changes

Enclomiphene is the trans-isomer of clomiphene, a selective estrogen receptor modulator with growing research interest in male reproductive endocrinology. When enclomiphene is converted to its citrate salt, a citric acid molecule pairs ionically with the enclomiphene base. This is not a cosmetic change.

The citrate counterion delivers three practical advantages:

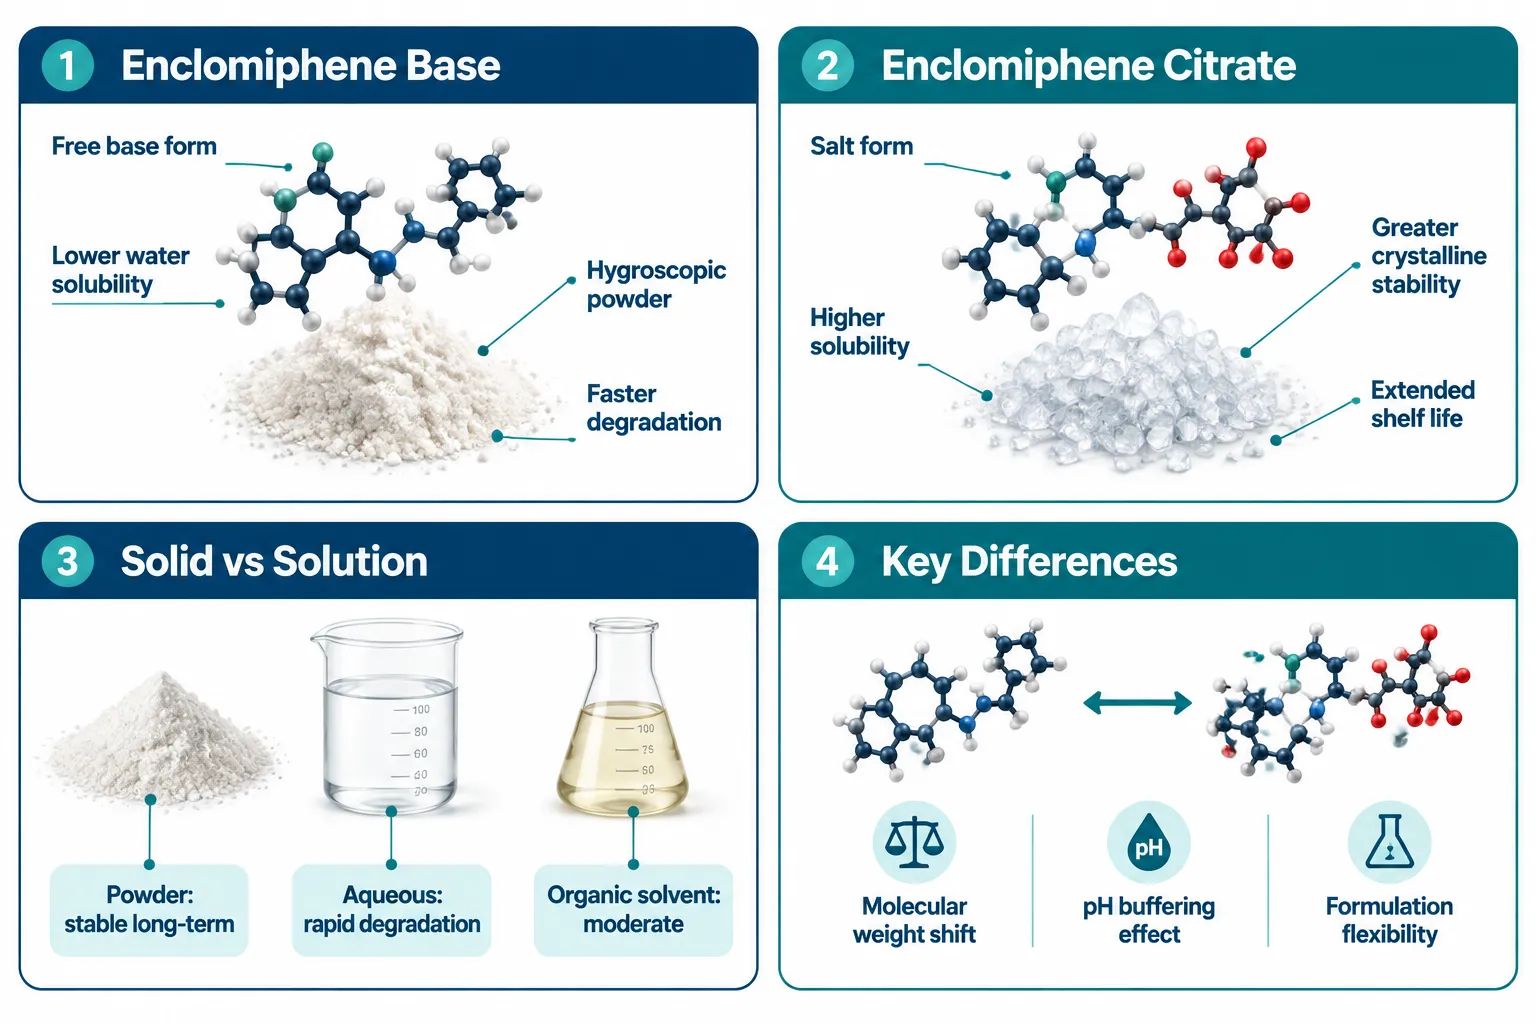
Property Enclomiphene (Free Base) Enclomiphene Citrate
Water solubility Low Moderately higher
Crystalline stability Moderate Greater
Formulation flexibility Limited Broader
Hygroscopicity High Reduced

The increased water solubility of the citrate form matters when preparing stock solutions for in vitro work. The free base requires organic solvents such as DMSO or ethanol to dissolve reliably, and those solvents introduce their own biological variables at higher concentrations. The citrate salt can often be dissolved in aqueous buffers at research-relevant concentrations, which simplifies assay design.

"The choice between enclomiphene base and enclomiphene citrate is not arbitrary, it directly affects dissolution behavior, solution stability, and the reproducibility of downstream assays."

The molecular weight difference between the two forms is also worth noting. Enclomiphene free base has a molecular weight of approximately 406 g/mol, while the citrate salt sits closer to 598 g/mol. Researchers calculating molar concentrations must account for this difference to avoid systematic dosing errors across experiments.

This distinction mirrors well-established patterns seen with the parent compound clomiphene citrate, where the salt form has long been preferred for pharmaceutical manufacturing because of its superior stability profile and more predictable dissolution kinetics.

Stability Factors: Light, Moisture, Heat, and Form

Stability Factors: Light, Moisture, Heat, and Form

Both enclomiphene and enclomiphene citrate are susceptible to the same primary degradation drivers: ultraviolet light, ambient moisture, and elevated temperature. However, the degree of vulnerability differs between solid powder, aqueous solution, and organic solution.

Solid Powder Stability

Research-grade powder, whether free base or citrate, is the most stable form. When stored correctly, properly manufactured powder can maintain integrity for 24 months or longer. Correct storage means:

  • Temperature at or below -20 °C for long-term archival
  • Desiccant packs inside a sealed, airtight container
  • Amber or opaque vials to block UV exposure
  • Minimal handling that introduces ambient air or humidity

The citrate form benefits from reduced hygroscopicity relative to the free base. In practical terms, this means the citrate powder is less likely to absorb atmospheric moisture during brief handling windows, which is a meaningful advantage in non-controlled lab environments.

Solution Stability

Aqueous solutions of enclomiphene citrate are markedly less stable than the solid form. At room temperature, degradation can become measurable within days. Refrigerated aqueous solutions (2-8 °C) extend working life but should still be used within a short window, typically 48 to 72 hours for research applications.

Organic solvent solutions (DMSO, ethanol) offer moderate stability but are not suitable for extended storage. Freeze-thaw cycling accelerates degradation in both aqueous and organic solutions, which is why aliquoting into single-use volumes before freezing is standard practice.

Finished Formulations

Capsule and liquid suspension formulations of enclomiphene citrate demonstrate extended stability at or below 25 °C when packaged with appropriate moisture barriers. Regulatory stability expectations for finished dosage forms generally require data supporting a shelf life of 24 months under controlled conditions, and enclomiphene citrate formulations have been evaluated under those frameworks in clinical development programs.

Practical Research Handling for Enclomiphene Citrate vs Enclomiphene

Practical Research Handling for Enclomiphene Citrate vs Enclomiphene

Applying the stability science above to day-to-day laboratory practice requires a clear protocol. The following guidance applies to both forms but is especially relevant for enclomiphene citrate given its broader use in research pipelines.

Before Use

  • Verify the certificate of analysis (COA) from the supplier, confirming HPLC purity of 98% or above
  • Confirm the compound is labeled correctly as citrate salt or free base, the two are not interchangeable in concentration calculations
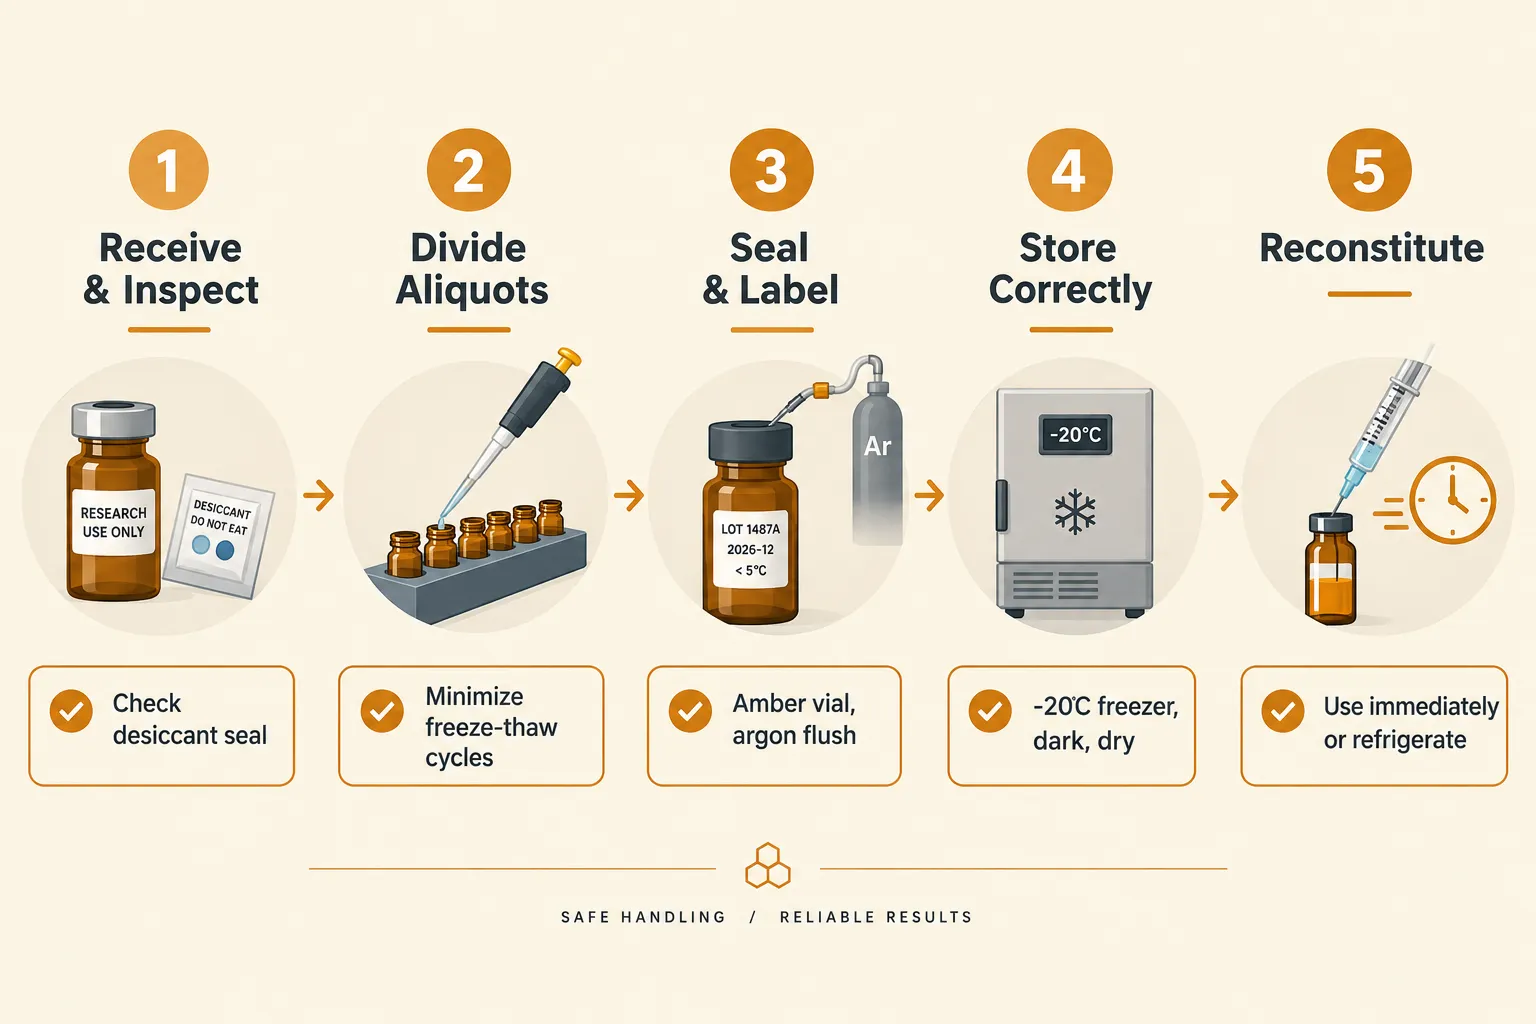
  • Inspect the desiccant seal; a broken seal is grounds for rejection

During Reconstitution

  • Warm sealed vials to room temperature before opening to prevent condensation on the powder
  • Use the appropriate solvent for the form: aqueous buffer for citrate, DMSO or ethanol for free base
  • Prepare only the volume needed; do not reconstitute bulk quantities

During Storage

  • Store reconstituted solutions at 2-8 °C and use within 48-72 hours
  • Store dry powder at -20 °C in amber vials with desiccant
  • Log every freeze-thaw cycle; limit to no more than two per aliquot

Researchers sourcing serms for comparative studies should apply the same handling discipline to related compounds. For those working with peptide-based research compounds alongside small-molecule serms, foundational guidance on compound classes is available in resources covering peptides 101 for research-use only buyers.

Vendor selection is equally important. A vendor scoring rubric that evaluates third-party testing, cold-chain shipping, and documentation practices will reduce the risk of receiving degraded or mislabeled material. Researchers running multi-compound protocols, for example, pairing a serm with a growth hormone secretagogue, can find relevant product context in resources such as the IPA Sermorelin stack research overview.

For those evaluating research-grade serm products specifically, the serm 10mg product page provides purity and specification details relevant to procurement decisions.

Conclusion

The distinction between enclomiphene citrate and enclomiphene free base is not semantic. The citrate salt offers measurably better crystalline stability, reduced hygroscopicity, and broader formulation options, but it also carries a different molecular weight that must be factored into every concentration calculation. Both forms demand cold, dark, dry storage in the solid state, and both degrade significantly faster once dissolved.

Actionable next steps for researchers in 2026:

  1. Audit current stock: confirm whether materials on hand are labeled as citrate salt or free base and recalculate molar concentrations accordingly.
  2. Implement single-use aliquoting before freezing to eliminate freeze-thaw degradation.
  3. Require HPLC-verified COAs from all suppliers before accepting shipments.
  4. Establish a 48-72 hour use window for all reconstituted solutions stored at 2-8 °C.
  5. Apply the same vendor documentation standards to all research compounds, not just serms.

Reproducibility in enclomiphene research depends on treating the compound form as a controlled variable, not an afterthought.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/enclomiphene-citrate-vs-enclomiphene-stability-storage-and-research-handling.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-15 13:04:102026-09-15 13:04:10Enclomiphene Citrate vs Enclomiphene: Stability, Storage, and Research Handling
Where to Buy Research-Grade Enclomiphene and Enclomiphene Citrate: serm Formulation, COA Standards, and Peptide-Adjunct Study Design

Where to Buy Research-Grade Enclomiphene and Enclomiphene Citrate: serm Formulation, COA Standards, and Peptide-Adjunct Study Design

September 6, 2026/0 Comments/in Uncategorized/by

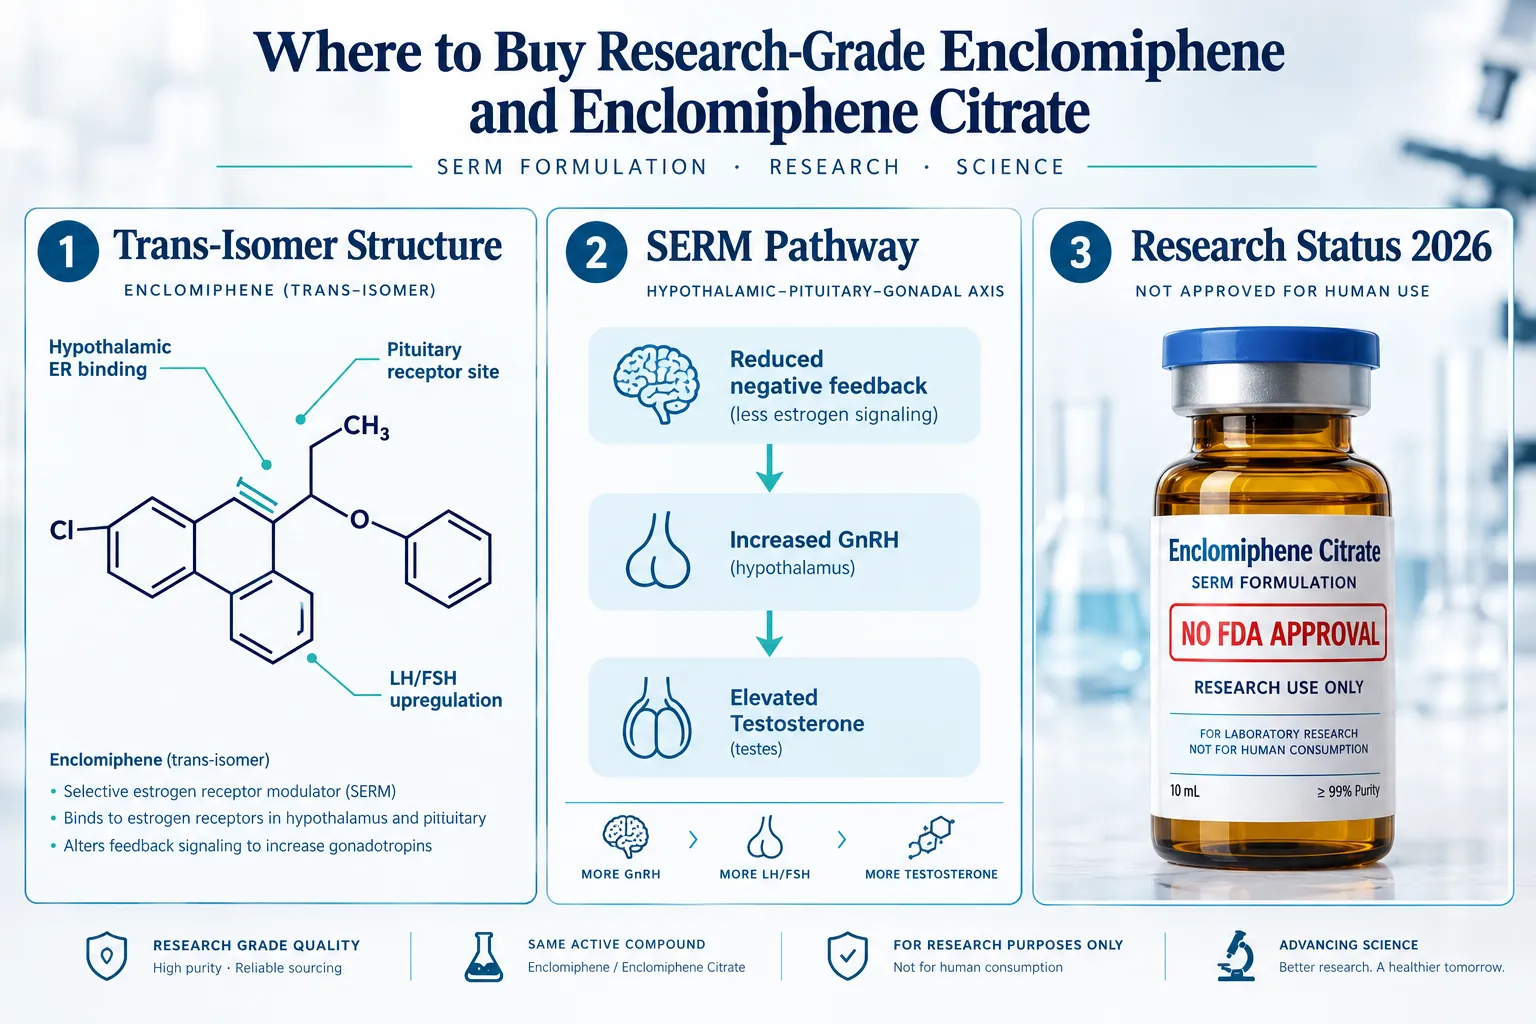
{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'Where to Buy Research-Grade Enclomiphene' (≤42 chars) in crisp white bold sans-serif centered on a deep navy semi-transparent overlay panel, 8% safe margins from every edge, no character touches the edge. Background: bright laboratory setting with glass vials of white crystalline powder, a printed Certificate of Analysis document, and molecular structure diagrams on a lightbox panel. Cool clinical lighting, teal and navy color palette, editorial pharmaceutical research magazine aesthetic, high contrast, sharp focus.","content":["Four-panel labelled infographic diagram (1536×1024) illustrating serm formulation science for enclomiphene and enclomiphene citrate. Panel 1 labeled 'Trans-Isomer Structure' shows a molecular ball-and-stick model with callout lines to 'Enclomiphene (trans)' and 'Zuclomiphene (cis)'. Panel 2 labeled 'Receptor Binding Sites' shows a stylized hypothalamic-pituitary axis diagram with arrows labeled 'LH Release' and 'FSH Release'. Panel 3 labeled 'Capsule Formulation' shows a 12.5mg capsule with callout 'CAS 15690-57-0'. Panel 4 labeled 'Research Use Only' shows a lab bottle with disclaimer label. Clean white background, teal-and-navy palette, thin callout lines, editorial medical-guide polish, no pricing text.","Annotated documentary-style editorial photograph (1536×1024) of a laboratory bench with a printed Certificate of Analysis document as the focal centerpiece, surrounded by HPLC chromatogram printouts and a batch identifier label. Four callout lines with short labels: 'Identity Testing', 'Purity Percentage', 'Batch Number', 'Lot Date Stamp'. Bright studio overhead lighting, cool white and steel-grey tones, shallow depth of field on the COA document, crisp clinical research atmosphere, magazine-quality editorial photography, no dollar amounts or pricing grids.","Numbered step-by-step flow diagram (1536×1024) illustrating a peptide-adjunct study design pairing enclomiphene with GH-axis and GLP-class peptides. Five horizontal steps connected by arrows: Step 1 'Select serm Compound' with icon of capsule vial; Step 2 'Choose Peptide Adjunct' with icons for GH peptide and GLP peptide; Step 3 'Verify COA Documents' with checklist icon; Step 4 'Define Endpoints' with graph icon labeled 'Testosterone, LH, FSH'; Step 5 'Order from Verified Vendor' with shield icon labeled 'Research Use Only'. Deep teal background with white and gold text labels, clean sans-serif typography, bold step numbers, editorial research-design infographic style, no pricing tables."]

Professional landscape hero image () with a reading "Where to Buy Research-Grade Enclomiphene". CRITICAL TYPOGRAPHY RULES:

Fewer than one in ten research buyers who source enclomiphene citrate for laboratory use ever request a full Certificate of Analysis before placing an order, yet COA quality is the single most important variable separating useful research-grade material from unreliable stock. For investigators planning studies around this selective estrogen receptor modulator (serm), understanding where to buy research-grade enclomiphene and enclomiphene citrate, how formulations differ, and how this compound fits into peptide-adjunct study designs is essential groundwork before any order is placed.

Key Takeaways

  • Enclomiphene is the trans-isomer of clomiphene and acts as a serm at hypothalamic and pituitary estrogen receptors, increasing LH, FSH, and endogenous testosterone in research models.
  • Research-grade enclomiphene citrate carries no FDA-approved indication as of 2026; all sourcing is strictly for laboratory use.
  • A valid COA for enclomiphene should include identity testing, purity data, batch number, lot date, and CAS number 15690-57-0.
  • Vendor reputation and third-party COA documentation are the two most critical evaluation criteria when comparing suppliers.
  • Enclomiphene is increasingly paired with GH-axis peptides and GLP-class compounds in combination study designs, requiring careful formulation compatibility planning.

Understanding Enclomiphene and Enclomiphene Citrate as Research serms

Enclomiphene is the trans-isomer of clomiphene, while zuclomiphene is the cis-isomer. Together they make up racemic clomiphene citrate, but enclomiphene is the pharmacologically dominant component at hypothalamic and pituitary estrogen receptors. By occupying those receptors, enclomiphene reduces negative feedback on gonadotropin-releasing hormone, which in turn raises luteinizing hormone (LH) and follicle-stimulating hormone (FSH), and ultimately increases endogenous testosterone production.

Understanding Enclomiphene and Enclomiphene Citrate as Research serms

A 2025 systematic review and meta-analysis covering ten randomized controlled trials and 819 patients found that serm therapy with clomiphene or enclomiphene raised total testosterone by a mean of 273.76 ng/dL versus placebo (95% CI 191.87-355.66). Separate Phase II and Phase III trial data in overweight men with baseline testosterone at or below 300 ng/dL showed mean testosterone rising from approximately 205 ng/dL to 413-446 ng/dL at 16 weeks, while sperm concentration was maintained. These outcomes position enclomiphene as a research tool of genuine interest in the study of secondary hypogonadism and HPG-axis modulation.

Researchers comparing the two salt forms should note that enclomiphene free base and enclomiphene citrate differ in molecular weight and solubility. The citrate salt (CAS 15690-57-0) is the form most commonly listed by research-grade suppliers and the form used in the clinical dose-escalation studies that evaluated 12.5 mg once daily with up-titration to 25 mg. For a detailed side-by-side analysis of how these two forms behave in lab planning contexts, see where researchers compare enclomiphene vs enclomiphene citrate in lab use planning.

Important regulatory note: As of April 2026, enclomiphene has no FDA-approved indication. A prior New Drug Application received a Complete Response Letter in 2015, with the agency requesting additional Phase 3 studies that were never completed. No new NDA or ANDA has been filed since. All procurement and use is therefore strictly for laboratory research purposes.

COA Standards: What Research Buyers Must Demand

When evaluating where to buy research-grade enclomiphene and enclomiphene citrate, the Certificate of Analysis is the non-negotiable starting point. A COA is only as useful as its content, and the research community has seen a wide range in quality, from detailed third-party HPLC reports to single-page documents with no analytical data at all.

COA Standards: What Research Buyers Must Demand

A research-grade COA for enclomiphene citrate should include:

COA Element What to Look For
Identity confirmation Matches CAS 15690-57-0 and "trans-clomiphene citrate"
Purity percentage Typically reported via HPLC; look for 98%+
Batch/lot number Unique identifier traceable to production records
Lot date Production and expiry or retest date
Analytical method HPLC, NMR, or mass spectrometry noted
Third-party testing Independent lab name and accreditation noted

A mid-2026 vendor comparison tracking EU suppliers of enclomiphene found significant disparity: one vendor rated poorly because its COA came from a third party without clear methodology, and another rated even lower because no COA information was publicly accessible at all. This illustrates that vendor reputation and documentation transparency must be evaluated together, not separately.

Buyers should also verify that the supplier explicitly labels enclomiphene as "for research use only" and not for diagnostic or therapeutic application. Reputable vendors group enclomiphene with other selective modulators in research-only catalogs and provide downloadable COA documents linked to specific lot numbers. Publicly accessible lot-specific COA pages, such as those listing identity, purity, and a linked lab-results document, represent the current industry standard that serious buyers should insist upon. One starting point for sourcing verified serm material is the serm 10mg product page, which reflects the kind of labeled research-grade documentation structure buyers should expect.

Peptide-Adjunct Study Design: Pairing Enclomiphene With GH-Axis and GLP-Class Compounds

The most sophisticated question facing researchers sourcing enclomiphene in 2026 is not simply where to buy research-grade enclomiphene and enclomiphene citrate, but how to integrate it into multi-compound study designs alongside peptide hormones. This is where formulation compatibility, endpoint selection, and vendor breadth all converge.

Peptide-Adjunct Study Design: Pairing Enclomiphene With GH-Axis and GLP-Class Compounds

Enclomiphene's mechanism operates at the HPG axis, while growth hormone-releasing peptides such as tesa and ipamorelin act at the GH axis. These are parallel but non-overlapping pathways, which makes them scientifically compatible in combination designs. Researchers studying body composition, metabolic function, or hormonal interplay may find value in pairing enclomiphene with GH-secretagogues. For context on how GH-releasing peptides function mechanistically, see tesa and ipamorelin peptides: mechanism, synergy, and growth hormone research design.

GLP-class peptides introduce a separate dimension. Because enclomiphene modulates estrogen receptor signaling and GLP compounds act on incretin receptors, researchers exploring metabolic endpoints may design studies that track testosterone, LH, FSH, insulin sensitivity, and body composition simultaneously. Understanding how serms interface with polypeptide hormones and GLP-class compounds at the receptor level is foundational to this design work, see estrogen receptors and enclomiphene: how serm research interfaces with polypeptide hormones and GLP-class peptides.

Key design considerations for combination studies:

  • Formulation compatibility: Enclomiphene citrate capsules (typically 12.5 mg or 25 mg) are orally administered; most GH-axis peptides are reconstituted for injection. Separate administration routes reduce interaction risk.
  • Endpoint alignment: Define whether primary endpoints are endocrine (testosterone, LH, FSH), metabolic (insulin sensitivity, body composition), or both.
  • Vendor breadth: Sourcing enclomiphene and peptide adjuncts from a single supplier with consistent COA standards simplifies documentation and batch traceability.
  • Storage compatibility: Enclomiphene citrate is stored at room temperature away from moisture; most peptides require refrigeration or freezing. Separate storage protocols must be planned.

For researchers exploring how molecular size and peptide class shape experimental design more broadly, peptides and polypeptides in modern research: how molecular size shapes function, stability, and experimental design provides useful structural context.

When metabolic pathways are a secondary endpoint, pairing enclomiphene with compounds studied for NAD+ and mitochondrial function adds another layer of complexity. Resources such as 5-Amino-1MQ peptide: how researchers frame NAD+ and metabolic pathway questions illustrate how small-molecule adjuncts are framed in multi-pathway designs.

Conclusion

Sourcing research-grade enclomiphene and enclomiphene citrate in 2026 demands more than finding a supplier with inventory. The actionable steps are clear: demand a lot-specific COA that includes identity confirmation, HPLC purity data, batch traceability, and an explicit "research use only" designation. Evaluate vendor reputation independently of price, and treat the absence of third-party analytical documentation as a disqualifying factor. When building peptide-adjunct study designs, map the mechanistic pathways of each compound before ordering, enclomiphene's HPG-axis activity is scientifically compatible with GH-axis peptides and GLP-class compounds, but only a well-structured protocol will yield interpretable data. Researchers who invest time in vendor evaluation and study design before procurement will consistently produce more reliable, reproducible results than those who treat sourcing as an afterthought.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/where-to-buy-research-grade-enclomiphene-and-enclomiphene-citrate-serm-formulati.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-06 13:04:372026-09-06 13:04:37Where to Buy Research-Grade Enclomiphene and Enclomiphene Citrate: serm Formulation, COA Standards, and Peptide-Adjunct Study Design
Prostate Specific Antigen, Enclomiphene, and Peptide Hormones: How Labs Design serm and GLP-Class Hormone Studies

Prostate Specific Antigen, Enclomiphene, and Peptide Hormones: How Labs Design serm and GLP-Class Hormone Studies

September 5, 2026/0 Comments/in Uncategorized/by

More than 40 million PSA tests are ordered in the United States each year, making prostate-specific antigen one of the most tracked biomarkers in modern medicine. Yet PSA does not exist in isolation. Increasingly, research programs studying Prostate Specific Antigen, Enclomiphene, and Peptide Hormones are weaving this marker into broader hormone study frameworks, frameworks that now include selective estrogen receptor modulators (serms) like enclomiphene and peptide-based agents in the GLP class. Understanding how labs design these studies reveals why PSA belongs in the same safety panel as testosterone, LH, FSH, and pharmacokinetic peptide data.

Key Takeaways

  • PSA serves as a critical safety biomarker in male hormone studies, including serm trials involving enclomiphene citrate.
  • Enclomiphene raises testosterone while preserving sperm production, distinguishing it from testosterone replacement therapy.
  • GLP-1 receptor agonist trials use ascending-dose, randomized, double-blind designs with composite endpoints.
  • Labs increasingly combine PSA monitoring with peptide pharmacokinetic data to build complete hormonal safety profiles.
  • Regulatory complexity, such as enclomiphene's relationship to clomiphene, directly shapes how study protocols are written.

PSA as a Biomarker in Hormone Research

PSA as a Biomarker in Hormone Research

PSA is a glycoprotein produced by prostate epithelial cells, and its serum level rises when androgen signaling increases. That biological fact makes it indispensable in any study that deliberately elevates testosterone. When a lab designs a serm trial for secondary hypogonadism, the protocol must account for the downstream androgenic effect on prostate tissue, and PSA is the most practical, non-invasive way to do that.

In enclomiphene phase III safety work, clinical laboratory tests form a core safety endpoint alongside physical exams, visual acuity checks, and slit-lamp eye examinations. Although published summaries do not always headline PSA explicitly, practitioners running off-label hormone protocols consistently include it in serial safety panels. The reasoning is straightforward: if enclomiphene successfully raises morning total testosterone from below 300 ng/dL into the normal range, prostate tissue will experience that androgen signal. Monitoring PSA at baseline, mid-study, and endpoint catches any clinically meaningful rise before it becomes a safety event.

Why PSA matters beyond prostate cancer screening:

  • It quantifies androgenic stimulation of prostate tissue in real time.
  • It provides a continuous safety variable rather than a binary pass/fail outcome.
  • It allows dose-adjustment decisions during titration phases.
  • It satisfies FDA expectations for safety data in androgen-modulating drug applications.

For researchers exploring therapeutic peptides alongside serms, PSA anchors the hormone safety panel to a well-validated clinical standard.

How Enclomiphene serm Studies Are Structured

The design of enclomiphene trials illustrates how Prostate Specific Antigen, Enclomiphene, and Peptide Hormones research frameworks are built from the ground up. Enclomiphene citrate is the trans-isomer of clomiphene, and its regulatory path has been complicated precisely because the FDA must decide how to treat the relationship between an isomer and an already-marketed parent compound. As of 2026, an NDA remains in progress with outstanding FDA questions on that relationship.

Phase III enclomiphene trials enrolled men aged 18-65 with secondary hypogonadism, defined as morning total testosterone below 300 ng/dL on two separate occasions with non-elevated LH. The open-label, escalating-dose design started participants at 12.5 mg with titration to 25 mg if needed over six months. The key clinical finding: enclomiphene raises total testosterone into the normal range while preserving LH, FSH, and sperm production, a meaningful advantage over exogenous testosterone replacement, which suppresses the hypothalamic-pituitary-gonadal axis.

"Enclomiphene's ability to maintain spermatogenesis while restoring testosterone makes it a structurally different intervention than TRT, and that difference demands a different safety monitoring strategy."

For more on how serm compounds are categorized and studied, researchers can explore current literature on receptor-selective mechanisms.

Standard safety panel in enclomiphene studies:

Endpoint Category Specific Measures
Androgenic safety PSA, hematocrit, lipid panel
Reproductive hormones Total testosterone, LH, FSH
Ocular safety Visual acuity, slit-lamp exam
General clinical labs CMP, CBC, adverse event log

GLP-Class Peptide Hormone Study Design

GLP-Class Peptide Hormone Study Design

The design logic for GLP-1 receptor agonist studies shares structural DNA with serm trials but diverges sharply in endpoint architecture. A first-in-human phase I study of a novel oral small-molecule GLP-1 receptor agonist illustrates the current template: three sequential parts covering single ascending dose (2.5-50 mg in healthy adults), a 28-day multiple ascending dose in healthy adults, and a 28-day weekly-titration multiple ascending dose in overweight or obese adults. All three parts are randomized, double-blind, and placebo-controlled, with safety and tolerability as primary endpoints and pharmacokinetics and pharmacodynamics as key secondary measures.

When labs repurpose existing GLP-1 agents for new indications, such as substance use disorders or neurodegenerative disease, a common design strategy emerges: keep established metabolic dosing (for example, semaglutide up to 1.0 mg once weekly) and concentrate design innovation on endpoints and patient populations. This approach reduces regulatory uncertainty because pharmacokinetic data already exists.

Researchers interested in signaling peptides and their receptor interactions will recognize that GLP-1 receptor agonists operate through similar second-messenger cascades as other peptide classes, making cross-class study design comparisons genuinely useful.

Key GLP-1 trial design principles in 2026:

  • Integrated cardiometabolic endpoints (cardiovascular events, kidney disease, weight)
  • "Low and slow" titration strategies to balance tolerability with efficacy
  • Real-world data sets used to power sample sizes and set event rate assumptions
  • Bridging studies that connect known pharmacology to new therapeutic uses

For context on how stacking or combining peptide agents affects study design, the discussion of single peptide vs stack approaches is directly relevant to multi-arm GLP-1 trial architectures.

Integrating PSA, serm, and Peptide Data Into a Unified Safety Framework

Integrating PSA, serm, and Peptide Data Into a Unified Safety Framework

The convergence of Prostate Specific Antigen, Enclomiphene, and Peptide Hormones research into unified safety frameworks reflects a broader shift in how hormone studies are powered and monitored. Labs running combination protocols, for instance, pairing a serm with a growth hormone-releasing peptide, must build safety panels that capture both androgenic effects (PSA, hematocrit) and peptide-specific effects (IGF-1, fasting glucose, injection-site reactions).

Research on Sermorelin, Ipamorelin, and CJC-1295 dosage demonstrates how multi-peptide protocols require layered monitoring, just as multi-arm GLP-1 trials require composite endpoint tracking. Similarly, Tesamorelin vs Sermorelin comparisons highlight how small structural differences between peptide agents can produce meaningfully different safety profiles, a lesson directly applicable to enclomiphene's isomeric relationship to clomiphene.

Labs designing these studies in 2026 are also increasingly using next-generation cardio-kidney-metabolic outcome frameworks, which propose explicit design principles emphasizing integrated endpoints, careful patient selection, and robust trial architectures. When PSA is included as a continuous safety variable rather than a binary screening test, it fits naturally within these multi-domain outcome structures.

Practical checklist for integrated hormone study design:

  • Define androgen exposure with testosterone, LH, FSH at baseline and each visit
  • Include PSA at minimum at baseline, 3 months, and endpoint
  • Add peptide-specific PK sampling windows aligned with dosing intervals
  • Pre-specify PSA thresholds that trigger dose hold or discontinuation
  • Align FDA engagement strategy (pre-IND, Type C, pre-NDA meetings) with study design milestones

For labs sourcing research-grade compounds, ensuring purity is non-negotiable. Lab tested peptides with verified certificates of analysis are the baseline standard for any protocol that will generate safety data intended for regulatory review.

Conclusion

The intersection of Prostate Specific Antigen, Enclomiphene, and Peptide Hormones in modern hormone study design is not accidental, it reflects the biological reality that androgen modulation, receptor selectivity, and peptide signaling all converge on shared safety endpoints. PSA is not simply a prostate cancer screening tool; it is a dynamic androgenic biomarker that belongs in every male hormone study protocol.

Actionable next steps for researchers and clinicians:

  1. Include PSA as a continuous safety variable in any serm or androgen-modulating protocol, with pre-specified thresholds for dose adjustment.
  2. Apply GLP-1 trial design principles, ascending dose, randomized, double-blind, composite endpoints, to novel peptide programs wherever regulatory precedent is limited.
  3. Use real-world prescribing data and existing pharmacokinetic datasets to power sample sizes and reduce phase II risk.
  4. Engage FDA early through pre-IND meetings when an investigational compound has a structural relationship to an approved drug, as enclomiphene's path illustrates.
  5. Source only verified, lab tested peptides for any study generating data intended for regulatory submission.

Rigorous study design, comprehensive biomarker panels, and early regulatory alignment are the pillars that turn promising hormone research into actionable clinical evidence.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prostate-specific-antigen-enclomiphene-and-peptide-hormones-how-labs-design-serm.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-05 13:05:452026-09-05 13:05:45Prostate Specific Antigen, Enclomiphene, and Peptide Hormones: How Labs Design serm and GLP-Class Hormone Studies
Estrogen Receptors and Enclomiphene: How serm Research Interfaces With Polypeptide Hormones and GLP‑Class Peptides

Estrogen Receptors and Enclomiphene: How serm Research Interfaces With Polypeptide Hormones and GLP‑Class Peptides

August 28, 2026/0 Comments/in Uncategorized/by

Fewer than 15% of men diagnosed with functional hypogonadism in 2026 are offered non-testosterone pharmacological alternatives, yet enclomiphene citrate, a selective estrogen receptor modulator (serm), has quietly accumulated a substantial research record that intersects with some of the most active areas in peptide science. Understanding estrogen receptors and enclomiphene, and how serm research interfaces with polypeptide hormones and GLP-class peptides, is no longer a niche academic exercise. It is a practical framework for clinicians, researchers, and informed patients navigating a rapidly expanding hormonal-optimization landscape.

Key Takeaways

  • Enclomiphene blocks hypothalamic estrogen receptors to amplify GnRH, LH, and FSH output, preserving endogenous testosterone production.
  • Emerging evidence points to a bidirectional crosstalk between estrogen receptor signaling and GLP-1 class peptide pathways, particularly in the arcuate nucleus.
  • Polypeptide hormones such as GHRH analogues and GLP-class peptides operate through distinct receptor families but share downstream metabolic overlap with serm-driven hormonal cascades.
  • As of 2026, enclomiphene remains off-label for male hypogonadism in most jurisdictions, while GLP-1 receptor agonists hold broad regulatory approval.
  • Purity and third-party verification of research peptides are critical variables when studying these interactions at the lab level.

How Enclomiphene Targets Estrogen Receptors

Enclomiphene is the trans-isomer of clomiphene citrate. While clomiphene contains both the zuclomiphene (cis) and enclomiphene (trans) isomers, the trans form carries most of the receptor-antagonist activity at the hypothalamic level. It binds competitively to estrogen receptor alpha (ERa) and estrogen receptor beta (ERb) in the hypothalamus and pituitary, blocking the negative feedback that estradiol normally exerts on gonadotropin-releasing hormone (GnRH) pulsatility.

How Enclomiphene Targets Estrogen Receptors

The result is a measurable increase in GnRH pulse frequency, which drives luteinizing hormone (LH) and follicle-stimulating hormone (FSH) secretion from the anterior pituitary. Elevated LH then stimulates Leydig cell testosterone synthesis in the testes. This mechanism is fundamentally different from exogenous testosterone replacement, which suppresses the hypothalamic-pituitary-gonadal (HPG) axis through negative feedback. Enclomiphene preserves, and actively stimulates, endogenous production.
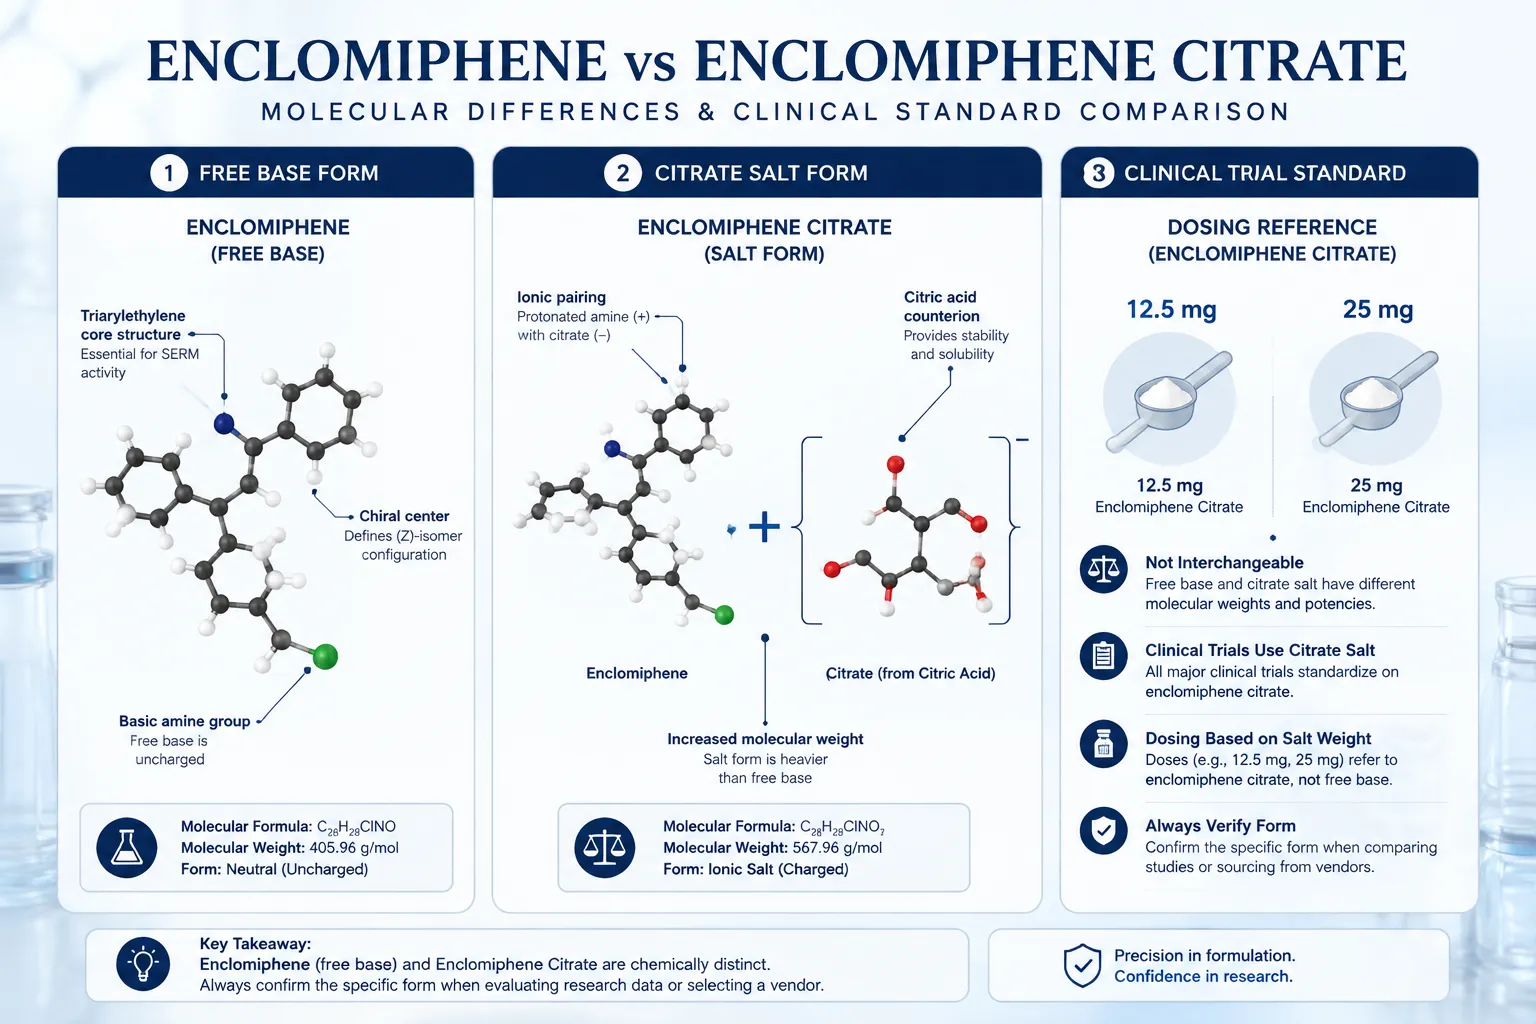
Key receptor pharmacology points:

  • ERa blockade in the hypothalamus is the primary driver of GnRH disinhibition
  • ERb activity in peripheral tissues influences mood, bone density, and cardiovascular tone
  • Enclomiphene's selectivity profile differs from tamoxifen and raloxifene, making direct class comparisons imprecise

A 2025 systematic review comparing enclomiphene to testosterone replacement in male functional hypogonadism found that enclomiphene produced comparable testosterone normalization while maintaining sperm production, a clinically significant advantage for men of reproductive age.

serm Research Interfaces With Polypeptide Hormones: The HPG-Peptide Connection

The phrase "estrogen receptors and enclomiphene: how serm research interfaces with polypeptide hormones and GLP-class peptides" captures a genuinely complex biological intersection. The HPG axis does not operate in isolation. It is modulated by a network of polypeptide signals, including growth hormone-releasing hormone (GHRH), kisspeptin, and GLP-1 receptor agonists.

serm Research Interfaces With Polypeptide Hormones: The HPG-Peptide Connection

GHRH analogues and the serm context

GHRH analogues such as sermorelin and CJC-1295 stimulate growth hormone (GH) release from the anterior pituitary through GHRH receptor activation. Research into sermorelin and ipamorelin CJC-1295 combinations has shown that GH secretion interacts with sex hormone-binding globulin (SHBG) levels, indirectly influencing free testosterone availability. When enclomiphene raises total testosterone, the concurrent use of GHRH analogues may alter SHBG dynamics, creating a meaningful lab-level variable.

For researchers exploring IPA sermorelin stack protocols, understanding how estrogen receptor modulation affects the downstream hormonal environment is essential for interpreting assay results accurately.

GLP-1 class peptides: the emerging crosstalk

GLP-1 receptor agonists, originally developed for glycemic control, have revealed unexpected neuroendocrine activity. GLP-1 receptors are expressed in the arcuate nucleus of the hypothalamus, a region dense with kisspeptin neurons that directly regulate GnRH pulsatility. Estrogen receptors are co-expressed in the same neuronal populations.

"The arcuate nucleus functions as a convergence point where estrogen signaling, GLP-1 receptor activation, and kisspeptin-driven GnRH control interact in ways that current research is only beginning to map."

This means that a serm like enclomiphene, acting on hypothalamic ERa, may have functional crosstalk with GLP-1 receptor signaling in the same anatomical region. Researchers working with GLP-1 peptides in metabolic or neuroendocrine models should account for this overlap when designing experiments that also involve ER-modulating compounds.

The GLP-2 peptide class, while primarily intestinotrophic, also shows central nervous system expression patterns that warrant attention in multi-peptide research designs.

Research Trajectory and Practical Positioning in 2026

As of 2026, the regulatory landscape remains fragmented. Enclomiphene holds no major market authorization specifically for male hypogonadism in the United States or European Union, though off-label prescribing is common in men's health clinics. GLP-1 receptor agonists, by contrast, carry broad approvals for type 2 diabetes and obesity management, with ongoing trials in cardiovascular and neurodegenerative indications.

Research Trajectory and Practical Positioning in 2026

Positioning comparison at a glance:

Factor Enclomiphene (serm) GLP-1 Class Peptides
Primary target Hypothalamic ERa/ERb GLP-1 receptor (gut, brain)
Regulatory status (2026) Off-label (most jurisdictions) Approved (metabolic indications)
HPG axis effect Stimulatory (raises LH, FSH, T) Indirect (arcuate nucleus crosstalk)
Fertility preservation Yes Not established
Research peptide purity needs High High

For lab-level studies examining these interactions, sourcing lab tested peptides with verified purity documentation is non-negotiable. Contaminants or isomeric impurities can confound receptor-binding assays and produce misleading downstream hormone data.

Researchers interested in the growth hormone axis should also review tesa peptide benefits data, as tesa's effects on visceral fat and IGF-1 levels create additional metabolic variables relevant to any multi-compound hormonal study design.

Forward-looking analyst perspective (speculative): The most likely near-term research direction involves combination protocols that pair serm-driven HPG axis stimulation with GLP-1 receptor agonism to address both hypogonadism and metabolic syndrome simultaneously. This is not yet supported by randomized controlled trial data, but mechanistic rationale is strong enough to justify structured pilot studies.
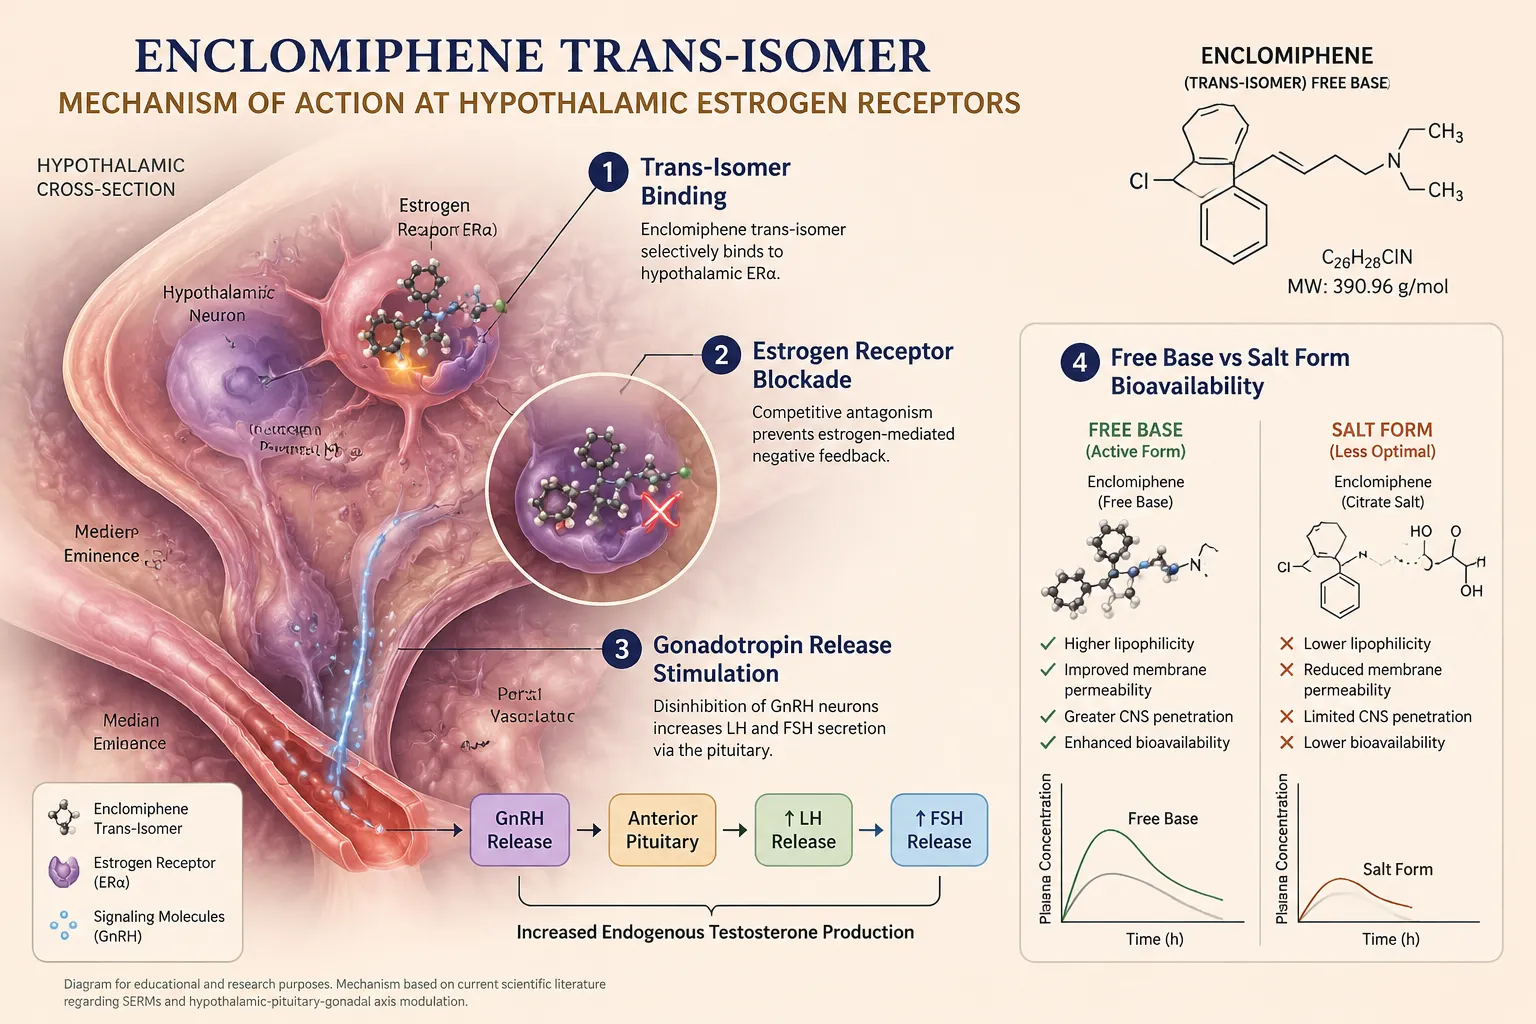
Conclusion

Estrogen receptors and enclomiphene represent a well-characterized pharmacological axis. How serm research interfaces with polypeptide hormones and GLP-class peptides is a newer and more complex question, one that demands rigorous methodology, verified reagents, and a clear understanding of the convergent biology at the hypothalamic level.
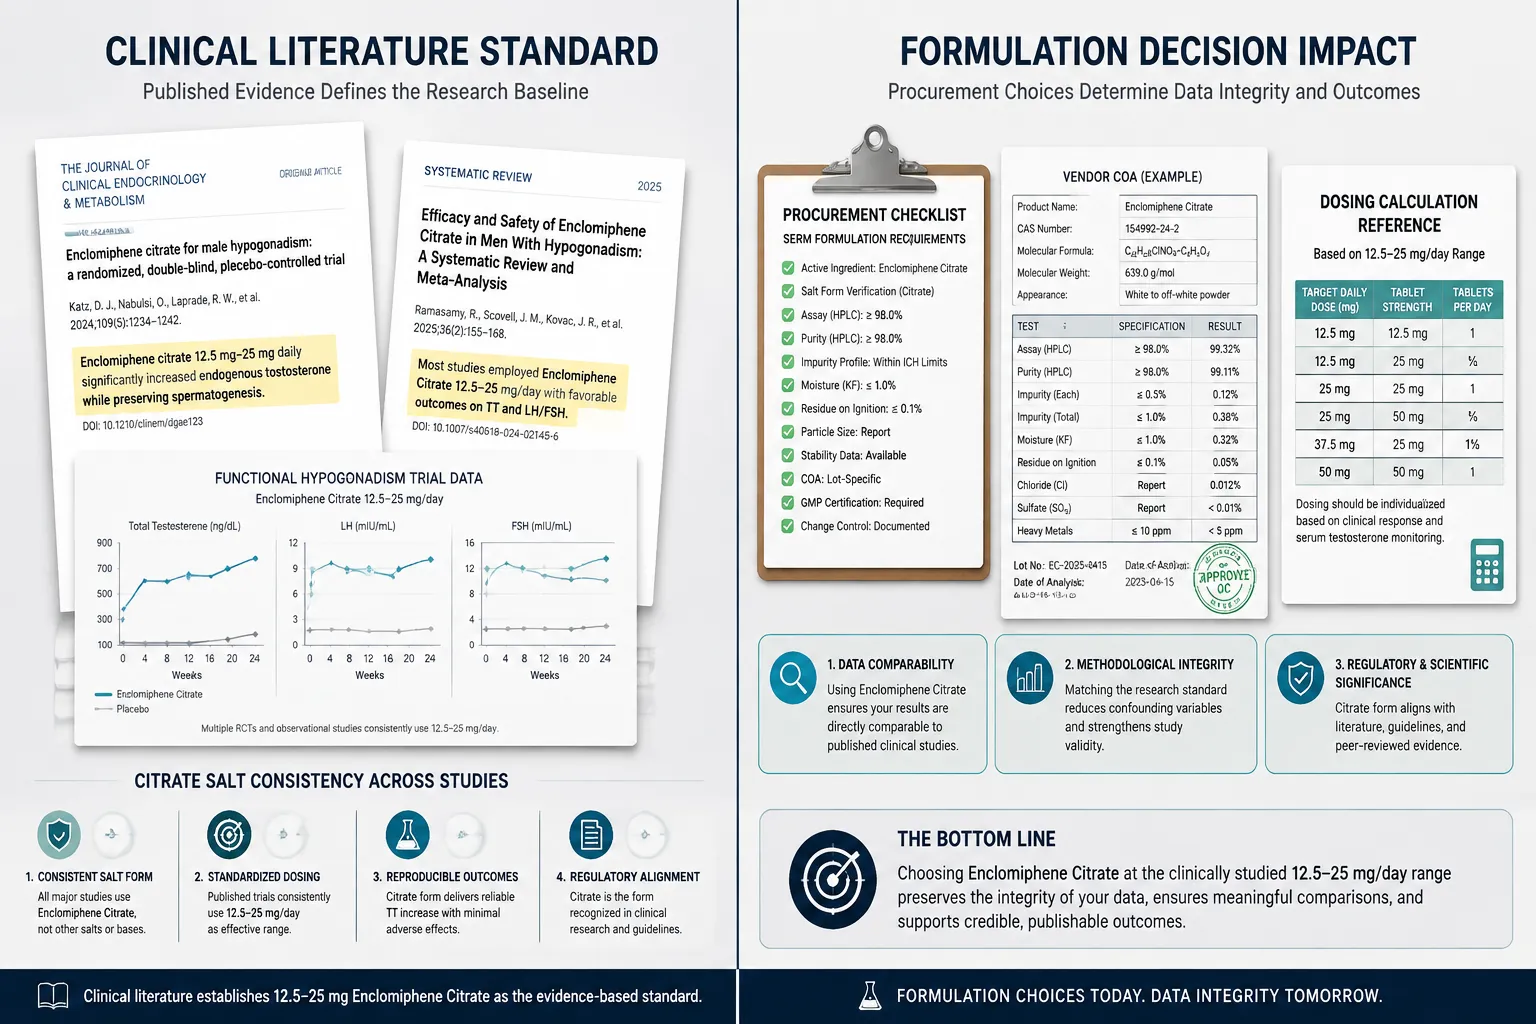
Actionable next steps for researchers and clinicians:

  1. Map estrogen receptor expression alongside GLP-1 receptor distribution in any neuroendocrine study design that involves enclomiphene or related serms.
  2. Account for SHBG dynamics when combining GHRH analogues with serm protocols, as free hormone availability will shift.
  3. Use only third-party verified, lab tested peptides to eliminate purity as a confounding variable.
  4. Monitor the regulatory environment closely, enclomiphene's off-label status may shift as trial data accumulates through 2026 and beyond.
  5. Treat GLP-1 and serm crosstalk findings as hypothesis-generating until controlled trial data is available.

The intersection of serm pharmacology and peptide hormone research is not a fringe topic. It is where the next generation of hormonal optimization protocols will be built.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/estrogen-receptors-and-enclomiphene-how-serm-research-interfaces-with-polypeptid.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-28 13:05:392026-08-28 13:05:39Estrogen Receptors and Enclomiphene: How serm Research Interfaces With Polypeptide Hormones and GLP‑Class Peptides
Enclomiphene vs Enclomiphene Citrate: How Labs Choose Between Research Formulations and Vendors

Enclomiphene vs Enclomiphene Citrate: How Labs Choose Between Research Formulations and Vendors

August 26, 2026/0 Comments/in Uncategorized/by

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay (≤42 chars): 'Enclomiphene vs Enclomiphene Citrate: How', crisp white sans-serif on a deep navy semi-transparent overlay panel, centered with 8% safe margins from every edge. Background: bright clinical research laboratory scene in daylight, glass vials of white crystalline powder, molecular structure diagrams on a lightboard, stainless steel lab bench, clean scientific aesthetic. Teal, navy, and white palette. Editorial magazine-cover quality, high contrast, sharp focus on foreground vials.","content":["Four-panel labelled comparison infographic (1536×1024) on a clean white background with teal-and-navy palette: Panel 1 labeled 'Free Base Form' showing a molecular diagram of enclomiphene with callout lines pointing to 'No salt counterion', 'Higher lipophilicity', 'Solvent-sensitive'; Panel 2 labeled 'Citrate Salt Form' showing enclomiphene citrate molecule with callouts 'Citric acid counterion', 'Better aqueous solubility', 'Standard in clinical trials'; Panel 3 labeled 'Dosing Reference' with callout '12.5-25 mg range'; Panel 4 labeled 'COA Check' with callouts 'Purity %', 'Salt form confirmed', 'HPLC trace'. Thin dividing lines between panels, editorial medical-guide polish, labels 1-6 words each inside 5% safe margin.","Annotated step-by-step numbered flow diagram (1536×1024) on a light gray background with deep teal and charcoal palette showing a lab vendor evaluation process: Step 1 'Request COA' with callout arrow pointing to a document icon labeled 'HPLC + NMR required'; Step 2 'Confirm Salt Form' with callout 'Free base vs citrate'; Step 3 'Check Solvent Compatibility' with callout 'DMSO or aqueous buffer'; Step 4 'Verify Stability Data' with callout 'Storage temp, shelf life'; Step 5 'Cross-reference Literature Dose' with callout '12.5-25 mg citrate standard'. Bold numbered circles in teal, clean sans-serif labels, arrows connecting each step, editorial scientific-guide quality, fully inside 5% safe margins.","Split-screen editorial landscape image (1536×1024): left half shows a close-up of a printed Certificate of Analysis document on a stainless steel lab bench under bright studio lighting, with three short annotation callouts, 'Purity above 98%', 'Salt form declared', 'Endotoxin tested', in teal label boxes with thin pointer lines; right half shows a mid-shot of a South Asian female researcher in her 30s in a white lab coat examining a small amber glass vial against a bright window, expression focused and analytical. High-contrast split composition, navy dividing line down the center, warm daylight on the right, cool studio light on the left, magazine editorial quality."]

Professional landscape hero image () with a reading "Enclomiphene vs Enclomiphene Citrate: How". CRITICAL TYPOGRAPHY RULES:

Only one letter separates the two names on most vendor catalogs, yet that difference carries real consequences for solubility, dosing math, and the validity of comparisons to published clinical data. Understanding the distinction between enclomiphene and enclomiphene citrate is not a trivial naming exercise, it is a foundational step in rigorous procurement for any research program working with selective estrogen receptor modulators (serms).

This guide focuses on the practical purchasing and formulation considerations that matter most: salt forms, solvent compatibility, stability, and how to interpret vendor Certificates of Analysis (COAs) when evaluating enclomiphene vs enclomiphene citrate and choosing between research formulations and vendors.

Key Takeaways

  • Enclomiphene is the free base form; enclomiphene citrate is the salt form created by pairing enclomiphene with citric acid, they are not interchangeable by weight.
  • All major clinical trials have used the citrate salt, making it the reference standard for dose comparisons.
  • The free base form offers higher lipophilicity but lower aqueous solubility, which affects solvent choice in research settings.
  • COA review should confirm salt form, purity by HPLC, and endotoxin levels before any procurement decision is made.
  • Vendor transparency, including NMR data and batch-specific stability information, is the clearest signal of supply chain reliability.

Understanding the Chemistry: Free Base vs Salt Form

Understanding the Chemistry: Free Base vs Salt Form

Enclomiphene is the trans-isomer of clomiphene, a serm that acts on hypothalamic estrogen receptors to stimulate endogenous gonadotropin release. When vendors list "enclomiphene" without qualification, they typically mean the free base form, the molecule without an ionic counterpart. "Enclomiphene citrate" refers to the same active molecule paired with citric acid to form a salt.

Why does this matter for labs?

The molecular weight difference is significant. Enclomiphene free base has a molecular weight of approximately 406 g/mol. Enclomiphene citrate adds the citrate counterion, raising the molecular weight to roughly 598 g/mol. That means a 25 mg dose of enclomiphene citrate does not deliver 25 mg of the active trans-isomer, it delivers proportionally less. Labs that fail to account for this difference will prepare solutions at incorrect molar concentrations, potentially compromising experimental reproducibility.

Solubility profiles also diverge:

Property Enclomiphene (Free Base) Enclomiphene Citrate
Aqueous solubility Low Moderate
Lipophilicity Higher Lower
Preferred solvent DMSO, ethanol Aqueous buffers, DMSO
Clinical trial standard No Yes

For researchers already familiar with sourcing frameworks for other research compounds, such as those described in guides on AOD-9604 storage and traceability, the same principle applies here: salt form affects both preparation protocol and shelf stability.

How Clinical Literature Shapes Formulation Choices

The clinical research record is unambiguous. Studies examining enclomiphene in functional hypogonadism have consistently used the citrate salt, with dosing patterns in trials typically ranging from 12.5 mg to 25 mg of enclomiphene citrate. A 2025 systematic review found that enclomiphene and clomiphene produced comparable testosterone restoration while preserving spermatogenesis, a meaningful distinction from exogenous testosterone therapy.

"Because all published efficacy and safety data reference the citrate salt, labs that use the free base form cannot directly map their in-vitro or preclinical findings onto human clinical benchmarks without a molar conversion step."

This is not a minor administrative detail. It is the difference between research that contributes to a translatable evidence base and research that exists in an isolated methodological silo.

As of mid-2026, no FDA-approved enclomiphene product exists. The compound retains investigational status, which means the regulatory environment for compounding and research supply remains fluid. Labs working in the broader hormone research space should monitor compounding pharmacy guidance closely, as regulatory shifts can affect both availability and permissible formulation types.

How Labs Choose Between Research Formulations and Vendors: A Practical Framework

How Labs Choose Between Research Formulations and Vendors: A Practical Framework

When evaluating enclomiphene vs enclomiphene citrate and choosing between research formulations and vendors, experienced procurement teams apply a structured review process. The following framework reflects best practices drawn from the clinical and regulatory context.

Step 1: Confirm the Salt Form on the COA

Every COA should explicitly state whether the material is the free base or citrate salt. If the document lists only "enclomiphene" without specifying the form, request clarification before purchasing. Ambiguity at this stage is a red flag.

Step 2: Review HPLC Purity Data

Purity should be confirmed by high-performance liquid chromatography (HPLC). Acceptable research-grade purity typically sits at 98% or above. Some vendors also provide nuclear magnetic resonance (NMR) spectroscopy data, which confirms molecular identity, not just purity. NMR data is a strong positive signal of vendor credibility.

Step 3: Check Isomeric Composition

Enclomiphene is the trans-isomer of clomiphene. Vendors sourcing from lower-quality synthesis pipelines may supply material with elevated zuclomiphene (the cis-isomer) contamination. The COA should confirm trans-isomer predominance.

Step 4: Evaluate Solvent Compatibility Documentation

Vendors should provide solubility data specific to the form they are selling. For aqueous-based assay systems, the citrate salt is the practical choice. For lipid-based or organic solvent systems, the free base may be appropriate. This mirrors the solvent-compatibility thinking applied in other research compound categories, including those covered in the GHK-Cu copper peptide sourcing guide.

Step 5: Verify Stability and Storage Specifications

Batch-specific stability data, including recommended storage temperature and projected shelf life, should accompany any research-grade order. Enclomiphene citrate is generally stable at -20°C when stored desiccated and away from light. Free base formulations may require tighter controls depending on the solvent system used.

Labs building out broader serm and peptide research programs can apply similar sourcing discipline across compound classes, the documentation-first approach outlined in resources like the BPC-157 core peptides documentation research guide translates directly to this workflow.

Interpreting COAs and Avoiding Common Vendor Pitfalls

Interpreting COAs and Avoiding Common Vendor Pitfalls

The COA is the single most important document in the vendor evaluation process. A well-constructed COA for enclomiphene citrate should include:

  • Identity confirmation: HPLC chromatogram and NMR spectrum
  • Purity result: Percentage purity with method stated
  • Salt form declaration: Explicit statement of free base or citrate
  • Isomeric ratio: Trans-isomer percentage confirmed
  • Endotoxin testing: Particularly relevant for in-vivo research models
  • Batch number and date: Enables traceability and reorder consistency

Vendors who resist providing full COA documentation, or who supply generic certificates not tied to a specific batch, should be deprioritized regardless of price.

For labs that also work with metabolic or mitochondrial research compounds, the same COA standards apply across the board, as illustrated in sourcing discussions for MOTS-C peptide and mitochondrial biogenesis research and SS-31 mitochondrial research themes.

Conclusion

The distinction between enclomiphene and enclomiphene citrate is not semantic, it is structural, chemical, and methodologically significant. Labs that treat the two names as interchangeable risk dosing errors, compromised data comparability, and wasted resources.

Actionable next steps for research teams:

  1. Audit existing inventory to confirm whether current stock is free base or citrate salt, and recalculate molar concentrations accordingly.
  2. Update procurement checklists to require explicit salt form declaration on all COAs.
  3. Prioritize vendors who supply batch-specific HPLC and NMR data, with confirmed trans-isomer purity above 98%.
  4. Align all dosing references to the citrate salt standard used in published clinical literature (12.5-25 mg range) to maintain translational validity.
  5. Monitor the regulatory environment through mid-2026 and beyond, as the compounding and investigational compound landscape for enclomiphene continues to evolve.

Rigorous formulation awareness is not an obstacle to productive research, it is the foundation that makes research results meaningful.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/enclomiphene-vs-enclomiphene-citrate-how-labs-choose-between-research-formulatio.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-26 13:03:582026-08-26 13:03:58Enclomiphene vs Enclomiphene Citrate: How Labs Choose Between Research Formulations and Vendors
Page 1 of 212
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top