Trazodone, Appetite, and Peptide Weight-Loss Models: Controlling Sedation, Sleep, and Food-Intake Confounders
Roughly 40% of adults prescribed trazodone use it primarily for sleep rather than depression, yet most peptide weight-loss trials fail to screen for concurrent sedative use. That gap is not trivial. When a sedating psychotropic runs alongside a metabolic peptide like retatrutide or a GLP-1 receptor agonist, the result is a tangled web of overlapping effects on sleep architecture, daytime activity, meal timing, and caloric intake. Untangling those effects is exactly what rigorous study design demands. Understanding trazodone, appetite, and peptide weight-loss models: controlling sedation, sleep, and food-intake confounders is therefore essential for anyone designing or interpreting metabolic research in 2026.
Key Takeaways
- Trazodone is largely weight-neutral but can shift sleep timing, reduce daytime activity, and alter meal patterns, all of which confound peptide weight-loss data.
- GLP-1 and related peptides reduce weight primarily by cutting caloric intake, not by raising energy expenditure, making food-intake measurement especially critical.
- Sleep duration and quality are independent predictors of weight-loss success; trazodone's sleep-extending effects must be separated from peptide-driven changes.
- Late-evening eating and compressed pre-sleep intervals measurably undermine peptide efficacy, and trazodone can shift both behaviors.
- Researchers should apply standardized confounder controls, actigraphy, meal-timing logs, sedation scales, before attributing weight outcomes to peptide pharmacology alone.
Trazodone's Pharmacological Profile and Its Weight Implications
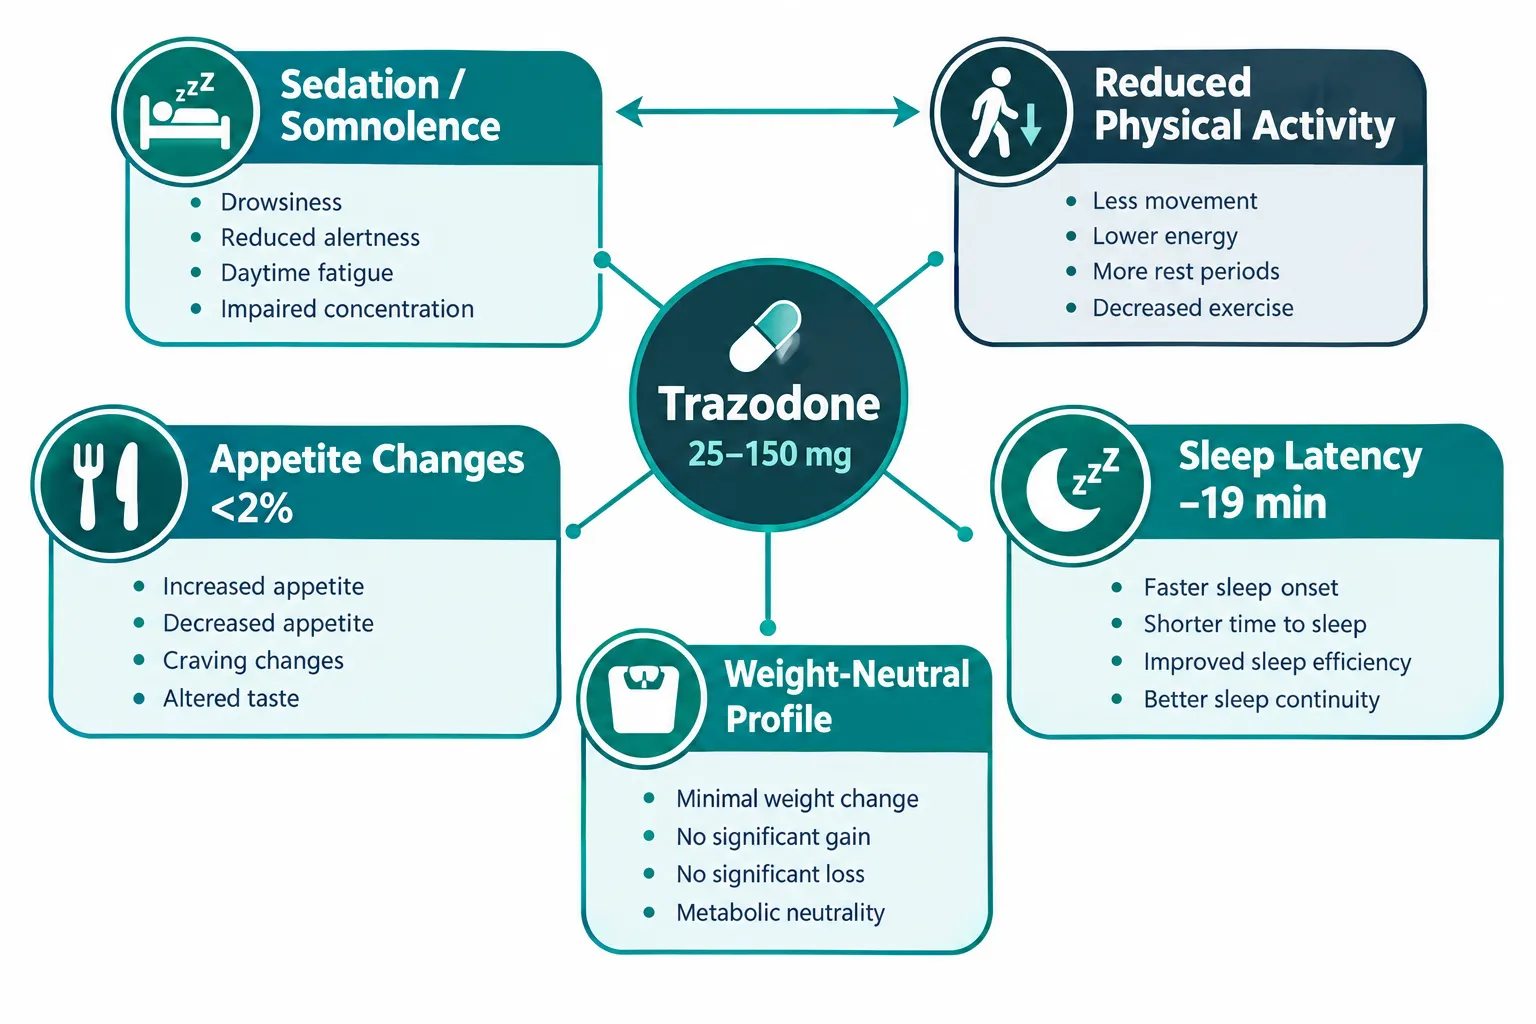
Trazodone is a serotonin antagonist and reuptake inhibitor (SARI) with pronounced sedative and anxiolytic properties at low doses of 25-75 mg, reaching full antidepressant effect at 150-300 mg. Its sedation profile places it alongside mirtazapine and tricyclics in terms of CNS burden, a fact that distinguishes it sharply from activating agents such as bupropion.
On appetite and weight, the picture is reassuring but nuanced:
- Increased appetite is listed as an adverse reaction with an incidence below 2% in controlled trials.
- Roughly equal proportions of trial participants gained weight (about 5%) and lost weight (about 6%), supporting a predominantly weight-neutral classification.
- Long-term data show minimal impact on glucose metabolism or body composition.
- Any observed weight change may partly reflect improved depressive symptoms rather than direct pharmacologic action on appetite circuits.
"Trazodone lacks the appetite-stimulating profile seen with mirtazapine and many antipsychotics, but its sedation burden is a separate and underappreciated confounder in metabolic studies."
Where trazodone becomes problematic in research is not through appetite stimulation but through behavioral pathways: increased total sleep time (approximately 40 minutes in randomized trials), reduced sleep-onset latency (roughly 19 minutes), and daytime grogginess that suppresses physical activity. These effects are most prominent at 50-150 mg, the exact range used off-label for insomnia.
Importantly, the American Academy of Sleep Medicine and VA/DoD guidelines advise against trazodone for chronic insomnia disorder, recommending it only when other options fail or comorbid depression is present. Despite this, off-label prescribing remains widespread, meaning researchers enrolling metabolic-study participants will frequently encounter undisclosed trazodone use.
GLP-1 and Retatrutide Mechanisms: Why Food Intake Measurement Is Non-Negotiable
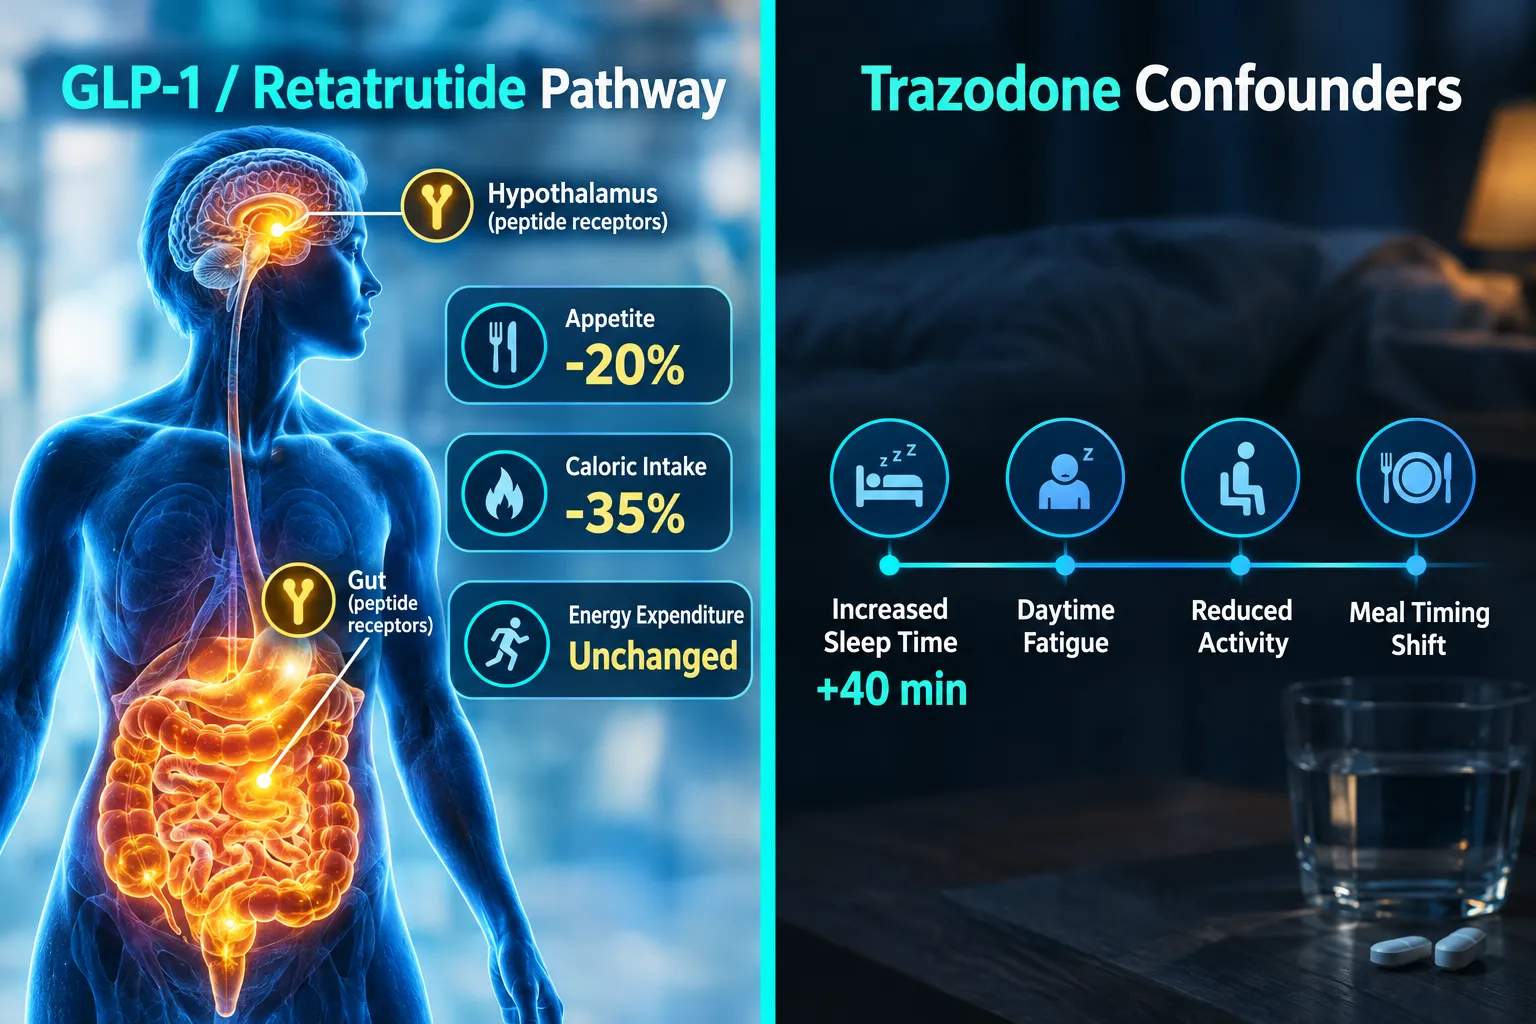
Understanding the intersection of trazodone, appetite, and peptide weight-loss models: controlling sedation, sleep, and food-intake confounders requires clarity on how peptide agents actually produce weight loss.
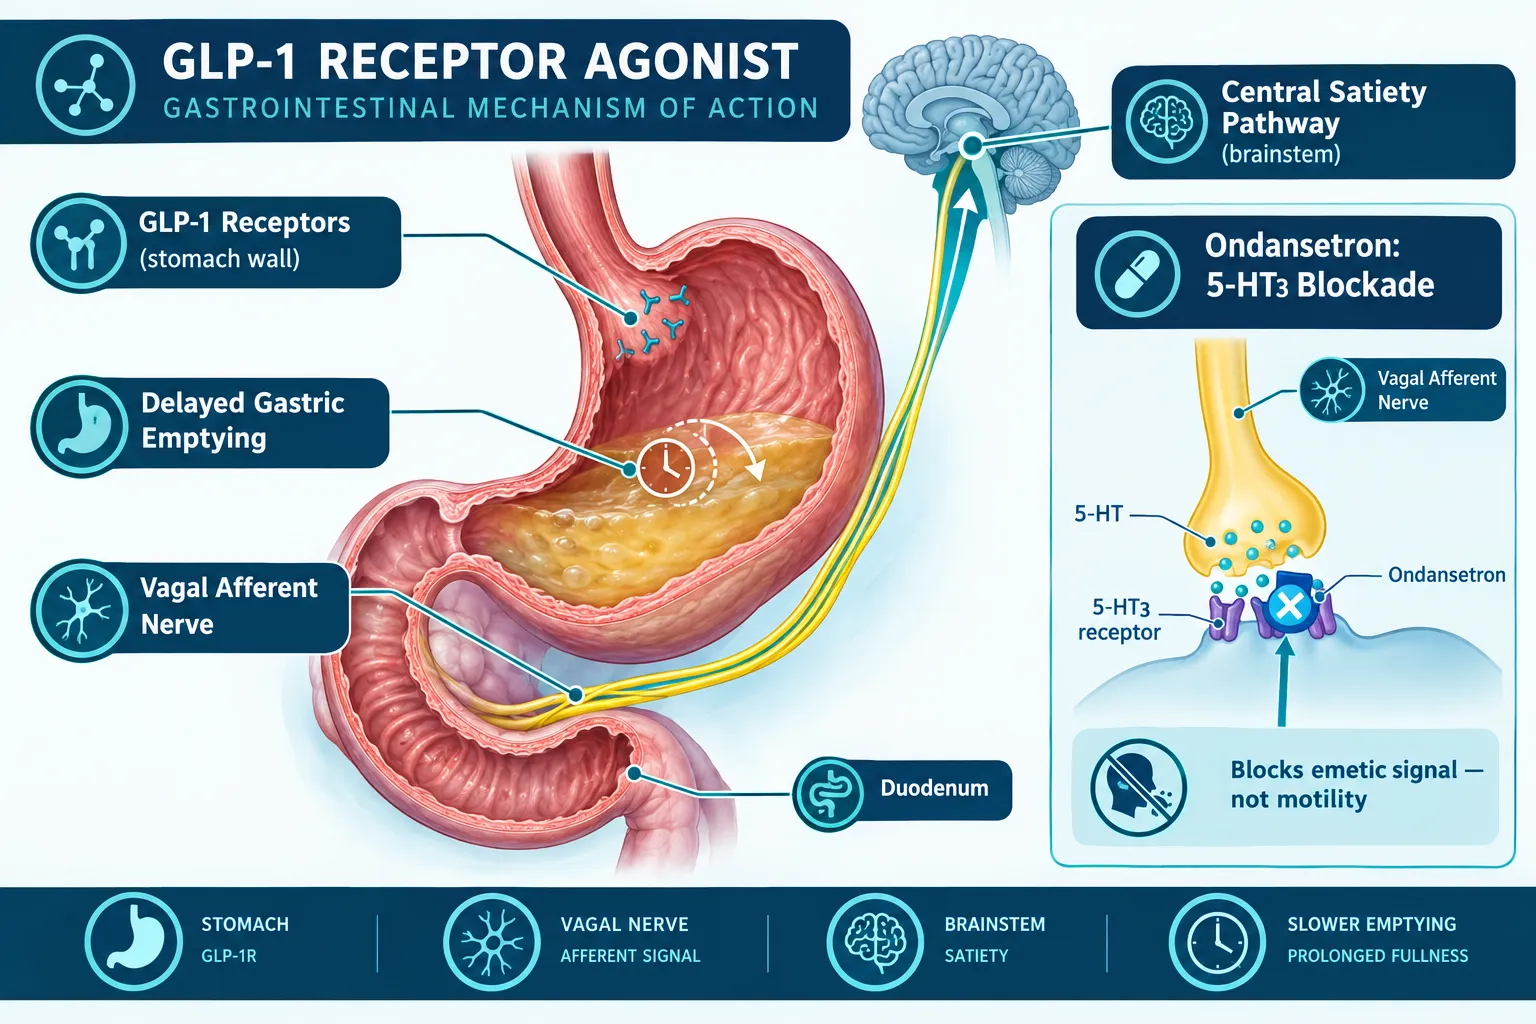
GLP-1 receptor agonists and next-generation multi-agonist peptides such as retatrutide reduce subjective appetite by approximately 0-20% and lower ad libitum energy intake by up to 35% in both obese and non-obese subjects. Crucially, across multiple studies, GLP-1 receptor agonist monotherapy or combination therapy showed non-significant effects on energy expenditure in a substantial proportion of trial datasets. Weight loss is therefore driven almost entirely by decreased caloric intake, not by metabolic rate changes.
This has a direct implication: any co-administered agent that alters eating behavior, meal timing, or sleep-related food consumption will distort the apparent efficacy of the peptide.
Key peptide-relevant confounders introduced by trazodone:
| Confounder | Mechanism | Direction of Bias |
|---|---|---|
| Extended sleep duration | Reduces waking hours available for eating | May falsely amplify peptide weight loss |
| Daytime sedation | Lowers physical activity and NEAT | May reduce energy expenditure independently |
| Meal timing shift | Sedation can delay or compress eating windows | Interacts with peptide gastric-emptying effects |
| Grogginess / dizziness | Reduces adherence to structured meal protocols | Introduces noise in intake measurements |
Researchers exploring what is the strongest peptide for weight loss need to account for these behavioral confounders before drawing mechanistic conclusions from body-weight endpoints.
GLP-1 agonists do improve obstructive sleep apnea, but this benefit is driven largely by weight loss rather than direct effects on sleep physiology. A concurrent sedative like trazodone can alter arousal threshold and sleep continuity in ways that mimic or mask those improvements, making it essential to model the two pharmacologic effects separately. Studies examining GLP-3 peptide variants or agents like cagrilintide peptide face the same confounding challenge when participants use sedating psychotropics.
Designing Confounder Controls for Trazodone in Peptide Weight-Loss Studies
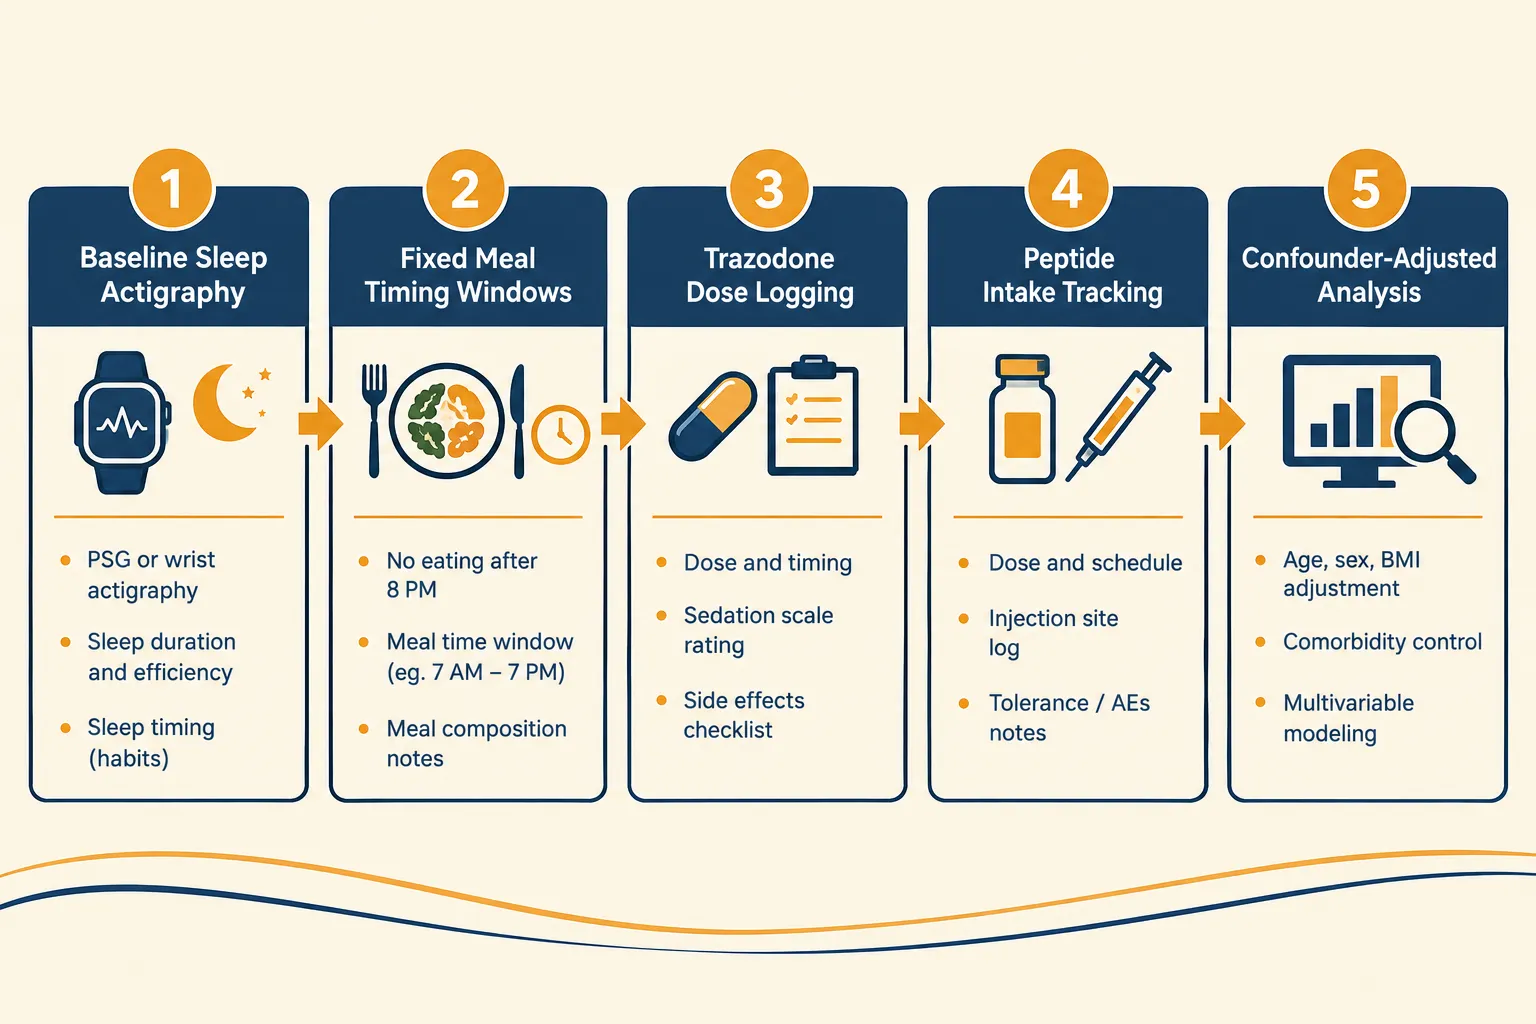
Addressing trazodone, appetite, and peptide weight-loss models: controlling sedation, sleep, and food-intake confounders at the design stage is far more effective than attempting statistical adjustment after data collection.
Sleep and activity controls:
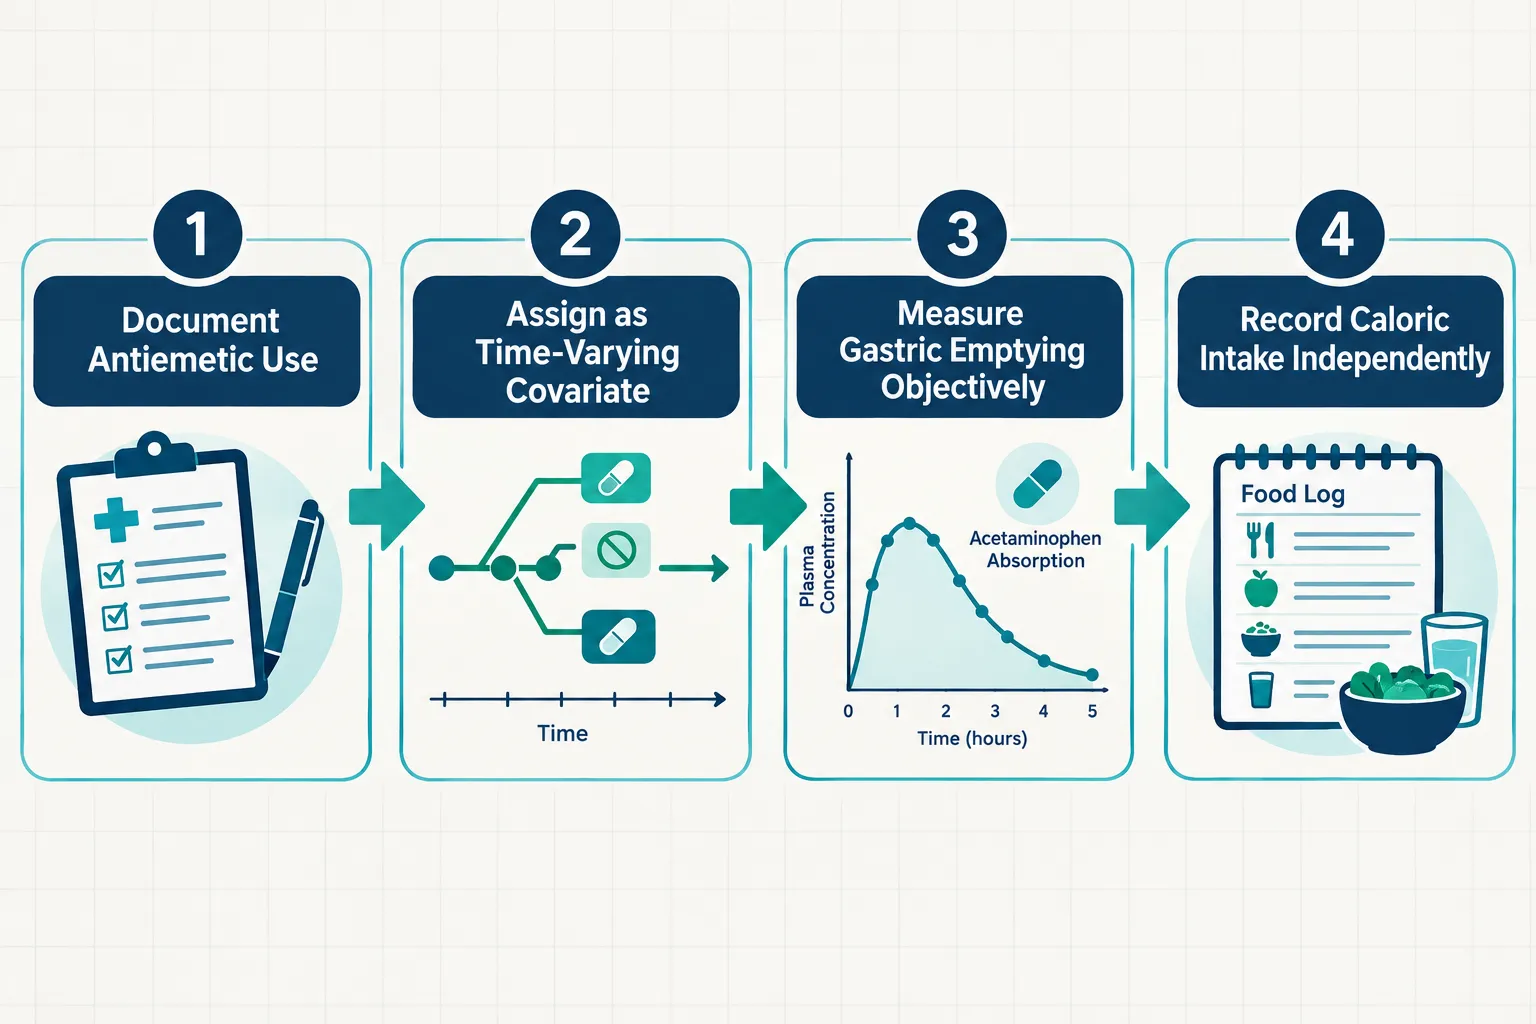
- Wrist actigraphy or polysomnography at baseline and follow-up intervals
- Standardized sedation rating scales administered at each study visit
- Daily step counts or accelerometry to capture trazodone-driven reductions in non-exercise activity thermogenesis (NEAT)
Meal-timing and food-intake controls:
- Fixed eating windows with no food intake after 8:00 p.m.
- A minimum three-hour gap between the last meal and sleep onset
- Validated 24-hour dietary recall or continuous food logging apps
Research published in 2025 found that severe stress, late dinner timing (after 9 p.m.), and less than three hours between dinner and bedtime significantly undermined peptide-based weight-loss treatment by disrupting sleep. Trazodone can shift all three of these variables simultaneously, compressing the pre-sleep interval by advancing sleep onset while leaving dinner timing unchanged.
Short objective sleep duration also predicts poor long-term weight-loss maintenance independently of intervention type, age, and sex. Worse perceived sleep quality during caloric restriction is associated with less total weight loss. This means trazodone's sleep-extending effect could artificially improve weight-loss outcomes in short trials while masking inadequate peptide response.
Recommended stratification variables:
- Trazodone dose (none / low 25-75 mg / therapeutic 150-300 mg)
- Baseline insomnia severity index score
- Comorbid depression status (since weight change may reflect mood improvement)
- BMI and type 2 diabetes status, both of which confound GLP-1 treatment selection and baseline disease severity
For researchers sourcing compounds for mechanistic studies, lab tested peptides with verified purity are a prerequisite for isolating pharmacologic effects from analytical noise. Similarly, understanding peptide half life is critical when scheduling blood draws and behavioral assessments around trazodone's own pharmacokinetic curve.
Emerging multi-receptor peptide agents, including those reviewed under buy reta peptide research tags, present additional complexity because their CNS effects, including possible alterations in sleep architecture and arousal, have not been fully characterized. A 2025 editorial in a leading sleep journal raised concerns that GLP-1 class agents may affect sleep continuity and circadian regulation in patients predisposed to hyperarousal, and called for systematic assessment of insomnia alongside peptide therapy. When trazodone is also present, combined CNS effects could mask or exaggerate true drug-related changes in both sleep and weight.
Conclusion
Trazodone's weight-neutral pharmacology does not make it a benign bystander in peptide weight-loss research. Its sedating effects extend sleep, suppress daytime activity, shift meal timing, and introduce behavioral confounders that can inflate, deflate, or simply obscure the true metabolic signal of GLP-1 agonists, retatrutide, and related compounds.
Actionable next steps for researchers and clinicians:
- Screen all participants for current trazodone use and dose at enrollment, not just at baseline questionnaire.
- Stratify or exclude trazodone users in primary analyses; include them in sensitivity analyses with dose as a covariate.
- Deploy objective sleep measurement (actigraphy minimum, polysomnography preferred) at baseline and at each major timepoint.
- Enforce meal-timing protocols with a hard cutoff at least three hours before trazodone-adjusted sleep onset.
- Separate sleep-quality improvements from peptide-driven weight loss using validated insomnia and sleep-apnea measures before attributing outcome differences to appetite suppression.
Rigorous control of these confounders is not methodological perfectionism, it is the minimum standard for generating trustworthy data on peptide-based metabolic therapies in a real-world population where sedative co-prescribing is common.