Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: metoprolol

Metoprolol in Peptide Experiments: Controlling Heart Rate, Blood Pressure, and Adrenergic Confounding

Metoprolol in Peptide Experiments: Controlling Heart Rate, Blood Pressure, and Adrenergic Confounding

October 6, 2026/0 Comments/in Uncategorized/by

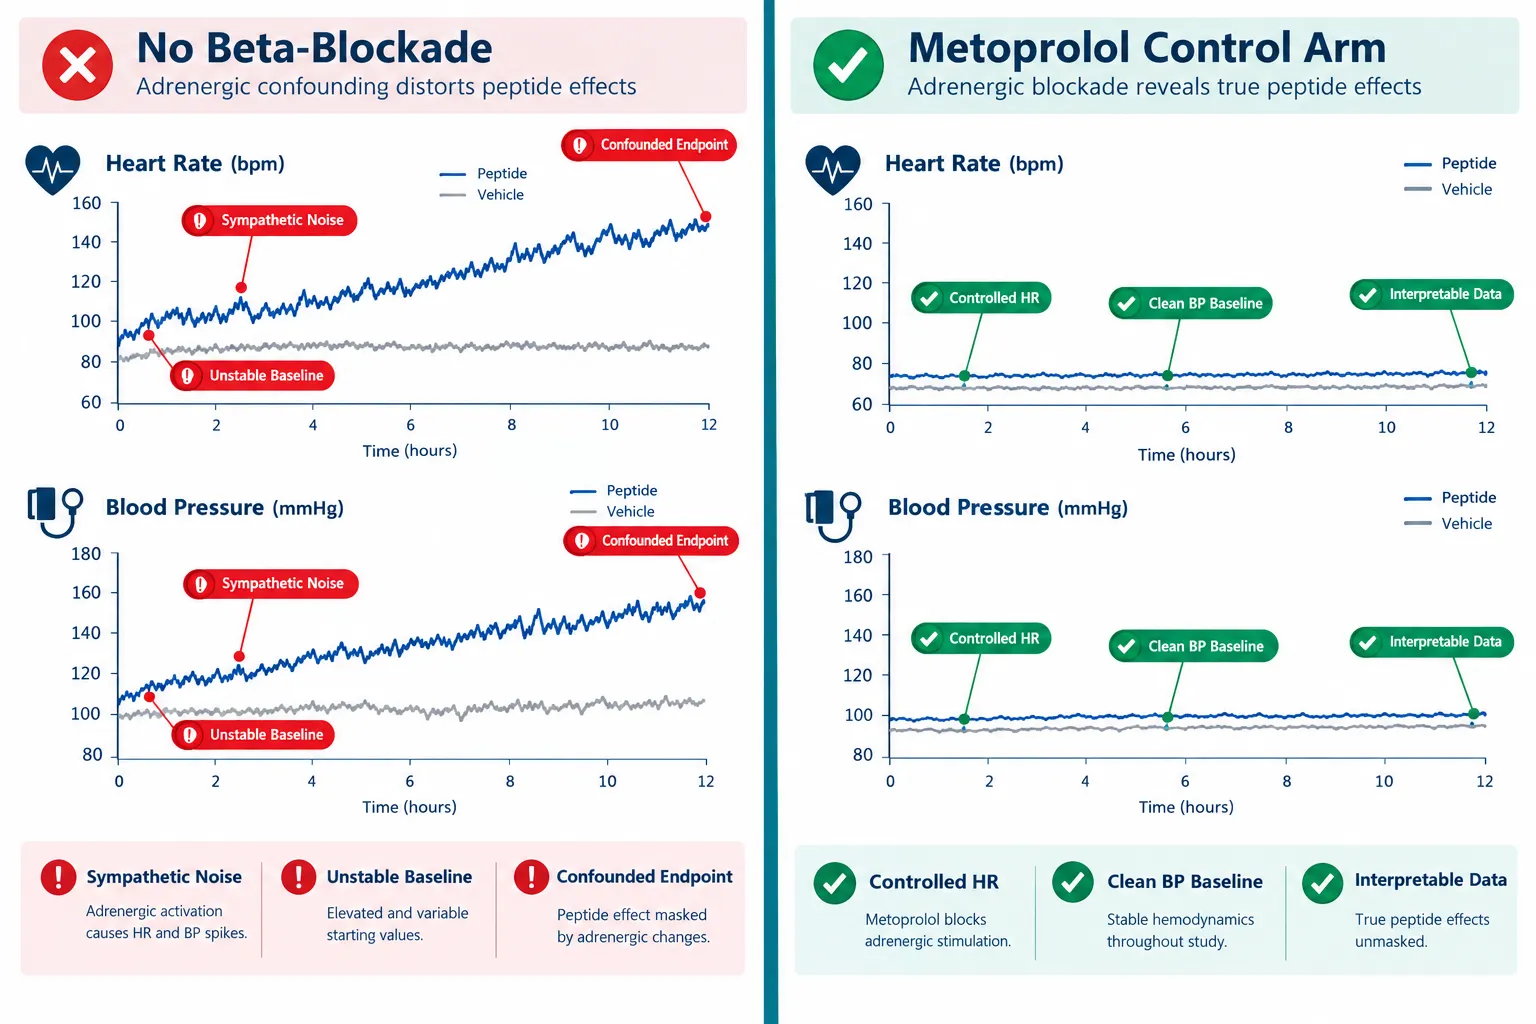
Cardiovascular endpoints fail silently when sympathetic noise is not controlled. Across retatrutide trials, growth-hormone-secretagogue models, and metabolic peptide studies, unmanaged adrenergic tone can shift heart rate by five to ten beats per minute and systolic blood pressure by several millimeters of mercury, differences large enough to obscure or mimic a genuine peptide effect. Understanding the role of metoprolol in peptide experiments for controlling heart rate, blood pressure, and adrenergic confounding is therefore not a minor methodological footnote; it is a foundational design decision.

Key Takeaways

  • Metoprolol is a beta-1 selective blocker that reduces heart rate, systolic blood pressure, and cardiac output without raising peripheral resistance, making it a precise tool for quieting adrenergic noise.
  • Placebo-corrected reductions of 3-6 mmHg systolic and 5-7 beats per minute are typical, but inter-subject variability, partly driven by CYP2D6 metabolizer status, can be substantial.
  • Stable beta-blockade takes approximately one week of oral dosing; acute sympathetic blockade begins within 15 minutes of a single dose, so experimental timing must match the intended control strategy.
  • Metoprolol controls adrenergic tone but does not normalize all advanced structural or functional endpoints, meaning it cannot substitute for a peptide's mechanism of action.
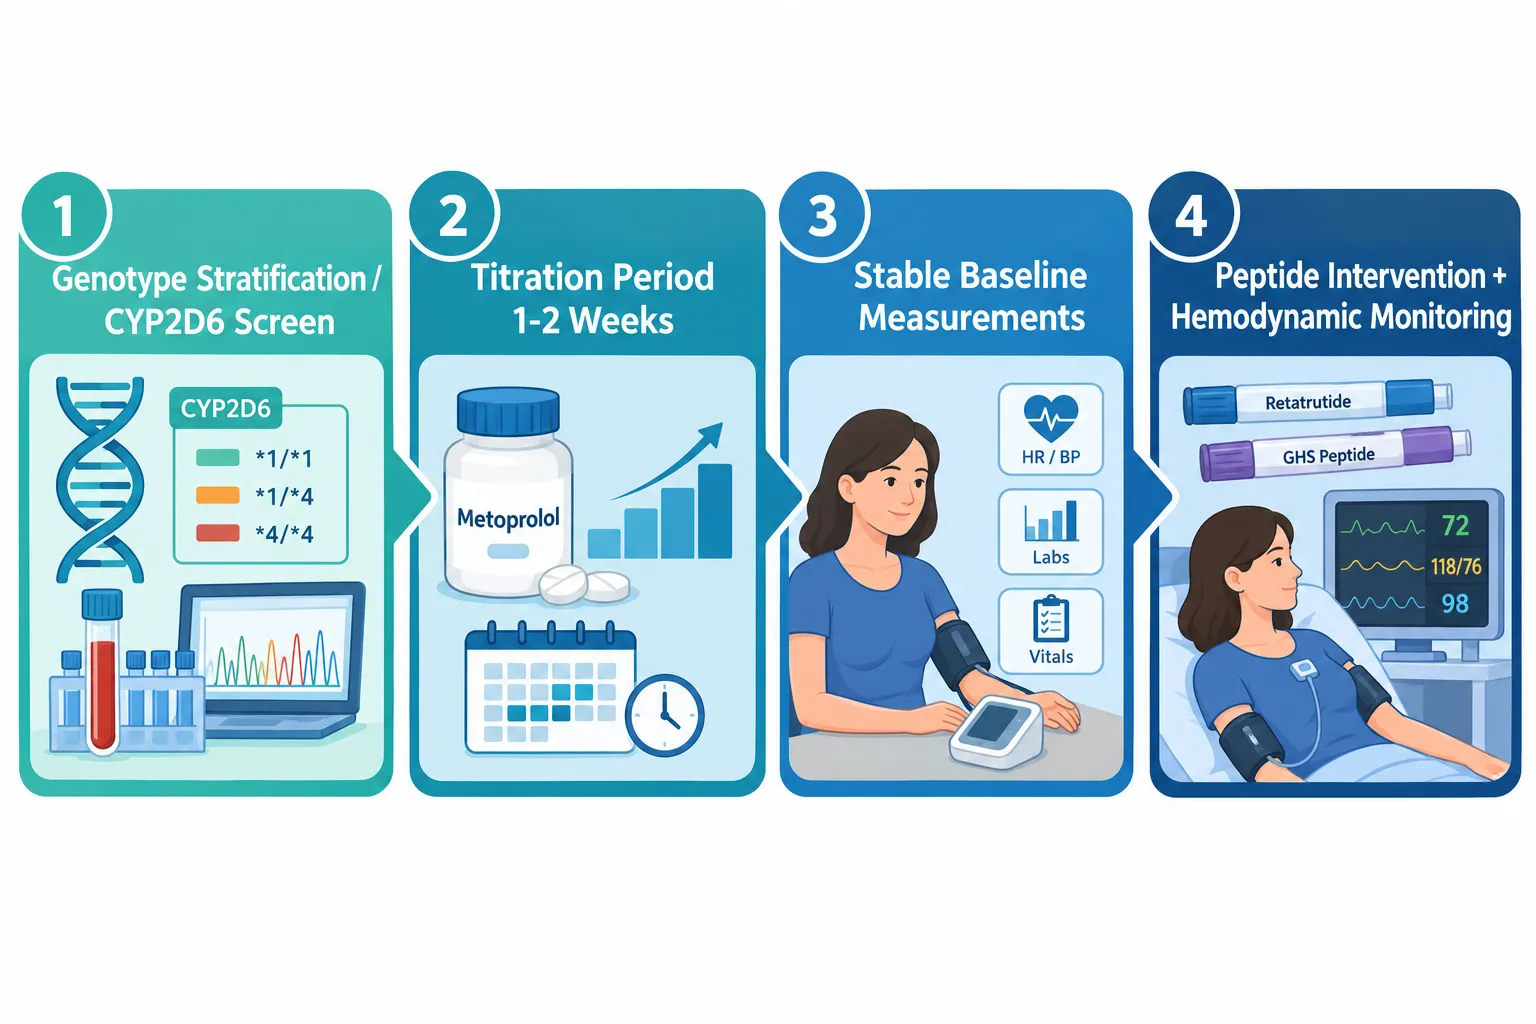
  • Proper use requires genotype stratification, defined titration periods, and both resting and exercise-state baseline measurements before any peptide intervention begins.

Why Adrenergic Tone Confounds Peptide Cardiovascular Readouts
Why Adrenergic Tone Confounds Peptide Cardiovascular Readouts

Many peptides under active investigation, including metabolic agents like retatrutide and GLP-3 class compounds, exert direct or indirect effects on the cardiovascular system. Growth-hormone secretagogues, vasoactive intestinal peptides such as VIP-5, and mitochondria-targeted peptides like SS-31 all operate in physiological environments where sympathetic tone fluctuates with stress, fasting state, exercise, and even the act of venipuncture.

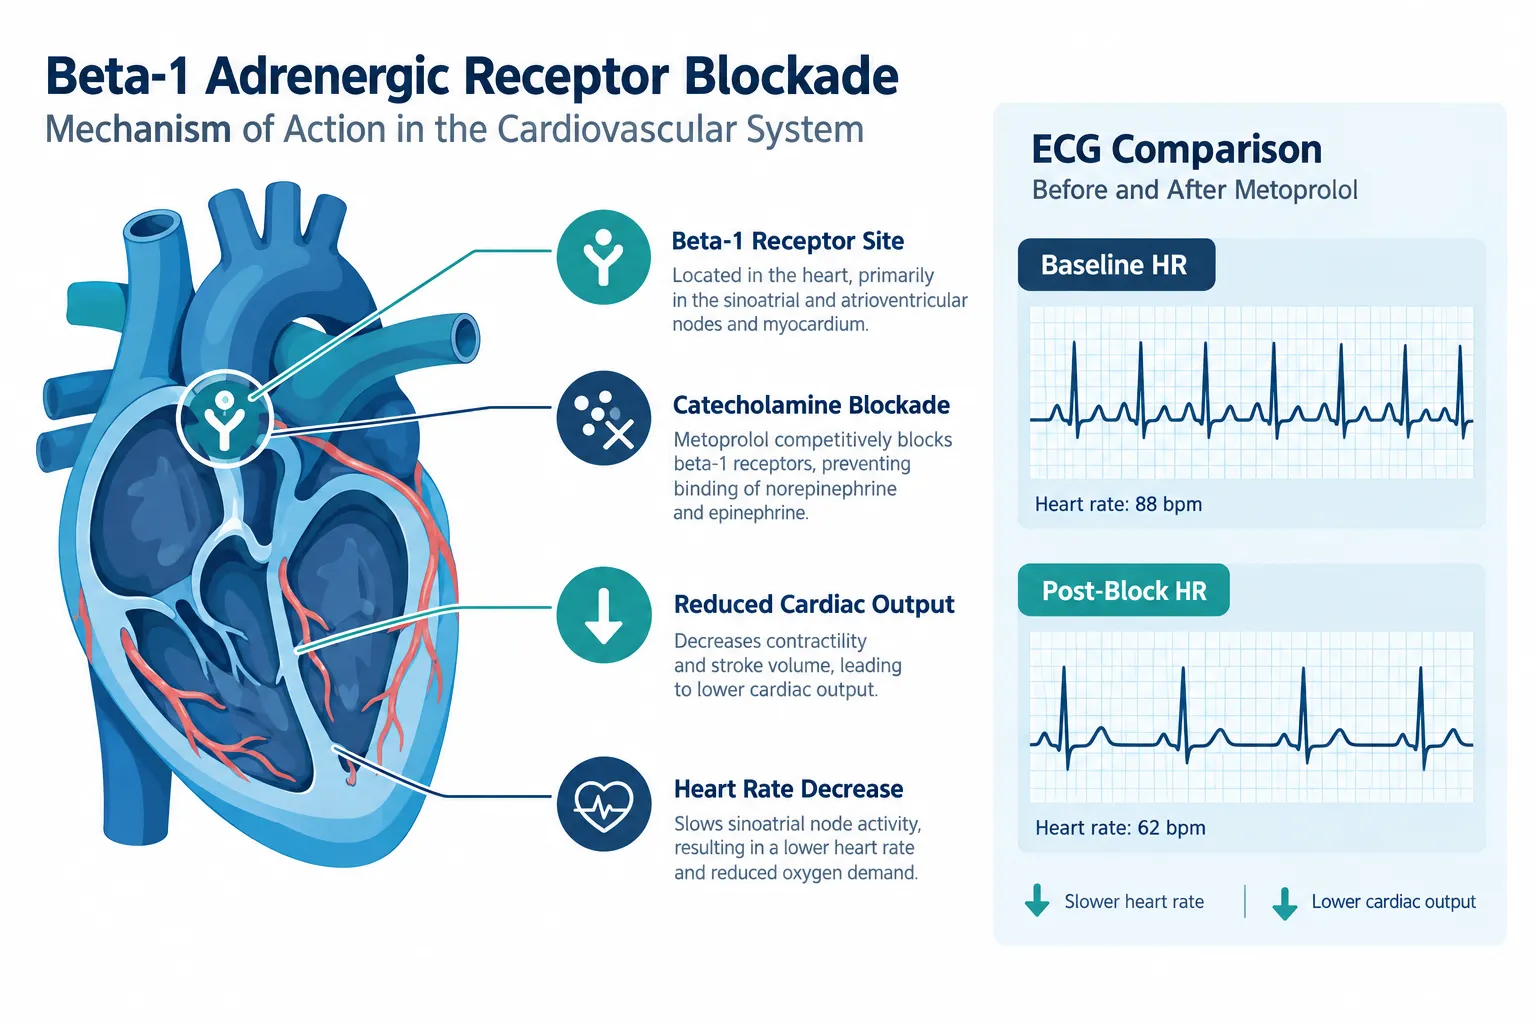
Catecholamines, adrenaline and noradrenaline, bind beta-1 receptors on the myocardium and raise heart rate, contractility, and blood pressure. If a peptide also raises or lowers these parameters through a separate pathway, the two signals overlap. Without a pharmacological anchor, investigators cannot cleanly attribute observed hemodynamic changes to the peptide alone.

This is the core problem metoprolol solves. By selectively blocking beta-1 adrenergic receptors, it attenuates catecholamine-driven cardiovascular fluctuations, providing a more stable hemodynamic backdrop against which peptide-specific effects can be measured.

"Metoprolol does not eliminate cardiovascular physiology, it standardizes the sympathetic component of it, allowing other signals to emerge more clearly."

Key adrenergic phenomena that metoprolol suppresses include:

  • Resting tachycardia driven by anxiety or metabolic stimulation
  • Exercise-induced heart rate overshoot
  • Isoproterenol-provoked tachycardia used in challenge protocols
  • Reflex orthostatic tachycardia during postural changes

Each of these can appear as a false-positive or false-negative peptide effect if left uncontrolled.


Practical Application of Metoprolol in Peptide Experiments: Controlling Heart Rate, Blood Pressure, and Adrenergic Confounding
Practical Application of Metoprolol in Peptide Experiments: Controlling Heart Rate, Blood Pressure, and Adrenergic Confoundin

Dose Range and Titration Timing

Oral metoprolol doses in hypertension and heart-rate control protocols typically range from 100 to 450 mg per day, titrated at weekly intervals. A single 50-80 mg dose begins reducing exercise systolic blood pressure within approximately 15 minutes, but stable, chronic antihypertensive effect requires roughly one week of consistent dosing.

This distinction matters enormously for experimental design:

Control Strategy Onset Use Case
Acute single dose ~15 minutes Rapid sympathetic stabilization before a one-time challenge
Chronic titration (1 week+) ~7 days Stable baseline for multi-day peptide dosing protocols

For most mechanistic peptide trials, including those assessing cardiometabolic polypeptide models, chronic titration is preferred because it removes day-to-day adrenergic variability rather than just blunting a single measurement window.

Accounting for CYP2D6 Metabolizer Status

A critical and often overlooked source of confounding within the metoprolol control arm itself is pharmacogenomic variability. Poor CYP2D6 metabolizers accumulate significantly higher serum metoprolol concentrations, producing greater and more consistent reductions in heart rate, diastolic blood pressure, and mean arterial pressure compared to extensive metabolizers at the same dose.

If subjects are not stratified by CYP2D6 status, the beta-blockade "control" becomes a new source of variance. Practical steps include:

  1. Pre-screen subjects for CYP2D6 poor-metabolizer status
  2. Stratify randomization accordingly
  3. Monitor resting and exercise heart rate at baseline, after titration, and at each peptide dosing interval

Baseline Measurement Protocol

Baseline measurements must capture both resting and dynamic (exercise) cardiovascular state. Metoprolol reduces heart rate and systolic blood pressure at rest and during exercise, these are separate physiological states that peptides may affect differently. Recording only resting values misses exercise-induced adrenergic surges that some metabolic peptides, including growth-hormone secretagogues, actively modulate.


Interpretation Cautions: What Metoprolol Cannot Control
Interpretation Cautions: What Metoprolol Cannot Control

Metoprolol's selectivity is both its strength and its limitation. As a beta-1 selective agent, it does not block alpha-1 receptors or beta-2 receptors. Contrast this with carvedilol, a non-selective blocker with additional alpha-1 antagonism, which suppresses adrenergic activity through a broader mechanism. The choice between these agents changes the nature of residual adrenergic confounding, a distinction highlighted in comparative cardiovascular outcome protocols.

For researchers working with peptides in endocrine pharmacology contexts or GH-analogue peptides, additional considerations include:

  • Structural endpoints: Beta-blockade does not normalize advanced structural or functional cardiac endpoints. Recent data from myosin inhibitor trials confirm that metoprolol, despite controlling heart rate and blood pressure, did not replicate the specific functional improvements seen with next-generation myosin-targeted agents. Peptide trials must not assume that hemodynamic control equals functional equivalence.
  • Peripheral vascular effects: Metoprolol does not increase peripheral resistance, but it also does not reduce it. Peptides with vasodilatory mechanisms, such as VIP-class agents, will still show vascular effects that metoprolol leaves unmasked.
  • Metabolic interactions: Some metabolic peptides affect insulin sensitivity and glucose metabolism in ways that secondarily alter sympathetic tone. Metoprolol blunts the cardiovascular expression of this interaction but does not eliminate the underlying metabolic signal.

Conclusion

Metoprolol in peptide experiments for controlling heart rate, blood pressure, and adrenergic confounding represents one of the most practical pharmacological tools available to cardiovascular researchers in 2026. Its beta-1 selectivity, well-characterized dose-response profile, and rapid onset make it well suited for both acute challenge designs and chronic multi-week protocols.

Actionable next steps for research teams:

  • Determine whether acute or chronic beta-blockade better matches the experimental timeline before dosing begins
  • Screen and stratify subjects by CYP2D6 metabolizer status to prevent pharmacogenomic variance from contaminating the control arm
  • Collect resting and exercise-state hemodynamic baselines after titration, not before
  • Document which adrenergic phenomena remain unblocked (alpha-1, beta-2 pathways) and account for them in statistical models
  • Avoid interpreting stable hemodynamic readings as evidence that all cardiovascular endpoints are normalized, structural and functional parameters require independent assessment

Selecting high-purity, well-characterized peptides from a reliable peptide supplier is equally important; compound variability introduces its own confounding that no pharmacological control can fully correct.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/metoprolol-in-peptide-experiments-controlling-heart-rate-blood-pressure-and-adre.webp 672 1008 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-06 13:10:002026-10-06 13:10:00Metoprolol in Peptide Experiments: Controlling Heart Rate, Blood Pressure, and Adrenergic Confounding
Metoprolol, Beta-Blockers, and Incretin Peptide Research: What Labs Track When Combining GLP-3 Retatrutide With Cardioactive Drugs

Metoprolol, Beta-Blockers, and Incretin Peptide Research: What Labs Track When Combining GLP-3 Retatrutide With Cardioactive Drugs

September 20, 2026/0 Comments/in Uncategorized/by

Roughly 40% of adults with obesity also carry a diagnosis of cardiovascular disease, making the overlap between metabolic therapies and heart-active medications not a niche concern but a near-universal research challenge. As retatrutide advances through Phase 3 TRIUMPH trials with striking cardiometabolic data, the question of how this triple-incretin agonist interacts with beta-blockers like metoprolol has become one of the most pressing topics in preclinical and translational lab design for 2026.

This guide addresses the core of that challenge: what measurements, markers, and safety checkpoints researchers track when studying metoprolol, beta-blockers, and incretin peptide research, specifically what labs track when combining GLP-3 retatrutide with cardioactive drugs in structured experimental frameworks.

Key Takeaways

  • Retatrutide activates GLP-1, GIP, and glucagon receptors simultaneously, creating a multi-axis effect on heart rate, blood pressure, and glucose that overlaps directly with beta-blocker pharmacology.
  • Metoprolol and other beta-blockers can mask hypoglycemia symptoms, a risk that becomes more complex when combined with incretin agents that lower glucose through multiple pathways.
  • Researchers tracking this combination should monitor cardiac rhythm, hemodynamics, glucose metabolism, and renal function as a minimum panel.
  • Emerging arrhythmia signals from triple-incretin agonist data make QTc interval and Holter monitoring critical additions to any lab protocol.
  • Purity and consistency of research-grade peptides are foundational to reproducible results in this interaction space.

Understanding the Pharmacological Overlap

Understanding the Pharmacological Overlap

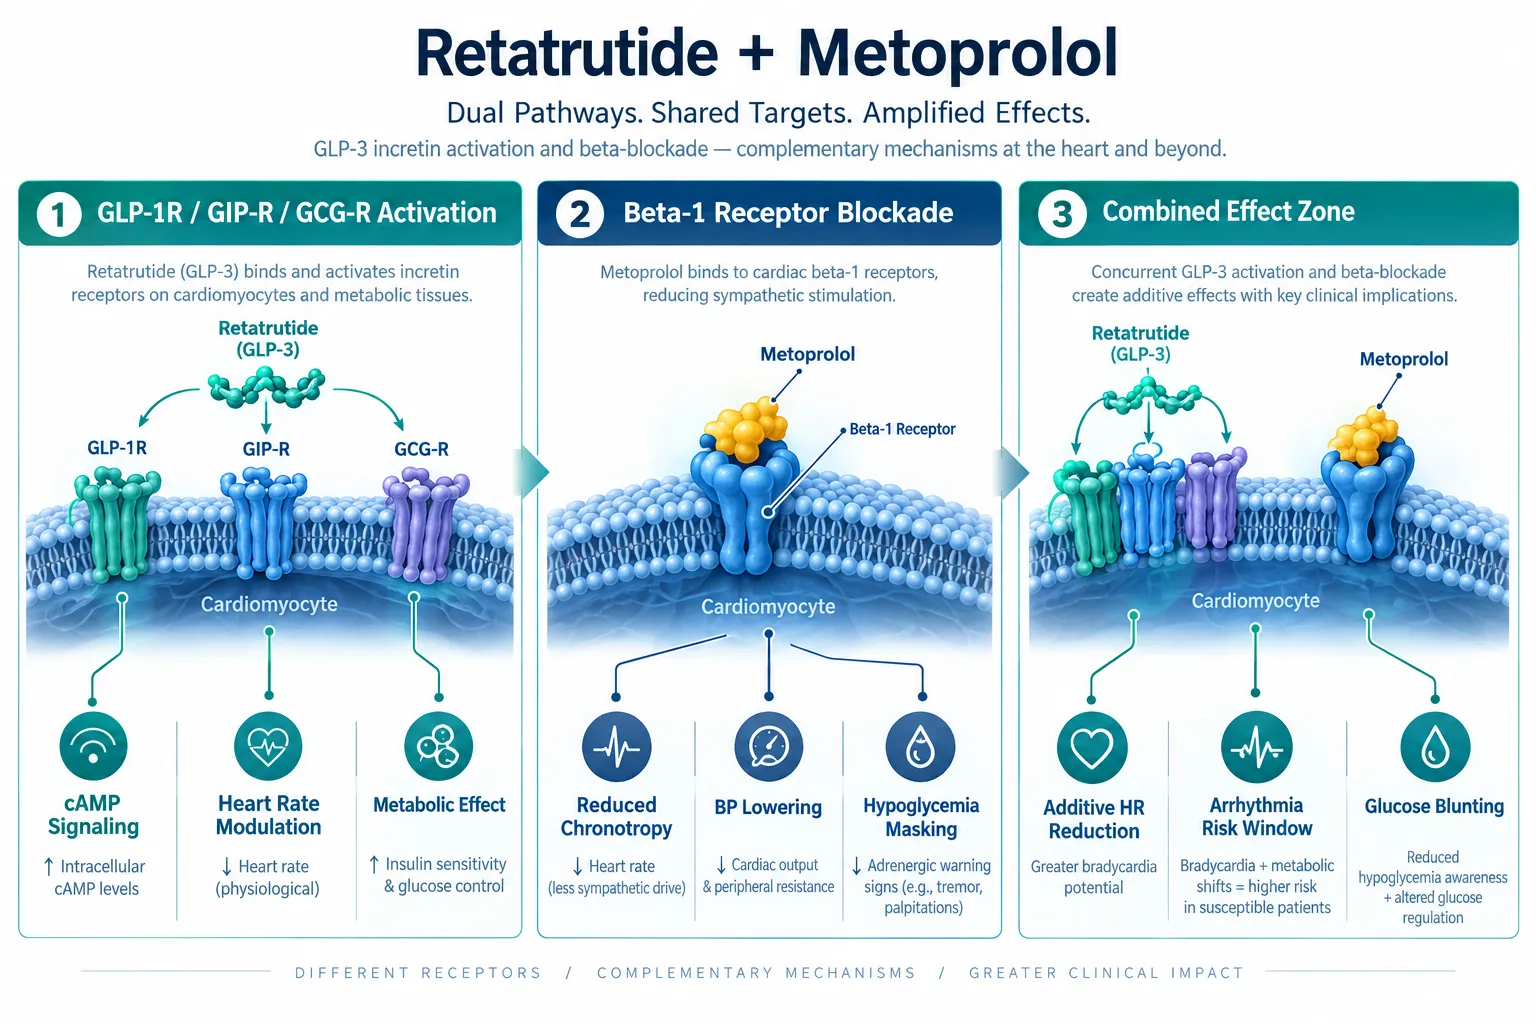
Retatrutide is a triple-receptor agonist targeting GLP-1R, GIPR, and glucagon receptors. Each of these pathways carries cardiovascular relevance. GLP-1 receptor activation raises cyclic AMP in cardiac tissue, which increases heart rate and cardiac output. Glucagon receptor activation has similar chronotropic effects. In isolation, these actions are manageable. When layered onto a beta-blocker framework, the dynamics shift.

Metoprolol is a selective beta-1 adrenergic antagonist. Its primary cardiac effects include reduced heart rate, lower blood pressure, and decreased myocardial oxygen demand. When a researcher or clinician introduces a GLP-class incretin peptide alongside metoprolol, the two agents are working on overlapping but mechanistically distinct pathways, one suppressing adrenergic drive, the other stimulating cAMP-mediated chronotropy.

The result is not simply additive or subtractive. The net heart rate effect depends on receptor density, dose, and individual variability. In vitro models studying GLP-3 peptide interactions need to account for this bidirectional tension explicitly in their experimental design.

A second layer of complexity involves glucose regulation. Beta-blockers are known to blunt the sympathoadrenal response to hypoglycemia, the very response that triggers awareness of low blood sugar. Incretin peptides lower glucose through multiple mechanisms. When combined, the hypoglycemia masking effect of metoprolol can obscure a glucose drop that the incretin agent has contributed to, creating a safety blind spot that labs must monitor actively.

Core Lab Panels for Metoprolol, Beta-Blockers, and Incretin Peptide Research

Core Lab Panels for Metoprolol, Beta-Blockers, and Incretin Peptide Research

Designing a rigorous monitoring protocol for this combination requires tracking across four domains: cardiac rhythm, hemodynamics, metabolic markers, and safety biomarkers.

Cardiac Rhythm and Electrophysiology

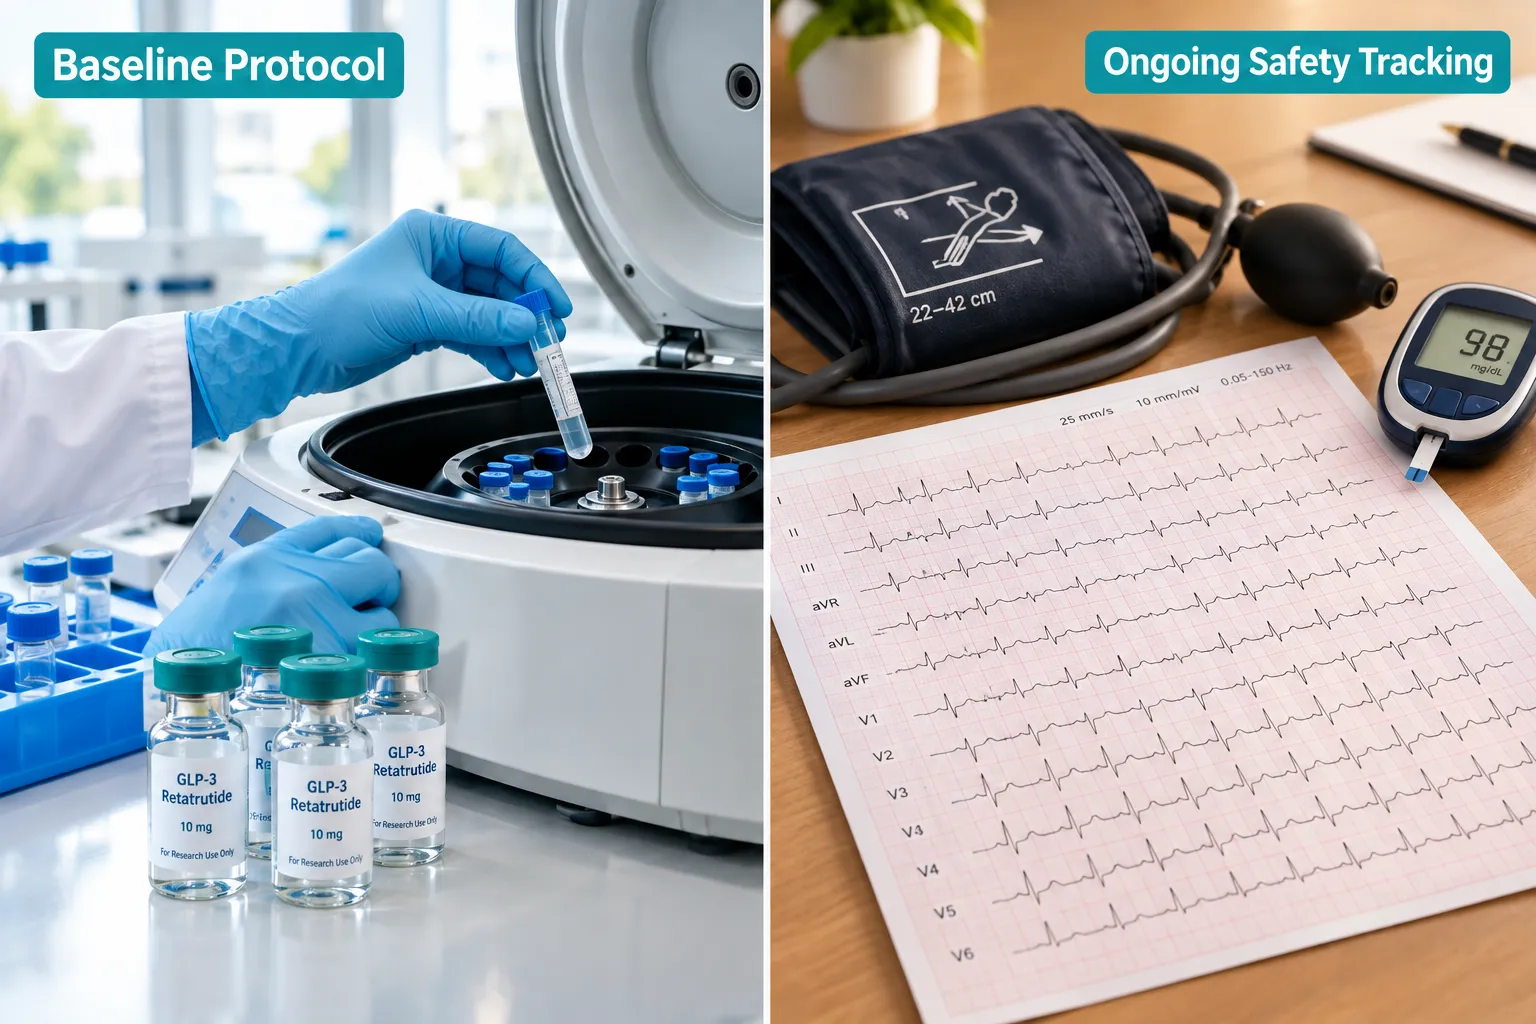
The most immediate concern when combining GLP-3 retatrutide with cardioactive drugs is arrhythmia risk. Emerging data from triple-incretin agonist research has flagged QTc prolongation as a signal requiring active surveillance. Labs should include:

  • 12-lead ECG at baseline and at defined intervals
  • QTc interval measurement using Fridericia or Bazett correction
  • Holter monitoring for continuous rhythm capture over 24-48 hours
  • Resting heart rate tracked across all time points

When peptide dosing protocols are adjusted, rhythm data should be recaptured to identify dose-dependent changes.

Hemodynamic Monitoring

Blood pressure response is a critical variable. Retatrutide has shown meaningful reductions in systolic blood pressure in TRIUMPH trial data. Metoprolol compounds this effect. Labs should record:

Measurement Frequency
Systolic blood pressure Every experimental session
Diastolic blood pressure Every experimental session
Mean arterial pressure Calculated at each time point
Orthostatic BP change Standing vs. supine, at peak drug effect

Orthostatic hypotension is a real concern in this combination and should not be treated as a secondary endpoint.

Metabolic and Glucose Panel

Given the hypoglycemia masking risk described above, glucose monitoring must be granular:

  • Fasting glucose at baseline and post-dose
  • Insulin and C-peptide levels
  • HbA1c for longer study windows
  • Glucagon levels, given retatrutide's direct glucagon receptor activity

Researchers sourcing GLP-3 retatrutide for lab use should confirm purity documentation, as impurities in the peptide can introduce confounding metabolic signals.

Safety Biomarkers

A complete panel also includes:

  • Serum electrolytes (potassium and magnesium, given arrhythmia risk)
  • Catecholamine levels (epinephrine, norepinephrine) to detect suppressed stress response
  • Renal function markers (creatinine, eGFR) given the renal clearance pathways of both drug classes
  • Liver enzymes for hepatic safety tracking

Designing the Monitoring Protocol: What Labs Track When Combining GLP-3 Retatrutide With Cardioactive Drugs

Designing the Monitoring Protocol: What Labs Track When Combining GLP-3 Retatrutide With Cardioactive Drugs

A well-structured protocol for studying metoprolol, beta-blockers, and incretin peptide research does not treat these measurements as isolated checkboxes. It builds them into a timeline that reflects the pharmacokinetics of both agents.

Retatrutide has a long half-life, approximately 6 days in clinical data, which means steady-state effects accumulate across a study window. Metoprolol, by contrast, has a much shorter half-life of 3-7 hours for standard formulations. This mismatch means:

  1. Baseline measurements must be captured before either agent is introduced.
  2. Acute monitoring should align with metoprolol's peak effect window (1-2 hours post-dose).
  3. Trough monitoring should capture the period when metoprolol is at its lowest plasma level but retatrutide remains pharmacologically active.
  4. Washout tracking should extend beyond retatrutide's half-life to confirm return to baseline cardiac and metabolic parameters.

Researchers working with GLP-3 nasal spray formulations or alternative delivery formats should adjust absorption timing windows accordingly, as pharmacokinetic profiles differ from injectable preparations.

For labs using complementary cardioprotective peptides alongside this combination, resources on SS-31 peptide research considerations may provide useful parallel monitoring frameworks, given SS-31's mitochondrial cardioprotective mechanism.

Sensory and Neurological Safety Signals

Phase 3 retatrutide data has introduced a newer sensory safety signal, peripheral sensory changes in a subset of subjects. While the mechanism is not fully characterized, labs studying this combination should include basic neurological assessments and track any reported sensory changes systematically. This is particularly relevant when beta-blockers are co-administered, as they can independently affect peripheral circulation.

Conclusion

The intersection of GLP-3 retatrutide and beta-blocker pharmacology is not a simple additive equation. For researchers designing protocols around metoprolol, beta-blockers, and incretin peptide research, what labs track when combining GLP-3 retatrutide with cardioactive drugs must span cardiac rhythm, hemodynamics, glucose metabolism, electrolytes, and emerging sensory signals, all mapped against the distinct pharmacokinetic timelines of each agent.

Actionable next steps for research teams in 2026:

  • Establish a pre-study baseline panel covering all four monitoring domains before any agent is introduced.
  • Build time-matched monitoring windows that reflect both the short half-life of metoprolol and the extended half-life of retatrutide.
  • Treat hypoglycemia masking as a primary, not secondary, safety concern in any protocol combining beta-blockers with incretin peptides.
  • Confirm third-party purity testing on all research-grade peptides used; explore GLP-3 peptide options with documented quality assurance.
  • Document sensory safety signals as a standard endpoint given the emerging data from triple-incretin agonist trials.

Rigorous lab design in this space is not just a procedural formality, it is the foundation for generating data that can meaningfully inform the next generation of cardiometabolic research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/metoprolol-beta-blockers-and-incretin-peptide-research-what-labs-track-when-comb.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-20 13:06:342026-09-20 13:06:34Metoprolol, Beta-Blockers, and Incretin Peptide Research: What Labs Track When Combining GLP-3 Retatrutide With Cardioactive Drugs

Tag Archive for: metoprolol

Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol

Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol

July 17, 2026/0 Comments/by Pure Tested

Three drugs, amlodipine, prednisone, and metoprolol, have shaped cardiovascular and endocrine medicine for decades. Yet their well-documented off-target effects on glucose metabolism, adrenal function, and mitochondrial signaling now serve as a compelling argument for why polypeptide peptides in endocrine and metabolic pharmacology deserve serious research attention in 2026.

Bright editorial split-screen infographic landscape (): left half shows a clean white-background molecular diagram of a

Key Takeaways

  • Amlodipine, prednisone, and metoprolol each interact with endocrine pathways in ways that go beyond their primary targets, producing metabolic side effects that peptide-based agents may avoid.
  • Polypeptide peptides in endocrine and metabolic pharmacology offer receptor selectivity, shorter off-target profiles, and tissue-specific action that small molecules often cannot match.
  • GLP-1 receptor agonists and multi-agonist peptides represent the most clinically advanced examples of this shift, with GLP-3 retatrutide research extending the frontier.
  • Mitochondrial peptides such as MOTS-c address metabolic dysregulation at the cellular energy level, a target unreachable by classic small molecules.
  • Understanding the pharmacological gaps left by legacy drugs helps researchers identify where peptide-based tools offer the greatest research value.

How Classic Small Molecules Interact With Endocrine Pathways

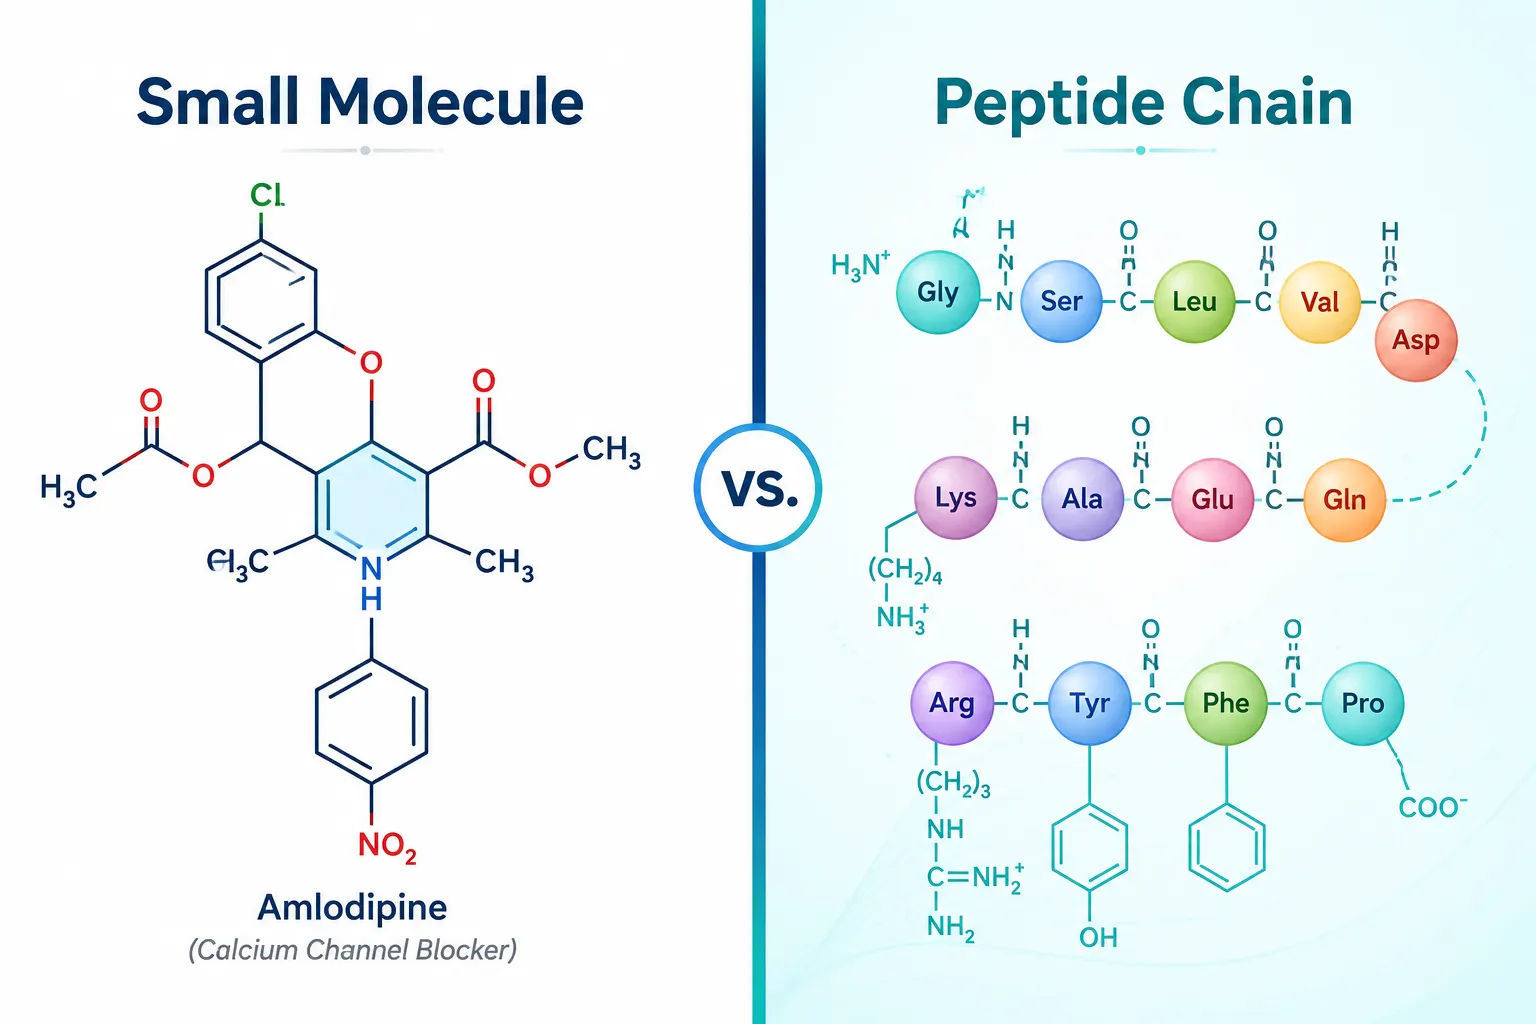
Amlodipine blocks L-type calcium channels in vascular smooth muscle, reducing blood pressure and myocardial oxygen demand. However, calcium signaling is also central to pancreatic beta-cell insulin secretion. Disrupting this pathway even modestly can impair glucose-stimulated insulin release, a finding that has been observed in long-term hypertension management research.

Prednisone, a synthetic glucocorticoid, binds glucocorticoid receptors with broad tissue distribution. Its anti-inflammatory power comes at a metabolic cost: stimulation of hepatic gluconeogenesis, suppression of peripheral insulin sensitivity, and disruption of the hypothalamic-pituitary-adrenal axis. These are not rare side effects, they are mechanistic consequences of how the drug binds.

Metoprolol, a beta-1 selective adrenergic blocker, reduces heart rate and cardiac output effectively. Its endocrine liability lies in masking hypoglycemic symptoms and blunting the catecholamine-driven recovery from low blood glucose, a clinically relevant concern in diabetic patients.

The pattern is consistent: each drug achieves its primary goal through a mechanism that inevitably touches endocrine or metabolic circuitry.

"The off-target metabolic effects of classic small molecules are not design flaws, they are the predictable result of targeting signaling pathways that evolution never isolated."


Polypeptide Peptides in Endocrine and Metabolic Pharmacology: The Receptor Targeting Advantage

Polypeptide Peptides in Endocrine and Metabolic Pharmacology: The Receptor Targeting Advantage

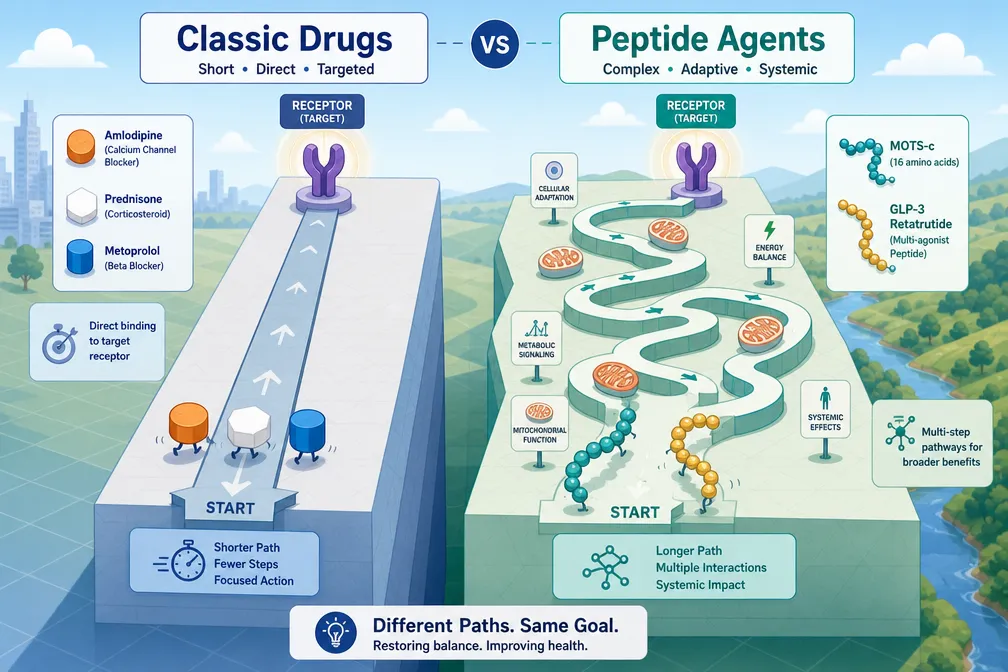
Where small molecules bind with high affinity but low tissue selectivity, polypeptide peptides in endocrine and metabolic pharmacology operate through receptor systems that are more anatomically restricted. This distinction is not merely theoretical.

Proglucagon-derived peptides, including GLP-1, GLP-2, glucagon, and oxyntomodulin, each act on distinct receptor populations across the gut, pancreas, brain, and liver. GLP-1 receptor agonists lower blood glucose by enhancing insulin secretion only when glucose is already elevated, a glucose-dependent mechanism that eliminates the hypoglycemia risk associated with metoprolol-class drugs.

The next generation goes further. Multi-agonist peptides combine amino acid sequences from GLP-1, glucagon, and GIP hormones into single molecules with enhanced potency and extended half-lives. Research into GLP-3 retatrutide represents this frontier, targeting multiple incretin receptors simultaneously to address obesity and type 2 diabetes with a precision that prednisone-driven metabolic disruption cannot approach.

The GIP receptor plays a particularly important role here. GIP works synergistically with GLP-1 to amplify insulin secretion and may also support bone metabolism and fat storage regulation, a multi-system effect achieved without the adrenal suppression that defines glucocorticoid pharmacology.

Key differences between small molecules and peptide agents:

Feature Small Molecules (e.g., Prednisone) Peptide Agents (e.g., GLP-1 agonists)
Receptor selectivity Broad Tissue-restricted
Metabolic off-target effects Common Reduced
Half-life engineering Limited Highly modifiable
Glucose-dependent action No Yes (GLP-1 class)

Adrenomedullin, a 52-amino acid peptide hormone, further illustrates the endocrine complexity peptides can address. It regulates cardiovascular tone and lymphatic function while also inhibiting insulin secretion in a dose-dependent manner, a finding that positions it as both a research target and a cautionary example of peptide pleiotropy.


Mitochondrial Peptides and the Metabolic Gap Left by Legacy Drugs

Mitochondrial Peptides and the Metabolic Gap Left by Legacy Drugs

Neither amlodipine, prednisone, nor metoprolol addresses cellular energy metabolism at the mitochondrial level. This is a significant gap. Chronic glucocorticoid use, in particular, impairs mitochondrial biogenesis and increases reactive oxygen species production, effects that accelerate metabolic aging.

This is precisely where mitochondrial-derived peptides enter the research conversation. MOTS-c, encoded within mitochondrial DNA, regulates glucose uptake, fatty acid oxidation, and insulin sensitivity through AMPK activation. Its mechanism operates entirely outside the receptor systems targeted by classic cardiovascular drugs, making it a complementary rather than competing research tool.

SS-31 peptide research addresses a related problem: mitochondrial membrane integrity under oxidative stress. Where prednisone-induced metabolic disruption increases oxidative burden, SS-31 targets cardiolipin on the inner mitochondrial membrane to preserve electron transport chain function.

For researchers exploring body composition and visceral adiposity, conditions worsened by long-term glucocorticoid exposure, tesa offers a growth hormone-releasing hormone analog that specifically reduces visceral fat without the broad hormonal disruption of steroid-class drugs.

Non-incretin peptide systems are also gaining traction. Apelin, spexin, and meteorin-like protein (METRNL) each interact with energy balance pathways that small molecules have historically ignored, opening new drug discovery targets for metabolic disease research.

For those examining AOD-9604 metabolic research, the lipolytic fragment of growth hormone provides another example of how peptide engineering can isolate a single metabolic function, fat mobilization, without replicating the full hormonal cascade of its parent molecule.


Conclusion

The lessons from amlodipine, prednisone, and metoprolol are not arguments against small-molecule pharmacology. They are a precise map of where that pharmacology ends and where polypeptide peptides in endocrine and metabolic pharmacology begin. Each classic drug reveals a metabolic vulnerability, impaired insulin secretion, adrenal suppression, blunted glycemic recovery, that modern peptide research is systematically designed to address.

Actionable next steps for researchers and clinicians:

  • Review the receptor selectivity profiles of any metabolic intervention against the endocrine off-target effects documented in glucocorticoid and beta-blocker literature.
  • Explore mitochondrial peptide tools such as MOTS-c and SS-31 for research models involving oxidative stress or insulin resistance secondary to classic drug exposure.
  • Track multi-agonist peptide development, particularly GLP-1/GIP/glucagon tri-agonists, as the most clinically proximate evolution of endocrine peptide pharmacology.
  • Use the pharmacological gaps in legacy drugs as a framework for identifying where peptide-based research tools add the most mechanistic value.

The field is not replacing its foundations. It is building precisely where those foundations show their limits.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/polypeptide-peptides-in-endocrine-and-metabolic-pharmacology-lessons-from-amlodi.webp 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-17 13:07:122026-07-20 14:59:49Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top