Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: prostate-specific antigen

Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research

Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research

September 12, 2026/0 Comments/in Uncategorized/by

Nearly one in eight men will receive a prostate cancer diagnosis during their lifetime, making prostate-specific antigen one of the most scrutinized biomarkers in all of medicine. As research into hormone-modulating compounds accelerates, particularly selective estrogen receptor modulators like enclomiphene and polypeptide agents such as GLP-1 and GLP-3 analogs, laboratories and clinicians face a practical question: how does PSA monitoring integrate with these newer interventions? Understanding Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research is no longer a niche concern; it sits at the intersection of endocrinology, oncology safety, and advanced peptide science.

Key Takeaways

  • PSA is a serine protease produced by prostate epithelium; any intervention that raises testosterone, including enclomiphene, can modestly influence PSA values.
  • Phase III enclomiphene trials have not demonstrated a statistically significant increase in PSA or a clear prostate cancer signal compared with placebo.
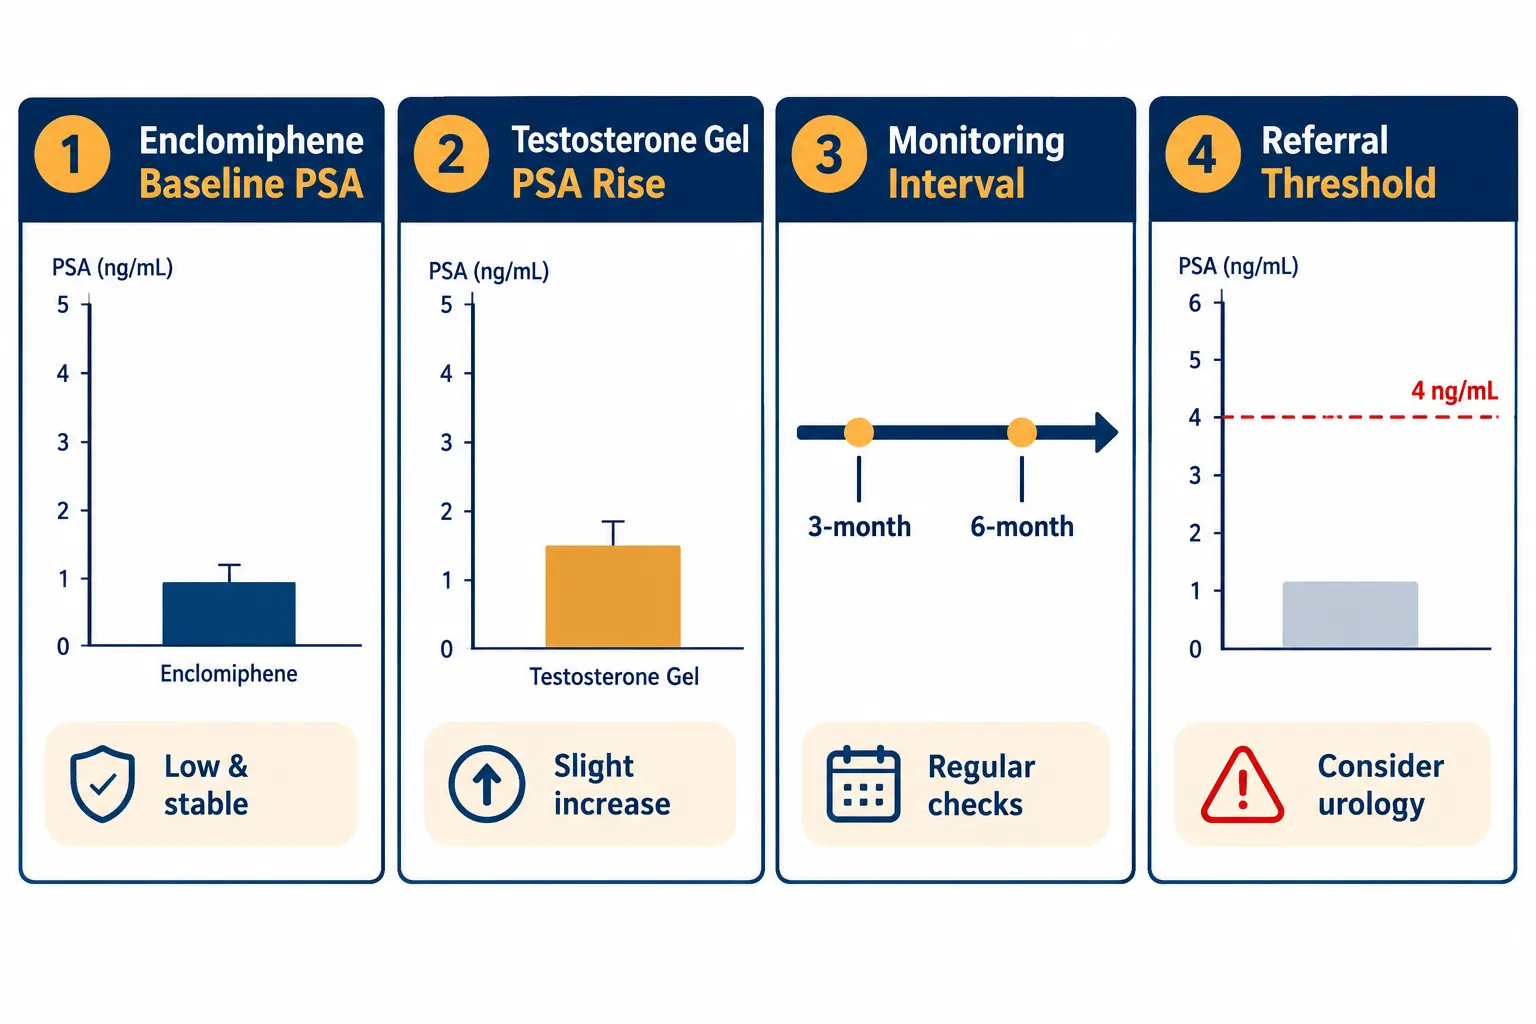
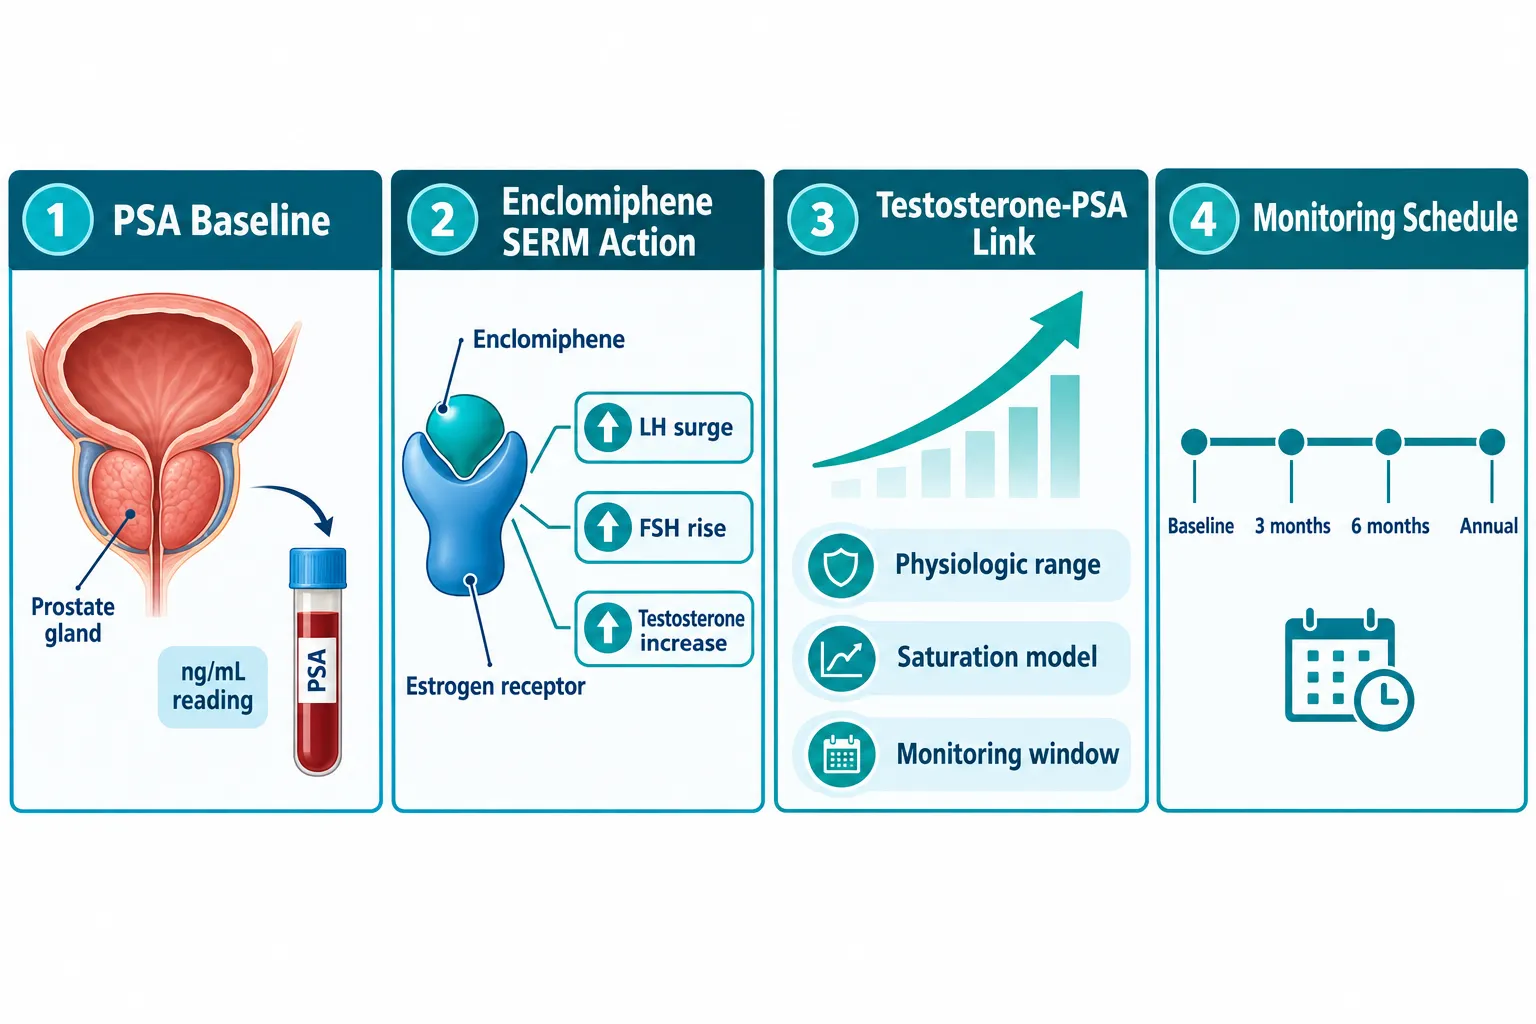
  • Standard monitoring practice mirrors testosterone-replacement protocols: baseline PSA, repeat at 3 and 6 months, then periodic review.
  • GLP-class peptides (GLP-1, GLP-3 analogs such as retatrutide) are not currently integrated into PSA-specific monitoring frameworks; their research focus remains metabolic and cardiovascular.
  • PSA monitoring functions as a safety net, not as evidence that hormone-modulating therapy causes prostate cancer.

What Is PSA and Why Does Hormone Status Matter
What Is PSA and Why Does Hormone Status Matter

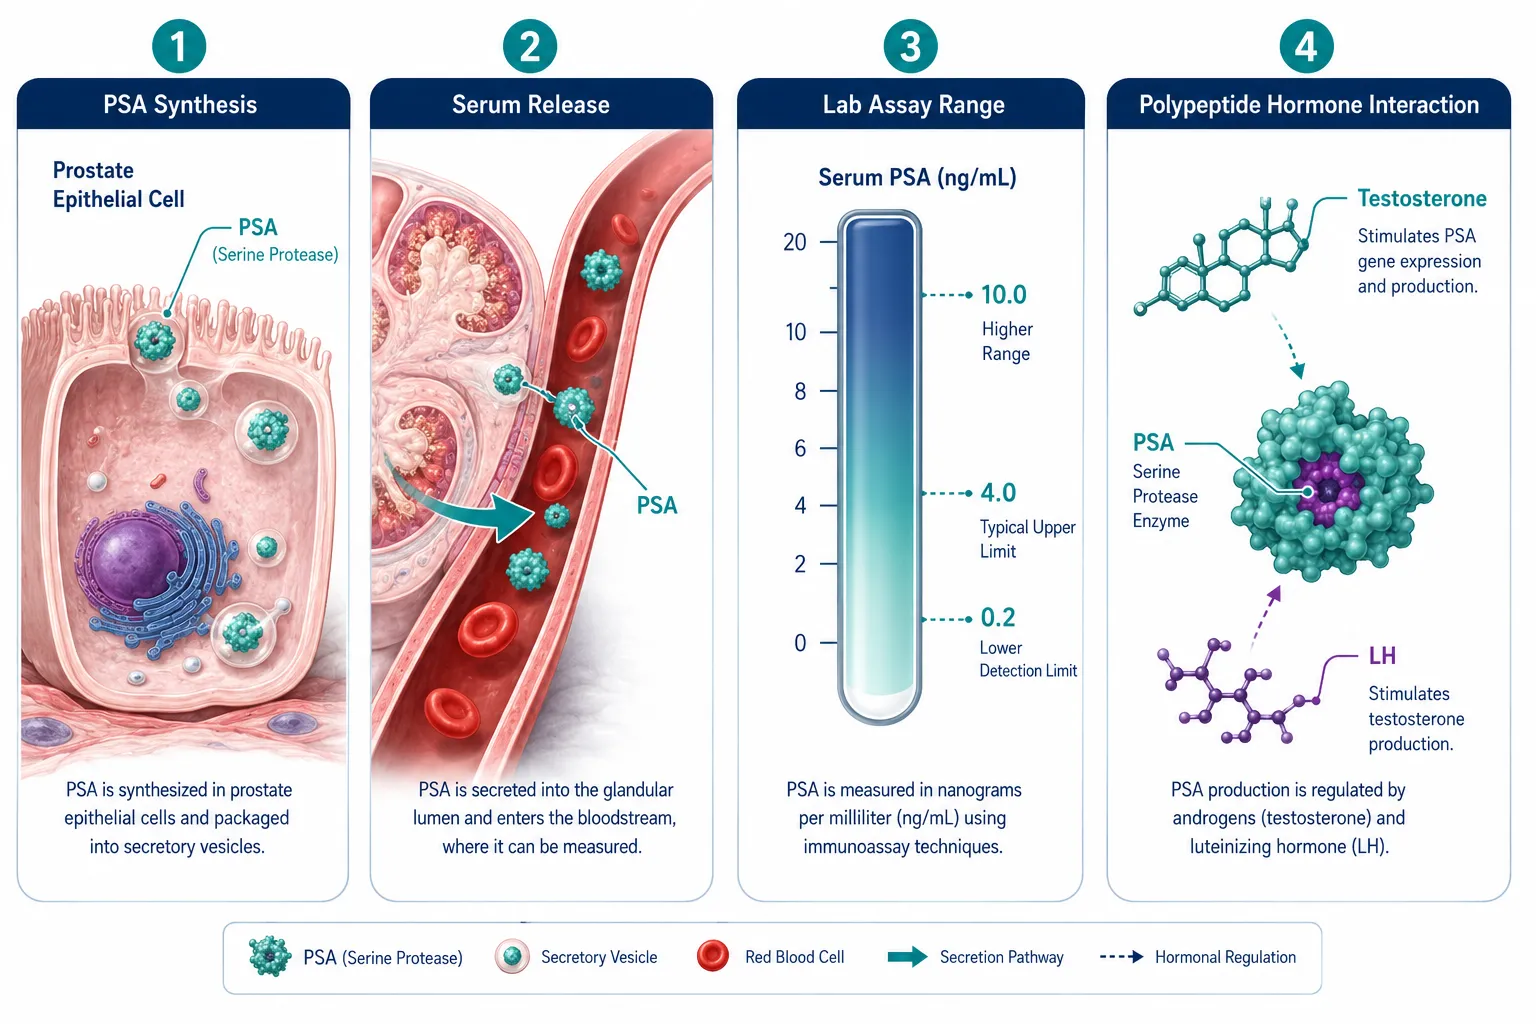
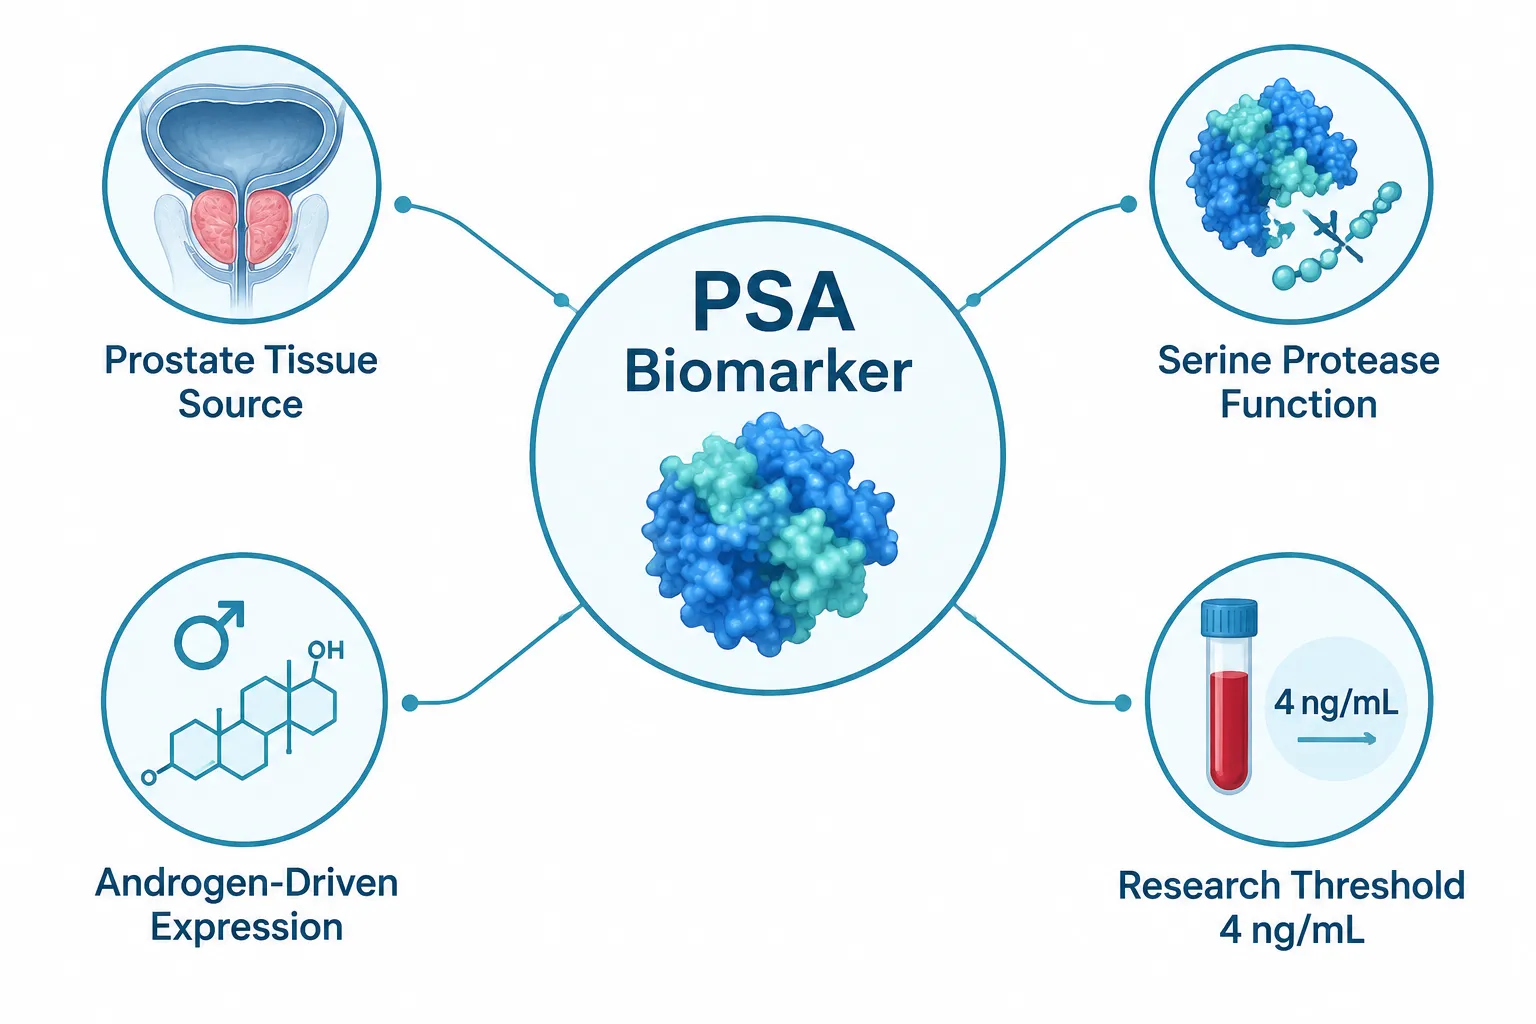
Prostate-specific antigen is a serine protease encoded by the KLK3 gene and secreted almost exclusively by prostate epithelial cells. Its primary physiologic role is liquefying seminal fluid, but because it leaks into circulation in proportion to prostate tissue volume and disruption, serum PSA has become the standard screening tool for prostate pathology.

Why does testosterone matter to PSA? Androgen receptors in prostate tissue directly regulate KLK3 transcription. When testosterone rises, whether from exogenous replacement or from endogenous stimulation, prostate cells can increase PSA secretion. This relationship is real but not linear. The "saturation model" of prostate androgen biology proposes that androgen receptors become fully occupied at relatively low testosterone concentrations (roughly 200-250 ng/dL), meaning that moving from low-normal to high-normal testosterone produces far less incremental PSA change than moving from castrate levels to low-normal. This model has important implications for how researchers interpret PSA data in enclomiphene studies.

Researchers exploring enclomiphene in male endocrine research and LH, FSH, and testosterone signaling need to understand this saturation dynamic before drawing conclusions from PSA fluctuations in study subjects.

Enclomiphene and PSA: What the Evidence Shows in 2026

Enclomiphene and PSA: What the Evidence Shows in 2026

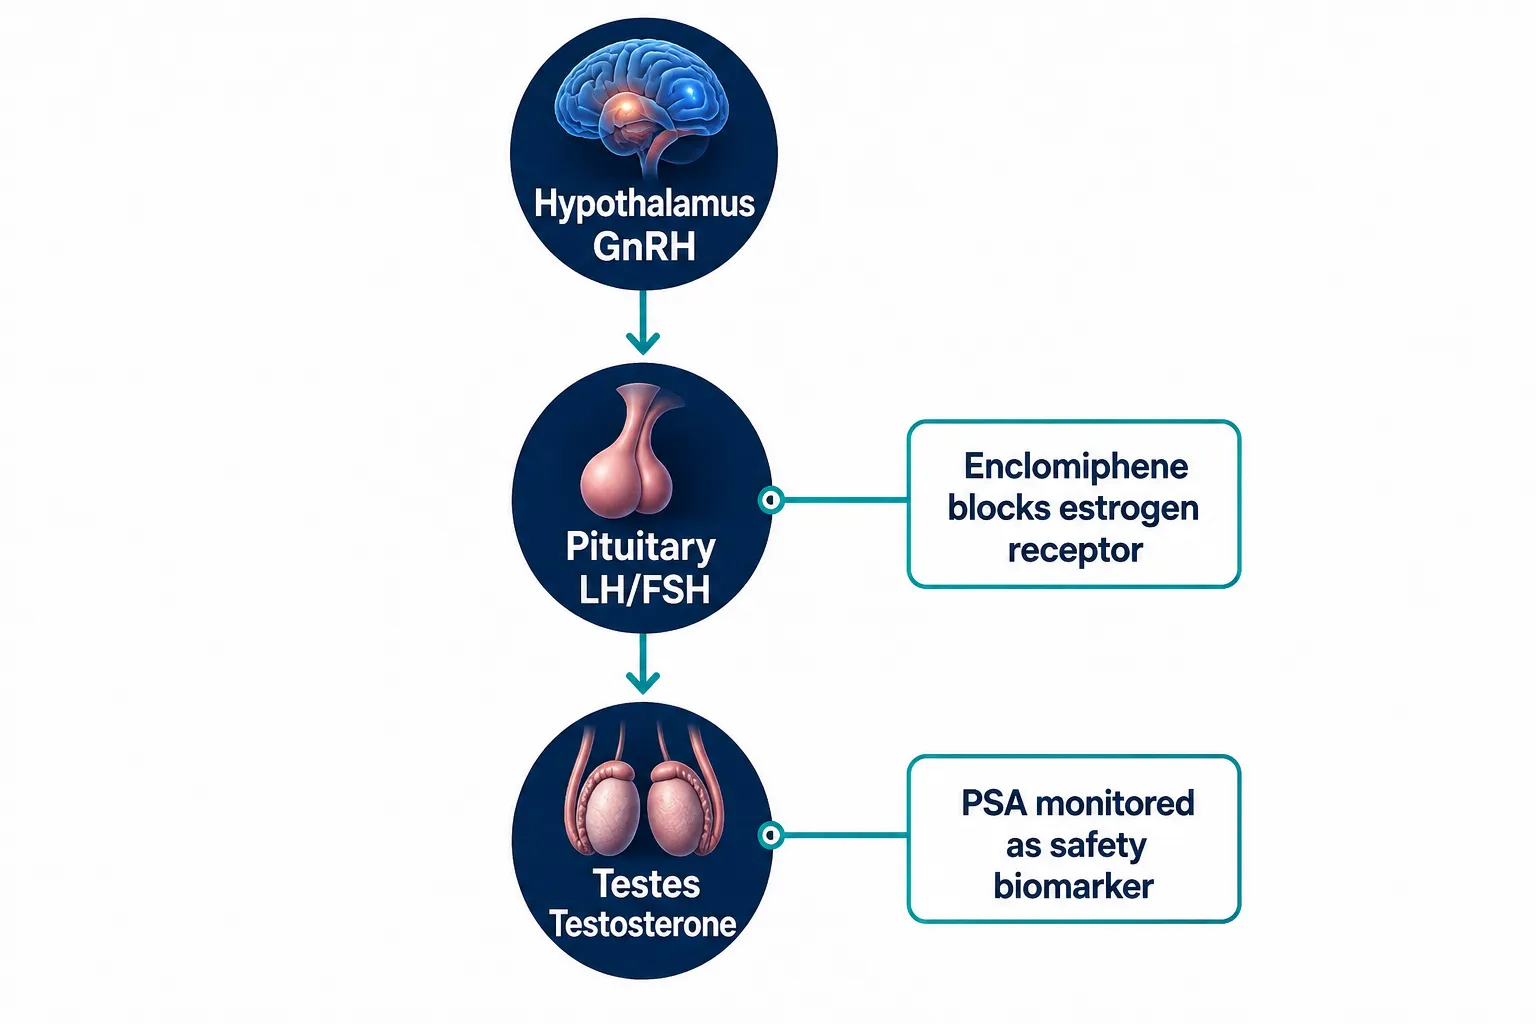
Enclomiphene is the trans-isomer of clomiphene citrate. Unlike the mixed-isomer parent compound, it acts as a pure estrogen receptor antagonist at the hypothalamic-pituitary axis, blocking negative feedback and driving endogenous LH and FSH secretion, which in turn stimulates testicular testosterone production. This mechanism makes it conceptually distinct from exogenous testosterone, yet the downstream effect on prostate tissue is similar: higher circulating testosterone.

Phase III trials enrolling up to approximately 354 men over roughly six months have not shown a statistically significant PSA increase compared with placebo. No trial to date has demonstrated a cancer-incidence signal attributable to enclomiphene. Older comparative data pitting oral enclomiphene against transdermal testosterone gels found only small, clinically insignificant PSA changes with enclomiphene, changes that were not consistently observed with gels, suggesting that endogenous stimulation via a serm may affect PSA differently than direct exogenous androgen delivery.

For researchers building study designs, understanding how serms interact with polypeptide hormones in research provides essential context for interpreting hormone panels alongside PSA data.

Practical PSA Monitoring Thresholds

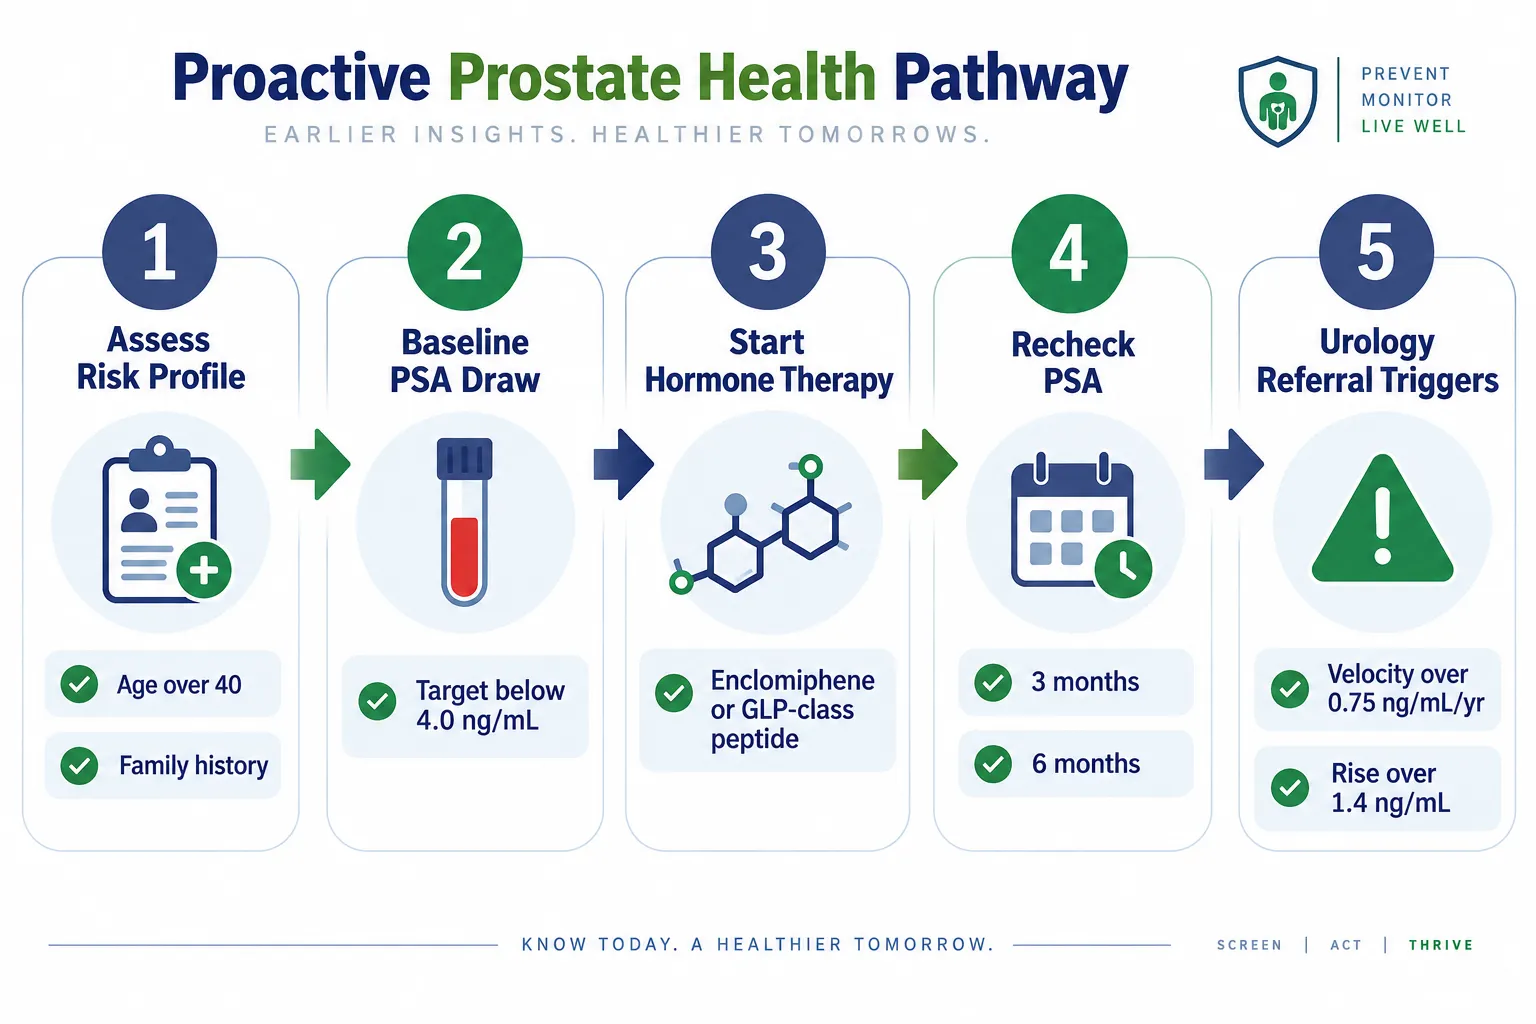
Current clinical guidance, updated through 2026, recommends the following framework for men receiving enclomiphene:

Checkpoint Action
Before starting (all men over 40) Obtain baseline PSA
Baseline PSA > 4.0 ng/mL Urology clearance before proceeding
Baseline PSA > 3.0 ng/mL + first-degree family history Urology clearance before proceeding
3-month recheck Compare with baseline; note velocity
6-month recheck Continue periodic monitoring
PSA rise > 1.4 ng/mL in any 3-12-month window Urology referral
PSA velocity > 0.75 ng/mL per year Urology referral

This framework mirrors Endocrine Society hypogonadism guidelines, which state that any testosterone-raising therapy, including enclomiphene, should be avoided in men with known prostate cancer, palpable nodules, or markedly elevated PSA at baseline.

GLP-Class Peptides and the PSA Interface: Where Research Stands
GLP-Class Peptides and the PSA Interface: Where Research Stands

GLP-1 receptor agonists and the newer triple-agonist GLP-3 class agents (such as retatrutide) have generated enormous research interest for their metabolic and cardiovascular effects. Researchers following GLP-3 retatrutide and triple-agonist peptide phase 3 obesity data will note that current endocrine and urology guidance does not integrate GLP-class agents into PSA-specific monitoring frameworks.

This absence is meaningful, not an oversight. GLP-1 and GLP-3 receptors are expressed in pancreatic beta cells, the gut, the brain, and cardiovascular tissue, but not in prostate epithelium at levels that would be expected to alter PSA transcription. These peptides work through cyclic AMP-mediated pathways that are mechanistically separate from the androgen receptor axis driving PSA production.

Where GLP-class research does intersect with prostate health indirectly:

  • Obesity is an established risk factor for aggressive prostate cancer; GLP-class agents that reduce visceral adiposity may theoretically reduce that background risk over time.
  • Weight loss lowers serum estrogen (produced in adipose tissue), which can slightly alter the testosterone-estrogen ratio, a variable that enclomiphene also modulates.
  • Researchers combining enclomiphene with GLP-class peptides in metabolic models, as explored in work on tesofensine, enclomiphene, and peptide-based approaches in metabolic research, should track PSA as part of a comprehensive safety panel even when GLP agents alone would not require it.

The key principle: PSA monitoring requirements are driven by the testosterone-raising component of any research protocol, not by the GLP-class peptide component.

Prostate Safety in Broader Hormone Research Contexts

Long-term observational data and multiple meta-analyses consistently show that testosterone replacement does not meaningfully accumulate in prostate tissue or provoke major biologic change beyond physiologic ranges. The American Urological Association permits carefully monitored testosterone therapy even in select men on active surveillance for low-risk prostate cancer, provided baseline and serial PSA plus imaging are tracked. This permissive but watchful stance extends logically to enclomiphene, which raises testosterone endogenously rather than exogenously.

Researchers working with growth hormone secretagogues alongside these agents can find relevant mechanistic background in the tesa and ipamorelin comparative analysis of growth hormone secretion mechanisms, as GH-axis peptides also affect body composition in ways that could influence the hormonal milieu relevant to PSA.

Conclusion

Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research comes down to one core principle: PSA is a downstream marker of androgen receptor activity in prostate tissue, and any compound that raises testosterone, directly or indirectly, warrants structured PSA surveillance. Enclomiphene raises endogenous testosterone and therefore fits within established monitoring protocols. GLP-class peptides, by contrast, operate through entirely different receptor pathways and carry no current evidence of PSA influence, though they may alter the broader hormonal environment when combined with serms.

Actionable steps for researchers and clinicians in 2026:

  1. Obtain a baseline PSA in all male subjects over 40 before initiating enclomiphene or any testosterone-raising protocol.
  2. Apply established velocity and threshold triggers (greater than 0.75 ng/mL per year; any single rise exceeding 1.4 ng/mL) to prompt urology evaluation.
  3. Do not apply PSA-specific monitoring requirements to GLP-class peptide protocols unless a testosterone-raising agent is co-administered.
  4. Document PSA alongside full hormone panels (LH, FSH, total and free testosterone) to distinguish therapy-driven changes from pathologic trends.
  5. Review the evolving literature on enclomiphene vs enclomiphene citrate formulation differences to ensure study compounds are correctly characterized before interpreting PSA data.

PSA monitoring is not a reason to avoid hormone-modulating research, it is the tool that makes that research safe and scientifically credible.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prostate-specific-antigen-and-hormone-modulating-compounds-how-psa-monitoring-in.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-12 13:12:172026-09-12 13:12:17Prostate Specific Antigen and Hormone-Modulating Compounds: How PSA Monitoring Interfaces With Enclomiphene and GLP-Class Peptide Research
Prostate Specific Antigen and Peptide Hormones: How PSA Is Used to Monitor Enclomiphene and GLP-Class Research Studies

Prostate Specific Antigen and Peptide Hormones: How PSA Is Used to Monitor Enclomiphene and GLP-Class Research Studies

September 8, 2026/0 Comments/in Uncategorized/by

Fewer than one in five researchers working with hormone-modulating peptides routinely track prostate-specific antigen as a safety endpoint, yet the field of prostate specific antigen and peptide hormones is rapidly reshaping how enclomiphene and GLP-class research studies are designed, monitored, and interpreted. Understanding the intersection of PSA biology with emerging serm and incretin-based research is no longer optional for anyone serious about endocrine safety endpoints.

Key Takeaways

  • PSA is a serine protease produced in prostate tissue and regulated by androgen signaling, making it a logical safety marker in any research protocol that modulates testosterone or related hormones.
  • Enclomiphene studies show small, clinically minor PSA increases compared with testosterone-replacement protocols, but baseline and periodic PSA monitoring remains standard practice.
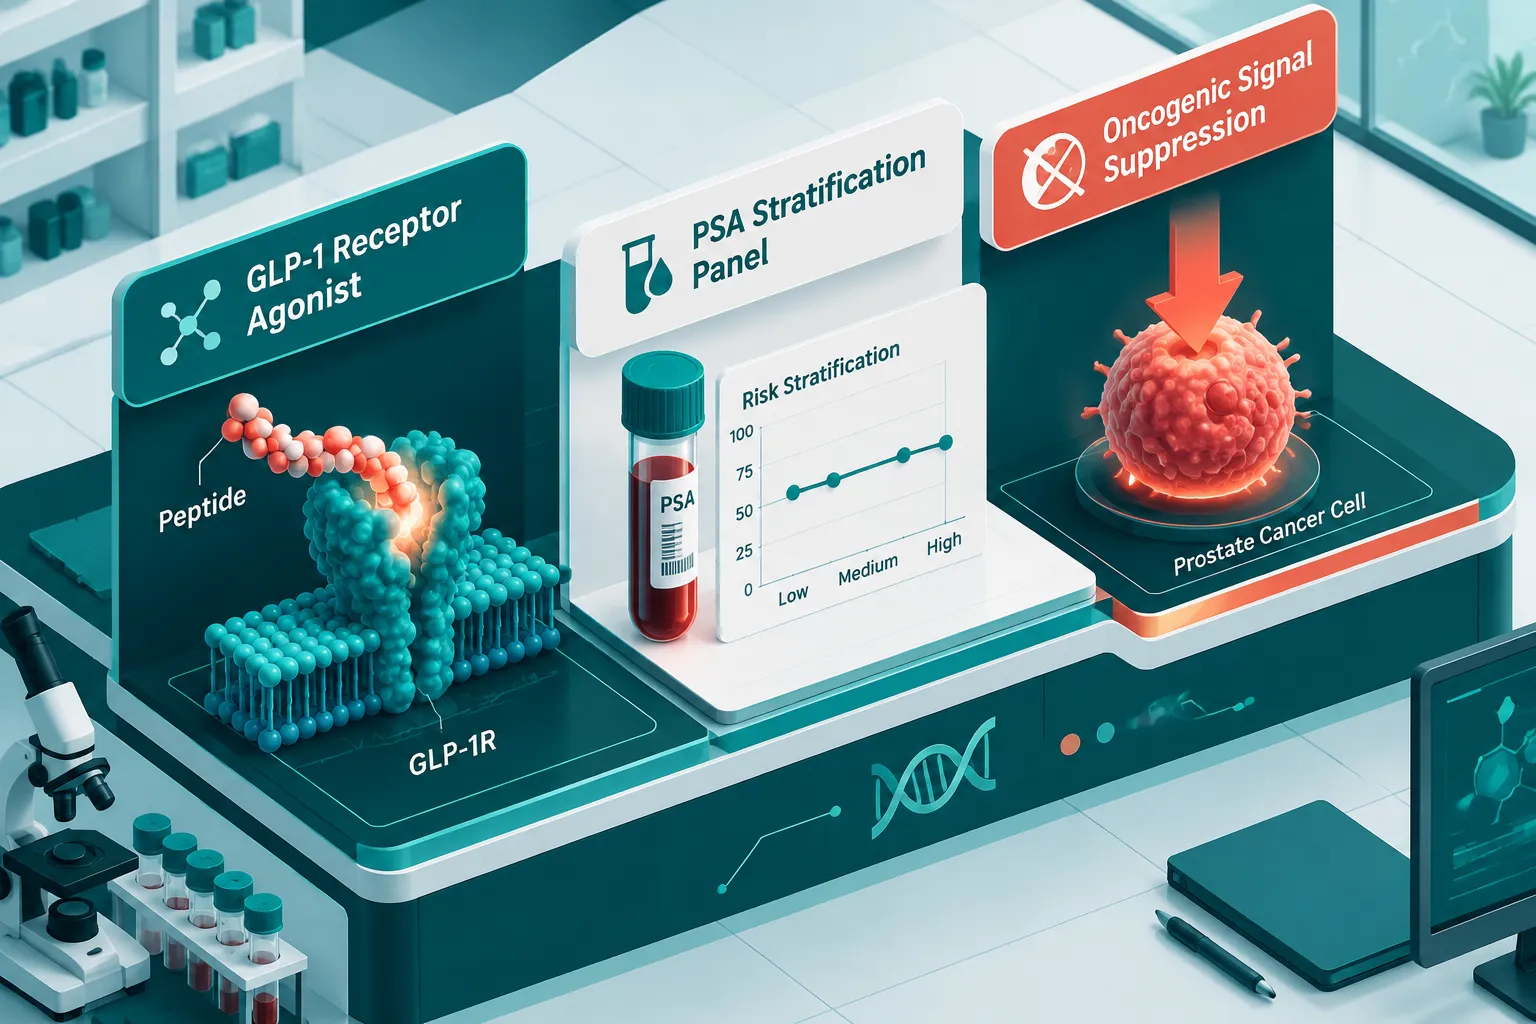
  • GLP-1 receptor agonist research uses PSA primarily for risk stratification rather than as a direct drug-response marker.
  • Mechanistic data suggest GLP-1 receptor activation may suppress oncogenic signaling in prostate tissue, giving PSA a secondary role as an indirect safety endpoint.
  • Unified PSA monitoring thresholds for enclomiphene and GLP-class research are expected to converge by 2030.

What PSA Is and Why It Matters in Peptide Hormone Research

What PSA Is and Why It Matters in Peptide Hormone Research

Prostate-specific antigen is a serine protease enzyme encoded by the KLK3 gene and secreted almost exclusively by prostate epithelial cells. Its primary physiological role is to liquefy seminal fluid, but because its expression is tightly driven by androgen receptor signaling, serum PSA levels rise and fall in response to changes in the androgen environment.

This androgen-sensitivity is precisely what makes PSA relevant to peptides and polypeptides in endocrine pharmacology. Any compound that raises circulating testosterone, whether a peptide hormone, a serm like enclomiphene, or an exogenous androgen, can theoretically stimulate PSA production. Conversely, compounds that blunt androgen signaling tend to suppress PSA.

Standard PSA thresholds used in research monitoring:

PSA Level (ng/mL) Interpretation in Research Context
Below 1.0 Low baseline; minimal androgen stimulation
1.0-4.0 Normal range; monitor for velocity changes
Above 4.0 Referral threshold; warrants further evaluation
Velocity > 0.75/year Clinically significant rise regardless of absolute value

For researchers working with peptides in basic cell biology and hormone analogues, PSA provides a low-cost, widely available window into androgen-axis activity that complements more expensive genomic or imaging endpoints.

Prostate Specific Antigen and Peptide Hormones in Enclomiphene Monitoring Protocols

Prostate Specific Antigen and Peptide Hormones in Enclomiphene Monitoring Protocols

Enclomiphene citrate is the trans-isomer of clomiphene and acts as a selective estrogen receptor modulator (serm) at the hypothalamic-pituitary axis. By blocking estrogen's negative feedback, it drives a rise in LH and FSH, which in turn stimulates endogenous testosterone production. Because testosterone is the primary driver of PSA expression, any enclomiphene-mediated testosterone increase carries at least a theoretical PSA signal.

Research published through 2025 and reviewed in 2026 consistently shows that enclomiphene produces small but measurable PSA increases, typically within the normal reference range and substantially lower than the rises observed with exogenous testosterone gels or injections. Over follow-up periods extending to three years, no significant PSA impact has been confirmed, though researchers and clinicians continue to advise monitoring because the androgen-axis stimulation is real.

Current enclomiphene PSA monitoring protocol (adapted from testosterone-therapy guidelines):

  1. Establish a baseline PSA before the study compound is introduced.
  2. Repeat PSA at 3 months and 6 months after initiation.
  3. Apply the same 4 ng/mL referral threshold and 0.75 ng/mL/year velocity rule used in testosterone-replacement research.
  4. Document any concurrent medications that could confound PSA (e.g., 5-alpha reductase inhibitors).

The borrowing of thresholds from testosterone-replacement guidelines reflects a practical reality: enclomiphene-specific PSA criteria do not yet exist. Debate continues in the literature about whether early routine PSA checks add meaningful safety data in younger, otherwise healthy research subjects, but baseline and periodic monitoring remain the consensus standard.

"The PSA changes seen with enclomiphene are minor relative to exogenous testosterone, but the absence of dedicated long-term data makes monitoring a non-negotiable safety step in responsible research design."

For a broader view of how enclomiphene fits within receptor biology, the article on enclomiphene and estrogen receptor biology provides useful mechanistic context.

GLP-Class Research Studies and the Role of PSA Risk Stratification

GLP-Class Research Studies and the Role of PSA Risk Stratification

The relationship between prostate specific antigen and peptide hormones in GLP-class research is fundamentally different from the enclomiphene context. GLP-1 receptor agonists, including the triple-agonist retatrutide studied in GLP-3 retatrutide phase 3 trials, do not directly stimulate androgen production. Instead, PSA enters GLP-class research as a risk stratification tool and a secondary safety endpoint.

Large-cohort analyses of GLP-1 receptor agonist users show a neutral to mildly protective prostate-cancer risk profile. Mechanistic studies add an important layer: GLP-1 receptor activation appears to suppress oncogenic signaling pathways in prostate cancer cell lines, suggesting a potential indirect protective effect. PSA is the practical instrument through which researchers detect any meaningful change in prostate cancer risk during these studies.

How PSA functions in GLP-class study designs:

  • Baseline stratification: Subjects with elevated baseline PSA are flagged for exclusion or sub-group analysis to prevent confounding.
  • Case detection: Any PSA rise during a GLP-1 study triggers standard urological workup, separating drug-related from incidental findings.
  • Cardiometabolic integration: PSA is increasingly analyzed alongside insulin resistance markers, visceral fat measurements, and inflammatory biomarkers in risk-reduction models.

This integrated approach is consistent with how carbohydrate antigens and peptide-based assays are being combined with modern research peptide endpoints to build richer safety profiles.

Researchers interested in the metabolic dimensions of GLP-class compounds can also explore tesofensine and metabolic research for a comparative look at how different appetite-modulating agents handle overlapping endpoints.

Where Enclomiphene and GLP-Class PSA Monitoring Are Headed

The convergence of prostate specific antigen and peptide hormones research across serm and incretin platforms is generating pressure for unified monitoring guidelines. Expert commentary in 2026 points toward a likely consensus by 2030 in which:

  • Formal PSA monitoring thresholds specific to enclomiphene will be established, rather than borrowed from testosterone-therapy protocols.
  • PSA dynamics will be incorporated as pre-specified secondary endpoints in GLP-1 and GLP-3 interventional trials, particularly those targeting obesity-related prostate cancer risk.
  • Composite biomarker panels, combining PSA with sex hormone-binding globulin, estradiol, and metabolic markers, will replace single-marker monitoring in advanced study designs.

Understanding how researchers classify hormone analogues and peptide chains is foundational to interpreting these evolving protocols. The overview at peptides in modern research covers the structural and mechanistic distinctions that underpin these monitoring decisions.

Conclusion

The intersection of prostate specific antigen and peptide hormones is no longer a niche concern. For enclomiphene research, PSA monitoring is a borrowed but essential safety practice, one that will likely gain its own dedicated thresholds as long-term data mature. For GLP-class studies, PSA serves a distinct role as a risk stratification and case-detection tool, with emerging mechanistic evidence suggesting these compounds may actually reduce prostate oncogenic signaling.

Actionable next steps for researchers:

  • Establish a documented PSA baseline before initiating any enclomiphene or testosterone-modulating protocol.
  • Apply the 4 ng/mL threshold and 0.75 ng/mL/year velocity rule as interim standards until enclomiphene-specific guidelines are published.
  • In GLP-class study designs, include PSA as a pre-specified secondary safety endpoint with a clear exclusion and referral algorithm.
  • Monitor the literature through 2026-2030 for convergence on unified PSA thresholds across serm and incretin research platforms.
  • Cross-reference PSA data with cardiometabolic and hormonal markers to build more complete safety profiles.

Staying current with these developments positions any research program to meet the higher safety and reporting standards that regulators and peer reviewers will increasingly expect.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prostate-specific-antigen-and-peptide-hormones-how-psa-is-used-to-monitor-enclom.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-08 13:08:202026-09-08 13:08:20Prostate Specific Antigen and Peptide Hormones: How PSA Is Used to Monitor Enclomiphene and GLP-Class Research Studies
Prostate Specific Antigen, Enclomiphene, and Peptide Hormones: How Labs Design serm and GLP-Class Hormone Studies

Prostate Specific Antigen, Enclomiphene, and Peptide Hormones: How Labs Design serm and GLP-Class Hormone Studies

September 5, 2026/0 Comments/in Uncategorized/by

More than 40 million PSA tests are ordered in the United States each year, making prostate-specific antigen one of the most tracked biomarkers in modern medicine. Yet PSA does not exist in isolation. Increasingly, research programs studying Prostate Specific Antigen, Enclomiphene, and Peptide Hormones are weaving this marker into broader hormone study frameworks, frameworks that now include selective estrogen receptor modulators (serms) like enclomiphene and peptide-based agents in the GLP class. Understanding how labs design these studies reveals why PSA belongs in the same safety panel as testosterone, LH, FSH, and pharmacokinetic peptide data.

Key Takeaways

  • PSA serves as a critical safety biomarker in male hormone studies, including serm trials involving enclomiphene citrate.
  • Enclomiphene raises testosterone while preserving sperm production, distinguishing it from testosterone replacement therapy.
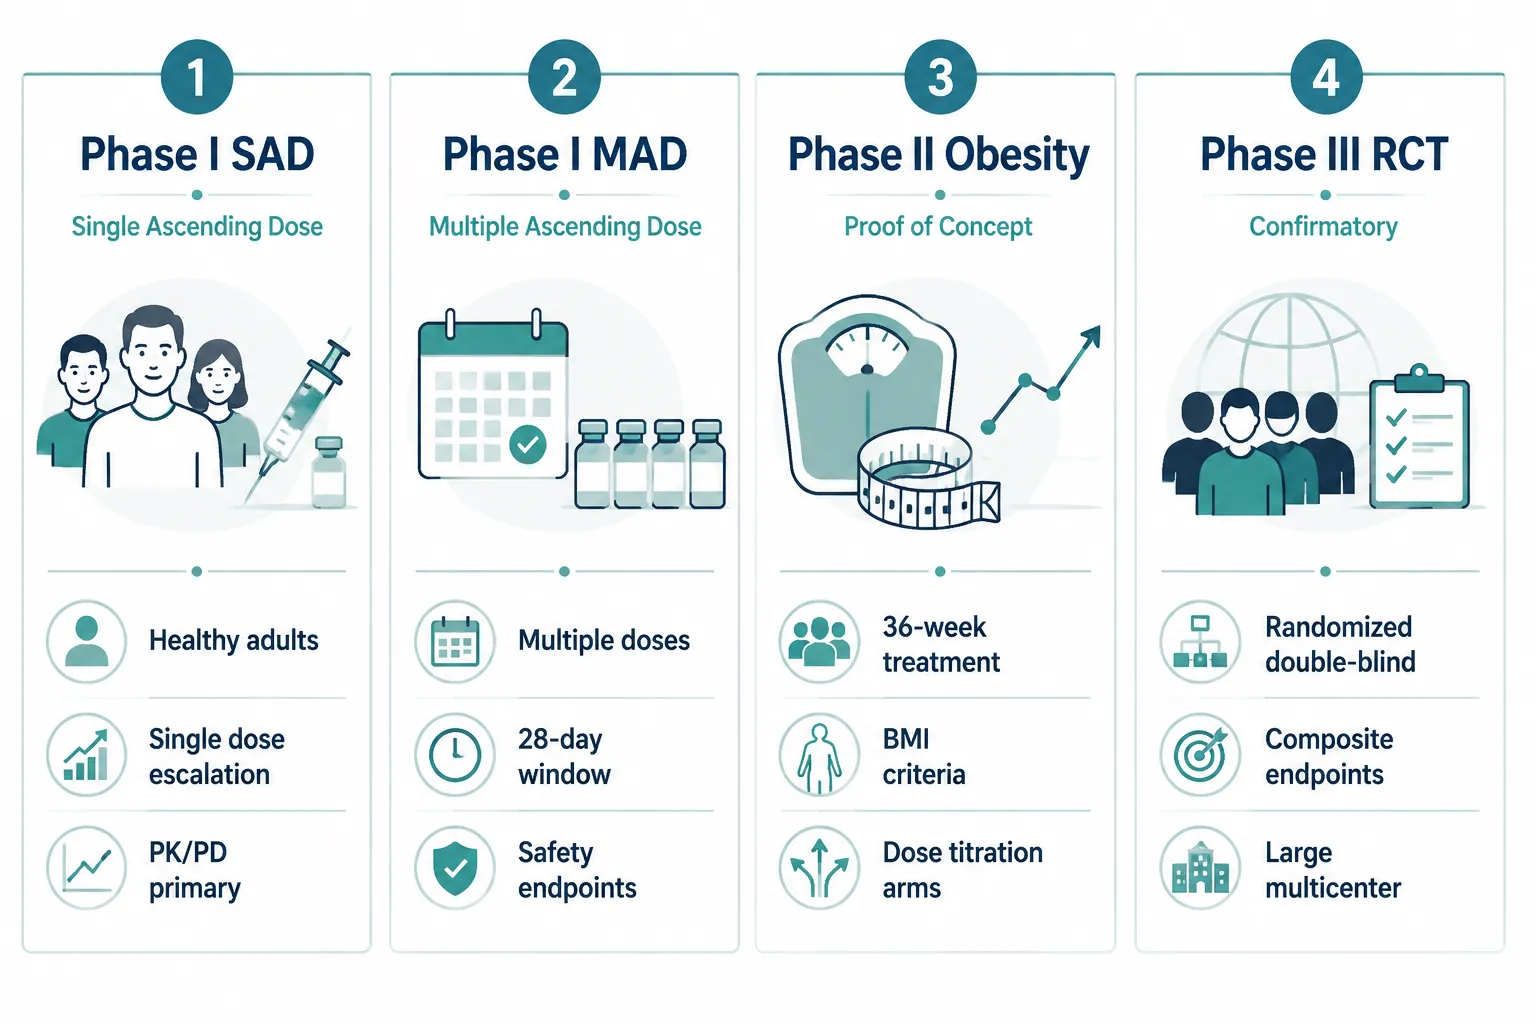
  • GLP-1 receptor agonist trials use ascending-dose, randomized, double-blind designs with composite endpoints.
  • Labs increasingly combine PSA monitoring with peptide pharmacokinetic data to build complete hormonal safety profiles.
  • Regulatory complexity, such as enclomiphene's relationship to clomiphene, directly shapes how study protocols are written.

PSA as a Biomarker in Hormone Research

PSA as a Biomarker in Hormone Research

PSA is a glycoprotein produced by prostate epithelial cells, and its serum level rises when androgen signaling increases. That biological fact makes it indispensable in any study that deliberately elevates testosterone. When a lab designs a serm trial for secondary hypogonadism, the protocol must account for the downstream androgenic effect on prostate tissue, and PSA is the most practical, non-invasive way to do that.

In enclomiphene phase III safety work, clinical laboratory tests form a core safety endpoint alongside physical exams, visual acuity checks, and slit-lamp eye examinations. Although published summaries do not always headline PSA explicitly, practitioners running off-label hormone protocols consistently include it in serial safety panels. The reasoning is straightforward: if enclomiphene successfully raises morning total testosterone from below 300 ng/dL into the normal range, prostate tissue will experience that androgen signal. Monitoring PSA at baseline, mid-study, and endpoint catches any clinically meaningful rise before it becomes a safety event.

Why PSA matters beyond prostate cancer screening:

  • It quantifies androgenic stimulation of prostate tissue in real time.
  • It provides a continuous safety variable rather than a binary pass/fail outcome.
  • It allows dose-adjustment decisions during titration phases.
  • It satisfies FDA expectations for safety data in androgen-modulating drug applications.

For researchers exploring therapeutic peptides alongside serms, PSA anchors the hormone safety panel to a well-validated clinical standard.

How Enclomiphene serm Studies Are Structured

The design of enclomiphene trials illustrates how Prostate Specific Antigen, Enclomiphene, and Peptide Hormones research frameworks are built from the ground up. Enclomiphene citrate is the trans-isomer of clomiphene, and its regulatory path has been complicated precisely because the FDA must decide how to treat the relationship between an isomer and an already-marketed parent compound. As of 2026, an NDA remains in progress with outstanding FDA questions on that relationship.

Phase III enclomiphene trials enrolled men aged 18-65 with secondary hypogonadism, defined as morning total testosterone below 300 ng/dL on two separate occasions with non-elevated LH. The open-label, escalating-dose design started participants at 12.5 mg with titration to 25 mg if needed over six months. The key clinical finding: enclomiphene raises total testosterone into the normal range while preserving LH, FSH, and sperm production, a meaningful advantage over exogenous testosterone replacement, which suppresses the hypothalamic-pituitary-gonadal axis.

"Enclomiphene's ability to maintain spermatogenesis while restoring testosterone makes it a structurally different intervention than TRT, and that difference demands a different safety monitoring strategy."

For more on how serm compounds are categorized and studied, researchers can explore current literature on receptor-selective mechanisms.

Standard safety panel in enclomiphene studies:

Endpoint Category Specific Measures
Androgenic safety PSA, hematocrit, lipid panel
Reproductive hormones Total testosterone, LH, FSH
Ocular safety Visual acuity, slit-lamp exam
General clinical labs CMP, CBC, adverse event log

GLP-Class Peptide Hormone Study Design

GLP-Class Peptide Hormone Study Design

The design logic for GLP-1 receptor agonist studies shares structural DNA with serm trials but diverges sharply in endpoint architecture. A first-in-human phase I study of a novel oral small-molecule GLP-1 receptor agonist illustrates the current template: three sequential parts covering single ascending dose (2.5-50 mg in healthy adults), a 28-day multiple ascending dose in healthy adults, and a 28-day weekly-titration multiple ascending dose in overweight or obese adults. All three parts are randomized, double-blind, and placebo-controlled, with safety and tolerability as primary endpoints and pharmacokinetics and pharmacodynamics as key secondary measures.

When labs repurpose existing GLP-1 agents for new indications, such as substance use disorders or neurodegenerative disease, a common design strategy emerges: keep established metabolic dosing (for example, semaglutide up to 1.0 mg once weekly) and concentrate design innovation on endpoints and patient populations. This approach reduces regulatory uncertainty because pharmacokinetic data already exists.

Researchers interested in signaling peptides and their receptor interactions will recognize that GLP-1 receptor agonists operate through similar second-messenger cascades as other peptide classes, making cross-class study design comparisons genuinely useful.

Key GLP-1 trial design principles in 2026:

  • Integrated cardiometabolic endpoints (cardiovascular events, kidney disease, weight)
  • "Low and slow" titration strategies to balance tolerability with efficacy
  • Real-world data sets used to power sample sizes and set event rate assumptions
  • Bridging studies that connect known pharmacology to new therapeutic uses

For context on how stacking or combining peptide agents affects study design, the discussion of single peptide vs stack approaches is directly relevant to multi-arm GLP-1 trial architectures.

Integrating PSA, serm, and Peptide Data Into a Unified Safety Framework

Integrating PSA, serm, and Peptide Data Into a Unified Safety Framework

The convergence of Prostate Specific Antigen, Enclomiphene, and Peptide Hormones research into unified safety frameworks reflects a broader shift in how hormone studies are powered and monitored. Labs running combination protocols, for instance, pairing a serm with a growth hormone-releasing peptide, must build safety panels that capture both androgenic effects (PSA, hematocrit) and peptide-specific effects (IGF-1, fasting glucose, injection-site reactions).

Research on Sermorelin, Ipamorelin, and CJC-1295 dosage demonstrates how multi-peptide protocols require layered monitoring, just as multi-arm GLP-1 trials require composite endpoint tracking. Similarly, Tesamorelin vs Sermorelin comparisons highlight how small structural differences between peptide agents can produce meaningfully different safety profiles, a lesson directly applicable to enclomiphene's isomeric relationship to clomiphene.

Labs designing these studies in 2026 are also increasingly using next-generation cardio-kidney-metabolic outcome frameworks, which propose explicit design principles emphasizing integrated endpoints, careful patient selection, and robust trial architectures. When PSA is included as a continuous safety variable rather than a binary screening test, it fits naturally within these multi-domain outcome structures.

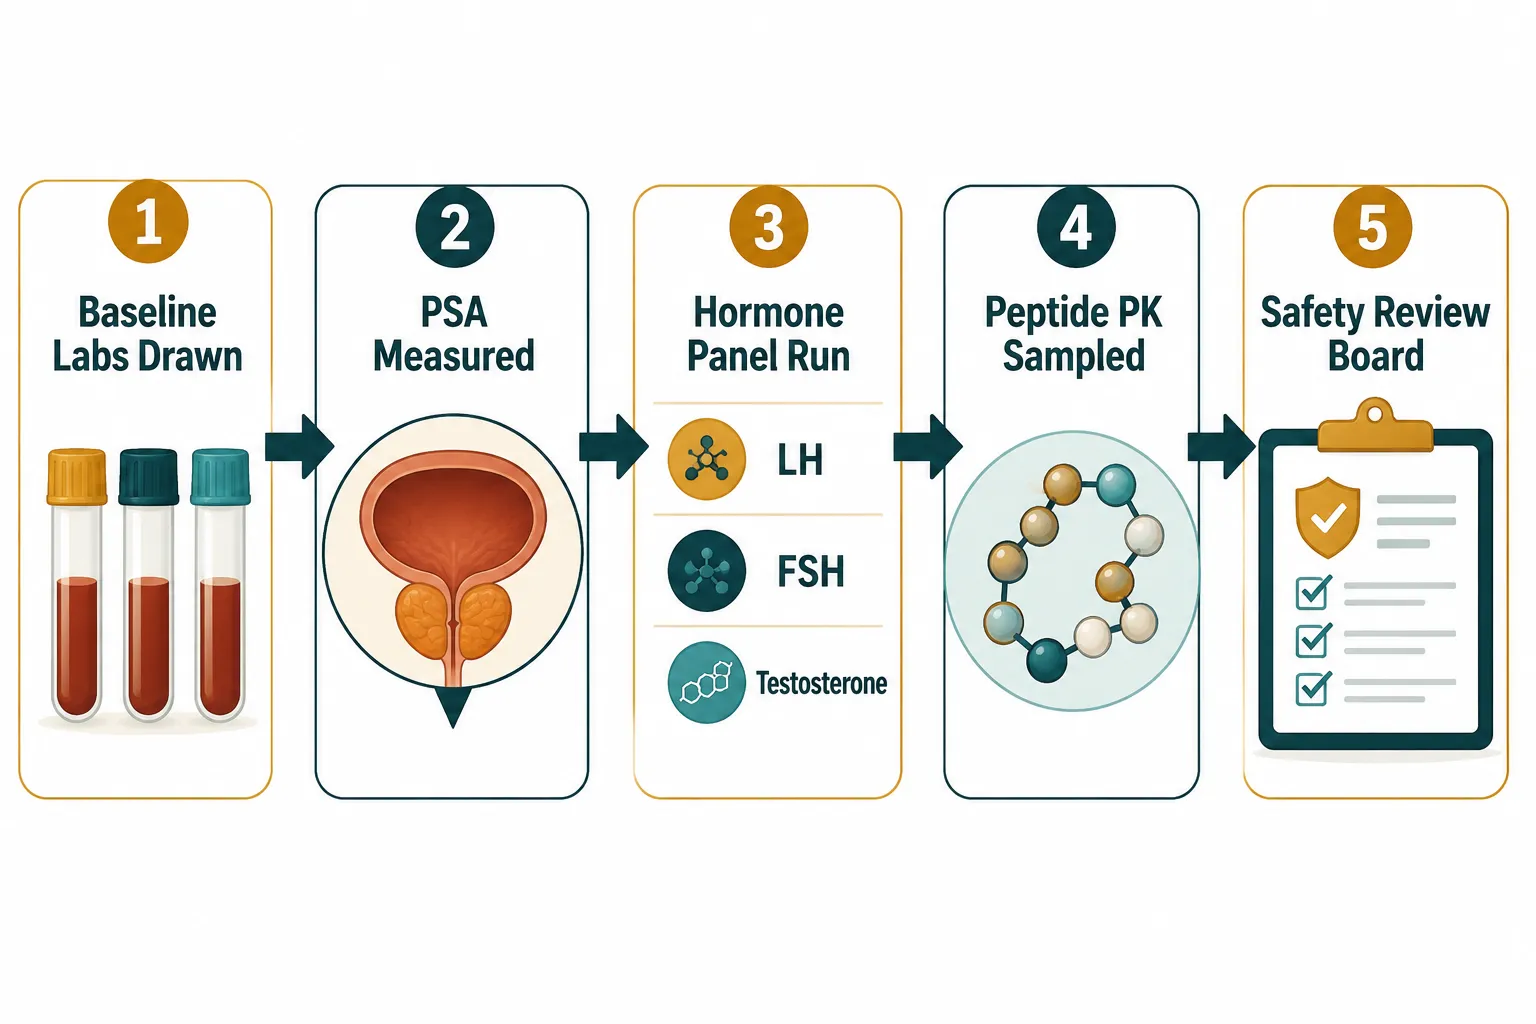
Practical checklist for integrated hormone study design:

  • Define androgen exposure with testosterone, LH, FSH at baseline and each visit
  • Include PSA at minimum at baseline, 3 months, and endpoint
  • Add peptide-specific PK sampling windows aligned with dosing intervals
  • Pre-specify PSA thresholds that trigger dose hold or discontinuation
  • Align FDA engagement strategy (pre-IND, Type C, pre-NDA meetings) with study design milestones

For labs sourcing research-grade compounds, ensuring purity is non-negotiable. Lab tested peptides with verified certificates of analysis are the baseline standard for any protocol that will generate safety data intended for regulatory review.

Conclusion

The intersection of Prostate Specific Antigen, Enclomiphene, and Peptide Hormones in modern hormone study design is not accidental, it reflects the biological reality that androgen modulation, receptor selectivity, and peptide signaling all converge on shared safety endpoints. PSA is not simply a prostate cancer screening tool; it is a dynamic androgenic biomarker that belongs in every male hormone study protocol.

Actionable next steps for researchers and clinicians:

  1. Include PSA as a continuous safety variable in any serm or androgen-modulating protocol, with pre-specified thresholds for dose adjustment.
  2. Apply GLP-1 trial design principles, ascending dose, randomized, double-blind, composite endpoints, to novel peptide programs wherever regulatory precedent is limited.
  3. Use real-world prescribing data and existing pharmacokinetic datasets to power sample sizes and reduce phase II risk.
  4. Engage FDA early through pre-IND meetings when an investigational compound has a structural relationship to an approved drug, as enclomiphene's path illustrates.
  5. Source only verified, lab tested peptides for any study generating data intended for regulatory submission.

Rigorous study design, comprehensive biomarker panels, and early regulatory alignment are the pillars that turn promising hormone research into actionable clinical evidence.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prostate-specific-antigen-enclomiphene-and-peptide-hormones-how-labs-design-serm.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-05 13:05:452026-09-05 13:05:45Prostate Specific Antigen, Enclomiphene, and Peptide Hormones: How Labs Design serm and GLP-Class Hormone Studies
Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies

Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies

September 3, 2026/0 Comments/in Uncategorized/by

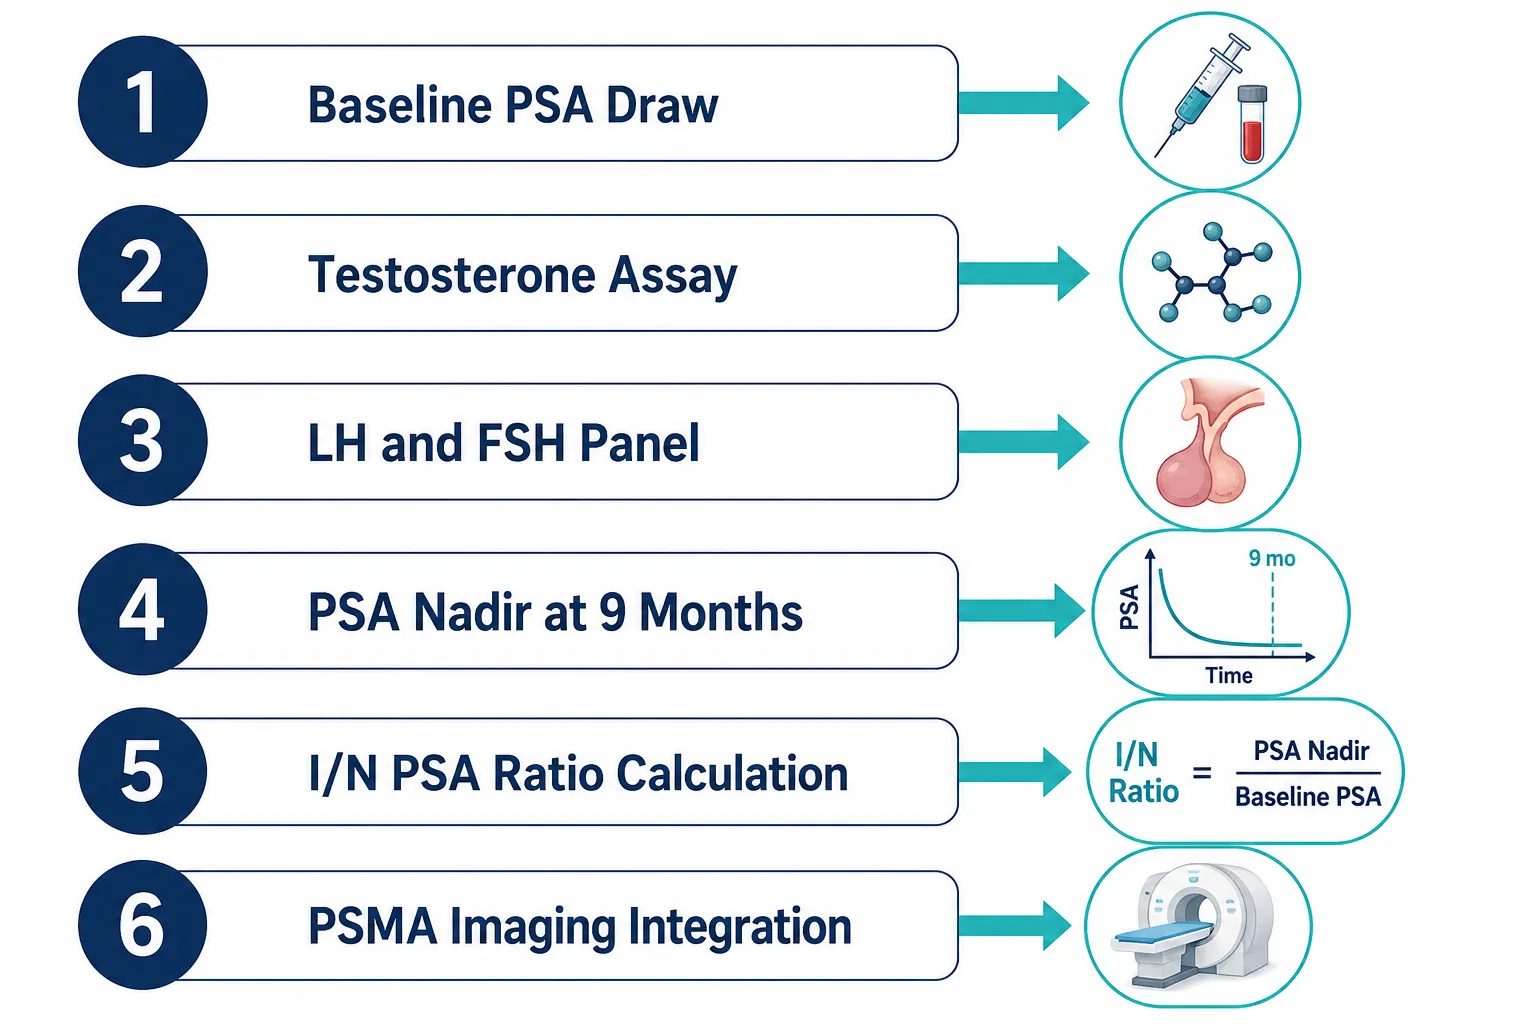
A PSA reading below 0.2 ng/mL within nine months of starting androgen deprivation therapy now ranks as one of the strongest independent predictors of long-term survival in hormone-sensitive prostate cancer research. That single data point illustrates why understanding Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies matters to anyone working in or following endocrine and oncology research.

Key Takeaways

  • PSA is a serine protease polypeptide and a primary efficacy endpoint in hormone and serm-related prostate research.
  • Research labs routinely pair PSA with testosterone, LH, and FSH to build a complete hormonal picture.
  • serm compounds, including enclomiphene, raise LH and FSH, which in turn elevates testosterone and can influence PSA levels.
  • Novel PSA indices such as the initial-to-nadir PSA ratio are emerging as independent predictors of treatment response.
  • Peptide and polypeptide hormone panels are expanding beyond PSA alone, integrating PSMA metrics and growth hormone secretagogue markers in translational trials.

What PSA Actually Is: A Polypeptide at the Center of Hormone Research

What PSA Actually Is: A Polypeptide at the Center of Hormone Research

Prostate-specific antigen is not merely a cancer screening number. It is a 237-amino-acid serine protease,a polypeptide produced primarily by prostate epithelial cells and regulated by androgenic signaling. Because testosterone and dihydrotestosterone directly stimulate PSA gene transcription via androgen receptor binding, PSA functions as a sensitive downstream readout of androgen activity. This makes it indispensable in any study that manipulates the hormonal axis.

In the context of Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies, PSA occupies a unique position: it is itself a polypeptide, it responds to polypeptide hormones such as luteinizing hormone (LH) and follicle-stimulating hormone (FSH), and it serves as the primary efficacy biomarker in androgen deprivation therapy (ADT) and androgen receptor pathway inhibitor (ARPI) trials.

Key polypeptide hormones measured alongside PSA in standard research panels include:

  • LH and FSH, pituitary glycoprotein hormones that regulate gonadal testosterone output
  • Testosterone (total and free), the primary androgenic driver of PSA expression
  • Sex hormone-binding globulin (SHBG), a transport protein that modulates free testosterone availability
  • Growth hormone and IGF-1, relevant in systemic peptide research that intersects with prostate biology

How serm Pharmacology Connects to PSA Monitoring

How serm Pharmacology Connects to PSA Monitoring

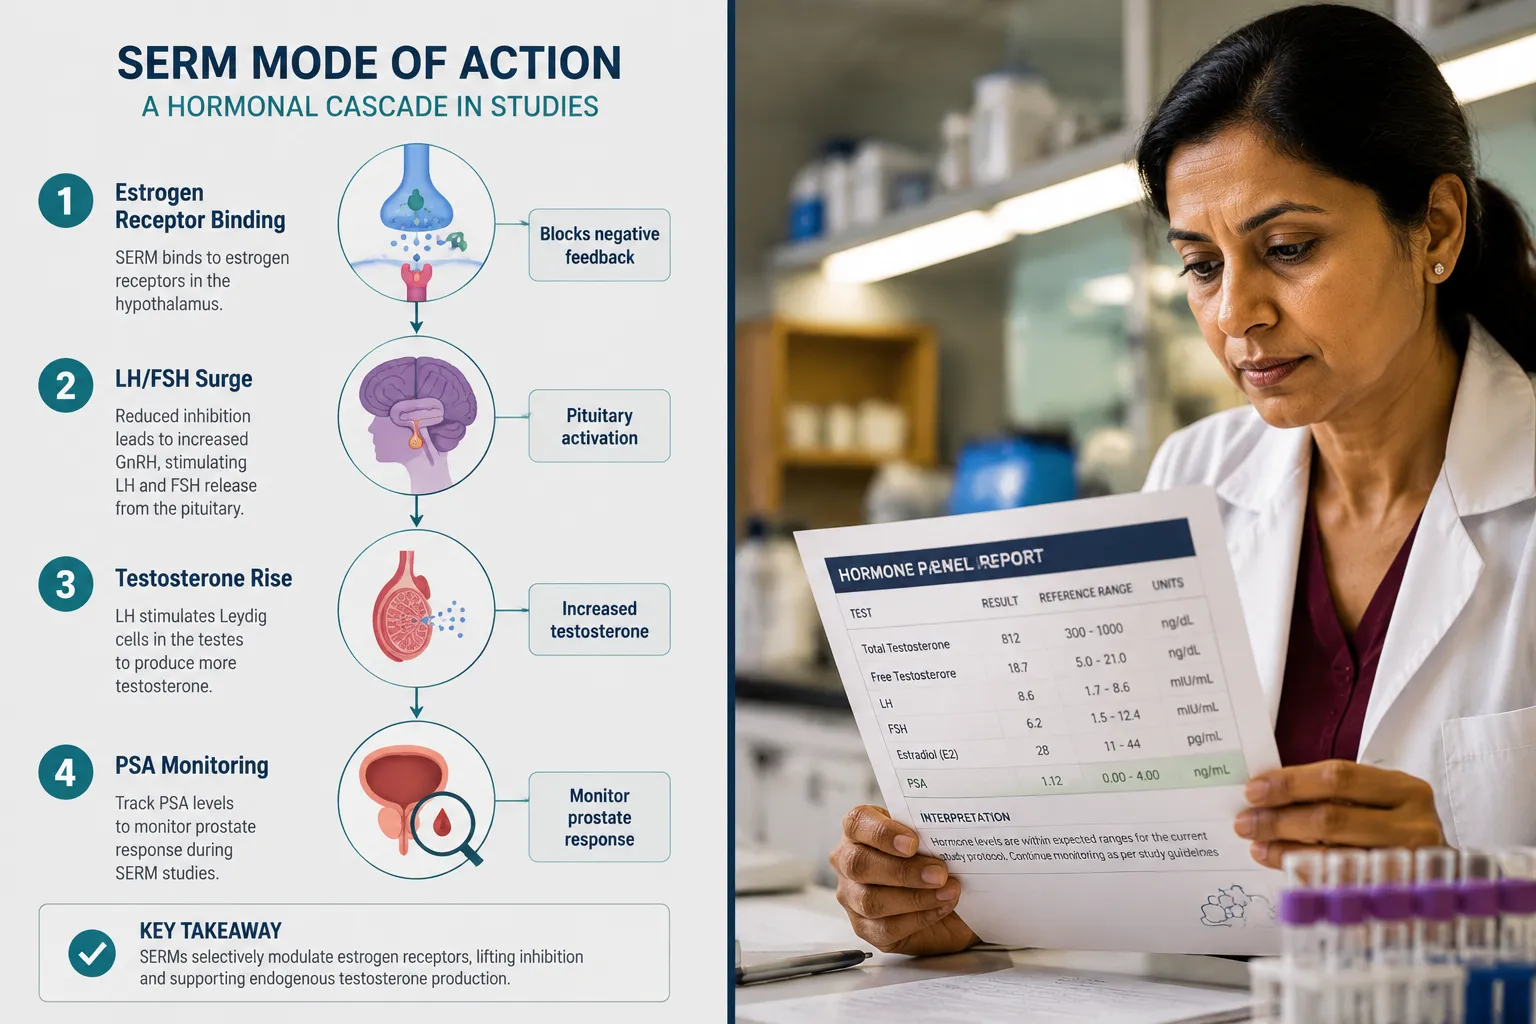
Selective estrogen receptor modulators (serms) such as enclomiphene, tamoxifen, and clomiphene block estrogen receptors in the hypothalamus and pituitary. This blockade removes negative feedback on GnRH pulsatility, causing a rise in LH and FSH, which then stimulates testicular testosterone production. Because PSA is androgen-sensitive, any intervention that raises testosterone carries the potential to shift PSA levels, a critical consideration in research design.

Understanding serm pharmacology is therefore inseparable from understanding PSA dynamics. Labs conducting serm research on male hypogonadism or testosterone restoration protocols routinely include PSA as a safety and efficacy endpoint precisely because of this hormonal cascade.

"In hormone and serm studies, PSA is not just a prostate cancer marker, it is a functional readout of androgenic activity across the entire hypothalamic-pituitary-gonadal axis."

A well-designed serm comparison study will typically measure:

Biomarker Role in Study
PSA (ng/mL) Primary safety and efficacy endpoint
Total testosterone Confirms androgenic response
LH and FSH Validates serm mechanism of action
Estradiol Monitors estrogenic rebound
SHBG Contextualizes free testosterone changes

The ARANOTE trial, which evaluated darolutamide combined with ADT, used undetectable PSA (below 0.2 ng/mL) as its key efficacy marker. Real-world cohort data confirm that PSA at six to twelve months of ADT plus ARPI predicts survival outcomes and guides decisions on treatment escalation or de-escalation.

What Research Labs Measure: The Full Panel in Hormone and serm Studies

What Research Labs Measure: The Full Panel in Hormone and serm Studies

The scope of Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies has expanded considerably in 2026. Beyond the classic PSA-plus-testosterone panel, modern translational trials incorporate several additional metrics.

Novel PSA Indices

The initial-to-nadir PSA ratio (I/N PSA) has emerged as an independent predictor of both treatment response and overall survival. Labs calculate this by dividing the baseline PSA by the lowest PSA achieved during therapy. A steep ratio signals robust androgen suppression and correlates with improved outcomes in ADT-treated cohorts.

PSA variability and repeat testing protocols have also received renewed attention. Screening analyses confirm that a single PSA draw carries meaningful biological variability, making serial measurements and standardized collection intervals essential for reliable research endpoints.

Integrating PSMA Metrics

Prostate-specific membrane antigen (PSMA) radioligand therapy trials such as the ENZA-p study now integrate both PSA and PSMA imaging metrics. PSMA is itself a transmembrane peptide, and its expression correlates with, but is not identical to, PSA levels. Labs running hormone-refractory disease studies must therefore treat PSA and PSMA as complementary rather than interchangeable endpoints.

Peptide Hormones in Growth Axis Research

Researchers exploring growth hormone secretagogues such as those studied in sermorelin, ipamorelin, and CJC-1295 protocols measure IGF-1 and growth hormone pulse amplitude alongside PSA when subjects are older males. This overlap reflects the broader principle that no single peptide or hormone acts in isolation. Translational research design increasingly demands multi-analyte panels that capture hormonal crosstalk.

For labs exploring mitochondria-targeted peptides, resources such as SS-31 mechanism and research highlight how oxidative stress markers can complement hormone panels in aging-related studies.

ADT-Sparing Strategies and PSA Thresholds

Emerging ADT-sparing research uses PSA as the primary marker for determining whether lifelong castration can be avoided. Guideline and cohort data now define specific PSA thresholds for initiating and timing ADT after local treatment relapse. The PSA-response-adapted radiation approach tested in the RANGER phase II trial exemplifies how a single polypeptide biomarker can drive individualized treatment algorithms.

Conclusion

The relationship between Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies is more integrated than most summaries suggest. PSA is simultaneously a polypeptide product, an androgen-axis readout, and a safety endpoint in serm and hormone research. Labs that treat it as a standalone number miss the broader hormonal narrative.

Actionable next steps for researchers and lab professionals:

  1. Adopt serial PSA measurement protocols with standardized intervals rather than relying on single-draw values.
  2. Pair PSA with LH, FSH, total testosterone, and SHBG to capture the full hormonal axis in serm and ADT studies.
  3. Calculate the I/N PSA ratio as a supplementary predictor of response and survival in ADT-treated cohorts.
  4. Integrate PSMA imaging data in hormone-refractory protocols to avoid over-relying on PSA alone.
  5. Review current serm research and translational research design frameworks to ensure multi-analyte panels reflect 2026 guideline updates.

Staying current with how PSA interacts with the broader peptide and polypeptide hormone landscape is no longer optional, it is the baseline standard for credible hormone and serm research design.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/prostate-specific-antigen-peptides-and-polypeptide-hormones-what-research-labs-m.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-03 13:05:362026-09-03 13:05:36Prostate Specific Antigen, Peptides, and Polypeptide Hormones: What Research Labs Measure in Hormone and serm Studies

Tag Archive for: prostate-specific antigen

Prostate-Specific Antigen and Peptide Research: Why PSA Appears in Hormone, Prostate, and Biomarker Content Strategy

Prostate-Specific Antigen and Peptide Research: Why PSA Appears in Hormone, Prostate, and Biomarker Content Strategy

June 16, 2026/0 Comments/by Pure Tested

Fewer than 5% of men under 40 have elevated PSA levels — yet the term "PSA" appears in an enormous share of research content spanning hormones, peptides, and biomarker diagnostics. That overlap is not accidental. Understanding Prostate-Specific Antigen and Peptide Research: Why PSA Appears in Hormone, Prostate, and Biomarker Content Strategy requires a clear look at what PSA actually is, how peptide science intersects with its measurement and targeting, and why content covering endocrine health, prostate biology, and research peptides so often converges on this single biomarker.

Key Takeaways

  • PSA is a serine protease enzyme — a peptide-cleaving protein — making it directly relevant to peptide research frameworks.
  • Hormone regulation, particularly androgen signaling, controls PSA expression, linking it firmly to endocrine content.
  • Newer biomarkers such as GRPR and modified PSA assays are expanding the diagnostic landscape beyond standard PSA testing.
  • Peptide-based prodrugs and imaging agents that exploit PSA's enzymatic activity represent an active research frontier.
  • Content covering prostate health, biomarker science, or research peptides will naturally intersect with PSA as a reference point.

Key Takeaways

What PSA Actually Is — And Why Peptide Research Overlaps

PSA, or Prostate-Specific Antigen, is a serine protease enzyme produced primarily by prostate epithelial cells. Its biological job is to liquefy seminal proteins — it does this by cleaving peptide bonds. That single function places PSA squarely within peptide biochemistry, not just urology.

Because PSA belongs to the human kallikrein family (specifically KLK3), it shares structural and functional characteristics with other kallikrein peptidases. Researchers studying peptide substrates, enzyme kinetics, or protease-activated drug delivery systems encounter PSA as a natural reference point.

"PSA is not merely a cancer screening number — it is an active peptide-processing enzyme whose substrate specificity has been mapped and exploited for targeted drug design."

This enzymatic identity explains why Prostate-Specific Antigen and Peptide Research topics appear together so frequently. Researchers have used phage display screening to identify peptides that bind specifically to PSA-low prostate cancer cells — work that is directly relevant to castration-resistant prostate cancer targeting. Separately, peptide-based inhibitors of PSA have been optimized as targeted imaging agents, and PSA-cleavable peptide substrates have been screened to develop albumin-binding anticancer prodrugs.

For researchers already exploring peptide mechanisms and research applications, PSA represents a well-characterized enzymatic model with translational implications.


What PSA Actually Is — And Why Peptide Research Overlaps

Hormone Regulation, Androgen Signaling, and PSA Expression

PSA expression is tightly regulated by androgen hormones, particularly testosterone and dihydrotestosterone (DHT), acting through androgen receptors. This hormonal control is why PSA levels drop when androgen deprivation therapy is used in prostate cancer management.

This connection to hormone signaling is a key reason Prostate-Specific Antigen and Peptide Research: Why PSA Appears in Hormone, Prostate, and Biomarker Content Strategy is such a relevant framework. Any content platform covering endocrine health, growth hormone peptides, or hormonal biomarkers will encounter PSA as a downstream androgen-regulated marker.

Key hormonal relationships involving PSA:

Factor Effect on PSA
Testosterone / DHT Upregulates PSA gene transcription
Androgen deprivation Suppresses PSA production
Estrogen (high levels) May reduce PSA expression
Inflammation Can elevate PSA independent of cancer

Research exploring gonadorelin and GnRH pulsatility is directly upstream of androgen signaling — and therefore upstream of PSA regulation. Similarly, content covering GLP-1 peptide research concepts or NAD research and metabolic peptides sits within the same broad endocrine-metabolic ecosystem that PSA inhabits.


Hormone Regulation, Androgen Signaling, and PSA Expression

Biomarker Evolution: Beyond Standard PSA Testing

Standard PSA immunoassays have well-documented limitations in specificity. Recent research has moved in two important directions: refining PSA measurement and identifying companion biomarkers.

On the measurement side, mass spectrometry-based approaches now allow direct quantification of PSA-derived peptides, offering a path to harmonize inconsistencies across different immunoassay platforms. A first-in-class antibody targeting alpha-1,6-fucosylated PSA has also been developed to improve diagnostic specificity — a glycoproteomic refinement that sits at the intersection of peptide chemistry and clinical diagnostics.

On the companion biomarker side, Gastrin-Releasing Peptide Receptor (GRPR) has emerged as a significant parallel target. Studies evaluating GRPR alongside PSMA and Neurotensin Receptor 1 suggest that multi-receptor panels improve prostate cancer stratification compared to PSA alone. Research published in 2026 continues to explore theranostic targets beyond PSMA, reflecting a broader shift toward peptide-receptor-based diagnostics.

Ultrasensitive biosensors using octabranched peptide scaffolds and silver nanoparticles now enable PSA quantification at extremely low concentrations in human serum — a development with direct implications for early detection research.

For those tracking quality testing protocols in peptide research, this evolution in biomarker measurement methodology is directly applicable. Researchers interested in epithalon and aging biomarkers or GHK-Cu longevity research themes will recognize the same pattern: single-marker approaches give way to multi-pathway, peptide-informed frameworks.

PSA-Targeted Prodrugs and Peptide Delivery

One of the most compelling intersections between Prostate-Specific Antigen and Peptide Research: Why PSA Appears in Hormone, Prostate, and Biomarker Content Strategy is the field of PSA-activated prodrugs. Because PSA cleaves specific peptide sequences, researchers have engineered prodrugs that remain inactive until PSA cleaves a peptide linker — releasing the therapeutic payload selectively at the tumor site. Disulfide-constrained peptides that bind to the extracellular portion of PSMA (Prostate-Specific Membrane Antigen, a related but distinct target) have also been identified, further expanding the peptide-targeting toolkit.


Conclusion

PSA occupies a unique position in biomedical research — it is simultaneously a clinical screening marker, an androgen-regulated gene product, and an active peptide-cleaving enzyme. That triple identity explains precisely why Prostate-Specific Antigen and Peptide Research: Why PSA Appears in Hormone, Prostate, and Biomarker Content Strategy is a legitimate and valuable content framework, not keyword overlap.

Actionable next steps for researchers and content strategists:

  • Treat PSA as a peptide biochemistry topic, not just a urology metric, when building research content architecture.
  • Explore companion biomarkers (GRPR, Neurotensin Receptor 1) alongside PSA for a more complete prostate health research picture.
  • Follow developments in PSA-cleavable prodrug design as a model for targeted peptide delivery systems.
  • Use PSA's hormonal regulation as a bridge between endocrine peptide content and prostate health discussions.

Readers exploring broader peptide research themes can find relevant context in MOTS-C mitochondrial peptide research and IPA muscle and fat research themes — both of which operate within the same endocrine-metabolic landscape that PSA monitoring informs.

https://www.puretestedpeptides.com/wp-content/uploads/2026/06/Prostate-Specific-Antigen-and-Peptide-Research-Why-PSA-Appears-in-Hormone-Prostate-and-Biomarker-Content-Strategy.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-06-16 13:05:072026-07-20 15:02:58Prostate-Specific Antigen and Peptide Research: Why PSA Appears in Hormone, Prostate, and Biomarker Content Strategy
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top