

Complement-Dependent Cytotoxicity and Peptide Research Safety: What Labs Track When Using GLP-3, BPC-157, and Novel Peptides
Fewer than 15% of novel peptide candidates that enter preclinical testing carry a structured complement-activation safety panel, yet complement-dependent cytotoxicity (CDC) remains one of the most consequential immune mechanisms that can derail a promising research compound. As labs in 2026 work with research-use peptides ranging from GLP-3 analogs and BPC-157 to TB-500 and macrocyclic probes, understanding complement-dependent cytotoxicity and peptide research safety is no longer optional background knowledge. It is a core part of responsible experimental design.
Key Takeaways
- Complement-dependent cytotoxicity is a well-defined immune effector mechanism involving C1 activation, C3b deposition, and membrane-attack complex formation that can affect peptide therapeutics, especially those conjugated to antibody scaffolds.
- Different CDC assay formats, dye-based, metabolic, and label-free MALDI, yield materially different potency estimates, so labs must document assay type alongside results.
- BPC-157 has shown an unusually clean preclinical toxicology profile through 2026, but the absence of robust human immunogenicity and CDC data means structured safety panels are still recommended.
- GLP-3 as a named research peptide class lacks published CDC-specific safety data; labs are currently extrapolating from biologic-drug safety paradigms.
- Regulatory expectations for integrated CDC and immunogenicity profiling in early-phase peptide trials are rising, making proactive safety tracking a competitive and compliance advantage.
How Complement-Dependent Cytotoxicity Works, and Why Peptide Labs Must Care
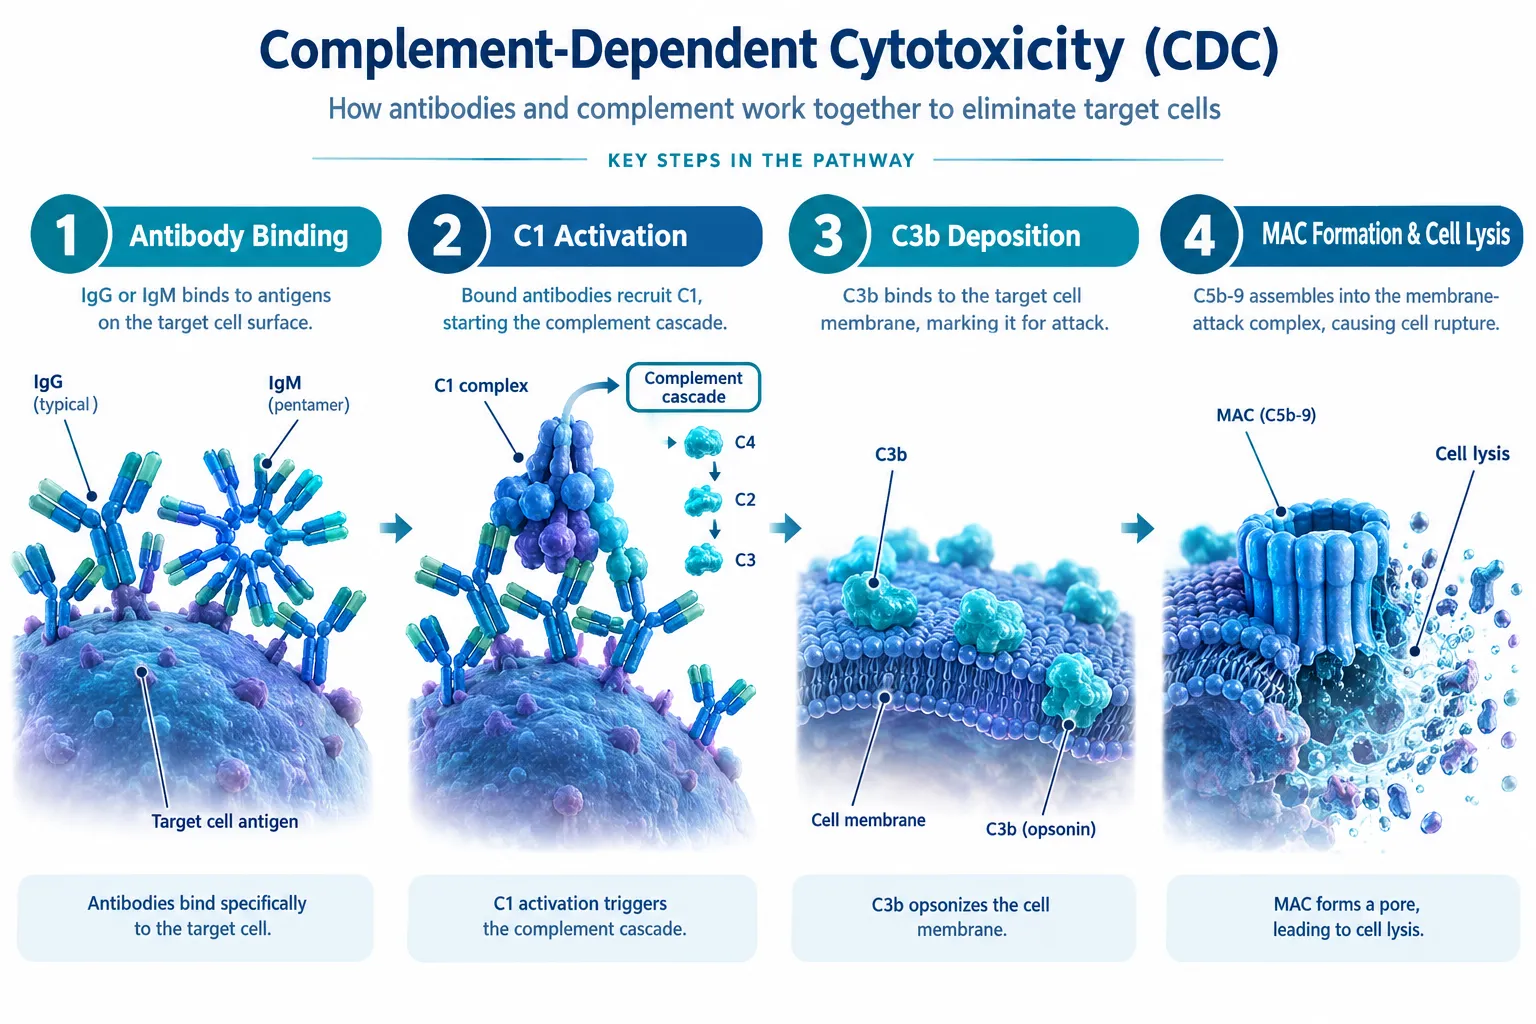
The complement system is an ancient branch of innate immunity. When IgG or IgM antibodies bind a target cell surface, they can recruit the C1 complex, triggering a cascade that deposits C3b on the membrane and ultimately assembles the membrane-attack complex (MAC). The MAC punches pores through the lipid bilayer, causing osmotic cell lysis, that process is complement-dependent cytotoxicity.
For classic monoclonal antibody drugs, CDC is a desired or at least well-characterized effect. For novel peptides, the picture is more complicated. Peptides that are conjugated to antibody scaffolds, that modulate complement regulatory proteins such as CD59, or that alter upstream C1 recognition can all engage CDC pathways in ways that are not always predicted from amino acid sequence alone.
Why this matters for peptide research safety:
- Peptide, antibody conjugates designed to enhance anti-CD20 CDC activity have demonstrated complement-mediated killing that is largely independent of NK cells, meaning the lysis mechanism is driven specifically by the complement arm.
- Macrocyclic peptide probes targeting CD59, a key complement inhibitor on human cells, can sensitize non-target tissues to lysis if systemic distribution is not carefully controlled.
- Complement-modulating peptides like the cL3 class can inhibit lysis without blocking C1 binding, creating a scenario where upstream complement recognition remains intact while downstream lysis is suppressed. Labs tracking only cell viability may miss this nuance entirely.
"A peptide that looks inert in a standard cytotoxicity screen can still be actively reshaping complement regulation in ways that only a targeted CDC panel will reveal."
For researchers exploring how peptides differ from classic small-molecule drugs in lab design, this mechanistic distinction is particularly important to internalize early.
Assay Selection: The Core of Complement-Dependent Cytotoxicity and Peptide Research Safety Tracking
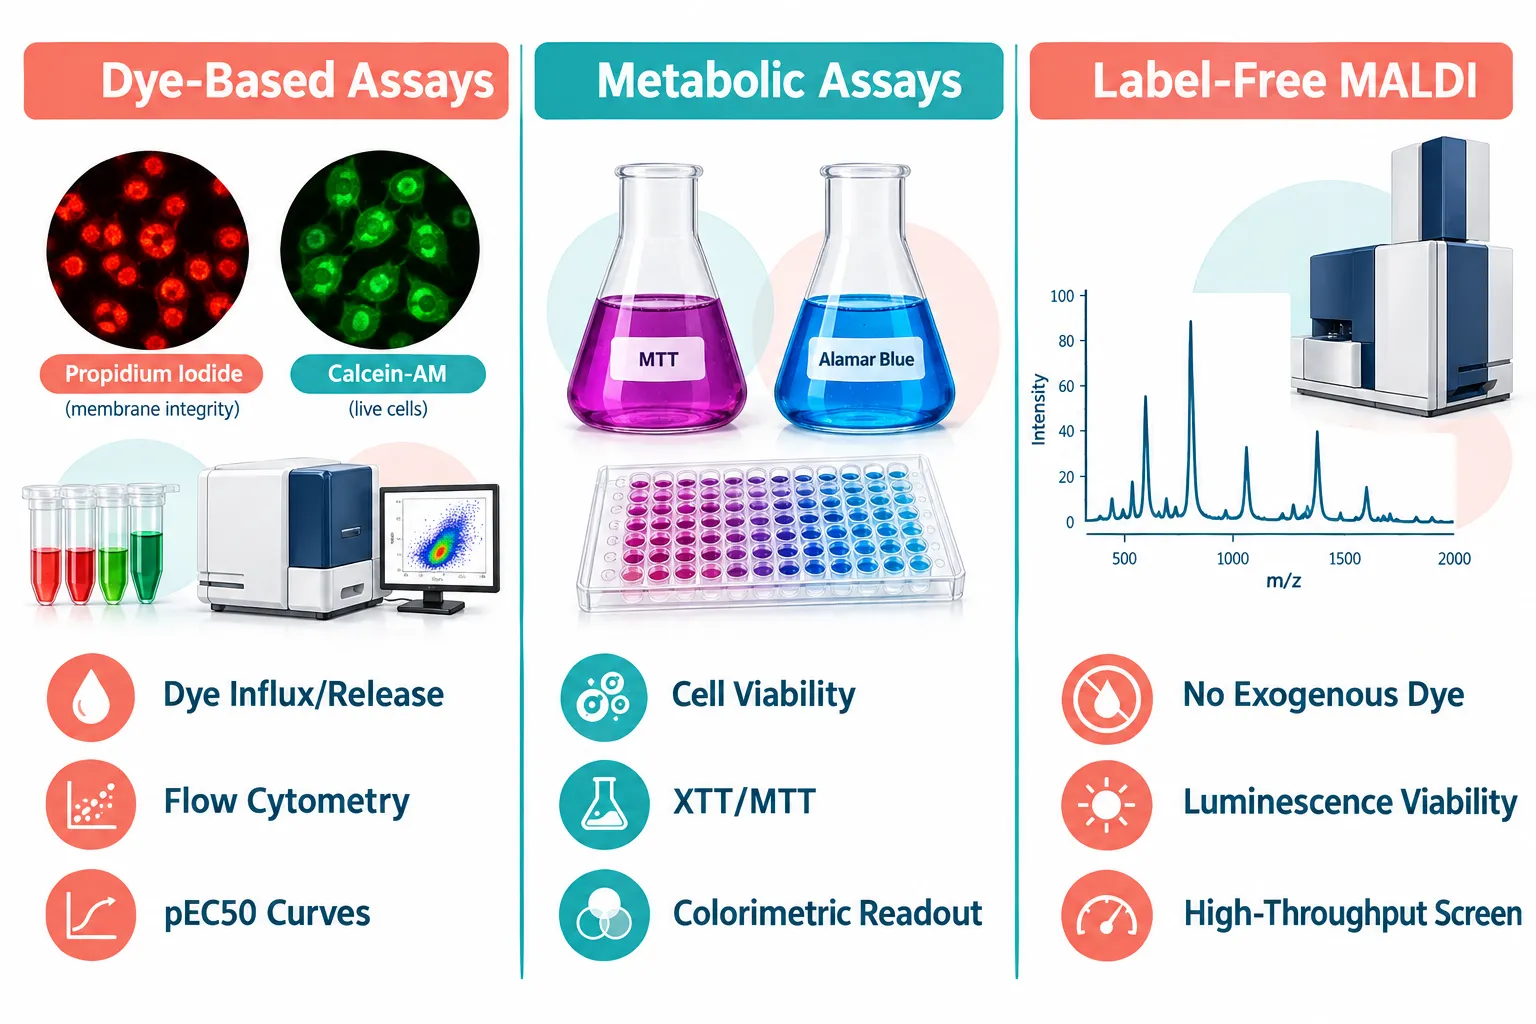
Not all CDC assays produce the same numbers, and in 2026 that is no longer a minor methodological footnote, it is a recognized source of cross-study variability that regulators and reviewers are beginning to scrutinize.
Four Assay Formats Labs Currently Use
| Assay Type | Readout | Key Advantage | Known Limitation |
|---|---|---|---|
| Dye influx (propidium iodide) | % PI-positive dead cells | Flow-cytometry compatible, precise pEC50 | Dye can interfere with some peptide structures |
| Dye release (calcein-AM) | Fluorescence in supernatant | Sensitive, widely validated | Background release in long incubations |
| Metabolic (MTT, XTT, Alamar Blue) | Cell metabolic activity | Plate-reader compatible, high throughput | Indirect viability; can miss rapid lysis events |
| Label-free MALDI | Direct cell-lysis via mass spec | No dye interference, richer mechanistic data | Higher equipment cost, emerging adoption |
A 2024 label-free whole-cell MALDI mass-spectrometry CDC bioassay demonstrated that complement-induced lysis can be monitored without exogenous dyes, using luminescence-based viability and concentration-response analysis to derive pEC50 values. This approach is expected to gain traction for high-throughput peptide screening precisely because it eliminates the assay-interference problem.
What labs must document for every CDC experiment:
- Assay format and detection method
- Complement source (human serum, rabbit serum, or recombinant components) and lot number
- Incubation time and temperature
- Target cell line and passage number
- Viability readout normalization method
Standardizing these parameters is especially critical when comparing results across sites or when building a regulatory submission package for a novel peptide candidate.
BPC-157, GLP-3, and Novel Peptides: What the Safety Data Actually Show

Complement-dependent cytotoxicity and peptide research safety considerations differ substantially depending on the specific compound class. The three categories most active in research labs in 2026, BPC-157, GLP-3 analogs, and novel immunomodulatory peptides, each present a distinct safety evidence landscape.
BPC-157: Strong Preclinical Record, Thin Human Data
BPC-157 is a 15-amino-acid peptide derived from human gastric juice protein. Its preclinical toxicology profile is, by peptide-drug standards, unusually clean:
- No lethal dose has been identified in mice, rats, rabbits, or dogs across a wide dose range, including limit-toxicity studies up to approximately 2 g/kg in rodents.
- No teratogenic, genotoxic, or anaphylactic effects have been detected.
- Mild local irritation has been noted in some multi-dose studies, but no dose-limiting organ toxicity.
For researchers interested in BPC-157's broader mechanisms, the article on mesenchymal stem cells and peptide-based modulators including BPC-157 provides useful context on how this peptide is applied in regenerative research models.
Despite this record, the human data gap is significant. Available clinical evidence consists largely of small pilot studies without robust statistical power. Regulatory-oriented analyses published in 2026 argue that adoption into clinical practice is not yet scientifically justified and recommend that future phase I/II trials include:
- Anti-peptide antibody assays (immunogenicity)
- Complement activation panels (C3/C5 activation, CDC assays)
- Cytokine profiling
- Standard organ-toxicity monitoring (clinical chemistry, histopathology)
GLP-3 Analogs: A Data Gap That Labs Must Acknowledge
As of 2026, there is no publicly indexed clinical or preclinical dataset specifically focused on CDC safety profiling for "GLP-3" peptides. Unlike GLP-1 analogs, which have extensive immunogenicity and safety datasets from large trials, GLP-3 as a named research peptide class remains largely undefined in major pharmacological databases.
Labs working with novel incretin-mimetic or metabolic peptides in this space are currently extrapolating from biologic-drug safety paradigms. This means tracking:
- Immunogenicity markers (anti-drug antibody formation)
- Complement activation markers (C3b deposition, complement consumption assays)
- Liver and cardiac safety labs
- Metabolic endpoints relevant to the compound's mechanism
For broader context on how triple-agonist metabolic peptides like retatrutide are reshaping research design, see the analysis of GLP-3 retatrutide in phase 3 trials and triple agonism.
Novel Immunomodulatory Peptides: The Highest CDC Risk Category
Peptides that directly interact with complement regulatory proteins carry the most direct CDC risk. Labs working with CD59-targeting macrocycles, complement-enhancing antibody conjugates, or cL3-class inhibitors should track:
- Hemolysis assays (direct red blood cell lysis)
- C3b deposition on target and non-target cells
- Complement consumption (total hemolytic complement, CH50)
- Cell-viability curves with pEC50 derivation
- Comparative lysis vs. unconjugated antibody controls
The polypeptide peptides and drug mechanisms resource offers additional pharmacology context relevant to understanding how these mechanisms translate across compound classes.
Building a Practical CDC Safety Tracking Protocol for Peptide Research
Translating the above into a usable lab workflow requires a tiered approach. Not every peptide warrants the same depth of CDC profiling, but every novel peptide warrants at least a screening-level assessment.
Tier 1, Screening (all novel peptides):
- Standard cell-viability assay in the presence of normal human serum
- Hemolysis assay with human red blood cells
- Complement consumption check (CH50 before and after peptide exposure)
Tier 2, Characterization (peptides with immune-modulating or antibody-recruiting properties):
- Flow-cytometry CDC assay with pEC50 derivation
- C3b deposition by ELISA or flow
- Anti-peptide antibody ELISA (immunogenicity screen)
- Cytokine panel (IL-6, TNF-alpha, C-reactive protein)
Tier 3, Regulatory-grade profiling (IND-enabling or first-in-human candidates):
- Label-free MALDI CDC bioassay for mechanistic depth
- Full complement activation panel (C3, C4, C5a, sC5b-9)
- Repeat-dose immunogenicity with titer tracking
- Integrated organ-toxicity histopathology
Labs interested in how administration route affects immune exposure should also review the nasal spray peptides bioavailability and research design considerations resource, as mucosal delivery can alter complement exposure profiles compared to systemic injection.
For metabolic peptide research specifically, the comparison of tesofensine vs GLP-3 retatrutide appetite-modulating pathways illustrates how different mechanistic classes require different safety endpoint selections.
Conclusion
Complement-dependent cytotoxicity and peptide research safety represent a rapidly maturing area of laboratory practice. The core message for 2026 is straightforward: the assay format matters, the peptide class matters, and the absence of published CDC data for a compound is not the same as the absence of CDC risk.
Actionable next steps for research labs:
- Audit current peptide safety protocols to confirm whether a CDC screening tier is included, even at the basic hemolysis and CH50 level.
- Document assay format, complement source, and incubation conditions for every CDC-related experiment to enable cross-study comparison.
- For BPC-157 and similar investigational peptides, add immunogenicity and complement-activation panels to any study design that will generate data intended for publication or regulatory review.
- Treat the GLP-3 CDC data gap as an active research priority rather than a reason to defer safety tracking.
- Follow the trajectory of label-free MALDI CDC assays and advanced flow-cytometry methods, as these are likely to become standard expectations in regulatory submissions within the next few years.
Rigorous safety tracking does not slow peptide research, it protects the investment in it.


Leave a Reply
Want to join the discussion?Feel free to contribute!