Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: glp-3 peptides

Atorvastatin, LDL Cholesterol, and Metabolic Peptides: Where MOTS-c, 5-Amino-1MQ, and GLP-3 Retatrutide Fit in Lipid Research

Atorvastatin, LDL Cholesterol, and Metabolic Peptides: Where MOTS-c, 5-Amino-1MQ, and GLP-3 Retatrutide Fit in Lipid Research

September 20, 2026/0 Comments/in Uncategorized/by

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'Atorvastatin, LDL Cholesterol' in crisp white modern sans-serif on a deep navy semi-transparent overlay panel, centered with 8% safe margins from every edge, no character touches the edge, two balanced lines. Background: high-resolution editorial medical illustration of a cross-section of a human artery with visible LDL cholesterol plaques, surrounded by floating molecular structures of statin compounds and peptide chains in teal and gold tones, clinical yet visually striking, magazine-cover aesthetic, sharp editorial lighting, professional 2-color palette of navy and teal with white typography.","content":["Annotated mechanism-of-action diagram (1536×1024 landscape) showing atorvastatin's HMG-CoA reductase inhibition pathway in a clean white-background infographic style. Four labeled stages arranged left to right: Stage 1 callout 'HMG-CoA Reductase Blocked' pointing to liver cell diagram, Stage 2 callout 'LDL Receptors Upregulated' with arrow to hepatocyte surface, Stage 3 callout 'LDL Cleared from Blood' showing artery cross-section, Stage 4 callout 'Target: <55 mg/dL ASCVD' with a bold threshold bar. Thin callout lines, teal-and-navy palette, numbered stages, editorial medical-guide polish, no pricing or dollar amounts.","Three-panel side-by-side comparison infographic (1536×1024 landscape) contrasting retatrutide, MOTS-c, and 5-Amino-1MQ as metabolic research agents. Left panel heading 'Retatrutide GLP-1/GIP/Glucagon' with bullet labels: Triple receptor agonist, LDL down ~15-20 percent, TG down ~40 mg/dL, Phase 3 trials. Center panel heading 'MOTS-c Mitochondrial Peptide' with bullet labels: NAD+ regulation, AMPK activation, Lipid oxidation, Preclinical stage. Right panel heading '5-Amino-1MQ NNMT Inhibitor' with bullet labels: NAD+ preservation, Lipogenesis suppressed, Fat oxidation shift, Animal models only. Clean white background, warm amber and teal accent colors, thin dividing lines, editorial infographic polish, callout lines to molecular icons per panel.","Split-screen editorial landscape image (1536×1024) illustrating layered cardiometabolic therapy concept. Left half: warm-lit clinical laboratory bench with statin pill bottles, a cholesterol panel blood report showing LDL values, and a molecular model of atorvastatin in amber studio lighting. Right half: cool-toned scientific research setting with peptide vials labeled MOTS-c and retatrutide, a digital screen showing triglyceride and metabolic pathway data, blue-white laboratory lighting. A bold center divider line with short label 'Established vs Investigational' separating the two halves. High-contrast magazine composition, deep focus, editorial quality."]
Professional landscape hero image () with a reading "Atorvastatin, LDL Cholesterol". CRITICAL TYPOGRAPHY RULES: render the

Cardiovascular disease remains the leading cause of death globally, yet only about half of high-risk patients reach their LDL-cholesterol targets even with statin therapy. That gap has driven intense research into metabolic peptides, molecules that act on mitochondrial signaling, NAD+ biology, and incretin receptors, as potential complements to classic lipid-lowering drugs. Understanding atorvastatin, LDL cholesterol, and metabolic peptides: where MOTS-c, 5-Amino-1MQ, and GLP-3 Retatrutide fit in lipid research requires a clear look at what each agent does, how the mechanisms compare, and what the current evidence actually supports.

Key Takeaways

  • Atorvastatin remains the primary pharmacological tool for reaching stringent LDL-C targets, with high-intensity dosing producing LDL reductions of 41-61%.
  • The 2026 ACC/AHA dyslipidemia guidelines set explicit LDL-C thresholds as low as less than 55 mg/dL for very-high-risk ASCVD patients.
  • Retatrutide, a triple receptor agonist targeting GLP-1, GIP, and glucagon pathways, shows meaningful lipid improvements in clinical trials but remains investigational with no regulatory approval as of 2026.
  • MOTS-c and 5-Amino-1MQ operate through mitochondrial and NAD+ pathways that influence lipid metabolism, but both remain in preclinical research stages.
  • Expert analysis increasingly frames future lipid management as layered therapy: statins for LDL targets plus metabolic peptides for residual cardiometabolic risk.

How Atorvastatin Shapes LDL-C Management in 2026

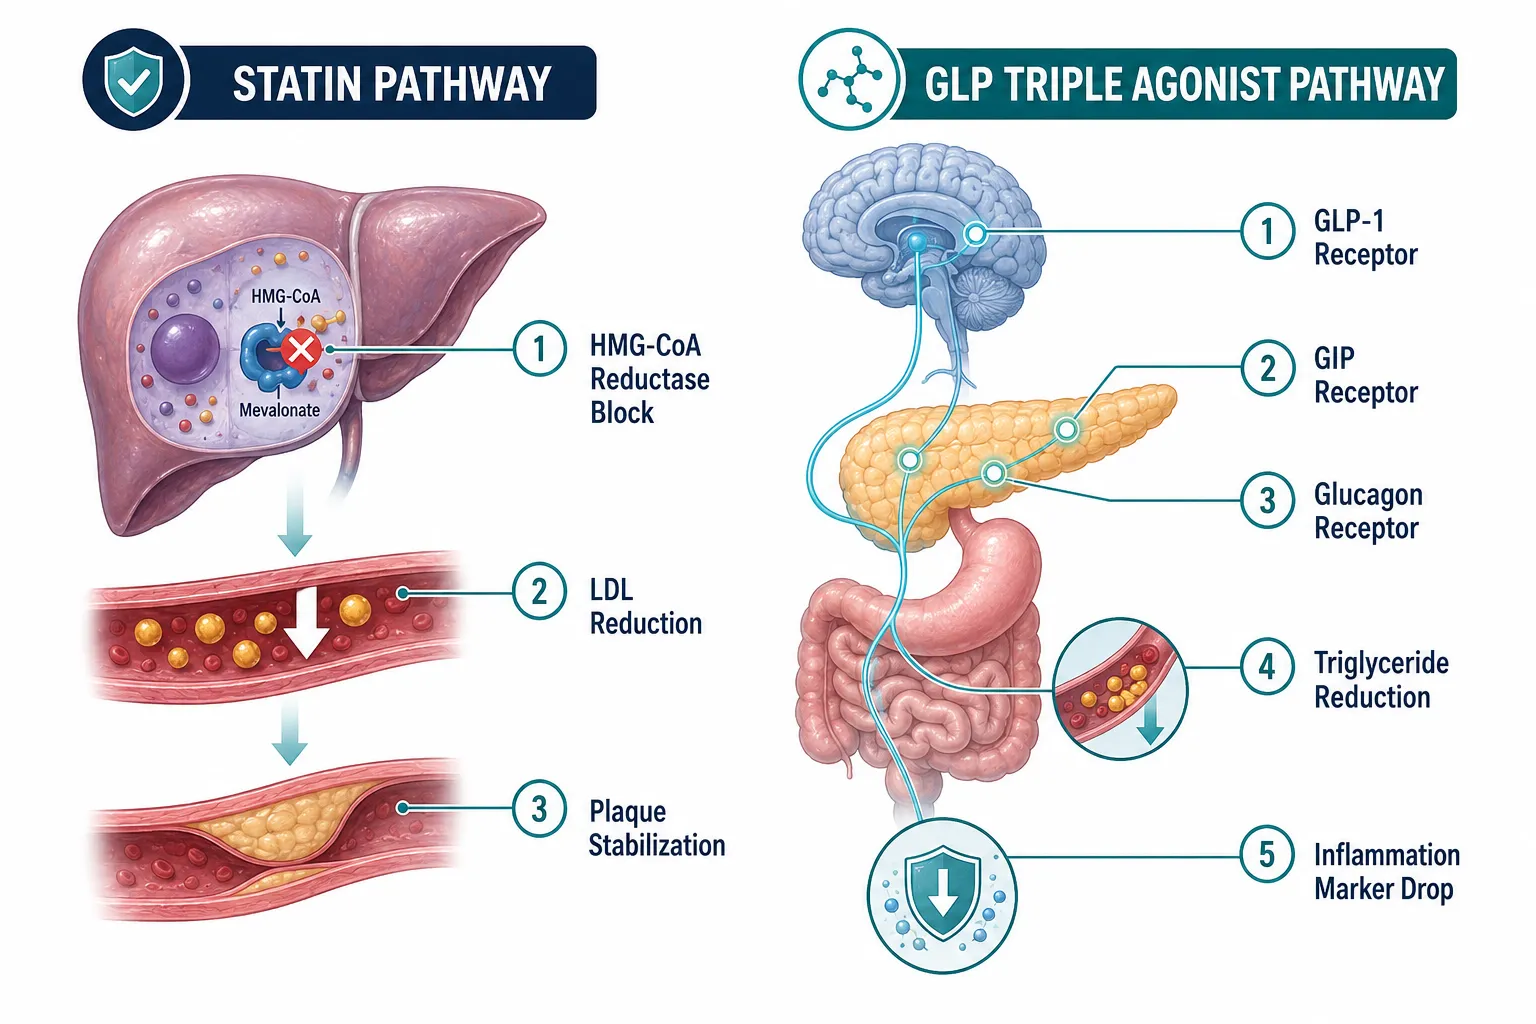
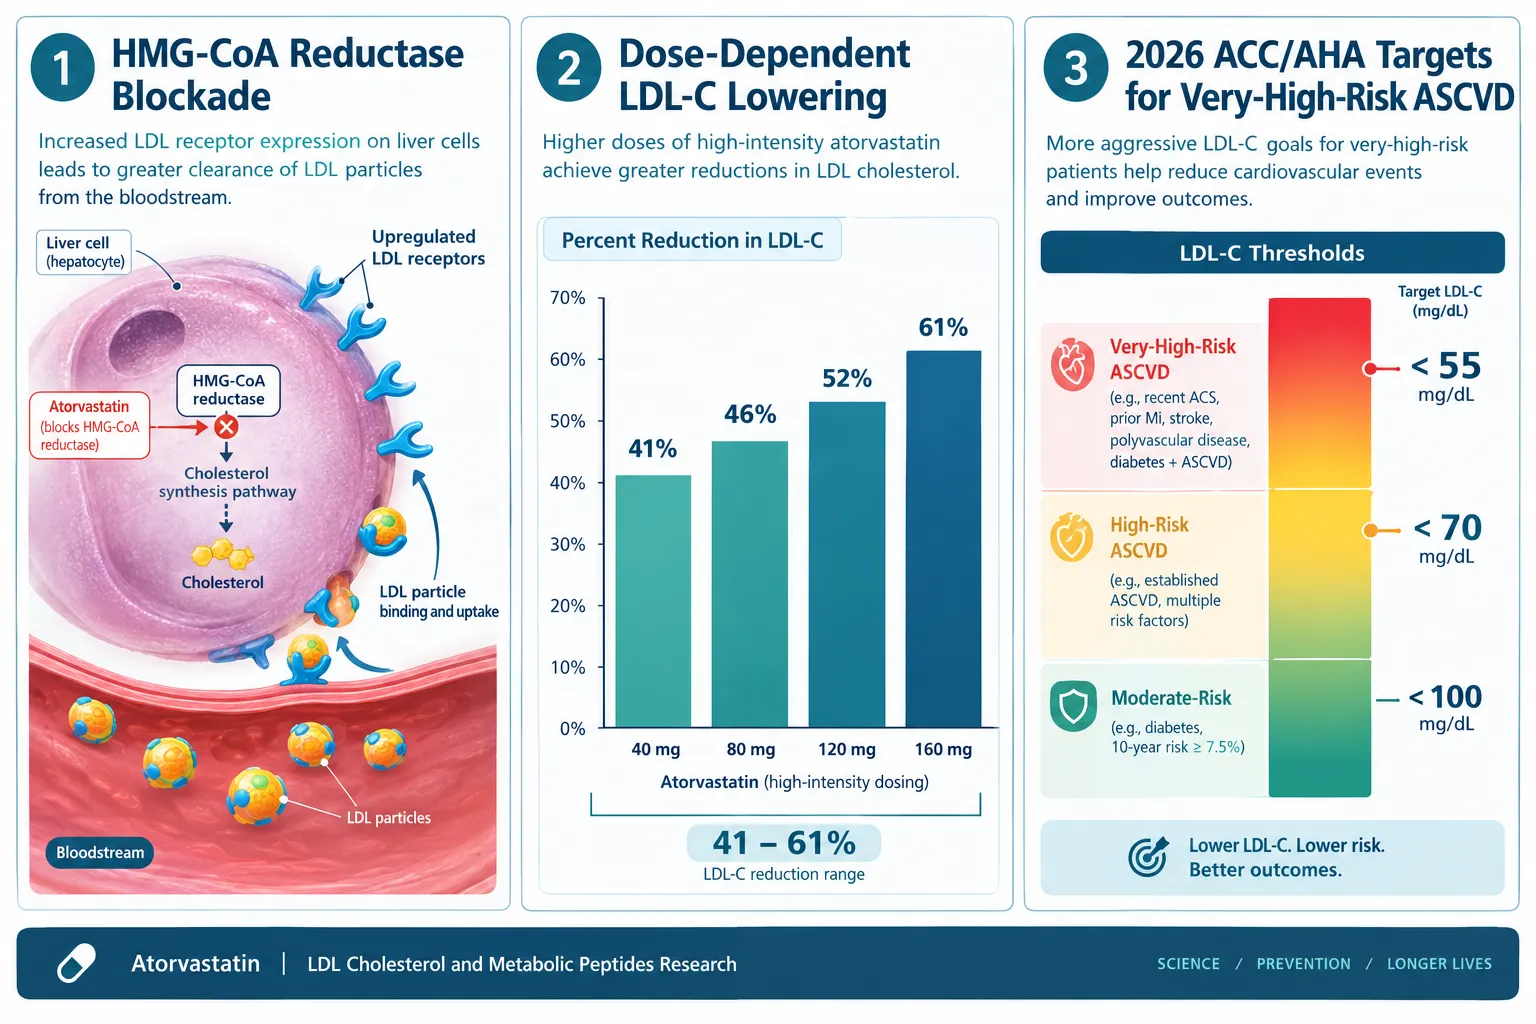
Atorvastatin works by blocking HMG-CoA reductase, the rate-limiting enzyme in hepatic cholesterol synthesis. When the liver produces less cholesterol internally, it upregulates LDL receptors on its surface, pulling more LDL particles out of circulation. The result is a dose-dependent and clinically significant reduction in atherogenic lipoproteins.
How Atorvastatin Shapes LDL-C Management in 2026

Dose, response data are well established. Depending on the dose and the patient's baseline risk profile, atorvastatin produces:

Lipid Marker Typical Reduction Range
Total Cholesterol 30-46%
LDL-C 41-61%
Triglycerides 14-33%
HDL-C Modest increase

The 2026 ACC/AHA multisociety dyslipidemia guideline has reintroduced explicit numeric LDL-C targets for the first time in over a decade. Very-high-risk ASCVD patients now have a target of less than 55 mg/dL, high-risk patients less than 70 mg/dL, and borderline-to-intermediate risk patients less than 100 mg/dL. High-intensity statins like atorvastatin are confirmed as the primary agents to reach these thresholds.

The core limitation: statins address LDL-C powerfully but leave residual risk from elevated triglycerides, visceral adiposity, insulin resistance, and inflammation. This is precisely where metabolic peptide research becomes relevant.

Retatrutide and GLP-Class Peptides: Lipid Effects Beyond Weight Loss

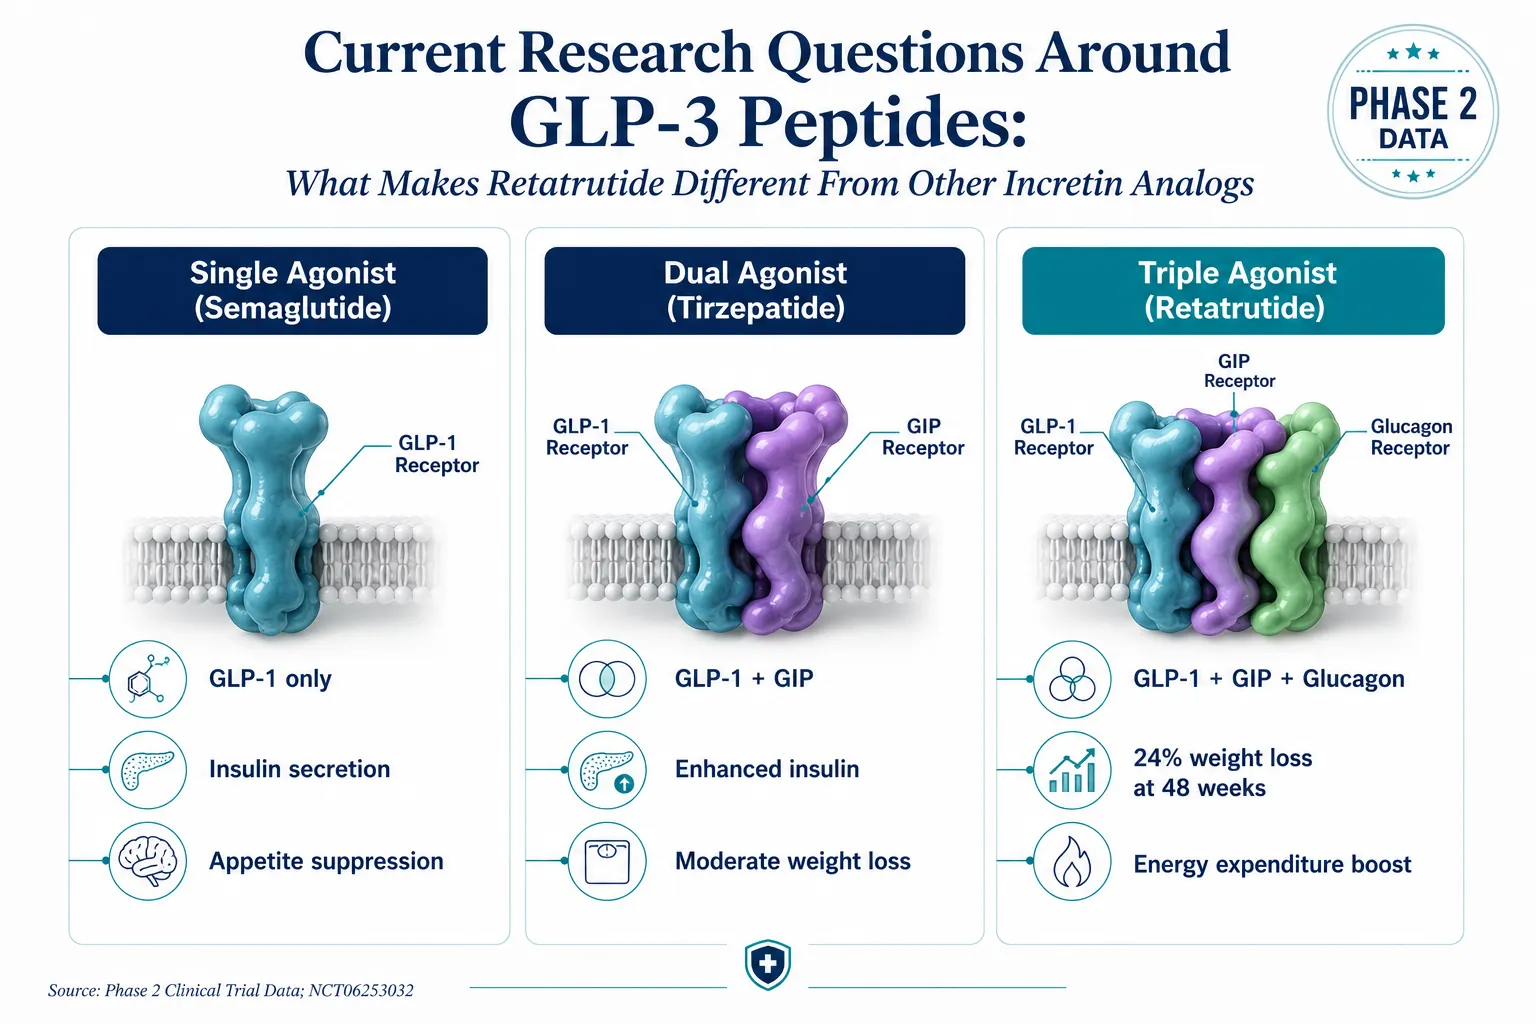
Retatrutide is a first-in-class investigational triple receptor agonist that activates GLP-1, GIP, and glucagon receptors simultaneously. While most public attention has focused on its dramatic weight loss results, its lipid effects are clinically noteworthy in their own right.

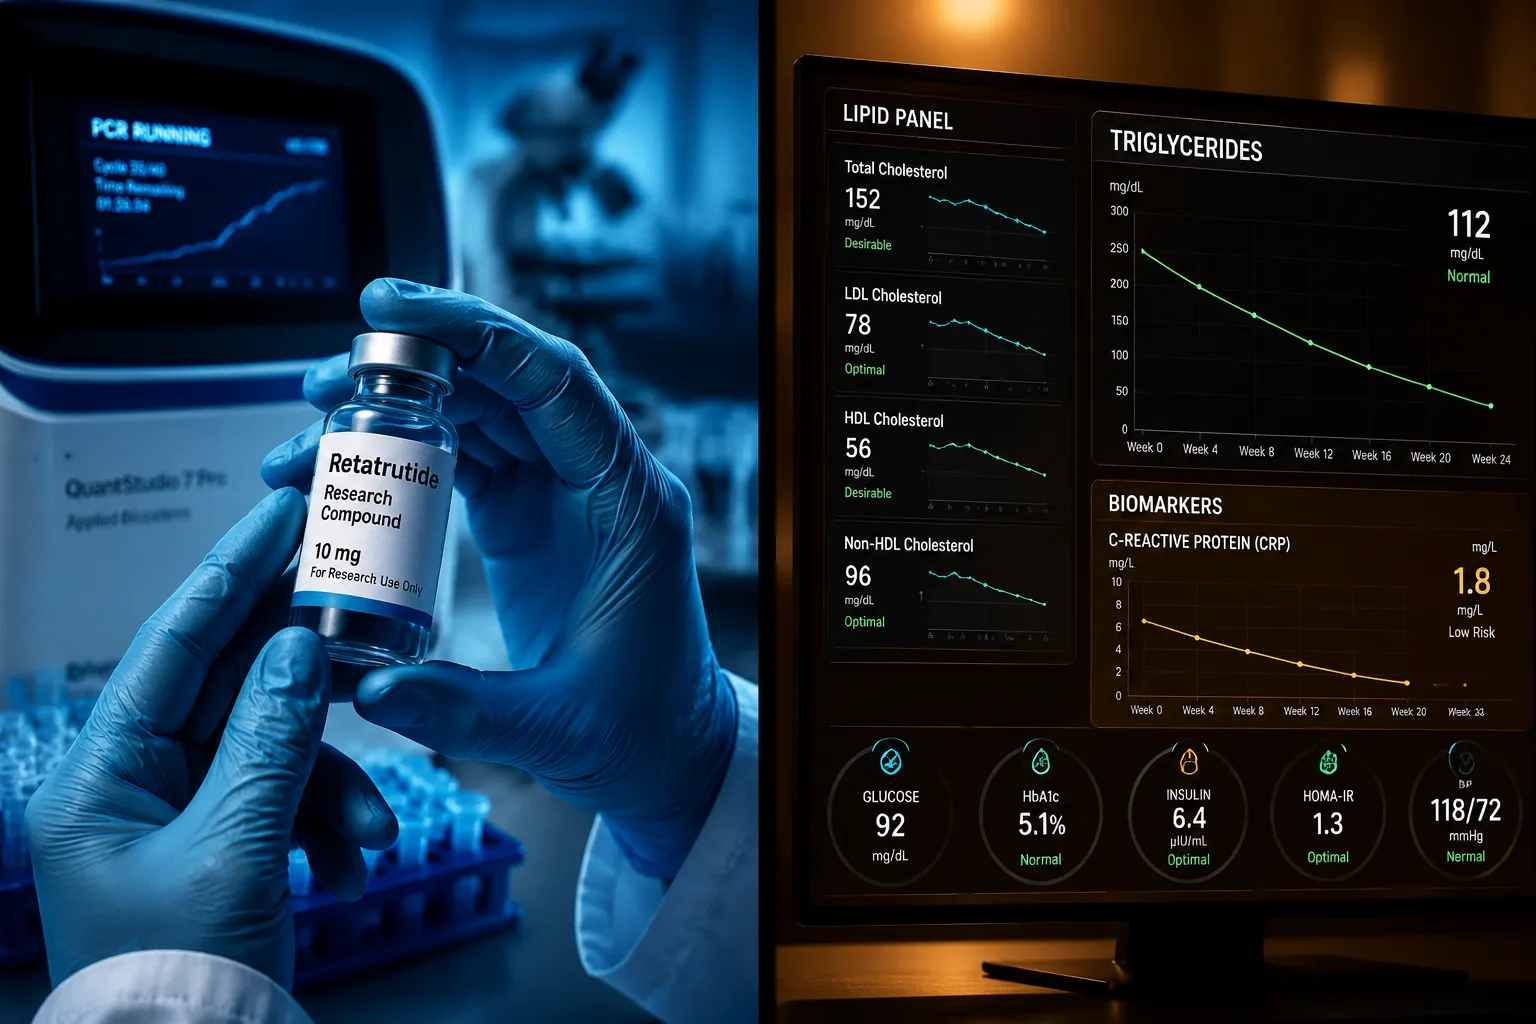
A 2026 systematic review and meta-analysis of randomized retatrutide trials found statistically significant improvements across multiple lipid markers. Total cholesterol fell by a weighted mean of approximately 21.88 mg/dL, LDL-C dropped by roughly 13.10 mg/dL, and triglycerides declined by about 40.90 mg/dL, all with p-values below 0.0001. HDL-C showed no meaningful change.

Phase 2 obesity trial data add further context. Non-HDL cholesterol fell approximately 15-17%, LDL declined around 15-20% in higher-dose regimens, and triglycerides dropped by roughly 32-44% across datasets. The mechanism appears to involve glucagon receptor agonism reducing circulating ANGPTL3 and ANGPTL8 concentrations, which in turn enhances lipoprotein lipase activity and alters hepatic lipoprotein production.

Important context: As of mid-2026, retatrutide has no approval from the FDA, EMA, or any other major regulator. Phase 3 TRIUMPH trial data are generating significant scientific interest, but retatrutide remains strictly investigational.

For researchers exploring the GLP peptide landscape, the GLP-3 peptides for sale category and retatrutide clinical trial resources provide useful context on current research-grade availability and trial status. Those interested in the broader incretin class can also review GLP-1 peptides research context for comparison.

MOTS-c and 5-Amino-1MQ: Mitochondrial Pathways in Lipid Research

This is where the science of atorvastatin, LDL cholesterol, and metabolic peptides diverges most sharply from conventional cardiology. MOTS-c and 5-Amino-1MQ do not lower LDL-C through receptor upregulation or incretin signaling. Instead, they act on the metabolic machinery inside cells.
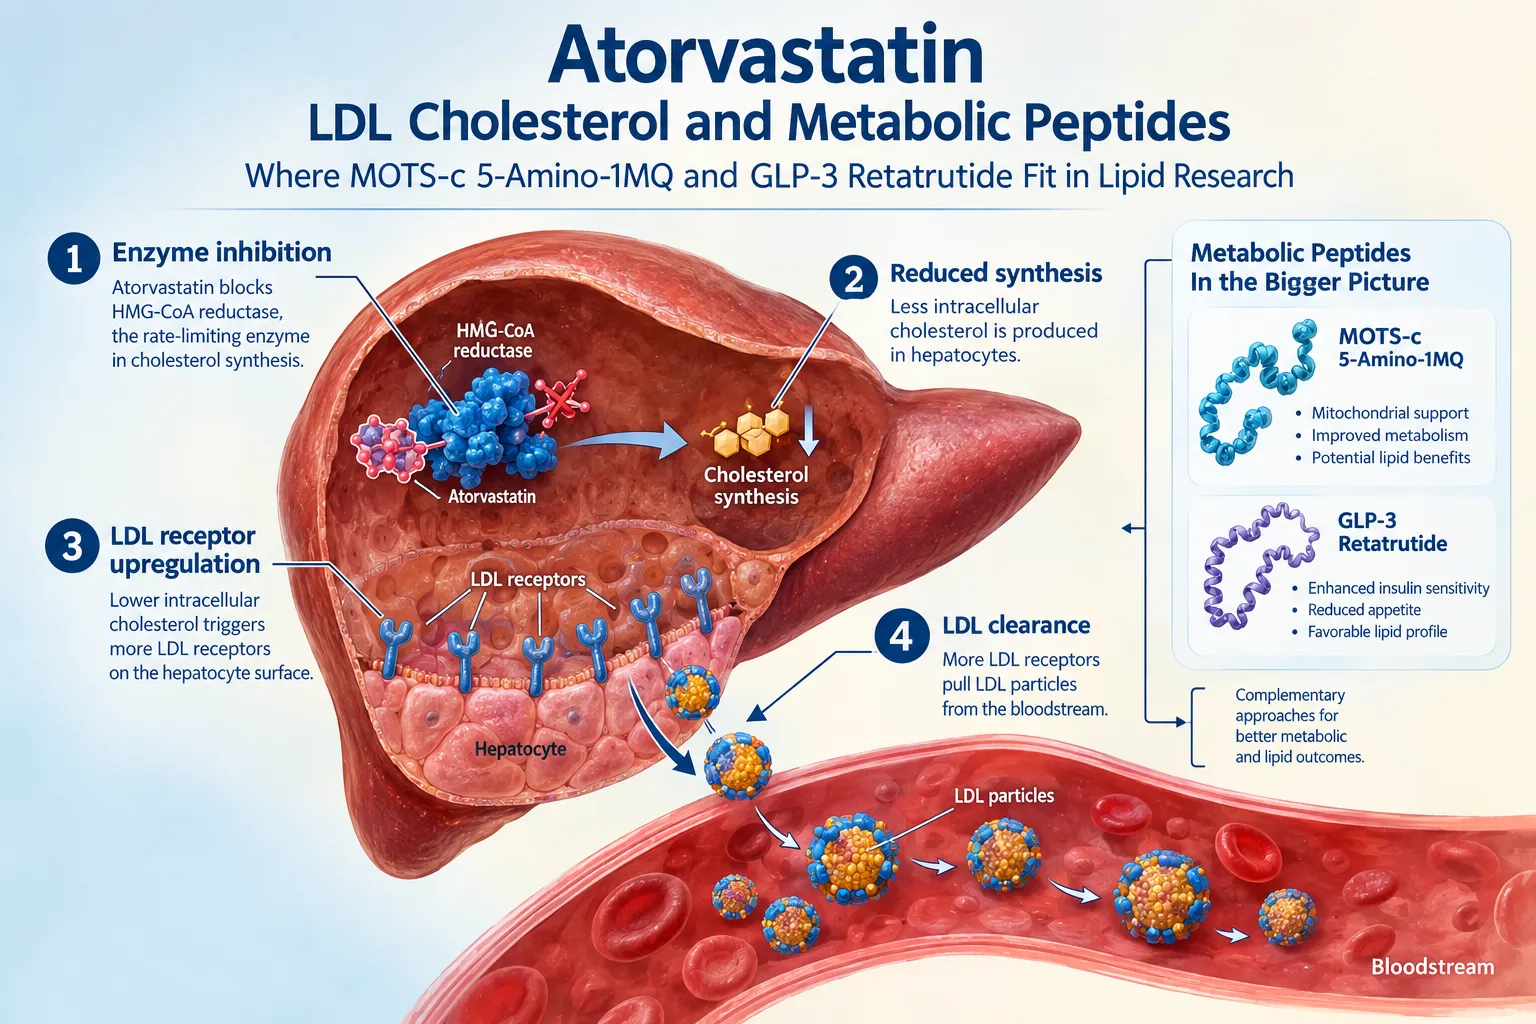
MOTS-c and 5-Amino-1MQ: Mitochondrial Pathways in Lipid Research

MOTS-c is a mitochondria-derived peptide encoded within the 12S rRNA region of mitochondrial DNA. Research models show it activates AMPK, regulates NAD+ metabolism, and promotes fatty acid oxidation over lipid storage. In preclinical settings, MOTS-c treatment is associated with improved insulin sensitivity and reduced lipid accumulation in metabolic tissues. For researchers, MOTS-c 10mg is available as a research-grade compound, and the broader MOTS-c peptide category provides additional options.

5-Amino-1MQ is a selective nicotinamide N-methyltransferase (NNMT) inhibitor. By blocking NNMT, it preserves intracellular NAD+ levels, decreases N1-methylnicotinamide, suppresses lipogenesis, and shifts adipocytes toward fat oxidation. In diet-induced obese mouse models, these effects translate to reduced fat mass and improved metabolic markers, with triglycerides often the most sensitive lipid marker to change.

Critical regulatory note: Neither MOTS-c nor 5-Amino-1MQ has an FDA-approved indication. 5-Amino-1MQ has no publicly documented IND or registered Phase 1-3 human trial as of 2026. All efficacy and safety data remain confined to cell culture and animal models.

No major 2025-2026 guideline integrates MOTS-c or 5-Amino-1MQ into formal LDL-cholesterol management pathways. Their role in lipid research is mechanistic and exploratory, not clinical.

For a broader grounding in how these peptide classes relate to each other mechanistically, the Peptides 101 for research-use only buyers guide covers structure, mechanisms, and classification in accessible detail.

Layered Therapy: How These Agents Complement Each Other in Research Models

The emerging framework in expert and industry analysis is one of layered cardiometabolic management:

  1. High-intensity statins (atorvastatin) address the primary LDL-C target mandated by guidelines.
  2. GLP-class investigational agents (retatrutide) tackle residual risk from weight, blood pressure, triglycerides, and glycemic status.
  3. Mitochondrial and NAD+ pathway agents (MOTS-c, 5-Amino-1MQ) represent a third layer focused on cellular metabolic efficiency, still preclinical, but scientifically compelling.
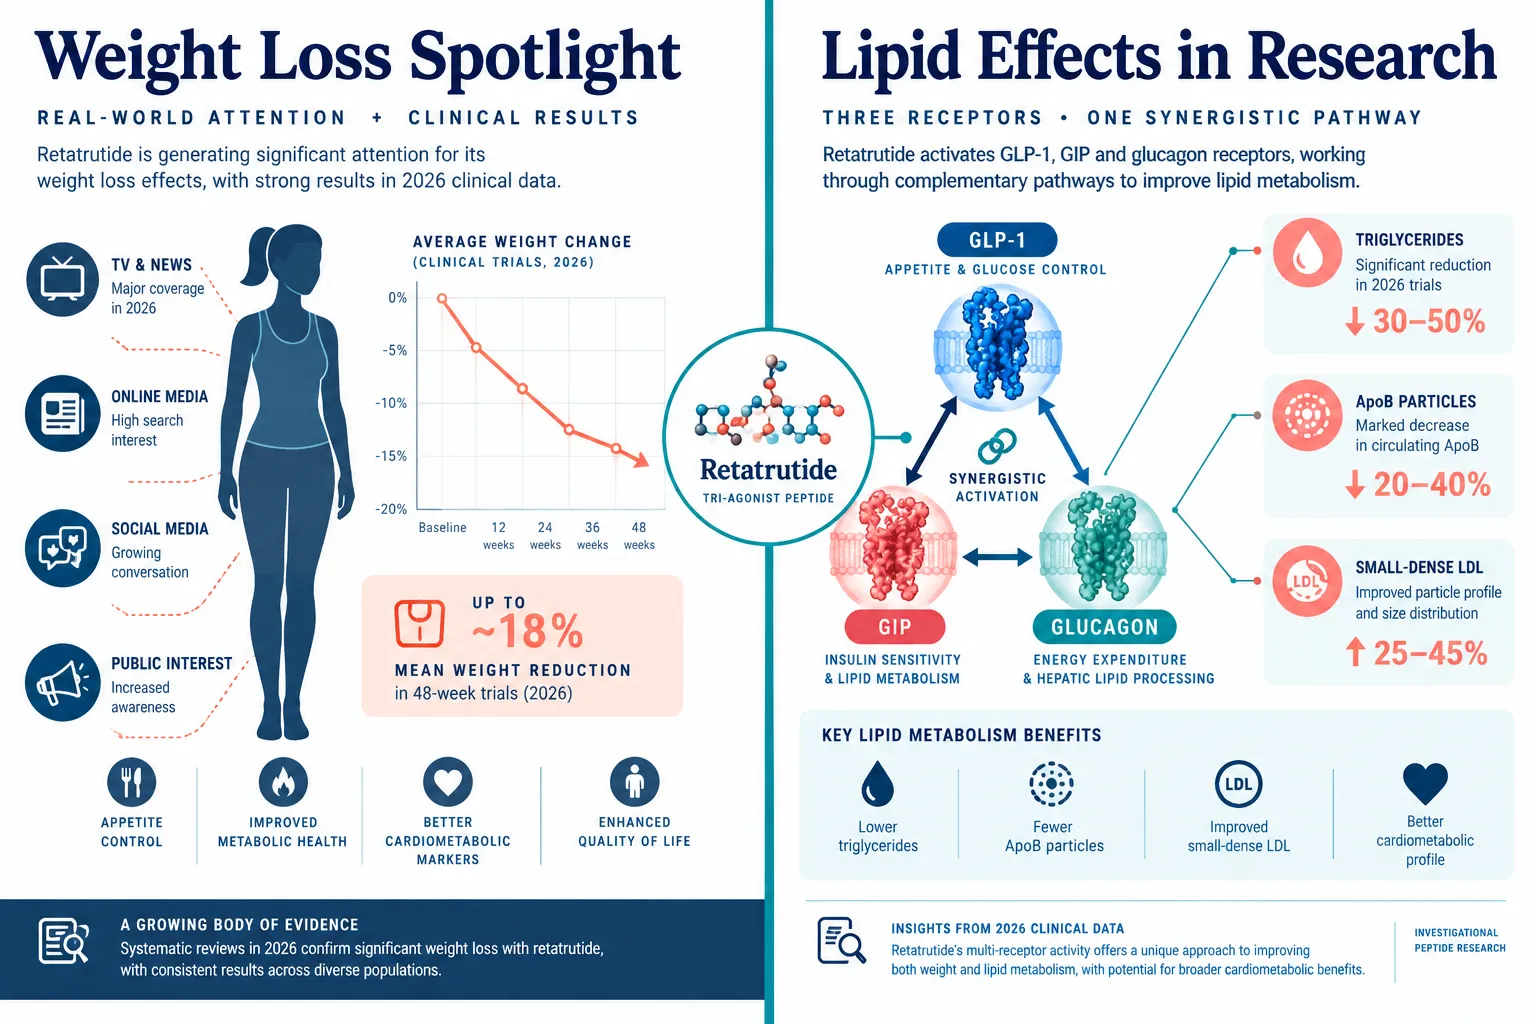
Layered Therapy: How These Agents Complement Each Other in Research Models

This layered model does not imply clinical equivalence. Atorvastatin has decades of randomized controlled trial data and guideline endorsement. Retatrutide has Phase 2 and emerging Phase 3 data. MOTS-c and 5-Amino-1MQ have preclinical data only. Researchers and clinicians must weigh evidence tiers carefully.

The intersection of atorvastatin, LDL cholesterol, and metabolic peptides: where MOTS-c, 5-Amino-1MQ, and GLP-3 Retatrutide fit in lipid research is ultimately a question about mechanism, evidence quality, and therapeutic stage, not a single unified treatment protocol.

For those exploring adjacent peptide research areas, resources on peptides and polypeptides in endocrine pharmacology provide useful mechanistic context on how different peptide classes interface with metabolic signaling systems.

Conclusion

Atorvastatin remains the cornerstone of LDL-C reduction in 2026, backed by robust dose-response data and explicit guideline targets that demand aggressive lipid lowering in high-risk patients. Retatrutide adds a meaningful investigational layer with documented lipid improvements, particularly for triglycerides, through a distinct incretin and glucagon receptor mechanism. MOTS-c and 5-Amino-1MQ represent the frontier of mitochondrial and NAD+ biology in lipid research, with scientifically interesting preclinical profiles but no clinical validation yet.

Actionable next steps for researchers:

  • Use current ACC/AHA LDL-C targets as the benchmark when designing lipid-focused research protocols.
  • Distinguish clearly between agents with clinical trial data (retatrutide) and those with only preclinical data (MOTS-c, 5-Amino-1MQ) when framing research questions.
  • Monitor Phase 3 TRIUMPH retatrutide data and ADA presentations for updated lipid endpoints.
  • Ensure all peptide compounds used in research settings are sourced from verified, high-purity suppliers with documented testing.
  • Consult regulatory guidance before any translational or human-adjacent research involving investigational peptides.

The science connecting statins, incretin-class peptides, and mitochondrial signaling molecules is evolving rapidly. Staying current with both guideline updates and preclinical mechanistic literature is essential for anyone working at this intersection.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/atorvastatin-ldl-cholesterol-and-metabolic-peptides-where-mots-c-5-amino-1mq-and.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-20 13:06:502026-09-20 13:06:50Atorvastatin, LDL Cholesterol, and Metabolic Peptides: Where MOTS-c, 5-Amino-1MQ, and GLP-3 Retatrutide Fit in Lipid Research
Complement-Dependent Cytotoxicity and Peptide Research Safety: What Labs Track When Using GLP-3, BPC-157, and Novel Peptides

Complement-Dependent Cytotoxicity and Peptide Research Safety: What Labs Track When Using GLP-3, BPC-157, and Novel Peptides

September 8, 2026/0 Comments/in Uncategorized/by

Fewer than 15% of novel peptide candidates that enter preclinical testing carry a structured complement-activation safety panel, yet complement-dependent cytotoxicity (CDC) remains one of the most consequential immune mechanisms that can derail a promising research compound. As labs in 2026 work with research-use peptides ranging from GLP-3 analogs and BPC-157 to TB-500 and macrocyclic probes, understanding complement-dependent cytotoxicity and peptide research safety is no longer optional background knowledge. It is a core part of responsible experimental design.

Key Takeaways

  • Complement-dependent cytotoxicity is a well-defined immune effector mechanism involving C1 activation, C3b deposition, and membrane-attack complex formation that can affect peptide therapeutics, especially those conjugated to antibody scaffolds.
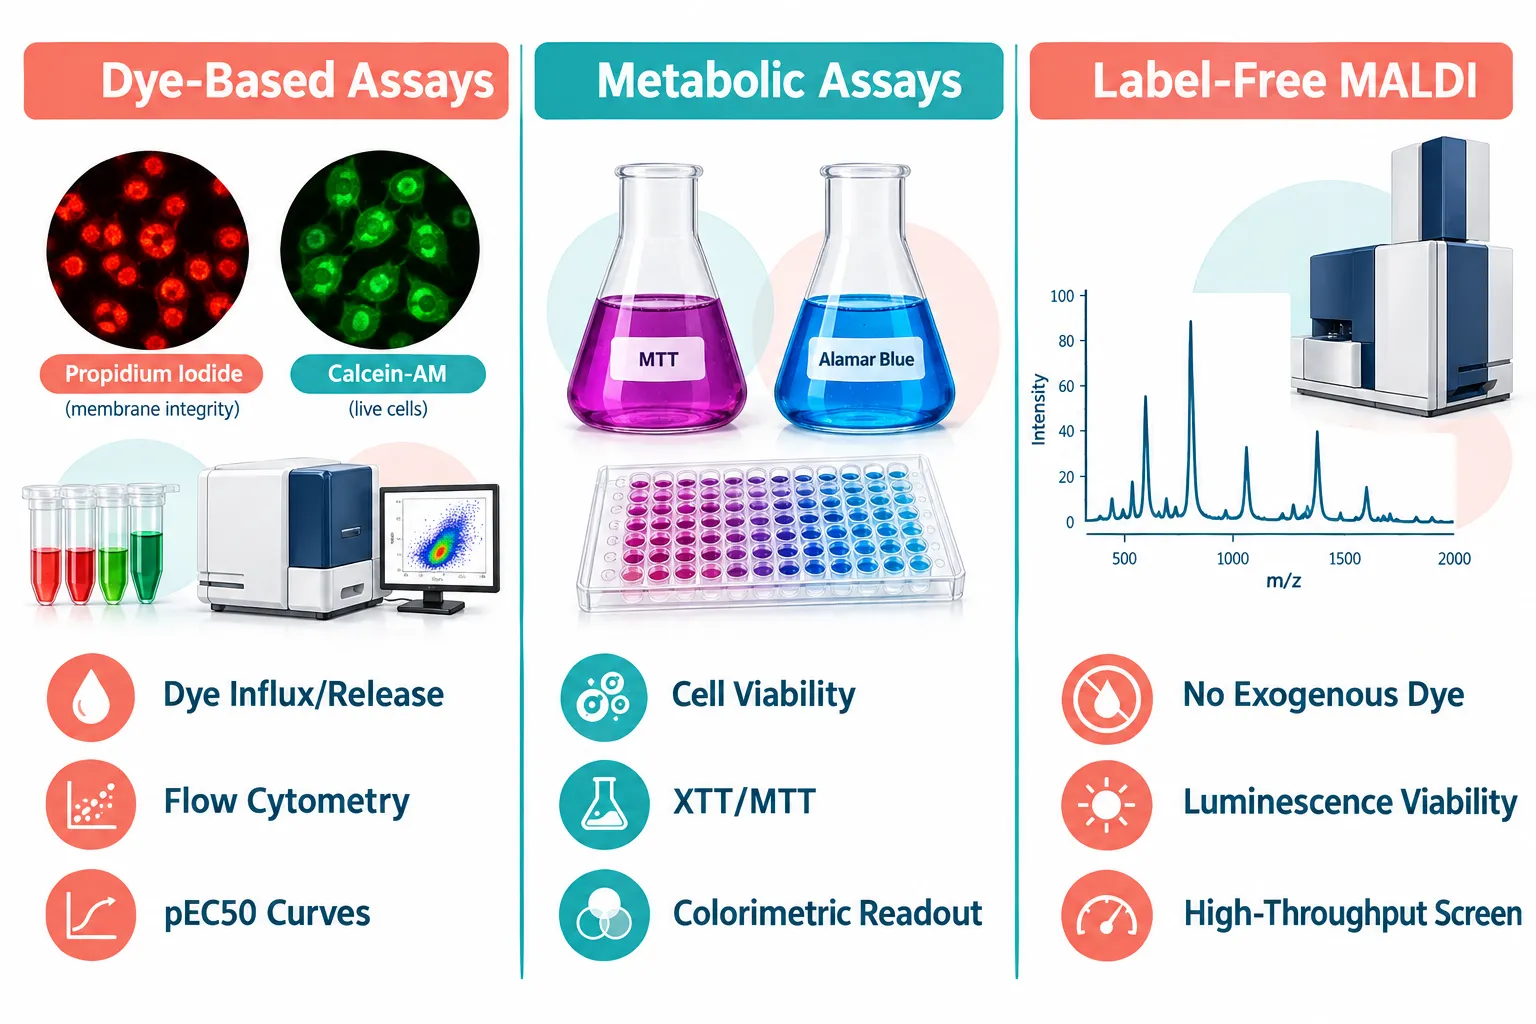
  • Different CDC assay formats, dye-based, metabolic, and label-free MALDI, yield materially different potency estimates, so labs must document assay type alongside results.
  • BPC-157 has shown an unusually clean preclinical toxicology profile through 2026, but the absence of robust human immunogenicity and CDC data means structured safety panels are still recommended.
  • GLP-3 as a named research peptide class lacks published CDC-specific safety data; labs are currently extrapolating from biologic-drug safety paradigms.
  • Regulatory expectations for integrated CDC and immunogenicity profiling in early-phase peptide trials are rising, making proactive safety tracking a competitive and compliance advantage.

How Complement-Dependent Cytotoxicity Works, and Why Peptide Labs Must Care

How Complement-Dependent Cytotoxicity Works, and Why Peptide Labs Must Care

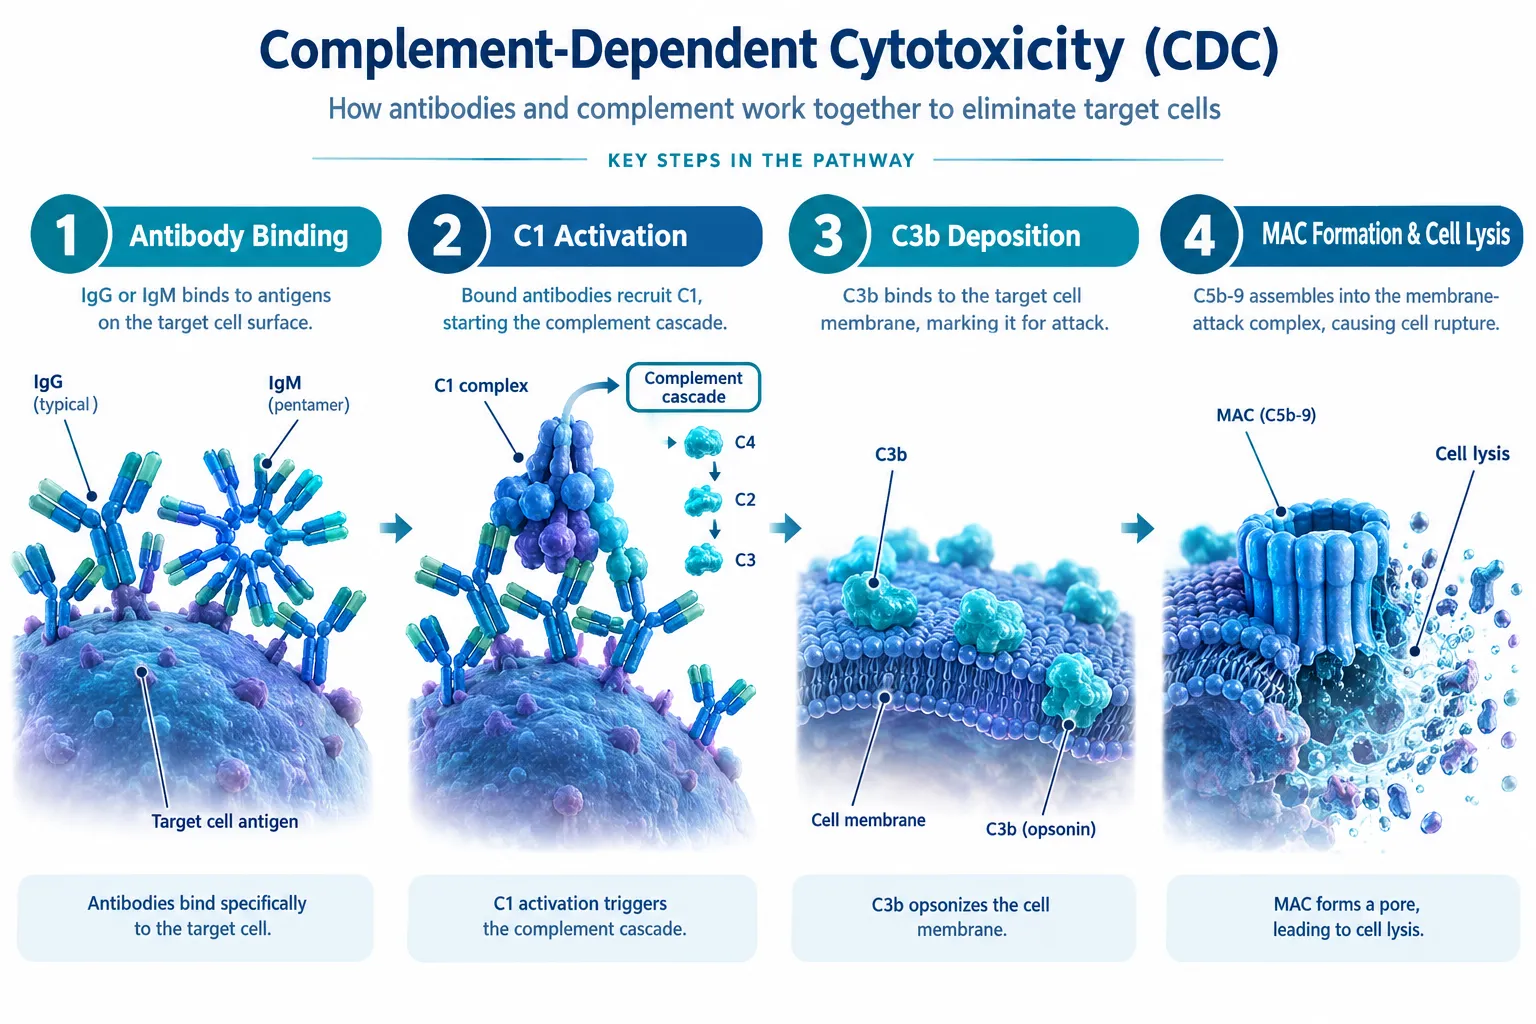
The complement system is an ancient branch of innate immunity. When IgG or IgM antibodies bind a target cell surface, they can recruit the C1 complex, triggering a cascade that deposits C3b on the membrane and ultimately assembles the membrane-attack complex (MAC). The MAC punches pores through the lipid bilayer, causing osmotic cell lysis, that process is complement-dependent cytotoxicity.

For classic monoclonal antibody drugs, CDC is a desired or at least well-characterized effect. For novel peptides, the picture is more complicated. Peptides that are conjugated to antibody scaffolds, that modulate complement regulatory proteins such as CD59, or that alter upstream C1 recognition can all engage CDC pathways in ways that are not always predicted from amino acid sequence alone.

Why this matters for peptide research safety:

  • Peptide, antibody conjugates designed to enhance anti-CD20 CDC activity have demonstrated complement-mediated killing that is largely independent of NK cells, meaning the lysis mechanism is driven specifically by the complement arm.
  • Macrocyclic peptide probes targeting CD59, a key complement inhibitor on human cells, can sensitize non-target tissues to lysis if systemic distribution is not carefully controlled.
  • Complement-modulating peptides like the cL3 class can inhibit lysis without blocking C1 binding, creating a scenario where upstream complement recognition remains intact while downstream lysis is suppressed. Labs tracking only cell viability may miss this nuance entirely.

"A peptide that looks inert in a standard cytotoxicity screen can still be actively reshaping complement regulation in ways that only a targeted CDC panel will reveal."

For researchers exploring how peptides differ from classic small-molecule drugs in lab design, this mechanistic distinction is particularly important to internalize early.

Assay Selection: The Core of Complement-Dependent Cytotoxicity and Peptide Research Safety Tracking

Assay Selection: The Core of Complement-Dependent Cytotoxicity and Peptide Research Safety Tracking

Not all CDC assays produce the same numbers, and in 2026 that is no longer a minor methodological footnote, it is a recognized source of cross-study variability that regulators and reviewers are beginning to scrutinize.

Four Assay Formats Labs Currently Use

Assay Type Readout Key Advantage Known Limitation
Dye influx (propidium iodide) % PI-positive dead cells Flow-cytometry compatible, precise pEC50 Dye can interfere with some peptide structures
Dye release (calcein-AM) Fluorescence in supernatant Sensitive, widely validated Background release in long incubations
Metabolic (MTT, XTT, Alamar Blue) Cell metabolic activity Plate-reader compatible, high throughput Indirect viability; can miss rapid lysis events
Label-free MALDI Direct cell-lysis via mass spec No dye interference, richer mechanistic data Higher equipment cost, emerging adoption

A 2024 label-free whole-cell MALDI mass-spectrometry CDC bioassay demonstrated that complement-induced lysis can be monitored without exogenous dyes, using luminescence-based viability and concentration-response analysis to derive pEC50 values. This approach is expected to gain traction for high-throughput peptide screening precisely because it eliminates the assay-interference problem.

What labs must document for every CDC experiment:

  • Assay format and detection method
  • Complement source (human serum, rabbit serum, or recombinant components) and lot number
  • Incubation time and temperature
  • Target cell line and passage number
  • Viability readout normalization method

Standardizing these parameters is especially critical when comparing results across sites or when building a regulatory submission package for a novel peptide candidate.

BPC-157, GLP-3, and Novel Peptides: What the Safety Data Actually Show

BPC-157, GLP-3, and Novel Peptides: What the Safety Data Actually Show

Complement-dependent cytotoxicity and peptide research safety considerations differ substantially depending on the specific compound class. The three categories most active in research labs in 2026, BPC-157, GLP-3 analogs, and novel immunomodulatory peptides, each present a distinct safety evidence landscape.

BPC-157: Strong Preclinical Record, Thin Human Data

BPC-157 is a 15-amino-acid peptide derived from human gastric juice protein. Its preclinical toxicology profile is, by peptide-drug standards, unusually clean:

  • No lethal dose has been identified in mice, rats, rabbits, or dogs across a wide dose range, including limit-toxicity studies up to approximately 2 g/kg in rodents.
  • No teratogenic, genotoxic, or anaphylactic effects have been detected.
  • Mild local irritation has been noted in some multi-dose studies, but no dose-limiting organ toxicity.

For researchers interested in BPC-157's broader mechanisms, the article on mesenchymal stem cells and peptide-based modulators including BPC-157 provides useful context on how this peptide is applied in regenerative research models.

Despite this record, the human data gap is significant. Available clinical evidence consists largely of small pilot studies without robust statistical power. Regulatory-oriented analyses published in 2026 argue that adoption into clinical practice is not yet scientifically justified and recommend that future phase I/II trials include:

  • Anti-peptide antibody assays (immunogenicity)
  • Complement activation panels (C3/C5 activation, CDC assays)
  • Cytokine profiling
  • Standard organ-toxicity monitoring (clinical chemistry, histopathology)

GLP-3 Analogs: A Data Gap That Labs Must Acknowledge

As of 2026, there is no publicly indexed clinical or preclinical dataset specifically focused on CDC safety profiling for "GLP-3" peptides. Unlike GLP-1 analogs, which have extensive immunogenicity and safety datasets from large trials, GLP-3 as a named research peptide class remains largely undefined in major pharmacological databases.

Labs working with novel incretin-mimetic or metabolic peptides in this space are currently extrapolating from biologic-drug safety paradigms. This means tracking:

  • Immunogenicity markers (anti-drug antibody formation)
  • Complement activation markers (C3b deposition, complement consumption assays)
  • Liver and cardiac safety labs
  • Metabolic endpoints relevant to the compound's mechanism

For broader context on how triple-agonist metabolic peptides like retatrutide are reshaping research design, see the analysis of GLP-3 retatrutide in phase 3 trials and triple agonism.

Novel Immunomodulatory Peptides: The Highest CDC Risk Category

Peptides that directly interact with complement regulatory proteins carry the most direct CDC risk. Labs working with CD59-targeting macrocycles, complement-enhancing antibody conjugates, or cL3-class inhibitors should track:

  • Hemolysis assays (direct red blood cell lysis)
  • C3b deposition on target and non-target cells
  • Complement consumption (total hemolytic complement, CH50)
  • Cell-viability curves with pEC50 derivation
  • Comparative lysis vs. unconjugated antibody controls

The polypeptide peptides and drug mechanisms resource offers additional pharmacology context relevant to understanding how these mechanisms translate across compound classes.

Building a Practical CDC Safety Tracking Protocol for Peptide Research

Translating the above into a usable lab workflow requires a tiered approach. Not every peptide warrants the same depth of CDC profiling, but every novel peptide warrants at least a screening-level assessment.

Tier 1, Screening (all novel peptides):

  • Standard cell-viability assay in the presence of normal human serum
  • Hemolysis assay with human red blood cells
  • Complement consumption check (CH50 before and after peptide exposure)

Tier 2, Characterization (peptides with immune-modulating or antibody-recruiting properties):

  • Flow-cytometry CDC assay with pEC50 derivation
  • C3b deposition by ELISA or flow
  • Anti-peptide antibody ELISA (immunogenicity screen)
  • Cytokine panel (IL-6, TNF-alpha, C-reactive protein)

Tier 3, Regulatory-grade profiling (IND-enabling or first-in-human candidates):

  • Label-free MALDI CDC bioassay for mechanistic depth
  • Full complement activation panel (C3, C4, C5a, sC5b-9)
  • Repeat-dose immunogenicity with titer tracking
  • Integrated organ-toxicity histopathology

Labs interested in how administration route affects immune exposure should also review the nasal spray peptides bioavailability and research design considerations resource, as mucosal delivery can alter complement exposure profiles compared to systemic injection.
For metabolic peptide research specifically, the comparison of tesofensine vs GLP-3 retatrutide appetite-modulating pathways illustrates how different mechanistic classes require different safety endpoint selections.

Conclusion

Complement-dependent cytotoxicity and peptide research safety represent a rapidly maturing area of laboratory practice. The core message for 2026 is straightforward: the assay format matters, the peptide class matters, and the absence of published CDC data for a compound is not the same as the absence of CDC risk.

Actionable next steps for research labs:

  1. Audit current peptide safety protocols to confirm whether a CDC screening tier is included, even at the basic hemolysis and CH50 level.
  2. Document assay format, complement source, and incubation conditions for every CDC-related experiment to enable cross-study comparison.
  3. For BPC-157 and similar investigational peptides, add immunogenicity and complement-activation panels to any study design that will generate data intended for publication or regulatory review.
  4. Treat the GLP-3 CDC data gap as an active research priority rather than a reason to defer safety tracking.
  5. Follow the trajectory of label-free MALDI CDC assays and advanced flow-cytometry methods, as these are likely to become standard expectations in regulatory submissions within the next few years.

Rigorous safety tracking does not slow peptide research, it protects the investment in it.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/complement-dependent-cytotoxicity-and-peptide-research-safety-what-labs-track-wh.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-08 13:09:032026-09-08 13:09:03Complement-Dependent Cytotoxicity and Peptide Research Safety: What Labs Track When Using GLP-3, BPC-157, and Novel Peptides
Peptides in Basic Cell Biology: How GLP-3, GLP-2-T, and Growth Hormone Secretagogues Interact With Animal and Plant Cells

Peptides in Basic Cell Biology: How GLP-3, GLP-2-T, and Growth Hormone Secretagogues Interact With Animal and Plant Cells

September 3, 2026/0 Comments/in Uncategorized/by

Fewer than five years ago, the concept of a single peptide activating three distinct hormone receptors simultaneously existed only in theoretical pharmacology. Today, the study of peptides in basic cell biology, how GLP-3, GLP-2-T, and growth hormone secretagogues interact with animal and plant cells, sits at the center of metabolic research, driving some of the most consequential findings in endocrine science and preclinical investigation.

Key Takeaways

  • GLP-3 is not a naturally occurring hormone but an informal label for synthetic triple agonist peptides such as retatrutide, which simultaneously activates GLP-1R, GIPR, and glucagon receptors in animal cells.
  • GLP-2-T refers to tirzepatide-class dual incretin peptides that target GLP-1R and GIPR, reshaping signaling in pancreatic, hepatic, and neuronal cell populations.
  • Growth hormone secretagogues act through the GHSR1a receptor, a seven-transmembrane GPCR found in pituitary, hypothalamic, and other vertebrate tissues.
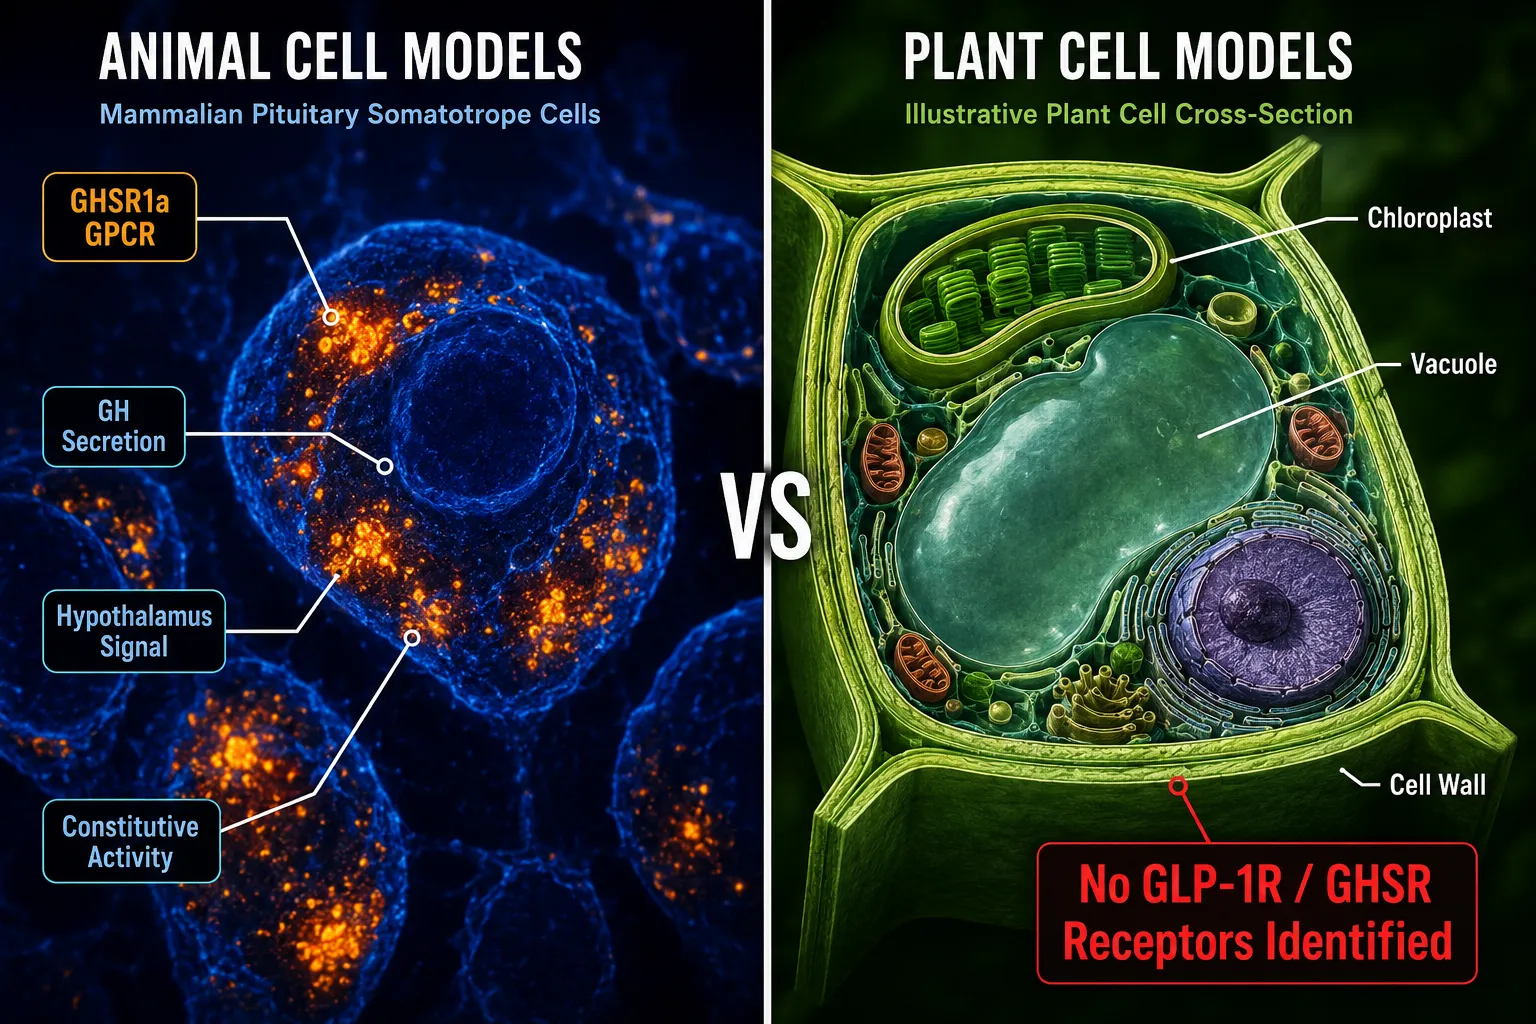
  • None of these receptor systems, GLP-1R, GIPR, GCGR, GLP-2R, or GHSR1a, have been identified in plant cell genomes, making their interaction with plant cells non-canonical and outside current mainstream research.
  • All three peptide classes are currently classified as research-use-only compounds, applied in controlled in-vitro and preclinical animal cell studies.

Understanding GLP-3 and GLP-2-T in Animal Cell Signaling

Understanding GLP-3 and GLP-2-T in Animal Cell Signaling

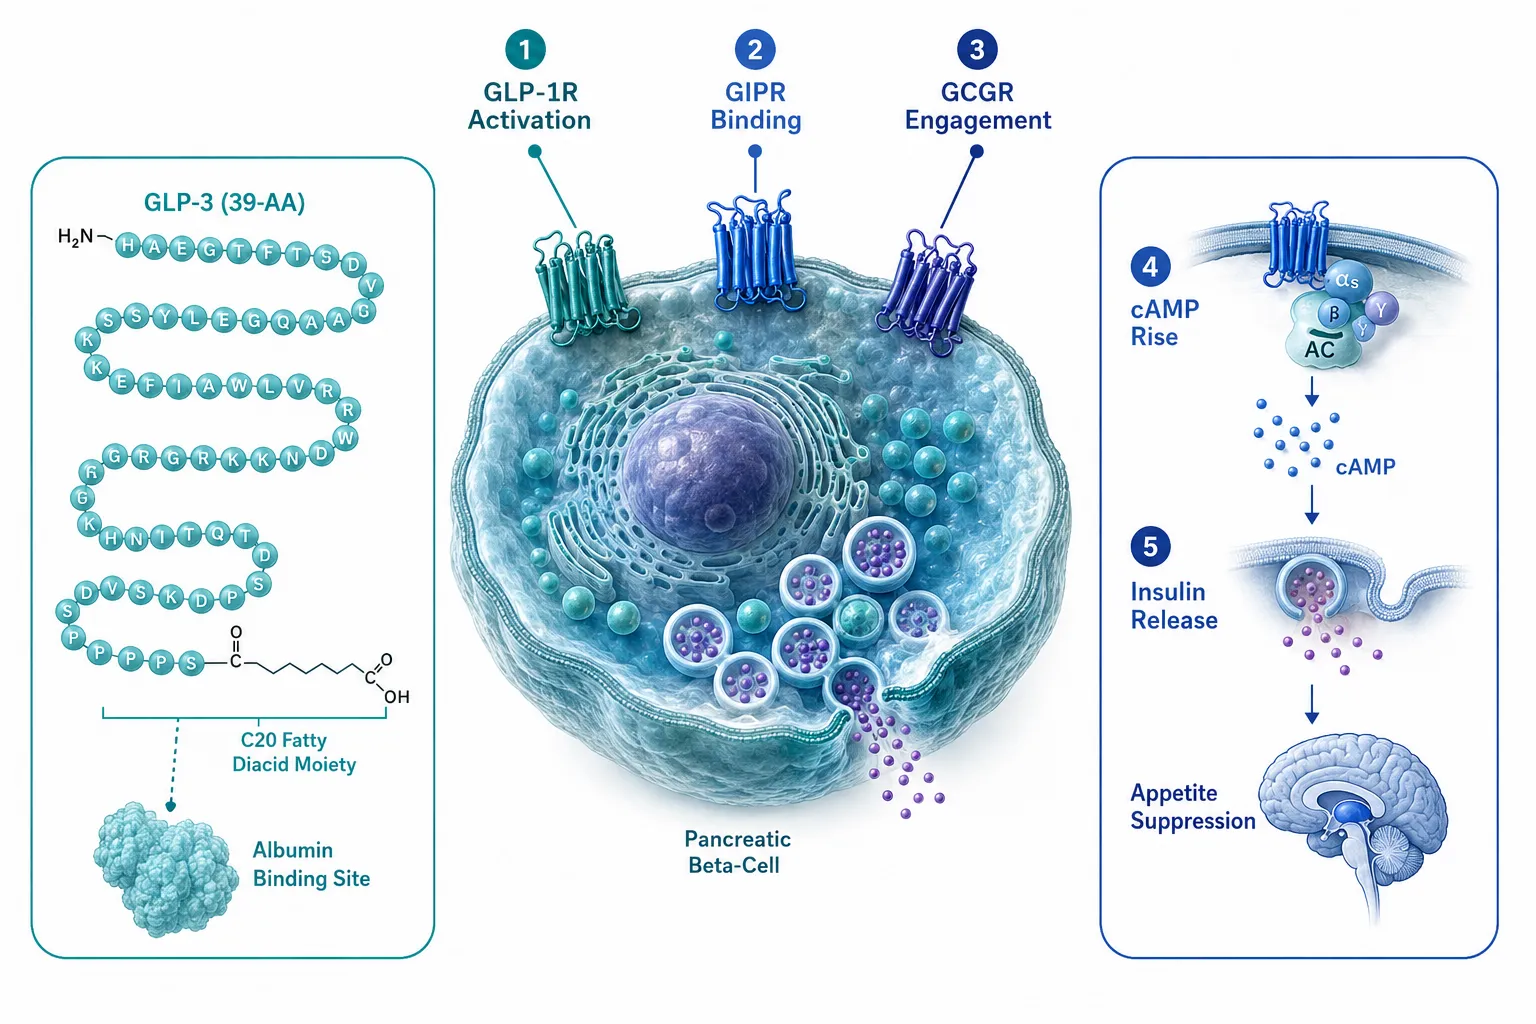
The label "GLP-3" does not correspond to a naturally secreted human hormone. Humans produce GLP-1 and GLP-2 from proglucagon processing, but no endogenous GLP-3 exists. Instead, the term has become informal shorthand for synthetic triple agonist peptides, most notably retatrutide (LY3437943), engineered to engage three receptors at once: the glucagon-like peptide-1 receptor (GLP-1R), the glucose-dependent insulinotropic polypeptide receptor (GIPR), and the glucagon receptor (GCGR).

Retatrutide is a 39-amino-acid acylated peptide built on a glucagon-based scaffold. Its C20 fatty diacid moiety promotes strong albumin binding, extending its pharmacokinetic half-life to approximately six days. In animal cell models, this structural feature alters receptor residence time and sustains signaling across pancreatic islets, hepatocytes, and central nervous system neurons. The coordinated activation of all three receptors drives glucose-dependent insulin secretion, appetite suppression via hypothalamic circuits, and increased energy expenditure, effects that no single-receptor agonist can fully replicate.

GLP-2-T, often associated with tirzepatide-class analogs (LY3298176), follows a related but distinct logic. These truncated peptide analogs are 39-amino-acid dual incretins with a C20 fatty diacid side chain, a molecular weight around 4.8 kDa, and an in-vivo half-life of roughly five days. Their "twincretin" behavior, balanced GIPR agonism paired with biased GLP-1R activation, targets pancreatic beta-cells, gut epithelium, and CNS appetite circuits in mammalian models.

Key distinction: GLP-3 engages three receptors simultaneously; GLP-2-T engages two. Both are tools for dissecting how multi-receptor incretin signaling reshapes metabolic cell networks.

Truncated GLP-2 variants, such as GLP-2(11-33) and the dipeptidyl peptidase IV (DPP-IV) metabolite GLP-2(3-33), serve as pharmacological probes in intestinal and endocrine cell research. DPP-IV cleaves both GLP-1 and GLP-2 at the N-terminus in vivo, generating metabolites with altered receptor binding and reduced signaling intensity. Studying these truncations helps researchers understand how peptide half-life and structural integrity govern GLP-2 receptor (GLP-2R) pharmacology in gut cells.

Growth Hormone Secretagogues and Their Cellular Mechanisms in Animal Models

Growth Hormone Secretagogues and Their Cellular Mechanisms in Animal Models

Growth hormone secretagogues (GHS) represent a structurally diverse class of peptides that share one defining feature: activation of the growth hormone secretagogue receptor 1a (GHSR1a), a 366-amino-acid, seven-transmembrane G-protein-coupled receptor (GPCR). GHSR1a was originally characterized as the receptor for synthetic GHS peptides before ghrelin was identified as its endogenous ligand.

GHSR1a is highly expressed in:

  • Anterior pituitary somatotrope cells (primary site of GH release)
  • Hypothalamic neurons (appetite and energy regulation)
  • Pancreatic tissue
  • Cardiac and neuronal cells (neuroprotection and cardiovascular signaling)
  • Thymic immune cells

One biologically unusual feature of GHSR1a is its high constitutive activity, it signals even without a ligand present. Two endogenous molecules modulate this baseline activity: octanoylated ghrelin, which acts as a full agonist, and LEAP2 (liver-expressed antimicrobial peptide 2), which functions as an inverse agonist and antagonist.

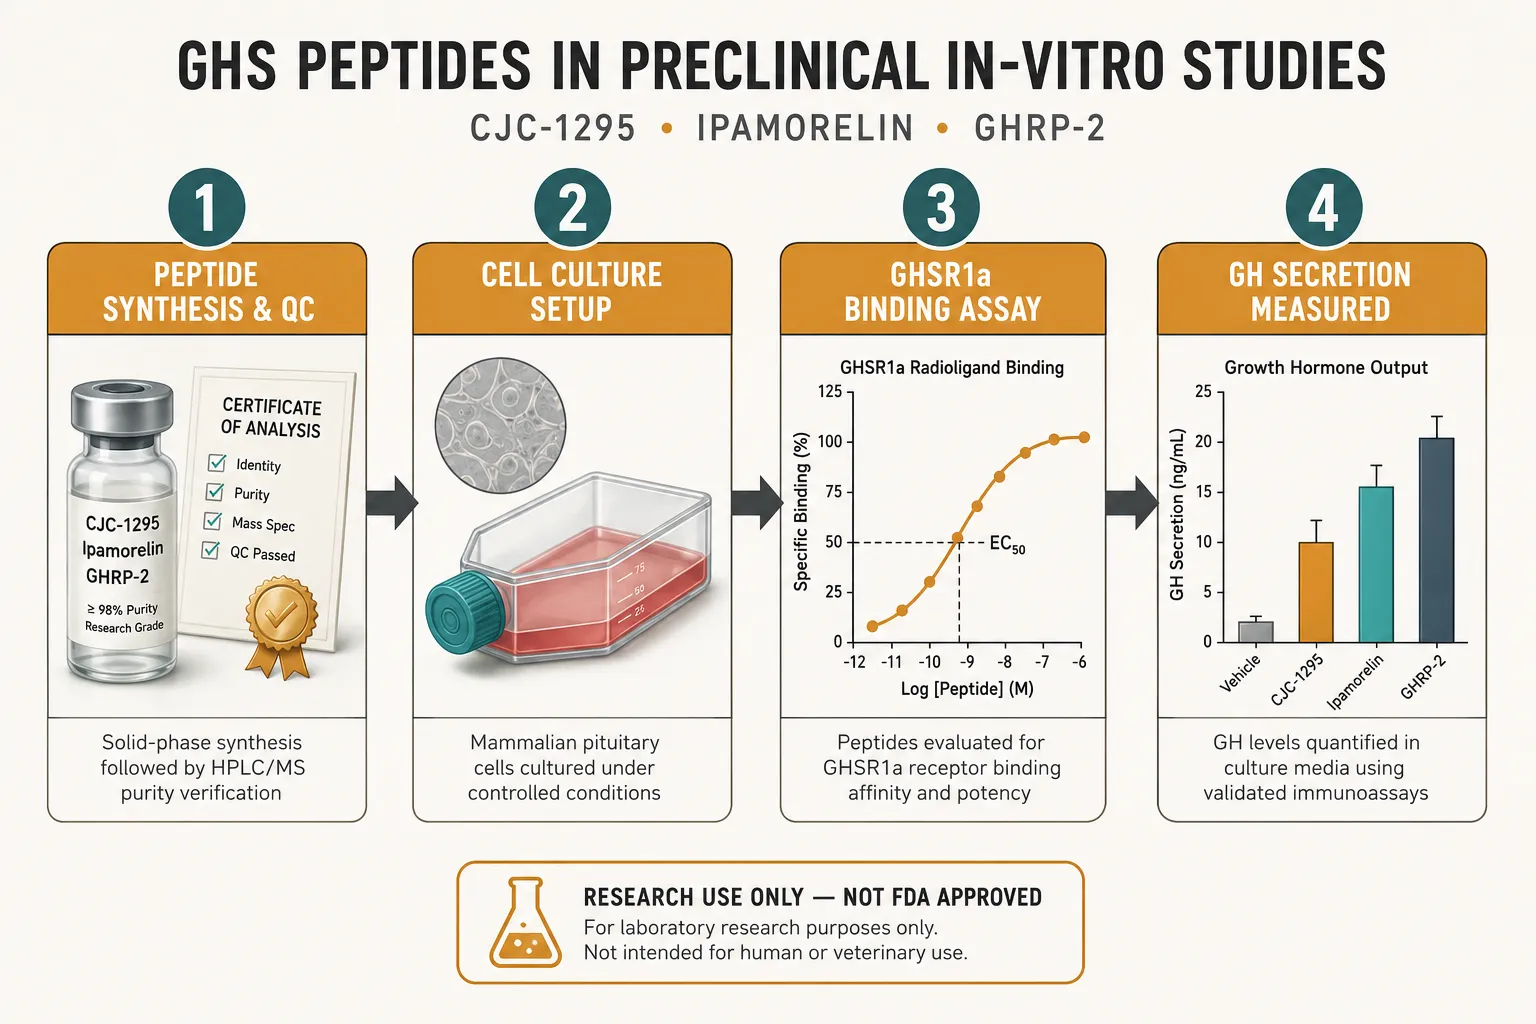
In 2026, the most studied synthetic GHS peptides include CJC-1295 (with or without drug affinity complex/DAC), ipamorelin, hexarelin, GHRP-2, GHRP-6, sermorelin, tesa, and the small-molecule MK-677 (ibutamoren). Researchers working with IPA peptides and related compounds apply these agents to pituitary and hypothalamic cell cultures to map intracellular signaling cascades, G-protein activation, calcium flux, and downstream transcriptional responses, that govern GH synthesis and secretion.

Beyond GH release, GHSR signaling exerts pleiotropic effects on cell populations across multiple tissues, including modulation of glucose and lipid metabolism, gastrointestinal motility, neuronal survival, and immune function.

Peptides in Basic Cell Biology Across Animal and Plant Systems

Peptides in Basic Cell Biology Across Animal and Plant Systems

A critical boundary in understanding peptides in basic cell biology, how GLP-3, GLP-2-T, and growth hormone secretagogues interact with animal and plant cells, is the receptor distribution question. The receptors central to GLP-3, GLP-2-T, and GHS pharmacology (GLP-1R, GIPR, GCGR, GLP-2R, and GHSR1a) are all vertebrate-specific GPCRs. Plant genomes do not encode these receptors. No credible evidence from current plant cell biology literature supports canonical GLP-3, GLP-2-T, or GHSR-mediated signaling in plant cells.

This distinction matters practically. Researchers designing study design peptides protocols for cross-kingdom comparative work must account for the absence of these receptor systems in plant models. Any peptide effects observed in plant cell assays would reflect non-specific or structural interactions rather than receptor-mediated signaling.

In contrast, animal cell models, particularly mammalian pancreatic islets, hepatocytes, pituitary cultures, and neuronal lines, remain the primary systems for applying these compounds. Researchers sourcing wholesale peptides for sale for preclinical programs consistently apply GLP-3 and GLP-2-T analogs in these controlled mammalian settings to interrogate incretin network biology.

All three peptide classes carry consistent "research use only" designations in 2026 catalogs. GLP-3/retatrutide remains in Phase 3 clinical trials and is not FDA-approved. GLP-2-T/tirzepatide-class research analogs are similarly restricted to laboratory use. These compounds are not intended for human or veterinary therapy outside approved clinical frameworks.

Research Context Note: The convergence of triple and dual incretin agonists as cell-biology tools marks a central 2026 development. Moving from single-receptor to multi-receptor agonists allows researchers to map how simultaneous receptor activation reshapes signaling networks in pancreatic beta-cells, hepatocytes, and CNS neurons, producing effects on glucose homeostasis and appetite that single-target compounds cannot replicate.

For researchers focused on tissue-level outcomes, tissue repair peptides and stimuli responsive peptides offer complementary frameworks for studying how peptide-receptor interactions translate into cellular repair and adaptive responses in animal models.

Conclusion

The study of peptides in basic cell biology, how GLP-3, GLP-2-T, and growth hormone secretagogues interact with animal and plant cells, reveals a field defined by precision engineering and receptor specificity. GLP-3/retatrutide-class triple agonists and GLP-2-T/tirzepatide-class dual incretins are powerful probes for dissecting multi-receptor metabolic signaling in mammalian cell systems. GHS peptides extend this toolkit into pituitary and hypothalamic biology through GHSR1a-mediated pathways.

Actionable next steps for researchers:

  1. Confirm receptor expression profiles in your specific cell line before selecting a GLP-class or GHS peptide, receptor absence invalidates the model.
  2. Account for DPP-IV-mediated truncation when designing in-vitro assays with GLP-1 or GLP-2 analogs; use DPP-IV-resistant variants or inhibitors where appropriate.
  3. Apply plant cell models only for non-receptor-mediated peptide studies; do not extrapolate GLP-3 or GHSR findings to plant systems.
  4. Source research-grade compounds with certificates of analysis and maintain strict research-use-only protocols in compliance with institutional guidelines.
  5. Monitor Phase 3 trial data for retatrutide, the mechanistic insights from clinical outcomes will refine in-vitro model design.
https://www.puretestedpeptides.com/wp-content/uploads/2026/09/peptides-in-basic-cell-biology-how-glp-3-glp-2-t-and-growth-hormone-secretagogue.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-03 13:06:212026-09-03 13:06:21Peptides in Basic Cell Biology: How GLP-3, GLP-2-T, and Growth Hormone Secretagogues Interact With Animal and Plant Cells
Peptides vs Classic Heart Drugs: How GLP-3 Retatrutide and GLP-2-T Compare With Atorvastatin in Cardiometabolic Research Models

Peptides vs Classic Heart Drugs: How GLP-3 Retatrutide and GLP-2-T Compare With Atorvastatin in Cardiometabolic Research Models

September 3, 2026/0 Comments/in Uncategorized/by

Cardiovascular disease remains the leading cause of death globally, yet the pharmacological toolkit has barely changed in three decades. Atorvastatin, introduced in 1996, still anchors most lipid-lowering protocols worldwide. Against that backdrop, the question driving cardiometabolic researchers in 2026 is pointed: can next-generation peptide agents like retatrutide redefine what "heart-protective" means in preclinical and clinical research models? The comparison of peptides vs classic heart drugs, specifically how GLP-3 retatrutide and GLP-2-T compare with atorvastatin in cardiometabolic research models, is now one of the most actively discussed topics in metabolic medicine.

Key Takeaways

  • Atorvastatin targets a single enzymatic pathway (HMG-CoA reductase) to lower LDL; retatrutide acts across GLP-1, GIP, and glucagon receptors simultaneously.
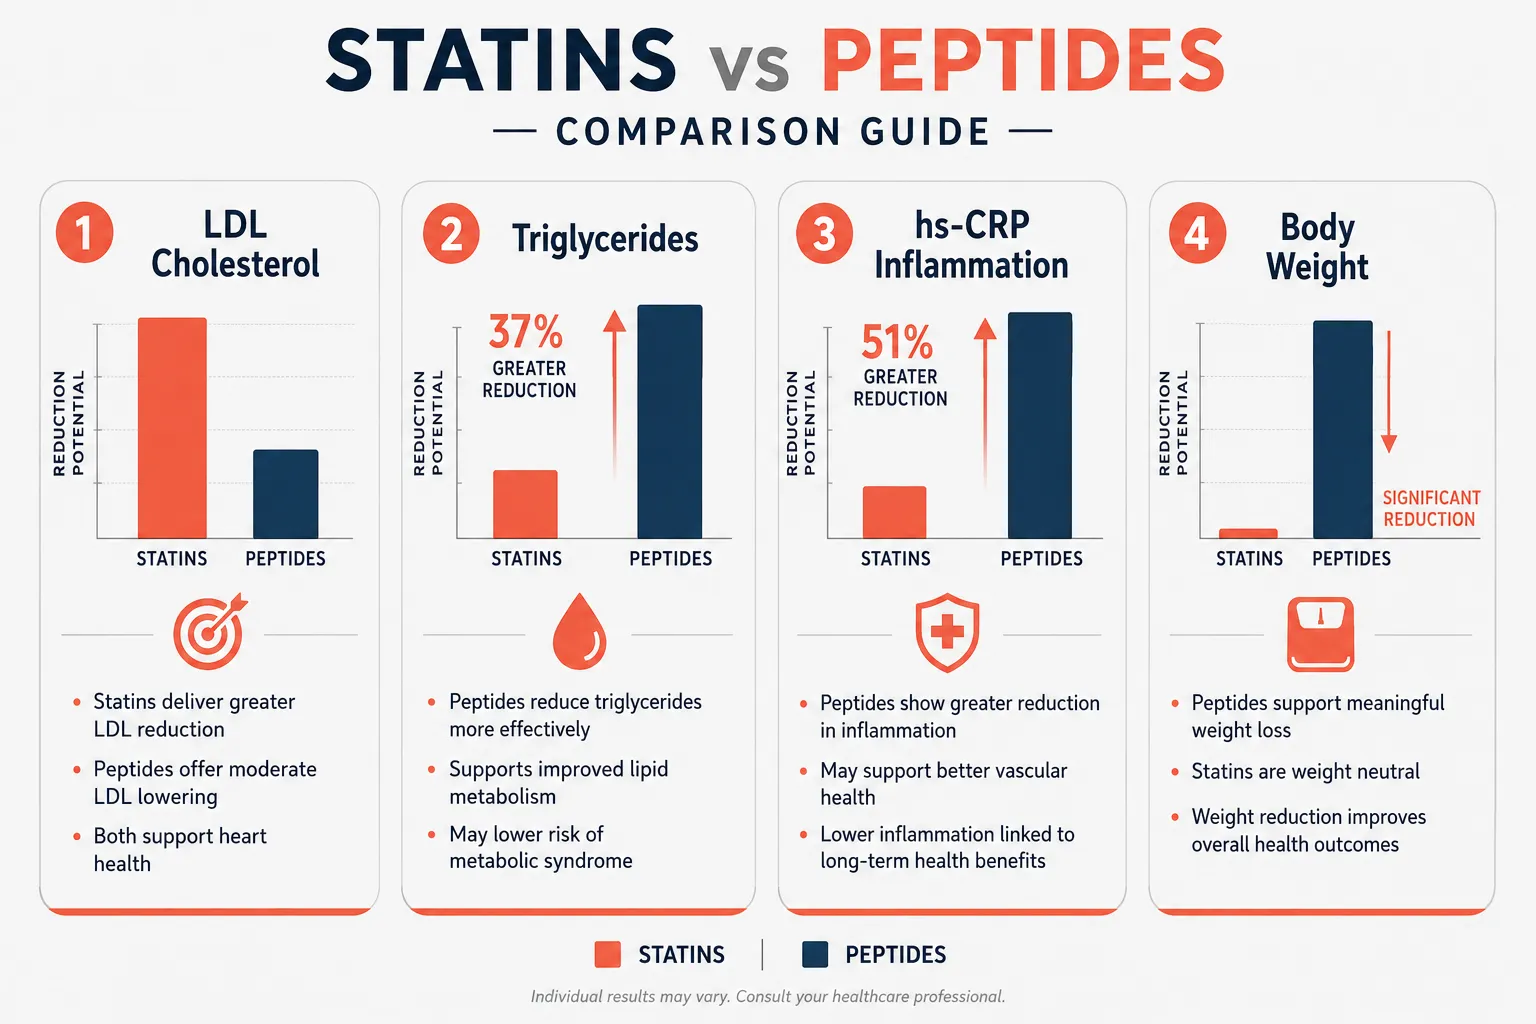
  • In phase 3 research models, retatrutide produced a 37% drop in triglycerides, a 51% reduction in hs-CRP, and a 17% fall in non-HDL cholesterol over 80 weeks.
  • No published head-to-head trial directly compares retatrutide or GLP-2-T with atorvastatin in atherosclerotic outcome models as of 2026.
  • The large TRIUMPH-OUTCOMES cardiovascular outcomes trial is underway and will provide harder endpoint data over approximately 248 weeks.
  • Researchers studying synergistic metabolic effects are increasingly interested in whether peptide-statin combinations could outperform either agent alone.

How Atorvastatin Works: The Classic Statin Mechanism

Atorvastatin belongs to the statin class of drugs, which function by inhibiting HMG-CoA reductase, the rate-limiting enzyme in hepatic cholesterol synthesis. By blocking this enzyme, the liver upregulates LDL receptor expression, pulling more LDL particles from circulation. The result is a well-documented 35-55% reduction in LDL cholesterol, modest triglyceride lowering, and modest HDL elevation.

How Atorvastatin Works: The Classic Statin Mechanism

Statins also carry pleiotropic effects, anti-inflammatory, antioxidant, and endothelial-stabilizing properties, that appear to extend cardiovascular protection beyond simple LDL reduction. However, the mechanism remains fundamentally narrow: one enzyme, one primary lipid target. This single-pathway approach is highly effective for LDL management but leaves other cardiometabolic risk factors, visceral adiposity, systemic inflammation, hyperglycemia, elevated triglycerides, largely unaddressed.

"Statins changed cardiology. But they were never designed to manage obesity, insulin resistance, or the full inflammatory burden that drives modern cardiovascular risk."

Retatrutide and GLP-2-T: Multi-Receptor Peptide Mechanisms in Research Models

Retatrutide is a triple agonist that simultaneously activates GLP-1 (glucagon-like peptide-1), GIP (glucose-dependent insulinotropic polypeptide), and glucagon receptors. This multi-receptor engagement produces a cascade of cardiometabolic effects that no single classic drug replicates. Researchers exploring systemic peptide research have noted that this breadth of action is what separates the newer peptide class from statins mechanistically.

In phase 3 TRIUMPH-3 obesity research data reported in mid-2026, weekly retatrutide 12 mg over 80 weeks produced:

Cardiometabolic Marker Change Observed
Triglycerides -37%
Non-HDL cholesterol -17%
Systolic blood pressure -9.3 mmHg
Waist circumference -19 cm
hs-CRP (inflammation) -51%

A 2025 review of triple-agonist therapies noted LDL reductions of approximately 12-22% and total cholesterol reductions of 15-18%, alongside an estimated 82% reduction in hepatic steatosis. These lipid improvements exceeded those seen with dulaglutide 1.5 mg in certain comparisons.

GLP-2-T is a less-characterized agent in cardiometabolic literature. Current published reviews and trial registries through September 2026 do not describe a well-validated "GLP-2-T" compound with dedicated cardiovascular outcome data. Researchers working with therapeutic peptides should note this distinction: retatrutide has a robust and growing evidence base, while GLP-2-T remains at an earlier characterization stage in published cardiometabolic models.

Retatrutide and GLP-2-T: Multi-Receptor Peptide Mechanisms in Research Models

Peptides vs Classic Heart Drugs: Direct Comparison in Cardiometabolic Research Models

When examining peptides vs classic heart drugs, specifically how GLP-3 retatrutide and GLP-2-T compare with atorvastatin in cardiometabolic research models, one critical fact stands out: no published head-to-head clinical or preclinical trial directly compares retatrutide with atorvastatin on atherosclerotic or cardiovascular outcome endpoints as of 2026.

What the evidence does allow is a mechanistic and biomarker-level comparison:

  • LDL reduction: Atorvastatin leads clearly, with 35-55% reductions vs retatrutide's 12-22%. For LDL-specific endpoints, statins remain the benchmark.
  • Triglycerides: Retatrutide's 35-40% reduction rivals or exceeds what statins typically achieve (15-30% in most models).
  • Systemic inflammation (hs-CRP): Retatrutide's 51% hs-CRP reduction is striking. Statins produce modest hs-CRP reductions, typically 15-25%.
  • Body weight and adiposity: Retatrutide produces substantial weight loss; statins have no meaningful effect on body weight.
  • Hepatic steatosis: Retatrutide's estimated 82% reduction in hepatic fat has no statin equivalent.

Those interested in semaglutide vs retatrutide comparisons will find that retatrutide's multi-receptor profile produces broader cardiometabolic shifts than earlier GLP-1 mono-agonists as well.

The large TRIUMPH-OUTCOMES trial (NCT06383390) is currently underway, designed to assess time to first major cardiovascular composite endpoint, including nonfatal myocardial infarction, nonfatal stroke, cardiovascular death, and heart-failure hospitalization, over approximately 248 weeks. Commentaries on TRIUMPH-3 data acknowledge that while cardiovascular risk markers trend favorably, the trial was not statistically powered for hard outcome endpoints, and observed event counts were lower than anticipated.

Safety considerations also differ. Statins carry well-known risks of myopathy and hepatotoxicity at higher doses. Retatrutide, like other incretin-based agents, can elevate heart rate, and recent work has examined inotropic effects in isolated human atrial tissue, finding increased contractile force without a clear proarrhythmic signal at this stage. Researchers working on stress pathway research and cardiac tissue models will find this an active area of investigation.

Peptides vs Classic Heart Drugs: Direct Comparison in Cardiometabolic Research Models

Those designing research protocols involving metabolic peptides may also find value in reviewing tesa research as a parallel example of a peptide with documented visceral fat and lipid effects in clinical models.

Conclusion

The comparison of peptides vs classic heart drugs, examining how GLP-3 retatrutide and GLP-2-T compare with atorvastatin in cardiometabolic research models, reveals a clear pattern: these are complementary rather than competing mechanisms. Atorvastatin remains superior for LDL reduction through a proven, targeted enzymatic block. Retatrutide, by contrast, addresses the broader cardiometabolic risk cluster, triglycerides, inflammation, visceral fat, hepatic steatosis, and blood pressure, through simultaneous multi-receptor engagement.

Actionable next steps for researchers in 2026:

  1. Monitor TRIUMPH-OUTCOMES trial results as they emerge over the next several years for hard cardiovascular endpoint data on retatrutide.
  2. Design combination model studies that pair statin-class LDL lowering with peptide-mediated inflammatory and adiposity endpoints to assess additive or synergistic effects.
  3. Treat GLP-2-T as a hypothesis-stage comparator until dedicated cardiometabolic outcome data appears in peer-reviewed literature.
  4. Ensure any peptide compounds used in research meet rigorous purity standards, resources on third party peptide testing provide useful guidance on verification protocols.
  5. Explore single peptide vs stack research designs to understand whether multi-agonist peptides offer advantages over sequential or combined classic drug regimens.

The next chapter in cardiometabolic research will likely not be about choosing between peptides and classic drugs, it will be about understanding precisely how each fits within an integrated, multi-target approach to cardiovascular risk reduction.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/peptides-vs-classic-heart-drugs-how-glp-3-retatrutide-and-glp-2-t-compare-with-a.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-03 13:05:252026-09-03 13:05:25Peptides vs Classic Heart Drugs: How GLP-3 Retatrutide and GLP-2-T Compare With Atorvastatin in Cardiometabolic Research Models
Where to Buy Research‑Grade GLP-3 Retatrutide and GLP-2-T Peptides: Purity, Certificates of Analysis, and Vendor Red Flags

Where to Buy Research‑Grade GLP-3 Retatrutide and GLP-2-T Peptides: Purity, Certificates of Analysis, and Vendor Red Flags

September 2, 2026/0 Comments/in Uncategorized/by

Fewer than 1 in 10 grey-market peptide vials tested by independent safety laboratories in 2026 matched the purity levels stated on their labels, a sobering statistic for any researcher sourcing GLP-class compounds. Understanding where to buy research-grade GLP-3 retatrutide and GLP-2-T peptides requires far more than a vendor comparison; it demands a working knowledge of purity standards, Certificate of Analysis (COA) interpretation, and the regulatory minefield that now surrounds these molecules.

Key Takeaways

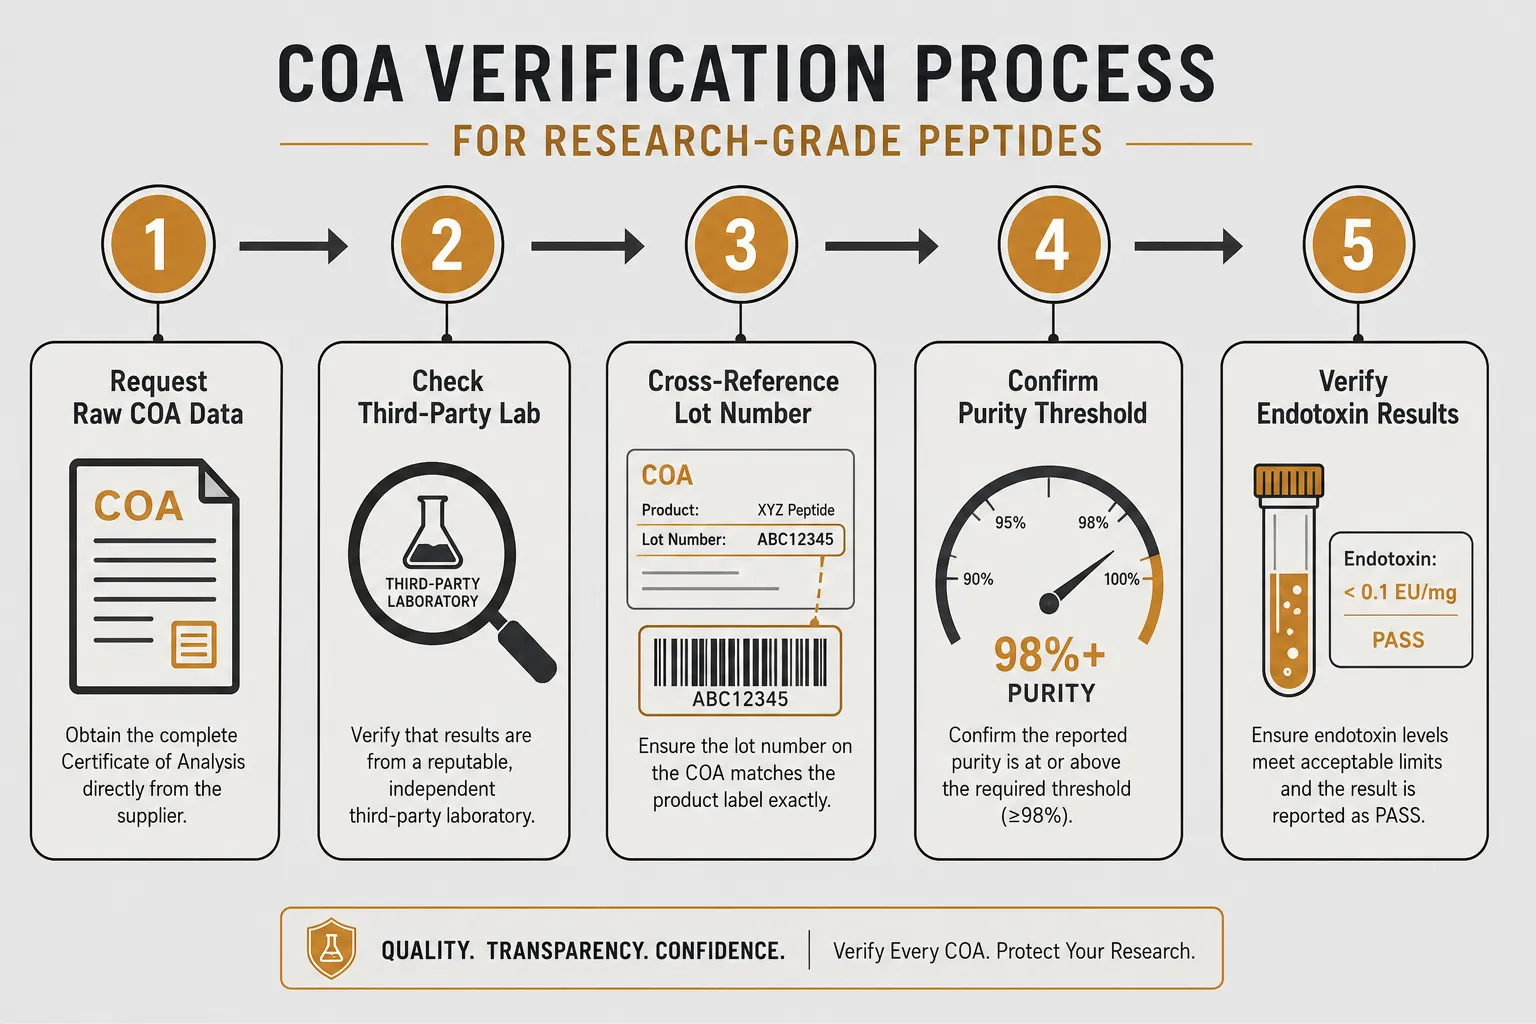
  • Retatrutide remains an investigational triple agonist with no FDA approval; any vendor selling it "for research use" while marketing human dosing protocols is operating in legally dangerous territory.
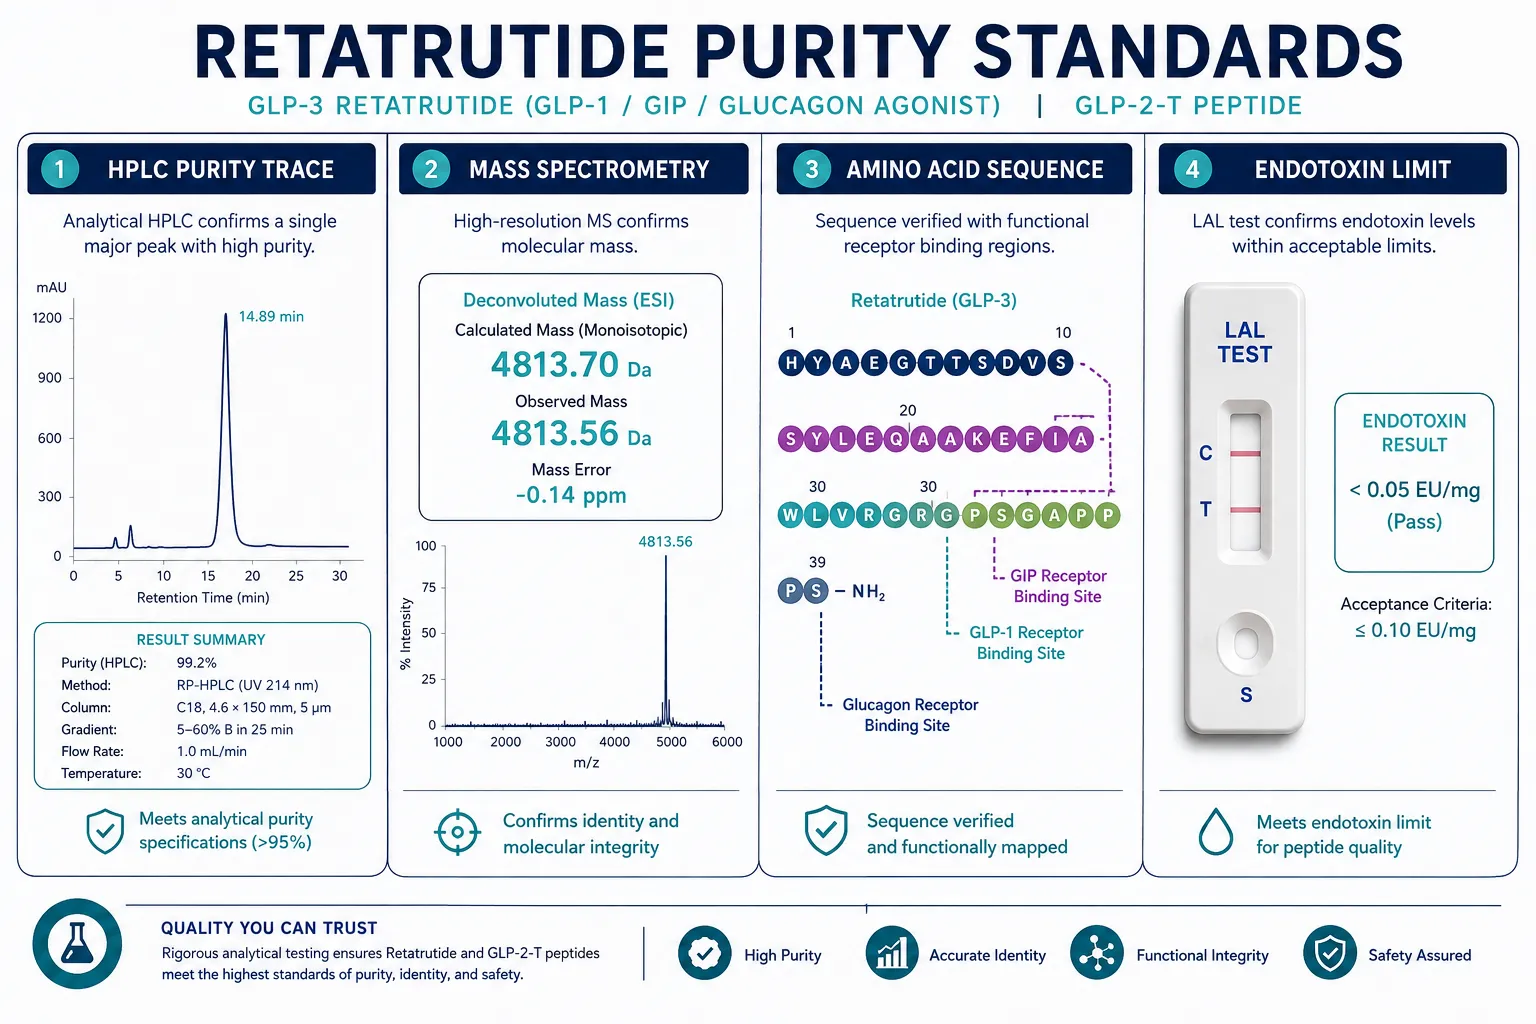
  • A valid COA must include HPLC purity data, mass spectrometry confirmation, and endotoxin testing from an identifiable third-party laboratory.
  • Black-market retatrutide consistently underperforms clinical-trial benchmarks, suggesting inferior formulations or outright counterfeiting.
  • GLP-2-T (a truncated GLP-2 analog) requires the same rigorous purity verification as full-length GLP-class peptides, including sequence confirmation.
  • Vendor red flags, dose regimens, patient testimonials, and no lot-traceable COAs, are disqualifying criteria for legitimate research procurement.

Understanding GLP-3 Retatrutide and GLP-2-T in a Research Context

Understanding GLP-3 Retatrutide and GLP-2-T in a Research Context

Retatrutide, developed by Eli Lilly, is a once-weekly triple agonist peptide targeting three receptors simultaneously: GIP, GLP-1, and glucagon. Phase III TRIUMPH trial data published in 2026 showed weight reductions of approximately 28 to 30 percent, placing it among the most potent metabolic peptides ever evaluated. Despite this, retatrutide holds no regulatory approval anywhere in the world as of August 2026. The only sanctioned access pathway is a tightly controlled expanded-access protocol (ClinicalTrials.gov NCT07629401) requiring documented failure of standard GLP-1/GIP therapies and significant obesity-related comorbidities, a far cry from open vendor sales.

GLP-2-T refers to truncated analogs of glucagon-like peptide-2, studied primarily for intestinal repair and mucosal recovery. Researchers exploring tissue recovery research often source GLP-2-T alongside longer-chain GLP-class peptides, making purity verification equally critical for both compound types.

"Any vendor advertising retatrutide with weight-loss protocols or patient testimonials is not operating as a legitimate research supplier, full stop."

The distinction between the Lilly investigational drug and the "GLP-3 retatrutide" sold by peptide vendors matters enormously. The term "GLP-3" is an informal label used in research communities; it is not an approved pharmacological designation. Researchers must treat any sourced material as a synthetic analog requiring independent verification, not as the clinical compound.

Purity Standards and COA Interpretation for GLP-Class Peptides

Purity Standards and COA Interpretation for GLP-Class Peptides

When evaluating where to buy research-grade GLP-3 retatrutide and GLP-2-T peptides, the Certificate of Analysis is the single most important document a vendor can provide. A legitimate COA is not a one-page marketing sheet, it is a traceable analytical report with the following components:

Minimum COA Requirements

Analysis Type Acceptable Standard What to Check
HPLC Purity Greater than or equal to 98% Peak area percentage, not just a stated number
Mass Spectrometry Molecular weight confirmation Must match theoretical MW of the sequence
Amino Acid Analysis Sequence verification Confirms correct residue composition
Endotoxin Testing Less than 1 EU/mg (research grade) LAL or rFC method, not absent from report
Appearance White to off-white lyophilized powder Visual and physical description included

Third-party versus in-house testing is a critical distinction. A COA generated by the same facility that synthesized the peptide carries significantly less weight than one issued by an independent analytical laboratory. The report should name the testing lab, include a lot number, and provide a date of analysis. Researchers should cross-reference the lot number against the vial label before use.

For signaling peptides and longer-chain analogs like retatrutide (39 amino acids), mass spectrometry confirmation is non-negotiable. Shorter peptides can occasionally pass HPLC with truncated sequences; MS data closes that gap.

Solvent and reconstitution data should also appear in supporting documentation. GLP-class peptides are typically reconstituted in sterile water or bacteriostatic water with acetic acid at low concentrations. Vendors that provide no guidance, or worse, recommend DMSO for injectable-grade research, signal a lack of formulation expertise.

Vendor Red Flags and the Regulatory Landscape in 2026

Vendor Red Flags and the Regulatory Landscape in 2026

The regulatory environment around research peptide vendors shifted dramatically in mid-2026. Eli Lilly filed six federal lawsuits against named vendors, including Aesthetic Envy, Astra Peptides, Legendary Peptides, Striker Pharmacy, Texas Peptides, and Lone Star Peptide, alleging that each marketed retatrutide for human consumption while labeling it "for research use only." Four of these defendants were explicitly classified as research-use peptide sellers who allegedly crossed into unapproved clinical application. This legal action defines the clearest possible red-flag checklist for researchers evaluating where to buy research-grade GLP-3 retatrutide and GLP-2-T peptides.

Disqualifying vendor behaviors include:

  • Publishing dose escalation protocols or injection schedules for human use
  • Displaying before-and-after weight-loss testimonials
  • Offering "medical consultations" or telehealth referrals alongside peptide sales
  • Providing COAs without named third-party laboratories or lot numbers
  • Selling retatrutide at prices inconsistent with legitimate synthesis costs for a 39-amino-acid peptide

Independent lab testing of black-market retatrutide in 2026 found that users outside clinical trials averaged weight loss of 3.6%, 7.1%, and 9.2% at measured intervals, compared to 5.7%, 11.9%, and 15.5% in formal trials. The gap strongly suggests inferior synthesis quality, incorrect sequences, or diluted formulations. Researchers relying on substandard material introduce uncontrolled variables that invalidate experimental results.

Legitimate research-grade vendors operate transparently. They restrict sales to verified research institutions, provide downloadable COAs with lot-traceable data, and do not market human applications. Researchers sourcing truncated peptide analogs or exploring somatotropin research alongside GLP-class compounds should apply identical scrutiny across all sourced materials. For additional context on evaluating peptide vendors, the guide on where to buy SS31 and Epithalon online offers a parallel framework applicable to GLP-class procurement.

Conclusion

Sourcing research-grade GLP-3 retatrutide and GLP-2-T peptides in 2026 demands a disciplined, evidence-based approach. The regulatory landscape has made clear that the line between "research use" and unapproved human administration is both legally enforced and scientifically consequential.

Actionable next steps for researchers:

  1. Require a third-party COA with HPLC purity at or above 98%, MS confirmation, and endotoxin data before placing any order.
  2. Verify the testing laboratory by name, search its accreditation independently.
  3. Cross-reference lot numbers between the COA and the physical vial upon receipt.
  4. Reject any vendor displaying human dosing protocols, testimonials, or telehealth referrals.
  5. Document the procurement chain for institutional compliance and reproducibility records.

Research integrity begins at the point of purchase. Applying a rigorous vendor-evaluation framework protects both experimental validity and institutional standing.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/where-to-buy-research-grade-glp-3-retatrutide-and-glp-2-t-peptides-purity-certif.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-02 13:04:092026-09-02 13:04:09Where to Buy Research‑Grade GLP-3 Retatrutide and GLP-2-T Peptides: Purity, Certificates of Analysis, and Vendor Red Flags
Tesofensine vs GLP-3 Peptides in Metabolic Research: How Labs Decide Which Compounds to Order

Tesofensine vs GLP-3 Peptides in Metabolic Research: How Labs Decide Which Compounds to Order

August 29, 2026/0 Comments/in Uncategorized/by

Only about 5% of obesity drug candidates that enter clinical development ever reach approval, a statistic that shapes every procurement decision a metabolic research lab makes. When evaluating Tesofensine vs GLP-3 Peptides in Metabolic Research: How Labs Decide Which Compounds to Order, the choice is rarely simple. It hinges on mechanistic goals, available evidence, translational potential, and practical sourcing factors that vary from lab to lab.

Key Takeaways

  • Tesofensine is a triple monoamine reuptake inhibitor with CNS-driven appetite suppression; GLP-based peptides act peripherally and centrally through incretin pathways.
  • GLP-1 receptor agonists and next-generation multi-agonists carry deeper clinical evidence and broader cardiometabolic endpoints than tesofensine.
  • Tesofensine remains a valid niche tool for labs studying central monoamine systems and appetite neuroscience.
  • Evidence depth, regulatory trajectory, and endpoint specificity are the three primary filters labs use when ordering compounds.
  • Sourcing quality, purity certification, stability data, and vendor transparency, is equally critical for both compound classes.

Understanding the Two Compound Classes

Understanding the Two Compound Classes

Before any procurement decision is made, researchers need a clear picture of what each compound actually does at the receptor level.

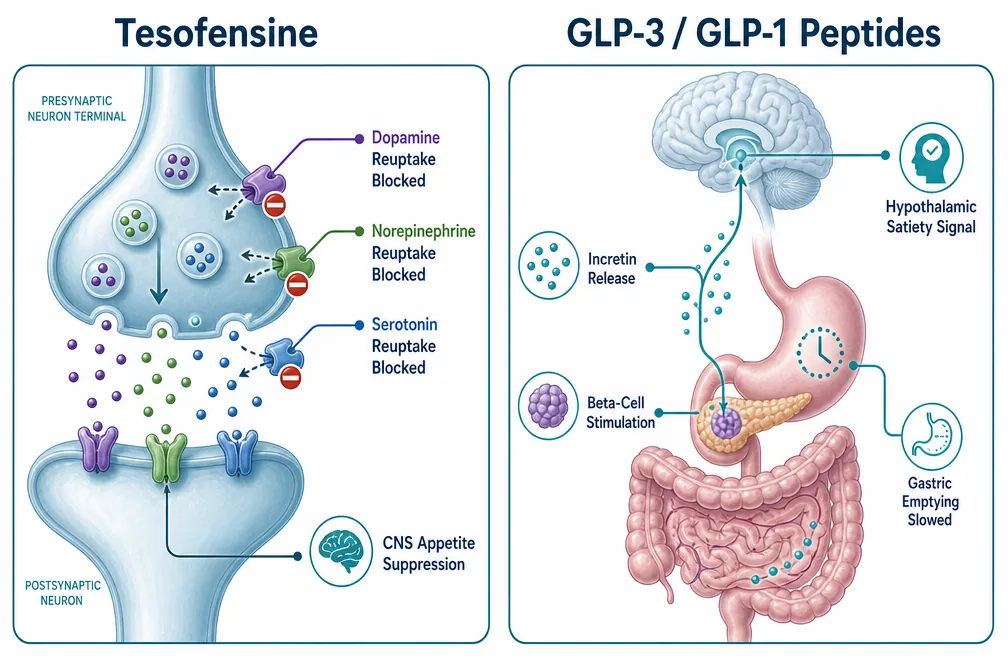
Tesofensine is a small-molecule triple reuptake inhibitor. It blocks the reuptake of dopamine, norepinephrine, and serotonin simultaneously, producing appetite suppression primarily through central nervous system pathways. Early monotherapy trials showed meaningful reductions in body weight, but cardiovascular signals, including elevated heart rate and blood pressure, slowed development. The Tesomet combination (tesofensine plus metoprolol) was designed to blunt those cardiovascular effects, and small trials have shown moderate but consistent weight loss. Pipeline analysts currently classify Tesomet as an early-stage anti-obesity candidate with modest efficacy compared to newer agents.

GLP-3 and related GLP-based peptides operate through a fundamentally different mechanism. GLP-1 receptor agonists stimulate incretin release, slow gastric emptying, activate hypothalamic satiety circuits, and promote insulin secretion in a glucose-dependent manner. Compounds such as retatrutide, a triple GLP-1/GIP/glucagon receptor co-agonist, represent the frontier of this class. For a deeper breakdown of how GLP-1, GLP-2, and GLP-3 relate to each other mechanistically, the GLP-3, GLP-1, and GLP-2 explained: a researcher's guide to the peptide family provides essential context.

"Mechanistic focus is the first filter. A lab studying central reward circuitry may legitimately need tesofensine. A lab studying cardiometabolic risk almost certainly needs a GLP-based agent."

Comparing Evidence Depth and Research Endpoints

Comparing Evidence Depth and Research Endpoints

When evaluating Tesofensine vs GLP-3 Peptides in Metabolic Research: How Labs Decide Which Compounds to Order, evidence depth is the most decisive factor for most labs.

Efficacy and Clinical Data

Factor Tesofensine GLP-Based Peptides
Weight loss magnitude Moderate Substantial to large
Cardiometabolic endpoints Limited Broad and well-documented
Translational pipeline depth Early-stage Advanced, multi-indication
Safety profile clarity Concerns noted Known, manageable
Multi-agonist variants None Tirzepatide, retatrutide, others

GLP-1 receptor agonists deliver larger, better-documented weight loss outcomes and cardiometabolic benefits than tesofensine across multiple trial populations. Pharmacovigilance data show known but manageable safety profiles for GLP-1 RAs, which reassures translational researchers planning longer study windows. Dual and multi-agonist GLP-based drugs, tirzepatide being the clearest example, have set a translational gold standard that newer lab programs aim to replicate or surpass.

Tesofensine's evidence base, while real, is narrower. Its value lies specifically in CNS-focused research: appetite neuroscience, reward pathway modulation, and monoamine system studies. Labs focused on those endpoints will find tesofensine uniquely suited. Labs pursuing metabolic syndrome, insulin resistance, or cardiovascular risk reduction will find GLP-based peptides far more aligned with their endpoints.

For researchers exploring GLP-1 peptide sourcing concepts and generational research notes, understanding how the evidence base has evolved across GLP generations is essential before finalizing compound orders.

How Labs Decide Which Compounds to Order: A Practical Framework

How Labs Decide Which Compounds to Order: A Practical Framework

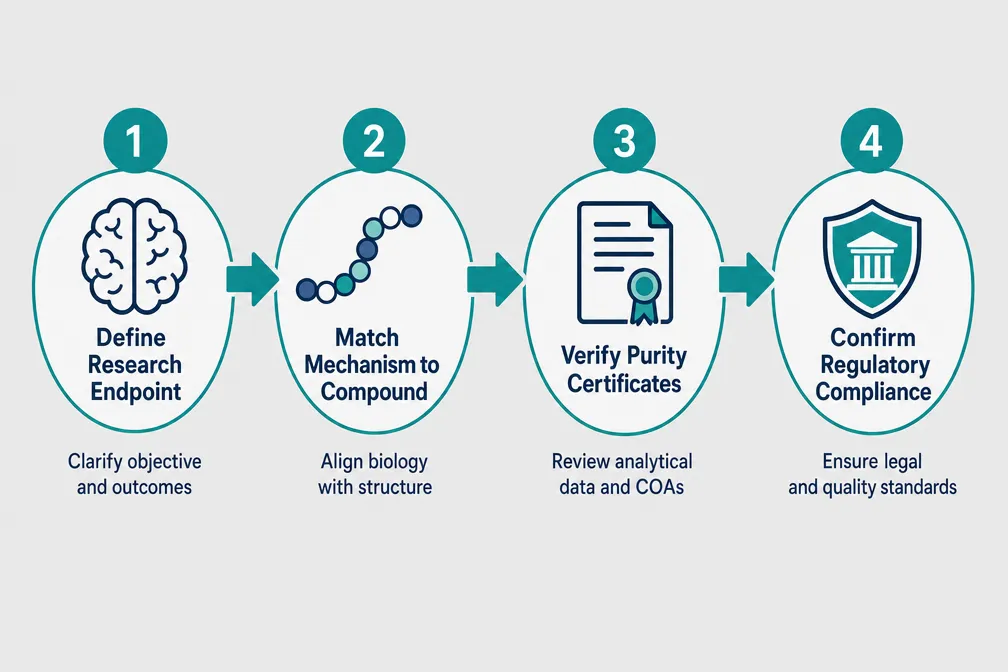
The practical side of Tesofensine vs GLP-3 Peptides in Metabolic Research: How Labs Decide Which Compounds to Order comes down to four structured decision points.

Step 1: Define the Research Endpoint

Labs must ask: Is the primary endpoint CNS-driven (appetite, reward, monoamine tone) or peripheral/metabolic (insulin sensitivity, body composition, cardiovascular markers)? CNS-focused endpoints favor tesofensine. Metabolic endpoints favor GLP-based peptides.

Step 2: Match Mechanism to Compound

Once the endpoint is clear, mechanism alignment follows naturally. Researchers studying hormone research compounds will recognize that GLP-based agents interact with incretin hormones in ways tesofensine simply does not. Conversely, monoamine reuptake inhibition cannot be replicated by any GLP-based compound.

Step 3: Evaluate Regulatory and Commercial Trajectory

Regulatory and commercial trajectories strongly push labs toward GLP-1-aligned programs. Labs seeking translational relevance, where preclinical data might eventually inform clinical development, will find GLP-based agents far better positioned. Next-generation GLP-based co-agonists and biased agonists are at the forefront of cutting-edge metabolic research investment globally.

Step 4: Verify Sourcing Quality

Regardless of which compound a lab selects, purity certification is non-negotiable. For peptide-based compounds, researchers should confirm:

  • Certificate of Analysis (CoA) with HPLC purity data
  • Mass spectrometry confirmation of molecular identity
  • Stability and storage specifications matched to the lab's conditions
  • Vendor transparency regarding synthesis methods

Labs sourcing GLP-class compounds can explore GLP-1 peptides available for research and review buy GLP-1 peptides options to compare available research-grade formulations. For broader compound discovery, all peptides for sale provides a wider catalog view. Understanding polypeptide peptides and drug mechanisms can also help researchers contextualize how each compound class fits within broader pharmacological frameworks.

The Short-Term Outlook for Each Compound Class

As of 2026, GLP-based agents remain the default ordering choice for the majority of metabolic research labs. The evidence base is deeper, the translational pipeline is more active, and regulatory momentum clearly favors incretin-based approaches. Tesofensine occupies a legitimate but narrow niche, valuable for CNS appetite research, less relevant for labs chasing cardiometabolic endpoints.

Labs should also monitor emerging hormone research developments, as the intersection of incretin biology and neuroendocrine signaling continues to generate new compound candidates that may eventually bridge both mechanistic worlds.

Conclusion

The decision between tesofensine and GLP-3 peptides is not a matter of one compound being universally superior. It is a matter of alignment, between the compound's mechanism and the lab's specific research question.

Actionable next steps for research teams:

  1. Audit current study endpoints before placing any compound order.
  2. If endpoints are metabolic or cardiometabolic, prioritize GLP-based peptides with documented multi-agonist profiles.
  3. If endpoints involve CNS appetite circuits or monoamine systems, evaluate tesofensine as a targeted tool.
  4. Require full CoA documentation and mass spectrometry data from any vendor.
  5. Stay current with pipeline developments, the GLP-based compound landscape is evolving rapidly in 2026.

Compound selection is a scientific decision first, and a sourcing decision second. Getting the order right on both counts is what separates rigorous metabolic research from inconclusive results.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/tesofensine-vs-glp-3-peptides-in-metabolic-research-how-labs-decide-which-compou.webp 672 1008 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-29 13:04:292026-08-29 13:04:29Tesofensine vs GLP-3 Peptides in Metabolic Research: How Labs Decide Which Compounds to Order
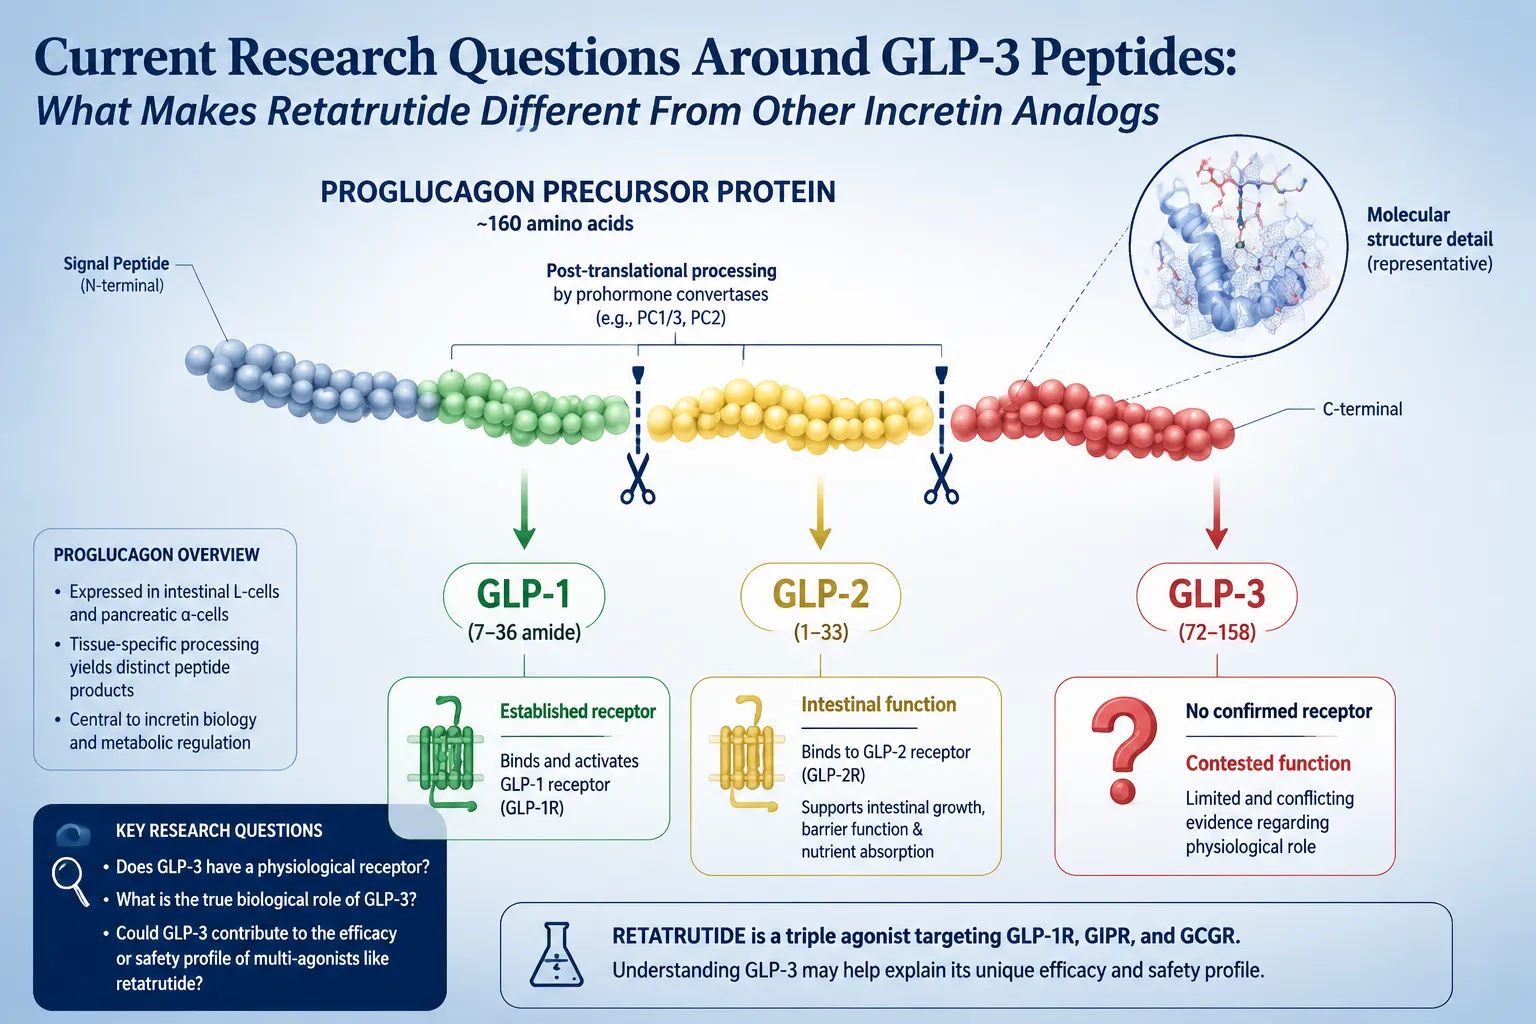
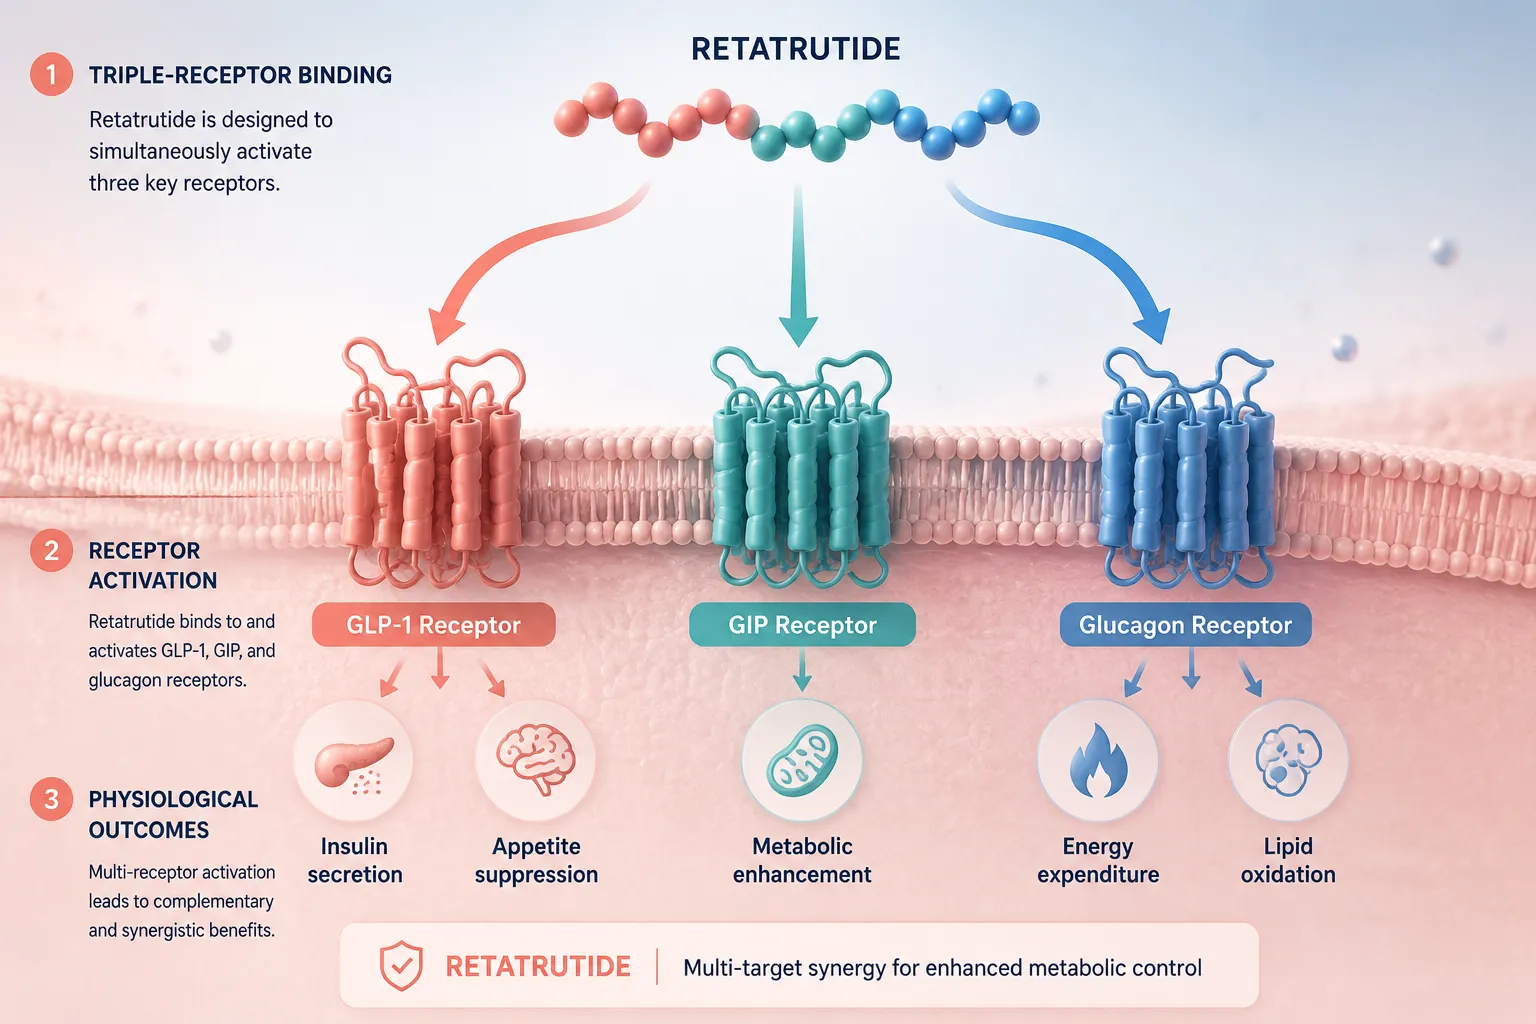
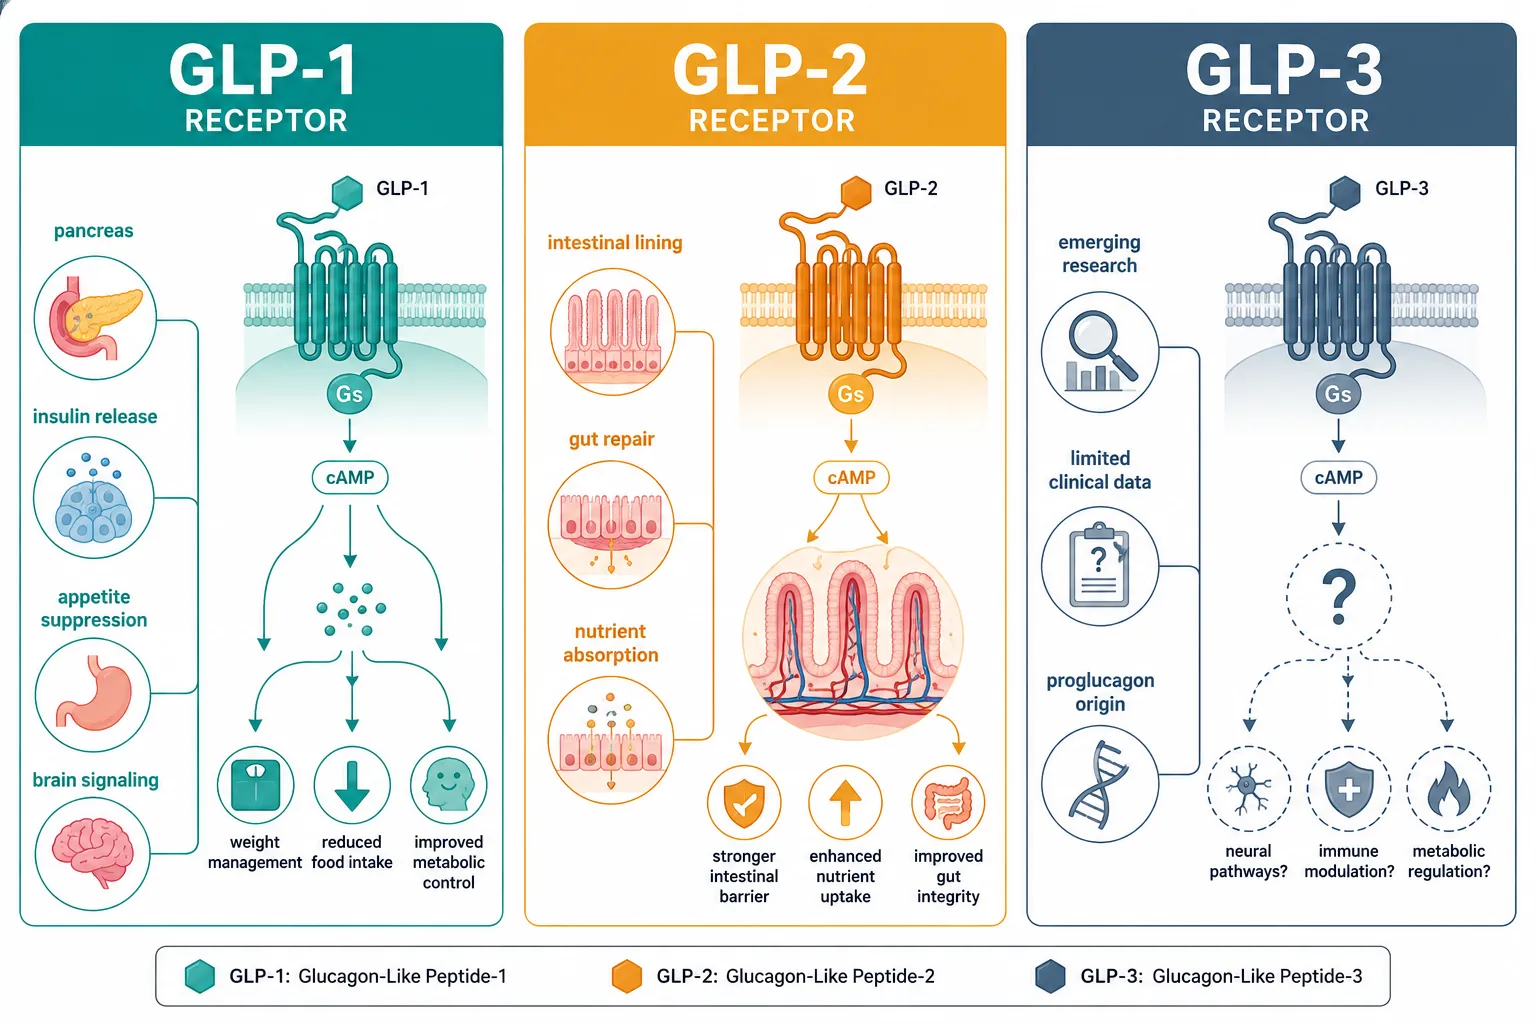
Current Research Questions Around GLP-3 Peptides: What Makes Retatrutide Different From Other Incretin Analogs

Current Research Questions Around GLP-3 Peptides: What Makes Retatrutide Different From Other Incretin Analogs

August 21, 2026/0 Comments/in Uncategorized/by

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'Current Research Questions Around GLP-3' in crisp white sans-serif on a deep teal semi-transparent overlay panel, centered with 8% safe margins from every edge. Background: high-resolution editorial illustration of a molecular peptide chain structure with triple-receptor binding sites rendered in luminous blue and gold against a clean dark navy gradient, suggesting advanced biochemical research. Magazine cover aesthetic, pharmaceutical science editorial quality, modern bold typography, no characters touching edges.","content":["Annotated mechanism-of-action diagram, landscape format (1536×1024): central illustration of a stylized human torso cross-section showing three receptor sites labeled 'GLP-1 Receptor,' 'GIP Receptor,' and 'Glucagon Receptor' with color-coded callout lines in teal, amber, and coral. Left panel heading: 'Single Agonist GLP-1' with 3 bullet labels: 'One receptor target,' 'Appetite suppression,' 'Insulin release.' Right panel heading: 'Triple Agonist Retatrutide' with 4 bullet labels: 'Three receptor targets,' 'Enhanced fat oxidation,' 'Glucagon modulation,' 'Broader metabolic reach.' Clean white background, medical-illustration style, navy-and-teal palette, editorial infographic polish.","Split-screen landscape format (1536×1024) editorial comparison: left half shows a simplified molecular diagram of semaglutide binding to a single GLP-1 receptor node, labeled 'Dual or Single Agonist' with sub-labels 'GLP-1 only' and 'Tirzepatide: GLP-1 + GIP.' Right half shows retatrutide binding to three glowing receptor nodes in a triangular arrangement, labeled 'Triple Agonist' with sub-labels 'GLP-1,' 'GIP,' 'Glucagon.' Bold dividing line down the center, cool blue left palette contrasting warm amber-gold right palette, crisp scientific illustration style, high-contrast editorial quality, no pricing or checkmark grids.","Numbered step-by-step research framework flow diagram, landscape format (1536×1024): five horizontally arranged research-question cards on a clean light-gray background. Card 1 labeled 'Receptor Selectivity' with sub-label 'Relative agonist ratios.' Card 2 labeled 'Durability' with sub-label 'Long-term weight maintenance.' Card 3 labeled 'GI Tolerability' with sub-label 'Triple-agonist side effects.' Card 4 labeled 'CV Outcomes' with sub-label 'MACE endpoint data.' Card 5 labeled 'Real-World Use' with sub-label 'Adherence and titration.' Connecting arrows between cards, teal accent color on card headers, navy body text, clean sans-serif typography, editorial medical-research infographic style, fully inside 5% safe margins."]

Professional landscape hero image () with a reading "Current Research Questions Around GLP-3". CRITICAL TYPOGRAPHY RULES:

Only one in three adults with obesity achieves durable weight loss through lifestyle intervention alone, a statistic that has driven a decade of accelerating research into incretin-based pharmacotherapy. At the frontier of that work sits retatrutide, a molecule that has forced researchers to reframe the current research questions around GLP-3 peptides: what makes retatrutide different from other incretin analogs is not just its potency, but the fundamental complexity it introduces into receptor biology, trial design, and long-term outcome prediction.

Key Takeaways

  • Retatrutide is a triple agonist targeting GLP-1, GIP, and glucagon receptors simultaneously, distinguishing it from single and dual incretin analogs.
  • Phase 2 data showed weight loss exceeding 24% over 48 weeks, surpassing earlier benchmarks set by semaglutide and tirzepatide.
  • The glucagon receptor arm introduces unique metabolic and hepatic effects not seen in GLP-1 or dual GIP/GLP-1 agents.
  • Open research questions center on receptor selectivity ratios, long-term durability, cardiovascular endpoints, and GI tolerability at scale.
  • Phase 3 TRIUMPH obesity trial data emerging in 2026 is actively reshaping how researchers define "third-generation" incretin therapy.

What Is a GLP-3 Peptide and Where Does the Term Come From

The label "GLP-3" circulates in research literature and supplement markets, but its meaning is contested. Glucagon-like peptide-3 refers to a cleavage product of proglucagon, the same precursor protein that yields GLP-1 and GLP-2. Unlike GLP-1, GLP-3 has no confirmed endogenous receptor and no established pharmacological action in humans as of 2026. This makes the term a source of genuine naming confusion in the research community.

For a deeper look at how GLP-2 naming conventions create similar product-label problems, the article on GLP2-T peptide and GLP2 Tirz peptide naming confusion is a useful reference. Understanding peptide classification frameworks helps clarify why these distinctions matter in both research and procurement contexts.

What Is a GLP-3 Peptide and Where Does the Term Come From

The practical implication: when researchers discuss "GLP-3 activity" in the context of retatrutide, they are typically using the term loosely to describe the glucagon receptor component of the triple-agonist mechanism, not a discrete GLP-3 receptor pathway. Precision in terminology is a live methodological debate.

How the Triple-Agonist Mechanism Sets Retatrutide Apart

The central question in current research questions around GLP-3 peptides, what makes retatrutide different from other incretin analogs, comes down to receptor architecture.

Single agonists like semaglutide act exclusively on the GLP-1 receptor, driving insulin secretion, appetite suppression, and gastric slowing. Dual agonists like tirzepatide add GIP receptor co-activation, which appears to amplify fat cell lipolysis and improve insulin sensitivity beyond GLP-1 alone. Retatrutide adds a third arm: glucagon receptor agonism.

Compound GLP-1 GIP Glucagon Receptor
Semaglutide Yes No No
Tirzepatide Yes Yes No
Retatrutide Yes Yes Yes

The glucagon receptor component is where most open research questions cluster. Glucagon is classically associated with raising blood glucose, the opposite of what metabolic therapies aim to achieve. Yet at the specific agonist ratios engineered into retatrutide, glucagon receptor activation appears to drive hepatic fat oxidation and thermogenesis without clinically significant hyperglycemia in trial populations. Whether this balance holds across diverse real-world populations remains an active area of investigation.

Researchers exploring metabolic peptide mechanisms may also find value in reviewing top research peptides for metabolic health to contextualize where triple agonism sits relative to other investigated compounds.

How the Triple-Agonist Mechanism Sets Retatrutide Apart

Key Research Questions Shaping the 2026 Trial Landscape

The current research questions around GLP-3 peptides: what makes retatrutide different from other incretin analogs cannot be answered by efficacy data alone. Researchers are working through several interconnected frameworks.

1. Optimal receptor selectivity ratios
Retatrutide's glucagon agonism is intentionally partial. A core question is whether the current ratio of GLP-1:GIP:glucagon activity is optimal, or whether future analogs should titrate these ratios differently for specific indications such as type 2 diabetes versus pure obesity management.

2. Long-term weight durability
Phase 2 data showed mean weight loss above 24% at 48 weeks, a figure that exceeded both semaglutide and tirzepatide benchmarks. However, durability after discontinuation remains poorly characterized. Early 2026 TRIUMPH trial data is beginning to address this, but multi-year follow-up is still needed.

3. Hepatic and MASLD endpoints
The glucagon receptor arm may offer distinct advantages in metabolic dysfunction-associated steatotic liver disease. Detailed discussion of this angle appears in the dedicated article on retatrutide and MASLD triple-agonist research.

4. Cardiovascular outcomes
Phase 3 data from the cardiovascular outcomes arm, with results emerging in mid-2026, is examining major adverse cardiovascular events (MACE). This is a critical gap because GLP-1 agents have established CV benefits, but the glucagon component introduces theoretical concerns about heart rate and blood pressure that require dedicated endpoint adjudication.

5. GI tolerability at scale
Triple agonism amplifies the nausea, vomiting, and diarrhea profile common to GLP-1 class drugs. Titration protocols in TRIUMPH have been refined to manage this, but discontinuation rates in broader populations, including those with comorbidities, remain a research priority.

6. Comparative effectiveness versus tirzepatide
No head-to-head randomized controlled trial between retatrutide and tirzepatide exists as of 2026. Indirect comparisons from separate trials carry significant methodological limitations, making this one of the most cited gaps in the incretin literature.

Key Research Questions Shaping the 2026 Trial Landscape

Researchers interested in how peptide measurement standards affect endpoint reliability will find that assay consistency is a recurring methodological concern across all three agonist pathways. For context on how other metabolic peptides are evaluated, the AOD 9604 research method notes on storage and traceability illustrate the quality-control demands that apply broadly to research-grade compounds.

What "Third-Generation" Incretin Therapy Actually Means

The phrase "third-generation incretin" is increasingly used to describe retatrutide and similar multi-receptor candidates. The generational framing maps roughly as follows: first-generation equals GLP-1 mono-agonists; second-generation equals dual GLP-1/GIP agonists; third-generation equals triple agonists incorporating glucagon receptor activity.

"The shift from dual to triple agonism is not merely additive, it introduces qualitatively different metabolic signaling that requires new endpoints, new safety frameworks, and new comparative benchmarks."

This framing has practical implications for trial design. Standard obesity trials measuring body weight as a primary endpoint may underestimate the hepatic and thermogenic contributions of glucagon receptor agonism. Researchers are actively debating whether body composition, liver fat fraction, and resting energy expenditure should become co-primary endpoints in future triple-agonist studies.

Regulatory agencies in the US and EU are watching the 2026 Phase 3 readouts closely. If TRIUMPH delivers cardiovascular non-inferiority or superiority data, the approval pathway could accelerate significantly. Market analysts anticipate a potential regulatory submission by late 2026 or early 2027, though this remains speculative pending full data disclosure.

Conclusion

The current research questions around GLP-3 peptides, and what makes retatrutide different from other incretin analogs, extend well beyond weight loss percentages. The glucagon receptor dimension opens new mechanistic territory, raises legitimate safety questions, and demands more sophisticated trial designs than the incretin field has used previously.

Actionable next steps for researchers and clinicians following this space:

  • Track TRIUMPH trial publications as they emerge through 2026 for durability and cardiovascular endpoint data.
  • Evaluate receptor selectivity ratio data critically; not all triple agonists will carry the same risk-benefit profile.
  • Monitor head-to-head comparative trial announcements, as indirect comparisons with tirzepatide remain methodologically limited.
  • Apply rigorous peptide quality and measurement standards when working with any incretin-class compound in a research context.
  • Follow evolving regulatory guidance on composite endpoints for multi-receptor agonists, as endpoint definitions are still being standardized.

The science is moving fast. Staying grounded in mechanism-level questions, rather than headline efficacy numbers alone, is the most reliable way to interpret what comes next.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/current-research-questions-around-glp-3-peptides-what-makes-retatrutide-differen.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-21 13:04:452026-08-21 13:04:45Current Research Questions Around GLP-3 Peptides: What Makes Retatrutide Different From Other Incretin Analogs
Peptides and Polypeptides: Complete Research Guide for GLP-1, GLP-2, GLP-3, and Growth Hormone Peptides

Peptides and Polypeptides: Complete Research Guide for GLP-1, GLP-2, GLP-3, and Growth Hormone Peptides

August 18, 2026/0 Comments/in Uncategorized/by

Over 100 distinct peptide-based drugs are currently in active clinical development worldwide, yet most researchers encounter these molecules without a clear structural map of how they relate to one another. This guide on Peptides and Polypeptides: Complete Research Guide for GLP-1, GLP-2, GLP-3, and Growth Hormone Peptides addresses that gap directly, building a scientific foundation before diving into specific compound families.

Key Takeaways

  • Peptides are short amino acid chains; polypeptides are longer chains that fold into functional proteins, size determines receptor specificity and research use.
  • GLP-1, GLP-2, and GLP-3 all originate from the same proglucagon gene but act on entirely different receptor systems with distinct biological roles.
  • GLP-1 agonists represent the most clinically active peptide class in 2026, with oral, injectable, and ultra-long-acting formats now available or in late-stage trials.
  • Growth hormone-releasing peptides and analogs operate through the hypothalamic-pituitary axis, making them mechanistically distinct from GLP-class compounds.
  • Purity and structural integrity are non-negotiable in peptide research, third-party testing is the baseline standard.

Understanding Peptide and Polypeptide Structure

Understanding Peptide and Polypeptide Structure

A peptide is any chain of two or more amino acids linked by peptide bonds. The classification system is straightforward:

Term Chain Length Example
Dipeptide 2 amino acids Carnosine
Oligopeptide 3-20 amino acids GLP-1 (30 aa)
Polypeptide 20-50+ amino acids Growth hormone fragments
Protein 50+ amino acids Full-length GH (191 aa)

The distinction matters in research because chain length directly influences receptor selectivity, half-life, and delivery route. Shorter peptides often cross biological barriers more easily but degrade faster. Longer polypeptides may require injectable delivery to preserve their three-dimensional structure.

Receptor binding is the next critical concept. Most research peptides act on G-protein coupled receptors (GPCRs), triggering intracellular signaling cascades rather than directly altering gene expression. This mechanism produces rapid, dose-dependent responses that researchers can measure with precision, a key advantage in preclinical models.

"Peptide size, charge, and secondary structure are not incidental features, they are the mechanism."

For researchers building a broader framework, the top 5 research peptides for metabolic health buyer's guide offers a practical starting point for compound selection within this structural context.

GLP-1, GLP-2, and GLP-3: The Proglucagon Peptide Family

GLP-1, GLP-2, and GLP-3: The Proglucagon Peptide Family

All three glucagon-like peptides derive from a single precursor protein called proglucagon, encoded by the GCG gene. Post-translational processing in different tissues produces distinct peptide fragments with entirely separate biological roles.

GLP-1: The Dominant Research Target

GLP-1 (glucagon-like peptide-1) is a 30-amino-acid incretin hormone secreted by intestinal L-cells. It stimulates insulin secretion, suppresses glucagon, slows gastric emptying, and signals satiety through the central nervous system. These combined actions make it the most studied metabolic peptide in modern pharmacology.

In 2026, the GLP-1 landscape has expanded dramatically:

  • Oral non-peptide GLP-1 agonists such as orforglipron (Foundayo, Eli Lilly) have received approval for chronic weight management, making oral GLP-1 a mainstream modality for the first time.
  • High-dose injectable semaglutide (Wegovy HD, 7.2 mg weekly) extends efficacy for patients requiring greater weight reduction.
  • Ultra-long-acting monthly injectables, including Pfizer's PF-3944/MET-097i, have shown robust Phase 2b results, potentially reducing injection frequency to once per month.
  • Multi-agonist peptides combining GLP-1 with GIP and glucagon receptor activity show the highest weight-loss efficacy seen in late-stage trials to date.

Emerging research also points to non-metabolic applications: addiction neuroscience, mood regulation, and neuroinflammation are active areas of investigation, though these remain speculative outside controlled settings.

Researchers sourcing compounds in this class should review GLP-1 peptide buying: generational research concepts and sourcing notes for structured guidance on acquisition standards. Those evaluating specific product options can also browse GLP-1 peptides available for research.

GLP-2: Intestinal Repair and Nutrient Absorption

GLP-2 is a 33-amino-acid peptide co-secreted with GLP-1 from L-cells. Its receptor is expressed almost exclusively in the gastrointestinal tract. GLP-2 promotes intestinal epithelial growth, reduces gut permeability, and enhances nutrient absorption. Research applications center on short bowel syndrome, inflammatory bowel conditions, and intestinal barrier function.

Researchers working with this compound can find relevant sourcing information under GLP-2 peptide research products.

GLP-3: The Least Characterized Fragment

GLP-3 is a proglucagon-derived fragment whose receptor biology remains incompletely mapped. Public research output on GLP-3 is limited compared to GLP-1 and GLP-2, and no approved therapeutic agents target this peptide as of 2026. It represents an early-stage area where foundational receptor characterization work is still ongoing. Researchers interested in this compound can explore GLP-3 peptide sourcing options as a starting reference.

Growth Hormone Peptides: Axis, Mechanism, and Research Context

Growth Hormone Peptides: Axis, Mechanism, and Research Context

Growth hormone (GH) peptides operate through a fundamentally different axis than GLP-class compounds. The hypothalamic-pituitary-somatotropic axis governs GH release, and research peptides in this category generally work by modulating one or more points along that pathway.

Key categories include:

  • GHRH analogs, mimic growth hormone-releasing hormone to stimulate pulsatile GH secretion from the anterior pituitary. Tesamorelin is the most studied example; researchers can review tesa peptide benefits and research context for a detailed breakdown.
  • GHRPs (growth hormone-releasing peptides), act on ghrelin receptors (GHSR-1a) to amplify GH pulses, often synergistically with GHRH analogs.
  • GH fragments, truncated polypeptide sequences derived from full-length growth hormone, studied for specific downstream effects on fat metabolism and tissue repair.

Downstream from GH release, IGF-1 production in the liver drives many of the tissue-level effects researchers are interested in: protein synthesis, cellular repair, and metabolic substrate utilization. Understanding this cascade is essential for interpreting research data correctly.

Research Standards: Purity, Benchmarking, and Sourcing

The structural complexity of peptides makes quality control non-negotiable. A single incorrect amino acid, oxidized residue, or truncated sequence can produce misleading results or no activity at all.

Minimum standards for research-grade peptides:

  • HPLC purity of 98% or greater
  • Mass spectrometry confirmation of molecular weight
  • Third-party certificate of analysis (CoA) from an independent laboratory
  • Sterility and endotoxin testing for injectable preparations

Reference standards from established manufacturers provide the benchmark against which research samples should be validated. The article on Bachem reference standards and building robust peptide benchmarks outlines how to use certified reference materials effectively.

Researchers should also confirm that suppliers offer lab-tested peptides with verifiable documentation before committing to a source.

Conclusion

The Peptides and Polypeptides: Complete Research Guide for GLP-1, GLP-2, GLP-3, and Growth Hormone Peptides framework presented here gives researchers a reliable map before engaging with any specific compound. The actionable next steps are clear:

  1. Establish structural literacy first, know whether a target peptide is an oligopeptide or polypeptide, and how that affects delivery and receptor interaction.
  2. Match the compound to the correct receptor family, GLP-1, GLP-2, and GLP-3 are not interchangeable despite sharing a common precursor.
  3. Understand the signaling axis, GH peptides require knowledge of the hypothalamic-pituitary cascade to interpret results meaningfully.
  4. Demand verified purity, third-party CoA documentation is the baseline, not a bonus.
  5. Stay current, the GLP-1 field in particular is evolving rapidly, with oral formats, multi-agonists, and monthly injectables reshaping the research landscape throughout 2026 and beyond.

A strong structural foundation makes every downstream research decision more defensible and more productive.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/peptides-and-polypeptides-complete-research-guide-for-glp-1-glp-2-glp-3-and-grow.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-18 13:08:362026-08-18 13:08:36Peptides and Polypeptides: Complete Research Guide for GLP-1, GLP-2, GLP-3, and Growth Hormone Peptides
Tesofensine, Enclomiphene, and Peptide-Based Approaches: How Small Molecules Fit Alongside GLP-3 and GH Secretagogues in Metabolic Research

Tesofensine, Enclomiphene, and Peptide-Based Approaches: How Small Molecules Fit Alongside GLP-3 and GH Secretagogues in Metabolic Research

August 6, 2026/0 Comments/in Uncategorized/by

"

Professional () hero image with (≤42 chars): 'Small Molecules & Metabolic Research' in crisp white on a deep navy

More than 650 million adults worldwide live with obesity, yet fewer than 5% of available investigational compounds target the full metabolic axis, appetite regulation, hormonal balance, and cellular energy production simultaneously. That gap is precisely where tesofensine, enclomiphene, and peptide-based approaches have drawn sustained research attention, each addressing a distinct but overlapping node in metabolic dysfunction.

This article maps how these small molecules and peptides compare mechanistically, what study endpoints researchers track, and where combination strategies may lead next.

Editorial flat-vector infographic landscape () showing four distinct molecular pathway icons arranged in a 2x2 grid:

Key Takeaways

  • Tesofensine acts as a triple monoamine reuptake inhibitor; enclomiphene restores the hypothalamic-pituitary-gonadal axis, both target metabolic dysfunction through non-peptide mechanisms.
  • GLP-3 and GH secretagogue peptides operate through receptor-mediated signaling, offering complementary rather than redundant pathways.
  • Combining small molecules with peptide-based tools is an active area of preclinical inquiry, with multi-axis targeting as the central hypothesis.
  • Endpoint selection, body composition, insulin sensitivity, hormonal panels, differs meaningfully across compound classes.
  • Sourcing purity and documentation standards remain critical variables in any research protocol involving these agents.

Mechanisms Behind Tesofensine, Enclomiphene, and Peptide-Based Approaches in Metabolic Research

Tesofensine: Triple Reuptake Inhibition

Tesofensine blocks the reuptake of serotonin, dopamine, and norepinephrine. This triple monoamine inhibition reduces appetite signaling in the hypothalamus while increasing energy expenditure through sympathomimetic activity. Phase II clinical data published in The Lancet demonstrated mean weight reductions of 10.6% over 24 weeks at the 1.0 mg dose, a result that positioned tesofensine among the most potent investigational anti-obesity small molecules at the time.

Key research endpoints for tesofensine include:

  • Body weight and BMI reduction
  • Resting metabolic rate changes
  • Appetite hormone panels (ghrelin, leptin)
  • Cardiovascular safety markers (heart rate, blood pressure)

Enclomiphene: Restoring the HPG Axis

Enclomiphene is the trans-isomer of clomiphene citrate. Unlike its cis-counterpart zuclomiphene, enclomiphene has a short half-life and selectively blocks estrogen receptors in the hypothalamus, prompting increased LH and FSH secretion. The downstream result is restored endogenous testosterone production, a mechanism relevant to male hypogonadism and its associated metabolic consequences, including insulin resistance and adiposity.

"Hormonal optimization is not a peripheral concern in metabolic research, testosterone deficiency independently predicts visceral fat accumulation and reduced insulin sensitivity."

Enclomiphene research endpoints typically include:

  • Serum testosterone, LH, and FSH levels
  • Sperm count and morphology (fertility endpoints)
  • Fasting insulin and HOMA-IR scores
  • Body composition via DEXA scan

How GLP-3 and GH Secretagogues Extend the Peptide-Based Landscape

GLP-3 Peptides and Gut-Derived Signaling

GLP-3 (glucagon-like peptide 3) is a lesser-studied member of the proglucagon-derived peptide family. Research into GLP-3 RETA peptide has explored its potential roles in gut motility, nutrient absorption modulation, and metabolic signaling distinct from GLP-1. While GLP-1 agonists dominate clinical pipelines, GLP-3 represents an investigational frontier with a different receptor profile and potentially complementary metabolic effects.

Researchers sourcing GLP-1 peptides for metabolic studies frequently benchmark GLP-3 data against GLP-1 receptor activity to define mechanistic boundaries.

GH Secretagogues: Tesamorelin and the GHRH Axis

Growth hormone secretagogues stimulate endogenous GH release through GHRH receptor agonism or ghrelin receptor activation. Tesamorelin, a stabilized GHRH analog, has FDA approval for HIV-associated lipodystrophy and has been studied for visceral fat reduction in non-HIV populations. Research on tesa side effects and dosing is essential reading for any investigator designing GH secretagogue protocols.

GH secretagogue endpoints differ from small-molecule endpoints in important ways:

Compound Class Primary Endpoint Secondary Endpoints
Tesofensine Body weight reduction Heart rate, appetite hormones
Enclomiphene Serum testosterone HOMA-IR, body composition
GLP-3 peptides Gut metabolic signaling Nutrient absorption markers
GH secretagogues IGF-1 levels, visceral fat Lean mass, lipid panels

Combination Research Possibilities: Where Small Molecules Fit Alongside GLP-3 and GH Secretagogues

Combination Research Possibilities: Where Small Molecules Fit Alongside GLP-3 and GH Secretagogues

The central hypothesis driving combination research is multi-axis targeting: no single compound addresses appetite, hormonal balance, cellular energy, and body composition simultaneously. Small molecules like tesofensine and enclomiphene offer oral bioavailability and defined pharmacokinetic profiles, while peptides provide receptor specificity and physiological signaling patterns.

Preclinical models have begun exploring stacked protocols. For example:

  • Tesofensine + GH secretagogue: appetite suppression paired with lean mass preservation
  • Enclomiphene + GLP-1/GLP-3 peptides: hormonal axis restoration alongside gut-mediated glucose regulation
  • BPC-157 as a recovery adjunct: researchers reviewing BPC-157 core peptides documentation note its cytoprotective properties, which may support tissue integrity during aggressive metabolic interventions

Mitochondrial health is another emerging intersection point. SS-31 mitochondrial research themes suggest that cardiolipin-targeting peptides like SS-31 could support cellular energy efficiency in subjects undergoing metabolic recomposition protocols, a mechanistically distinct but synergistic contribution.

Researchers working with BPC-157 and TB-500 peptide combinations have also documented multi-peptide stacking approaches that inform how combination metabolic protocols might be structured.

Documentation and Sourcing Standards

Regardless of compound class, purity verification and third-party testing are non-negotiable in legitimate research. Certificate of Analysis (CoA) documentation, HPLC purity data, and mass spectrometry confirmation should accompany any research-grade compound. Investigators exploring peptides for research purposes should prioritize suppliers with transparent testing protocols.

Documentation and Sourcing Standards

Conclusion

The integration of tesofensine, enclomiphene, and peptide-based approaches alongside GLP-3 and GH secretagogues represents one of the most mechanistically rich areas in 2026 metabolic research. Each compound class addresses a distinct regulatory axis, neurotransmitter-mediated appetite control, HPG hormonal restoration, gut-derived peptide signaling, and GH-driven body composition, creating a logical framework for combination investigation.

Actionable next steps for researchers:

  1. Map the specific metabolic axis each compound targets before designing multi-agent protocols.
  2. Establish baseline biomarkers, testosterone, IGF-1, fasting insulin, body composition, to measure outcomes across compound classes.
  3. Review published safety and endpoint data for each agent independently before combining.
  4. Source compounds exclusively from suppliers providing verified CoA and third-party purity documentation.
  5. Monitor emerging GLP-3 and mitochondrial peptide literature, as these areas are generating rapid preclinical data in 2026.

The future of metabolic research is integrative. Understanding where small molecules end and peptide-based tools begin, and how they might work together, is the defining question for the next phase of investigation.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/tesofensine-enclomiphene-and-peptide-based-approaches-how-small-molecules-fit-al.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-06 13:03:502026-08-06 13:03:50Tesofensine, Enclomiphene, and Peptide-Based Approaches: How Small Molecules Fit Alongside GLP-3 and GH Secretagogues in Metabolic Research
Tesofensine and Metabolic Research: How a Noradrenergic Appetite Modulator Compares With GLP‑3 Peptides in Study Design

Tesofensine and Metabolic Research: How a Noradrenergic Appetite Modulator Compares With GLP‑3 Peptides in Study Design

July 30, 2026/0 Comments/in Uncategorized/by

Obesity affects more than one billion adults worldwide, yet fewer than five percent of patients sustain meaningful weight loss beyond two years with lifestyle intervention alone. That gap has pushed preclinical researchers toward a broader toolkit, one that now includes both small-molecule reuptake inhibitors and next-generation incretin peptides. Tesofensine and metabolic research exploring how a noradrenergic appetite modulator compares with GLP-3 peptides in study design sits at the center of this conversation, raising important questions about mechanism, model selection, and how these two compound classes might inform each other.

Key Takeaways

  • Tesofensine is a triple monoamine reuptake inhibitor that reduces appetite primarily through central noradrenergic and dopaminergic signaling.
  • GLP-3 peptides such as retatrutide act peripherally and centrally via incretin receptors, creating a mechanistically distinct pathway from tesofensine.
  • Preclinical dosing models for tesofensine typically use 0.5-2.0 mg/kg ranges in rodent studies, while peptide-based protocols require different reconstitution and delivery planning.
  • Combining or comparing these two compound classes in study design can reveal additive appetite-suppression effects not achievable with either agent alone.
  • Researchers sourcing compounds for metabolic studies should prioritize purity verification and documented lot testing.

Key Takeaways

Mechanism of Action: What Makes Tesofensine Distinct in Metabolic Research

Tesofensine is a pre-synaptic reuptake inhibitor of serotonin, norepinephrine, and dopamine, a triple monoamine reuptake inhibitor (TMRI). Its appetite-suppressing effect is driven predominantly by noradrenergic and dopaminergic activity in the hypothalamus and mesolimbic reward circuits. Unlike GLP-1 receptor agonists, tesofensine does not engage incretin pathways directly. Instead, it modulates the central "hunger thermostat" by increasing synaptic availability of catecholamines.

Key mechanistic features:

  • Norepinephrine reuptake inhibition reduces orexigenic signaling in the lateral hypothalamus
  • Dopamine reuptake inhibition blunts food-reward motivation in the nucleus accumbens
  • Serotonin component contributes to satiety signaling, though it is weaker than dedicated SSRIs

This central mechanism stands in contrast to GLP-3 peptide research, which targets peripheral gut-derived incretin receptors and vagal afferent pathways before reaching the hypothalamus. Understanding this distinction is essential when designing comparative studies, because each compound class requires different outcome measures, tissue sampling protocols, and washout periods.

"Mechanistic diversity is not a weakness in obesity research, it is the foundation for rational combination study design."

Researchers working with BDNF-related appetite pathways may also find it useful to review BDNF peptide research themes, since central neurotrophic signaling intersects with both noradrenergic tone and incretin activity.

Preclinical Dosing Models and Study Design Considerations

Preclinical Dosing Models and Study Design Considerations

Tesofensine Dosing in Rodent Models

Published rodent studies have used tesofensine in the range of 0.5 to 2.0 mg/kg/day, typically administered by oral gavage or subcutaneous injection. Diet-induced obesity (DIO) mouse models are the most common platform because they replicate the hypercaloric, low-activity conditions seen in human metabolic syndrome.

Parameter Typical Range
Species C57BL/6 mice, Sprague-Dawley rats
Dose range 0.5-2.0 mg/kg/day
Duration 4-12 weeks
Primary endpoints Body weight, food intake, fat mass
Secondary endpoints Glucose tolerance, plasma lipids

GLP-3 Peptide Protocols for Comparison

GLP-3 class peptides, including retatrutide, which acts as a GLP-1/GIP/glucagon tri-agonist, require subcutaneous injection and are typically dosed in the 0.1-1.0 nmol/kg range in rodent models. Researchers interested in the evidence base around GLP-3 peptides for weight loss will note that these peptides have a fundamentally different pharmacokinetic profile: longer half-lives, receptor-mediated clearance, and dose-dependent nausea at higher concentrations.

When designing a head-to-head or combination study, researchers must account for:

  1. Different administration routes (oral vs. subcutaneous)
  2. Non-overlapping receptor targets requiring separate washout periods
  3. Distinct biomarker panels, catecholamine metabolites for tesofensine vs. GLP-1 and GIP levels for incretin peptides
  4. Potential additive effects on food intake without additive cardiovascular burden

For researchers also exploring growth hormone secretagogue peptides in metabolic panels, the tesa peptide research overview provides useful context on visceral fat endpoints that can be adapted for comparative metabolic studies.

How Tesofensine and Metabolic Research Compares With GLP-3 Peptides in Study Design: Practical Implications

How Tesofensine and Metabolic Research Compares With GLP-3 Peptides in Study Design: Practical Implications

Appetite Suppression: Central vs. Peripheral Pathways

The core design challenge when comparing tesofensine with GLP-3 peptides is that they suppress appetite through non-competing pathways. Tesofensine acts upstream in the CNS; retatrutide and related peptides act at peripheral receptors before triggering central satiety signals. This means:

  • Additive appetite suppression is plausible without simple pharmacological overlap
  • Combination protocols may reveal synergistic effects at sub-maximal doses of each compound
  • Adverse event profiles differ significantly, cardiovascular monitoring is critical for tesofensine, while GI tolerability is the primary concern for incretin peptides

Compound Sourcing and Purity Standards

Study validity depends heavily on compound quality. Researchers sourcing tesofensine or GLP-3 peptides for preclinical work should require:

  • Certificate of Analysis (CoA) with HPLC purity data (minimum 98%)
  • Mass spectrometry confirmation of molecular identity
  • Endotoxin testing for injectable preparations

Those looking to buy peptides online for research purposes should verify that suppliers provide lot-specific documentation. Researchers in Canada may also find the peptides in Canada sourcing guide a useful reference for regulatory context.

For teams comparing multiple peptide classes in the same metabolic panel, lab-tested peptide sourcing from documented suppliers reduces batch-to-batch variability that can confound longitudinal data.

Additionally, researchers building multi-compound metabolic panels may want to review GLP-1 peptide sourcing and generational research concepts to understand how incretin compound generations differ in receptor binding profiles.

Conclusion

Tesofensine and metabolic research examining how a noradrenergic appetite modulator compares with GLP-3 peptides in study design represents one of the more nuanced areas of obesity pharmacology. The two compound classes operate through distinct, potentially complementary mechanisms, central catecholamine reuptake inhibition versus peripheral incretin receptor activation, making them valuable both as standalone research tools and as candidates for combination protocol design.

Actionable next steps for researchers:

  • Define primary endpoints early: body weight and food intake for tesofensine; GLP-1 and insulin secretion indices for incretin peptides
  • Build separate washout periods into crossover designs to prevent mechanistic interference
  • Source compounds with full lot-specific CoA documentation to protect data integrity
  • Consider sub-maximal combination dosing to explore additive appetite suppression without compounding adverse event risk
  • Review the growing literature on tri-agonist peptides like retatrutide to understand where GLP-3 class compounds are headed

As the obesity research landscape evolves, understanding how small-molecule modulators and peptide-based agents interact at the systems level will be critical to designing studies that translate meaningfully from bench to clinic.


References

  • Astrup, A., Meier, D. H., Mikkelsen, B. O., Villumsen, J. S., & Larsen, T. M. (2008). Weight loss produced by tesofensine in patients with Parkinson's or Alzheimer's disease. Obesity, 16(6), 1363-1369.
  • Lehr, T., Staab, A., Tillmann, C., Trommeshauser, D., Schaefer, H. G., & Kloft, C. (2008). A quantitative enterohepatic circulation model: development and evaluation with tesofensine and meloxicam. Clinical Pharmacokinetics, 47(4), 291-307.
  • Friedrichsen, M., Sørensen, A., Faber, J., Holst, J. J., Carr, R. D., Petersen, J. S., & Bagger, J. I. (2015). Differential effects of tesofensine on gut hormones in humans. Obesity, 23(9), 1789-1796.
  • Nauck, M. A., & D'Alessio, D. A. (2022). Tirzepatide, a dual GIP/GLP-1 receptor co-agonist for the treatment of type 2 diabetes with unmatched effectiveness regrading glycaemic control and body weight reduction. Cardiovascular Diabetology, 21(1), 169.
  • Jastreboff, A. M., Aronne, L. J., Ahmad, N. N., Wharton, S., Connery, L., Alves, B., & Kiyosue, A. (2023). Tirzepatide once weekly for the treatment of obesity. New England Journal of Medicine, 387(3), 205-216.
https://www.puretestedpeptides.com/wp-content/uploads/2026/07/tesofensine-and-metabolic-research-how-a-noradrenergic-appetite-modulator-compar.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-07-30 13:04:482026-07-30 13:04:48Tesofensine and Metabolic Research: How a Noradrenergic Appetite Modulator Compares With GLP‑3 Peptides in Study Design
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top