Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: tissue repair peptides

Prednisone and Research-Use Peptides: How Glucocorticoid Exposure Can Distort Metabolic, Immune, and Tissue-Repair Readouts

Prednisone and Research-Use Peptides: How Glucocorticoid Exposure Can Distort Metabolic, Immune, and Tissue-Repair Readouts

October 6, 2026/0 Comments/in Uncategorized/by

Roughly one in five research subjects enrolled in metabolic or immune-modulating studies carries an active or recent glucocorticoid prescription, yet fewer than half of published peptide protocols formally account for this exposure. The problem of Prednisone and Research-Use Peptides: How Glucocorticoid Exposure Can Distort Metabolic, Immune, and Tissue-Repair Readouts is not theoretical. When a subject is taking prednisone, the drug reshapes glucose handling, cytokine profiles, body composition, and wound biology simultaneously, making it nearly impossible to attribute changes in those endpoints to a peptide compound without deliberate experimental controls.

This guide is written for researchers, protocol designers, and informed buyers of research-use peptide compounds who need a clear, actionable map of where glucocorticoid confounding is most severe and how to design around it.


Key Takeaways

  • Prednisone induces a "pseudo-metabolic syndrome" that directly mimics or masks outcomes targeted by metabolic peptides.
  • Standard inflammatory biomarkers, CRP, leukocyte count, neutrophil ratio, are dose-dependently suppressed by glucocorticoids, distorting immune readouts.
  • Tissue-repair and wound-healing endpoints are particularly vulnerable because glucocorticoids both dampen acute inflammation and impair collagen remodeling.
  • Anabolic and sarcopenia-targeted peptides face the strongest confounding from glucocorticoid-driven muscle catabolism.
  • Glucocorticoid exposure should be treated as a core design variable, not background noise, in any peptide research protocol.

How Glucocorticoids Create a Pseudo-Metabolic Syndrome
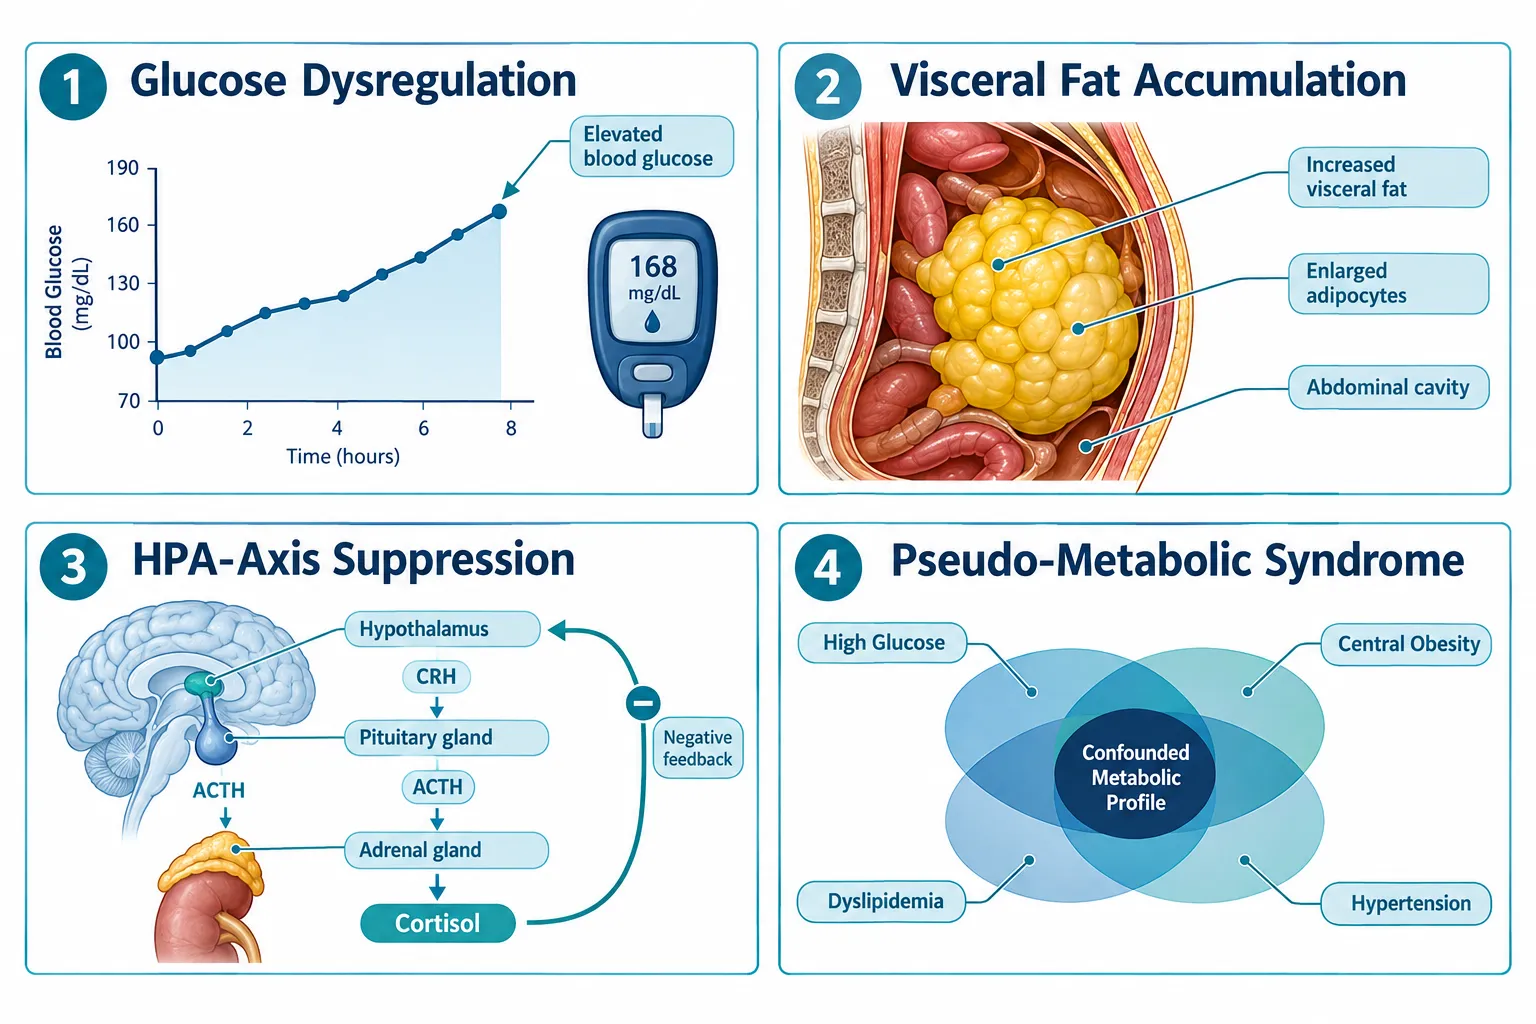
How Glucocorticoids Create a Pseudo-Metabolic Syndrome

Prednisone does not simply suppress inflammation. At doses commonly used in clinical and research-adjacent settings, it triggers a cascade of metabolic changes that closely resemble metabolic syndrome: elevated fasting glucose, increased visceral adiposity, dyslipidemia, and insulin resistance. For researchers studying cardiometabolic peptide compounds, this is a direct collision.

The core metabolic confounders introduced by prednisone include:

Endpoint Glucocorticoid Effect Research Risk
Fasting glucose Elevated (hepatic gluconeogenesis) Masks GLP-class peptide efficacy
Visceral fat Increased via lipid redistribution Distorts body-composition endpoints
Insulin sensitivity Reduced Confounds metabolic peptide response
Appetite / caloric intake Increased Alters weight-loss peptide readouts
Cortisol / HPA axis Suppressed endogenous output Disrupts hormonal biomarker panels

The HPA-axis suppression point deserves particular attention. When exogenous glucocorticoids are present, endogenous cortisol production falls. This changes the hormonal baseline against which peptide pharmacodynamics are measured. For GH-analogue peptides and compounds that interact with the growth hormone axis, this hormonal shift can produce entirely misleading dose-response curves.

Researchers studying visceral fat redistribution should also note that glucocorticoid-driven adiposity preferentially accumulates centrally, the same compartment tracked in visceral fat research models. Without a glucocorticoid-naive control arm, it becomes impossible to separate peptide-driven changes from steroid-driven ones.


Immune Biomarker Distortion: What Prednisone Does to CRP, Cytokines, and Leukocytes
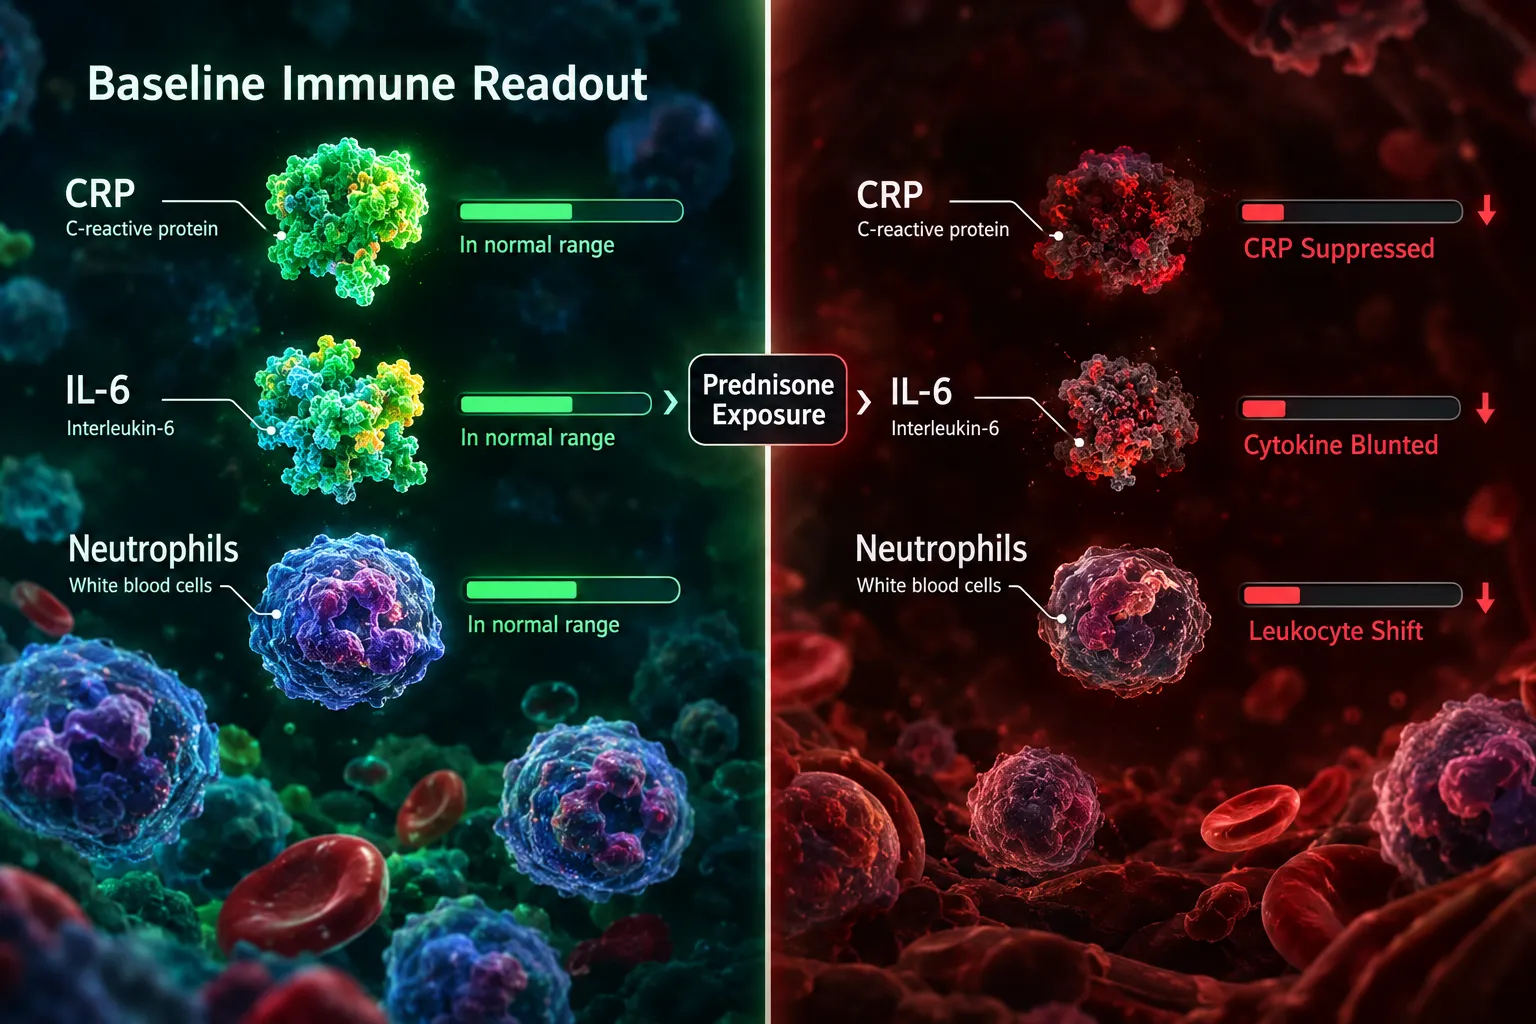
Immune Biomarker Distortion: What Prednisone Does to CRP, Cytokines, and Leukocytes

The immune-modulating effects of prednisone are both well-documented and deeply problematic for peptide research. The drug produces strong, dose-dependent suppression of nearly every standard inflammatory biomarker used in research protocols.

Biomarkers most severely distorted by glucocorticoid exposure:

  • C-reactive protein (CRP): Hepatic CRP synthesis is directly suppressed, producing artificially low readings that can mimic anti-inflammatory peptide effects.
  • Interleukin-6 (IL-6) and TNF-alpha: Both are blunted by glucocorticoid receptor activation, masking inflammatory resolution that a peptide may or may not be driving.
  • Leukocyte and neutrophil counts: Prednisone causes a characteristic leukocytosis with neutrophilia and lymphopenia, a pattern that can be mistaken for an immune-activation signal from a peptide compound.
  • Tissue-resident immune cells: Recent work confirms that glucocorticoids selectively modulate tissue-resident macrophages and mast cells in ways that differ from circulating immune cells. This matters enormously for regenerative peptides like BPC-157 and TB-500, where local tissue immune activity is the primary readout.

"When prednisone is present, the immune landscape a peptide encounters is fundamentally different from the one it was designed to modulate. Treating that as a minor covariate is a protocol error."

The practical consequence is that an immune-modulating peptide may appear highly effective, completely ineffective, or even counterproductive depending entirely on the glucocorticoid dose the subject carries. Without stratifying subjects by steroid exposure, or excluding active users entirely, the data cannot be interpreted with confidence.


Tissue-Repair and Anabolic Readouts: Where Glucocorticoid Confounding Is Most Severe
Tissue-Repair and Anabolic Readouts: Where Glucocorticoid Confounding Is Most Severe

Wound healing and tissue repair represent perhaps the most complex confounding scenario in Prednisone and Research-Use Peptides: How Glucocorticoid Exposure Can Distort Metabolic, Immune, and Tissue-Repair Readouts. Glucocorticoids produce a paradoxical two-phase effect on repair biology.

Phase 1 (acute): Inflammation is suppressed, which can make a wound-healing peptide appear to accelerate early healing simply because the steroid has already cleared the inflammatory field.

Phase 2 (remodeling): Glucocorticoids impair fibroblast proliferation, reduce collagen synthesis, and suppress angiogenesis. A peptide that promotes collagen remodeling may show blunted or absent efficacy, not because it failed, but because the steroid has suppressed the very cellular machinery the peptide targets.

For anabolic and sarcopenia-targeted peptides, the problem is equally stark. Glucocorticoids drive skeletal muscle catabolism through multiple mechanisms: they upregulate muscle-specific ubiquitin ligases, suppress IGF-1 signaling, and reduce protein synthesis rates. Any peptide designed to promote lean mass retention or muscle repair is working against a pharmacologically imposed catabolic state. The net readout will underestimate peptide efficacy, sometimes dramatically.

Mitochondrial function is also affected. Glucocorticoids impair mitochondrial biogenesis in muscle tissue, which is directly relevant for compounds studied in SS-31 mitochondrial research contexts.

Designing Around Glucocorticoid Confounding: Practical Protocol Controls

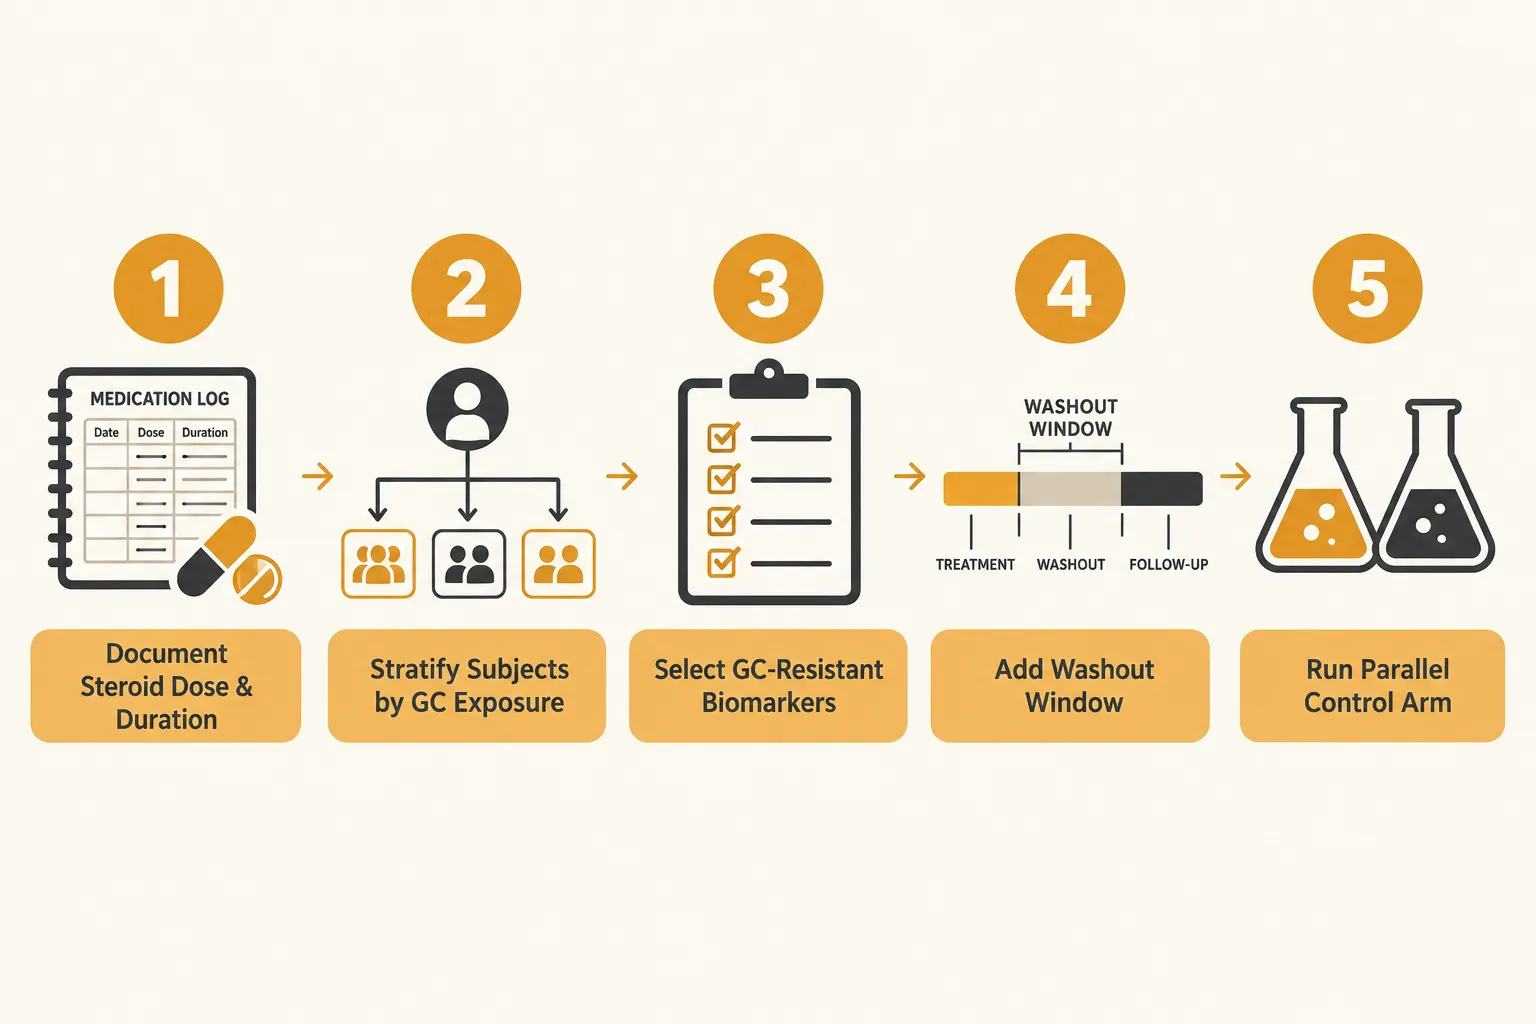
Researchers in 2026 have several validated strategies to reduce or detect glucocorticoid confounding:

  1. Screen and stratify at enrollment. Collect steroid use history, current dose, and duration. Stratify rather than exclude where possible to preserve sample size.
  2. Use glucocorticoid-resistant biomarkers where available. Some cytokines and repair markers are less sensitive to steroid suppression and can serve as secondary endpoints.
  3. Build in washout windows. For subjects who can safely discontinue steroids, a documented washout period before peptide exposure begins reduces confounding substantially.
  4. Run parallel control arms. A glucocorticoid-exposed control arm receiving vehicle only allows direct quantification of steroid-driven endpoint changes.
  5. Report steroid exposure as a primary covariate. Statistical models should treat glucocorticoid dose as a continuous variable, not a binary yes/no flag.

Conclusion

The relationship between Prednisone and Research-Use Peptides: How Glucocorticoid Exposure Can Distort Metabolic, Immune, and Tissue-Repair Readouts is now well enough characterized that ignoring it constitutes a preventable design flaw. Across glucose metabolism, inflammatory cytokines, collagen remodeling, body composition, and immune-cell measurements, prednisone introduces quantifiable, directional biases that can make an effective peptide look inert, or an inert one look effective.

Actionable next steps for research protocol designers:

  • Add glucocorticoid screening to all enrollment checklists for metabolic, immune, or repair-focused peptide studies.
  • Pre-specify steroid dose as a covariate in the statistical analysis plan before data collection begins.
  • Consult updated 2026 biomarker guidance on glucocorticoid-resistant immune endpoints when designing immune-modulating peptide studies.
  • Review compound-specific confounding risk, peptides targeting GH axis, collagen synthesis, or mitochondrial function carry the highest vulnerability.

Treating glucocorticoid exposure as a core design variable rather than background noise is the single highest-leverage methodological improvement available to most peptide research teams today.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/prednisone-and-research-use-peptides-how-glucocorticoid-exposure-can-distort-met.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-06 13:06:132026-10-06 13:06:13Prednisone and Research-Use Peptides: How Glucocorticoid Exposure Can Distort Metabolic, Immune, and Tissue-Repair Readouts
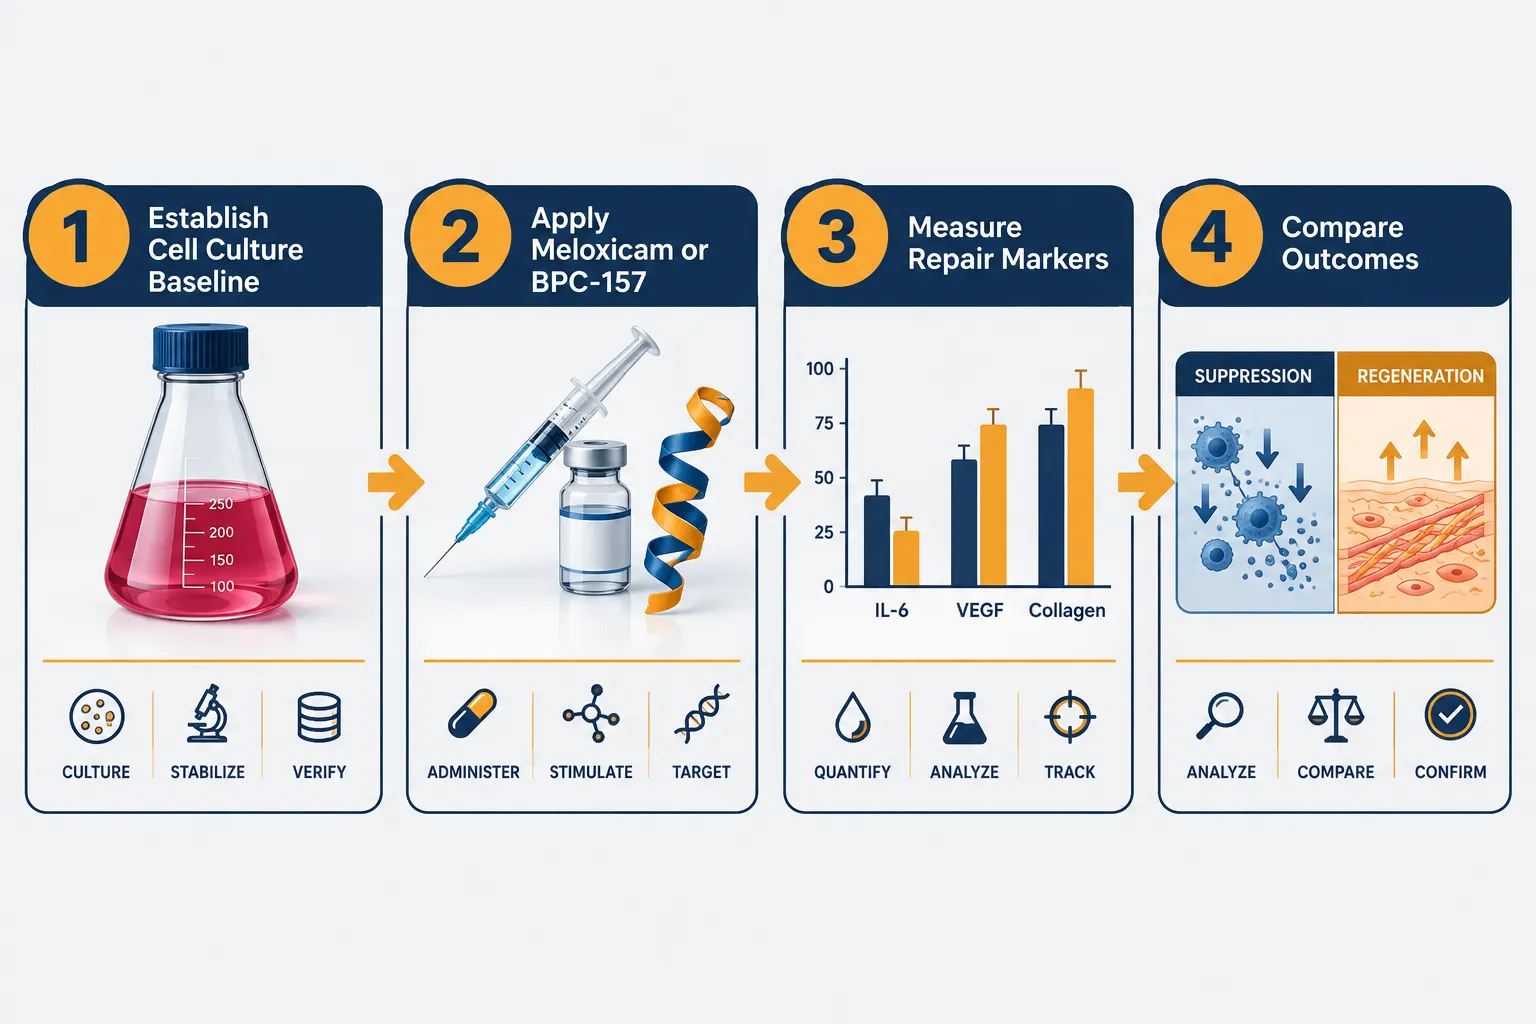
Meloxicam vs BPC-157 and TB-500: How NSAIDs and Tissue-Repair Peptides Differ in In Vitro Injury Models

Meloxicam vs BPC-157 and TB-500: How NSAIDs and Tissue-Repair Peptides Differ in In Vitro Injury Models

September 20, 2026/0 Comments/in Uncategorized/by

Selective COX-2 inhibition reduces myofiber cross-sectional area by up to 33% during the first three weeks after muscle injury, a finding that challenges the routine use of NSAIDs like meloxicam in early musculoskeletal recovery. This single data point captures the central tension explored in Meloxicam vs BPC-157 and TB-500: How NSAIDs and Tissue-Repair Peptides Differ in In Vitro Injury Models: two fundamentally different pharmacological strategies, one aimed at quieting inflammation and one aimed at rebuilding tissue, produce strikingly different outcomes at the cellular level.

Key Takeaways

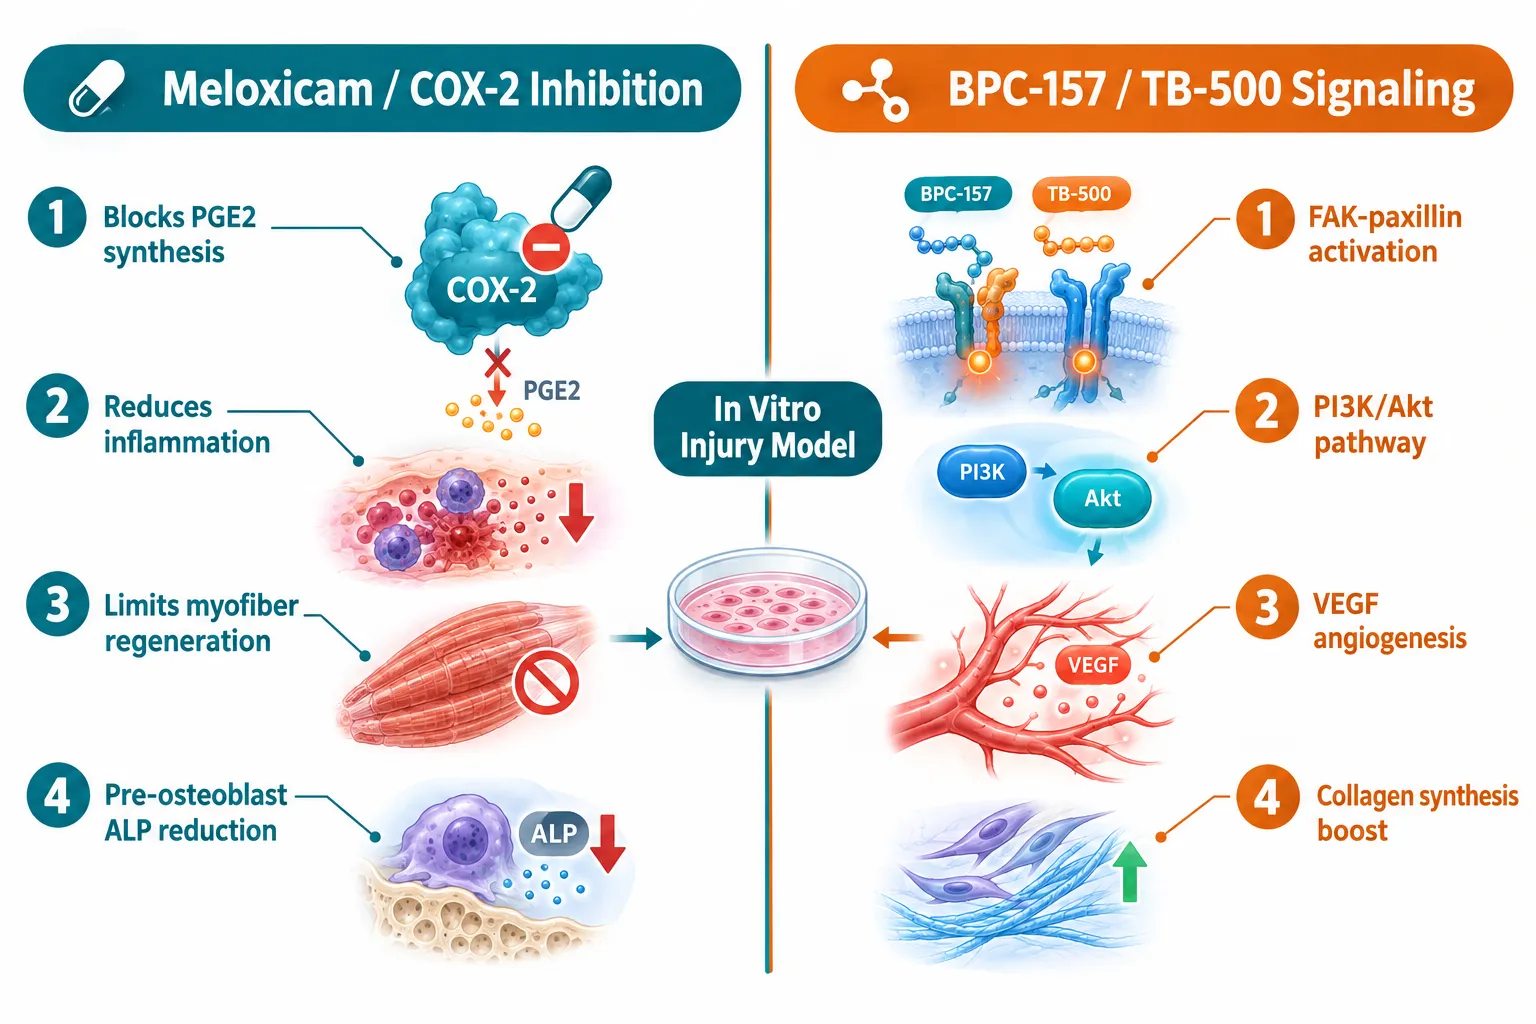
  • Meloxicam suppresses COX-2-dependent prostaglandin signaling, which reduces inflammation but may simultaneously impair early tissue regeneration in muscle, bone, and tendon models.
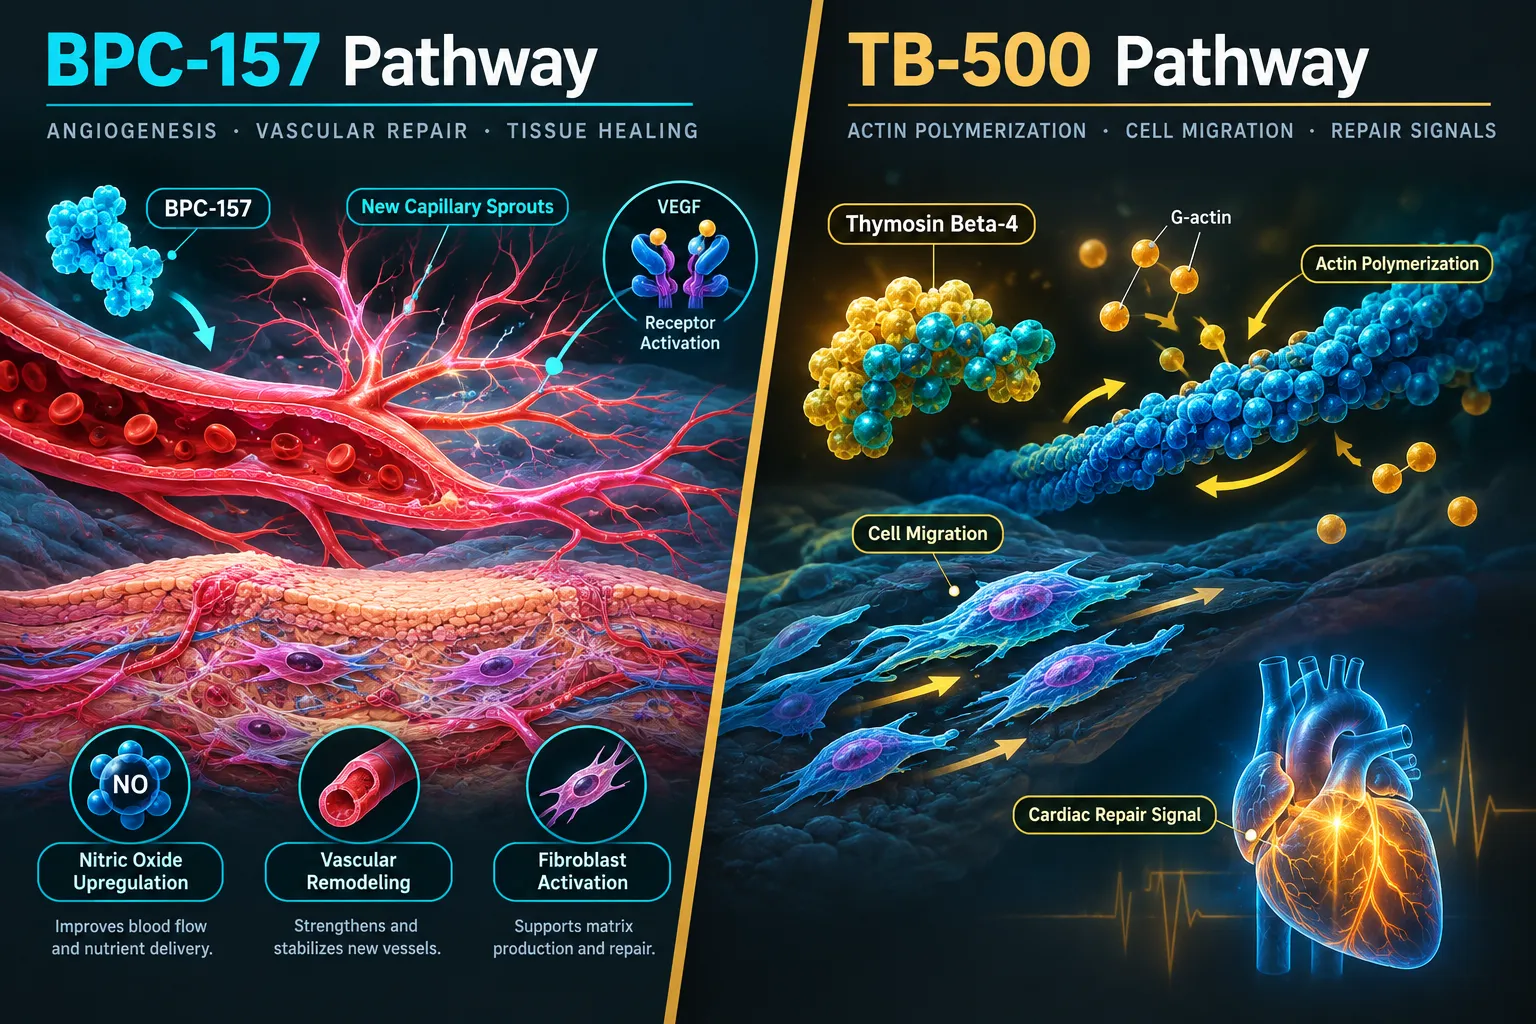
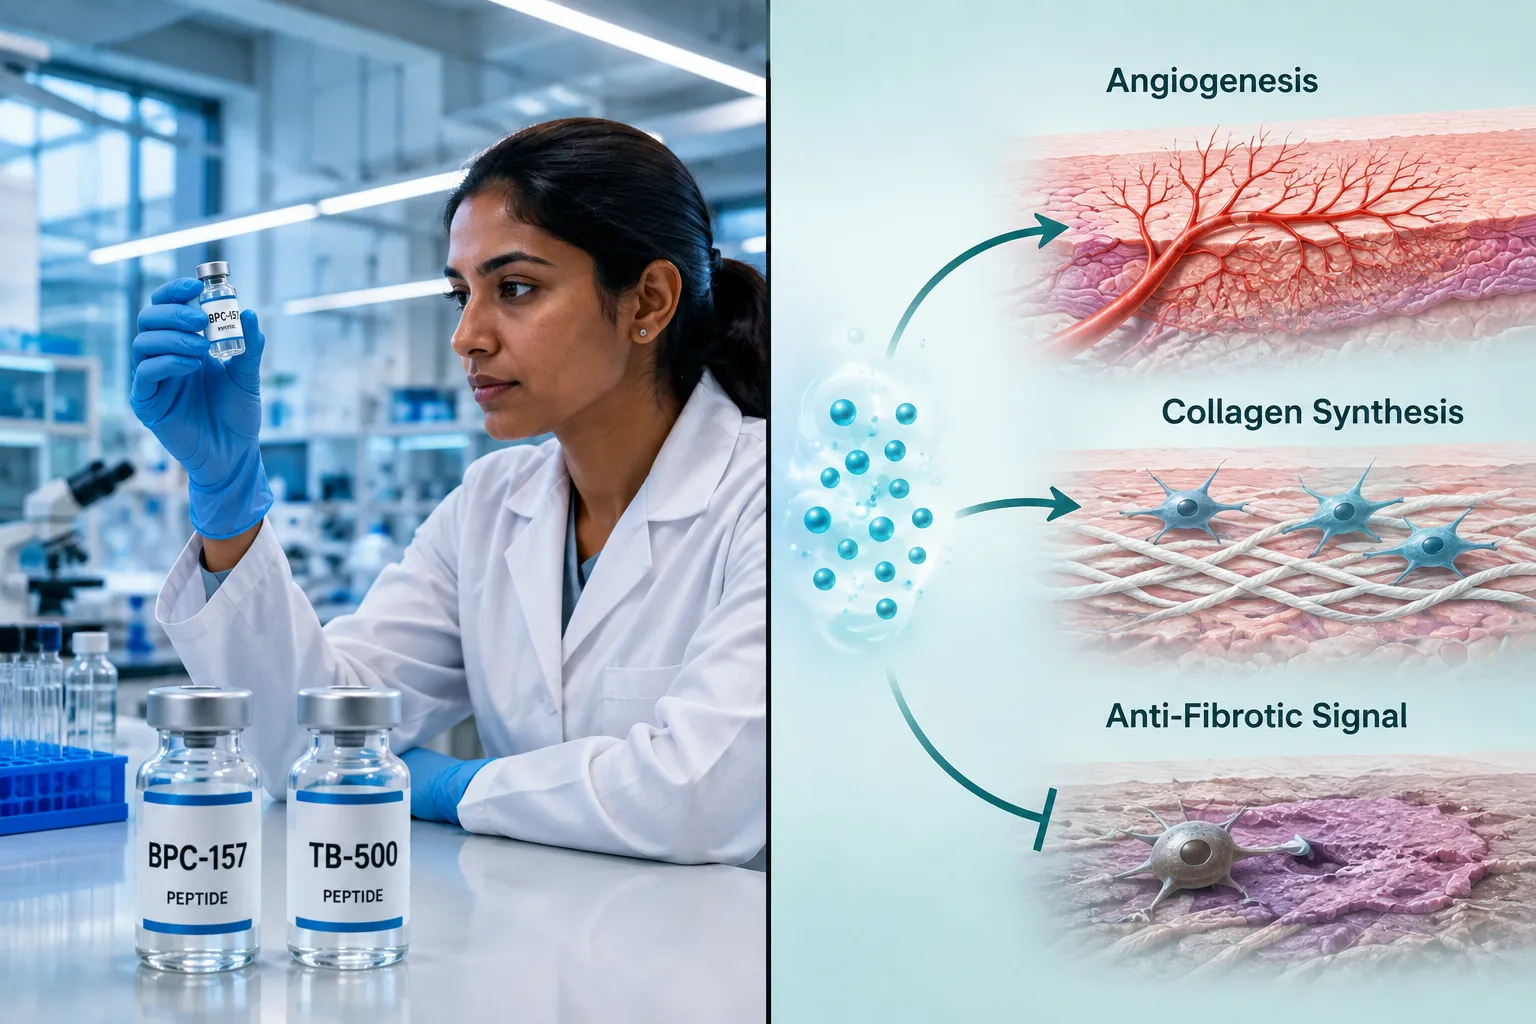
  • BPC-157 activates FAK-paxillin, PI3K/Akt, VEGF, and TGF-beta pathways in vitro, supporting fibroblast proliferation, collagen synthesis, and angiogenesis.
  • TB-500 promotes actin polymerization, progenitor cell recruitment, and collagen fiber organization through MAPK, NF-kB, and cytoskeletal repair pathways.
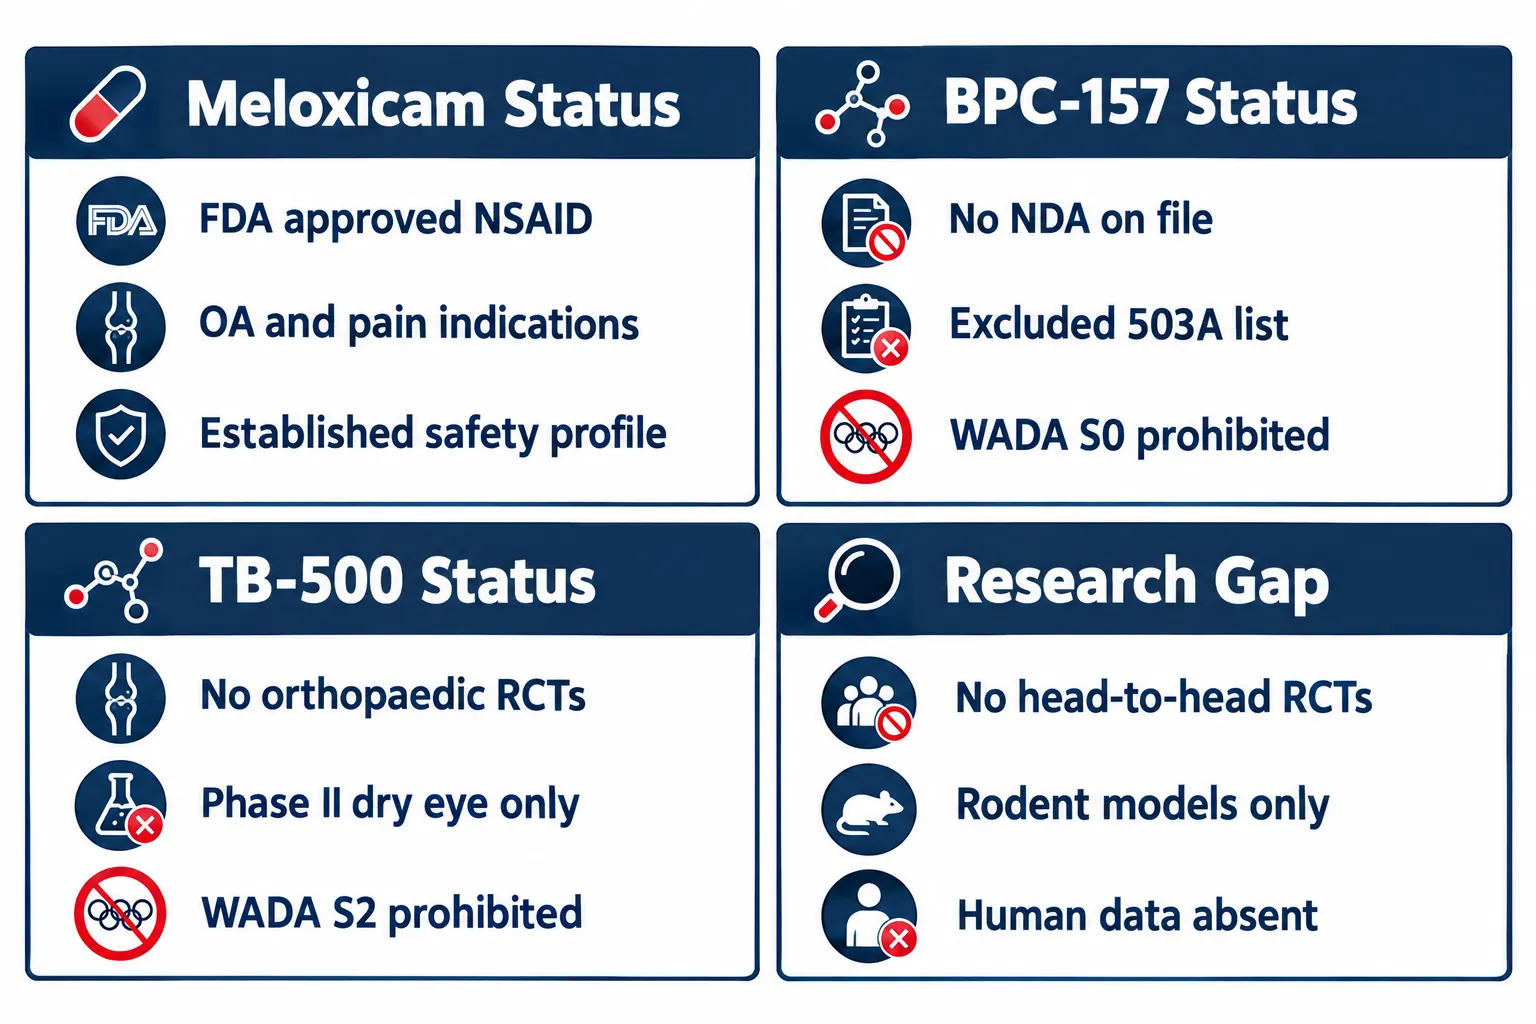
  • No robust human randomized controlled trials currently compare BPC-157 or TB-500 with meloxicam in musculoskeletal injury; all comparative evidence comes from cell and rodent studies.
  • Both peptides remain unapproved, are excluded from FDA compounding lists, and are prohibited under WADA rules, making them strictly research-use compounds as of 2026.

How Meloxicam Works in Tissue-Injury Cell Models

Meloxicam is a COX-2-preferential NSAID with a COX-2:COX-1 IC50 ratio of approximately 0.09 in human whole-blood assays, meaning it inhibits COX-2 at concentrations far below those needed to affect COX-1. This selectivity drives its analgesic and anti-inflammatory profile, but it also places COX-2-dependent regenerative signaling directly in the line of fire.

How Meloxicam Works in Tissue-Injury Cell Models

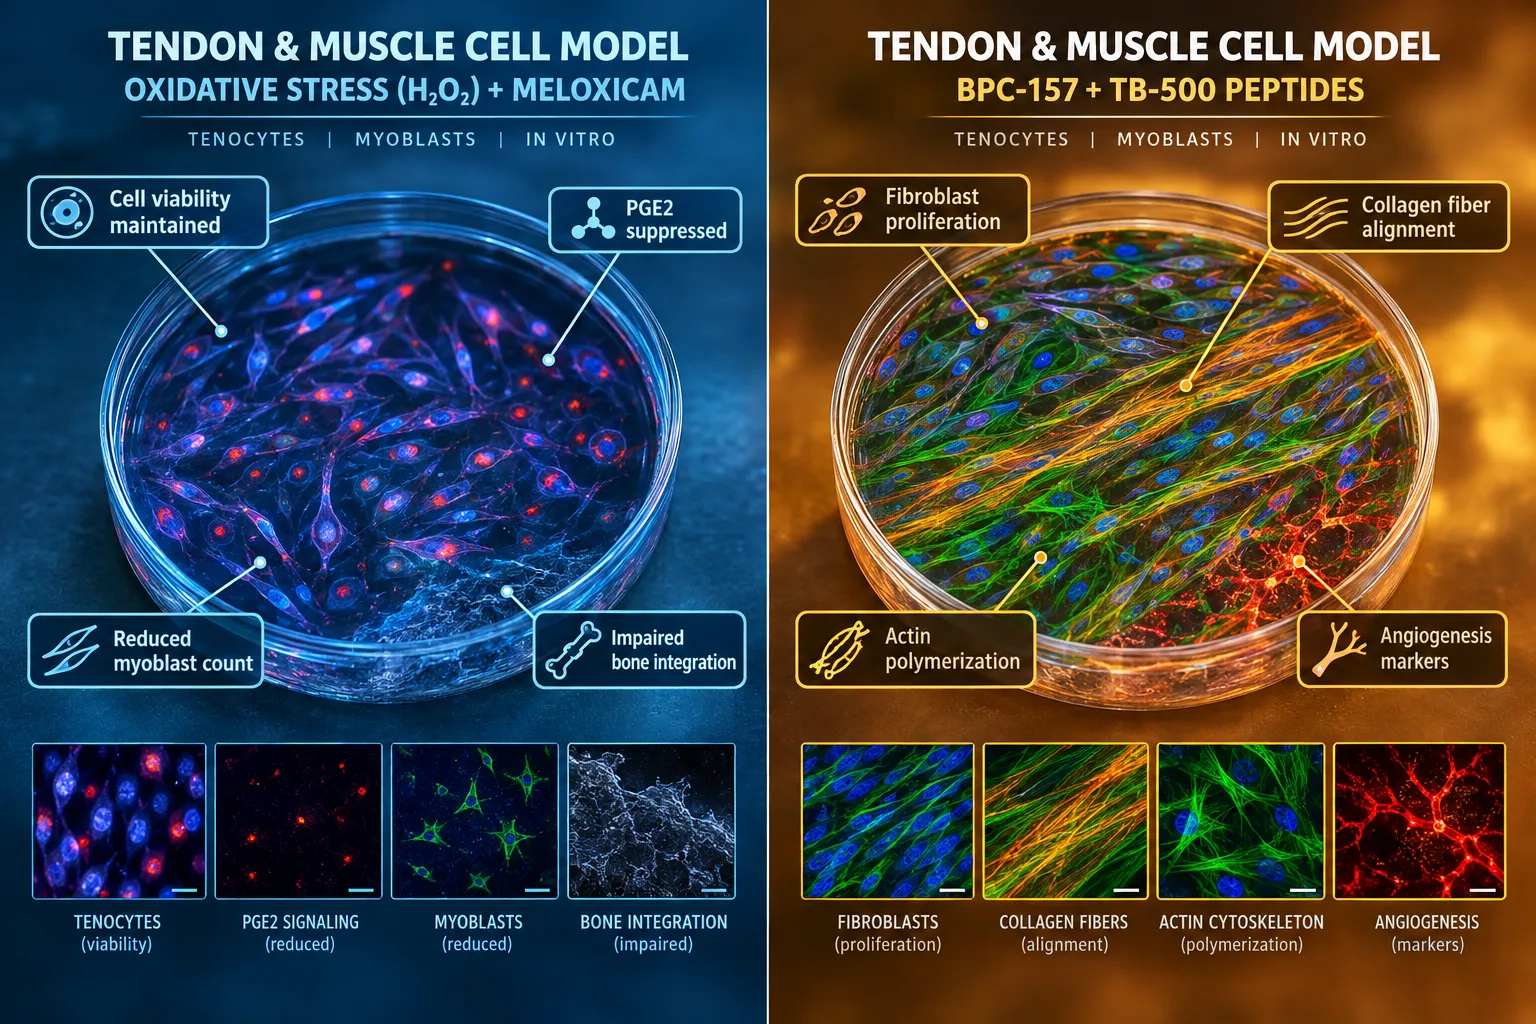
In human Achilles tendon-derived tenocytes exposed to oxidative stress via hydrogen peroxide, 24-hour meloxicam treatment can increase cell metabolic activity relative to untreated controls. At the same time, it consistently reduces prostaglandin E2 (PGE2) production through COX-2 inhibition. This creates a mechanistic paradox: the drug may support short-term cell viability under stress while simultaneously blunting the prostaglandin signals that coordinate early repair cascades.

The downstream consequences vary by tissue type:

  • Muscle: COX-2 inhibitors analogous to meloxicam reduce myoblast count and inflammatory cell recruitment, impairing fiber regeneration during the first three weeks post-injury.
  • Bone: Preclinical fracture models show impaired healing with COX-2 inhibitors, including meloxicam, and animal tendon-to-bone repair studies report compromised integration compared with acetaminophen controls.
  • Cartilage: In osteoarthritic canine chondrocytes, up to 30 days of meloxicam exposure does not increase matrix metalloproteinase production, suggesting the cartilage matrix is relatively preserved.
  • Osteogenesis: Meloxicam reduces alkaline phosphatase activity in pre-osteoblasts, yet some selective COX-2 inhibitors leave osteogenic differentiation of human adipose-derived stromal cells unaltered.

"The data on meloxicam in musculoskeletal cell models are mechanistically coherent but contextually mixed, tissue type and injury timing determine whether COX-2 inhibition helps or hinders."

These nuances are directly relevant to researchers designing wound models that use meloxicam as a reference compound.

BPC-157 and TB-500 Signaling in the Same In Vitro Systems

When examining Meloxicam vs BPC-157 and TB-500: How NSAIDs and Tissue-Repair Peptides Differ in In Vitro Injury Models, the peptide side of the comparison reveals a fundamentally different mechanistic profile. Rather than suppressing a single enzymatic pathway, both peptides activate multiple pro-repair cascades simultaneously.

BPC-157 and TB-500 Signaling in the Same In Vitro Systems

BPC-157 is a 15-amino-acid synthetic peptide with a broad signaling footprint in tendon and ligament models:

  • Enhances tendon fibroblast proliferation and collagen synthesis
  • Activates focal adhesion kinase (FAK)-paxillin signaling, rescuing tendocyte growth under oxidative stress
  • Upregulates growth hormone receptor expression and signals through PI3K/Akt, VEGF, NO/eNOS, and TGF-beta pathways
  • Accelerates tendon explant outgrowth and supports extracellular matrix remodeling

In transected rat Achilles tendon models, BPC-157 improves biomechanical endpoints including failure load and Young's modulus, outcomes that reflect genuine structural repair rather than pain suppression alone.

TB-500, a synthetic fragment of thymosin beta-4, works through complementary but distinct biology:

  • Promotes actin polymerization and progenitor cell recruitment
  • Enhances cell migration indices in ligament repair models
  • Produces more uniform collagen fiber bundles and larger fibril diameters at four weeks
  • Activates MAPK, NF-kB, FAK, and cytoskeletal repair pathways alongside pro-angiogenic activity

Researchers exploring these mechanisms can find relevant wound repair peptides and resources on wound repair and wound healing peptides for further context on how these compounds are studied in controlled settings.

A 2023 rat Achilles rupture-repair study found that both BPC-157 and TB-500 improved histopathological organization and extracellular matrix remodeling during early repair. However, direct head-to-head comparisons of both peptides within the same in vitro model remain sparse, and the preponderance of BPC-157 data comes from a single research group.

Regulatory Status, Research Gaps, and Lab Safety Considerations

Understanding Meloxicam vs BPC-157 and TB-500: How NSAIDs and Tissue-Repair Peptides Differ in In Vitro Injury Models requires an honest accounting of where the evidence stands and what the regulatory environment looks like as of 2026.

Regulatory Status, Research Gaps, and Lab Safety Considerations

Meloxicam is an established, FDA-approved NSAID with well-characterized pharmacokinetics, approved indications for osteoarthritis and other pain conditions, and decades of human safety data.

BPC-157 and TB-500 occupy a very different position:

Dimension Meloxicam BPC-157 TB-500
FDA approval Yes No No
Human RCT data (orthopaedic) Extensive None None
WADA status Permitted S0 prohibited S2 prohibited
503A compounding Permitted Excluded Excluded
Highest-quality evidence Phase III/IV trials Rodent + cell studies Phase II (dry eye only)

Both peptides have been excluded from the FDA's 503A bulk-drug compounding list, are not listed for 503B outsourcing compounding, and remain unapproved with no New Drug Applications on file. The FDA's Pharmacy Compounding Advisory Committee reviewed both compounds in July 2026 in the context of wound-healing and orthopaedic compounding, but neither has moved to an approved status.

For researchers sourcing compounds for in vitro work, using a best peptide supplier with verified purity documentation is essential. Researchers should also review resources on wholesale peptides for sale to ensure laboratory-grade material is used strictly within approved research protocols.

The only human data for BPC-157 in a musculoskeletal context is a single small case series of 17 patients receiving intra-articular injections for knee tendon and ligament symptoms, a study with significant methodological limitations. TB-500 has completed two Phase II trials, both in dry eye disease, with no orthopaedic RCTs published to date.

Conclusion

The comparison of Meloxicam vs BPC-157 and TB-500: How NSAIDs and Tissue-Repair Peptides Differ in In Vitro Injury Models reveals two pharmacological philosophies operating at opposite ends of the repair spectrum. Meloxicam suppresses a single enzymatic node, COX-2, with well-understood consequences for inflammation and, depending on tissue type and timing, potentially for regeneration itself. BPC-157 and TB-500 activate broad, overlapping pro-repair networks in cell and animal models, producing structural improvements in collagen organization, cell migration, and biomechanical endpoints that no NSAID is designed to achieve.

Actionable next steps for researchers:

  1. When using meloxicam as a reference NSAID in injury models, account for tissue type, muscle and bone models are more sensitive to COX-2 inhibition than cartilage models.
  2. Treat BPC-157 and TB-500 data critically: most evidence is rodent-derived, and human orthopaedic outcome data are essentially absent as of 2026.
  3. Source peptides only from suppliers with verified purity certificates and use them exclusively within approved institutional research frameworks.
  4. Monitor FDA Pharmacy Compounding Advisory Committee deliberations, as the regulatory status of both peptides remains under active review.
  5. Design future in vitro studies with direct head-to-head comparisons of NSAID and peptide conditions within the same cell model to generate more translatable mechanistic data.

The mechanistic gap between these compound classes is large and scientifically meaningful. Closing it will require well-designed, independently replicated human trials, work that has not yet been done.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/meloxicam-vs-bpc-157-and-tb-500-how-nsaids-and-tissue-repair-peptides-differ-in.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-20 13:06:102026-09-20 13:06:10Meloxicam vs BPC-157 and TB-500: How NSAIDs and Tissue-Repair Peptides Differ in In Vitro Injury Models
Meloxicam and Tissue-Repair Peptides: Comparing Nonsteroidal Anti-Inflammatory Drugs with BPC-157 in In Vitro Models

Meloxicam and Tissue-Repair Peptides: Comparing Nonsteroidal Anti-Inflammatory Drugs with BPC-157 in In Vitro Models

September 16, 2026/0 Comments/in Uncategorized/by

COX-2 inhibition and growth factor upregulation are not two sides of the same coin, they are mechanistically opposite strategies for managing tissue injury. This fundamental difference sits at the center of any rigorous comparison of meloxicam and tissue-repair peptides: comparing nonsteroidal anti-inflammatory drugs with BPC-157 in in vitro models. As cell culture research grows more sophisticated in 2026, the contrast between these two approaches has become sharper, more clinically relevant, and more debated.

Key Takeaways

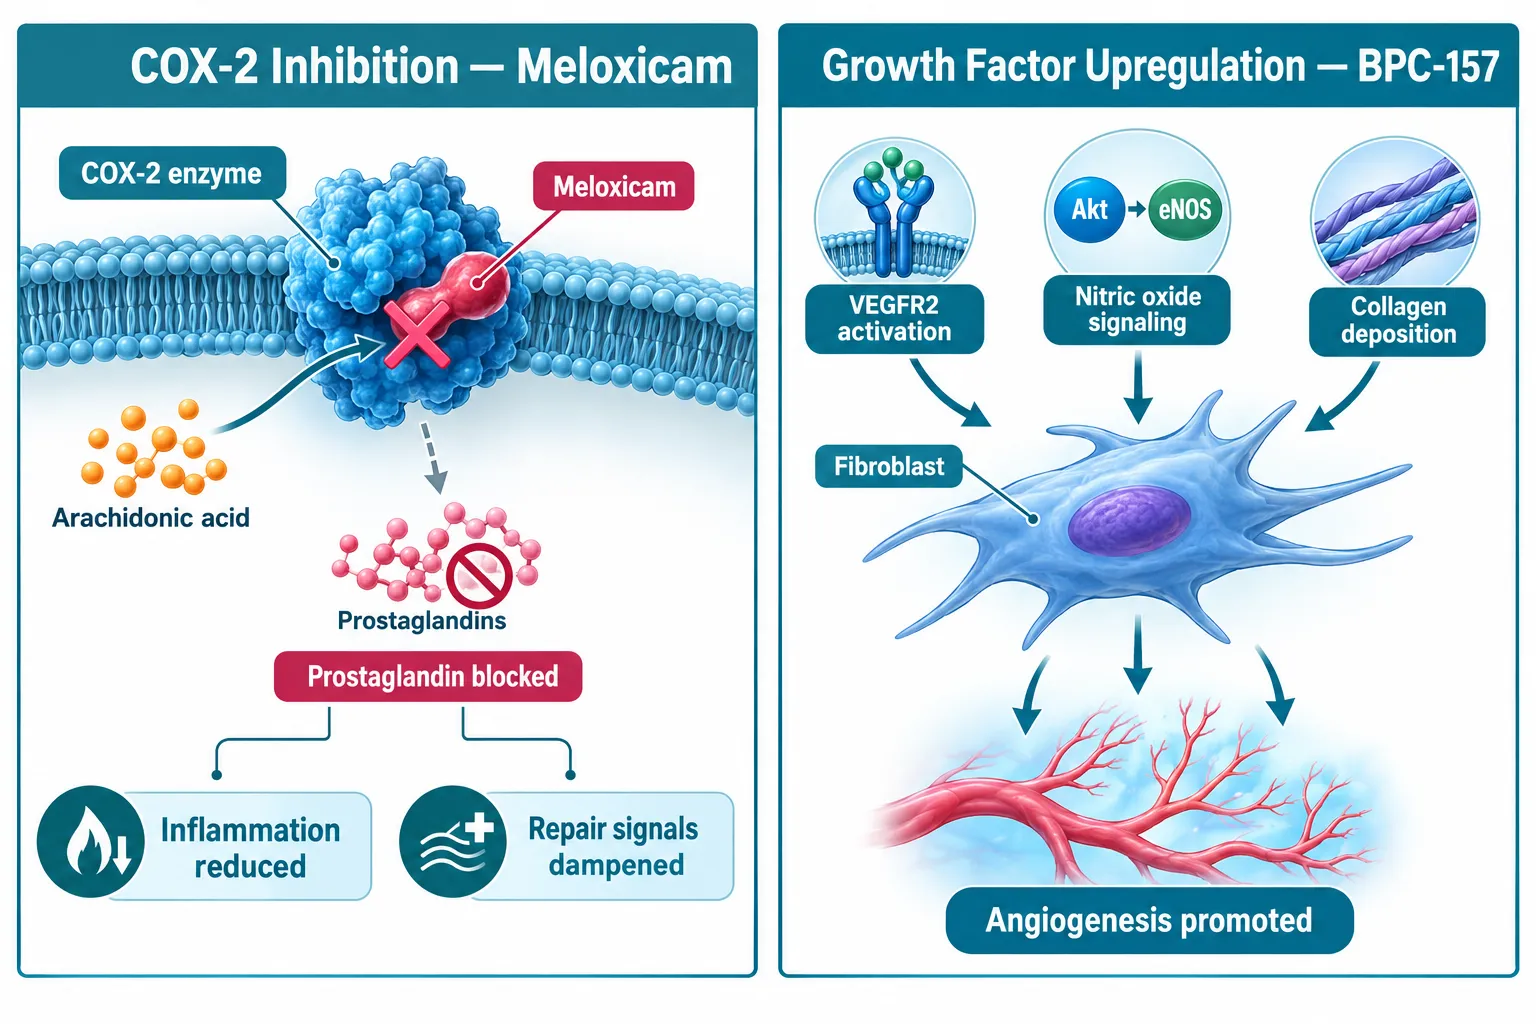
  • Meloxicam reduces inflammation primarily by blocking COX-2 enzymes and suppressing prostaglandin synthesis, which may also dampen early repair signaling.
  • BPC-157 is a pleiotropic tissue-repair peptide that activates VEGFR2, the Akt-eNOS nitric oxide axis, and promotes fibroblast activity, collagen deposition, and angiogenesis.
  • In vitro musculoskeletal models consistently show BPC-157 enhancing tenocyte survival, fibroblast migration, and growth hormone receptor expression.
  • NSAIDs such as meloxicam have been repeatedly associated with reduced collagen synthesis in preclinical models, contrasting with BPC-157's repair-promoting profile.
  • BPC-157 remains a research-only compound without major regulatory approval; meloxicam is a fully approved NSAID with no clinical indication for tissue regeneration.

How COX-2 Inhibition and Peptide Signaling Differ at the Cellular Level

Understanding the mechanistic gap between meloxicam and BPC-157 starts at the receptor level.

Meloxicam is a COX-2-preferential NSAID. It works by blocking cyclooxygenase-2 enzymes, which halts the conversion of arachidonic acid into prostaglandins. This reduces pain and swelling efficiently. However, prostaglandins also serve as early-phase messengers that recruit repair cells to damaged tissue. When that signal is suppressed, the downstream cascade of fibroblast recruitment, collagen synthesis, and angiogenesis can be partially blunted.

How COX-2 Inhibition and Peptide Signaling Differ at the Cellular Level

BPC-157, by contrast, operates through an entirely different set of molecular targets. It activates VEGFR2 (vascular endothelial growth factor receptor 2) and the Akt-eNOS nitric oxide pathway, which directly promotes new blood vessel formation and cell survival. It also upregulates growth hormone receptors on fibroblasts and tenocytes, enhancing their proliferative and migratory capacity. Rather than silencing an inflammatory cascade, BPC-157 accelerates the transition from injury to active repair.

Key distinction: Meloxicam turns down the inflammatory signal. BPC-157 turns up the repair signal. These are not equivalent actions.

This mechanistic separation is why researchers studying meloxicam and tissue-repair peptides in cell culture systems often find these two compounds occupying non-overlapping functional roles rather than competing for the same outcome.

What In Vitro Models Reveal About BPC-157 and NSAID Effects on Tissue Repair

Cell culture studies have produced some of the clearest evidence for BPC-157's repair-promoting properties.

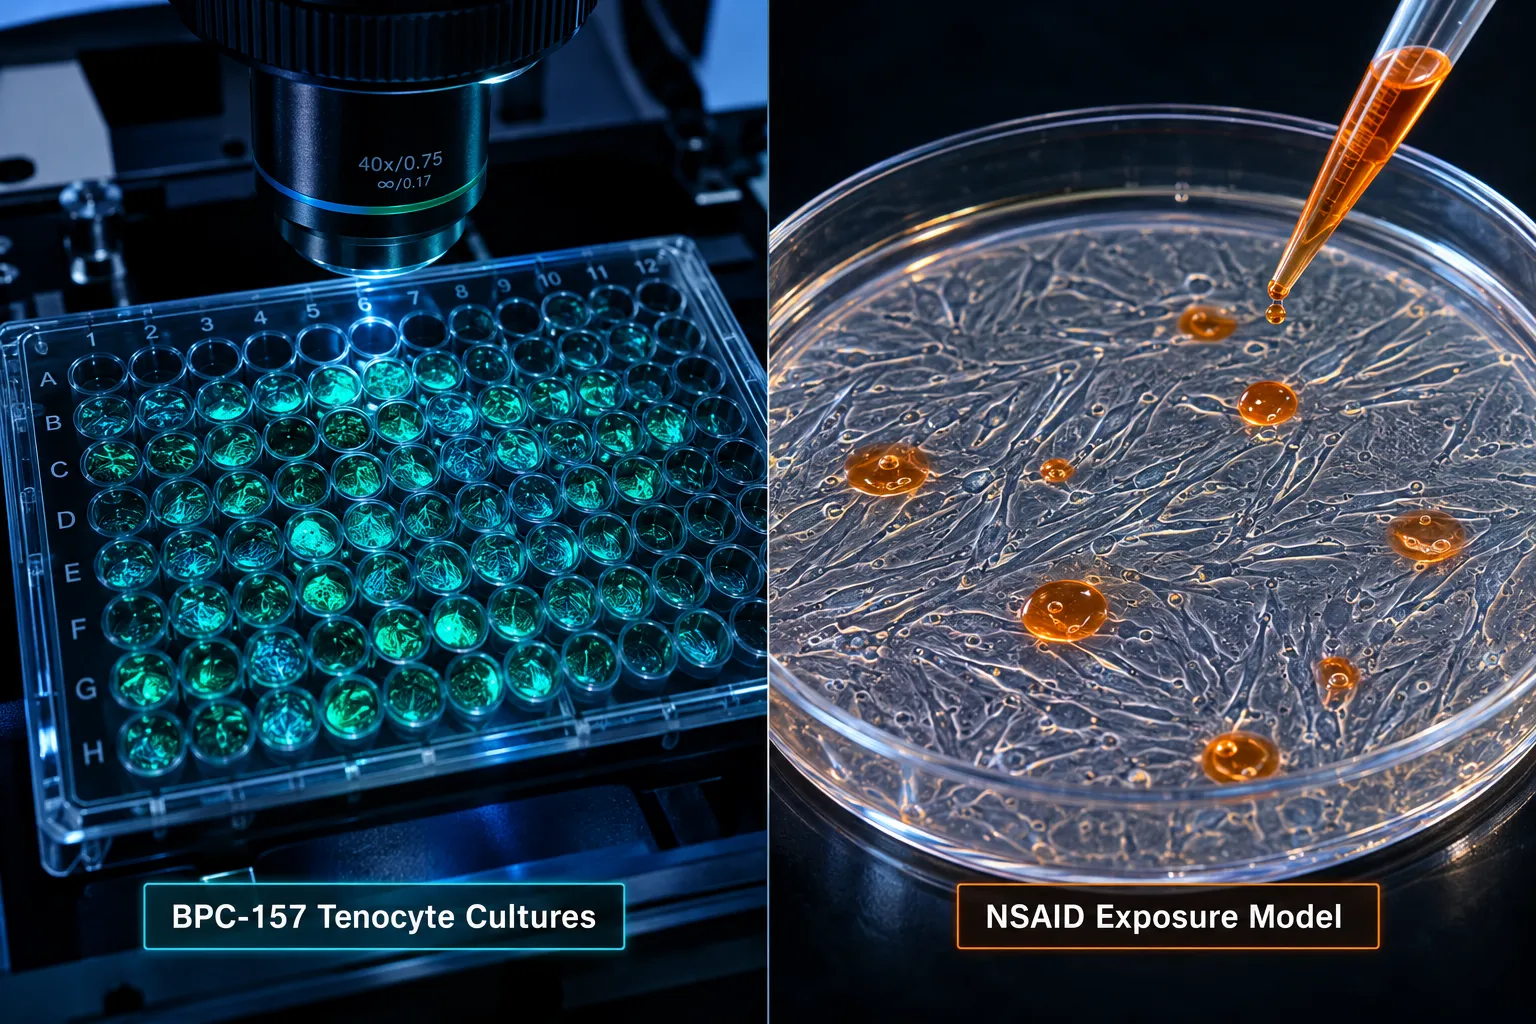
In rat Achilles tenocyte cultures, BPC-157 exposure consistently produces enhanced cell survival and proliferation. Fibroblast cultures treated with BPC-157 show increased growth hormone receptor expression, which correlates with improved collagen fiber organization. Wound-healing scratch assays demonstrate accelerated cell migration into the injury zone, and angiogenesis assays confirm increased tubule formation in endothelial cell models.

What In Vitro Models Reveal About BPC-157 and NSAID Effects on Tissue Repair

NSAIDs tell a different story in the same types of models. Multiple preclinical musculoskeletal studies, including a 2026 systematic overview of 36 studies, have linked conventional NSAID use to reduced collagen synthesis and slower long-term structural healing. Ibuprofen and naproxen are the most cited examples, but the COX-2 inhibition mechanism shared with meloxicam raises similar theoretical concerns for repair-focused endpoints.

Summary of in vitro findings:

Compound Primary Mechanism Effect on Collagen Effect on Angiogenesis Effect on Fibroblast Activity
Meloxicam COX-2 inhibition Potentially reduced Neutral to negative Minimal direct effect
BPC-157 VEGFR2 / Akt-eNOS activation Enhanced Strongly promoted Significantly increased

A particularly compelling area of in vitro research involves gastrointestinal cell models. BPC-157 has repeatedly protected gastric and intestinal mucosal cells from NSAID-induced damage in rat studies, positioning it as a cytoprotective reference compound rather than an NSAID substitute. For researchers exploring SS-31 peptides for sale or other mitochondria-targeted compounds, this cytoprotective angle offers a useful parallel framework.

Practical Research Considerations When Comparing NSAIDs with BPC-157 in Cell Culture Systems

Designing in vitro experiments that meaningfully compare meloxicam and tissue-repair peptides: comparing nonsteroidal anti-inflammatory drugs with BPC-157 in in vitro models requires careful attention to endpoint selection, dosing protocols, and timing.

Practical Research Considerations When Comparing NSAIDs with BPC-157 in Cell Culture Systems

Key design considerations include:

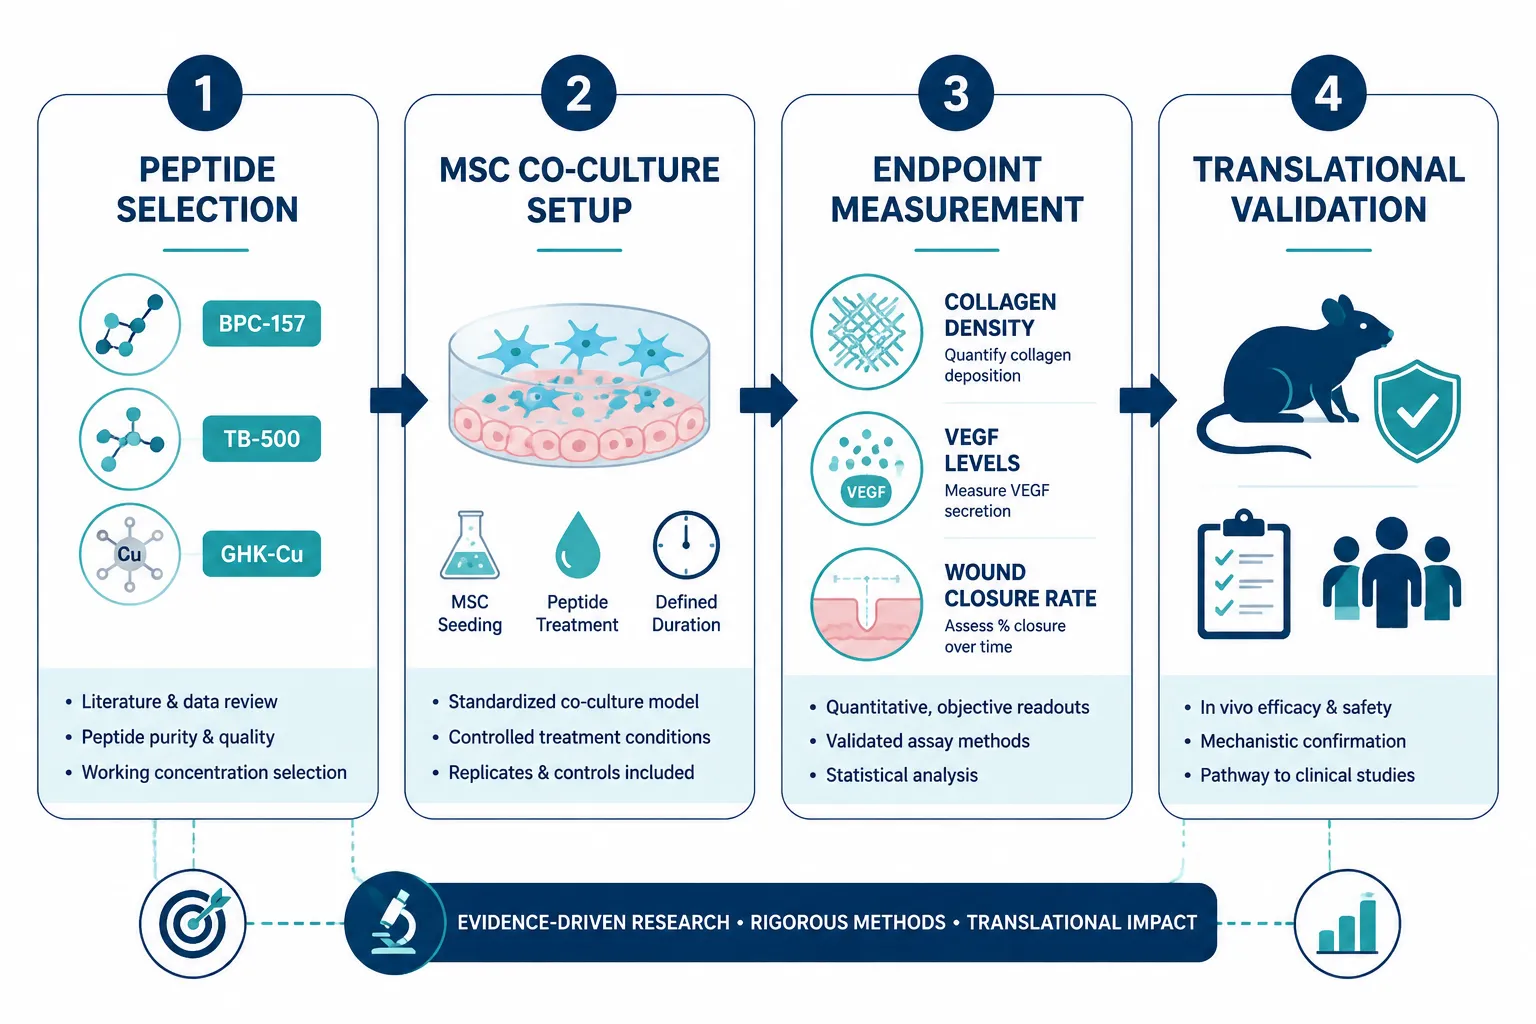
  • Endpoint selection: If the primary endpoint is inflammation suppression (IL-6, TNF-alpha, PGE2), meloxicam performs reliably. If the endpoint is structural repair (collagen density, cell migration rate, VEGF expression), BPC-157 is the mechanistically appropriate comparator.
  • Timing of compound exposure: COX-2 inhibition is most relevant in the early inflammatory phase. BPC-157's growth-factor-driven effects are most active during the proliferative and remodeling phases. Applying both simultaneously may produce conflicting signals.
  • Concentration calibration: BPC-157 research protocols for gut and NSAID-induced damage models typically span 4-6 weeks in animal studies; in vitro timelines should account for the compound's mechanism of action rather than simply mirroring NSAID dosing schedules.

Researchers working with multiple peptide classes, such as those exploring GHK-Cu peptide for skin and connective tissue models, or reviewing CJC-1295 pharmacokinetic comparisons for growth hormone axis research, will recognize that peptide-driven repair signaling requires different experimental frameworks than small-molecule anti-inflammatory drugs.

One 2026 molecular docking study identified FER, TUBA1B, and MICAL2 as proteins where meloxicam shows strong in silico binding affinity, suggesting possible cytoskeletal and signaling roles beyond prostaglandin suppression. However, these findings remain computational and have not yet been validated in dedicated cell culture assays.

Regulatory context matters: BPC-157 is currently a research-only compound under ongoing regulatory review, while meloxicam is a fully approved NSAID. Researchers combining them in experimental settings should note that continuous COX-2 inhibition may theoretically blunt BPC-157's growth-factor-driven repair signaling. Using the lowest effective NSAID dose and avoiding around-the-clock administration during BPC-157 protocols is a commonly recommended precaution when structural repair is the primary endpoint.

Those exploring complementary peptide combinations may also find value in reviewing the synergy of LL-37 and SS-31 for additional context on how peptide combinations interact in repair-focused models. Similarly, researchers studying metabolic and hormonal contexts alongside tissue repair may reference Tesamorelin and Ipamorelin combination safety considerations as a model for responsible multi-compound research design.

For those sourcing research-grade compounds, wholesale peptides with verified purity documentation are essential for reproducible in vitro results.

Conclusion

The comparison of meloxicam and tissue-repair peptides: comparing nonsteroidal anti-inflammatory drugs with BPC-157 in in vitro models ultimately reveals two compounds with fundamentally different roles in tissue biology. Meloxicam is a well-characterized, clinically approved tool for reducing prostaglandin-mediated inflammation, effective, predictable, but limited in its capacity to actively drive structural repair. BPC-157 is a pleiotropic research peptide that promotes angiogenesis, collagen deposition, and fibroblast activity through growth factor pathways, offering a mechanistically distinct and potentially complementary profile.

Actionable next steps for researchers:

  1. Define repair-specific endpoints (VEGF, collagen, cell migration) separately from inflammation endpoints (IL-6, COX-2, PGE2) in study design.
  2. Avoid applying NSAID dosing logic to BPC-157 protocols; align exposure timing with the compound's mechanism of action.
  3. Treat computational findings (such as meloxicam's docking affinity to cytoskeletal proteins) as hypothesis-generating, not conclusive.
  4. Source third-party tested, purity-verified peptides to ensure experimental reproducibility.
  5. Monitor the regulatory landscape for BPC-157, as its status continues to evolve in 2026.

The field is moving toward a clearer understanding that analgesia with suppression and analgesia with repair are not interchangeable goals, and that in vitro models are the most precise tool available for distinguishing between them.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/meloxicam-and-tissue-repair-peptides-comparing-nonsteroidal-anti-inflammatory-dr.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-16 13:06:352026-09-16 13:06:35Meloxicam and Tissue-Repair Peptides: Comparing Nonsteroidal Anti-Inflammatory Drugs with BPC-157 in In Vitro Models
Spironolactone, Cardiorenal Pathways, and Tissue-Repair Peptides: How BPC-157 and TB-500 Complement Classic Heart and Kidney Drug Models

Spironolactone, Cardiorenal Pathways, and Tissue-Repair Peptides: How BPC-157 and TB-500 Complement Classic Heart and Kidney Drug Models

September 13, 2026/0 Comments/in Uncategorized/by

Nearly 64 million people worldwide live with heart failure, and a large proportion of them carry simultaneous kidney dysfunction, a dual burden that no single drug has fully solved. The intersection of spironolactone, cardiorenal pathways, and tissue-repair peptides: how BPC-157 and TB-500 complement classic heart and kidney drug models is now a serious focus in advanced cardiometabolic research. Understanding where established mineralocorticoid receptor antagonists (MRAs) succeed, where they fall short, and how regenerative peptides might fill mechanistic gaps is increasingly relevant for researchers and clinicians alike.

Key Takeaways

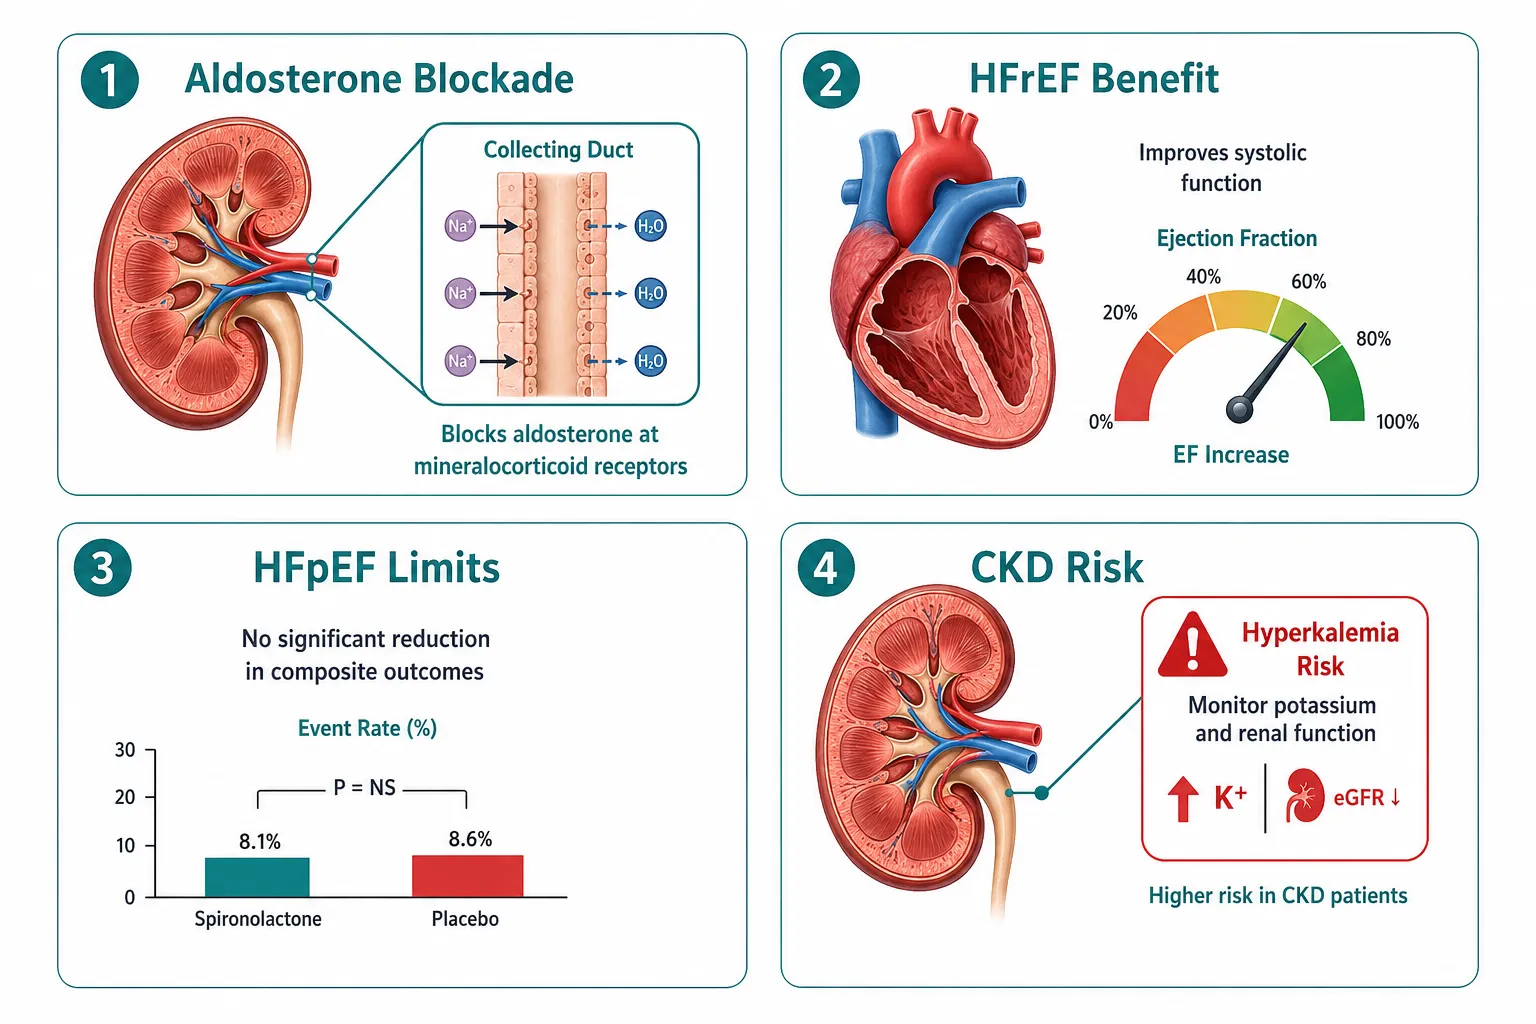
  • Spironolactone blocks aldosterone receptors to reduce fibrosis and fluid retention, but large trials in specific populations, including dialysis patients, show limits to its cardiovascular benefit.
  • Newer non-steroidal MRAs like finerenone demonstrate stronger cardiorenal outcome data, signaling that the MRA class is still evolving.
  • BPC-157 and TB-500 operate through vascular and tissue-repair pathways that are mechanistically distinct from neurohormonal blockade.
  • Both peptides have compelling animal-model data for cardiac and vascular endpoints, but human clinical evidence remains early and limited.
  • Combining neurohormonal drugs with tissue-repair peptides is a conceptual frontier, not yet a validated clinical strategy.

How Spironolactone Shapes Cardiorenal Pathways

How Spironolactone Shapes Cardiorenal Pathways

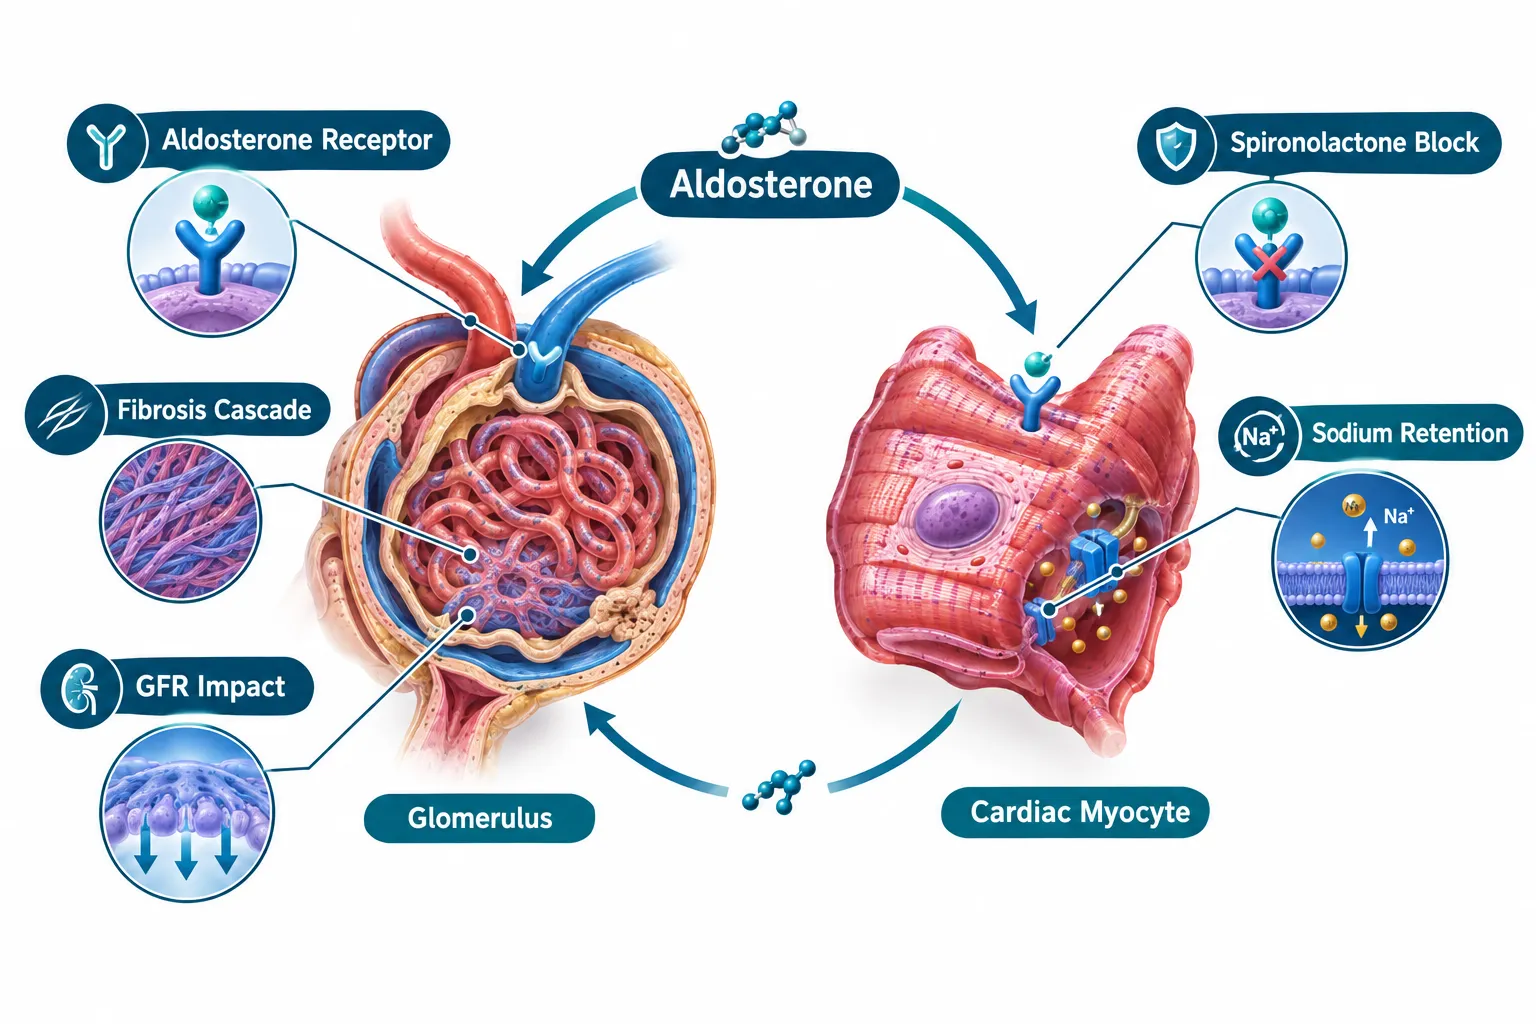
Spironolactone has been a cornerstone of heart failure therapy for decades. It works by blocking aldosterone receptors in the kidney, heart, and vasculature, reducing sodium retention, lowering blood pressure, and most importantly, suppressing the fibrotic signaling that aldosterone drives in cardiac and renal tissue.

The fibrosis connection is critical. Aldosterone excess promotes collagen deposition in the myocardium and glomeruli. By blocking this pathway, spironolactone reduces myocardial stiffness and slows the structural decline that characterizes both heart failure with preserved ejection fraction (HFpEF) and chronic kidney disease (CKD).

However, clinical trial results have complicated the picture:

  • The SPIRIT-HF program, running from 2018 through 2024, produced neutral outcomes for spironolactone in HFpEF and heart failure with mildly reduced ejection fraction (HFmrEF).
  • A large trial in dialysis patients was stopped early for futility, spironolactone showed no cardiovascular benefit in that population.
  • The CLEAR SYNERGY post-MI trial found that spironolactone reduced new or worsening heart failure, but did not significantly reduce major cardiovascular events overall.

These results do not dismiss spironolactone, they clarify its boundaries. The pragmatic SPIRRIT-HFpEF registry continues to test MRAs in real-world HFpEF populations, acknowledging that patient selection matters enormously.

Finerenone, a third-generation non-steroidal MRA, has now produced robust cardiorenal outcome data across both heart failure and diabetic kidney disease populations. Its greater receptor selectivity reduces the side-effect burden of older steroidal MRAs while maintaining anti-fibrotic potency. The modern cardiorenal therapeutic core now integrates MRAs alongside SGLT2 inhibitors and incretin-based therapies, a multi-pathway approach that reflects how complex cardiorenal disease truly is.

"The cardiorenal axis is not a single switch, it is a network of overlapping signals, and blocking one node rarely resolves the whole system."

BPC-157 and TB-500: Tissue-Repair Mechanisms in Cardiorenal Research

BPC-157 and TB-500: Tissue-Repair Mechanisms in Cardiorenal Research

This is where the conversation about spironolactone, cardiorenal pathways, and tissue-repair peptides, and how BPC-157 and TB-500 complement classic heart and kidney drug models, becomes genuinely novel. These two peptides work through entirely different biological levers than MRAs.

BPC-157 (Body Protection Compound-157) is a synthetic pentadecapeptide derived from a gastric protein. In animal models, it has demonstrated:

  • Upregulation of nitric oxide synthase, improving vascular tone
  • Promotion of angiogenesis through VEGF receptor pathways
  • Reduction of fibrotic markers in cardiac and renal tissue
  • Accelerated healing in wound models relevant to ischemic injury

TB-500 (synthetic thymosin beta-4) targets actin polymerization and cell migration. In small animal cardiac studies, it has shown potential to:

  • Stimulate cardiac progenitor cell activation after ischemic injury
  • Reduce scar formation in post-MI myocardium
  • Support endothelial repair and vascular remodeling

These are properties that MRAs simply do not possess. Spironolactone blocks a hormonal signal; BPC-157 and TB-500 actively promote structural repair. Researchers exploring wound healing peptides in vascular contexts recognize this distinction as foundational.

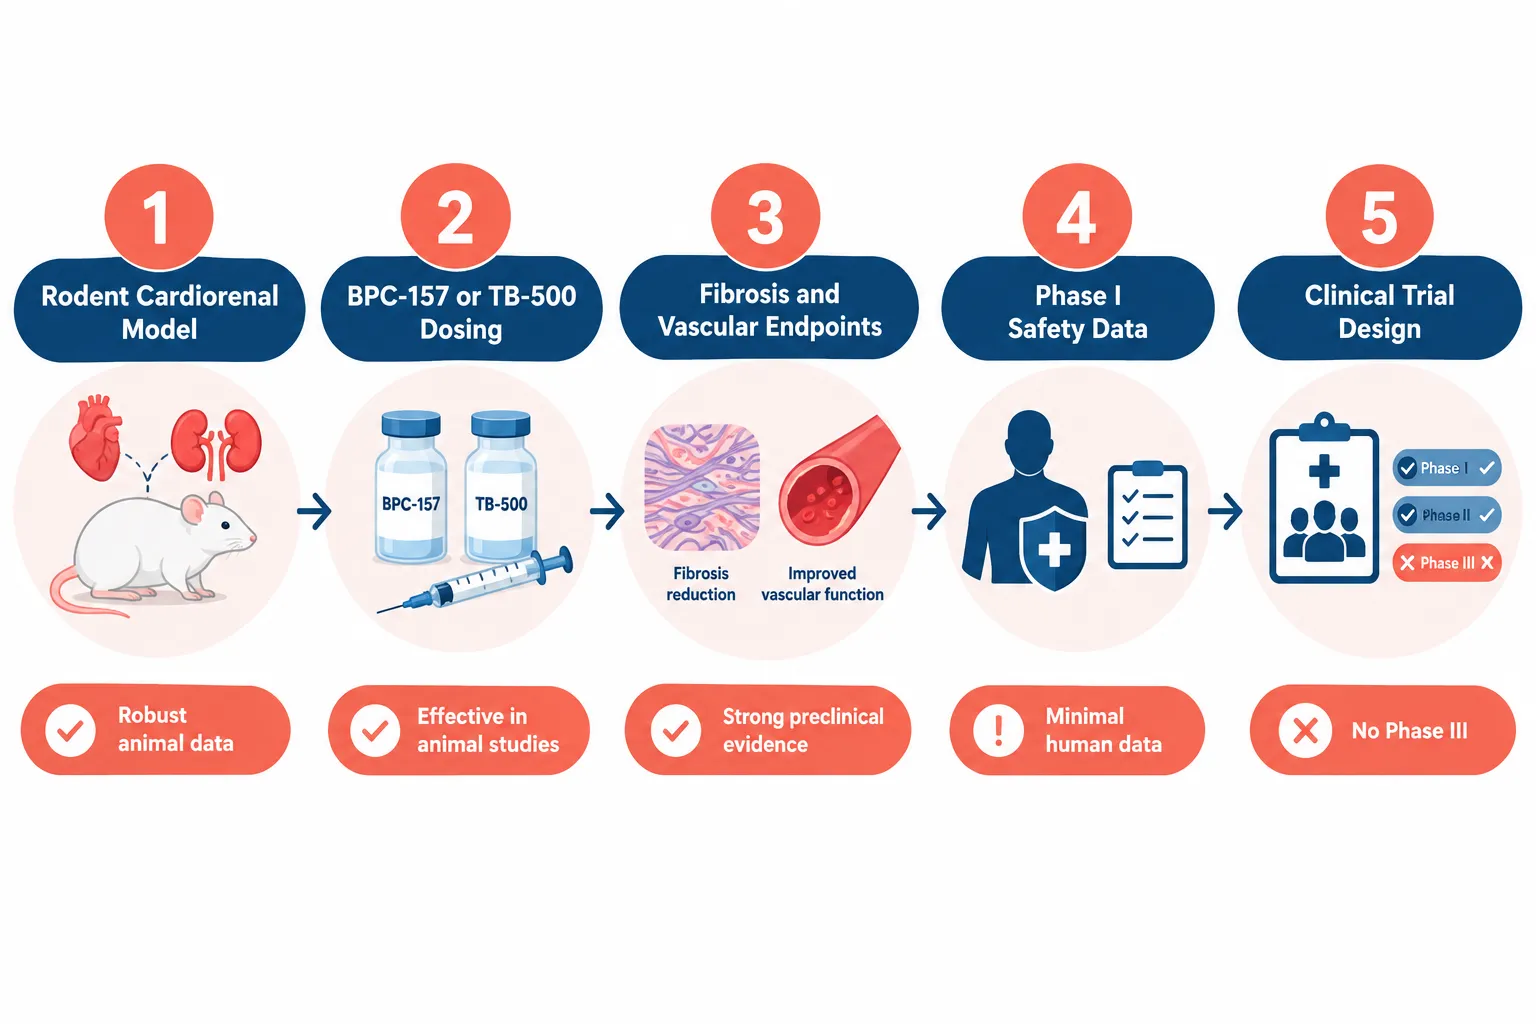
The critical caveat: almost all of this evidence comes from rodent and small-animal models. Current human trials for BPC-157 focus on musculoskeletal repair, not cardiorenal indications. TB-500 has small human studies with mixed signals and no Phase III data. Neither peptide is approved by any regulatory agency; BPC-157 is classified as a Category 2 bulk substance in several jurisdictions.

For researchers sourcing compounds for preclinical work, working with a best peptide manufacturer that provides verified purity documentation is essential for valid experimental outcomes.

Mechanistic Complementarity: Where the Two Models Meet

Mechanistic Complementarity: Where the Two Models Meet

The most intellectually productive framing of spironolactone, cardiorenal pathways, and tissue-repair peptides, and how BPC-157 and TB-500 complement classic heart and kidney drug models, is mechanistic layering, not replacement.

Mechanism Spironolactone / Finerenone BPC-157 TB-500
Aldosterone blockade Yes No No
Anti-fibrotic signaling Yes (indirect) Yes (direct, animal data) Partial (animal data)
Angiogenesis promotion No Yes (animal data) Yes (animal data)
Cardiac structural repair No Emerging Emerging
Human outcome data Robust Minimal Minimal

The table above illustrates why these are complementary, not competing, research targets. MRAs address the neurohormonal driver of cardiorenal damage. Tissue-repair peptides, if their animal-model promise translates to humans, could address the downstream structural consequences, the scarring, the vascular rarefaction, the impaired healing that persists even after hormonal blockade.

Researchers working with 5 amino peptide compounds and related short-chain structures are increasingly interested in how these molecules interact with established pharmacological frameworks. Similarly, interest in GHK-Cu peptide for vascular and tissue remodeling endpoints reflects a broader shift toward regenerative mechanisms in cardiometabolic research.

The integrated cardiorenal model, combining MRAs, SGLT2 inhibitors, and incretin therapies, already demonstrates that multi-pathway intervention outperforms single-target strategies. The logical next research question is whether tissue-repair peptides can add a structural-regeneration layer on top of that neurohormonal foundation.

Sourcing quality compounds from a verified best peptide supplier remains a prerequisite for any preclinical work attempting to answer that question rigorously.

Conclusion

The relationship between spironolactone, cardiorenal pathways, and tissue-repair peptides, and how BPC-157 and TB-500 complement classic heart and kidney drug models, represents one of the more promising conceptual frontiers in cardiometabolic research in 2026. Spironolactone and its successor finerenone have defined the neurohormonal anti-fibrotic standard, even as large trials have refined the populations most likely to benefit. BPC-157 and TB-500 offer a mechanistically distinct toolkit, vascular repair, angiogenesis, and structural healing, that animal models suggest could layer meaningfully onto established pharmacology.

Actionable next steps for researchers:

  1. Review the current SPIRRIT-HFpEF registry data to understand real-world MRA performance benchmarks.
  2. Design preclinical cardiorenal studies that include both fibrosis endpoints (relevant to MRAs) and vascular repair endpoints (relevant to BPC-157 and TB-500).
  3. Demand purity-verified peptide compounds for any experimental work to ensure data validity.
  4. Monitor emerging Phase I human data on BPC-157 musculoskeletal trials, the safety signals from those studies will inform whether cardiorenal indications are feasible.
  5. Consider finerenone's non-steroidal MRA profile as the appropriate comparator benchmark when designing combination studies.

The gap between animal-model promise and clinical validation remains wide. Closing it requires rigorous, well-sourced research, and a clear understanding of what each drug class can and cannot do.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/spironolactone-cardiorenal-pathways-and-tissue-repair-peptides-how-bpc-157-and-t.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-13 13:04:082026-09-13 13:04:08Spironolactone, Cardiorenal Pathways, and Tissue-Repair Peptides: How BPC-157 and TB-500 Complement Classic Heart and Kidney Drug Models
Spironolactone vs Research-Use Peptides: How Tissue-Repair Peptides Like BPC-157 and TB-500 Complement Classic Cardiorenal Drugs

Spironolactone vs Research-Use Peptides: How Tissue-Repair Peptides Like BPC-157 and TB-500 Complement Classic Cardiorenal Drugs

September 5, 2026/0 Comments/in Uncategorized/by

Roughly 64 million people worldwide live with heart failure, yet the drugs anchoring most treatment protocols were developed decades ago. That gap between established pharmacology and emerging regenerative science is exactly where the conversation around Spironolactone vs Research-Use Peptides: How Tissue-Repair Peptides Like BPC-157 and TB-500 Complement Classic Cardiorenal Drugs becomes most relevant for researchers and clinicians trying to understand what each tool does, and what it cannot.

Key Takeaways

  • Spironolactone is a well-validated aldosterone antagonist with proven mortality benefits in heart failure with reduced ejection fraction (HFrEF), but its utility in HFpEF and chronic kidney disease is narrower than once assumed.
  • The SPIRIT-HF trial (2026) confirmed spironolactone does not significantly reduce cardiovascular death or HF hospitalization in HFpEF or mildly reduced ejection fraction populations.
  • Research-use peptides BPC-157 and TB-500 operate through distinct tissue-repair and angiogenic pathways that do not overlap with aldosterone blockade.
  • In preclinical frameworks, these peptides are studied as complementary agents rather than replacements for classic cardiorenal drugs.
  • Rigorous translational research design is essential before any conclusions about combined protocols can be drawn.

How Spironolactone Works in Cardiorenal Disease

Spironolactone is a potassium-sparing diuretic and aldosterone receptor antagonist with a long clinical track record. It is FDA-approved for HFrEF, resistant hypertension, primary hyperaldosteronism, cirrhotic edema, nephrotic-syndrome edema, and hypokalemia. In patients with NYHA class II, IV HFrEF, guidelines recommend its use when renal function and potassium levels are adequately controlled.

The landmark RALES trial established that spironolactone reduced all-cause mortality by approximately 30% and heart-failure hospitalization by roughly 35% in chronic HFrEF with ejection fraction below 35%. Real-world data in older populations have reinforced these findings, showing an 8-13% lower risk of mortality and HF readmission when eligibility criteria are respected.

How Spironolactone Works in Cardiorenal Disease

However, 2026 data have sharpened the boundaries of that benefit. The SPIRIT-HF trial, presented at ACC.26 in March 2026, found that spironolactone did not significantly reduce the composite of HF hospitalization and cardiovascular death over 24 months in patients with heart failure with preserved or mildly reduced ejection fraction (HFpEF/HFmrEF). Event rates were 10.8 versus 12.7 per 100 patient-years for placebo versus spironolactone, a difference that did not reach significance. Secondary analyses also showed higher rates of total hospitalizations, hypotension, renal events, and hyperkalemia in the spironolactone group.

Earlier HFpEF work had similarly concluded that spironolactone may improve diastolic function and left ventricular remodeling without clearly reducing all-cause or cardiovascular mortality, positioning it as a selective rather than universal therapy.

In chronic kidney disease (CKD), the picture is equally nuanced. Hospital-based cohort data show spironolactone use associated with increased all-cause mortality and severe hyperkalemia, yet reduced major adverse cardiovascular events, driven largely by lower stroke risk. In advanced CKD combined with HFpEF, very close laboratory surveillance is mandatory given the elevated risks of hyperkalemia and worsening renal function. Studies in advanced heart failure do suggest that higher spironolactone doses can be generally safe when patients are already on ACE inhibitors, beta-blockers, and loop diuretics, provided careful outpatient monitoring is in place.

Key insight: Spironolactone's power lies in aldosterone blockade and fluid regulation, it does not directly promote tissue regeneration, angiogenesis, or extracellular matrix repair.

Understanding Research-Use Peptides: BPC-157 and TB-500

The term "research-use peptides" refers to compounds studied exclusively in preclinical and laboratory settings, not approved for human therapeutic use. BPC-157 (Body Protection Compound-157) and TB-500 (a synthetic analog of Thymosin Beta-4) are two of the most studied examples in tissue repair research.

BPC-157 is a 15-amino-acid peptide derived from a gastric protein. In animal models, it has been studied for its effects on:

  • Accelerating tendon and ligament healing
  • Promoting angiogenesis via upregulation of VEGFR2
  • Modulating nitric oxide pathways
  • Reducing fibrotic tissue formation

TB-500 is associated with actin-binding activity and has been investigated for its role in cell migration, wound healing, and anti-inflammatory signaling. Research into tissue repair pathways suggests TB-500 may support cardiac muscle recovery in ischemia models by reducing apoptosis and promoting endothelial repair.

Understanding Research-Use Peptides: BPC-157 and TB-500

Both peptides act through mechanisms entirely distinct from aldosterone blockade. Where spironolactone controls fluid retention and electrolyte balance, BPC-157 and TB-500 target the cellular machinery of repair, collagen synthesis, angiogenesis, and inflammatory resolution. This distinction is what makes them conceptually complementary in research frameworks rather than interchangeable.

For researchers interested in broader regenerative applications, systemic peptide research and tissue remodeling resources provide additional context on how these compounds are being modeled across organ systems.

Spironolactone vs Research-Use Peptides: Designing Complementary Research Frameworks

When researchers frame the question of Spironolactone vs Research-Use Peptides: How Tissue-Repair Peptides Like BPC-157 and TB-500 Complement Classic Cardiorenal Drugs, the most productive framing is not competition but layered inquiry. Each class of compound addresses a different biological problem.

Feature Spironolactone BPC-157 / TB-500
Primary mechanism Aldosterone receptor antagonism Angiogenesis, actin binding, tissue repair
Regulatory status FDA-approved (multiple indications) Research use only (preclinical)
Target tissue Kidney, heart, vasculature Musculoskeletal, cardiac, GI, vascular
Key risk Hyperkalemia, renal impairment Limited long-term safety data
Research gap addressed Fluid overload, aldosterone excess Structural repair, regeneration

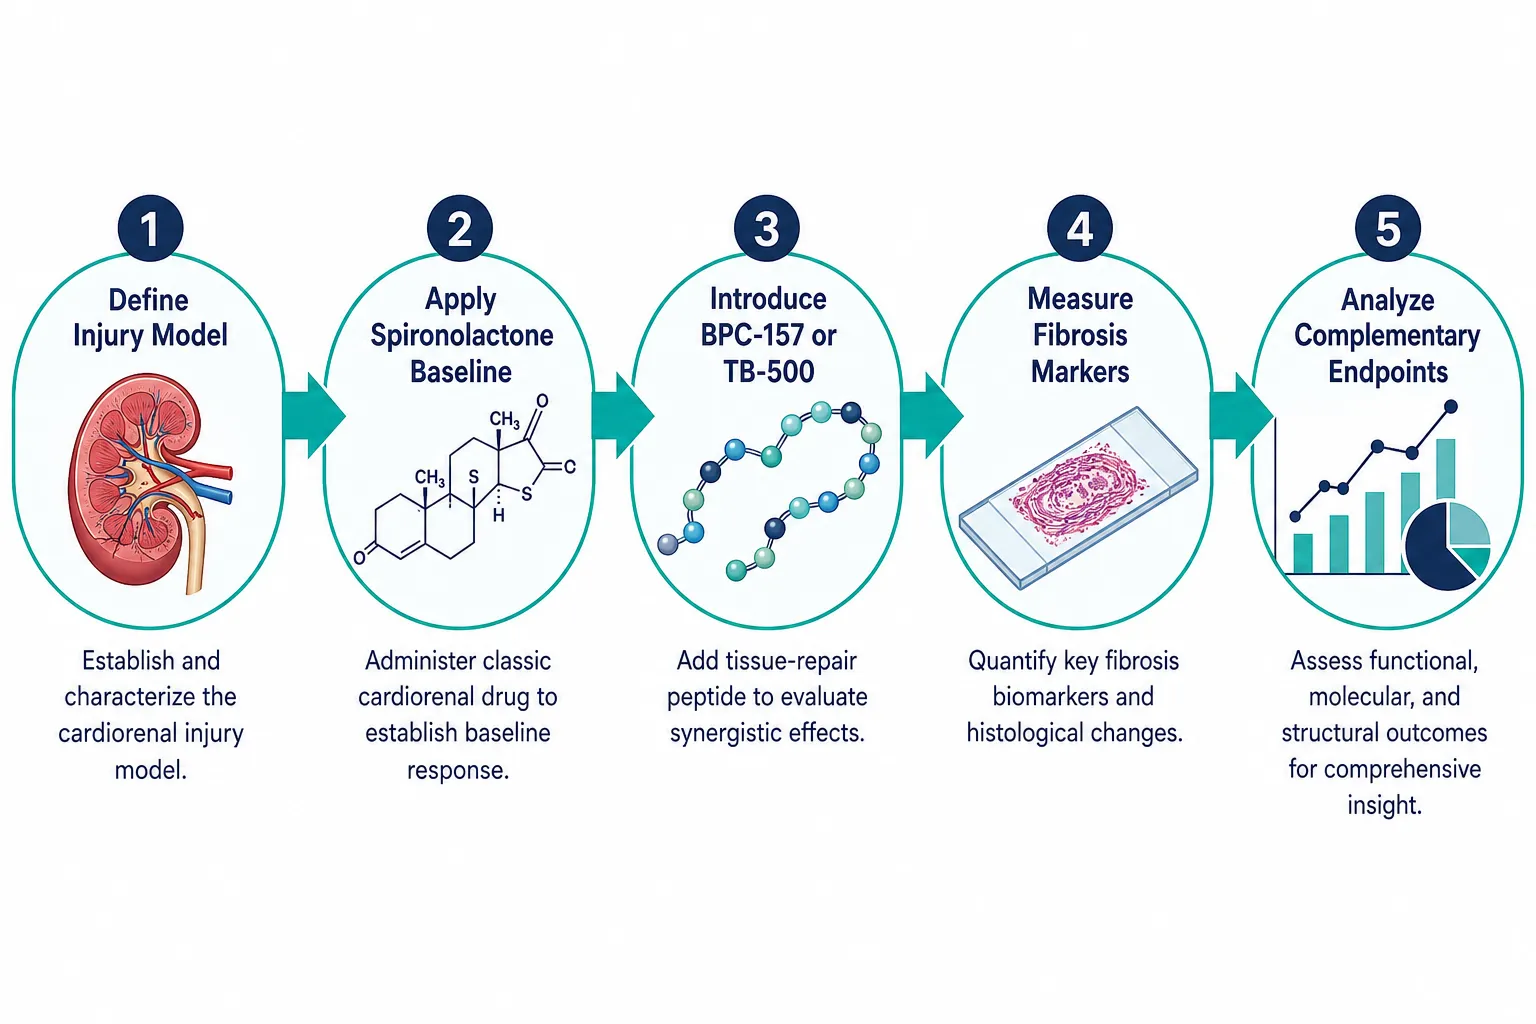
In well-designed preclinical models, a spironolactone baseline can control the hemodynamic and electrolyte environment while peptide interventions are assessed for their structural repair effects. This layered approach aligns with principles outlined in translational research design, where controlling one variable allows cleaner measurement of another.

Spironolactone vs Research-Use Peptides: Designing Complementary Research Frameworks

It is also worth noting that mitochondrial health is an emerging endpoint in cardiorenal research. Resources like SS-31 mitochondrial research themes illustrate how peptide science is expanding into energy metabolism, another domain where classic diuretics have no direct action.

Three principles for sound comparative research design:

  1. Establish baseline pharmacology, document spironolactone's hemodynamic effects before introducing peptide variables.
  2. Use orthogonal endpoints, measure fibrosis markers, angiogenic density, and electrolyte panels separately to avoid conflating mechanisms.
  3. Account for CKD status, renal function alters both spironolactone metabolism and peptide clearance, making it a critical covariate.

Conclusion

The debate framed as Spironolactone vs Research-Use Peptides: How Tissue-Repair Peptides Like BPC-157 and TB-500 Complement Classic Cardiorenal Drugs is ultimately a false competition. Spironolactone remains a cornerstone of HFrEF management with strong mortality data, but 2026 evidence from SPIRIT-HF confirms its limits in HFpEF and CKD populations. Research-use peptides like BPC-157 and TB-500 operate through entirely different biological pathways, targeting structural repair rather than fluid regulation, which makes them conceptually additive in laboratory frameworks.

Actionable next steps for researchers:

  • Review current SPIRIT-HF data to understand the precise HFpEF population where spironolactone adds limited benefit.
  • Explore tissue repair research literature to identify validated preclinical endpoints for BPC-157 and TB-500.
  • Design studies with orthogonal outcome measures so that cardiorenal drug effects and peptide-mediated repair signals can be distinguished cleanly.
  • Monitor electrolyte and renal function parameters rigorously in any model combining aldosterone antagonism with systemic peptide administration.
  • Consult translational research design frameworks before scaling from animal models to more complex study protocols.

The future of cardiorenal research likely lies not in choosing between classic drugs and regenerative peptides, but in understanding precisely where each one's mechanism begins and ends.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/spironolactone-vs-research-use-peptides-how-tissue-repair-peptides-like-bpc-157.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-05 13:05:552026-09-05 13:05:55Spironolactone vs Research-Use Peptides: How Tissue-Repair Peptides Like BPC-157 and TB-500 Complement Classic Cardiorenal Drugs
Collagen and GHK-Cu Peptides: How Copper-Dependent Collagen Signaling Differs From Classic Collagen Supplements in Research

Collagen and GHK-Cu Peptides: How Copper-Dependent Collagen Signaling Differs From Classic Collagen Supplements in Research

September 3, 2026/0 Comments/in Uncategorized/by

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'Collagen and GHK-Cu Peptides: How' in crisp white modern sans-serif centered on a deep teal semi-transparent overlay panel, 8% safe margins from every edge, no character touches the border. Background: stunning macro editorial photograph of copper-toned molecular lattice structures blending into luminous skin-tone dermal fiber networks, with a subtle copper peptide vial in soft focus at lower right, rich teal and copper color palette, editorial science magazine aesthetic, bright studio lighting, high contrast, professional depth of field.","content":["Annotated mechanism-of-action diagram landscape format (1536×1024): two-panel split-screen comparison guide. Left panel labeled 'Classic Collagen Supplement' shows a stylized oral capsule releasing glycine-proline-hydroxyproline peptide fragments into a bloodstream illustration, with callout labels: 'Amino acid substrate supply', 'Systemic fibroblast stimulation', 'No copper delivery', 'Hydration and elasticity endpoint'. Right panel labeled 'GHK-Cu Copper Peptide' shows a molecular tripeptide structure with a copper ion chelated at center, callout lines pointing to: 'Cu(II) cofactor delivery', 'Lysyl oxidase activation', 'Collagen cross-linking', 'TGF-beta signaling cascade'. Clean white background, teal-and-copper palette, thin callout lines, editorial medical-science illustration style, sharp typography, 5% safe margins on all labels.","Numbered step-by-step mechanism flow diagram landscape format (1536×1024): five sequential horizontal steps illustrating GHK-Cu signal cascade in human dermal fibroblasts. Step 1 labeled 'GHK-Cu binds fibroblast receptor' with small copper-tripeptide icon. Step 2 labeled 'TGF-beta1 and Smad2/3 phosphorylation' with phosphorylation arrow icon. Step 3 labeled 'COL1A1 and COL3A1 gene transcription' with DNA helix icon. Step 4 labeled 'NRF2-HO-1 antioxidant activation' with shield icon. Step 5 labeled 'MMP-TIMP rebalancing and ECM remodeling' with matrix fiber network icon. Each step in a rounded card with copper-to-teal gradient progression, thin connecting arrows between cards, dark navy background for contrast, bold white short labels, editorial scientific infographic style, fully inside 5% safe margins.","Split-screen editorial documentary photograph landscape format (1536×1024): left half shows a close-up of a laboratory bench with small glass vials of hydrolyzed collagen powder supplement beside a measuring scoop, warm natural studio lighting, soft-focus background of clinical trial documents and skin elasticity measurement printouts, label overlay 'Oral Collagen: Substrate Supply' in clean navy sans-serif. Right half shows a high-magnification microscopy-style rendering of copper peptide molecular structures in a dermal collagen fiber matrix, glowing copper and teal bioluminescent tones, label overlay 'GHK-Cu: Signal Plus Cofactor' in white sans-serif. Central dividing line is a thin copper-colored vertical rule. Magazine editorial quality, high contrast, rich color separation between warm left and cool right panels, all labels inside 5% safe margins, 1536×1024 landscape."]

Professional landscape hero image () with a reading "Collagen and GHK-Cu Peptides: How". CRITICAL TYPOGRAPHY RULES: render

A single copper ion bound to a three-amino-acid peptide can trigger a cascade of collagen synthesis, antioxidant defense, and matrix remodeling that no amount of hydrolyzed collagen powder has been shown to replicate. That distinction sits at the heart of the growing research interest in GHK-Cu, and it is precisely why understanding collagen and GHK-Cu peptides: how copper-dependent collagen signaling differs from classic collagen supplements in research matters for anyone working in skin biology, tissue repair, or peptide science.

Key Takeaways

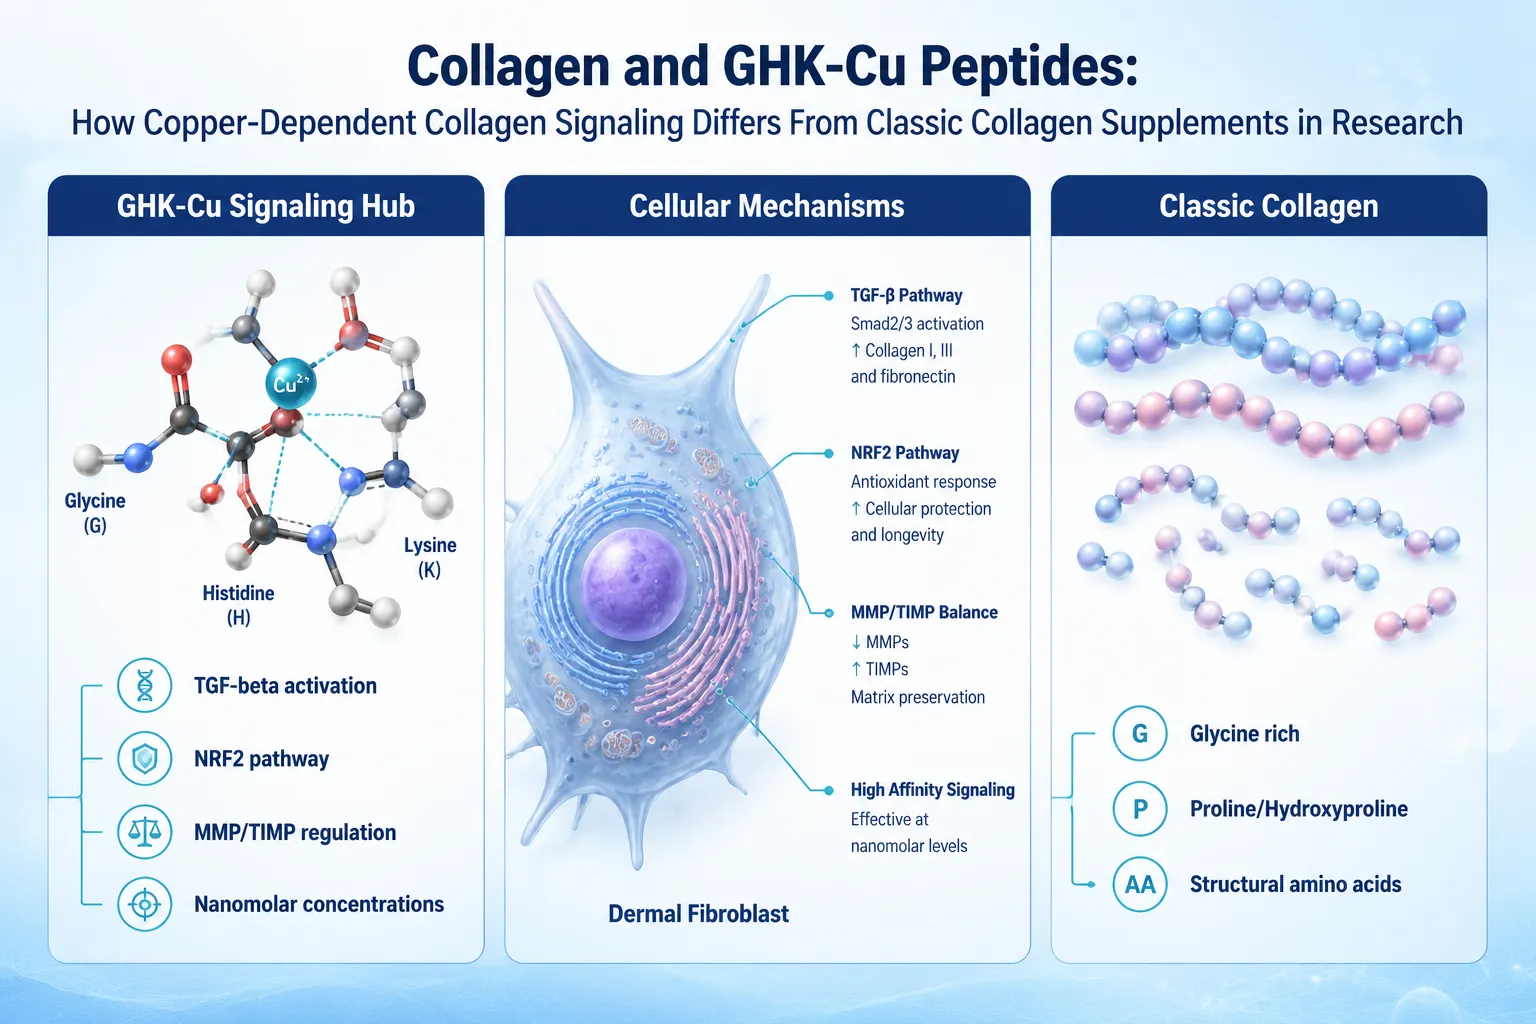
  • GHK-Cu is a copper-chelating tripeptide that acts as a signaling hub, activating TGF-beta, NRF2, and MMP/TIMP pathways in dermal fibroblasts at nanomolar concentrations.
  • Classic hydrolyzed collagen supplements supply structural amino acids and bioactive fragments that modestly improve skin hydration and elasticity but do not deliver targeted copper or activate the same enzymatic pathways.
  • GHK-Cu provides copper as a cofactor for lysyl oxidase, the enzyme that cross-links collagen and elastin fibers, a function oral collagen supplements do not perform.
  • In vitro studies report collagen synthesis increases of roughly 70-200% with GHK-Cu at optimal concentrations, while clinical trials of oral collagen show small-to-moderate standardized mean differences of approximately 0.4-0.6 for hydration and elasticity.
  • Oral collagen has multiple large randomized controlled trials supporting cosmetic benefits; GHK-Cu's human clinical evidence is still emerging as of 2026.

What Are Classic Collagen Supplements and What Does the Research Show?

Hydrolyzed collagen supplements, sold as collagen peptides, collagen hydrolysate, or marine collagen, are produced by enzymatically breaking down animal connective tissue into short peptide fragments. These fragments are rich in glycine, proline, and hydroxyproline, the same amino acids that form the triple-helix backbone of structural collagen in human skin, tendons, and cartilage.

What Are Classic Collagen Supplements and What Does the Research Show?

The clinical evidence base for oral collagen is now substantial. A July 2026 meta-analysis of 35 randomized controlled trials involving 2,534 participants found that oral collagen peptides significantly improved instrumental measures of skin hydration (standardized mean difference approximately 0.44), elasticity (SMD approximately 0.62), and reduced transepidermal water loss. A separate August 2026 systematic review examining 11 studies and 805 patients confirmed gains in skin elasticity, hydration, and dermal collagen density, with favorable short-to-medium-term safety. A 2024 double-blind, placebo-controlled trial using confocal laser scanning microscopy even documented measurable improvements in facial skin collagen architecture after 12 weeks of supplementation.

However, current expert consensus describes oral collagen as a "functional systemic moisturizer" with modest anti-aging effects. Effect sizes are real but not dramatic, most studies use daily doses of 1.6-10 grams over 8-12 weeks, and a notable proportion of the research is industry-sponsored. Critically, oral collagen does not deliver copper, does not directly activate enzymatic cross-linking, and shows little evidence of finely tuning matrix metalloproteinase (MMP) or tissue inhibitor of metalloproteinase (TIMP) balance. For deeper context on skin biology research and how dermal structure is studied, that distinction becomes increasingly important.

GHK-Cu as a Copper-Dependent Collagen Signaling Hub

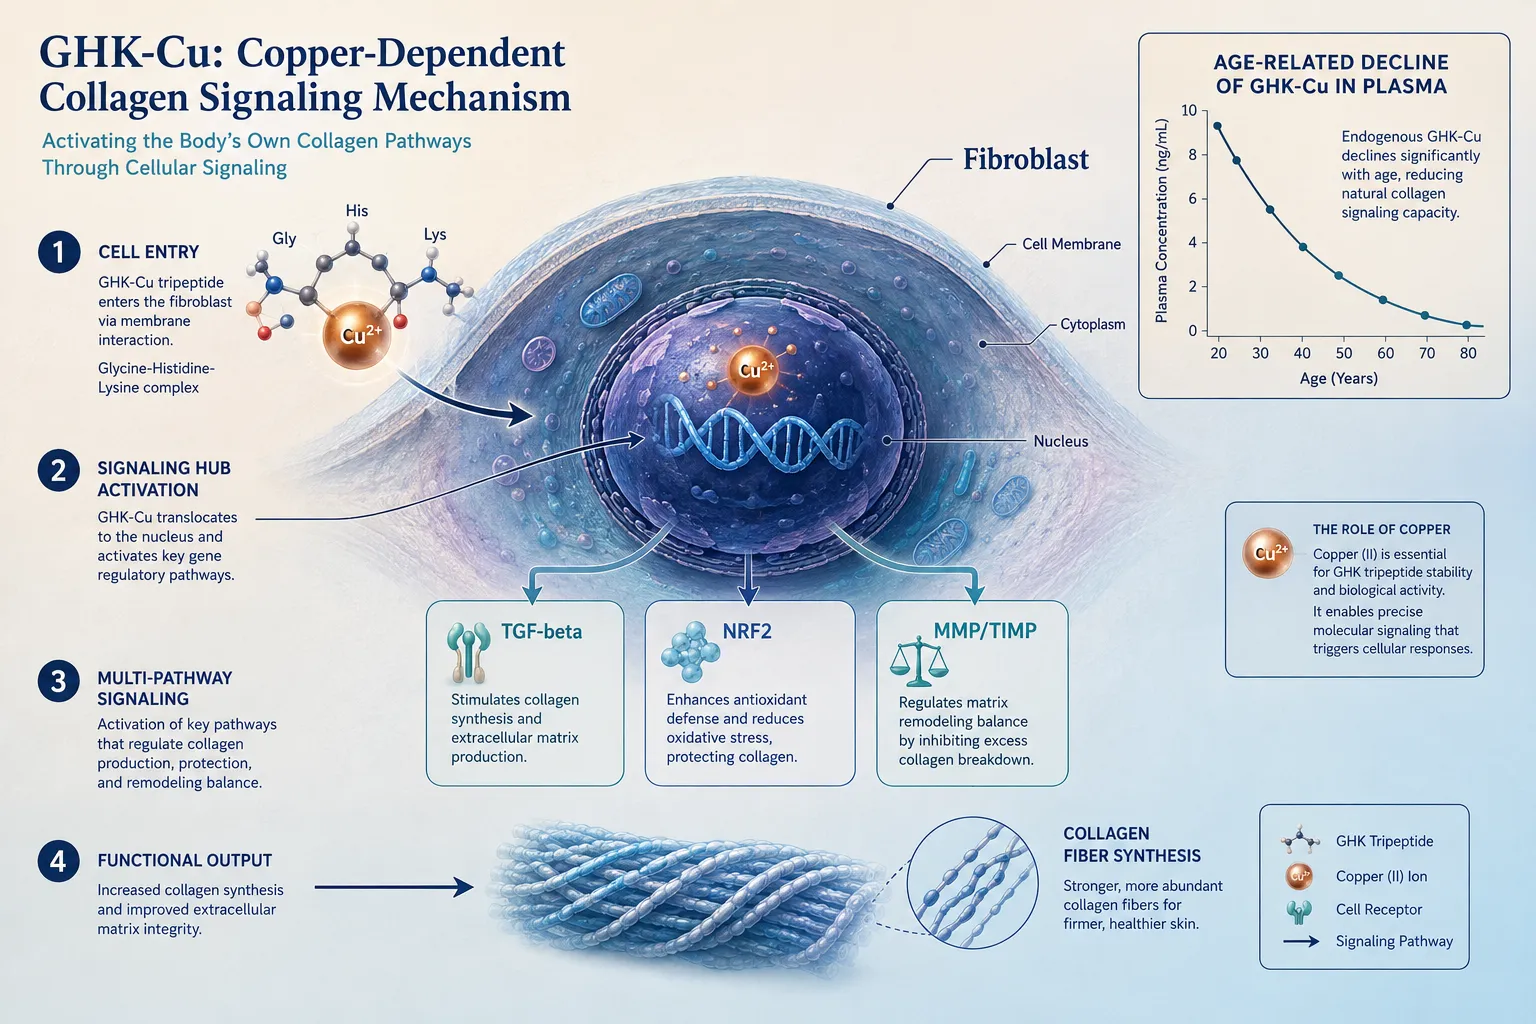
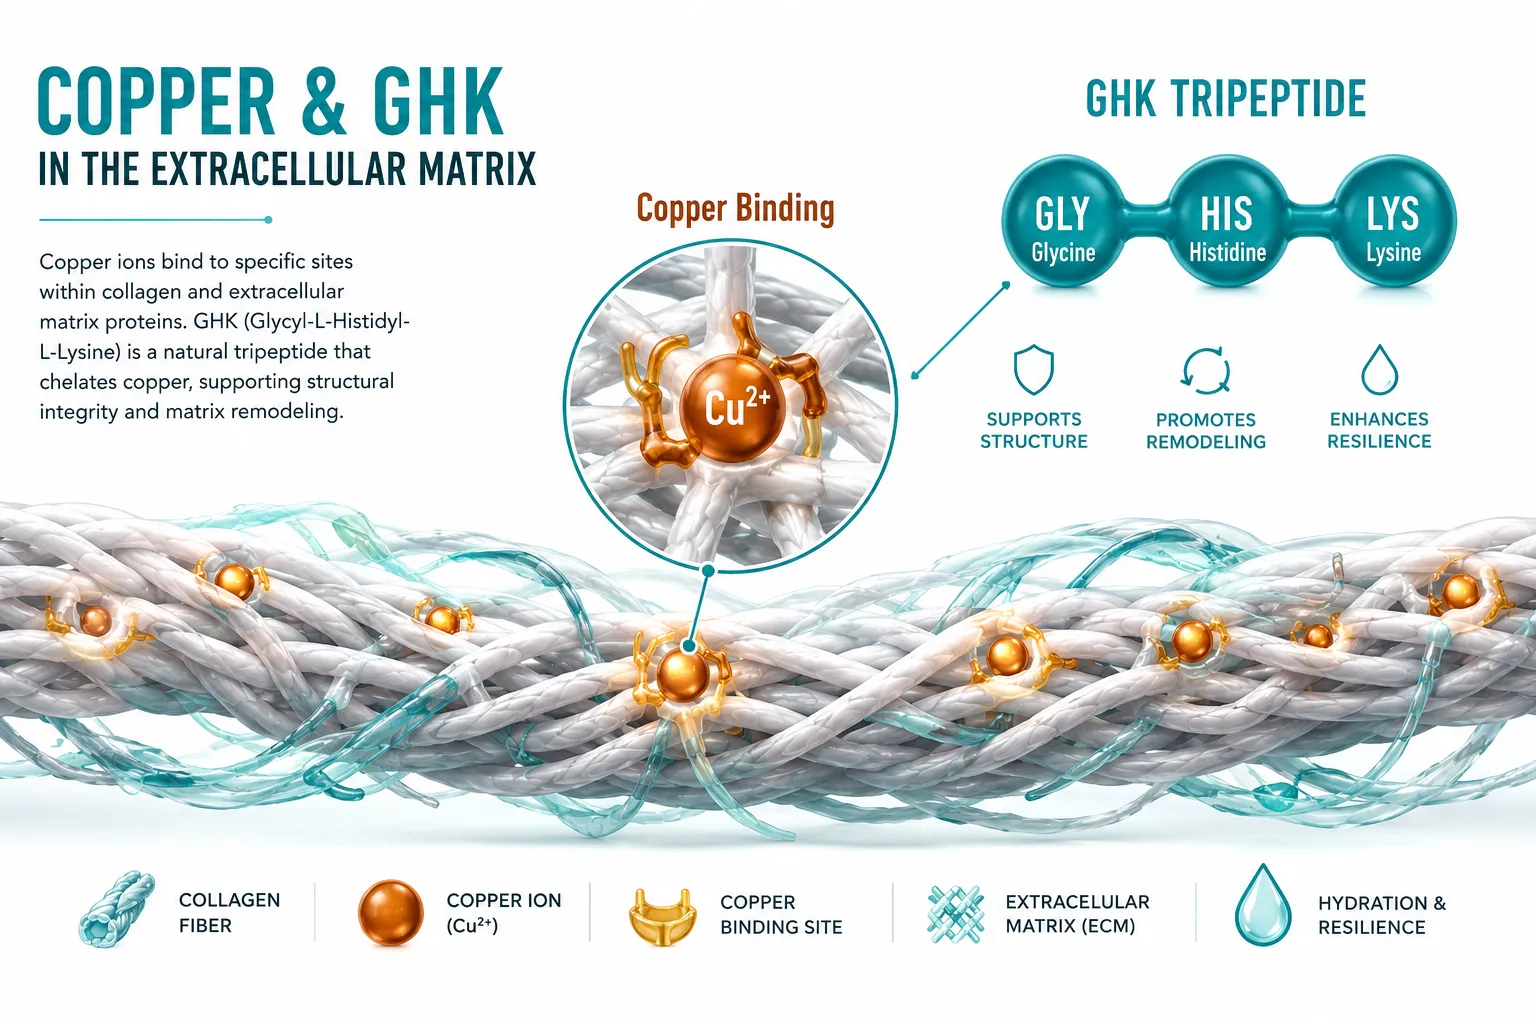
GHK-Cu (glycine-histidine-lysine complexed with copper II) is a naturally occurring tripeptide found in human plasma, saliva, and urine. Its concentration declines significantly with age, which has prompted research interest in its role in skin aging and tissue repair research.

What separates GHK-Cu from a simple collagen precursor is its dual identity as both a signaling molecule and a copper delivery vehicle.

Signal cascades activated by GHK-Cu include:

  • TGF-beta1/beta2 with Smad2/3 phosphorylation, driving transcription of COL1A1 and COL3A1 (the genes for collagen types I and III)
  • PI3K-Akt survival signaling in fibroblasts, supporting cell viability during remodeling
  • NRF2-HO-1 antioxidant pathway, upregulating protective enzymes in the dermal matrix
  • MMP/TIMP rebalancing, suppressing excessive matrix degradation while allowing controlled remodeling

In human dermal fibroblast studies, GHK-Cu upregulates collagen types I and III, elastin, and glycosaminoglycans, with collagen synthesis increases in the range of 70-200% versus controls at optimal nanomolar concentrations. Notably, these effects begin at picomolar-to-nanomolar concentrations (roughly 10^-12 to 10^-9 M) and are independent of cell proliferation, meaning GHK-Cu is stimulating biosynthesis, not simply causing cells to divide.

GHK-Cu as a Copper-Dependent Collagen Signaling Hub

This level of targeted pathway engagement is not observed with oral collagen supplementation, which primarily provides amino acid substrate and may stimulate fibroblasts indirectly through systemic peptide absorption. For researchers exploring therapeutic peptides with multi-pathway activity, GHK-Cu represents a mechanistically distinct category.

How Copper-Dependent Collagen Signaling Differs From Classic Collagen Supplements in Research: The Enzymatic Cofactor Argument

The most structurally important distinction in the collagen and GHK-Cu peptides: how copper-dependent collagen signaling differs from classic collagen supplements in research debate is the role of copper itself.

Collagen fibers require cross-linking to achieve tensile strength. This cross-linking is catalyzed by lysyl oxidase, a copper-dependent enzyme. Without adequate copper delivery to the extracellular matrix, newly synthesized collagen chains cannot be properly cross-linked, resulting in structurally weaker fibers. GHK-Cu delivers Cu(II) directly to this enzymatic machinery. It also contributes superoxide-dismutase-like antioxidant activity, protecting the dermal matrix from oxidative degradation.

Classic collagen supplements provide none of this. They supply the raw amino acid building blocks, the bricks, but not the mortar or the construction crew.

Research Perspective: “GHK-Cu acts as signal plus cofactor; oral collagen acts as substrate plus systemic modulation.”, Emerging framing in 2026 peptide and aesthetic medicine commentaries.

This distinction also extends to matrix turnover. GHK-Cu actively coordinates both synthesis and controlled breakdown of extracellular matrix (ECM) components, modulating MMPs and TIMPs to favor constructive remodeling over scarring. Oral collagen trials report changes in hydration, elasticity, and transepidermal water loss, but provide little direct evidence of finely tuned ECM turnover dynamics.

For researchers interested in tissue recovery research or synergistic peptides that act on overlapping pathways, GHK-Cu's multi-target profile is particularly relevant.

How Copper-Dependent Collagen Signaling Differs From Classic Collagen Supplements in Research: The Enzymatic Cofactor Argumen

Clinical Evidence and Safety: Where Each Approach Stands in 2026

Factor Oral Collagen Supplements GHK-Cu Peptide
Mechanism Amino acid substrate; indirect fibroblast stimulation Multi-pathway signaling; copper cofactor delivery
Effective dose range 1.6-10 g/day oral Picomolar, nanomolar (in vitro)
Human RCT evidence 35+ RCTs; meta-analyses available Early wound-healing trial registered 2026 (NCT07437586)
Effect size (human) SMD ~0.4-0.6 for hydration and elasticity Not yet established in large RCTs
Safety profile Well-established; no serious AEs in 12-week trials Favorable preclinical and cosmetic history; formal data emerging
Copper delivery None Yes, Cu(II) for lysyl oxidase and antioxidant defense

Oral collagen's safety record is strong. Multiple randomized trials report no serious adverse events over 12 weeks, with normal lab parameters and only occasional mild gastrointestinal complaints. GHK-Cu has a long track record in experimental and cosmetic applications, with mechanistic work suggesting low toxicity and broad protective actions. However, formal safety data from large, controlled human trials are still being generated, with the 2026 registered wound-healing study marking a meaningful step toward that evidence base.

Researchers interested in translational research design will note that the gap between GHK-Cu's in vitro effect sizes (70-200% collagen synthesis increases) and its as-yet-undefined human effect sizes is one of the most important open questions in the field. For those sourcing materials for preclinical work, lab tested peptides and third party peptide testing standards are essential considerations.

Conclusion

The research landscape in 2026 draws a clear line between two fundamentally different approaches to collagen biology. Oral hydrolyzed collagen supplements are well-supported by clinical trial data for modest, consistent cosmetic improvements in skin hydration and elasticity, they work as substrate-level interventions that feed the collagen production system. GHK-Cu operates at a different level entirely: it signals fibroblasts through multiple gene-regulatory pathways, delivers copper as an enzymatic cofactor for cross-linking, and coordinates active ECM remodeling in ways that oral collagen cannot replicate.

Actionable next steps for researchers and practitioners:

  • When evaluating collagen-related interventions, distinguish between substrate-supply mechanisms (oral collagen) and signaling-plus-cofactor mechanisms (GHK-Cu) before drawing comparisons.
  • Prioritize mechanistic outcome measures, MMP/TIMP ratios, COL1A1 transcription, lysyl oxidase activity, when designing GHK-Cu studies, as these capture effects that standard hydration and elasticity endpoints miss.
  • Monitor the 2026 wound-healing RCT (NCT07437586) for the first regulated human efficacy and safety data on topical GHK-Cu.
  • For preclinical work, ensure peptide purity through verified third party peptide testing to maintain experimental validity.
  • Consider GHK-Cu within the broader context of skin biology research and tissue repair research rather than as a direct substitute for or upgrade of oral collagen, they address different biological targets.

Understanding collagen and GHK-Cu peptides: how copper-dependent collagen signaling differs from classic collagen supplements in research is not about choosing one over the other. It is about applying the right tool to the right biological question, and that requires knowing exactly what each tool does at the molecular level.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/collagen-and-ghk-cu-peptides-how-copper-dependent-collagen-signaling-differs-fro.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-03 13:06:022026-09-03 13:06:02Collagen and GHK-Cu Peptides: How Copper-Dependent Collagen Signaling Differs From Classic Collagen Supplements in Research
Mesenchymal Stem Cells and Tissue-Repair Peptides: Where BPC-157, TB-500, and GHK-Cu Intersect in Regenerative Research

Mesenchymal Stem Cells and Tissue-Repair Peptides: Where BPC-157, TB-500, and GHK-Cu Intersect in Regenerative Research

September 1, 2026/0 Comments/in Uncategorized/by

Fewer than a handful of completed randomized controlled trials exist for the most widely discussed regenerative peptides in sports medicine, yet preclinical models using mesenchymal stem cells have already mapped out plausible biological mechanisms for each of them. That gap between laboratory insight and clinical proof defines exactly where regenerative research stands in 2026. Understanding Mesenchymal Stem Cells and Tissue-Repair Peptides: Where BPC-157, TB-500, and GHK-Cu Intersect in Regenerative Research requires looking at both the cellular biology and the evolving clinical evidence with equal rigor.

Key Takeaways

  • Mesenchymal stem cells (MSCs) are a primary model system for studying how regenerative peptides influence angiogenesis, extracellular matrix remodeling, and cell migration.
  • BPC-157, TB-500, and GHK-Cu each target distinct but overlapping pathways relevant to tissue repair, making them frequent subjects of multi-peptide research protocols.
  • As of early 2026, the first randomized Phase 2 human trial of BPC-157 is actively recruiting, marking a significant milestone after years of preclinical-only data.
  • Regulatory status varies by peptide and jurisdiction; researchers must verify compliance before sourcing or using these compounds.
  • MSC co-culture models remain the most reproducible in vitro framework for isolating peptide-specific effects on wound healing and connective tissue regeneration.

What Are Mesenchymal Stem Cells and Why Do They Matter in Peptide Research

What Are Mesenchymal Stem Cells and Why Do They Matter in Peptide Research

Mesenchymal stem cells are multipotent stromal cells found in bone marrow, adipose tissue, and connective tissue throughout the body. They can differentiate into osteoblasts, chondrocytes, and myofibroblasts, but their most research-relevant function may be paracrine signaling, the release of growth factors and cytokines that coordinate local tissue repair. This makes MSC culture systems an ideal platform for tissue repair research involving bioactive peptides.

When researchers add BPC-157, TB-500, or GHK-Cu to MSC cultures, they can measure discrete outputs: changes in vascular endothelial growth factor (VEGF) expression, collagen synthesis rates, cell migration velocity, and inflammatory cytokine profiles. These endpoints translate directly to the biological processes that govern wound closure, tendon healing, and cartilage restoration.

Why MSCs specifically? Several reasons make them the preferred model:

  • They express receptors relevant to all three peptides under study.
  • They are relatively easy to harvest and standardize across experiments.
  • Their paracrine outputs mirror the signaling environment of an actual injury site.
  • Results from MSC models have historically shown reasonable predictive validity for in vivo outcomes.

BPC-157, TB-500, and GHK-Cu: Distinct Mechanisms, Shared Endpoints

BPC-157, TB-500, and GHK-Cu: Distinct Mechanisms, Shared Endpoints

Each peptide in this triad operates through a different primary mechanism, which is precisely what makes their intersection in tissue regeneration research so scientifically interesting.

BPC-157: Angiogenesis and Cytoprotection

BPC-157 (Body Protection Compound-157) is a synthetic pentadecapeptide derived from a gastric protein. In MSC models, it consistently upregulates VEGF and promotes the formation of new capillary networks, a process called angiogenesis. Without adequate blood supply, injured tissue cannot receive the oxygen and nutrients needed for repair. BPC-157 also appears to modulate nitric oxide pathways, which influences vascular tone and reduces oxidative stress at injury sites.

Clinically, the evidence base remains early. As of early 2026, the entire published human dataset consists of roughly three small pilot trials plus limited Phase I/II safety data. However, a landmark development occurred in February 2026: the first randomized, double-blind, placebo-controlled Phase 2 human trial of injectable BPC-157 began recruiting 120 participants with MRI-confirmed acute grade II hamstring strains. The co-primary endpoints are time to return to unrestricted sport and change in MRI-assessed injury volume at day 14, endpoints directly informed by MSC angiogenesis data. Explore broader systemic peptide research for related context.

TB-500: Actin Dynamics and Cell Migration

TB-500 is a synthetic analog of Thymosin Beta-4, a ubiquitous intracellular protein that regulates actin polymerization. Actin filament dynamics govern how cells move, a critical function during wound healing when fibroblasts and MSCs must migrate into a lesion site. In co-culture experiments, TB-500 accelerates MSC migration rates and increases the expression of matrix metalloproteinases (MMPs), enzymes that break down damaged extracellular matrix to clear the way for new tissue.

TB-500's systemic distribution profile makes it relevant to tissue recovery research beyond localized injury models, as Thymosin Beta-4 is naturally upregulated across multiple organ systems following trauma.

GHK-Cu: Extracellular Matrix Remodeling and Skin Repair

GHK-Cu (glycyl-L-histidyl-L-lysine copper complex) is a naturally occurring tripeptide-copper complex with a well-documented role in extracellular matrix (ECM) remodeling. It stimulates collagen and glycosaminoglycan synthesis, activates tissue remodeling enzymes, and downregulates pro-inflammatory cytokines. In MSC models, GHK-Cu increases the deposition of type I and type III collagen, the structural proteins most critical to tendon, skin, and ligament integrity.

GHK-Cu's dual role in skin repair pathways and deeper connective tissue remodeling makes it a frequent companion peptide in multi-agent research protocols. Its favorable safety profile in dermatological research has also supported interest in skin rejuvenation research applications.

Peptide Primary MSC Mechanism Key Research Endpoint
BPC-157 VEGF upregulation, angiogenesis Capillary density, injury volume
TB-500 Actin polymerization, cell migration Migration rate, MMP expression
GHK-Cu ECM remodeling, collagen synthesis Collagen deposition, cytokine profile

Translational Research Design and the Road Ahead

Translational Research Design and the Road Ahead

The convergence of MSC biology and peptide pharmacology has opened a productive path for translational research design. The standard pipeline moves from MSC co-culture assays to rodent injury models, and finally to human trials, each stage refining dosing parameters and endpoint selection.

A key challenge in 2026 is regulatory alignment. BPC-157 is currently categorized by the U.S. FDA as a compound requiring an Investigational New Drug (IND) application for human use, which is why the February 2026 Phase 2 trial represents such a pivotal moment. TB-500 and GHK-Cu occupy different regulatory positions depending on jurisdiction and application route, and researchers sourcing these compounds must verify current compliance requirements before initiating any protocol.

Best practices for research teams working at this intersection include:

  • Using validated MSC isolation and culture protocols to ensure reproducibility.
  • Selecting endpoints that map directly to clinical outcomes (e.g., collagen density to tensile strength).
  • Running single-peptide controls before multi-peptide combination experiments to isolate mechanism.
  • Documenting regulatory status at the time of procurement and throughout the study period.

The Glow Blend concept, combining GHK-Cu with complementary peptides in a single research formulation, represents one direction this multi-agent approach is heading, particularly in skin barrier research and dermal regeneration studies where layered ECM effects are desirable.

Conclusion

The intersection of mesenchymal stem cell biology and tissue-repair peptides is one of the most active and promising areas in regenerative research today. BPC-157, TB-500, and GHK-Cu each contribute distinct mechanisms, angiogenesis, cell migration, and ECM remodeling respectively, that collectively address the core biology of tissue healing. MSC models provide the reproducible, mechanistically transparent platform needed to study these effects before translating findings to clinical settings.

Actionable next steps for researchers and research institutions in 2026:

  1. Monitor the outcomes of the ongoing BPC-157 Phase 2 trial, as its results will set the evidentiary standard for injectable peptide interventions in musculoskeletal injury.
  2. Prioritize single-peptide MSC assays before designing combination protocols, to build a defensible mechanistic rationale.
  3. Verify regulatory classification for each peptide in the relevant jurisdiction before procurement.
  4. Align in vitro endpoints with clinically meaningful outcomes to strengthen the translational case for future IND applications.

The science is advancing. Rigorous methodology and regulatory awareness are what will carry it from the laboratory into validated clinical practice.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/mesenchymal-stem-cells-and-tissue-repair-peptides-where-bpc-157-tb-500-and-ghk-c.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-01 13:05:372026-09-01 13:05:37Mesenchymal Stem Cells and Tissue-Repair Peptides: Where BPC-157, TB-500, and GHK-Cu Intersect in Regenerative Research
GHK-Cu Peptide: Collagen Synthesis, Tissue Repair, and Longevity Research Applications

GHK-Cu Peptide: Collagen Synthesis, Tissue Repair, and Longevity Research Applications

August 9, 2026/0 Comments/in Uncategorized/by

A single copper ion can change how a peptide behaves at the molecular level. That principle sits at the heart of GHK-Cu research, a tripeptide-copper complex that has attracted serious scientific attention since Loren Pickart first isolated it from human plasma in 1973. Today, GHK-Cu peptide: collagen synthesis, tissue repair, and longevity research applications represent one of the more mechanistically rich areas in peptide biology, drawing interest from researchers working across dermatology, wound healing, and aging science.

Bright editorial infographic-style landscape (): cross-section diagram of extracellular matrix collagen fibers with copper

Key Takeaways

  • GHK-Cu is a naturally occurring tripeptide (glycine-histidine-lysine) that binds copper(II) ions, enabling a wide range of biological signaling functions.
  • Research shows GHK-Cu upregulates collagen, elastin, and glycosaminoglycan synthesis by activating fibroblast activity in the extracellular matrix.
  • Beyond skin biology, GHK-Cu has demonstrated tissue-repair activity in wound models, nerve tissue, and lung fibrosis research.
  • Longevity researchers have identified GHK-Cu as a potential gene-expression modulator, with studies linking it to reversal of aging-associated transcriptional changes.
  • GHK-Cu is frequently studied alongside other repair-focused peptides such as BPC-157 and TB-500 in multi-compound research protocols.

The Copper-Binding Biology Behind GHK-Cu

The letters in GHK stand for the three amino acids that form this tripeptide: glycine, histidine, and lysine. What makes GHK-Cu distinct from many other short peptides is its high-affinity binding to copper(II) ions. This copper-chelating property is not incidental, it is central to the compound's biological activity.

Copper is a trace element involved in over 30 enzymatic reactions in the human body. Enzymes like lysyl oxidase (which crosslinks collagen and elastin fibers) and superoxide dismutase (an antioxidant enzyme) depend on copper as a cofactor. When GHK binds copper, it acts as a bioavailable copper-delivery vehicle, shuttling the ion to sites where these enzymes are active.

To understand how short peptides like GHK-Cu function within broader molecular frameworks, the polypeptide peptides explained: structure, function, and research resource provides useful foundational context.

Key copper-dependent processes relevant to GHK-Cu research:

Process Relevant Enzyme Role in Tissue Biology
Collagen crosslinking Lysyl oxidase Structural integrity of ECM
Antioxidant defense Superoxide dismutase Reduces oxidative damage
Angiogenesis Ceruloplasmin New blood vessel formation
Melanin synthesis Tyrosinase Pigmentation and skin repair

Beyond copper delivery, GHK itself appears to function as a signaling molecule. In vitro studies have shown it can activate pathways associated with TGF-beta (transforming growth factor beta), a cytokine that drives fibroblast proliferation and matrix remodeling.

GHK-Cu Peptide: Collagen Synthesis and Extracellular Matrix Remodeling

The extracellular matrix (ECM) is the structural scaffold that surrounds cells in connective tissue. It is composed primarily of collagen fibers, elastin, fibronectin, and glycosaminoglycans (GAGs). Maintaining ECM integrity is critical for wound healing, organ function, and tissue resilience.

Research into GHK-Cu peptide: collagen synthesis, tissue repair, and longevity research applications has consistently pointed to fibroblast activation as a primary mechanism. Fibroblasts are the cells responsible for producing and maintaining ECM components. Studies have shown that GHK-Cu:

  • Increases collagen synthesis, particularly types I and III, the most abundant structural collagens
  • Upregulates elastin production, improving tissue elasticity
  • Stimulates GAG synthesis, including hyaluronic acid and dermatan sulfate, which support hydration and structural spacing in the ECM
  • Activates matrix metalloproteinases (MMPs), enzymes that break down damaged or disorganized collagen, enabling remodeling

This dual action, promoting new matrix synthesis while clearing old or damaged matrix, makes GHK-Cu particularly relevant to wound repair models. Researchers studying multi-peptide repair protocols often pair GHK-Cu with other compounds; the Skin Repair Stack (BPC-157 + TB-500 + GHK-Cu) is one documented example of this combinatorial approach in research contexts.

For broader comparison of tissue-repair peptides, the BPC-157 vs TB-500 complete research comparison guide offers useful mechanistic contrasts.

GHK-Cu Peptide: Collagen Synthesis and Extracellular Matrix Remodeling

Tissue Repair, Nerve Regeneration, and Organ-Level Research

GHK-Cu research extends well beyond skin biology. Several preclinical studies have examined its effects in:

Wound Healing Models
Animal wound models have shown accelerated closure rates and improved tensile strength in GHK-Cu-treated tissue compared to controls. The mechanism appears to involve both fibroblast recruitment and enhanced angiogenesis, the formation of new blood vessels that supply healing tissue with oxygen and nutrients.

Lung and Organ Fibrosis
Research by Pickart and colleagues identified GHK-Cu as a potential modulator of fibrotic processes in lung tissue. Rather than promoting uncontrolled fibrosis, GHK-Cu appears to support organized matrix remodeling, a distinction that has made it relevant to pulmonary research.

Nerve Tissue
Some studies have examined GHK-Cu in nerve repair contexts, with findings suggesting it may support Schwann cell activity and axonal regrowth. This aligns with its broader role in activating growth factors associated with neural tissue maintenance.

Researchers interested in mitochondrial and cellular longevity mechanisms may find it useful to compare GHK-Cu's gene-expression profile with that of other compounds; the MOTS-C mitochondrial research themes article covers complementary cellular pathways.

For foundational context on how peptides interact with biological systems at the research level, peptides 101 for research-use only buyers: structure, mechanisms, and applications provides a strong primer.

GHK-Cu Peptide: Longevity Research Applications and Gene Expression

Perhaps the most compelling recent dimension of GHK-Cu peptide: collagen synthesis, tissue repair, and longevity research applications is its potential role in gene expression modulation.

In 2010, Pickart and Margolina published analysis suggesting that GHK-Cu could reset gene expression patterns in aged human fibroblasts toward a younger phenotype. A 2014 study using the Broad Institute's Connectivity Map database found that GHK-Cu gene expression signatures overlapped with the reversal of multiple aging-associated transcriptional changes, including genes related to inflammation, oxidative stress, and DNA repair.

GHK-Cu Peptide: Longevity Research Applications and Gene Expression

Key findings from longevity-focused GHK-Cu research include:

  • Downregulation of genes associated with chronic inflammation (including several NF-kB pathway genes)
  • Upregulation of DNA repair and antioxidant defense genes
  • Potential interaction with VEGF (vascular endothelial growth factor) pathways, relevant to tissue vascularization in aging
  • Modulation of p53 pathway genes, which govern cellular senescence and apoptosis

These findings position GHK-Cu as a candidate for research into biological aging mechanisms, not merely as a cosmetic ingredient, but as a compound with plausible systemic relevance. Researchers exploring quality standards for such compounds can review Bachem and reference standards: building robust peptide benchmarks for guidance on sourcing and verification.

The BPC-157 core peptides documentation first research guide also offers a useful model for how documentation standards apply to repair-focused peptide research.

Conclusion

GHK-Cu occupies a mechanistically distinct position in the peptide research landscape. Its copper-binding biology connects it directly to enzymatic processes governing collagen crosslinking, antioxidant defense, and angiogenesis. Its fibroblast-activating properties make it relevant to ECM remodeling and wound repair research. And its emerging role in gene expression modulation places it at the intersection of tissue biology and longevity science.

Actionable next steps for researchers in 2026:

  1. Review primary literature from Pickart and Margolina alongside the 2014 Connectivity Map analysis before designing GHK-Cu protocols.
  2. Consider combinatorial study designs pairing GHK-Cu with complementary repair peptides, using documented stacks as a reference point.
  3. Verify peptide purity through third-party testing and reference standards before any experimental use.
  4. Distinguish between topical and systemic delivery contexts when interpreting existing data, as bioavailability profiles differ significantly.
  5. Monitor emerging longevity research for updates on GHK-Cu's gene-expression findings, particularly in the context of senescence and oxidative stress models.

References

  • Pickart, L. (1973). "A tripeptide from human serum which prolongs survival of normal liver cells." Journal of Theoretical Biology, 39(2), 373-382.
  • Pickart, L., & Margolina, A. (2010). "Regenerative and protective actions of the GHK-Cu peptide in the light of the new gene data." International Journal of Molecular Sciences, 11(10), 4010-4028.
  • Pickart, L., Vasquez-Soltero, J. M., & Margolina, A. (2015). "GHK peptide as a natural modulator of multiple cellular pathways in skin regeneration." BioMed Research International, 2015, 648108.
  • Pickart, L., & Margolina, A. (2018). "Regenerative and protective actions of the GHK-Cu peptide in the light of the new gene data." International Journal of Molecular Sciences, 19(7), 1987.
  • Lamb, J., et al. (2006). "The Connectivity Map: using gene-expression signatures to connect small molecules, genes, and disease." Science, 313(5795), 1929-1935.
https://www.puretestedpeptides.com/wp-content/uploads/2026/08/ghk-cu-peptide-collagen-synthesis-tissue-repair-and-longevity-research-applicati.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-09 13:05:072026-08-09 13:05:07GHK-Cu Peptide: Collagen Synthesis, Tissue Repair, and Longevity Research Applications
Complement-Dependent Cytotoxicity and Peptide-Based Assays: Safety Considerations for BPC-157, GHK-Cu, and Glow Blend Research

Complement-Dependent Cytotoxicity and Peptide-Based Assays: Safety Considerations for BPC-157, GHK-Cu, and Glow Blend Research

August 2, 2026/0 Comments/in Uncategorized/by

Less than 15% of preclinical peptide studies include formal immunotoxicology screening before advancing to in vivo models, a gap that becomes critical when working with bioactive compounds that interact with immune signaling pathways. Complement-dependent cytotoxicity and peptide-based assays: safety considerations for BPC-157, GHK-Cu, and Glow Blend research represent an emerging priority for researchers who want rigorous, reproducible data from tissue-repair and copper-binding peptide studies.

Key Takeaways

  • Complement-dependent cytotoxicity (CDC) assays measure whether a compound activates the complement system to lyse target cells, making them a core immunosafety tool.
  • BPC-157 and GHK-Cu have distinct mechanisms that can interact with immune pathways in preclinical models, warranting CDC screening.
  • Glow Blend formulations combine multiple bioactive peptides, increasing the complexity of immunological profiling.
  • Assay design, peptide purity, and concentration controls directly determine the reliability of CDC results.
  • Sourcing research-grade peptides with verified certificates of analysis is a prerequisite for valid safety screening.

Key Takeaways

Understanding Complement-Dependent Cytotoxicity in Preclinical Research

The complement system is a branch of innate immunity comprising more than 30 proteins. When activated, it forms the membrane attack complex (MAC), which punches holes in cell membranes and causes lysis. CDC assays exploit this mechanism to test whether antibodies, or, in peptide research, bioactive compounds, trigger complement activation against specific cell populations.

How a standard CDC assay works:

  1. Target cells are incubated with the test compound (e.g., BPC-157 or GHK-Cu at defined concentrations).
  2. Exogenous complement serum (typically rabbit or human) is added.
  3. After incubation, cell viability is measured using dye exclusion (trypan blue) or luminescence-based methods.
  4. Results are expressed as percentage cytotoxicity compared to positive and negative controls.

"A well-designed CDC assay does not simply detect toxicity, it identifies whether a peptide compound co-opts the complement cascade as part of its mechanism of action."

For tissue-repair peptides, this distinction matters. A compound that reduces inflammation through complement modulation may show apparent cytotoxicity in a CDC assay without being inherently harmful. Context and controls are everything.

Key variables that affect CDC assay outcomes:

Variable Impact on Results
Complement source Human vs. rabbit serum alters sensitivity
Peptide concentration Dose-dependent effects must be mapped
Incubation temperature 37 degrees C is standard; deviations skew lysis rates
Cell line selection Primary cells vs. immortalized lines respond differently
Peptide purity Impurities can independently activate complement

Purity is not a minor footnote. Researchers sourcing peptides for CDC screening should consult resources like building robust peptide benchmarks with reference standards to understand how impurity profiles from different synthesis batches can introduce false positives in complement assays.

BPC-157, GHK-Cu, and Glow Blend: Immunological Profiles in CDC Models

BPC-157, GHK-Cu, and Glow Blend: Immunological Profiles in CDC Models

BPC-157 and Complement Pathway Interactions

BPC-157 is a 15-amino-acid synthetic peptide derived from a gastric protein sequence. Preclinical data suggests it modulates nitric oxide pathways, angiogenesis, and cytokine signaling. Because cytokine networks overlap with complement regulation, researchers applying complement-dependent cytotoxicity and peptide-based assays to BPC-157 studies should account for potential indirect complement modulation rather than direct activation.

Researchers working with BPC-157 and TB-500 peptide combinations should note that stacking peptides in the same assay well can produce additive or antagonistic complement effects. Running single-compound controls alongside combination wells is non-negotiable for clean data interpretation. For a detailed comparison of these two compounds, the TB-500 vs BPC-157 research overview provides useful background on their distinct mechanisms.

GHK-Cu: Copper Binding and Immune Signaling

GHK-Cu (glycine-histidine-lysine copper complex) is a naturally occurring tripeptide with well-documented roles in wound healing, collagen synthesis, and anti-inflammatory signaling. The copper ion itself is biologically active and can influence reactive oxygen species (ROS) levels in cell culture systems.

In CDC assays, the copper component introduces a confounding variable: copper ions at supraphysiological concentrations are independently cytotoxic. Researchers must therefore:

  • Run GHK-Cu at physiologically relevant concentrations (typically 1-100 nM range in cell models).
  • Include copper sulfate controls at equivalent molar copper concentrations.
  • Distinguish peptide-mediated complement activation from copper-mediated oxidative lysis.

The GHK-Cu peptide sourcing and research guide outlines purity specifications that directly affect how copper content is quantified per batch, a critical input for accurate CDC dosing.

Glow Blend: Multi-Peptide Complexity in Safety Assays

Glow Blend formulations typically combine GHK-Cu with additional skin-repair or regenerative peptides. This multi-compound matrix complicates CDC assay design because each component may interact with complement proteins independently or synergistically.

The Glow Blend research formulation is designed for preclinical skin biology models. When running CDC safety screening on Glow Blend, researchers should:

  • Test the full blend AND individual components in parallel.
  • Use a complement titration approach to identify the lowest lytic concentration.
  • Document any synergistic cytotoxicity that exceeds the sum of individual peptide effects.

Assay Design Best Practices for Peptide Safety Screening

Assay Design Best Practices for Peptide Safety Screening

Applying complement-dependent cytotoxicity and peptide-based assays rigorously to BPC-157, GHK-Cu, and Glow Blend research requires attention to several protocol-level decisions that are often underspecified in published methods.

Critical controls for every CDC peptide assay:

  • Positive control: Known complement-activating antibody to confirm complement activity.
  • Negative control: Peptide-free vehicle (e.g., sterile water or DMSO at matched concentration).
  • Peptide-alone control: Peptide without complement serum to isolate direct cytotoxicity.
  • Complement-alone control: Serum without peptide to detect non-specific lysis.

Researchers combining peptides with growth hormone secretagogues or other compounds, such as those studying combination safety profiles of tesa and ipamorelin, should apply the same multi-control framework when CDC assays are part of their safety battery.

Sourcing considerations: Peptide purity directly determines assay validity. Researchers can review where to buy research-grade peptides for guidance on supplier qualification criteria that support defensible preclinical data.

Additionally, teams studying mitochondrial-targeted peptides alongside complement assays may find the SS-31 peptide research overview useful for understanding how cardioprotective peptides behave in immune-adjacent assay systems.

Conclusion

Complement-dependent cytotoxicity and peptide-based assays represent a rigorous, underutilized tool for characterizing the immunological safety profiles of BPC-157, GHK-Cu, and Glow Blend compounds in preclinical models. The key to reliable results lies in disciplined assay design: matched controls, physiologically relevant concentrations, and research-grade peptide sourcing.

Actionable next steps for researchers in 2026:

  • Incorporate CDC assays into standard preclinical safety batteries for any new peptide blend.
  • Validate peptide purity with certificates of analysis before initiating immunotoxicology screening.
  • Run individual component controls alongside full-blend wells for multi-peptide formulations.
  • Document copper-specific cytotoxicity separately when working with GHK-Cu.
  • Cross-reference findings against published complement biology literature before drawing mechanism-of-action conclusions.

Rigorous immunosafety screening at the preclinical stage protects the integrity of downstream data and advances the field toward more translatable research outcomes.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/complement-dependent-cytotoxicity-and-peptide-based-assays-safety-considerations.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-02 13:03:462026-08-02 13:03:46Complement-Dependent Cytotoxicity and Peptide-Based Assays: Safety Considerations for BPC-157, GHK-Cu, and Glow Blend Research
Mesenchymal Stem Cells and Peptide-Based Modulators: How BPC‑157, GHK‑Cu, and Glow Blend Are Used in Regenerative Research Models

Mesenchymal Stem Cells and Peptide-Based Modulators: How BPC‑157, GHK‑Cu, and Glow Blend Are Used in Regenerative Research Models

July 29, 2026/0 Comments/in Uncategorized/by

Fewer than 5% of injured tissue sites in adult mammals achieve full structural restoration without external intervention, a gap that has pushed regenerative biology toward combining cellular and molecular strategies. Mesenchymal stem cells and peptide-based modulators, including BPC‑157, GHK‑Cu, and Glow Blend, have emerged as a paired research focus precisely because peptides can influence the signaling environment that determines whether transplanted or resident MSCs differentiate, survive, and remodel damaged tissue effectively.

Key Takeaways

  • Mesenchymal stem cells (MSCs) are multipotent stromal cells central to injury repair, fibrosis modulation, and wound-healing research.
  • BPC‑157 supports angiogenesis and tendon-fibroblast signaling in preclinical models, making it a frequent co-investigative agent alongside MSC studies.
  • GHK‑Cu is a copper-binding tripeptide studied for its role in collagen remodeling and anti-fibrotic gene expression.
  • Glow Blend combines multiple peptide actives to target overlapping pathways relevant to skin and connective tissue regeneration.
  • Purity and documentation of research compounds are critical variables when designing reproducible MSC-peptide co-culture experiments.

Key Takeaways

Understanding Mesenchymal Stem Cells in Regenerative Research

Mesenchymal stem cells are multipotent stromal progenitors found in bone marrow, adipose tissue, umbilical cord, and several other niches. In research models, they are valued for three core properties:

  1. Multilineage differentiation, capacity to become osteoblasts, chondrocytes, adipocytes, and myofibroblasts under appropriate stimuli.
  2. Paracrine secretion, release of growth factors (VEGF, TGF-beta, HGF) that modulate the local repair microenvironment.
  3. Immunomodulation, suppression of pro-inflammatory T-cell and macrophage activity, relevant in fibrosis and autoimmune injury models.

Because MSC behavior is highly context-dependent, researchers often introduce exogenous signaling molecules, including bioactive peptides, to steer differentiation or amplify paracrine output. This is where the study of mesenchymal stem cells and peptide-based modulators becomes particularly productive as a combined research framework.

"The peptide microenvironment does not replace MSC biology, it shapes the conditions under which that biology expresses itself."

Why Peptide Co-Treatment Matters in MSC Models

Peptides are short amino acid chains that interact with receptors, ion channels, and transcription cofactors at low concentrations. Compared to small-molecule drugs, they tend to exhibit higher target specificity and lower off-target cytotoxicity in cell culture settings, two properties that make them attractive as adjuncts in MSC co-culture and in vivo implantation studies.

BPC‑157, GHK‑Cu, and Glow Blend: Mechanisms in Tissue-Repair Models

BPC‑157, GHK‑Cu, and Glow Blend: Mechanisms in Tissue-Repair Models

BPC‑157 in Injury and Angiogenesis Research

BPC‑157 (Body Protection Compound-157) is a synthetic 15-amino-acid peptide derived from a gastric protein sequence. In preclinical rodent models, it has been studied in the context of:

  • Tendon and ligament repair, upregulation of collagen type I synthesis and fibroblast migration.
  • Angiogenesis, interaction with the VEGFR2 pathway to promote new vessel formation at injury sites.
  • Gut mucosal healing, reduction of inflammatory cytokines in intestinal epithelial models.

When MSCs are seeded into scaffolds pre-treated with BPC‑157 analogs, early data from in vitro wound-scratch assays suggest accelerated cell migration rates. Researchers sourcing compounds for these protocols often consult BPC‑157 core documentation and research guides to verify sequence integrity and purity certificates before designing experiments.

For studies that combine BPC‑157 with another widely researched peptide, the BPC‑157 and TB‑500 combination resource provides useful background on complementary mechanisms in musculoskeletal models.

GHK‑Cu: Copper Peptide Signaling and Collagen Remodeling

GHK‑Cu (glycyl-L-histidyl-L-lysine copper complex) is a naturally occurring tripeptide with high affinity for copper(II) ions. Its research profile in regenerative models includes:

Pathway Observed Effect in Preclinical Models
Collagen synthesis Upregulation of collagen I and III gene expression
MMP regulation Modulation of matrix metalloproteinases to reduce fibrosis
Antioxidant defense Activation of superoxide dismutase pathways
Stem cell niche Potential enhancement of MSC adhesion to extracellular matrix

The anti-fibrotic dimension of GHK‑Cu is especially relevant to MSC research because excessive fibrosis represents a failure mode in many repair models. Researchers looking to source this compound for laboratory use often review GHK‑Cu peptide research sourcing guides to confirm chelation stability and storage requirements.

Glow Blend: Multi-Component Peptide Formulations

Glow Blend represents a category of multi-peptide research formulations designed to engage several regenerative pathways simultaneously. Rather than isolating a single mechanism, blended peptide preparations allow researchers to study synergistic or additive effects on tissue remodeling endpoints. Typical targets in skin and connective tissue models include:

  • Fibroblast proliferation and ECM deposition
  • Melanocyte signaling and pigmentation normalization
  • Keratinocyte migration in wound-closure assays

The Glow Blend product documentation outlines the component profile relevant to researchers designing multi-pathway co-culture experiments.

Applying Mesenchymal Stem Cells and Peptide-Based Modulators in Experimental Protocols

Applying Mesenchymal Stem Cells and Peptide-Based Modulators in Experimental Protocols

Fibrosis and Wound-Healing Model Design

When designing experiments that integrate mesenchymal stem cells and peptide-based modulators, three protocol variables consistently affect data quality:

  1. Peptide concentration windows, Most bioactive peptides show bell-curve dose-response relationships; concentrations that stimulate MSC activity at nanomolar levels may become inhibitory at micromolar levels.
  2. Timing of peptide introduction, Pre-conditioning MSCs with peptides before seeding versus co-administration at implantation produces different differentiation outcomes in fibrosis models.
  3. Compound purity, Contaminated peptide batches introduce confounding variables. Researchers should prioritize suppliers offering third-party mass spectrometry and HPLC certificates. Resources like quality peptide sourcing references help laboratories establish baseline procurement standards.

Complementary Peptide Agents in MSC Research

Beyond BPC‑157, GHK‑Cu, and Glow Blend, several other peptides appear in the broader MSC research literature:

  • TB‑500 (Thymosin Beta-4), studied for actin-cytoskeleton regulation and cell migration; see the TB‑500 research documentation for experimental context.
  • Epithalon, a tetrapeptide investigated in telomere-related aging models alongside MSC longevity assays.
  • GLP-1 analogs, relevant to MSC studies in metabolic tissue contexts; background available in GLP-1 generational research sourcing notes.

Reproducibility and Documentation Standards

Reproducibility in MSC-peptide research depends on rigorous batch documentation. Every compound introduced into a co-culture system should carry:

  • Certificate of Analysis (CoA) with HPLC purity percentage
  • Mass spectrometry confirmation of molecular weight
  • Endotoxin testing results (critical for cell viability assays)
  • Storage and reconstitution records

Researchers working across multiple peptide classes can use consolidated sourcing platforms that provide lab-tested peptide documentation to maintain chain-of-custody records.

Conclusion

The intersection of mesenchymal stem cell biology and peptide-based modulators represents one of the most active areas in preclinical regenerative research as of 2026. BPC‑157 offers a well-characterized angiogenic and fibroblast-signaling profile; GHK‑Cu contributes copper-mediated collagen remodeling and anti-fibrotic gene regulation; and multi-component formulations like Glow Blend allow researchers to probe synergistic pathway interactions in wound-healing and connective tissue models.

Actionable next steps for research teams:

  • Audit current peptide suppliers for third-party purity documentation before initiating MSC co-culture studies.
  • Design dose-response pilot experiments to establish the optimal peptide concentration window for the specific MSC lineage under investigation.
  • Incorporate both single-peptide and blended-peptide conditions in parallel to isolate mechanistic contributions.
  • Review published preclinical literature on BPC‑157 and GHK‑Cu to align experimental endpoints with established assay standards.

Rigorous compound sourcing, careful protocol design, and systematic documentation remain the foundation on which reproducible MSC-peptide research is built.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/mesenchymal-stem-cells-and-peptide-based-modulators-how-bpc-157-ghk-cu-and-glow.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-07-29 13:05:512026-07-29 13:05:51Mesenchymal Stem Cells and Peptide-Based Modulators: How BPC‑157, GHK‑Cu, and Glow Blend Are Used in Regenerative Research Models
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top