Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: 5-ht3 receptor antagonist

Ondansetron in GLP-Class Research: Separating Antiemetic Effects From Gastric-Emptying and Intake Measurements

Ondansetron in GLP-Class Research: Separating Antiemetic Effects From Gastric-Emptying and Intake Measurements

October 7, 2026/0 Comments/in Uncategorized/by

Nearly half of all participants in major semaglutide trials report nausea, yet weight loss outcomes remain robust even in those who never feel sick. That gap between symptom prevalence and therapeutic outcome sits at the heart of a critical methodological challenge: when ondansetron is co-prescribed to manage GLP-1-associated nausea, do researchers risk blurring the very endpoints they are trying to measure?

Ondansetron in GLP-Class Research: Separating Antiemetic Effects From Gastric-Emptying and Intake Measurements is not just a pharmacology question. It is a study-design question that shapes how reliably investigators can attribute changes in food intake, body weight, and gastric motility to the GLP-class agent itself.

Key Takeaways

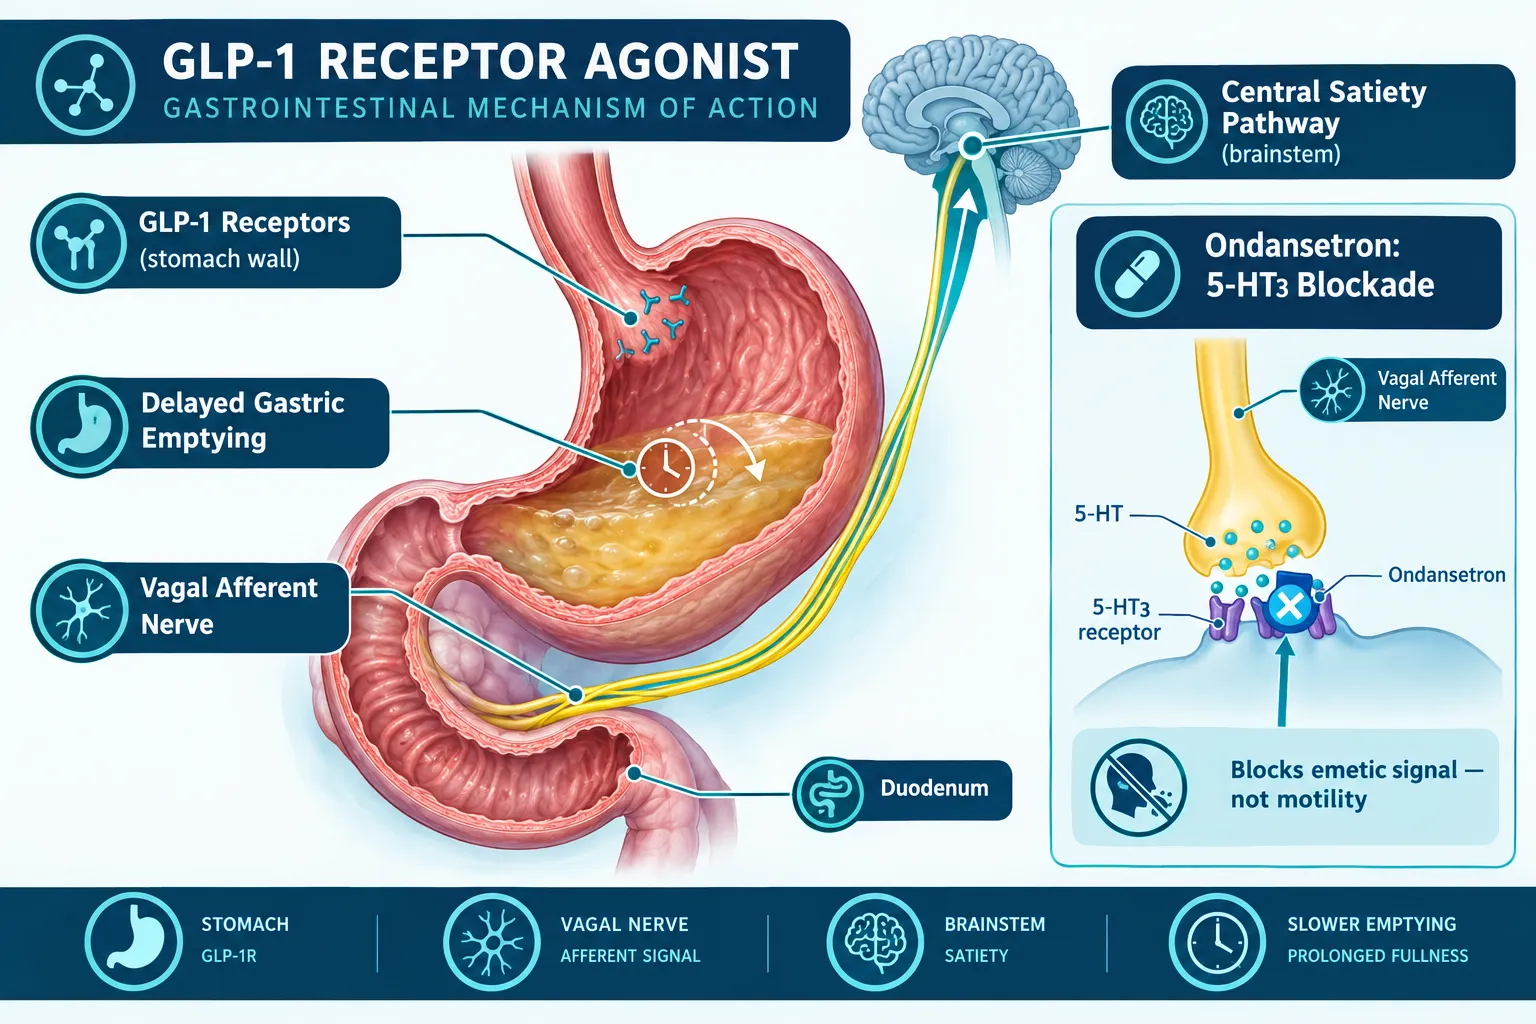
  • GLP-1 receptor agonists slow gastric emptying through peripheral and central mechanisms that are distinct from the pathways that cause nausea.
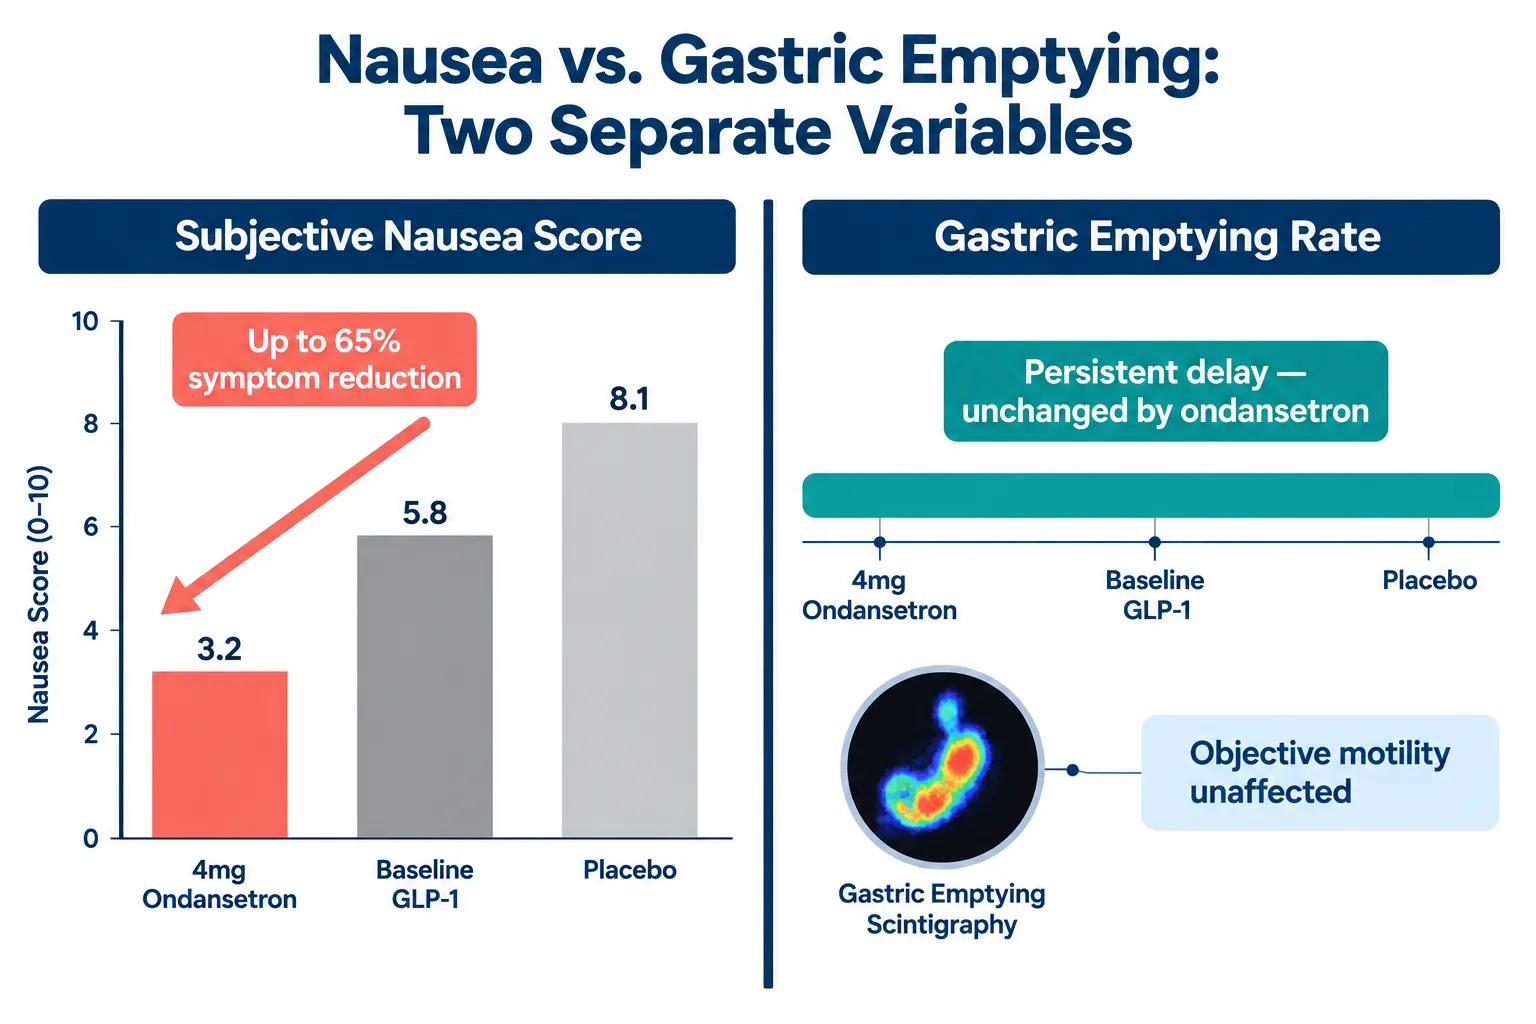
  • Ondansetron reduces subjective nausea by blocking 5-HT3 receptors at vagal afferents but does not meaningfully reverse GLP-1-induced gastric stasis.
  • Nausea rates in GLP-1 trials range from roughly 17% to 44%, yet all dose groups produce substantial weight loss, showing that nausea alone does not drive intake reduction.
  • In research settings, ondansetron should be treated as a time-varying covariate, not a confounder of GLP-1 pharmacodynamics on motility or intake.
  • Objective measures such as acetaminophen absorption curves and gastric scintigraphy remain valid even when ondansetron is co-administered.

How GLP-1 Agents Alter Gastric Emptying and Food Intake

GLP-1 receptor agonists act on receptors located in the stomach wall, the duodenum, and the brainstem. The result is a well-documented slowing of gastric emptying that is independent of whether a patient feels nauseated. Semaglutide, for example, delays gastric emptying by roughly 30-40% in the first weeks of therapy. Even after 12 weeks of chronic use, gastric retention remains 10-33% longer than baseline. Gastric scintigraphy and acetaminophen absorption studies consistently confirm this effect.

This motility change matters for intake because food stays in the stomach longer, prolonging satiety signals and reducing how much a person eats at the next meal. Central appetite pathways reinforce that effect. The practical result is that reduced caloric intake on GLP-class drugs reflects both peripheral gastric slowing and central satiety signaling, not nausea-driven food avoidance.

For researchers exploring the GLP-3 peptide signaling pathway and related incretin biology, understanding this mechanistic separation is foundational before any antiemetic covariate is introduced.
How GLP-1 Agents Alter Gastric Emptying and Food Intake


Nausea Prevalence Does Not Equal Mechanism: What Trial Data Show

The pooled STEP trials reported nausea in approximately 42-44% of participants on semaglutide 2.4 mg, compared with roughly 17% on placebo. Tirzepatide trials in the SURPASS and SURMOUNT programs showed nausea rates in the 17-33% range, with a clear dose-response: 24.6% at the lowest dose, rising to 33.3% at mid-dose, then plateauing near 31% at the highest dose. Critically, all dose groups produced substantial and comparable weight loss.

This pattern supports a key conclusion: delayed gastric emptying and central appetite suppression, not nausea per se, are the primary drivers of reduced intake and weight outcomes on GLP-class drugs.

Trial Program Agent Nausea Rate Weight Outcome
STEP (pooled) Semaglutide 2.4 mg ~42-44% Substantial across all groups
SURMOUNT-1 Tirzepatide 5 mg ~24.6% Significant
SURMOUNT-1 Tirzepatide 10 mg ~33.3% Significant
SURMOUNT-1 Tirzepatide 15 mg ~31.0% Significant

Nausea is a real side effect, but it is a parallel signal, not the causal pathway. Researchers reviewing GLP-1 third-generation agents should keep this distinction in mind when designing endpoints.
Nausea Prevalence Does Not Equal Mechanism: What Trial Data Show


Ondansetron in GLP-Class Research: Separating Antiemetic Effects From Gastric-Emptying and Intake Measurements in Practice

Ondansetron is now the most commonly prescribed antiemetic for GLP-1-associated nausea in clinical practice, typically at 4-8 mg as needed. It is used in roughly 15-20% of patients during early titration or after dose escalations. Expert reviews consistently frame it as a short-term tolerability tool, not a modifier of the pharmacologic effects on gastric emptying or weight.

Mechanistically, the separation is clean:

  • GLP-1 agents slow gastric emptying via peripheral GLP-1 receptors and central satiety circuits.
  • Ondansetron blocks 5-HT3 receptors at vagal afferents and in the brainstem chemoreceptor trigger zone.
  • These are anatomically and pharmacologically distinct targets.

Clinical data back this up. Small retrospective analyses report roughly 40-65% reductions in nausea scores with 4-8 mg ondansetron in GLP-1-treated patients, yet objective gastric-emptying measures remain persistently delayed. Case reports of semaglutide-induced gastroparesis managed with intravenous ondansetron describe improved symptom tolerance but continued motility impairment on imaging.

Preclinical work adds nuance: in a musk shrew model, exendin-4-induced emesis was not blocked by ondansetron, suggesting that GLP-1-triggered vomiting does not rely exclusively on 5-HT3 pathways. Human patients still benefit clinically, but this finding reinforces the conceptual gap between GLP-1 emetic circuitry and the peripheral motility changes that drive intake reduction.

"Ondansetron addresses the symptom without counteracting the therapeutic mechanism", a principle that should anchor how researchers handle antiemetic co-exposure in GLP-class studies.

For broader context on how peptide mechanisms interact across systems, the Peptides 101 resource for research-use buyers provides useful background on receptor-level distinctions.


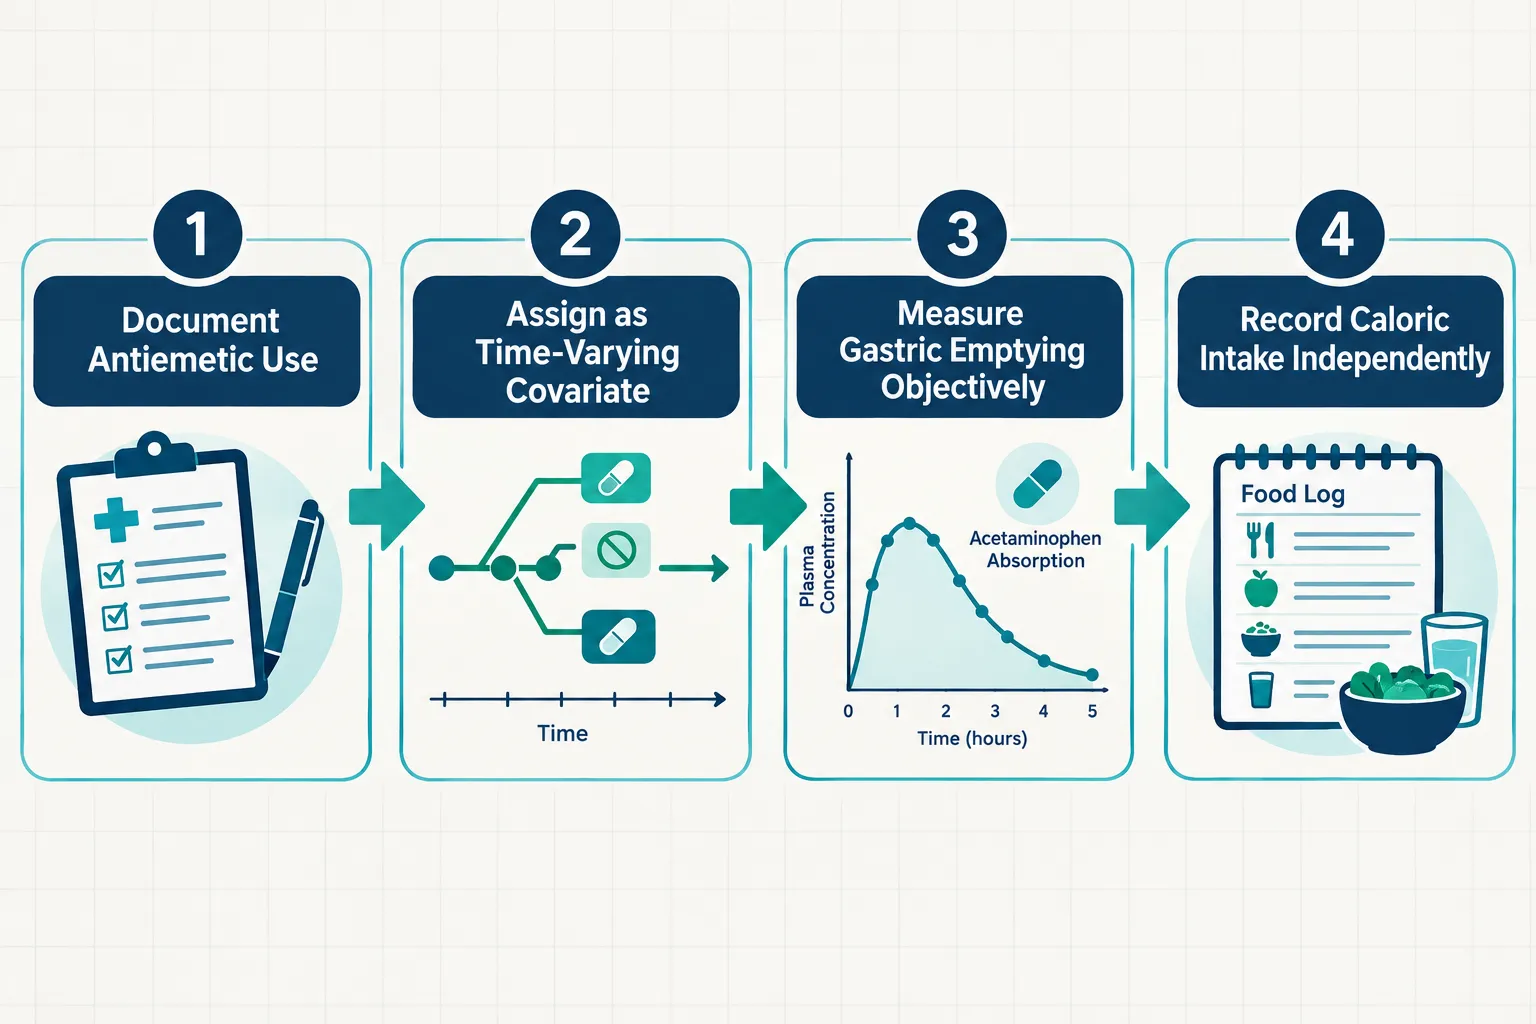
Research Design: Treating Ondansetron as a Covariate, Not a Confounder

Ondansetron in GLP-Class Research: Separating Antiemetic Effects From Gastric-Emptying and Intake Measurements demands a clear methodological response. As of 2026, no large randomized trial has tested ondansetron for GLP-1 nausea with prespecified gastric-emptying or caloric intake endpoints. Most current evidence comes from retrospective analyses and practice guidelines. That gap creates practical obligations for investigators.

Recommended research-design steps:

  1. Document antiemetic use prospectively, record dose, timing, and duration for every participant.
  2. Assign ondansetron as a time-varying covariate in statistical models, not a fixed group variable.
  3. Use objective gastric-emptying measures, acetaminophen absorption curves or scintigraphy, rather than relying on self-reported fullness.
  4. Record caloric intake independently using validated dietary recall or direct observation, not nausea-behavior proxies.
  5. Monitor GI motility endpoints separately, ondansetron can worsen constipation in patients already prone to bowel slowing on GLP-1 agents, making stool frequency a necessary secondary endpoint.

That last point deserves emphasis. A 2026 clinical commentary specifically cautions that ondansetron may exacerbate GLP-1-related constipation, recommending non-pharmacologic alternatives such as hydration, fiber, and ginger when bowel slowing threatens adherence. For any study tracking broader GI motility, ondansetron use becomes a meaningful covariate, not just for nausea, but for the full motility picture.

Researchers also interested in how peptide combinations affect tolerability profiles can review data on cagrilintide and retatrutide as examples of multi-mechanism agents where covariate management becomes even more complex.

No clinically significant pharmacokinetic interaction between ondansetron and semaglutide or other major GLP-1 agents has been identified through mid-2026, and weight-loss or glucose-lowering efficacy appears unchanged when ondansetron is co-prescribed. This strengthens the case for treating it as a symptom-control covariate rather than a variable that alters GLP-1 pharmacodynamics.
Research Design: Treating Ondansetron as a Covariate, Not a Confounder


Looking Ahead: What Future Studies Need to Resolve

As of 2026, no GLP-1-specific antiemetic has reached phase 3 trials. Growing clinical use of GLP-class agents, including newer agents discussed in resources on GLP-1 reta formulations, is expected to drive development of nausea-targeted adjuncts that modulate GLP-1 emetic pathways without touching gastric emptying or appetite suppression.

Future trials are anticipated to randomize participants to antiemetic versus placebo arms while measuring gastric-emptying times, caloric intake, and weight outcomes in parallel. That design would finally provide definitive data on whether ondansetron or its successors can be used in GLP-class research without confounding mechanistic endpoints.

Until then, the available evidence strongly supports a working framework: ondansetron modifies symptom perception, not gastric-emptying kinetics. Researchers who document its use carefully and apply appropriate statistical controls can preserve the integrity of their motility and intake measurements.


Conclusion

The core finding is straightforward: ondansetron reduces nausea through 5-HT3 receptor blockade at vagal afferents, while GLP-1 agents slow gastric emptying through a separate set of peripheral and central receptors. These mechanisms do not meaningfully overlap, and current evidence confirms that gastric stasis persists even when nausea is well controlled.

Actionable next steps for researchers and clinicians in 2026:

  • Pre-register antiemetic use as a time-varying covariate in any GLP-class study that includes gastric-emptying or caloric intake endpoints.
  • Use objective motility measures, not patient-reported nausea, as primary evidence of GLP-1 pharmacodynamic activity.
  • Track constipation and broader GI motility separately, since ondansetron can compound bowel slowing already induced by GLP-1 agents.
  • Advocate for randomized antiemetic sub-studies embedded within larger GLP-class trials to close the current evidence gap.

Separating what ondansetron does from what GLP-class agents do is not merely an academic exercise. It is the methodological foundation that makes gastric-emptying and intake data trustworthy, and that makes the science of GLP-class research credible.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/ondansetron-in-glp-class-research-separating-antiemetic-effects-from-gastric-emp.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-07 13:04:192026-10-07 13:04:19Ondansetron in GLP-Class Research: Separating Antiemetic Effects From Gastric-Emptying and Intake Measurements
Evaluating Antiemetic Protocols in Incretin Research: Ondansetron Mechanisms During GLP-3 Retatrutide Administration

Evaluating Antiemetic Protocols in Incretin Research: Ondansetron Mechanisms During GLP-3 Retatrutide Administration

September 16, 2026/0 Comments/in Uncategorized/by

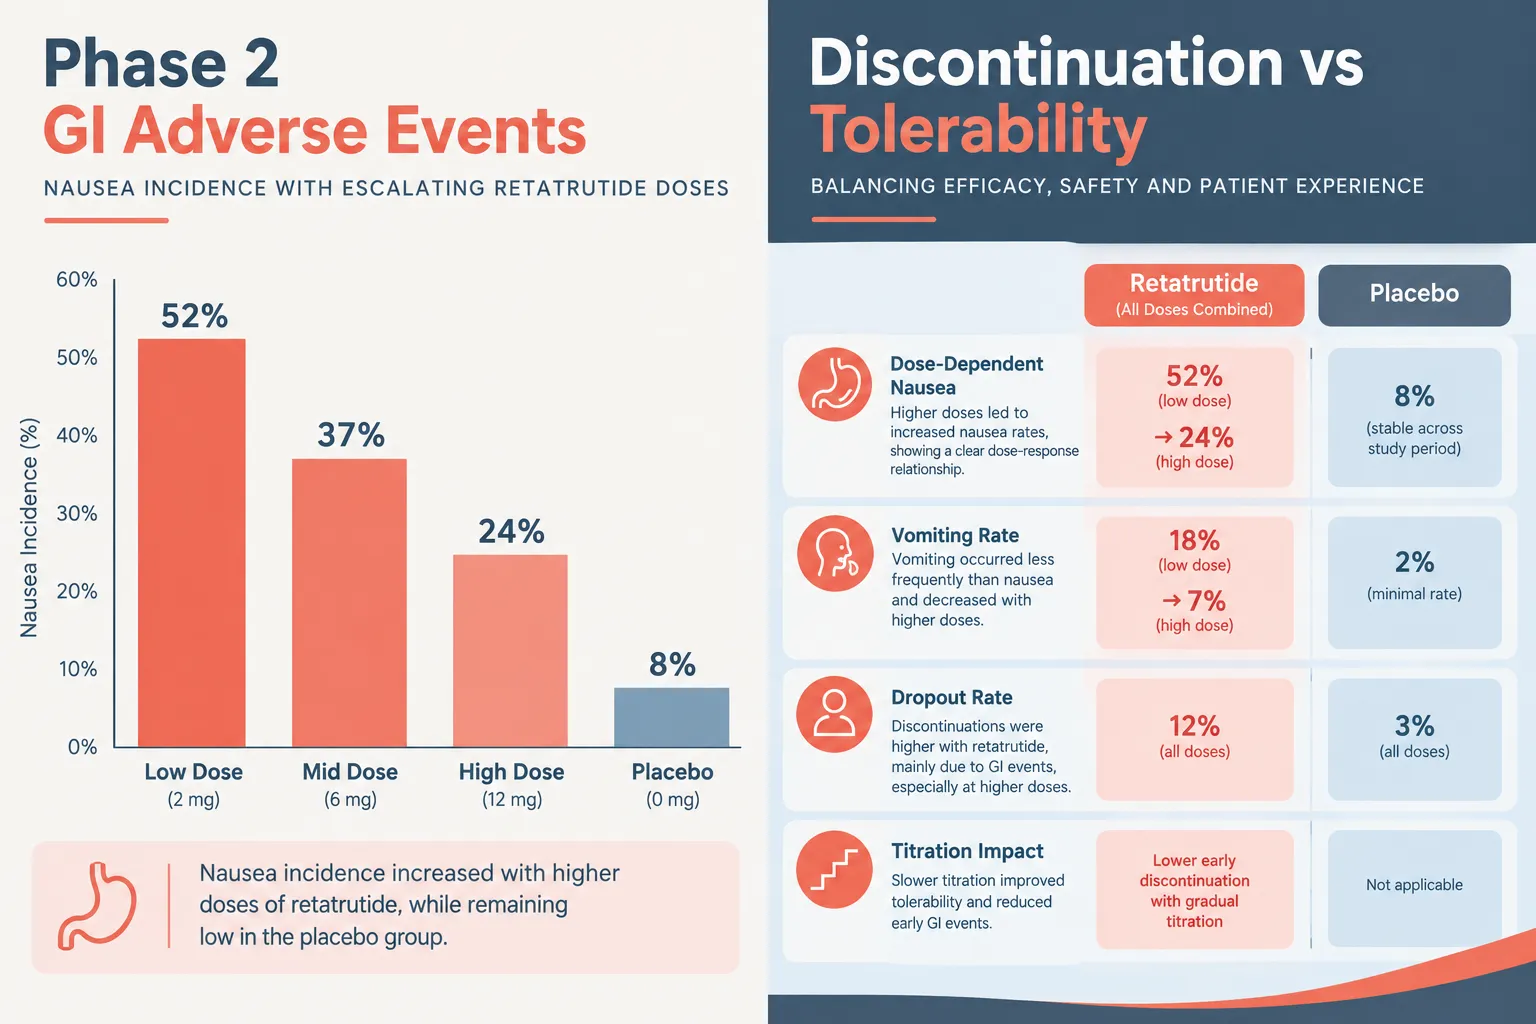
Nausea affects more than 40% of participants in high-dose retatrutide arms during Phase 2 trials, a rate that places gastrointestinal (GI) tolerability at the center of every research design decision. As investigators push toward maximizing metabolic efficacy with this potent multi-incretin agonist, evaluating antiemetic protocols in incretin research, including the role of ondansetron mechanisms during GLP-3 retatrutide administration, has become a critical and underexplored frontier.

Key Takeaways

  • Retatrutide (LY3437943) is a triple incretin agonist targeting GLP-1, GIP, and glucagon receptors, producing dose-dependent GI side effects.
  • Nausea and vomiting rates in high-dose retatrutide cohorts are among the highest observed in the incretin drug class.
  • Ondansetron, a selective 5-HT3 receptor antagonist, targets both central and peripheral serotonin pathways implicated in incretin-induced emesis.
  • No formal ondansetron-specific antiemetic protocols have been published for retatrutide trials as of 2026; current management relies on dose titration.
  • Structured antiemetic research protocols represent a significant opportunity to improve participant retention and trial outcomes.

Understanding Retatrutide and Its GI Burden

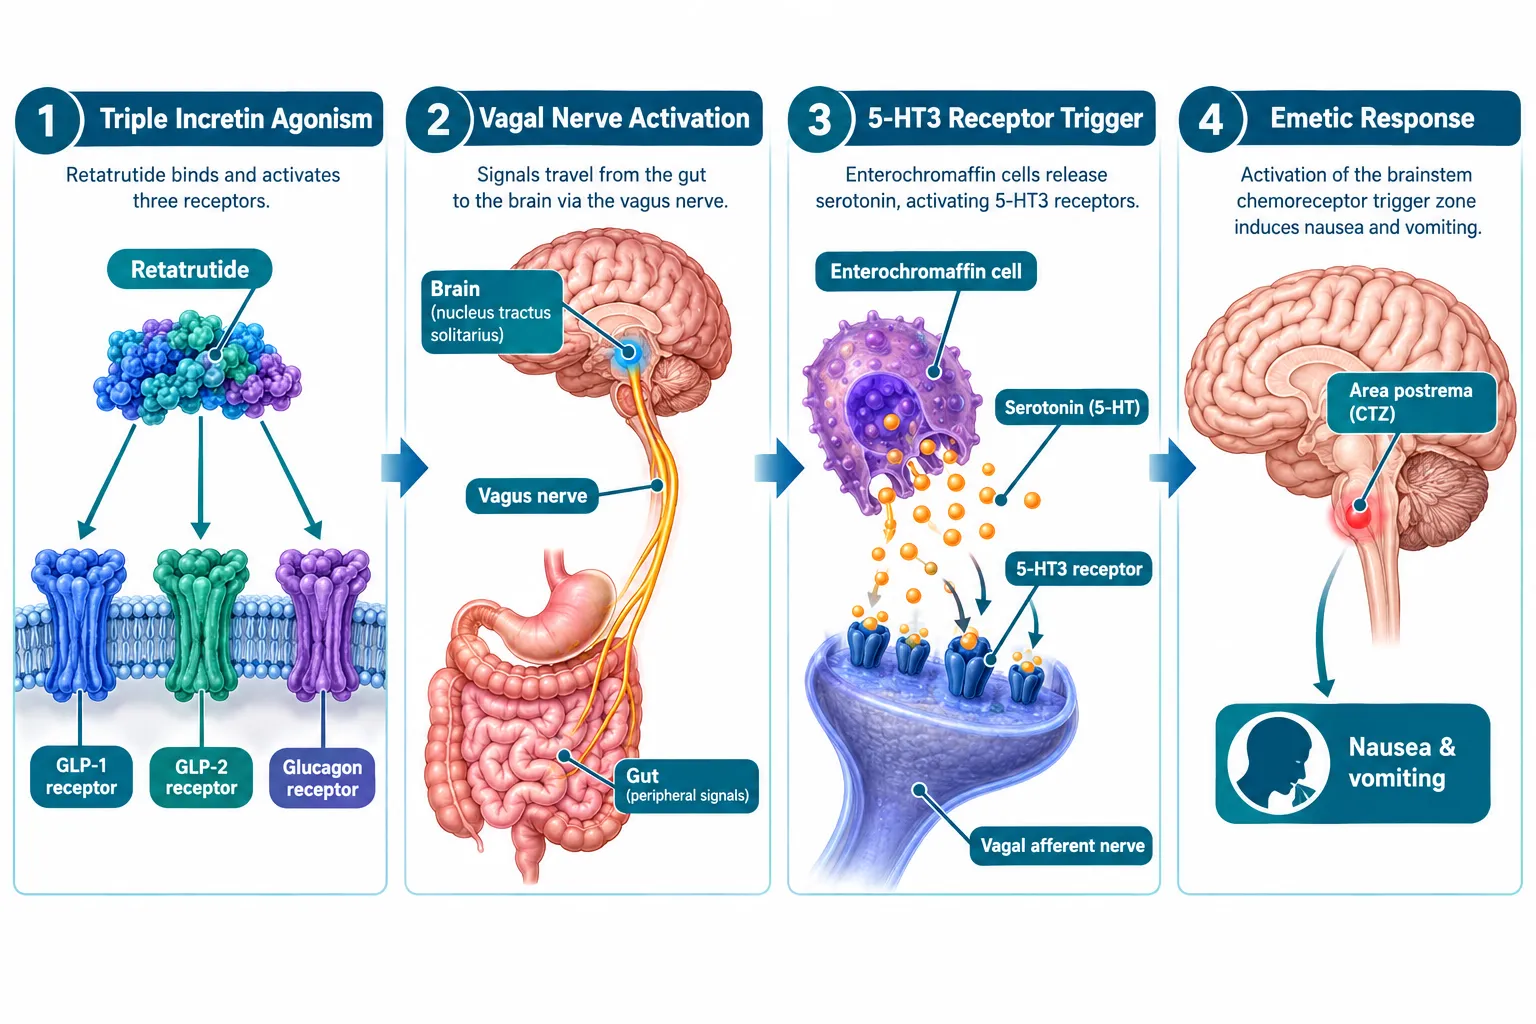
Retatrutide, developed under the designation LY3437943, is a single-molecule triple agonist that simultaneously activates glucagon-like peptide-1 (GLP-1), glucose-dependent insulinotropic polypeptide (GIP), and glucagon receptors. This multi-receptor engagement drives impressive reductions in body weight and improvements in metabolic markers, but it also amplifies the GI signaling cascades that produce nausea, vomiting, and early satiety.

Understanding Retatrutide and Its GI Burden

In Phase 2 dose-ranging studies, nausea incidence climbed steeply with dose escalation. At the highest tested doses, nausea was reported in over 40% of participants, with vomiting affecting a substantial subset. These figures exceed rates typically seen with GLP-1 receptor agonists alone, reflecting the additive GI burden of triple incretin engagement. Researchers exploring retatrutide clinical trials have consistently flagged GI tolerability as the primary dose-limiting factor.

The timing of adverse events follows a predictable pattern: symptoms peak during dose escalation phases and tend to attenuate as participants acclimate. However, the severity during escalation is sufficient to drive meaningful discontinuation rates, which in turn compromises the statistical integrity of long-term efficacy data.

Key GI adverse event characteristics in retatrutide research:

Adverse Event Onset Timing Dose Relationship Primary Mechanism
Nausea Early escalation Dose-dependent GLP-1 vagal activation, 5-HT3 signaling
Vomiting Concurrent with nausea Dose-dependent Central emetic pathway activation
Early satiety Persistent Moderate Gastric motility slowing
Discontinuation Peak escalation High-dose cohorts Cumulative GI burden

The 5-HT3 Pathway: Why Ondansetron Is Relevant

The central question in evaluating antiemetic protocols in incretin research involving ondansetron mechanisms during GLP-3 retatrutide administration lies in the biology of serotonin signaling. GLP-1 receptor activation in the gut stimulates enterochromaffin cells to release serotonin (5-hydroxytryptamine, or 5-HT). This serotonin binds to 5-HT3 receptors on vagal afferent neurons, transmitting an emetic signal to the brainstem's chemoreceptor trigger zone (CTZ) and the nucleus tractus solitarius (NTS).

Ondansetron is a highly selective 5-HT3 receptor antagonist. By blocking these receptors at both peripheral (gut-vagal) and central (CTZ) sites, it interrupts the serotonin-mediated emetic cascade before it reaches full activation. This dual-site mechanism makes it mechanistically well-suited to incretin-induced nausea, which originates peripherally but is amplified centrally.

Ondansetron's selectivity for the 5-HT3 receptor makes it a pharmacologically logical candidate for managing the serotonin-driven nausea associated with potent multi-incretin agonists like retatrutide.

The triple-agonist profile of retatrutide likely intensifies this cascade compared to single-receptor agents. Glucagon receptor activation adds motility effects, while GIP receptor engagement may further modulate gut hormone signaling. The cumulative result is a more complex emetic environment than ondansetron was originally designed to address, but one in which 5-HT3 blockade still targets a primary mechanistic node.

The 5-HT3 Pathway: Why Ondansetron Is Relevant

Current Protocol Gaps and the Path Forward

Despite the clear mechanistic rationale, a critical evidence gap exists. As of 2026, no published retatrutide trial has incorporated a formal, pre-specified ondansetron antiemetic protocol. Current management strategies rely almost entirely on conservative dose titration schedules and general supportive care guidance. Participants are typically advised to eat smaller meals, avoid high-fat foods, and wait out the escalation period.

This approach has limitations. Dose titration slows the research timeline and may prevent some participants from reaching target doses. Supportive care guidance is inconsistently applied across sites. And without standardized antiemetic co-administration data, researchers cannot determine whether pharmacological intervention would meaningfully reduce discontinuation rates.

For those sourcing research-grade compounds, the GLP-3 Reta 10mg research peptide represents one avenue for preclinical investigation, and resources on buying GLP-3 Reta for research purposes are available for qualified investigators. Similarly, researchers exploring related peptide tolerability profiles may find value in SS-31 mitochondrial research themes as a parallel framework for understanding cellular stress responses during peptide administration.

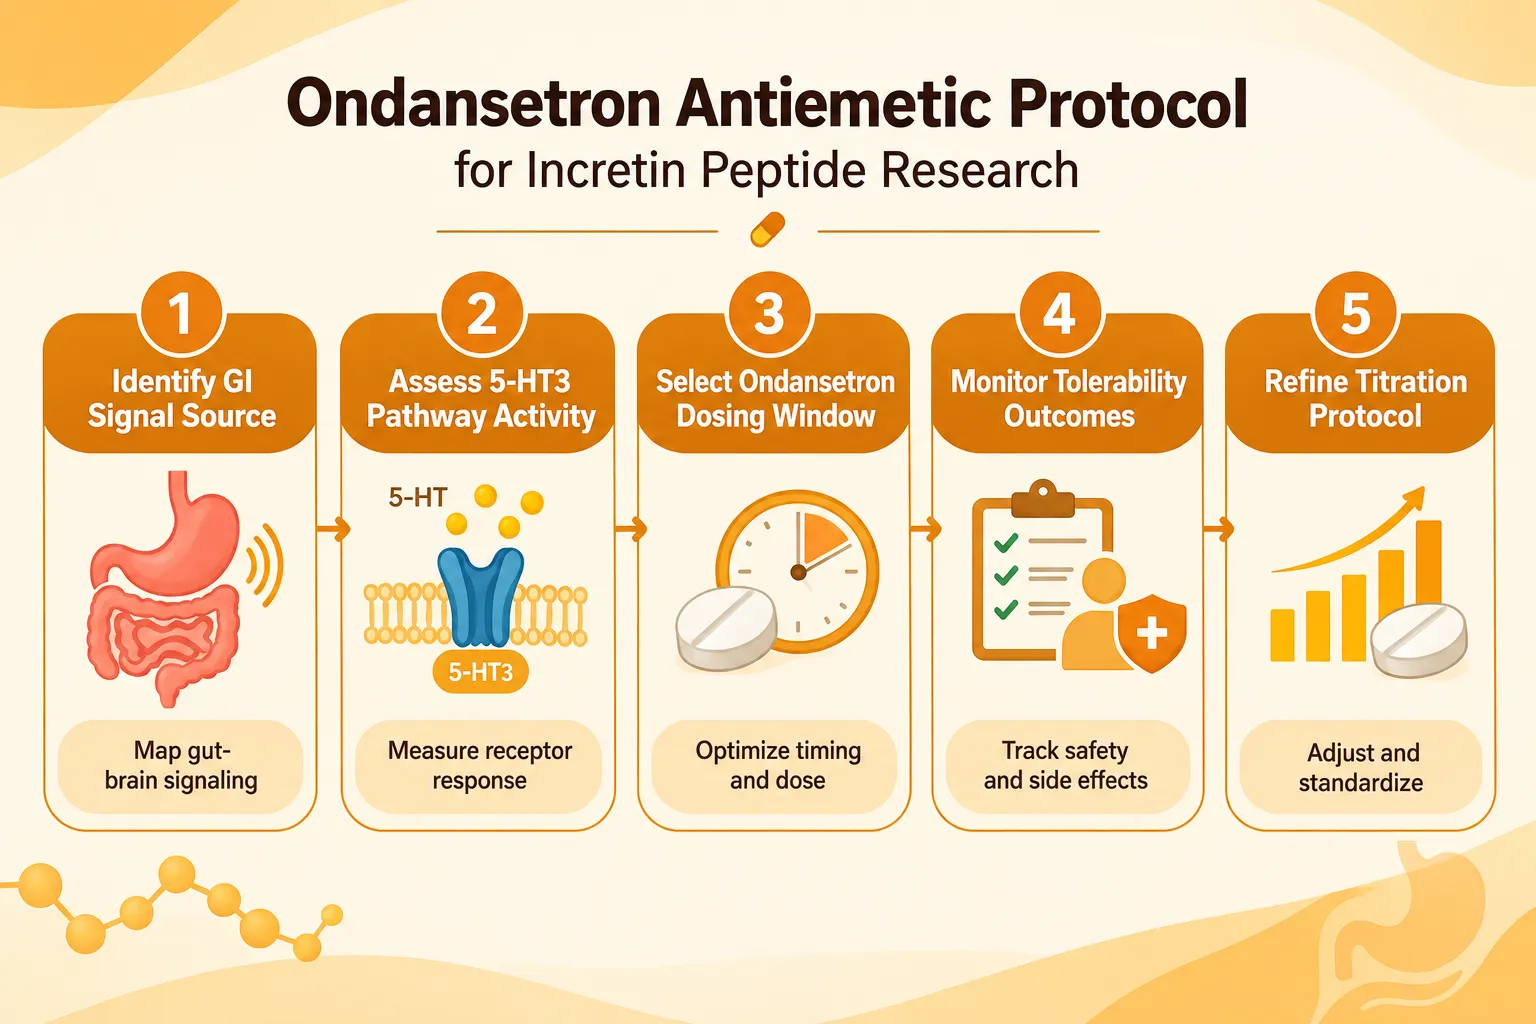
Proposed elements of a structured ondansetron protocol for incretin research:

  • Timing: Administer ondansetron 30-60 minutes prior to retatrutide injection during dose escalation phases.
  • Dosing window: Standard antiemetic dosing (4-8 mg oral) aligned with escalation schedules.
  • Duration: Protocol-defined use limited to escalation periods, with reassessment at maintenance doses.
  • Outcome tracking: Standardized nausea severity scales (e.g., FLIE, VAS) recorded at consistent intervals.
  • Discontinuation monitoring: Compare dropout rates between antiemetic-supported and standard-care arms.

Researchers interested in buying retatrutide peptide for preclinical work should also consider how antiemetic co-administration variables will be documented in their protocols. Parallel work in Semax research demonstrates how neuropeptide tolerability frameworks can inform protocol design across compound classes.

Current Protocol Gaps and the Path Forward

The risk-benefit calculus here is straightforward: if ondansetron reduces early discontinuation by even a modest percentage, the downstream gains in data completeness and statistical power justify its inclusion in trial designs. The question is no longer whether to study this intervention, but how to structure that study rigorously.

Conclusion

Evaluating antiemetic protocols in incretin research, specifically ondansetron mechanisms during GLP-3 retatrutide administration, is no longer a secondary concern. It is a prerequisite for generating reliable, high-quality data from one of the most promising metabolic research compounds in development.

Actionable next steps for research teams:

  1. Incorporate pre-specified 5-HT3 antagonist co-administration arms into upcoming retatrutide Phase 3 sub-studies.
  2. Standardize nausea outcome measurement tools across all sites to enable meaningful cross-trial comparison.
  3. Publish tolerability sub-analyses that isolate the effect of antiemetic support on dose completion rates.
  4. Engage regulatory bodies early on antiemetic co-administration as a protocol variable, not a post-hoc intervention.

The serotonin pathway is not a minor footnote in incretin pharmacology, it is a central driver of the GI burden that limits these compounds' research potential. Addressing it with the same rigor applied to efficacy endpoints will define the next generation of incretin trial design.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/evaluating-antiemetic-protocols-in-incretin-research-ondansetron-mechanisms-duri.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-16 13:06:492026-09-16 13:06:49Evaluating Antiemetic Protocols in Incretin Research: Ondansetron Mechanisms During GLP-3 Retatrutide Administration
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top