Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: cardiometabolic research

MOTS‑c and 5‑Amino‑1MQ Beyond Adiposity: How Labs Are Starting to Explore Cognitive, Cardiometabolic, and Longevity Endpoints

MOTS‑c and 5‑Amino‑1MQ Beyond Adiposity: How Labs Are Starting to Explore Cognitive, Cardiometabolic, and Longevity Endpoints

August 29, 2026/0 Comments/in Uncategorized/by

Mitochondria do more than generate ATP, they secrete signaling molecules that influence the brain, heart, and aging clock simultaneously. That biological reality is driving a new wave of research interest in two compounds: MOTS‑c, a mitochondria-derived peptide, and 5‑Amino‑1MQ (5A1MQ), a small-molecule NNMT inhibitor. Most public discussion has centered on their anti-obesity effects, but the frontier of MOTS‑c and 5‑Amino‑1MQ beyond adiposity, how labs are starting to explore cognitive, cardiometabolic, and longevity endpoints, is where the most scientifically interesting questions now live.

Key Takeaways

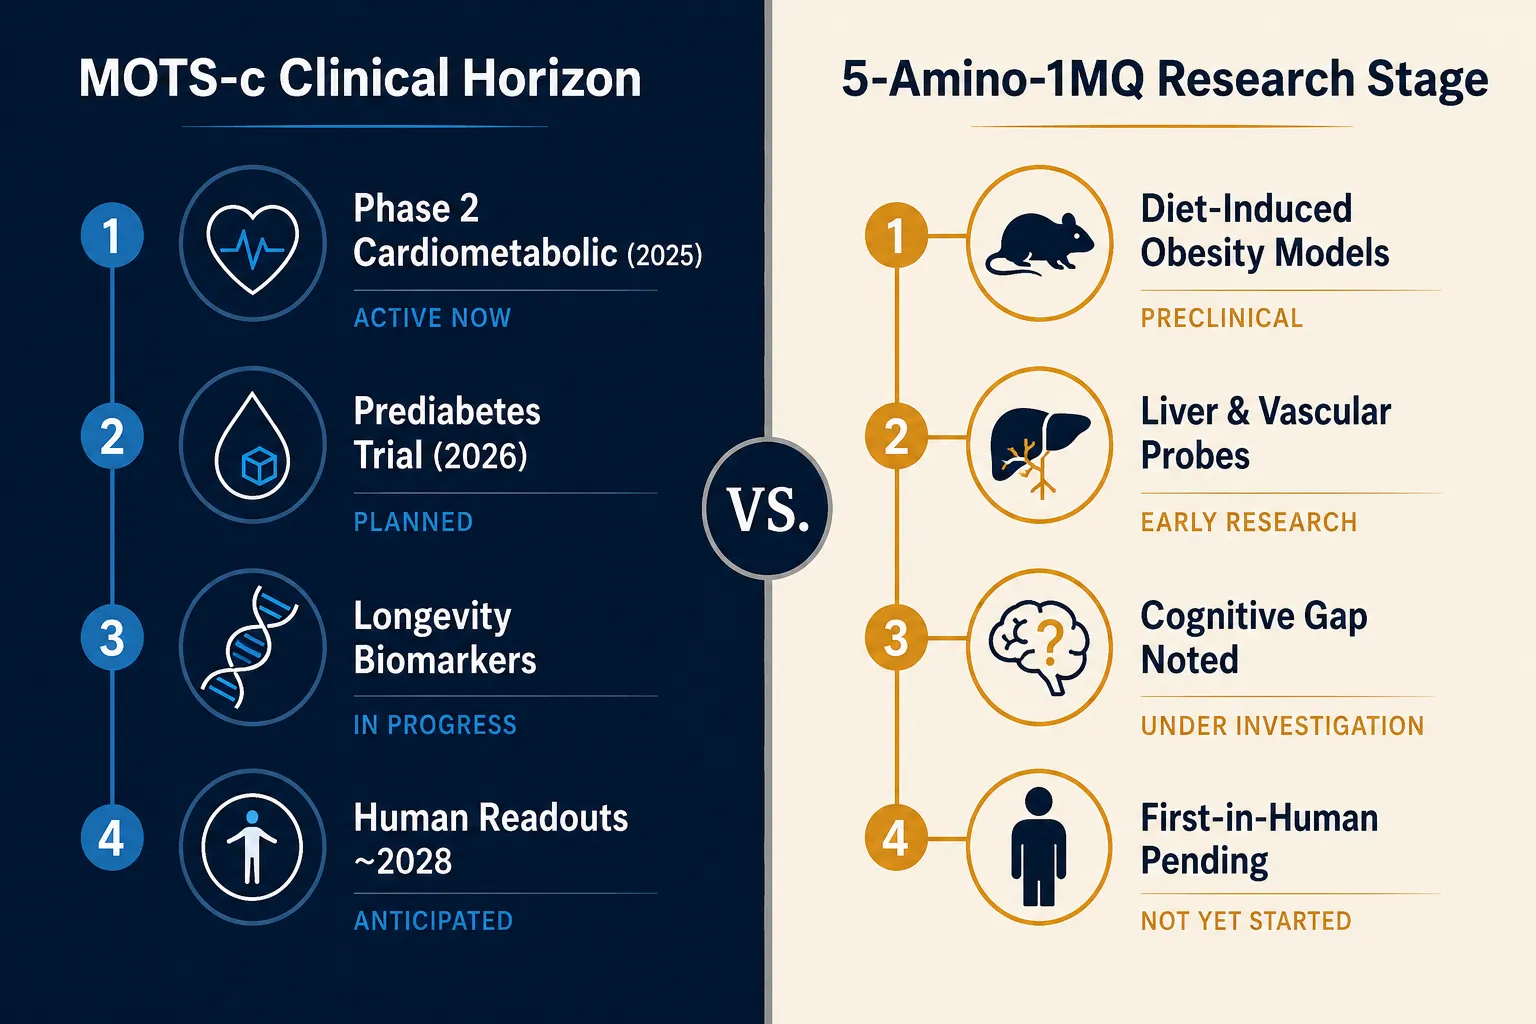
  • MOTS‑c completed its first Phase 2 cardiometabolic trial in 2025, showing modest but significant benefits; a 2026 prediabetes trial is ongoing.
  • Cognitive endpoints for MOTS‑c remain preclinical and contested, with blood-brain barrier penetration still unresolved.
  • 5‑Amino‑1MQ has robust preclinical metabolic data but has not yet entered human trials for any indication.
  • Both compounds are framed as potential longevity agents, but human evidence for aging biomarkers is largely observational.
  • Evidence lags significantly behind marketing narratives at longevity clinics, researchers urge caution.

What MOTS‑c and 5‑Amino‑1MQ Actually Do
What MOTS‑c and 5‑Amino‑1MQ Actually Do

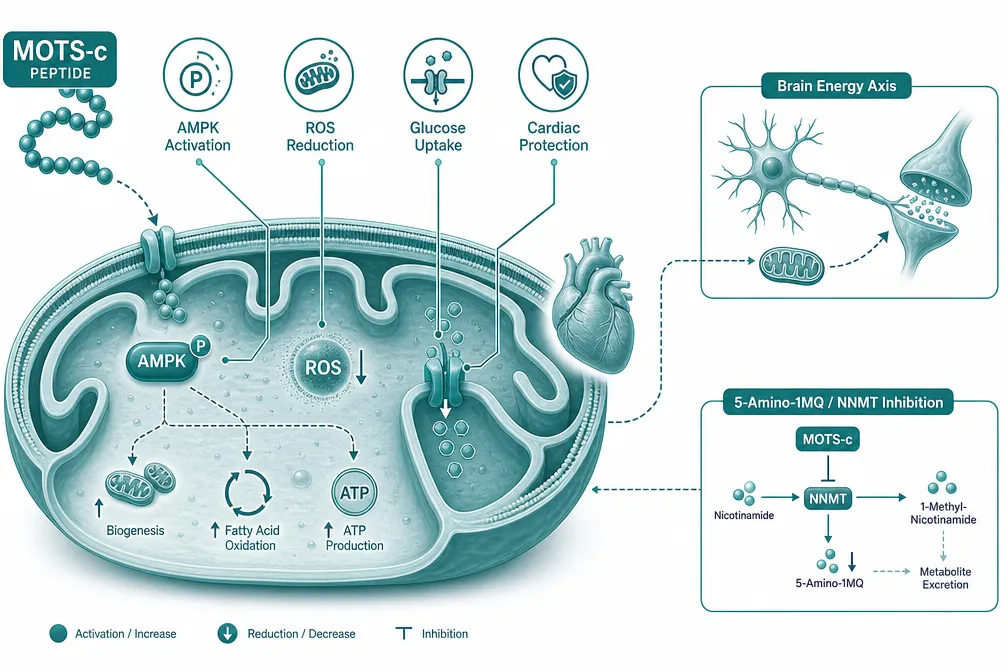
MOTS‑c is a 16-amino-acid peptide encoded in mitochondrial DNA. It activates AMPK, reduces reactive oxygen species, and improves glucose uptake in skeletal muscle. Researchers increasingly describe it as a "mitochondrial hormone", a circulating signal that coordinates whole-body energy sensing rather than acting locally. Levels decline with age and rise with exercise, which has made it a subject of longevity biology interest.

5‑Amino‑1MQ works through a different mechanism. It inhibits nicotinamide N-methyltransferase (NNMT), an enzyme overexpressed in adipose tissue during obesity. By blocking NNMT, 5A1MQ raises NAD+ precursor availability and shifts cellular metabolism toward fat oxidation. In diet-induced obese mouse models, the compound produced robust reductions in body weight and fat mass without significant toxicity signals.

Both compounds intersect at a common node: mitochondrial efficiency and metabolic reprogramming. That shared biology is why researchers studying one often look at the other, and why SS-31 and MOTS-c are frequently paired in mitochondria-focused research stacks. For researchers sourcing verified material, buying MOTS-c peptide from a lab-tested supplier is a standard first step before designing any preclinical protocol.

Cardiometabolic and Cognitive Frontiers: Where the Data Actually Stands
Cardiometabolic and Cognitive Frontiers: Where the Data Actually Stands

Cardiometabolic Evidence

The most concrete human data belongs to MOTS‑c. A Phase 2 trial completed in 2025 reported modest but statistically significant cardiometabolic improvements, including insulin sensitivity and lipid markers, in its target population. The word "modest" matters here; expert commentary has been careful not to overstate the signal. A follow-on Phase 2a trial launched in 2026 specifically targets prediabetes with broader mechanistic endpoints, including vascular biomarkers and inflammatory markers alongside glycemic outcomes. Definitive cardiometabolic readouts are not expected before approximately 2028.

Preclinical cardiac data are more striking. MOTS‑c appears to protect the diabetic heart by preserving mitochondrial membrane integrity and reducing oxidative stress in cardiomyocytes. This is consistent with the broader research theme explored in SS-31 mitochondrial research, where mitochondria-targeted peptides show cardioprotective properties across multiple model systems.

For 5‑Amino‑1MQ, cardiometabolic work is earlier-stage. Animal studies probing liver fat accumulation and vascular inflammation are underway, but no human data exist. The compound's NNMT inhibition mechanism theoretically reduces metabolic inflammation, a driver of cardiovascular risk, but that pathway has not been validated in clinical populations. Researchers interested in the metabolic axis may also want to review GLP-3 retatrutide and the future of metabolic research for context on how the broader field is evolving.

Cognitive Endpoints

This is where the gap between marketing and science is widest. MOTS‑c's cognitive potential is entirely preclinical, and the evidence is mixed. Some rodent studies suggest it may reduce neuroinflammation and support brain energy metabolism, plausible given that neurons are among the most mitochondria-dense cells in the body. However, blood-brain barrier (BBB) penetration remains unresolved. Peripheral injection does not guarantee central nervous system exposure, and conflicting claims about MOTS‑c's BBB permeability circulate widely in longevity clinic marketing without adequate support.

For 5‑Amino‑1MQ, cognitive endpoints are essentially absent from the published literature. No preclinical models have systematically tested its effects on memory, neuroinflammation, or synaptic function. Researchers exploring peptide cognitive endpoints will find far more developed data in neuropeptide categories like Semax and Selank, covered in depth in the comparative research on neurogenesis and synaptic plasticity.

Key distinction: MOTS‑c has a plausible cognitive mechanism but unconfirmed CNS access. 5‑Amino‑1MQ has no meaningful cognitive dataset at all.

Longevity Endpoints and What Researchers Should Watch
Longevity Endpoints and What Researchers Should Watch

The longevity framing around MOTS‑c is scientifically grounded in one important respect: circulating MOTS‑c levels in humans correlate inversely with age and positively with physical fitness. Centenarian studies have found elevated MOTS‑c relative to age-matched controls. These are observational associations, not intervention evidence, but they anchor the hypothesis that restoring youthful MOTS‑c levels could slow aging-related decline.

Aging biomarker endpoints being considered for future trials include:

  • Telomere length and telomerase activity, connected to mitochondrial health signals
  • Inflammatory cytokines (IL-6, TNF-alpha), modulated by AMPK activation
  • Epigenetic clocks, increasingly used as surrogate aging endpoints in peptide trials
  • Vascular stiffness measures, relevant to both cardiometabolic and longevity outcomes

For 5‑Amino‑1MQ, longevity research is speculative. NAD+ pathway involvement is the primary theoretical link, since NNMT inhibition increases NAD+ precursor flux, a mechanism shared with well-studied longevity compounds. But without first-in-human data, longevity claims remain hypothesis-generating rather than evidence-based.

Researchers building aging-focused protocols may find relevant context in aging support research categories and in the hTERT-related work tagged under hTERT longevity research.

Research Caution: Authoritative reviews consistently note that both MOTS‑c and 5‑Amino‑1MQ carry no approved human indications as of 2026. Off-label use through longevity clinics outpaces the available evidence by a significant margin.

Conclusion

The research trajectory for MOTS‑c and 5‑Amino‑1MQ beyond adiposity, spanning cognitive, cardiometabolic, and longevity endpoints, is genuinely promising but unevenly developed. MOTS‑c has crossed into human trials with modest early signals and a plausible mechanistic story for vascular and brain energy benefits. 5‑Amino‑1MQ remains a preclinical compound with strong metabolic data and an untested cognitive profile.

Actionable next steps for researchers and clinicians:

  1. Track the 2026 MOTS‑c prediabetes Phase 2a trial for mechanistic endpoint data, these results will clarify whether cardiometabolic benefits extend beyond glycemic control.
  2. Treat cognitive claims for both compounds as hypothesis-generating until BBB penetration and CNS efficacy are confirmed in controlled studies.
  3. Use longevity biomarker panels (epigenetic clocks, vascular stiffness, inflammatory markers) as outcome measures in any preclinical stack design, not just body composition.
  4. Apply strict sourcing standards; lab-tested peptides with documented purity are non-negotiable for reproducible research.
  5. Revisit the evidence base in 2028 when more definitive cardiometabolic readouts from MOTS‑c trials are expected to be available.

The science is moving, but it is moving at the pace of rigorous trials, not marketing timelines.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/mots-c-and-5-amino-1mq-beyond-adiposity-how-labs-are-starting-to-explore-cogniti.webp 672 1008 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-29 13:10:582026-08-29 13:10:58MOTS‑c and 5‑Amino‑1MQ Beyond Adiposity: How Labs Are Starting to Explore Cognitive, Cardiometabolic, and Longevity Endpoints
GLP Peptides vs Traditional Small‑Molecule Metabolic Drugs: Where GLP‑3 Retatrutide, GLP‑2‑T, and Tesofensine Fit in Cardiometabolic Research

GLP Peptides vs Traditional Small‑Molecule Metabolic Drugs: Where GLP‑3 Retatrutide, GLP‑2‑T, and Tesofensine Fit in Cardiometabolic Research

August 28, 2026/0 Comments/in Uncategorized/by

Cardiovascular disease and metabolic dysfunction together account for more than 17 million deaths annually worldwide, yet the dominant drugs managing these conditions, including atorvastatin, amlodipine, and prednisone, were designed decades before researchers understood the gut-hormone axis. The emergence of GLP peptides vs traditional small-molecule metabolic drugs as a central debate in 2026 cardiometabolic research reflects a genuine mechanistic shift, not just a trend. Understanding where GLP-3 retatrutide, GLP-2-T, and tesofensine fit in cardiometabolic research requires mapping each agent against the biological pathways that older drug classes were never built to target.

Key Takeaways

  • GLP peptides operate through receptor-level hormonal signaling, while traditional small molecules like statins and calcium channel blockers inhibit specific enzymes or ion channels.
  • Retatrutide is a triple agonist targeting GLP-1, GIP, and glucagon receptors simultaneously, producing weight loss of up to approximately 30% in phase 2 data.
  • GLP-2-T remains an experimental dual agonist with limited formal validation but growing preclinical interest.
  • Tesofensine is a small-molecule monoamine reuptake inhibitor with potent weight-loss effects but a narrower cardiometabolic profile than GLP peptides.
  • Combination research pairing GLP agents with SGLT2 inhibitors represents one of the most active frontiers in 2026 metabolic drug development.

The Mechanistic Divide: How GLP Peptides Differ From Traditional Small-Molecule Drugs

The Mechanistic Divide: How GLP Peptides Differ From Traditional Small-Molecule Drugs

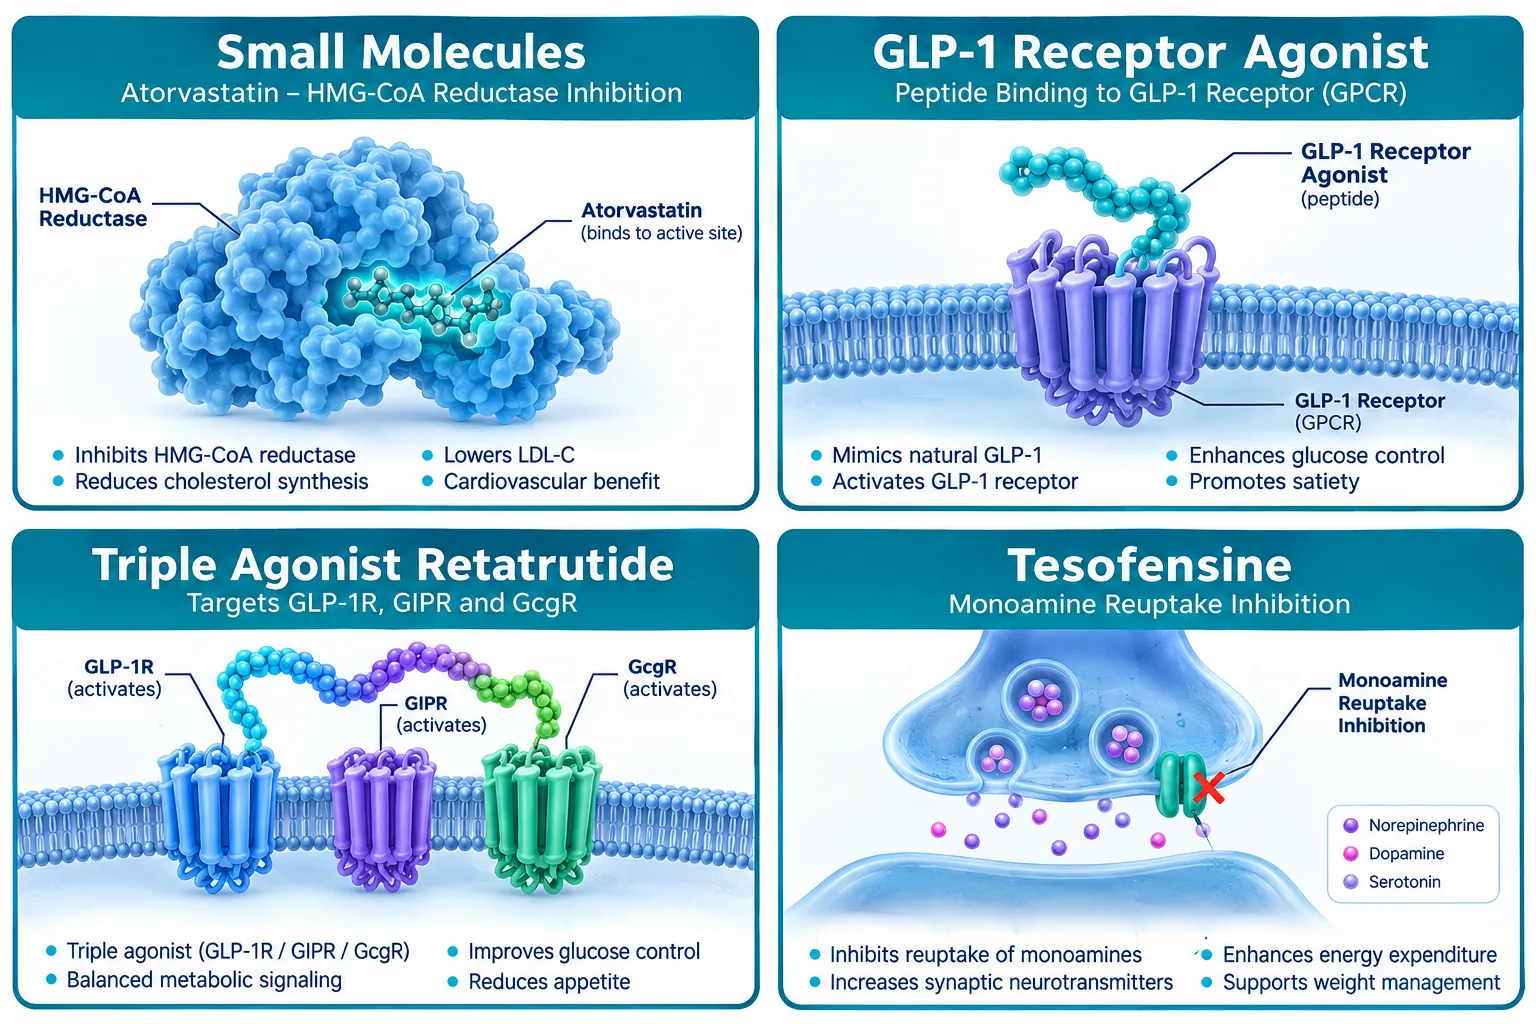
Traditional cardiometabolic drugs work by blocking or inhibiting a single molecular target. Atorvastatin inhibits HMG-CoA reductase to reduce LDL cholesterol. Amlodipine blocks L-type calcium channels to lower blood pressure. Prednisone suppresses inflammatory cytokines through glucocorticoid receptor binding. Each of these agents is chemically synthesized, orally bioavailable, and designed for a narrow, well-defined pathway.

GLP peptides operate differently. They are amino acid chains that mimic or modulate endogenous gut hormones, binding to G-protein-coupled receptors (GPCRs) that regulate insulin secretion, appetite, gastric emptying, and energy expenditure. This multi-system engagement is the core reason GLP peptides vs traditional small-molecule metabolic drugs has become such a meaningful research distinction.

Key mechanistic differences at a glance:

Feature GLP Peptides Traditional Small Molecules
Molecular structure Amino acid chains Synthesized organic compounds
Route of administration Typically subcutaneous Often oral
Target specificity Multi-receptor hormonal Single enzyme or channel
Metabolic scope Broad (weight, glucose, CV) Narrow (lipid, BP, inflammation)
Degradation pathway Enzymatic (DPP-4) Hepatic metabolism

This mechanistic breadth is precisely why researchers are now studying GLP agents alongside, and sometimes in place of, older drug classes in cardiometabolic protocols.

For researchers exploring the broader peptide landscape, the GLP-3, GLP-1, and GLP-2 explained: a researcher's guide to the peptide family provides essential foundational context.

Retatrutide, GLP-2-T, and the Multi-Agonist Paradigm in Cardiometabolic Research

Retatrutide, GLP-2-T, and the Multi-Agonist Paradigm in Cardiometabolic Research

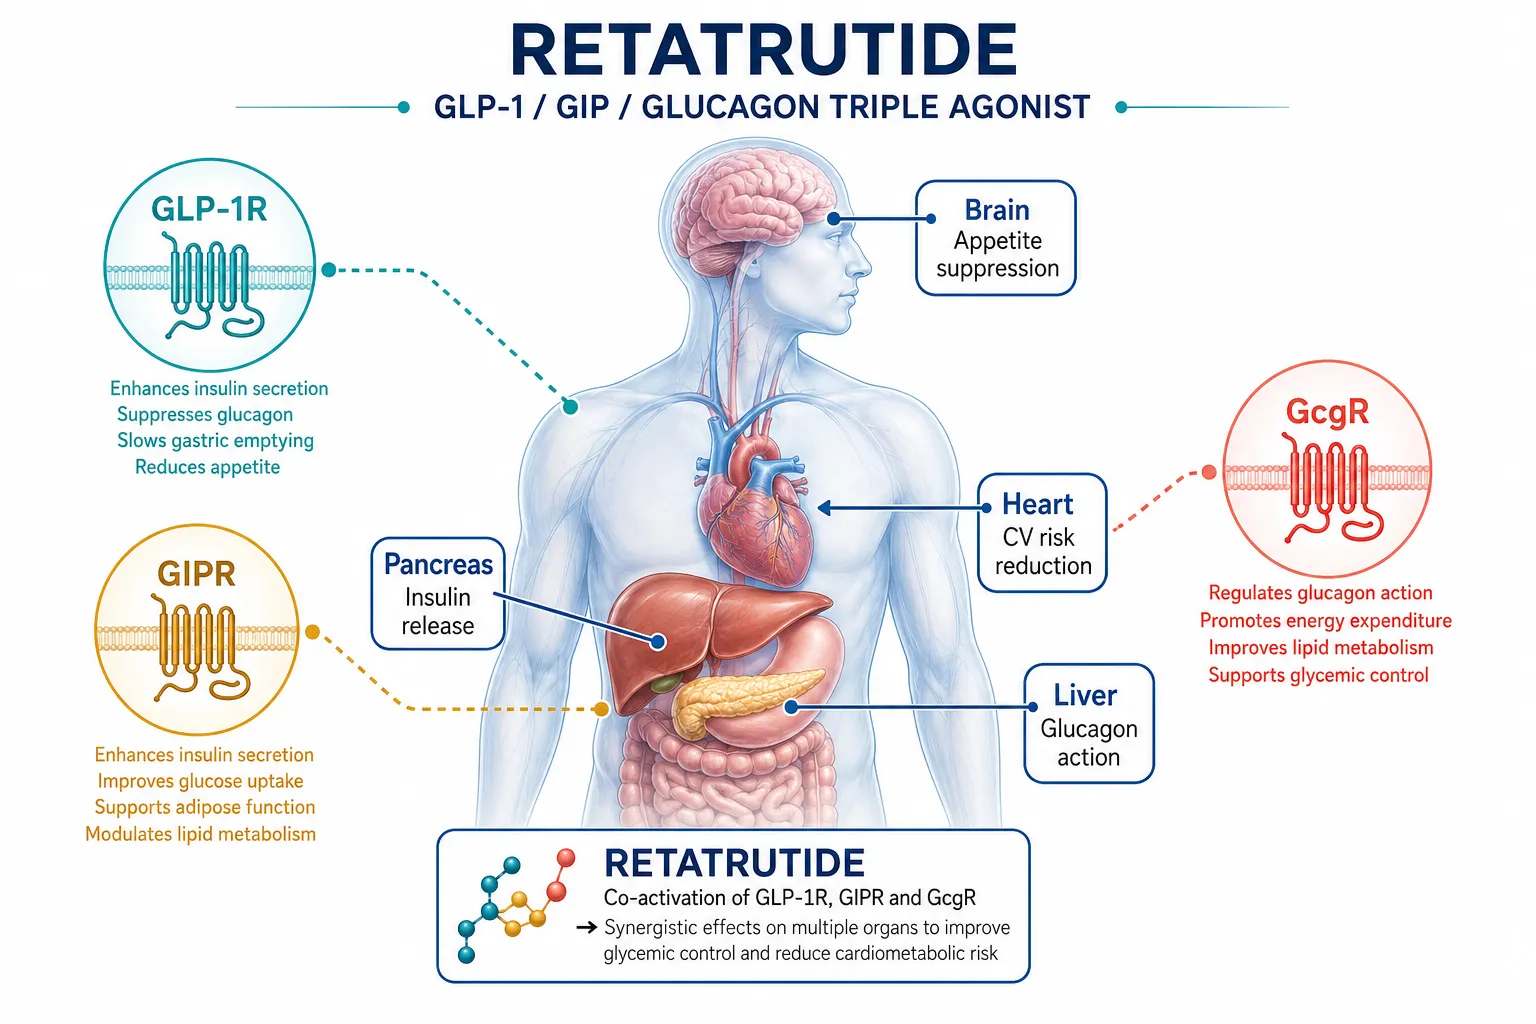
The most significant development in GLP peptides vs traditional small-molecule metabolic drugs research is the emergence of multi-receptor agonists. Retatrutide, often referred to informally as a "GLP-3-like" agent, simultaneously activates GLP-1, GIP (glucose-dependent insulinotropic polypeptide), and glucagon receptors. This triple agonism drives insulin sensitization, appetite suppression, and increased energy expenditure through three distinct but complementary pathways.

Phase 2 clinical data for retatrutide demonstrated weight reduction of up to approximately 24-30% from baseline, surpassing outcomes seen with GLP-1 mono-agonists like semaglutide. The TRIUMPH phase 3 program, now actively enrolling across multiple cardiometabolic indications in 2025-2026, is evaluating retatrutide not just for obesity but for heart failure, metabolic-associated steatohepatitis (MASH), and type 2 diabetes. This breadth of indication reflects the multi-system nature of triple agonism.

"Triple agonism in retatrutide targets three receptor systems that no single traditional small molecule was designed to address simultaneously."

Researchers can explore the triple agonist retatrutide research profile for detailed mechanistic data, and those sourcing research-grade material may reference Reta 10mg specifications.

GLP-2-T is a distinct experimental compound, a dual agonist with activity at GLP-2 receptors alongside a secondary target. GLP-2 receptors are expressed in intestinal epithelium and have established roles in gut barrier integrity and nutrient absorption. In cardiometabolic research, GLP-2-T is being studied for its potential to reduce systemic inflammation originating from gut permeability, a pathway entirely absent from the pharmacology of atorvastatin or amlodipine. Formal clinical validation remains limited, but preclinical models show meaningful reductions in inflammatory markers relevant to atherosclerosis.

For researchers tracking GLP-1 peptides for research purposes, understanding GLP-2-T's distinct receptor profile is important for accurate experimental design.

Tesofensine and the Role of Small-Molecule Weight-Loss Agents Alongside GLP Peptides

Tesofensine and the Role of Small-Molecule Weight-Loss Agents Alongside GLP Peptides

Tesofensine occupies a unique position in the GLP peptides vs traditional small-molecule metabolic drugs conversation. It is a small molecule, not a peptide, that inhibits the reuptake of serotonin, dopamine, and norepinephrine in the central nervous system. This triple monoamine reuptake inhibition produces significant appetite suppression and has shown weight loss of 6-12% in clinical trials, placing it well above older agents like orlistat but below GLP-1 mono-agonists.

As of 2026, tesofensine remains approved in limited markets, primarily in Latin America, without broad regulatory clearance from the FDA or EMA. This geographic restriction shapes its role in research: it is studied as a comparator agent and as a potential combination partner rather than a frontline cardiometabolic therapy.

Where tesofensine fits in research design:

  • As a CNS-pathway comparator to GLP-1's peripheral appetite suppression
  • In combination studies examining monoaminergic plus incretin-based weight loss
  • As a reference compound when evaluating tolerability profiles of newer peptides

The tolerability distinction between GLP peptides and tesofensine is clinically meaningful. GLP agents primarily cause gastrointestinal side effects (nausea, vomiting) that are dose-dependent and typically transient. Tesofensine carries cardiovascular signals including elevated heart rate and blood pressure, a concern that limits its cardiometabolic framing despite its weight-loss efficacy.

Researchers interested in mitochondrial and cellular energy pathways as complementary research targets may find value in reviewing MOTS-C peptide and mitochondrial biogenesis research, which addresses energy metabolism from a distinct mechanistic angle.

Integration with traditional cardiometabolic drugs is another active research area. GLP-1 agents combined with SGLT2 inhibitors (such as empagliflozin) show additive reductions in cardiovascular events, HbA1c, and body weight, a combination that no traditional drug pairing achieves with comparable breadth. Retatrutide's triple agonism may further amplify these benefits when studied alongside SGLT2 inhibitors in future phase 3 substudies.

For researchers sourcing verified compounds, high purity peptide sourcing and peptide CoA verification resources are critical for maintaining experimental integrity.

Conclusion

The debate around GLP peptides vs traditional small-molecule metabolic drugs is not a competition, it is a map of complementary mechanisms. Atorvastatin, amlodipine, and prednisone remain essential tools for managing lipid levels, blood pressure, and inflammation through well-characterized single-target pathways. Retatrutide, GLP-2-T, and tesofensine address metabolic dysfunction through hormonal signaling, gut-barrier modulation, and CNS appetite regulation, pathways that traditional drugs were not designed to reach.

Actionable next steps for researchers in 2026:

  1. Define the specific receptor pathway under investigation before selecting a GLP agent or small-molecule comparator.
  2. Review TRIUMPH phase 3 data as it publishes to understand retatrutide's evolving cardiometabolic evidence base.
  3. When designing combination protocols, consider GLP-1 plus SGLT2 pairings as the current evidence-supported benchmark.
  4. Treat GLP-2-T as a hypothesis-generating agent requiring rigorous in vitro validation before advancing to complex models.
  5. Source all research peptides with documented purity certificates to ensure data reproducibility.

The cardiometabolic research landscape in 2026 is defined by multi-mechanism thinking. Researchers who understand where each agent sits in this landscape, peptide or small molecule, will design more precise, reproducible, and ultimately meaningful studies.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/glp-peptides-vs-traditional-small-molecule-metabolic-drugs-where-glp-3-retatruti.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-28 13:05:232026-08-28 13:05:23GLP Peptides vs Traditional Small‑Molecule Metabolic Drugs: Where GLP‑3 Retatrutide, GLP‑2‑T, and Tesofensine Fit in Cardiometabolic Research
Peptides and Polypeptides in Cardiometabolic Research: How Atorvastatin and GLP-3 Retatrutide Answer Different Questions

Peptides and Polypeptides in Cardiometabolic Research: How Atorvastatin and GLP-3 Retatrutide Answer Different Questions

August 25, 2026/0 Comments/in Uncategorized/by

Cardiovascular disease still accounts for roughly one in three deaths worldwide, yet the research tools available to study it have never been more mechanistically diverse. Peptides and polypeptides in cardiometabolic research, alongside small-molecule agents like atorvastatin, now occupy distinct but complementary niches, and understanding those niches is essential for any researcher designing a rigorous cardiometabolic model in 2026. Retatrutide, Lilly's triple hormone receptor agonist, and atorvastatin, a well-characterized HMG-CoA reductase inhibitor, are not rivals. They answer fundamentally different scientific questions.

Key Takeaways

  • Atorvastatin targets LDL cholesterol through hepatic enzyme inhibition and has decades of hard cardiovascular endpoint data behind it.
  • Retatrutide is a large polypeptide triple agonist (GLP-1, GIP, and glucagon receptors) that produces simultaneous weight loss, glycemic improvement, and multi-factor lipid and inflammatory marker changes.
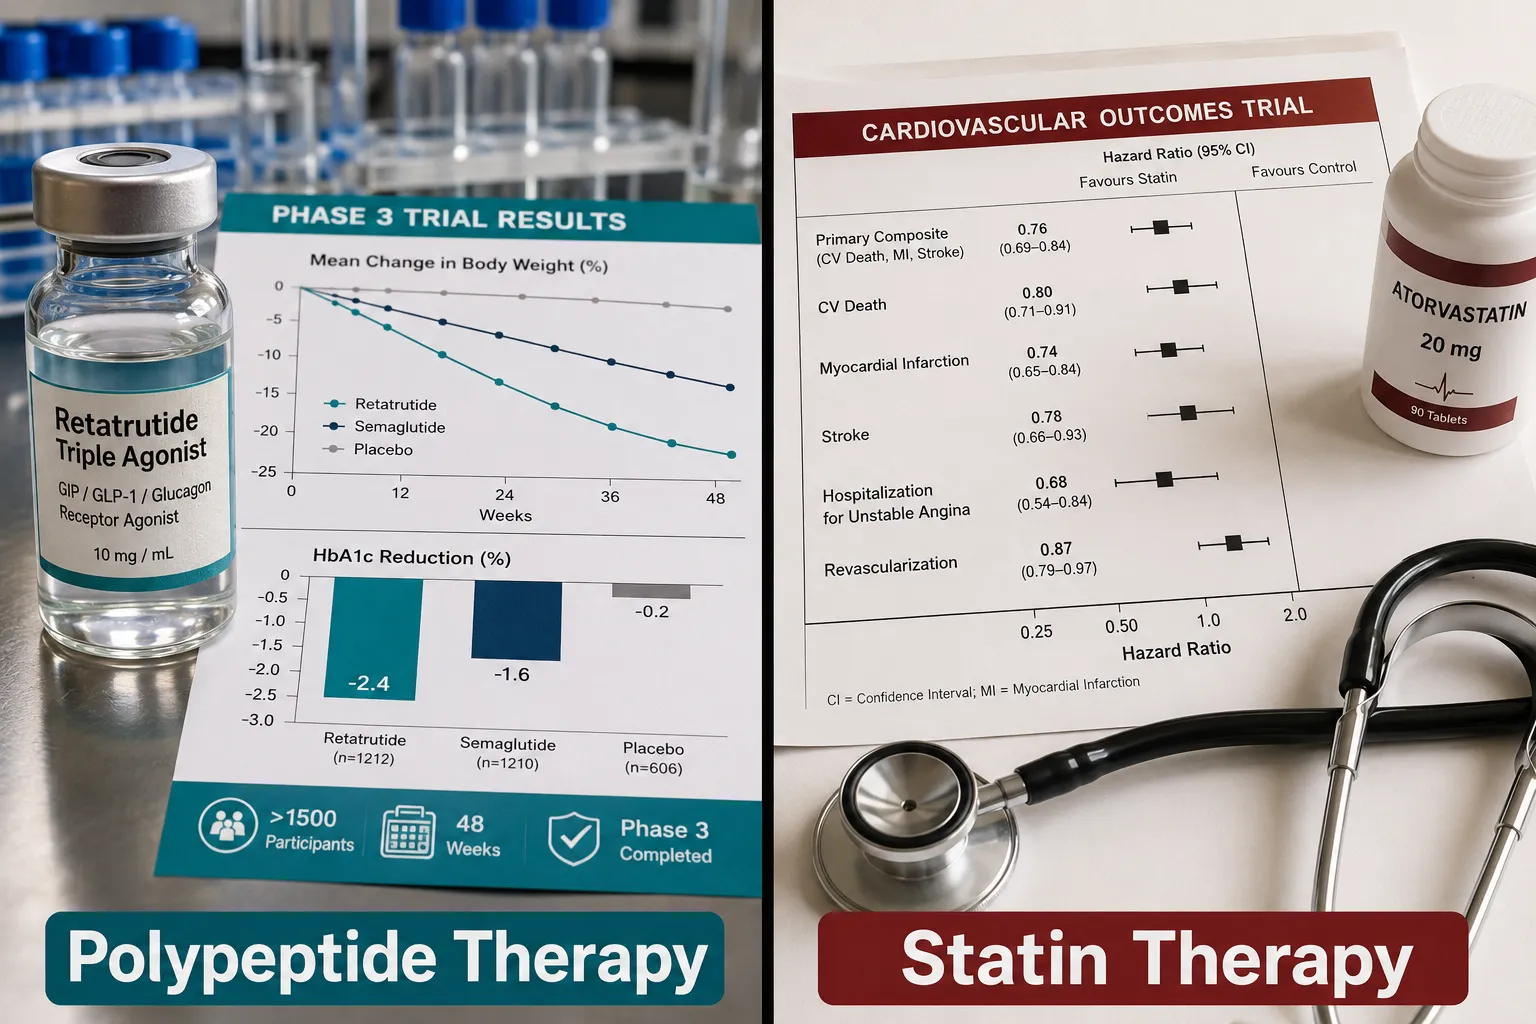
  • Phase 3 TRIUMPH data from 2026 show retatrutide delivering roughly 20.8% body-weight loss and a 1.6-point HbA1c reduction in people with type 2 diabetes and obesity.
  • Hard cardiovascular outcomes data for retatrutide are still prospective; atorvastatin remains the benchmark for proven event reduction.
  • Future cardiometabolic research protocols are likely to combine both classes rather than substitute one for the other.

Two Mechanistic Niches, One Research Field

Two Mechanistic Niches, One Research Field

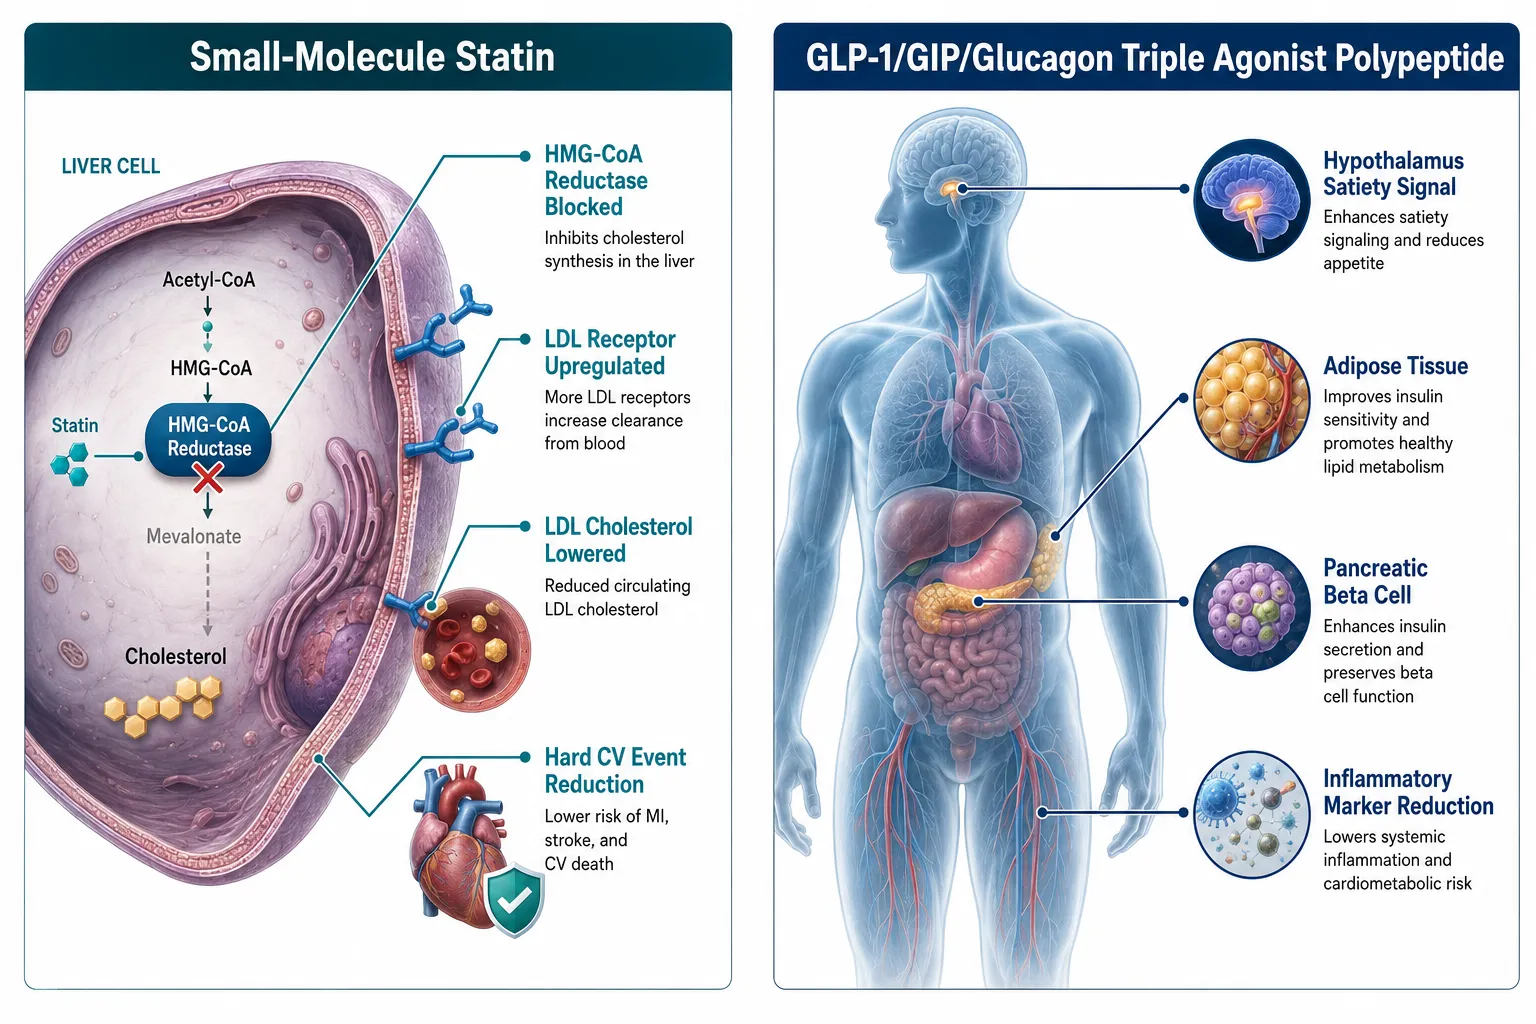
The clearest way to understand peptides and polypeptides in cardiometabolic research is to start with mechanism. Atorvastatin is a small molecule, it diffuses into hepatocytes and competitively inhibits HMG-CoA reductase, the rate-limiting enzyme in cholesterol synthesis. The liver responds by upregulating LDL receptors, pulling LDL particles out of circulation. The result is a focused, well-quantified reduction in a single atherogenic driver. Extended follow-up of atorvastatin trials shows a hazard ratio of 0.81 for nonfatal myocardial infarction plus fatal coronary heart disease, 0.88 for total coronary events, and 0.86 for cardiovascular mortality versus placebo. These are hard endpoints, not surrogate markers.

Retatrutide works at an entirely different level of biological complexity. As a polypeptide agonist, it simultaneously activates three hormone receptors:

  • GLP-1 receptor, suppresses appetite, slows gastric emptying, improves insulin secretion
  • GIP receptor, enhances insulin sensitivity and modulates fat storage
  • Glucagon receptor, drives hepatic fat oxidation and energy expenditure

This triple-receptor engagement produces a cascade of downstream effects that no small molecule currently replicates. Researchers exploring the broader GLP-3, GLP-1, and GLP-2 peptide family will recognize that incretin-class polypeptides are structurally and functionally distinct from statins at every level of analysis.

Key distinction: Atorvastatin answers the question "How do we lower LDL and prevent myocardial infarction?" Retatrutide answers the question "How do we simultaneously reduce body weight, improve glycemia, and shift multiple cardiometabolic risk factors in obesity?"

What Phase 3 Retatrutide Data Reveal in 2026

What Phase 3 Retatrutide Data Reveal in 2026

The TRIUMPH phase 3 program has produced some of the most discussed cardiometabolic data of 2026. In an 80-week trial in adults with type 2 diabetes and obesity or overweight, the highest retatrutide dose delivered approximately 20.8% body-weight loss and a 1.6-point HbA1c reduction. Separate 40-week data from the TRANSCEND-T2D program showed roughly a 1.9-percentage-point HbA1c reduction versus 0.8 points with placebo, alongside 15.3% body-weight loss versus 2.6% with placebo.

Beyond weight and glycemia, post-hoc analysis of two phase 2 trials documented striking changes in atherogenic lipoproteins and inflammatory markers:

Biomarker Change with Retatrutide
Non-HDL cholesterol (no diabetes) Down ~26.9%
Apolipoprotein B Down ~21-24%
Large triglyceride-rich particles Down ~76-84%
Small LDL particles Down ~32%
High-sensitivity CRP Down ~54.8%
Interleukin-6 Down ~29.6%

These numbers explain why researchers sourcing GLP-3 triple agonist research compounds are designing multi-endpoint protocols rather than single-biomarker studies.

However, one critical caveat applies. Safety data presented in June 2026 identified seven arrhythmia events and three major cardiovascular complications among 403 retatrutide participants, compared with none in the placebo group. Formal cardiovascular outcomes trials are underway, but the evidence base as of mid-2026 remains dominated by surrogate endpoints. Researchers following hormone research protocols should account for this distinction when designing study endpoints.

How Peptide and Statin Research Protocols Complement Each Other

How Peptide and Statin Research Protocols Complement Each Other

The practical implication for cardiometabolic researchers is that these two compound classes are additive, not interchangeable. A well-designed protocol might use atorvastatin as the LDL-lowering backbone, where decades of outcomes data provide a reliable comparator, while layering a polypeptide agonist like retatrutide to interrogate weight-dependent, inflammation-dependent, and glycemia-dependent pathways simultaneously.

Three research design principles follow from this:

  1. Define the primary endpoint clearly. If the question is "Does this intervention reduce hard cardiovascular events?", atorvastatin-class data remain the gold standard comparator. If the question involves weight loss, metabolic syndrome reversal, or multi-factor risk reduction, polypeptide agonists open new model territory.

  2. Use purity-verified compounds. Both small-molecule and peptide research depends on compound integrity. Resources on peptide COA verification and high purity peptide sourcing are essential starting points before any protocol is finalized.

  3. Track complementary biomarker panels. Retatrutide's lipid effects (non-HDL, ApoB, triglycerides) overlap with but do not duplicate statin effects (LDL-C, coronary event risk). Running both panels in parallel captures the full mechanistic picture.

Researchers working on metabolic comorbidities, particularly sarcopenia alongside obesity, may also find value in reviewing sarcopenia research resources, since muscle-mass preservation is an emerging consideration in aggressive weight-loss peptide protocols.

For those building broader incretin-focused models, GLP-1 peptide research compounds provide a useful baseline comparator against the triple-agonist profile of retatrutide.

Conclusion

Peptides and polypeptides in cardiometabolic research occupy a mechanistic space that small-molecule statins were never designed to fill, and the reverse is equally true. Atorvastatin remains the benchmark for durable LDL reduction and hard cardiovascular event prevention. Retatrutide, as a polypeptide triple agonist, is redefining what simultaneous weight loss, glycemic control, and multi-factor risk reduction can look like in a single compound. The TRIUMPH phase 3 data of 2026 make the case for retatrutide's surrogate-marker efficacy compellingly; the hard outcomes question is the next frontier.

Actionable next steps for researchers:

  • Audit current protocols to identify whether the primary question is LDL-centric (statin-appropriate) or multi-factor metabolic (polypeptide-appropriate), then design accordingly.
  • Verify compound purity through COA documentation before initiating any peptide-based cardiometabolic model.
  • Monitor the TRIUMPH cardiovascular outcomes arm as data mature toward Lilly's anticipated regulatory submission around Q1 2027.
  • Consider combination protocols that use both compound classes to capture the full breadth of cardiometabolic biology.

The field is not moving away from statins. It is building a more complete picture around them, one polypeptide at a time.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/peptides-and-polypeptides-in-cardiometabolic-research-how-atorvastatin-and-glp-3.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-25 13:05:402026-08-25 13:05:40Peptides and Polypeptides in Cardiometabolic Research: How Atorvastatin and GLP-3 Retatrutide Answer Different Questions
Polypeptide Peptides in Cardiometabolic Research: How GLP-2-T and GLP-3 Fit With Classic Drug Pathways

Polypeptide Peptides in Cardiometabolic Research: How GLP-2-T and GLP-3 Fit With Classic Drug Pathways

August 15, 2026/0 Comments/in Uncategorized/by

Cardiovascular disease and metabolic dysfunction together account for more than 17 million deaths globally each year, yet the pharmacological toolkit used to address them has expanded dramatically beyond the small-molecule era. Polypeptide peptides in cardiometabolic research, including how GLP-2-T and GLP-3 fit with classic drug pathways, represent one of the most active frontiers in that expansion. Understanding where these peptides sit relative to established agents like atorvastatin or amlodipine requires a clear look at receptor biology, half-life engineering, and the boundaries between preclinical investigation and approved therapy.

Key Takeaways

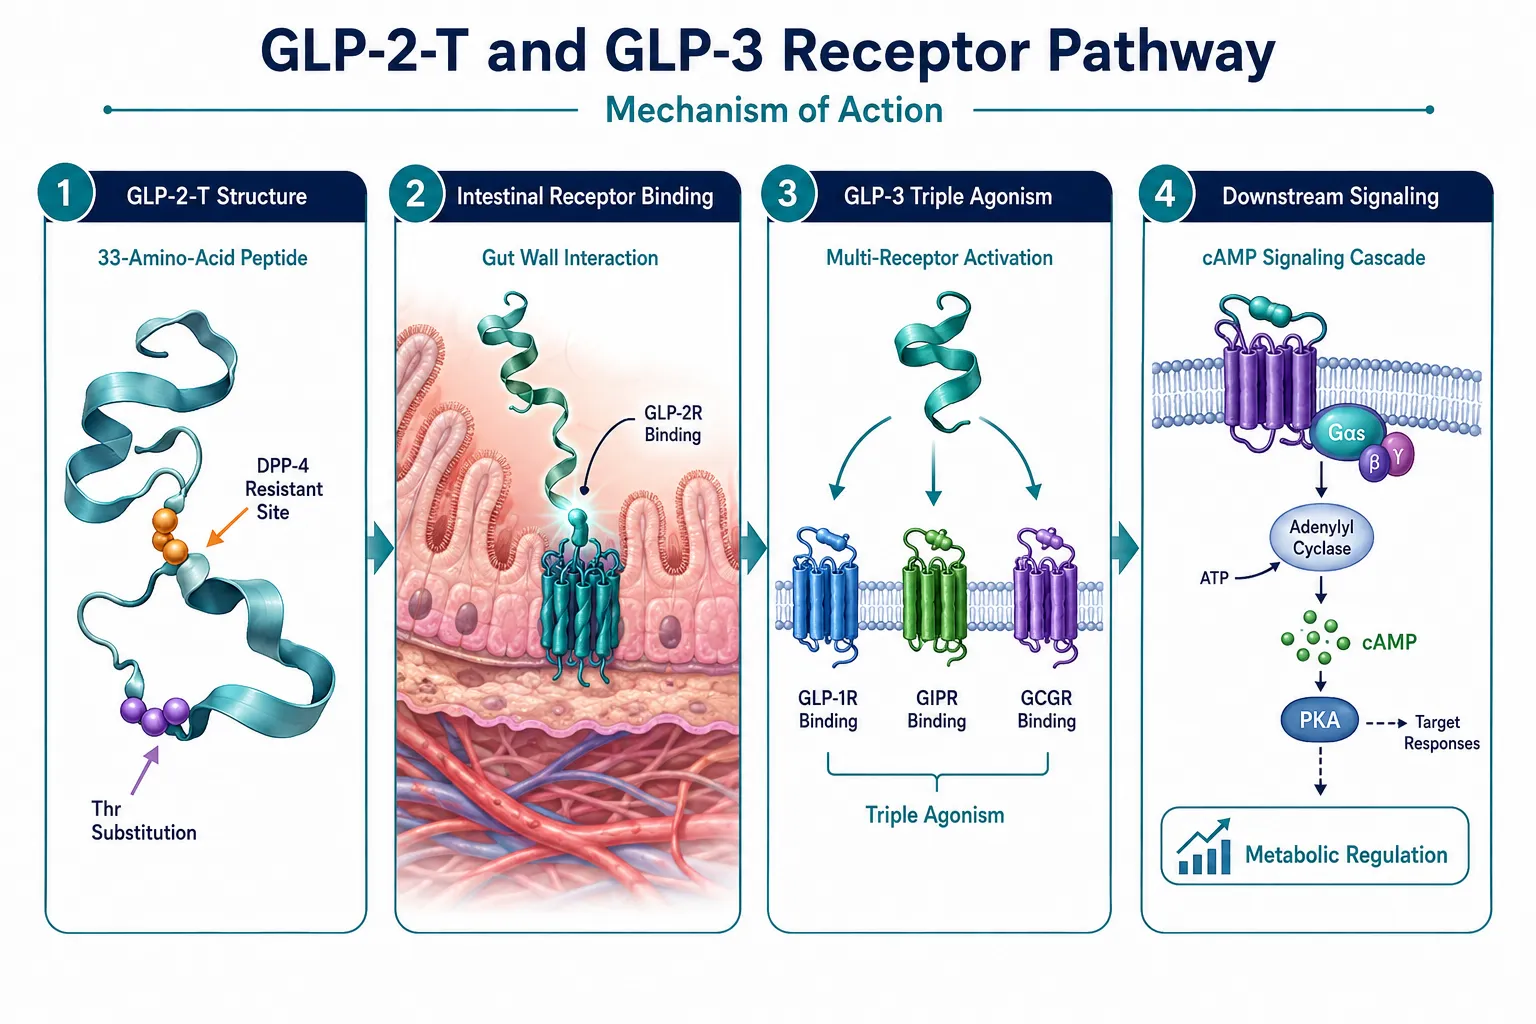
  • GLP-2-T is a stability-enhanced analog of the native 33-amino-acid peptide GLP-2, engineered to resist DPP-4 degradation for use in controlled laboratory research.
  • GLP-3, as part of the retatrutide triple-agonist framework, targets GLP-1R, GIPR, and GCGR simultaneously, distinguishing it mechanistically from classic single-target small molecules.
  • Classic cardiometabolic drugs such as statins and calcium channel blockers act via well-defined, orally bioavailable small-molecule mechanisms; research peptides operate through receptor agonism requiring parenteral delivery.
  • No GLP-2 or GLP-2-T analog currently holds approval for cardiometabolic indications; all available data remain preclinical as of 2026.
  • Researchers comparing these compound classes must account for differences in molecular size, route of administration, and endpoint design.

What GLP-2-T and GLP-3 Are, and Why They Matter to Cardiometabolic Science

What GLP-2-T and GLP-3 Are, and Why They Matter to Cardiometabolic Science

Native glucagon-like peptide-2 (GLP-2) is a 33-amino-acid peptide derived from proglucagon. Its primary roles include promoting intestinal mucosal growth, enhancing nutrient absorption, reducing bone resorption, and linking nutrient intake to gut-derived hormonal signaling. These functions place it squarely in the gut-liver axis, a pathway with growing relevance to metabolic disease.

GLP-2-T is a laboratory-grade, modified analog of GLP-2. The "T" designation reflects threonine substitutions and other structural changes designed to resist degradation by dipeptidyl peptidase-4 (DPP-4), the enzyme that rapidly inactivates native GLP-2. By extending the peptide's half-life, GLP-2-T allows researchers to study GLP-2 receptor pharmacology in in-vitro and animal models without the confounding effect of rapid enzymatic breakdown. Multiple vendors classify it explicitly as a research-use-only compound, not authorized for human or veterinary administration.

GLP-3, in the context of modern metabolic research, is most closely associated with the triple-agonist framework exemplified by retatrutide. This peptide simultaneously engages three receptors:

  • GLP-1R (glucagon-like peptide-1 receptor)
  • GIPR (glucose-dependent insulinotropic polypeptide receptor)
  • GCGR (glucagon receptor)

That multi-receptor profile is a fundamental departure from how classic cardiometabolic drugs are designed. For a deeper look at how triple-agonist peptides are reshaping research endpoints, the article on GLP-3 Retatrutide and triple-agonist peptides in phase 3 obesity data provides useful context.

Polypeptide Peptides in Cardiometabolic Research: Comparing Mechanisms With Classic Small Molecules

Polypeptide Peptides in Cardiometabolic Research: Comparing Mechanisms With Classic Small Molecules

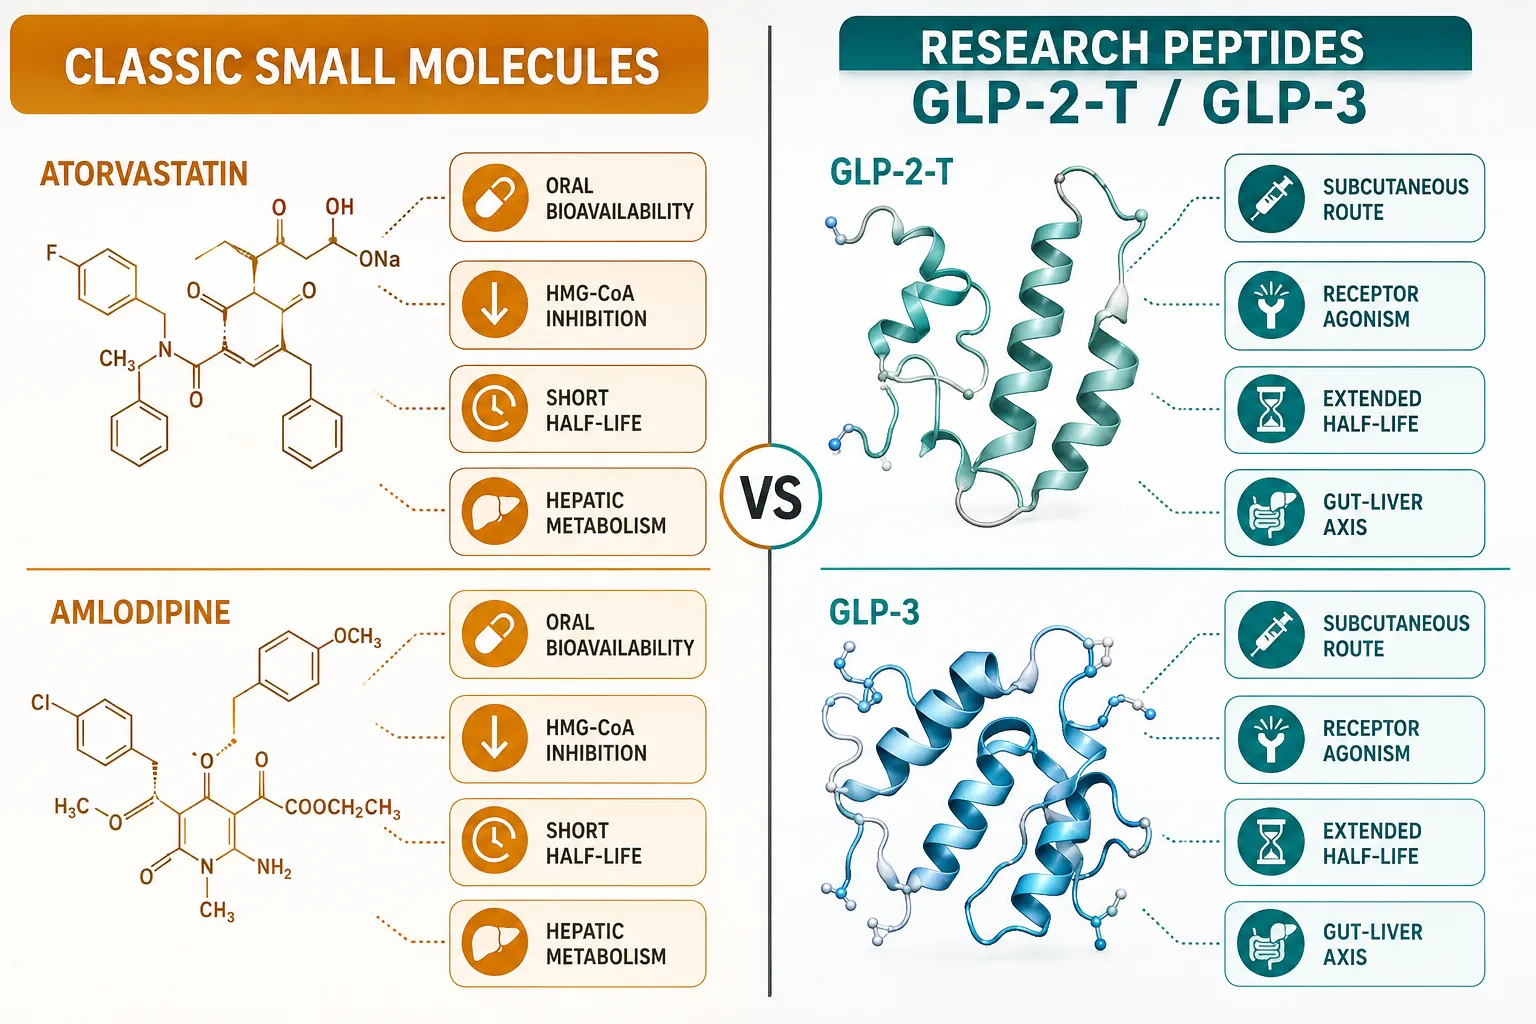
The contrast between polypeptide research peptides and classic small-molecule cardiometabolic drugs is best understood across four dimensions: molecular size, receptor targeting, route of administration, and half-life.

Property Classic Small Molecules (e.g., Atorvastatin, Amlodipine) Research Peptides (GLP-2-T, GLP-3)
Molecular Weight ~300-600 Da ~3,000-5,000 Da
Primary Target Single enzyme or channel (HMG-CoA reductase, L-type Ca2+ channel) G-protein-coupled receptors (GLP-2R, GLP-1R, GIPR, GCGR)
Route Oral Subcutaneous or IV (research models)
Half-Life Engineering Hepatic metabolism governs duration DPP-4 resistance, fatty acid conjugation, or amino acid substitution
Regulatory Status (2026) FDA-approved, guideline-endorsed Research use only; not FDA-approved for cardiometabolic indications

Atorvastatin inhibits HMG-CoA reductase, a single hepatic enzyme, reducing LDL cholesterol through a well-mapped pathway. Amlodipine blocks L-type calcium channels in vascular smooth muscle, lowering peripheral resistance. Both are orally bioavailable and have decades of cardiovascular outcome data behind them.

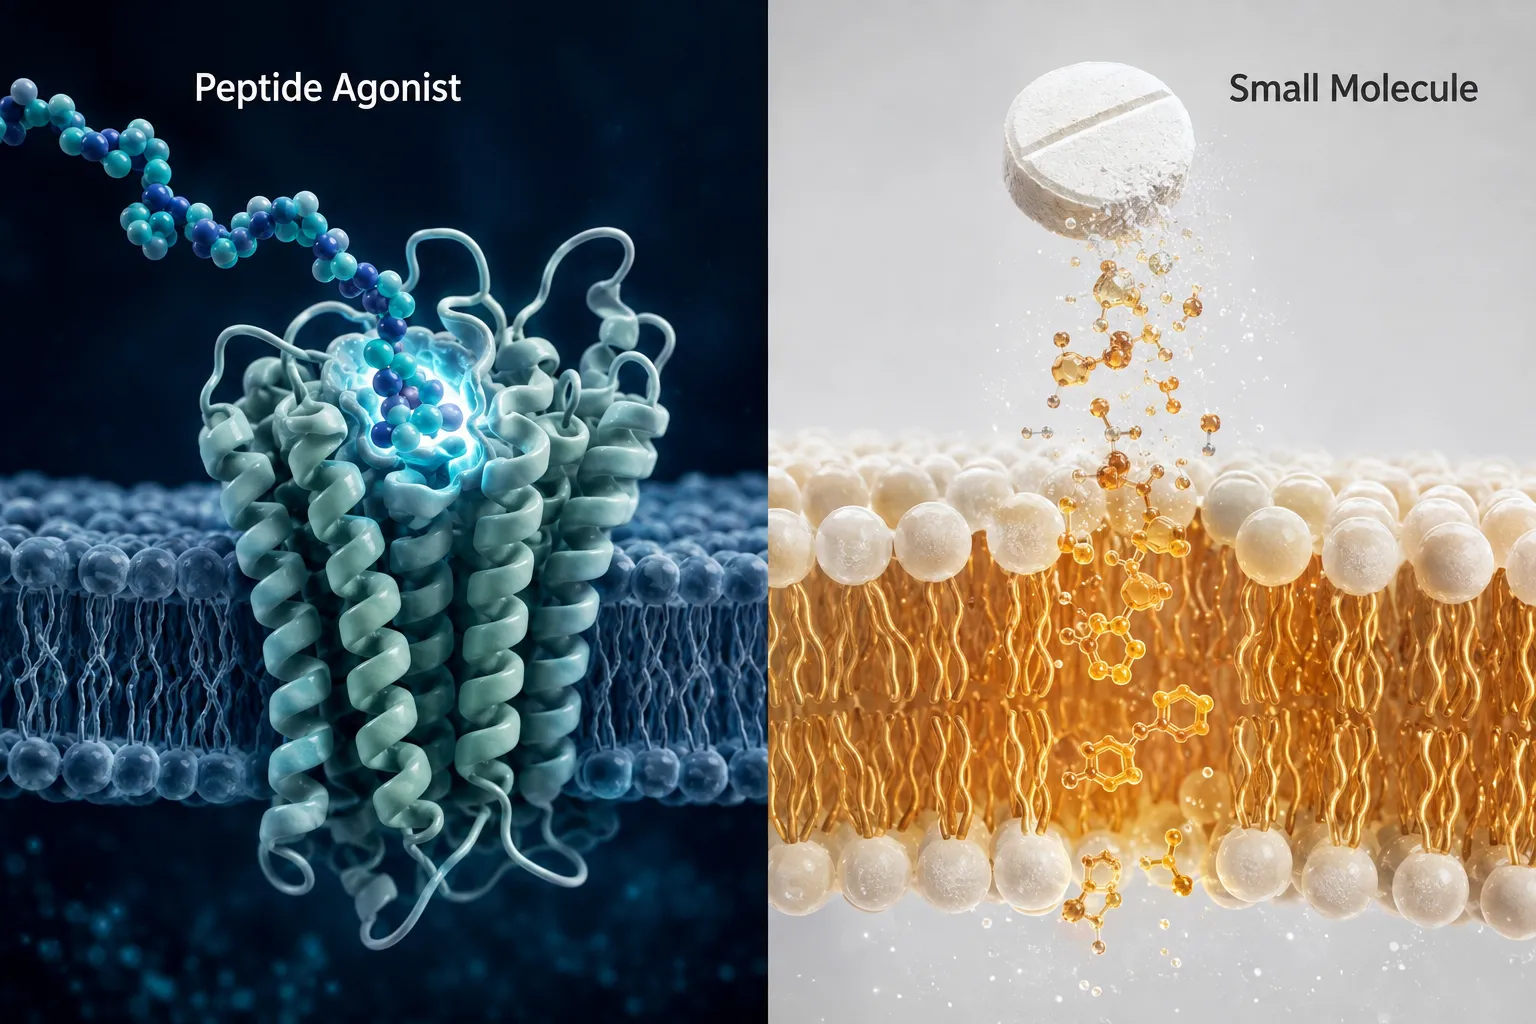
GLP-2-T and GLP-3 analogs operate differently. They bind G-protein-coupled receptors, triggering intracellular cAMP cascades that influence gene expression, cell proliferation, and metabolic flux. Because peptides are enzymatically degraded in the gastrointestinal tract, oral delivery is not viable without special formulation, a core practical difference from classic drugs.

"The shift from single-enzyme inhibition to multi-receptor agonism is not just a chemical distinction, it reframes what an endpoint even means in a cardiometabolic study."

For a broader comparison of how peptide size shapes experimental design, the resource on peptides and polypeptides in modern research and how molecular size shapes function is worth reviewing. Researchers also benefit from understanding the differences between peptides and classic small-molecule drugs like prednisone, amlodipine, and metoprolol.

Polypeptide Peptides in Cardiometabolic Research: Endpoints, Regulatory Boundaries, and What the Data Show

Polypeptide Peptides in Cardiometabolic Research: Endpoints, Regulatory Boundaries, and What the Data Show

The only GLP-2 analog currently in routine clinical use is teduglutide, a DPP-4-resistant GLP-2 analog approved for short-bowel syndrome, not for any cardiometabolic indication. This distinction is critical. GLP-2-T is not teduglutide, and no GLP-2-T formulation carries approval for metabolic disease management as of mid-2026.

Research involving GLP-2-T focuses on:

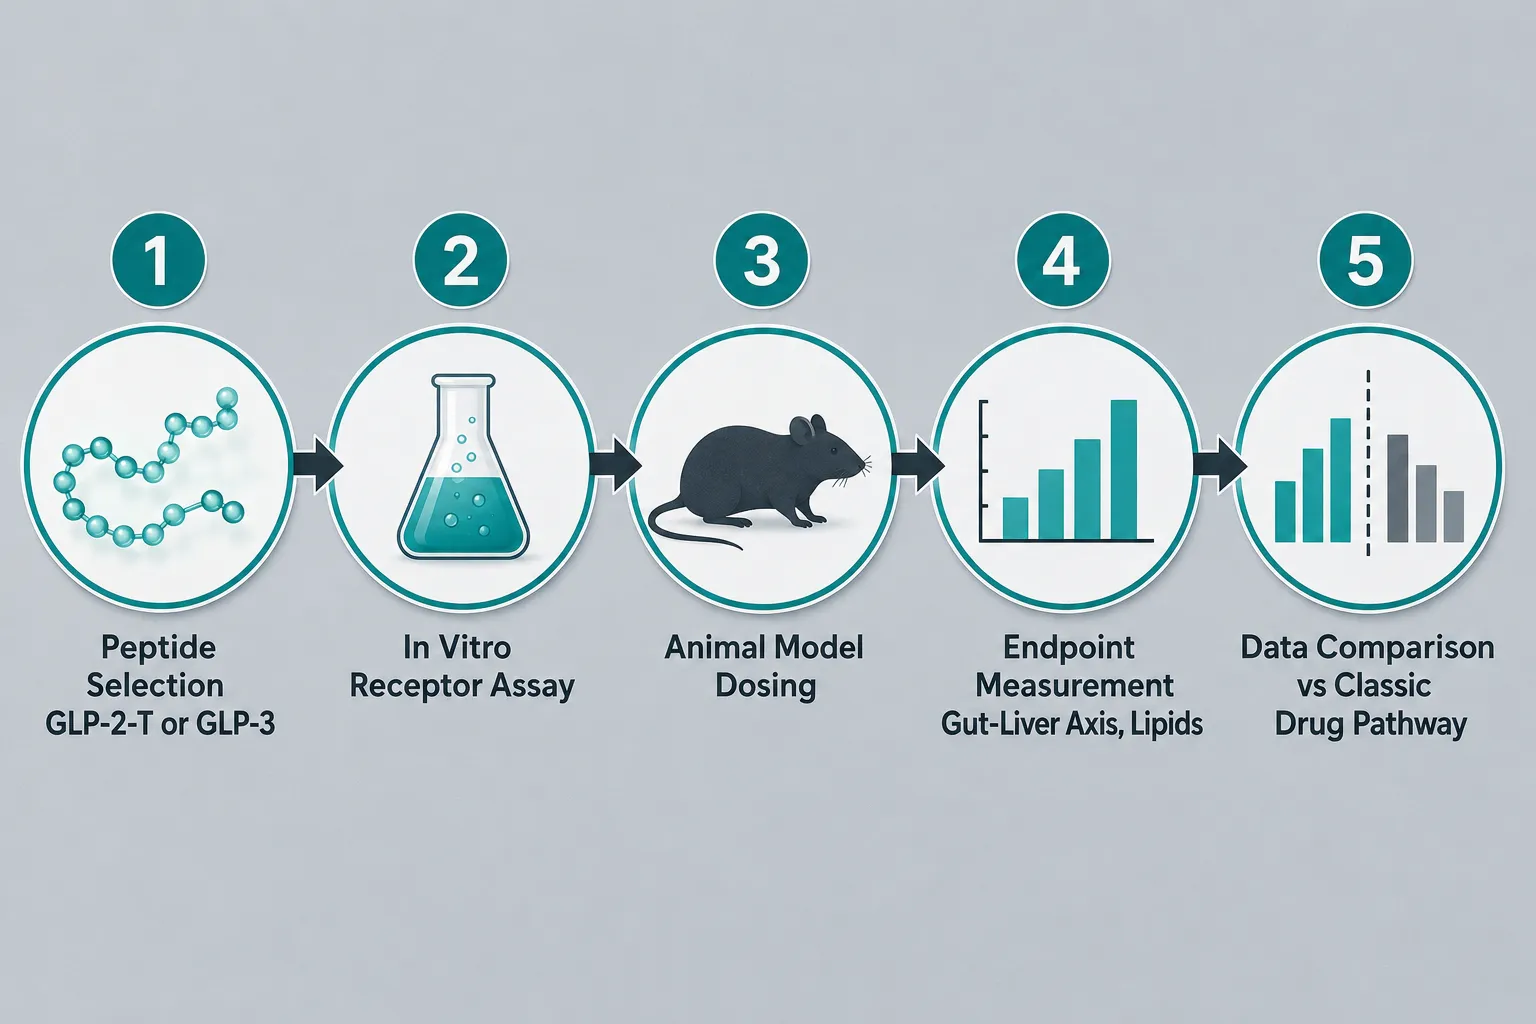
  1. Intestinal barrier integrity, studying tight-junction proteins and mucosal repair in cell culture and rodent models
  2. Nutrient sensing, examining how gut-derived hormonal signals influence hepatic lipid handling via the gut-liver axis
  3. Receptor pharmacology, mapping GLP-2R binding kinetics and downstream signaling in controlled systems

Any cardiometabolic relevance of GLP-2-T is therefore likely to be indirect, mediated through inflammation reduction, improved nutrient absorption efficiency, and gut-liver crosstalk, not through direct cardiovascular receptor effects.

GLP-3 research, by contrast, targets pathways with more direct metabolic overlap. The triple-agonist framework engages GCGR to promote energy expenditure, GIPR to modulate insulin secretion and fat storage, and GLP-1R to slow gastric emptying and reduce appetite. Researchers studying these interactions alongside classic drug mechanisms can consult the detailed breakdown on polypeptide peptides in cardiometabolic models comparing tesofensine, GLP-3, retatrutide, and GLP-2-T with classic small-molecule drugs.

No major cardiovascular or metabolism society guideline in 2026 lists GLP-2 or GLP-2-T analogs as part of standard cardiometabolic therapy. GLP-1 receptor agonists and SGLT2 inhibitors remain the guideline-endorsed peptide-adjacent agents in that space. For researchers tracking where GLP-3 retatrutide data are heading, the ongoing analysis of GLP-3 retatrutide in phase 3 trials and how triple agonism is reshaping obesity and MASLD research endpoints offers current perspective.

Researchers designing studies that incorporate these peptides alongside classic drugs should also consider how drug-mechanism context shapes study validity. The overview of polypeptide peptides and drug mechanisms, what common medications reveal about research-use peptide pharmacology addresses this directly.

Conclusion

Polypeptide peptides in cardiometabolic research, particularly how GLP-2-T and GLP-3 fit with classic drug pathways, represent a genuinely distinct pharmacological category, not simply a larger version of a small molecule. GLP-2-T extends the half-life of a gut-derived hormone to probe intestinal and metabolic signaling in preclinical systems. GLP-3, within the triple-agonist framework, simultaneously engages multiple metabolic receptors in ways that no single classic drug attempts.

Actionable next steps for researchers and informed readers:

  • Clearly distinguish GLP-2-T (research-only analog) from teduglutide (approved clinical agent) when reviewing literature or designing studies.
  • When comparing peptide endpoints to small-molecule endpoints, account for route of administration, receptor multiplicity, and the absence of cardiovascular-outcome trial data for research peptides.
  • Treat all GLP-2-T and GLP-3 preclinical data as hypothesis-generating, not as evidence of clinical efficacy or safety.
  • Use established comparison frameworks, such as those contrasting peptide and small-molecule pharmacology, to contextualize new findings accurately.

The field is moving quickly. Staying grounded in mechanism, regulatory status, and endpoint design is the most reliable way to interpret what these peptides genuinely offer to cardiometabolic science.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/polypeptide-peptides-in-cardiometabolic-research-how-glp-2-t-and-glp-3-fit-with.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-15 13:05:422026-08-15 13:05:42Polypeptide Peptides in Cardiometabolic Research: How GLP-2-T and GLP-3 Fit With Classic Drug Pathways
Polypeptide Peptides in Cardiometabolic Models: How Tesofensine, GLP-3 Retatrutide, and GLP-2-T Differ From Classic Small-Molecule Drugs

Polypeptide Peptides in Cardiometabolic Models: How Tesofensine, GLP-3 Retatrutide, and GLP-2-T Differ From Classic Small-Molecule Drugs

August 3, 2026/0 Comments/in Uncategorized/by

Cardiovascular disease and metabolic dysfunction together account for more than 17 million deaths annually worldwide, yet the dominant drug classes used to treat them, beta-blockers, statins, ACE inhibitors, were designed around receptor pharmacology that has barely changed since the 1970s. The emergence of polypeptide peptides in cardiometabolic models has fundamentally shifted what researchers believe is possible, offering multi-receptor engagement, tissue-level signaling precision, and endpoint profiles that classic small-molecule drugs simply cannot replicate.

Understanding how Tesofensine, GLP-3 Retatrutide, and GLP-2-T differ from agents like metoprolol or atorvastatin requires a close look at receptor biology, study design conventions, and the endpoints that matter most in modern metabolic research.

Key Takeaways

  • Polypeptide peptides engage G-protein-coupled receptors (GPCRs) with high structural specificity, whereas classic small molecules often act on enzyme active sites or ion channels.
  • Retatrutide is a triple agonist (GLP-1/GIP/glucagon receptors), giving it a multi-axis metabolic footprint that no single small-molecule drug can match.
  • Tesofensine targets monoamine reuptake through a CNS-mediated pathway, bridging neurological and metabolic endpoints in a way that statins and beta-blockers do not.
  • GLP-2-T primarily modulates intestinal and cardiovascular tissue remodeling, making it relevant to cardiometabolic models focused on gut-heart crosstalk.
  • Study design for peptides demands different controls, stability protocols, and biomarker panels than standard small-molecule trials.

Key Takeaways

Receptor Biology: Where Peptides and Small Molecules Diverge

The most fundamental difference between polypeptide peptides in cardiometabolic models and classic small-molecule drugs lies in how they bind and what they activate.

Small molecules like atorvastatin inhibit HMG-CoA reductase, an intracellular enzyme. Metoprolol blocks beta-1 adrenergic receptors through competitive antagonism. Both mechanisms are relatively narrow, one receptor, one pathway, one primary endpoint. This is pharmacologically clean but metabolically limited.

Polypeptide peptides, by contrast, bind to the extracellular domains of GPCRs and trigger conformational changes that cascade through multiple intracellular signaling arms, cAMP, PI3K/Akt, MAPK, simultaneously. This is not a side effect; it is the mechanism.

Key receptor differences at a glance:

Feature Classic Small Molecules Polypeptide Peptides
Binding site Enzyme active site or receptor pocket Extracellular GPCR domain
Signaling breadth Narrow, single-pathway Multi-axis, pleiotropic
Molecular weight Typically under 500 Da 1,000-5,000+ Da
Metabolic clearance Hepatic CYP450 enzymes Proteolytic degradation
Receptor selectivity High for single target Tunable across receptor families

Retatrutide exemplifies this multi-axis design. As a GLP-3 Retatrutide triple agonist, it simultaneously activates GLP-1, GIP, and glucagon receptors, three distinct GPCRs with overlapping but non-identical metabolic roles. No statin or beta-blocker operates across three receptor families at once.

For researchers sourcing reference-grade materials, understanding how Bachem and reference standards shape peptide benchmarks is essential to designing valid comparative assays.

Receptor Biology: Where Peptides and Small Molecules Diverge

Comparing Tesofensine, GLP-3 Retatrutide, and GLP-2-T in Cardiometabolic Study Design

When researchers design cardiometabolic studies, the choice of compound determines nearly every other variable: dosing frequency, biomarker selection, tissue endpoints, and control group structure.

Tesofensine: CNS-Metabolic Bridge

Tesofensine inhibits the reuptake of serotonin, norepinephrine, and dopamine, a triple monoamine mechanism. Unlike classic weight-loss drugs or antihypertensives, it engages central appetite regulation and peripheral metabolic rate in the same model. This makes it uniquely useful in studies examining the neurological drivers of cardiometabolic dysfunction.

Compared to metoprolol, which reduces cardiac output by blocking beta-1 receptors, Tesofensine's cardiovascular effects are indirect, mediated through body composition changes, sympathetic tone modulation, and energy expenditure. Study designs using Tesofensine therefore require CNS-relevant endpoints (appetite hormone panels, dopaminergic markers) alongside standard cardiometabolic readouts like blood pressure and lipid profiles. Researchers interested in MC4R signaling pathways will find Tesofensine's monoamine mechanism intersects with melanocortin receptor biology in appetite-focused models.

GLP-3 Retatrutide: Triple-Axis Metabolic Remodeling

Retatrutide's triple agonism produces effects on insulin secretion, glucagon suppression, gastric emptying, and adipose tissue lipolysis, all within a single compound. Classic small molecules require combination therapy (e.g., a statin plus a GLP-1 agonist) to approach this endpoint breadth.

In study design terms, this creates both opportunity and complexity. Researchers must account for:

  • Glucose homeostasis markers (HbA1c, fasting insulin, HOMA-IR)
  • Lipid remodeling endpoints (triglycerides, LDL particle size)
  • Body composition imaging (DEXA or MRI for visceral fat)
  • Cardiovascular surrogates (arterial stiffness, inflammatory cytokines)

For labs building GLP-1 peptide research protocols, Retatrutide represents a logical next step beyond single-receptor GLP-1 analogs. Researchers can also explore GLP-3 buy-online resources when planning triple-agonist study inventories.

GLP-2-T: Gut-Heart Crosstalk and Tissue Remodeling

GLP-2-T acts primarily on GLP-2 receptors expressed in intestinal epithelium, cardiac tissue, and vascular endothelium. Its relevance to cardiometabolic models centers on gut barrier integrity, mucosal blood flow, and cardiac remodeling endpoints, a profile with no direct equivalent among classic antihypertensives or lipid-lowering agents.

Where atorvastatin reduces LDL through hepatic cholesterol synthesis inhibition, GLP-2-T modulates the gut-heart axis through tissue trophic effects. Studies using GLP-2-T typically incorporate intestinal permeability assays, endothelial function markers, and cardiac fibrosis panels alongside standard metabolic readouts. Researchers planning GLP-1 and GLP-2 comparative studies should build assay panels that capture both receptor families.

GLP-2-T: Gut-Heart Crosstalk and Tissue Remodeling

Study Design Considerations Unique to Polypeptide Peptides in Cardiometabolic Models

The shift from small-molecule to peptide-based cardiometabolic research requires rethinking several standard design assumptions.

Stability and storage are non-trivial. Unlike metoprolol tablets, polypeptide peptides require cold-chain handling, reconstitution protocols, and degradation controls. Researchers should establish peptide integrity checkpoints at baseline and throughout the study window.

Control group design must account for vehicle effects. Peptide vehicles (bacteriostatic water, DMSO blends) can independently affect some metabolic endpoints, a confound that does not arise with oral small-molecule controls.

Biomarker panel breadth must expand. A statin study might track LDL, ALT, and CK. A Retatrutide study demands glucose, insulin, GLP-1 active, GIP, glucagon, triglycerides, body weight, and inflammatory markers at minimum.

Dosing interval differs fundamentally. Most peptides have short plasma half-lives and require more frequent dosing than once-daily oral drugs. Some, like fatty-acid-conjugated GLP-1 analogs, are engineered for extended half-life, but this must be verified per compound. Researchers exploring related growth hormone-axis peptides can review GHRP-2 versus Sermorelin comparisons for parallel design lessons in peptide half-life management.

"The endpoint profile of a triple-agonist peptide is not three times the data of a single-receptor drug, it is a fundamentally different picture of metabolic biology."

For labs building comprehensive peptide research inventories, reviewing available peptide research catalogs helps align compound selection with study endpoints before procurement.

Conclusion

The comparison between polypeptide peptides in cardiometabolic models and classic small-molecule drugs is not simply a matter of newer versus older. It reflects a deeper divergence in receptor biology, signaling architecture, and what researchers define as a meaningful endpoint. Tesofensine, GLP-3 Retatrutide, and GLP-2-T each engage cardiometabolic biology through mechanisms that metoprolol and atorvastatin were never designed to reach.

Actionable next steps for researchers in 2026:

  1. Audit current study designs to determine whether single-receptor endpoints adequately capture the biology under investigation.
  2. Build expanded biomarker panels that reflect multi-axis peptide mechanisms, glucose, lipid, inflammatory, and tissue-remodeling markers together.
  3. Establish peptide-specific stability and storage protocols before study initiation.
  4. Source reference-grade compounds with verified purity documentation to ensure assay validity.
  5. Consider comparative arms that include both a classic small-molecule control and a peptide comparator to generate translational contrast data.

The mechanistic gap between these two drug classes is not a limitation of small molecules, it is an opportunity that peptide-based cardiometabolic research is uniquely positioned to explore.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/polypeptide-peptides-in-cardiometabolic-models-how-tesofensine-glp-3-retatrutide.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-03 13:04:312026-08-03 13:04:31Polypeptide Peptides in Cardiometabolic Models: How Tesofensine, GLP-3 Retatrutide, and GLP-2-T Differ From Classic Small-Molecule Drugs

Tag Archive for: cardiometabolic research

GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It

July 21, 2026/0 Comments/by Pure Tested

Cover Image

A single misread label in a research catalog can send an entire study in the wrong direction. That is precisely the risk buried inside the term "GLP2 Tirz Peptide", a shorthand that looks like it refers to the biological hormone GLP-2 but actually points to something else entirely. Understanding the GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It is not a minor vocabulary exercise. It is a foundational step in accurate research design.

GLP2 Tirz Peptide dual receptor diagram

Key Takeaways

  • "GLP2 Tirz" is an informal catalog label for tirzepatide, not a reference to the biological peptide GLP-2.
  • Tirzepatide is a dual agonist targeting the GLP-1 and GIP receptors, it does not act on the GLP-2 receptor.
  • The "2" in GLP2 Tirz likely reflects a vendor numbering system for dual-receptor compounds, not receptor identity.
  • Confusing GLP-2 with tirzepatide can lead to flawed study design and incorrect interpretation of results.
  • Research-grade tirzepatide requires strict storage at -20°C and is intended for laboratory use only.

What the Term "GLP2 Tirz Peptide" Actually Means

The phrase "GLP2 Tirz Peptide" does not describe a peptide that binds to the glucagon-like peptide-2 receptor. Instead, it is an informal naming convention used by some research suppliers to catalog tirzepatide, a synthetic dual incretin mimetic.

Tirzepatide is the compound's World Health Organization-assigned generic name. The "tirz-" stem signals its dual incretin activity. It was developed as a once-weekly injectable agent and works by co-activating two distinct receptors:

  • The GLP-1 receptor (glucagon-like peptide-1), which regulates insulin secretion, appetite suppression, and gastric emptying.
  • The GIP receptor (glucose-dependent insulinotropic polypeptide), which influences fat storage, insulin sensitivity, and energy balance.

Neither of these is the GLP-2 receptor. GLP-2 is a separate peptide with a distinct biological role, it primarily supports intestinal epithelial growth and gut barrier integrity. Tirzepatide has no known affinity for the GLP-2 receptor.

"The number '2' in GLP2 Tirz does not identify a receptor subtype. It appears to reflect a vendor-assigned sequence number for dual-receptor compounds within a product catalog."

For researchers already familiar with the broader incretin landscape, the GLP-1 T research breakdown on dual receptor agonism provides useful context on how single versus dual agonism differs at the receptor level.

Why the Name Exists: Catalog Logic vs. Scientific Nomenclature

Understanding the GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It requires a look at how research suppliers build their catalogs.

Vendors often assign internal shorthand codes to compounds, especially those that share receptor families or structural similarities. In this case, the "GLP" prefix was applied to tirzepatide because it belongs to the incretin mimetic class. The number "2" was likely appended to distinguish it from a single-agonist GLP-1 compound (sometimes listed as "GLP1") in the same catalog.

This creates a numbering logic that reads:

Catalog Label Actual Compound Receptors Targeted
GLP1 Tirz Semaglutide-type single agonist GLP-1 only
GLP2 Tirz Tirzepatide GLP-1 + GIP
GLP3 Triple agonist compounds GLP-1 + GIP + Glucagon

The "2" in GLP2 Tirz counts the number of receptor targets, not the receptor name. This distinction is critical. Researchers who encounter this label without that context may incorrectly assume the compound interacts with the GLP-2 receptor, a completely different biological pathway.

For those exploring the next step in this progression, the GLP3 triple agonist overview explains how triple-receptor compounds extend this catalog logic further.

How Researchers Should Interpret GLP2 Tirz Peptide

Naming confusion between GLP-2 and Tirz in research

Accurate interpretation of GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It comes down to three practical steps.

Step 1: Verify the Compound Identity

Always cross-reference the catalog label against the molecular formula and Certificate of Analysis (CoA). Research-grade tirzepatide carries the molecular formula C225H348N48O68 and a molecular weight of approximately 4,813.5 g/mol. If those figures match, the compound is tirzepatide regardless of what the label says.

Reputable suppliers provide HPLC-verified purity of 99% or greater. Reviewing the quality testing protocols for research peptides helps researchers understand what documentation to request before use.

Step 2: Align Study Design with the Correct Receptor Targets

Any study designed around GLP2 Tirz should be structured around GLP-1 and GIP receptor pathways, not GLP-2. Research themes for tirzepatide include:

  • Glycemic control, insulin secretion dynamics and glucose-dependent responses
  • Weight and fat mass, adipose tissue mobilization and appetite signaling
  • Cardiometabolic markers, lipid profiles, blood pressure, and inflammatory indicators

Designing experiments around intestinal epithelial repair or gut barrier function, which are GLP-2 domains, would be a fundamental mismatch.

Related research into metabolic peptide mechanisms can be found in the cagrilintide synergy with GLP-1 overview, which explores how complementary compounds interact within overlapping metabolic pathways.

Step 3: Handle and Store the Compound Correctly

Tirzepatide supplied for research purposes is typically lyophilized, freeze-dried into a powder form. Proper handling requires:

  • Storage temperature: -20°C in a sealed, desiccated container
  • Light protection: opaque or amber vials to prevent photodegradation
  • Reconstitution: sterile bacteriostatic water, used immediately or stored short-term at 4°C

Researchers interested in how other metabolic peptides are handled in similar conditions may find the GIP receptor and its importance article useful for comparative context.

Regulatory and Patent Context for 2026

Researcher reviewing Certificate of Analysis for tirzepatide

Tirzepatide's patent protection extends at least through 2036. This has two practical effects on the research market. First, branded pharmaceutical versions remain under exclusive commercial control. Second, it has driven demand for research-grade compounded versions among laboratory researchers who require the compound for preclinical study.

As of 2026, tirzepatide remains classified strictly as a research compound when sourced outside pharmaceutical channels. It is not approved for human or veterinary use in research-grade form. Researchers must document its use within institutional review frameworks and comply with applicable laboratory regulations.

For those exploring how other dual-pathway or metabolic research compounds are positioned in 2026, the NAD+ energetics and longevity research themes article offers a parallel look at how complex compounds are studied within rigorous frameworks.

Conclusion

The label "GLP2 Tirz Peptide" is a vendor shorthand, not a scientific classification. It refers to tirzepatide, a dual GLP-1 and GIP receptor agonist, and the "2" counts receptor targets, not receptor names. Confusing it with the biological peptide GLP-2 is an easy mistake with significant consequences for study design.

Actionable next steps for researchers:

  1. Always verify compound identity through molecular weight and HPLC documentation before designing any protocol.
  2. Build experimental frameworks around GLP-1 and GIP receptor biology, not GLP-2 pathways.
  3. Store lyophilized tirzepatide at -20°C in desiccated, light-protected conditions.
  4. Stay current with regulatory classifications in your jurisdiction, as the research peptide landscape continues to evolve through 2026 and beyond.

Precision in terminology is not bureaucratic caution, it is the first variable in every reliable experiment.

https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 0 0 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-21 13:18:092026-07-27 13:32:23GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top