Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: spironolactone

Spironolactone and Peptide Metabolism Studies: Aldosterone, Potassium, Fluid Volume, and Hormonal Readouts

Spironolactone and Peptide Metabolism Studies: Aldosterone, Potassium, Fluid Volume, and Hormonal Readouts

October 13, 2026/0 Comments/in Uncategorized/by

}

Professional () hero image with 'Spironolactone and Peptide Metabolism' in crisp white on a deep navy semi-transparent

Fewer drug mechanisms have remained as consistently relevant to endocrine research as aldosterone antagonism, and yet, as 2026 proteomic studies reveal, the downstream effects of spironolactone extend well beyond simple electrolyte shifts. Researchers designing peptide metabolism studies increasingly encounter spironolactone and peptide metabolism studies: aldosterone, potassium, fluid volume, and hormonal readouts as a methodological framework that demands careful interpretation of multiple, often interdependent biomarkers.

Key Takeaways

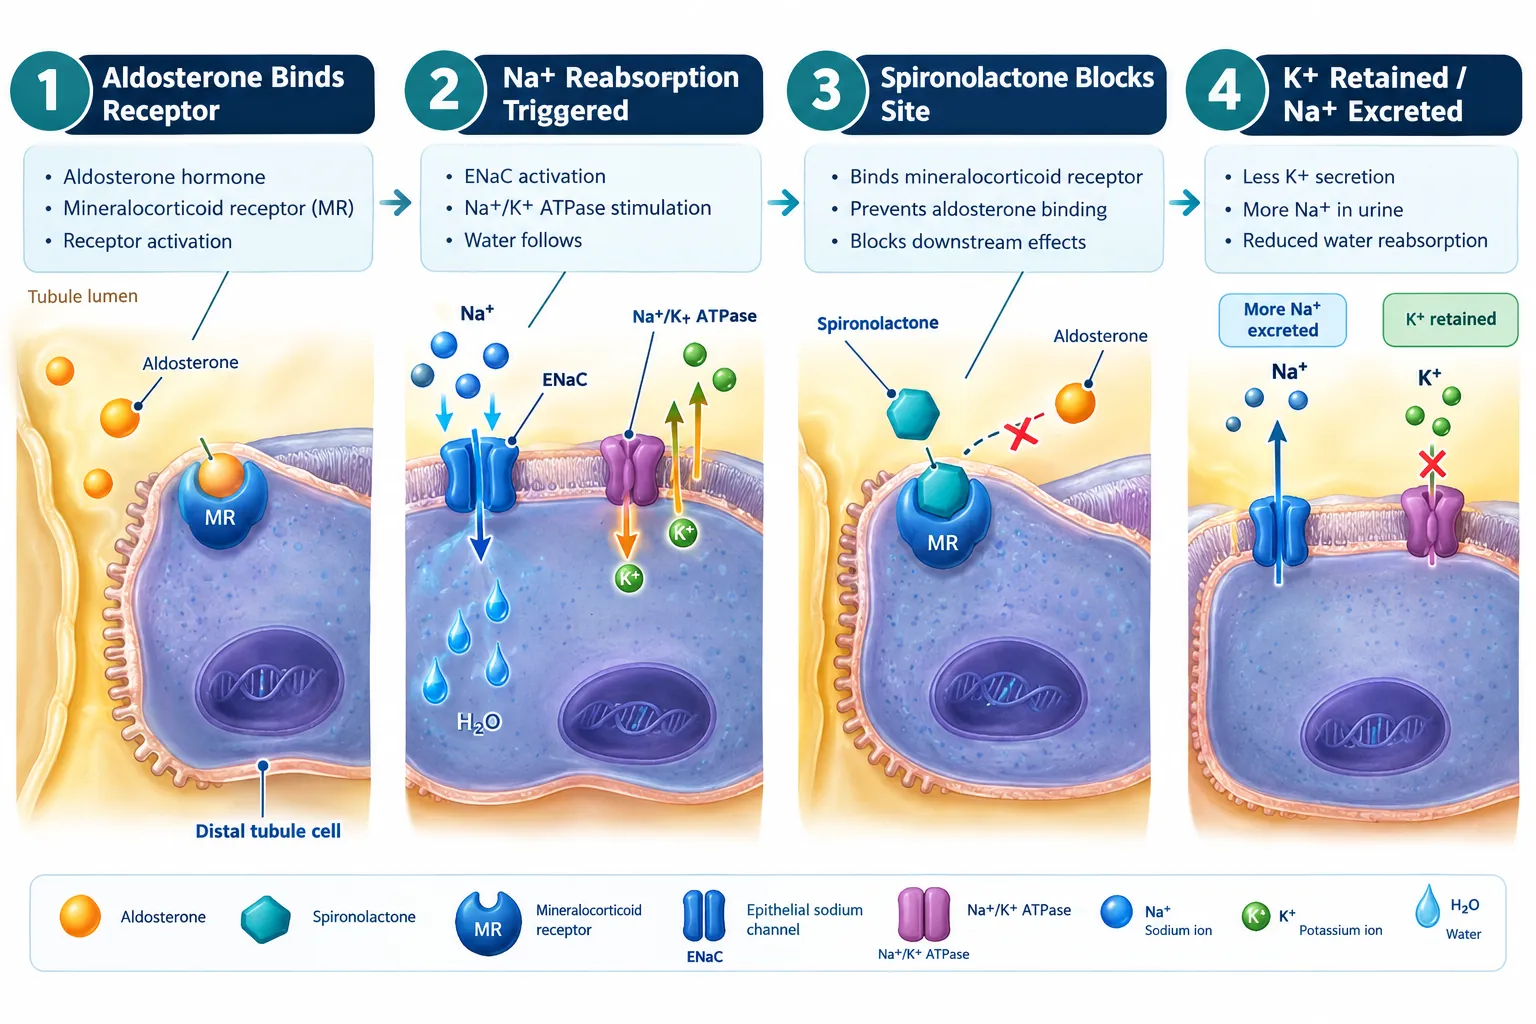
  • Spironolactone blocks aldosterone at the distal renal tubule, driving sodium and water excretion while retaining potassium.
  • Fluid volume reduction is a core, measurable outcome in both clinical and preclinical peptide models.
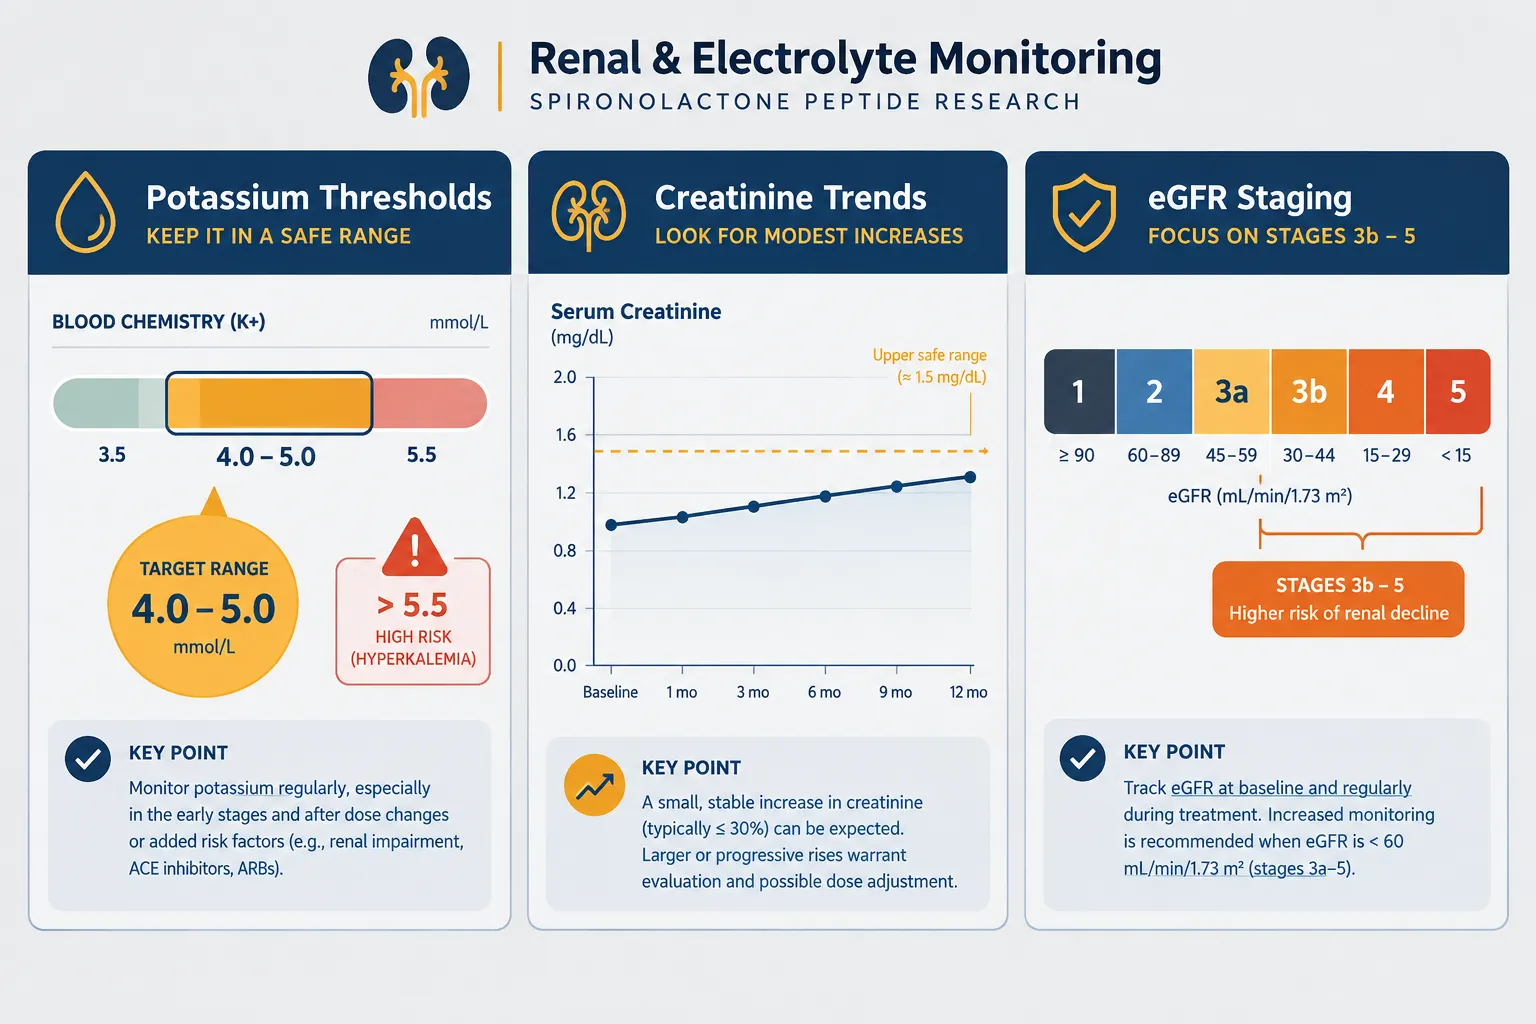
  • Potassium monitoring thresholds (stop/seek advice at greater than 6 mmol/L) remain a critical safety parameter in research protocols.
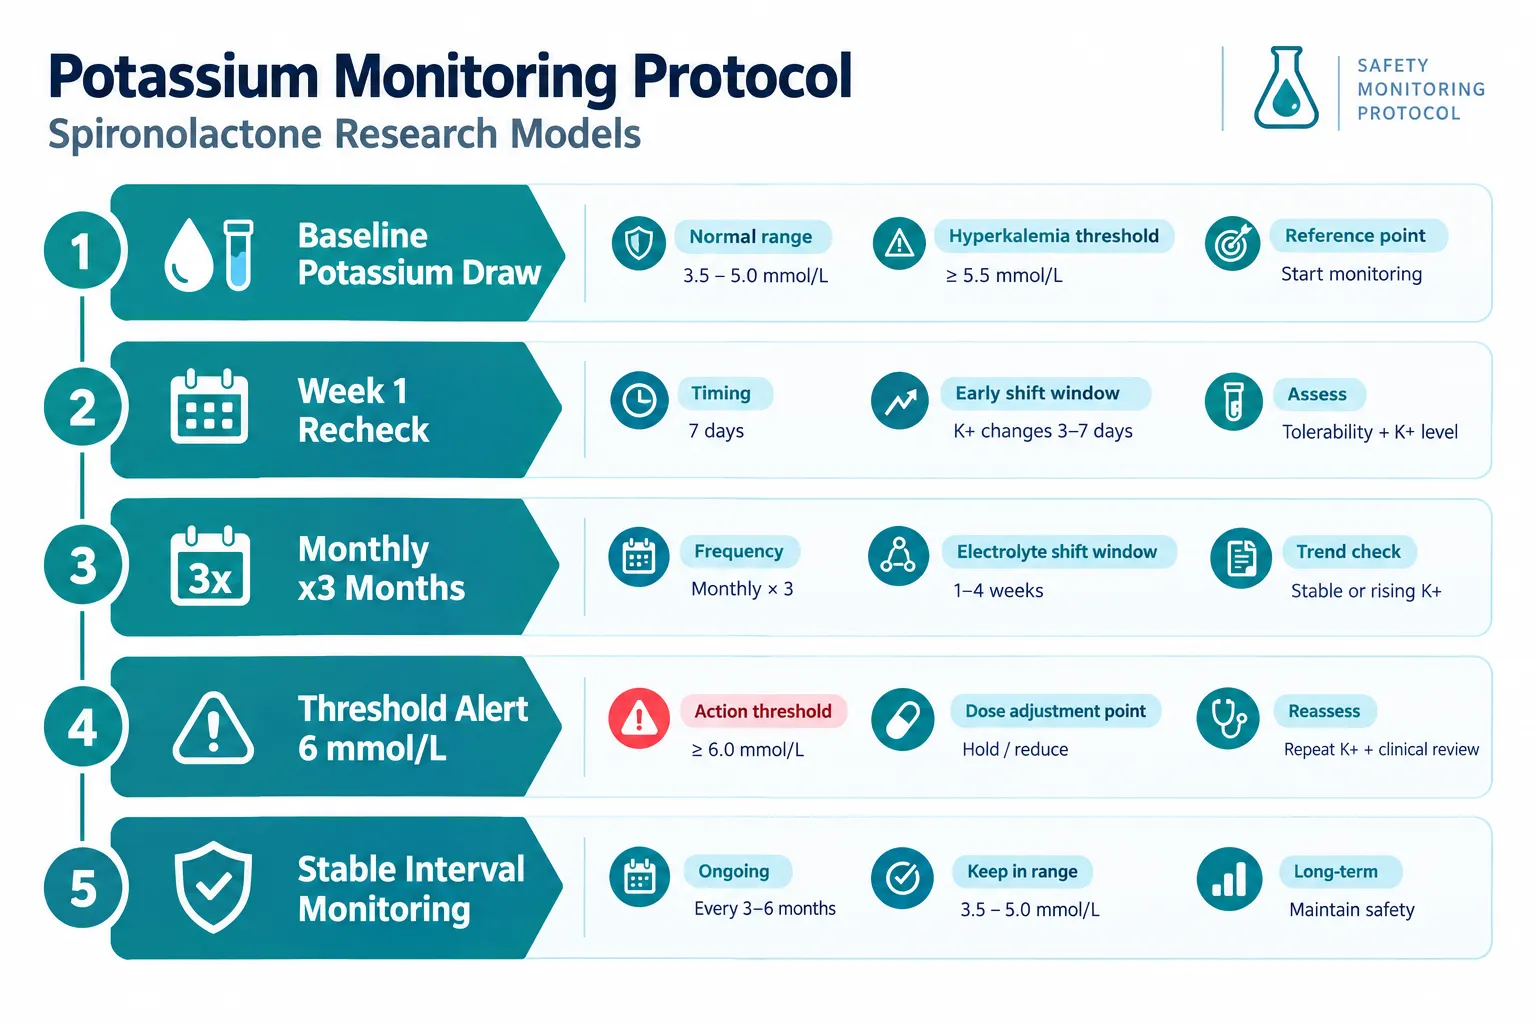
  • 2026 biomarker studies show spironolactone affects hormonal markers such as PICP, GAL9, THBS2, and REN, independent of classic electrolyte changes.
  • Interpreting hormonal readouts in peptide experiments requires distinguishing direct aldosterone-antagonist effects from broader RAAS-mediated signaling.

Mineralocorticoid Receptor Antagonism: The Mechanistic Foundation

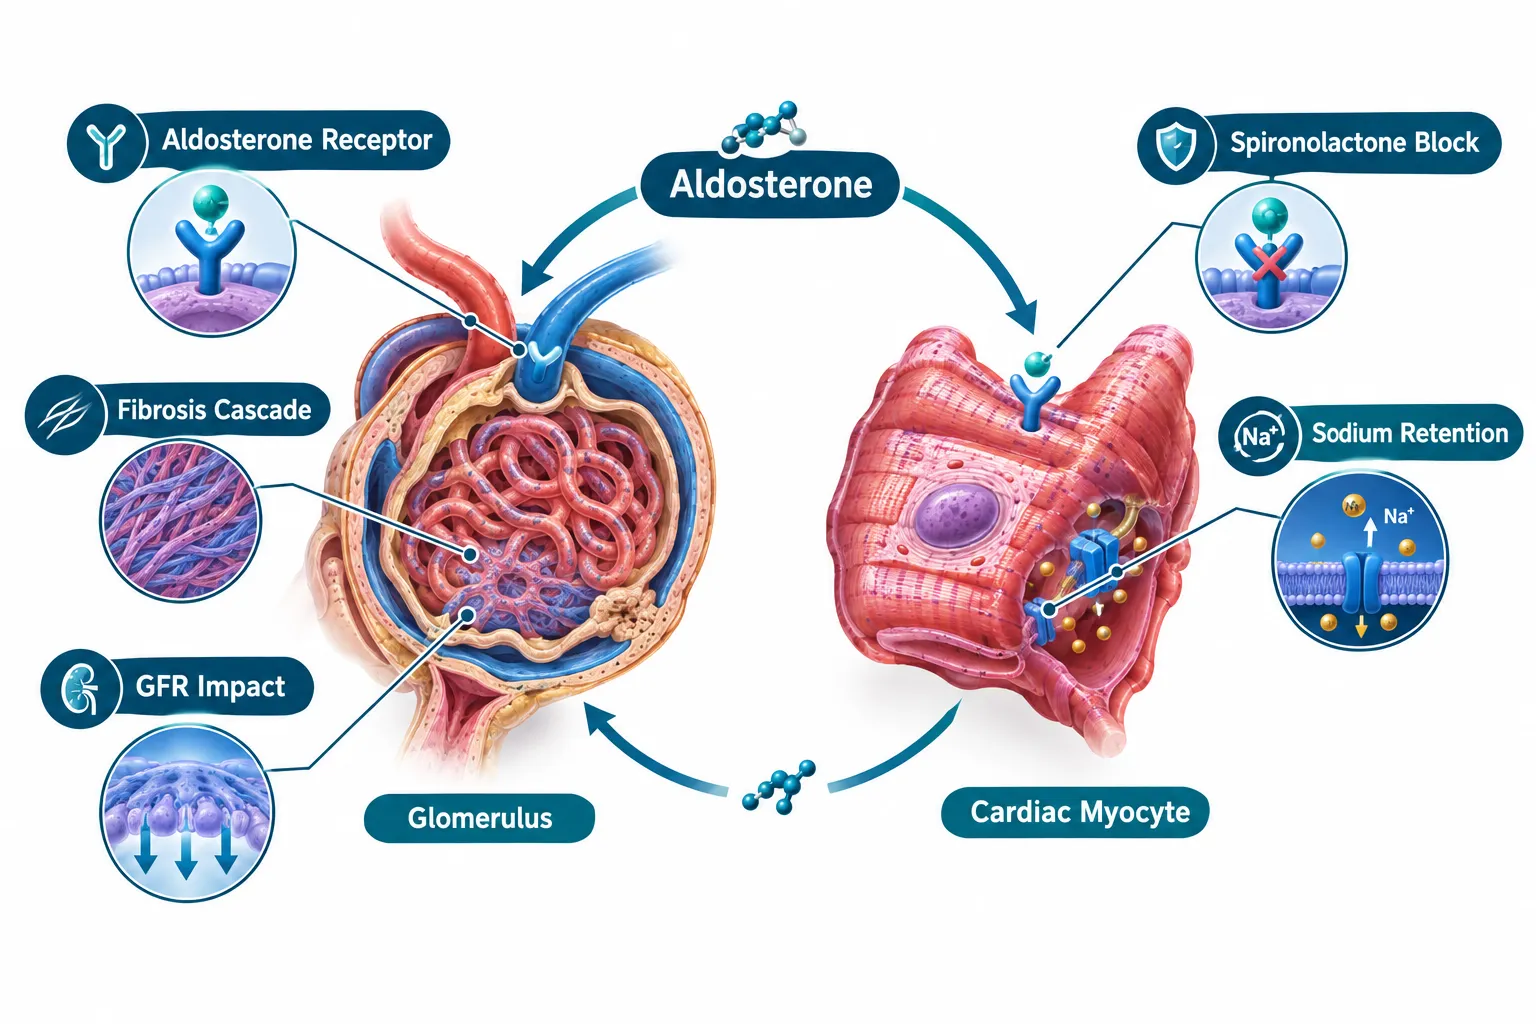
Spironolactone acts as a specific antagonist of aldosterone at the aldosterone-dependent sodium-potassium exchange site in the distal renal tubule. When aldosterone is blocked, the tubule excretes more sodium and water while retaining potassium. This mechanism, unchanged in the most current U.S. product labeling as of August 2026, forms the backbone of every study design that incorporates this compound.
Mineralocorticoid Receptor Antagonism: The Mechanistic Foundation

For researchers working with peptide models, this baseline pharmacology matters for three reasons:

  • Fluid volume decreases predictably, which affects peptide distribution and concentration in biological fluids.
  • Potassium retention alters the electrochemical environment of cells, potentially influencing receptor-ligand interactions.
  • Aldosterone suppression disrupts the renin-angiotensin-aldosterone system (RAAS), creating secondary hormonal shifts that can confound peptide readouts.

Hyperaldosteronism, a state of excess aldosterone driving sodium retention and potassium wasting, remains one of the primary endocrine indications for spironolactone. In research models mimicking this condition, baseline aldosterone levels must be documented before interpreting any downstream peptide or hormonal data.

Researchers studying mitochondria-targeted compounds such as SS-31 peptide should note that cellular potassium gradients, altered by spironolactone's mechanism, can influence mitochondrial membrane potential measurements.


Potassium, Fluid Volume, and Electrolyte Readouts in Peptide Experiments

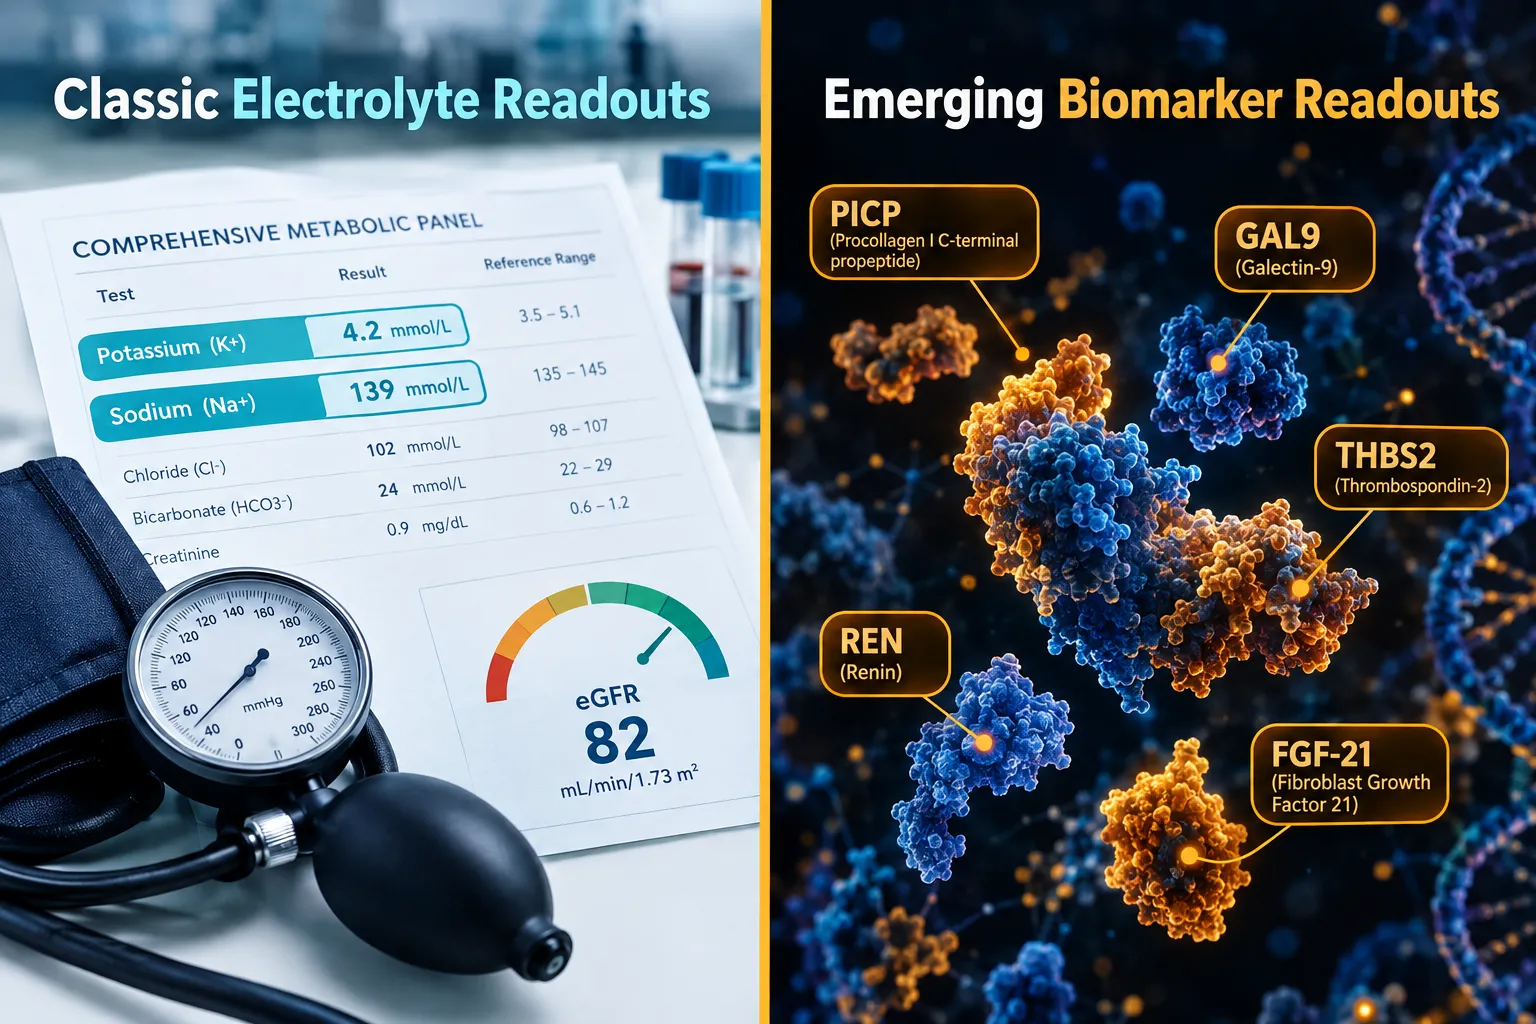
Because spironolactone is classified as a potassium-sparing diuretic, potassium monitoring is non-negotiable in any study protocol. Current NHS Specialist Pharmacy Service guidance updated in 2026 recommends potassium checks after one week of initiation, then monthly for three months, then at reduced frequency once values stabilize. A potassium level exceeding 6 mmol/L triggers a stop/seek-advice threshold, a figure that serves as a practical upper boundary in research safety monitoring as well.
Potassium, Fluid Volume, and Electrolyte Readouts in Peptide Experiments

Fluid volume changes are equally measurable and clinically meaningful. Spironolactone's natriuretic and diuretic effects reduce edema in heart failure, cirrhosis, and kidney disease models. In peptide metabolism studies, this volume reduction has direct consequences:

Parameter Expected Direction Research Implication
Serum sodium Decrease Affects peptide solubility and distribution
Serum potassium Increase Alters membrane electrochemistry
Body weight Decrease Reflects fluid loss, not tissue change
Blood pressure Decrease Confounds cardiovascular peptide endpoints

A 2026 NIH-hosted analysis in heart-failure-risk subjects found that after one month of spironolactone treatment, weight, serum sodium, and blood pressure all decreased, consistent with natriuresis and diuresis. These variables must be controlled or co-reported when interpreting peptide concentration data.

For studies involving GLP-1 peptides or metabolic signaling agents, fluid volume shifts can directly alter the apparent pharmacokinetics of co-administered peptides, making careful baseline fluid assessment essential.


Hormonal Readouts Beyond Electrolytes: What 2026 Studies Reveal

The most significant methodological development in spironolactone and peptide metabolism studies: aldosterone, potassium, fluid volume, and hormonal readouts is the growing recognition that spironolactone's effects extend into proteomic and hormonal territory far beyond simple electrolyte management.
Hormonal Readouts Beyond Electrolytes: What 2026 Studies Reveal

A 2026 NIH-published analysis in heart-failure-risk patients found that spironolactone reduced serum procollagen Type I C-terminal propeptide (PICP), a marker of cardiac fibrosis. Critically, the analysis implicated mediators including GAL9, THBS2, and REN, none of which are classic electrolyte markers. Changes in blood pressure, sodium, potassium, or eGFR were not the strongest variables associated with PICP shifts. This means that some hormonal and biomarker readouts in peptide studies are only partly explained by the drug's diuretic mechanism.

"Hormonal readouts in spironolactone-treated models reflect RAAS modulation at multiple levels, not just the aldosterone-potassium axis."

Separately, a 2026 veterinary proteomic study using combined angiotensin and spironolactone treatment reported changes in FGF-21, a metabolic signaling protein, pointing to downstream metabolic readouts tied to RAAS modulation. Researchers using lab-tested peptides in RAAS-modulated models should account for these off-target hormonal signals when designing assay panels.

For studies incorporating GLP-3 peptide formulations or other metabolic peptides, the FGF-21 signal is particularly relevant because it intersects with energy metabolism pathways that spironolactone indirectly modulates through RAAS suppression.

Researchers should also consider the SS-31 peptide benefits in oxidative stress contexts, since potassium retention and altered mitochondrial membrane potential may interact with mitochondria-targeted peptide activity in co-treatment models.

Three practical rules for interpreting hormonal readouts:

  1. Always separate electrolyte-driven changes from RAAS-mediated proteomic changes in your analysis plan.
  2. Include PICP, GAL9, or REN measurements if cardiac or fibrotic endpoints are relevant to your peptide model.
  3. Report fluid volume and weight changes alongside hormonal data to allow readers to distinguish diuretic from endocrine effects.

Conclusion

Designing rigorous spironolactone and peptide metabolism studies: aldosterone, potassium, fluid volume, and hormonal readouts requires more than tracking potassium levels. The 2026 research landscape makes clear that spironolactone modulates a layered hormonal environment, one where PICP, GAL9, THBS2, REN, and FGF-21 can shift independently of classic electrolyte markers.

Actionable next steps for researchers:

  • Establish potassium and sodium baselines before any spironolactone co-treatment protocol.
  • Apply the 6 mmol/L potassium threshold as a safety ceiling in preclinical models where applicable.
  • Expand hormonal assay panels beyond electrolytes to include RAAS-related biomarkers.
  • Control for fluid volume and weight changes when reporting peptide pharmacokinetic data.
  • Review the latest SS-31 10mg research peptide considerations when designing mitochondria-targeted co-treatment studies with mineralocorticoid antagonists.

Understanding the full scope of spironolactone's hormonal footprint is no longer optional for peptide researchers, it is a prerequisite for producing interpretable, reproducible results.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/spironolactone-and-peptide-metabolism-studies-aldosterone-potassium-fluid-volume.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-13 13:03:522026-10-13 13:03:52Spironolactone and Peptide Metabolism Studies: Aldosterone, Potassium, Fluid Volume, and Hormonal Readouts
Spironolactone and Peptide Research: Interpreting Potassium, Renal, Hormonal, and Fluid-Balance Variables

Spironolactone and Peptide Research: Interpreting Potassium, Renal, Hormonal, and Fluid-Balance Variables

October 7, 2026/0 Comments/in Uncategorized/by

Aldosterone blockade does not simply pull water out of the body, it reshapes the entire hormonal landscape that peptide researchers depend on for clean endpoint interpretation. Understanding Spironolactone and Peptide Research: Interpreting Potassium, Renal, Hormonal, and Fluid-Balance Variables is therefore essential for anyone designing or analyzing studies where mineralocorticoid receptor (MR) antagonism intersects with natriuretic peptides, renal biomarkers, and fluid status. As of 2026, updated pharmacovigilance datasets confirm that hyperkalaemia and renal function shifts remain the most clinically significant safety signals with spironolactone, yet the drug's disease-modifying effects on hormonal and peptide endpoints make it indispensable in cardiovascular and renal research.

Key Takeaways

  • Spironolactone blocks aldosterone at the mineralocorticoid receptor, causing predictable potassium retention and modest sodium excretion that must be tracked as confounders in peptide studies.
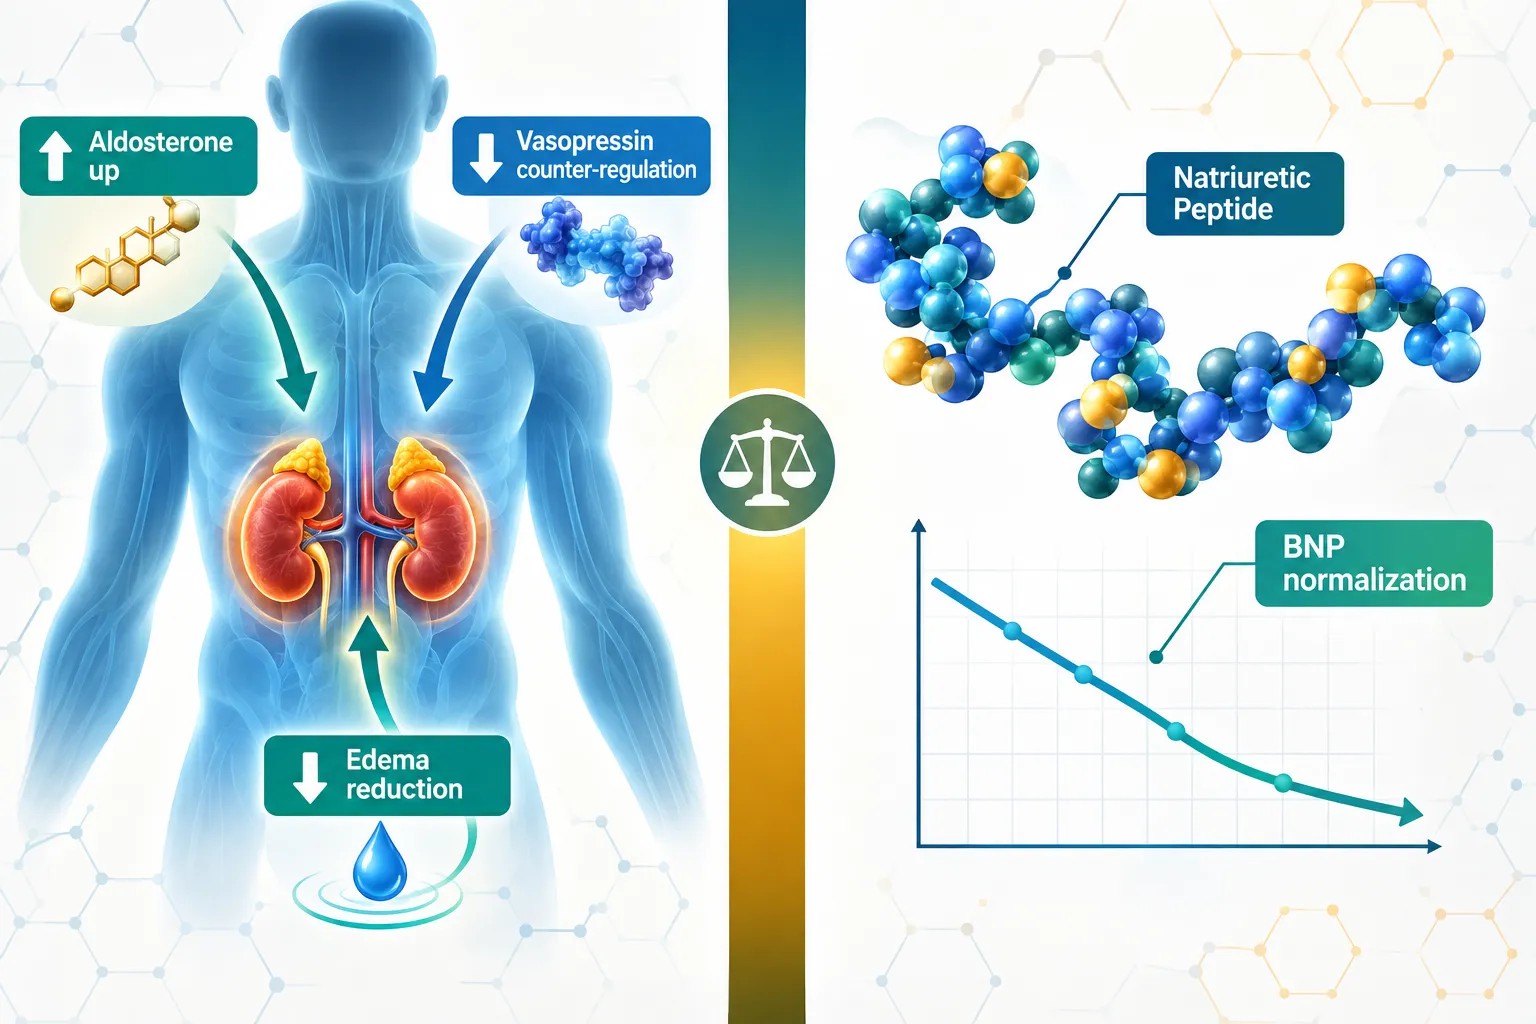
  • Natriuretic peptide levels, including BNP and NT-proBNP, fall with spironolactone use even as RAAS feedback drives aldosterone and angiotensin II upward.
  • Creatinine and eGFR shifts are small but consistent; monitoring thresholds in 2026 guidance remain strict, especially in CKD stages 3b, 5.
  • Fluid-balance and volume metrics improve alongside natriuretic peptide normalization in resistant hypertension cohorts.
  • Accurate interpretation of peptide research data requires separating spironolactone's direct MR-antagonist effects from secondary hormonal feedback loops.

How Mineralocorticoid Receptor Antagonism Shapes Peptide Research Variables

How Mineralocorticoid Receptor Antagonism Shapes Peptide Research Variables

Spironolactone competitively binds the mineralocorticoid receptor in the distal nephron, blocking aldosterone's instruction to retain sodium and excrete potassium. The downstream consequences are not limited to electrolytes. When aldosterone signaling is suppressed at the receptor level, the body compensates through RAAS feedback, aldosterone and angiotensin II levels rise in plasma even as their end-organ effects are blunted. This dual signal creates a confounding environment for any peptide assay that uses aldosterone or angiotensin-related markers as primary endpoints.

Three core variables shift predictably with spironolactone:

Variable Direction of Change Research Implication
Serum potassium Increases Risk of hyperkalaemia; confounds cardiac peptide safety data
Serum creatinine Modest increase Apparent renal function decline; not always true GFR loss
Natriuretic peptides (BNP/NT-proBNP) Decreases Reflects reduced cardiac wall stress, not peptide catabolism

For researchers working with SS-31 peptide or other mitochondria-targeted compounds that influence renal tubular function, spironolactone's effect on tubular sodium transport is a critical baseline variable. Any study failing to account for concurrent MR antagonism risks misattributing renal transporter changes to the investigational peptide.

"Spironolactone is disease-modifying beyond simple diuresis, but potassium and renal markers remain the critical guardrails for peptide-driven research.", 2026 expert consensus


Potassium and Renal Thresholds: The Non-Negotiable Guardrails

Potassium and Renal Thresholds: The Non-Negotiable Guardrails

Current 2026 clinical guidance maintains strict thresholds for spironolactone initiation and continuation. Serum potassium above 5.0 mEq/L typically triggers dose reduction or discontinuation, and eGFR below 30 mL/min/1.73m² generally contraindicates use in standard clinical settings. However, emerging 2025 data from advanced CKD cohorts (stages 3b, 5) show that low-dose spironolactone combined with ACE inhibitor or ARB therapy can deliver cardiovascular benefit without excess hyperkalaemia or accelerated renal failure when monitoring is rigorous.

For peptide researchers, these thresholds matter because:

  • Potassium elevation can independently alter cardiac electrophysiology, confounding any peptide study with cardiac safety endpoints.
  • Creatinine rise within the first 2-4 weeks of spironolactone use reflects haemodynamic adjustment, not structural nephron loss, a distinction critical when interpreting renal peptide biomarkers.
  • eGFR staging determines which renal transporter pathways are active, directly affecting the pharmacokinetics of co-administered peptides.

Researchers exploring peptide dosing protocols alongside mineralocorticoid antagonists must pre-specify potassium and creatinine monitoring windows. Multi-year heart failure cohort data confirm that renal and electrolyte shifts with spironolactone are small but consistent, meaning cumulative drift can cross safety thresholds over extended study periods.

Recommended monitoring intervals in research settings:

  1. Baseline potassium and creatinine before spironolactone introduction
  2. Repeat at 1 week and 4 weeks post-initiation
  3. Every 3 months during stable dosing phases
  4. Immediately after any dose change or addition of RAAS-active co-therapy

Hormonal and Fluid-Balance Endpoints in Spironolactone and Peptide Research

Hormonal and Fluid-Balance Endpoints in Spironolactone and Peptide Research

The hormonal picture in Spironolactone and Peptide Research: Interpreting Potassium, Renal, Hormonal, and Fluid-Balance Variables is layered. Aldosterone and vasopressin are the primary counter-regulators of water and sodium balance, and both respond to MR antagonism in ways that directly affect peptide endpoint interpretation.

Natriuretic peptide dynamics are particularly instructive. Spironolactone lowers BNP and NT-proBNP levels in heart failure and resistant hypertension cohorts, reflecting reduced ventricular wall stress as volume overload resolves. This reduction is not caused by peptide degradation or receptor downregulation, it is a genuine haemodynamic improvement. Researchers studying GLP-3 peptide compounds or other metabolic peptides that influence fluid retention must therefore distinguish spironolactone-driven natriuretic peptide changes from those attributable to the investigational agent.

Vasopressin remains an underappreciated variable. As spironolactone reduces volume overload, vasopressin secretion adjusts, altering free water clearance. Studies on peptides with antidiuretic properties, including vasoactive intestinal peptide analogs such as those found in VIP-5 peptide research, need to account for this vasopressin modulation as a confounder.

In primary aldosteronism, meta-analyses position spironolactone as first-line medical therapy, with potassium outcomes comparable to newer selective MRAs. This makes it a relevant background medication in any hormonal peptide study where aldosterone excess is a design variable. Researchers examining peptides and polypeptides in endocrine pharmacology will recognize that RAAS-peptide crosstalk extends well beyond simple sodium balance.

Ongoing trials in 2026 are titrating spironolactone to renin and blood pressure responses in low-renin hypertension, with integrated hormonal endpoints that include natriuretic peptides, aldosterone-to-renin ratios, and plasma angiotensin II. These trials provide a methodological template for any peptide study that incorporates MR antagonism as a background or co-intervention variable.

For researchers also examining mitochondrial or cytoprotective peptides, the SS-31 peptide benefits literature offers a useful parallel: renal tubular protection endpoints in that body of work face similar confounding from background diuretic and RAAS-active therapies.


Conclusion

Spironolactone and Peptide Research: Interpreting Potassium, Renal, Hormonal, and Fluid-Balance Variables demands a structured, mechanistically grounded approach. The drug's MR-antagonist action creates predictable shifts in potassium, creatinine, natriuretic peptides, aldosterone feedback, and vasopressin tone, each of which can masquerade as a peptide-specific effect if not properly controlled.

Actionable next steps for researchers:

  • Pre-specify potassium and eGFR thresholds as stopping rules in any protocol that includes spironolactone.
  • Separate haemodynamic natriuretic peptide changes from direct peptide-receptor effects using time-matched biomarker panels.
  • Account for RAAS feedback elevation (aldosterone, angiotensin II) when interpreting hormonal peptide endpoints.
  • Apply 2026 monitoring intervals, baseline, week 1, week 4, then quarterly, as the minimum standard for renal and electrolyte safety.
  • Cross-reference fluid-balance metrics with vasopressin and osmolality data to isolate volume effects from peptide-specific actions.

Rigorous variable interpretation is what separates publishable peptide research from ambiguous data. Spironolactone's hormonal reach is wide; accounting for it fully is the foundation of credible results.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/spironolactone-and-peptide-research-interpreting-potassium-renal-hormonal-and-fl.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-07 13:03:532026-10-07 13:03:53Spironolactone and Peptide Research: Interpreting Potassium, Renal, Hormonal, and Fluid-Balance Variables
Spironolactone, Cardiorenal Pathways, and Tissue-Repair Peptides: How BPC-157 and TB-500 Complement Classic Heart and Kidney Drug Models

Spironolactone, Cardiorenal Pathways, and Tissue-Repair Peptides: How BPC-157 and TB-500 Complement Classic Heart and Kidney Drug Models

September 13, 2026/0 Comments/in Uncategorized/by

Nearly 64 million people worldwide live with heart failure, and a large proportion of them carry simultaneous kidney dysfunction, a dual burden that no single drug has fully solved. The intersection of spironolactone, cardiorenal pathways, and tissue-repair peptides: how BPC-157 and TB-500 complement classic heart and kidney drug models is now a serious focus in advanced cardiometabolic research. Understanding where established mineralocorticoid receptor antagonists (MRAs) succeed, where they fall short, and how regenerative peptides might fill mechanistic gaps is increasingly relevant for researchers and clinicians alike.

Key Takeaways

  • Spironolactone blocks aldosterone receptors to reduce fibrosis and fluid retention, but large trials in specific populations, including dialysis patients, show limits to its cardiovascular benefit.
  • Newer non-steroidal MRAs like finerenone demonstrate stronger cardiorenal outcome data, signaling that the MRA class is still evolving.
  • BPC-157 and TB-500 operate through vascular and tissue-repair pathways that are mechanistically distinct from neurohormonal blockade.
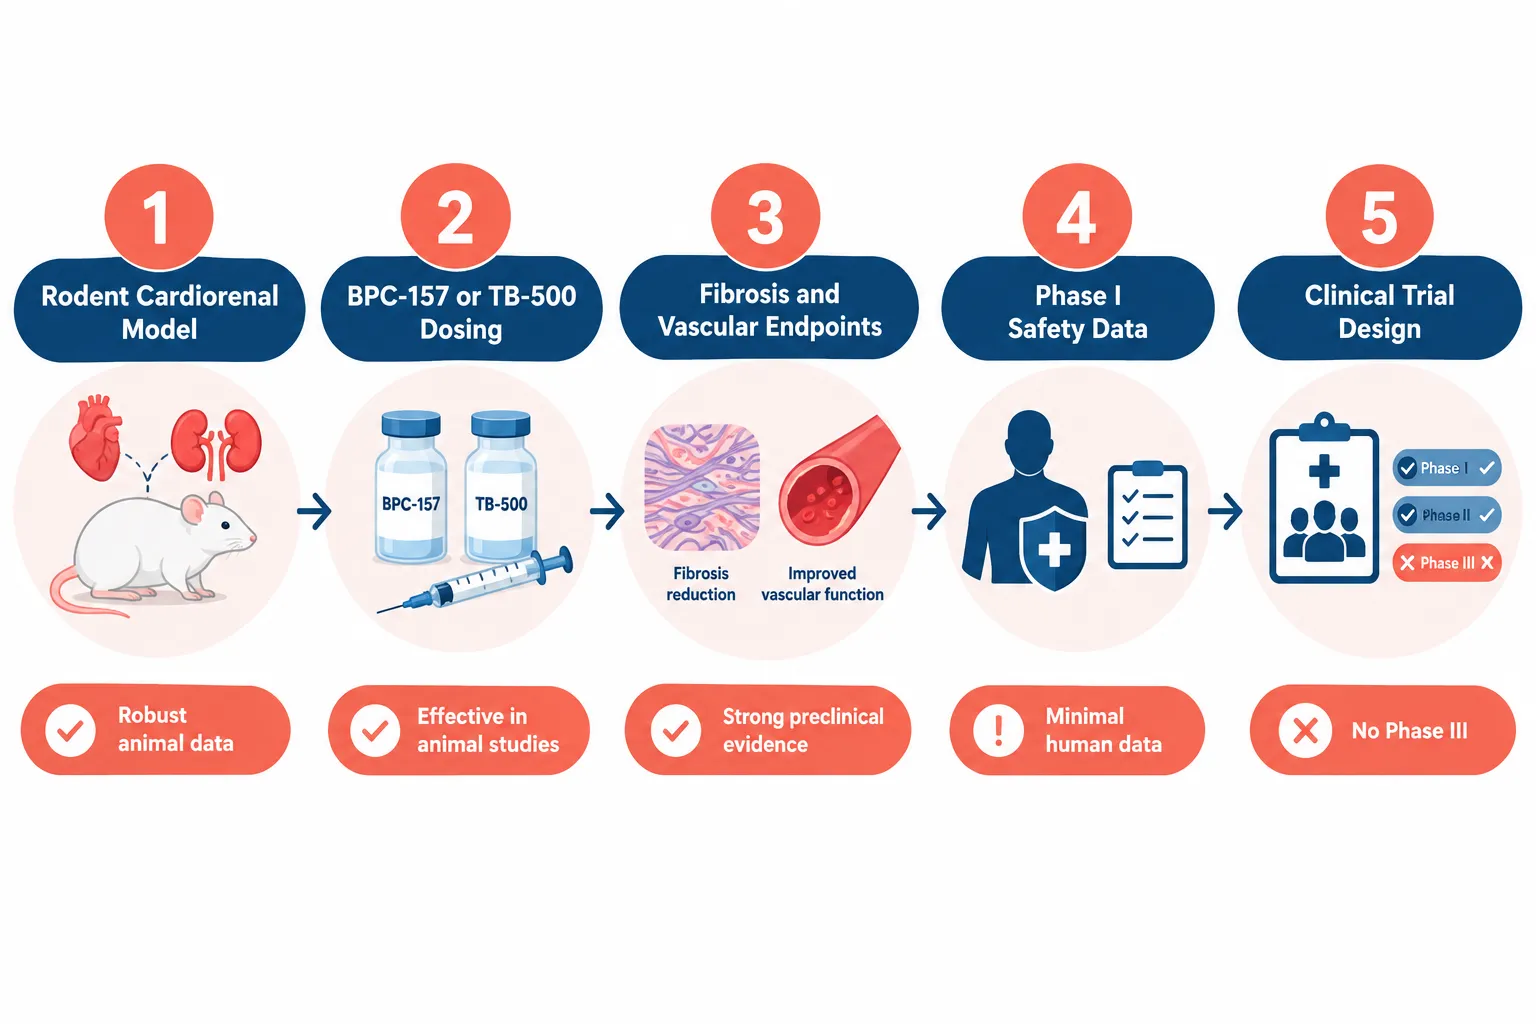
  • Both peptides have compelling animal-model data for cardiac and vascular endpoints, but human clinical evidence remains early and limited.
  • Combining neurohormonal drugs with tissue-repair peptides is a conceptual frontier, not yet a validated clinical strategy.

How Spironolactone Shapes Cardiorenal Pathways

How Spironolactone Shapes Cardiorenal Pathways

Spironolactone has been a cornerstone of heart failure therapy for decades. It works by blocking aldosterone receptors in the kidney, heart, and vasculature, reducing sodium retention, lowering blood pressure, and most importantly, suppressing the fibrotic signaling that aldosterone drives in cardiac and renal tissue.

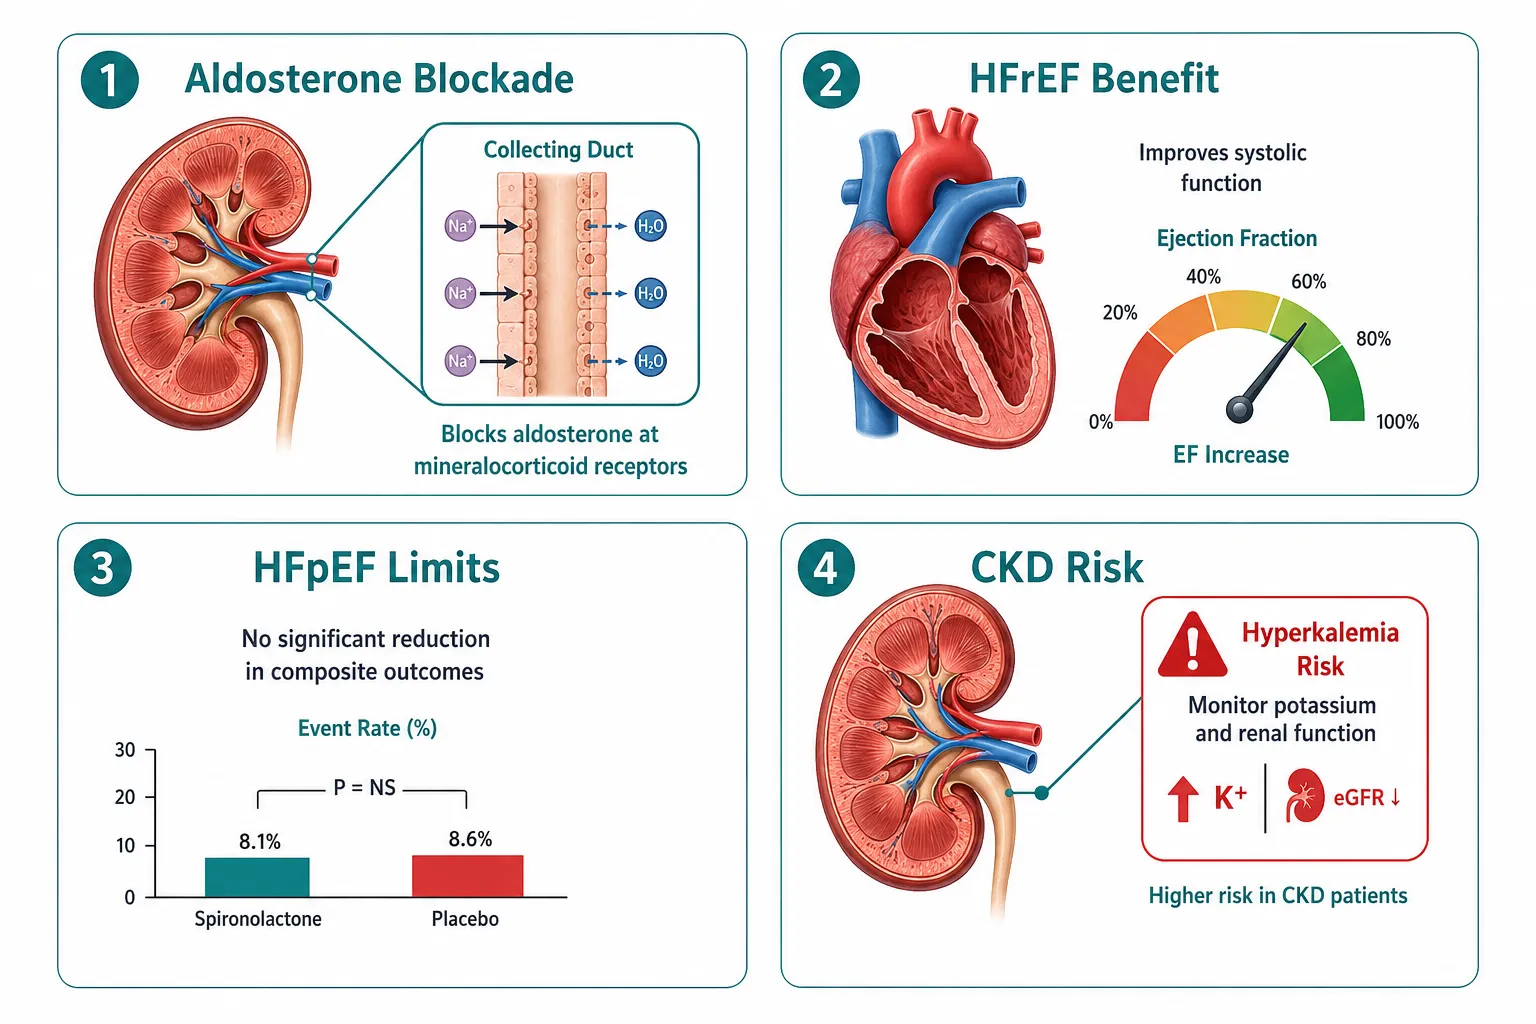
The fibrosis connection is critical. Aldosterone excess promotes collagen deposition in the myocardium and glomeruli. By blocking this pathway, spironolactone reduces myocardial stiffness and slows the structural decline that characterizes both heart failure with preserved ejection fraction (HFpEF) and chronic kidney disease (CKD).

However, clinical trial results have complicated the picture:

  • The SPIRIT-HF program, running from 2018 through 2024, produced neutral outcomes for spironolactone in HFpEF and heart failure with mildly reduced ejection fraction (HFmrEF).
  • A large trial in dialysis patients was stopped early for futility, spironolactone showed no cardiovascular benefit in that population.
  • The CLEAR SYNERGY post-MI trial found that spironolactone reduced new or worsening heart failure, but did not significantly reduce major cardiovascular events overall.

These results do not dismiss spironolactone, they clarify its boundaries. The pragmatic SPIRRIT-HFpEF registry continues to test MRAs in real-world HFpEF populations, acknowledging that patient selection matters enormously.

Finerenone, a third-generation non-steroidal MRA, has now produced robust cardiorenal outcome data across both heart failure and diabetic kidney disease populations. Its greater receptor selectivity reduces the side-effect burden of older steroidal MRAs while maintaining anti-fibrotic potency. The modern cardiorenal therapeutic core now integrates MRAs alongside SGLT2 inhibitors and incretin-based therapies, a multi-pathway approach that reflects how complex cardiorenal disease truly is.

"The cardiorenal axis is not a single switch, it is a network of overlapping signals, and blocking one node rarely resolves the whole system."

BPC-157 and TB-500: Tissue-Repair Mechanisms in Cardiorenal Research

BPC-157 and TB-500: Tissue-Repair Mechanisms in Cardiorenal Research

This is where the conversation about spironolactone, cardiorenal pathways, and tissue-repair peptides, and how BPC-157 and TB-500 complement classic heart and kidney drug models, becomes genuinely novel. These two peptides work through entirely different biological levers than MRAs.

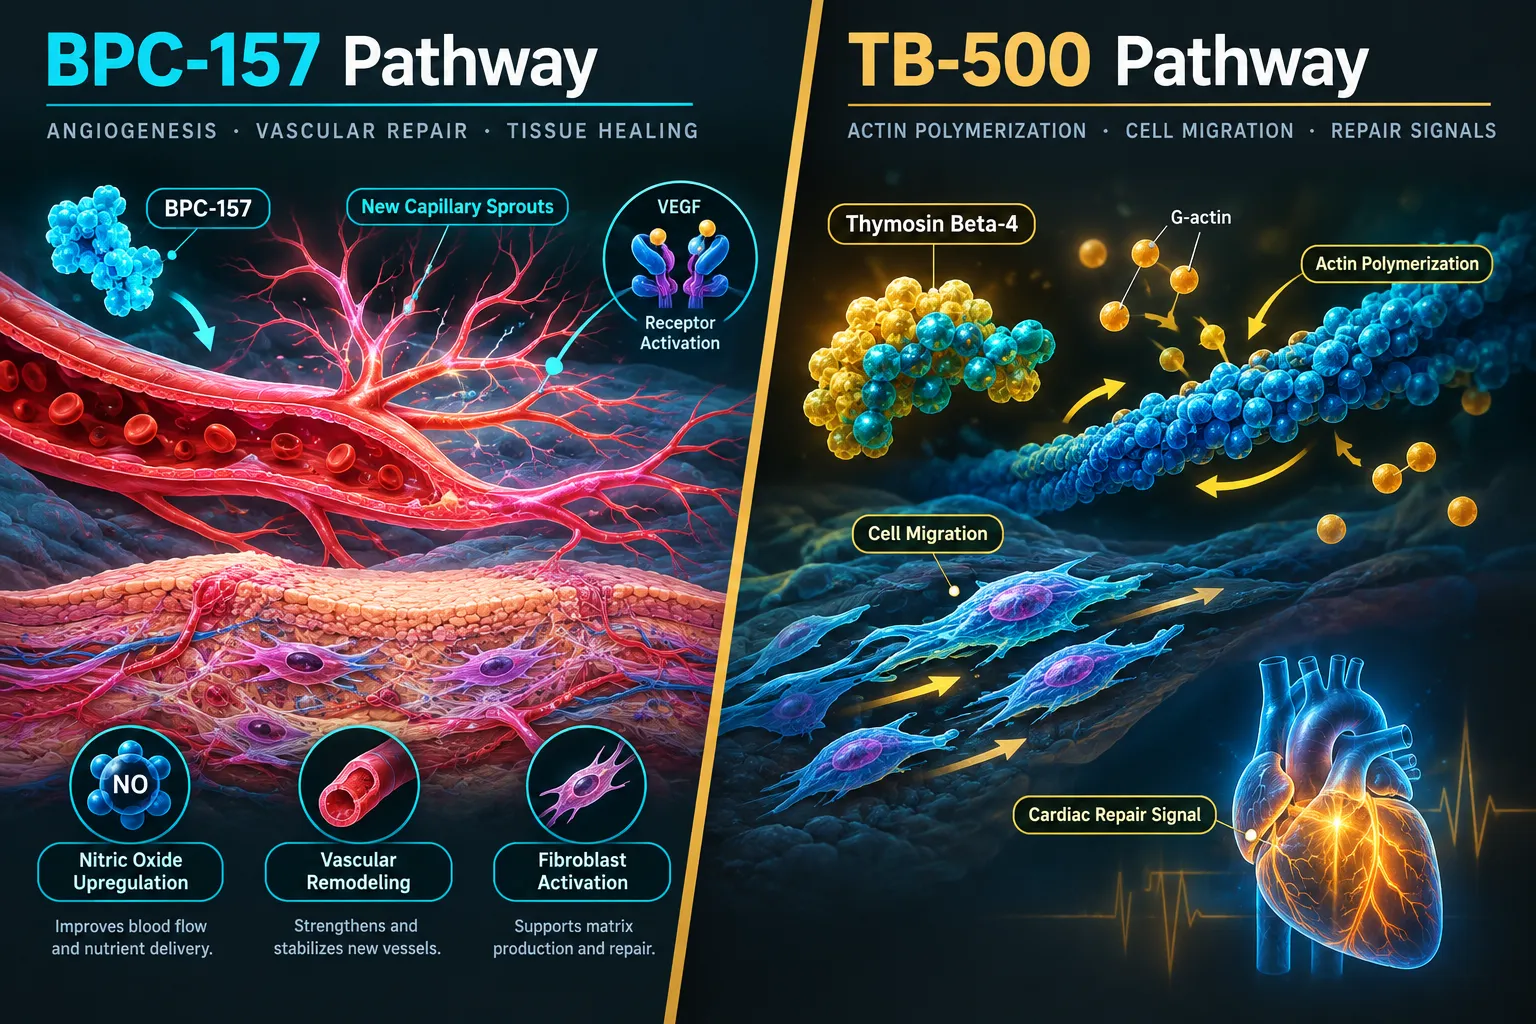
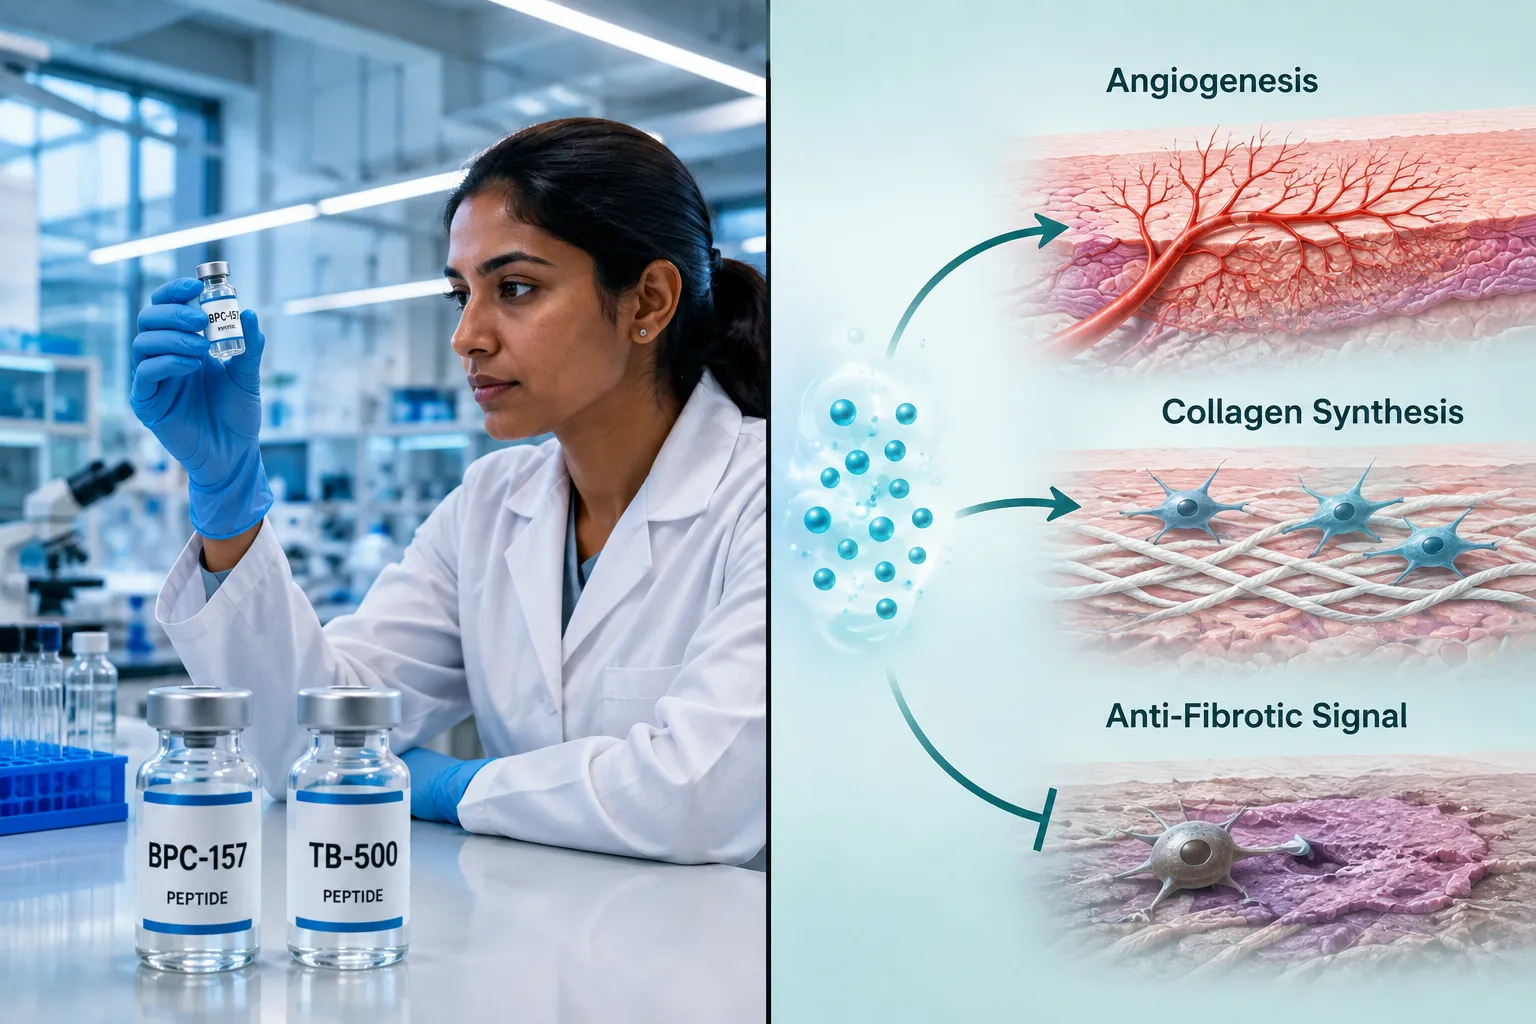
BPC-157 (Body Protection Compound-157) is a synthetic pentadecapeptide derived from a gastric protein. In animal models, it has demonstrated:

  • Upregulation of nitric oxide synthase, improving vascular tone
  • Promotion of angiogenesis through VEGF receptor pathways
  • Reduction of fibrotic markers in cardiac and renal tissue
  • Accelerated healing in wound models relevant to ischemic injury

TB-500 (synthetic thymosin beta-4) targets actin polymerization and cell migration. In small animal cardiac studies, it has shown potential to:

  • Stimulate cardiac progenitor cell activation after ischemic injury
  • Reduce scar formation in post-MI myocardium
  • Support endothelial repair and vascular remodeling

These are properties that MRAs simply do not possess. Spironolactone blocks a hormonal signal; BPC-157 and TB-500 actively promote structural repair. Researchers exploring wound healing peptides in vascular contexts recognize this distinction as foundational.

The critical caveat: almost all of this evidence comes from rodent and small-animal models. Current human trials for BPC-157 focus on musculoskeletal repair, not cardiorenal indications. TB-500 has small human studies with mixed signals and no Phase III data. Neither peptide is approved by any regulatory agency; BPC-157 is classified as a Category 2 bulk substance in several jurisdictions.

For researchers sourcing compounds for preclinical work, working with a best peptide manufacturer that provides verified purity documentation is essential for valid experimental outcomes.

Mechanistic Complementarity: Where the Two Models Meet

Mechanistic Complementarity: Where the Two Models Meet

The most intellectually productive framing of spironolactone, cardiorenal pathways, and tissue-repair peptides, and how BPC-157 and TB-500 complement classic heart and kidney drug models, is mechanistic layering, not replacement.

Mechanism Spironolactone / Finerenone BPC-157 TB-500
Aldosterone blockade Yes No No
Anti-fibrotic signaling Yes (indirect) Yes (direct, animal data) Partial (animal data)
Angiogenesis promotion No Yes (animal data) Yes (animal data)
Cardiac structural repair No Emerging Emerging
Human outcome data Robust Minimal Minimal

The table above illustrates why these are complementary, not competing, research targets. MRAs address the neurohormonal driver of cardiorenal damage. Tissue-repair peptides, if their animal-model promise translates to humans, could address the downstream structural consequences, the scarring, the vascular rarefaction, the impaired healing that persists even after hormonal blockade.

Researchers working with 5 amino peptide compounds and related short-chain structures are increasingly interested in how these molecules interact with established pharmacological frameworks. Similarly, interest in GHK-Cu peptide for vascular and tissue remodeling endpoints reflects a broader shift toward regenerative mechanisms in cardiometabolic research.

The integrated cardiorenal model, combining MRAs, SGLT2 inhibitors, and incretin therapies, already demonstrates that multi-pathway intervention outperforms single-target strategies. The logical next research question is whether tissue-repair peptides can add a structural-regeneration layer on top of that neurohormonal foundation.

Sourcing quality compounds from a verified best peptide supplier remains a prerequisite for any preclinical work attempting to answer that question rigorously.

Conclusion

The relationship between spironolactone, cardiorenal pathways, and tissue-repair peptides, and how BPC-157 and TB-500 complement classic heart and kidney drug models, represents one of the more promising conceptual frontiers in cardiometabolic research in 2026. Spironolactone and its successor finerenone have defined the neurohormonal anti-fibrotic standard, even as large trials have refined the populations most likely to benefit. BPC-157 and TB-500 offer a mechanistically distinct toolkit, vascular repair, angiogenesis, and structural healing, that animal models suggest could layer meaningfully onto established pharmacology.

Actionable next steps for researchers:

  1. Review the current SPIRRIT-HFpEF registry data to understand real-world MRA performance benchmarks.
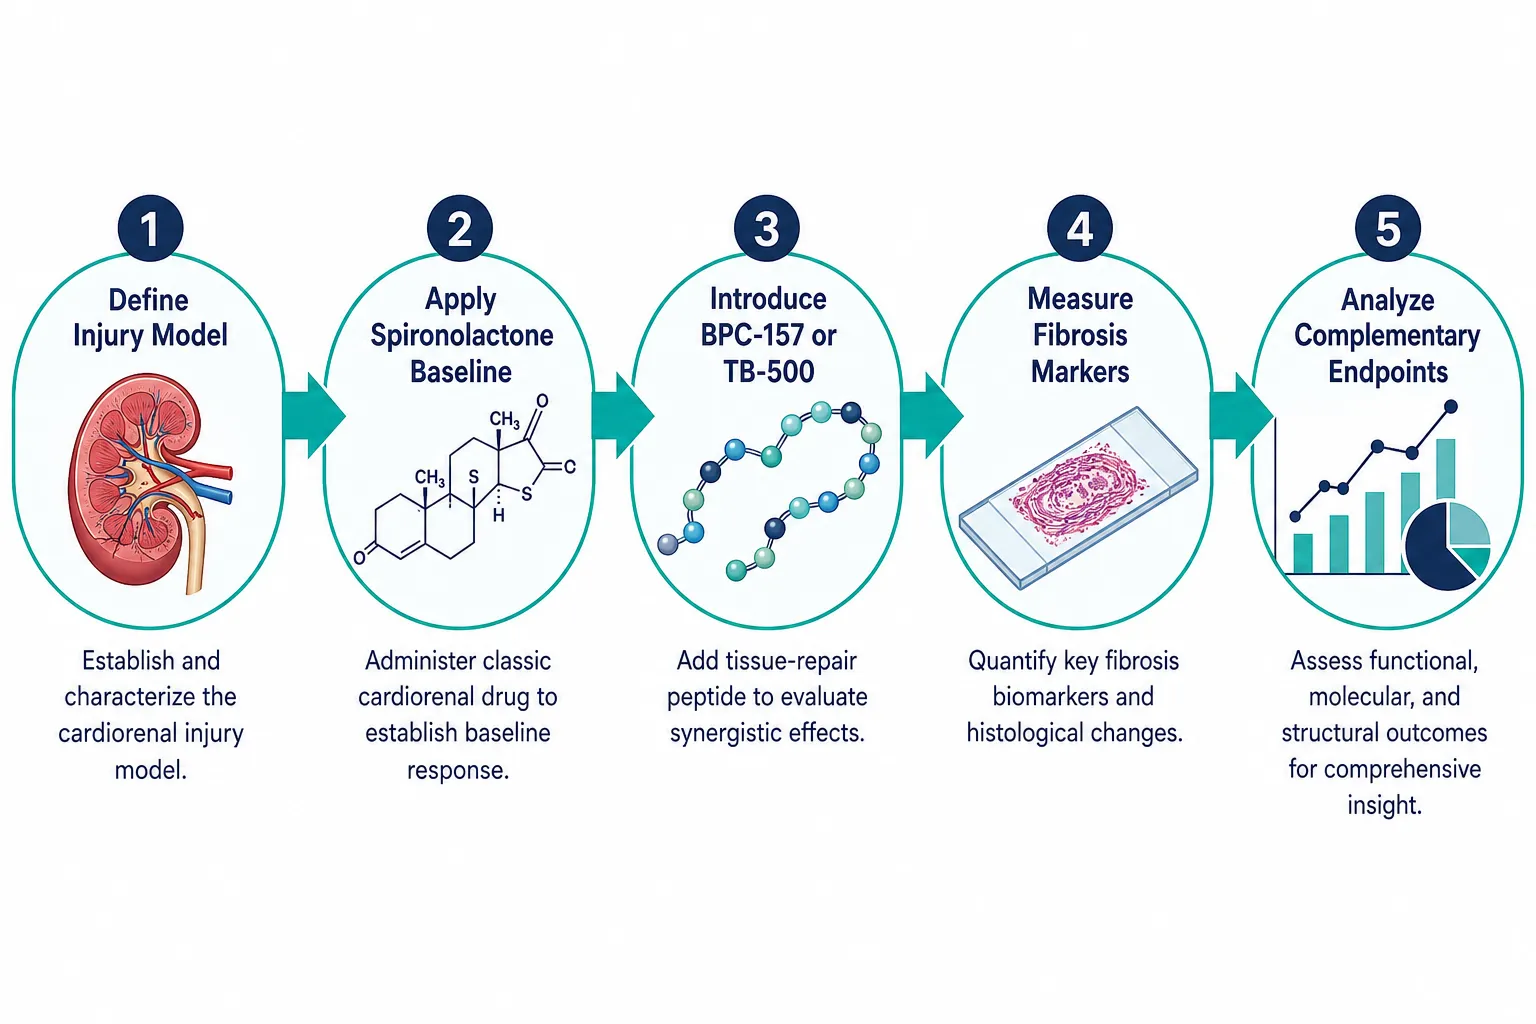
  2. Design preclinical cardiorenal studies that include both fibrosis endpoints (relevant to MRAs) and vascular repair endpoints (relevant to BPC-157 and TB-500).
  3. Demand purity-verified peptide compounds for any experimental work to ensure data validity.
  4. Monitor emerging Phase I human data on BPC-157 musculoskeletal trials, the safety signals from those studies will inform whether cardiorenal indications are feasible.
  5. Consider finerenone's non-steroidal MRA profile as the appropriate comparator benchmark when designing combination studies.

The gap between animal-model promise and clinical validation remains wide. Closing it requires rigorous, well-sourced research, and a clear understanding of what each drug class can and cannot do.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/spironolactone-cardiorenal-pathways-and-tissue-repair-peptides-how-bpc-157-and-t.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-13 13:04:082026-09-13 13:04:08Spironolactone, Cardiorenal Pathways, and Tissue-Repair Peptides: How BPC-157 and TB-500 Complement Classic Heart and Kidney Drug Models
Spironolactone vs Research-Use Peptides: How Tissue-Repair Peptides Like BPC-157 and TB-500 Complement Classic Cardiorenal Drugs

Spironolactone vs Research-Use Peptides: How Tissue-Repair Peptides Like BPC-157 and TB-500 Complement Classic Cardiorenal Drugs

September 5, 2026/0 Comments/in Uncategorized/by

Roughly 64 million people worldwide live with heart failure, yet the drugs anchoring most treatment protocols were developed decades ago. That gap between established pharmacology and emerging regenerative science is exactly where the conversation around Spironolactone vs Research-Use Peptides: How Tissue-Repair Peptides Like BPC-157 and TB-500 Complement Classic Cardiorenal Drugs becomes most relevant for researchers and clinicians trying to understand what each tool does, and what it cannot.

Key Takeaways

  • Spironolactone is a well-validated aldosterone antagonist with proven mortality benefits in heart failure with reduced ejection fraction (HFrEF), but its utility in HFpEF and chronic kidney disease is narrower than once assumed.
  • The SPIRIT-HF trial (2026) confirmed spironolactone does not significantly reduce cardiovascular death or HF hospitalization in HFpEF or mildly reduced ejection fraction populations.
  • Research-use peptides BPC-157 and TB-500 operate through distinct tissue-repair and angiogenic pathways that do not overlap with aldosterone blockade.
  • In preclinical frameworks, these peptides are studied as complementary agents rather than replacements for classic cardiorenal drugs.
  • Rigorous translational research design is essential before any conclusions about combined protocols can be drawn.

How Spironolactone Works in Cardiorenal Disease

Spironolactone is a potassium-sparing diuretic and aldosterone receptor antagonist with a long clinical track record. It is FDA-approved for HFrEF, resistant hypertension, primary hyperaldosteronism, cirrhotic edema, nephrotic-syndrome edema, and hypokalemia. In patients with NYHA class II, IV HFrEF, guidelines recommend its use when renal function and potassium levels are adequately controlled.

The landmark RALES trial established that spironolactone reduced all-cause mortality by approximately 30% and heart-failure hospitalization by roughly 35% in chronic HFrEF with ejection fraction below 35%. Real-world data in older populations have reinforced these findings, showing an 8-13% lower risk of mortality and HF readmission when eligibility criteria are respected.

How Spironolactone Works in Cardiorenal Disease

However, 2026 data have sharpened the boundaries of that benefit. The SPIRIT-HF trial, presented at ACC.26 in March 2026, found that spironolactone did not significantly reduce the composite of HF hospitalization and cardiovascular death over 24 months in patients with heart failure with preserved or mildly reduced ejection fraction (HFpEF/HFmrEF). Event rates were 10.8 versus 12.7 per 100 patient-years for placebo versus spironolactone, a difference that did not reach significance. Secondary analyses also showed higher rates of total hospitalizations, hypotension, renal events, and hyperkalemia in the spironolactone group.

Earlier HFpEF work had similarly concluded that spironolactone may improve diastolic function and left ventricular remodeling without clearly reducing all-cause or cardiovascular mortality, positioning it as a selective rather than universal therapy.

In chronic kidney disease (CKD), the picture is equally nuanced. Hospital-based cohort data show spironolactone use associated with increased all-cause mortality and severe hyperkalemia, yet reduced major adverse cardiovascular events, driven largely by lower stroke risk. In advanced CKD combined with HFpEF, very close laboratory surveillance is mandatory given the elevated risks of hyperkalemia and worsening renal function. Studies in advanced heart failure do suggest that higher spironolactone doses can be generally safe when patients are already on ACE inhibitors, beta-blockers, and loop diuretics, provided careful outpatient monitoring is in place.

Key insight: Spironolactone's power lies in aldosterone blockade and fluid regulation, it does not directly promote tissue regeneration, angiogenesis, or extracellular matrix repair.

Understanding Research-Use Peptides: BPC-157 and TB-500

The term "research-use peptides" refers to compounds studied exclusively in preclinical and laboratory settings, not approved for human therapeutic use. BPC-157 (Body Protection Compound-157) and TB-500 (a synthetic analog of Thymosin Beta-4) are two of the most studied examples in tissue repair research.

BPC-157 is a 15-amino-acid peptide derived from a gastric protein. In animal models, it has been studied for its effects on:

  • Accelerating tendon and ligament healing
  • Promoting angiogenesis via upregulation of VEGFR2
  • Modulating nitric oxide pathways
  • Reducing fibrotic tissue formation

TB-500 is associated with actin-binding activity and has been investigated for its role in cell migration, wound healing, and anti-inflammatory signaling. Research into tissue repair pathways suggests TB-500 may support cardiac muscle recovery in ischemia models by reducing apoptosis and promoting endothelial repair.

Understanding Research-Use Peptides: BPC-157 and TB-500

Both peptides act through mechanisms entirely distinct from aldosterone blockade. Where spironolactone controls fluid retention and electrolyte balance, BPC-157 and TB-500 target the cellular machinery of repair, collagen synthesis, angiogenesis, and inflammatory resolution. This distinction is what makes them conceptually complementary in research frameworks rather than interchangeable.

For researchers interested in broader regenerative applications, systemic peptide research and tissue remodeling resources provide additional context on how these compounds are being modeled across organ systems.

Spironolactone vs Research-Use Peptides: Designing Complementary Research Frameworks

When researchers frame the question of Spironolactone vs Research-Use Peptides: How Tissue-Repair Peptides Like BPC-157 and TB-500 Complement Classic Cardiorenal Drugs, the most productive framing is not competition but layered inquiry. Each class of compound addresses a different biological problem.

Feature Spironolactone BPC-157 / TB-500
Primary mechanism Aldosterone receptor antagonism Angiogenesis, actin binding, tissue repair
Regulatory status FDA-approved (multiple indications) Research use only (preclinical)
Target tissue Kidney, heart, vasculature Musculoskeletal, cardiac, GI, vascular
Key risk Hyperkalemia, renal impairment Limited long-term safety data
Research gap addressed Fluid overload, aldosterone excess Structural repair, regeneration

In well-designed preclinical models, a spironolactone baseline can control the hemodynamic and electrolyte environment while peptide interventions are assessed for their structural repair effects. This layered approach aligns with principles outlined in translational research design, where controlling one variable allows cleaner measurement of another.

Spironolactone vs Research-Use Peptides: Designing Complementary Research Frameworks

It is also worth noting that mitochondrial health is an emerging endpoint in cardiorenal research. Resources like SS-31 mitochondrial research themes illustrate how peptide science is expanding into energy metabolism, another domain where classic diuretics have no direct action.

Three principles for sound comparative research design:

  1. Establish baseline pharmacology, document spironolactone's hemodynamic effects before introducing peptide variables.
  2. Use orthogonal endpoints, measure fibrosis markers, angiogenic density, and electrolyte panels separately to avoid conflating mechanisms.
  3. Account for CKD status, renal function alters both spironolactone metabolism and peptide clearance, making it a critical covariate.

Conclusion

The debate framed as Spironolactone vs Research-Use Peptides: How Tissue-Repair Peptides Like BPC-157 and TB-500 Complement Classic Cardiorenal Drugs is ultimately a false competition. Spironolactone remains a cornerstone of HFrEF management with strong mortality data, but 2026 evidence from SPIRIT-HF confirms its limits in HFpEF and CKD populations. Research-use peptides like BPC-157 and TB-500 operate through entirely different biological pathways, targeting structural repair rather than fluid regulation, which makes them conceptually additive in laboratory frameworks.

Actionable next steps for researchers:

  • Review current SPIRIT-HF data to understand the precise HFpEF population where spironolactone adds limited benefit.
  • Explore tissue repair research literature to identify validated preclinical endpoints for BPC-157 and TB-500.
  • Design studies with orthogonal outcome measures so that cardiorenal drug effects and peptide-mediated repair signals can be distinguished cleanly.
  • Monitor electrolyte and renal function parameters rigorously in any model combining aldosterone antagonism with systemic peptide administration.
  • Consult translational research design frameworks before scaling from animal models to more complex study protocols.

The future of cardiorenal research likely lies not in choosing between classic drugs and regenerative peptides, but in understanding precisely where each one's mechanism begins and ends.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/spironolactone-vs-research-use-peptides-how-tissue-repair-peptides-like-bpc-157.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-05 13:05:552026-09-05 13:05:55Spironolactone vs Research-Use Peptides: How Tissue-Repair Peptides Like BPC-157 and TB-500 Complement Classic Cardiorenal Drugs
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top