

Retatrutide Phase 3 Results in 2026: How Researchers Should Interpret Weight Loss, A1C, and Cardiometabolic Endpoints
Fewer than five years after GLP-1 receptor agonists reshaped obesity medicine, a triple-receptor agonist is now producing weight loss figures that exceed nearly every benchmark set by its predecessors. Retatrutide Phase 3 Results in 2026, specifically from Eli Lilly's TRIUMPH program, have placed the research and clinical communities in the unusual position of needing new interpretive frameworks rather than simply updated numbers. Understanding what these results mean, how the trials were designed, and where the data should not be extrapolated is essential for any researcher working with this compound.
Key Takeaways
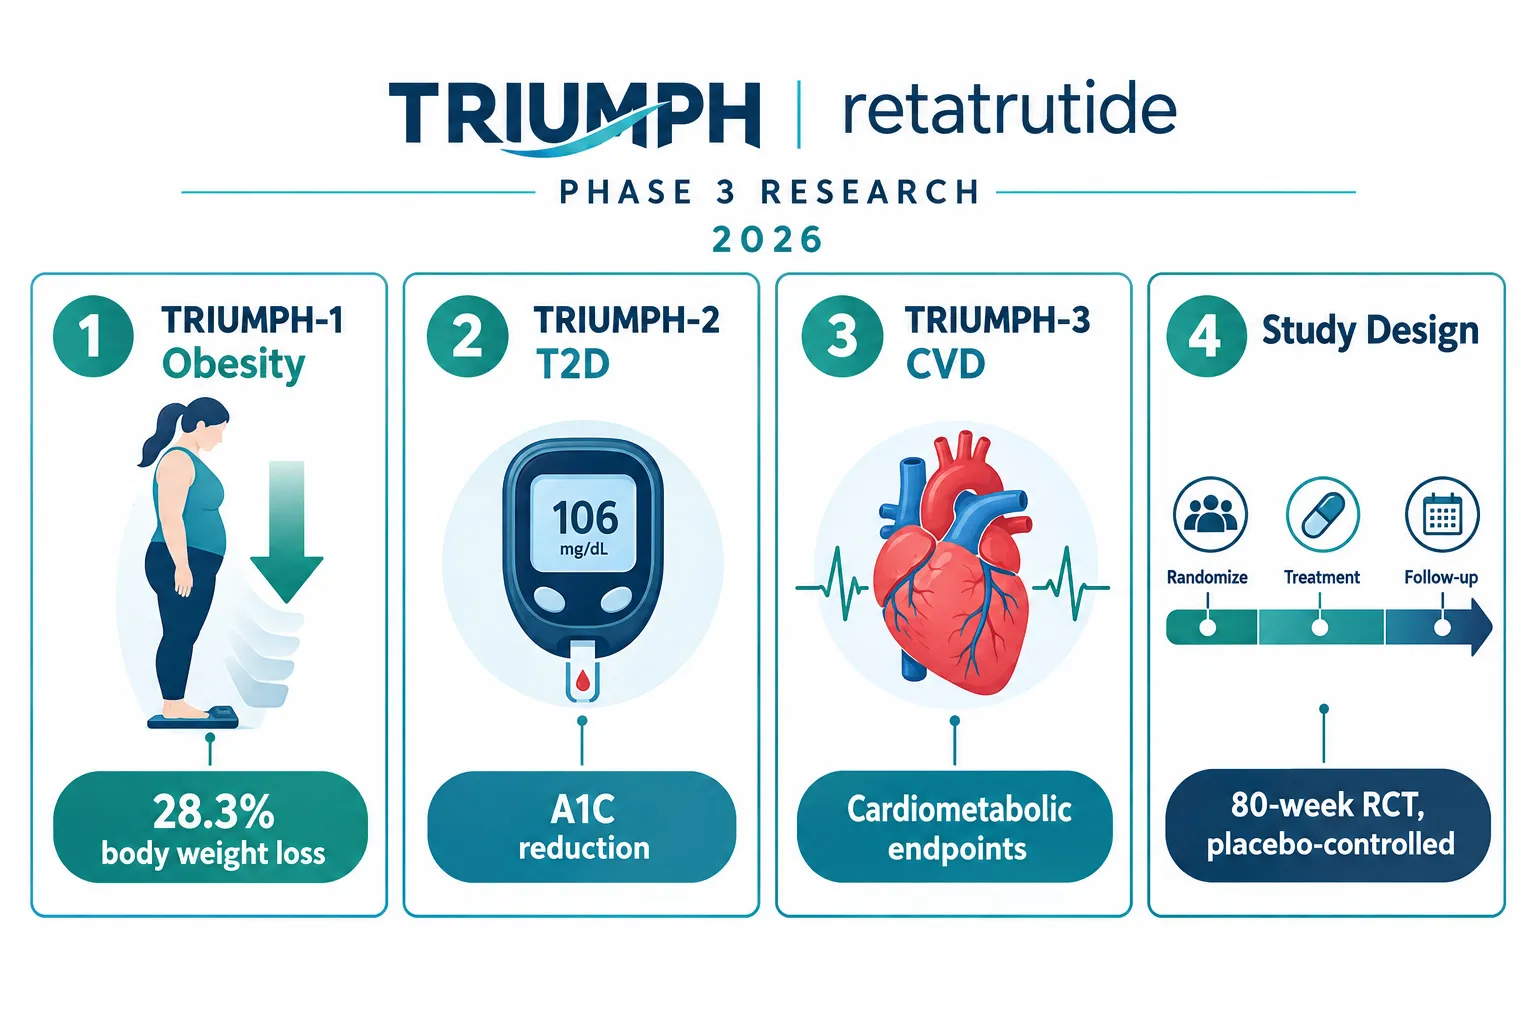
- TRIUMPH-1 showed average body weight reductions of up to 28.3% at 80 weeks on the 12 mg dose, with roughly 45% of participants achieving at least 30% weight loss.
- TRIUMPH-2 demonstrated meaningful A1C reductions alongside weight loss in adults with type 2 diabetes and obesity or overweight.
- TRIUMPH-3 targeted adults with severe obesity and established cardiovascular disease, expanding the cardiometabolic endpoint dataset.
- All three trials were 80-week, randomized, double-blind, placebo-controlled studies, setting a high methodological standard for interpretation.
- Phase 3 clinical findings should not be directly extrapolated to research-use peptide materials without accounting for purity, formulation, and dosing differences.
Understanding the TRIUMPH Trial Architecture
The TRIUMPH program consists of three pivotal Phase 3 trials, each enrolling distinct populations to isolate different aspects of retatrutide's effects. TRIUMPH-1 enrolled adults with obesity or overweight without type 2 diabetes. TRIUMPH-2 enrolled adults who had both type 2 diabetes and obesity or overweight. TRIUMPH-3 focused on adults with severe obesity and established cardiovascular disease. Each trial ran for 80 weeks under a randomized, double-blind, placebo-controlled design, the gold standard for regulatory-grade evidence.
Retatrutide itself is a triple agonist acting simultaneously on GLP-1, GIP, and glucagon receptors. This mechanism distinguishes it from dual agonists like tirzepatide and single-receptor agents like semaglutide. Researchers reviewing the retatrutide clinical trial literature should note that the multi-receptor activity complicates direct comparisons with earlier compounds, since each receptor pathway contributes differently to energy expenditure, appetite suppression, and glucose metabolism.
Key dose arms tested across TRIUMPH trials:
| Dose | Trial Inclusion | Primary Role |
|---|---|---|
| 4 mg once weekly | TRIUMPH-1, TRIUMPH-2 | Lower-dose comparator |
| 8 mg once weekly | TRIUMPH-1, TRIUMPH-2 | Mid-range efficacy arm |
| 9 mg once weekly | TRIUMPH-1 | High-dose efficacy arm |
| 12 mg once weekly | TRIUMPH-1, TRIUMPH-2, TRIUMPH-3 | Maximum dose efficacy arm |
Interpreting Weight Loss Endpoints from Retatrutide Phase 3 Results in 2026
TRIUMPH-1 produced the most widely cited weight loss figures. Participants on the 9 mg dose lost an average of 64.4 lb, representing 25.9% of baseline body weight. Those on the 12 mg dose lost an average of 70.3 lb, or 28.3% of baseline weight. The placebo group lost approximately 2.2%. Approximately 45% of the roughly 2,500 participants achieved at least 30% weight loss, a threshold that had rarely appeared in prior obesity pharmacotherapy trials.
An extension to 104 weeks showed that participants with a BMI of 35 kg/m² or higher on the highest dose lost approximately 30.3% of body weight on average, suggesting the effect is durable rather than plateauing early.
"A 28% average weight reduction in a randomized controlled trial is not a ceiling, it is a new baseline expectation for next-generation obesity pharmacotherapy."
Researchers reviewing these figures alongside retatrutide endpoints data should apply several interpretive cautions:
- Responder heterogeneity: Mean weight loss masks a wide distribution. Some participants lost far less; others exceeded 35%.
- Baseline BMI matters: Higher baseline BMI was associated with greater absolute weight loss but not always greater percentage loss.
- Titration schedules: The dose escalation protocol used in TRIUMPH trials is specific and structured. Rapid titration in research settings produces different tolerability profiles.
- Placebo subtraction: The net treatment effect, not the absolute loss, is the relevant efficacy signal for mechanistic research.
A1C, Glycemic Control, and Cardiometabolic Endpoints: What the Data Show
TRIUMPH-2 specifically addressed glycemic outcomes in adults with type 2 diabetes. Retatrutide produced substantial A1C reductions across all active dose arms, with the 12 mg arm achieving the largest decreases from baseline. These reductions were accompanied by meaningful weight loss, making it difficult to isolate the glycemic effect of the receptor agonism from the indirect benefit of fat mass reduction, a distinction that matters significantly for mechanistic researchers.
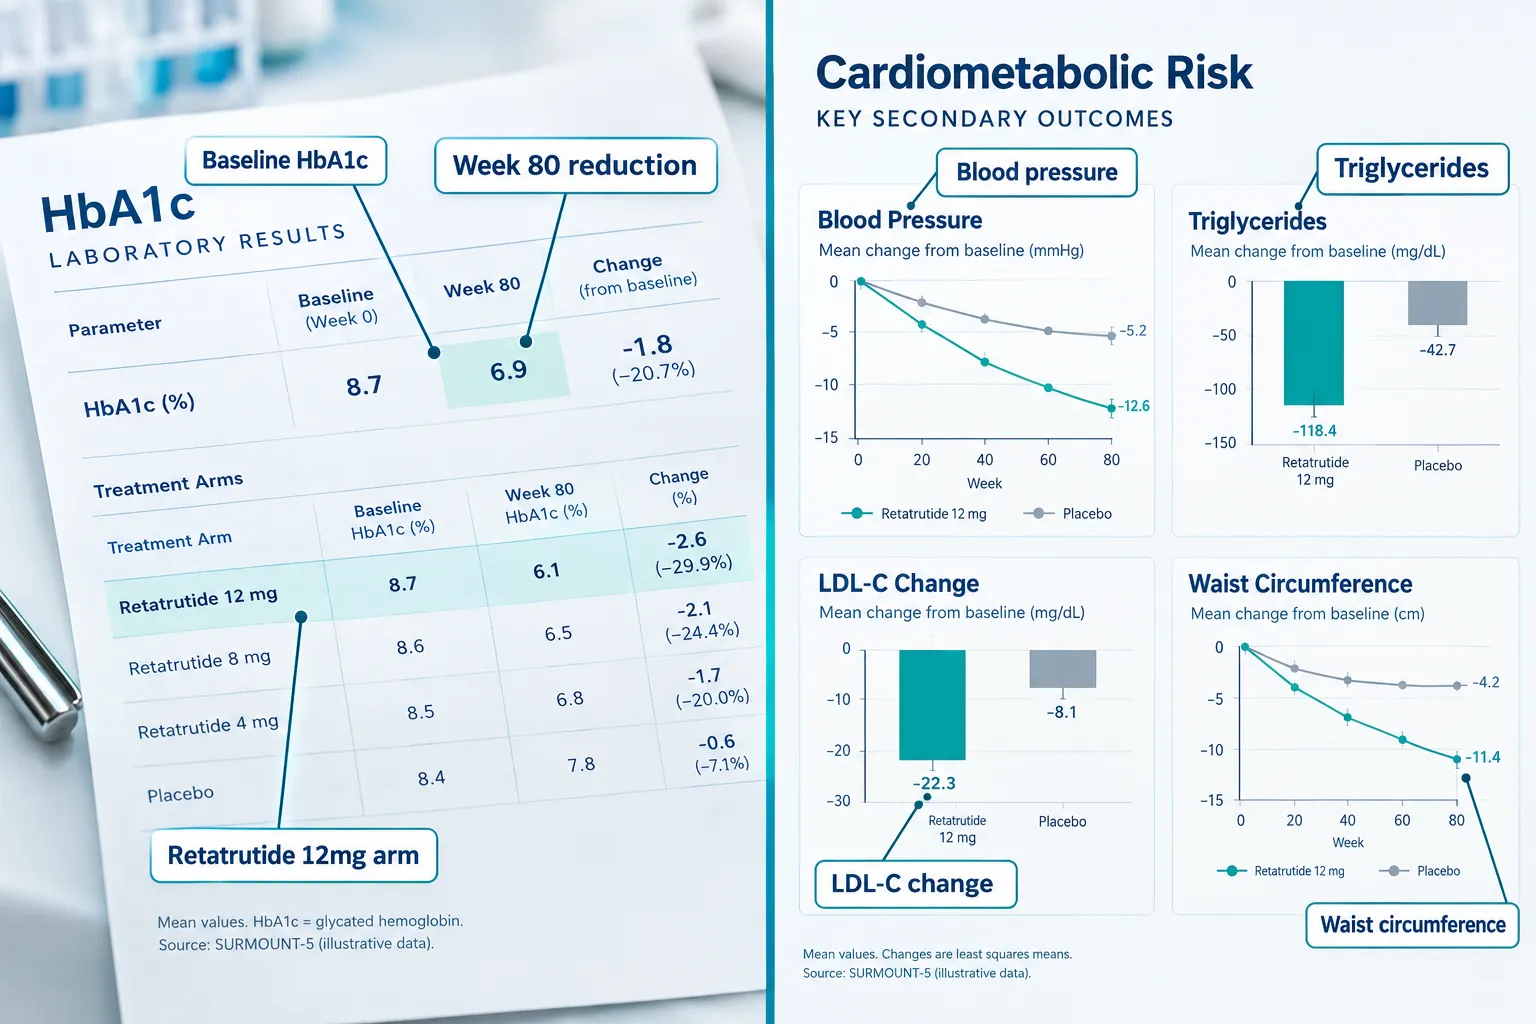
TRIUMPH-3 extended the dataset to cardiometabolic markers in a higher-risk population. Reported endpoints included changes in blood pressure, triglycerides, LDL-C, and waist circumference. While full cardiovascular outcomes data from a dedicated MACE trial are still pending as of 2026, the surrogate marker improvements observed in TRIUMPH-3 are consistent with the metabolic effects predicted by the triple-receptor mechanism.
Cardiometabolic endpoints researchers should track:
- Systolic and diastolic blood pressure reduction
- Fasting triglyceride change from baseline
- HDL-C and LDL-C shifts
- Waist circumference as a visceral adiposity proxy
- Liver enzyme normalization in participants with metabolic-associated steatotic liver disease
How Researchers Should Avoid Misextrapolating Phase 3 Findings
Retatrutide Phase 3 Results in 2026 represent pharmaceutical-grade, GMP-manufactured material administered under controlled clinical conditions. Research-use peptide materials, such as those available as GLP-3 Reta 30mg or GLP-3 Reta 20mg for laboratory use, differ in formulation, excipient profile, and intended application. Researchers sourcing material should consult verified retatrutide peptide buy online resources that provide third-party purity documentation.

The following extrapolation errors are most common in the literature:
- Assuming equivalent bioavailability between pharmaceutical formulations and research-grade lyophilized peptides
- Applying TRIUMPH dose arms directly to non-human or in vitro research models without allometric scaling
- Conflating A1C reduction with direct receptor-mediated glycemic control when weight loss itself accounts for a significant portion of the glycemic benefit
- Ignoring the titration variable, TRIUMPH participants were dose-escalated over weeks, not started at maximum dose
- Overstating cardiovascular conclusions before dedicated MACE trial data are published
For researchers comparing retatrutide to other metabolic peptides, reviewing Tesamorelin dosage for fat loss frameworks offers a useful methodological contrast, since Tesamorelin's visceral fat reduction mechanism and endpoint structure differ substantially from triple-receptor agonism.
Conclusion
The Retatrutide Phase 3 Results in 2026 represent a landmark dataset for obesity, diabetes, and cardiometabolic research. The TRIUMPH program's three-trial architecture provides layered evidence across distinct populations, dose arms, and outcome categories. For researchers, the actionable steps are clear:
- Treat the 80-week, placebo-controlled TRIUMPH data as the interpretive anchor for all mechanistic hypotheses involving retatrutide.
- Distinguish between mean efficacy signals and responder distributions before drawing mechanistic conclusions.
- Separate glycemic benefits attributable to weight loss from those attributable to direct receptor agonism when designing downstream studies.
- Source research-grade material only from suppliers providing verified purity documentation, and never apply clinical dose arms directly to preclinical models without appropriate scaling.
- Monitor the emerging MACE trial data before drawing cardiovascular outcome conclusions from surrogate markers alone.
The TRIUMPH results do not simply update a number, they reframe what metabolic pharmacotherapy can achieve and raise the methodological bar for how researchers must interpret, contextualize, and apply the data responsibly.


Leave a Reply
Want to join the discussion?Feel free to contribute!