

Metoprolol in Peptide Experiments: Controlling Heart Rate, Blood Pressure, and Adrenergic Confounding
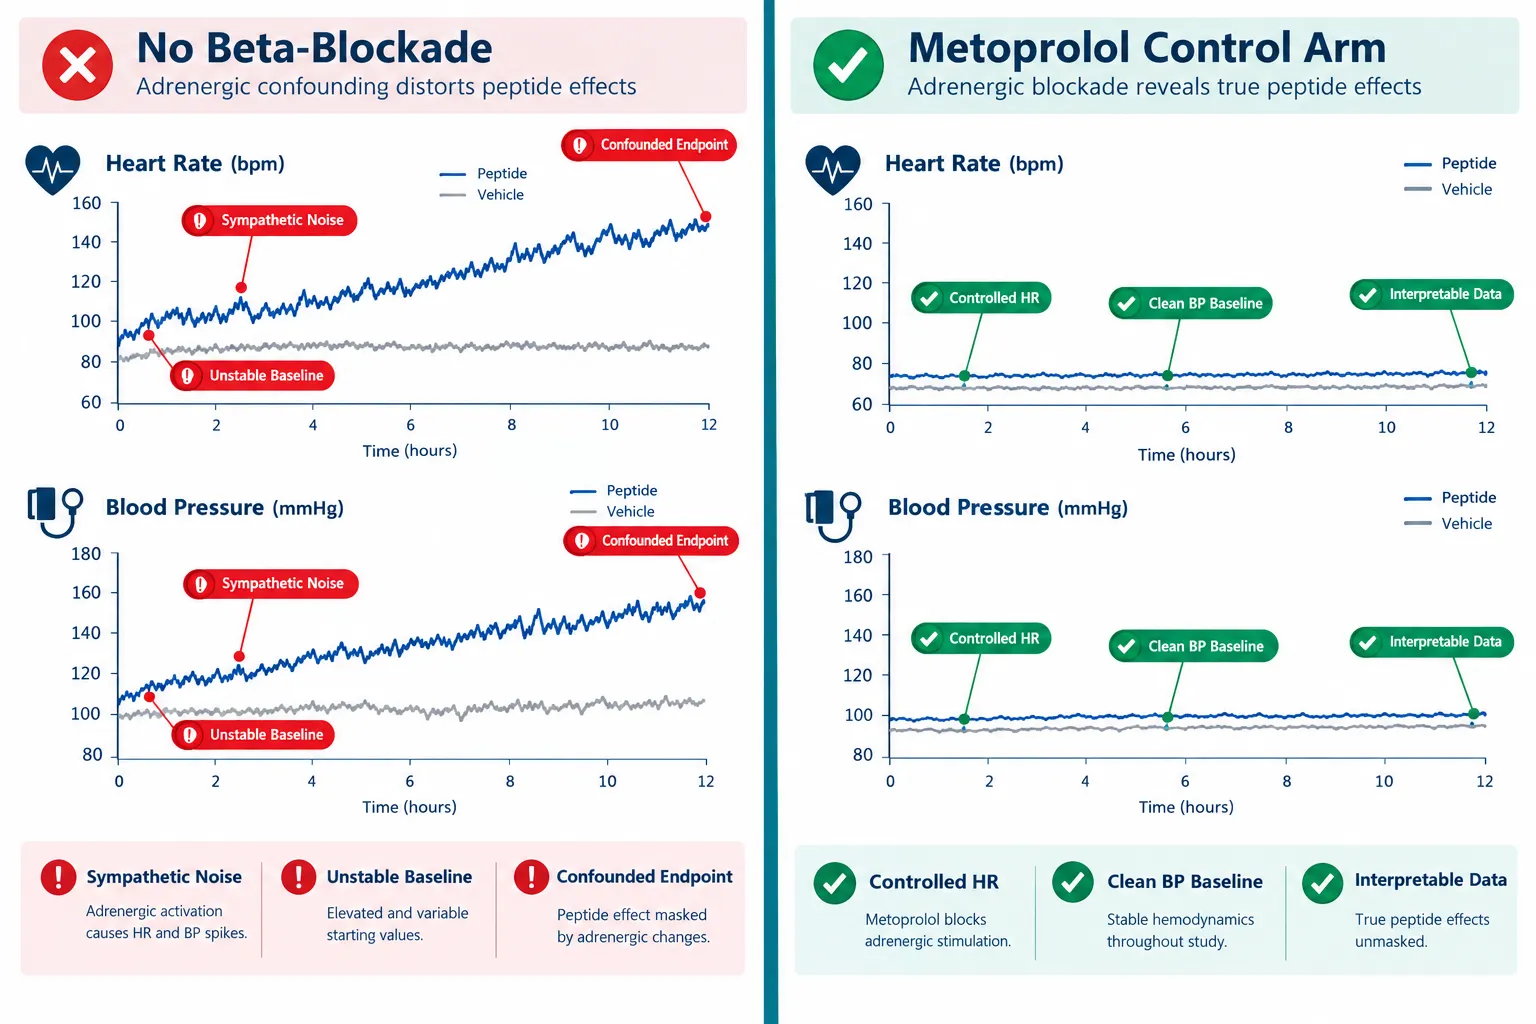
Cardiovascular endpoints fail silently when sympathetic noise is not controlled. Across retatrutide trials, growth-hormone-secretagogue models, and metabolic peptide studies, unmanaged adrenergic tone can shift heart rate by five to ten beats per minute and systolic blood pressure by several millimeters of mercury, differences large enough to obscure or mimic a genuine peptide effect. Understanding the role of metoprolol in peptide experiments for controlling heart rate, blood pressure, and adrenergic confounding is therefore not a minor methodological footnote; it is a foundational design decision.
Key Takeaways
- Metoprolol is a beta-1 selective blocker that reduces heart rate, systolic blood pressure, and cardiac output without raising peripheral resistance, making it a precise tool for quieting adrenergic noise.
- Placebo-corrected reductions of 3-6 mmHg systolic and 5-7 beats per minute are typical, but inter-subject variability, partly driven by CYP2D6 metabolizer status, can be substantial.
- Stable beta-blockade takes approximately one week of oral dosing; acute sympathetic blockade begins within 15 minutes of a single dose, so experimental timing must match the intended control strategy.
- Metoprolol controls adrenergic tone but does not normalize all advanced structural or functional endpoints, meaning it cannot substitute for a peptide's mechanism of action.
- Proper use requires genotype stratification, defined titration periods, and both resting and exercise-state baseline measurements before any peptide intervention begins.
Why Adrenergic Tone Confounds Peptide Cardiovascular Readouts
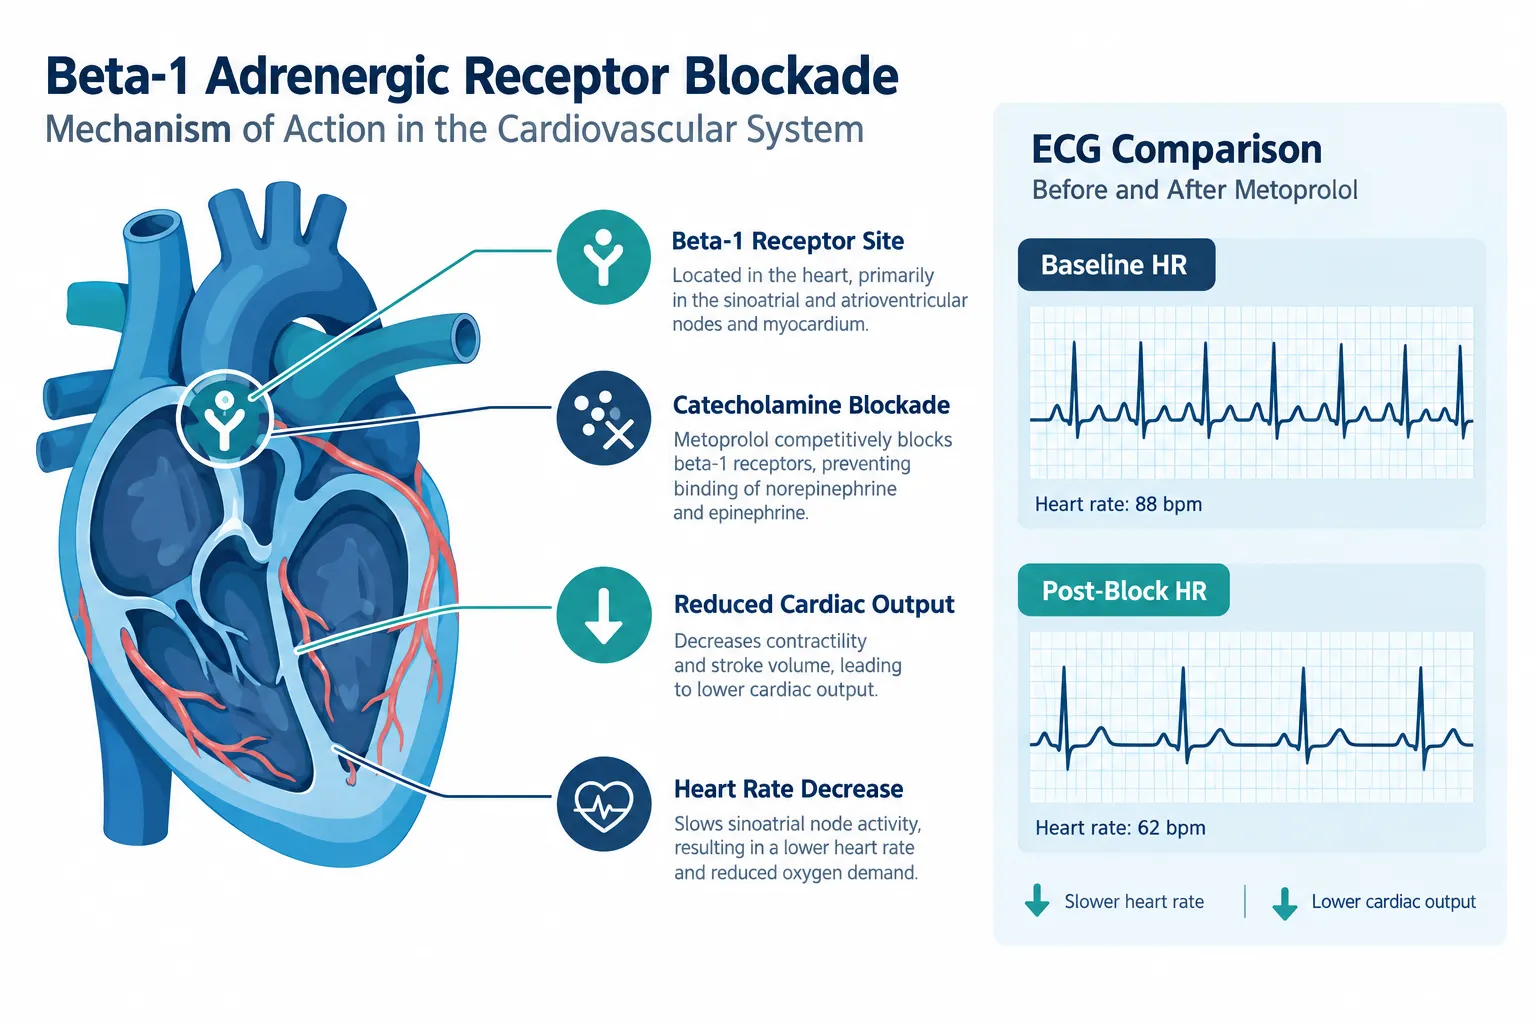
Many peptides under active investigation, including metabolic agents like retatrutide and GLP-3 class compounds, exert direct or indirect effects on the cardiovascular system. Growth-hormone secretagogues, vasoactive intestinal peptides such as VIP-5, and mitochondria-targeted peptides like SS-31 all operate in physiological environments where sympathetic tone fluctuates with stress, fasting state, exercise, and even the act of venipuncture.
Catecholamines, adrenaline and noradrenaline, bind beta-1 receptors on the myocardium and raise heart rate, contractility, and blood pressure. If a peptide also raises or lowers these parameters through a separate pathway, the two signals overlap. Without a pharmacological anchor, investigators cannot cleanly attribute observed hemodynamic changes to the peptide alone.
This is the core problem metoprolol solves. By selectively blocking beta-1 adrenergic receptors, it attenuates catecholamine-driven cardiovascular fluctuations, providing a more stable hemodynamic backdrop against which peptide-specific effects can be measured.
"Metoprolol does not eliminate cardiovascular physiology, it standardizes the sympathetic component of it, allowing other signals to emerge more clearly."
Key adrenergic phenomena that metoprolol suppresses include:
- Resting tachycardia driven by anxiety or metabolic stimulation
- Exercise-induced heart rate overshoot
- Isoproterenol-provoked tachycardia used in challenge protocols
- Reflex orthostatic tachycardia during postural changes
Each of these can appear as a false-positive or false-negative peptide effect if left uncontrolled.
Practical Application of Metoprolol in Peptide Experiments: Controlling Heart Rate, Blood Pressure, and Adrenergic Confounding
Dose Range and Titration Timing
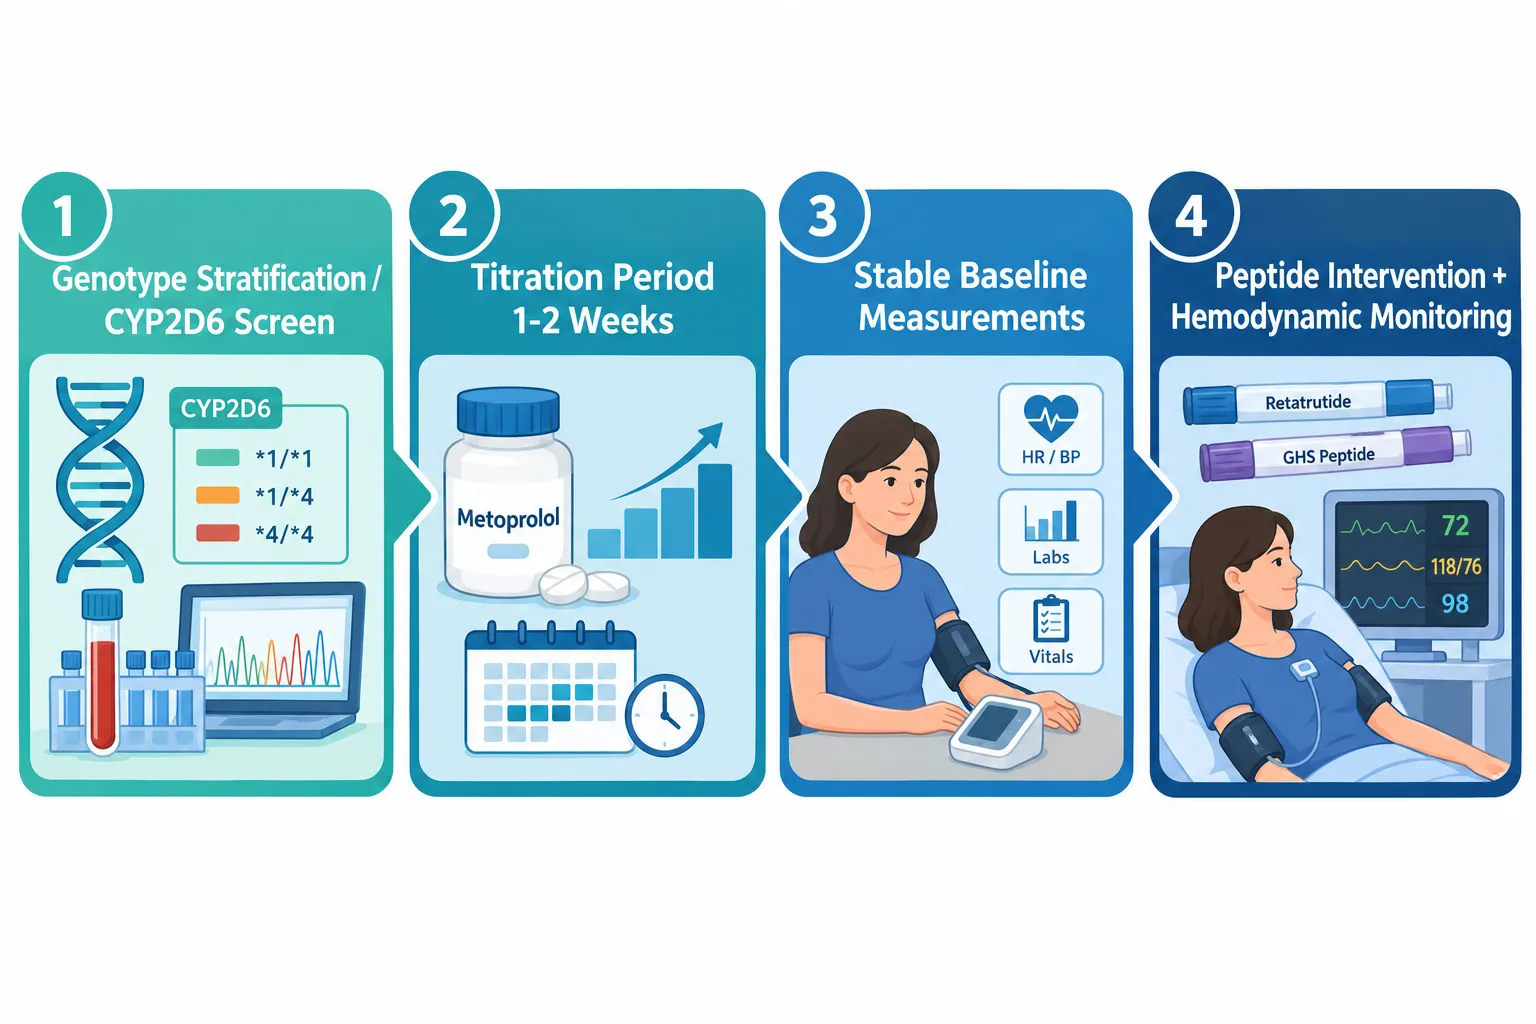
Oral metoprolol doses in hypertension and heart-rate control protocols typically range from 100 to 450 mg per day, titrated at weekly intervals. A single 50-80 mg dose begins reducing exercise systolic blood pressure within approximately 15 minutes, but stable, chronic antihypertensive effect requires roughly one week of consistent dosing.
This distinction matters enormously for experimental design:
| Control Strategy | Onset | Use Case |
|---|---|---|
| Acute single dose | ~15 minutes | Rapid sympathetic stabilization before a one-time challenge |
| Chronic titration (1 week+) | ~7 days | Stable baseline for multi-day peptide dosing protocols |
For most mechanistic peptide trials, including those assessing cardiometabolic polypeptide models, chronic titration is preferred because it removes day-to-day adrenergic variability rather than just blunting a single measurement window.
Accounting for CYP2D6 Metabolizer Status
A critical and often overlooked source of confounding within the metoprolol control arm itself is pharmacogenomic variability. Poor CYP2D6 metabolizers accumulate significantly higher serum metoprolol concentrations, producing greater and more consistent reductions in heart rate, diastolic blood pressure, and mean arterial pressure compared to extensive metabolizers at the same dose.
If subjects are not stratified by CYP2D6 status, the beta-blockade "control" becomes a new source of variance. Practical steps include:
- Pre-screen subjects for CYP2D6 poor-metabolizer status
- Stratify randomization accordingly
- Monitor resting and exercise heart rate at baseline, after titration, and at each peptide dosing interval
Baseline Measurement Protocol
Baseline measurements must capture both resting and dynamic (exercise) cardiovascular state. Metoprolol reduces heart rate and systolic blood pressure at rest and during exercise, these are separate physiological states that peptides may affect differently. Recording only resting values misses exercise-induced adrenergic surges that some metabolic peptides, including growth-hormone secretagogues, actively modulate.
Interpretation Cautions: What Metoprolol Cannot Control
Metoprolol's selectivity is both its strength and its limitation. As a beta-1 selective agent, it does not block alpha-1 receptors or beta-2 receptors. Contrast this with carvedilol, a non-selective blocker with additional alpha-1 antagonism, which suppresses adrenergic activity through a broader mechanism. The choice between these agents changes the nature of residual adrenergic confounding, a distinction highlighted in comparative cardiovascular outcome protocols.
For researchers working with peptides in endocrine pharmacology contexts or GH-analogue peptides, additional considerations include:
- Structural endpoints: Beta-blockade does not normalize advanced structural or functional cardiac endpoints. Recent data from myosin inhibitor trials confirm that metoprolol, despite controlling heart rate and blood pressure, did not replicate the specific functional improvements seen with next-generation myosin-targeted agents. Peptide trials must not assume that hemodynamic control equals functional equivalence.
- Peripheral vascular effects: Metoprolol does not increase peripheral resistance, but it also does not reduce it. Peptides with vasodilatory mechanisms, such as VIP-class agents, will still show vascular effects that metoprolol leaves unmasked.
- Metabolic interactions: Some metabolic peptides affect insulin sensitivity and glucose metabolism in ways that secondarily alter sympathetic tone. Metoprolol blunts the cardiovascular expression of this interaction but does not eliminate the underlying metabolic signal.
Conclusion
Metoprolol in peptide experiments for controlling heart rate, blood pressure, and adrenergic confounding represents one of the most practical pharmacological tools available to cardiovascular researchers in 2026. Its beta-1 selectivity, well-characterized dose-response profile, and rapid onset make it well suited for both acute challenge designs and chronic multi-week protocols.
Actionable next steps for research teams:
- Determine whether acute or chronic beta-blockade better matches the experimental timeline before dosing begins
- Screen and stratify subjects by CYP2D6 metabolizer status to prevent pharmacogenomic variance from contaminating the control arm
- Collect resting and exercise-state hemodynamic baselines after titration, not before
- Document which adrenergic phenomena remain unblocked (alpha-1, beta-2 pathways) and account for them in statistical models
- Avoid interpreting stable hemodynamic readings as evidence that all cardiovascular endpoints are normalized, structural and functional parameters require independent assessment
Selecting high-purity, well-characterized peptides from a reliable peptide supplier is equally important; compound variability introduces its own confounding that no pharmacological control can fully correct.


Leave a Reply
Want to join the discussion?Feel free to contribute!