Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu
GLP-2-T and GLP2 Tirz Peptides: Naming Confusion, Mechanistic Differences, and Research Use Cases

GLP-2-T and GLP2 Tirz Peptides: Naming Confusion, Mechanistic Differences, and Research Use Cases

July 13, 2026/0 Comments/by Pure Tested

GLP-2-T vs GLP2 Tirz Peptides cover image

Researchers searching for "GLP-2 Tirz" in 2026 frequently land on content about tirzepatide, a dual incretin agonist, when they actually need information about GLP-2-T, a modified analog of glucagon-like peptide-2 studied for gut barrier biology. That single naming overlap can derail an entire literature review. Understanding GLP-2-T and GLP2 Tirz Peptides: Naming Confusion, Mechanistic Differences, and Research Use Cases is therefore not just an academic exercise; it directly shapes which experimental model a researcher selects and which receptor pathways they target.

Key Takeaways

  • "GLP-2 Tirz" is an informal, technically inaccurate label for tirzepatide, a GLP-1/GIP dual agonist with no direct GLP-2 pathway activity.
  • GLP-2-T is a research-grade, stability-enhanced analog of the endogenous peptide GLP-2, focused on intestinal mucosal biology.
  • The two compounds act on completely different receptors and serve distinct research purposes.
  • Informal generational numbering (GLP-2, GLP-3) for incretin drugs creates systematic confusion in the research community.
  • Selecting the correct compound requires understanding both receptor targets and the biological systems under study.

Where the Naming Confusion Originates

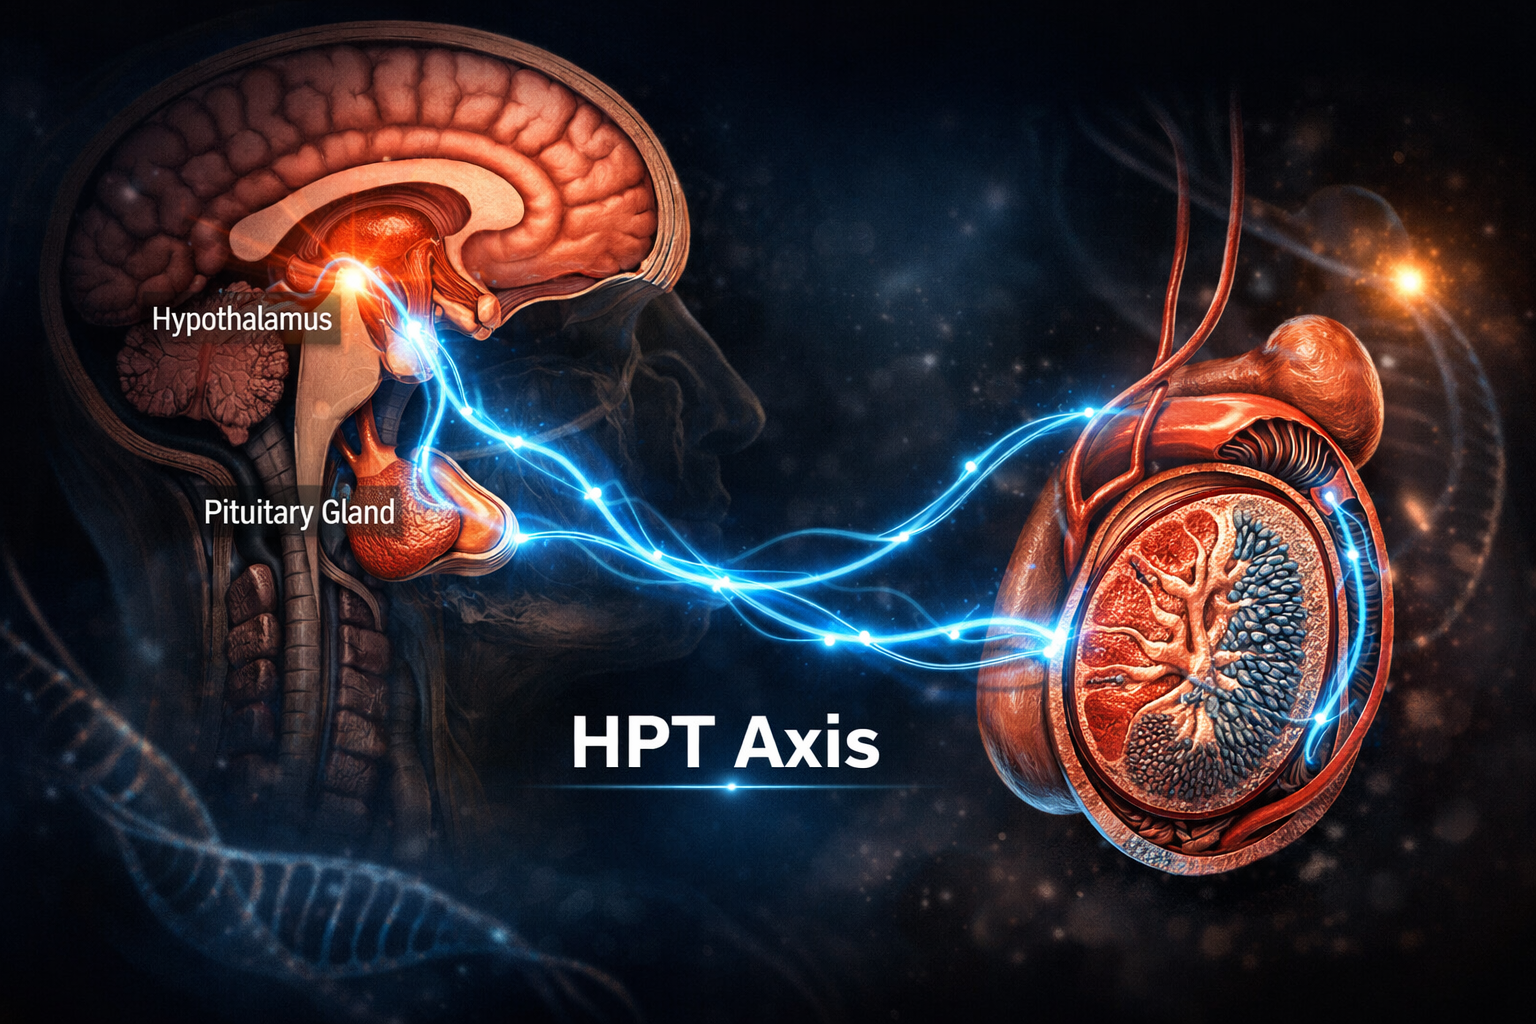
Split diagram comparing GLP-2-T and Tirzepatide molecular pathways

The confusion around GLP-2-T and GLP2 Tirz Peptides stems from an informal numbering convention that circulates in research blogs, supplement forums, and even some vendor catalogs. In this system, semaglutide is called "GLP-1," tirzepatide is called "GLP-2," and retatrutide is called "GLP-3." The logic follows the number of receptor targets each drug engages.

The problem: these numbers already belong to real, endogenous peptides.

  • GLP-1 (glucagon-like peptide-1): a well-characterized incretin hormone.
  • GLP-2 (glucagon-like peptide-2): a 33-amino acid hormone secreted by intestinal L-cells, primarily involved in gut mucosal growth and barrier function.
  • GLP-3: not a recognized endogenous hormone; "retatrutide" is its informal nickname, targeting GLP-1, GIP, and glucagon receptors.

The World Health Organization's International Nonproprietary Names system designates the generic name tirzepatide, with the stem "-tirz-" signaling its dual incretin activity. Calling tirzepatide "GLP-2 Tirz" blends an endogenous peptide name with a drug suffix, producing a label that implies receptor overlap where none exists.

For researchers exploring incretin-based metabolic research, the GLP-1-T incretin research themes page provides a useful parallel on how GLP-1 analogs are properly categorized. Similarly, the GLP-3 Reta research page illustrates how the triple-agonist space is being studied without conflating it with endogenous peptide families.


Mechanistic Differences: Two Compounds, Two Entirely Different Systems

Researcher's lab bench with peptide vials and pathway research cards

The core issue in the GLP-2-T and GLP2 Tirz Peptides naming confusion is that these compounds act through fundamentally separate biological systems.

How GLP-2 and GLP-2-T Work

GLP-2 is co-released with GLP-1 from enteroendocrine L-cells after nutrient intake. Its primary roles include:

  • Promoting intestinal mucosal growth and villus elongation
  • Supporting tight junction regulation and gut barrier integrity
  • Modulating enteric nervous system signaling

Critically, the GLP-2 receptor is expressed in the enteric nervous system rather than directly on intestinal epithelial cells, which means GLP-2 acts through an indirect mechanism involving neural intermediaries.

GLP-2-T is a modified, stability-enhanced analog of this endogenous peptide. Its structural modifications extend its half-life, allowing researchers to study longer-lasting gut mucosal effects without repeated peptide dosing in experimental setups. This makes it a practical tool for intestinal barrier and villus growth models.

How Tirzepatide (Informally "GLP-2 Tirz") Works

Tirzepatide is a dual agonist at the GLP-1 receptor and the glucose-dependent insulinotropic polypeptide (GIP) receptor. Its research-relevant actions include:

  • Stimulating glucose-dependent insulin secretion
  • Suppressing appetite via central GLP-1 receptor pathways
  • Modulating fat metabolism through GIP receptor activity

Tirzepatide has no direct activity at the GLP-2 receptor. Placing it under a "GLP-2" label is therefore mechanistically misleading. Researchers interested in dual incretin signaling may also find value in reviewing cagrilintide synergy with GLP-1 to understand how complementary peptide combinations are studied in metabolic contexts.

Feature GLP-2-T Tirzepatide ("GLP-2 Tirz")
Receptor target GLP-2 receptor GLP-1 + GIP receptors
Primary system Intestinal/gut mucosal Metabolic/pancreatic
Research focus Gut barrier, villi growth Insulin secretion, appetite
Endogenous basis GLP-2 analog Synthetic dual agonist

Research Use Cases: Selecting the Right Compound

GLP-2-T research use cases infographic with four key application icons

Understanding GLP-2-T and GLP2 Tirz Peptides: Naming Confusion, Mechanistic Differences, and Research Use Cases becomes most practical when deciding which compound belongs in a specific experimental design.

GLP-2-T Research Applications

GLP-2-T is primarily examined in preclinical gut biology models for:

  1. Intestinal villi growth and maintenance, studying how mucosal architecture responds to GLP-2 receptor stimulation
  2. Gut barrier permeability models, examining tight junction proteins and paracellular transport
  3. Enteric nervous system signaling, probing how GLP-2 receptor activation translates into epithelial responses via neural intermediaries
  4. Metabolic gut hub research, because the gut functions as a metabolic signaling organ, GLP-2-T is increasingly discussed alongside metabolic peptides

Recent research directions have also explored long-acting GLP-2 analogs through lipidation strategies, which enhance half-life and gut-tropic efficacy in rodent models, a design principle that informs GLP-2-T's structural modifications.

For researchers building multi-peptide protocols, longevity peptide research and MOTS-C mechanism and research offer context on how gut-metabolic signaling intersects with broader longevity pathways.

Tirzepatide Research Applications

Tirzepatide is studied for:

  • Glucose homeostasis and beta-cell function models
  • Adipose tissue metabolism via GIP receptor pathways
  • Appetite regulation through central GLP-1 receptor mechanisms

These are entirely separate research domains from GLP-2-T's intestinal focus. Researchers who require verified, lab-tested compounds for either pathway should consult resources on peptide purity testing to ensure compound integrity before experimental use.

Key distinction: If the research question involves gut mucosal biology, tight junctions, or intestinal villi, GLP-2-T is the relevant compound. If the question involves insulin secretion, appetite, or dual incretin signaling, tirzepatide is the appropriate subject, and it should be referred to by its correct INN name.


Conclusion

The naming overlap between GLP-2-T and "GLP-2 Tirz" (tirzepatide) is not a minor stylistic issue, it represents a mechanistic mismatch that can send researchers down the wrong experimental path. GLP-2-T targets the GLP-2 receptor and serves gut mucosal biology research. Tirzepatide targets GLP-1 and GIP receptors and belongs to metabolic and incretin research. They share no receptor overlap, no shared biological system, and no interchangeable research applications.

Actionable next steps for researchers:

  • Use the WHO-designated INN name "tirzepatide" in all literature and protocols, not the informal "GLP-2 Tirz" label.
  • Confirm receptor targets before selecting a compound for any experimental model.
  • Cross-reference vendor catalogs against peer-reviewed receptor pharmacology data.
  • Explore the all peptides for sale resource for context on how research-grade peptides are classified and combined.
  • Review innovative peptide delivery systems for updates on stability-enhancing modifications relevant to GLP-2-T analog design.

Precise nomenclature is the foundation of reproducible science. Resolving this naming confusion is the first step toward cleaner experimental design and more reliable results.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/glp-2-t-and-glp2-tirz-peptides-naming-confusion-mechanistic-differences-and-rese-1.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-13 13:18:122026-07-20 15:00:12GLP-2-T and GLP2 Tirz Peptides: Naming Confusion, Mechanistic Differences, and Research Use Cases

Using a Peptides Calculator for Accurate Reconstitution: Worked Examples for CJC‑1295, Ipamorelin, PT‑141, and BPC‑157

July 13, 2026/0 Comments/by Pure Tested

Cover Image

A dosing error as small as 0.05 mL can mean the difference between delivering 100 mcg and 250 mcg of a research peptide, a 150% overshoot from a single misread syringe line. Using a peptides calculator for accurate reconstitution: worked examples for CJC‑1295, Ipamorelin, PT‑141, and BPC‑157 removes that guesswork entirely by converting vial weight, bacteriostatic water (BAC water) volume, and target dose into a precise syringe unit every time.

Peptide reconstitution step-flow infographic showing vial, water, and syringe

Key Takeaways

  • A peptides calculator requires only three inputs: vial size (mg), BAC water volume (mL), and desired dose (mcg).
  • The core formula is: Draw volume (mL) = Desired dose (mcg) / Concentration (mcg/mL).
  • Concentration is set entirely by how much BAC water is added, not by the peptide itself.
  • Standard U-100 insulin syringes read in units; 1 unit = 0.01 mL, so 10 units = 0.10 mL.
  • Running the same math through a dedicated calculator tool eliminates manual arithmetic errors.

The Core Formula Behind Every Peptides Calculator

Before working through individual compounds, it helps to lock in the two-step math that every peptides calculator runs automatically.

Step 1, Calculate concentration:

Concentration (mcg/mL) = Vial size (mcg) / BAC water added (mL)

Step 2, Calculate draw volume:

Draw volume (mL) = Desired dose (mcg) / Concentration (mcg/mL)

Step 3, Convert mL to insulin syringe units (U-100):

Syringe units = Draw volume (mL) × 100

That is the entire engine. Tools such as PeptiTools, DrawDose, and VialDex automate these three steps and add a visual syringe guide so researchers can verify the correct fill line at a glance.


Using a Peptides Calculator for Accurate Reconstitution: Worked Examples for CJC‑1295, Ipamorelin, PT‑141, and BPC‑157

CJC‑1295 (No DAC), 2 mg Vial, 100 mcg Dose

CJC‑1295 without DAC is a short-acting growth hormone-releasing hormone analogue commonly studied at doses between 100-300 mcg. For CJC‑1295 no-DAC research applications, a 2 mg vial reconstituted with 2 mL BAC water is a practical starting point.

Variable Value
Vial size 2,000 mcg
BAC water added 2.0 mL
Concentration 1,000 mcg/mL
Target dose 100 mcg
Draw volume 0.10 mL
Syringe units (U-100) 10 units

Ipamorelin, 5 mg Vial, 200 mcg Dose

Ipamorelin is a selective ghrelin mimetic often paired with CJC‑1295. Research on the CJC‑1295 plus Ipamorelin combination typically targets 200-300 mcg of Ipamorelin per injection.

Variable Value
Vial size 5,000 mcg
BAC water added 2.5 mL
Concentration 2,000 mcg/mL
Target dose 200 mcg
Draw volume 0.10 mL
Syringe units (U-100) 10 units

Note how a higher concentration still produces the same draw volume, a counterintuitive result that a peptides calculator makes immediately clear.

PT‑141 (Bremelanotide), 10 mg Vial, 1 mg Dose

PT‑141 is a melanocortin receptor agonist. For PT‑141 research contexts, doses are typically expressed in milligrams rather than micrograms, so the unit conversion is slightly different.

Variable Value
Vial size 10,000 mcg
BAC water added 2.0 mL
Concentration 5,000 mcg/mL
Target dose 1,000 mcg (1 mg)
Draw volume 0.20 mL
Syringe units (U-100) 20 units

BPC‑157-5 mg Vial, 250 mcg Dose

BPC‑157 is a synthetic pentadecapeptide studied for tissue repair and angiogenesis. Researchers exploring BPC‑157 angiogenesis and tendon research often work in the 250-500 mcg range.

Variable Value
Vial size 5,000 mcg
BAC water added 2.0 mL
Concentration 2,500 mcg/mL
Target dose 250 mcg
Draw volume 0.10 mL
Syringe units (U-100) 10 units

Four research peptide vials with syringe and handwritten calculations


Practical Tips for Reducing Reconstitution Errors

Even with a calculator, lab technique matters. The following practices reduce error at the bench:

  • Always use bacteriostatic water, not sterile water, for multi-use vials. BAC water contains 0.9% benzyl alcohol, which inhibits microbial growth.
  • Inject BAC water slowly down the vial wall, never directly onto the lyophilized cake, to preserve peptide structure.
  • Swirl gently; never vortex. Aggressive agitation can degrade fragile peptide bonds.
  • Store reconstituted vials at 2-8°C and use within the manufacturer's recommended window.
  • Double-check units vs. mL. The most common syringe error is confusing "units" on an insulin syringe with milliliters. On a U-100 syringe, 10 units = 0.10 mL, always.

For researchers working with multi-peptide protocols, tools like VialDex and PepPal support blend calculations, which is especially useful when studying Tesamorelin/CJC‑1295/Ipamorelin 12 mg blends where each component has a different concentration within the same vial.

Researchers interested in broader peptide categories can also explore the full peptide blends research catalog for additional compound options, or review the GH-axis product line overview for context on growth hormone secretagogue research.

Those studying recovery-focused compounds should also reference the recovery and tissue biology overview for dosing context alongside BPC‑157 reconstitution work.

Scientist using peptide calculator tablet beside reconstitution vials


Conclusion

Using a peptides calculator for accurate reconstitution, with worked examples for CJC‑1295, Ipamorelin, PT‑141, and BPC‑157, reduces the three-step math to a reliable, repeatable process. The formula never changes: divide vial micrograms by BAC water volume to get concentration, then divide target dose by concentration to get draw volume, and multiply by 100 to read off syringe units.

Actionable next steps for 2026 research protocols:

  1. Select a dedicated calculator tool (PeptiTools, DrawDose, VialDex, or EZ PepCalc) and bookmark it before any reconstitution session.
  2. Record every reconstitution in a lab notebook: vial lot, BAC water volume, date, and resulting concentration.
  3. Cross-reference calculated draw volumes against a visual syringe guide before each draw.
  4. Review compound-specific dosing literature, such as the Sermorelin/Ipamorelin/CJC‑1295 dosage reference, to confirm that target doses fall within studied research ranges.

Precision at the reconstitution stage is the foundation of reproducible peptide research. A calculator does not replace scientific judgment, but it does eliminate the arithmetic errors that undermine it.

https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 0 0 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-13 13:18:112026-07-20 15:00:13Using a Peptides Calculator for Accurate Reconstitution: Worked Examples for CJC‑1295, Ipamorelin, PT‑141, and BPC‑157

Retatrutide for Metabolic Dysfunction-Associated Steatotic Liver Disease: What the Phase 2a Data Suggest

July 13, 2026/0 Comments/by Pure Tested

Cover Image

Nearly one in three adults worldwide carries excess fat in their liver, yet until recently, no drug had demonstrated the ability to reduce liver fat by more than 80% in a controlled clinical trial. The Phase 2a data on retatrutide for Metabolic Dysfunction-Associated Steatotic Liver Disease change that picture dramatically, offering some of the most striking liver-fat reduction numbers ever recorded in a randomized study.

Retatrutide triple agonist mechanism targeting liver fat in MASLD

Key Takeaways

  • Retatrutide reduced liver fat content by up to 86% at 48 weeks in the highest-dose group, far exceeding placebo.
  • Up to 86% of participants in the 12 mg group achieved normal liver fat levels (below 5%) by week 24.
  • The drug targets three metabolic receptors, GIP, GLP-1, and glucagon, creating a multi-pathway effect on fat metabolism.
  • Body weight fell by roughly 22-24% in the higher-dose groups, which likely amplifies liver-fat clearance.
  • Gastrointestinal side effects were common but serious adverse events were comparable to placebo.

How Retatrutide Works: A Triple-Receptor Approach

Retatrutide is a triple agonist that activates three distinct receptors simultaneously: glucose-dependent insulinotropic polypeptide (GIP), glucagon-like peptide-1 (GLP-1), and glucagon receptors. This sets it apart from single or dual agonists currently in use.

Each receptor pathway contributes something different:

  • GLP-1 activation slows gastric emptying, reduces appetite, and improves insulin secretion.
  • GIP activation supports fat storage regulation and amplifies the insulin response.
  • Glucagon activation increases energy expenditure and directly promotes fat breakdown in the liver.

The glucagon component is especially relevant for liver health. Glucagon receptor signaling drives hepatic fat oxidation, the process by which the liver burns stored fat for fuel. This is a key reason why retatrutide's liver-fat reductions outpace what GLP-1 agonists alone typically achieve.

For a broader look at how incretin-based peptides are evolving, the GLP-1 dual receptor agonism research breakdown provides useful context on how adding receptor targets changes metabolic outcomes. Researchers interested in generational differences among these agents can also explore the evolution of GLP-1 generations.


Phase 2a Trial Design and Primary Liver-Fat Findings

The Phase 2a trial enrolled 98 adults with MASLD who had a liver fat content of at least 10% at baseline. Participants received once-weekly subcutaneous injections of retatrutide at doses of 1 mg, 4 mg, 8 mg, or 12 mg, or a placebo, over 48 weeks in a randomized, double-blind, placebo-controlled design.

Liver Fat Reduction at 24 Weeks

The primary endpoint, relative change in liver fat at 24 weeks, showed a clear dose-response relationship:

Dose Mean Relative Change in Liver Fat Participants Reaching <5% Liver Fat
Placebo +0.3% 0%
1 mg -42.9% 27%
4 mg -57.0% 52%
8 mg -81.4% 79%
12 mg -82.4% 86%

All retatrutide doses were statistically significant versus placebo (P < 0.001).

Sustained Reductions at 48 Weeks

The reductions held and, in most groups, deepened by week 48:

  • 1 mg: -51.3%
  • 4 mg: -59.0%
  • 8 mg: -81.7%
  • 12 mg: -86.0%
  • Placebo: -4.6%

"An 86% reduction in liver fat content at 48 weeks represents a clinically meaningful threshold, one that could translate into histological resolution of steatosis in a large proportion of treated patients."

These results place retatrutide for Metabolic Dysfunction-Associated Steatotic Liver Disease among the most promising investigational therapies in hepatology. For comparison, tesa, a growth hormone-releasing hormone analogue with established liver-fat effects, offers a different mechanistic angle worth understanding; see the tesa benefits research overview for that perspective.

Researcher reviewing liver fat reduction data from retatrutide Phase 2a trial


Weight Loss, Insulin Sensitivity, and Safety Signals

Body Weight and Metabolic Outcomes

Weight loss was substantial in the higher-dose groups. Participants on 8 mg lost an average of 22.8% of body weight at 48 weeks; those on 12 mg lost 24.2%. This degree of weight reduction is clinically significant on its own, and it likely contributes to liver-fat clearance through reduced free fatty acid flux to the liver.

Improved insulin sensitivity is expected to follow from both the direct receptor effects and the secondary weight loss, though the Phase 2a data focused primarily on liver fat as the primary endpoint. Phase 3 trials will need to assess insulin resistance markers, triglyceride panels, and histological fibrosis scores more rigorously.

Researchers tracking peptide-based metabolic interventions may also find value in reviewing cagrilintide synergy with GLP-1 agents as a related area of combination therapy research.

Safety Profile

Adverse events were predominantly gastrointestinal, nausea, vomiting, and diarrhea, consistent with the GLP-1 mechanism. Incidence rates ranged from 73% to 94% across retatrutide groups versus 70% in the placebo group. Importantly, serious adverse events were comparable between retatrutide and placebo, suggesting the tolerability profile does not introduce major safety concerns at this stage.

The higher-dose groups (8 mg and 12 mg) showed the greatest gastrointestinal burden, which is a known trade-off with more aggressive receptor activation. Dose titration strategies will likely be refined in Phase 3 to manage this.

For those researching the broader landscape of peptide therapies and their safety considerations, the ultimate guide to peptide therapy offers a useful foundational reference.

Retatrutide liver fat reduction and weight loss comparison at 48 weeks


What the Phase 2a Data Suggest About Retatrutide for Metabolic Dysfunction-Associated Steatotic Liver Disease

The Phase 2a findings establish three critical signals:

  1. Dose-dependent efficacy, higher doses produce proportionally greater liver-fat clearance.
  2. Durability, reductions are maintained and often amplified between weeks 24 and 48.
  3. Normalization potential, up to 86% of participants in the highest-dose group reached normal liver fat levels, a benchmark that has rarely been achieved pharmacologically.

What remains unanswered is whether these imaging-based improvements translate into histological resolution of steatohepatitis and fibrosis regression, the endpoints that matter most for long-term liver outcomes. Phase 3 trials with liver biopsy endpoints are the logical next step.

The GLP-1 incretin research themes page tracks the evolving evidence base for this class of agents and provides useful context for interpreting where retatrutide fits within the broader incretin landscape.


Conclusion

The Phase 2a data on retatrutide for Metabolic Dysfunction-Associated Steatotic Liver Disease are among the most compelling early-phase results in metabolic liver disease research in 2026. Liver fat reductions of up to 86%, combined with nearly 25% body weight loss and a manageable safety profile, position retatrutide as a high-priority candidate for Phase 3 investigation.

Actionable next steps for clinicians and researchers:

  • Monitor Phase 3 trial registrations for biopsy-confirmed endpoints in MASLD and MASH populations.
  • Track triglyceride and insulin sensitivity data as secondary endpoints in upcoming studies.
  • Review the evolving triple-agonist mechanism literature to understand how glucagon receptor activation differentiates retatrutide from GLP-1 monotherapy.
  • Explore the retatrutide research profile for the latest compound-specific updates.

The liver-fat signal from this trial is too strong to ignore, and the next phase of evidence will determine whether that signal translates into a genuine disease-modifying therapy.

https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 0 0 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-13 13:18:092026-07-20 15:00:13Retatrutide for Metabolic Dysfunction-Associated Steatotic Liver Disease: What the Phase 2a Data Suggest
Enclomiphene and LH/FSH Modulation: Exploring Non-Steroidal Approaches in Male Hormone Research

Enclomiphene and LH/FSH Modulation: Exploring Non-Steroidal Approaches in Male Hormone Research

July 12, 2026/0 Comments/by Pure Tested

Nearly 40% of men over age 45 show some degree of testosterone deficiency, yet conventional testosterone replacement therapy carries a well-documented trade-off: it suppresses the very hormonal signals needed for sperm production. Research into enclomiphene and LH/FSH modulation: exploring non-steroidal approaches in male hormone research has opened a compelling alternative pathway, one that works with the body's own feedback systems rather than overriding them.

Key Takeaways

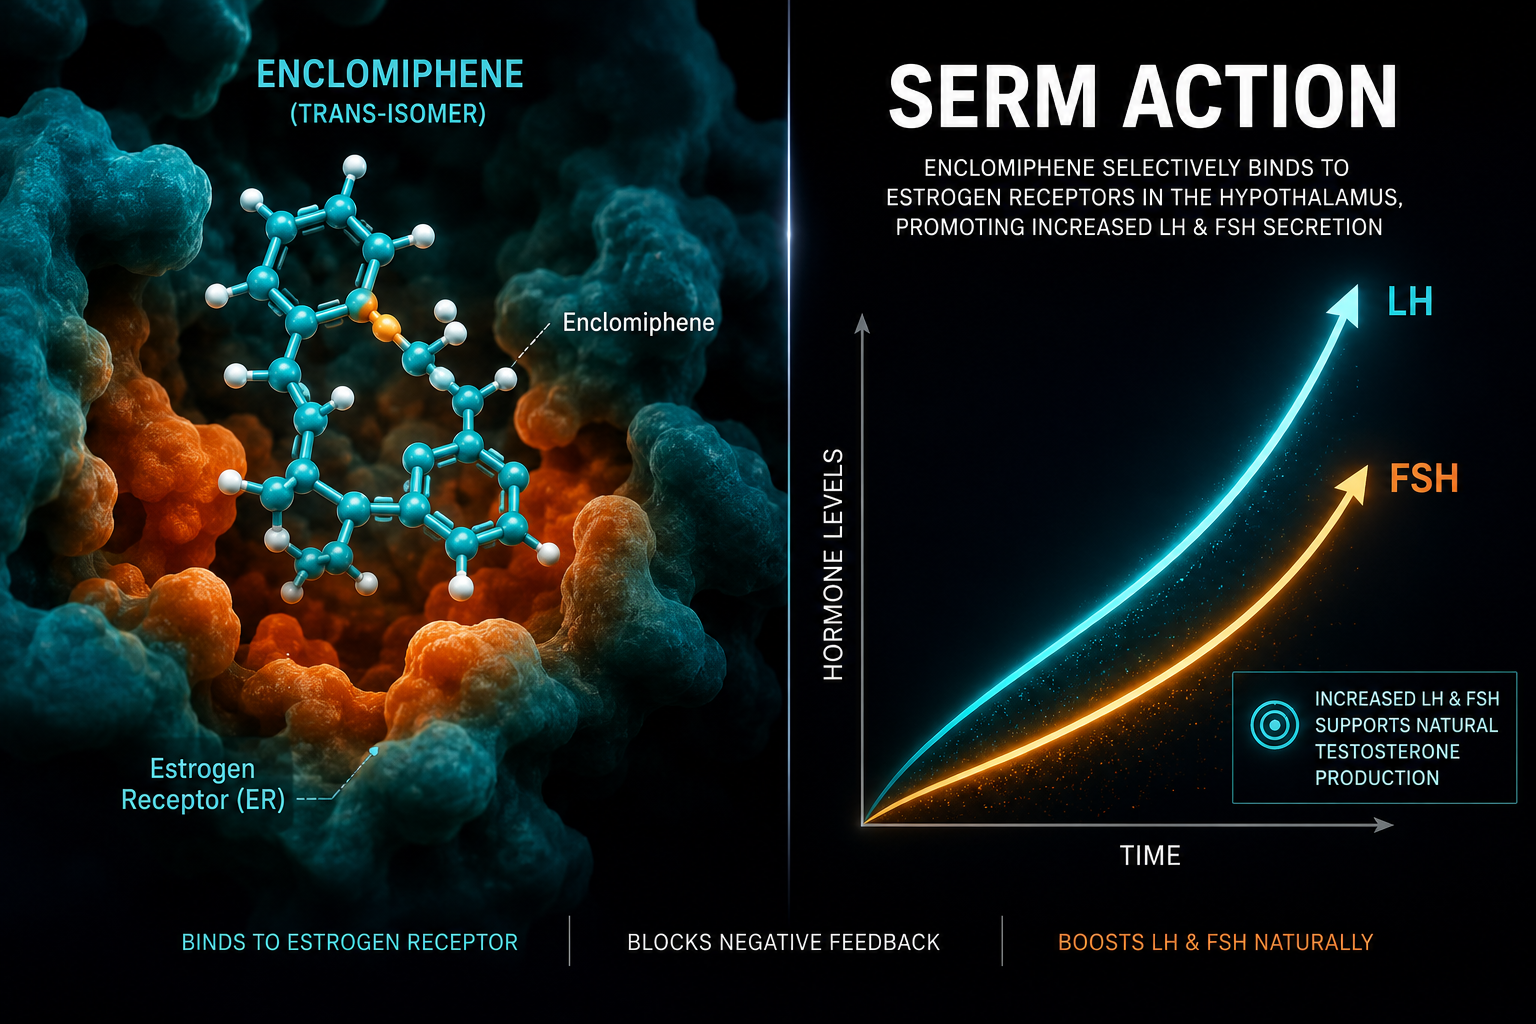
  • Enclomiphene is the active trans-isomer of clomiphene citrate and functions as a selective estrogen receptor modulator (serm) at the hypothalamus and pituitary.
  • By blocking estrogen receptors upstream, enclomiphene increases GnRH pulse frequency, which drives measurable rises in both LH and FSH.
  • Unlike exogenous testosterone, enclomiphene preserves and may enhance spermatogenesis during treatment.
  • Clinical data show comparable testosterone and gonadotropin increases between enclomiphene and clomiphene over 12 months, with enclomiphene offering a cleaner pharmacological profile.
  • As of 2026, enclomiphene is not FDA-approved as a standalone agent but is accessible through compounding pharmacies for research and clinical use.

Key Takeaways

How Enclomiphene Modulates LH and FSH at the Receptor Level

Clomiphene citrate is a mixture of two geometric isomers: enclomiphene (trans) and zuclomiphene (cis). Research has clarified that the trans-isomer carries the bulk of the therapeutic activity. Zuclomiphene contributes little to the intended hormonal outcomes and may linger in circulation due to a much longer half-life.

Enclomiphene works by occupying estrogen receptors in the hypothalamus and pituitary gland. Under normal physiology, circulating estradiol binds those receptors and signals the brain to reduce gonadotropin-releasing hormone (GnRH) output. When enclomiphene occupies those same receptors without activating them, the brain interprets the signal as low estrogen and responds by increasing GnRH pulse frequency.

That upstream change produces a cascade:

  • GnRH rises – pulsatile release from the hypothalamus intensifies
  • LH surges – the pituitary releases more luteinizing hormone
  • FSH increases – follicle-stimulating hormone output also climbs
  • Testosterone rises – Leydig cells in the testes respond to elevated LH by producing more endogenous testosterone
  • Spermatogenesis continues – Sertoli cells, driven by FSH, maintain sperm production

This mechanism is fundamentally different from exogenous testosterone, which suppresses the HPT axis through negative feedback. Enclomiphene's half-life of roughly 10 hours supports once-daily oral dosing, typically in the 12.5 to 25 mg range, making it a practical research candidate.

Researchers exploring related peptide-based hormonal pathways may also find value in reviewing IPA serm stack research and the broader context of metabolic modulation research lines when designing multi-axis studies.


How Enclomiphene Modulates LH and FSH at the Receptor Level

Clinical Evidence Supporting Enclomiphene and LH/FSH Modulation

A randomized phase II clinical trial demonstrated that enclomiphene citrate produced meaningful increases in morning serum testosterone, estradiol, and LH in men with secondary hypogonadism. Critically, sperm counts remained within the normal range throughout the study period, while men using topical testosterone experienced a marked reduction in spermatogenesis.

A longer comparative study published in 2024 found that enclomiphene and clomiphene produced similar increases in testosterone, estradiol, FSH, and LH over 12 months. That finding is significant because it validates enclomiphene's efficacy while highlighting its advantage: the absence of the zuclomiphene isomer means a cleaner pharmacokinetic profile and potentially fewer off-target effects.

Parameter Enclomiphene Topical Testosterone
LH levels Increased Suppressed
FSH levels Increased Suppressed
Sperm count Maintained Reduced
Endogenous T production Stimulated Replaced

Who is an ideal research candidate? Men with secondary hypogonadism whose testes retain the capacity to respond to LH stimulation represent the most relevant study population. Their HPT axis is intact but under-stimulated, making serm-based intervention a logical research target.

Those investigating broader hormonal and recovery research may find useful context in BPC-157 research themes and TB-500 muscle recovery research, as tissue-level recovery often intersects with hormonal optimization in research models.


Clinical Evidence Supporting Enclomiphene and LH/FSH Modulation

Regulatory Context and Future Research Directions

As of 2026, enclomiphene is not FDA-approved as a standalone therapeutic agent. It remains available through compounding pharmacies, which has shaped how researchers and clinicians access it. Experts in the field have noted that the compound warrants further prospective evaluation given its favorable gonadotropin profile and fertility-preserving properties.

The broader landscape of non-steroidal approaches in male hormone research continues to expand. Researchers are increasingly interested in how serms like enclomiphene interact with other signaling pathways, including those modulated by peptides targeting the growth hormone axis. Resources such as what is new in peptide research and the serm product research page offer additional context for those mapping intersecting research domains.

Parallel interest in mitochondrial and cellular longevity pathways, such as those explored in MOTS-c mitochondrial research and GHK-Cu longevity research themes, reflects a growing recognition that male hormonal health does not exist in isolation.


Conclusion

Research into enclomiphene and LH/FSH modulation: exploring non-steroidal approaches in male hormone research has produced a compelling body of evidence. By selectively blocking estrogen receptors at the hypothalamus and pituitary, enclomiphene amplifies the body's own GnRH-LH-FSH cascade, raises endogenous testosterone, and preserves fertility in a way that exogenous testosterone cannot.

Actionable next steps for researchers and clinicians in 2026:

  1. Review available phase II and comparative trial data to understand the gonadotropin response profile across different dosing windows.
  2. Consider enclomiphene's pharmacokinetics (half-life approximately 10 hours, oral dosing 12.5-25 mg daily) when designing study protocols.
  3. Evaluate patient or subject suitability based on intact HPT axis function and fertility preservation goals.
  4. Monitor LH, FSH, testosterone, estradiol, and sperm concentration as primary outcome markers.
  5. Stay current with regulatory developments, as the compounding pharmacy pathway may evolve.

The non-steroidal serm approach represents one of the most mechanistically precise tools available in male hormone research today.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/enclomiphene-and-lh-fsh-modulation-exploring-non-steroidal-approaches-in-male-ho.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-12 13:17:402026-07-20 15:00:14Enclomiphene and LH/FSH Modulation: Exploring Non-Steroidal Approaches in Male Hormone Research
CJC-1295 with Ipamorelin vs. Tesamorelin: Which GHRH Mimetic Stack is Best for Your Research?

CJC-1295 with Ipamorelin vs. Tesamorelin: Which GHRH Mimetic Stack is Best for Your Research?

July 12, 2026/0 Comments/by Pure Tested

Only one growth hormone peptide has ever cleared FDA approval, and it is not the stack that dominates anti-aging clinics worldwide. That contrast sits at the heart of the CJC-1295 with Ipamorelin vs. Tesamorelin debate, and understanding it can sharpen the focus of any serious growth hormone research program in 2026.

Editorial () split-screen conceptual illustration: left half shows a stylized dual-vial peptide stack labeled 'CJC-1295' and

Key Takeaways

  • CJC-1295 paired with Ipamorelin exploits two distinct pituitary signaling pathways simultaneously, producing a synergistic, pulsatile GH release pattern.
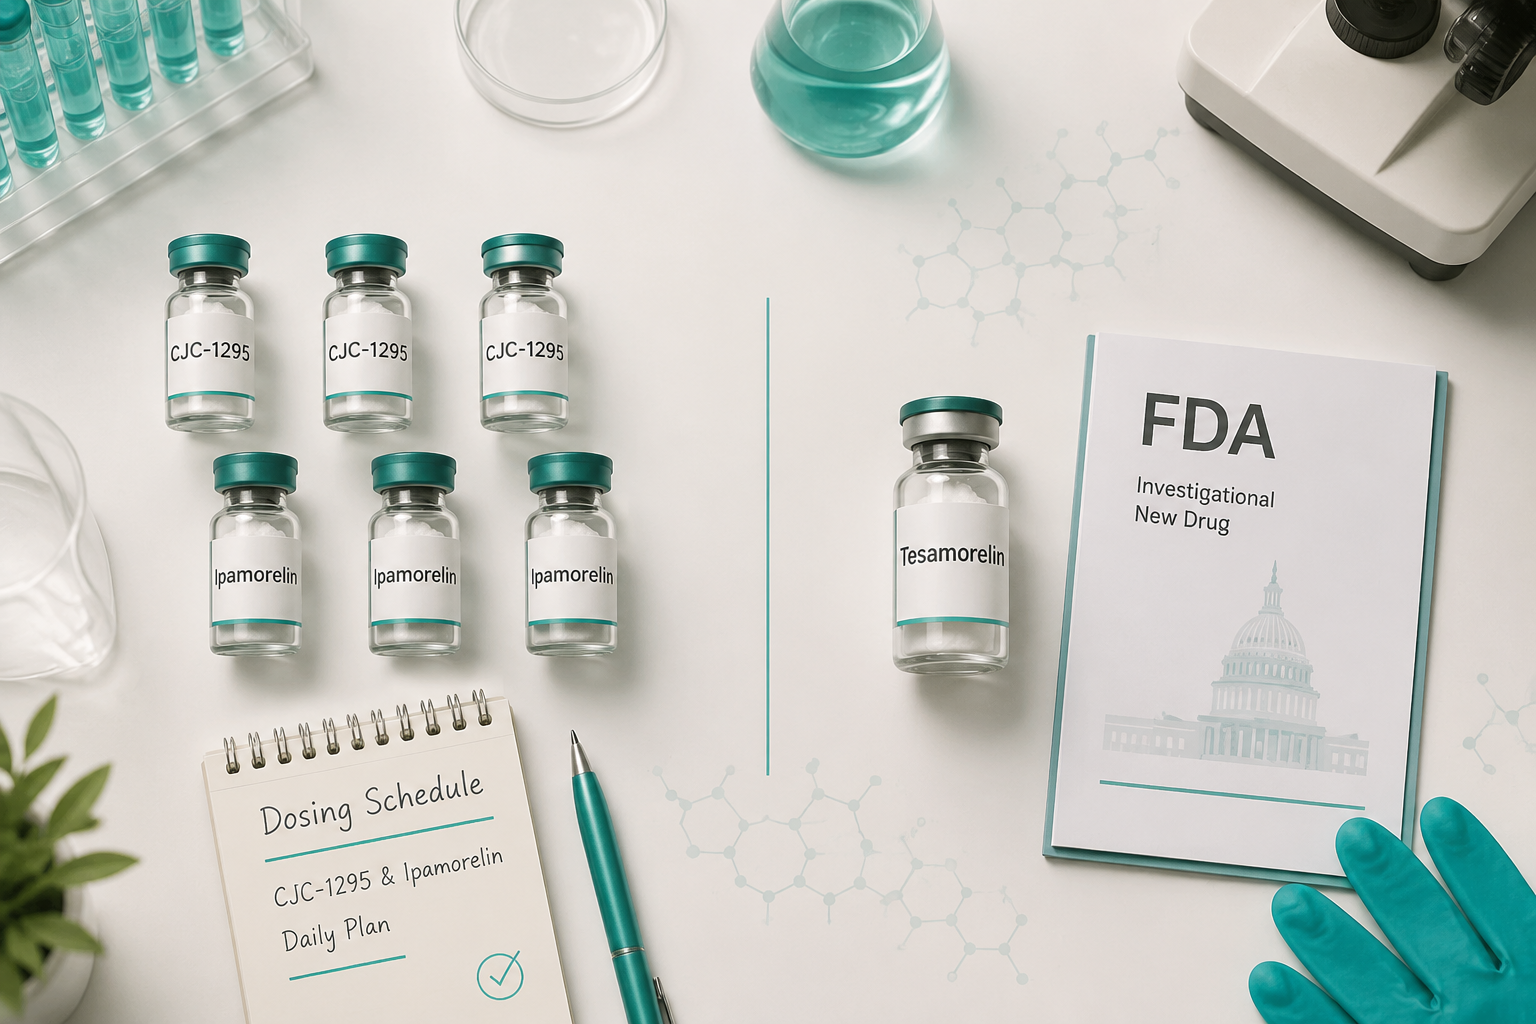
  • Tesamorelin is the only FDA-approved GHRH analog, backed by multiple randomized controlled trials confirming visceral fat reduction.
  • The dual-peptide stack offers more flexible dosing protocols; Tesamorelin follows a fixed, well-validated clinical regimen.
  • Side-effect profiles differ meaningfully: Ipamorelin's selectivity avoids cortisol and prolactin spikes, while Tesamorelin's risks are thoroughly documented from clinical trial data.
  • Choosing between these options depends on the specific research question, dual-pathway GH modulation versus targeted visceral adiposity outcomes.

Mechanisms of Action: How Each Approach Stimulates GH

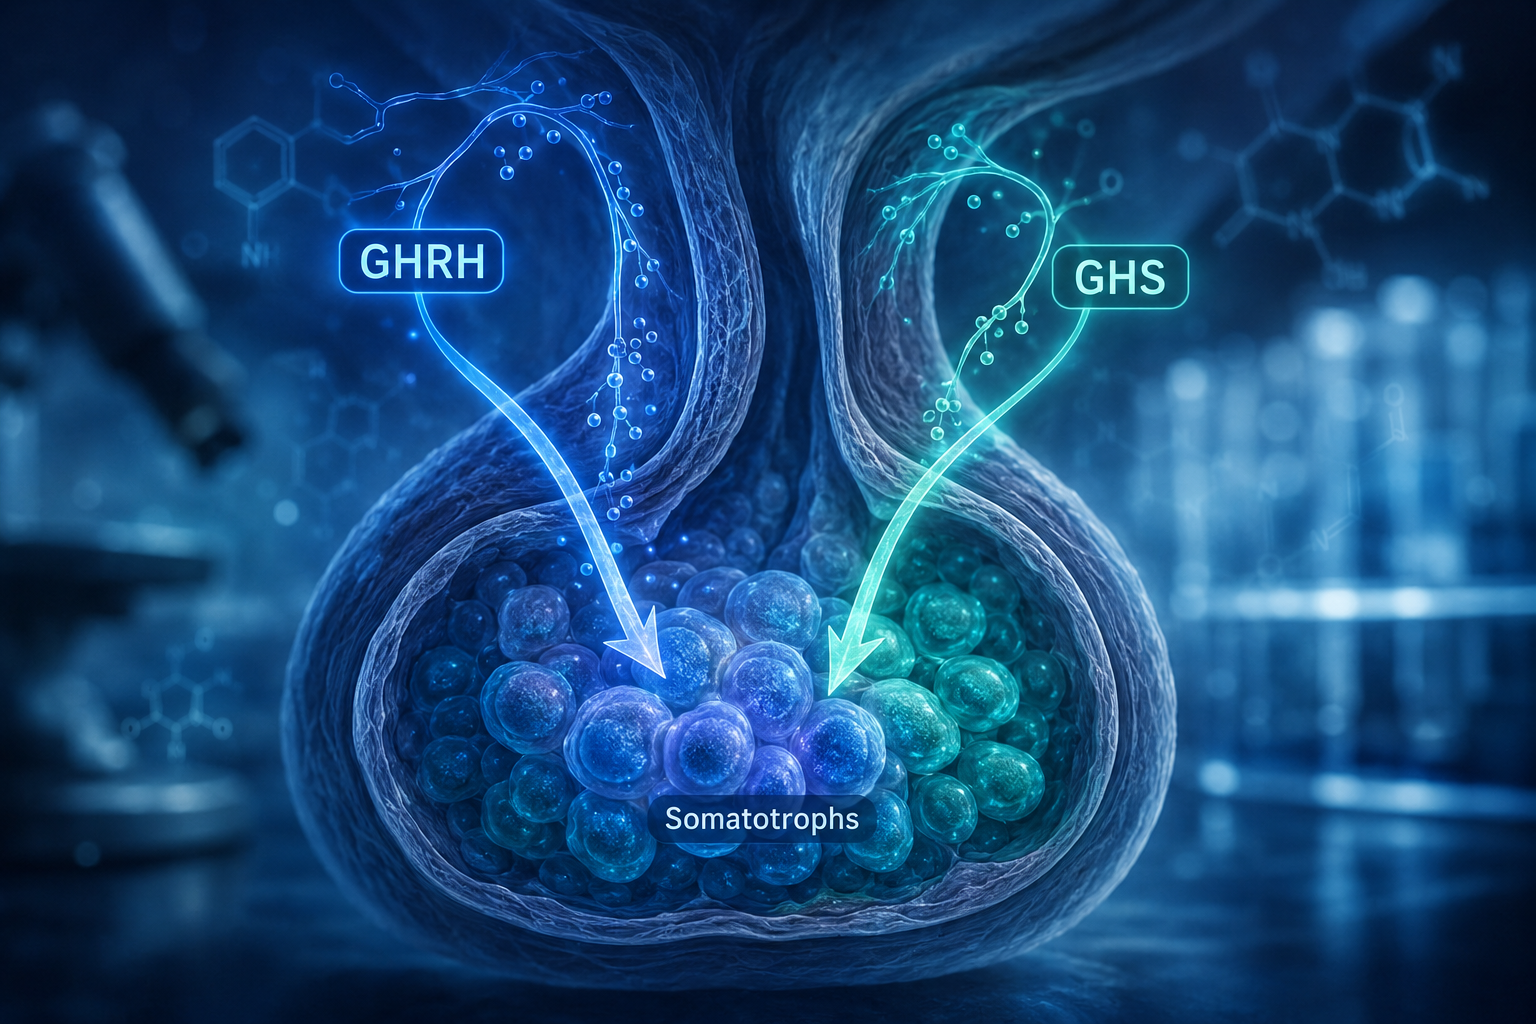
CJC-1295 is a synthetic GHRH analog that binds GHRH receptors on pituitary somatotroph cells, prompting them to synthesize and release growth hormone. Its standard (non-DAC) form carries a half-life of roughly 30 minutes, closely mimicking the natural GHRH pulse. Researchers interested in CJC-1295 research findings will note that the DAC-modified version extends the half-life dramatically but at the cost of disrupting the pulsatile GH pattern.

Ipamorelin operates through a completely different receptor. Originally developed by Novo Nordisk, it is a selective ghrelin receptor agonist, a Growth Hormone Secretagogue (GHS), with a half-life of approximately two hours. Critically, it does not elevate cortisol or prolactin at research-relevant doses, a selectivity advantage that older GHRPs lack. Explore the Ipamorelin research profile for a deeper look at its receptor pharmacology.

Tesamorelin is a synthetic GHRH analog comprising all 44 amino acids of human GHRH plus a trans-3-hexenoic acid group attached at the N-terminus. This structural modification boosts receptor binding affinity and provides modest resistance to dipeptidyl peptidase-IV (DPP-IV) cleavage. Its half-life ranges from 26 to 38 minutes, similar to native GHRH, yet its clinical performance is meaningfully stronger than unmodified GHRH.

"The synergistic interaction between GHRH-pathway and ghrelin-pathway signaling creates a permissive window that amplifies GH output beyond what either peptide achieves alone."


Synergistic Effects and Research Applications of the CJC-1295 with Ipamorelin vs. Tesamorelin Comparison

Synergistic Effects and Research Applications of the CJC-1295 with Ipamorelin vs. Tesamorelin Comparison

The Dual-Pathway Advantage of the Stack

When CJC-1295 and Ipamorelin are co-administered, they act on two distinct receptor populations on the same somatotroph cell. CJC-1295 activates the GHRH receptor; Ipamorelin activates the ghrelin receptor (GHS-R1a). The result is a synergistic amplification of GH pulse amplitude while preserving the natural pulsatile secretion pattern, a research-relevant feature because pulsatility governs downstream IGF-1 signaling and metabolic effects.

This combination is the most widely used GH peptide stack in anti-aging research settings. Typical research protocols administer 100-300 mcg of each peptide in a single subcutaneous injection, one to three times daily, often timed before sleep to align with endogenous GH peaks. Cycles commonly run 8-12 weeks on a 5-days-on, 2-days-off schedule.

For researchers exploring broader peptide combination strategies, the Sermorelin, Ipamorelin, and CJC-1295 stack overview provides useful context on stacking GHRH analogs with secretagogues.

Tesamorelin's Targeted Research Niche

Tesamorelin's research value is concentrated and well-defined. It received FDA approval in 2010 under the brand name Egrifta for HIV-associated lipodystrophy, making it the only GH-axis peptide with a validated clinical indication. Multiple randomized controlled trials using CT-measured visceral fat as an endpoint confirm its efficacy in reducing abdominal adiposity.

For researchers focused on visceral fat outcomes, the tesa dosage for fat loss resource outlines the validated 2 mg subcutaneous daily protocol with abdominal injection site rotation.

The trade-off is scope: Tesamorelin's evidence base is deep but narrow. The CJC-1295/Ipamorelin stack has broader exploratory application but far less published clinical-trial data supporting body composition outcomes specifically.

Feature CJC-1295 + Ipamorelin Tesamorelin
FDA Approval No Yes (2010, Egrifta)
Half-Life ~30 min / ~2 hr 26-38 min
Mechanism GHRH + GHS dual-pathway GHRH analog only
Primary Research Use Broad GH modulation Visceral fat reduction
Clinical RCT Data Limited Multiple trials

Choosing the Right Option: Practical Guidance for Researchers Comparing CJC-1295 with Ipamorelin vs. Tesamorelin

Choosing the Right Option: Practical Guidance for Researchers Comparing CJC-1295 with Ipamorelin vs. Tesamorelin

Matching Peptide Choice to Research Objectives

Choose the CJC-1295/Ipamorelin stack when:

  • The research question involves broad GH pulse modulation
  • Dual-pathway receptor pharmacology is the focus
  • Flexible dosing frequency is operationally important
  • Cortisol and prolactin neutrality is a study requirement

Choose Tesamorelin when:

  • Visceral adiposity is the primary endpoint
  • Regulatory-grade clinical precedent is required
  • A single-compound, once-daily protocol simplifies the study design
  • Comparison to FDA-approved benchmarks is methodologically necessary

Researchers comparing these agents against other GHRH-related compounds may also find value in the tesa vs. sermorelin comparison and the broader tesa research sourcing guide.

Blend Formulations as a Third Path

A growing area of interest involves pre-formulated blends that combine all three peptides. The Tesamorelin, CJC-1295, and Ipamorelin 12 mg blend consolidates the GHRH analog and GHS mechanisms into a single research compound, reducing preparation complexity. Detailed dosage guidance for the 12 mg blend is available for researchers designing protocols around this formulation.


Conclusion

The CJC-1295 with Ipamorelin vs. Tesamorelin question does not have a single universal answer, it has a research-design answer. The dual-peptide stack delivers synergistic, pulsatile GH stimulation through complementary receptor pathways, making it the more versatile tool for exploratory GH-axis research. Tesamorelin offers something the stack cannot: a validated, FDA-backed clinical record with reproducible visceral fat endpoints.

Actionable next steps for researchers in 2026:

  1. Define the primary endpoint before selecting a compound, body composition, GH pulse amplitude, or receptor pharmacology each favor a different agent.
  2. Review the IPA and Sermorelin stack research overview to benchmark against adjacent peptide combinations.
  3. Consult the tesa daily dosage protocols to ensure any Tesamorelin study arm aligns with established clinical parameters.
  4. Consider pre-blended formulations when protocol simplicity and multi-pathway coverage are both priorities.

Rigorous peptide research begins with matching the compound's mechanism to the study's question, and on that basis, both options have a legitimate, distinct place in the modern growth hormone research toolkit.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/cjc-1295-with-ipamorelin-vs-tesa-which-ghrh-mimetic-stack-is-best-for-you.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-12 13:03:352026-07-20 15:00:14CJC-1295 with Ipamorelin vs. Tesamorelin: Which GHRH Mimetic Stack is Best for Your Research?
5-Amino-1MQ Peptide: Investigating Its Role in NAD+ Metabolism and Sirtuin Activation

5-Amino-1MQ Peptide: Investigating Its Role in NAD+ Metabolism and Sirtuin Activation

July 12, 2026/0 Comments/by Pure Tested

Nicotinamide N-methyltransferase (NNMT) consumes up to 30% of available methyl groups in metabolically active tissues, a biochemical drain that quietly suppresses NAD+ availability and silences longevity-linked sirtuin enzymes. Understanding how 5-Amino-1MQ Peptide: Investigating Its Role in NAD+ Metabolism and Sirtuin Activation has become one of the more compelling areas in metabolic research circles, precisely because this small-molecule inhibitor targets that enzymatic bottleneck at its source.

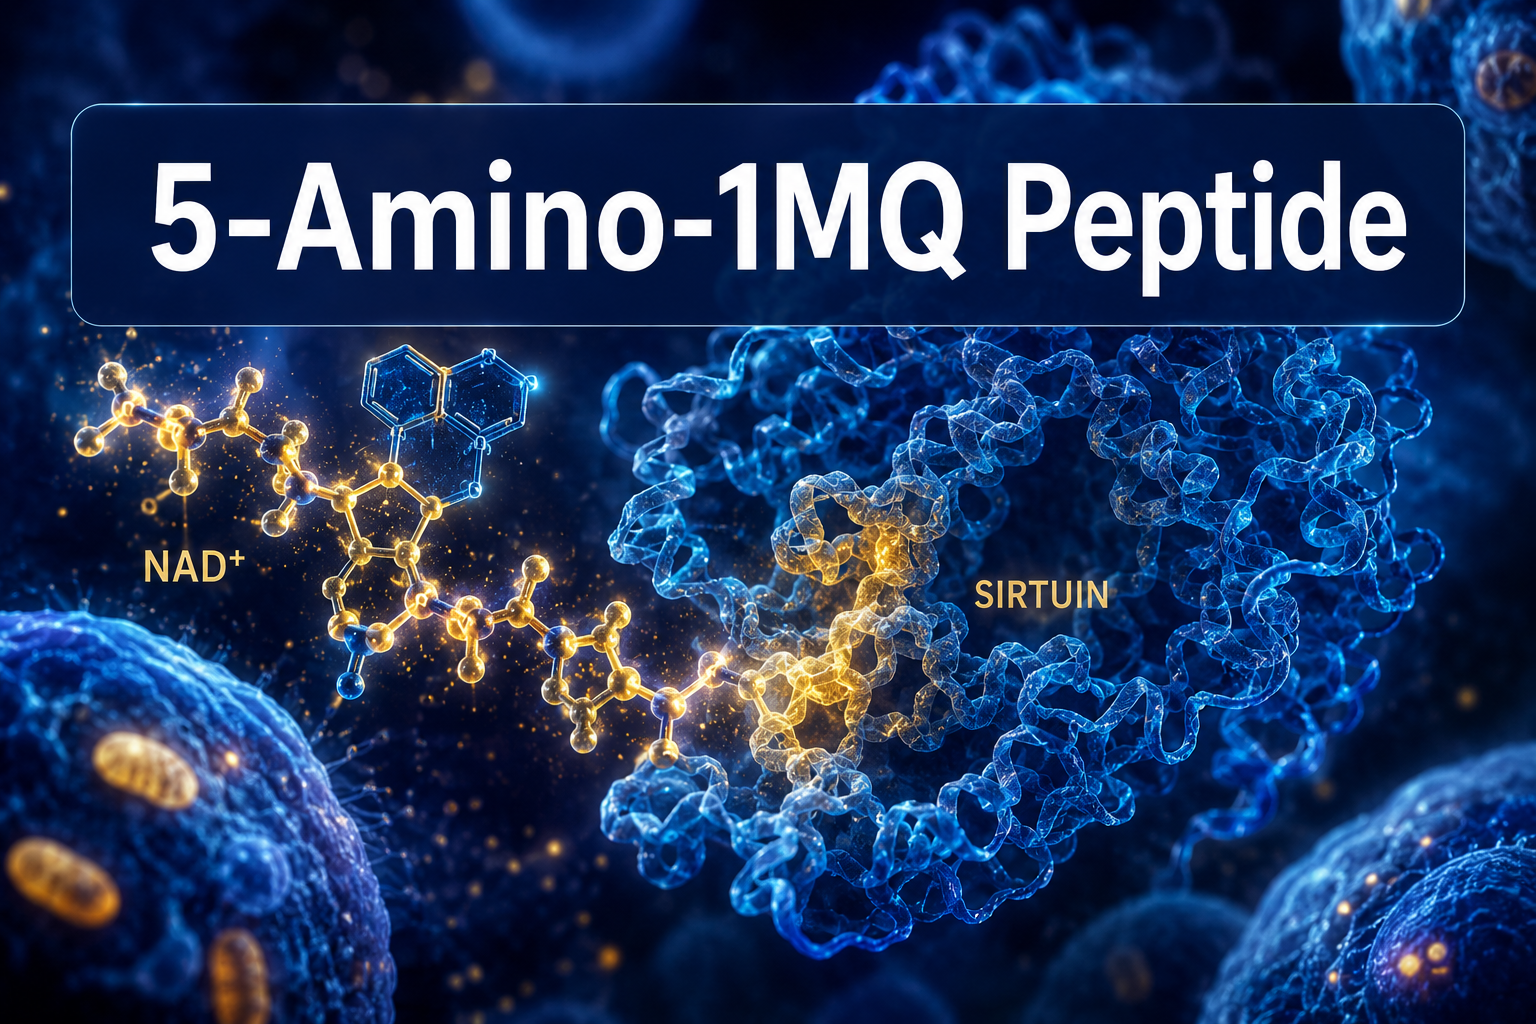
Professional () hero image with '5-Amino-1MQ Peptide' in large white on a deep semi-transparent navy bar, centered in upper

Key Takeaways

  • 5-Amino-1MQ is a selective NNMT inhibitor that works by blocking the enzyme responsible for excess NAD+ precursor consumption.
  • By inhibiting NNMT, the compound raises intracellular NAD+ levels, which directly fuels sirtuin enzyme activity.
  • Sirtuins (SIRT1-SIRT7) depend on NAD+ as a co-substrate; higher NAD+ availability translates to greater deacetylase and metabolic regulatory activity.
  • Preclinical research models suggest downstream effects on fat cell differentiation, mitochondrial function, and cellular energy balance.
  • Purity and sourcing quality are critical variables when evaluating any research-grade compound, including 5-Amino-1MQ.

How 5-Amino-1MQ Inhibits NNMT: The Mechanism Explained

How 5-Amino-1MQ Inhibits NNMT: The Mechanism Explained

NNMT catalyzes the methylation of nicotinamide, converting it into 1-methylnicotinamide (MNA) using S-adenosylmethionine (SAM) as the methyl donor. This reaction has two costly consequences: it depletes the methyl pool and removes nicotinamide from the NAD+ biosynthesis pathway.

5-Amino-1MQ (5-amino-1-methylquinolinium) is a quaternary ammonium compound designed to fit into the substrate-binding pocket of NNMT. Its structural features allow it to competitively occupy that pocket without being methylated itself, effectively stalling the enzyme's activity.

Key structural advantages include:

  • A quinolinium ring system that mimics nicotinamide's binding geometry
  • A positively charged nitrogen that anchors the molecule within the active site
  • A 5-amino substituent that enhances binding affinity and selectivity for NNMT over related methyltransferases

When NNMT is inhibited, nicotinamide is redirected toward the NAD+ salvage pathway, where NAMPT (nicotinamide phosphoribosyltransferase) converts it into NMN and ultimately into NAD+. The result is a measurable rise in intracellular NAD+ concentrations in research cell models.

For researchers exploring related longevity peptide research, this mechanism represents a distinct upstream intervention compared to direct NAD+ precursor supplementation strategies.


NAD+ Metabolism: What Changes Downstream of NNMT Inhibition

NAD+ Metabolism: What Changes Downstream of NNMT Inhibition

Raising NAD+ is not a single-step event, it cascades through multiple metabolic systems. When 5-Amino-1MQ Peptide: Investigating Its Role in NAD+ Metabolism and Sirtuin Activation is studied in preclinical models, researchers observe several downstream shifts:

Downstream Effect Observed Direction Relevant Pathway
Intracellular NAD+ levels Increase Salvage pathway
SAM availability Increase Methyl donor pool
Adipogenesis markers Decrease PPAR-gamma signaling
Mitochondrial biogenesis Upregulated PGC-1alpha axis
Cellular energy charge Improved AMPK activation

Adipocyte differentiation is one of the most studied downstream targets. NNMT is highly expressed in white adipose tissue, and its inhibition appears to reduce the conversion of precursor cells into mature fat cells in vitro. This links the compound to broader metabolic modulation research programs examining body composition at the cellular level.

Mitochondrial function is another area of active inquiry. NAD+ is an essential electron carrier in the mitochondrial electron transport chain. Higher NAD+ availability supports more efficient ATP production, which may explain observed improvements in cellular energy markers in treated research models.

"NAD+ is not merely a coenzyme, it is a signaling currency that coordinates metabolism, DNA repair, and gene expression across virtually every cell type."


Sirtuin Activation: The Longevity Pathway Downstream of 5-Amino-1MQ

Sirtuin Activation: The Longevity Pathway Downstream of 5-Amino-1MQ

Sirtuins are a family of seven NAD+-dependent deacylase enzymes (SIRT1 through SIRT7). They require NAD+ as a co-substrate, not just a cofactor, meaning they consume one molecule of NAD+ for every deacetylation reaction they catalyze. When NAD+ levels fall, sirtuin activity falls with them.

This is where 5-Amino-1MQ Peptide: Investigating Its Role in NAD+ Metabolism and Sirtuin Activation becomes particularly relevant to longevity-focused research. By restoring NAD+ availability through NNMT inhibition, the compound indirectly reactivates sirtuin pathways that tend to decline with age or metabolic stress.

Sirtuin functions relevant to this mechanism:

  • SIRT1, Regulates glucose and lipid metabolism; activates PGC-1alpha for mitochondrial biogenesis
  • SIRT3, Mitochondria-resident; deacetylates electron transport chain components
  • SIRT6, DNA repair and telomere maintenance
  • SIRT7, Ribosomal gene expression and stress response

Researchers studying aging support compounds often place sirtuin activation alongside other longevity-relevant targets. The NNMT-NAD+-sirtuin axis represents a coherent, mechanistically grounded pathway rather than a speculative one.

Comparisons with other mitochondria-targeting compounds, such as those reviewed in SS-31 mitochondrial research, illustrate that multiple complementary mechanisms exist for supporting cellular energy homeostasis, each acting at a different node.

For broader context on where 5-Amino-1MQ fits within the research landscape, the 5-Amino-1MQ research overview provides additional background on current investigational directions.

Researchers interested in compound purity, a critical variable in any mechanistic study, should review available peptide purity testing resources before sourcing materials for in vitro or preclinical work.

Those exploring complementary longevity-related compounds may also find the longevity peptide research series a useful reference for situating NNMT inhibition within wider anti-aging research frameworks.


Conclusion

The mechanistic case for 5-Amino-1MQ centers on a precise enzymatic intervention: blocking NNMT to redirect nicotinamide toward NAD+ biosynthesis and restore the co-substrate availability that sirtuin enzymes require to function. Preclinical research models consistently show downstream effects on adipogenesis, mitochondrial efficiency, and cellular energy signaling, making this compound a structurally rational tool for studying the NNMT-NAD+-sirtuin axis.

Actionable next steps for researchers:

  1. Review published NNMT inhibitor studies to establish baseline efficacy parameters before designing experiments.
  2. Confirm compound purity through third-party certificate of analysis documentation before use.
  3. Pair 5-Amino-1MQ investigations with validated NAD+ quantification assays to measure pathway response directly.
  4. Consider complementary mechanistic targets, such as mitochondrial membrane dynamics, when designing multi-pathway longevity research protocols.

The science surrounding this compound is still developing, but the mechanistic foundation is clear enough to justify continued, rigorous preclinical investigation.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/5-amino-1mq-peptide-investigating-its-role-in-nad-metabolism-and-sirtuin-activat.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-12 13:02:592026-07-20 15:00:155-Amino-1MQ Peptide: Investigating Its Role in NAD+ Metabolism and Sirtuin Activation
Understanding Peptide Purity and Impurities: A Guide for Research-Grade GLP-3 Retatrutide

Understanding Peptide Purity and Impurities: A Guide for Research-Grade GLP-3 Retatrutide

July 12, 2026/0 Comments/by Pure Tested

Fewer than 30% of research failures involving synthetic peptides are traced back to protocol errors, the majority stem from compromised compound quality that was never detected before the experiment began. For researchers working with complex triple-agonist molecules, understanding peptide purity and impurities: a guide for research-grade GLP-3 Retatrutide is not optional reading. It is a prerequisite for generating data that holds up to scrutiny.

Key Takeaways

  • Peptide purity directly affects experimental reproducibility and the validity of research outcomes.
  • Common impurities in synthetic peptides include deletion sequences, oxidized residues, and residual solvents.
  • A Certificate of Analysis (COA) is the primary tool for evaluating research-grade peptide quality.
  • HPLC purity of 98% or greater is the accepted benchmark for reliable research-grade peptides.
  • Proper storage and handling preserve purity after the vial leaves the manufacturer.

Key Takeaways

What Makes Peptide Purity Critical for GLP-3 Retatrutide Research

Retatrutide is a 39-amino-acid peptide that simultaneously targets GLP-1, GIP, and glucagon receptors. Its structural complexity makes it more susceptible to synthesis-related impurities than shorter, simpler peptides. Even minor contaminants can bind off-target receptors, alter dose-response curves, or trigger inflammatory artifacts in cell-based assays.

Researchers sourcing material for in vitro or preclinical work should treat purity as a primary variable, not an afterthought. For context on how reference standards and benchmarks are established across the peptide research field, the resource on Bachem and reference standards for peptide benchmarks provides a useful foundation.

The 98% Purity Threshold

The research community broadly accepts 98% HPLC purity as the minimum standard for peptides used in quantitative assays. Below this threshold:

  • Impurities may represent 1 in 50 molecules in solution
  • Biological activity measurements become unreliable
  • Batch-to-batch reproducibility drops significantly

For a peptide as structurally demanding as Retatrutide, some researchers prefer 99%+ purity to reduce noise in receptor-binding studies.

Common Impurities Found in Synthetic Peptides

Understanding peptide purity and impurities in research-grade GLP-3 Retatrutide requires knowing exactly what contaminants to look for. Impurities in synthetic peptides fall into three main categories:

Impurity Type Origin Risk to Research
Deletion sequences Incomplete coupling during synthesis Altered receptor binding
Oxidized residues Methionine/tryptophan oxidation Reduced biological activity
Residual solvents Incomplete purification Cytotoxicity in cell assays
Aggregates Improper lyophilization Inconsistent solubility
Acetylation artifacts Capping reagent carryover False activity signals

Deletion sequences are the most common impurity. They arise when a single amino acid coupling step fails during solid-phase synthesis, producing a truncated chain that is one or more residues shorter than the target molecule.

Oxidized methionine is particularly relevant for Retatrutide because oxidation can occur during storage if the peptide is exposed to moisture or oxygen. This is one reason proper lyophilization and cold-chain storage matter as much as the synthesis itself.

Researchers working with other peptide classes such as AOD-9604 research methods and storage will recognize that these same impurity categories apply broadly across synthetic peptides.

Common Impurities Found in Synthetic Peptides

How to Read a COA for Research-Grade GLP-3 Retatrutide

A Certificate of Analysis (COA) is the primary quality document for any research peptide. When evaluating a COA for Retatrutide, look for these specific data points:

  1. HPLC chromatogram, The main peak area percentage should be clearly stated and visually dominant. Request the raw chromatogram, not just a number.
  2. Mass spectrometry confirmation, The observed molecular weight should match the theoretical mass of Retatrutide (approximately 4,531 Da). This confirms the correct sequence was synthesized.
  3. Water content (Karl Fischer), Lyophilized peptides typically contain 5-12% water by weight. High water content reduces the effective peptide dose per milligram.
  4. Residual solvent testing, Confirms that acetonitrile and TFA from the purification process have been removed to safe levels.
  5. Lot-specific data, A legitimate COA is lot-specific, not a generic document reused across batches.

"A COA without a lot number is not a COA, it is a marketing document."

Researchers can review verified COA documentation standards to understand what a properly formatted quality document should contain.

For additional context on how purity standards apply to other research peptides, the GLP-1 Retatrutide product page and the Reta 10mg product tag offer relevant sourcing information.

Storage Conditions That Preserve Purity

Even a 99% pure peptide degrades rapidly under poor storage conditions. Follow these guidelines:

  • Store lyophilized peptide at -20C or colder
  • Avoid repeated freeze-thaw cycles (aliquot before first use)
  • Reconstitute only the volume needed for immediate use
  • Use sterile bacteriostatic water or DMSO as appropriate for the assay

These principles apply across the research peptide category. For example, the same cold-chain logic governs SS-31 peptide research considerations and other sensitive compounds.

Storage Conditions That Preserve Purity

Sourcing and Verification Best Practices

Understanding peptide purity and impurities in a guide for research-grade GLP-3 Retatrutide ultimately comes down to sourcing decisions. Researchers should apply the following checklist before committing to a supplier:

  • Does the supplier provide lot-specific COAs with HPLC and MS data?
  • Is the synthesis performed under GMP-aligned conditions?
  • Are third-party analytical results available on request?
  • Does the supplier use HPLC-grade solvents and validated purification columns?

Researchers planning multi-peptide protocols, such as those combining GLP-class compounds with growth hormone secretagogues, should also review resources like the IPA-Sermorelin stack research guide to understand how purity standards interact across compound combinations.

For those evaluating broader catalog options, the GLP-3 for sale research planning guide provides practical sourcing and planning context specific to triple-agonist peptides.

Conclusion

Peptide purity is not a background variable, it is a core experimental parameter. For researchers working with structurally complex molecules like Retatrutide, even a 2-3% impurity burden can introduce confounding signals that invalidate assay results. The actionable steps are clear: demand lot-specific COAs with both HPLC and mass spectrometry data, verify the molecular weight against the theoretical value, confirm proper storage conditions from synthesis through delivery, and aliquot immediately upon receipt to prevent degradation. Treating purity verification as a standard pre-experiment step, alongside buffer preparation and calibration, is what separates reproducible research from wasted resources.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/understanding-peptide-purity-and-impurities-a-guide-for-research-grade-glp-3-ret.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-12 13:02:542026-07-20 15:00:16Understanding Peptide Purity and Impurities: A Guide for Research-Grade GLP-3 Retatrutide
GLP3 Peptide vs. Retatrutide: Understanding the Nomenclature and Research Implications

GLP3 Peptide vs. Retatrutide: Understanding the Nomenclature and Research Implications

July 12, 2026/0 Comments/by Pure Tested

Researchers searching for "GLP3 peptide" in 2026 are often looking for the same compound, yet the terminology they use can lead them to entirely different bodies of literature, products, and regulatory contexts. The conversation around GLP3 Peptide vs. Retatrutide: Understanding the Nomenclature and Research Implications matters because imprecise language in peptide science does not just cause confusion; it can distort research intent, misalign sourcing decisions, and obscure a compound's actual clinical standing.

Editorial () showing a conceptual split-screen illustration: left half features the text label 'GLP-3 Descriptor' in over an

Key Takeaways

  • "GLP-3" is an informal, community-driven descriptor, not an official scientific classification for retatrutide.
  • Retatrutide is a specific triple agonist targeting GLP-1, GIP, and glucagon receptors, developed by Eli Lilly.
  • Phase 3 trials show up to 28.7% mean body weight reduction over approximately 68 weeks.
  • As of 2026, retatrutide has not received FDA approval and carries no official brand name.
  • Understanding this nomenclature gap is critical for accurate research, sourcing, and clinical interpretation.

What "GLP-3" Actually Means, and What It Does Not

The label "GLP-3" did not originate in a peer-reviewed journal or a regulatory filing. It emerged organically in biohacking communities and research forums as shorthand for retatrutide's triple-receptor mechanism, activating glucagon-like peptide-1 (GLP-1), glucose-dependent insulinotropic polypeptide (GIP), and glucagon receptors simultaneously.

This is a meaningful distinction. GLP-1 and GLP-2 are actual endogenous peptides with defined biological roles. There is no naturally occurring "GLP-3" in human physiology. When researchers or enthusiasts use the term, they are borrowing the naming convention to signal a step beyond dual agonists like tirzepatide, not describing a distinct peptide family.

"GLP-3" functions as a category label born from search behavior, not from biochemistry.

For anyone exploring the newest GLP-1 triple agonist research, recognizing this distinction prevents conflating informal community terminology with peer-reviewed compound classifications. Related resources on GLP-3 and Retatrutide provide further context on how this terminology has evolved in the research space.


Retatrutide: The Compound Behind the Label

Retatrutide is a once-weekly subcutaneous injection developed by Eli Lilly. Its mechanism is what drives the "GLP-3" nickname, by activating three metabolic receptors at once, it amplifies both appetite suppression and energy expenditure beyond what single or dual agonists can achieve.

Clinical trial results have been striking:

  • Phase 2 trials demonstrated a mean body weight reduction of 24.2% at 48 weeks using a 12 mg dose.
  • Phase 3 data from the TRIUMPH program reported up to 28.7% weight loss over approximately 68 weeks.
  • These figures surpass outcomes associated with semaglutide (Ozempic/Wegovy) and tirzepatide (Mounjaro/Zepbound).

Common side effects observed in trials include:

  • Nausea
  • Diarrhea
  • Vomiting
  • Constipation

Discontinuation rates at higher doses ranged from roughly 12-18%, compared to approximately 4% for placebo, a consideration for any research protocol design.

As of 2026, retatrutide remains in Phase 3 trials and has not been approved by the FDA. Eli Lilly is expected to pursue approval pending successful trial completion, possibly by the end of 2026. It currently carries no official brand name.

For researchers interested in how metabolic peptides interact with broader longevity pathways, the longevity peptide research overview offers relevant context. Those examining synergistic mechanisms may also find value in reviewing cagrilintide synergy with GLP-1 as a comparative framework.

Retatrutide: The Compound Behind the Label


Why the Nomenclature Gap Has Real Research Implications

Understanding GLP3 Peptide vs. Retatrutide: Understanding the Nomenclature and Research Implications is not purely academic. The terminology used when sourcing, citing, or designing studies around this compound has downstream consequences.

Three key implications stand out:

  1. Search intent misalignment, Researchers querying "GLP-3 peptide" may encounter products or literature that conflate the informal term with unrelated compounds, creating sourcing errors.
  2. Regulatory blind spots, Because retatrutide has no approved brand name yet, informal labels like "GLP-3" or "Reta" circulate in research communities without the traceability that official nomenclature provides.
  3. Comparative analysis errors, Treating "GLP-3" as equivalent to "triple agonist" as a class, rather than as a nickname for one specific molecule, can skew meta-analyses or literature reviews.

Researchers working with metabolic peptides should cross-reference compound identifiers carefully. Resources covering NAD research and where to buy peptides online illustrate how sourcing decisions intersect with nomenclature clarity in the broader peptide research space.

For those tracking the full pipeline of investigational metabolic compounds, reviewing tesofensine peptide research and MOTS-c mitochondrial research themes provides useful comparative framing for how novel compounds acquire informal labels before formal approval.

Why the Nomenclature Gap Has Real Research Implications


Conclusion

The debate around GLP3 Peptide vs. Retatrutide: Understanding the Nomenclature and Research Implications ultimately comes down to precision. Retatrutide is a well-defined, clinically investigated compound with Phase 3 data supporting extraordinary weight loss outcomes. "GLP-3" is a useful shorthand, but only when both parties in a research conversation understand it as informal nomenclature, not a recognized scientific category.

Actionable next steps for researchers and practitioners:

  • Always use "retatrutide" as the primary identifier in formal documentation, protocols, and sourcing requests.
  • Treat "GLP-3" and "Reta" as search and community terms, helpful for discovery, unreliable for precision.
  • Monitor the TRIUMPH Phase 3 program and FDA submission timelines, as approval could reshape how the compound is officially labeled and referenced.
  • Cross-reference any sourced material against verified compound identifiers to avoid conflation with unrelated peptides.

Clarity in nomenclature is not a minor detail, in peptide research, it is the foundation of reproducible, credible science.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/glp3-peptide-vs-retatrutide-understanding-the-nomenclature-and-research-implicat.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-12 13:02:542026-07-20 15:00:16GLP3 Peptide vs. Retatrutide: Understanding the Nomenclature and Research Implications
GLP-2-T Peptide: Unraveling Its Impact on Gut Microbiome and Intestinal Homeostasis Research

GLP-2-T Peptide: Unraveling Its Impact on Gut Microbiome and Intestinal Homeostasis Research

July 11, 2026/0 Comments/by Pure Tested

Fewer than one in ten adults with short bowel syndrome have access to targeted peptide-based therapies, yet the molecule at the center of that treatment gap, GLP-2, is now revealing a far broader story. Research in 2026 increasingly focuses on GLP-2-T peptide: unraveling its impact on gut microbiome and intestinal homeostasis research has become one of the most active frontiers in gastrointestinal science, moving well beyond barrier repair into the dynamic world of microbial ecology.

Editorial () showing a detailed scientific illustration of a 33-amino acid peptide chain labeled 'GLP-2' in white text (5

Key Takeaways

  • GLP-2-T is a next-generation analog of the naturally occurring 33-amino acid gut hormone GLP-2, with enhanced stability and receptor activity.
  • It binds the GLP-2 receptor (GLP-2R) to stimulate crypt cell proliferation, reduce apoptosis, and increase intestinal mass.
  • Preclinical data show GLP-2 treatment can shift gut microbiota composition, reducing pathogenic genera while boosting beneficial bacteria.
  • GLP-2-T strengthens intestinal barrier integrity by tightening epithelial junctions and limiting systemic inflammation.
  • Therapeutic research now spans short bowel syndrome, inflammatory bowel disease, chemotherapy-induced mucositis, and emerging metabolic applications.

What Is GLP-2-T and How Does It Work

GLP-2 is a 33-amino acid peptide hormone secreted from intestinal L-cells alongside GLP-1 in direct response to nutrient intake. While GLP-1 governs glucose regulation and appetite, a topic explored in detail in the generations of GLP-1 differences overview, GLP-2 focuses specifically on intestinal growth and repair. GLP-2-T refers to a stabilized, truncation-resistant analog engineered to extend the peptide's short plasma half-life and amplify receptor engagement.

The mechanism is precise. GLP-2-T binds the GLP-2 receptor (GLP-2R), activating downstream signaling cascades that:

  • Stimulate crypt cell proliferation, expanding the intestinal epithelial surface
  • Inhibit enterocyte apoptosis, preserving mucosal architecture
  • Enhance nutrient absorption, increasing functional digestive capacity
  • Modulate nitric oxide pathways, supporting intestinal lipid absorption and chylomicron secretion

This receptor-driven mechanism is what makes GLP-2-T distinct from broader gut-healing peptides. Researchers comparing it to multi-target compounds like BPC-157 note that GLP-2-T's action is highly tissue-specific, concentrated in the small intestine and proximal colon.

"GLP-2-T's receptor specificity allows researchers to isolate intestinal growth signals from systemic metabolic noise, a critical advantage in controlled preclinical models."


GLP-2-T Peptide: Unraveling Its Impact on Gut Microbiome Composition

This is where the science becomes particularly compelling. Preclinical studies using Sprague-Dawley rat models demonstrated that GLP-2 treatment produced a measurable shift in gut microbiota composition. Aged rats showed a significant reduction in pathogenic bacterial genera alongside a concurrent increase in beneficial commensal populations. These findings suggest that GLP-2-T's influence on intestinal homeostasis extends beyond the epithelial layer into the microbial ecosystem itself.

GLP-2-T Peptide: Unraveling Its Impact on Gut Microbiome Composition

The proposed mechanisms linking GLP-2-T to microbiome modulation include:

Pathway Proposed Effect
Reduced epithelial permeability Less translocation of pro-inflammatory lipopolysaccharides
Increased mucosal surface area More habitat for beneficial anaerobes
Reduced luminal inflammation Selective pressure favoring commensal species
Enhanced mucus layer thickness Physical barrier supporting Lactobacillus and Bifidobacterium colonization

This bidirectional relationship, where GLP-2-T shapes the microbiome and the microbiome in turn influences L-cell secretion, mirrors patterns seen in research on other gut-active peptides. Those interested in multi-pathway gut and metabolic interactions may also find the KLow blend multi-pathway research discussion relevant to this systems-level view.


GLP-2-T Peptide: Intestinal Homeostasis Research and Therapeutic Potential

Maintaining intestinal homeostasis requires a constant balance between mucosal renewal, immune tolerance, and microbial stability. GLP-2-T addresses all three arms of this balance.

Barrier integrity is a primary focus. By tightening epithelial tight junctions and reducing paracellular permeability, GLP-2-T limits the translocation of bacterial antigens and endotoxins into systemic circulation, a process directly linked to chronic low-grade inflammation. This mechanism has drawn comparisons to the anti-inflammatory tissue-repair work documented in BPC-157 and TB-500 combination research.

GLP-2-T Peptide: Intestinal Homeostasis Research and Therapeutic Potential

Current therapeutic research areas include:

  • Short bowel syndrome, the basis for teduglutide (Gattex), the approved GLP-2 analog
  • Inflammatory bowel disease, reducing mucosal damage during active flares
  • Chemotherapy-induced mucositis, protecting rapidly dividing crypt cells from cytotoxic damage
  • Metabolic disorders, leveraging GLP-2-T's role in lipid absorption and chylomicron regulation

Beyond the gut, early data point to neuroprotective properties, including reduced neuronal apoptosis and potential neurogenesis support, an area being watched alongside broader peptide longevity research such as NAD+ energetics and longevity research themes.

For researchers sourcing compounds to study gut-active peptides, reviewing lab-tested peptide standards is an important step in ensuring experimental integrity. Those exploring the broader GLP receptor family should also review the GIP receptor and its importance for complementary context.


Conclusion

GLP-2-T peptide: unraveling its impact on gut microbiome and intestinal homeostasis research is no longer a niche pursuit, it sits at the intersection of mucosal immunology, microbial ecology, and metabolic medicine. The evidence to date supports a peptide that does far more than grow intestinal tissue. It actively reshapes the microbial environment, fortifies the epithelial barrier, and modulates lipid and inflammatory pathways simultaneously.

Actionable next steps for researchers:

  1. Review current preclinical microbiome shift data and identify gaps in human translational models.
  2. Compare GLP-2-T analog stability profiles against first-generation GLP-2 compounds in study design.
  3. Explore synergistic research designs pairing GLP-2-T with complementary gut-active peptides.
  4. Ensure all research-grade compounds are sourced from verified, lab-tested peptide suppliers to maintain data reproducibility.
  5. Monitor emerging data on GLP-2-T's neuroprotective and metabolic applications as the field expands.

The gut is not a passive organ, and GLP-2-T is not a passive molecule. As 2026 research continues to unfold, this peptide's role in shaping the body's internal ecosystem may prove to be one of the most significant stories in gastrointestinal science.


https://www.puretestedpeptides.com/wp-content/uploads/2026/07/glp-2-t-peptide-unraveling-its-impact-on-gut-microbiome-and-intestinal-homeostas.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-11 13:38:062026-07-20 15:00:17GLP-2-T Peptide: Unraveling Its Impact on Gut Microbiome and Intestinal Homeostasis Research
Where to Buy High-Purity Enclomiphene for Hormone Research: A Supplier Evaluation Guide

Where to Buy High-Purity Enclomiphene for Hormone Research: A Supplier Evaluation Guide

July 11, 2026/0 Comments/by Pure Tested

Fewer than 5% of researchers sourcing selective estrogen receptor modulators (serms) ever verify a supplier's third-party purity data before placing an order, a gap that can compromise an entire study. This guide to Where to Buy High-Purity Enclomiphene for Hormone Research: A Supplier Evaluation Guide addresses that gap directly, helping researchers navigate licensing requirements, purity benchmarks, and red flags that separate credible suppliers from risky ones.

Editorial landscape image () for the article section "Key Takeaways" about Where to Buy High-Purity Enclomiphene for Hormone

Key Takeaways

  • Enclomiphene is not FDA-approved and is legally available in the U.S. only through licensed compounding pharmacies with a valid prescription.
  • Any supplier offering enclomiphene without requiring a prescription is operating outside regulatory boundaries.
  • A Certificate of Analysis (COA) from an independent laboratory confirming purity above 98% is the minimum acceptable quality standard.
  • Pricing significantly below $100 per month is a reliable warning sign of substandard or mislabeled product.
  • Researchers sourcing other investigational compounds should apply the same rigorous supplier evaluation criteria used here.

Understanding Enclomiphene's Regulatory Status Before You Source

Enclomiphene is the trans-isomer of clomiphene citrate and acts as a selective estrogen receptor modulator with particular relevance to hypothalamic-pituitary-gonadal axis research. As of 2026, it remains unapproved by the FDA, meaning no commercially manufactured product exists on the U.S. market.

The only legal pathway for obtaining enclomiphene in the United States runs through licensed compounding pharmacies, and only when a licensed healthcare provider has issued a valid prescription. Compounding pharmacies prepare the compound to individual prescription specifications, operating under state pharmacy board oversight and, in many cases, federal USP standards.

Purchasing enclomiphene without a prescription, or from unregulated online vendors, may violate federal and state law. Researchers operating within institutional frameworks should confirm compliance with their IRB or legal counsel before procurement.

This regulatory context is the foundation of any honest supplier evaluation guide for high-purity enclomiphene hormone research.


Critical Supplier Evaluation Criteria for High-Purity Enclomiphene

Licensing and Accreditation

The first filter is simple: does the supplier hold verifiable credentials? For compounding pharmacies, look for:

  • State pharmacy board licensure (verifiable through the NABP database)
  • PCAB (Pharmacy Compounding Accreditation Board) accreditation
  • Compliance with USP 795 and 797 guidelines for non-sterile and sterile preparations

Suppliers lacking these credentials should be disqualified immediately, regardless of pricing or marketing claims.

Certificate of Analysis Requirements

A COA is non-negotiable. When evaluating any supplier, request documentation that confirms:

Parameter Minimum Standard
Compound identity Confirmed via HPLC or NMR
Purity Greater than 98%
Residual solvents Below ICH Q3C limits
Microbial contamination Absent or within USP limits
Issuing laboratory Independent, third-party accredited lab

Suppliers who cannot produce a COA from an independent laboratory, not an in-house document, should be avoided. Reviewing quality testing protocols used by reputable peptide suppliers provides a useful benchmark for what rigorous third-party documentation looks like.

Similarly, reviewing COA documentation standards from established research compound suppliers illustrates the level of transparency that serious researchers should demand.

Pricing as a Quality Signal

Legitimate pharmaceutical-grade compounding involves costly raw material sourcing, quality control testing, and regulatory compliance. Typical monthly pricing for compounded enclomiphene falls between $100 and $300. Products priced significantly below this range are a strong indicator of compromised raw materials, inadequate testing, or both.

"If the price seems too good to be true in pharmaceutical compounding, the quality almost certainly reflects it."


Evaluating Research Chemical Suppliers: Risks and Red Flags

Some online vendors sell enclomiphene labeled "for research use only," positioning themselves outside prescription requirements. This category warrants serious caution.

Key risks include:

  • No regulatory oversight of raw material sourcing
  • Purity claims unsupported by independent testing
  • Potential for contamination with related isomers (zuclomiphene) or process impurities
  • Legal exposure for the purchasing researcher or institution

Medical professionals and research compliance officers consistently advise against using research chemical-grade enclomiphene for any study intended to generate publishable or clinically relevant data.

Researchers familiar with the rigorous standards applied to compounds like gonadorelin and GnRH pulsatility research will recognize that hormonal axis research demands equivalent sourcing discipline for enclomiphene.

Evaluating Research Chemical Suppliers: Risks and Red Flags

Red Flags Checklist

  • No prescription verification required
  • COA unavailable or issued by the same company selling the product
  • No physical address or verifiable business registration
  • Vague or absent information about raw material sourcing
  • Prices below $80 per month for a 25-50mg daily dose formulation

Applying the Same Standards Across Hormone Research Compounds

The supplier evaluation framework developed here extends naturally to related investigational compounds. Researchers studying the broader endocrine system often work with growth hormone secretagogues, metabolic peptides, and longevity-related compounds alongside serms like enclomiphene.

For context, the same purity and documentation standards apply when sourcing compounds covered in resources like this overview of the GH axis product line or when reviewing MOTS-c metabolic flexibility research. The principles of independent COA verification, licensed sourcing, and transparent quality control are universal.

Researchers exploring Bachem reference standards and peptide benchmarks will find additional guidance on how pharmaceutical-grade benchmarking works in practice, directly applicable to evaluating any enclomiphene supplier's documentation.

Applying the Same Standards Across Hormone Research Compounds


Conclusion

The question of where to buy high-purity enclomiphene for hormone research has a clear, defensible answer in 2026: through licensed compounding pharmacies operating under verified accreditation, with a valid prescription, and with independent COA documentation confirming purity above 98%. Any sourcing pathway that bypasses these requirements introduces unacceptable scientific and legal risk.

Actionable next steps for researchers:

  1. Confirm institutional compliance requirements with your IRB or legal team before procurement.
  2. Identify PCAB-accredited compounding pharmacies through the NABP verification database.
  3. Request a full COA from an independent third-party laboratory before accepting any shipment.
  4. Apply the same evaluation criteria to all investigational compounds in your research protocol.
  5. Treat pricing significantly below market norms as an automatic disqualification criterion.

Rigorous sourcing is not a bureaucratic formality, it is the foundation of reproducible, credible hormone research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/07/where-to-buy-high-purity-enclomiphene-for-hormone-research-a-supplier-evaluation.png 1024 1536 Pure Tested https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg Pure Tested2026-07-11 13:05:292026-07-20 15:00:25Where to Buy High-Purity Enclomiphene for Hormone Research: A Supplier Evaluation Guide
Page 45 of 81«‹4344454647›»
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top