Call or Text 727-513-9780
  • Shopping Cart Shopping Cart
    0Shopping Cart
Pure Tested Peptides | America's most trusted Peptides for sale online
  • Peptides for sale
    • Oral Peptides for sale
      • Peptide Capsules for sale
      • BPC 157 Capsules 1000mcg
      • SLU-PP-332 Capsules | 1000 mcg
      • 5-Amino-1MQ 50mg Capsules
      • Tesofensine 500mcg
    • All Peptides for sale
    • Peptide Sprays
      • BPC 157 Nasal Spray Kit
      • BPC-157 TB500 Nasal Spray Kit
      • Semax Nasal Spray 10mg
      • Selank – Nasal Spray Kit – 10mg
      • Epithalon 50MG Nasal Spray Kit
      • Ipamorelin 10mg Nasal Spray
      • Klow Nasal Spray (BPC-157 + TB-500 + GHK-Cu + KPV) | 80mg
      • Hulk Nasal Spray Tesa / Ipa Blend 6/3 MG
      • Klow Nasal Spray
      • NAD + 500 mg Nasal Spray
      • PT-141 Nasal Spray Kit
    • GHRH Peptides
      • Ipa Peptides
      • CJC-1295 Peptides
        • CJC-1295 with DAC 5 mg
        • CJC-1295 without DAC 5 mg
        • CJC-1295 Ipa 10mg
      • Tesa Peptides
        • Tesa Peptide
        • Tesa 20 mg
    • GHK-Cu Peptides
      • All GHK-Cu Peptides
      • GHK-Cu 100mg
      • KLOW Peptide Blend – Buy KLOW blend online
    • BPC Peptides
      • All BPC Peptides
      • BPC-157
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • SLU-PP-332 Peptides
      • All SLU-PP-332 Peptides
      • SLU-PP-332 5mg
    • GLP3 Peptides
    • PT-141 Peptides
      • PT-141 Peptides for sale
      • PT-141 10mg
      • PT-141 Nasal Spray
    • CAG Peptides
      • Lipo-C Peptide Blend
      • CAG 5mg
      • CAG 10mg
    • MOTS-C Peptides
      • MOTS-C Peptides for sale
      • MOTS-c peptide
      • MOTS-c 10mg *6 pack*
    • 5 Amino 1MQ Peptides
      • 5 Amino 1MQ Peptides for sale
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
    • Epithalon Peptides
      • Epithalon Peptides for sale
      • Epithalon 10mg
      • Epithalon 50mg
  • Shop
    • GLPs
      • 5-Amino-1MQ 50mg Capsules
      • 5-Amino-1MQ 5mg
      • L-Carnitine 500mg/ml
      • Tesofensine 500mcg
      • SLU-PP-332 5mg
      • MOTS-c 10mg *6 pack*
    • Epithalon & BPC Peptides
      • Epithalon 10mg
      • Epithalon 50mg
      • BPC-157
      • BPC 157 capsules 1000mcg
      • BPC-157 TB-500
      • BPC-157 TB500 Nasal Spray Kit
      • BPC 157 Nasal Spray Kit
    • BPC TB-500 & NAD+ Peptides
      • NAD+ 500 mg
      • KLOW Peptide Blend – Buy KLOW blend online
      • GLOW Peptide Blend
      • TB 500 5mg
      • BPC 157 capsules 1000mcg – Supplement
      • BPC 157 Nasal Spray Kit
      • BPC-157
      • BPC-157 TB500 Nasal Spray Kit
      • BPC-157 TB-500
      • BPC 157 capsules 1000mcg
    • LL-37 Peptide
      • LL-37 10 mg
    • MOTS-C & Selank
      • MOTS-c peptide
      • Selank 10mg
    • GHK Peptides
      • GHK-Cu 100mg
      • GLOW Peptide Blend
      • KLOW Peptide Blend – Buy KLOW blend online
  • COAs
  • Wholesale
    • Wholesale Peptides for sale
  • PTP FAQ
  • Affiliates
    • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
      • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
          • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
            • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
          • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
          • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
      • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
          • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
          • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
            • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
          • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
            • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
              • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                  • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                    • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                      • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Selank Peptide: Advanced Pharmacological Mechanisms Underlying Its Anxiolytic and Nootropic Effects in Research
                        • MOTS-C Peptide: Unraveling Its Role in Mitochondrial Dynamics and Energy Metabolism Research
                        • Peptides and Polypeptides in Modern Pharmacology: What Research on Metoprolol, Prednisone, and Amlodipine Reveals
                        • Peptides and Polypeptides in Endocrine Pharmacology: How GLP-1, GLP-2, and GLP-3 Retatrutide Differ From Classic Drugs Like Prednisone and Amlodipine
                        • 5-Amino-1MQ Peptide: Detailed Mechanisms of NNMT Inhibition and Its Impact on Cellular Metabolism Research
                        • Mesenchymal Stem Cells, BPC‑157, and GHK‑Cu: How Tissue Repair Peptides Compare With Classic NSAIDs Like Naproxen in Injury Models
                        • Peptide Calculator Use Cases Beyond Growth Hormone: Working Through GLP‑3 Retatrutide, MOTS‑c, and BPC‑157 Research Dosing
                        • GLP2-T vs GLP2 Tirz Peptide: Understanding the Naming, Mechanistic Nuances, and Research Implications for Gut Health
                        • Polypeptide Peptides in Endocrine and Metabolic Pharmacology: Lessons From Amlodipine, Prednisone, and Metoprolol
                        • Polypeptide Peptides vs NSAIDs: What Naproxen and Diclofenac Teach Tissue-Repair Researchers About BPC‑157 and TB‑500
                        • Peptides and Polypeptides in Human Physiology: How Molecular Size Shapes Research Applications
                        • Peptides Calculator for Advanced Blends: Worked Examples for Tesamorelin, CJC‑1295, and Ipamorelin Stacks
                        • 5‑Amino‑1MQ Peptide and NNMT Inhibition: How It Compares With Statins Like Atorvastatin in Adipose and Lipid Metabolism Research
                        • Enclomiphene, Estrogen Receptor Signaling, and Luteinizing Phase Biology: What Hormone Researchers Should Measure
                        • Epithalon Peptide and Telomerase Regulation: Investigating Its Impact on Cellular Senescence and Lifespan Research Models
                        • Best research protocol Klow blend
                        • best time to take BPC-157
                        • best time to take DSIP (Delta Sleep Inducing Peptide)
                        • best time to take CJC-1295
                        • best time to take AOD-9604
                        • best time to take Follistatin 344
                        • best time to take Ipamorelin
                        • best time to take MK-677 (Ibutamoren)
                        • best time to take Ligandrol (LGD-4033) — research compound
                        • best time to take Ostarine (MK-2866) — research compound
                        • best time to take GHK-CU
                        • best time to take TB-500
                        • best time to take MOTS-c
                        • best time to take Semax
                        • best time to take RAD-140 (Testolone) — research compound
                        • best time to take Thymosin Alpha-1
                        • best time to take PEG-MGF
                        • Biolife Plasma, Octapharma Plasma, and Research Peptides: How Plasma Donation Labs Differ From Peptide Suppliers
                        • best time to take YK-11 — research compound
                        • best time to take PT-141 (Bremelanotide)
                        • Best research protocol Klow blend
                        • 5-Amino-1MQ and MOTS-C Synergy: Metabolic Signaling, Mitochondria, and Research Design
                        • BPC-157 and TB-500: Investigating Their Combined Effects on Angiogenesis and Cellular Migration in Tissue Repair Models
                        • BPC-157 Peptide: Gut Barrier Function, Inflammation, and Tissue-Recovery Research
                        • 5‑Amino‑1MQ and MOTS‑c Synergy in Metabolic Research: Designing NNMT and Mitochondrial Biogenesis Stacks
                        • CJC-1295 with DAC vs. Without DAC: Half-Life, Release Kinetics, and Research Implications
                        • CJC‑1295 with DAC vs. Without DAC: Expanding on Half‑Life Differences Using Tesamorelin and Ipamorelin Blend Case Studies
                        • Collagen Biology and Copper‑Binding Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Interact with Skin and Connective Tissue
                        • Collagen Biology and Regenerative Peptides: How GHK‑Cu, Glow Blend, and Klow Blend Affect Extracellular Matrix Research
                    • DNA, Telomeres, and Longevity Peptides: Positioning Epithalon and MOTS‑c in Genetic Aging Research
                      • Enclomiphene Citrate: serm Mechanism, Testosterone Research, and Stack Compatibility
                        • Enclomiphene vs Enclomiphene Citrate: Formulation, Bioavailability, and Research Distinctions
                        • Epithalon Peptide Research: Telomerase Activation, Aging, and Pineal Gland Function
                        • Estrogen Receptor Signaling and Enclomiphene: How Selective Modulators Compare with Classic Polypeptide Hormones
                        • GHK-Cu Peptide: Advanced Mechanisms in Extracellular Matrix Remodeling and Wound Healing Research
                        • GHK-Cu Peptide: Collagen Synthesis, Wound Repair, and Skin-Barrier Research Models
                        • GLP-1 vs GLP-3 vs GLP-2: Peptide Classification and Research Applications
                        • GLP-2 Peptide Research Guide: Gut Barrier Function, Nutrient Absorption, and Intestinal Recovery Models
                        • GLP-3 Retatrutide vs. GLP-1 Drugs: What Triple-Agonist Biology Changes in Research Models
                        • Ipamorelin and Tesamorelin Combination: Synergistic GH Secretagogue Research and Dosing Protocols
                        • GLP2 Tirz Peptide: What It Is, Why the Name Exists, and How Researchers Should Interpret It
                        • Klow Blend Peptide Nasal Spray: What the Formulation Is Trying to Do in Cognitive Research
                        • Mitochondria, NNMT Inhibition, and Peptide Modulators: Where MOTS‑c and 5‑Amino‑1MQ Fit in Cellular Energy Research
                        • MOTS-c Peptide: Mitochondrial Function, Energy Metabolism, and What Researchers Measure
                        • MOTS-c vs. 5-Amino-1MQ: Which Metabolic Research Questions Each Compound Actually Answers
                        • Nasal Spray Peptides: Bioavailability, Administration, and Semax/Selank Research Applications
                        • PT-141 Peptide Research: Mechanism of Action and Melanocortin Receptor Signaling
                        • Retatrutide for Research: Mechanism, Structure, and GLP-1/GLP-3 Dual Action
                        • Retatrutide for Obesity and Type 2 Diabetes: What the Latest Trial Data Suggest
                        • Tesofensine Peptide Research: Mechanism, Appetite Suppression, and Neuropeptide Y Pathways
  • Contact
    • Contact Customer Service
    • Text Customer Support
  • About US
  • Shop all peptides
  • Affiliate Program
    • Affiliate Signup
  • Login / Register Login / Register Page Link Login / Register Page Link
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Tag Archive for: tesofensine

What Is Tesofensine? Dopamine, Norepinephrine, and Serotonin Transporter Biology in Appetite Research

What Is Tesofensine? Dopamine, Norepinephrine, and Serotonin Transporter Biology in Appetite Research

October 31, 2026/0 Comments/in Uncategorized/by

Obesity pharmacology took a sharp turn when researchers discovered that simultaneously blocking all three monoamine transporters, not just one, could produce weight loss magnitudes previously unseen with oral small molecules. That discovery sits at the heart of tesofensine, a synthetic tropane derivative that has become a reference compound in appetite biology. Understanding what tesofensine is and how dopamine, norepinephrine, and serotonin transporter biology shape appetite research reveals why this molecule continues to command scientific attention in 2026.

Key Takeaways

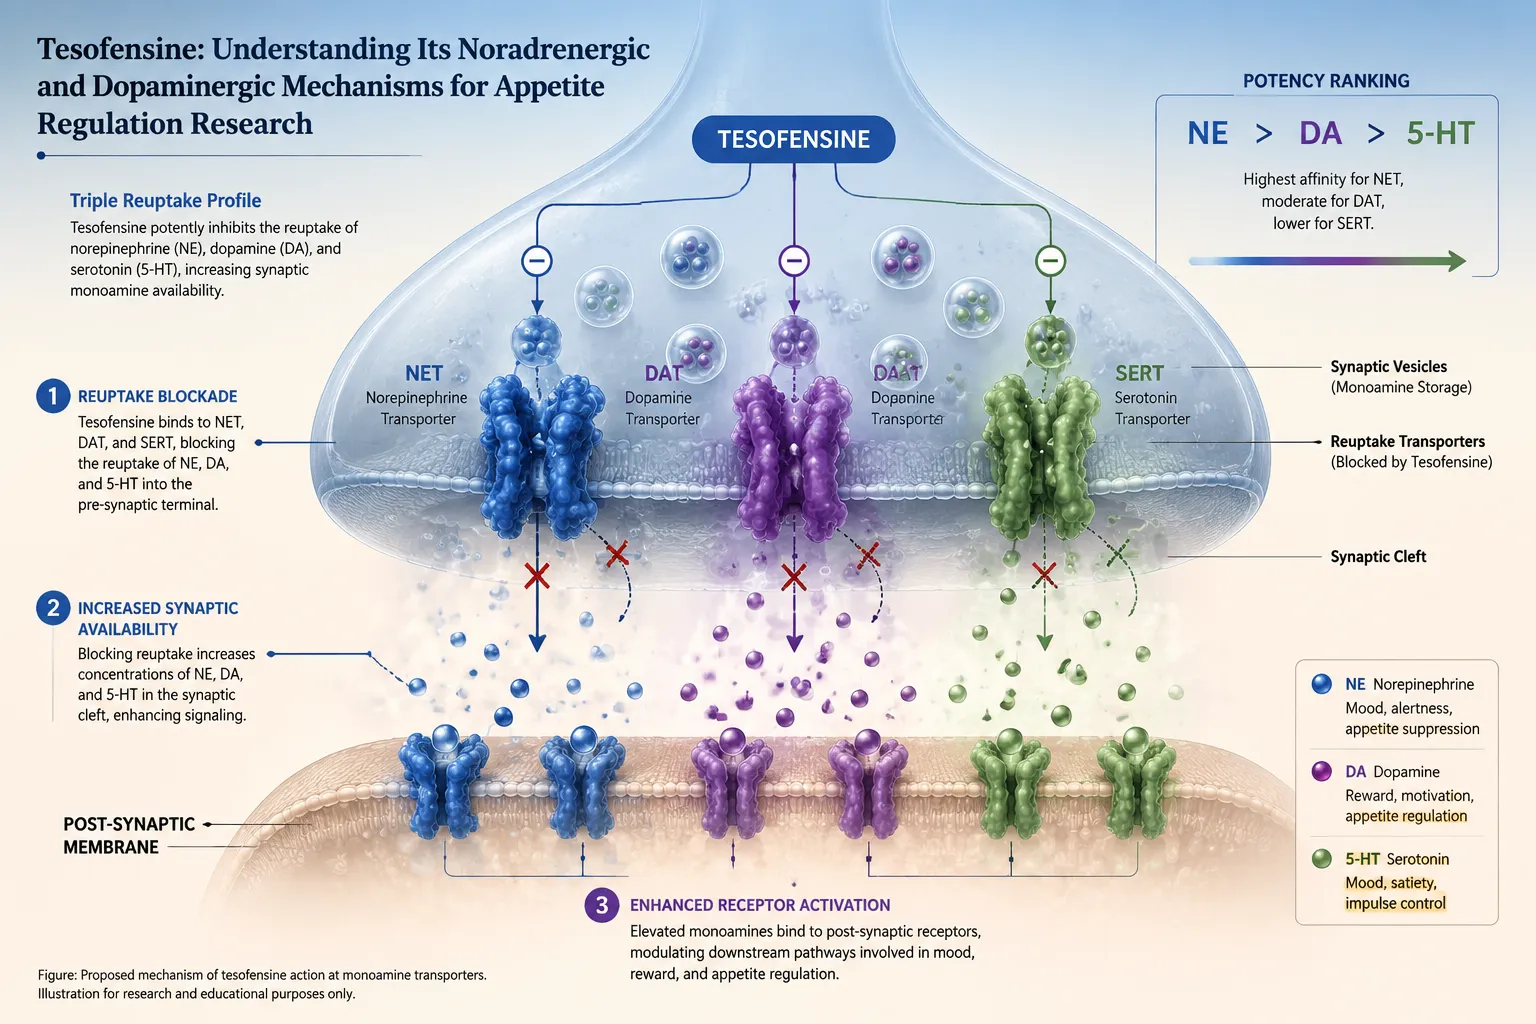
  • Tesofensine is a triple monoamine reuptake inhibitor (SNDRI) that blocks norepinephrine, dopamine, and serotonin transporters simultaneously.
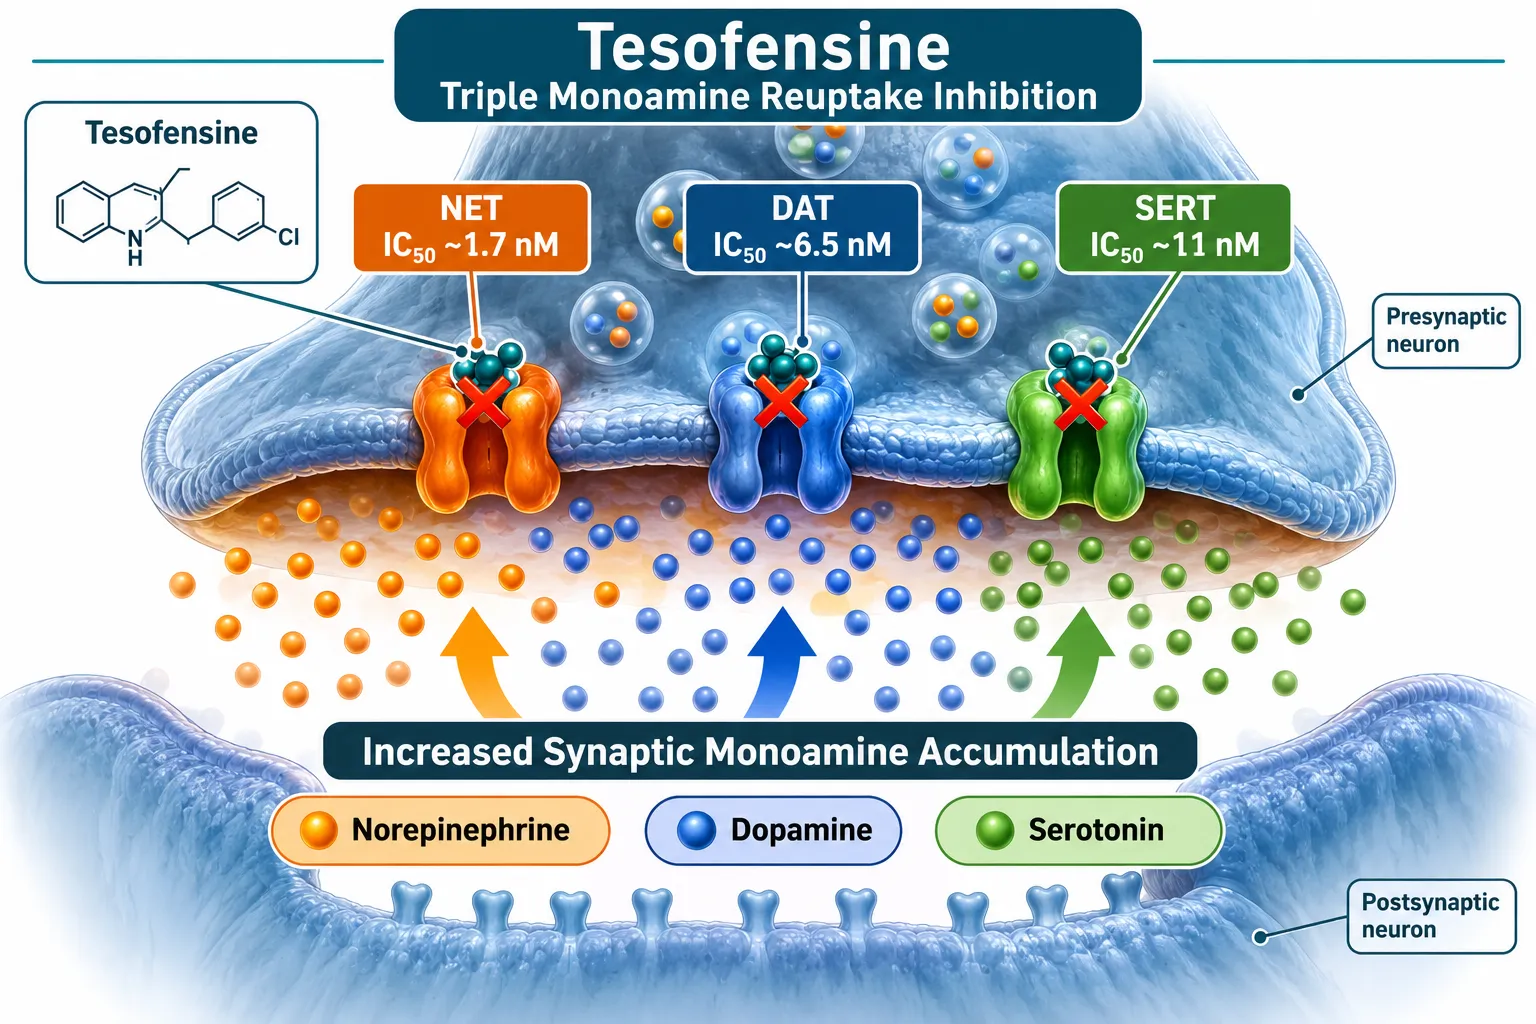
  • Its transporter affinities are strongest at NET (1.7 nM), intermediate at DAT (6.5 nM), and lowest at SERT (~11 nM).
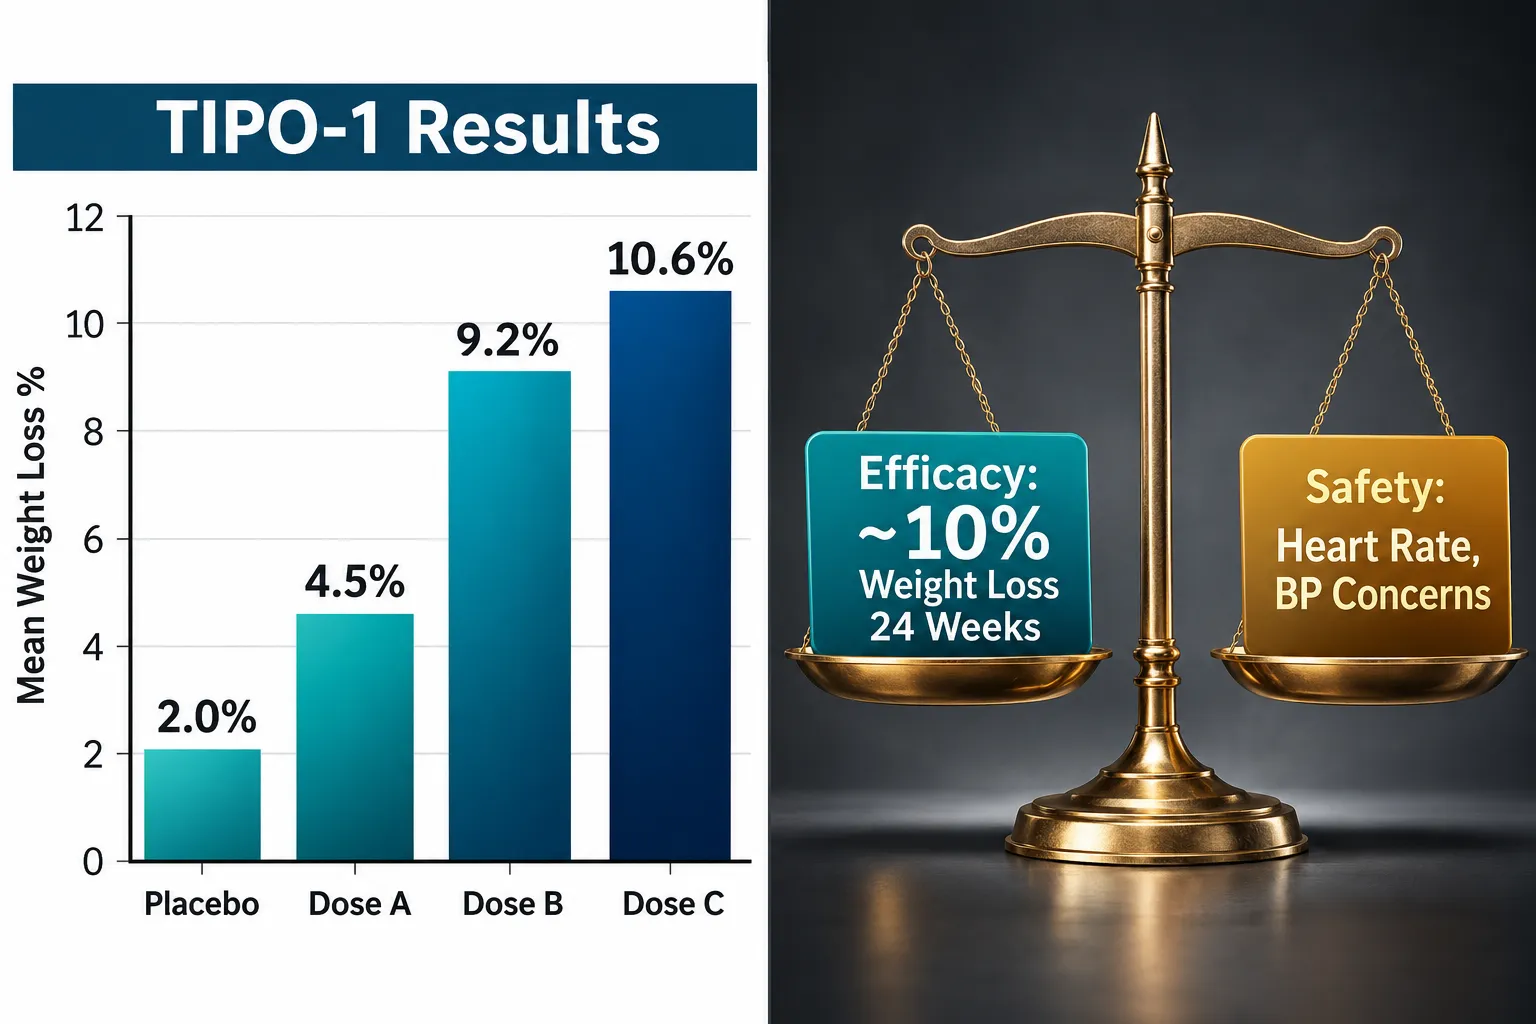
  • The Phase 2b TIPO-1 trial reported up to 10.6% mean weight loss at 24 weeks, among the highest seen in oral obesity pharmacology at the time.
  • Tesofensine differs fundamentally from GLP-1, class peptides; it is a small synthetic molecule acting centrally on monoamine circuits rather than on gut-derived hormone receptors.
  • As of 2026, tesofensine remains investigational and unapproved by the FDA, with unresolved cardiovascular safety data limiting Phase 3 progress.

Tesofensine Pharmacology: A Triple Monoamine Reuptake Inhibitor
Tesofensine Pharmacology: A Triple Monoamine Reuptake Inhibitor

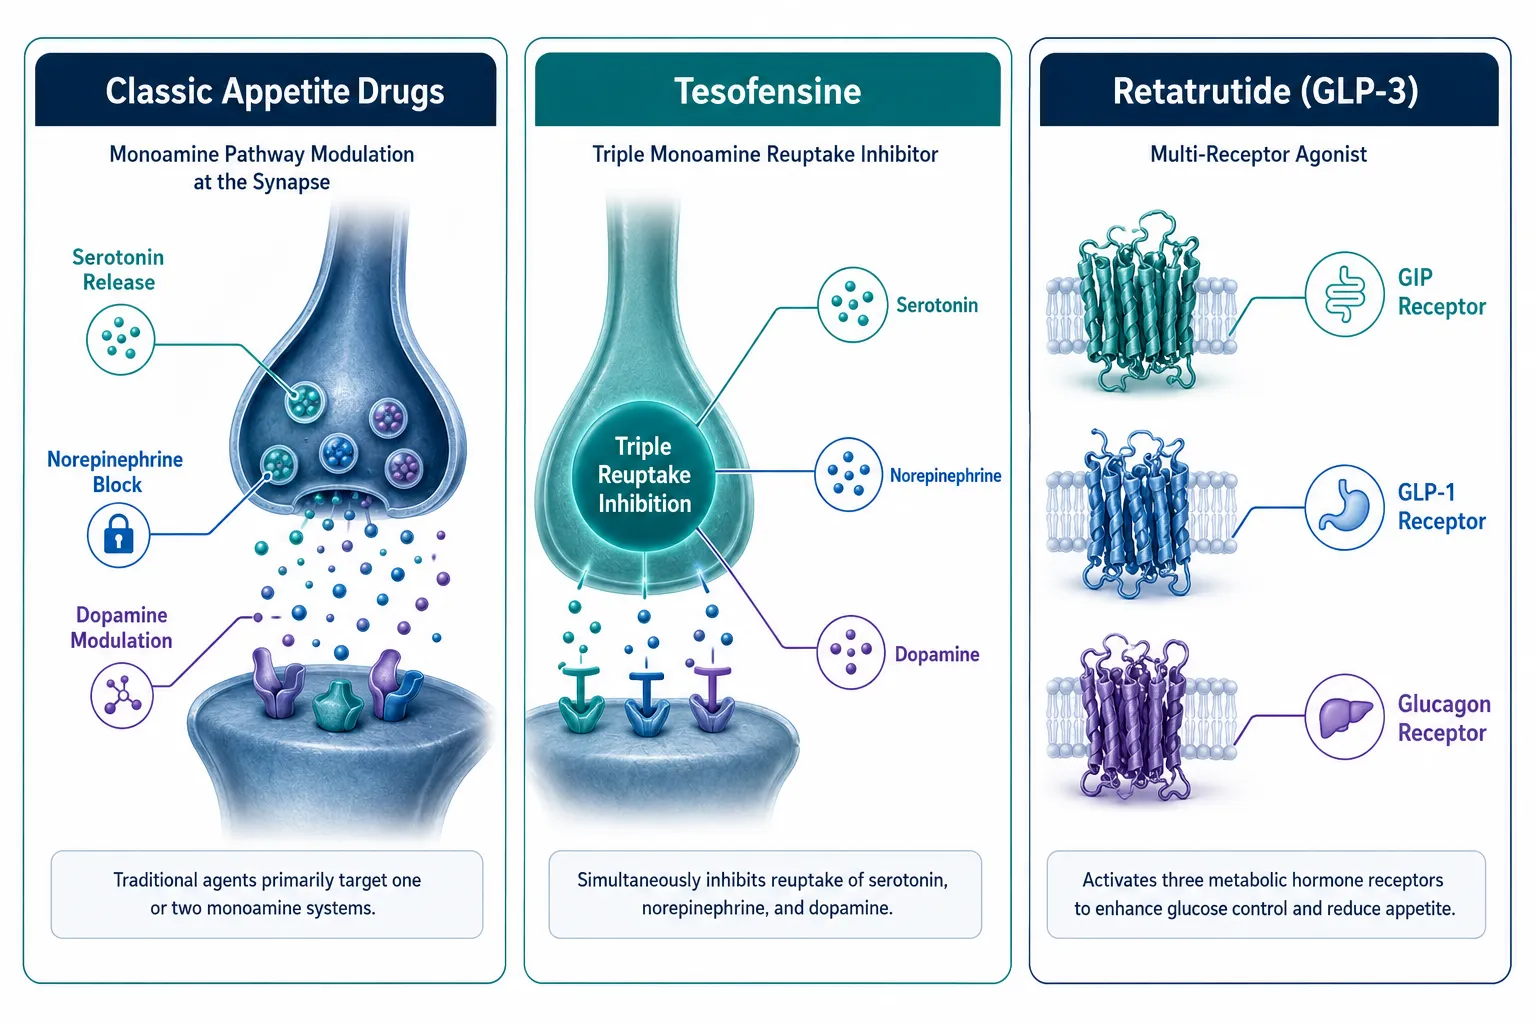
Tesofensine belongs to the phenyltropane chemical class, the same structural family as cocaine and certain antidepressants, but was purpose-engineered as a serotonin, norepinephrine, dopamine reuptake inhibitor (SNDRI). Its mechanism is straightforward in concept: it physically occupies the monoamine transporter proteins responsible for clearing dopamine, norepinephrine, and serotonin from synaptic gaps, allowing all three neurotransmitters to accumulate and act for longer.

What makes tesofensine pharmacologically unusual is the potency profile across all three targets:

Transporter Target Reported IC50
NET Norepinephrine ~1.7 nM
DAT Dopamine ~6.5 nM
SERT Serotonin ~11 nM

These nanomolar values mean that even at low clinical doses, the molecule can produce substantial transporter occupancy. Positron emission tomography (PET) studies in human volunteers confirmed meaningful dopamine transporter occupancy in the living brain, providing a direct biological bridge between lab binding data and human pharmacology.

How does this differ from GLP-1 peptides? GLP-1, class agents such as those reviewed in research on what is the strongest peptide for weight loss act on gut-derived incretin hormone receptors, largely in the periphery and brainstem, slowing gastric emptying and modulating insulin. Tesofensine, by contrast, is a small synthetic oral molecule with no peptide structure and no GLP-1 receptor activity. Its appetite suppression is driven entirely by central monoamine modulation. This distinction matters for researchers comparing mechanisms or combining approaches, including those exploring GLP-1 and related compound research.


Transporter Biology and Appetite Circuits: How Dopamine, Norepinephrine, and Serotonin Shape Food Intake
Transporter Biology and Appetite Circuits: How Dopamine, Norepinephrine, and Serotonin Shape Food Intake

The three monoamines that tesofensine elevates each serve a distinct role in feeding behavior. Understanding their biology is essential to grasping why a triple inhibitor outperforms single-target agents.

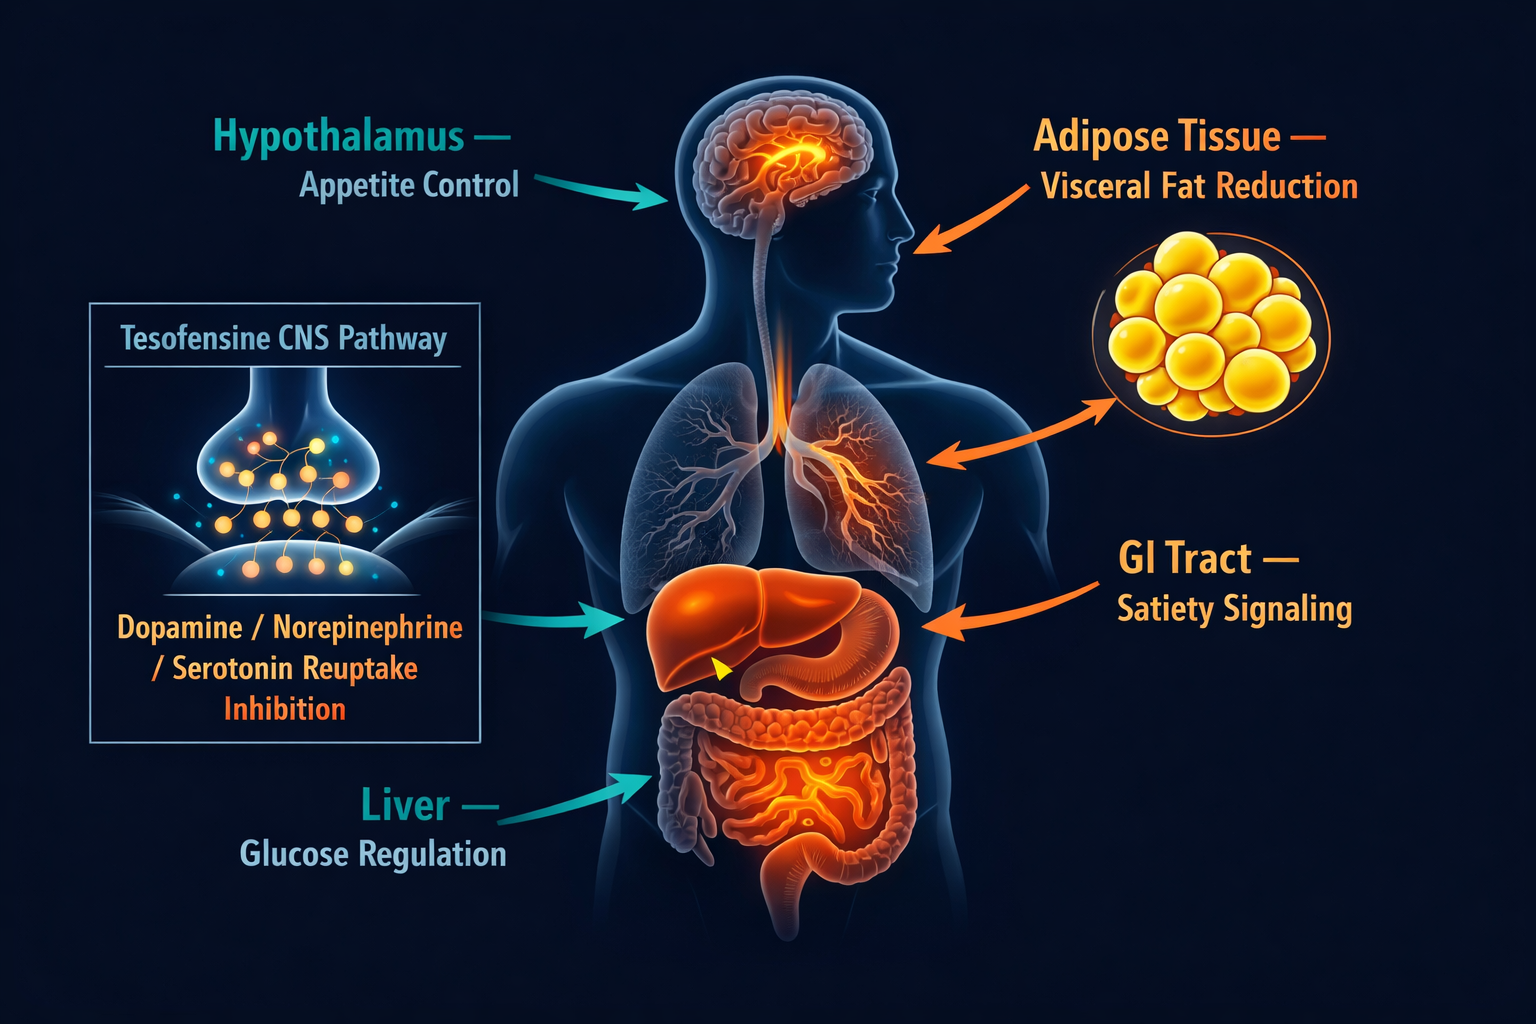
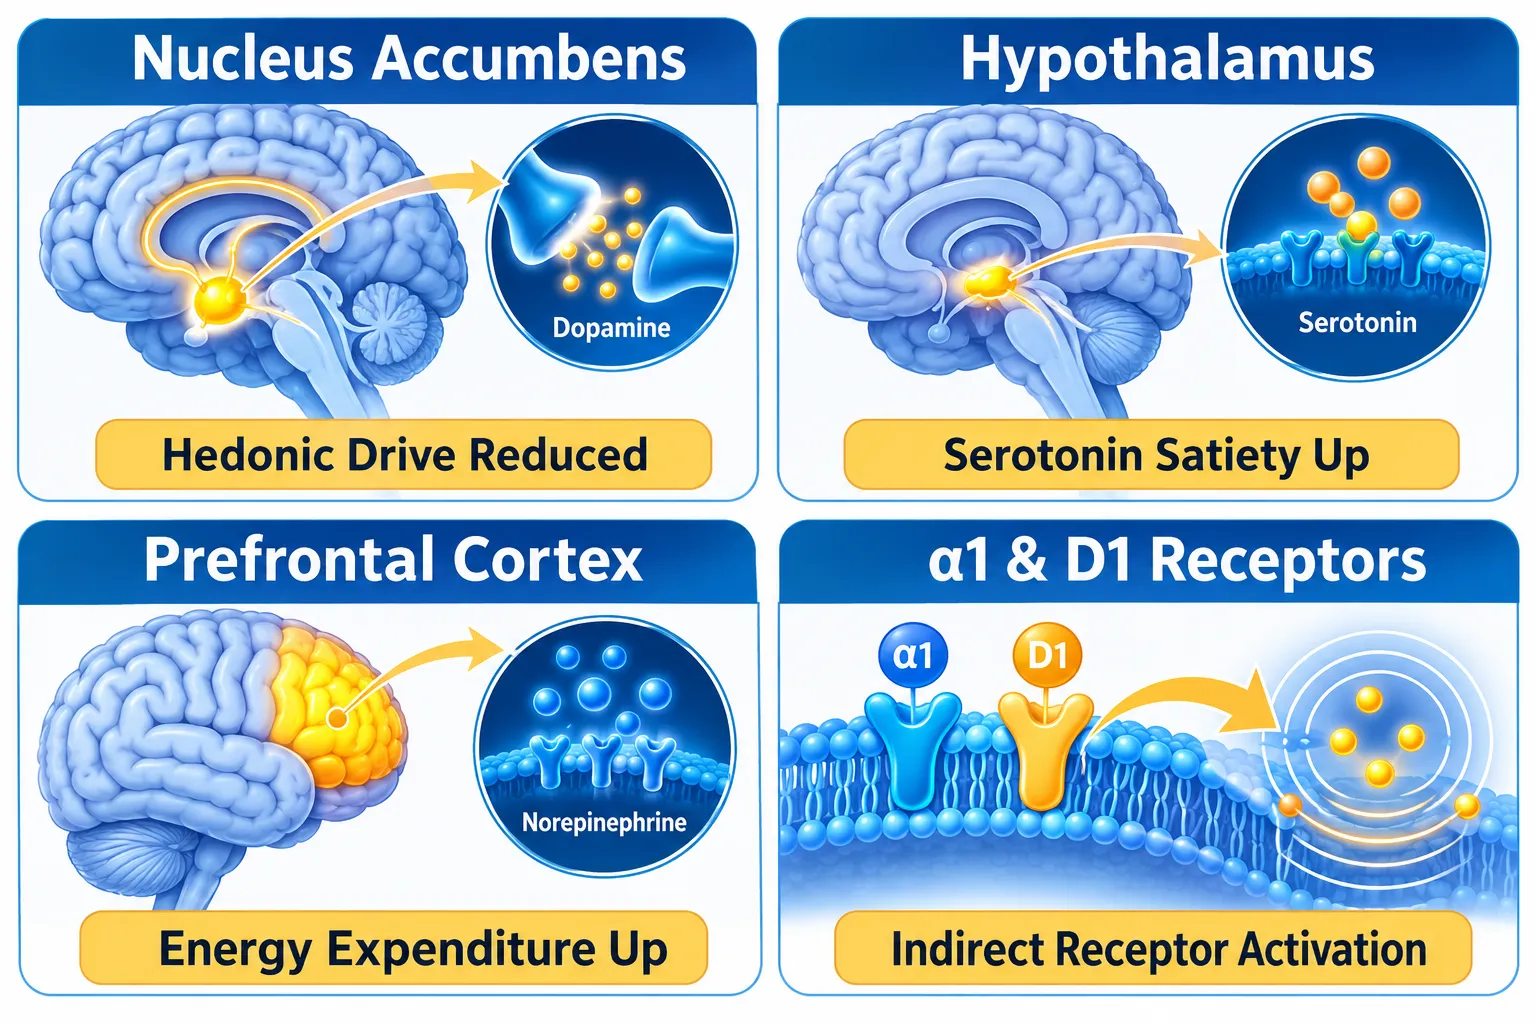
Dopamine and reward-driven eating. Dopamine signals in the nucleus accumbens and prefrontal cortex encode the motivational value of food. In diet-induced obese rodents, dopamine levels in these regions are chronically suppressed, a state that promotes compulsive overeating to compensate for blunted reward. Tesofensine reverses this deficit, restoring nucleus accumbens dopamine and modifying dopamine transporter binding in the dorsal striatum. The result is reduced hedonic drive to eat.

Norepinephrine and energy expenditure. Norepinephrine's role is dual: it raises metabolic rate and suppresses appetite via hypothalamic circuits. Tesofensine's strongest affinity sits at the norepinephrine transporter (NET), and downstream work in obese rats shows that its appetite-suppressive effects are mediated in part by indirect stimulation of α1-adrenoceptors, receptors that normally signal satiety and arousal.

Serotonin and satiety timing. Serotonin modulates meal size and the speed at which fullness develops. Classical serotonergic anorectics like fenfluramine targeted SERT alone; tesofensine's SERT blockade contributes to satiety enhancement but is the weakest of its three targets, suggesting dopaminergic and noradrenergic mechanisms carry more of the weight-loss load.

"Simultaneous modulation of all three monoamine systems may explain why tesofensine achieves weight loss magnitudes that single-target agents rarely reach."

In high-fat diet, induced obese rats given tesofensine at 2 mg/kg subcutaneously, both body weight and food intake fell significantly versus controls. Critically, the mechanism involves D1 receptor pathway stimulation downstream of elevated synaptic dopamine, an indirect receptor effect, not direct agonism, which may partly explain why tolerance develops more slowly than with direct stimulants.

Researchers exploring metabolic peptides such as AOD 9604 research methods or tesa benefits work in overlapping metabolic territory, though through entirely different mechanisms, growth hormone, related rather than monoamine-based.


Clinical Evidence and Development Status in 2026
Clinical Evidence and Development Status in 2026

The pivotal Phase 2b trial, TIPO-1 (NCT00394667), enrolled 203 adults with obesity across five Danish centers, randomizing them to placebo or one of three tesofensine doses combined with an energy-restricted diet for 24 weeks. Mean weight loss outcomes were striking:

  • Placebo: ~2.0%
  • Low dose: ~4.5%
  • Mid dose: ~9.2%
  • High dose: ~10.6% (p<0.0001 vs. placebo)

A 10%+ reduction in body weight at 24 weeks with an oral agent was, at the time, described as among the most substantial pharmacologic weight loss results on record. As of 2026, these figures still compare favorably with many established obesity drugs.

Yet development has stalled. Tesofensine remains classified as investigational and is not approved by the U.S. FDA, despite the agency reportedly endorsing a Phase 3 program. The cardiovascular trial NCT00481104, focused on heart rate and blood pressure in 140 obese patients, has no posted results, leaving cardiac safety unresolved in the public domain.

The core tension is this: the same dopaminergic pathway that suppresses hedonic eating also activates the brain's reward circuitry, raising concerns about abuse liability. And the noradrenergic load that boosts energy expenditure also elevates heart rate and blood pressure, a pattern that historically derailed sympathomimetic diet drugs.

Most 2026 expert analyses expect a multi-year timeline before any major-market approval. Some commentators suggest that refined analogues tuning transporter selectivity, perhaps reducing DAT affinity to lower abuse potential while preserving NET and SERT effects, may ultimately be more viable than tesofensine itself.

For research teams also studying appetite and metabolic pathways, resources on retatrutide clinical trial data and peptide physician resources offer complementary perspectives on where multi-target metabolic agents are heading.


Conclusion

Tesofensine stands as a compelling case study in what is tesofensine, dopamine, norepinephrine, and serotonin transporter biology in appetite research, demonstrating that multi-monoamine reuptake blockade can produce clinically meaningful weight loss through convergent effects on reward, satiety, and energy expenditure. Its pharmacology is well-characterized, its Phase 2b efficacy is robust, and its mechanistic logic is sound.

The practical path forward requires resolving cardiovascular and abuse-liability concerns through well-powered Phase 3 trials. Researchers and clinicians following this compound should:

  1. Monitor NCT00481104 and any future Phase 3 registrations for cardiac safety endpoints.
  2. Compare tesofensine's monoamine profile against emerging multi-target small molecules entering development.
  3. Consider how its dopamine circuit effects differ fundamentally from incretin-based approaches when designing combination research programs.
  4. Review GLP-1 class research products as a mechanistic contrast when evaluating appetite-modulating agents.

Tesofensine's legacy in appetite biology may ultimately be less about its own approval timeline and more about what it taught researchers: that hitting dopamine, norepinephrine, and serotonin together, in the right proportions, opens a pharmacological window that single-target drugs cannot reach.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/what-is-tesofensine-dopamine-norepinephrine-and-serotonin-transporter-biology-in.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-31 13:20:082026-10-31 13:20:08What Is Tesofensine? Dopamine, Norepinephrine, and Serotonin Transporter Biology in Appetite Research
Retatrutide vs Tesofensine: How Receptor Biology and Monoamine Signaling Shape Metabolic Research Design

Retatrutide vs Tesofensine: How Receptor Biology and Monoamine Signaling Shape Metabolic Research Design

October 31, 2026/0 Comments/in Uncategorized/by

Nearly 24 percent of adults worldwide now meet criteria for obesity-related metabolic disease, yet two compounds under research scrutiny, retatrutide and tesofensine, attempt to address that burden through fundamentally different biological mechanisms. Understanding Retatrutide vs Tesofensine: How Receptor Biology and Monoamine Signaling Shape Metabolic Research Design is not simply an academic exercise. The receptor class each compound targets determines the endpoints researchers can reasonably measure, the safety signals they must monitor, and the patient populations they can safely study.

Key Takeaways

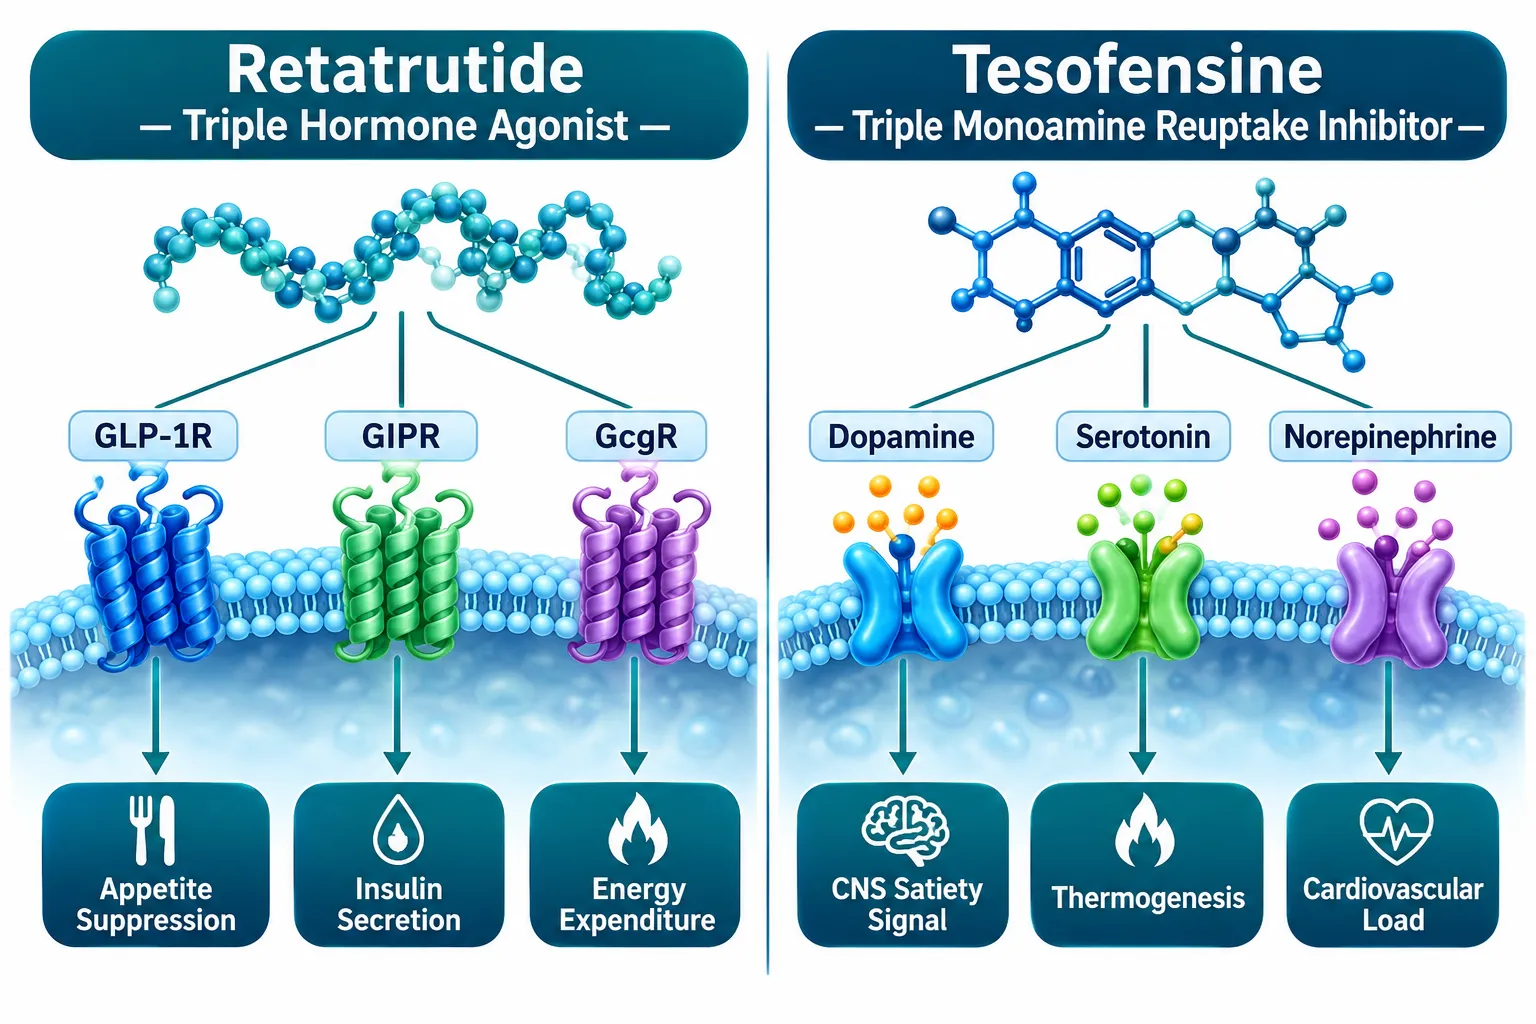
  • Retatrutide is a triple hormone receptor agonist (GLP-1R, GIPR, GcgR); tesofensine is a small-molecule triple monoamine reuptake inhibitor, these are fundamentally different pharmacological classes.
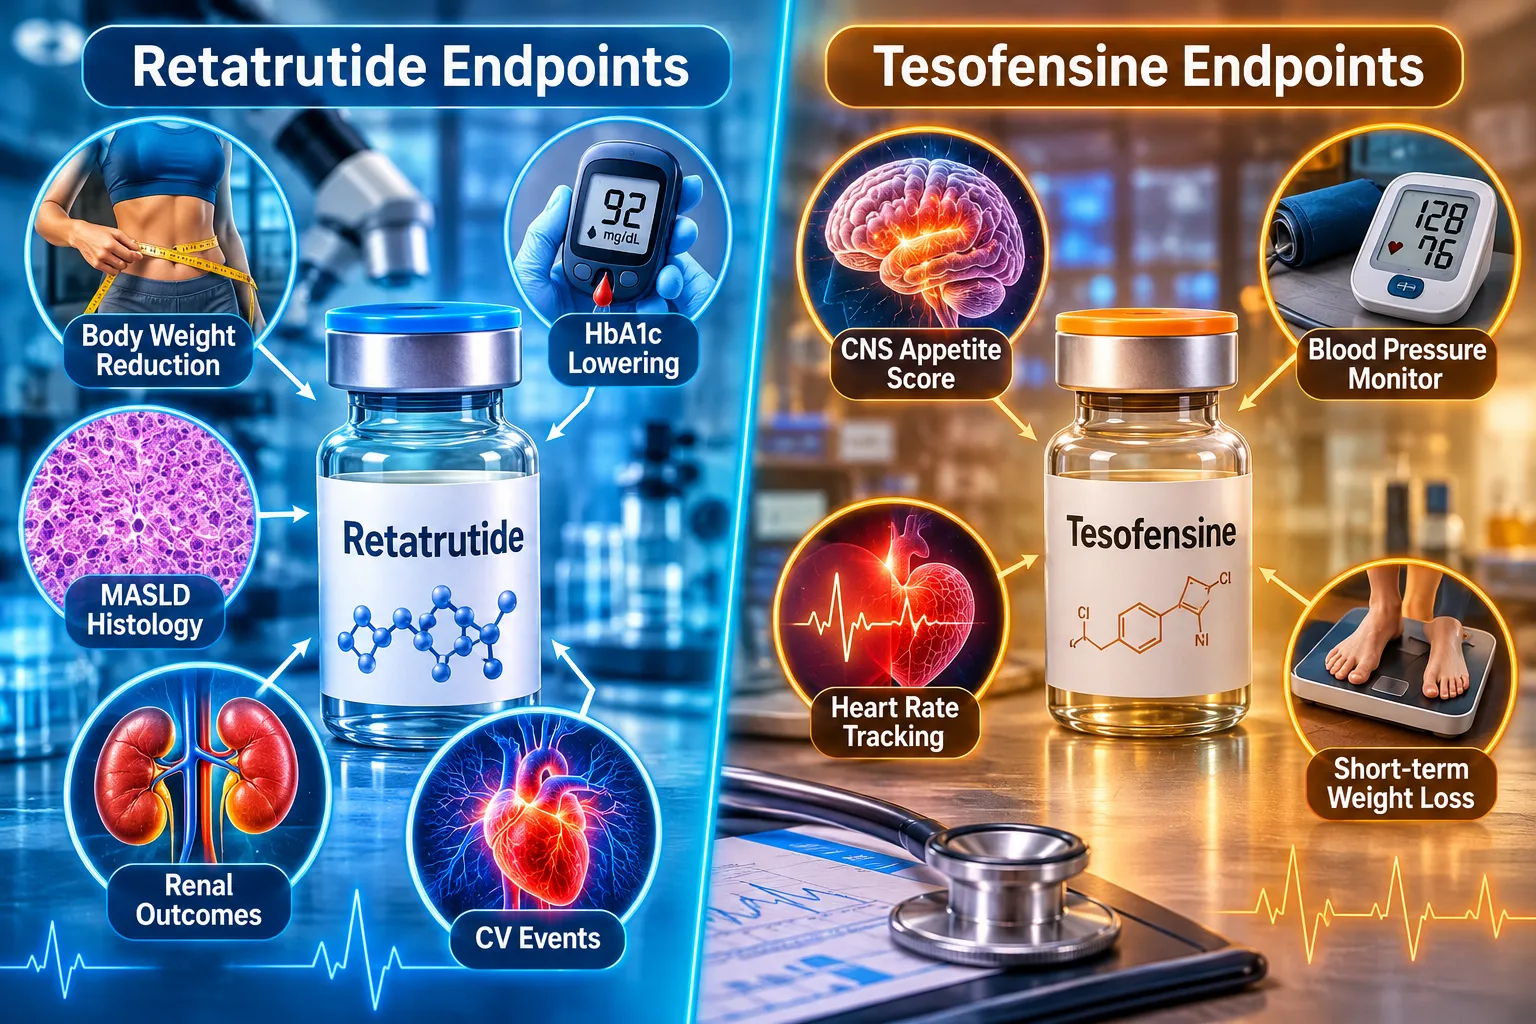
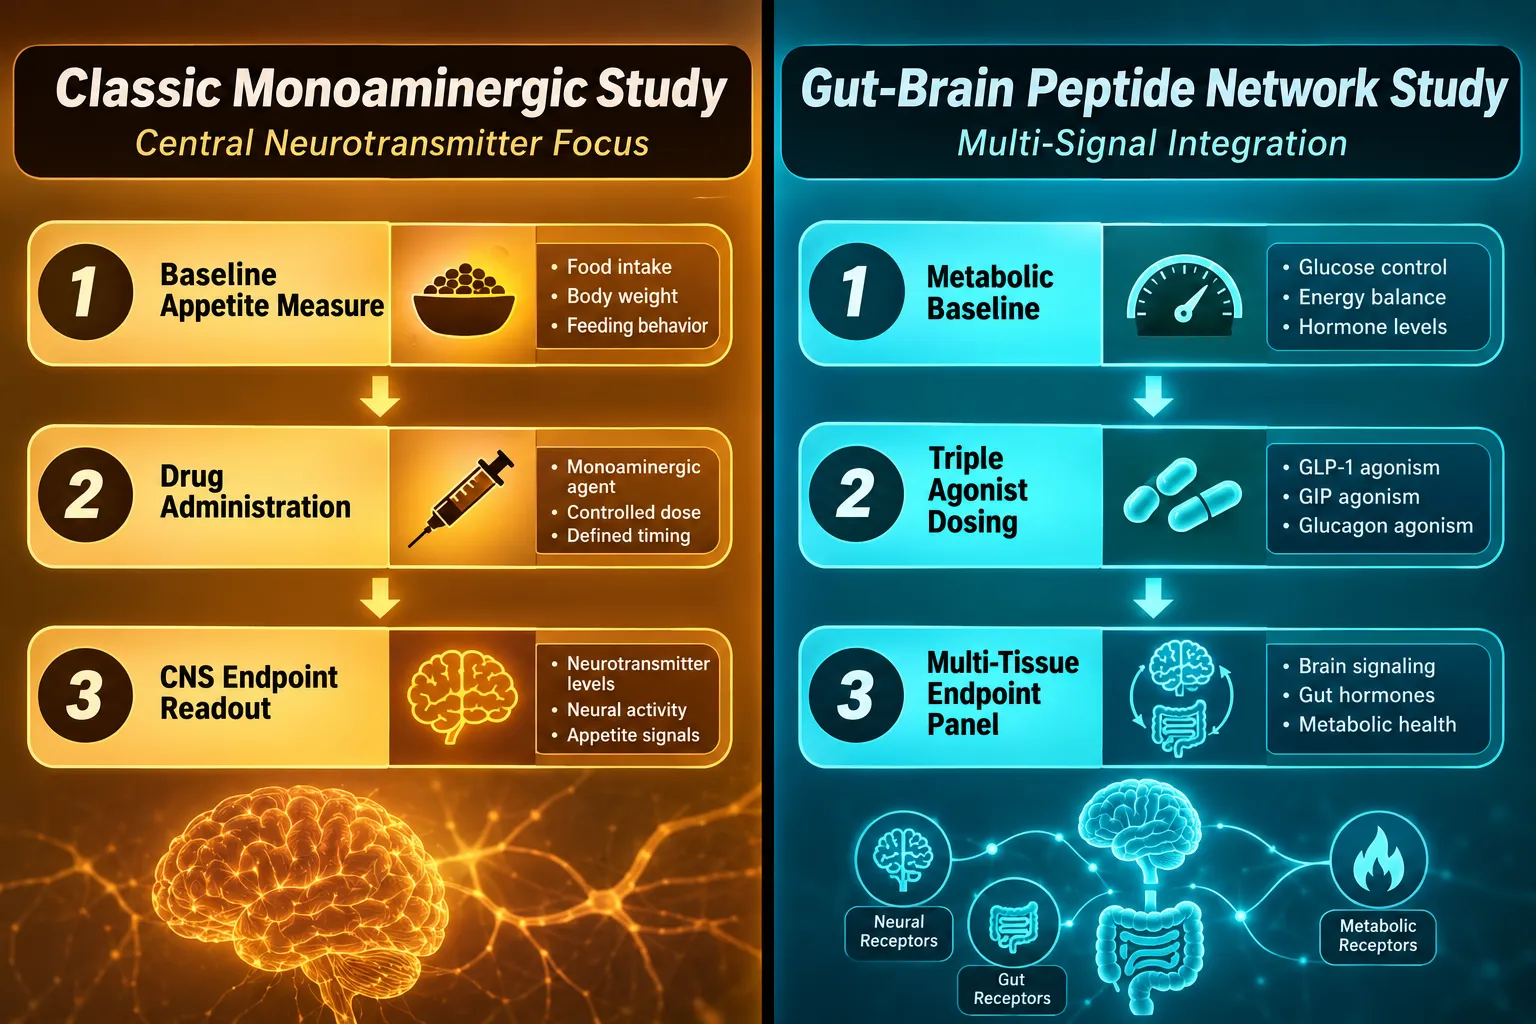
  • Receptor biology drives endpoint selection: hormone agonism supports glycemic, hepatic, renal, and cardiovascular endpoints, while monoamine blockade demands central nervous system and cardiovascular safety monitoring.
  • Retatrutide's TRIUMPH-1 phase 3 data set a new efficacy benchmark for obesity pharmacotherapy.
  • Tesofensine remains a niche research compound with a narrower endpoint profile and a more cautious regulatory trajectory.
  • Choosing between these mechanisms as a research scaffold determines which patient populations can ethically be included in a trial.

Distinct Mechanisms: Triple Hormone Agonism vs Monoamine Reuptake Inhibition

Distinct Mechanisms: Triple Hormone Agonism vs Monoamine Reuptake Inhibition

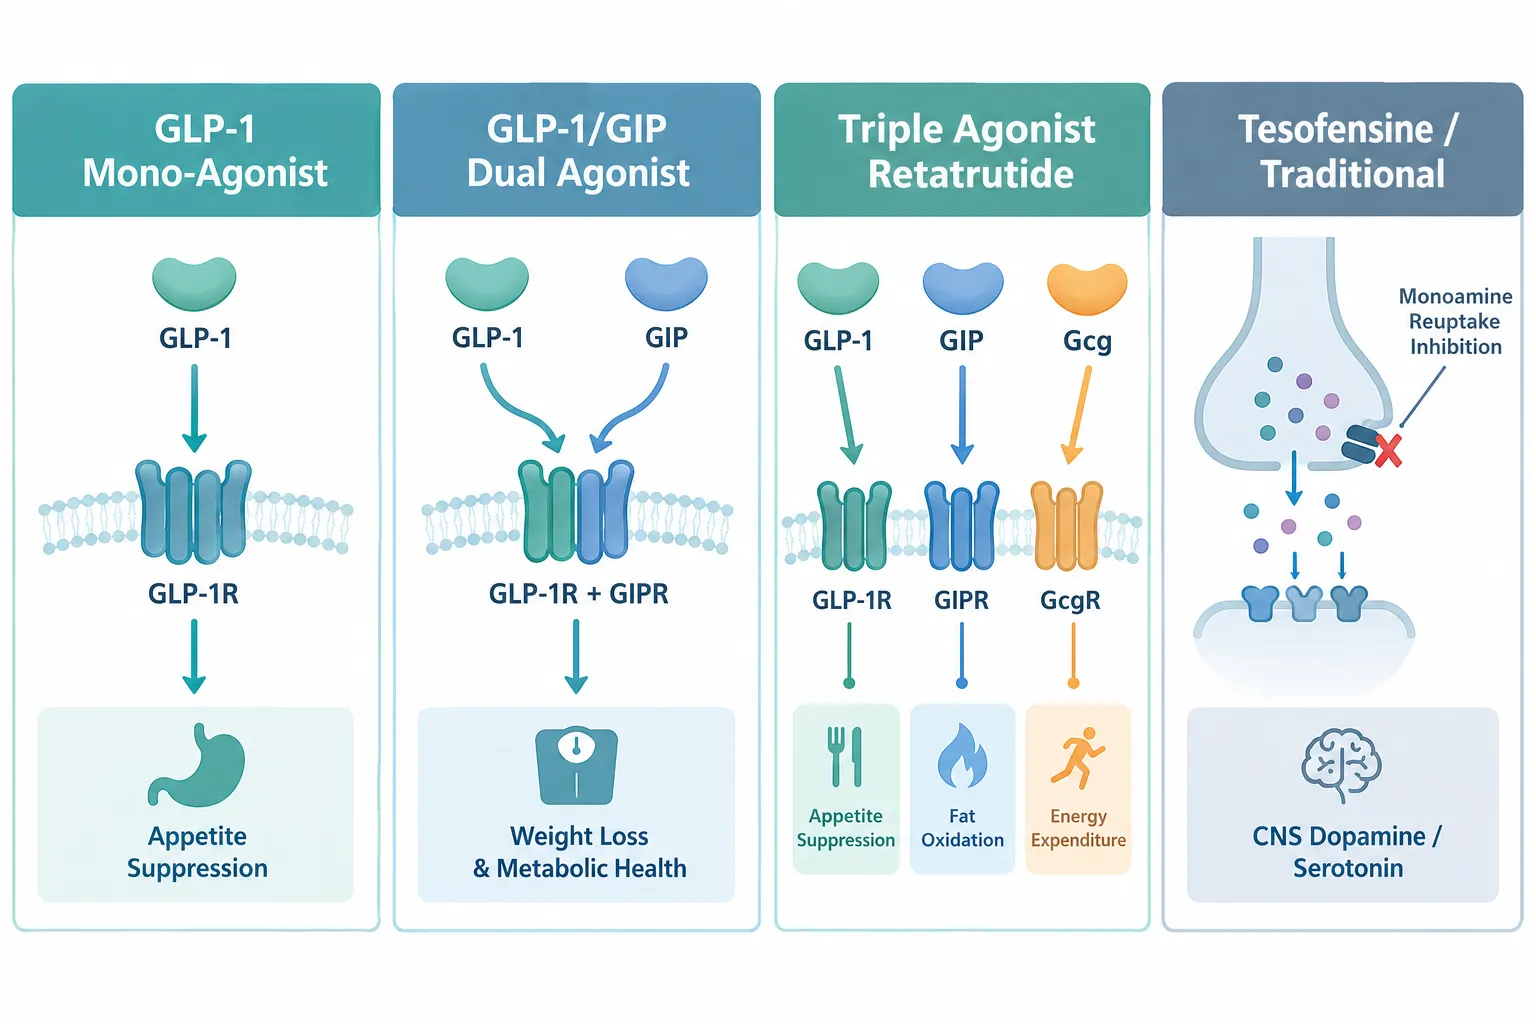
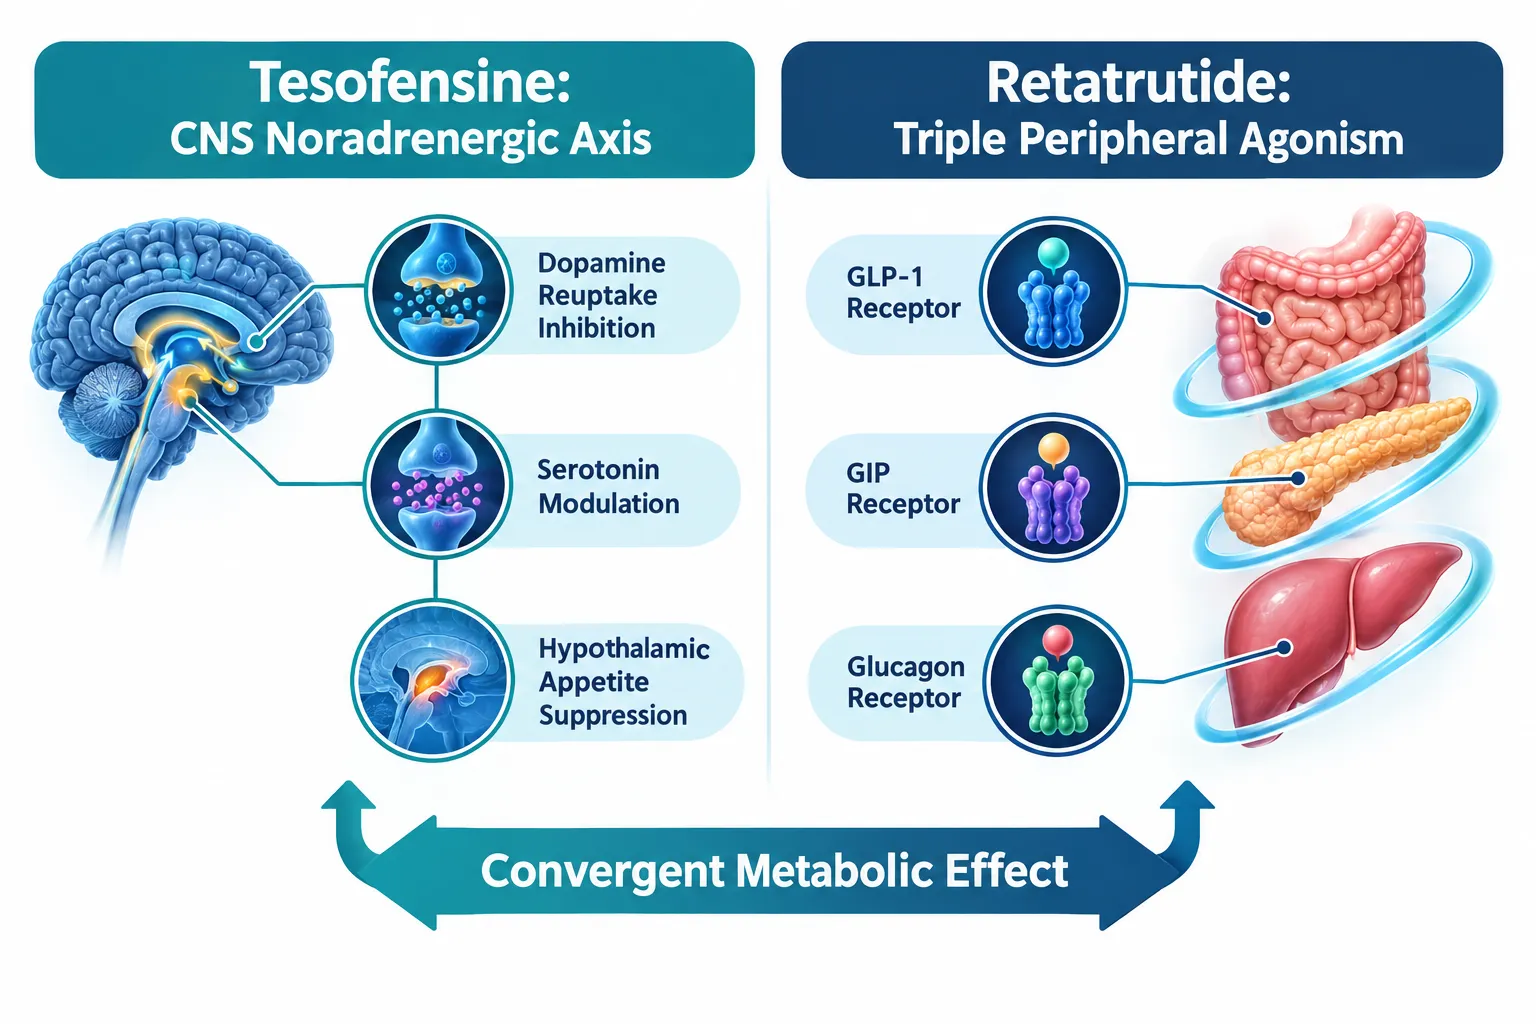
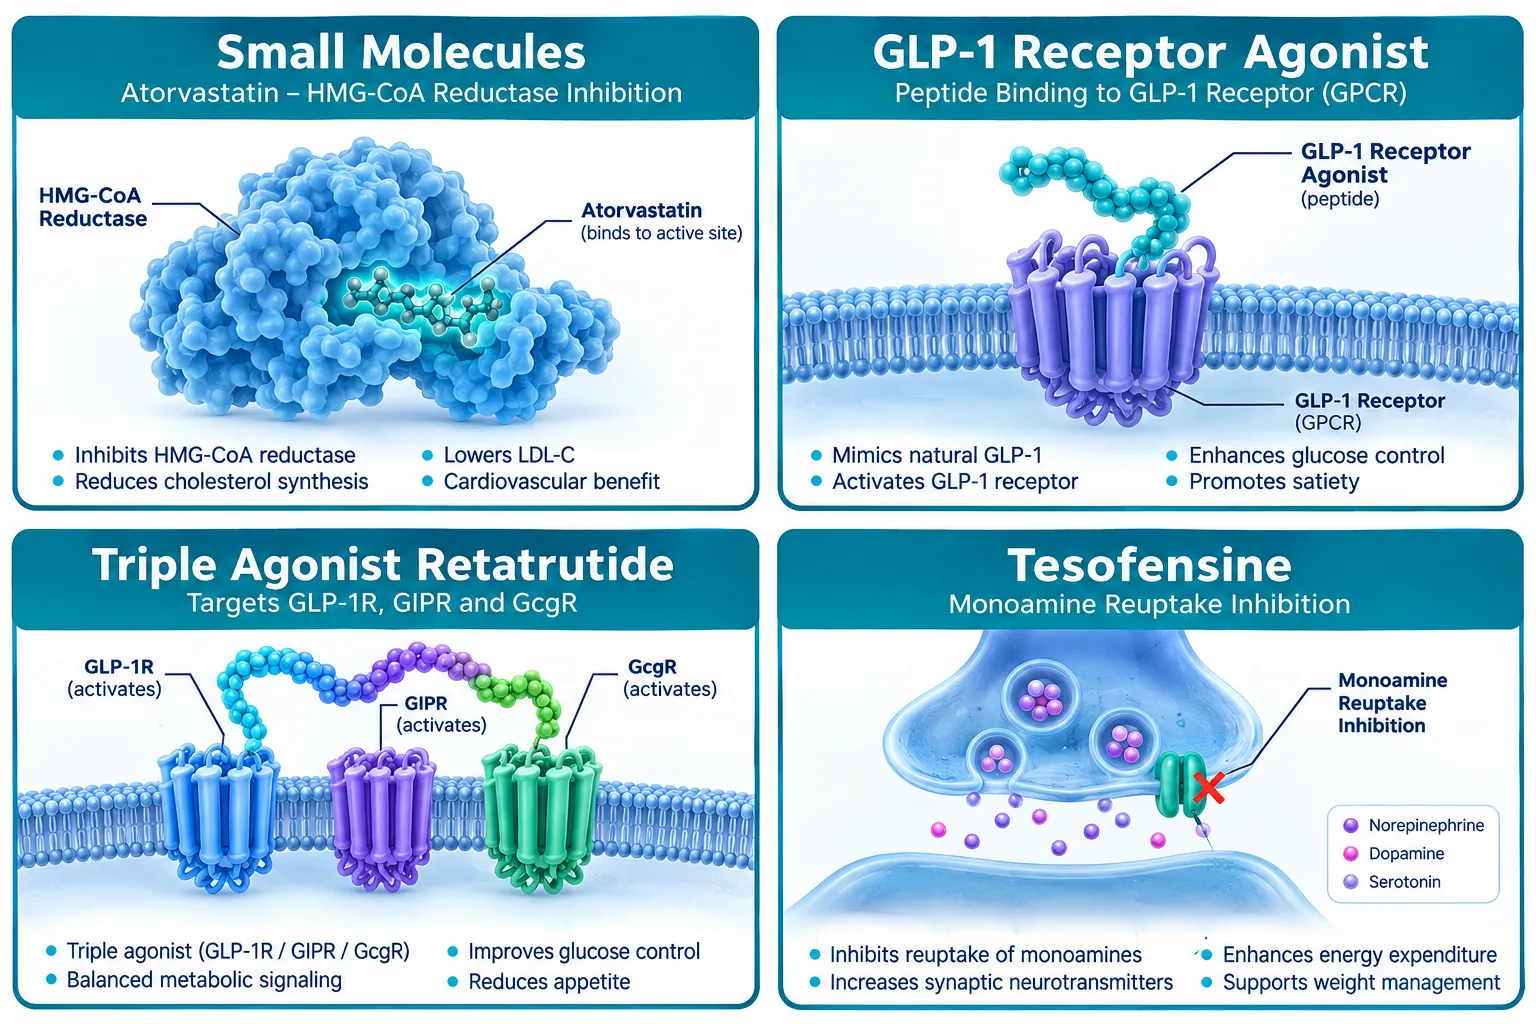
Retatrutide is a peptide-based triple agonist that activates three G-protein-coupled receptors (GPCRs): the glucagon-like peptide-1 receptor (GLP-1R), the glucose-dependent insulinotropic polypeptide receptor (GIPR), and the glucagon receptor (GcgR). Each receptor axis contributes a distinct metabolic function. GLP-1R activation reduces appetite and slows gastric emptying. GIPR activation enhances insulin release and may augment the satiety signal from GLP-1R. GcgR activation increases hepatic glucose output at low doses but, more importantly at therapeutic doses, raises energy expenditure through brown adipose tissue activation.

Tesofensine is a small molecule, not a peptide, that blocks the reuptake of dopamine, serotonin, and norepinephrine in the central nervous system. This monoamine reuptake inhibition reduces food intake primarily through central appetite suppression and may modestly increase thermogenesis via sympathomimetic activity. Because it does not engage endocrine GPCRs, it produces no direct incretin effect and no glucagon-mediated boost to energy expenditure.

"The receptor class a compound targets is the single most important variable a metabolic research team will confront when designing a trial from the ground up."

This mechanistic divide explains why researchers exploring visceral fat research increasingly orient their protocols around GPCR-based compounds rather than monoamine modulators: the hormone agonist axis provides multiple measurable tissue-level endpoints that monoamine signaling simply cannot reach.


Cardiometabolic Endpoints: Where Receptor Biology Shapes Research Design

Cardiometabolic Endpoints: Where Receptor Biology Shapes Research Design

The depth of measurable outcomes differs sharply between these two pharmacological classes. Retatrutide's TRIUMPH-1 phase 3 trial data, the most rigorous dataset available for the compound, demonstrated average body weight reductions that surpassed any previously approved pharmacotherapy in comparable populations. Beyond weight, the hormone receptor axes produce quantifiable effects across a broad endpoint portfolio.

Retatrutide endpoint categories in active investigation:

  • Glycemia: HbA1c reduction and fasting glucose in type 2 diabetes
  • Hepatic histology: Liver fat fraction and inflammation scores relevant to metabolic dysfunction-associated steatotic liver disease (MASLD)
  • Cardiovascular: Blood pressure, lipid panels, and emerging cardiovascular outcome trials
  • Renal: Albuminuria and estimated glomerular filtration rate (eGFR)
  • Musculoskeletal: Osteoarthritis pain and functional scores
  • Sleep: Apnea severity indices

Researchers sourcing retatrutide for clinical trial work can therefore design basket-style protocols that capture multi-system effects within a single compound arm.

Tesofensine's endpoint landscape is narrower. The monoamine mechanism does produce meaningful short-term weight reduction, but the primary safety concern, elevated heart rate and blood pressure from norepinephrine signaling, constrains the populations eligible for inclusion. Patients with pre-existing cardiovascular disease, which represents a large share of the high-BMI population, require careful screening and more intensive monitoring when tesofensine is the study compound.

Key monitoring differences by mechanism class:

Monitoring Domain Retatrutide (GPCR Agonist) Tesofensine (Monoamine Inhibitor)
Gastrointestinal tolerability Titration-managed nausea Minimal
Cardiovascular Blood pressure, lipid trending Heart rate, blood pressure, primary concern
CNS effects Minimal Mood, insomnia, anxiety screening
Glycemic safety Hypoglycemia in T2D combos Not applicable

Trial Population Design and Regulatory Trajectory

Trial Population Design and Regulatory Trajectory

Understanding Retatrutide vs Tesofensine: How Receptor Biology and Monoamine Signaling Shape Metabolic Research Design at the population level reveals another critical divergence. Because retatrutide's titration profile manages gastrointestinal side effects gradually and does not carry significant sympathomimetic cardiovascular load, trial teams can include patients with severe obesity (BMI above 40) and those with established cardiovascular disease. This broadens the generalizability of findings and aligns with regulatory expectations for a broad obesity pharmacotherapy label.

Tesofensine's sympathomimetic activity demands that researchers apply stricter cardiovascular exclusion criteria. This effectively limits the study population to lower-risk participants, which may inflate observed efficacy relative to the general target population, a recognized limitation in earlier phase 2 work.

From a regulatory standpoint, retatrutide is advancing toward new drug application filings following strong phase 3 readouts. Expert and association commentary in 2026 has described it as the first "triple hormone therapy" for obesity, a framing that reflects genuine novelty in the GPCR agonist space. Tesofensine remains a niche investigational compound without a clear path to broad regulatory approval in major markets, making it more relevant as a mechanistic research tool than a clinical development candidate.

Researchers working with related peptide scaffolds can explore resources on GLP-3 triple agonist research planning to understand how multi-receptor designs are being structured across the broader incretin space. Those sourcing materials for cardiometabolic studies should also review AOD 9604 research method notes on storage and traceability for best practices applicable across metabolic peptide protocols.

For researchers looking at specific retatrutide material formats, catalog options such as RETA 20mg for sale and GLP-3 RETA 30mg reflect the range of dosing configurations available for pre-clinical and translational work. Mitochondrial energy expenditure pathways relevant to GcgR activation are explored further in SS-31 mitochondrial research themes.


Conclusion

The comparison of Retatrutide vs Tesofensine: How Receptor Biology and Monoamine Signaling Shape Metabolic Research Design ultimately reduces to one foundational question: which receptor class aligns with the metabolic questions a research team wants to answer?

Retatrutide's triple GPCR agonism enables broad, multi-system endpoint selection, inclusive trial populations, and a regulatory trajectory consistent with eventual clinical adoption. Tesofensine's monoamine reuptake inhibition is a useful mechanistic tool for studying central appetite circuitry, but its cardiovascular monitoring demands and narrow endpoint scope limit its utility in high-risk populations.

Actionable steps for research teams in 2026:

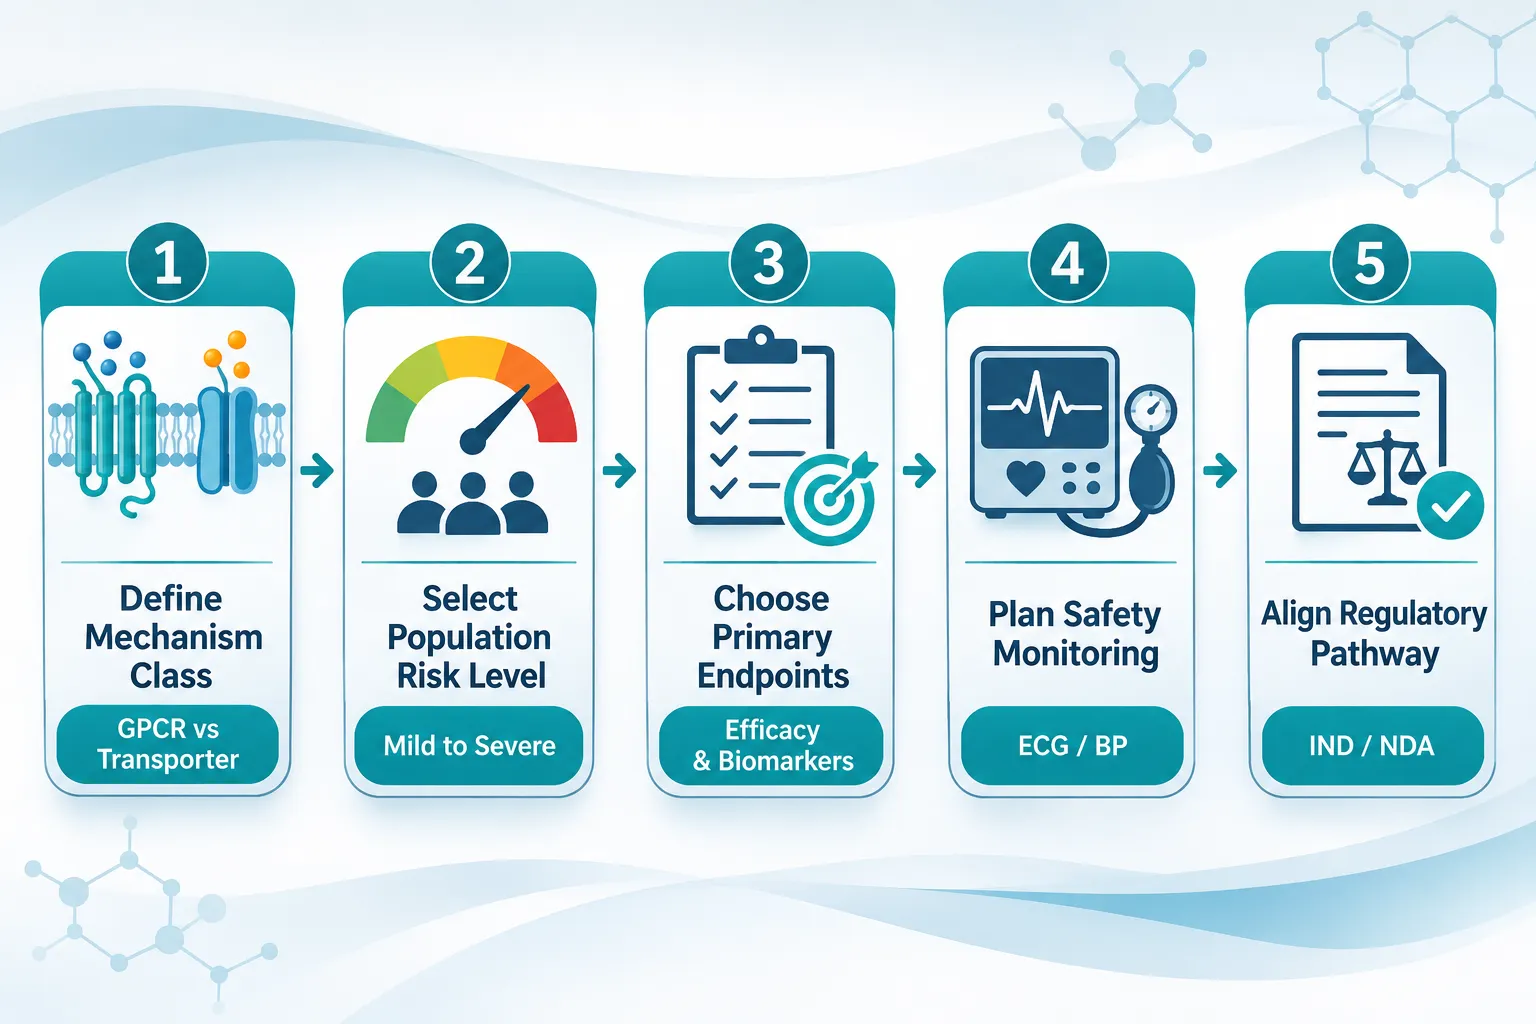
  1. Map receptor targets to endpoints first, confirm that the compound's mechanism can actually produce measurable change at your chosen endpoint before committing to a protocol.
  2. Assess population risk tolerance, monoamine reuptake inhibition requires tighter cardiovascular exclusion criteria; plan for this during power calculations.
  3. Align safety monitoring to mechanism class, GPCR agonists demand GI tolerability tracking and titration schedules; monoamine inhibitors demand heart rate and blood pressure surveillance.
  4. Consider multi-system designs for GPCR agonists, the breadth of retatrutide's receptor engagement supports basket-style trial architectures that would be impractical with monoamine-based compounds.
  5. Track regulatory signals closely, retatrutide's development timeline is accelerating; research programs designed around its mechanism are more likely to translate into clinical practice.

Choosing the right mechanistic scaffold is not merely a pharmacology decision, it is a research design decision that shapes every downstream element of a study.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-vs-tesofensine-how-receptor-biology-and-monoamine-signaling-shape-me.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-31 13:05:202026-10-31 13:05:20Retatrutide vs Tesofensine: How Receptor Biology and Monoamine Signaling Shape Metabolic Research Design
Retatrutide Research Alternatives: Comparing Incretin Peptides, Tesofensine, and Metabolic Small Molecules by Endpoint Fit

Retatrutide Research Alternatives: Comparing Incretin Peptides, Tesofensine, and Metabolic Small Molecules by Endpoint Fit

October 9, 2026/0 Comments/in Uncategorized/by

Selecting the wrong compound for a metabolic research model does not just waste resources, it produces uninterpretable data. That problem is the core reason why retatrutide research alternatives: comparing incretin peptides, tesofensine, and metabolic small molecules by endpoint fit has become one of the most practical questions in preclinical and translational obesity science as of 2026. With retatrutide's TRIUMPH phase 3 program delivering landmark results, including a 23.7% mean body-weight reduction at 68 weeks in the TRIUMPH-4 trial, researchers now need a rigorous framework for matching comparator compounds to specific endpoint targets, not to marketing claims.

Key Takeaways

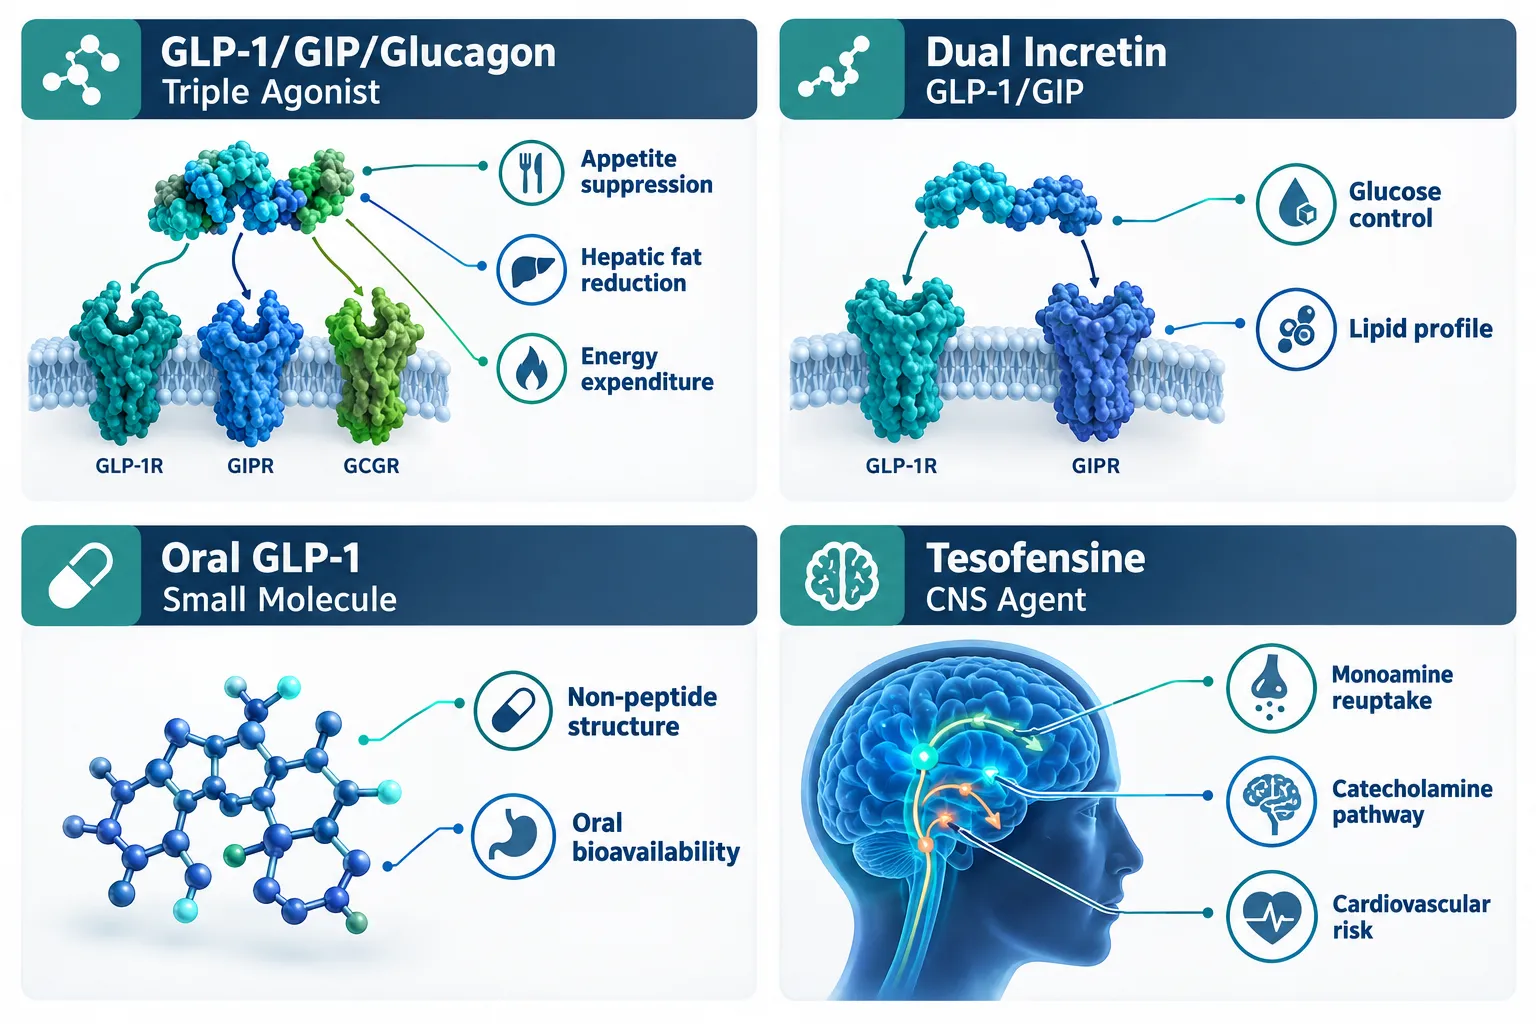
  • Retatrutide's triple agonist mechanism (GLP-1, GIP, glucagon receptors) produces the broadest endpoint coverage of any current incretin peptide, making it a high-bar comparator.
  • Dual incretin peptides like tirzepatide suit glucose and lipid endpoints but offer narrower energy-expenditure signaling than triple agonists.
  • Oral GLP-1 small molecules such as orforglipron expand access research but carry less mature phase 3 data than injectable incretin peptides.
  • Tesofensine addresses catecholamine and central appetite pathways but carries cardiovascular safety concerns that limit endpoint compatibility.
  • Model selection should begin with the primary endpoint, appetite, glucose, lipid, energy expenditure, catecholamine, or receptor signaling, before choosing a compound.

Why Endpoint Fit Matters More Than Compound Popularity

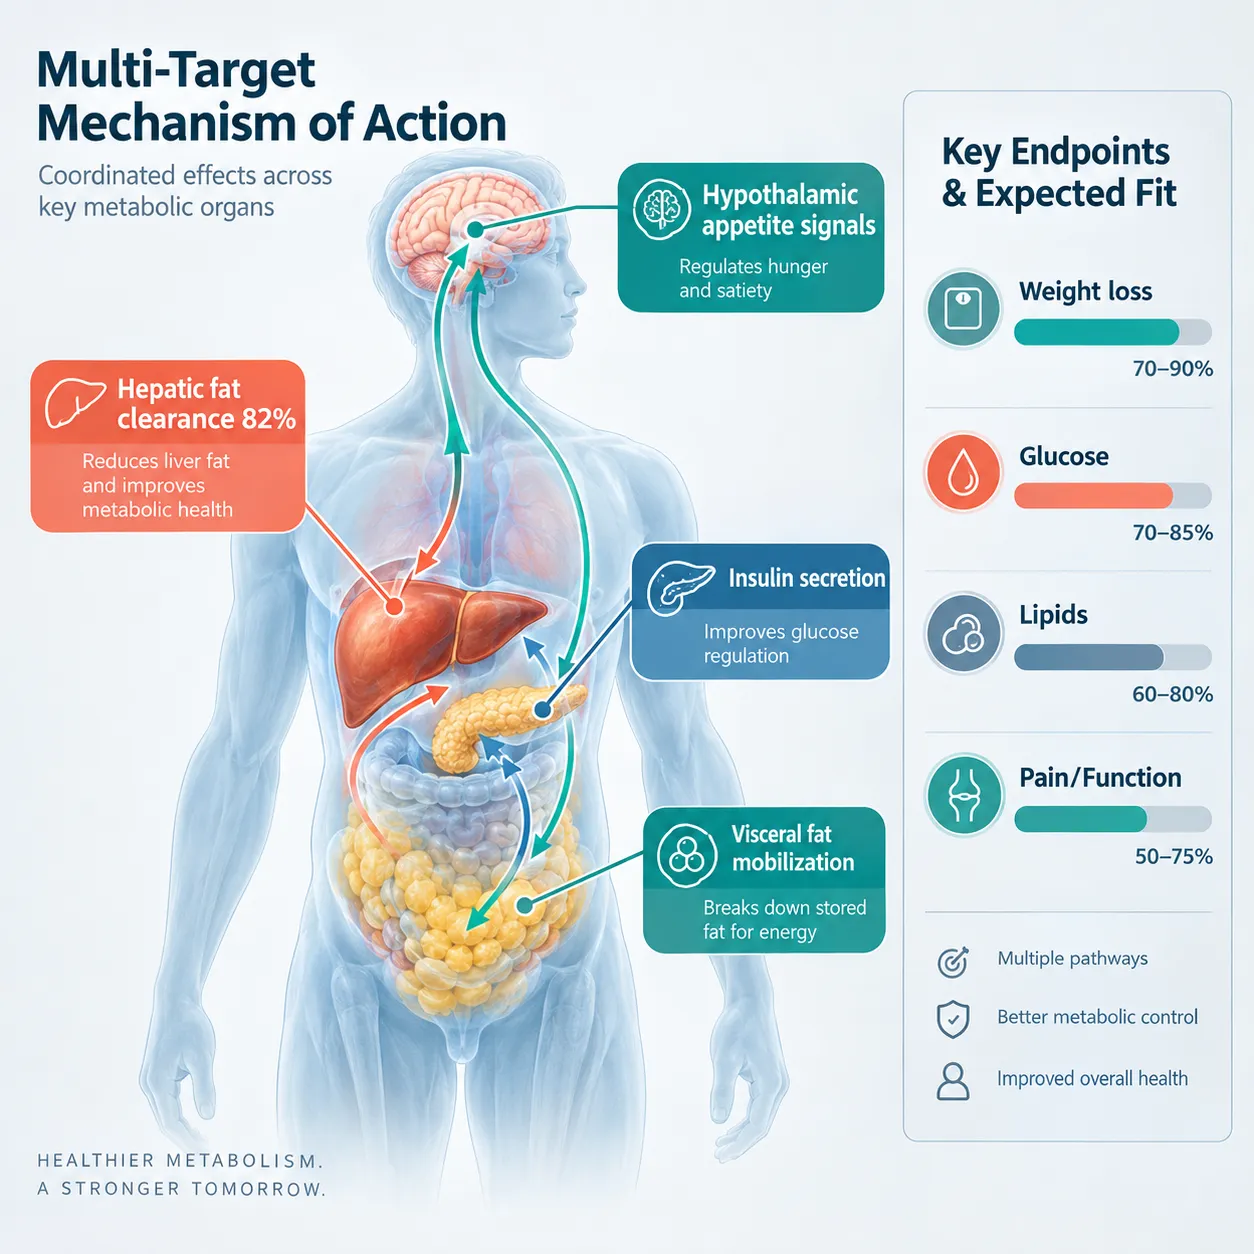
The metabolic research field in 2026 is crowded with potent compounds, and popularity is a poor proxy for scientific fit. Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, generating overlapping signals across appetite suppression, hepatic fat clearance, insulin secretion, and thermogenesis. Phase 2 data showed approximately 82% relative reduction in liver fat alongside a 24.2% mean weight loss at 48 weeks with the 12 mg dose. That breadth is valuable, but it also means retatrutide is a noisy tool when a study only needs to isolate one pathway.

Why Endpoint Fit Matters More Than Compound Popularity

A decision matrix built around the primary research endpoint cuts through this complexity. The six endpoint categories most relevant to metabolic compound selection are:

  • Appetite / satiety signaling, hypothalamic and vagal pathways
  • Glucose homeostasis, insulin secretion, HbA1c, fasting plasma glucose
  • Lipid metabolism, hepatic fat, triglycerides, LDL/HDL profiles
  • Energy expenditure, thermogenesis, resting metabolic rate, glucagon-driven brown adipose activation
  • Catecholamine / monoamine signaling, dopamine, norepinephrine, serotonin reuptake
  • Receptor-level signaling fidelity, clean agonism at a single receptor vs. multi-receptor crosstalk

Mapping each compound to these categories before designing a protocol prevents the most common error in metabolic research: choosing a compound because it produces the largest weight-loss number rather than because it isolates the pathway under investigation.


Incretin Peptides: Where Retatrutide and Its Closest Alternatives Sit

Among injectable incretin peptides, the comparison landscape in 2026 centers on three tiers of receptor engagement.

Retatrutide (GLP-1 / GIP / Glucagon triple agonist) is the highest-coverage option. The meta-analytic evidence across three randomized controlled trials confirms mean weight reduction of approximately 14.33%, BMI reduction of 5.38 units, and meaningful improvements in fasting plasma glucose, HbA1c, and blood pressure, all at very low statistical significance thresholds. For researchers studying retatrutide endpoints that span weight, metabolic, and musculoskeletal outcomes simultaneously, this breadth is the primary advantage. The TRIUMPH program's pairing of weight loss with pain endpoints in TRIUMPH-4 (knee osteoarthritis) and TRIUMPH-7 (chronic low back pain) illustrates this endpoint-fit strategy explicitly.

Tirzepatide (GLP-1 / GIP dual agonist) is the closest comparator for glucose and lipid endpoints without glucagon-driven thermogenesis. TRIUMPH-5 will provide direct head-to-head data against retatrutide in obesity, which will clarify how much the glucagon arm contributes to incremental weight loss and energy expenditure. Until those data arrive, tirzepatide remains the preferred compound when glucagon receptor crosstalk would confound interpretation.

Single GLP-1 receptor agonists (semaglutide class) offer the cleanest receptor-signaling fidelity for studies where isolating GLP-1R biology is the goal. For a broader overview of how these peptide classes are structured mechanistically, the Peptides 101 for Research-Use Only Buyers resource provides a useful structural and mechanistic foundation.

Researchers sourcing GLP-3/retatrutide analogs for preclinical work can review GLP-3 peptides for research use or explore lab tested peptides verified by third-party analysis to ensure compound integrity before endpoint data collection begins.


Tesofensine and Oral Small Molecules: Endpoint Fit for Catecholamine and Access Research

Tesofensine and Oral Small Molecules: Endpoint Fit for Catecholamine and Access Research

Tesofensine: A Legacy CNS Tool With a Narrow Endpoint Window

Tesofensine is a centrally acting triple monoamine reuptake inhibitor, blocking dopamine, norepinephrine, and serotonin reuptake, originally developed for neurodegenerative conditions. In mid-2000s obesity trials, it produced roughly 10-12% weight loss over approximately 24 weeks. That figure is meaningful in absolute terms but is substantially below the 20-24% range seen with retatrutide at higher doses.

More importantly, tesofensine's endpoint fit is narrow and specific:

Endpoint Category Tesofensine Fit Retatrutide Fit
Appetite / CNS satiety Strong (catecholamine) Strong (incretin)
Glucose homeostasis Weak Strong
Hepatic lipid reduction Weak Strong (~82% relative)
Energy expenditure Moderate (sympathomimetic) Strong (glucagon arm)
Cardiovascular safety margin Narrow (HR/BP elevation) Broader (phase 3 data)
Musculoskeletal pain endpoints Not established Active (TRIUMPH-4, 7)

Tesofensine is a legitimate research tool when the study question specifically involves catecholamine-mediated appetite suppression or monoamine pathway modulation. It is not a frontline alternative for glucose, lipid, or energy-expenditure endpoints, and its cardiovascular signal, increased heart rate and blood pressure, introduces confounders in cardiometabolic models. As of 2026, no new phase 3 obesity program for tesofensine has been widely reported, confirming its position as a legacy pharmacologic comparator rather than a contemporary competitor.

Oral GLP-1 Small Molecules: Orforglipron and the Access Endpoint

Orforglipron represents a structurally distinct category: a non-peptide, oral GLP-1 receptor agonist evaluated in the ATTAIN-1 trial for obesity. Its primary research value is not maximum weight-loss magnitude but oral bioavailability and adherence modeling. For studies where the endpoint involves treatment access, patient adherence behavior, or oral-route pharmacokinetics, orforglipron and related oral GLP-1 receptor agonists are the appropriate comparators.

The tradeoff is data maturity. As of early 2026, oral GLP-1 small molecules carry less complete phase 3 obesity data than injectable incretin peptides. Researchers designing studies that will need to reference a robust efficacy benchmark should note this gap when selecting comparators.


Building the Decision Matrix: Matching Compound to Research Question

The practical output of this analysis is a compound-selection protocol driven by the primary endpoint, not by compound prestige. The framework below summarizes the match:

Use retatrutide or a GLP-3 analog when:

  • The primary endpoint spans weight, metabolic markers, and functional outcomes simultaneously
  • Visceral fat research is a core outcome
  • Energy expenditure and glucagon-receptor biology are within scope

Use a dual incretin (tirzepatide class) when:

  • Glucose and lipid endpoints are primary, and glucagon-arm crosstalk would confound
  • Head-to-head incretin comparison is the study design

Use a single GLP-1 agonist when:

  • Receptor-signaling fidelity at GLP-1R alone is required
  • The study needs the cleanest possible GLP-1 pathway attribution

Use tesofensine when:

  • The research question is explicitly about monoamine reuptake inhibition or catecholamine-mediated satiety
  • Cardiovascular confounders are controlled for or are themselves the endpoint

Use oral GLP-1 small molecules when:

  • The endpoint involves oral-route pharmacology, adherence, or access modeling
  • Injectable peptide format is a study constraint

Building the Decision Matrix: Matching Compound to Research Question

Researchers reviewing the full retatrutide clinical trials landscape, including TRIUMPH-1 through TRIUMPH-8, will find that Eli Lilly's own endpoint-fit strategy mirrors this matrix: each TRIUMPH sub-study pairs retatrutide's weight-loss mechanism with a distinct comorbidity endpoint, from knee osteoarthritis pain to chronic low back pain to long-term weight maintenance. That design logic is directly transferable to preclinical model selection.

For researchers sourcing compounds, the TESA IPA blend peptide page offers a relevant example of how multi-mechanism blends are positioned for specific research applications, reinforcing the endpoint-fit principle at the product level.


Conclusion

The most consequential decision in metabolic peptide research is not which compound produces the largest effect size, it is which compound isolates the pathway the study is actually designed to interrogate. Retatrutide research alternatives: comparing incretin peptides, tesofensine, and metabolic small molecules by endpoint fit is not an academic exercise; it is a protocol-design requirement.

Actionable next steps for research teams in 2026:

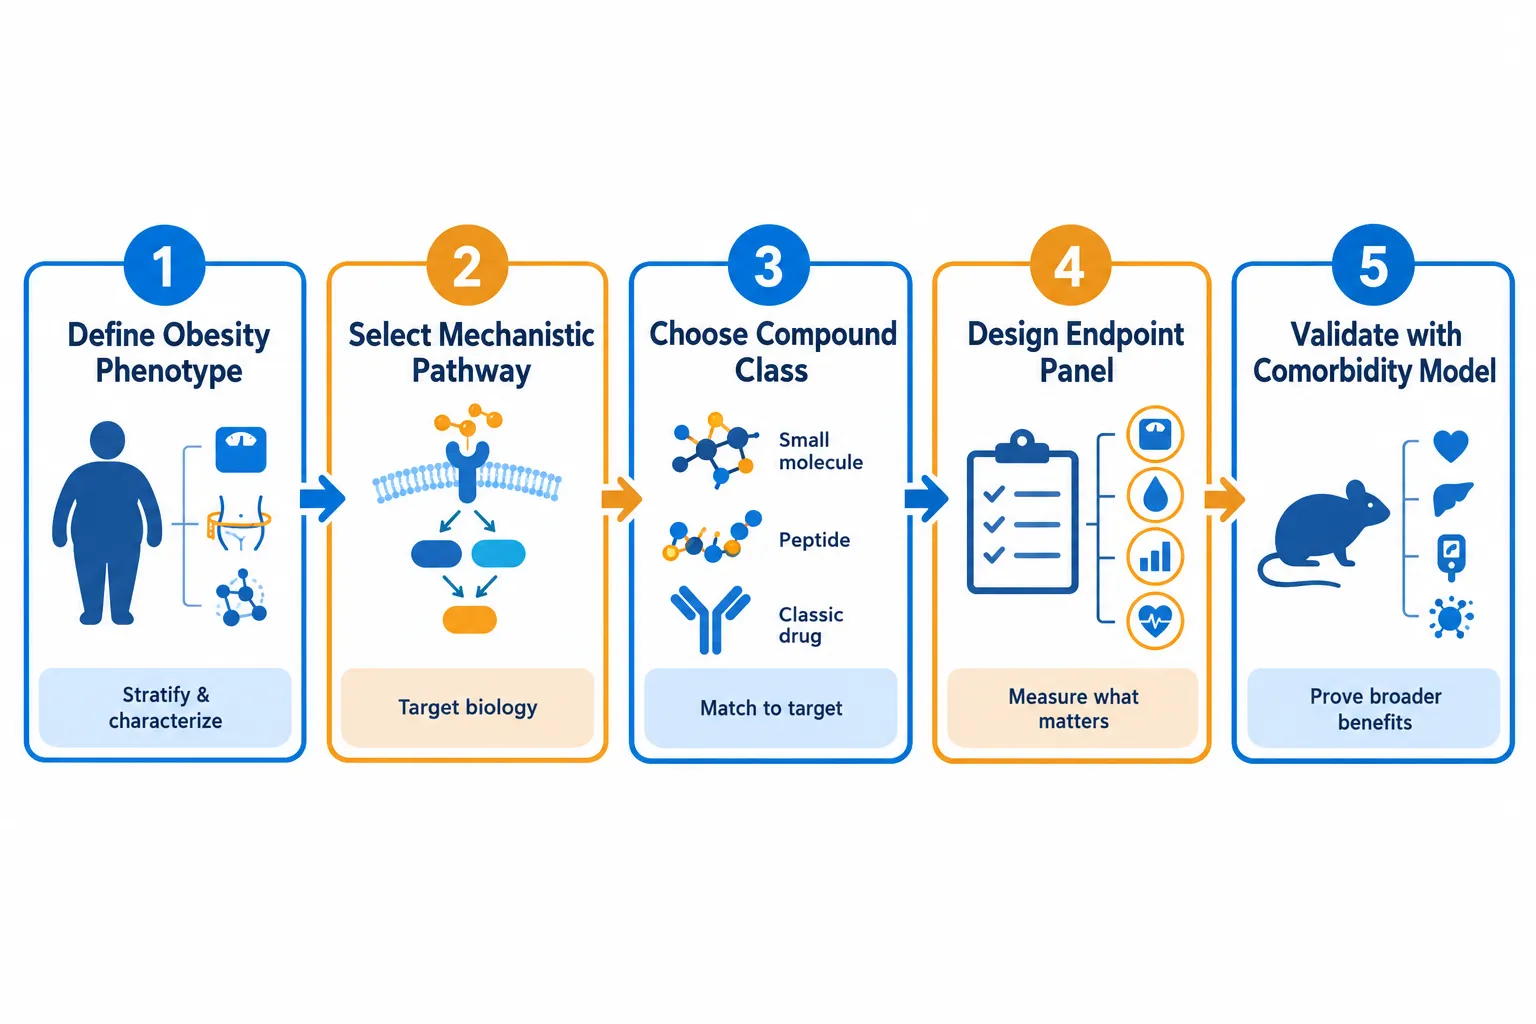
  1. Define the primary endpoint category first, appetite, glucose, lipid, energy expenditure, catecholamine, or receptor signaling, before shortlisting compounds.
  2. Use retatrutide or GLP-3 analogs for broad metabolic and functional endpoint studies; use single-receptor agonists when signaling fidelity is paramount.
  3. Reserve tesofensine for CNS monoamine pathway studies with appropriate cardiovascular controls.
  4. Monitor TRIUMPH phase 3 readouts through 2026 to update the efficacy benchmarks used in comparator selection.
  5. Verify compound purity through third-party testing before any endpoint data collection begins, using lab tested peptides from verified suppliers.

Endpoint fit, not headline weight-loss numbers, is the standard that produces reproducible, interpretable metabolic research.

https://www.puretestedpeptides.com/wp-content/uploads/2026/10/retatrutide-research-alternatives-comparing-incretin-peptides-tesofensine-and-me.webp 672 1008 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-10-09 13:10:262026-10-09 13:10:26Retatrutide Research Alternatives: Comparing Incretin Peptides, Tesofensine, and Metabolic Small Molecules by Endpoint Fit
GLP-1 Peptide Alternatives: How Retatrutide, Tesofensine, and Traditional Weight-Loss Drugs Differ in Research Models

GLP-1 Peptide Alternatives: How Retatrutide, Tesofensine, and Traditional Weight-Loss Drugs Differ in Research Models

September 30, 2026/0 Comments/in Uncategorized/by

Obesity-related metabolic disease now affects more than one billion people worldwide, yet the pharmacological tools available to researchers have expanded dramatically in just the past few years. At the center of that expansion sits a deceptively simple question: what separates the new wave of receptor-targeted compounds from the older drugs that came before them? Exploring GLP-1 peptide alternatives, how retatrutide, tesofensine, and traditional weight-loss drugs differ in research models, reveals not just a difference in potency, but a fundamental shift in how scientists approach metabolic endpoints, receptor pharmacology, and trial design.

Key Takeaways

  • Retatrutide activates three receptors simultaneously (GLP-1R, GIPR, GcgR), producing greater weight-loss magnitude in preclinical and clinical models than any single-receptor agent.
  • Tesofensine works through monoamine reuptake inhibition in the central nervous system, a mechanism distinct from peptide-based receptor agonism.
  • Traditional agents such as orlistat and phentermine act peripherally or centrally through narrow pathways, limiting both efficacy and comorbidity coverage.
  • Modern research models prioritize multi-domain endpoints, cardiometabolic, hepatic, and renal outcomes, rather than weight reduction alone.
  • Purity and reference-standard quality are critical variables when comparing compound performance across preclinical studies.

Receptor Pharmacology: The Foundation of Difference

Receptor Pharmacology: The Foundation of Difference

Understanding GLP-1 peptide alternatives begins at the receptor level. GLP-1 receptor agonists mimic glucagon-like peptide-1, a gut-derived incretin hormone that signals satiety to the hypothalamus and regulates insulin secretion. First-generation compounds such as exenatide targeted only GLP-1R. Dual agonists like tirzepatide added glucose-dependent insulinotropic polypeptide receptor (GIPR) activation, amplifying both metabolic and appetite effects.

Retatrutide takes this further by adding glucagon receptor (GcgR) agonism to the GLP-1R and GIPR combination. This triple-receptor engagement increases energy expenditure through thermogenic mechanisms while simultaneously reducing caloric intake and improving hepatic fat metabolism. Researchers studying retatrutide clinical trials have noted that this layered mechanism produces additive, and in some models, synergistic, effects across metabolic pathways.

Tesofensine operates through an entirely different mechanism. It inhibits the presynaptic reuptake of dopamine, norepinephrine, and serotonin in the central nervous system. This monoamine reuptake inhibition reduces appetite via hypothalamic pathways but does not engage incretin receptors, insulin signaling, or glucagon pathways. The result is a narrower metabolic footprint compared to triple agonists.

Traditional agents occupy an even narrower pharmacological space:

  • Orlistat blocks pancreatic lipase in the gut, reducing dietary fat absorption by roughly 30%
  • Phentermine stimulates norepinephrine release, suppressing appetite centrally
  • Topiramate modulates GABA receptors and voltage-gated channels with appetite suppression as a secondary effect

"The shift from peripheral lipase inhibition to multi-receptor hormonal agonism represents one of the most significant mechanistic leaps in metabolic pharmacology in decades."


Weight-Loss Magnitude and Metabolic Endpoints in Research Models

Weight-Loss Magnitude and Metabolic Endpoints in Research Models

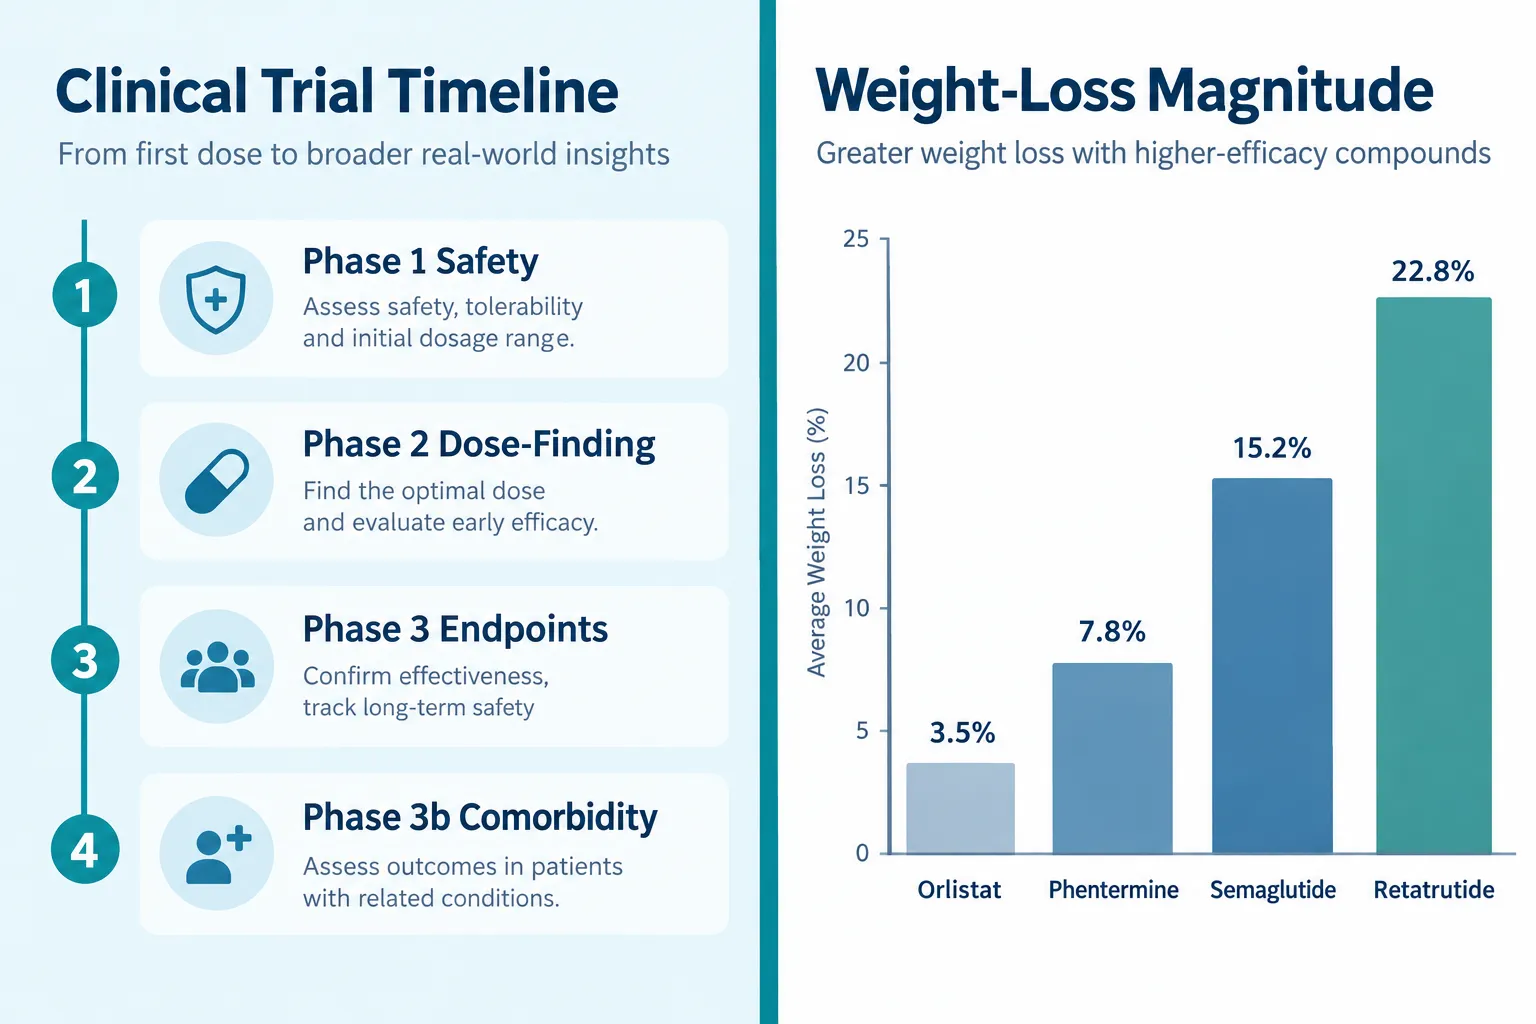
When comparing compounds in controlled research models, weight-loss magnitude is the most cited metric, but it is far from the only one. Phase 2 data for retatrutide demonstrated mean body weight reductions exceeding 17% at 24 weeks in human subjects, a figure that surpassed both semaglutide and tirzepatide benchmarks at comparable timepoints. Researchers tracking retatrutide endpoints have documented simultaneous improvements in triglycerides, fasting glucose, liver fat fraction, and blood pressure.

Tesofensine phase 2 trials showed weight reductions of approximately 10-12% over 24 weeks, meaningful but below the triple-agonist range. Traditional agents typically produce 5-8% weight loss over 12 months, with limited effects on cardiometabolic markers beyond what weight loss itself produces.

Visceral fat is a particularly important endpoint in modern models. Retatrutide's GcgR component appears to preferentially mobilize visceral adipose tissue, which carries the highest cardiometabolic risk. Research into visceral fat research confirms that visceral depot reduction correlates more strongly with metabolic improvement than total body weight alone.

Comparative Weight-Loss Summary Across Model Types

Compound Class Primary Mechanism Approx. Weight Loss (Research Models)
Retatrutide (triple agonist) GLP-1R + GIPR + GcgR 17-24%
Semaglutide (GLP-1 mono) GLP-1R only 12-15%
Tesofensine Monoamine reuptake inhibition 10-12%
Orlistat / Phentermine Lipase inhibition / NE release 5-8%

Trial Design, Safety Profiles, and the Future of GLP-1 Peptide Alternatives in Research Models

Trial Design, Safety Profiles, and the Future of GLP-1 Peptide Alternatives in Research Models

The design of research models has evolved alongside the compounds themselves. Early trials for orlistat and phentermine measured weight as the sole primary endpoint over 12-52 weeks. Modern phase 3 programs for retatrutide span multiple years and incorporate cardiovascular outcomes, liver histology, kidney function, and quality-of-life measures as co-primary or key secondary endpoints. This comorbidity-focused architecture reflects the understanding that metabolic disease is systemic, not merely a matter of body mass index.

For researchers sourcing compounds for preclinical work, the quality of the peptide used directly affects the reproducibility of results. Resources like Bachem and reference standards for peptide benchmarks highlight how reference-grade materials reduce inter-study variability. Researchers exploring GLP-3 peptide options or looking to buy Reta GLP-3 peptide should prioritize suppliers with verified purity documentation.

Safety profiles also diverge significantly across compound classes:

  • Retatrutide and GLP-1 agonists share a gastrointestinal tolerability profile (nausea, vomiting at initiation) that is dose-dependent and typically transient
  • Tesofensine carries cardiovascular monitoring requirements due to its sympathomimetic properties, including modest increases in heart rate and blood pressure
  • Traditional agents like orlistat produce gastrointestinal side effects tied to fat malabsorption; phentermine carries addiction and cardiovascular risk considerations

As of late 2026, retatrutide is advancing through a global phase 3 program with cardiovascular outcomes data expected to shape its regulatory pathway. Tesofensine remains in development for specific obesity subpopulations. Neither is approved for clinical use, and both are studied exclusively in research contexts.


Conclusion

The landscape of GLP-1 peptide alternatives, how retatrutide, tesofensine, and traditional weight-loss drugs differ in research models, reflects a broader transformation in metabolic science. Receptor pharmacology, not just caloric restriction, now drives compound selection. Retatrutide's triple-agonist mechanism sets a new benchmark for weight-loss magnitude and multi-domain endpoint coverage. Tesofensine offers a distinct CNS-based pathway with meaningful but more limited metabolic reach. Traditional agents remain reference points for historical comparison rather than leading candidates in modern research design.
Actionable next steps for researchers:

  1. Align compound selection with the specific receptor pathways relevant to the research question
  2. Prioritize reference-standard purity to ensure reproducible preclinical outcomes
  3. Design studies around multi-domain endpoints, including visceral fat, hepatic markers, and cardiometabolic indicators
  4. Monitor regulatory developments for retatrutide's phase 3 cardiovascular outcomes data, expected to redefine treatment algorithm modeling
  5. Consult verified suppliers for research-grade GLP-1 pathway compounds, including options available through GLP peptide for sale and GLP-1 Reta peptide product lines
https://www.puretestedpeptides.com/wp-content/uploads/2026/09/glp-1-peptide-alternatives-how-retatrutide-tesofensine-and-traditional-weight-lo.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-30 13:33:042026-09-30 13:33:04GLP-1 Peptide Alternatives: How Retatrutide, Tesofensine, and Traditional Weight-Loss Drugs Differ in Research Models
Tesofensine vs GLP-3 Retatrutide: Comparing Appetite, Dopamine, Noradrenergic, and Incretin Signaling

Tesofensine vs GLP-3 Retatrutide: Comparing Appetite, Dopamine, Noradrenergic, and Incretin Signaling

September 30, 2026/0 Comments/in Uncategorized/by

Obesity pharmacology has split into two sharply different philosophies: rewire the brain's reward circuitry with monoamine reuptake inhibition, or flood peripheral and central receptors with gut-derived hormone signals. Tesofensine vs GLP-3 Retatrutide: Comparing Appetite, Dopamine, Noradrenergic, and Incretin Signaling sits at the center of that debate, and the contrast reveals just how many routes the body uses to regulate food intake, energy expenditure, and metabolic homeostasis.

Key Takeaways

  • Tesofensine suppresses appetite by blocking dopamine, norepinephrine, and serotonin reuptake in the central nervous system, while retatrutide activates three distinct gut-hormone receptors simultaneously.
  • Retatrutide's triple agonism at GLP-1, GIP, and glucagon receptors produces weight loss of up to 24% in phase 2 data, with phase 3 TRIUMPH-2 trials ongoing as of 2026.
  • Tesofensine's monoamine mechanism raises distinct cardiovascular and neuropsychiatric monitoring concerns not shared by incretin-based agents.
  • Both compounds converge on reduced caloric intake, but through entirely different upstream signaling cascades.
  • Retatrutide shows broader metabolic potential, including hepatic glucose regulation and improvements in insulin sensitivity, beyond appetite suppression alone.

How Tesofensine Works: Dopamine, Noradrenergic, and Serotonin Reuptake Inhibition

Tesofensine is a triple monoamine reuptake inhibitor. It blocks the reuptake transporters for dopamine, norepinephrine, and serotonin in presynaptic neurons, extending the time these neurotransmitters remain active in the synaptic cleft.

Tesofensine vs retatrutide mechanism-of-action diagram with receptor callouts

Dopamine signaling is central to reward-driven eating. By prolonging dopamine availability in the mesolimbic and hypothalamic pathways, tesofensine reduces the motivational drive to seek food, particularly calorie-dense, highly palatable foods. This is sometimes described as blunting hedonic hunger.

Noradrenergic signaling adds a second layer. Elevated norepinephrine in the hypothalamus activates alpha-2 adrenergic receptors and suppresses orexigenic neuropeptide Y (NPY) signaling, a well-established appetite-stimulating pathway. The result is a reduction in homeostatic hunger alongside the hedonic suppression from dopamine.

Serotonergic contributions are comparatively modest in tesofensine's profile but reinforce satiety signaling through 5-HT2C receptor activation, a mechanism shared with older weight-loss agents like lorcaserin.

"Tesofensine's strength is its central reach, it simultaneously targets reward, homeostatic, and satiety circuits in the brain."

Phase 2 clinical data showed meaningful short-term weight reduction, with some studies reporting 6-10% body weight loss over 24 weeks. However, cardiovascular monitoring remains a critical safety endpoint because elevated norepinephrine tone can increase heart rate and blood pressure. Neuropsychiatric effects, including insomnia and mood changes, are also tracked closely given the dopaminergic mechanism.

For researchers exploring peptide-based mechanisms, the Peptides 101 guide covering GLP-3, MOTS-C, and 5-Amino-1MQ provides useful structural context on how different compound classes interact with metabolic pathways.


How Retatrutide Works: Triple Incretin and Glucagon Receptor Agonism

Retatrutide operates on an entirely different axis. Rather than modulating neurotransmitter availability, it acts as a simultaneous agonist at three receptors: glucagon-like peptide-1 (GLP-1), glucose-dependent insulinotropic polypeptide (GIP), and glucagon receptors. This is why it is often labeled a GLP-3 receptor agonist in research contexts, the triple-receptor profile distinguishes it from dual agonists like tirzepatide.

Retatrutide vs tesofensine clinical trial weight loss comparison 2026

GLP-1 receptor agonism slows gastric emptying, enhances glucose-dependent insulin secretion, and activates hypothalamic satiety neurons directly. This is the mechanism shared with semaglutide.

GIP receptor agonism amplifies the insulinotropic response and may improve adipocyte insulin sensitivity, reducing lipid overflow into non-adipose tissues.

Glucagon receptor agonism is the differentiating element. Glucagon increases hepatic glucose output and, critically, raises basal energy expenditure by stimulating fatty acid oxidation. This thermogenic effect means retatrutide does not simply reduce caloric intake, it also increases the rate at which stored energy is burned.

Phase 2 data from the retatrutide clinical trial program demonstrated up to 24.2% body weight reduction at 48 weeks, a figure that exceeds any approved anti-obesity pharmacotherapy to date. The TRIUMPH-2 phase 3 program, actively enrolling and reporting interim data through 2026, is evaluating these outcomes at scale across diverse populations.

Researchers can review available GLP-3 retatrutide peptide formats as part of ongoing preclinical investigation.


Side-by-Side Comparison: Signaling Pathways, Efficacy, and Safety

Feature Tesofensine Retatrutide
Primary mechanism Monoamine reuptake inhibition Triple receptor agonism (GLP-1, GIP, glucagon)
Appetite pathway Dopamine, norepinephrine, serotonin Incretin hormones, hypothalamic GLP-1R
Energy expenditure Modest increase via noradrenergic tone Significant increase via glucagon receptor
Glucose regulation Indirect, secondary to weight loss Direct via GLP-1 and GIP insulinotropic action
Phase 2 weight loss 6-10% over 24 weeks Up to 24% over 48 weeks
Key safety watch Heart rate, blood pressure, mood GI tolerability, gallbladder, heart rate
Regulatory status (2026) Phase 2 completed; not approved Phase 3 TRIUMPH-2 ongoing

Metabolic Scope Beyond Weight Loss

The comparison in Tesofensine vs GLP-3 Retatrutide: Comparing Appetite, Dopamine, Noradrenergic, and Incretin Signaling extends well beyond the scale.

Retatrutide metabolic signaling organs liver pancreas hypothalamus diagram

Retatrutide's glucagon component raises its potential in non-alcoholic fatty liver disease (NAFLD) and metabolic-associated steatohepatitis (MASH), conditions driven by hepatic lipid accumulation. By stimulating hepatic fatty acid oxidation, retatrutide addresses the liver pathology that often accompanies severe obesity, a target tesofensine does not reach directly.

Tesofensine, by contrast, may have a role in populations where central reward dysregulation is the dominant driver of excess intake, such as binge-eating phenotypes, given its direct action on dopaminergic circuits. Its noradrenergic component also raises the possibility of mild thermogenic benefit, though this is modest compared to retatrutide's glucagon-driven energy expenditure increase.

For research teams studying broader peptide pharmacology, resources on peptides and polypeptides in endocrine pharmacology offer relevant mechanistic context. Those sourcing GLP-3 peptides for research use should verify purity documentation and third-party testing before use.


Conclusion

The Tesofensine vs GLP-3 Retatrutide: Comparing Appetite, Dopamine, Noradrenergic, and Incretin Signaling framework makes clear that these are not competing versions of the same drug, they are fundamentally different tools built on different biological theories of obesity.

Actionable next steps for researchers and clinicians in 2026:

  • Monitor TRIUMPH-2 phase 3 interim data releases for retatrutide's cardiovascular and hepatic endpoints, which will define its approval trajectory.
  • Evaluate tesofensine's monoamine profile in study designs focused on reward-driven eating behavior, where dopaminergic modulation may offer unique mechanistic insight.
  • When designing metabolic research protocols, consider whether the target endpoint is central appetite regulation (favoring monoamine approaches) or peripheral metabolic correction (favoring incretin-glucagon agonism).
  • Ensure all research-grade peptide sourcing uses lab-tested peptides with verified purity certificates to maintain experimental integrity.

Both compounds represent serious scientific advances. Retatrutide's efficacy data currently leads by a wide margin, but tesofensine's neurochemical mechanism keeps it relevant for specific research questions that incretin agonists cannot address.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/tesofensine-vs-glp-3-retatrutide-comparing-appetite-dopamine-noradrenergic-and-i.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-30 13:20:102026-09-30 13:20:10Tesofensine vs GLP-3 Retatrutide: Comparing Appetite, Dopamine, Noradrenergic, and Incretin Signaling
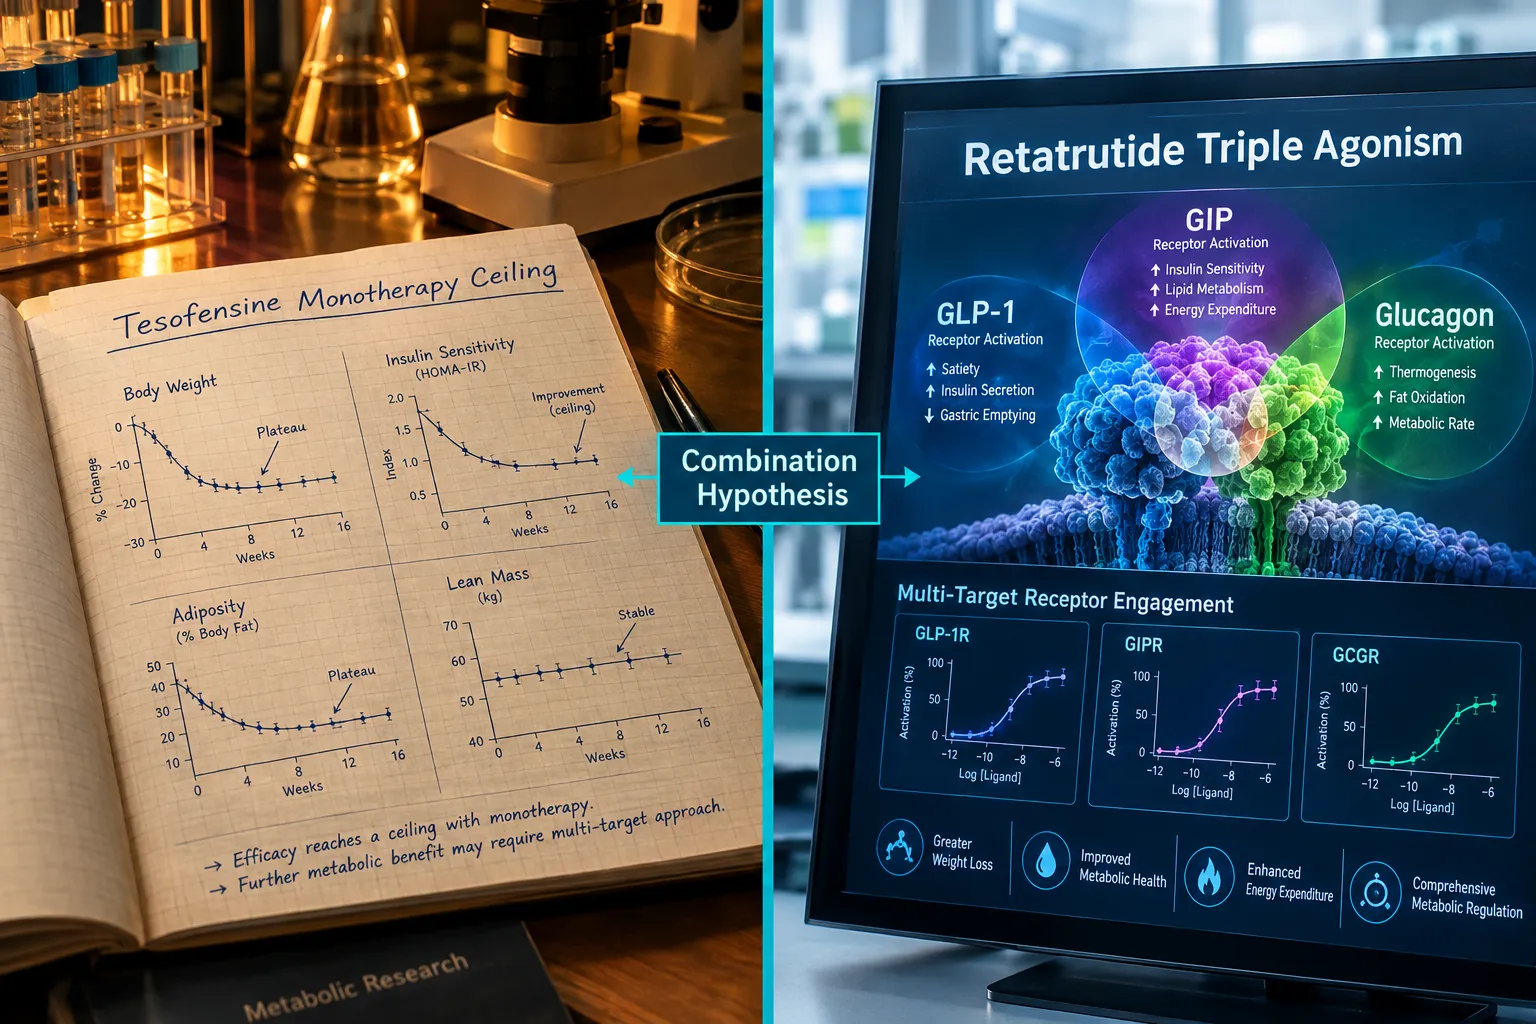
Tesofensine and GLP-3 Retatrutide: Advanced Combination Hypotheses for Future Metabolic Research

Tesofensine and GLP-3 Retatrutide: Advanced Combination Hypotheses for Future Metabolic Research

September 6, 2026/0 Comments/in Uncategorized/by

Obesity affects more than one billion people globally, yet even the most effective single-agent therapies leave a meaningful subset of patients with incomplete or plateauing responses. That gap is precisely where the intersection of tesofensine and GLP-3 retatrutide: advanced combination hypotheses for future metabolic research becomes one of the most intellectually compelling frontiers in 2026 pharmacology.

Both agents operate through fundamentally different biological axes. Retatrutide targets three distinct hormonal receptors simultaneously, while tesofensine modulates central nervous system neurotransmitter reuptake. Studying them together, even hypothetically, raises important questions about complementary mechanisms, additive efficacy, and the safety boundaries of multi-target metabolic intervention.

Key Takeaways

  • Retatrutide is a triple agonist acting on GLP-1, GIP, and glucagon receptors, producing substantial weight loss in Phase 2 trials.
  • Tesofensine suppresses appetite through central noradrenergic, dopaminergic, and serotonergic reuptake inhibition.
  • Their mechanistic separation, peripheral hormonal vs. central neural, forms the theoretical basis for combination research hypotheses.
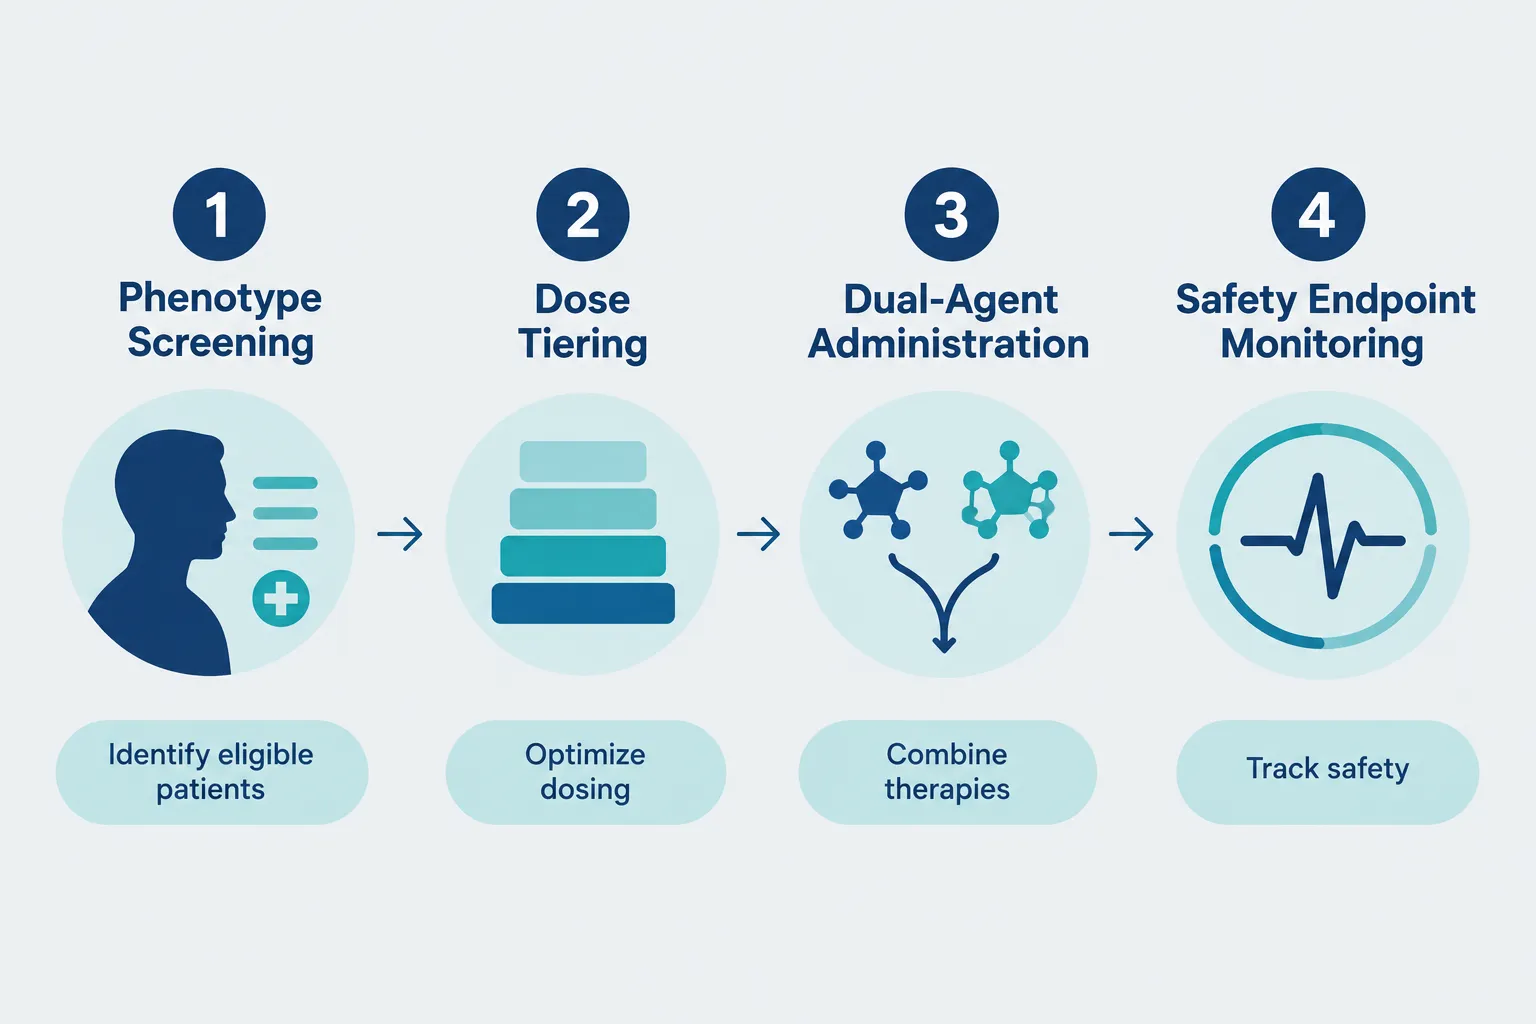
  • Three distinct research frameworks exist: CNS-plus-peripheral synergy, plateau-breaking strategies, and phenotype-guided tiered regimens.
  • Any future combination study must rigorously address cardiovascular, neurological, and gastrointestinal safety endpoints.

Understanding the Two Agents Individually

Understanding the Two Agents Individually

Before exploring combination hypotheses, it helps to understand what each compound does on its own.

Retatrutide is a single-molecule triple agonist that activates GLP-1, GIP, and glucagon receptors simultaneously. This multi-receptor engagement drives energy expenditure, reduces caloric intake, improves insulin sensitivity, and promotes fat oxidation. Phase 2 trial data showed average body weight reductions exceeding 17% at 24 weeks in participants with obesity, a magnitude that surpassed earlier dual-agonist results. For a deeper look at how this receptor profile operates at the cellular level, see Peptides Mechanism 101: From GLP-3 Retatrutide to CJC-1295 and MOTS-c.

Tesofensine works through an entirely different axis. It inhibits the presynaptic reuptake of noradrenaline, dopamine, and serotonin in the central nervous system, reducing appetite and increasing satiety signals from the hypothalamus. Originally investigated for Parkinson's disease, it was repurposed for obesity after trials demonstrated significant weight reduction. Unlike retatrutide, tesofensine does not directly engage incretin or glucagon pathways.

"The mechanistic distance between these two agents, one peripheral and hormonal, one central and neural, is precisely what makes their theoretical combination worth examining."

This separation of mechanism is the foundational rationale for exploring tesofensine and GLP-3 retatrutide: advanced combination hypotheses for future metabolic research.

Three Research Hypotheses Worth Investigating

Three Research Hypotheses Worth Investigating

Hypothesis 1: CNS Appetite Suppression Plus Peripheral Triple Agonism

The most straightforward hypothesis proposes that tesofensine's central appetite-suppressing effects could complement retatrutide's peripheral metabolic actions without significant pathway overlap.

Retatrutide reduces appetite partly through GLP-1 receptor signaling in the brain, but its primary metabolic work occurs at peripheral tissues, liver, pancreas, adipose, and skeletal muscle. Tesofensine, by contrast, operates upstream in the hypothalamus and striatum. Combining them could theoretically produce additive appetite suppression while simultaneously addressing the peripheral metabolic dysfunction that drives obesity.

Key research endpoints for this hypothesis would include:

  • Total energy intake reduction (caloric diary and indirect calorimetry)
  • Resting metabolic rate changes over 12 to 24 weeks
  • Adipokine panels including leptin and adiponectin
  • CNS tolerability markers such as heart rate variability and blood pressure

Researchers exploring retatrutide's expanding metabolic applications should also review Retatrutide and MASLD: How Triple-Agonist Research Is Reframing Liver Fat Endpoints for context on how peripheral endpoints are being defined.

Hypothesis 2: Breaking Weight-Loss Plateaus and Addressing Response Heterogeneity

A second hypothesis addresses a well-documented clinical problem: weight-loss plateaus. Even with powerful agents like retatrutide, some research subjects show diminishing returns after initial rapid loss. This plateau likely reflects adaptive neurobiological responses, the brain compensating for reduced energy stores by increasing hunger drive.

Tesofensine's central mechanism could theoretically interrupt this adaptive hunger signaling, allowing the peripheral metabolic improvements driven by retatrutide to continue progressing. This is particularly relevant given that GLP-3 Retatrutide in Phase 3 Trials data continues to reveal subpopulations with variable response rates.

Proposed endpoints for this framework:

  • Plateau onset timing (weeks to weight stabilization)
  • Hunger hormone panels (ghrelin, peptide YY) at plateau phase
  • Responder vs. non-responder stratification by baseline BMI and metabolic phenotype

Hypothesis 3: Phenotype-Guided, Tiered Regimens for Severe or Refractory Obesity

The most ambitious hypothesis envisions a tiered approach where retatrutide serves as a foundational metabolic agent and tesofensine is added selectively for individuals who meet specific neurobiological or behavioral criteria, such as elevated reward-driven eating scores or documented hypothalamic resistance.

This aligns with the broader direction discussed in Triple Agonist Therapies Beyond GLP-3, where multi-target peptide design is increasingly viewed as phenotype-dependent rather than universal.

Safety Considerations for Any Future Combination Protocol

Safety Considerations for Any Future Combination Protocol

No combination hypothesis is scientifically credible without a parallel safety framework. Both agents carry individual risk profiles that could interact in meaningful ways.

Cardiovascular monitoring is the most critical concern. Tesofensine has demonstrated modest increases in heart rate and blood pressure in prior trials. Retatrutide's glucagon agonism also carries cardiovascular implications. Any combination protocol would require continuous telemetry and strict blood pressure inclusion criteria.

Gastrointestinal tolerability is a secondary concern. Retatrutide's GLP-1 component produces nausea and vomiting in a proportion of subjects. Adding tesofensine, which can cause dry mouth and constipation, may compound GI burden.

Neuropsychiatric endpoints must also be tracked. Tesofensine's monoamine reuptake inhibition raises questions about mood, anxiety, and sleep architecture when combined with the neuroendocrine effects of triple agonism.

For researchers building multi-agent protocols, the foundational pharmacology resource Peptides 101 for Research-Use Only Buyers provides useful structural context.

The current Phase 3 landscape for retatrutide, outlined in Retatrutide Phase 3 and Beyond, will also generate safety data that future combination researchers will need as a baseline reference.

Conclusion

The intersection of tesofensine and GLP-3 retatrutide: advanced combination hypotheses for future metabolic research represents a scientifically grounded but still speculative area of inquiry. The mechanistic separation between central neural appetite modulation and peripheral hormonal metabolic regulation creates a logical basis for studying these agents together, but that logic must be tested rigorously before any conclusions are drawn.

Actionable next steps for research teams:

  1. Map the individual receptor and neurotransmitter profiles of each agent against known interaction databases before designing any co-administration protocol.
  2. Define phenotype-specific inclusion criteria to identify which subject profiles are most likely to benefit from dual-mechanism approaches.
  3. Establish cardiovascular and neuropsychiatric safety endpoints as primary, not secondary, outcomes in any pilot study design.
  4. Monitor Phase 3 retatrutide safety data as it emerges, this will serve as the essential baseline for any future combination work.

The field is moving toward precision metabolic medicine. Combination hypotheses like these are not merely speculative exercises; they are the early intellectual scaffolding on which tomorrow's trials will be built.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/tesofensine-and-glp-3-retatrutide-advanced-combination-hypotheses-for-future-met.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-06 13:04:092026-09-06 13:04:09Tesofensine and GLP-3 Retatrutide: Advanced Combination Hypotheses for Future Metabolic Research
Best Nasal Spray Peptides for Cognitive and Appetite Research: Semax, Selank, Klow Spray, and Tesofensine Compared

Best Nasal Spray Peptides for Cognitive and Appetite Research: Semax, Selank, Klow Spray, and Tesofensine Compared

September 2, 2026/0 Comments/in Uncategorized/by

Fewer than one in ten research compounds reach clinical advisory review at the FDA level, yet as of 2026, Semax is formally scheduled before the US Pharmacy Compounding Advisory Committee, a milestone that sets it apart from most peptides still confined to unregulated research markets. For labs evaluating intranasal peptide options, this regulatory asymmetry matters as much as formulation chemistry. This guide to the best nasal spray peptides for cognitive and appetite research: Semax, Selank, Klow Spray, and Tesofensine compared covers formulation details, excipients, dosing schemes, and bioavailability considerations that directly affect ordering decisions.

Key Takeaways

  • Semax and Selank are the dominant intranasal cognitive peptides in 2026, often combined in a single spray for complementary nootropic and anxiolytic effects.
  • Klow Spray is a branded intranasal blend designed for appetite and metabolic research, while Tesofensine is a monoamine reuptake inhibitor studied primarily for appetite suppression.
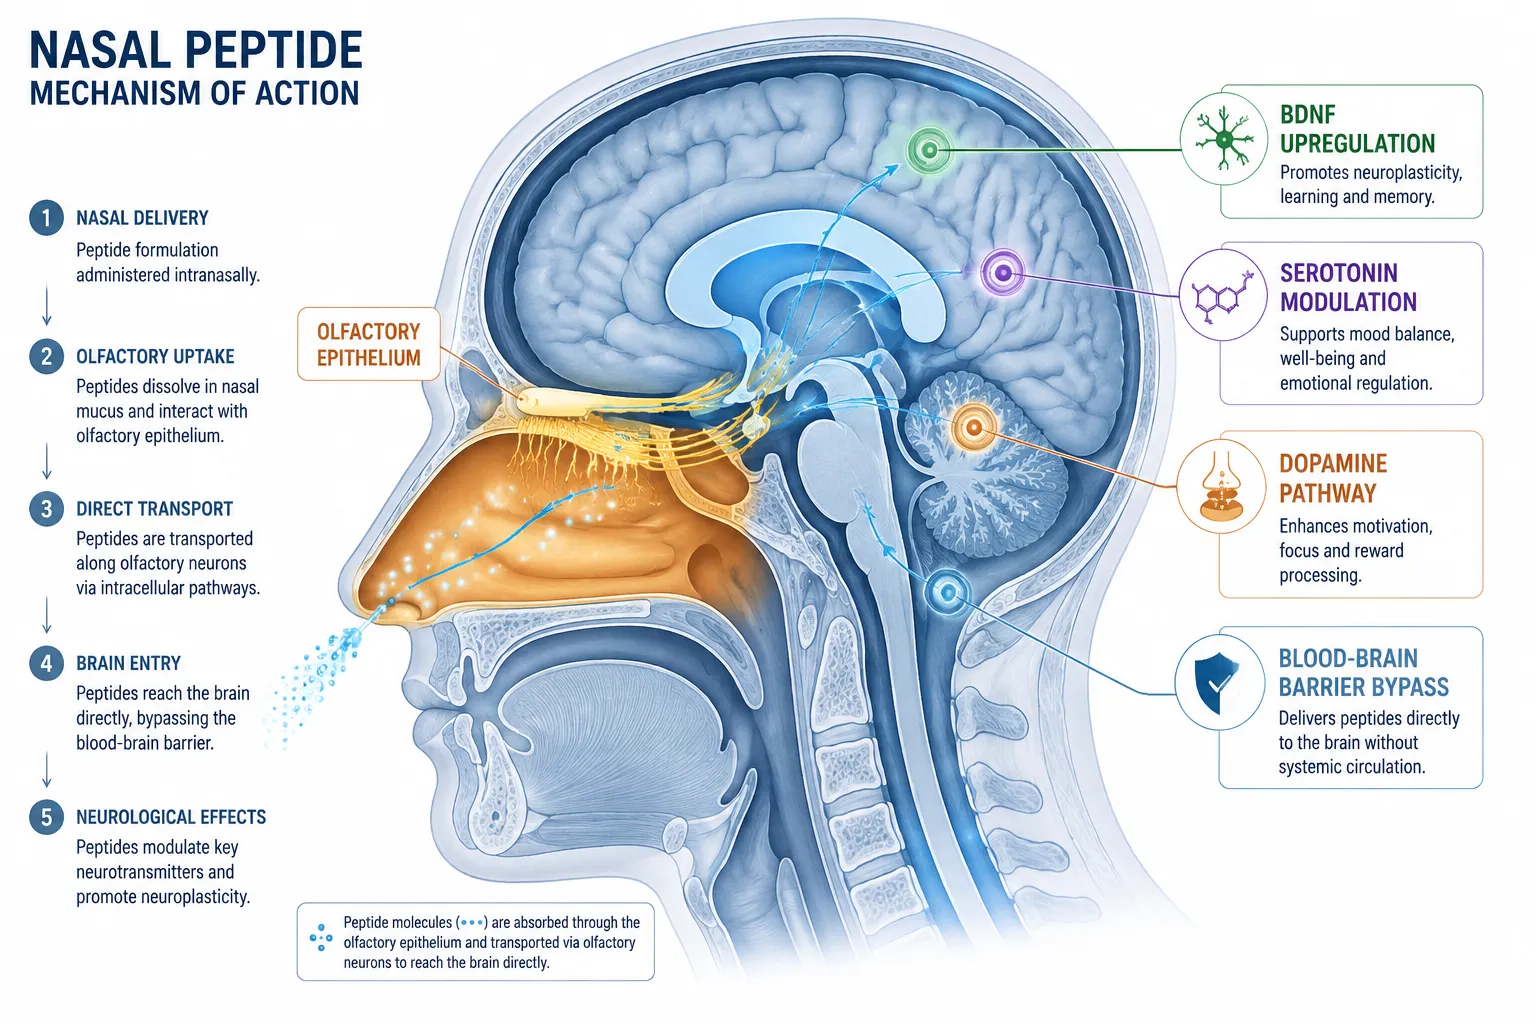
  • Intranasal delivery bypasses first-pass metabolism and may allow direct olfactory-to-brain transport, making excipient choice and actuation volume critical quality variables.
  • Combined Semax/Selank sprays typically offer lower cost per milligram than separate formulations, a practical factor for multi-week research protocols.
  • Regulatory status differs significantly across these four compounds, which affects sourcing, labeling, and permissible research contexts.

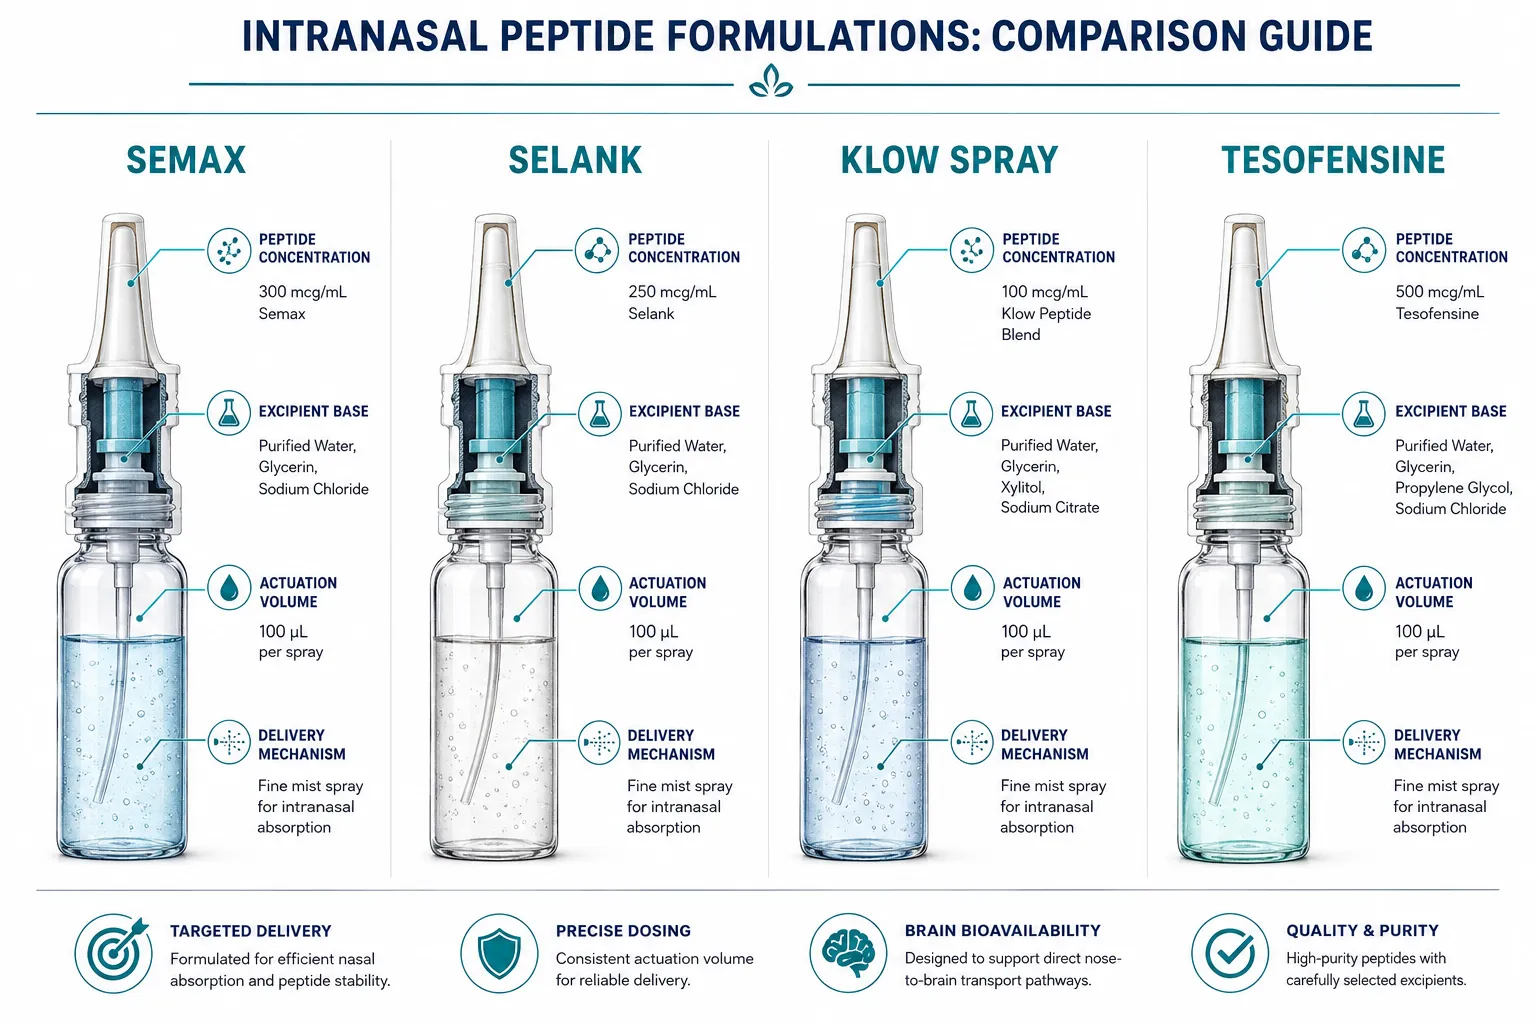
Formulation and Excipient Profiles Across the Four Compounds

Formulation and Excipient Profiles Across the Four Compounds

Understanding what surrounds the active peptide is as important as the peptide itself. Excipients affect stability, mucosal absorption, and shelf life, all critical for reproducible research outcomes.

Semax is an ACTH analog heptapeptide typically supplied as an aqueous nasal spray. Standard research formulations use sterile water or saline as the carrier, sometimes with a small amount of preservative such as benzalkonium chloride. Concentrations in research-grade products commonly range from 0.1% (1 mg/mL) to 1% (10 mg/mL). The Semax ACTH analog classification is relevant here because its short peptide chain confers reasonable aqueous stability without requiring lyophilization in most commercial formats.

Selank shares a similar aqueous delivery format. As an intranasal anxiolytic peptide, it is frequently co-formulated with Semax in dual-peptide blends. Research suppliers offer combined sprays at concentrations such as 2.5 mg/mL of each peptide, delivering approximately 250 mcg per actuation. Larger blends of 20 mg Semax plus 20 mg Selank per bottle are marketed for cognition and neuroprotection research. For labs comparing these two compounds, the Selank vs Semax profile is a useful starting reference. The Selank intranasal delivery format is well-documented in research contexts, and its aqueous stability is comparable to Semax.

Klow Spray is a branded intranasal formulation targeting appetite and metabolic pathways. While exact proprietary excipient data varies by supplier, Klow-type sprays typically use a buffered saline base with absorption enhancers designed to improve mucosal uptake of larger or more hydrophilic peptide structures. Labs should request a certificate of analysis confirming pH range (ideally 4.5-6.5 for nasal tolerability) and osmolality.

Tesofensine differs structurally from the peptide trio above. It is a small-molecule monoamine reuptake inhibitor, not a peptide, that inhibits reuptake of serotonin, dopamine, and norepinephrine. Intranasal tesofensine formulations are less standardized than oral capsule formats. Excipient considerations include solubility enhancers and viscosity agents to ensure consistent actuation. Its non-peptide nature means it does not face the same stability challenges as Semax or Selank, but it requires careful pH management to prevent mucosal irritation.

Dosing Schemes and Bioavailability Considerations

Dosing Schemes and Bioavailability Considerations

Bioavailability through the nasal mucosa is generally estimated at 10-30% for peptides, depending on molecular weight, lipophilicity, and formulation. The olfactory epithelium pathway offers a potential direct route to the central nervous system, bypassing the blood-brain barrier, a key reason intranasal delivery is preferred for cognitive peptides over subcutaneous injection in many research protocols.

Semax dosing in current 2026 research guides typically falls between 200 and 600 mcg intranasally, administered one to three times daily. A Semax BDNF upregulation mechanism is frequently cited as the basis for its cognitive-enhancement profile, with BDNF supporting neuroplasticity and memory consolidation.

Selank dosing is generally slightly lower, at 200-400 mcg per session. A well-documented 2026 stack protocol pairs 300 mcg Semax in the morning with 250 mcg Selank in the morning or early afternoon, cycled five days on and two days off. This cycling approach treats both peptides as short-course nootropics rather than continuous therapies. The Selank peptide research profile consistently highlights its anxiolytic and mood-stabilizing properties without sedation, a meaningful distinction from benzodiazepine-class compounds. Labs interested in that comparison can review the Selank vs benzodiazepine literature.

Klow Spray dosing protocols vary by supplier and target pathway. Research designs typically use one to two actuations per session, with sessions spaced to avoid receptor desensitization. Bioavailability data for Klow-type formulations is limited compared to the Semax/Selank literature, which is a consideration for labs designing quantitative outcome studies.

Tesofensine intranasal research doses are generally lower than oral equivalents due to the avoidance of first-pass metabolism. Oral clinical trials used 0.25-1 mg daily; intranasal equivalents require careful titration. The triple monoamine mechanism makes tesofensine relevant to triple agonist peptides research frameworks, even though tesofensine itself is not a peptide.

Key formulation note: For all four compounds, actuation volume consistency, typically 50-100 mcL per spray, directly determines dose reproducibility. Labs should verify actuation volume and pump mechanism before committing to a supplier.

Comparing Research Applications: Cognitive vs. Appetite Targets

Comparing Research Applications: Cognitive vs. Appetite Targets

The four compounds divide naturally into two research categories, though overlap exists.

Compound Primary Research Target Delivery Format Regulatory Note (2026)
Semax Cognition, neuroprotection, BDNF Aqueous nasal spray PCAC review scheduled July 2026
Selank Anxiety reduction, calm focus Aqueous nasal spray Research use only; no US docket
Klow Spray Appetite, metabolic modulation Buffered intranasal blend Research use only
Tesofensine Appetite suppression, monoamine reuptake Small-molecule spray or oral Research use only

For labs focused on cognitive outcomes, the Semax/Selank combination remains the most evidence-supported intranasal option in 2026. The "focus and drive" profile of Semax complements the "calm and steady" anxiolytic character of Selank, and combined sprays reduce both cost and protocol complexity. Separate 30 mg sprays of each typically cost more per milligram than combined 1:1 blends, making dual-peptide formulations a practical choice for multi-week studies.

For appetite and metabolic research, Klow Spray and tesofensine address different mechanistic targets. Klow Spray operates through peptide-based pathways relevant to satiety signaling, while tesofensine's monoamine reuptake inhibition affects appetite through central dopaminergic and serotonergic circuits. Labs should not treat these as interchangeable; study design should reflect the distinct mechanisms. Broader systemic peptide research frameworks can help contextualize how these compounds interact with whole-body metabolic signaling.

Conclusion

For labs evaluating the best nasal spray peptides for cognitive and appetite research, Semax, Selank, Klow Spray, and Tesofensine compared, the ordering decision comes down to three practical priorities: research target alignment, formulation quality, and regulatory awareness.

Actionable next steps for research teams:

  • Verify excipient data before ordering any intranasal peptide. Request certificates of analysis confirming pH, osmolality, preservative type, and actuation volume.
  • Match the compound to the research question. Use Semax and Selank for cognitive and neuroprotective endpoints; use Klow Spray or tesofensine for appetite and metabolic studies.
  • Apply cycling protocols for Semax and Selank (five days on, two days off) to maintain receptor sensitivity across multi-week study designs.
  • Monitor Semax regulatory developments closely. Its July 2026 PCAC review could affect compounding availability and labeling requirements within the US market.
  • Source from suppliers with transparent labeling. Products explicitly marked "for research use only" with full compositional disclosure are the appropriate standard for laboratory procurement.

Selecting the right intranasal peptide formulation is not just a chemistry decision, it is a study design decision. Matching mechanism to endpoint, and formulation to protocol, is what separates reproducible research from inconclusive data.

https://www.puretestedpeptides.com/wp-content/uploads/2026/09/best-nasal-spray-peptides-for-cognitive-and-appetite-research-semax-selank-klow.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-09-02 13:04:472026-09-02 13:04:47Best Nasal Spray Peptides for Cognitive and Appetite Research: Semax, Selank, Klow Spray, and Tesofensine Compared
Tesofensine vs GLP‑3 Retatrutide vs Classic Appetite Drugs: Which Pathways Researchers Model for Weight‑Related Studies

Tesofensine vs GLP‑3 Retatrutide vs Classic Appetite Drugs: Which Pathways Researchers Model for Weight‑Related Studies

August 28, 2026/0 Comments/in Uncategorized/by

Fewer than one in five adults with obesity achieve durable weight loss through lifestyle intervention alone, a gap that has pushed research labs to evaluate an increasingly diverse toolkit of pharmacological agents. The question of Tesofensine vs GLP‑3 Retatrutide vs Classic Appetite Drugs: Which Pathways Researchers Model for Weight‑Related Studies is no longer academic; it directly shapes how labs allocate resources, design endpoints, and interpret data in 2026.

Key Takeaways

  • Tesofensine acts as a triple monoamine reuptake inhibitor, targeting the central nervous system, while retatrutide engages three peripheral metabolic receptors simultaneously.
  • Classic appetite drugs operate through single or dual monoaminergic pathways, making them simpler to model but narrower in scope.
  • Retatrutide's TRIUMPH-1 Phase 3 data produced weight-loss magnitudes approaching bariatric surgery outcomes.
  • Researchers increasingly favor gut-brain peptide network models over pure CNS-appetite frameworks.
  • Study design choices, including endpoint selection and comorbidity integration, differ substantially across all three compound classes.

Mechanistic Foundations: Three Distinct Pathways

Mechanistic Foundations: Three Distinct Pathways

Understanding the mechanistic differences is the starting point for any lab comparing these agents. For context on how tesofensine fits within the broader noradrenergic and monoaminergic landscape, see this detailed breakdown of tesofensine and metabolic research as a noradrenergic appetite modulator.

Classic appetite drugs, including older phentermine-class agents and serotonergic compounds, work primarily by stimulating catecholamine release or blocking serotonin reuptake in the hypothalamus. Their mechanism is relatively linear: reduce hunger signals, lower caloric intake, observe body weight change. This simplicity made them the default model substrate for decades, but it also limits their translational value for complex metabolic phenotypes.

Tesofensine expands on that architecture by simultaneously inhibiting the reuptake of serotonin, norepinephrine, and dopamine. This triple reuptake inhibition produces stronger appetite suppression than single-target agents and also affects reward-related eating behavior. Researchers modeling tesofensine must account for CNS-driven endpoints alongside peripheral metabolic markers, adding complexity but also richer mechanistic insight.

Retatrutide represents a structural departure from both. As a triple agonist at GIP, GLP-1, and glucagon receptors, it operates primarily through gut-derived hormonal signaling rather than central monoamine pathways. For a thorough overview of how this peptide family is classified, the GLP-3, GLP-1, and GLP-2 researcher's guide to the peptide family provides essential background. Labs modeling retatrutide must incorporate insulin secretion dynamics, glucagon suppression, gastric emptying, and energy expenditure, a multi-tissue endpoint panel that classic appetite drug models were never designed to handle.

Study Design Considerations Across Compound Classes

Study Design Considerations Across Compound Classes

The divergence in mechanism translates directly into divergent study architectures. When researchers examine Tesofensine vs GLP‑3 Retatrutide vs Classic Appetite Drugs: Which Pathways Researchers Model for Weight‑Related Studies, the endpoint selection question becomes central.

Classic appetite drug models typically use:

  • Short-duration feeding behavior assays
  • Hypothalamic gene expression panels
  • Single-tissue (adipose or liver) metabolic readouts
  • Monoamine metabolite profiling in cerebrospinal fluid or plasma

Tesofensine-focused models commonly add:

  • Dopaminergic reward circuit assessments
  • Locomotor activity tracking to distinguish appetite suppression from stimulant effects
  • Multi-neurotransmitter plasma panels
  • Longer washout periods given CNS accumulation dynamics

Retatrutide models require the most expansive design:

  • Pancreatic beta-cell function assays
  • Incretin hormone time-course sampling
  • Multi-organ imaging endpoints (liver fat, visceral adipose volume)
  • Comorbidity integration for cardiovascular, sleep apnea, and osteoarthritis markers

This last point is not incidental. The TRIUMPH program, the Phase 3 trial series for retatrutide, explicitly integrates obesity-related comorbidities including obstructive sleep apnea, osteoarthritis, and cardiovascular disease into its endpoints. A dedicated cardiovascular outcomes trial completed enrollment in 2026, signaling that multi-indication modeling is now the expected standard for next-generation obesity agents. Labs that design single-endpoint studies for retatrutide risk missing the compound's most scientifically significant effects.

"The shift from monoaminergic appetite suppression to gut-brain peptide network modulation represents the most significant methodological change in obesity research in two decades."

For researchers interested in how cellular energy pathways intersect with these metabolic models, the work on MOTS-C peptide and mitochondrial biogenesis for cellular energy research offers a complementary framework.

Selecting the Right Compound for a Research Program

Selecting the Right Compound for a Research Program

Choosing between these agents is not purely a mechanistic decision, it is also a question of what the research program is designed to answer. The full picture of Tesofensine vs GLP‑3 Retatrutide vs Classic Appetite Drugs: Which Pathways Researchers Model for Weight‑Related Studies depends on research objectives, available infrastructure, and the target phenotype.

Research Goal Best-Fit Compound Class
CNS appetite circuit mapping Classic appetite drugs or tesofensine
Reward-driven eating behavior Tesofensine
Multi-tissue metabolic profiling Retatrutide
Cardiovascular-obesity interaction Retatrutide
Rapid, low-cost pilot screening Classic appetite drugs

For labs focused on hormone regulation studies, retatrutide's incretin-axis activity makes it the most information-dense option. Its Phase 3 data demonstrated weight loss approaching bariatric surgery outcomes, a benchmark that repositions the compound from a pharmacological agent to a near-procedural intervention in research framing.

Tesofensine occupies a valuable middle ground. Its CNS-peripheral hybrid mechanism makes it well-suited for studies that need to bridge appetite neuroscience with metabolic outcomes without the full complexity of a triple incretin agonist protocol. Researchers can find additional context on how retatrutide advances beyond single-receptor agents in this overview of GLP-3 retatrutide and the future of metabolic research beyond GLP-1.

Classic appetite drugs retain relevance as mechanistic controls and for studies requiring well-characterized pharmacokinetic baselines. Their regulatory and safety profiles are extensively documented, making them useful reference compounds in comparative designs.

Conclusion

The comparison of Tesofensine vs GLP‑3 Retatrutide vs Classic Appetite Drugs: Which Pathways Researchers Model for Weight‑Related Studies ultimately reflects a field in transition, moving from single-pathway CNS models toward integrated gut-brain-metabolic frameworks. Labs designing weight-related studies in 2026 should take three concrete steps: first, define whether the primary research question is CNS-centric, peripherally metabolic, or multi-system; second, select the compound class whose mechanism maps directly to that question; third, build endpoint panels that match the compound's known biology rather than defaulting to legacy assay formats. Retatrutide's TRIUMPH data and its anticipated 2027 regulatory filing will continue to raise the methodological bar, researchers who align their study designs now will be best positioned to generate translatable, high-impact findings.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/tesofensine-vs-glp-3-retatrutide-vs-classic-appetite-drugs-which-pathways-resear.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-28 13:08:022026-08-28 13:08:02Tesofensine vs GLP‑3 Retatrutide vs Classic Appetite Drugs: Which Pathways Researchers Model for Weight‑Related Studies
GLP Peptides vs Traditional Small‑Molecule Metabolic Drugs: Where GLP‑3 Retatrutide, GLP‑2‑T, and Tesofensine Fit in Cardiometabolic Research

GLP Peptides vs Traditional Small‑Molecule Metabolic Drugs: Where GLP‑3 Retatrutide, GLP‑2‑T, and Tesofensine Fit in Cardiometabolic Research

August 28, 2026/0 Comments/in Uncategorized/by

Cardiovascular disease and metabolic dysfunction together account for more than 17 million deaths annually worldwide, yet the dominant drugs managing these conditions, including atorvastatin, amlodipine, and prednisone, were designed decades before researchers understood the gut-hormone axis. The emergence of GLP peptides vs traditional small-molecule metabolic drugs as a central debate in 2026 cardiometabolic research reflects a genuine mechanistic shift, not just a trend. Understanding where GLP-3 retatrutide, GLP-2-T, and tesofensine fit in cardiometabolic research requires mapping each agent against the biological pathways that older drug classes were never built to target.

Key Takeaways

  • GLP peptides operate through receptor-level hormonal signaling, while traditional small molecules like statins and calcium channel blockers inhibit specific enzymes or ion channels.
  • Retatrutide is a triple agonist targeting GLP-1, GIP, and glucagon receptors simultaneously, producing weight loss of up to approximately 30% in phase 2 data.
  • GLP-2-T remains an experimental dual agonist with limited formal validation but growing preclinical interest.
  • Tesofensine is a small-molecule monoamine reuptake inhibitor with potent weight-loss effects but a narrower cardiometabolic profile than GLP peptides.
  • Combination research pairing GLP agents with SGLT2 inhibitors represents one of the most active frontiers in 2026 metabolic drug development.

The Mechanistic Divide: How GLP Peptides Differ From Traditional Small-Molecule Drugs

The Mechanistic Divide: How GLP Peptides Differ From Traditional Small-Molecule Drugs

Traditional cardiometabolic drugs work by blocking or inhibiting a single molecular target. Atorvastatin inhibits HMG-CoA reductase to reduce LDL cholesterol. Amlodipine blocks L-type calcium channels to lower blood pressure. Prednisone suppresses inflammatory cytokines through glucocorticoid receptor binding. Each of these agents is chemically synthesized, orally bioavailable, and designed for a narrow, well-defined pathway.

GLP peptides operate differently. They are amino acid chains that mimic or modulate endogenous gut hormones, binding to G-protein-coupled receptors (GPCRs) that regulate insulin secretion, appetite, gastric emptying, and energy expenditure. This multi-system engagement is the core reason GLP peptides vs traditional small-molecule metabolic drugs has become such a meaningful research distinction.

Key mechanistic differences at a glance:

Feature GLP Peptides Traditional Small Molecules
Molecular structure Amino acid chains Synthesized organic compounds
Route of administration Typically subcutaneous Often oral
Target specificity Multi-receptor hormonal Single enzyme or channel
Metabolic scope Broad (weight, glucose, CV) Narrow (lipid, BP, inflammation)
Degradation pathway Enzymatic (DPP-4) Hepatic metabolism

This mechanistic breadth is precisely why researchers are now studying GLP agents alongside, and sometimes in place of, older drug classes in cardiometabolic protocols.

For researchers exploring the broader peptide landscape, the GLP-3, GLP-1, and GLP-2 explained: a researcher's guide to the peptide family provides essential foundational context.

Retatrutide, GLP-2-T, and the Multi-Agonist Paradigm in Cardiometabolic Research

Retatrutide, GLP-2-T, and the Multi-Agonist Paradigm in Cardiometabolic Research

The most significant development in GLP peptides vs traditional small-molecule metabolic drugs research is the emergence of multi-receptor agonists. Retatrutide, often referred to informally as a "GLP-3-like" agent, simultaneously activates GLP-1, GIP (glucose-dependent insulinotropic polypeptide), and glucagon receptors. This triple agonism drives insulin sensitization, appetite suppression, and increased energy expenditure through three distinct but complementary pathways.

Phase 2 clinical data for retatrutide demonstrated weight reduction of up to approximately 24-30% from baseline, surpassing outcomes seen with GLP-1 mono-agonists like semaglutide. The TRIUMPH phase 3 program, now actively enrolling across multiple cardiometabolic indications in 2025-2026, is evaluating retatrutide not just for obesity but for heart failure, metabolic-associated steatohepatitis (MASH), and type 2 diabetes. This breadth of indication reflects the multi-system nature of triple agonism.

"Triple agonism in retatrutide targets three receptor systems that no single traditional small molecule was designed to address simultaneously."

Researchers can explore the triple agonist retatrutide research profile for detailed mechanistic data, and those sourcing research-grade material may reference Reta 10mg specifications.

GLP-2-T is a distinct experimental compound, a dual agonist with activity at GLP-2 receptors alongside a secondary target. GLP-2 receptors are expressed in intestinal epithelium and have established roles in gut barrier integrity and nutrient absorption. In cardiometabolic research, GLP-2-T is being studied for its potential to reduce systemic inflammation originating from gut permeability, a pathway entirely absent from the pharmacology of atorvastatin or amlodipine. Formal clinical validation remains limited, but preclinical models show meaningful reductions in inflammatory markers relevant to atherosclerosis.

For researchers tracking GLP-1 peptides for research purposes, understanding GLP-2-T's distinct receptor profile is important for accurate experimental design.

Tesofensine and the Role of Small-Molecule Weight-Loss Agents Alongside GLP Peptides

Tesofensine and the Role of Small-Molecule Weight-Loss Agents Alongside GLP Peptides

Tesofensine occupies a unique position in the GLP peptides vs traditional small-molecule metabolic drugs conversation. It is a small molecule, not a peptide, that inhibits the reuptake of serotonin, dopamine, and norepinephrine in the central nervous system. This triple monoamine reuptake inhibition produces significant appetite suppression and has shown weight loss of 6-12% in clinical trials, placing it well above older agents like orlistat but below GLP-1 mono-agonists.

As of 2026, tesofensine remains approved in limited markets, primarily in Latin America, without broad regulatory clearance from the FDA or EMA. This geographic restriction shapes its role in research: it is studied as a comparator agent and as a potential combination partner rather than a frontline cardiometabolic therapy.

Where tesofensine fits in research design:

  • As a CNS-pathway comparator to GLP-1's peripheral appetite suppression
  • In combination studies examining monoaminergic plus incretin-based weight loss
  • As a reference compound when evaluating tolerability profiles of newer peptides

The tolerability distinction between GLP peptides and tesofensine is clinically meaningful. GLP agents primarily cause gastrointestinal side effects (nausea, vomiting) that are dose-dependent and typically transient. Tesofensine carries cardiovascular signals including elevated heart rate and blood pressure, a concern that limits its cardiometabolic framing despite its weight-loss efficacy.

Researchers interested in mitochondrial and cellular energy pathways as complementary research targets may find value in reviewing MOTS-C peptide and mitochondrial biogenesis research, which addresses energy metabolism from a distinct mechanistic angle.

Integration with traditional cardiometabolic drugs is another active research area. GLP-1 agents combined with SGLT2 inhibitors (such as empagliflozin) show additive reductions in cardiovascular events, HbA1c, and body weight, a combination that no traditional drug pairing achieves with comparable breadth. Retatrutide's triple agonism may further amplify these benefits when studied alongside SGLT2 inhibitors in future phase 3 substudies.

For researchers sourcing verified compounds, high purity peptide sourcing and peptide CoA verification resources are critical for maintaining experimental integrity.

Conclusion

The debate around GLP peptides vs traditional small-molecule metabolic drugs is not a competition, it is a map of complementary mechanisms. Atorvastatin, amlodipine, and prednisone remain essential tools for managing lipid levels, blood pressure, and inflammation through well-characterized single-target pathways. Retatrutide, GLP-2-T, and tesofensine address metabolic dysfunction through hormonal signaling, gut-barrier modulation, and CNS appetite regulation, pathways that traditional drugs were not designed to reach.
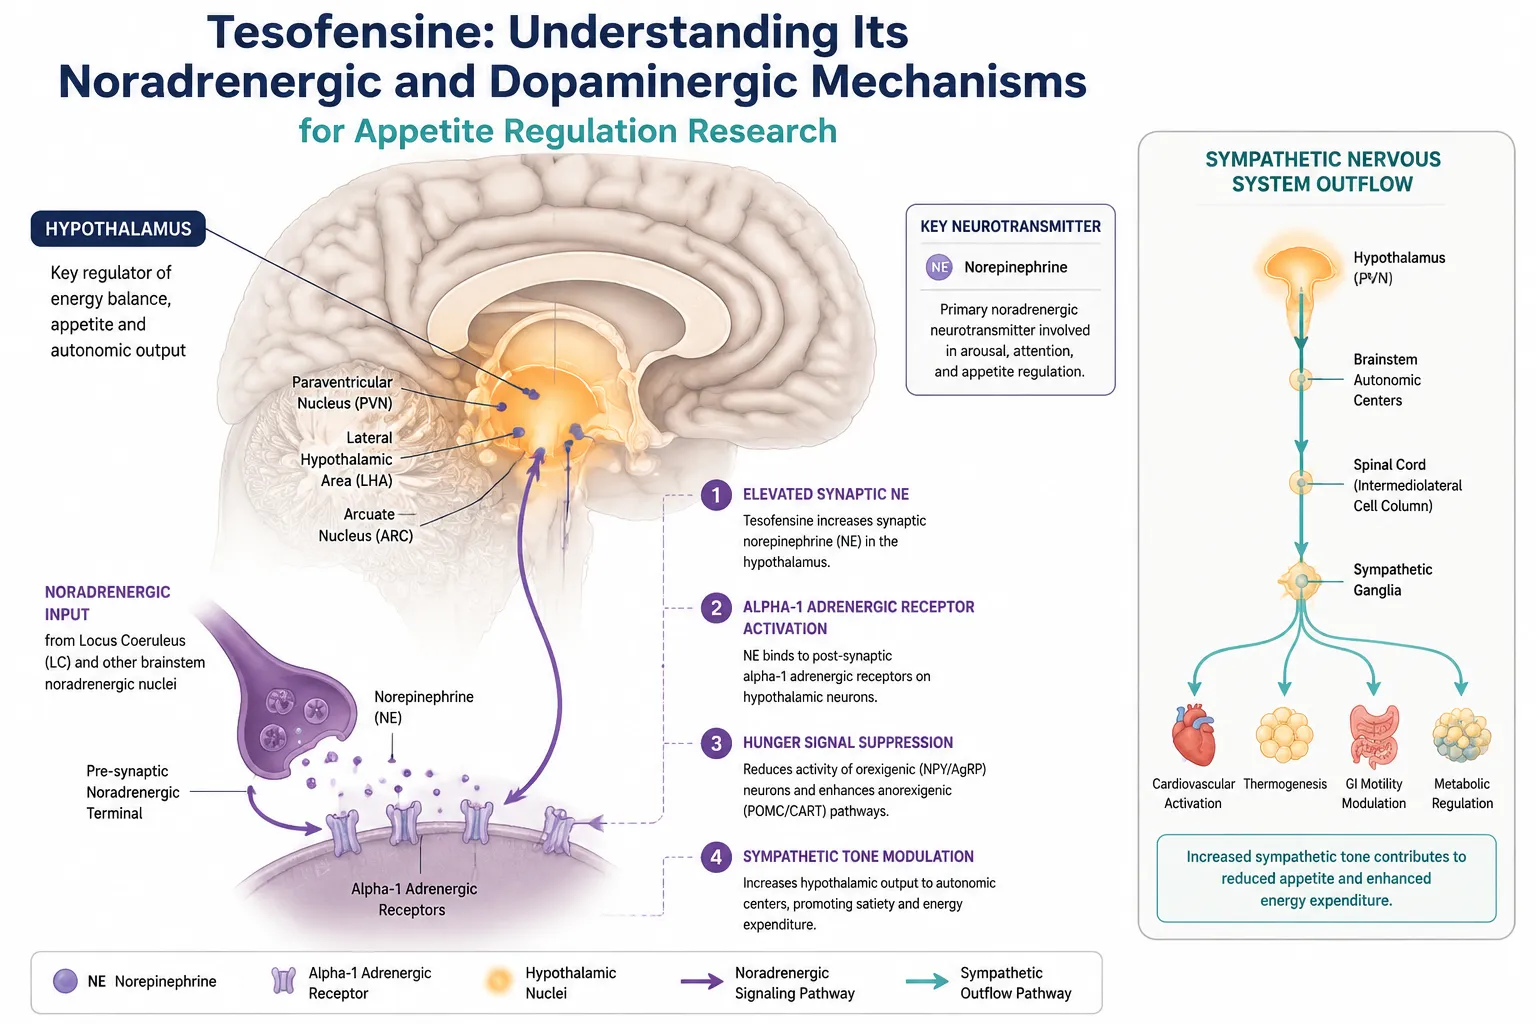
Actionable next steps for researchers in 2026:

  1. Define the specific receptor pathway under investigation before selecting a GLP agent or small-molecule comparator.
  2. Review TRIUMPH phase 3 data as it publishes to understand retatrutide's evolving cardiometabolic evidence base.
  3. When designing combination protocols, consider GLP-1 plus SGLT2 pairings as the current evidence-supported benchmark.
  4. Treat GLP-2-T as a hypothesis-generating agent requiring rigorous in vitro validation before advancing to complex models.
  5. Source all research peptides with documented purity certificates to ensure data reproducibility.

The cardiometabolic research landscape in 2026 is defined by multi-mechanism thinking. Researchers who understand where each agent sits in this landscape, peptide or small molecule, will design more precise, reproducible, and ultimately meaningful studies.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/glp-peptides-vs-traditional-small-molecule-metabolic-drugs-where-glp-3-retatruti.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-28 13:05:232026-08-28 13:05:23GLP Peptides vs Traditional Small‑Molecule Metabolic Drugs: Where GLP‑3 Retatrutide, GLP‑2‑T, and Tesofensine Fit in Cardiometabolic Research
Tesofensine: Understanding Its Noradrenergic and Dopaminergic Mechanisms for Appetite Regulation Research

Tesofensine: Understanding Its Noradrenergic and Dopaminergic Mechanisms for Appetite Regulation Research

August 26, 2026/0 Comments/in Uncategorized/by

{"cover":"Professional landscape format (1536×1024) hero image with bold text overlay 'Tesofensine: Understanding Its' in crisp white modern sans-serif centered on a deep navy semi-transparent overlay panel, 8% safe margins from every edge, no character touching the border. Background: dramatic macro editorial illustration of a glowing neural synapse cross-section showing norepinephrine and dopamine molecular structures floating between neuron terminals, teal and electric-blue bioluminescent glow against deep navy, ultra-sharp scientific magazine aesthetic, high contrast, editorial quality.","content":["Annotated mechanism-of-action diagram, landscape format (1536×1024): central illustration of a stylized neuron synapse with three labeled transporter proteins, NET (norepinephrine transporter), DAT (dopamine transporter), SERT (serotonin transporter), each with a callout arrow and short label. Tesofensine molecule shown blocking all three, teal callout lines pointing to each site. Side panel shows potency hierarchy: NE greater than DA greater than 5-HT with short bar indicators. Clean white background, teal-and-navy palette, clinical infographic polish, all labels 1-5 words, inside 5% safe margin.","Four-panel labelled comparison guide, landscape format (1536×1024): Panel 1 labeled 'Noradrenergic Pathway' shows hypothalamus with alpha-1 receptor activation callout and 'Satiety Signal' arrow; Panel 2 labeled 'Dopaminergic Pathway' shows mesolimbic circuit with DAT blockade callout and 'Reward Suppression' label; Panel 3 labeled 'LH GABAergic Silencing' shows lateral hypothalamus with inhibitory neuron highlighted; Panel 4 labeled 'Integrated Effect' shows appetite suppression outcome with downward arrow. Teal-and-slate color scheme, thin callout lines, clinical editorial style, all labels under 6 words, white background.","Split-screen editorial infographic, landscape format (1536×1024): left half titled 'Monoamine-Based Approach' shows a stylized brain diagram with NE and DA pathway highlights, noradrenergic and dopaminergic circuit arrows, warm amber-teal palette; right half titled 'GLP-1 Based Approach' shows a gut-brain axis diagram with incretin hormone arrows and hypothalamic receptor icons, cool blue-green palette. Center dividing line with label 'Appetite Regulation Comparison'. All panel labels 1-5 words, callout lines sharp and non-overlapping, inside 5% safe margin, editorial medical-guide polish, high contrast."]

Professional landscape hero image () with a reading "Tesofensine: Understanding Its". CRITICAL TYPOGRAPHY RULES: render the

Fewer than a dozen small-molecule compounds have demonstrated the ability to simultaneously modulate three monoamine systems in the brain while producing measurable reductions in caloric intake in controlled human studies. Tesofensine is one of them. Originally developed as a neurological agent, it drew significant scientific attention when early metabolic trials revealed robust appetite-suppressing effects tied to its triple reuptake inhibition profile. Tesofensine: Understanding Its Noradrenergic and Dopaminergic Mechanisms for Appetite Regulation Research has become a priority area for investigators examining central nervous system control of hunger, reward-driven feeding, and energy homeostasis.

Key Takeaways

  • Tesofensine inhibits the reuptake of norepinephrine, dopamine, and serotonin, with norepinephrine as the dominant target.
  • Its noradrenergic action drives satiety signaling through alpha-1 receptor activation and sympathetic outflow modulation.
  • Dopamine transporter blockade reduces reward-driven feeding by dampening mesolimbic circuit activity.
  • The two pathways produce additive anorexigenic effects, particularly in hypothalamic and limbic circuits.
  • Research in 2026 has focused on lateral hypothalamus GABAergic silencing as a key downstream mechanism.

The Triple Reuptake Profile: Where Tesofensine Begins

The Triple Reuptake Profile: Where Tesofensine Begins

Tesofensine functions as a pre-synaptic reuptake inhibitor, blocking three monoamine transporters: the norepinephrine transporter (NET), the dopamine transporter (DAT), and the serotonin transporter (SERT). Its potency ranking follows a clear hierarchy, norepinephrine (NE) greater than dopamine (DA) greater than serotonin (5-HT). This ordering is not merely pharmacological trivia; it directly shapes the compound's downstream effects on appetite circuits.

Why the NE-dominant profile matters: Norepinephrine is the primary catecholamine driving sympathetic activation and hypothalamic satiety signaling. When NET is blocked, synaptic NE concentrations rise, prolonging adrenergic receptor engagement. This sets Tesofensine apart from pure serotonergic appetite suppressants and from dopamine-centric stimulants, giving it a mechanistically distinct footprint.

Transporter Relative Potency Primary Downstream Effect
NET (Norepinephrine) Highest Satiety signaling, sympathetic outflow
DAT (Dopamine) Moderate Reward modulation, reduced hedonic eating
SERT (Serotonin) Lowest Mood stabilization, secondary satiety

Researchers comparing this profile to GLP-1-based therapies, explored in detail in the GLP-3, GLP-1, and GLP-2 peptide family research guide, note that while incretin-based agents work peripherally through gut-brain signaling, Tesofensine acts centrally from the synapse outward.

Noradrenergic Mechanisms: Satiety, Sympathetic Tone, and Hypothalamic Control

Noradrenergic Mechanisms: Satiety, Sympathetic Tone, and Hypothalamic Control

The noradrenergic component of Tesofensine: Understanding Its Noradrenergic and Dopaminergic Mechanisms for Appetite Regulation Research is arguably its most clinically significant feature. Elevated synaptic NE activates alpha-1 adrenergic receptors in the hypothalamus, a region central to hunger and satiety regulation. This activation promotes sympathetic outflow and suppresses orexigenic (hunger-promoting) neuronal activity.

Key noradrenergic effects observed in research:

  • Increased alpha-1 receptor stimulation in the paraventricular nucleus (PVN) of the hypothalamus
  • Enhanced sympathetic nervous system tone, raising metabolic rate and reducing appetite drive
  • Suppression of neuropeptide Y (NPY) signaling, a potent hunger-promoting pathway
  • Prolonged satiety scores in human appetite studies, with subjects reporting reduced hunger between meals

A notable research application involves hypothalamic injury-induced obesity, a condition where normal satiety circuitry is disrupted. In these models, Tesofensine has been studied alongside beta-blockers to preserve its appetite-suppressing effects while managing the cardiovascular consequences of elevated noradrenergic tone. This co-administration strategy reflects the precision required when working with NE-dominant compounds.

Research note: The noradrenergic pathway's contribution to appetite suppression is not simply about reducing caloric intake, it also appears to accelerate the onset of satiety, meaning subjects feel full sooner during a meal, not just less hungry before it.

This mechanism complements research into other metabolically active peptides. For instance, investigators studying AOD-9604 research methods, storage, and traceability often examine how lipolytic agents interact with central appetite signals, a question that becomes more nuanced when central NE tone is also elevated.

Dopaminergic Mechanisms: DAT Blockade and Reward-Driven Feeding

The dopaminergic dimension of Tesofensine's profile targets a fundamentally different but equally important feeding circuit. DAT blockade elevates synaptic dopamine in the mesolimbic pathway, the brain's primary reward system. Elevated DA then activates D1 receptors, which are associated with reduced motivation for food-seeking behavior, particularly in the context of hedonic or reward-driven eating.

What this means for appetite research:

  • Reduced dopaminergic signaling in the nucleus accumbens diminishes the rewarding value of highly palatable foods
  • D1 receptor activation in the prefrontal cortex strengthens inhibitory control over impulsive eating
  • DAT kinetics studied in 2026 analyses suggest that Tesofensine's dopamine elevation is sustained but moderate, avoiding the sharp peaks associated with addictive stimulant profiles

This is a critical distinction. A sharp, rapid dopamine surge produces euphoria and reinforces compulsive behavior. Tesofensine's moderate, sustained DAT blockade appears to blunt reward salience for food without generating the reinforcement cycle seen with classical stimulants.

Researchers exploring parallel reward-modulation mechanisms in metabolic peptide research, such as those reviewing GLP-3 triple agonist research planning and catalog navigation, recognize that targeting reward circuitry alongside incretin pathways may represent a complementary strategy for comprehensive appetite management research.

Integrated NE and DA Effects: Hypothalamic and Mesolimbic Convergence

When noradrenergic and dopaminergic mechanisms are considered together, the picture becomes more compelling. Tesofensine: Understanding Its Noradrenergic and Dopaminergic Mechanisms for Appetite Regulation Research reveals that these two pathways do not simply add their effects, they converge on shared circuits to produce amplified anorexigenic outcomes.

Integrated NE and DA Effects: Hypothalamic and Mesolimbic Convergence

The lateral hypothalamus (LH) connection: Updated mechanistic analyses from 2024 to 2026 have highlighted LH GABAergic silencing as a downstream consequence of combined NE and DA elevation. The LH contains orexin-producing neurons that drive feeding motivation. When GABAergic interneurons in this region are activated by elevated monoamine tone, orexin output is suppressed, reducing the drive to eat.

Additive anorexigenic effects in key circuits:

  1. Hypothalamic satiety axis, NE activates PVN satiety neurons while DA reduces orexigenic LH output
  2. Mesolimbic reward circuit, DA dampens nucleus accumbens food-reward signaling
  3. Prefrontal-limbic inhibition, Combined NE and DA elevation strengthens top-down control over impulsive eating

Human appetite data from controlled studies show sustained appetite suppression and significantly higher satiety scores compared to placebo, consistent with this multi-circuit mechanism. These findings position Tesofensine distinctly within the anti-obesity research landscape, where most monoamine-based approaches target only one or two of these circuits.

Researchers working with growth hormone secretagogues such as those described in the CJC-1295 without DAC half-life and growth hormone research guide may find value in understanding how central monoamine tone interacts with GH-axis signaling in metabolic regulation studies.

Positioning Tesofensine in the 2026 Research Landscape

The current research environment in 2026 places Tesofensine in an interesting position. GLP-1-based therapies dominate clinical obesity treatment, yet they work through fundamentally different mechanisms, peripheral incretin signaling, gastric emptying, and gut-brain vagal pathways. Tesofensine's monoamine-driven approach operates upstream of these peripheral signals, acting directly on the central circuits that generate hunger and food-seeking behavior.

Comparative positioning:

  • GLP-1 agents: Peripheral gut-brain axis, incretin receptor activation, strong clinical adoption
  • Tesofensine: Central monoamine reuptake inhibition, NE-dominant, direct hypothalamic and mesolimbic action
  • Combination research potential: Investigators are examining whether central monoamine modulation and peripheral incretin signaling produce complementary or synergistic appetite suppression

Researchers interested in the broader incretin peptide landscape can explore the GLP-1 for sale research category for context on how GLP-1-based compounds are currently catalogued for research use.

Additionally, those studying mitochondrial and metabolic peptides, such as those reviewed in the research-grade MOTS-c and 5-Amino-1MQ quality criteria guide, may find that understanding central monoamine tone adds important context to whole-body energy regulation studies.

Conclusion

Tesofensine: Understanding Its Noradrenergic and Dopaminergic Mechanisms for Appetite Regulation Research provides a framework for appreciating how central monoamine modulation can produce meaningful, multi-circuit appetite suppression. Its NE-dominant reuptake inhibition drives hypothalamic satiety signaling and sympathetic tone, while its dopaminergic component reduces reward-driven feeding through DAT blockade and D1 receptor activation. Together, these pathways converge on the lateral hypothalamus and mesolimbic circuits to amplify anorexigenic effects.

Actionable next steps for researchers:

  • Review the latest DAT/NET kinetic data from 2024 to 2026 mechanistic analyses when designing appetite suppression protocols
  • Consider beta-blocker co-administration strategies when studying Tesofensine in models with elevated cardiovascular sensitivity
  • Compare central monoamine mechanisms against GLP-1 pathway data to identify potential complementary research designs
  • Ensure compound sourcing meets purity and traceability standards before initiating any in vitro or in vivo work
  • Document all storage conditions and handling protocols to maintain experimental integrity across study phases

The mechanistic depth of Tesofensine's noradrenergic and dopaminergic profile makes it a valuable research tool for investigators serious about understanding the central nervous system's role in appetite and metabolic regulation.

https://www.puretestedpeptides.com/wp-content/uploads/2026/08/tesofensine-understanding-its-noradrenergic-and-dopaminergic-mechanisms-for-appe.webp 1024 1536 https://www.puretestedpeptides.com/wp-content/uploads/2026/01/buy-peptides-online.jpg 2026-08-26 13:04:252026-08-26 13:04:25Tesofensine: Understanding Its Noradrenergic and Dopaminergic Mechanisms for Appetite Regulation Research
Page 1 of 212
×

Helpful Links

  • My account
  • Cart
  • Checkout
  • Refund and Returns Policy
  • Privacy Policy
  • SMS Privacy Policy
  • Login
  • My Account
  • Logout

USA Made Lab Tested Peptides

All products are sold for research, laboratory, or analytical purposes only, and are not for human consumption


Pure Tested Peptides is a chemical supplier. Pure Tested Peptides is not a compounding / chemical compounding facility as defined under 503A of the Federal Food, Drug, and Cosmetic act. Pure Tested Peptides is not an outsourcing facility as defined under 503B of the Federal Food, Drug, and Cosmetic act.

The statements made within this website have not been evaluated by the US Food and Drug Administration. The products we offer are not intended to diagnose, treat, cure or prevent any disease.

Human/Animal Consumption Prohibited. Laboratory/In-Vitro Experimental Use Only

Scroll to top Scroll to top Scroll to top