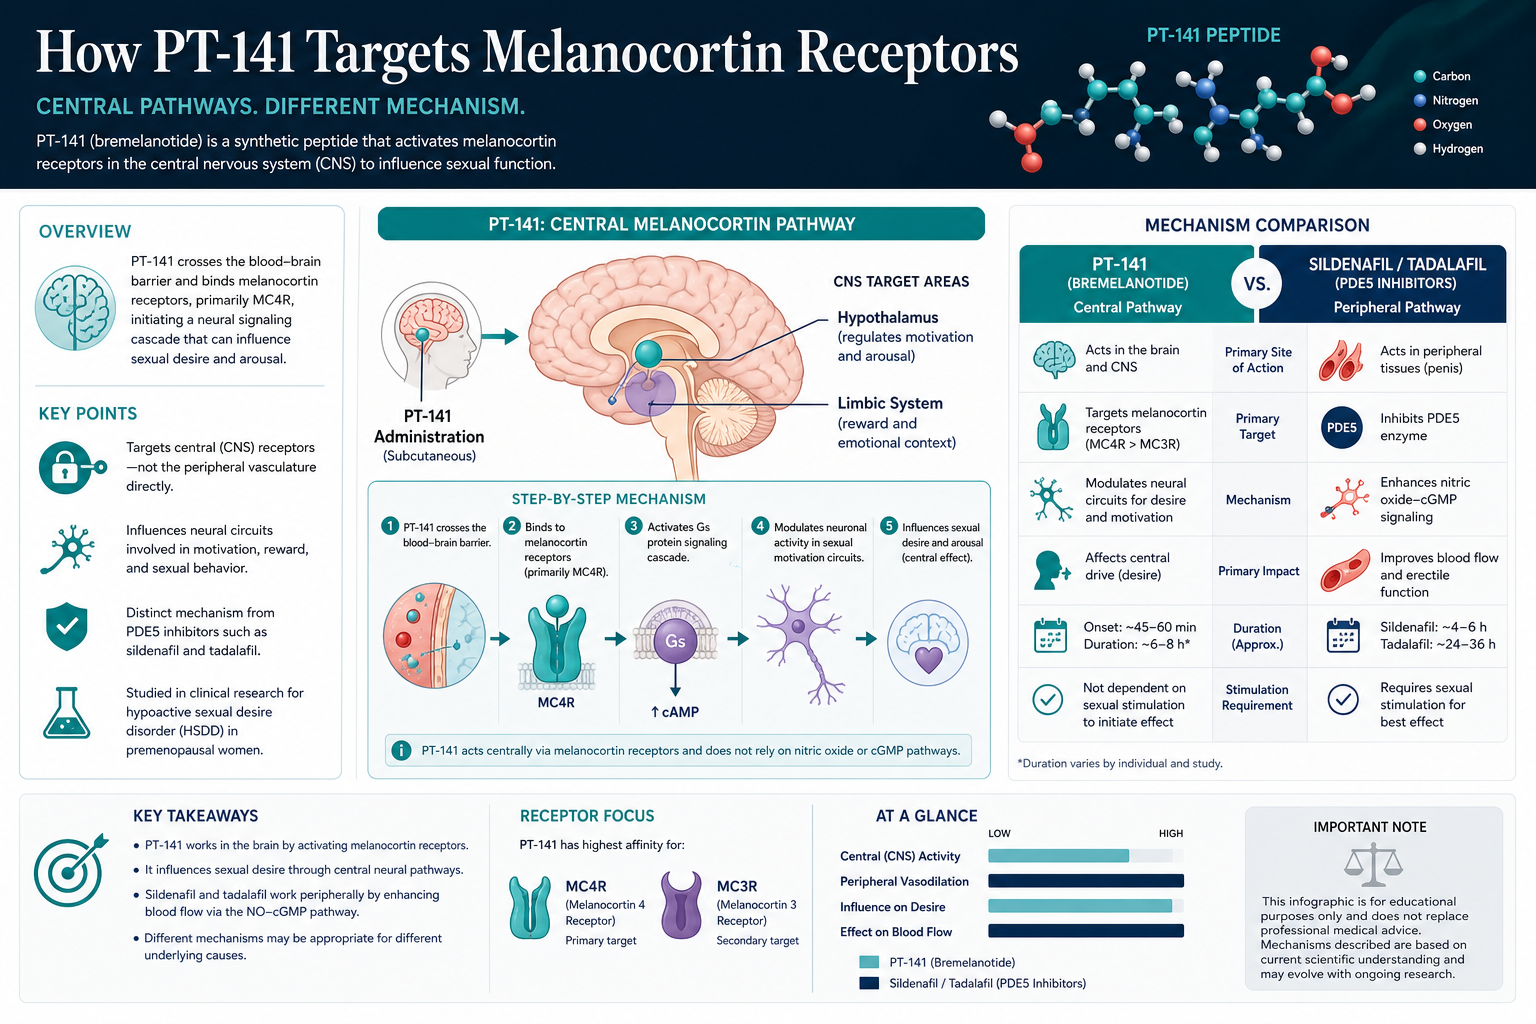
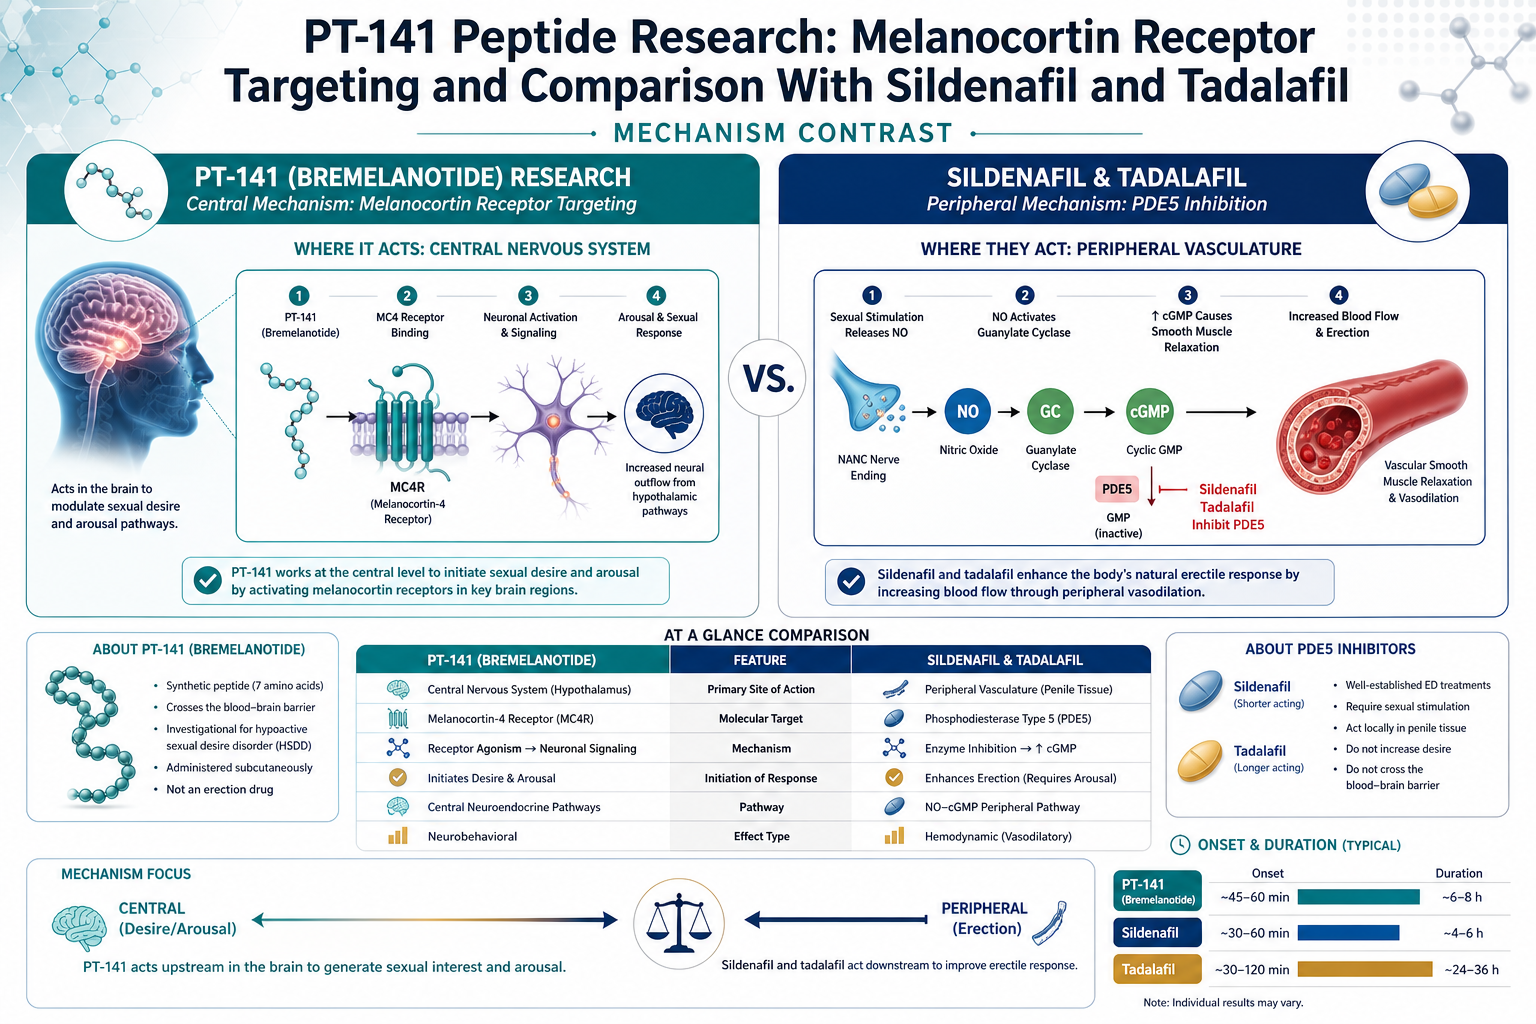
PT-141 Peptide Research Safety Guide: Dosing, Timing, and Tolerability Questions Labs Ask
Roughly 40% of participants in early PT-141 clinical trials experienced nausea significant enough to require protocol adjustments, yet the compound still advanced through multiple phases of human study and reached regulatory approval. That tension between biological activity and tolerability management sits at the heart of every serious PT-141 Peptide Research Safety Guide: Dosing, Timing, and Tolerability Questions Labs Ask.
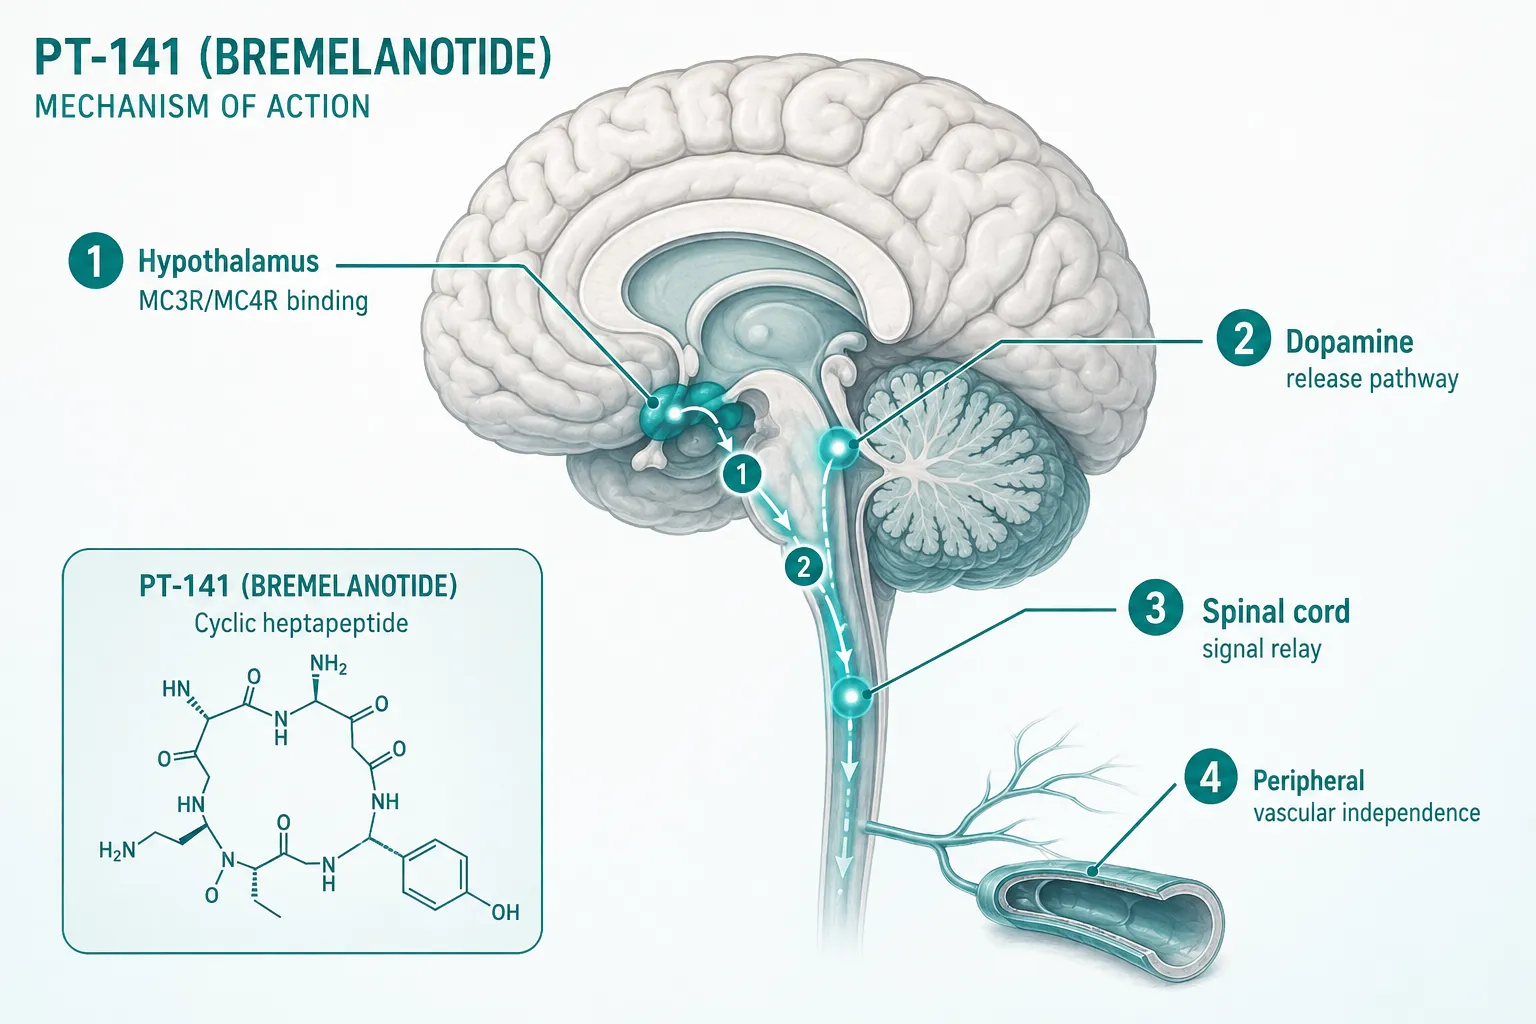
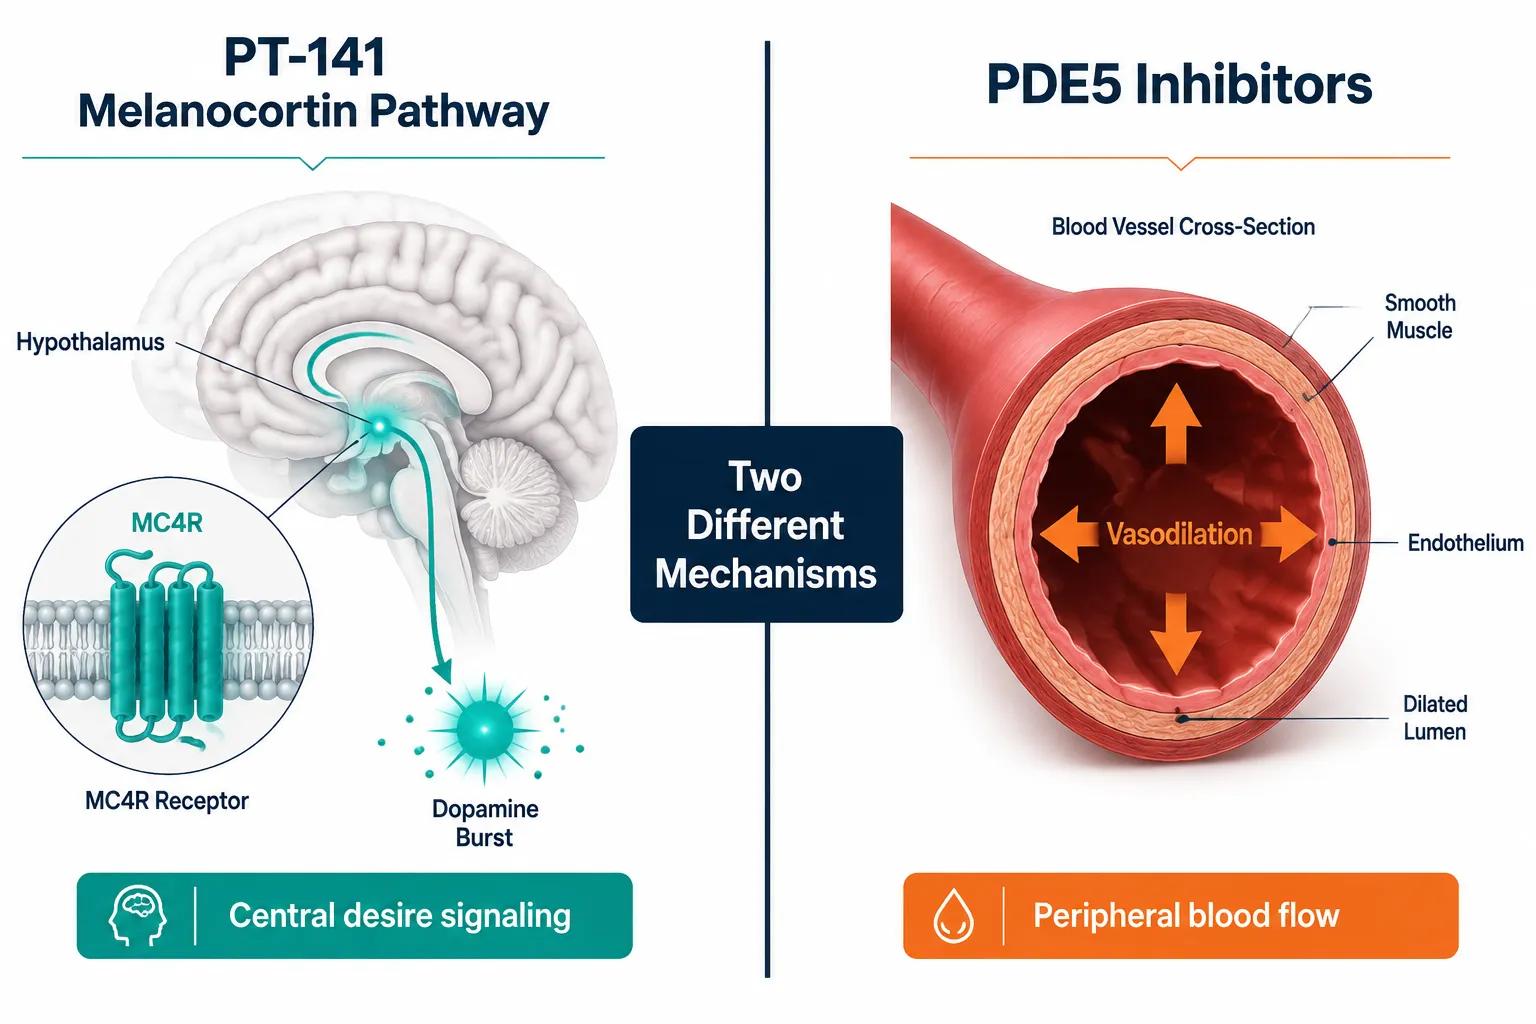
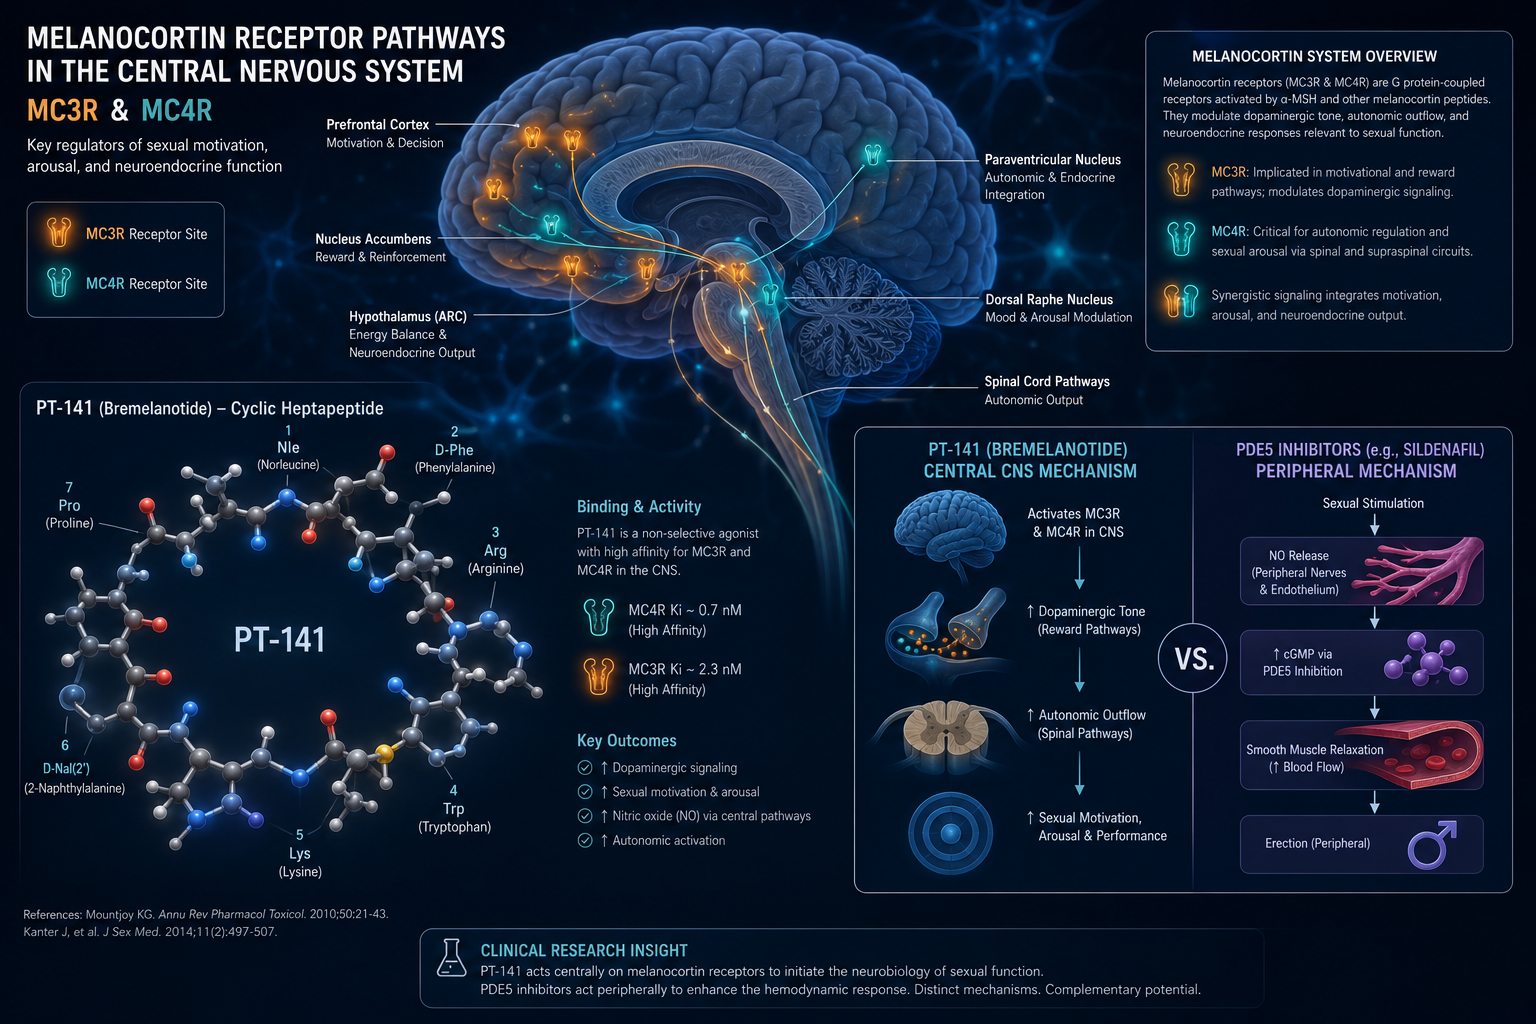
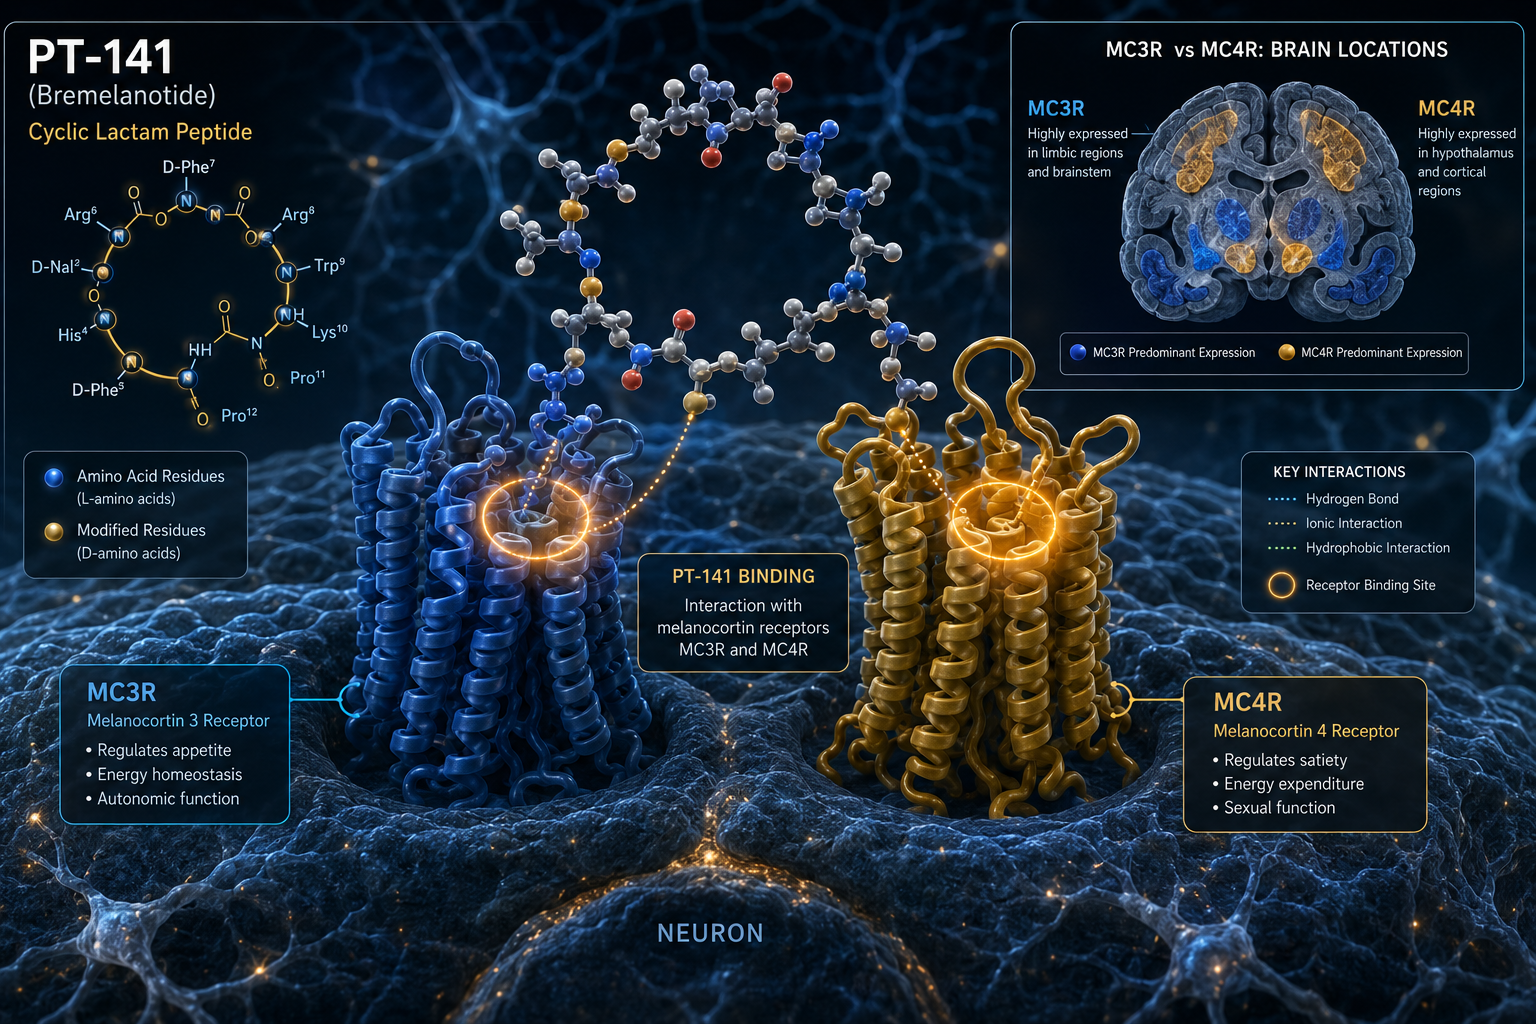
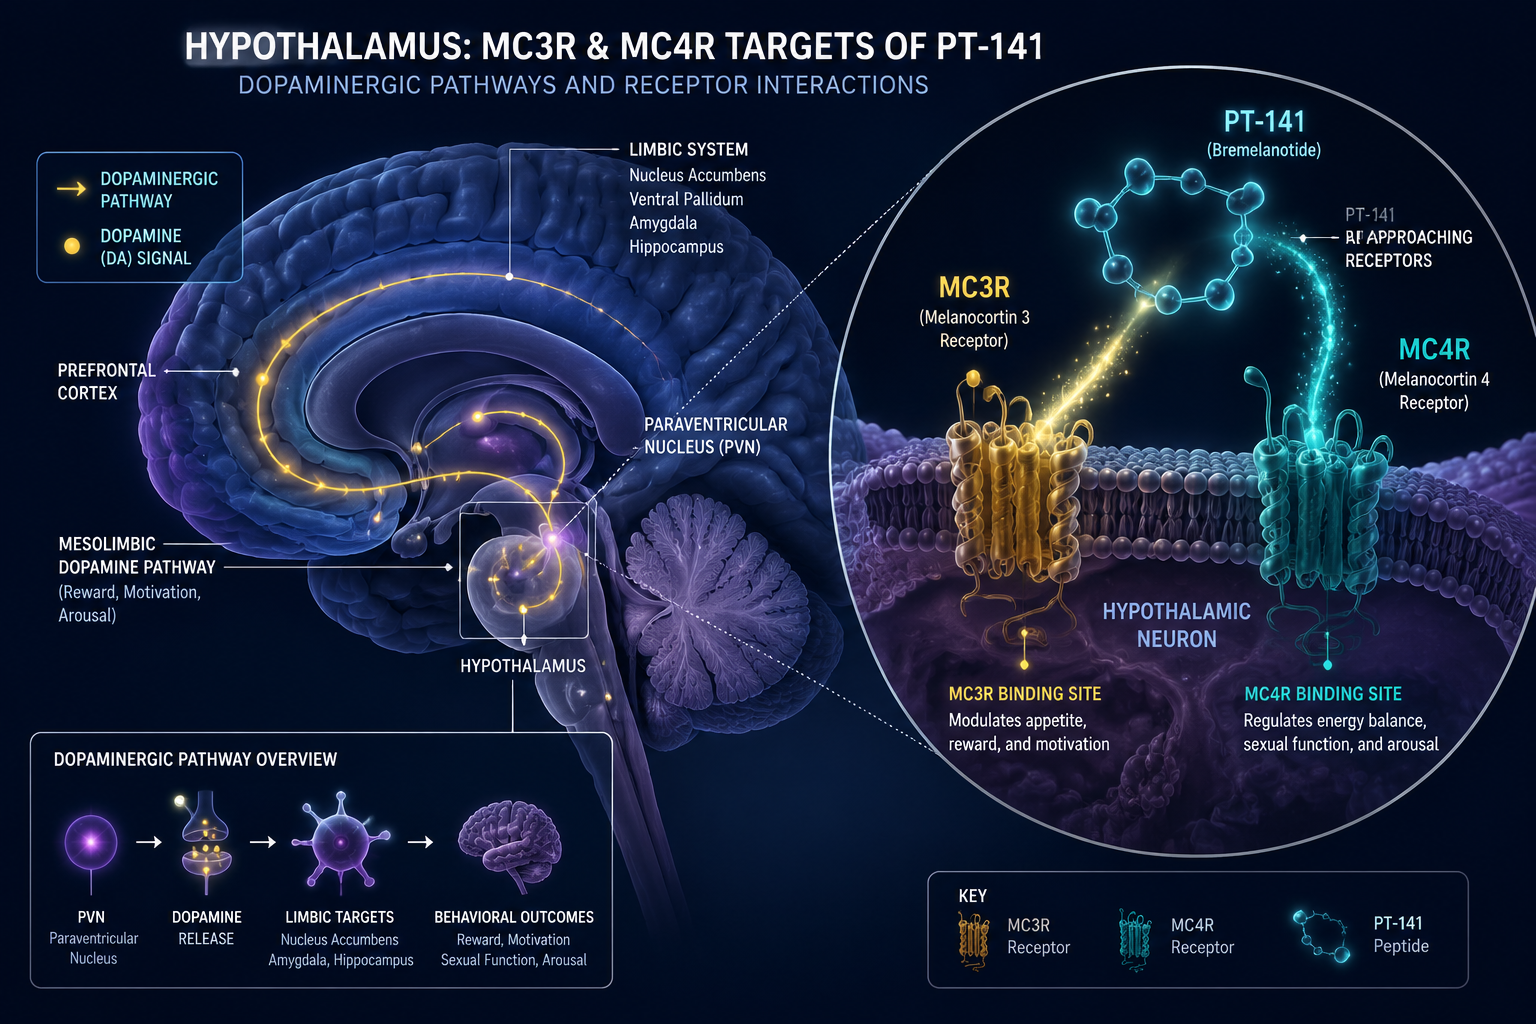
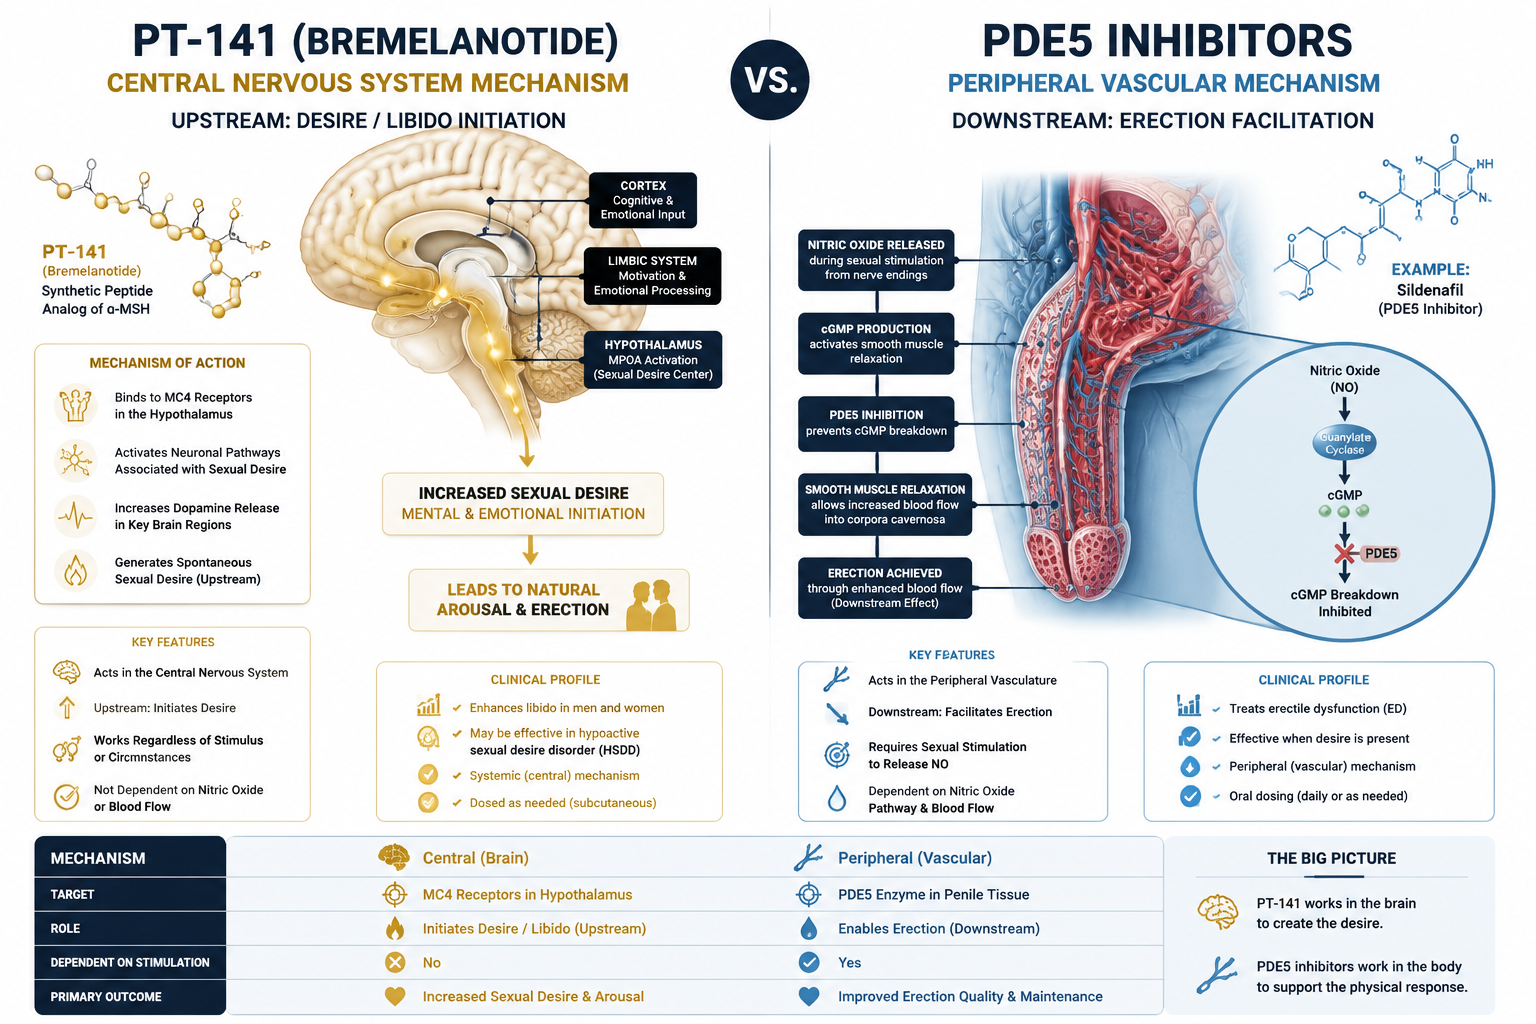
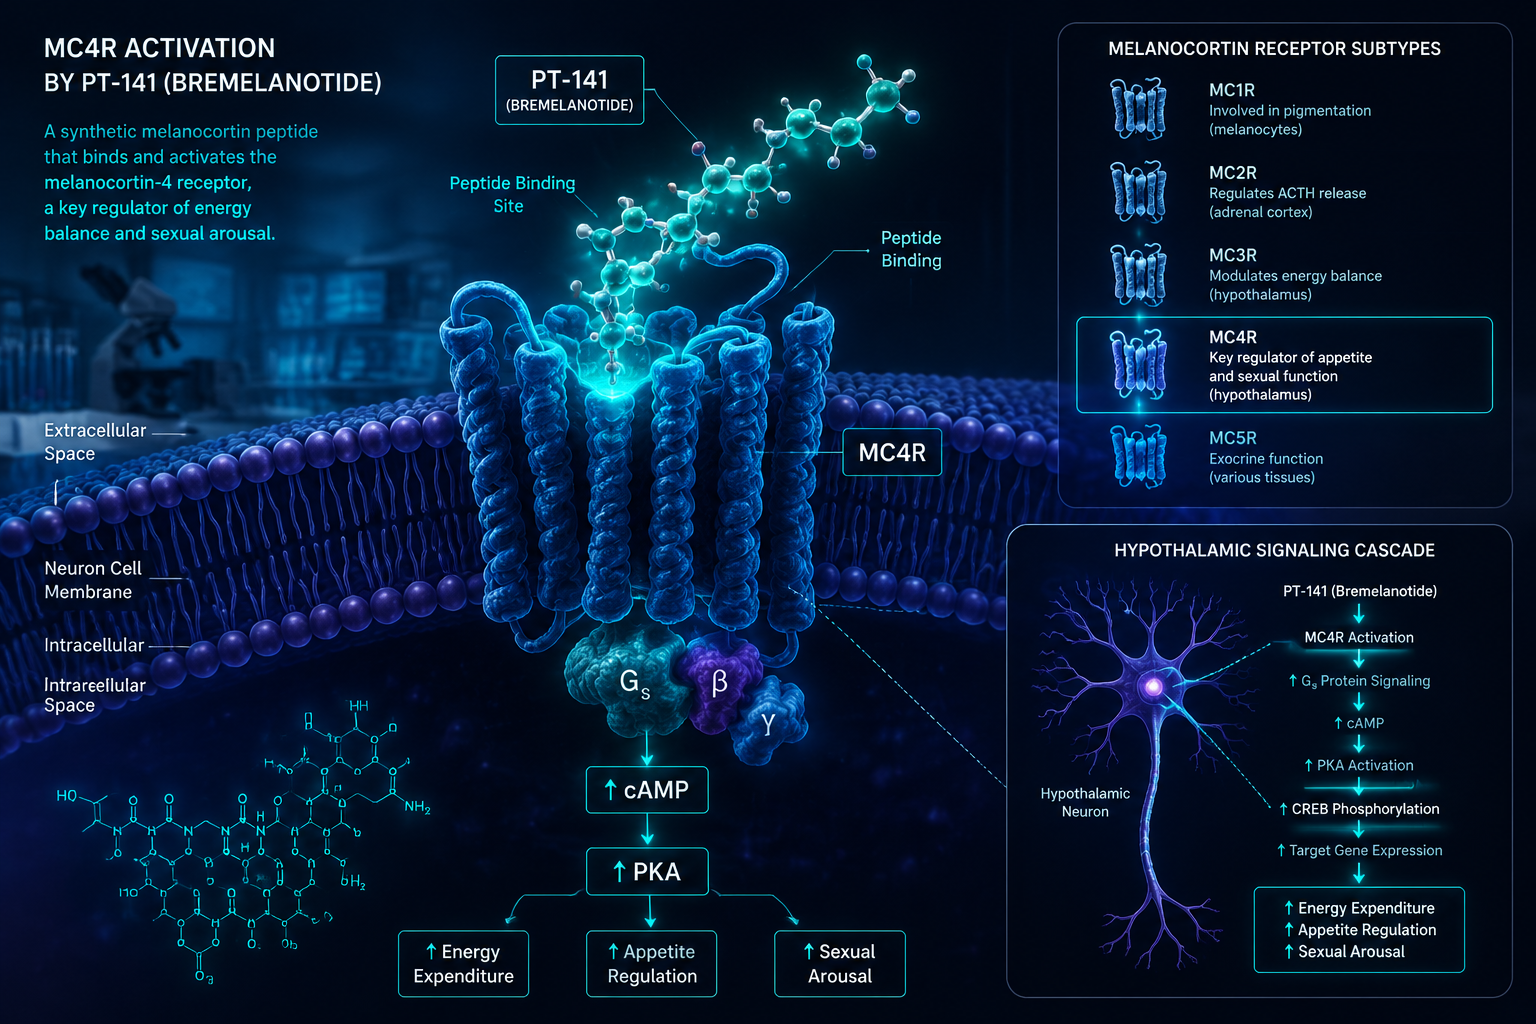
This article moves past mechanism basics. It focuses on the practical protocol questions that researchers, study designers, and compounding labs raise once they already understand how PT-141 (bremelanotide) activates melanocortin receptors.
Key Takeaways
- PT-141 has a well-characterized dose-dependent tolerability profile; nausea is the primary limiting adverse event and is strongly tied to dose size.
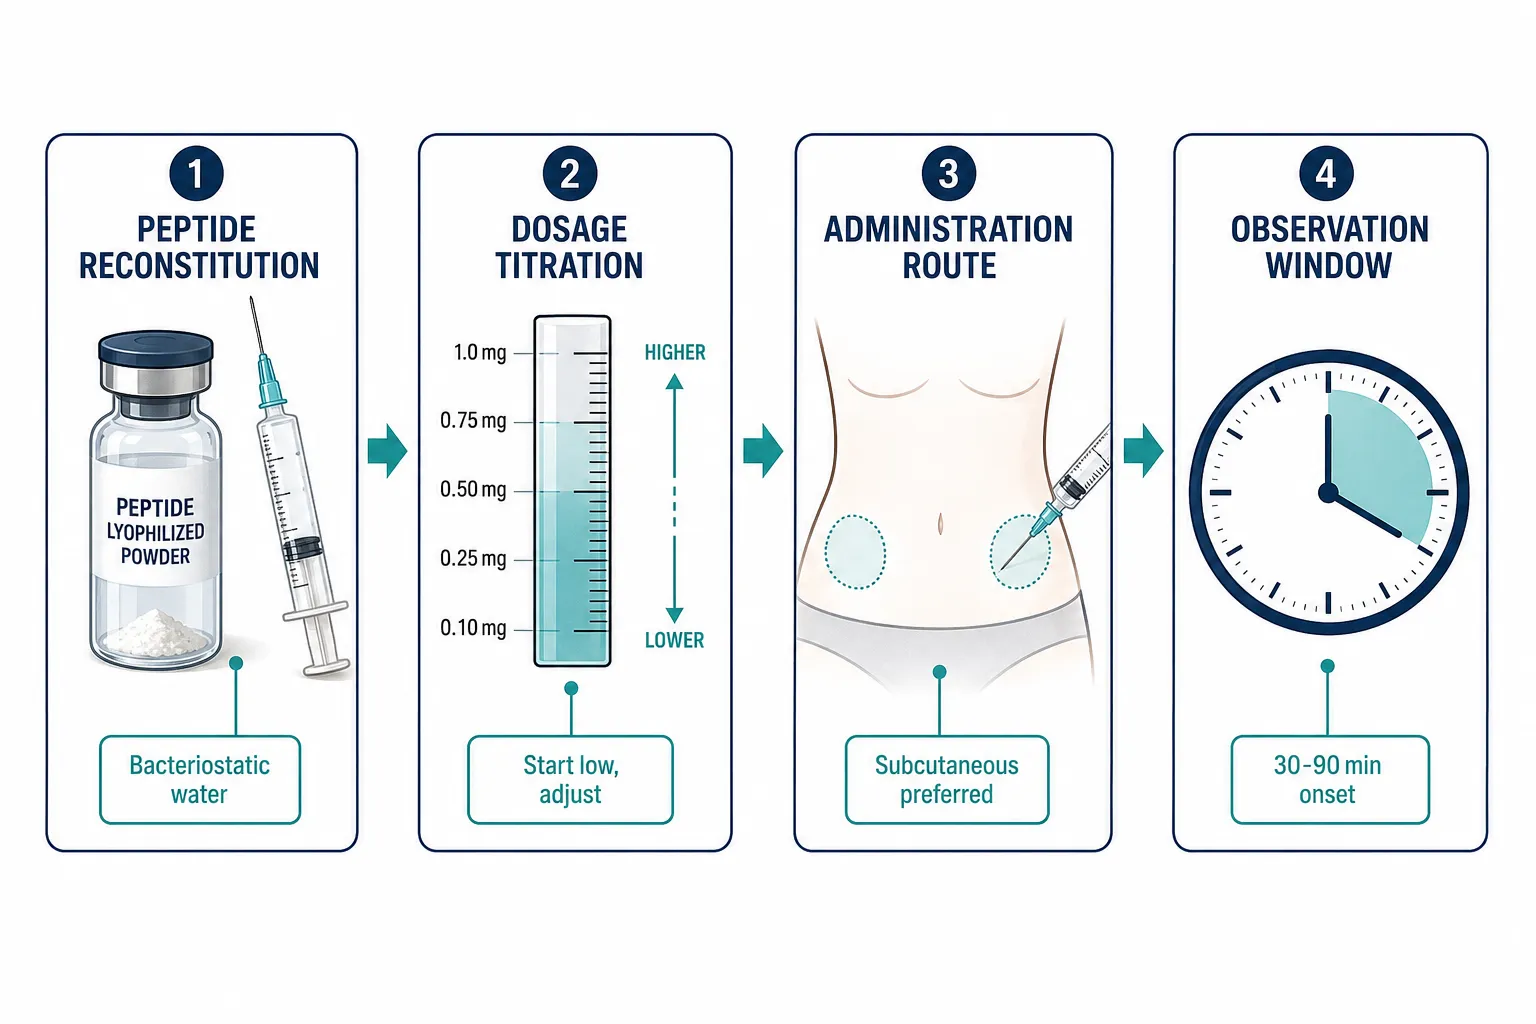
- Approved subcutaneous dosing sits at 1.75 mg, but research protocols often start lower (0.5-1.0 mg) and titrate carefully.
- Frequency of administration is a critical variable, hyperpigmentation risk rises sharply with repeated, closely spaced dosing.
- Cardiovascular monitoring, especially blood pressure, is a non-negotiable safety checkpoint in any responsible study design.
- Male and female research populations show meaningfully different tolerability patterns that labs must account for in study design.
What the Approved Dose Framework Tells Researchers
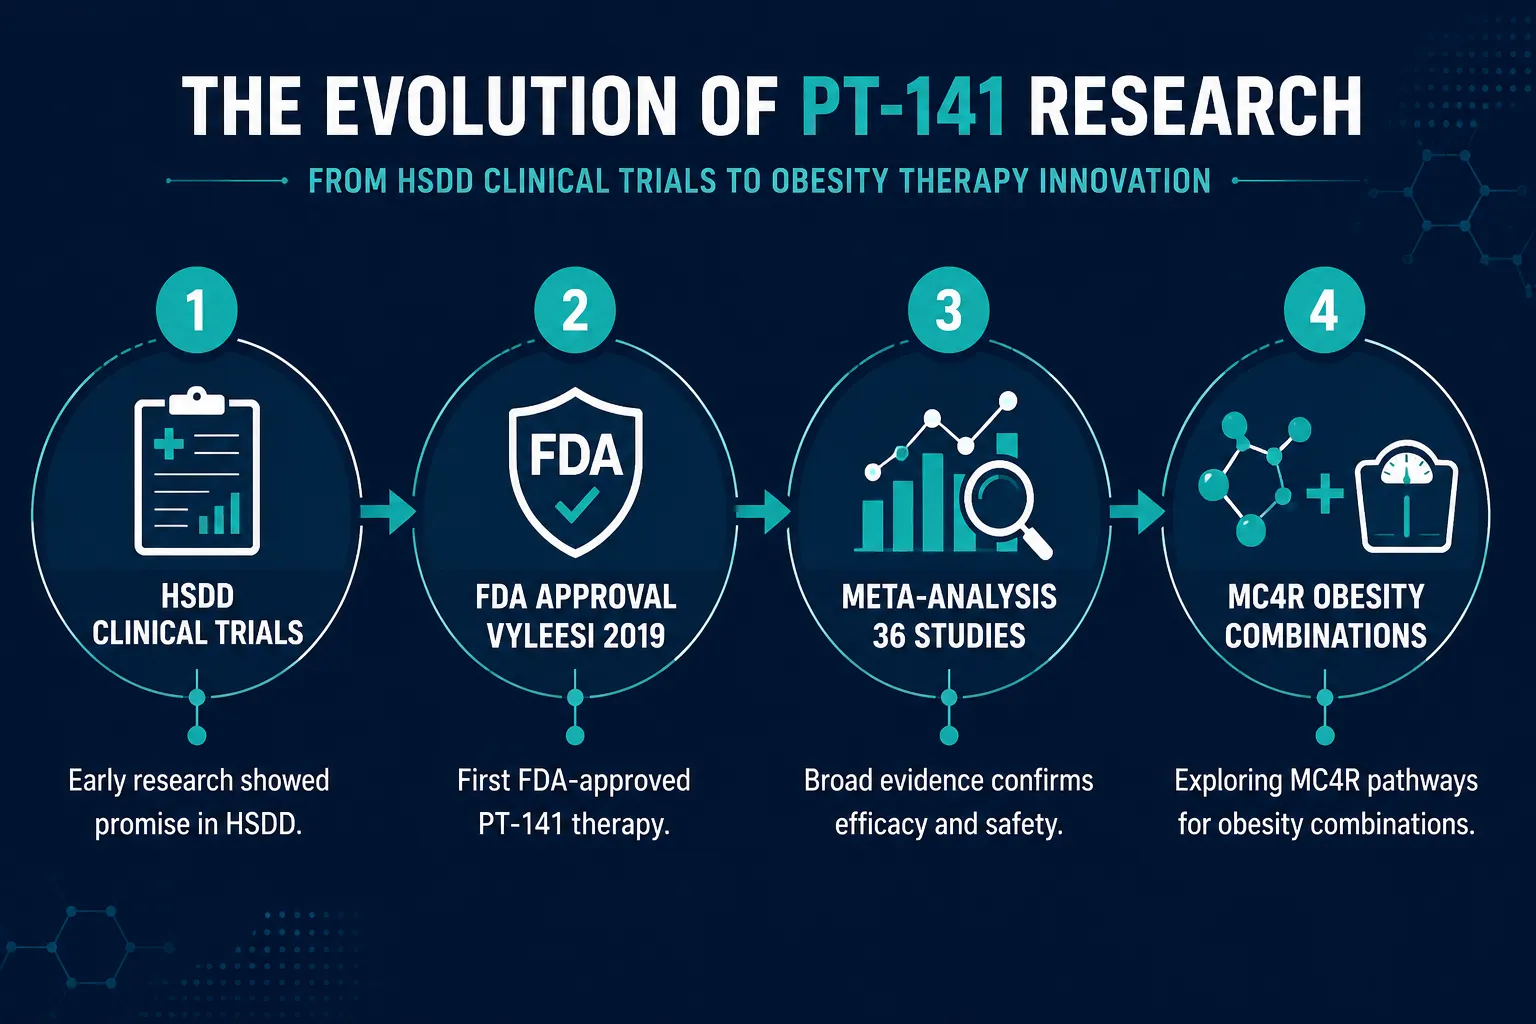
The FDA-approved subcutaneous dose of 1.75 mg, administered approximately 45 minutes before anticipated activity, forms the baseline reference point for any PT-141 Peptide Research Safety Guide: Dosing, Timing, and Tolerability Questions Labs Ask. Clinical monographs specify a maximum of one dose per 24 hours and no more than one dose every 72 hours in standard use.
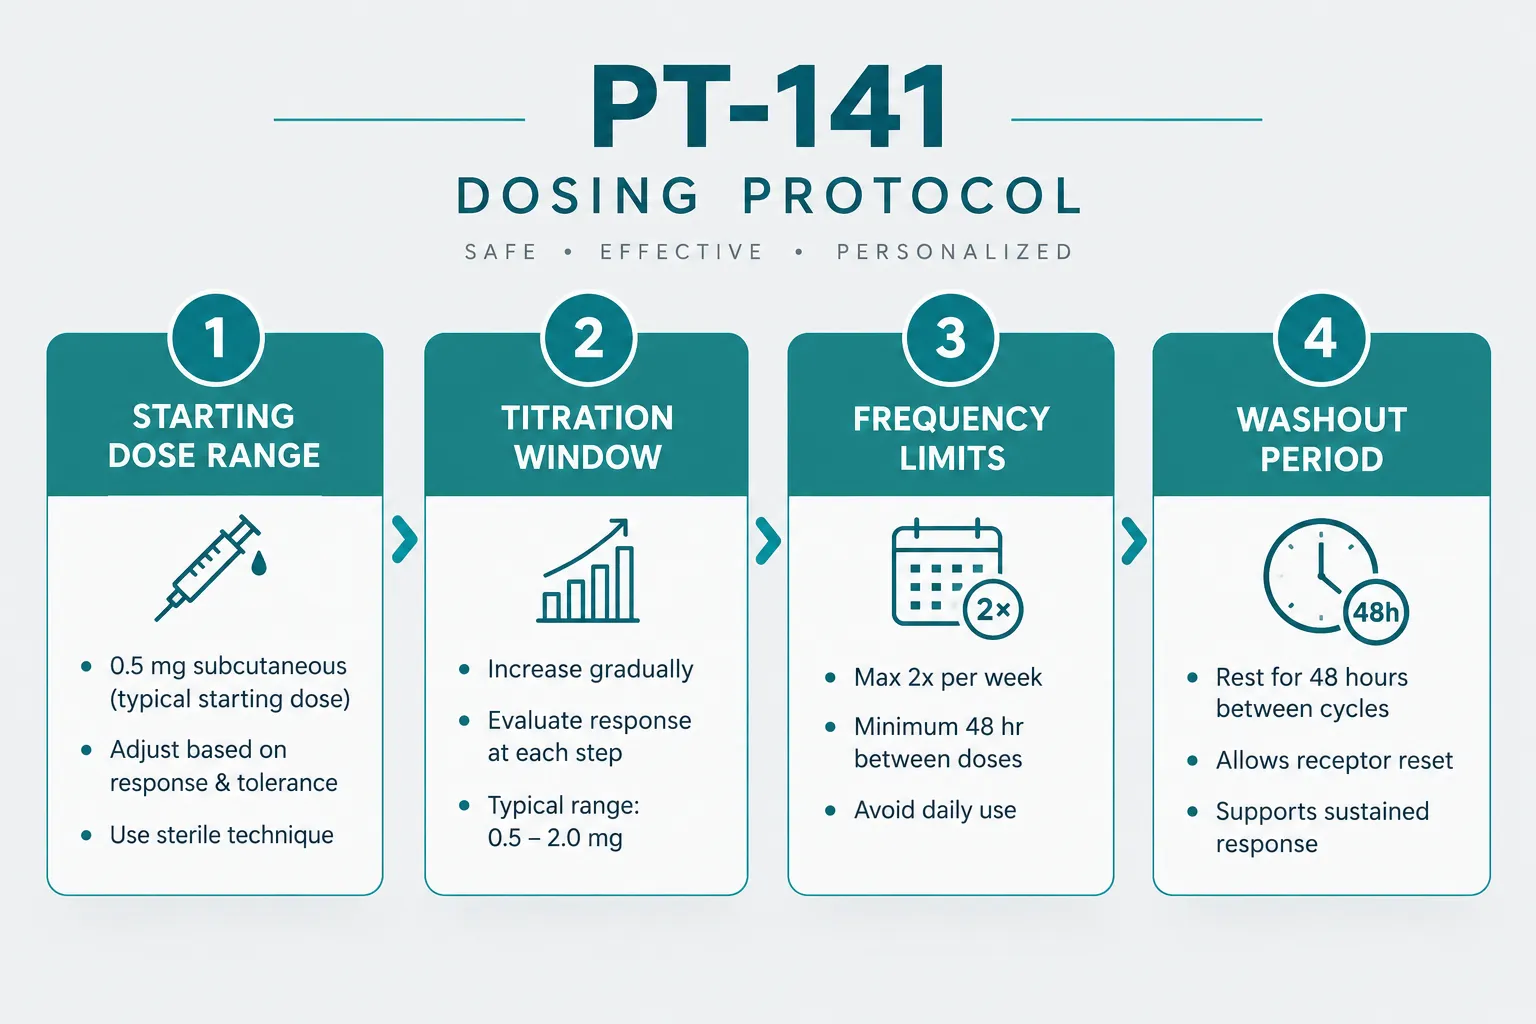
For research settings, these boundaries matter because they define the outer edge of a well-studied safety envelope. Most investigational protocols use this approved framework as a ceiling, not a starting point. Common research titration approaches include:
- Starting dose: 0.5 mg subcutaneous to assess individual response
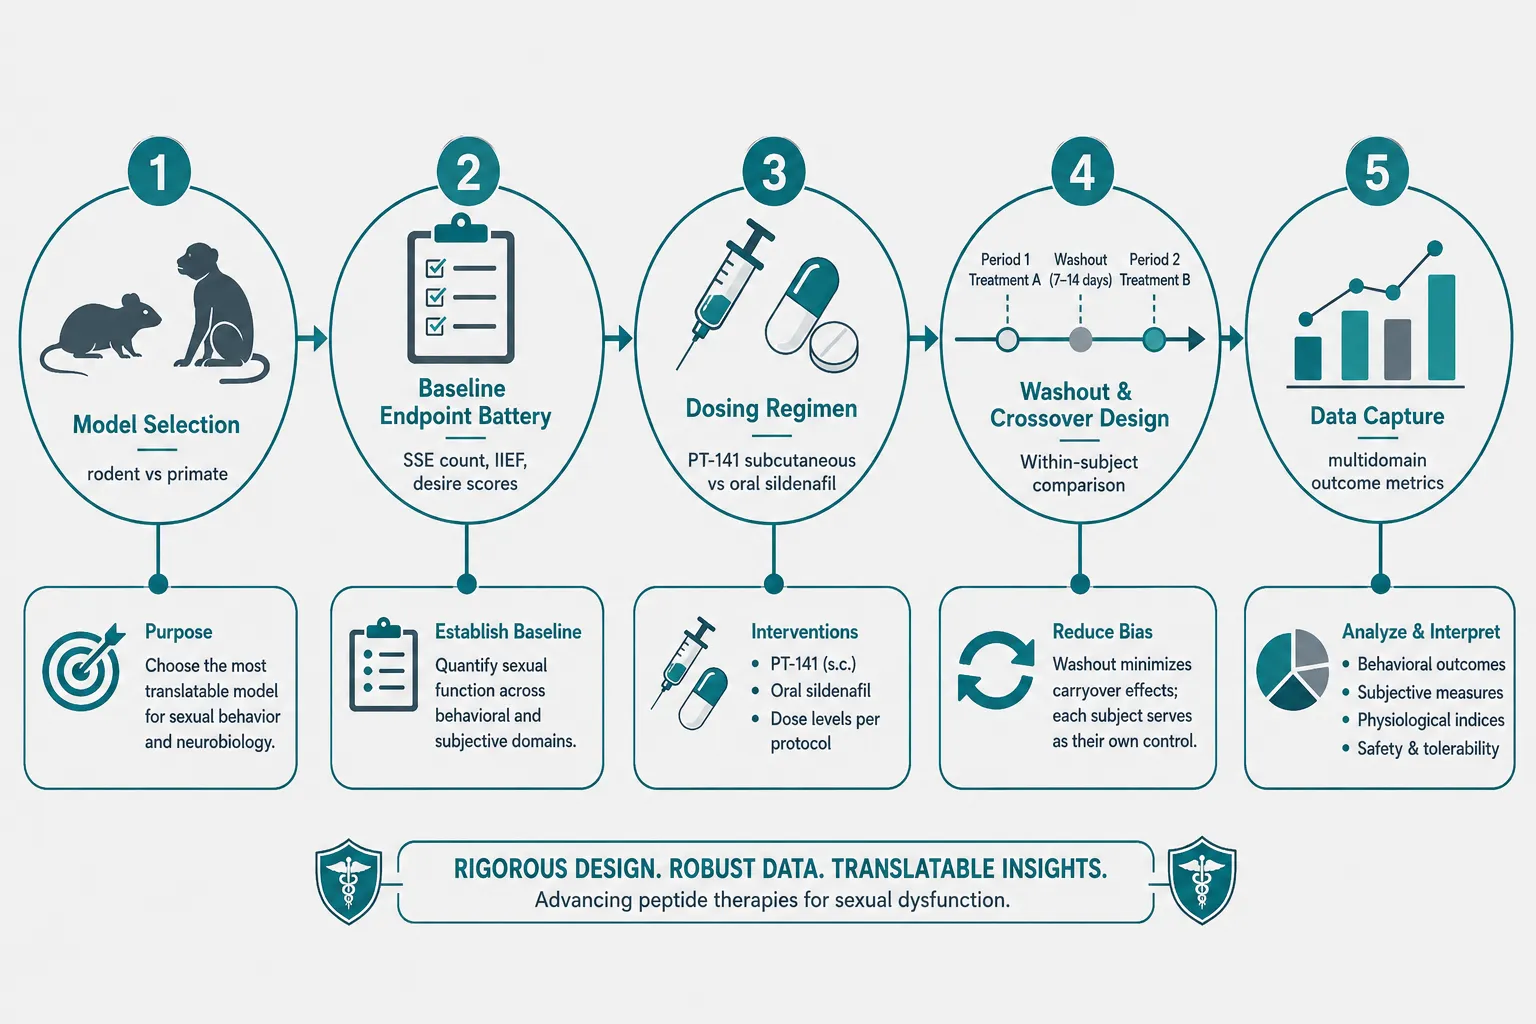
- Intermediate dose: 1.0 mg if the 0.5 mg dose is well tolerated after two to three exposures
- Standard research dose: 1.75 mg, consistent with the approved label
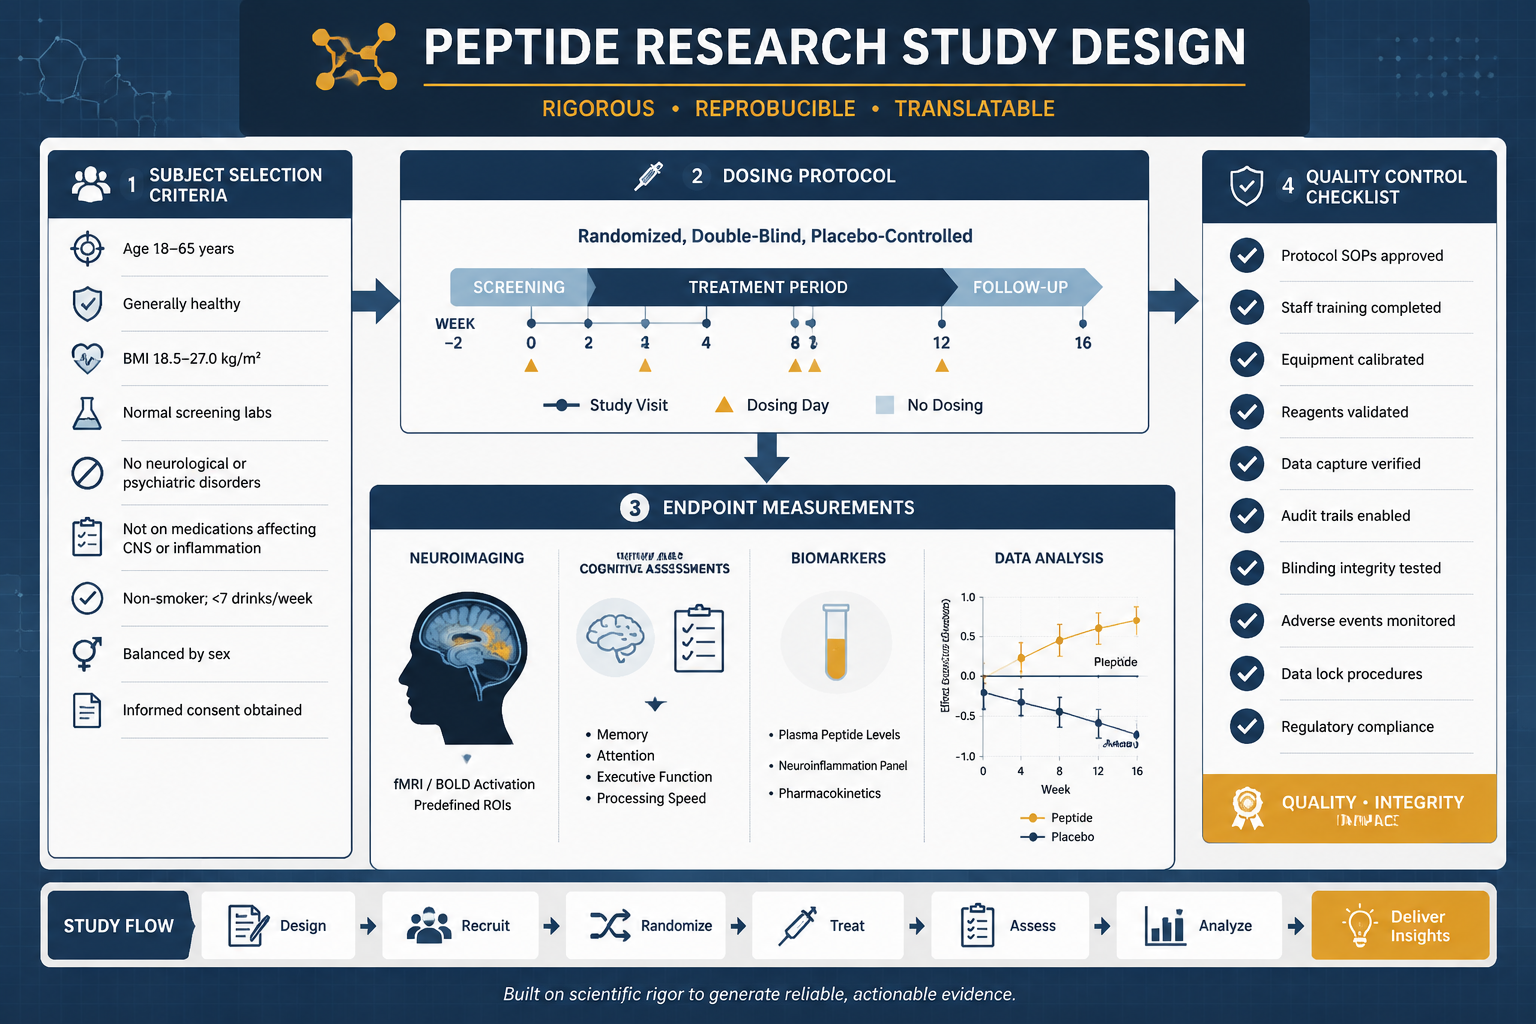
- Frequency limit: No more than twice weekly in most current study designs, with a minimum 48-hour gap between doses
"The dose is only half the equation. How often a subject receives PT-141 determines a different set of risks entirely."
Intranasal administration was studied in earlier trials at doses up to 20 mg. Maximum-tolerated dose data from that work helped define the nausea threshold that now informs subcutaneous titration strategies. Subcutaneous delivery produces a more controlled absorption curve and is the standard route in current research.
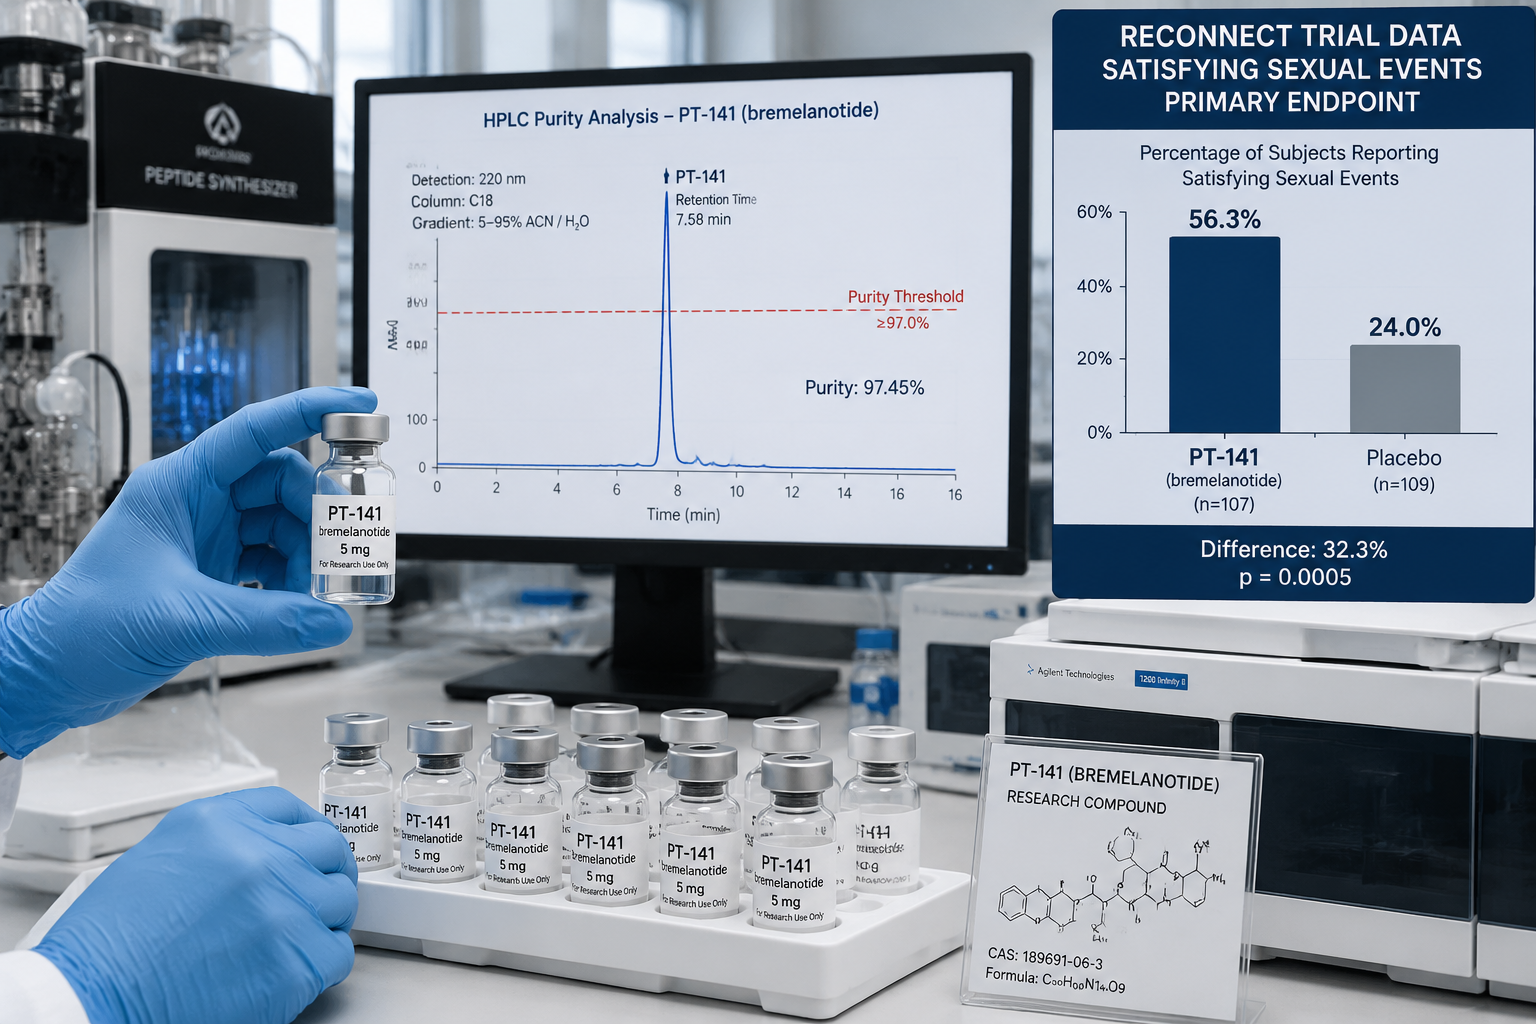
For labs sourcing compounds for controlled studies, working with lab tested peptides is a baseline quality requirement before any dosing protocol can be considered valid.
Tolerability Profile: The Questions Labs Must Answer First
Every credible PT-141 Peptide Research Safety Guide: Dosing, Timing, and Tolerability Questions Labs Ask places tolerability assessment before efficacy measurement. The adverse event profile is well-characterized and dose-dependent.
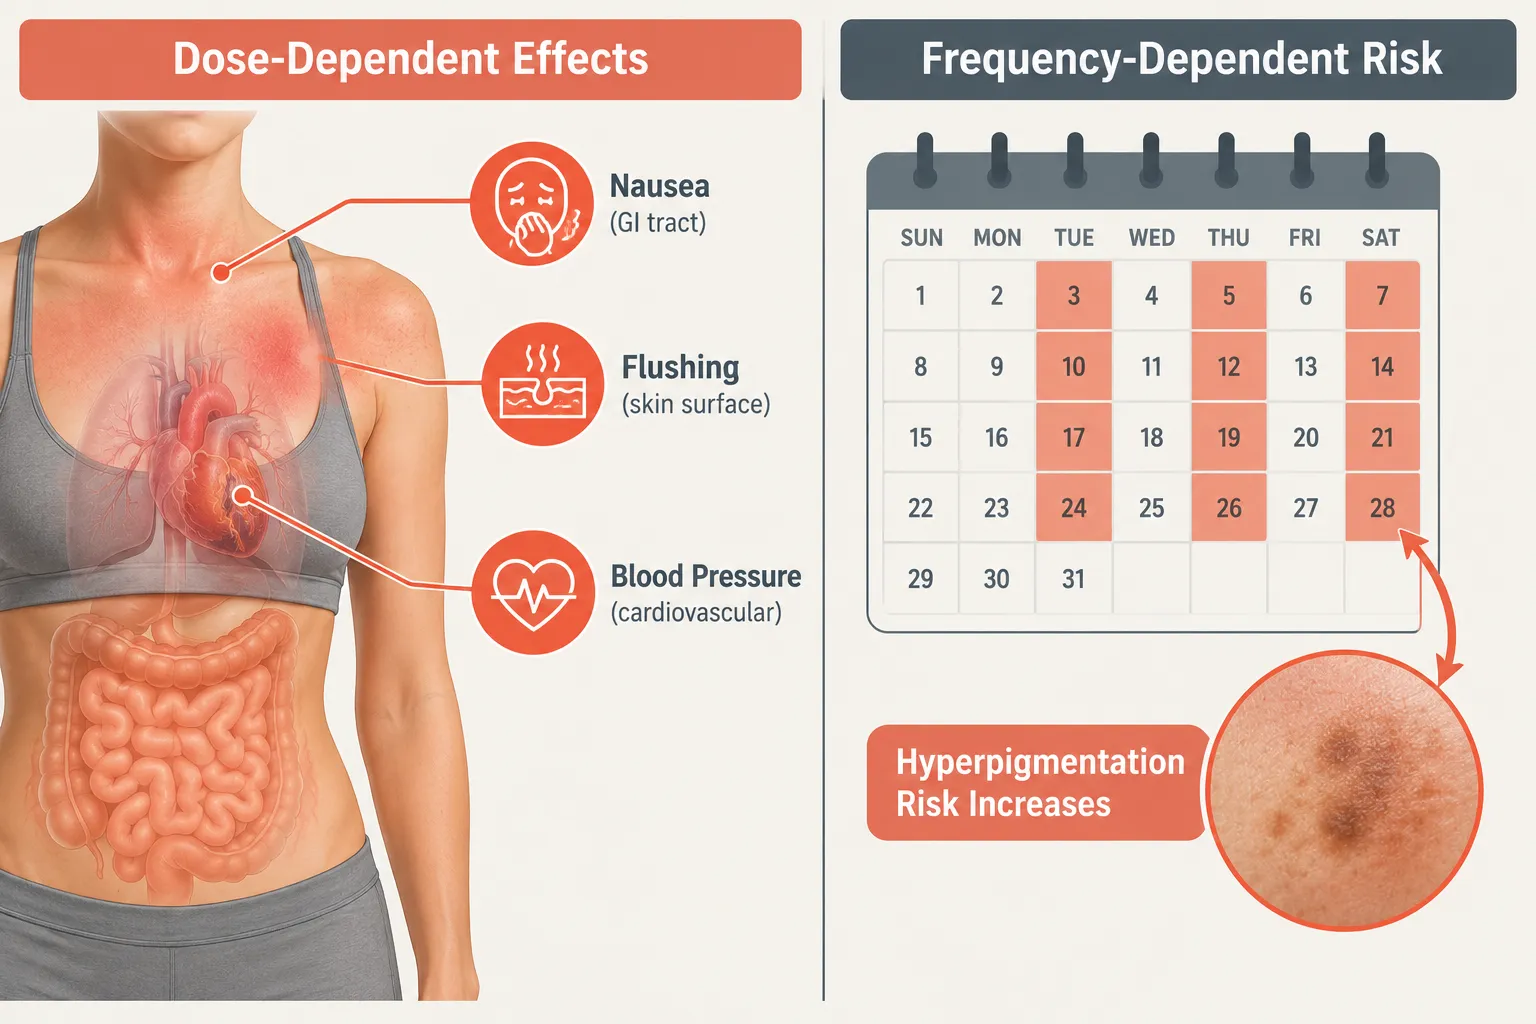
Nausea and Gastrointestinal Effects
Nausea is the most commonly reported adverse event across all PT-141 trials. Key findings from clinical data include:
- Nausea incidence rises sharply above 1.75 mg
- Onset typically occurs within 30-60 minutes of administration
- Duration is usually under two hours at approved doses
- Pre-dosing with a light meal reduces severity in most subjects
Labs designing multi-dose studies should build nausea scoring into every session log. Dropout rates in trials that did not manage nausea proactively were meaningfully higher than in those with structured tolerability support.
Cardiovascular and Blood Pressure Monitoring
PT-141 produces a transient, dose-dependent decrease in blood pressure followed by a rebound increase. This biphasic cardiovascular effect is one of the most important safety questions labs must address. Standard monitoring requirements include:
| Monitoring Point | Timing Relative to Dose |
|---|---|
| Baseline blood pressure | 10 minutes before administration |
| First post-dose check | 30 minutes after administration |
| Peak effect window | 45-90 minutes after administration |
| Return-to-baseline check | 3 hours after administration |
Subjects with pre-existing cardiovascular conditions are typically excluded from PT-141 research protocols for this reason.
Skin Hyperpigmentation
This adverse effect is strongly frequency-dependent rather than dose-dependent. Melanocortin receptor activation drives melanin production, and repeated stimulation accumulates the effect. Labs running extended or repeat-dose studies must:
- Document baseline skin tone and any existing pigmentation changes
- Limit dosing frequency to no more than twice weekly
- Include washout periods of at least two weeks between study phases
- Monitor focal injection sites separately from systemic pigmentation changes
Male vs. Female Research Populations and Off-Label Study Design
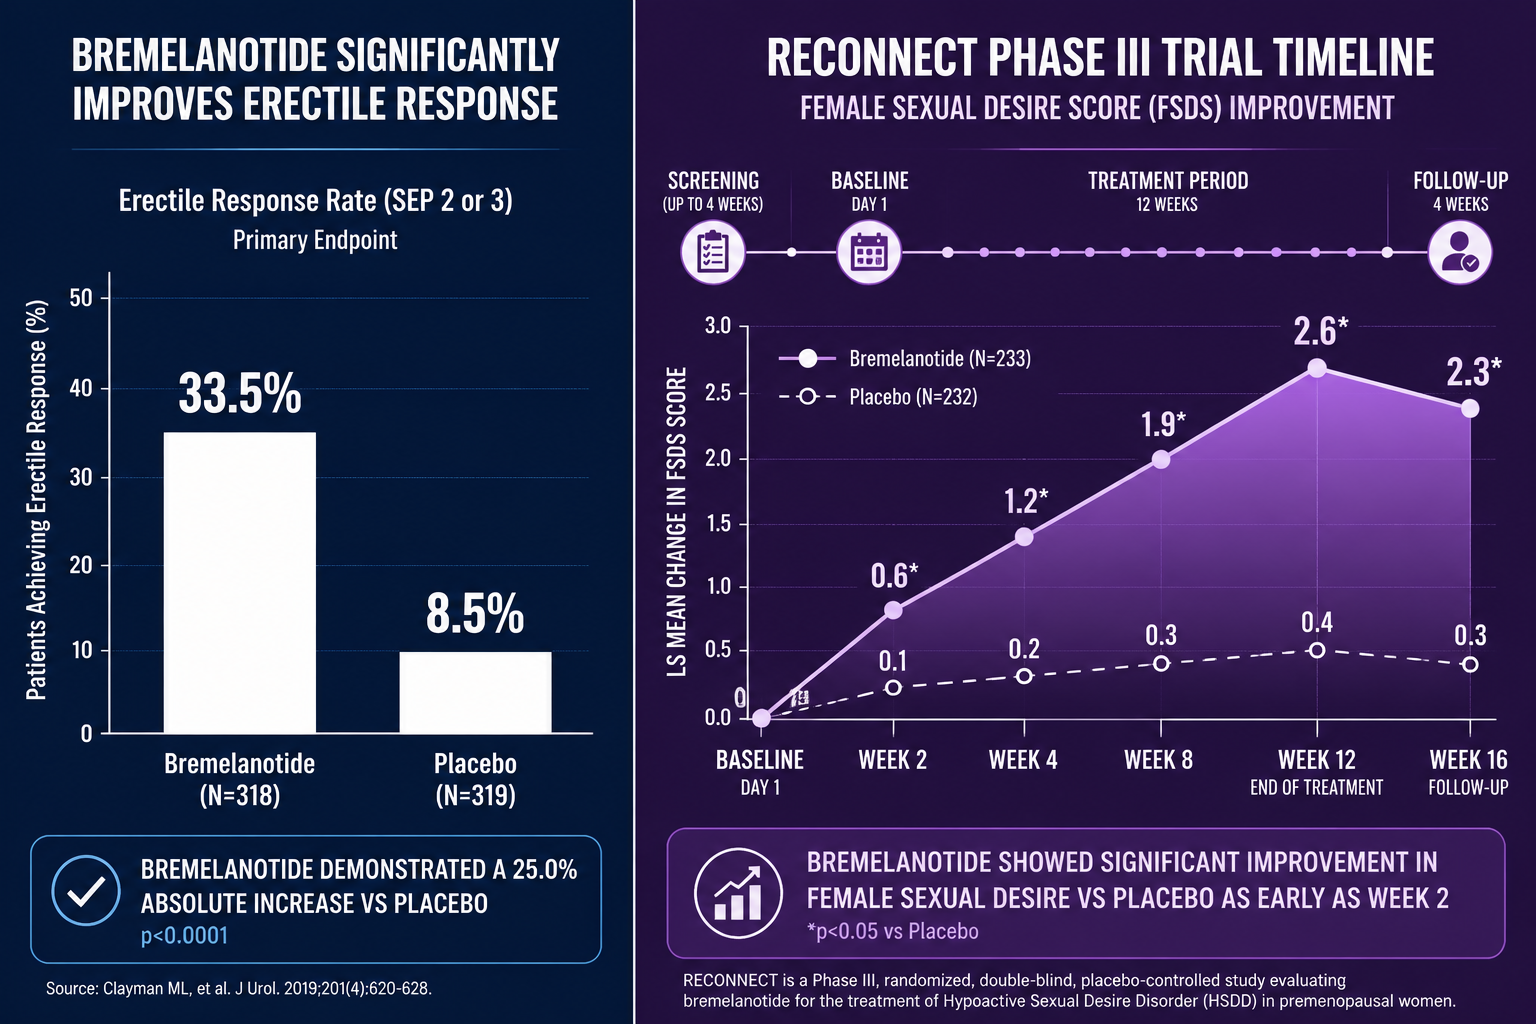
The approved indication for PT-141 is hypoactive sexual desire disorder in premenopausal women. However, a significant portion of current research examines male populations and other off-label applications, which raises distinct study design questions.
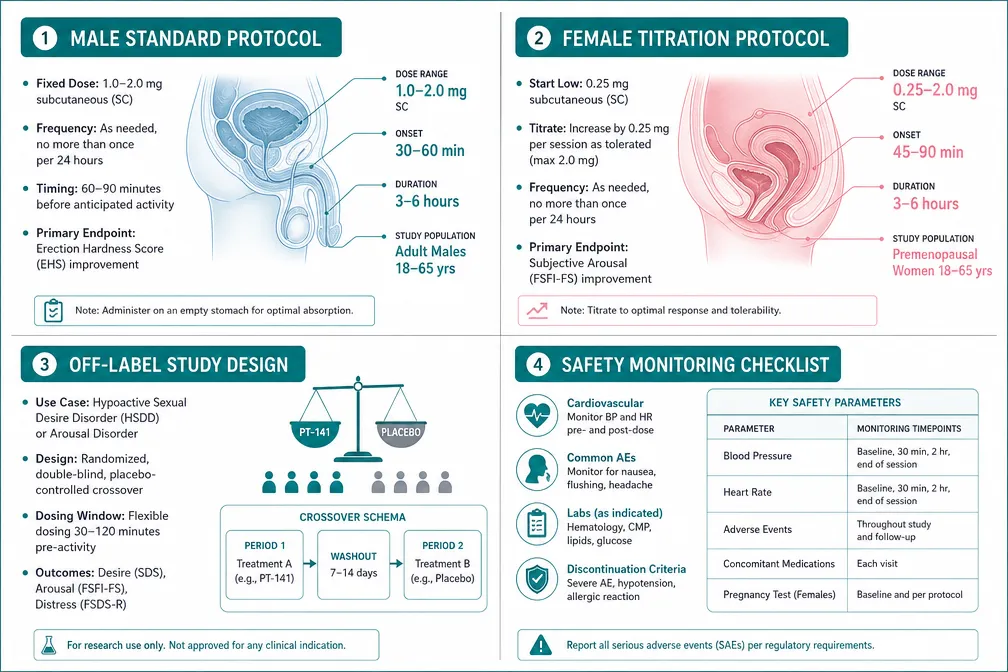
In female populations, the tolerability profile aligns closely with label data. Hormonal cycle phase at time of dosing is a variable some protocols now track, as receptor sensitivity may fluctuate across the cycle.
In male populations, research data suggest comparable efficacy signals at similar doses, but the tolerability curve differs slightly. Flushing and transient blood pressure changes appear more pronounced in some male cohorts. Labs designing male-focused studies often use a more conservative titration schedule.
Off-label research considerations for labs in 2026 include:
- Clearly defined primary endpoints that do not rely solely on subjective self-report
- Structured washout periods between study phases (minimum two weeks)
- Exclusion criteria that address cardiovascular risk, active skin conditions, and concurrent melanocortin-affecting medications
- Ethics board documentation that explicitly addresses the off-label nature of the research
Researchers comparing PT-141 to other peptides with central nervous system or receptor-mediated mechanisms may also find value in reviewing Semax research and Semax peptide literature for parallel study design frameworks. Similarly, labs building multi-peptide research panels sometimes reference SS-31 mitochondrial research themes for safety monitoring methodology applicable across peptide classes. For labs sourcing multiple compounds, wholesale peptides for sale options can support broader research programs, and GHK-Cu peptide studies offer additional reference points for skin-related adverse event monitoring protocols.
Conclusion
The PT-141 Peptide Research Safety Guide: Dosing, Timing, and Tolerability Questions Labs Ask comes down to three operational priorities: start low and titrate deliberately, treat frequency as a distinct risk variable from dose size, and build cardiovascular monitoring into every session regardless of subject health status.
Actionable next steps for labs:
- Establish a written titration protocol starting at 0.5 mg before moving to the 1.75 mg reference dose.
- Cap dosing frequency at twice weekly and document all inter-dose intervals.
- Implement a standardized blood pressure monitoring timeline at every administration session.
- Include skin pigmentation photography at baseline and at each study phase checkpoint.
- Differentiate male and female cohort protocols rather than applying a single design across populations.
- Source compounds only from suppliers providing documented purity and sterility testing.
Research into PT-141 continues to generate useful safety data in 2026. Labs that build rigorous tolerability frameworks from the start produce cleaner datasets and reduce the risk of protocol-disrupting adverse events mid-study.