Retatrutide Phase 3 Evidence Update: What New Triple-Agonist Results Change for GLP-3 Research Models
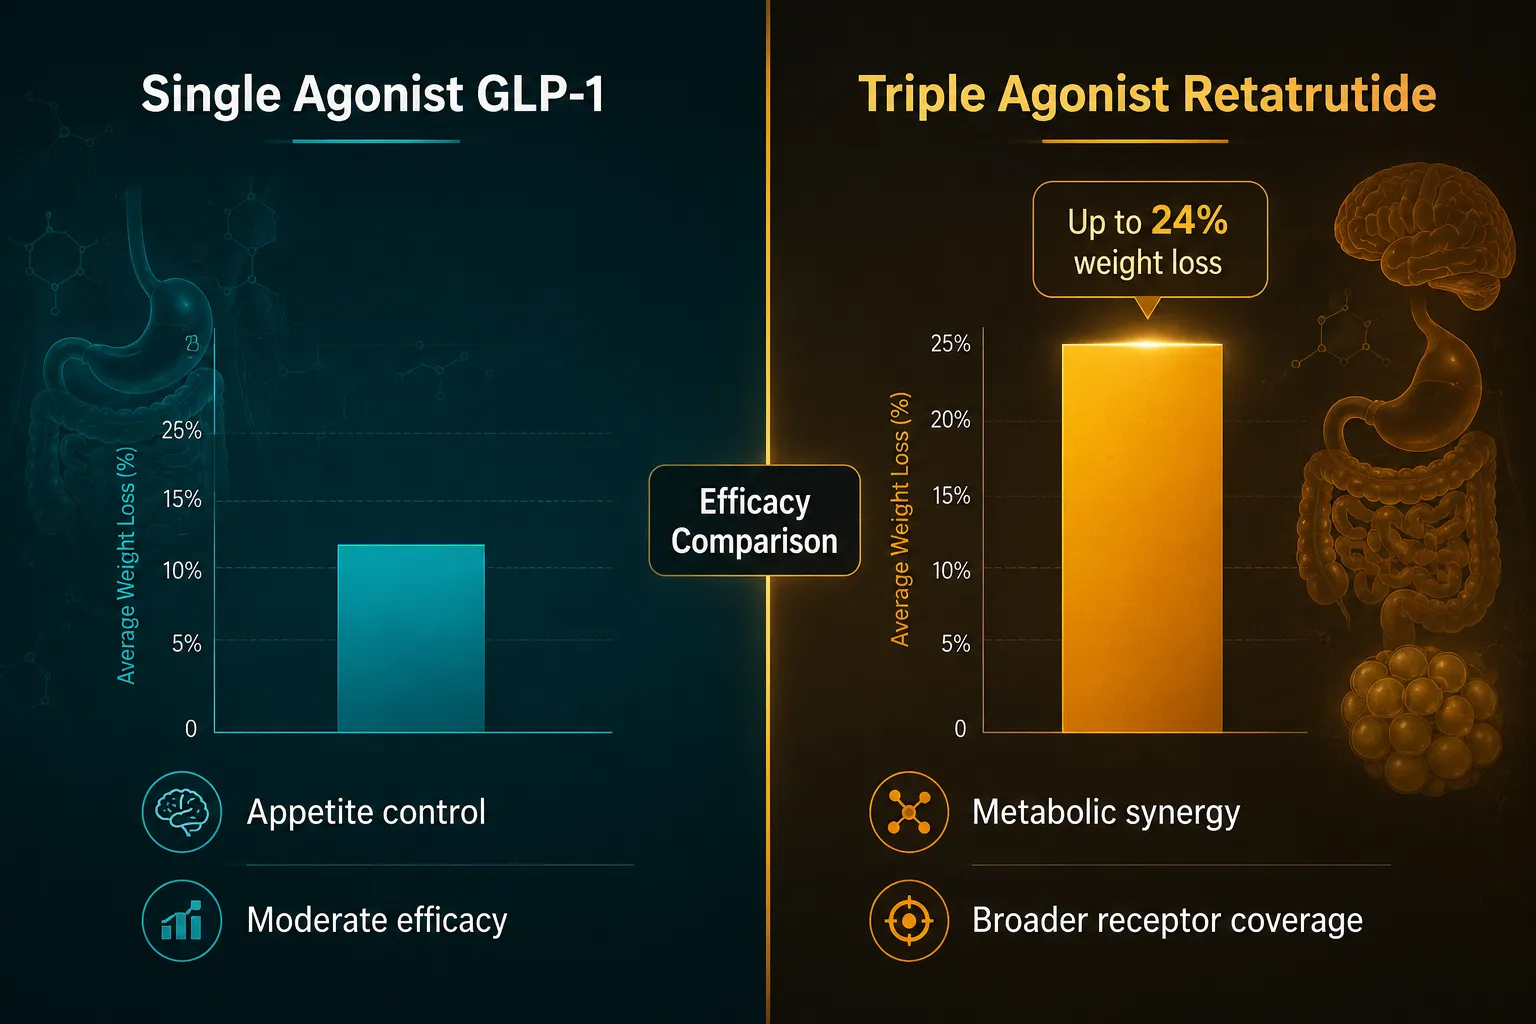
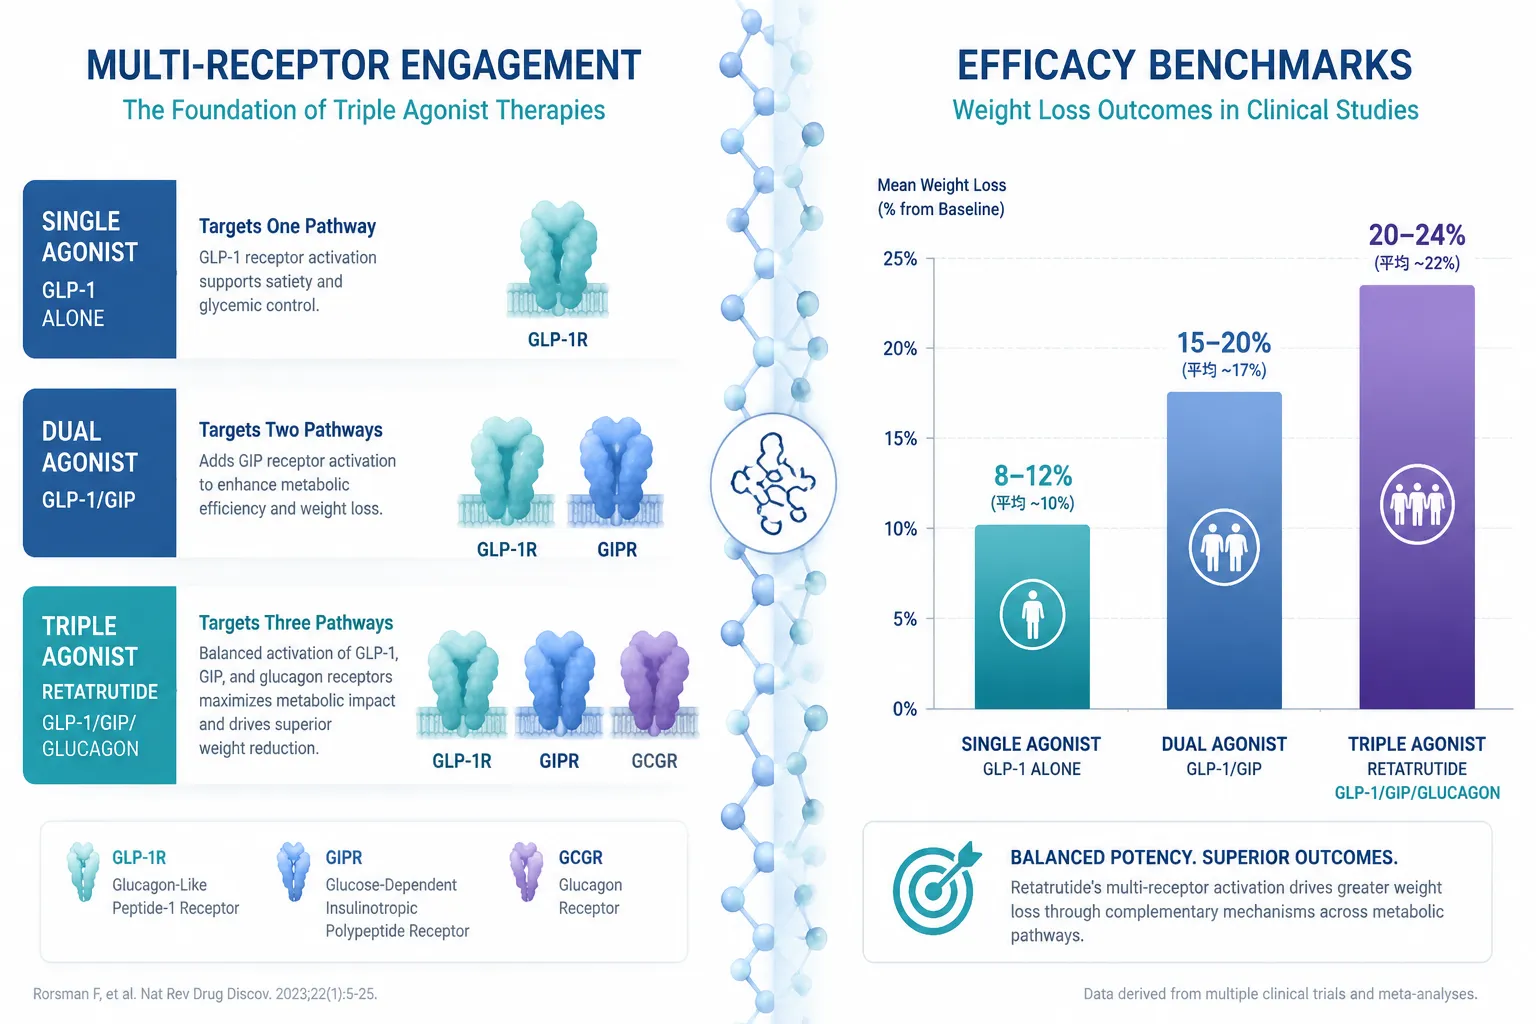
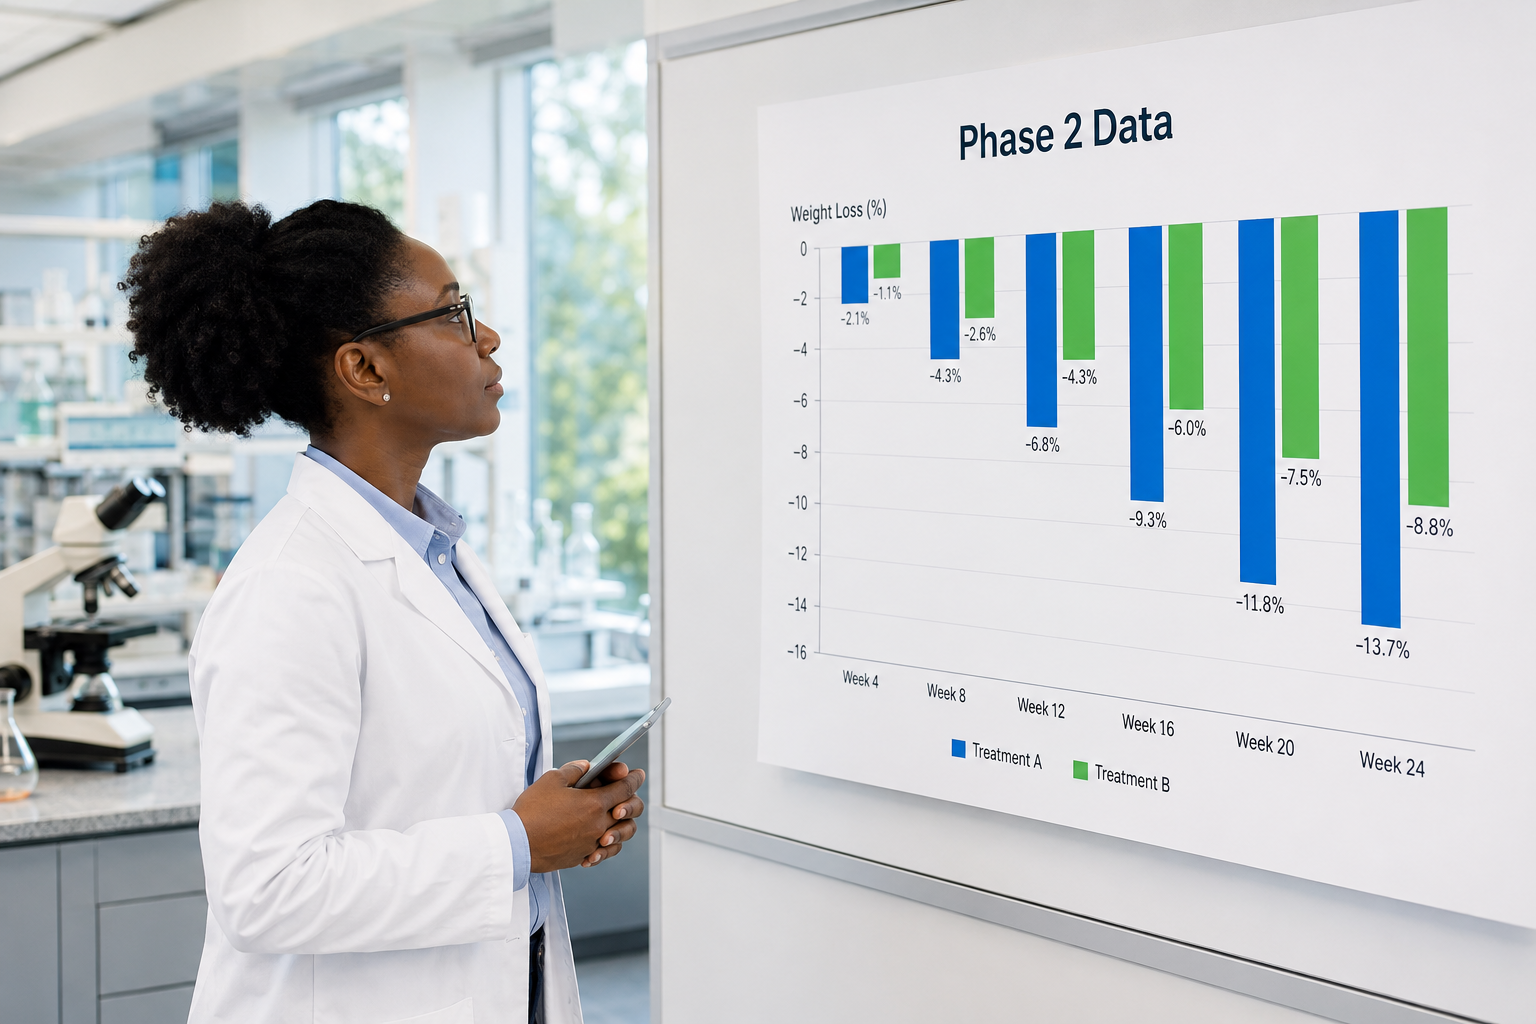
Roughly 24% mean body weight reduction at 48 weeks, that was the phase 2 signal that made retatrutide one of the most closely watched peptides in metabolic research. Now, with multiple phase 3 readouts published or presented through 2026, the question is no longer whether the triple-agonist effect is real. The question is what the Retatrutide Phase 3 Evidence Update: What New Triple-Agonist Results Change for GLP-3 Research Models means for how researchers design experiments around GLP-1, GIP, and glucagon receptor signaling going forward.
Key Takeaways
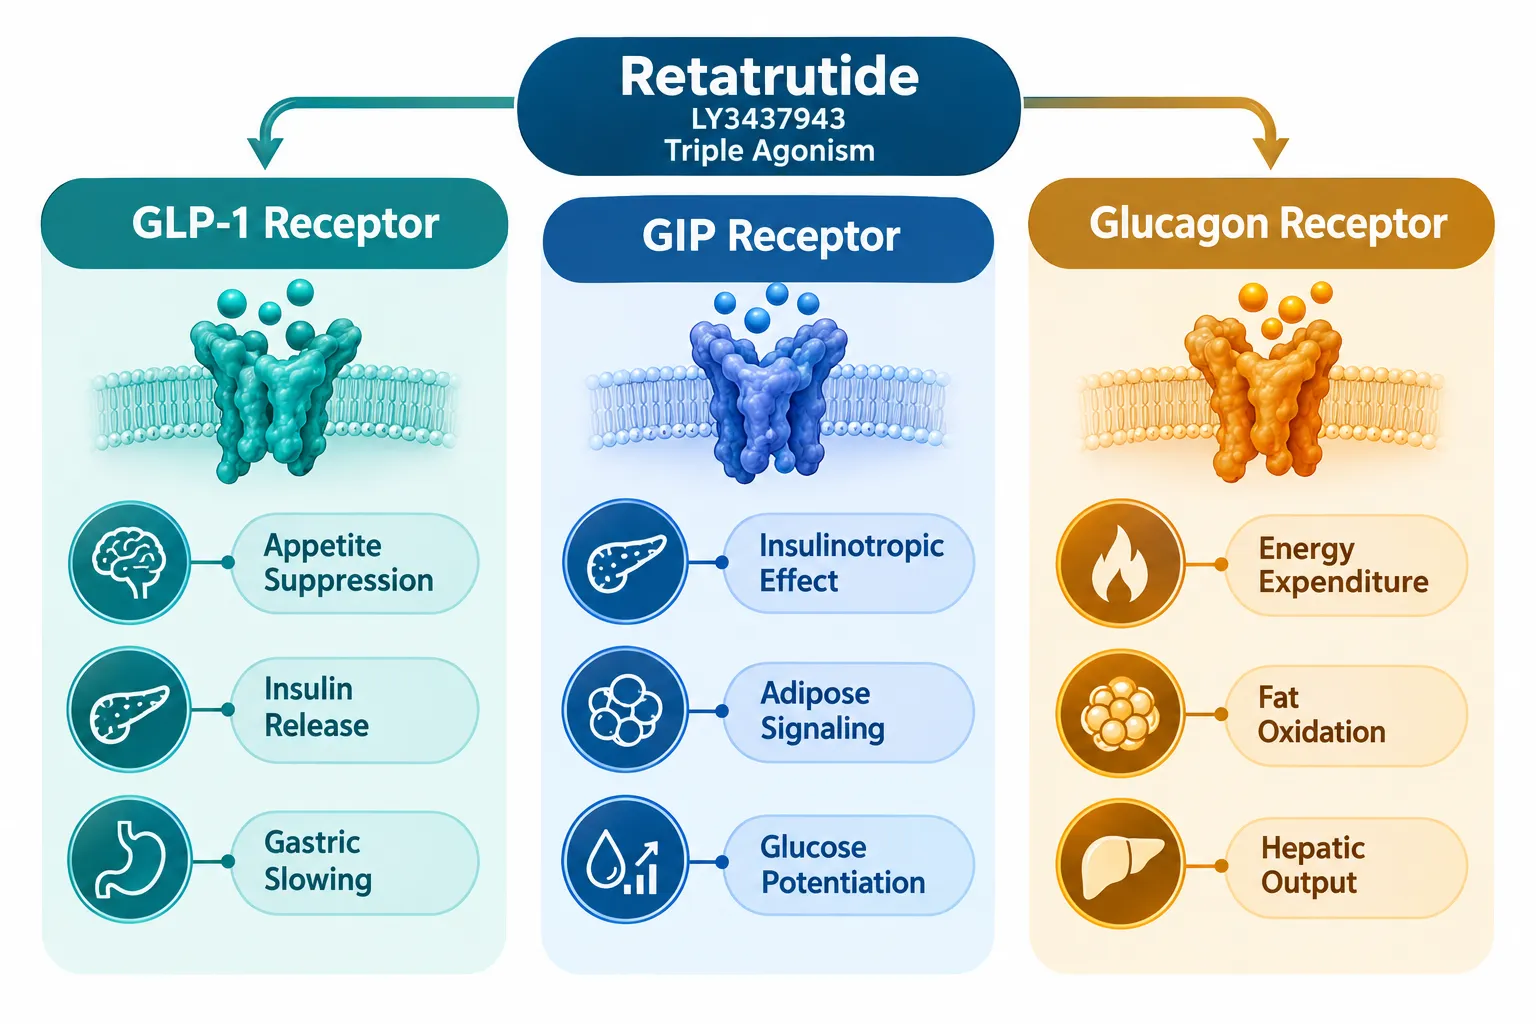
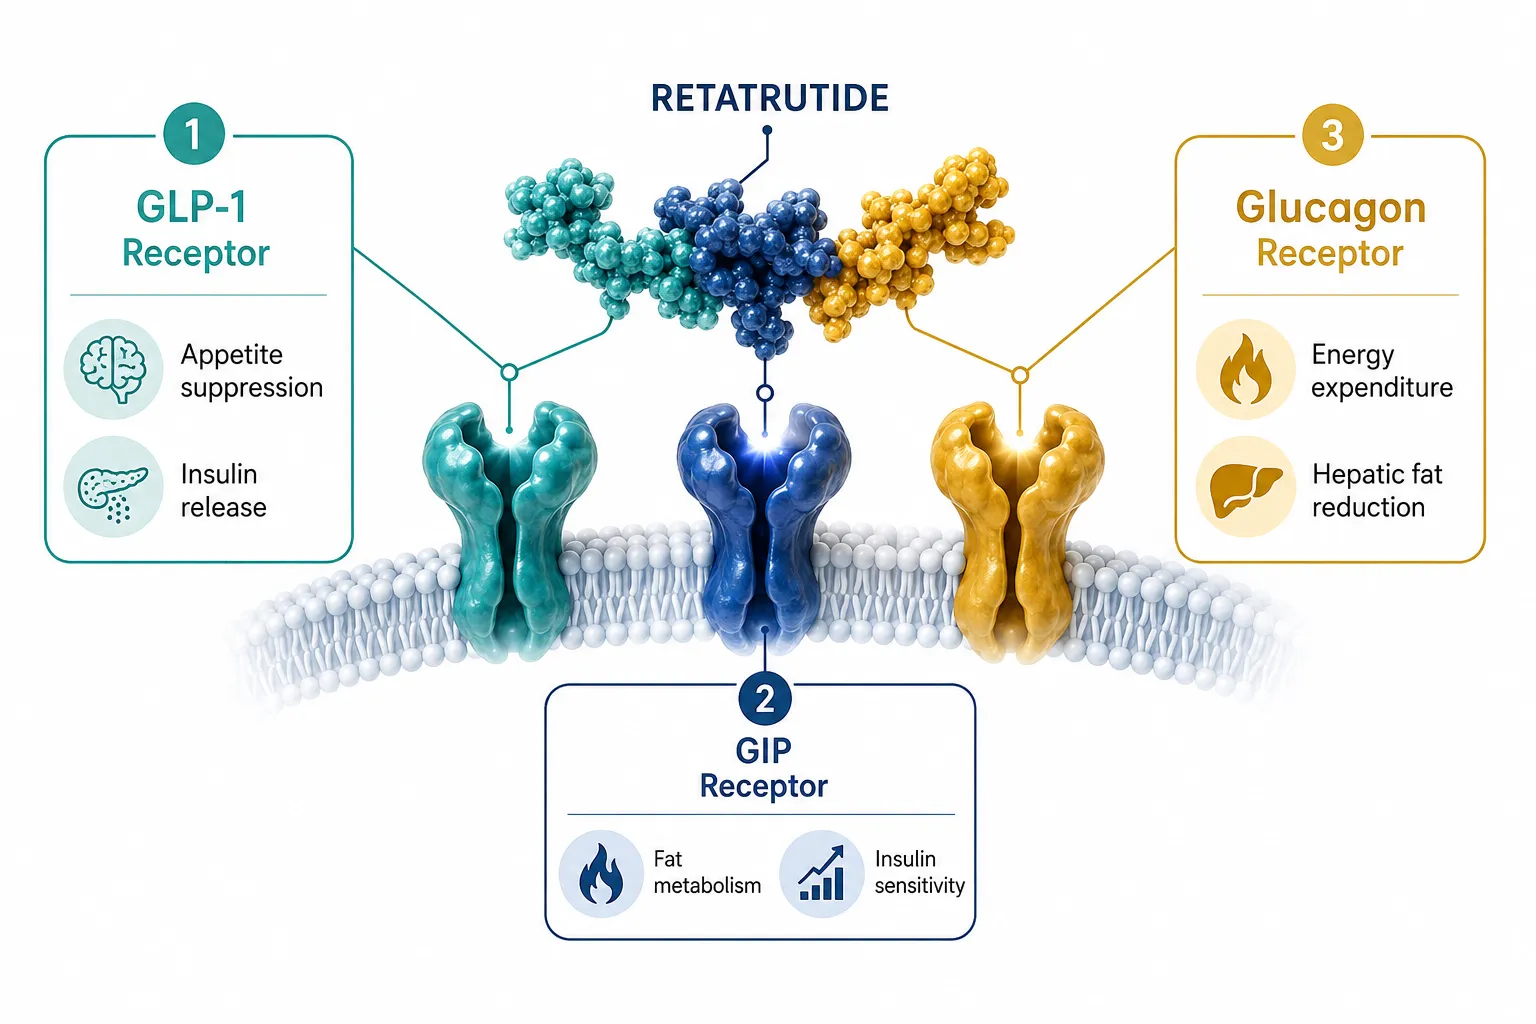
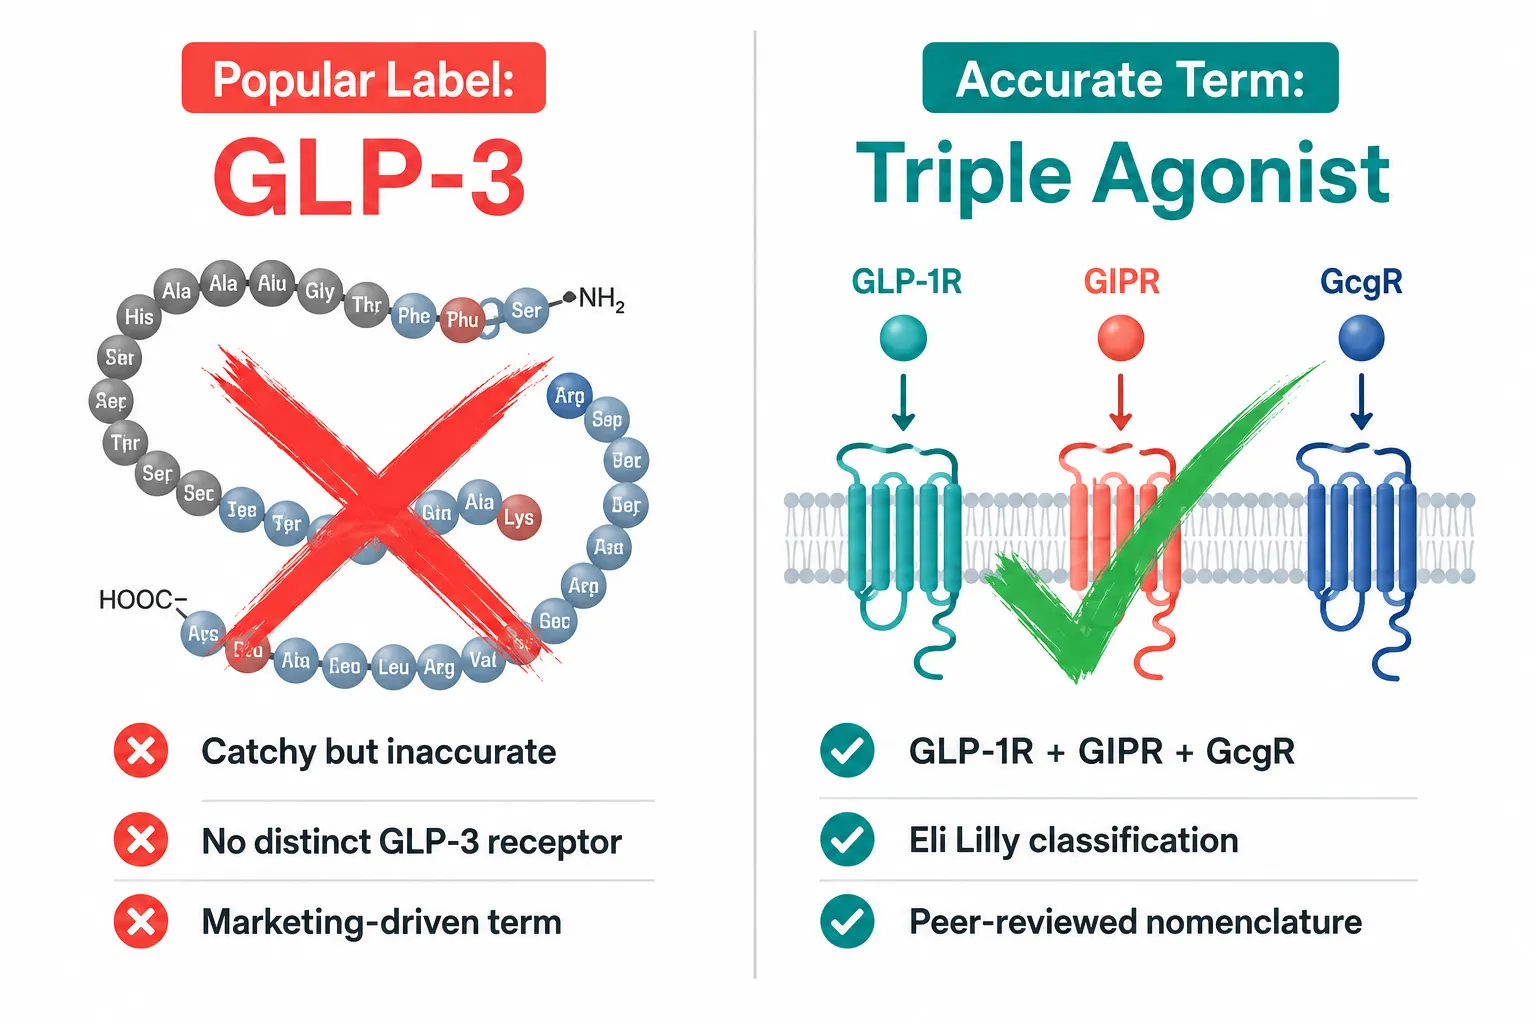
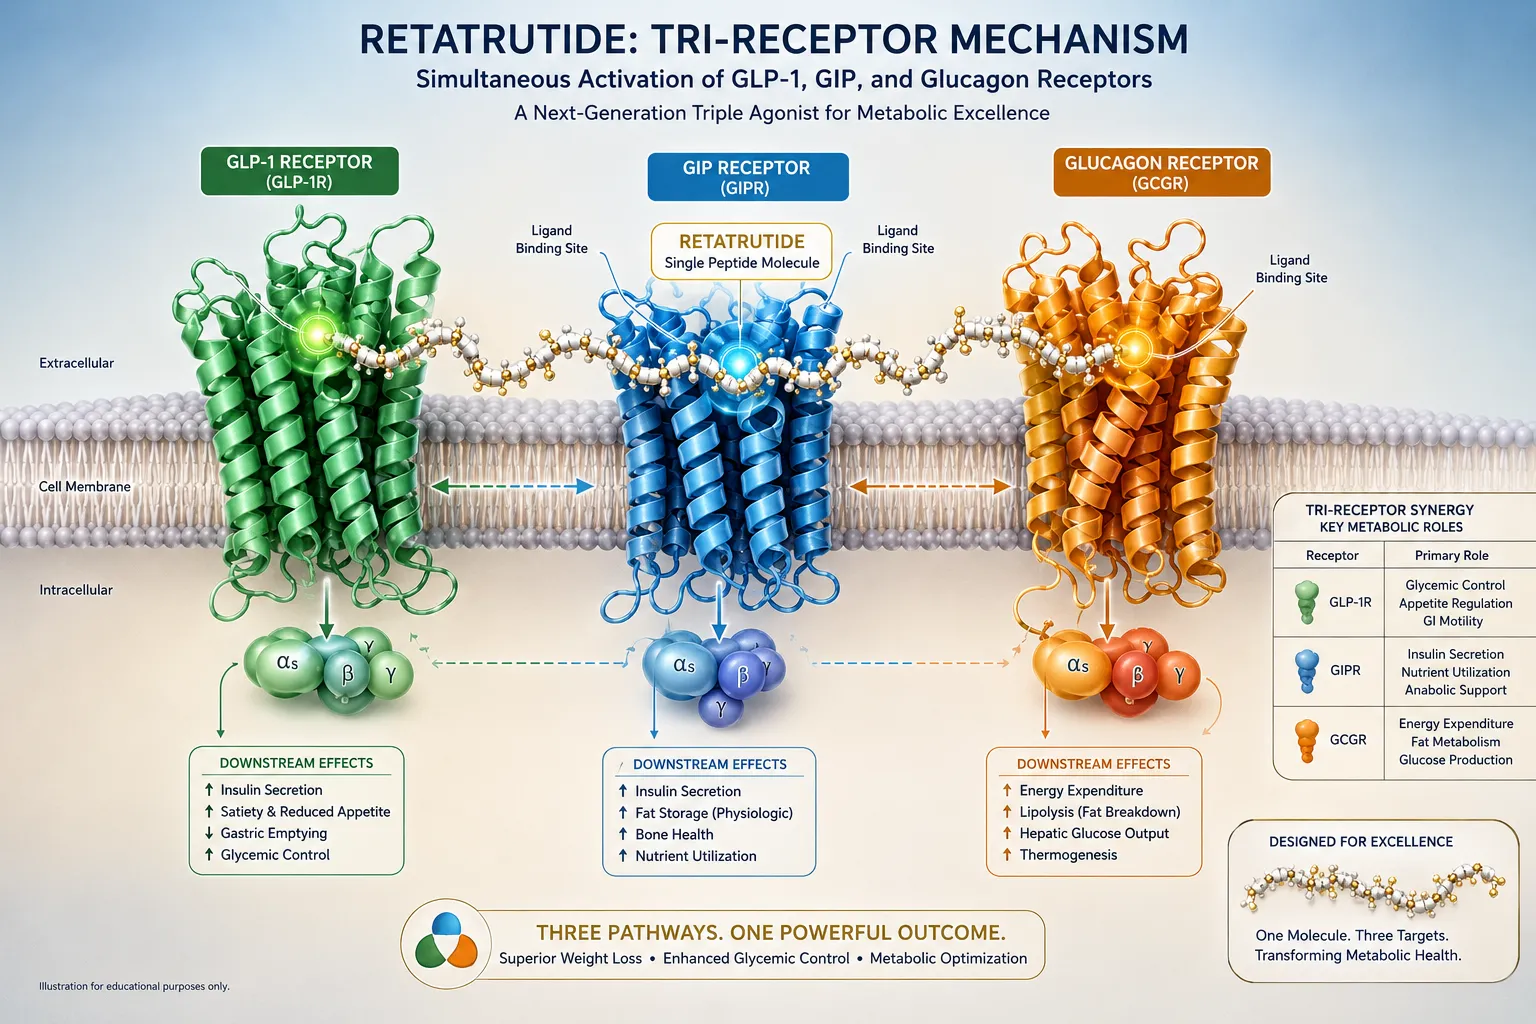
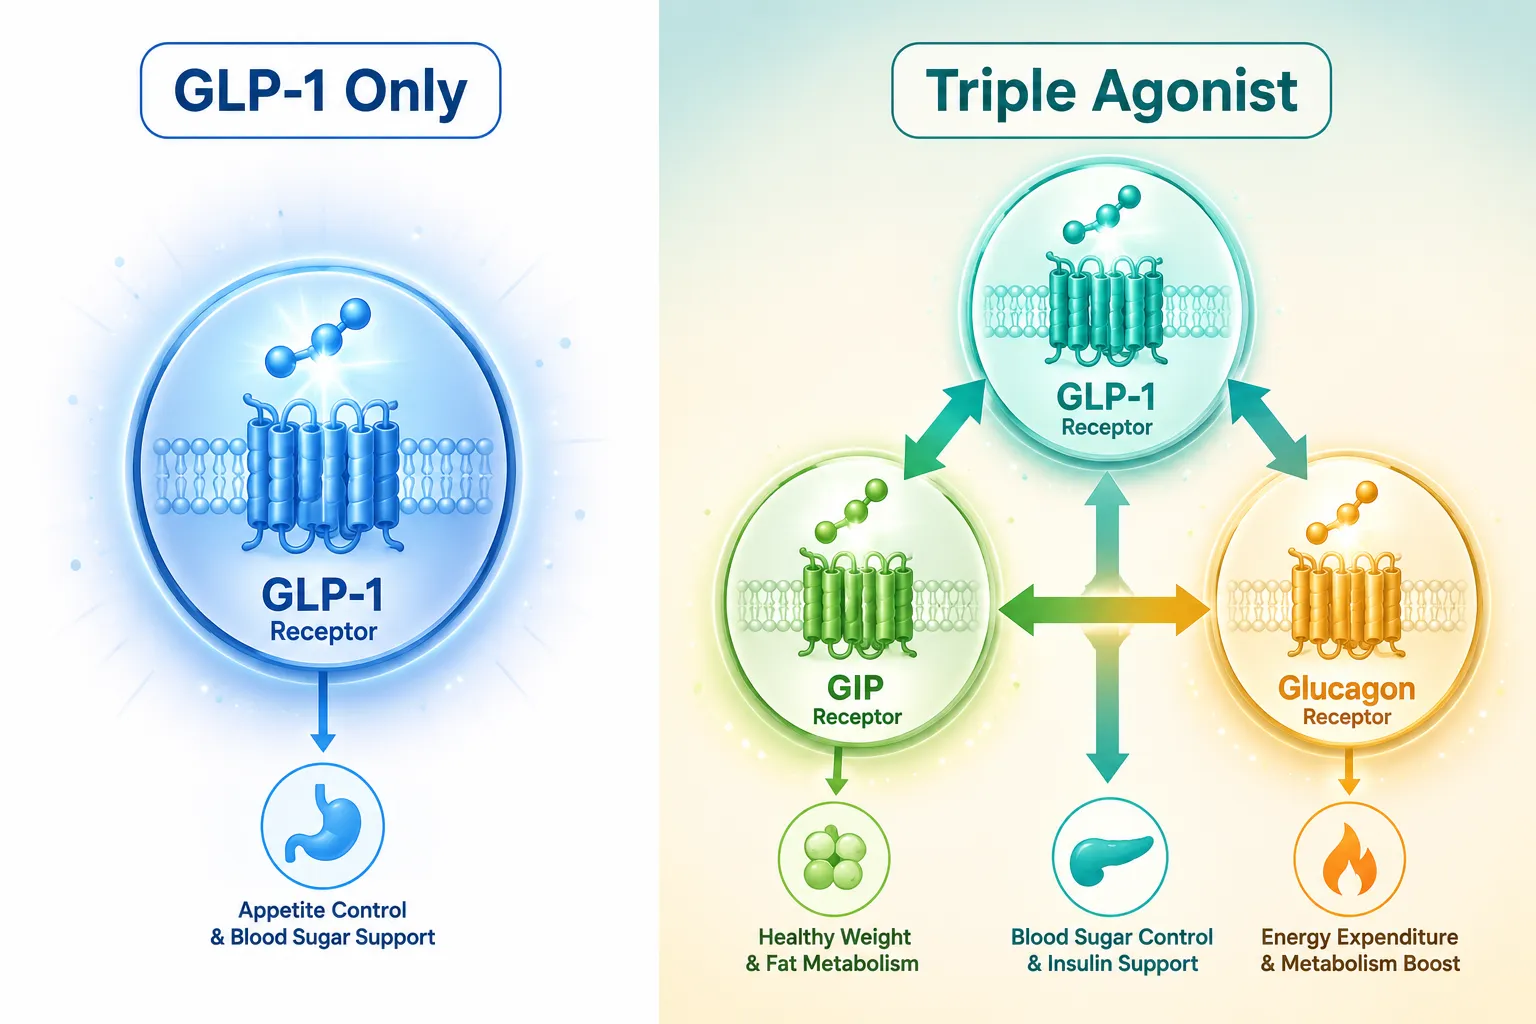
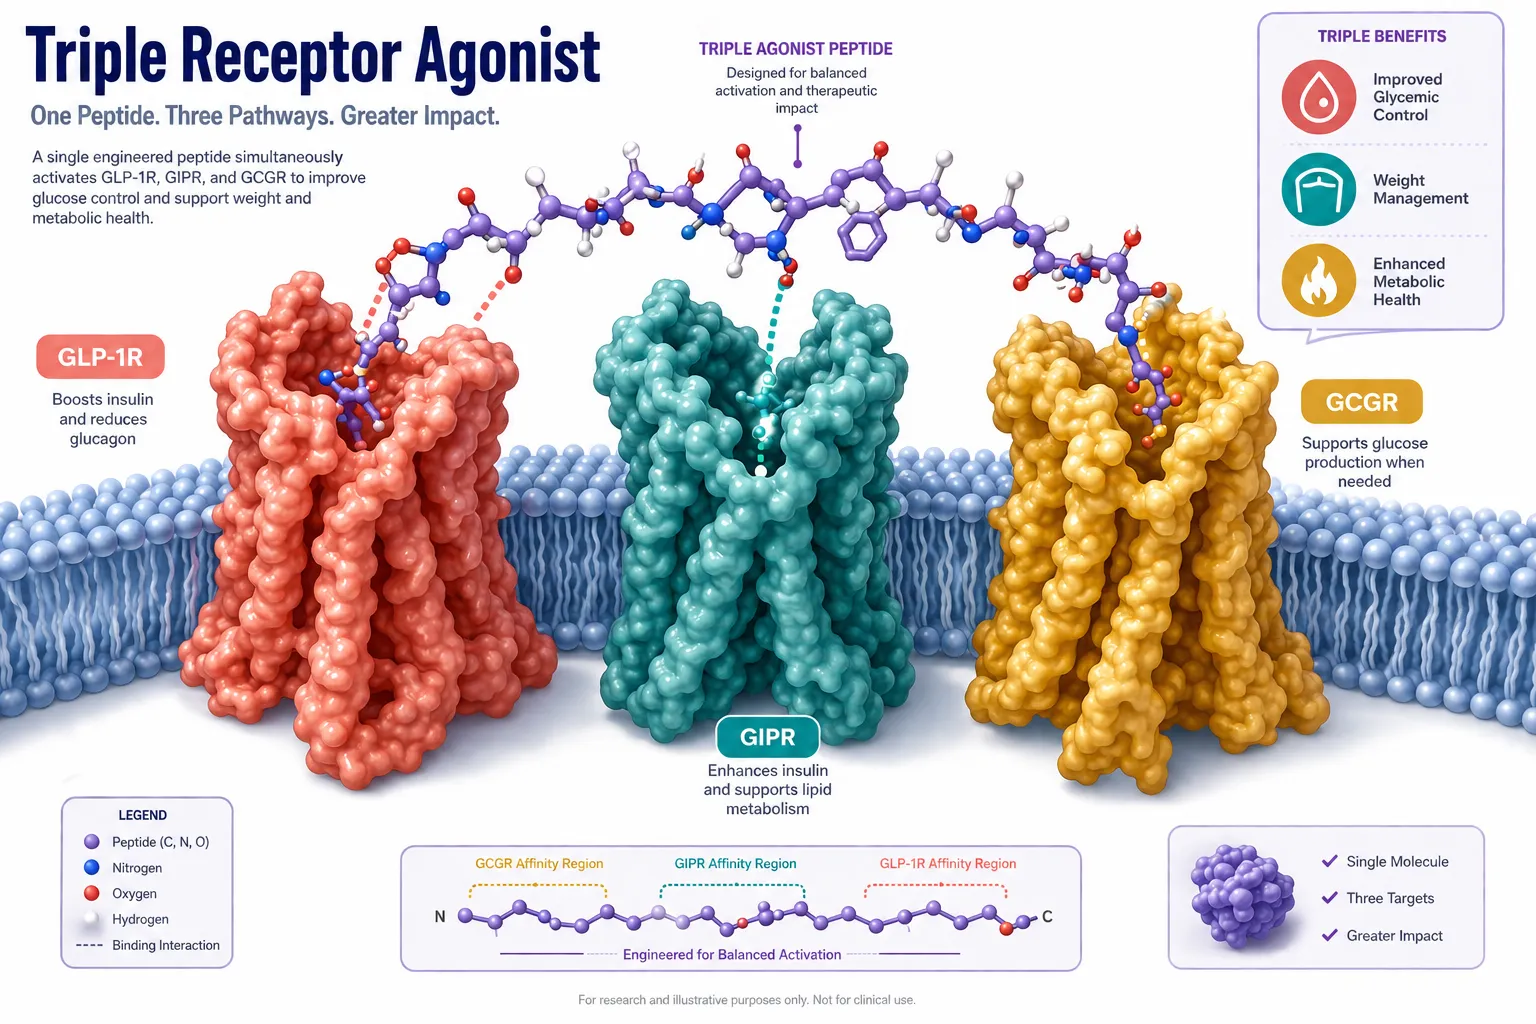
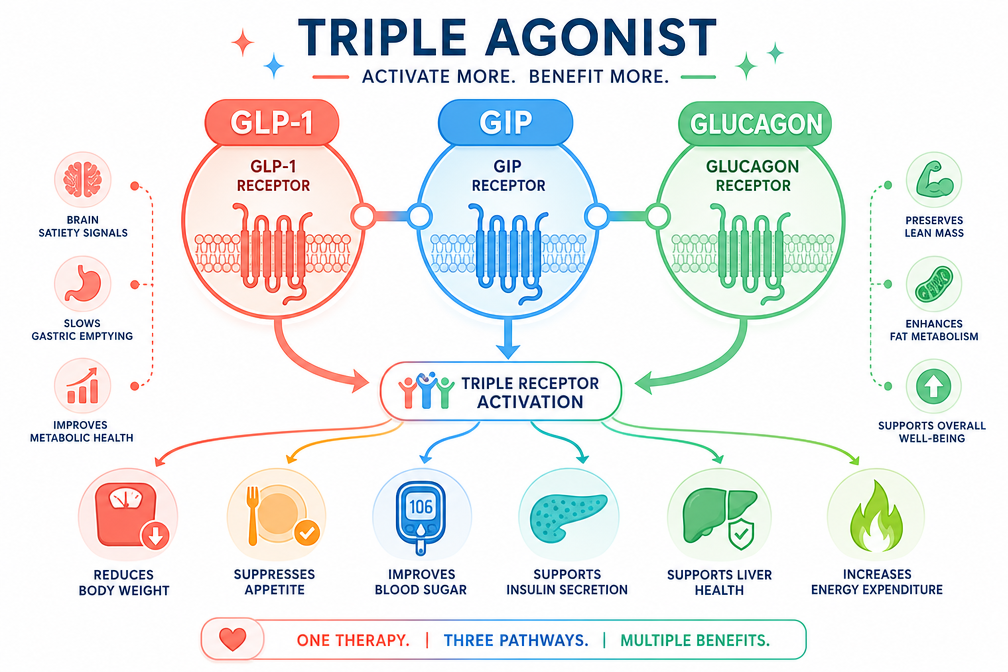
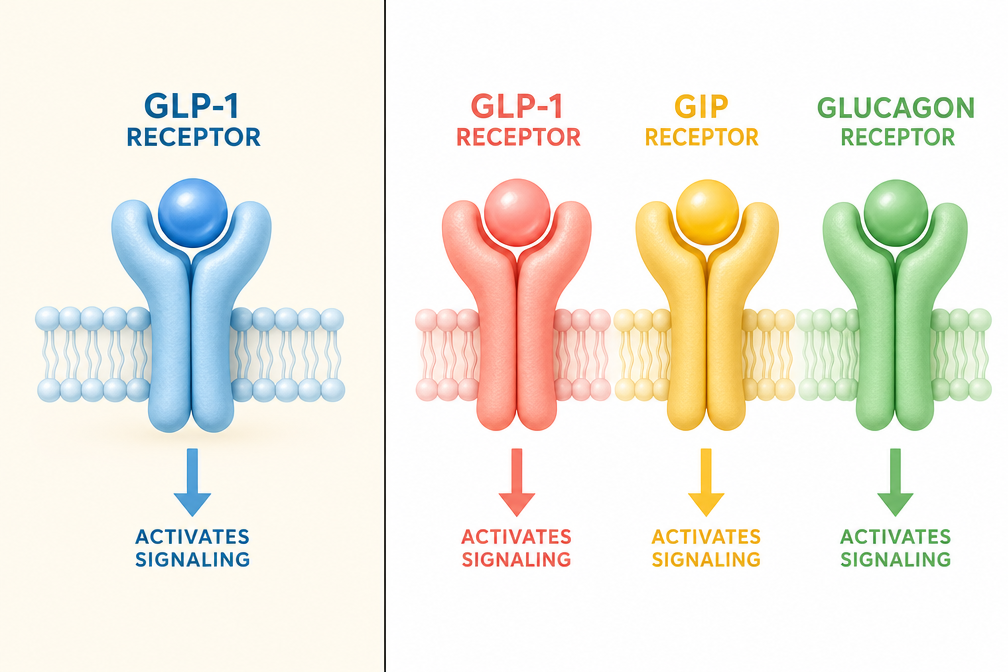
- Retatrutide simultaneously activates GLP-1, GIP, and glucagon receptors, a tri-receptor profile that separates it mechanistically from earlier incretin-only agents.
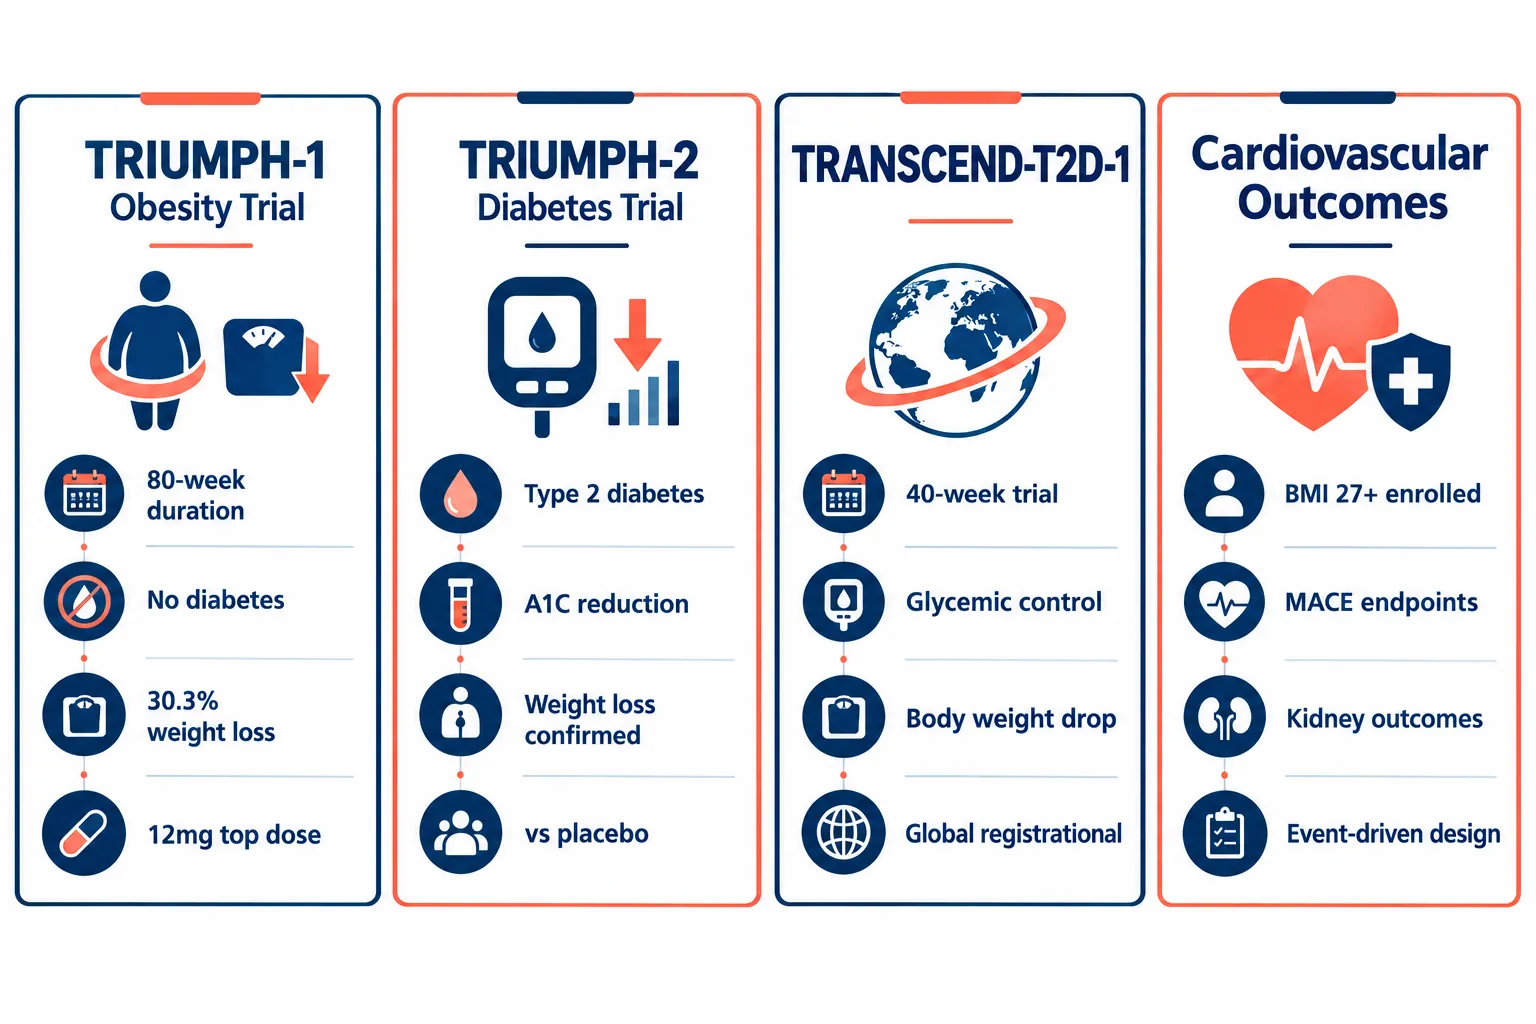
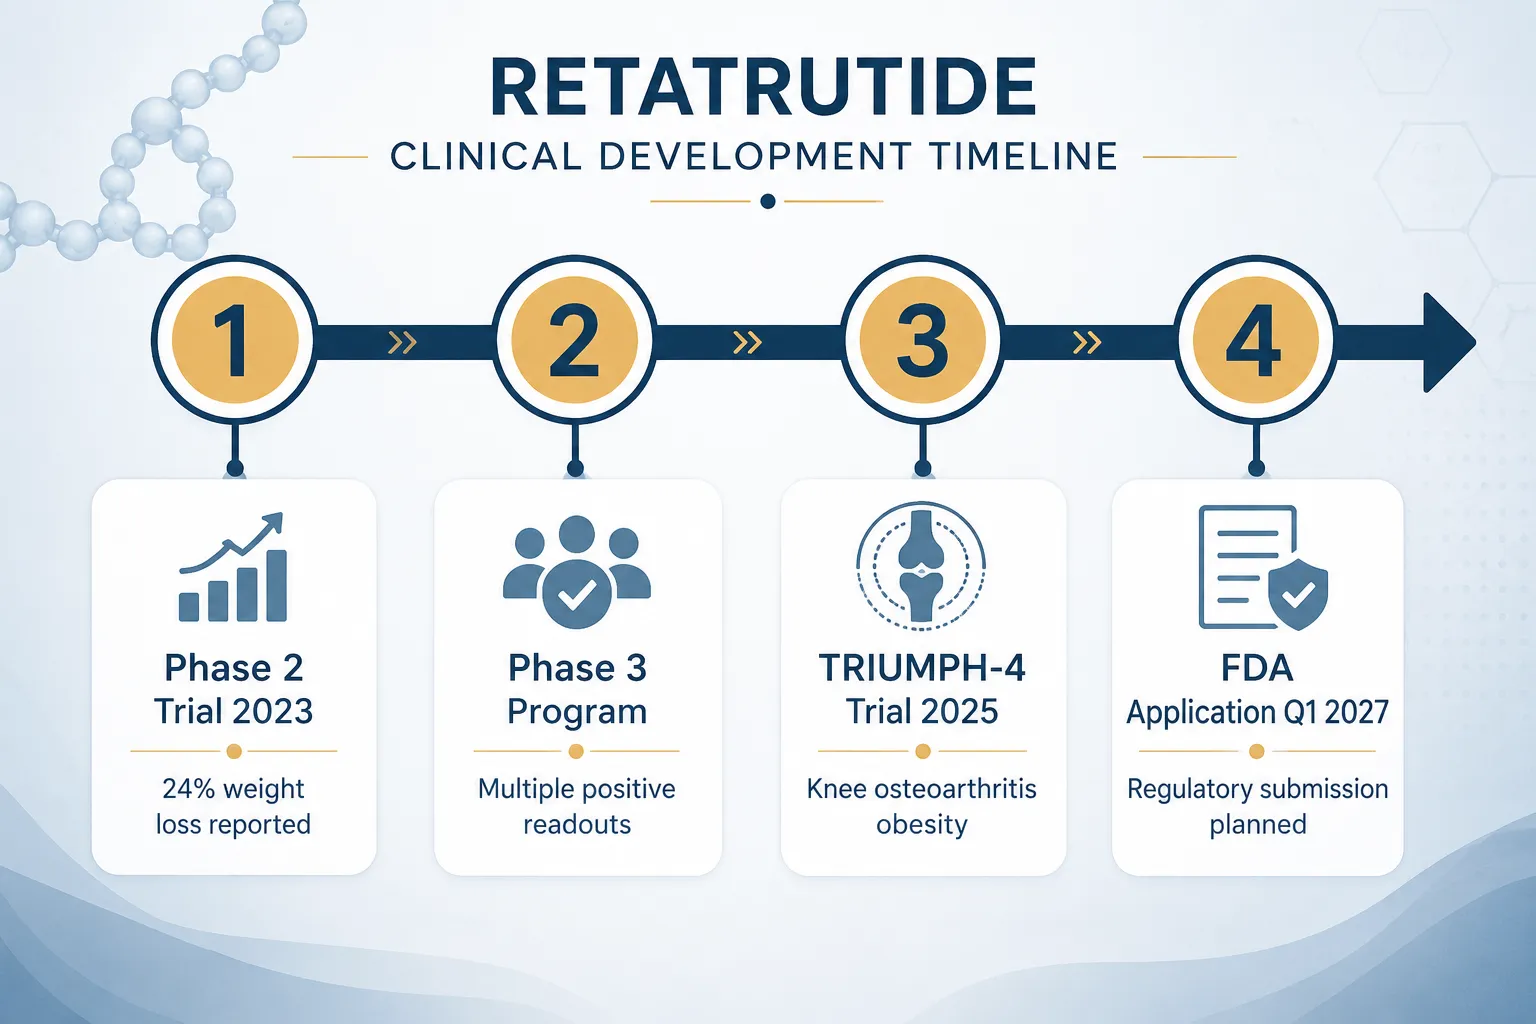
- Phase 3 TRIUMPH-1 (obesity, 80 weeks) and TRIUMPH-2 (type 2 diabetes with obesity) confirm dual metabolic endpoints at a scale phase 2 could not.
- TRIUMPH-4 extends the evidence base to musculoskeletal outcomes, specifically knee osteoarthritis with obesity, a first for this receptor class.
- The phase 3 portfolio now spans obesity, type 2 diabetes, cardiovascular disease, sleep apnea, MASLD, and chronic low back pain, forcing researchers to think beyond weight-loss endpoints.
- For preclinical and translational research models, receptor-selective controls and dose-exposure titration have become essential design requirements.
What the Triple-Agonist Mechanism Demands From Research Design
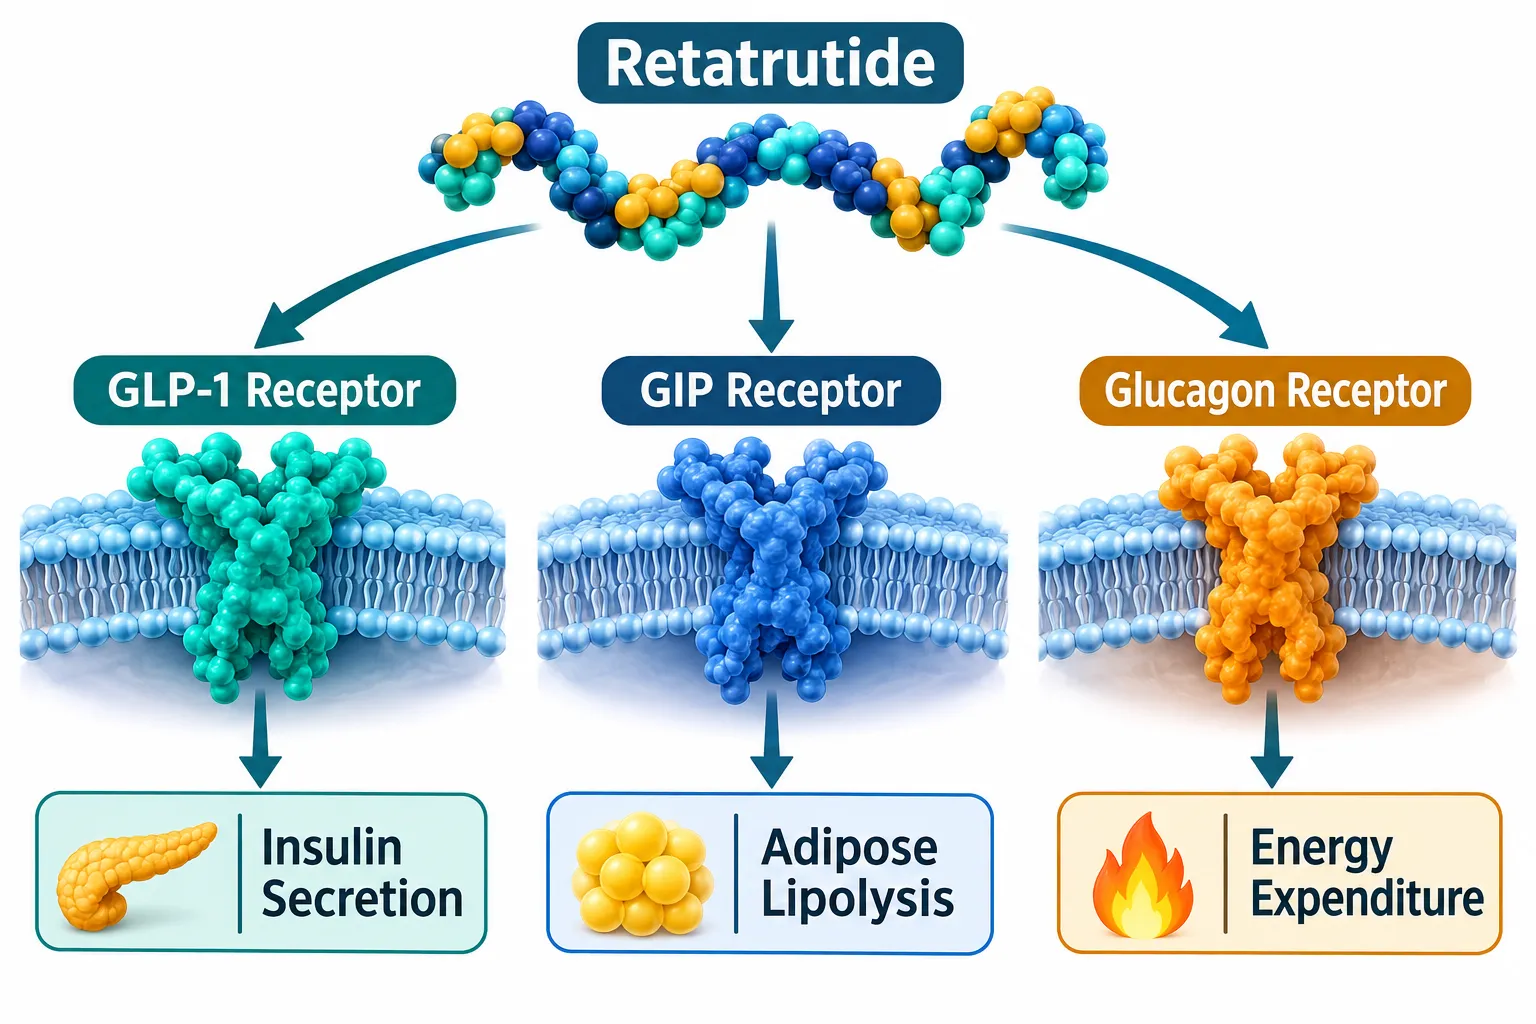
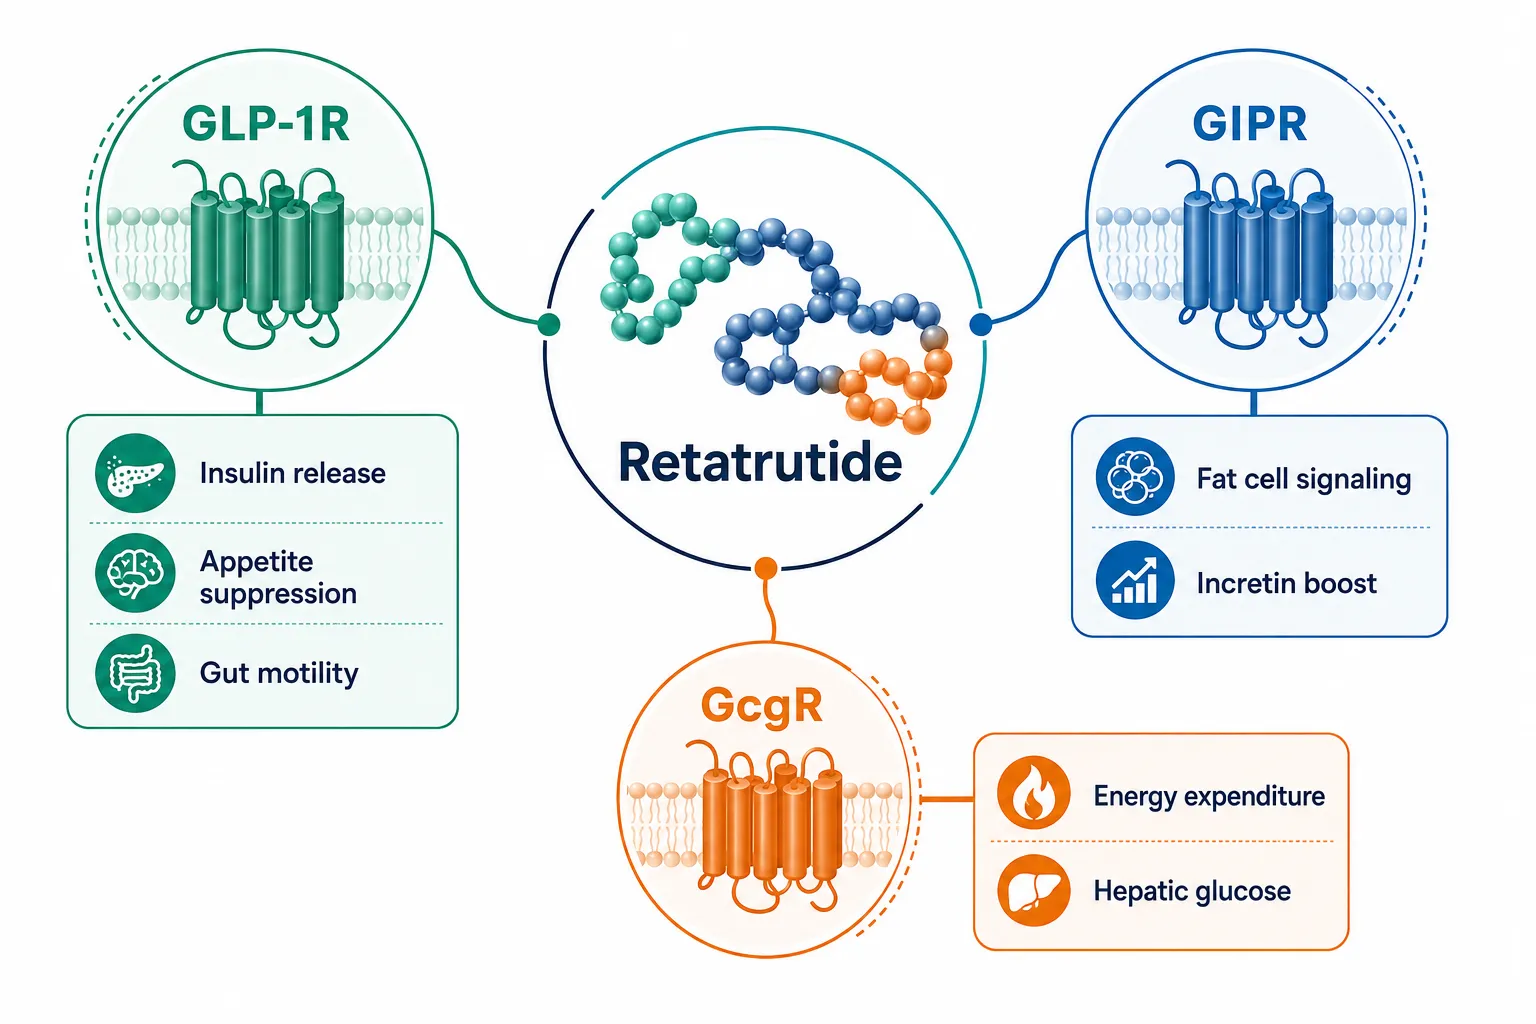
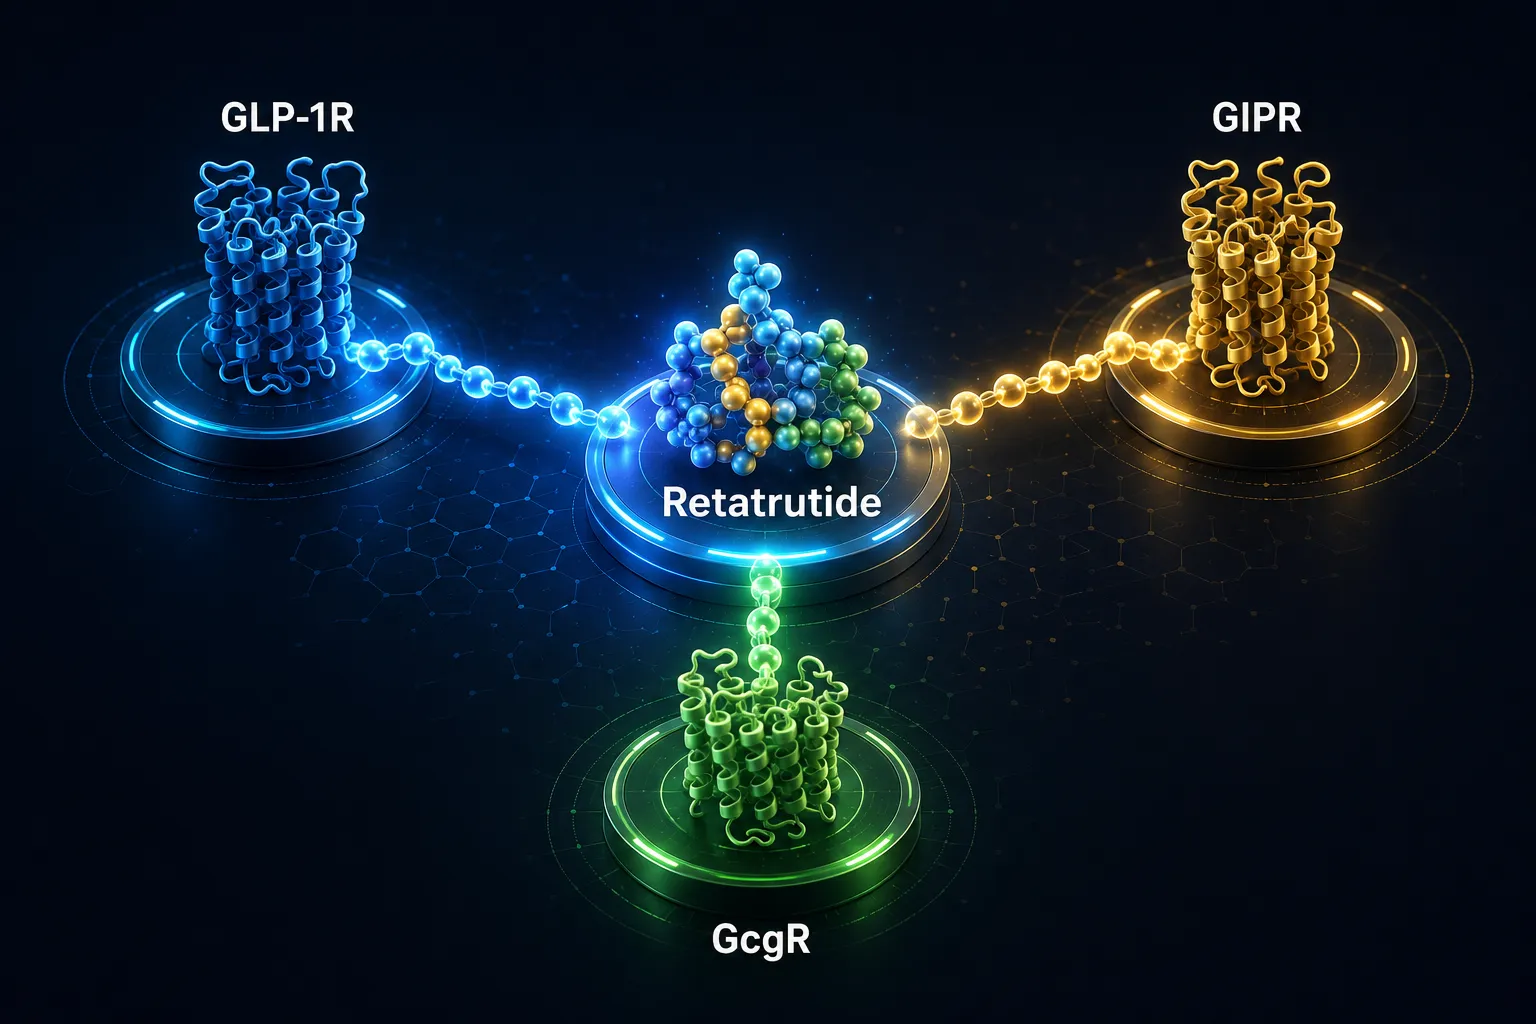
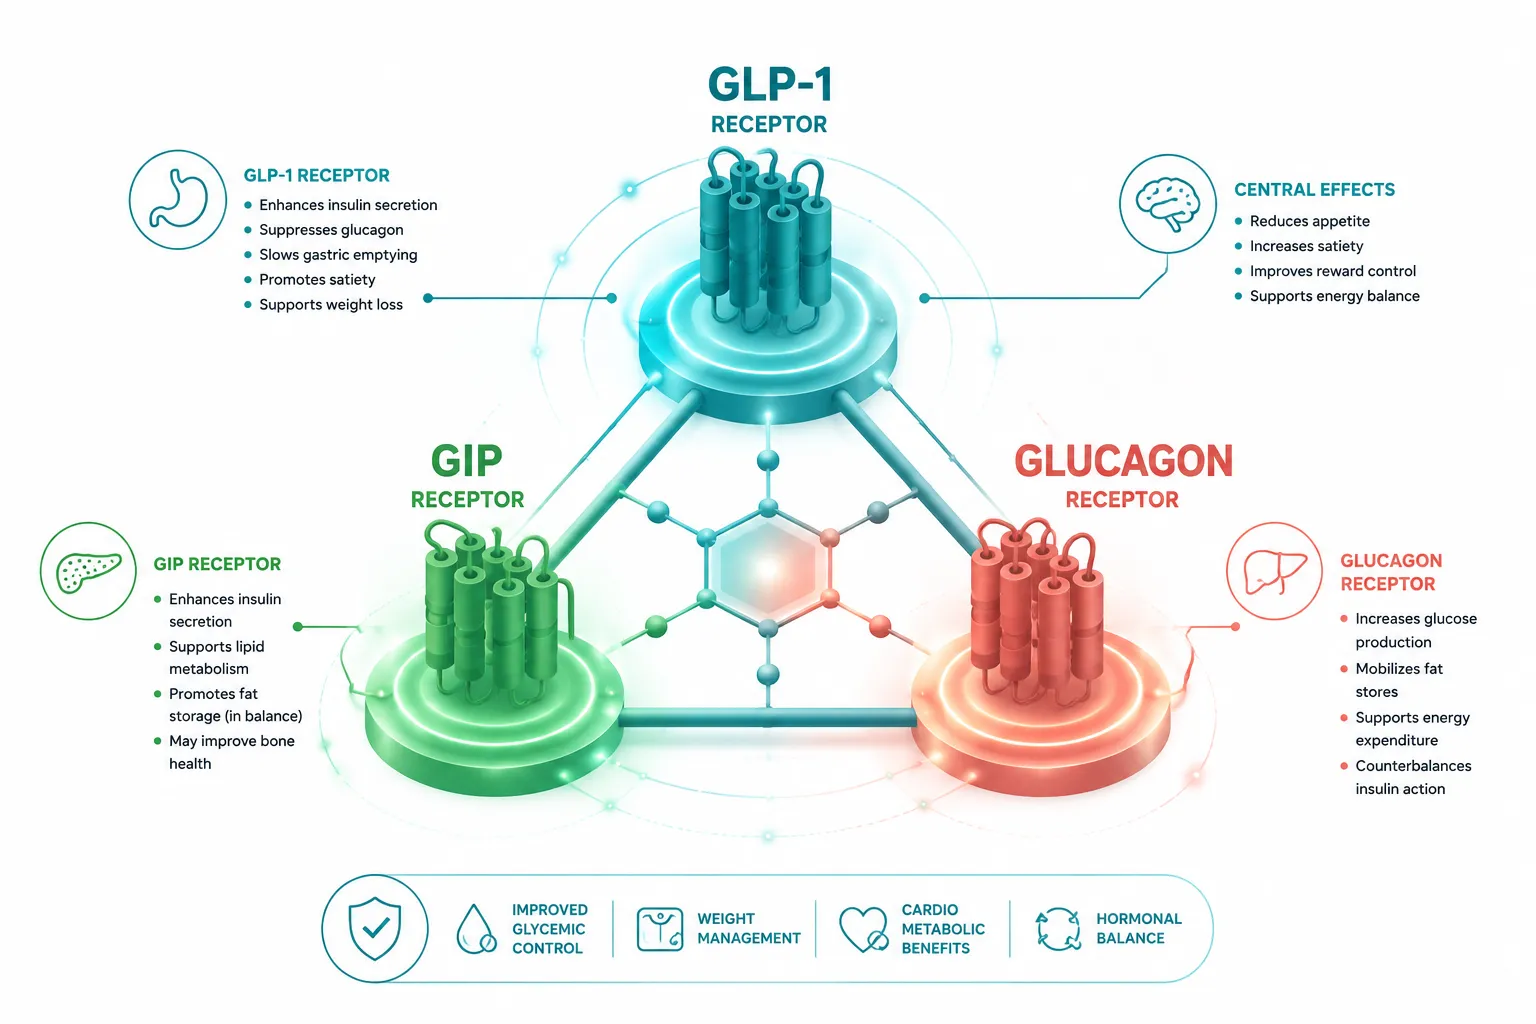
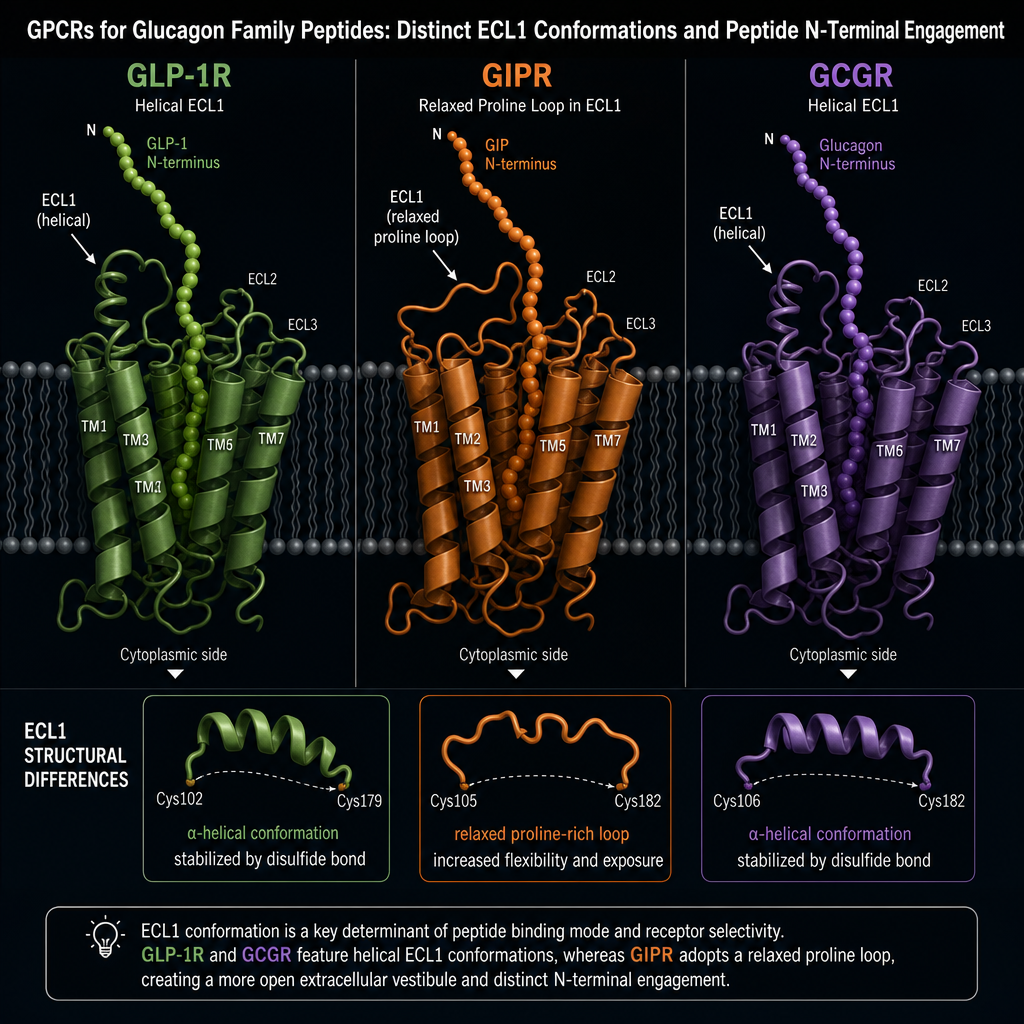
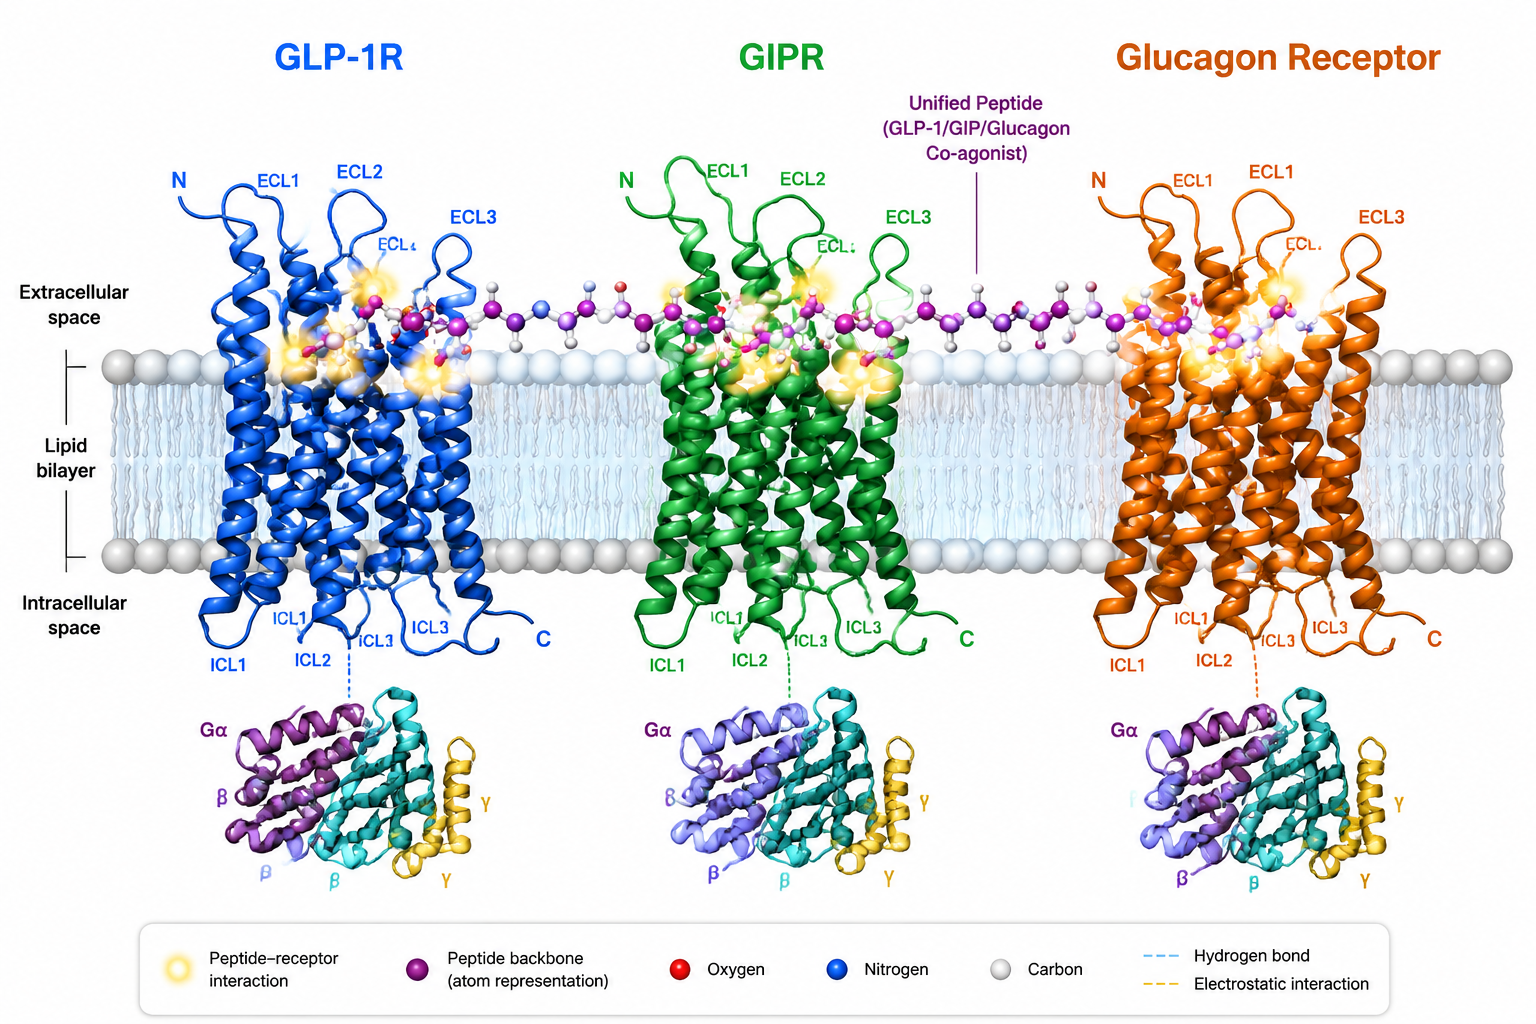
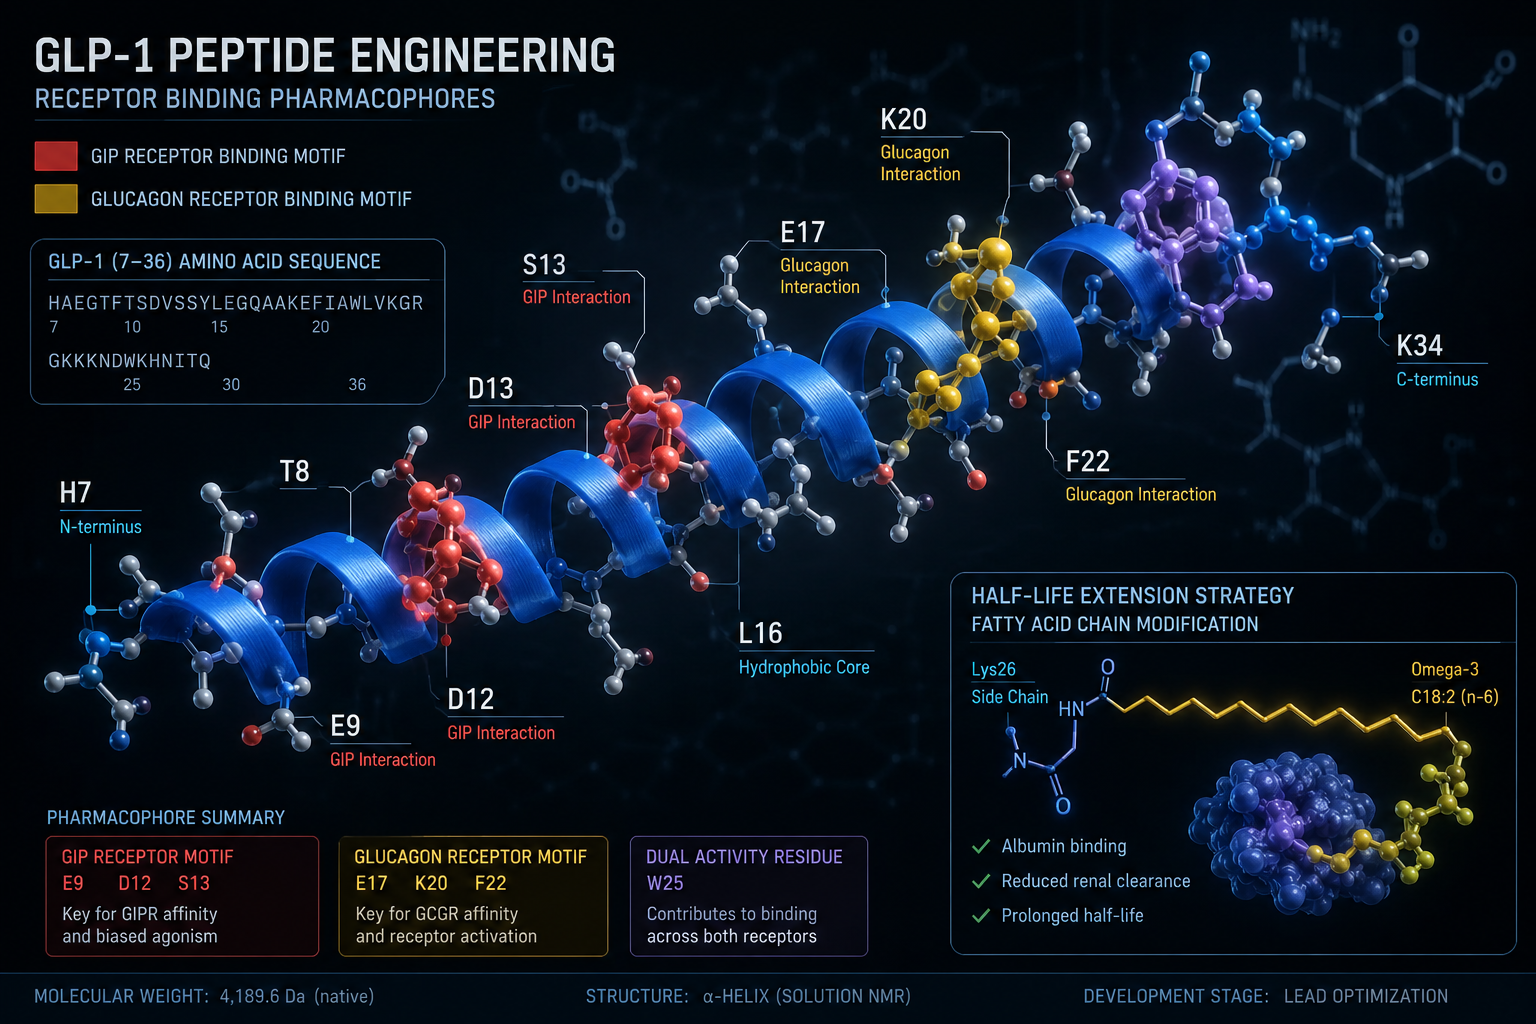
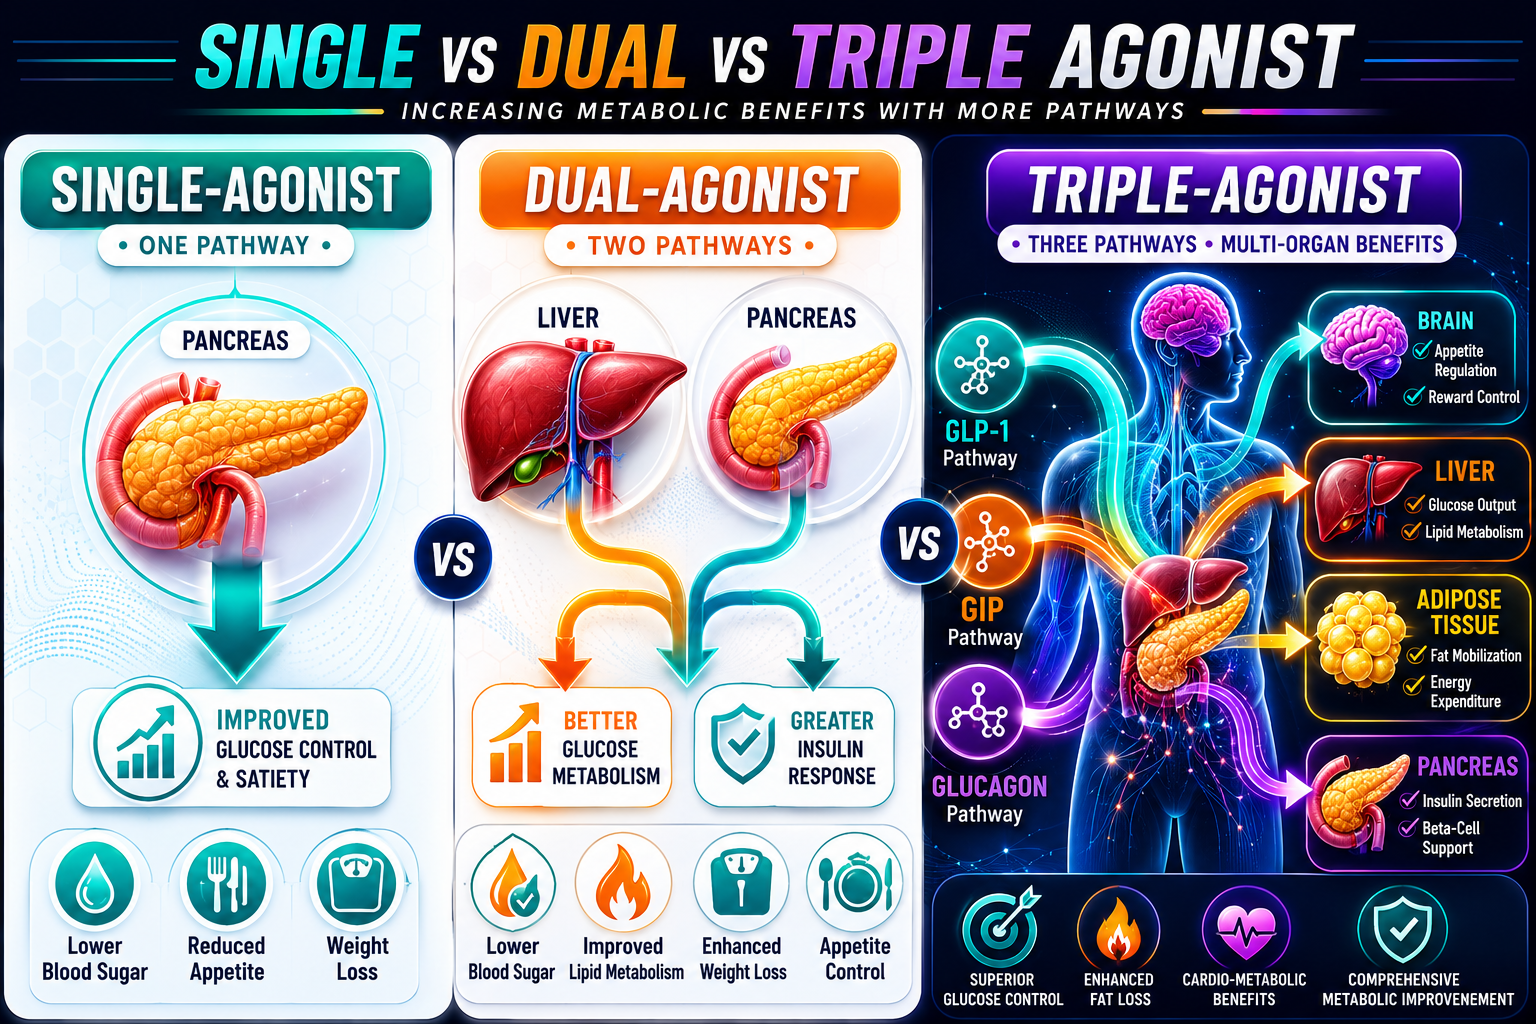
Retatrutide binds three receptors, GLP-1R, GIPR, and glucagon receptor (GCGR), simultaneously. Each receptor drives a distinct but overlapping metabolic cascade. GLP-1R activation suppresses appetite and slows gastric emptying. GIPR activation modulates adipose tissue and potentiates insulin secretion. GCGR activation increases hepatic glucose output and thermogenic energy expenditure.
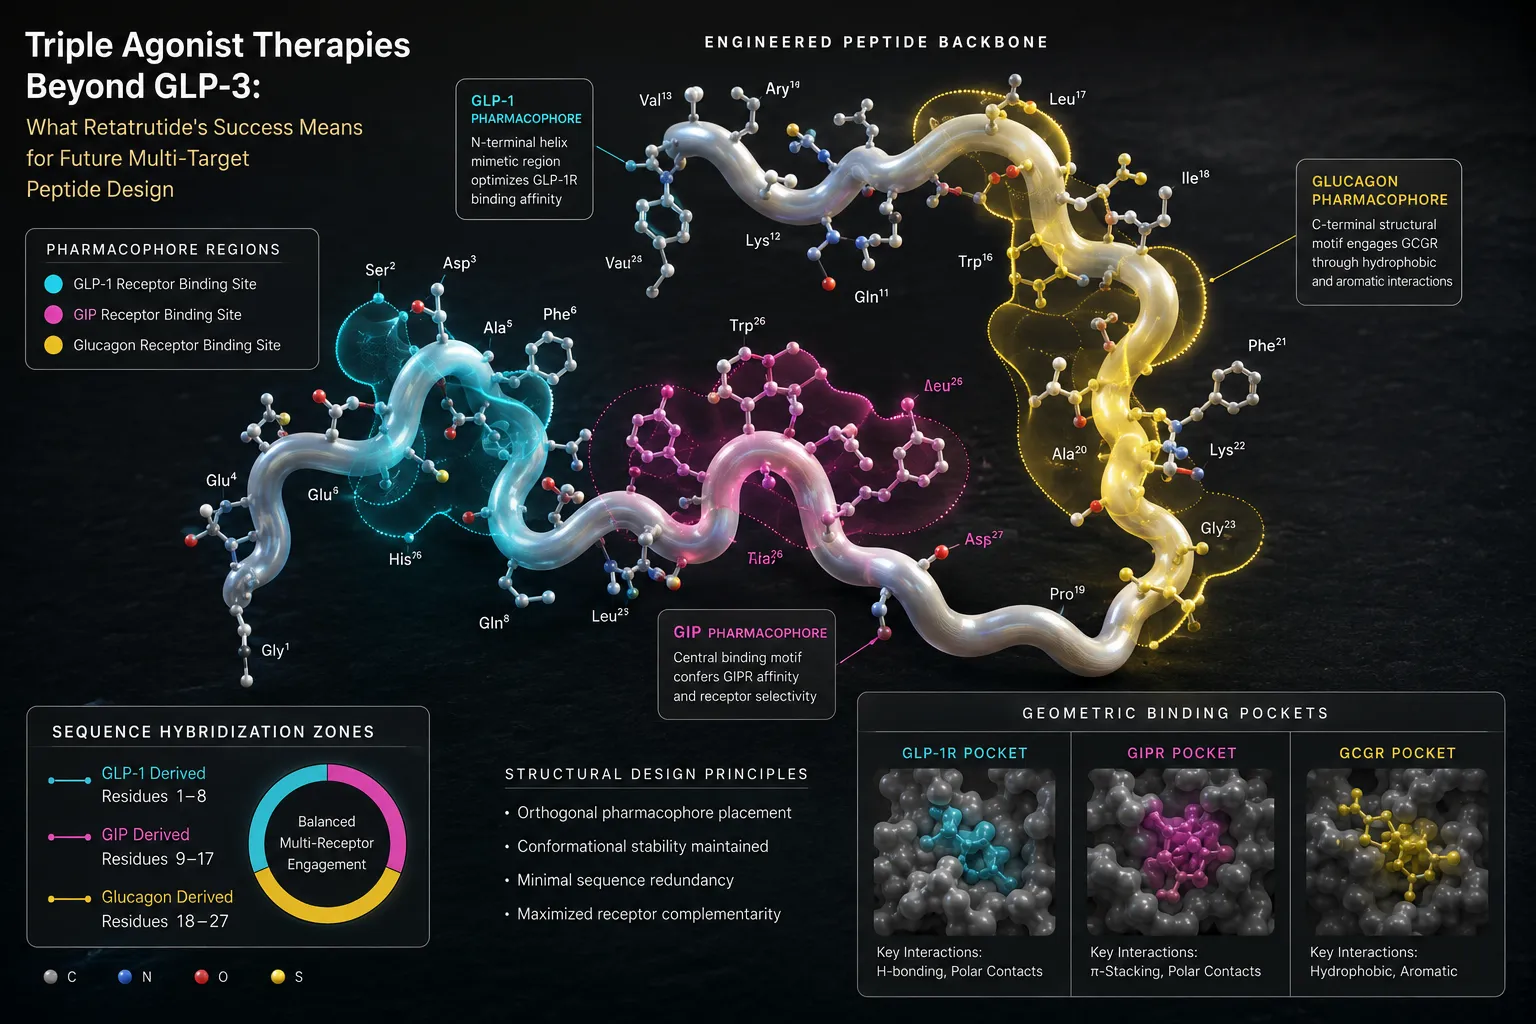
This layered pharmacology is precisely what makes the Retatrutide Phase 3 Evidence Update so consequential for GLP-3 research models. When a single compound hits all three axes, attribution becomes a central methodological problem. Which portion of the observed weight loss or glycemic improvement comes from which receptor? Phase 3 trials are powered for clinical endpoints, not mechanistic dissection, so that burden falls on bench and translational research.
Key design implications:
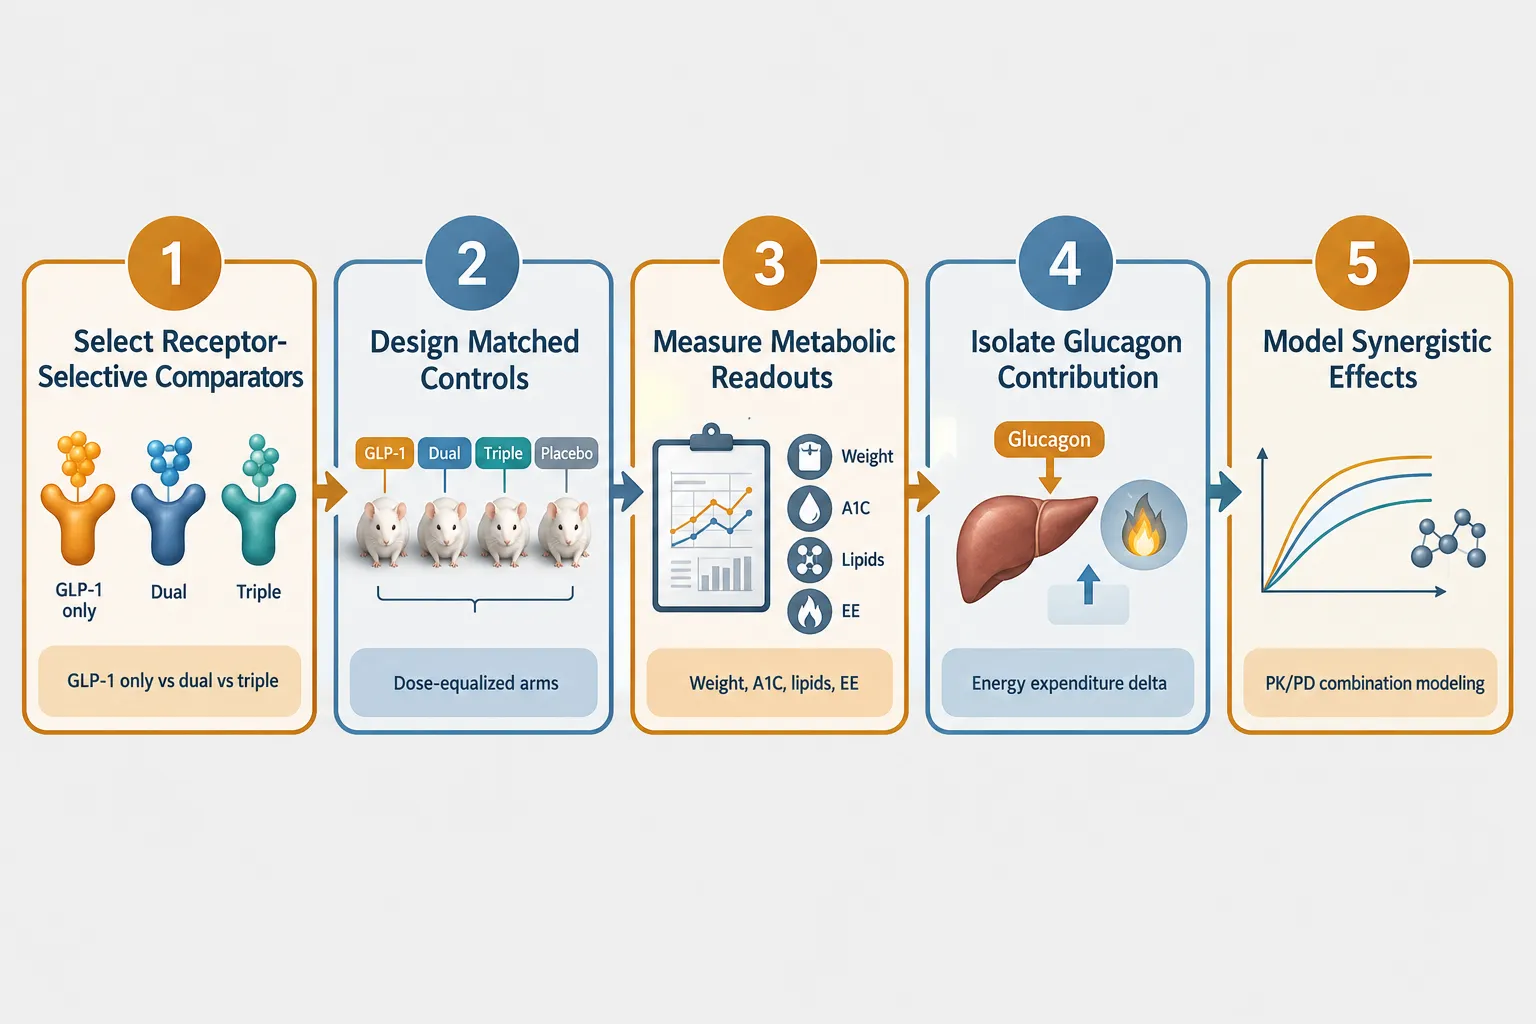
- Including receptor-selective agonist controls (GLP-1-only, GIP-only, GCGR-only) alongside a triple-agonist arm is now a baseline expectation in well-constructed studies.
- Dose-exposure matching across receptor arms is non-trivial; equipotent dosing at each receptor requires careful titration rather than simple weight-based scaling.
- Metabolic endpoint panels should capture lipid flux, hepatic glucose production, and thermogenic markers, not just body weight or fasting glucose.
Researchers exploring GLP-3 triple agonist research planning and catalog navigation should map their experimental endpoints to this receptor-specific attribution framework before committing to a protocol.
Phase 3 Trial Portfolio: What the New Evidence Base Covers
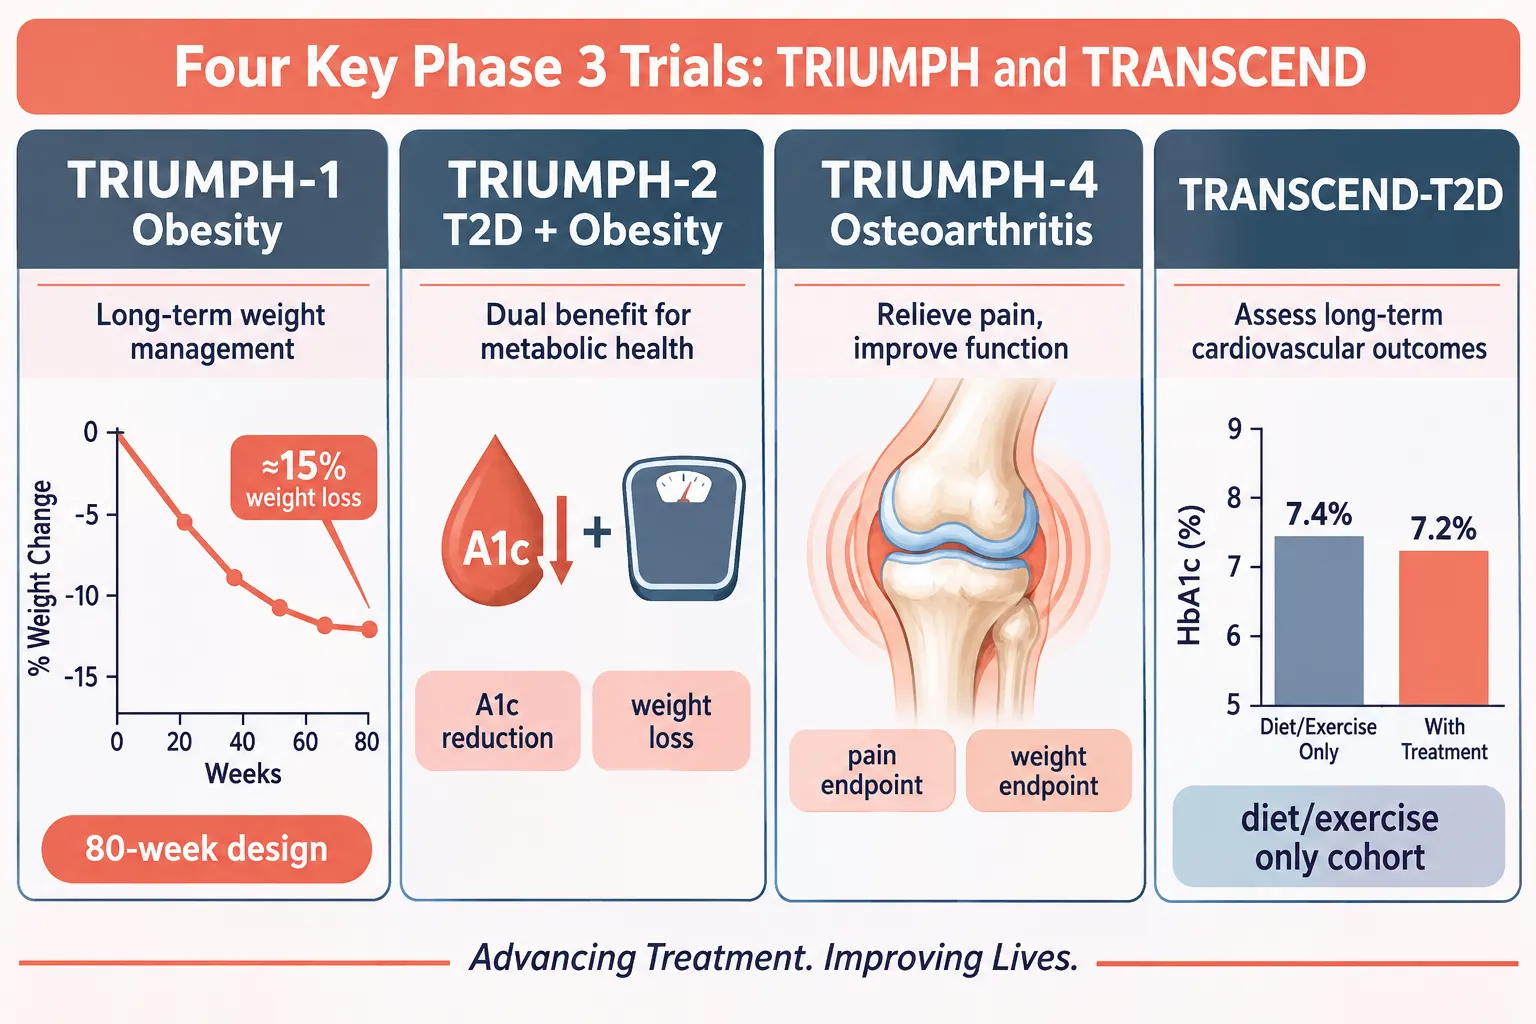
The 2026 evidence base now spans a broad portfolio of phase 3 programs. Understanding what each trial adds, and what it leaves unresolved, directly informs research model selection.
TRIUMPH-1 (80-week, adults with obesity without diabetes, published in NEJM) established the pivotal obesity efficacy signal at scale. More than half of participants achieved at least 20% weight loss, echoing the phase 2 benchmark.
TRIUMPH-2 (type 2 diabetes with overweight or obesity, 80 weeks) confirmed dual metabolic benefit, meaningful A1c reduction alongside substantial weight loss. This matters because GLP-1R and GIPR contributions to glycemic control are partially dissociable from their weight effects.
TRANSCEND-T2D-1 (diet and exercise-only background in type 2 diabetes) isolates glycemic potential without confounding from background pharmacotherapy. For researchers building glucose-metabolism models, this cohort design provides the cleanest signal of receptor-driven glycemic change.
TRANSCEND-T2D-2 (head-to-head versus semaglutide 2 mg) demonstrated superiority in both A1c reduction and weight outcomes. This comparative evidence shifts the competitive benchmarking discussion and raises the bar for what a "strong responder" looks like.
TRIUMPH-3 enrolled adults with severe obesity and established cardiovascular disease, a high-risk phenotype where glucagon receptor contributions to cardiac and hepatic outcomes deserve particular scrutiny.
TRIUMPH-4 is the most novel addition. Topline osteoarthritis data (knee, obesity comorbidity) presented at ACR 2026 showed dual endpoints, pain reduction and weight loss, moving the conversation beyond metabolic models entirely. This has direct implications for researchers studying the interaction between adiposity, systemic inflammation, and joint health.
The broader portfolio also includes sleep apnea, MASLD, chronic low back pain, and renal and cardiovascular outcomes trials, signaling that the glucagon receptor axis may carry tissue-specific benefits well beyond energy balance.
For context on how peptide weight-loss research has evolved across compound classes, the overview of what is the strongest peptide for weight loss provides a useful comparative baseline.
Translating Phase 3 Readouts Into GLP-3 Research Model Decisions
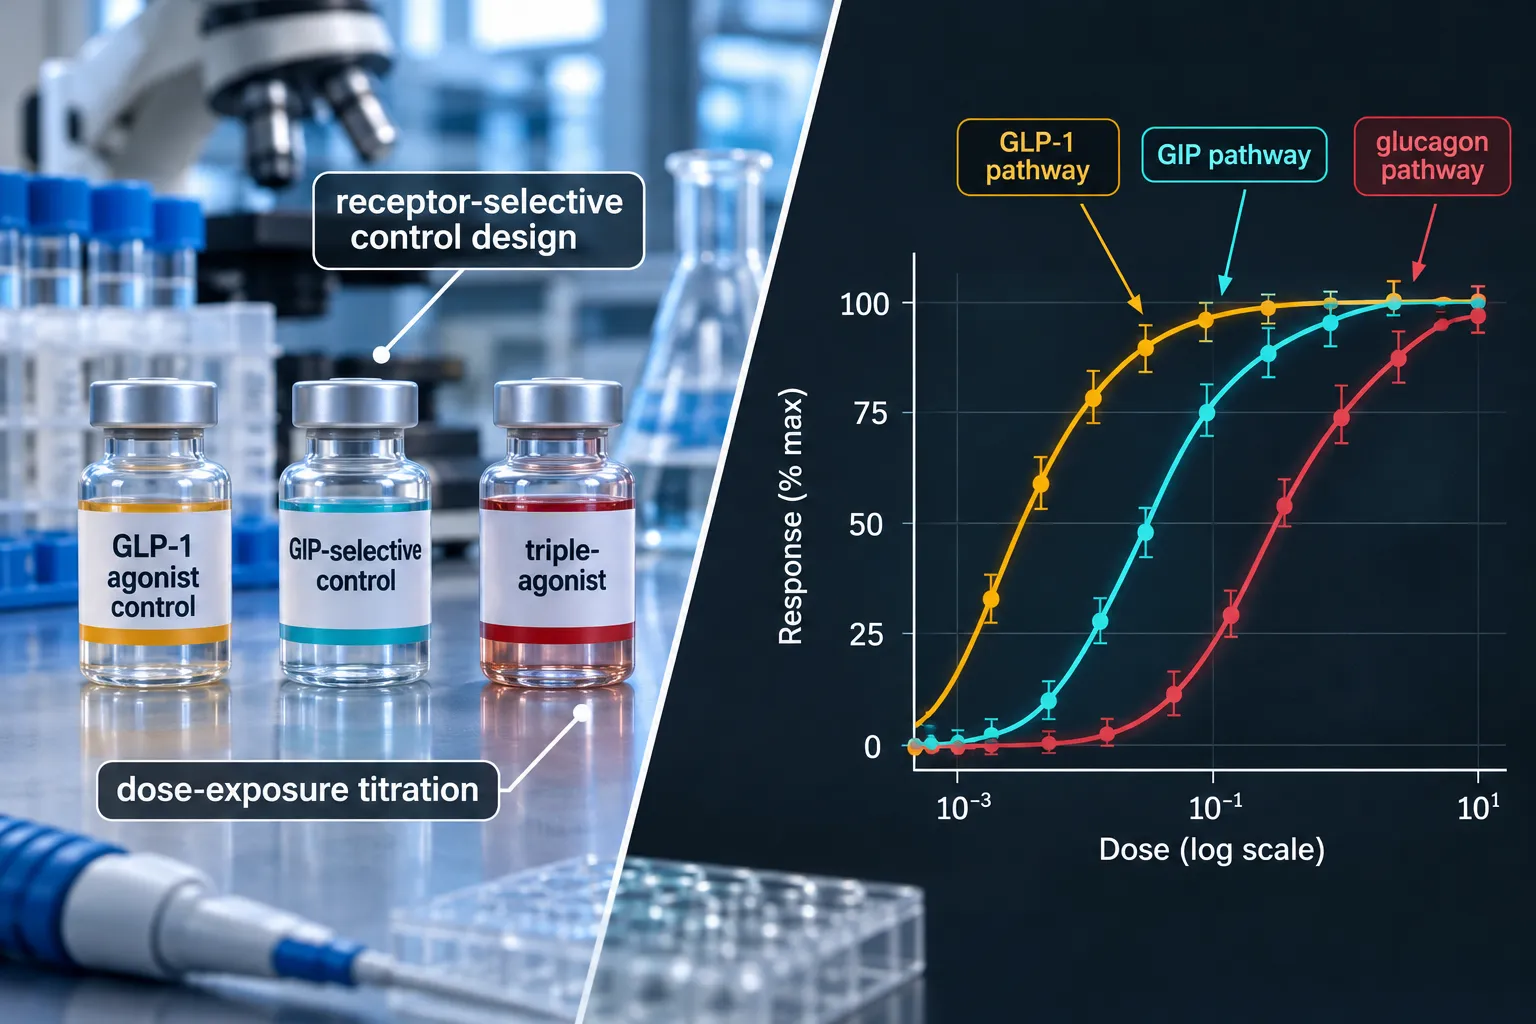
The Retatrutide Phase 3 Evidence Update: What New Triple-Agonist Results Change for GLP-3 Research Models goes beyond efficacy headlines. It reframes three core experimental design questions.
1. What is the right control arm?
Phase 3 superiority data versus a GLP-1-only comparator (semaglutide) makes GIP and glucagon receptor contributions the logical focus of mechanistic inquiry. A GLP-1-only arm is now the minimum standard comparator, not a placebo.
2. How should dose exposure be reported?
Phase 2 data at 12 mg over 48 weeks remain foundational for understanding the exposure-response relationship. Phase 3 protocols use titrated dosing. Research models that apply a single fixed dose without escalation data may underestimate ceiling effects at individual receptors.
3. Which metabolic endpoints matter most?
Given the MASLD and cardiovascular outcome programs now underway, hepatic fat fraction, visceral adiposity imaging, and inflammatory biomarkers belong in metabolic endpoint panels alongside standard glycemic and anthropometric measures.
Safety context also matters for model design. GI adverse events are consistent with the broader incretin class. Glucagon receptor activation introduces additional considerations around hepatic glucose output and potential counter-regulatory signaling that need appropriate monitoring in rodent and in vitro models.
Researchers sourcing material for these studies can explore buy Reta peptide and Reta GLP-3 peptide options through verified catalog sources. For those planning dosing protocols specifically, the Reta 10mg format provides a common starting reference for research-grade preparation.
It is worth noting that comparisons with other metabolically active peptides, such as tesa, which targets growth hormone secretion and visceral fat, help illustrate how different receptor pathways converge on overlapping metabolic outcomes through distinct mechanisms.
Conclusion
The Retatrutide Phase 3 Evidence Update: What New Triple-Agonist Results Change for GLP-3 Research Models is not simply a news event, it is a methodological inflection point. The expanded trial portfolio confirms that GLP-1, GIP, and glucagon receptor co-activation produces clinically meaningful outcomes across obesity, type 2 diabetes, musculoskeletal disease, and likely cardiovascular and hepatic endpoints.
Actionable next steps for researchers:
- Redesign control arms to include receptor-selective agonists, not just placebo, in any triple-agonist study.
- Align dose-exposure protocols with titration schedules validated in phase 3, not fixed phase 2 dose points alone.
- Expand endpoint panels to include hepatic, inflammatory, and cardiovascular biomarkers consistent with the phase 3 indication portfolio.
- Consult updated phase 3 publications, particularly TRIUMPH-1 and TRANSCEND-T2D-2, before finalizing model selection or outcome hypotheses.
- Source verified, purity-tested research-grade material to ensure experimental reproducibility.
The triple-agonist era has moved from promising to pivotal. Research models that do not account for multi-receptor attribution will increasingly struggle to generate interpretable, publishable findings.